Patients › Elbow
கீழ்முனைப் பைசெப்ஸ் தசைநாண் அறுவு (Distal Biceps Rupture)
Distal biceps rupture causes sudden elbow pain, bruising, and weakness—often needing surgical repair.
நீங்கள் உணர்வது
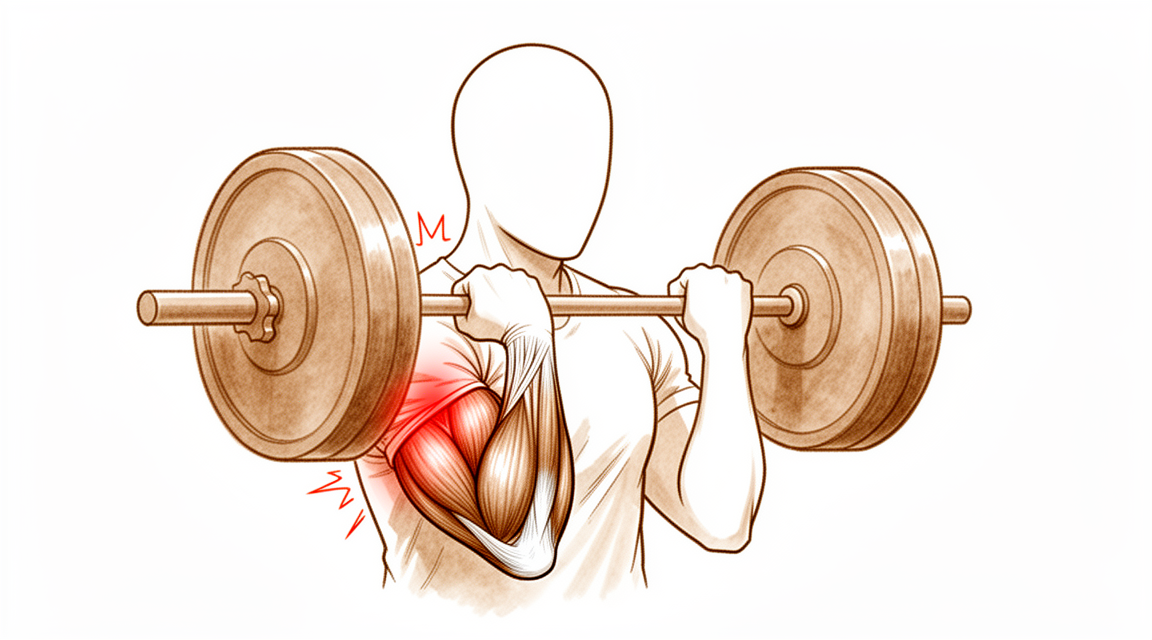
கீழ்முனைப் பைசெப்ஸ் தசைநாண் அறுவு (distal biceps rupture) மாதக்கணக்கில் அல்லாமல், ஒரே ஒரு கணத்தில் நிகழ்கிறது. 90 டிகிரி மடங்கியிருக்கும் கையைத் திடீரென, எதிர்பாராமல் நேராக்கும் ஒரு விசையால் இது பொதுவாக ஏற்படுகிறது — எடுத்துக்காட்டாக, கீழே விழும் கனமான ஒன்றைப் பிடிப்பது, அல்லது உங்கள் கை இழுக்கப்பட்டு நேராக்கப்படும்போது இறுக்கமாகப் பற்றிப் பிடித்திருப்பது. இது நிகழும்போது, பலர் முழங்கையின் முன்பக்கத்தில் "படக்" என்ற ஒன்றை உணர்கிறார்கள் அல்லது கேட்கிறார்கள். தசைநாண் பொதுவாக முன்கை எலும்புகளில் ஒன்றில் உள்ள அதன் நங்கூரப் புள்ளியிலிருந்து கிழிந்து விலகுகிறது. தசை கையின் மேல்நோக்கி இழுபட்டு, நடுப்பகுதிக்கு அருகில் திரள்வதால், அதன் வடிவம் மாறுவதை நீங்கள் கவனிக்கலாம்.
உடனடியாகவே, உங்கள் முழங்கையின் முன்பக்கம் வலியுடனும் வீக்கத்துடனும் இருக்க வாய்ப்புள்ளது. சிராய்ப்புக் கறை (bruising) பொதுவானது; அடுத்த ஓரிரு நாட்களில் முழங்கையையும் முன்கையையும் சுற்றி அது தோன்றலாம். கையை மடக்குவதும் திருகுவதும் வலிக்கும்; எனவே கெட்டிலைத் தூக்குவது, கதவுக் குமிழைத் திருப்புவது, அல்லது வாகனத்தின் சுக்கானை (steering wheel) உறுதியாகப் பிடிப்பது போன்றவற்றை நீங்கள் தவிர்ப்பதைக் காணலாம். திருப்புளியைப் (screwdriver) பயன்படுத்துவது போல, எதிர்ப்புக்கு எதிராக உள்ளங்கையை மேல்நோக்கித் திருப்புவதே பெரும்பாலும் மிகக் கடினமான அசைவு. வேறு தசைகள் உதவுவதால் சிலரால் இன்னும் முழங்கையை மடக்க முடியும்; இது காயத்தை உண்மையில் இருப்பதைவிடக் குறைவான தீவிரம் கொண்டதாக உணரச் செய்யலாம்.
முதல் சில நாட்களிலும் வாரங்களிலும், அசைவின்போது வலி பெரும்பாலும் அதிகமாக இருக்கும்; இரவில் வலிக்கவும் செய்யலாம். கிழிந்த தசைநாணைச் சுற்றி உடல் குணமடையத் தொடங்கும்போது, அது படிப்படியாகத் தணிகிறது. வீக்கமும் சிராய்ப்புக் கறையும் ஓரிரு வாரங்களில் குறைகின்றன; ஆனால் வலிமை இழப்பு தானாகச் சரியாவதில்லை, ஏனெனில் தசைநாண் எலும்பிலிருந்து பிய்ந்து விலகிவிட்டது, அது இருக்க வேண்டிய இடத்தில் தன்னைத் தானே மீண்டும் இணைத்துக்கொள்ள அதனால் முடியாது.
சில எச்சரிக்கை அறிகுறிகளுக்கு விரைவான நடவடிக்கை தேவை. உங்கள் கை (hand) அல்லது விரல்கள் வெளிறியோ, குளிர்ந்தோ, வெள்ளையாகவோ, நீலமாகவோ மாறினால், அல்லது காயத்துக்குப் பிறகு கையில் (hand) திடீரென உணர்வையோ அசைவையோ இழந்தால், அதே நாளில் அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். வலி தணியாமல் இருந்தால், வாரக்கணக்கில் மோசமாகிக்கொண்டிருந்தால், அல்லது இரவில் உங்களை எழுப்பினால், உங்கள் GP-யைப் பாருங்கள் அல்லது சிறப்பு மருத்துவரின் மதிப்பாய்வைக் கேளுங்கள்.
உண்மையில் என்ன நடக்கிறது
பைசெப்ஸ் தசை உங்கள் மேல்கையின் முன்பக்கமாகக் கீழ்நோக்கிச் சென்று, முழங்கைக்குச் சற்று முன்பு, தசைநாண் எனப்படும் ஒரு வலுவான நாணாக மாறுகிறது. அந்தத் தசைநாண், முன்கை எலும்புகளில் ஒன்றான ரேடியஸ் (radius) எலும்பில் உள்ள ஒரு சிறிய எலும்புத் திட்டோடு நங்கூரமிட்டுப் பிணைகிறது. உங்கள் உள்ளங்கை மேல்நோக்கித் திரும்பும்படி முன்கையைத் திருகுவதும், முழங்கையை மடக்க உதவுவதுமே அதன் பணி.
தசைநாண் கிழியும்போது, அது எலும்பில் உள்ள அந்தத் திட்டிலிருந்து பிய்ந்து விலகி, கையின் மேல்நோக்கிச் சுருங்கிப் பின்வாங்குகிறது. தசை இன்னும் ஆரோக்கியமாகவே இருக்கிறது; ஆனால் அது அசைக்கும் எலும்போடு இனி இணைக்கப்படவில்லை, எனவே அதன் இழுவிசை எங்கும் பயன்படுவதில்லை. உள்ளங்கையை மேல்நோக்கித் திருப்புவதே மிகவும் பாதிக்கப்படும் அசைவு; ஏனெனில் வேறு எந்தத் தசையாலும் அந்தப் பணியை ஏற்க முடியாது. பைசெப்ஸுக்குக் கீழே உள்ள இரண்டாவது தசை ஒன்று உதவுவதால், முழங்கையை மடக்கும் திறன் பொதுவாக நன்றாக மீள்கிறது.
ஓர் இழுவை இயந்திரத்தோடு (winch) நங்கூரமிடப்பட்ட ஒரு கயிற்றை நினைத்துப் பாருங்கள். கயிறு உருளையிலிருந்து அறுந்துவிட்டால், இயந்திரத்தின் மோட்டார் இன்னும் ஓடும்; ஆனால் எதுவும் சுழலாது. கயிறு தானாகத் திரும்பி வந்து தன்னைக் கட்டிக்கொள்வதில்லை. அதை மீண்டும் இணைக்க வேண்டும்.
அப்படியே விட்டுவிட்டால், கிழிந்த முனை அது இருக்க வேண்டிய இடத்தில் எலும்போடு மீண்டும் ஒட்டிக் குணமடைவதில்லை. அதற்குப் பதிலாக, இடைவெளி வடுத் திசுவால் (scar tissue) நிரம்புகிறது; அது பாகங்களை ஒன்றாகப் பிடித்து வைக்கிறது, ஆனால் வலிமையை மீட்டுத் தருவதில்லை. இணைப்பு மீண்டும் உறுதியாகக் குணமடையும்படி, அறுவை சிகிச்சை தசைநாணின் முனையை அதன் அசல் நங்கூரப் புள்ளியோடு மீண்டும் இணைக்கிறது.
இந்தக் கிழிவு பொதுவாக நாற்பதுகளிலிருந்து அறுபதுகள் வரையிலான வயதுடைய ஆண்களின் அதிகம் பயன்படுத்தும் கையில் ஏற்படுகிறது; பெரும்பாலும் எடை தூக்குவது போல, கை மடங்கியும் உள்ளங்கை மேல்நோக்கியும் இருக்கும்போது செய்யப்படும் ஒரே ஒரு கனமான முயற்சியின்போது நிகழ்கிறது. தசைநாண் அதன் நீளவாக்கில் பிளவுபடுவதைவிட, கிட்டத்தட்ட எப்போதும் எலும்பிலிருந்து முழுமையாகக் கிழிந்து விலகுகிறது; இருப்பினும், தசைநாணின் ஒரு பகுதியை இன்னும் ஒட்டியபடியே விட்டுவைக்கும் பகுதியளவு கிழிவுகளும் (partial tears) ஏற்படலாம்.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் பணியாற்றும் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் குறிப்பிட்ட காயத்துக்கு ஏற்ற சிகிச்சையைத் தேர்ந்தெடுக்கிறார். சில கீழ்முனைப் பைசெப்ஸ் கிழிவுகளை அறுவை சிகிச்சை இல்லாமலேயே கையாள முடியும்; வேறு சிலவற்றுக்குக் காயம் ஏற்பட்ட சிறிது காலத்திலேயே அறுவை சிகிச்சை தேவைப்படுகிறது; எனவே உடனடி மதிப்பீடு முக்கியம். நோயாளிகள் பொதுவாக அவர்களுடைய GP (பொது மருத்துவர்) மூலம் எங்கள் கிளினிக்கிற்குப் பரிந்துரைக்கப்படுகின்றனர்; ஒரு இயன்முறை சிகிச்சையாளர் (physiotherapist) எங்களைப் பார்க்கும்படி பரிந்துரைத்திருந்தாலும், Medicare தள்ளுபடியைப் (rebate) பெறத் தகுதி பெற உங்கள் GP-யிடமிருந்து பரிந்துரைக் கடிதம் (referral) இன்னும் தேவைப்படும். கிளினிக்கில், நாங்கள் உங்கள் மருத்துவ வரலாற்றைக் கேட்டறிந்து, உங்கள் இரண்டு முழங்கைகளையும் பரிசோதித்து, உதவியாக இருக்கும் இடங்களில் படப் பரிசோதனைகளுக்கு ஏற்பாடு செய்கிறோம். வழக்கமான முதல் பரிசோதனை எக்ஸ்-ரே (X-ray); தசைநாண் கிழிந்துள்ளதா, எவ்வளவு மோசமாகக் கிழிந்துள்ளது என்பதை MRI ஸ்கேன் உறுதிப்படுத்த முடியும்.
தசைநாண் எலும்பிலிருந்து முழுமையாகப் பிய்ந்துவிட்ட முழுமையான கிழிவுக்கு, தொடக்கத்திலிருந்தே அறுவை சிகிச்சை பரிந்துரைக்கப்படுகிறது. உடல் உழைப்புத் தொழிலாளர்கள், விளையாட்டு வீரர்கள் போல, வேலைக்கோ விளையாட்டுக்கோ முன்கையை வலுவாகத் திருக வேண்டியவர்களுக்கு இது பொதுவாகச் சரியான தேர்வு. வலிமையும் செயல்பாடும் திரும்பும்படி, இந்த அறுவை சிகிச்சை தசைநாணை அதன் அசல் நங்கூரப் புள்ளியோடு மீண்டும் இணைக்கிறது. ஒரு சிறிய பொத்தான் பொருத்தியைப் (button fixation) பயன்படுத்திச் செய்யப்படும் சரிசெய்தல், கிட்டத்தட்ட இயல்பான வலிமையையும் செயல்பாட்டையும் மீட்டுத் தருகிறது; இந்த அறுவை சிகிச்சையில் கடுமையான சிக்கல்களின் விகிதம் குறைவு. சரிசெய்தலுக்குப் பிறகு ஏற்படும் சிறிய பிரச்சினைகளில் பெரும்பாலானவை, காலப்போக்கில் தணியும் மரத்துப்போன பகுதிகளே. காயம் ஏற்பட்ட சிறிது காலத்திலேயே — முடிந்தால் சுமார் 3 வாரங்களுக்குள் — சரிசெய்யும்போது அது சிறப்பாகப் பலனளிக்கிறது; ஏனெனில் தசைநாண் கையின் மேல்நோக்கிச் சுருங்கிப் பின்வாங்குகிறது, அது இருந்த இடத்தில் வடுத் திசு உருவாகிவிடுகிறது. தாமதமான சரிசெய்தல் சில நேரங்களில் சாத்தியம்; ஆனால் அது மிகவும் சவாலானது, நீளத்தை மீட்க ஒரு தசைநாண் ஒட்டுத் திசு (tendon graft) தேவைப்படலாம்.
தசைநாணின் ஒரு பகுதி இன்னும் ஒட்டியிருக்கும் பகுதியளவு கிழிவுக்கு, அறுவை சிகிச்சை அல்லாத சிகிச்சை சில நேரங்களில் ஒரு நியாயமான தேர்வு. இது, கைத்தாங்கியிலோ (sling) பிளவுக்கட்டையிலோ (splint) கைக்கு ஓய்வளிப்பது, கிழிவு குணமடையும்போது அதைப் பாதுகாப்பது, உங்கள் கை சிகிச்சையாளருடன் (hand therapist) படிப்படியாக அசைவுக்குத் திரும்புவது ஆகியவற்றை உள்ளடக்கியது. அறுவை சிகிச்சையைத் தவிர்ப்பதற்காக ஓரளவு வலிமையை விட்டுக்கொடுக்கும் பாதை இது; அந்த ஆதாய-இழப்புச் சமநிலை (trade-off), நாம் இருவரும் சேர்ந்து எடுக்கும் உண்மையான கூட்டு முடிவு. உள்ளங்கையை மேல்நோக்கித் திருப்புவதில் ஏற்படும் பலவீனம் உங்கள் வேலைக்கோ அன்றாட வாழ்க்கைக்கோ ஏற்கத்தக்கதாக இருக்காது என்றால், அறுவை சிகிச்சை உங்களுக்கு மேலும் பொருத்தமாக இருக்கலாம்.
நீங்கள் எந்தப் பாதையைத் தேர்ந்தெடுத்தாலும், ஆரம்ப வாரங்களின் அடிப்படைகள் ஒன்றே: வலிக் கட்டுப்பாடு, குணமடையும்போது கையைப் பாதுகாப்பது, சரியான கட்டத்தில் கை சிகிச்சை (hand therapy). அறுவை சிகிச்சைக்குப் பிறகு, உங்கள் கை சிகிச்சையாளர் உங்கள் மீட்சியை வழிநடத்தி, உங்களுக்குத் தேவைப்படும் எந்தப் பிளவுக்கட்டையையும் (splint) செய்து தருவார்; Extend Rehabilitation-இல் Ruby Doolan-உடனான மறுவாழ்வு அறுவை சிகிச்சைக்குப் பிறகு விரைவிலேயே தொடங்குகிறது, ஆரம்பகால மென்மையான அசைவு நன்றாகத் தாங்கிக்கொள்ளப்படுகிறது.
என்ன எதிர்பார்க்கலாம்
கீழ்முனைப் பைசெப்ஸ் அறுவுக்குப் பிறகு குணமடைவது விரைவான தீர்வு அல்ல; அது மெதுவாகக் கட்டியெழுப்பப்படும் ஒன்று. தசைநாண் எலும்போடு மீண்டும் ஒட்டிக் குணமடைய நேரம் தேவை; வலிமை நாட்களில் அல்லாமல் மாதக்கணக்கில் படிப்படியாகத் திரும்புகிறது. முதல் சில வாரங்களில், குணமடையும்போது கையைப் பாதுகாப்பதே முக்கிய நோக்கம்; காயத்துக்குப் பிந்தைய ஆரம்ப நாட்களில் தணிந்ததைப் போலவே வலியும் வீக்கமும் தணிகின்றன.
நீங்கள் அறுவை சிகிச்சை செய்துகொண்டால்: பெரும்பாலானோர் தங்கள் பணிகளில் எந்த மாற்றமும் இல்லாமல் வேலைக்குத் திரும்புகிறார்கள்; வேலைக்குத் திரும்புவதற்கான சராசரிக் காலம் சுமார் 14 வாரங்கள். விளையாட்டுக்கு அதிக காலம் ஆகும். சுமார் 95% விளையாட்டு வீரர்கள் விளையாட்டுக்குத் திரும்புகிறார்கள்; 82% பேர் காயத்துக்கு முன் போட்டியிட்ட அதே தரத்திற்குத் திரும்புகிறார்கள் — விளையாட்டைப் பொறுத்து, சுமார் 40 வாரங்களில். கையை மடக்குவதிலும் திருகுவதிலும் உள்ள வலிமை கிட்டத்தட்ட இயல்பான நிலைக்குத் திரும்பலாம். காயத்துக்கு முன்பு இருந்த கையோடு ஒப்பிடுகையில், குறிப்பாகத் திரும்பத் திரும்பத் திருகும்போது, ஒரு சிறிய வேறுபாட்டைச் சிலர் கவனிக்கிறார்கள்.
உங்கள் கிழிவு அறுவை சிகிச்சை இல்லாமல் கையாளப்பட்டால், குணமடையும்போது கைக்குக் கைத்தாங்கியிலோ பிளவுக்கட்டையிலோ ஓய்வளிக்கப்படுகிறது; உங்கள் கை சிகிச்சையாளருடன் சேர்ந்து நீங்கள் படிப்படியாக அசைவை மீண்டும் கட்டியெழுப்புகிறீர்கள். இந்தப் பாதை, உள்ளங்கையை மேல்நோக்கித் திருப்புவதில் ஓரளவு நீடித்த பலவீனத்தை விட்டுச்செல்கிறது; இந்தப் பக்கத்தில் முன்பே விவாதிக்கப்பட்ட ஆதாய-இழப்புச் சமநிலை இதுதான்.
பெரும்பாலானோர் நன்றாக மீள்கிறார்கள்; ஆனாலும் என்ன தவறு நேரலாம் என்பதை அறிந்திருப்பதே நேர்மையானது. சரிசெய்தலுக்குப் பிறகு உள்ள முக்கிய அபாயங்கள்: நரம்புக் காயம் (பெரும்பாலும் காலப்போக்கில் தணியும் ஒரு மரத்துப்போன பகுதி), முழங்கையில் விறைப்பு, சரிசெய்தல் மீண்டும் கிழிவது. சரிசெய்தல் மீண்டும் கிழிவதற்கான வாய்ப்பு குறைவு — 1.5%; அது நிகழும்போது, பொதுவாக அறுவை சிகிச்சைக்குப் பிறகு 3 வாரங்களுக்குள் நிகழ்கிறது. சில நேரங்களில் முன்கையின் குறுக்கே புதிய எலும்பு உருவாகித் திருகும் அசைவைக் கட்டுப்படுத்தலாம்; இருப்பினும் இது நிகழும்போதும், அளவிடக்கூடிய வேறுபாடு எதுவும் இல்லாமல் வலிமை தக்கவைக்கப்படலாம்.
சில அறிகுறிகளுக்கு விரைவான நடவடிக்கை தேவை. உங்கள் கை (hand) அல்லது விரல்கள் வெளிறியோ, குளிர்ந்தோ, வெள்ளையாகவோ, நீலமாகவோ மாறினால், அல்லது காயத்துக்குப் பிறகு கையில் (hand) திடீரென உணர்வையோ அசைவையோ இழந்தால், அதே நாளில் அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். வலியோ விறைப்போ தணியாமல் இருந்தால், வாரக்கணக்கில் மோசமாகிக்கொண்டிருந்தால், அல்லது உங்கள் கையைப் பயன்படுத்த விடாமல் தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது சிறப்பு மருத்துவரின் மதிப்பாய்வைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
உங்கள் கை (arm) வெளிப்படையாக உருக்குலைந்து தோன்றினால், காயத்தின் மேல் திறந்த புண் இருந்தால், அல்லது அந்தக் கையை உங்களால் சற்றும் பயன்படுத்த முடியவில்லை என்றால், அவசர சிகிச்சையை நாடுங்கள். உங்கள் கை (hand) அல்லது விரல்கள் வெளிறியோ, குளிர்ந்தோ, வெள்ளையாகவோ, நீலமாகவோ மாறினால், அல்லது காயத்துக்குப் பிறகு கையில் (hand) திடீரென உணர்வையோ அசைவையோ இழந்தால், அதே நாளில் அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். இந்த அறிகுறிகள் இந்தப் பக்கத்தில் முன்பே விவரிக்கப்பட்டுள்ளன.
மற்ற எல்லாவற்றுக்கும், உங்கள் GP-யிடமிருந்து தொடங்குங்கள். வலி தணியாமல் இருந்தால், அல்லது குணமடைதல் முன்னேறும்போது வீக்கம், அசைவு அல்லது வலிமை வாரத்துக்கு வாரம் மேம்படவில்லை என்றால், உங்கள் GP-யைப் பாருங்கள் அல்லது சிறப்பு மருத்துவரின் மதிப்பாய்வைக் கேளுங்கள். முழங்கையின் முன்பக்கத்தில் திடீரென "படக்" என்ற உணர்வுடன் தசையின் வடிவத்திலும் மாற்றம் ஏற்பட்டால், அதை உடனடியாகப் பரிசோதித்துக்கொள்வது நல்லது; ஏனெனில் காயம் ஏற்பட்டு சுமார் 3 வாரங்களுக்குள் சரிசெய்யும்போதுதான் அது சிறப்பாகப் பலனளிக்கிறது.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
இந்தப் பகுதி, உங்கள் சொந்தச் சிகிச்சை முடிவுகளுக்குத் தேவையானதைவிட ஆழமாகச் செல்கிறது. கீழ்முனைப் பைசெப்ஸ் தசைநாண் அறுவு பற்றிக் கூடுதலாகப் படிப்பது பயனுள்ளது; ஏனெனில், அறுவை சிகிச்சை இல்லாமல் குணமடைவது மீட்டுத் தராத ஒன்றை அறுவை சிகிச்சை நிரூபிக்கத்தக்க வகையில் மீட்டுத் தரும், இந்த இணையதளத்தில் உள்ள ஒரு சில காயங்களில் இதுவும் ஒன்று. இது ஆதாய-இழப்புச் சமநிலையை (trade-off) வழக்கத்துக்கு மாறாகத் தெளிவாக்குகிறது; சிக்கல் விகிதங்களையும் வழக்கத்துக்கு மாறாகப் பொருத்தமானவையாக்குகிறது.
இங்கே, அறுவை சிகிச்சை செயல்பாட்டை உண்மையிலேயே மாற்றுகிறது
இந்த இணையதளத்தில் உள்ள ஒப்பீடுகளில் பெரும்பாலானவை "குறிப்பிடத்தக்க வேறுபாடு இல்லை" என்றே முடிகின்றன. இது அப்படி அல்ல. 2,481 நோயாளிகளின் தரவுகளை ஒன்றிணைத்தபோது, அறுவை சிகிச்சை அல்லாத சிகிச்சையைவிட அறுவை சிகிச்சை சிறந்த முழங்கை மற்றும் முன்கை வலிமையையும் தாங்குந்திறனையும் தந்தது; அத்துடன் சிறந்த DASH மற்றும் Mayo Elbow Performance மதிப்பெண்களையும் தந்தது [1].
இதற்கான காரணம் புள்ளியியல் சார்ந்தது அல்ல, உடற்கூறு சார்ந்தது. கீழ்முனைப் பைசெப்ஸ்தான் முன்கையின் முதன்மையான சுப்பினேட்டர் (supinator) — அதாவது எதிர்ப்புக்கு எதிராக உள்ளங்கையை மேல்நோக்கித் திருப்பும் தசை. தசைநாண் ரேடியஸ் (radius) எலும்பிலிருந்து விலகும்போது, அது கையின் மேல்நோக்கிச் சுருங்கிப் பின்வாங்குகிறது; அதைச் சுற்றி வேறு எது குணமடைந்தாலும், அந்தத் தசையால் இனி அந்தச் சுழற்சியை உருவாக்க முடியாது. முழங்கையை மடக்கும் வேலையை ப்ரேக்கியாலிஸ் (brachialis) தசை ஓரளவு ஈடுகட்டுகிறது; எனவே முழங்கை மடங்கும் திறன் நியாயமான அளவுக்குத் திரும்புகிறது. ஆனால் சுப்பினேஷனுக்கு (supination) அப்படி ஒரு மாற்று நடிகர் இல்லை.
அதனால்தான் இந்த இழப்பு, ஒரே ஒரு அதிகபட்ச முயற்சியில் அல்லாமல், தாங்குந்திறனில் (endurance) மிகத் தெளிவாகத் தெரிகிறது. திரும்பத் திரும்பத் திருப்புவதில் — திருப்புளி, கதவுப் பிடி, நீண்ட பயணத்தில் வாகனத்தின் சுக்கான் — அந்த வேறுபாடு உணரப்படுகிறது.
சிக்கல் விகிதம்தான் இந்த முடிவின் மறுபாதி
வலிமையை நம்பகமாக மீட்டுத் தரும் ஒரு அறுவை சிகிச்சையும் அறுவை சிகிச்சைதான்; இதன் அபாயத் தன்மை நன்கு ஆவணப்படுத்தப்பட்டுள்ளது. 3,091 நோயாளிகளை உள்ளடக்கிய மிகப் பெரிய பகுப்பாய்வில், பெரிய சிக்கல் விகிதம் 4.6% ஆக இருந்தது [2].
ஏற்படுவதில் பெரும்பாலானவை சிறியவையும் தற்காலிகமானவையும்: ஒரு சிறிய உணர்வு நரம்பின் மீது இழுவை விழுவதால் முன்கையின் பின்புறத்தில் ஏற்படும் மரத்துப்போதல்தான் மிகவும் பொதுவானது, அது பொதுவாகச் சரியாகிவிடும். நுட்பத்தை வடிவமைக்கும் பெரிய சிக்கல்கள் இவை: நிரந்தர நரம்புக் காயம், ஹெட்டிரோடோபிக் ஆசிஃபிகேஷன் (heterotopic ossification — முன்கையின் குறுக்கே புதிய எலும்பு உருவாகிச் சுழற்சியைக் கட்டுப்படுத்துவது), மேலும் மீண்டும் அறுந்துபோதல்.
இரண்டு அணுகுமுறைகள், அவற்றுக்கிடையிலான ஆதாய-இழப்புச் சமநிலை உண்மையானது
சரிசெய்யும் அறுவை சிகிச்சை, முழங்கையின் முன்பக்கத்தில் ஒரே ஒரு கீறல் மூலமாகவோ, அல்லது முன்னும் பின்னுமாக இரண்டு சிறிய கீறல்கள் மூலமாகவோ செய்யப்படுகிறது. இரண்டுமே வெவ்வேறு திசைகளிலிருந்து ஒரே எலும்பை அடைகின்றன; ஒவ்வொன்றும் வெவ்வேறு அபாயத்தைத் தவிர்க்கிறது.
2,622 நோயாளிகளிடையே, செயல்பாட்டு மதிப்பெண்களில் குறிப்பிடத்தக்க வேறுபாடுகள் எதுவும் இல்லை. ஒற்றைக் கீறல் அணுகுமுறை அதிக மடக்கு (flexion) மற்றும் ப்ரோனேஷன் (pronation) அசைவு வீச்சையும், ஹெட்டிரோடோபிக் ஆசிஃபிகேஷன் மற்றும் மறு அறுவை சிகிச்சைக்கான குறைந்த அபாயத்தையும் தந்தது; இரட்டைக் கீறல் அணுகுமுறை வேறு சில அளவீடுகளில் மேலும் சாதகமாக இருந்தது [3]. 2,833 நோயாளிகள் பற்றிய 2025-ஆம் ஆண்டின் ஒரு மெட்டா-பகுப்பாய்வும் இதே வடிவத்தையே கண்டறிந்தது: ஒற்றைக் கீறல் மேலும் சாதகமான புறவயச் செயல்பாட்டோடும் குறைவான கட்டமைப்புச் சிக்கல்களோடும் தொடர்புடையது; இரட்டைக் கீறல் சில உணர்வு நரம்புக் காயங்களுக்கான குறைந்த அபாயத்தோடு தொடர்புடையது [4].
இரண்டையும் சேர்த்துப் படித்தால், இந்தத் தேர்வு முன்பக்கத்தில் உள்ள நரம்புக்கும் பின்பக்கத்தில் உள்ள எலும்புக்கும் இடையிலானது. இரண்டு அணுகுமுறைகளுமே தவறானவை அல்ல; இந்தக் கேள்வி முடிவுக்கு வந்ததாகக் கருதுவதற்கு முன், உயர்தரமான சமவாய்ப்பு (randomised) ஆய்வுகள் தேவை என்று இரு தரப்பு ஆசிரியர்களுமே கோருகின்றனர்.
மற்ற இடங்களைவிட இங்கே கால அளவு ஏன் அதிக முக்கியத்துவம் பெறுகிறது
தசைநாண் சுருங்கிப் பின்வாங்குவதாலும், அது இருந்த இடத்தில் வடுத் திசு உருவாவதாலும், தாமதம் மீண்டும் இணைப்பதைக் கடினமாக்குகிறது; நேரடியாகச் சரிசெய்வது இயலாத நிலையில், ஒட்டுத் திசு (graft) கொண்டு மறுகட்டமைப்பு செய்வது தேவையாகிறது. பெரும்பாலான தசைநாண் காயங்களைவிடக் கீழ்முனைப் பைசெப்ஸ் தசைநாண் அறுவு அதிக அவசரத்துடன் கையாளப்படுவதற்கான நடைமுறைக் காரணம் இதுவே; முழங்கையின் முன்பக்கத்தில் திடீரென வலியுடன் "படக்" என்ற உணர்வும், தசையின் வடிவத்தில் கண்ணுக்குத் தெரியும் மாற்றமும் ஏற்பட்டால், காத்திருந்து கவனிப்பதைவிட உடனடி மதிப்பீடு ஏன் அவசியம் என்பதற்கான காரணமும் இதுவே.
அறுவை சிகிச்சை அல்லாத சிகிச்சை ஒரு நியாயமான தேர்வாகவே இருக்கிறது; குறிப்பாகக் கையின் மீது அதிகத் தேவை இல்லாதவர்களுக்கும், வலிமையான, திரும்பத் திரும்பச் செய்யும் சுப்பினேஷன் தேவைப்படாதவர்களுக்கும். இது, அளவிடக்கூடிய ஒரு குறைபாட்டை வேண்டுமென்றே ஏற்றுக்கொள்ளும் முடிவு; அதே முடிவின் தாழ்ந்த வடிவம் அல்ல.
மேற்கோள்கள்
[1] Looney AM, Day J, Bodendorfer BM, Wang D, Fryar CM, Murphy JP, et al. Operative vs. nonoperative treatment of distal biceps ruptures: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2022;31(4):e169-e189. https://doi.org/10.1016/j.jse.2021.12.001
[2] Amarasooriya M, Bain GI, Roper T, Bryant K, Iqbal K, Phadnis J. Complications after distal biceps tendon repair: a systematic review. Am J Sports Med. 2020;48(12):3103-11. https://doi.org/10.1177/0363546519899933
[3] Castioni D, Mercurio M, Fanelli D, Cosentino O, Gasparini G, Galasso O. Single- versus double-incision technique for the treatment of distal biceps tendon rupture: a systematic review and meta-analysis of comparative studies. Bone Joint J. 2020;102-B(12):1608-17. https://doi.org/10.1302/0301-620X.102B12.BJJ-2020-0822.R2
[4] Awad G, Boutros M, Hajj Youssef M, Elhassan B. Comparing single-incision and double-incision techniques in distal biceps tendon repair: a systematic review and meta-analysis. Shoulder Elbow. 2025. https://doi.org/10.1177/17585732251399838
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Distal biceps tendon injuries typically occur in middle-aged, higher-demand patients who often require surgical reconstruction to optimize outcome and performance [24].
- Surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications regardless of approach or technique [8, 9, 11, 12].
- Distal biceps repair is associated with a 7.5% major complication rate and a 4.5% reoperation rate [7].
- A systematic review indicates a major complication rate of 4.6% after distal biceps repair [31].
- Patients should be counseled that 1 in 5 patients will have a minor complication and 1 in 20 patients will have a major complication after surgery on the distal biceps tendon [14].
- The overall frequency of reported complications is higher for single-incision distal biceps repair than for double-incision repair [1].
- Nerve injury is the most common complication following distal biceps tendon repair [38].
- The early complication rate following partial distal biceps tendon repair was 20.5% [23].
- Surgical treatment of chronic distal biceps injuries yields favorable objective and subjective outcomes [3].
- Although there may be a slightly higher immediate complication rate for chronic distal biceps ruptures, functional outcomes remain comparable with those seen in the patient population with acute distal biceps [6].
- Patients who underwent distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair [18].
- Even in the setting of a distal biceps reconstruction with graft augmentation, patients can expect low complications and good functional results [10].
- Surgical repair of the distal biceps insertion reliably regains both supination and flexion strength in appropriate patients [55].
- Athletes sustaining distal biceps tendon rupture have a high postoperative return to sport rate, independently of selected surgical technique or rehabilitation program [50].
- Surgical management of distal biceps tears was a predictor of improved patient-reported outcomes only for patients with complete tears [16].
Anatomy & Pathophysiology
Anatomy
- The biceps brachii is the primary supinator and a secondary flexor of the elbow [52].
- The short head of the biceps muscle arises from the coracoid process of the scapula [52].
- The long head of the biceps originates from the supraglenoid tubercle of the scapula and the glenoid labrum [52].
- The long head merges with the short head to form the distal biceps tendon and its medial extension, the lacertus fibrosus [52].
- The distal biceps tendon rotates 90 degrees such that the medial side of the tendon attaches to the distal portion of the radial tuberosity [52].
- The distal biceps tendon is a paratenon-covered extrasynovial tendon with three zones of blood supply [120].
- Zone 1 of the distal biceps tendon blood supply receives vessels from the brachial artery via branches extending past the musculotendinous junction to supply the bulk of the tendon [120].
- Zone 3 of the distal biceps tendon blood supply receives contributions from the posterior interosseous recurrent artery and is limited to the tendon enthesis on the radial tuberosity [120].
- Zone 2 of the distal biceps tendon is covered in a significantly thinner paratenon and receives vessels from both Zone 1 and Zone 3 sources through its extratendinous paratenon cover [120].
- The junction among the three zones of blood supply in the distal biceps tendon may be a transition area where tendon repair mechanisms are limited [120].
- The narrow passage between the lateral ulnar border and the radial tuberosity decreases by roughly 50% in pronation as compared with supination [120].
- The brachialis tendon is an intramuscular tendon at the level of the antecubital fossa and cannot be hooked away from an underlying muscle belly [37].
- The normal lacertus fibrosus often remains intact even with biceps rupture and must be discriminated from the biceps tendon during examination [34].
Pathophysiology
- Distal biceps injuries frequently occur in middle-aged males after an eccentric load to the elbow in flexion [17].
- Distal biceps tendon ruptures typically occur in the dominant arm of males during the fifth to sixth decade of life [37].
- The incidence of distal biceps tendon ruptures is 1.2 per 100,000 persons per year [37].
- Distal biceps tendon ruptures are associated with a traumatic event causing a sudden, eccentric load to a flexed and supinated forearm [37].
- Common risk factors for distal biceps tendon rupture include anabolic steroid use, body building, and smoking [37].
- Distal biceps tendon ruptures were most commonly observed in weightlifting with a slightly flexed or isometrically extended elbow and forearm supination [98].
- In a series of competitive strength athletes, the most common strength sport activities leading to distal biceps tendon rupture were deadlifting (20%) and biceps curls (13%) [119].
- Outside of sporting activities, the most common mechanisms of injury for distal biceps tendon rupture were lifting (34%) or carrying (11%) a heavy object and falling onto the outstretched arm (13%) [119].
- A hypovascular zone near the tendon insertion on the tuberosity can limit repair mechanisms in this area [52].
- A 50% narrowing of the space available for the tendon between the radius and ulna occurs in pronation as opposed to supination [52].
- Preexisting inflammatory or degenerative changes involving the distal biceps tendon predispose to rupture from the radial tuberosity [120].
- The junction among the three zones of blood supply in the distal biceps tendon is more prone to attritional injury and rupture [120].
- Rupture of the distal insertion of the biceps tendon necessarily completely eliminates the function of the muscle [52].
- Distal biceps tendon rupture has been found to result in a 30–50% decrease in supination endurance and strength [52].
- Distal biceps tendon rupture has been found to result in an approximate 20% decrease in flexion strength [52].
- Partial distal biceps tendon tears encompass a spectrum of disease from tendinopathic micro-tears to near-full-thickness rupture from the radial tuberosity [2].
- The mechanism of full-thickness distal biceps tendon tears is well reported with a defined episode of injury, deformity, pain, and weakness [2].
- Partial distal biceps tendon tears may have a variable presentation with either an insidious or acute traumatic history, pain, mechanical symptoms, and subtle examination findings [2].
- The condition of partial distal biceps tendon tears may remain undiagnosed or mismanaged, leading to a delay in treatment [2].
- The insertion site of the distal biceps tendon on the radial tuberosity undergoes degenerative changes that begin with partial tearing of the tendon [40].
- Degenerative changes at the distal biceps insertion can be painful but also clearly can be asymptomatic [40].
- Patients with distal biceps ruptures often show signs of significant chronic degeneration with partial tearing before the acute rupture [40].
- Many patients with distal biceps ruptures deny having any symptoms referable to their distal biceps insertion before the acute event that caused them to present for treatment [40].
- Partial biceps tendon tears may result from an acute event or tearing in conjunction with chronic degeneration [40].
Classification
- Partial distal biceps tendon tears encompass a spectrum of disease ranging from tendinopathic micro-tears to near-full-thickness rupture from the radial tuberosity [2].
- Full-thickness distal biceps tendon tear patients tend to present acutely [2].
- Recommended management algorithms for partial distal biceps tendon tears typically focus on patient factors and a tear percentage of 50% as a guide for conservative treatment versus repair [2].
- The '50%-rule' on a 2-dimensional MRI measurement is likely an over-simplified parameter for a complex three-dimensional structure with known anatomical variants [2].
- Isolated short head ruptures are a rare and distinct form of distal biceps tear that present with consistent clinical findings that can aid in diagnosis [19].
- The incidence of women sustaining a distal biceps tendon tear is 3.2% [20].
- Partial tears are statistically more common than complete ruptures in women sustaining a distal biceps tendon tear [20].
- Injury to the distal biceps typically occurs in middle aged, higher demand patients who often require surgical reconstruction to optimize outcome and performance [24].
- Distal biceps tendon ruptures occur at a rate of 1.2 ruptures per 100,000 persons per year [47].
- Distal biceps tendon ruptures account for approximately 3% of all biceps tendon injuries [47].
- Distal biceps tendon ruptures remain a predominately male injury, possibly due to the larger cross-sectional area of biceps in men [47].
- Distal biceps tendon injuries are most likely traumatic events arising when sudden extension load is applied to a flexed, supinated arm [47].
- The aetiology of biceps tendon ruptures is most likely multifactorial, involving a variety of mechanical, degenerative and hypovascular factors [47].
- Seiler et al. discovered three vascular zones in the tendon and reported an approximately 2 cm zone of hypovascularity between the proximal and distal zones [47].
- A more than 50% decrease in the cross sectional area available for the tendon from full supination to full pronation leads to an increased risk for rupture [47].
- Kannus and colleagues reported degenerative tendinopathy in ruptured tendons, based on histopathologic findings [47].
- Smokers have a 7.5 times higher risk of a total rupture compared with non smokers [47].
- Smoking along with anabolic steroids may be related to tendon degeneration and rupture [47].
- There was a 7-fold increase in the incidence of distal biceps tendon rupture surgery in Finnish men during 1997 to 2016 [25].
- There was a 28-fold increase in the incidence of distal biceps tendon rupture surgery in Swedish men during 1997 to 2016 [25].
Clinical Presentation
Epidemiology and Risk Factors
- Distal biceps tendon ruptures typically occur in the dominant arm of males during the fifth to sixth decade of life at a rate of 1.2 per 100,000 persons per year [37].
- The vast majority of complete distal biceps tendon ruptures occurs in men between 40 and 60 years of age [46].
- The dominant limb is involved in 52% of complete distal biceps tendon rupture cases [46].
- An 8% cumulative incidence of bilateral biceps tendon ruptures has been reported [46].
- The incidence of women sustaining a distal biceps tendon tear is 3.2%, with partial tears being statistically more common than complete ruptures in women [20].
- In women, distal biceps tendon ruptures are described as having a more gradual onset of symptoms and a higher incidence of partial tears [46].
- There was a 7-fold increase in the incidence of distal biceps tendon rupture surgery in Finnish men between 1997 and 2016 [25].
- There was a 28-fold increase in the incidence of distal biceps tendon rupture surgery in Swedish men between 1997 and 2016 [25].
History and Mechanism
- Patients with full-thickness distal biceps tendon tears tend to present acutely [2].
- Distal biceps tendon ruptures are associated with a traumatic event which causes a sudden, eccentric load to a flexed and supinated forearm [37].
- A patient typically relates a history of lifting an object or a forced extension of a flexed and loaded forearm [40].
- The patient may recall an audible pop over the anterior elbow [37].
- Patients with chronic and slowly degenerative partial tears often complain of nonspecific elbow pain that is worsened with daily activities [40].
Physical Examination Findings
- A patient with biceps pathologic conditions exhibits pain and weakness in flexion and supination [34].
- Ecchymoses in the antecubital fossa may be present in patients with biceps pathologic conditions [34].
- An abnormal muscle contour of the biceps may be observed in patients with biceps pathologic conditions [34].
- Inspection of the soft tissues tends to demonstrate swelling of the soft tissues in the antecubital fossa [37].
- Retraction of the muscle belly with a visible bulge, known as a reverse Popeye deformity, is a clinical finding supporting the diagnosis of distal biceps rupture [37].
- Weakness in flexion and supination is a clinical finding supporting the diagnosis of distal biceps rupture [37].
- Bruising is a clinical finding supporting the diagnosis of distal biceps rupture [37].
- If seen a few days after the injury episode, ecchymosis is commonly present over the elbow and proximal forearm [40].
- Patients often point out the asymmetry and the "Pop-eye" deformity in the biceps muscle belly [40].
- In partial tears, the biceps may still be palpable [40].
- Patients with chronic partial tears often point to the anterior middle aspect of the antecubital fossa but do not specifically point to the posterolateral aspect of the elbow or the area of the radial tuberosity [40].
- Pain elicited by deep palpation of the radial tuberosity from the posterolateral aspect while passively pronating the forearm is a good indication of tendinopathy involving the insertion of the distal biceps [40].
- Isolated short head ruptures present with consistent clinical findings that can aid in diagnosis [19].
Diagnostic Tests
- The hook test involves having the patient's elbow in 90° of flexion and full supination, then hooking a finger around the lateral edge of the distal biceps tendon as it spans the antecubital fossa [37].
- The hook test has proven 100% sensitivity and specificity for making a prompt diagnosis of distal biceps rupture [37].
- The hook test allows for the distinction between complete avulsion, which results in an abnormal hook test, and partial avulsion, which yields a painful hook test [37].
- O'Driscoll hook test sensitivity is not 100% but remains a useful clinical test to assess patients with suspected distal biceps tendon tears [81].
- A negative O'Driscoll hook test does not exclude rupture [81].
- The evidence-based diagnostic algorithm using the combination of the Flexion Initiation Test (FIT) and hook test demonstrates high accuracy for the diagnosis of both complete and high-grade partial distal biceps tendon tears [33].
- Missed injuries have been attributed to the examiner palpating an intact brachialis tendon, which is an intramuscular tendon at the level of the antecubital fossa and cannot be hooked away from an underlying muscle belly [37].
- Occasionally, some fibers or a fascial sleeve may remain intact, giving an appearance of an intact tendon [34].
- The examiner must discriminate between the normal lacertus fibrosus, which often remains intact even with biceps rupture, and the biceps tendon [34].
Imaging
- Plain film radiographs are most commonly normal and do not show pathologic changes in distal biceps ruptures [34].
- Biceps ruptures typically do not involve bony ruptures, and minimal changes are seen on standard radiographs of the elbow [34].
- MRI may show rupture but is unnecessary in most cases and occasionally may be read as falsely negative [34].
- Some authors suggest a 100% correlation between MRI findings and intraoperative findings for distal biceps ruptures [34].
- MRI did not affect the operative plan in the setting of rupture of a previously repaired ruptured distal biceps tendon [34].
- MRI is useful to exclude alternative diagnoses and to evaluate the extent of suspected partial rupture [34].
- MRI is useful in cases where the history suggests a biceps rupture but the clinical examination is unclear [34].
- MRI tells the surgeon the expected location of the distal tendon end and whether it has retracted proximally [34].
- MRI findings suggestive of complete rupture include absence of the tendon insertion or a fluid-filled sheath [34].
- Partial ruptures on MRI are typically seen as high signal intensity, fluid within the tendon sheath, or thinning or thickening of the tendon distally [34].
- The FABS view (shoulder abducted over the head, elbow in 90 degrees of flexion, forearm in supination) has been suggested to improve visualization of the distal biceps insertion into the radial tuberosity [34].
- Ultrasound is a lower-cost diagnostic tool that is usually unnecessary but has been shown to be accurate in the diagnosis of complete or partial tears [34].
- Ultrasound findings suggestive of complete rupture include tendon absence, fluid, and mass in the antecubital fossa [34].
- Incomplete rupture on ultrasound may be represented by a focal hypoechogenic area or thinning of the tendon [34].
- Advanced imaging with MRI or ultrasonography is helpful in cases of partial avulsions as it can assess the biceps insertion [37].
- The finding that distal biceps MRI signal changes consistent with tendinopathy are common even in asymptomatic elbows reduces the probability that symptoms correlate with pathology on imaging [42].
- The prevalence of distal biceps tendon signal changes on MRI in asymptomatic patients is very low [43].
Investigations
Clinical Examination
- The hook test has proven 100% sensitivity and specificity for making a prompt diagnosis of distal biceps tendon rupture [37].
- Missed injuries have been attributed to the examiner palpating an intact brachialis tendon, which is an intramuscular tendon at the level of the antecubital fossa and cannot be hooked away from an underlying muscle belly as in the case of an intact distal biceps tendon [37].
- On clinical examination, a patient with biceps pathologic conditions exhibits pain and weakness in flexion and supination and sometimes ecchymoses in the antecubital fossa or an abnormal muscle contour of the biceps [34].
- With the elbow at 90 degrees of flexion, the examiner may ask the patient to rotate the pronated forearm into supination; normally, the examiner can hook the tip of his or her thumb around the biceps tendon in the cubital fossa, but with distal avulsion of the tendon, this may be impossible [34].
- Deep palpation of the radial tuberosity from the posterolateral aspect while passively pronating the forearm sometimes elicits pain, which is a very good indication of tendinopathy involving the insertion of the distal biceps [40].
Imaging
- Plain film radiographs should be obtained but are most commonly normal and do not show pathologic changes, as biceps ruptures typically do not involve bony ruptures [34].
- MRI may show rupture, but it is unnecessary in most cases and occasionally may be read as falsely negative [34].
- Some authors suggest a 100% correlation between MRI findings and intraoperative findings for distal biceps rupture [34].
- If obtained, the surgeon should view the MRI images themselves, as the radiologic interpretation is just an interpretation [34].
- In the setting of rupture of a previously repaired ruptured distal biceps tendon, MRI did not affect the operative plan [34].
- MRI may be useful to exclude alternative diagnoses and to evaluate the extent of suspected partial rupture [34].
- MRI may be useful in cases in which the history suggests a biceps rupture but the clinical examination is unclear [34].
- Positioning the prone patient with the shoulder abducted over the head and the elbow in 90 degrees of flexion and the forearm in supination (the FABS view) has been suggested to improve visualization of the distal biceps insertion into the radial tuberosity [34].
- Obtaining an MRI view of the elbow during flexion, abduction, and supination allows for optimal evaluation of the tendon along its long axis and minimizes error by reducing volume averaging [37].
Treatment
Non-Operative Management
- Nonoperative management of complete distal biceps tendon ruptures does not restore function to the elbow [45].
- Conservative treatment is a viable option for very low-demand patients who have concerns about problems connected to surgery [86].
- For partial distal biceps tears, nonoperative treatment is recommended initially if less than 50% of the tendon is involved [86].
- Patients with partial distal biceps tears should be treated nonoperatively for the first 3 to 6 months [87].
- Patients with partial distal biceps tears are encouraged to avoid heavy lifting and use the arm primarily for activities of daily living only [87].
- Strengthening exercises and physical therapy are unnecessary for patients with partial biceps tendon ruptures [87].
- In a cohort study, 82% of participants with partial distal biceps tears had failed non-surgical treatment [86].
- In a study by Bauer et al., 55.7% of patients who tried a nonoperative course for partial distal biceps tears ultimately underwent surgery [36].
- High-need patients, as defined by occupation, were more likely to report ideal recovery if they underwent surgery compared to those who did not [36].
- An MRI-diagnosed tear of greater than 50% was a predictor of needing surgery for partial distal biceps tears [36].
- A meta-analysis showed the superiority of surgical management over the nonoperative approach for distal biceps tendon detachment, with superior flexion and supination strength and better patient-reported outcomes [73].
- In two case reports of nonoperative management for distal biceps tendon rupture, flexion and supination strength returned to normal limits when compared with the opposite upper extremity [22].
Operative Management
- Surgical reinsertion of the biceps tendon to the radial tuberosity is considered the treatment of choice for most complete ruptures [112].
- Although there may be a slightly higher immediate complication rate for chronic distal biceps repairs, functional outcomes remain comparable with those seen in the patient population with acute distal biceps [6].
- Patients undergoing distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair [18].
- Patients can be consulted that direct repair in the acute setting is preferred; however, even in the setting of a distal biceps reconstruction with graft augmentation, they can expect low complications and good functional results [10].
- Distal biceps tendon repair surgery can be safely and successfully executed with either a single- or double-incision approach [48].
- Single anterior incision with suture anchor repair may be utilized for repair of ruptures of the distal biceps tendon with good clinical and functional outcomes and minimal loss of range of motion and strength [80].
- Bioabsorbable interference screw fixation of distal biceps ruptures through a single anterior incision is a safe and successful technique [15].
- Anatomic reattachment of the distal biceps tendon is a successful operative treatment option [29].
- In chronic biceps tendon rupture, anatomical reinsertion is the desired surgical approach due to a high unsatisfactory results rate of 40% in non-anatomical insertion [86].
- Morrey et al. suggest performing primary distal biceps tendon repairs in up to 90 degrees of flexion [86].
- Operative treatment for significant partial distal biceps tears that do not improve after 6 months of nonoperative treatment involves taking down the remaining fibers of the distal biceps and repair to the insertion site [87].
- Operative management for significant partial distal biceps tears has been found to be satisfactory with restoration of function and resolution of symptoms through a single posterior incision [87].
- Patients who present with a classic history of a “pop” in the arm with resisted motion and sudden onset of pain should be treated as having complete biceps tears regardless of MRI findings suggestive of “partial tear” [87].
- The average time to surgery for the operative group in a study of distal biceps tendon ruptures was 9 days, ranging from 3 days to 4 weeks [69].
Complications and Outcomes
- Complication rates after distal biceps repair are low [5].
- Distal biceps repair is associated with a 7.5% major complication rate and 4.5% reoperation rate [7].
- Workers' compensation patients who underwent distal biceps tendon repair took longer to return to work and had worse DASH scores than non-workers' compensation patients [56].
Complications
- The short-term clinical influence of biceps complications on shoulder outcome is very limited [4].
- Although there may be a slightly higher immediate complication rate, the functional outcomes remain comparable with those seen in the patient population with acute distal biceps [6].
- The study examined clinical and surgical outcomes for distal biceps tendon repairs in a large cohort, finding that anterior single incision techniques were used in the majority of cases with varying fixation methods [13].
- This is a safe and successful technique for the management of distal biceps tendon ruptures [15].
- Patients that underwent distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair [18].
- Minor complications were common after distal biceps tendon repair; however, most were sensory nerve injuries that resolved with time [26].
- This is the largest analysis of complications after distal biceps repair, indicating a major complication rate of 4.6% [31].
- Complication rates after distal biceps tendon repair performed by newly trained surgeons were similar to those previously reported in large cohort studies, with nerve injury as the most common complication [38].
Complication Rates and Outcomes
Specific Complications and Risk Factors
- Timing significantly impacts surgical technique selection in distal biceps tendon ruptures, with direct repair favored for acute injuries and high flexion angle repair or allograft reconstruction for chronic cases [39].
Functional Recovery and Strength
- Distal biceps repair/reconstruction can restore near-normal flexion and supination strength [108].
Key Evidence
- [L1] The overall frequency of reported complications is higher for single-incision distal biceps repair than for double-incision repair. [1] (10.1177/2325967116668137)
- [L5] [2] (10.1177/17585732241245054)
- [L1] Surgical treatment of chronic distal biceps injuries yields favorable objective and subjective outcomes. [3] (10.1016/j.xrrt.2022.02.007)
- [L3] Nevertheless, the short-term clinical influence of biceps complications on shoulder outcome is very limited. [4] (10.1177/2325967121s00362)
- [L3] Complication rates after distal biceps repair are low. [5] (10.5397/cise.2021.00472)
- [L4] Although there may be a slightly higher immediate complication rate, the functional outcomes remain comparable with those seen in the patient population with acute distal biceps. [6] (10.1177/23259671211065772)
- [L3] Distal biceps repair is associated with a 7.5% major complication rate and 4.5% reoperation rate. [7] (10.1016/j.jse.2018.06.028)
- [L3] Surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications regardless of approach or technique. [8] (10.1016/j.jse.2017.06.021)
- [L3] Surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications regardless of approach or technique. [9] (10.1016/j.jse.2017.06.020)
- [L3] Patients can be consulted that direct repair in the acute setting is preferred; however, even in the setting of a distal biceps reconstruction with graft augmentation, they can expect low complications and good functional results. [10] (10.1016/j.jseint.2020.10.023)
- [L3] The surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications, regardless of approach or technique. [11] (10.1177/0363546517720200)
- [L3] The surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications, regardless of approach or technique. [12] (10.1016/j.arthro.2017.08.065)
- [L3] The study examined clinical and surgical outcomes for distal biceps tendon repairs in a large cohort, finding that anterior single incision techniques were used in the majority of cases with varying fixation methods. [13] (10.1016/j.jse.2016.12.053)
- [L4] Patients should be counseled that 1 in 5 patients will have a minor complication and 1 in 20 patients will have a major complication after surgery on the distal biceps tendon. [14] (10.1016/j.jse.2016.02.032)
- [Paper] This is a safe and successful technique for the management of distal biceps tendon ruptures. [15] (10.1007/s00402-009-0974-x)
- [L2] Surgical management of distal biceps tears was a predictor of improved patient-reported outcomes only for patients with complete tears. [16] (10.1016/j.jhsa.2025.12.027)
- [Paper] Distal biceps injuries frequently occur in middle-aged males after an eccentric load to the elbow in flexion. [17] (10.1016/j.injury.2025.112556)
- [L3] Patients that underwent distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair. [18] (10.1016/j.jse.2020.01.062)
- [L4] Isolated short head ruptures are a rare and distinct form of distal biceps tear that present with consistent clinical findings that can aid in diagnosis. [19] (10.1016/j.jse.2020.04.038)
- [L4] The incidence of women sustaining a distal biceps tendon tear is 3.2%, with partial tears being statistically more common than complete ruptures. [20] (10.1016/j.jse.2014.02.006)
- [L5] In both patients, flexion and supination strength returned to normal limits when compared with the opposite upper extremity. [22] (10.1016/j.jht.2020.03.013)
- [L4] The early complication rate following partial distal biceps tendon repair was 20.5%. [23] (10.1016/j.jhsa.2025.04.012)
- [Paper] Injury to the distal biceps typically occurs in middle aged, higher demand patients who often require surgical reconstruction to optimize outcome and performance. [24] (10.1016/j.csm.2020.02.004)
- [L4] There was a 7-fold and a 28-fold increase in the incidence of distal biceps tendon rupture surgery in Finnish and Swedish men during 1997 to 2016. [25] (10.1016/j.jhsa.2020.07.024)
- [L4] Minor complications were common after distal biceps tendon repair; however, most were sensory nerve injuries that resolved with time. [26] (10.1016/j.jhsa.2012.06.022)
- [Case_report] Anatomic reattachment of the distal biceps tendon is a successful operative treatment option. [29] (10.1186/s12891-020-03304-3)
- [L2] This is the largest analysis of complications after distal biceps repair, indicating a major complication rate of 4.6%. [31] (10.1177/0363546519899933)
- [L4] The evidence-based diagnostic algorithm using the combination of the FIT and hook test demonstrates high accuracy for the diagnosis of both complete and high-grade partial distal biceps tendon tears. [33] (10.1016/j.asmr.2021.01.010)
- [L4] [36] (10.1016/j.jse.2017.12.010)
- [L4] Complication rates after distal biceps tendon repair performed by newly trained surgeons were similar to those previously reported in large cohort studies, with nerve injury as the most common complication. [38] (10.1016/j.jse.2022.09.014)
- [L3] Timing significantly impacts surgical technique selection in distal biceps tendon ruptures, with direct repair favored for acute injuries and high flexion angle repair or allograft reconstruction for chronic cases. [39] (10.1016/j.jse.2025.07.027)
- [L4] The finding that distal biceps MRI signal changes consistent with tendinopathy are common even in asymptomatic elbows reduces the probability that symptoms correlate with pathology on imaging. [42] (10.5397/cise.2023.00164)
- [L3] The prevalence of distal biceps tendon signal changes on MRI in asymptomatic patients is very low. [43] (10.1016/j.jhsa.2022.01.020)
- [L5] Nonoperative management does not restore function to the elbow. [45] (10.1007/s11552-013-9551-4)
- [L4] [46] (10.1302/2058-5241.6.200145)
- [Paper] [47] (10.1016/j.injury.2013.01.003)
- [L4] Distal biceps tendon repair surgery can be safely and successfully executed with either a single- or double-incision approach. [48] (10.1016/j.jse.2010.11.009)
- [L4] Athletes sustaining distal biceps tendon rupture have a high postoperative return to sport rate, independently of selected surgical technique or rehabilitation program. [50] (10.1016/j.jse.2022.02.027)
- [L4] [52] (10.1097/00130911-199812000-00005)
- [L4] Surgical repair of the distal biceps insertion reliably regains both supination and flexion strength in appropriate patients. [55] (10.5435/00124635-201003000-00003)
- [L3] WC patients who underwent distal biceps tendon repair took longer to return to work and had worse DASH scores than non-WC patients. [56] (10.1016/j.jse.2012.11.011)
- [L4] [69] (10.1016/s1058-2746(00)90059-4)
- [L1] The results of this meta-analysis showed the superiority of surgical management over the nonoperative approach for distal biceps tendon detachment, with superior flexion and supination strength and better patient-reported outcomes. [73] (10.1177/23259671211037311)
- [L4] Single anterior incision with suture anchor repair may be utilized for repair of ruptures of the distal biceps tendon with good clinical and functional outcomes and minimal loss of range of motion and strength. [80] (10.1097/bco.0000000000000529)
- [L3] O'Driscoll hook test sensitivity is not 100% but remains a useful clinical test to assess patients with suspected distal biceps tendon tears; a negative test does not exclude rupture. [81] (10.1177/1758573219847146)
- [L5] [86] (10.1530/eor-23-0035)
- [L4] Distal biceps tendon ruptures were most commonly observed in weightlifting with a slightly flexed or isometrically extended elbow and forearm supination. [98] (10.1016/j.jse.2023.02.061)
- [L5] Distal biceps repair/reconstruction can restore near-normal flexion and supination strength. [108] (10.1016/j.jhsa.2019.09.014)
- [Paper] Surgical reinsertion of the biceps tendon to the radial tuberosity is considered the treatment of choice for most complete ruptures. [112] (10.1097/bte.0000000000000011)
- [L4] [119] (10.1177/23259671251322700)
- [L5] [120] (10.1016/s1058-2746(05)80044-8)
References
[1] Complications of Distal Biceps Tendon Repair. Orthopaedic Journal of Sports Medicine. 2016. DOI: 10.1177/2325967116668137
[2] Current concepts in the aetiology, assessment and management of partial distal biceps tendon tears. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241245054
[3] Outcomes and complications after different surgical techniques for the treatment of chronic distal biceps tendon ruptures: a systematic review and quantitative synthesis. JSES Reviews, Reports, and Techniques. 2022. DOI: 10.1016/j.xrrt.2022.02.007
[4] Biceps-related complications after tenotomy associated with arthroscopic rotator cuff repair: risk factors and clinical impact. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/2325967121s00362
[5] Determining the incidence and risk factors for short-term complications following distal biceps tendon repair. Clinics in Shoulder and Elbow. 2022. DOI: 10.5397/cise.2021.00472
[6] Surgical Results of Chronic Distal Biceps Ruptures: A Systematic Review. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671211065772
[7] Major complications after distal biceps tendon repairs: retrospective cohort analysis of 970 cases. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2018.06.028
[8] Analysis of 784 surgically treated distal biceps tendon ruptures. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.06.021
[9] The distal biceps deficient arm, “the short arc syndrome”. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.06.020
[10] Outcomes of chronic distal biceps reconstruction with tendon grafting: a matched comparison with primary repair. JSES International. 2021. DOI: 10.1016/j.jseint.2020.10.023
[11] Surgical Treatment of Distal Biceps Tendon Ruptures: An Analysis of Complications in 784 Surgical Repairs. The American Journal of Sports Medicine. 2017. DOI: 10.1177/0363546517720200
[12] Paper #76: All‐Endoscopic Distal Biceps Repair: Cadaveric Portal Safety Analysis and Technical Feasibility Using 2 Fixation Techniques. Arthroscopy. 2017. DOI: 10.1016/j.arthro.2017.08.065
[13] The distal biceps deficient arm, “the short arc syndrome”. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2016.12.053
[14] Factors associated with adverse events after distal biceps tendon repair or reconstruction. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2016.02.032
[15] Bioabsorbable interference screw fixation of distal biceps ruptures through a single anterior incision: a single-surgeon case series and review of the literature. Archives of Orthopaedic and Trauma Surgery. 2009. DOI: 10.1007/s00402-009-0974-x
[16] Thirty-Six Percent Conversion to Surgery Rate for Nonsurgical Treatment of Complete and Partial Distal Biceps Tears. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.12.027
[17] Distal biceps injuries: an overview. Injury. 2025. DOI: 10.1016/j.injury.2025.112556
[18] Chronic Distal Biceps Repair with Tendon Grafting: A Matched Comparison to Primary Repair. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.01.062
[19] Distal biceps short head tears: repair, reconstruction, and systematic review. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.04.038
[20] Re-rupture rate of primarily repaired distal biceps tendon injuries. Journal of Shoulder and Elbow Surgery. 2014. DOI: 10.1016/j.jse.2014.02.006
[22] Distal biceps tendon rupture: Is surgery the best course of treatment? Two case reports. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.03.013
[23] Early Postoperative Complications Following Partial Distal Biceps Tendon Surgical Repair. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.04.012
[24] Distal Biceps Injuries. Clinics in Sports Medicine. 2020. DOI: 10.1016/j.csm.2020.02.004
[25] Distal Biceps Tendon Rupture Surgery: Changing Incidence in Finnish and Swedish Men Between 1997 and 2016. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2020.07.024
[26] Complications Following Distal Biceps Repair. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.06.022
[29] No functional differences in anatomic reconstruction with one vs. two suture anchors after non-simultaneous bilateral distal biceps brachii tendon rupture: a case report and review of the literature. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03304-3
[31] Complications After Distal Biceps Tendon Repair: A Systematic Review. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546519899933
[33] The Flexion Initiation Test and an Evidence‐Based Diagnostic Algorithm for Distal Biceps Tendon Tears. Arthroscopy, Sports Medicine, and Rehabilitation. 2021. DOI: 10.1016/j.asmr.2021.01.010
[34] Green S Operative Hand Surgery. DISTAL BICEPS RUPTURE > Diagnosis.
[36] Is nonoperative management of partial distal biceps tears really successful?. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2017.12.010
[37] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Tendinopathy, Elbow Ligament Reconstruction, and Throwing Injuries > Tendinopathy > Distal Biceps Injury.
[38] Trends and complications of distal biceps tendon repair among American Board of Orthopaedic Surgery part II oral examination candidates. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2022.09.014
[39] Effect of time from injury to surgery on surgical technique and complication rate in distal biceps tendon repair. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.07.027
[40] Green S Operative Hand Surgery. DISTAL BICEPS RUPTURE.
[42] Prevalence of incidental distal biceps signal changes on magnetic resonance imaging. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00164
[43] Evaluation of MRI Signal Changes of the Distal Biceps Tendon in Asymptomatic Patients. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.01.020
[45] Treatment of Chronic Biceps Tendon Ruptures. HAND. 2013. DOI: 10.1007/s11552-013-9551-4
[46] Acute complete and partial distal biceps tendon ruptures: what have we learned? A review. EFORT Open Reviews. 2021. DOI: 10.1302/2058-5241.6.200145
[47] Distal biceps and triceps ruptures. Injury. 2013. DOI: 10.1016/j.injury.2013.01.003
[48] Controversies in the surgical treatment of distal biceps tendon ruptures: single versus double-incision repairs. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.11.009
[50] Systematic review of distal biceps tendon rupture in athletes: treatment and rehabilitation. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.02.027
[52] Single Incision Repair of Distal Biceps Tendon Rupture. Techniques in Hand & Upper Extremity Surgery. 1998. DOI: 10.1097/00130911-199812000-00005
[55] Surgical Treatment of Distal Biceps Rupture. American Academy of Orthopaedic Surgeon. 2010. DOI: 10.5435/00124635-201003000-00003
[56] Outcomes after distal biceps repair in patients with workers' compensation claims. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2012.11.011
[69] Repair of distal biceps brachii tendon ruptures. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1016/s1058-2746(00)90059-4
[73] Operative Versus Nonoperative Management for Distal Biceps Brachii Tendon Lesions: A Systematic Review and Meta-analysis. Orthopaedic Journal of Sports Medicine. 2021. DOI: 10.1177/23259671211037311
[80] Clinical outcomes of single-incision suture anchor repair of distal biceps tendon rupture. Current Orthopaedic Practice. 2017. DOI: 10.1097/bco.0000000000000529
[81] Distal biceps hook test – Sensitivity in acute and chronic tears and ability to predict the need for graft reconstruction. Shoulder & Elbow. 2019. DOI: 10.1177/1758573219847146
[86] Distal biceps tendon rupture: a comprehensive overview. EFORT Open Reviews. 2023. DOI: 10.1530/eor-23-0035
[87] Green S Operative Hand Surgery. AUTHORS’ PREFERRED METHOD OF TREATMENT: PARTIAL BICEPS TEARS.
[98] Distal Biceps Tendon Ruptures Occur With The Almost Extended Elbow And Supinated Forearm – An Online Video Analytic Study. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2023.02.061
[108] Distal Biceps Tendon Repair and Reconstruction. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.09.014
[112] Repair and Rehabilitation of Distal Biceps Ruptures. Techniques in Shoulder & Elbow Surgery. 2014. DOI: 10.1097/bte.0000000000000011
[119] Distal Biceps Tendon Repair in Competitive Strength Athletes: A Retrospective Series of 183 Athletes. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/23259671251322700
[120] The distal biceps tendon. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80044-8