Patients › Hand
கட்டைவிரல் UCL தசைநார்க் காயம் (Thumb UCL injury)
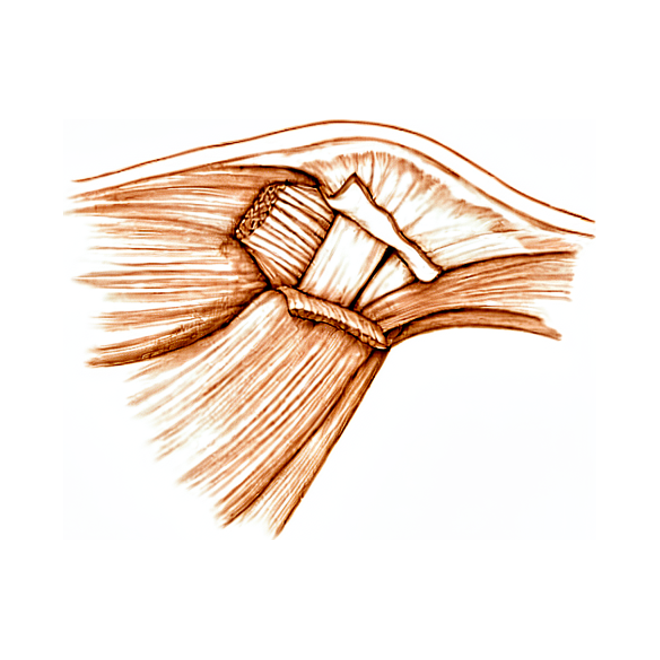
நீங்கள் உணர்வது
கட்டைவிரல் UCL காயம், கட்டைவிரல் கையுடன் இணையும் மூட்டில், உங்கள் கட்டைவிரலின் உள் விளிம்பில் உள்ள தசைநாரைப் (ligament) பாதிக்கிறது. உங்கள் கட்டைவிரல் பக்கவாட்டில் கூர்மையாக வளைக்கப்படும்போது, பெரும்பாலும் நீட்டிய கையின் மீது விழும்போது, இந்தக் காயம் பொதுவாக ஏற்படுகிறது. ஸ்கீயிங்கில் (skiing), ஸ்கீ கம்பைப் பிடித்தபடியே நீங்கள் விழுந்தால் இது ஏற்படலாம்; ஸ்னோபோர்டு (snowboard) விளையாடுபவர்களும் விழுகைகளின்போதும் திருப்பங்களின்போதும் கட்டைவிரலைக் காயப்படுத்திக்கொள்ளலாம்.
வலி உங்கள் கட்டைவிரலின் உள் விளிம்பின் மேல், உள்ளங்கைக்கு மிக அருகில் உள்ள மூட்டில் இருக்கும். இது பொதுவாக ஒரு திடீர்க் காயத்துடன் தொடங்குகிறது; அந்த இடத்தில் வீக்கமும் தொட்டால் வலிக்கும் தன்மையும் சேர்ந்து வரும். கிள்ளுதல், பற்றிப் பிடித்தல், உங்கள் கட்டைவிரலைப் பக்கவாட்டில் தள்ளும் எதுவும் வலிக்கும். கட்டைவிரலின் மேல் இவ்வாறு சுமையை ஏற்றும் அன்றாடப் பணிகள் கடினமாகின்றன: சாவியைத் திருப்புவது, ஜாடியைத் திறப்பது, கனமான வாணலியை அதன் விளிம்பைப் பிடித்துத் தூக்குவது. உங்கள் கட்டைவிரல் நிலையற்றதாகவும் உணரலாம் — எதன் மேலாவது அதை அழுத்தும்போது அது விட்டுக்கொடுத்துவிடும் என்பது போல.
கட்டைவிரல் மூட்டின் உள் விளிம்பில் ஒரு சிறிய, திடமான கட்டி இருப்பதைச் சிலர் கவனிக்கிறார்கள். மற்றக் கட்டைவிரலோடு ஒப்பிடும்போது, உங்கள் கட்டைவிரல் சற்றே நேர்கோட்டிலிருந்து விலகியோ திருகியோ அமர்ந்திருக்கலாம். காயம் சில காலத்துக்கு முன்பு ஏற்பட்டிருந்தால், வலி அவ்வளவு வெளிப்படையாக இல்லாமல் இருக்கலாம்; ஆனால் நீங்கள் கிள்ளும்போதோ பற்றும்போதோ கட்டைவிரல் இன்னும் பலவீனமாகவோ தளர்வாகவோ உணரப்படலாம்.
இந்த அறிகுறிகளைக் கவனித்து, அதே நாளிலேயே நடவடிக்கை எடுங்கள்: சூடாகவும், சிவந்தும், வீங்கியும், வலியுடனும் மாறும் விரல், கை அல்லது புஜம், குறிப்பாகக் காய்ச்சலுடன் இருந்தால்; காயமடைந்த மூட்டின் மேல் தோல் கிழிந்திருத்தல், எலும்பு வெளியே தெரிதல், அல்லது வெளிப்படையான உருக்குலைவு; வெளிறியோ, குளிர்ந்தோ, வெள்ளையாகவோ, நீலமாகவோ மாறும் கட்டைவிரல் அல்லது கை; அல்லது காயத்துக்குப் பிறகு திடீரென உணர்ச்சியோ அசைவோ இழக்கப்படுதல். இவற்றுக்கு உடனடியாக அவசர சிகிச்சைப் பிரிவில் சிகிச்சை தேவை; அதற்கு GP பரிந்துரைக் கடிதம் (referral) தேவையில்லை.
உங்கள் அறிகுறிகள் தணியாவிட்டால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களை எழுப்பினால், அல்லது வேலை செய்வதையோ உங்கள் கையைப் பயன்படுத்துவதையோ தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
உண்மையில் என்ன நடக்கிறது
உங்கள் கட்டைவிரலின் உள் விளிம்பில், அது கையுடன் இணையும் இடத்தில், அல்நார் கொலேட்டரல் தசைநார் (ulnar collateral ligament) எனப்படும் உறுதியான தசைநார்ப் பட்டை ஒன்று உள்ளது. கூடாரக் கம்பத்தை நிலையாகப் பிடித்து வைக்கும் இழுவைக் கயிறு போல அதை நினைத்துக்கொள்ளுங்கள்: நீங்கள் கிள்ளும்போதோ பற்றும்போதோ கட்டைவிரல் மூட்டு பக்கவாட்டில் வளையாமல் அது தடுக்கிறது. உங்கள் கட்டைவிரலை ஒரு விரலுக்கு எதிராக அழுத்தும் ஒவ்வொரு முறையும், இந்தப் பட்டையே சுமையைத் தாங்குகிறது. அதனால்தான் இங்கே ஏற்படும் கிழிவு, சரியாக அந்தப் பணிகளிலேயே பலவீனமாகவும் வலியாகவும் வெளிப்படுகிறது.
உங்கள் கட்டைவிரல் வலுக்கட்டாயமாகப் பக்கவாட்டில் தள்ளப்படும்போது, இந்தப் பட்டை நீளலாம், ஓரளவு கிழியலாம், அல்லது முழுவதுமாகக் கிழியலாம். அது எவ்வளவு கிழிந்துள்ளது என்பதைக் கொண்டு மருத்துவர்கள் அதைப் படிநிலைப்படுத்துகிறார்கள் (grade): நீட்சி அல்லது பகுதிக் கிழிவு, மற்றும் தசைநார் எலும்பிலிருந்து பிரிந்துவிடும் முழுமையான கிழிவு. சில சமயங்களில் தசைநார் ஒரு சிறிய எலும்புத் துண்டுடன் சேர்ந்து எலும்பிலிருந்து கிழிந்து வருகிறது. பகுதிக் கிழிவு பொதுவாக ஒரு ஸ்பிளிண்டில் (splint) குணமடையலாம். முழுமையான கிழிவு பெரும்பாலும் குணமடைவதில்லை; ஏனெனில் கிழிந்த முனை பின்னோக்கி மடங்கி, மூட்டின் மேல் அமைந்துள்ள ஒரு திசு மடிப்பின் கீழ் சிக்கிக்கொள்ளலாம். அப்படி நிகழ்ந்தவுடன், தசைநார் மீண்டும் ஒட்ட வேண்டிய எலும்பிலிருந்து விலகியே கிடக்கிறது; அதனால் அது தானாக மீண்டும் ஒன்றுசேர முடியாது.
கிழிவுக்குச் சிகிச்சை அளிக்கப்படாவிட்டால், மூட்டு தளர்வாகவே இருக்கும். பக்கவாட்டுச் சுமையின் கீழ் உங்கள் கட்டைவிரல் தொடர்ந்து விட்டுக்கொடுக்கும்; ஆண்டுகள் செல்லச் செல்ல, அந்தத் தொடர்ச்சியான அசைவு மூட்டைத் தேய்த்து, மூட்டழற்சிக்கு (arthritis) வழிவகுக்கலாம். அதனால்தான், ஒரு சாதாரணச் சுளுக்கு போல உணரப்பட்டாலும், இந்தக் காயம் தீவிரமாக எடுத்துக்கொள்ளப்படுகிறது.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்களுடைய குறிப்பிட்ட காயத்திற்கேற்பச் சிகிச்சையைப் பொருத்துகிறார். சில கட்டைவிரல் தசைநார்க் கிழிவுகள் அறுவை சிகிச்சை இல்லாமலேயே குணமடைகின்றன; மற்றவற்றுக்கு விரைவிலேயே அறுவை சிகிச்சை தேவைப்படுகிறது; எனவே உடனடி மதிப்பீடு முக்கியம். நோயாளிகள் பொதுவாக அவர்களுடைய GP (பொது மருத்துவர்) மூலம் எங்கள் கிளினிக்கிற்குப் பரிந்துரைக்கப்படுகின்றனர்; ஒரு இயன்முறை சிகிச்சையாளர் (physiotherapist) எங்களைப் பார்க்கும்படி பரிந்துரைத்திருந்தாலும், Medicare தள்ளுபடியைப் (rebate) பெறத் தகுதி பெற உங்கள் GP-யிடமிருந்து பரிந்துரைக் கடிதம் (referral) இன்னும் தேவைப்படும். கிளினிக்கில், நாங்கள் உங்கள் மருத்துவ வரலாற்றைக் கேட்டறிந்து, உங்கள் கட்டைவிரலைப் பரிசோதித்து, தேவைப்படும் இடங்களில் ஸ்கேன்களுக்கு (imaging) ஏற்பாடு செய்கிறோம். அவற்றில் எக்ஸ்-ரே, அல்ட்ராசவுண்ட் ஸ்கேன், அல்லது MRI ஆகியவை அடங்கலாம்; MRI ஒரு சக்திவாய்ந்த காந்தத்தைப் பயன்படுத்தித் தசைநாரின் விரிவான படங்களை எடுக்கிறது. தசைநார் முழுவதுமாகக் கிழிந்துள்ளதா, கிழிந்த முனை இடம்பெயர்ந்து மடங்கியுள்ளதா என்பதை இந்த ஸ்கேன்கள் காட்டுகின்றன.
கிழிவு பகுதியானதாக இருந்தால், அல்லது தசைநார் இடம்பெயராத ஒரு சிறிய எலும்புத் துண்டுடன் எலும்பிலிருந்து பிரிந்திருந்தால், நாங்கள் பொதுவாக 4 வாரங்கள் வரை கட்டைவிரலை ஒரு கட்டில் (cast) அசையாமல் பிடித்து வைக்கிறோம். அதன் பிறகு, மேலும் 3 வாரங்களுக்குக் கழற்றக்கூடிய ஒரு ஸ்பிளிண்டை அணிந்து, மென்மையான அசைவுப் பயிற்சிகளைத் தொடங்குவீர்கள். Extend Rehabilitation-இல் உள்ள உங்கள் கை சிகிச்சையாளர் (hand therapist) Ruby Doolan இந்தப் பயிற்சிகளை வழிநடத்தி, உங்களுக்குத் தேவைப்படும் எந்த ஸ்பிளிண்டையும் செய்து தருவார். கிழிந்த முனை இடம்பெயர்ந்து மடங்காத முழுமையான கிழிவுக்கு, பொதுவாக முதலில் அசையாமல் வைக்கும் சிகிச்சை முயற்சிக்கப்படுகிறது: தசைநார் மீண்டும் ஒன்றுசேர வாய்ப்பளிக்க, மூட்டு 4 முதல் 6 வாரங்களுக்கு அசையாமல் பிடித்து வைக்கப்படுகிறது.
கிழிவு முழுமையானதாகவும் நிலையற்றதாகவும் இருக்கும்போது, கிழிந்த தசைநார் முனை இடம்பெயர்ந்து மடங்கியிருக்கும்போது, அல்லது ஒரு எலும்புத் துண்டு நேர்கோட்டிலிருந்து விலகியிருக்கும்போது அறுவை சிகிச்சை பரிசீலிக்கப்படுகிறது. இந்தச் சூழல்களில் தசைநார் தானாக மீண்டும் எலும்போடு குணமடைய முடியாது; எனவே ஒரு அறுவை சிகிச்சை அதை மீண்டும் இணைக்கிறது. காயம் சில காலத்துக்கு முன்பு ஏற்பட்டு, தசைநாரை இனி நேரடியாகச் சரிசெய்ய முடியாவிட்டால், உங்கள் சொந்தப் புஜத்திலிருந்து (arm) எடுக்கப்படும் ஒரு தசைநாண் துண்டைப் (strip of tendon) பயன்படுத்தியோ, தானமாகப் பெறப்பட்ட திசுவைப் பயன்படுத்தியோ அதை மீண்டும் கட்டியமைக்க முடியும். இந்த அறுவை சிகிச்சைக்கென்று தனிப் பக்கம் உள்ளது; நீங்கள் எதையும் முடிவு செய்வதற்கு முன், அதில் என்ன செய்யப்படுகிறது என்பதை நாம் சேர்ந்து பேசுவோம்.
என்ன எதிர்பார்க்கலாம்
சிகிச்சை அளிக்கப்படும்போது, பெரும்பாலான கட்டைவிரல் தசைநார்க் கிழிவுகள் நன்றாகச் சரியாகின்றன. ஸ்பிளிண்டிலோ கட்டிலோ அசையாமல் பிடித்து வைக்கப்படும் பகுதிக் கிழிவு பொதுவாகக் குணமடைகிறது; கிள்ளுவதற்கும் பற்றிப் பிடிப்பதற்குமான வலிமையை உங்கள் கட்டைவிரல் மீண்டும் பெறுகிறது. உங்களுக்கு அறுவை சிகிச்சை தேவைப்பட்டால், முடிவுகள் பொதுவாக நன்றாக இருக்கின்றன: பெரும்பாலானோர் தங்கள் கட்டைவிரலின் அசைவையும், கிள்ளும் வலிமையையும், பற்றும் வலிமையையும் தக்கவைத்துக்கொள்கிறார்கள்; அறுவை சிகிச்சைக்குப் பிறகான பிரச்சினைகள் அரிது. இந்த அறுவை சிகிச்சையைச் செய்துகொண்டவர்கள் தங்கள் முந்தைய நிலையிலேயே மீண்டும் விளையாட்டில் ஈடுபட்டுள்ளனர்; தொழில்முறை வீரர்கள் அதன் பிறகு இணையான எண்ணிக்கையிலான ஆட்டங்களில் விளையாடி, இணையான கால அளவு விளையாட்டு வாழ்க்கையையும் கொண்டிருந்தார்கள்.
மீட்சிக்குப் பொறுமை தேவை. முதலில் உங்கள் கட்டைவிரல் அசையாமல் பிடித்து வைக்கப்படும்; ஏனெனில் பின்னாளில் தவிர்க்க வேண்டிய முக்கியமான விஷயம் ஆரம்பகால விறைப்புதான். அசைவு அனுமதிக்கப்பட்டவுடன், மென்மையான, படிப்படியான பயிற்சிகள் முக்கியம்: குணமடையும் தசைநாரின் மேல் மெதுவாகச் சுமையை ஏற்றி நீட்டுவது அசைவையும் செயல்பாட்டையும் மேம்படுத்துகிறது. நோயாளிகள் தாங்களே தெரிவிக்கும் முடிவுகள், அறுவை சிகிச்சைக்கு முன்பு இருந்ததோடு ஒப்பிடும்போது, அறுவை சிகிச்சைக்குப் பிறகு மூன்று மற்றும் 12 மாதங்களில் குறிப்பிடத்தக்க அளவில் மேம்படுகின்றன. உங்கள் காயம் சில காலத்துக்கு முன்பு ஏற்பட்டிருந்தாலும், சரிசெய்தல் இன்னும் பலனளிக்கிறது; இருப்பினும், ஆரம்பத்திலேயே சரிசெய்திருந்தால் இருந்ததைவிட, தாமதமாகச் சரிசெய்வதில் கட்டைவிரல் அசைவில் சற்று அதிகமாக இழக்க நேரிடும் போக்கு உள்ளது.
சிகிச்சை இல்லாவிட்டால், எதிர்காலம் வேறுபட்டது. ஓய்வு கொடுத்தாலும்கூட, நான்கில் மூன்று முழுமையான கிழிவுகள் தாமாகக் குணமடைவதில்லை. மூட்டு தளர்வாகவே இருக்கும், சுமையின் கீழ் உங்கள் கட்டைவிரல் தொடர்ந்து விட்டுக்கொடுக்கும், கிள்ளுதல் பலவீனமாகவும் வலியுடனும் இருக்கும். ஆண்டுகள் செல்லச் செல்ல, அந்தத் தொடர்ச்சியான தளர்வு மூட்டைத் தேய்த்துவிடுகிறது: நாள்பட்ட கிழிவைப் பின்னர் சரிசெய்துகொண்டவர்களில் 88% பேருக்கு, கட்டைவிரல் மூட்டில் ஏற்கெனவே ஓரளவு மூட்டழற்சி இருந்தது. காயம் ஏற்படும்போது வயது அதிகமாக இருப்பது, அந்த மூட்டில் அதிகக் கடுமையான மூட்டழற்சியுடன் தொடர்புடையது.
முன்கூட்டியே திட்டமிடும்போது சில விஷயங்களைத் தெரிந்துகொள்வது நல்லது. உங்கள் கட்டைவிரல் சூடாகவும், சிவந்தும், வீங்கியும், வலியுடனும் மாறினால், குறிப்பாகக் காய்ச்சலுடன் இருந்தால், அதே நாளிலேயே அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்; GP பரிந்துரைக் கடிதம் தேவையில்லை. அறிகுறிகள் தணியாவிட்டால் அல்லது வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
உங்கள் கட்டைவிரல் வலுக்கட்டாயமாகப் பக்கவாட்டில் தள்ளப்படும் எந்தக் காயத்துக்குப் பிறகும், அது ஒரு சாதாரணச் சுளுக்கு போலத் தோன்றினாலும், விரைவில் அதைப் பரிசோதித்துக்கொள்ளுங்கள். முழுமையான கிழிவு எவ்வளவு விரைவில் மதிப்பீடு செய்யப்படுகிறதோ, அவ்வளவு அதிகமான தேர்வுகள் உங்களுக்குக் கிடைக்கும்; ஏனெனில் நீண்ட காலம் விடப்பட்ட கிழிவுக்குப் பெரிய அறுவை சிகிச்சை தேவைப்படலாம், அல்லது அது நீடித்த விறைப்பையும் பலவீனத்தையும் விட்டுச்செல்லலாம். நீங்கள் கிள்ளும்போதோ பற்றும்போதோ உங்கள் கட்டைவிரல் இன்னும் விட்டுக்கொடுத்தால், சில வாரங்களுக்குப் பிறகும் கிள்ளுதல் பலவீனமாகவோ வலியுடனோ இருந்தால், அல்லது மூட்டின் உள் விளிம்பில் ஒரு சிறிய திடமான கட்டியை உணர முடிந்தால், நிபுணரின் பரிசோதனையைக் கேளுங்கள். காயம் சில காலத்துக்கு முன்பு ஏற்பட்டு, உங்கள் கட்டைவிரல் தளர்வாகவோ தேய்மானம் அடைந்துகொண்டோ இருந்தால், அதை மதிப்பீடு செய்துகொள்வது இன்னும் பயனுள்ளதே. மேலும், உங்கள் கட்டைவிரல் சூடாகவும், சிவந்தும், வீங்கியும், வலியுடனும் மாறினால், குறிப்பாகக் காய்ச்சலுடன் இருந்தால், அதே நாளிலேயே அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
இந்தப் பிரிவு, உங்களுடைய சொந்தச் சிகிச்சை முடிவுகளுக்குத் தேவைப்படுவதைவிட ஆழமாகச் செல்கிறது. கட்டைவிரலின் அல்நார் கொலேட்டரல் தசைநார்க் காயம் இந்தக் கூடுதல் வாசிப்புக்குத் தகுதியானது; ஏனெனில் முடிவு முழுவதும் ஒரே ஓர் உடற்கூற்று வினாவைச் சார்ந்தே அமைகிறது — கிழிந்த தசைநார் எட்ட முடியாத இடத்திற்குப் புரண்டு போய்விட்டதா என்பதே அது; மேலும், அதைத் தீர்மானிக்க எந்த ஸ்கேனைப் பயன்படுத்துவது என்பதற்கு இப்போது தெளிவான பதில் இருக்கிறது.
ஸ்டெனர் காயம், அது ஏன் எல்லாவற்றையும் மாற்றுகிறது
ஒவ்வொரு கிள்ளுதலிலும் பற்றுதலிலும் ஏற்படும் பக்கவாட்டு விசைக்கு எதிராக அல்நார் கொலேட்டரல் தசைநார் கட்டைவிரலை நிலைப்படுத்துகிறது. அது தான் ஒட்டியிருக்கும் இடத்திலிருந்து கிழியும்போது, வழக்கமாக அது குணமடையக்கூடிய இடத்திலேயே இருக்கிறது.
சில சமயங்களில் அப்படி இருப்பதில்லை. அடக்டர் அபோனியூரோசிஸ் (adductor aponeurosis) எனப்படும் ஒரு தசைநாண் தகடு தசைநாருக்கு மேற்புறமாக அமைந்திருக்கிறது; கிழிந்த முனை அந்தத் தகட்டின் மேற்பக்கமாகப் பின்னோக்கிச் சுருங்கி விலகினால், அபோனியூரோசிஸ் தசைநாருக்கும் எலும்புக்கும் இடையில் வந்து நிற்கிறது. அதுவே ஒரு ஸ்டெனர் காயம் (Stener lesion); பெரும்பாலான சுளுக்குகளிலிருந்து வேறுபட்ட முறையில் இந்தக் காயம் சிகிச்சையளிக்கப்படுவதற்கு அதுவே காரணம்: தசைநார், தான் குணமடைந்து ஒட்ட வேண்டிய எலும்போடு இனி தொடர்பில் இல்லை; எனவே எவ்வளவு காலம் ஸ்பிளிண்ட் அணிந்தாலும் அது மீண்டும் ஒட்டிக்கொள்ளாது.
அது நிகழ்ந்திருக்கிறதா இல்லையா என்பதிலிருந்தே சிகிச்சை பற்றிய அனைத்தும் தீர்மானிக்கப்படுகிறது.
இதற்குப் பதிலளிக்க அல்ட்ராசவுண்டே போதும்
முடிவு இரண்டில் ஒன்றாகவும் விளைவு மிக்கதாகவும் இருப்பதால், ஸ்கேன் தொடர்பான வினா வழக்கத்திற்கு மாறாகத் தெளிவாக வரையறுக்கப்பட்டுள்ளது — அதற்குப் பதிலும் கிடைத்துவிட்டது. 422 நோயாளிகளைக் கொண்ட ஆய்வுகளில், ஸ்டெனர் காயங்களைக் கண்டறிவதில் அல்ட்ராசவுண்ட் மற்றும் MRI ஆகிய இரண்டுமே உயர்ந்த நோயறிதல் துல்லியத்தைக் காட்டுகின்றன, மேலும் அல்ட்ராசவுண்ட் முதல்-நிலை ஸ்கேன் முறையாகப் பொருத்தமானது [1].
இது நடைமுறையில் பயனுள்ள ஒரு தகவல். MRI-ஐவிட அல்ட்ராசவுண்ட் விரைவானது, செலவு குறைவானது, எளிதில் கிடைக்கக்கூடியது; அனுபவம் வாய்ந்த ஒருவர் அதைச் செய்யும் இடத்தில், அது ஏற்கெனவே காட்டியதை உறுதிப்படுத்த அதைத் தொடர்ந்து MRI செய்ய வேண்டிய அவசியம் இல்லை. அது இயங்குநிலைப் பரிசோதனையும் கூட — ஸ்கேன் செய்யும்போதே கட்டைவிரலுக்கு அழுத்தம் கொடுத்துப் பார்க்க முடியும்.
ஸ்டெனர் காயம் இல்லாத இடத்தில், மூட்டுத் தளர்ச்சியே முடிவைத் தீர்மானிக்கிறது
The British Society for Surgery of the Hand-இன் வழிகாட்டு நெறிமுறை இந்தப் பாதையைத் தெளிவாக வகுத்துச் சொல்கிறது. திடீர்க் காயங்கள் உள்ள நோயாளிகள் மருத்துவ வரலாறு, மருத்துவப் பரிசோதனை மற்றும் எக்ஸ்-ரே படங்கள் மூலம் மதிப்பிடப்பட வேண்டும். குறிப்பிடத்தக்க மூட்டுத் தளர்ச்சி இல்லாதவர்களுக்கு அறுவை சிகிச்சை இல்லாமல் சிகிச்சை அளிக்க முடியும்; குறிப்பிடத்தக்க தளர்ச்சி உள்ளவர்களுக்கு, பகிர்ந்த முடிவெடுத்தலுக்குப் பிறகு, அறுவை சிகிச்சை அல்லாத அசைவின்மைச் சிகிச்சை அல்லது அறுவை சிகிச்சை மூலம் சரிசெய்தல் ஆகிய இரண்டில் ஏதேனும் ஒன்றால் சிகிச்சை அளிக்கப்படலாம் [2].
இரண்டு விஷயங்களைத் தனியே சுட்டிக்காட்ட வேண்டும். முதலாவது, மேம்பட்ட ஸ்கேன்களுக்கு முன்பு எக்ஸ்-ரே படங்கள் வருகின்றன; ஓரளவு அது பிடுங்கல் எலும்பு முறிவை (avulsion fracture) விலக்கிப் பார்ப்பதற்காக — அது மீண்டும் சிகிச்சையை மாற்றுகிறது. இரண்டாவது, குறிப்பிடத்தக்க தளர்ச்சி இருந்தாலும்கூட அது அறுவை சிகிச்சையைக் கட்டாயமாக்குவதில்லை: அசைவின்மைச் சிகிச்சைக்கும் சரிசெய்யும் அறுவை சிகிச்சைக்கும் இடையிலான ஒரு பகிர்ந்த முடிவாகவே வழிகாட்டு நெறிமுறை அதை வெளிப்படையாக வைக்கிறது; அறுவை சிகிச்சையை ஒரே வழியாகக் காட்டுவதைவிட இது நேர்மையான நிலைப்பாடு.
அதைத் தவறாகக் கணித்தால் ஏற்படும் விளைவுகள் ஏன் குறிப்பிட்டவையாக இருக்கின்றன
செயலிழந்த அல்நார் கொலேட்டரல் தசைநார், ஓய்வில் இருக்கும்போது வலியையோ பெரும்பாலான செயல்களில் சிரமத்தையோ ஏற்படுத்துவதில்லை. அது ஏற்படுத்துவது, பக்கவாட்டுச் சுமையின் கீழ் விட்டுக்கொடுக்கும் ஒரு கட்டைவிரலை — சாவியைத் திருப்புவது, ஜாடியைத் திறப்பது, கனமான பாத்திரத்தை அதன் விளிம்பைப் பிடித்துத் தூக்குவது; ஏனெனில் கிள்ளுதல், அழுத்திக்கொள்வதற்கு ஓர் உறுதியான தூணைச் சார்ந்திருக்கிறது.
சிகிச்சை அளிக்கப்படாமல் விடப்பட்டால், நாள்பட்ட நிலையின்மை ஆண்டுகள் செல்லச் செல்ல அந்த மூட்டில் மூட்டழற்சிக்கு வழிவகுக்கிறது. ஒரு சாதாரண சுளுக்கு போலத் தோன்றும் ஒரு காயத்திற்கு உறுதியான மதிப்பீடு தேவைப்படுவதற்கு இதுவே காரணம்: அதைத் தவறவிட்டதன் விலை, கட்டைவிரல் அமைதியடைந்து நன்றாக இருப்பது போலத் தோன்றும் அடுத்த சில வாரங்களில் உணரப்படுவதில்லை; மிகவும் பிற்பாடுதான் உணரப்படுகிறது.
மேற்கோள்கள்
[1] Qamhawi Z, Shah K, Kiernan G, Furniss D, Teh J, Azzopardi C. Diagnostic accuracy of ultrasound and magnetic resonance imaging in detecting Stener lesions of the thumb: systematic review and meta-analysis. J Hand Surg Eur Vol. 2021;46(9):946-53. https://doi.org/10.1177/1753193421993015
[2] Dean B, Rodrigues J, Riley N, Rabey N, Donnison E, Challen K, et al. Guideline on managing thumb ulnar collateral ligament injuries: the British Society for Surgery of the Hand. J Hand Surg Eur Vol. 2024;49(10):1195-201. https://doi.org/10.1177/17531934241274612
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Diagnosis and Imaging
- Ultrasonography has evolved as a reliable adjunct to clinical examination in the evaluation of the ulnar collateral ligament (UCL) of the thumb [1].
- MRI evaluation reveals greater details enabling better understanding and management of ulnar collateral ligament injuries of the thumb metacarpophalangeal (MCP) joint [2].
- A 4-stage, treatment-oriented classification of thumb UCL injury is based on the degree of UCL displacement, with correlation with the likelihood of success with either immobilization or operative intervention [10].
- The presence of a displaced fleck sign has implications for offering surgery to patients with thumb UCL injuries because of a high likelihood of a Stener lesion [17].
Clinical Indications and Natural History
- Valgus laxity greater than 30 degrees or more than 15 degrees more than in the noninjured thumb with the MCP joint in extension is an indication for operative management [3].
- Untreated ulnar collateral ligament injury of the thumb metacarpophalangeal joint can lead to long-term pain and functional limitations [5].
- 75% of cases with complete rupture of the ulnar collateral ligament of the thumb will fail to heal with conservative treatment [13].
- The rate of surgery for acute thumb MP UCL injury varies based on patient characteristics and the individual treating surgeon [6].
Treatment Outcomes
- Surgical management of thumb UCL injuries produces overall favorable results [4].
- Patient-reported outcomes improve significantly at three and 12 months after open surgical repair of the thumb UCL compared to baseline [24].
- Patients with both acute and chronic thumb UCL injuries have similarly acceptable functional outcomes, postoperative pain, and satisfaction [11].
- Return-to-play rates after surgical treatment of thumb UCL injuries are high, with reassuring return to preinjury level of play with few complications [9].
- Thumb ulnar collateral ligament injuries can be safely and effectively managed by football position demands [14].
- Players who underwent thumb UCL repair played in a similar number of games per season and had similar career lengths in the MLB as controls [16].
- Treatment of a thumb UCL complete rupture (Grade III) using a custom-made hinged splint shows promise in the conservative management of compliant patients [19].
Surgical Techniques and Rehabilitation
- A controlled active motion therapy protocol after suture anchor repair of a ruptured UCL of the thumb is safe from a biomechanical point of view [8].
- Intraosseous suture anchor repair is a safe and effective method for repair of complete tears of the ulnar collateral ligament of the thumb MP joint [12].
- Both pull-out sutures and bone anchor techniques are safe and effective for treating thumb ulnar collateral ligament injuries [23].
- Thumb UCL repair with suture tape augmentation demonstrates short-term outcomes comparable to what has been reported for other methods of repair [26].
- Mini hook plate fixation could be an alternative treatment technique for thumb UCL avulsion fractures [21].
- The surgical treatment of an ulnar collateral ligament lesion of the thumb using the Fiji Anchor can lead to an excellent clinical outcome with a minor complication rate [48].
- An accelerated rehabilitation protocol has been clinically applied in athletes following thumb MCP UCL repair with suture tape augmentation [22].
- The patient is placed in the supine position with a small bump on which to rest the thumb for open repair of the UCL [28].
- The surgeon should position themselves between the shoulder and head to allow easier access to the ulnar aspect of the thumb during UCL repair [28].
- A lazy S approach is used on the ulnar aspect of the thumb for UCL repair [28].
- Careful identification of the radial sensory nerve is required during UCL repair, with prior documentation of sensibility [28].
- The adductor aponeurosis is incised on the ulnar side during UCL repair [28].
- The site of rupture for the UCL is identified as distal off the phalanx, midsubstance, or proximal [28].
- Nonabsorbable suture with pullout button, bone anchors, or figure-of-eight imbrication of midsubstance repair are options for repairing the UCL [28].
- Motion is limited for the first 4 to 6 weeks depending on chronicity of the injury, with more chronic injuries immobilized longer [28].
- Guided therapy at 6 weeks in a removable splint is part of the postoperative protocol for UCL repair [28].
Anatomy & Pathophysiology
Bony Anatomy and Joint Mechanics
- The thumb metacarpophalangeal (MCP) articulation is of a condylar type [52].
- Flexion of the thumb MCP joint is always accompanied by radial deviation and pronation, which stretches the ulnar metacarpophalangeal ligament [52].
- The stability of the thumb MCP joint is considered more important than movement from a functional viewpoint [52].
- The carpometacarpal ray of the thumb is anterior to the plane of the other metacarpals and makes an angle of about 47 degrees with the second ray [52].
- The distal articular surface of the trapezium is likened to a saddle whose concave curvature lies in a dorsopalmar direction [52].
- The corresponding surface on the base of the first metacarpal presents a grooved surface in the radioulnar direction [52].
- The trapeziometacarpal joint has two longitudinal axes and two degrees of freedom [52].
- The shape of the trapeziometacarpal articular surface does not make for good stability except in anteposition and pronation when the two surfaces are congruent [52].
- The necessary stability of the trapeziometacarpal joint is provided by a complex ligamentous system which does not limit mobility [52].
- This ligamentous system essentially consists of a strong ulnar ligament from the base of the first metacarpal to the second metacarpal and to the trapezoid [52].
- The ulnar ligament of the trapeziometacarpal joint is the structure that resists in a Bennett fracture [52].
- The radial side of the trapeziometacarpal joint has a much weaker ligament [52].
- There is an intrinsic instability at the level of the trapeziometacarpal joint where the pressure is very high [52].
- This pressure is proportional to the force of the grip at the distal end of the thumb and to the length of the lever arm [52].
- Cooney and Chao (1977) found that joint compression forces during simple pinch averaged 3.0 kg of force at the interphalangeal joint, 5.4 kg at the metacarpophalangeal joint, and 12.0 kg at the carpometacarpal joint [52].
- Compression forces of up to 120 kg may occur at the carpometacarpal joint during strong grasp [52].
- Stability of the trapeziometacarpal joint is dynamically provided by a single structure, the tendon of the abductor pollicis longus [52].
- The abductor pollicis longus tendon has stabilizing function only when the first metacarpal is abducted [52].
- In adduction, the long abductor increases the risk of subluxation of the trapeziometacarpal joint [52].
Ligamentous Anatomy and Injury Patterns
- The ulnar collateral ligament (UCL) serves as the primary stabilizer against valgus stress at the thumb MCP joint [20].
- The UCL plays an essential role in pinch strength, grasping function, and dexterity [20].
- The mechanism of injury to the UCL is sudden, forced radial deviation (abduction), often resulting from a fall on an outstretched hand with the thumb abducted [44].
- In skiing, if a person falls while gripping the ski pole, the handle abducts the thumb [44].
- Associated injuries to UCL tears include tears of the dorsal capsule and ulnar aspect of the volar plate [44].
- Associated injuries to UCL tears occasionally include a rent in the adductor aponeurosis [44].
- Volar subluxation of the MCP joint may result from concomitant tears of the dorsal capsule and UCL [44].
- Distal tears of the UCL at its insertion in the proximal phalangeal base are more common than proximal tears from the metacarpal [44].
- Ruptures within the substance of the ligament occasionally occur [44].
- The collateral ligaments of the thumb MP joint afford lateral stability and resist volar subluxation [44].
- If one collateral ligament is torn, the proximal phalanx tends to rotate volarly on the side of the tear, with the opposite intact ligament serving as the axis [44].
- In the case of an isolated UCL rupture, the proximal phalanx rotates in supination around the intact radial collateral ligament [44].
- An avulsion fracture of the ulnar base of the proximal phalanx at the insertion of the ligament is the most common fracture pattern associated with UCL injuries [44].
- Typically, the avulsion fracture fragment is small and includes little of the articular surface [44].
- Fractures involving more than 10% of the articular surface can occur and may require fixation if they are displaced 2 mm or more and associated with articular incongruity [44].
- Avulsion fractures from the metacarpal head and intraarticular shearing fractures of the volar surface of the radial condyle of the metacarpal head have also been reported [44].
- A rare but potentially problematic fracture pattern involves a rupture of the UCL from the proximal phalanx and a simultaneous articular shear fracture of the proximal phalangeal base [44].
- In the skeletally immature individual, isolated rupture of the UCL without a Salter fracture of the proximal phalanx is rare but does occur [44].
- The UCL ruptures off the base of the proximal phalanx [62].
- The avulsed ligament, with or without a bony fragment, can become displaced above the adductor aponeurosis, preventing healing [62].
- This displacement is known as a Stener lesion [62].
- In 25 of 39 patients with complete ruptures of the UCL, Stener found the adductor aponeurosis interposed between the ruptured ulnar collateral ligament and its site of insertion on the base of the proximal phalanx [47].
- On clinical examination, a prominent lump can be palpated that represents the ulnar collateral ligament being proximally and superficially displaced by the adductor aponeurosis [47].
- Pathologic rotation of the thumb may be evident in Stener lesions [47].
- If left uncorrected, a Stener lesion prevents proper healing and leads to chronic instability and subsequent arthrosis [47].
- Other injuries associated with tears of the UCL include avulsion fractures, dorsal capsular tears, and volar plate tears [47].
- The adductor aponeurosis interposition prevents direct ligament healing without surgery [42].
- The UCL is typically avulsed distally [35].
- Although the injury is often at the distal portion where it attaches to the proximal volar aspect of the phalanx, midsubstance and metacarpal-based tears can occur [35].
- The anatomic attachment site for a distal avulsion of the UCL is 25% dorsal from the volar surface of the proximal phalanx [94].
- A single anchor is placed volar to the axis of the joint for distal avulsion repair [94].
- The radial collateral ligament (RCL) ruptures from its origin, from its insertion, or at the midsubstance [62].
- RCL ruptures are frequently associated with dorsal or dorsoradial capsular tears and with extensor pollicis brevis avulsions or tears [62].
- No equivalent of the Stener lesion exists for the RCL [62].
- RCL ruptures seem susceptible to chronic instability [62].
- The radial-based abductor cannot create a Stener-type lesion [63].
Pathophysiology and Biomechanics
- Sequential tearing of the thumb UCL leads to progressive instability of the MCP joint [7].
- Untreated complete ruptures may result in chronic instability, weakness of pinch, pain, and functional impairment [20].
- Causes of chronic instability of the UCL include an untreated acute tear, failure to recognize a Stener lesion, or progressive attenuation of the ligament [100].
- Patients with chronic instability usually present with pain, swelling, and weakness of the involved thumb [100].
- The pain tends to be exacerbated by forceful pinch and activities requiring torsional motions of the hand, such as unscrewing jar tops [100].
- Holding large objects like a half-gallon container of milk may be painful and may cause a feeling of instability or lack of power because of the thumb’s inability to resist counterpressure [100].
- Chronic instability is manifested by gross instability to valgus stress with no endpoint [100].
- Crepitus with active motion suggests degenerative disease in chronic UCL instability [100].
- The resting posture of the thumb should be observed for volar subluxation or radial deviation of the MP joint in chronic instability [100].
- Biomechanically, there are no treatments of repair or reconstruction using native tissues that provide equivalent strength to the preinjured ligament [105].
- No static ligament reconstruction restores the normal stability characteristics of the thumb UCL [15].
- Single- and double-bundle UCL reconstructions of the thumb MCP joint have comparable biomechanical properties in regard to joint congruity under valgus load [40].
- The reconstruction tunnel positioning of triangular configuration with apex proximal stabilizes the thumb MCP joint while maintaining flexion/extension range of motion [60].
- Although both suture tape and suture anchor constructs recapitulate native joint stiffness, repair with suture tape demonstrated the greatest biomechanical strength in stiffness and load-to-failure [90].
- In round joints, only the non-anatomic Glickel procedure restores normal range of motion and stability [111].
- In flat joints, the Glickel procedure and a modified Fairhurst configuration with origins dorsal in the metacarpal head restore range of motion and stability [111].
- Nonanatomic repositioning of the UCL might affect joint motion [30].
- Palmar placement of the UCL origin on the metacarpal increased radial deviation from a mean of 18° to a mean of 27° compared with the intact joint [30].
- Proximal placement of the UCL origin on the metacarpal decreased radial deviation from a mean of 18° to a mean of 10° compared with the intact joint [30].
- Dorsal placement of the UCL insertion on the phalanx increased radial deviation from a mean of 18° to a mean of 25° compared with the intact joint [30].
- Distal positioning of the UCL insertion on the phalanx decreased radial deviation from a mean of 18° to a mean of 11° compared with the intact joint [30].
- Performing a physical examination to assess the amount of instability of an ulnar collateral ligament injury did not create a Stener lesion if the exam was performed in a controlled, gentle manner with the thumb held without rotation [112].
- It was possible to create a Stener lesion when the thumb was tested in a flexed and supinated position, but only if there was sectioning of the proper UCL, the accessory UCL, and the origin of the ulnar sagittal band at the adductor aponeurosis [112].
- Supination and flexion of the thumb provided less stability when both components of the UCL were sectioned [112].
- Pronation and supination play a role in stability of the thumb MCP joint [112].
Classification
- The BSSH BEST guideline defines significant UCL laxity as no firm endpoint, OR > 20 degrees laxity vs. the other side, OR > 30 degrees laxity [39].
- The term ‘Stener lesion’ is used to describe when the ligament is completely torn and is displaced superficial to the adductor aponeurosis [18].
- In a Stener lesion, the ruptured ligament becomes displaced superficial to the adductor aponeurosis and is unable to heal anatomically without surgical intervention [20].
- Presence of a displaced fleck sign has implications for offering surgery to patients with thumb UCL injuries because of a high likelihood of a Stener lesion [17].
Clinical Presentation
Symptoms and Signs
- Patients commonly report pain, swelling, and ecymosis around the thumb metacarpophalangeal joint [47].
- Tenderness is greatest over the ulnar aspect of the thumb metacarpophalangeal joint [47].
- A prominent lump can be palpated representing the ulnar collateral ligament being proximally and superficially displaced by the adductor aponeurosis in the presence of a Stener lesion [47].
- Pathologic rotation of the thumb may be evident in cases of Stener lesion [47].
- Incomplete acute tears and nondisplaced avulsion fractures are managed with a thumb spica cast for up to 4 weeks, followed by removable protective splinting for 3 more weeks with active range-of-motion exercises [42].
- Skier's thumb can lead to chronic pain and instability when diagnosed incorrectly [83].
Clinical Examination
- The metacarpophalangeal joint is generally examined by applying a radial force in extension and with approximately 30° of MCPJ flexion to relax the palmar plate [18].
- Physical examination is performed with a valgus stress applied in neutral rotation to the thumb in both extension (testing the accessory ligament) and 30° to 35° flexion (proper ligament) [42].
- An injured thumb that shows more than 30 degrees of instability compared with the uninjured side indicates a complete rupture [47].
- Valgus instability of more than 30°—or more than 10° compared with the contralateral thumb in both flexion and extension—indicates complete rupture of the proper and accessory UCL [80].
- Instability of the MCP joint in flexion indicates rupture of the proper UCL only [80].
- Comparison with the uninjured contralateral thumb is unreliable in many individuals due to significant variation between right and left thumbs [32].
- New evidence suggests that a lack of definite end point rather than comparison with the uninjured side should be used to define complete UCL rupture [42].
- If a hard endpoint is not encountered and there is increased deviation (>20 degrees) at the MP joint, surgery is recommended [35].
- For those patients with significant guarding, a digital block may be necessary to carry out the stress test [35].
- The ulnar side of the joint should be palpated for a Stener lesion, where both the proper and accessory ligament are retracted and lie on the adductor aponeurosis [42].
- Physical examination is required to determine stability with injuries to the ulnar structures of the thumb metacarpophalangeal joint [31].
- Clinical examination is recommended to assess for significant laxity of the UCL, defined as no firm endpoint, or > 20 degrees laxity vs. the other side, or > 30 degrees laxity [39].
Imaging and Diagnostic Tests
- Plain radiographs should be obtained prior to any stress examinations to avoid displacing an otherwise nondisplaced fracture [42].
- Plain radiographs should be obtained prior to any stress examinations to exclude obvious fractures and dislocation or subluxation [58].
- Anteroposterior stress radiographs can be obtained of both thumbs for comparison purposes [47].
- Stress radiographs are useful for identifying Stener lesions, however, these are often uncomfortable for the patient and guarding may lead to false-negative results [42].
- Fluoroscopy can aid the diagnosis to see if the joint becomes incongruent and to measure the deviation compared to the contralateral limb [35].
- Ultrasonography has evolved as a reliable adjunct to clinical examination in evaluation of the UCL of the thumb [1].
- MRI evaluation reveals greater details enabling better understanding and management of ulnar collateral ligament injuries of the thumb MCP joint [2].
- Ultrasound had a positive predictive value for rupture of 94% when compared with the operative finding [58].
- The overall agreement between specialist clinic examination and ultrasound for injury to the ulnar collateral ligament was 85% (kappa 0.647) [58].
- Senior House Officers in the A&E department were able to correctly diagnose only 45% of the ruptures of the ulnar collateral ligament [58].
- In a study of 49 patients, ultrasound identified Stener lesions with a sensitivity of 36% and specificity of 61% [51].
- MRI and US of suspected UCL injury did not demonstrate good enough sensitivity for the authors to recommend their implementation and use in clinical situations [51].
- A magnetic resonance imaging scan is recommended for additional preoperative planning because it provides a detailed assessment of tear location, injury grade, and ligament quality [80].
- Clinical assessment of a thumb ulnar collateral ligament injury should be supplemented with radiographs, as underlying pathology, such as an enchondroma, may be a factor [61].
Investigations
Clinical Examination
- The MCP joint is generally examined by applying a radial force in extension and with approximately 30° of MCP joint flexion to relax the palmar plate, which is thought to isolate the UCL proper [18].
- Careful stress testing of the injured and uninjured side in both extension and flexion can often elucidate those with a significant tear of their UCL/RCL [35].
- The absence of a normal “endpoint” with radial stress is a key diagnostic finding signifying a complete ligament tear [35].
- For patients with significant guarding, a digital block may be necessary to carry out the stress test [35].
- Patients with a soft endpoint, incongruent joint, or Stener lesion require surgical intervention [35].
Imaging
- Ultrasonography (US) has evolved as a reliable adjunct to clinical examination in evaluation of the UCL of the thumb [1].
- Diagnostic ultrasound is a useful, noninvasive tool for assessing the extent of rupture of the ulnar collateral ligament [114].
- Ultrasound or MRI can be helpful to gather more information when it is difficult to ascertain if there is a Stener lesion based on palpation [35].
- Ultrasound and MRI findings do not have 100% accuracy and their findings should only be one component of the decision-making algorithm [35].
Treatment
Non-Operative Management
- A thumb spica cast or functional brace is recommended for 4 to 6 weeks for incomplete ruptures of the ulnar collateral ligament [47].
- Tears of the UCL of the thumb MCP joint without a Stener lesion are believed to heal with 4 to 6 weeks of immobilization [62].
- In patients having less than 30 degrees of laxity of the UCL, less than a 15-degree differential in laxity compared with the contralateral side, and a discrete endpoint to joint opening, nonoperative treatment consists of immobilization of the MP joint for 4 weeks in neutral alignment and slight flexion [104].
- Untreated ulnar collateral ligament (UCL) injury of the thumb metacarpophalangeal joint can lead to long-term pain and functional limitations [5].
Indications for Surgery
- Injuries that are unstable (usually 30° more opening with radial stress than the opposite uninjured side) are believed to have Stener lesions and are treated surgically [62].
- Complete tears require open repair with suture anchors or bone tunnels placed at the site of the avulsion, which most commonly is the proximal phalanx [42].
- The tear will not heal in the setting of a Stener lesion because of adductor aponeurosis interposition [42].
- Acute complete rupture of the ulnar collateral ligament should be surgically repaired [47].
- Ulnar collateral ligament retraction more than 3 mm and interposed soft tissue are reasonable guides to surgical intervention [47].
Operative Techniques
- Repair of the UCL of the thumb is one of the most common ligamentous repairs in the hand, with options including a pullout suture and button, bone anchors, or a combination of the two with local tissue augmentation or imbrication [63].
- A K-wire across the joint is often employed to allow proper ligament tensioning and to maintain joint stability postoperatively [63].
- The surgical approach involves a lazy S incision on the ulnar aspect of the thumb, with careful identification and retraction of the dorsal sensory branch of the radial nerve [28].
- The adductor aponeurosis is incised longitudinally to allow repair after the collateral ligament repair [28].
- Direct repair of the ligament should be obtained with the use of one or two bone anchors, preferably small metallic anchors with stout nonabsorbable suture material [35].
- Additional sutures are used to augment the repair to the volar plate distally and capsule dorsally [35].
- The capsule and adductor aponeurosis should be repaired in separate layers [35].
- For chronic tears with excessive laxity, the adductor insertion can be advanced to increase dynamic stability [35].
- Both pull-out suture and bone anchor techniques are safe and effective for treating thumb ulnar collateral ligament injuries [23].
- In a biomechanical model, thumb UCL repair with suture tape augmentation demonstrated greater maximum and clinical failure loads compared with nonaugmented repair at time 0 [41].
- Arthroscopic treatment of acute complete thumb metacarpophalangeal ulnar collateral ligament tears resulted in key pinch, tip pinch, grip strength, and range of motion equal to or greater than in the thumb on the unaffected side in most cases [46].
Chronic Injury and Reconstruction
- If the diagnosis is delayed for 1 month or longer, fibrosis makes ligament identification and repair more difficult, although repair can be done by dissecting out the ligament from within the fibrotic mass and reattaching it appropriately [47].
- The detached tendinous insertion of the adductor muscle can be advanced and reattached to furnish a dynamic reinforcement in delayed repairs [47].
- If the repair is done several months after the injury, a graft can be used [47].
- Chronic ruptures of the UCL can be challenging to reconstruct, but most often there is enough local tissue present to allow for direct repair with the existing native ligament [35].
- Graft reconstruction of the UCL can often be accomplished with either an autograft palmaris/plantaris tendon or with an allograft [35].
- Newer techniques for chronic reconstruction involve the use of 3.0-mm drills, the graft, fibertape, and interference screws [35].
- An X or Y type configuration is often needed to appropriately reconstruct the surface area of the ligament to prevent recurrent instability in chronic cases [35].
- If a Y construct is used for chronic reconstruction, the single limb is placed distally and the dual limb proximally to prevent iatrogenic injury [35].
- A K-wire is highly recommended in chronic reconstruction to allow adequate healing and provide sufficient stability to permit early mobilization of the adjacent IP and CMC joints [35].
- The pin is typically removed in the office at 6 weeks following chronic reconstruction [35].
- Nonbiological ligament reconstruction of the thumb ulnar collateral ligament generates short-term outcomes comparable with those of biological reconstruction, potentially allowing for expedited recovery and rehabilitation [45].
- Patient-reported outcomes, including pain and function, improved after thumb UCL reconstruction with a tendon autograft [36].
- Increased time from injury to treatment (beyond 6 weeks) may decrease the likelihood of direct repair [104].
- If no local tissue is available for chronic repair, UCL reconstruction is most commonly performed with a free tendon graft [104].
- The graft is tensioned at 45 degrees of flexion with some ulnar deviation placed on the MCP joint during reconstruction [104].
- A relative contraindication to ligament reconstruction is marked volar subluxation and/or supination of the MP joint [104].
- The only absolute contraindication to reconstruction is osteoarthritis of the MP joint, in which case arthrodesis is a very dependable option [104].
Outcomes and Rehabilitation
- Collegiate football athletes treated for thumb UCL injuries with suture anchor repair had quick return to play, reliable return to the same level of activity, and excellent long-term clinical outcomes [33].
- Complications are rare and most patients show preservation of motion, key pinch, and grip strength [25].
- Thumb MCP joint collateral ligament injuries have a good outcome with appropriate diagnosis and treatment [34].
- There was no significant change in pinch strength in patients with chronic UCL reconstructions, but significantly better results were achieved in grip strength, flexion, extension, ulnar and radial deviation [29].
- This is the first clinical application of an accelerated rehabilitation protocol in athletes following thumb MCP UCL repair [22].
- Strenuous activity is avoided for 3 months, with unrestricted return to sport usually at 2 to 3 months [42].
- Limit motion for the first 4 to 6 weeks depending on chronicity of the injury; more chronic injuries are immobilized longer [28].
- Guided therapy at 6 weeks in a removable splint is part of the postoperative protocol [28].
- A thumb spica cast is worn for 4 weeks postoperatively after reconstruction, followed by hand therapy and protection for an additional 5 weeks in a splint [104].
Complications
Non-Operative
Operative
- Long-term dangers and the cost effectiveness of the procedure using the Fiji Anchor® are not known yet [48].
- Thumb spica casting risks placing additional stress upon adjacent joints and causing adjacent injury [37].
Recovery
Outcomes and Function
- Recovery of pinch grip strength measured using two point palmar pinch is on average within 92 per cent of expected values after normalization for dominance [66].
Return to Sport and Work
- Players who underwent thumb UCL surgery played in a similar number of games per season and had similar career lengths in the NFL as controls [67].
Rehabilitation Protocols
Key Evidence
- [L4] Ultrasonography (US) has evolved as a reliable adjunct to clinical examination in evaluation of the UCL of the thumb. [1] (10.1148/rg.264055117)
- [L4] MRI evaluation reveals greater details enabling better understanding and management of ulnar collateral ligament injuries of the thumb MCP joint. [2] (10.1016/s0363-5023(09)60139-8)
- [L5] Valgus laxity greater than 30 degrees or more than 15 degrees more than in the noninjured thumb with the MCP joint in extension is an indication for operative management. [3] (10.5435/00124635-199707000-00006)
- [L1] Surgical management of thumb UCL injuries produces overall favorable results. [4] (10.5435/jaaosglobal-d-25-00082)
- [L5] Untreated ulnar collateral ligament (UCL) injury of the thumb metacarpophalangeal joint can lead to long-term pain and functional limitations. [5] (10.2106/jbjs.k.01024)
- [L3] The rate of surgery for acute thumb MP UCL injury varies based on patient characteristics and the individual treating surgeon. [6] (10.1177/1558944716681974)
- [L5] Sequential tearing of the thumb UCL leads to progressive instability of the MCP joint. [7] (10.1177/1558944719868518)
- [L5] A controlled active motion therapy protocol after suture anchor repair of a ruptured UCL of the thumb is safe from a biomechanical point of view. [8] (10.1016/j.jhsa.2004.04.017)
- [L4] Return-to-play rates after surgical treatment of thumb UCL injuries are high, with reassuring return to preinjury level of play with few complications. [9] (10.1016/j.jhsg.2023.03.005)
- [L4] Our 4-stage, treatment-oriented classification of thumb UCL injury is based on the degree of UCL displacement, with correlation with the likelihood of success with either immobilization or operative intervention. [10] (10.1016/j.jhsa.2014.08.033)
- [L3] Patients with both acute and chronic thumb UCL injuries have similarly acceptable functional outcomes, postoperative pain, and satisfaction. [11] (10.1016/j.jhsg.2022.02.008)
- [L3] The authors concluded that this is a safe and effective method for repair of complete tears of the ulnar collateral ligament of the thumb MP joint. [12] (10.1016/s0363-5023(97)80113-x)
- [L5] 75% of cases with complete rupture of the ulnar collateral ligament of the thumb will fail to heal with conservative treatment. [13] (10.1007/s11552-008-9145-8)
- [L4] Thumb ulnar collateral ligament injuries can be safely and effectively managed by football position demands. [14] (10.1177/2325967114s00092)
- [L5] No static ligament reconstruction restores the normal stability characteristics of the thumb UCL. [15] (10.1016/j.jhsa.2004.09.012)
- [L3] Players who underwent thumb UCL repair played in a similar number of games per season and had similar career lengths in the MLB as controls. [16] (10.1177/2325967117747268)
- [L4] Presence of a displaced fleck sign has implications for offering surgery to patients with thumb UCL injuries because of a high likelihood of a Stener lesion. [17] (10.1016/j.jhsa.2024.12.003)
- [L1] [18] (10.1177/17531934241274612)
- [L4] Treatment of a thumb UCL complete rupture (Grade III) using a custom-made hinged splint shows promise in the conservative management of compliant patients. [19] (10.1016/j.jht.2009.10.001)
- [L4] [20] (10.1016/j.injury.2026.113711)
- [L4] It could be an alternative treatment technique for thumb UCL avulsion fractures. [21] (10.1016/j.otsr.2019.01.008)
- [L4] This is the first clinical application of an accelerated rehabilitation protocol in athletes following thumb MCP UCL repair. [22] (10.1016/j.jht.2022.07.007)
- [L3] Both repair methods are safe and effective for treating thumb ulnar collateral ligament injuries. [23] (10.1097/prs.0b013e3181882163)
- [L2] Patient-reported outcomes improve significantly at three and 12 months after open surgical repair of the thumb UCL compared to baseline. [24] (10.1016/j.jhsa.2023.05.003)
- [L5] Complications are rare and most patients show preservation of motion, key pinch, and grip strength. [25] (10.1016/j.ocl.2014.11.007)
- [L4] Thumb UCL repair with suture tape augmentation demonstrates short-term outcomes comparable to what has been reported for other methods of repair. [26] (10.1142/s2424835520500046)
- [L3] There was no significant change in pinch strength in patients with chronic UCL reconstructions, but significantly better results were achieved in grip strength, flexion, extension, ulnar and radial deviation. [29] (10.1016/j.hansur.2020.03.002)
- [L5] [30] (10.1053/jhsu.1999.0283)
- [L5] This suggests that physical examination is required to determine stability with injuries to the ulnar structures of the thumb metacarpophalangeal joint. [31] (10.1016/s0363-5023(98)80158-5)
- [L4] Comparison with the uninjured contralateral thumb is unreliable in many individuals due to significant variation between right and left thumbs. [32] (10.1177/1753193408100957)
- [L4] Collegiate football athletes treated for thumb UCL injuries with suture anchor repair had quick return to play, reliable return to the same level of activity, and excellent long-term clinical outcomes. [33] (10.1016/j.jhsa.2014.06.132)
- [L5] Thumb MCP joint collateral ligament injuries have a good outcome with appropriate diagnosis and treatment. [34] (10.1016/j.csm.2014.09.004)
- [L4] Patient-reported outcomes, including pain and function, improved after thumb UCL reconstruction with a tendon autograft. [36] (10.1016/j.jhsa.2024.05.005)
- [L4] Thumb spica casting protects the surgically repaired thumb UCL and allows for earlier return to play, but risks placing additional stress upon adjacent joints and causing adjacent injury. [37] (10.1177/1558944718788644)
- [L5] [39] (10.1177/17531934241311826)
- [L5] Single- and double-bundle UCL reconstructions of the thumb MCP joint have comparable biomechanical properties in regard to joint congruity under valgus load. [40] (10.1177/1558944717744338)
- [L5] In this model, thumb UCL repair with suture tape augmentation demonstrated greater maximum and clinical failure loads compared with nonaugmented repair at time 0, that is, without any biological healing. [41] (10.1016/j.jhsa.2018.02.002)
- [L4] Nonbiological ligament reconstruction of the thumb ulnar collateral ligament generates short-term outcomes comparable with those of BLR, potentially allowing for expedited recovery and rehabilitation. [45] (10.1016/j.jhsa.2024.01.008)
- [L4] In most cases, key pinch, tip pinch, grip strength, and range of motion were equal to or greater than in the thumb on the unaffected side. [46] (10.1016/s0363-5023(05)80156-x)
- [Paper] The surgical treatment of an ulnar collateral ligament lesion of the thumb using the Fiji Anchor® can lead to an excellent clinical outcome with a minor complication rate; however, long-term dangers and the cost effectiveness of the procedure are not known yet. [48] (10.1007/s00402-020-03625-x)
- [L4] [51] (10.1177/1753193420932496)
- [L2] [58] (10.1054/jhsb.1999.0283)
- [L5] The reconstruction tunnel positioning of triangular configuration with apex proximal stabilizes the thumb MCP joint while maintaining flexion/extension range of motion. [60] (10.1016/j.jhsa.2005.05.004)
- [L5] This case highlights that clinical assessment of a thumb ulnar collateral ligament injury should be supplemented with radiographs, as underlying pathology, such as an enchondroma, may be a factor. [61] (10.1177/17531934251315313)
- [L4] Recovery of pinch grip strength measured using two point palmar pinch is on average within 92 per cent of expected values after normalization for dominance. [66] (10.1016/0020-1383(94)90179-1)
- [L4] Players who underwent thumb UCL surgery played in a similar number of games per season and had similar career lengths in the NFL as controls. [67] (10.1177/1558944718760001)
- [L5] [80] (10.1016/j.eats.2025.103957)
- [L5] Skier's thumb is an often-encountered injury and can lead to chronic pain and instability when diagnosed incorrectly. [83] (10.1186/1865-1380-6-31)
- [L5] Although both ST and SA constructs recapitulate native joint stiffness, repair with ST demonstrated the greatest biomechanical strength in stiffness and load-to-failure. [90] (10.1016/j.jhsa.2021.09.028)
- [L5] Biomechanically, there are no treatments of repair or reconstruction using native tissues that provide equivalent strength to the preinjured ligament. [105] (10.5435/jaaos-d-22-00112)
- [L5] In round joints, only the non-anatomic Glickel procedure restores normal ROM and stability, while in flat joints, the Glickel procedure and a modified Fairhurst configuration with origins dorsal in the metacarpal head restore ROM and stability. [111] (10.1177/17531934231164260)
- [L5] [112] (10.1142/s0218810417500411)
- [L5] Diagnostic ultrasound is a useful, noninvasive tool for assessing the extent of rupture of the ulnar collateral ligament. [114] (10.1016/0363-5023(94)90025-6)
References
[1] US Diagnosis of UCL Tears of the Thumb and Stener Lesions: Technique, Pattern-based Approach, and Differential Diagnosis. RadioGraphics. 2006. DOI: 10.1148/rg.264055117
[2] MRI Classification of Ulnar Collateral Ligament Injuries of the Thumb MCP Joint. The Journal of Hand Surgery. 2009. DOI: 10.1016/s0363-5023(09)60139-8
[3] Injuries to the Ulnar Collateral Ligament of the Thumb Metacarpophalangeal Joint. Journal of the American Academy of Orthopaedic Surgeons. 1997. DOI: 10.5435/00124635-199707000-00006
[4] Surgical Management of Thumb Ulnar Collateral Ligament Injuries: A Systematic Review and Meta-analysis of 614 Patients With a Minimum 1 Year Follow-up. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-25-00082
[5] Management of Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries. Journal of Bone and Joint Surgery. 2012. DOI: 10.2106/jbjs.k.01024
[6] Variation in the Rate of Surgery for Ulnar Collateral Ligament Injury of the Metacarpophalangeal Joint of the Thumb. HAND. 2016. DOI: 10.1177/1558944716681974
[7] Biomechanical Analysis of Thumb Ulnar Collateral Ligament Tear Kinematics. HAND. 2019. DOI: 10.1177/1558944719868518
[8] A biomechanical modeling of injury, repair, and rehabilitation of ulnar collateral ligament injuries of the thumb. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.017
[9] Return to Play After Thumb Ulnar Collateral Ligament Injuries Managed Surgically in Athletes—A Systematic Review. Journal of Hand Surgery Global Online. 2023. DOI: 10.1016/j.jhsg.2023.03.005
[10] Gamekeeper’s Thumb—A Treatment-Oriented Magnetic Resonance Imaging Classification. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.08.033
[11] A Comparison of Acute Versus Chronic Thumb Ulnar Collateral Ligament Surgery Using Primary Suture Anchor Repair and Local Soft Tissue Advancement. Journal of Hand Surgery Global Online. 2022. DOI: 10.1016/j.jhsg.2022.02.008
[12] Repair of acute ulnar collateral ligament injuries of the thumb metacarpophalangeal joint with an intraosseous suture anchor. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80113-x
[13] Injury to the Ulnar Collateral Ligament of the Thumb. HAND. 2008. DOI: 10.1007/s11552-008-9145-8
[14] Return to Play and Long-Term Clinical Outcomes after Suture Anchor Repair of Thumb Ulnar Collateral Ligament Injuries in Collegiate Football Athletes. Orthopaedic Journal of Sports Medicine. 2014. DOI: 10.1177/2325967114s00092
[15] Reconstruction of the ulnar collateral ligament of the thumb metacarpophalangeal joint: A cadaver study. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2004.09.012
[16] Performance and Return to Sport After Thumb Ulnar Collateral Ligament Repair in Major League Baseball Players. Orthopaedic Journal of Sports Medicine. 2018. DOI: 10.1177/2325967117747268
[17] The Displaced Fleck Sign: Description of a Radiographic Finding Consistent with Grade III Thumb Ulnar Collateral Ligament Tears with Stener Lesions. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.12.003
[18] Guideline on managing thumb ulnar collateral ligament injuries: the British Society of Surgery for the Hand Evidence for Surgical Treatment (BEST) findings and recommendations. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241274612
[19] Treatment of Grade III Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries with Early Controlled Motion Using a Hinged Splint. Journal of Hand Therapy. 2010. DOI: 10.1016/j.jht.2009.10.001
[20] Return to Duty After Suture Anchor Repair of Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries in Active Duty Soldiers. Injury. 2026. DOI: 10.1016/j.injury.2026.113711
[21] Mini hook plate fixation for thumb ulnar collateral ligament avulsion fracture: A technical report. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2019.01.008
[22] Accelerated rehabilitation following thumb ulnar collateral ligament repair with suture tape augmentation: A case series of professional basketball players. Journal of Hand Therapy. 2023. DOI: 10.1016/j.jht.2022.07.007
[23] Repair of Acute Ulnar Collateral Ligament Injuries of the Thumb Metacarpophalangeal Joint: A Retrospective Comparison of Pull-Out Sutures and Bone Anchor Techniques. Plastic and Reconstructive Surgery. 2008. DOI: 10.1097/prs.0b013e3181882163
[24] Patient-Reported Outcomes and Function After Surgical Repair of the Ulnar Collateral Ligament of the Thumb. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.05.003
[25] Ulnar Collateral Ligament Injuries of the Thumb. Orthopedic Clinics of North America. 2015. DOI: 10.1016/j.ocl.2014.11.007
[26] Thumb Ulnar Collateral Ligament Repair with Suture Tape Augmentation. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520500046
[28] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Open Repair of the Ulnar or Radial Collateral Ligament of the MCP Joint of the Thumb: Preoperative Planning Checklist.
[29] The effects of rehabilitation on the outcomes of surgically treated acute and chronic thumb metacarpophalangeal ulnar collateral ligament ruptures. Hand Surgery and Rehabilitation. 2020. DOI: 10.1016/j.hansur.2020.03.002
[30] The effect of thumb metacarpophalangeal ulnar collateral ligament attachment site on joint range of motion: An in vitro study. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0283
[31] The stener lesion revisited: A case report. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80158-5
[32] Clinical Testing of Ulnar Collateral Ligament Injuries of the Thumb. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193408100957
[33] Return to Football and Long-Term Clinical Outcomes After Thumb Ulnar Collateral Ligament Suture Anchor Repair in Collegiate Athletes. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.132
[34] Thumb Ulnar Collateral and Radial Collateral Ligament Injuries. Clinics in Sports Medicine. 2015. DOI: 10.1016/j.csm.2014.09.004
[35] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Thumb MCP Ligament Repair.
[36] Patient-Reported and Clinical Outcomes After Tendon Autograft Reconstruction of the Thumb Ulnar Collateral Ligament. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.05.005
[37] Early Return to Play With Thumb Spica Gauntlet Casting for Ulnar Collateral Ligament Injuries Complicated by Adjacent Joint Dislocations in Collegiate Football Linemen. HAND. 2018. DOI: 10.1177/1558944718788644
[39] Re. Dean B, Rodrigues J, Riley N, Rabey N, Donnison E, Challen K, Bradford S; BSSH BEST UCL Guideline Development Group. Guideline on managing thumb ulnar collateral ligament injuries: the British Society of Surgery for the Hand Evidence for Surgical Treatment (BEST) findings and recommendations. J Hand Surg Eur. 2024, 49: 1195–201. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934241311826
[40] Single-Bundle vs Double-Bundle (Anatomical) Reconstruction of the Thumb Ulnar Collateral Ligament: Biomechanical Study. HAND. 2017. DOI: 10.1177/1558944717744338
[41] Suture Tape Augmentation of the Thumb Ulnar Collateral Ligament Repair: A Biomechanical Study. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.002
[42] Orthopaedic Knowledge Update Sports Medicine 6. Hand and Wrist Injuries > Hand Injuries > Skier’s Thumb.
[44] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Acute Ulnar Collateral Ligament Injuries (Skier’s Thumb).
[45] Biological Versus Nonbiological Reconstruction of the Ulnar Collateral Ligament of the Thumb Metacarpophalangeal Joint: A Retrospective Study. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.01.008
[46] Arthroscopic treatment of acute complete thumb metacarpophalangeal ulnar collateral ligament tears. The Journal of Hand Surgery. 1995. DOI: 10.1016/s0363-5023(05)80156-x
[47] Campbell S Operative Orthopaedics 4 Volume Set. FRACTURES, DISLOCATIONS, AND LIGAMENTOUS INJURIES OF THE HAND AND WRIST > THUMB METACARPOPHALANGEAL JOINT ULNAR COLLATERAL LIGAMENT RUPTURE.
[48] Clinical results of the BoneWelding®Fiji® anchor for the treatment of Stener lesions of the thumb. Archives of Orthopaedic and Trauma Surgery. 2020. DOI: 10.1007/s00402-020-03625-x
[51] The value of magnetic resonance imaging and ultrasound in diagnosing displaced rupture of the thumb ulnar collateral ligament. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420932496
[52] Exam Of The Hand Wrist 2Ed. Movements of the thumb.
[58] The Use of Ultrasound in the Diagnosis of Injuries of the Ulnar Collateral Ligament of the Thumb. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.1999.0283
[60] Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries: A Biomechanical Simulation Study of Four Static Reconstructions. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.05.004
[61] Clinical thumb ulnar collateral ligament injury owing to a pathological fracture through an enchondroma of the proximal phalanx. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251315313
[62] Aaos Comprehensive Orthopaedic Review 3. Hand Trauma > VI. Thumb Metacarpophalangeal Ligament Injuries and Dislocations.
[63] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Open Repair of the Ulnar or Radial Collateral Ligament of the MCP Joint of the Thumb.
[66] Gamekeeper's thumb: a quantitative evaluation of acute surgical repair. Injury. 1994. DOI: 10.1016/0020-1383(94)90179-1
[67] Performance and Return to Sport After Thumb Ulnar Collateral Ligament Surgery in National Football League Players. HAND. 2018. DOI: 10.1177/1558944718760001
[80] Thumb Ulnar Collateral Ligament Repair Using Suture Anchors and Suture Tape Augmentation. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2025.103957
[83] Rupture of the ulnar collateral ligament of the thumb – a review. International Journal of Emergency Medicine. 2013. DOI: 10.1186/1865-1380-6-31
[90] Biomechanical Comparison of 3 Thumb Ulnar Collateral Ligament Repair Methods. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2021.09.028
[94] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Types of Operations > Technique of open repair of the thumb metacarpophalangeal ulnar collateral ligament..
[100] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Chronic Ulnar Collateral Ligament Injuries (Gamekeeper’s Thumb) > Preoperative Evaluation.
[104] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Chronic Ulnar Collateral Ligament Injuries (Gamekeeper’s Thumb) > Types of Operations.
[105] Thumb Metacarpophalangeal Joint Ulnar Collateral Ligament Injuries: Management and Biomechanical Evaluation. Journal of the American Academy of Orthopaedic Surgeons. 2023. DOI: 10.5435/jaaos-d-22-00112
[111] Thumb metacarpophalangeal joint morphology and reconstruction of the ruptured ulnar collateral ligament. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231164260
[112] Can Physical Examination Create a Stener Lesion?. The Journal of Hand Surgery (Asian-Pacific Volume). 2017. DOI: 10.1142/s0218810417500411
[114] Ultrasonographic detection of thumb ulnar collateral ligament injuries: A cadaveric study. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90025-6