Patients › Wrist
மணிக்கட்டு கேங்க்லியான்கள்
Wrist ganglia are common, fluid-filled lumps – often painless – and this page covers observation, aspiration, and excision.
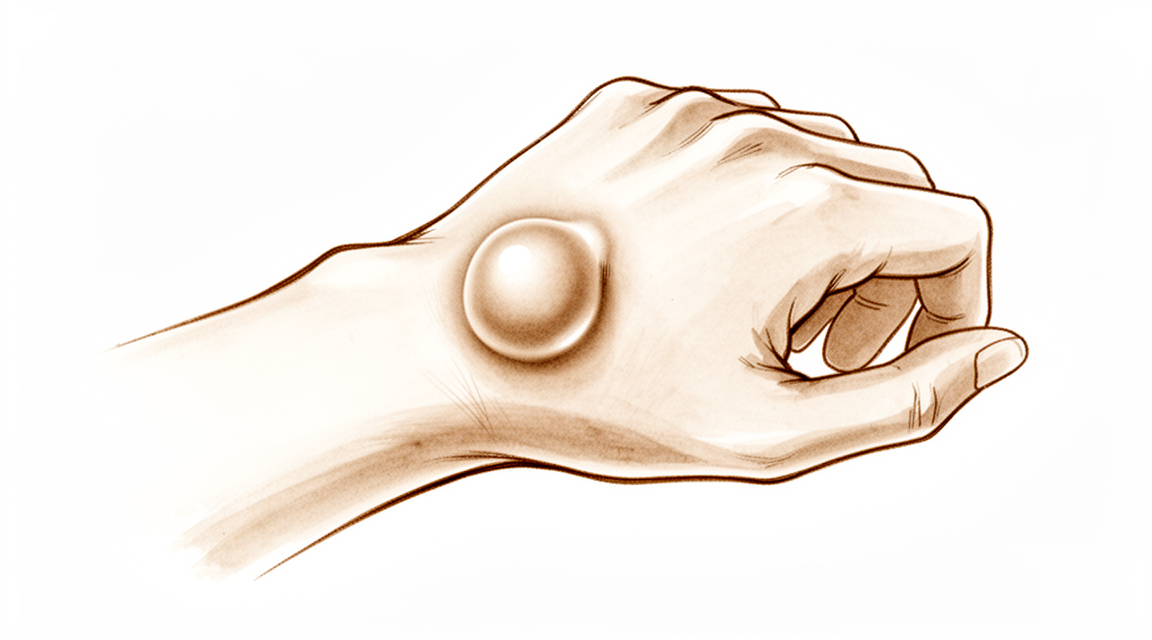
நீங்கள் உணர்வது
மணிக்கட்டு கேங்க்லியான் (wrist ganglion) என்பது, மணிக்கட்டு மூட்டிலிருந்தோ ஒரு தசைநாண் உறையிலிருந்தோ வளரும், திரவம் நிரம்பிய ஒரு கட்டி. இது தீங்கான எதுவாகவும் மாறும் வளர்ச்சி அல்ல. பலர் முதலில் அதை மணிக்கட்டின் பின்புறத்தில் ஒரு மென்மையான புடைப்பாகக் கவனிக்கிறார்கள்; இருப்பினும் அது உள்ளங்கைப் பக்கத்திலும் தோன்றலாம். அது திடமாக உணரப்படலாம்; காலப்போக்கில் அதன் அளவு மாறலாம்.
கட்டி தானாக பெரும்பாலும் வலியற்றது. வலி இருக்கும்போது, அது மணிக்கட்டுக்குள் ஆழமாக, கட்டிக்கு அருகில் இருக்கும் போக்கு உள்ளது; செயல்பாட்டுடன் அது அடிக்கடி அதிகரிக்கிறது. நாற்காலியிலிருந்து கைகளை ஊன்றி எழுவது, கடைப் பைகளைச் சுமப்பது, அல்லது கனமான பாத்திரத்தைப் பற்றிப் பிடிப்பது போன்ற, மணிக்கட்டை வளைக்கும் அல்லது அதன் மீது எடை சுமத்தும் பணிகள் அதை வலிக்கச் செய்யலாம். சிலருக்கு மணிக்கட்டு வழக்கத்தைவிடப் பலவீனமாகவோ விறைப்பாகவோ உணரப்படுகிறது; அது தட்டச்சு செய்வதையோ, எழுதுவதையோ, ஜாடிகளைத் திறப்பதையோ கடினமாக்கலாம்.
கட்டி மணிக்கட்டில் உள்ள நரம்புகளுக்கு அருகில் அமர்ந்திருப்பதால், கேங்க்லியான் சில நேரங்களில் அவற்றின் மீது அழுத்தலாம். இது கையில் கூச்சம், மரத்துப்போதல், அல்லது பலவீனத்தை ஏற்படுத்தலாம். இந்த நரம்பு அறிகுறிகளில் எதையாவது நீங்கள் கவனித்தால், தாமதிக்காமல் விரைவிலேயே மணிக்கட்டைப் பரிசோதித்துக்கொள்வது நல்லது; ஏனெனில் அந்த அழுத்தத்திலிருந்து நரம்புக்கு விடுபடல் தேவை.
கட்டியோ வலியோ தணியாவிட்டால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், அல்லது உங்கள் கையைப் பயன்படுத்துவதையோ வேலை செய்வதையோ தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
உண்மையில் என்ன நடக்கிறது
கேங்க்லியான் உங்கள் மணிக்கட்டு மூட்டின் உட்படலத்தில் உள்ள ஒரு சிறிய, ஒருவழி வால்விலிருந்து (valve) வளர்கிறது. பொதுவாக மூட்டை வழுவழுப்பாக்கும் திரவம் இந்த வால்வு வழியாக வெளியே தள்ளப்படுகிறது; ஆனால் அதனால் திரும்பிப் பாய முடிவதில்லை. அது தோலுக்கு அடியில் ஒரு பையில் சேர்கிறது; நீங்கள் பார்க்கும், தொட்டு உணரும் கட்டி அந்தப் பைதான். கட்டி ஒரு மெல்லிய காம்பின் மூலம் மூட்டுடன் இணைந்துள்ளது; அதனால்தான் மூட்டு அதிகமாகவோ குறைவாகவோ திரவத்தை உற்பத்தி செய்யும்போது கட்டியின் அளவு மாற முடிகிறது.
பெரும்பாலான கேங்க்லியான்கள் ஸ்கேஃபோலூனேட் தசைநாரிலிருந்து (scapholunate ligament) வளர்கின்றன; இது இரண்டு சிறிய மணிக்கட்டு எலும்புகளை ஒன்றாகப் பிடித்து வைத்திருக்கும் ஒரு குட்டையான திசுப் பட்டை. அது அவற்றுக்கிடையே ஒரு கேஸ்கெட் (gasket) போலச் சற்றுச் செயல்படுகிறது. இந்தப் பட்டையைச் சுற்றியுள்ள உட்படலம், பெரும்பாலும் ஒரு லேசான சுளுக்கு அல்லது மீண்டும் மீண்டும் ஏற்படும் இழுவிசைக்குப் பிறகு, எரிச்சலடைகிறது; அங்கிருந்தே திரவம் கசிகிறது. வலி ஏன் தோலில் அல்லாமல் மணிக்கட்டுக்குள் ஆழமாக இருக்கிறது என்பதையும் இது விளக்குகிறது: பிரச்சினை கட்டியில் அல்ல, மூட்டிலேயே உள்ளது.
கட்டியின் இருப்பிடம் உங்கள் மற்ற அறிகுறிகளை விளக்குகிறது. மணிக்கட்டின் பின்புறத்தில், அது பொதுவாக அந்தத் தசைநாரின் நேர் மேலே, உங்கள் விரல்களை நேராக்கும் தசைநாண்களுக்கு அருகில் அமர்ந்திருக்கிறது. உள்ளங்கைப் பக்கத்தில், அது பெரும்பாலும் முக்கியத் தமனிக்கும் (artery) உங்கள் கைக்குள் செல்லும் நரம்புகளுக்கும் அருகில் வளர்கிறது; அதனால்தான் நீர்க்கட்டி அவற்றின் மீது அழுத்தும்போது கூச்சமோ மரத்துப்போதலோ ஏற்படலாம். சில கட்டிகள் சிறியவையாகவும் மறைந்தவையாகவும் இருந்து, மணிக்கட்டு முன்னோக்கி வளைக்கப்படும்போது மட்டுமே தோன்றுகின்றன; இருப்பினும் அவை ஆழமான வலியை ஏற்படுத்தலாம்.
கேங்க்லியான்கள் பொதுவானவை என்பதைத் தெரிந்துகொள்வது நல்லது. பலருக்கு எந்த அறிகுறிகளும் இல்லாமலேயே அவை இருக்கின்றன; வலியற்ற மணிக்கட்டுகளின் ஸ்கேன்களில் நீங்கள் எதிர்பார்ப்பதைவிட அடிக்கடி அவை கண்டறியப்படுகின்றன. ஒன்று இருப்பது, உங்கள் மணிக்கட்டு மூட்டின் அமைப்பிலேயே ஏதோ தவறு இருக்கிறது என்று பொருளாகாது.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் நிலைக்குப் பொருத்தமான, உடலுக்குள் மிகக் குறைவாகத் தலையிடும் தேர்வுகளுடன் தொடங்குகிறார். நோயாளிகள் பொதுவாக அவர்களுடைய GP (பொது மருத்துவர்) மூலம் எங்கள் கிளினிக்கிற்குப் பரிந்துரைக்கப்படுகின்றனர்; ஒரு இயன்முறை சிகிச்சையாளர் (physiotherapist) எங்களைப் பார்க்கும்படி பரிந்துரைத்திருந்தாலும், Medicare தள்ளுபடியைப் (rebate) பெறத் தகுதி பெற உங்கள் GP-யிடமிருந்து பரிந்துரைக் கடிதம் (referral) இன்னும் தேவைப்படும். உங்கள் மருத்துவ வரலாறு, பரிசோதனை, தேவைப்படும் இடங்களில் ஸ்கேன்கள் ஆகியவற்றுடன் கூடிய கிளினிக் மதிப்பீடு நோயறிதலை உறுதிப்படுத்துகிறது.
கேங்க்லியான் தீங்கற்றது என்பதால், எதுவும் செய்யாமல் இருப்பது ஒரு நியாயமான முதல் படி. பல கேங்க்லியான்கள் தாமாகவே மறைந்துவிடுகின்றன. மணிக்கட்டு கேங்க்லியான்களில் 28% முதல் 58% வரை எந்தச் சிகிச்சையும் இல்லாமலேயே தணிந்துவிடுகின்றன. 10 வயதுக்குக் குறைவான குழந்தைகளில், கேங்க்லியான்கள் பொதுவாக மணிக்கட்டின் உள்ளங்கைப் பக்கத்தில் அமர்ந்திருக்கின்றன; இவற்றில் 69% முதல் 79% வரை 12 முதல் 18 மாதங்களுக்குள் தாமாகவே சுருங்கி மறைந்துவிடுகின்றன. கவனித்துக் காத்திருப்பது, சில நேரங்களில் வசதிக்காக ஒரு சிம்புடன் (splint), கை அல்லது மணிக்கட்டு கேங்க்லியான் உள்ள பெரும்பாலான குழந்தைகளுக்குப் பொருத்தமானது.
கட்டி தொல்லை தந்தால், அதை ஒரு ஊசியால் வடித்தெடுக்க முடியும். இது திரவம் எடுத்தல் (aspiration) எனப்படுகிறது. ஒன்று, இரண்டு அல்லது மூன்று முறை செய்யப்படும்போது, திரவத்தை வெளியே எடுப்பது 85% வரையிலான கேங்க்லியான்களை அகற்றுகிறது. அதன் பிறகு சிறிது திரவம் அடிக்கடி மீண்டும் வருகிறது; ஏனெனில் வடித்தெடுத்தல் கட்டியைக் காலியாக்குகிறது, ஆனால் அதை உருவாக்கிய வால்வை அப்படியே விட்டுவிடுகிறது. இருந்தாலும், திரவம் எடுத்தலுடன் கட்டியைப் பற்றிய எளிய அறிவுரையும் பெற்ற பிறகு 74% பேர் திருப்தி அடைகிறார்கள். முதலில் வடித்தெடுப்பது, அறுவை சிகிச்சையை முதல் நடவடிக்கையாக அல்லாமல் பின்னாளுக்கான ஒரு தேர்வாக வைத்திருக்கவும் உதவுகிறது. மணிக்கட்டின் பின்புறத்தில் மறைந்திருக்கும் கேங்க்லியான், அதாவது ஆழமான வலியை ஏற்படுத்தினாலும் கண்ணுக்குத் தெரியாத ஒன்று, பொதுவாக முதலில் அறுவை சிகிச்சை இல்லாமல் கையாளப்படுகிறது: மணிக்கட்டை அசையாமல் பிடித்து வைத்தும், மூட்டின் உட்படலத்துக்குள் ஸ்டீராய்டு (steroid) ஊசிகள் செலுத்தியும்.
இந்தப் படிகள் போதுமான நிவாரணம் தராதபோது, அறுவை சிகிச்சை மூலம் கேங்க்லியானை அகற்ற முடியும். இந்த அறுவை சிகிச்சை, கட்டியையும் அதன் காம்பையும், அதாவது மணிக்கட்டு மூட்டுடனான மெல்லிய இணைப்பையும், அகற்றுகிறது; ஏனெனில் காம்பை விட்டுவைப்பது கட்டி மீண்டும் வருவதற்கான வாய்ப்பை அதிகரிக்கிறது. இதைத் திறந்த அறுவை சிகிச்சையாகவோ, சிறிய துவாரங்கள் (portals) வழியாகச் செய்யப்படும் சாவித்துளை அறுவை சிகிச்சையாகவோ (keyhole surgery) செய்யலாம். உங்கள் மணிக்கட்டுக்கு எது பொருத்தமானது என்பதை நாம் சேர்ந்து பேசுவோம்; அறுவை சிகிச்சை உங்களுக்குப் பயனுள்ளதா என்பதை நீங்கள் எங்களுடன் சேர்ந்து முடிவு செய்வீர்கள்.
என்ன எதிர்பார்க்கலாம்
பல மணிக்கட்டு கேங்க்லியான்கள் அப்படியே இருப்பதற்குப் பதிலாகக் காலப்போக்கில் மாறுகின்றன. அவை சுருங்கலாம், வீங்கலாம், அல்லது வந்து வந்து போகலாம். சில தாமாகவே தணிந்துவிடுகின்றன: முதன்முதலில் மதிப்பிடப்பட்ட பிறகான முதல் 6 ஆண்டுகளில் மணிக்கட்டு கேங்க்லியான்களில் சுமார் 40% சிறியதாகின்றன; மணிக்கட்டின் பின்புறத்தில் உள்ள கேங்க்லியான்களில் 39% முதல் 42% வரை எந்தச் சிகிச்சையும் இல்லாமலேயே மறைந்துவிடுகின்றன. சிறு குழந்தைகளில், பெரும்பாலான கை மற்றும் மணிக்கட்டு நீர்க்கட்டிகள், பொதுவாக ஓர் ஆண்டுக்குள், தாமாகவே சரியாகிவிடுகின்றன. உங்களுடையது அதிகத் தொல்லை தராவிட்டால், காத்திருப்பது ஒரு நியாயமான தேர்வு; கட்டியை அப்படியே விட்டுவிட்டால் அது தீங்கான எதுவாகவும் மாறாது.
சிகிச்சை வாய்ப்புகளை மாற்றுகிறது. ஊசியால் கட்டியை வடித்தெடுப்பது அதைக் காலியாக்குகிறது; ஆனால் திரவம் எடுத்தலுக்குப் பிறகு பெரும்பாலான கேங்க்லியான்கள் மீண்டும் வருகின்றன, ஏனெனில் கட்டியை உருவாக்கிய வால்வு இன்னும் அங்கேயே உள்ளது. கட்டியையும் அதன் காம்பையும் அகற்றும் அறுவை சிகிச்சையில் மீண்டும் வருவதற்கான வாய்ப்பு மிகக் குறைவு: அறுவை சிகிச்சைக்குப் பிறகு மணிக்கட்டு கேங்க்லியான்களில் சுமார் 10% மீண்டும் வருகின்றன; மணிக்கட்டின் பின்புறத்தில் உள்ள கேங்க்லியானைத் திறந்த முறையில் அகற்றிய பிறகு 3% முதல் 12% வரை மீண்டும் வருகின்றன. அறுவை சிகிச்சை செய்துகொள்பவர்களில் பெரும்பாலானோருக்கு அறிகுறிகள் தணிகின்றன. இருப்பினும், அதன் பிறகு சிறிது வலி நீடிக்கலாம், குறிப்பாக உங்கள் வேலைக்கோ விளையாட்டுக்கோ மணிக்கட்டை வலுவாகப் பின்னோக்கி வளைக்க வேண்டியிருந்தால்.
நீங்கள் அறுவை சிகிச்சையைத் தேர்ந்தெடுத்தால், மீட்சி பொதுவாக நேரடியானது. தொடக்கத்தில் உங்களை வசதியாக வைத்திருக்க, உங்கள் கை தடிமனான ஒரு கட்டால் சுற்றப்பட்டு உயர்த்தி வைக்கப்படுகிறது; மணிக்கட்டு அசைவு ஆரம்பத்திலேயே, உள்ளங்கைப் பக்க கேங்க்லியான் அறுவை சிகிச்சைக்குப் பிறகு முதல் 2 வாரங்களுக்குள், தொடங்குகிறது. மணிக்கட்டை விரைவில் அசைப்பது முக்கியம்: விறைப்பு அசாதாரணமானது, ஆனால் ஆரம்பகால அசைவு ஊக்குவிக்கப்படாவிட்டால் அது ஏற்படலாம். அறுவை சிகிச்சைக்குப் பிறகான கை சிகிச்சை (hand therapy) Extend Rehabilitation-இல் உள்ள Ruby Doolan-உடன் நடைபெறும்; அவர் உங்கள் பயிற்சிகளை வழிநடத்தி, உங்களுக்குத் தேவைப்படும் எந்தச் சிம்பையும் செய்து தருவார். உள்ளங்கைப் பக்கத்தில் செய்யப்படும் சாவித்துளை அறுவை சிகிச்சைக்குப் பிறகு, கட்டி இருந்த இடத்தில் ஒரு திடமான அல்லது தொட்டால் வலிக்கும் இடம் 3 வாரங்கள் வரை நீடிக்கலாம்; அறிவுறுத்தப்பட்டபடி அந்த இடத்தை மசாஜ் செய்வது அது தணிய உதவுகிறது. எந்த அறுவை சிகிச்சையிலும் வடுக்கள் ஒரு பகுதி; மணிக்கட்டு மடிப்புகளுக்கு அருகில் உள்ள வளைவான வெட்டுகள் நேர்த்தியான வடுக்களுடன் ஆறுவதற்கான வாய்ப்பு அதிகம்.
சிகிச்சை அளிக்கப்பட்ட கட்டியோ உங்கள் அறிகுறிகளோ தணியாவிட்டால், அல்லது வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
மணிக்கட்டு கேங்க்லியான்களில் பெரும்பாலானவை தீங்கற்றவை, பல தாமாகவே தணிந்துவிடுகின்றன; எனவே கட்டி மட்டும் இருப்பது அவசர நிலை அல்ல. கட்டியோ வலியோ வாரக்கணக்கில் தணியாவிட்டால், மோசமாகிக்கொண்டே போனால், அல்லது வேலை செய்வதையோ உங்கள் கையைப் பயன்படுத்துவதையோ தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள். கையில் கூச்சம், மரத்துப்போதல் அல்லது பலவீனம் இருந்தால், இன்னும் விரைவில் கேளுங்கள்; ஏனெனில் நீர்க்கட்டி ஒரு நரம்பின் மீது அழுத்துகிறது என்பதை அது குறிக்கிறது. உங்கள் கையோ விரல்களோ வெளிறியோ, குளிர்ந்தோ, வெள்ளையாகவோ, நீலமாகவோ மாறினால், அல்லது ஒரு காயத்துக்குப் பிறகு கையில் திடீரென உணர்ச்சியோ அசைவோ இழந்தால், அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். கேங்க்லியானுடன் இவை அரிதானவை; ஆனால் இவற்றுக்கு அதே நாளில் சிகிச்சை தேவை.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
உங்கள் சொந்த சிகிச்சை முடிவுகளுக்குத் தேவைப்படுவதைவிட இந்தப் பகுதி மேலும் ஆழமாகச் செல்கிறது. மணிக்கட்டு கேங்க்லியான்கள் இந்தக் கூடுதல் வாசிப்புக்குத் தகுதியானவை; ஏனெனில் இங்கு தேர்வு என்பது, மீண்டும் வருவதற்கான அபாயத்தை ஏற்றுக்கொள்வதற்கும் ஓர் அறுவை சிகிச்சையை ஏற்றுக்கொள்வதற்கும் இடையிலானது; அந்த ஒப்பீட்டுக்குப் பின்னால் உள்ள எண்கள், முடிவெடுக்கும் அளவுக்குத் தெளிவாக உள்ளன.
திரவம் எடுத்தல் மீண்டும் வருகிறது; அகற்றுதல் அவ்வளவு அடிக்கடி இல்லை
செயலூக்கமான இரண்டு சிகிச்சைகள் இவை: ஊசியால் நீர்க்கட்டியிலிருந்து திரவத்தை வெளியே எடுப்பது, மற்றும் அதன் காம்புடன் சேர்த்து அதை அறுவை சிகிச்சையால் அகற்றுவது. 2,239 நோயாளிகளை ஒன்றிணைத்த பகுப்பாய்வில், திரவம் எடுப்பதைவிடத் திறந்த அறுவை சிகிச்சை அகற்றுதலில் மீண்டும் வருவதற்கான வாய்ப்பு கணிசமாகக் குறைவு. ஆர்த்ரோஸ்கோபிக் (arthroscopic) அகற்றுதல் நம்பிக்கை தரும் முடிவுகளை அளித்துள்ளது; ஆனால் ஒப்பீட்டு ஆய்வுத் தரவுகள் குறைவாகவே உள்ளன, மேலும் அவை அதன் மேன்மையை நிரூபிக்கவில்லை [1].
இயங்குமுறையே அந்த வித்தியாசத்தை விளக்குகிறது. கேங்க்லியான் என்பது தன்னிச்சையாக மிதக்கும் திரவப் பை அல்ல; ஒரு காம்பின் மூலம் அது அடியில் உள்ள மூட்டு உறையுடன் (joint capsule) இணைந்துள்ளது, மேலும் மூட்டு தொடர்ந்து திரவத்தை உற்பத்தி செய்துகொண்டே இருக்கிறது. திரவம் எடுத்தல் தேக்கத்தைக் காலி செய்துவிட்டு மூலத்தை அப்படியே விட்டுவிடுகிறது; எனவே மீண்டும் நிரம்புவது சிகிச்சைத் தோல்வி என்பதைவிட ஒரு பொதுவான விளைவே. அகற்றுதல், காம்பை அதன் தோற்றுவாய் வரை கண்டறிந்து நீக்குவதை நோக்கமாகக் கொண்டுள்ளது.
சாவித்துளை அகற்றுதலும் திறந்த அகற்றுதலும் ஒரேபோல் செயல்படுகின்றன
அகற்றுதல் தேர்ந்தெடுக்கப்படும் இடத்தில், அணுகுமுறைகள் நேரடியாக ஒப்பிடப்பட்டுள்ளன. 910 நோயாளிகளை உள்ளடக்கிய ஆய்வில், மீண்டும் வருவதிலும் சிக்கல்களிலும் ஆர்த்ரோஸ்கோபிக் மற்றும் திறந்த அணுகுமுறைகள் ஒப்பிடத்தக்க விளைவுத் தோற்றத்தைக் கொண்டுள்ளன; தரப்படுத்தப்பட்ட, போதுமான ஆய்வுவலிமை கொண்ட ஆய்வுகள் தேவை என்று ஆசிரியர்கள் கோருகின்றனர் [2].
அது, மீண்டும் வருவதற்கான அபாயத்தின் அடிப்படையில் அல்லாமல், இரண்டாம் நிலைக் காரணிகளின் அடிப்படையில் முடிவை வைக்கிறது — வடு, அறுவை சிகிச்சை நிபுணருக்கு எந்த முறையில் பரிச்சயம் உள்ளது, மற்றும் மூட்டுக்குள் உள்ள வேறு நோய்நிலையை அதே நேரத்தில் பரிசோதிக்க வேண்டுமா என்பது.
அதற்குப் பிறகு என்ன செய்வது என்பதில் யாருக்கும் ஒத்த கருத்து இல்லை; அது முக்கியமானதாகவும் இல்லாமல் இருக்கலாம்
சிறிய, நேர்மையான ஒரு கண்டுபிடிப்பு. கை அறுவை சிகிச்சை நிபுணர்களிடையே நடத்தப்பட்ட ஒரு முறைமையான ஆய்வும் கருத்துக் கணிப்பும், மணிக்கட்டின் பின்புறக் கேங்க்லியானை அகற்றிய பிறகு மணிக்கட்டை அசைவின்றி வைத்திருக்க வேண்டுமா என்பதில் அவர்கள் பிளவுபட்டிருப்பதைக் கண்டறிந்தன; செயல்பாட்டு விளைவைப் பொறுத்தவரை, ஒரு உத்தி மற்றொன்றைவிடச் சிறந்தது என்று கூறுவதற்குத் திடமான தரவு எதுவும் இல்லை [3].
இங்கு அறுவை சிகிச்சை நிபுணர்களுக்கிடையே அறிவுறுத்தல்கள் வேறுபடுவது, அவர்களில் ஒருவர் தவறாக இருப்பதைக் காட்டுவதல்ல; மாறாக, உண்மையான சமநிலையான ஐயத்தையே (equipoise) பிரதிபலிக்கிறது என்பதைத் தெரிந்துகொள்வது நல்லது.
மிகவும் வலுவான வாதம் பெரும்பாலும் எதுவும் செய்யாமல் இருப்பதற்கே
மேலே உள்ள எதுவும், ஒரு கேங்க்லியானுக்குச் சிகிச்சை அளிக்கப்பட வேண்டும் என்பதை நிறுவவில்லை. இவை தீங்கற்ற நீர்க்கட்டிகள். இவற்றின் அளவு அடிக்கடி ஏறியும் இறங்கியும் மாறுகிறது; ஒரு பகுதி எந்தத் தலையீடும் இல்லாமலேயே சரியாகிவிடுகிறது. இவை வேறு எதுவாகவும் மாறுவதில்லை.
அது முடிவை வேறு கோணத்தில் வைக்கிறது. சிகிச்சை அளிப்பதற்கான காரணங்கள் இவை: வலி, மணிக்கட்டு அசைவுக்கோ பிடிக்கோ ஏற்படும் தடை, அருகிலுள்ள ஒரு நரம்பின் மீதான அழுத்தம், அல்லது அந்த நபரை உண்மையிலேயே தொந்தரவு செய்யும் அளவு — கட்டி இருக்கிறது என்பது மட்டும் அல்ல. திரவம் எடுத்தலுக்குக் குறிப்பிடத்தக்க அளவு மீண்டும் வரும் விகிதம் உள்ளது; அகற்றுதலோ ஒரு மூட்டு உறையில் செய்யப்படும் அறுவை சிகிச்சையின் அபாயங்களைக் கொண்டுள்ளது. இதைக் கருத்தில் கொண்டால், கவனிப்புடன் காத்திருப்பது ஒரு முறையான முதல் நிலைப்பாடு; செயல்படத் தவறியது என்று கருதாமல், அதைத் தெளிவாகச் சொல்வதே சரி.
இதற்கு விதிவிலக்கு, நரம்பு சார்ந்த அறிகுறிகளை — மரத்துப்போதல், பலவீனம், அல்லது கைக்குள் பரவும் வலி — ஏற்படுத்தும் கேங்க்லியான்; அங்கு நீர்க்கட்டி, அந்த அழுத்தத்தைக் காலவரம்பின்றித் தாங்க முடியாத ஓர் அமைப்பை அழுத்திக்கொண்டிருக்கிறது; அங்கு கவனிப்புடன் காத்திருப்பது இனி குறைந்த அபாயமுள்ள தேர்வு அல்ல.
மேற்கோள்கள்
[1] Head L, Gencarelli JR, Allen M, Boyd KU. Wrist ganglion treatment: systematic review and meta-analysis. J Hand Surg Am. 2015;40(3):546-553.e8. https://doi.org/10.1016/j.jhsa.2014.12.014
[2] Crawford C, Keswani A, Lovy AJ, Levy I, Lutz K, Kim J, et al. Arthroscopic versus open excision of dorsal ganglion cysts: a systematic review and meta-analysis. J Hand Surg Eur Vol. 2017;43(6):659-64. https://doi.org/10.1177/1753193417734428
[3] Wong CR, Karpinski M, Hatchell AC, McRae MH, Murphy J, McRae MC. Immobilization of the wrist after dorsal wrist ganglion excision: a systematic review and survey. Hand (N Y). 2021;18(2):254-63. https://doi.org/10.1177/15589447211014631
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Epidemiology and Natural History
- The dorsal wrist ganglion is the prototype of all hand and wrist ganglions, accounting for 60% to 70% of all hand and wrist ganglions [1].
- Volar wrist ganglia are the second most common ganglion of the hand and wrist, accounting for 18% to 20% of cases [11].
- In an asymptomatic population, 51% of 103 wrists scanned demonstrated ganglia on MRI [7].
- In an asymptomatic population evaluated by MRI, volar wrist ganglia are more common than dorsal wrist ganglia [2].
- Neither surgical excision nor aspiration provides a clear long-term benefit over the natural history of the dorsal wrist ganglion [6].
- Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist [4].
Clinical Presentation and Diagnosis
- The main cyst of a dorsal wrist ganglion is usually located directly over the scapholunate ligament [1].
- Dorsal wrist ganglions may occur anywhere between the extensor tendons and can be connected to the scapholunate ligament through an elongated pedicle [1].
- Careful preoperative palpation of a dorsal wrist ganglion with digital compression often reveals its extent and the direction of the pedicle [1].
- Transillumination or aspiration confirms the diagnosis of a wrist ganglion preoperatively [1].
- In patients with recalcitrant dorsal wrist pain in the area of the scapholunate interval, occult dorsal wrist ganglions had a prevalence of 11 out of 14 [3].
- Routine wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [5].
- A systematic X-ray should be performed for painful dorsal wrist ganglia [13].
- Preoperative x-rays should be obtained as part of the routine workup for a dorsal wrist ganglion [22].
- Volar wrist ganglions may appear small clinically but can be surprisingly extensive at surgery, with multiloculated cysts extending under the thenar muscles, along the flexor carpi radialis tendon, into the carpal canal, and under the first extensor compartment [11].
- The Allen test should be performed routinely to assess the patency of the radial and ulnar arteries in patients with volar wrist ganglions [11].
Operative Considerations
- Failure to identify and excise the pedicle attachment to the scapholunate ligament increases the likelihood of recurrence for dorsal wrist ganglions [1].
- A small, mucin-filled duct is invariably seen piercing the transverse fibers of the scapholunate ligament, connecting the underlying scapholunate joint with the main cyst [1].
- The radial artery is frequently intimately attached to the wall of a volar wrist ganglion and may be completely encircled by the ganglion [11].
- Some authors recommend leaving a portion of the volar ganglion cyst wall attached to the radial artery to avoid arterial injury [11].
- The best indication for arthroscopic treatment of a volar wrist ganglion is a sessile type arising from the radiocarpal joint and centered on the proximal wrist crease [12].
- Mobile volar ganglia with a long pedicle are poor candidates for arthroscopic surgery [12].
- Open excision of dorsal wrist ganglia leads to a lower recurrence rate than arthroscopic excision [25].
- Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes [35].
- Arthroscopic resection of dorsal wrist ganglia has low morbidity, with unnoticeable scars and wrist mobility and strength close to normal by three months [10].
- Arthroscopic resection of radiocarpal volar ganglia is a reasonable alternative to open excision with decreased postoperative morbidity, easy technique, and a high rate of good results [56].
- Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia [39].
- Surgical excision of primary wrist ganglia significantly reduces patient symptoms with low recurrence rates and high patient satisfaction [18].
- Open surgical excision offers a significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions [59].
- Female patients who have preoperative pain around dorsal wrist ganglia are the most likely to have residual pain after surgery [8].
- Patients whose occupation or activities require forceful wrist extension should be counseled on the considerable risk of residual pain and functional limitations that may occur after open dorsal wrist ganglion excision [26].
- Hand surgeons are divided regarding the need to immobilize the wrist after dorsal wrist ganglion excision [63].
Pediatric Management
- There is no consensus within the literature regarding the best management of pediatric wrist ganglia, and no single treatment modality confers a particular advantage or disadvantage over another [14].
- Surgical excision of pediatric hand and wrist ganglions is indicated for those that are symptomatic, do not resolve after approximately 2 months of observation and/or splinting, or recur [31].
Anatomy & Pathophysiology
Dorsal Wrist Ganglion
- Dorsal wrist ganglions may occur anywhere else between the extensor tendons, connected to the scapholunate ligament through an elongated pedicle [1].
- Failure to identify and excise the pedicle attachment to the scapholunate ligament increases the likelihood of recurrence [1].
- Although ganglions have been reported in other carpal joints, they are rare, and attachments to the scapholunate joint must be ruled out before a dissection is considered complete [1].
- Dorsal wrist ganglions can be confused with carpal bosses, which are osteoarthritic spurs or prominences that develop at the base of the second or third carpometacarpal joints [23].
- A small ganglion is associated with a carpal boss in 30% of cases [23].
- Unlike protruding dorsal ganglions, smaller, occult dorsal ganglions are easily overlooked and can often only be palpated with the involved wrist in marked volar flexion [64].
- An occult ganglion may be the cause of unexplained wrist pain and is disproportionately tender [64].
- Dorsal ganglions occasionally occur in association with an underlying scapholunate diastasis [64].
- Dorsal prominence of the proximal pole of the scaphoid secondary to intercarpal instability may be confused with a painful occult ganglion [64].
- Chronic tenosynovitis of the extensor tendons can be confused with a dorsal ganglion but is distinguished by the diffuse nature of the swelling and the puckering seen with digital extension, known as the tuck sign [64].
- Ganglions arising on or within extensor tendons typically occur over the metacarpals and are distinguished by their proximal motion with the fingers in extension [125].
- Two anomalous muscles, the anomalous extensor indicis proprius and the extensor digitorum brevis manus, may be found in the area of the dorsal wrist ganglion and can complicate management [151].
Volar Wrist Ganglion
- The volar wrist ganglion is the second most common ganglion of the hand and wrist, accounting for 18% to 20% of cases [11].
- The majority of volar ganglions occur either directly over the distal edge of the radius or slightly more distally over the scaphoid tubercle [11].
- Volar ganglions arising from the distal edge of the radius originate from the capsular and ligamentous fibers of the radiocarpal joint and occur under the volar wrist crease between the flexor carpi radialis and abductor pollicis longus tendons [11].
- The main cyst of a volar ganglion may be intertwined with bifurcating branches of the radial artery [11].
- Another type of volar ganglion arises from the capsule of the scaphotrapezial joint [11].
- Volar ganglions may appear small clinically but can be surprisingly extensive at surgery, with multiloculated cysts extending under the thenar muscles, along the flexor carpi radialis tendon, into the carpal canal, and under the first extensor compartment [11].
- The radial artery is frequently intimately attached to the wall of a volar ganglion and may even be completely encircled by the ganglion [11].
- The radioscaphocapitate and long radiolunate ligament interval may be the site of origin for the volar wrist ganglion [27].
- Ganglia arising from the interval between the radioscapocapitate (RSC) and long radiolunate (LRL) ligament appear at the more lateral aspect of the distal radius on arthrogram [12].
- Ganglia arising from the interval between the long radiolunate (LRL) and short radiolunate (SRL) ligaments appear at a more central position of the distal radius on arthrogram [12].
- Ganglia arising from the midcarpal joint or scaphotrapeziotrapezoid (STT) joint will not be revealed by an arthrogram of the radiocarpal joint unless an interosseous ligament at the proximal carpal row is ruptured [12].
Intraneural Ganglion
- Involvement of the peripheral nerves of the upper extremity by intraneural ganglion is rare [42].
- The ulnar nerve is the most commonly involved nerve in the upper extremity for intraneural ganglions [42].
- Most patients with intraneural ganglions are aged 30 to 50 years, though occurrence in children has also been reported [42].
- Most patients with intraneural ganglions present with a painless mass, while some may present with symptoms of nerve irritation or entrapment neuropathy [42].
- The articular (synovial) theory has gained worldwide acceptance as a scientifically proven explanation for the formation of intraneural ganglions [42].
Wrist Anatomy & Biomechanics
- The wrist is the anatomic region between the forearm and the hand, including the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones [69].
- The eight carpal bones include the scaphoid, lunate, triquetrum, and pisiform in the proximal row and the trapezium, trapezoid, capitate, and hamate in the distal row [69].
- The radiocarpal joints are formed by the articulation of the distal radius with the scaphoid and lunate through their respective concave facets on the distal radius and the triquetrum on the triangular fibrocartilage [69].
- The distal concave articular surfaces of the proximal carpal row form the midcarpal articulations with the distal row [69].
- The triangular fibrocartilage complex (TFCC) attaches to the base of the ulnar styloid and separates the hyaline cartilage–covered ulnar head from the styloid [69].
- The scapholunate interosseous ligament is C-shaped in the sagittal plane, with the dorsal third being the thickest and strongest portion [70].
- The volar portion of the lunotriquetral ligament is the thickest [70].
- The proximal carpal row has no muscular or tendinous attachments and is an intercalary segment [70].
- With axial loading through the neutral wrist, approximately 80% of forces are transmitted through the distal radius (60% scaphoid facet, 40% lunate facet) and 20% through the distal ulna [70].
- With wrist flexion, 60% of the motion is midcarpal and 40% is radiocarpal [70].
- With wrist extension, 33% of the motion is midcarpal and 66% is radiocarpal [70].
- The wrist can essentially be considered to be a two-joint system linking the hand to the forearm around the highly mobile bones of the proximal carpal row [71].
- The joints within the proximal carpal row govern 35% of the wrist extension-flexion arc and 33% of the wrist radial-ulnar deviation arc [94].
- Wrist ligaments co-ordinate the positioning of the bones in the mid-range of carpal motions and restrict further motion in extreme positions of the wrist joint [97].
- The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches with longitudinal connections [72].
- The dorsal intercarpal arch is the largest of the dorsal arches and supplies the distal carpal row and, through anastomoses with the radiocarpal arch, the lunate and triquetrum [72].
- The deep palmar arch at the level of the metacarpal bases is consistent and communicates with the dorsal basal metacarpal arch and the palmar metacarpal arteries [72].
- The distal radial articular surface has a double obliquity of 12–15 degrees in the lateral view and 15–20 degrees in the anteroposterior view [78].
- The carpus is more stable in flexion than extension due to its anterior concavity [78].
- The stability of the carpal bones relies largely on interosseous ligaments and bony configuration rather than tendon insertions, with the exception of the pisiform [78].
- The scaphoid presents a long axis inclined by 45 degrees to the long axis of the radius [78].
- The lunate sits on the capitate and has anterior and posterior horns, with a line drawn between them lying perpendicular to the long axis of the wrist in neutral position [78].
- The ulnar head sits proximal to the distal radius and has only an indirect effect on stability of the wrist [78].
- Extension of the wrist is dependent on the extensor carpi radialis longus (ECRL), extensor carpi radialis brevis (ECRB), and extensor carpi ulnaris (ECU) [79].
- The ECRB is the primary wrist extensor because it has the greatest tension and the most favorable moment arm [79].
- The ECU is an extensor of the wrist in supination and primarily causes ulnar deviation of the wrist in pronation [79].
- The moment arms for extension of the wrist are 16.30 mm for the ECRB and 12.50 mm for the ECRL [79].
- The moment arm for extension of the wrist by the ECU is 6.3 mm in supination and becomes zero when the wrist is in complete pronation [79].
- The most frequently used wrist movements are not in the axis of flexion–extension but in semipronation, with an oblique axis between the ECRL/ECRB and the flexor carpi ulnaris [79].
- The superficial branch of the radial nerve averages 16 mm (range 5 to 22 mm) from the 3-4 arthroscopic portal [27].
- The dorsal sensory branch of the ulnar nerve averages 8 mm (range 0 to 14 mm) from the 6R arthroscopic portal [27].
- The 1-2 arthroscopic portal carries a high risk of injury to the superficial branch of the radial nerve [27].
- The 6U arthroscopic portal carries a high risk of injury to the dorsal sensory branch of the ulnar nerve [27].
- The ideal working portal for arthroscopic excision of a dorsal wrist ganglion is the 3-4 portal with visualization from the 4-5 or 6R portals [27].
Pathophysiology & Diagnostic Associations
- Preoperative x-rays should be obtained as part of the routine workup for a dorsal wrist ganglion to rule out interosseous components or instability [22].
- MRI is useful in confirming the diagnosis of an occult dorsal ganglion and differentiating pain related to scapholunate ligament injury [64].
- Excising a dorsal ganglion alone might not alleviate all the patient’s preoperative pain if other causes of wrist pain and tenderness, especially directly over the scapholunate ligament, are present [64].
- An occult dorsal ganglion is best initially treated conservatively by immobilization and steroid injections directly into the dorsal capsule if other causes of wrist pain are excluded [64].
- Excision of the posterior interosseous nerve at the level of the radiocarpal joint may help alleviate pain and add to the patient’s postoperative comfort in cases of dorsal ganglion [64].
- Arthroscopic resection was an effective treatment method for well-selected volar wrist ganglion arising from the radiocarpal joint in the long run [20].
- Abnormal synovitis at the interligamentous sulcus is a hallmark of a volar ganglion from the radiocarpal joint [47].
- Pressing the ganglion externally should demonstrate bulging of the origin of the ganglion as viewed intraarticularly during arthroscopy [47].
- The complex nature of the wrist has plagued clinicians and hampered the ability to formulate concise, yet thorough, algorithmic approaches to evaluation and treatment [45].
- A wrist joint should be considered biomechanically unstable when it is not able to bear loads and does not exhibit normal kinematics throughout its arc of motion [67].
- The longitudinal 'columnar' concept of wrist kinematics does not fit in with many of the recent findings related to carpal instabilities [68].
- Traction (distraction) changes normal carpal kinematics and motion of the wrist combined with traction induces abnormal patterns of motion [73].
- Distal radial fractures that result in a loss of normal palmar tilt lead to progressive load on the ulnocarpal and radioscaphoid articulations [103].
- The most significant effect on radiocarpal joint contact characteristics occurs with a depression of the scaphoid side of the joint [110].
- Findings of abnormalities in the scapholunate joint were observed in 10 of 16 wrists with painful dorsal ganglia based on arthroscopic assessment [149].
- In most cases of dorsal wrist ganglion, there is a mild chronic 'sprain' of the scapholunate ligament which does not give rise to the well-recognised radiological and clinical features associated with scapholunate instability [149].
- Only one of 16 wrist radiographs showed radiological scapholunate widening in a study of painful dorsal ganglia [149].
- The anatomical configuration of ulnar nerve compression by a synovial cyst should be investigated if clinical signs do not improve following surgical decompression of the ulnar nerve at the wrist [32].
Classification
- In a selected patient group with recalcitrant dorsal wrist pain in the area of the scapholunate interval, occult dorsal wrist ganglions had a high prevalence of 11 of 14 [3].
- There is a significant prevalence of asymptomatic wrist ganglia, with 51% of 103 wrists scanned demonstrating ganglia [7].
- In a series of 543 ganglions of the hand and wrist, 57% occurred over the dorsal aspect of the wrist [65].
- In a series of 543 ganglions of the hand and wrist, 17% occurred over the volar aspect of the wrist [65].
- In a series of 543 ganglions of the hand and wrist, 26% occurred on the fingers [65].
- In a series of 543 ganglions of the hand and wrist, 7% were mucous cysts [65].
- Approximately 65% of anterior wrist ganglia arise from the radioscaphoid/scapholunate interval [48].
- Approximately 34% of anterior wrist ganglia arise from the scaphotrapezial joint [48].
- Ganglions in pediatric populations most commonly affect the dorsal wrist [28].
- In a longitudinal follow-up of 14 children less than 10 years old, 79% of all hand and wrist cysts spontaneously resolved, with the majority resolving within a year [37].
- The incidence of dorsal wrist ganglia was higher in the military population compared with the civilian population [40].
- In a series of 543 ganglions, 80% of patients were between twenty and fifty years of age [65].
- In a series of 543 ganglions, there were 363 females and 180 males, an almost 2 to 1 ratio [65].
- In a series of 543 ganglions, only one-fourth of patients complained of pain when first seen [65].
- In a series of 543 ganglions, the left and right hands were equally involved (242/257) [65].
- In a series of 543 ganglions, 90% were less than two centimeters in diameter [65].
- In a series of 543 ganglions, 50% were between 0.5 and 2.0 centimeters in diameter [65].
- In a series of 543 ganglions, the majority had been present for less than two years when patients sought attention [65].
- In a series of 543 ganglions, specific injury related to the onset of the ganglion occurred in only fifty patients [65].
- Ganglions may arise from a variety of additional sites over the dorsal wrist capsule, particularly in the region of the capitate, although a scapholunate origin is usual [15].
- Ganglions arising from wrist joints can present as painless masses in the center of the palm without signs or symptoms of median or ulnar nerve compression [17].
- The ulnar nerve is the most commonly involved nerve in the upper extremity by intraneural ganglion [42].
- Most patients with intraneural ganglions are aged 30 to 50 years, but occurrence in children has also been reported [42].
- Most patients with intraneural ganglions present with a painless mass, though some may present with symptoms of nerve irritation or entrapment neuropathy [42].
Clinical Presentation
Dorsal Wrist Ganglion
- The dorsal wrist ganglion accounts for 60% to 70% of all hand and wrist ganglions [1].
- Dorsal wrist ganglions may occur anywhere else between the extensor tendons, connected to the scapholunate ligament by an elongated pedicle [1].
- Transillumination or aspiration confirms the diagnosis of a dorsal wrist ganglion preoperatively [1].
- Review of preoperative radiographs is wise to rule out an interosseous component in dorsal wrist ganglions [1].
- MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard [38].
- Female patients who have preoperative pain around dorsal wrist ganglia were the most likely to have residual pain after surgery [8].
- Although a scapholunate origin is usual, ganglia may also arise from a variety of additional sites over the dorsal wrist capsule, particularly in the region of the capitate [15, 16].
- A dorsal wrist ganglion can present preoperatively as an anterior wrist ganglion [19].
- The incidence of dorsal wrist ganglia was higher in the military compared with the civilian population [40].
Volar Wrist Ganglion
- The volar wrist ganglion is the second most common ganglion of the hand and wrist, accounting for 18% to 20% [11].
- Volar ganglions arising from the distal edge of the radius occur under the volar wrist crease between the flexor carpi radialis and abductor pollicis longus tendons [11].
- Volar ganglions arising from the scaphotrapezial joint capsule are a distinct type from those arising from the radiocarpal joint [11].
- Although volar ganglions may appear small clinically, they can be surprisingly extensive at surgery, with multiloculated cysts extending under the thenar muscles, along the flexor carpi radialis tendon, into the carpal canal, and under the first extensor compartment [11].
- Extensions of volar ganglions can often be appreciated preoperatively by careful palpation and digital compression [11].
- Unlike previous surgical and pathological series, an MRI study showed volar wrist ganglia are more common than dorsal wrist ganglia in an asymptomatic population [2].
- Wrist joint ganglions can present as painless masses in the center of the palm without signs or symptoms of median or ulnar nerve compression [17].
General Characteristics and Epidemiology
- There is a significant prevalence of asymptomatic wrist ganglia, with 51% of the 103 wrists scanned demonstrating ganglia [7].
- Ganglions in pediatric populations, which most commonly affect the dorsal wrist, demonstrate a female predilection [28].
- In children aged <10 years, ganglions mainly occur on the volar wrist [33].
- In children aged <10 years, 69% to 79% of ganglions display spontaneous regression within a span of 12-18 months [33].
- In a cohort of 14 children less than 10 years old, 79% of all cysts spontaneously resolved, the majority within a year [37].
- Ganglia are the most common benign soft tissue tumours of the hand [44].
- The majority of ganglia resolve spontaneously over 1 to 2 years [44].
- In a study of 50 patients with ganglia, 38% were concerned about the cosmetic appearance and 28% were concerned that their ganglion was a malignant growth [44].
- A minority of patients sought advice and treatment for ganglia because of pain [44].
Differential Diagnosis and Imaging
- The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [5].
- It is suggested that preoperative x-rays should be obtained as part of the routine workup for a dorsal wrist ganglion [22].
- Sonography can localize occult ganglia [66].
- Preoperative ultrasound scanning helps to confirm the articular origin and nature of the cystic mass for volar wrist ganglions [12].
Investigations
Clinical Examination and Physical Diagnosis
- Careful preoperative palpation of the cyst with digital compression often reveals its extent and the direction of the pedicle [1].
- Transillumination or aspiration confirms the diagnosis preoperatively [1].
- A firm, bony, nonmobile, tender mass visible and palpable at the base of the carpometacarpal joints, especially when the wrist is flexed, is characteristic of a carpal boss [23].
- Dorsal wrist ganglions can be confused with carpal bosses [23].
Radiography
- Review of the patient's preoperative radiographs to rule out an interosseous component is wise [1].
- The mass of a carpal boss is best visualized radiologically with the hand in 30 to 40 degrees of supination and 20 to 30 degrees of ulnar deviation ("carpal boss view") [23].
Magnetic Resonance Imaging (MRI)
- In a selected patient group with recalcitrant dorsal wrist pain in the area of the scapholunate interval, occult dorsal wrist ganglions had a high prevalence (11 of 14) [3].
- MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes [109].
- Convolutional neural networks (CNNs) can detect ganglion cysts in wrist MRI [136].
- Unlike previous surgical and pathological series, an MRI study of an asymptomatic population showed volar wrist ganglia are more common than dorsal wrist ganglia [2].
Arthrography and Arthroscopy
- A wrist arthrogram can be performed immediately prior to arthroscopic intervention or as a separate investigative procedure for volar wrist ganglions [12].
- Intraoperative arthrogram of a ganglion arising from the radiocarpal joint involves injecting 3 to 5 cc of nonionic contrast solution admixed with 2% lidocaine into the radiocarpal joint at the 3-4 portal site under fluoroscopic guidance [12].
- The relative position of the contrast-filling stalk on arthrogram can aid the identification of the true stalk during the actual arthroscopic procedure [12].
- Ganglia arising from the midcarpal joint or scaphotrapeziotrapezoid (STT) joint will not be revealed by arthrogram of the radiocarpal joint unless an interosseous ligament at the proximal carpal row is ruptured and creates a free communication between the radiocarpal and midcarpal joints [12].
- Arthroscopy is not the gold standard for the diagnosis of carpal ganglia because the majority of the cyst is found either subcutaneously or at the point of the capsular attachment to the proximal carpal row, external to the wrist joint [62].
- Sonography-assisted arthroscopic resection is a safer and more reliable method for treating volar wrist ganglia [21].
Treatment
Non-Operative Management
- The spontaneous resolution rate for wrist ganglia is reported as 28% to 58% [106].
- Aspiration treatment of ganglion cysts of the wrist and hand can safely remove 85% of these tumors if one, two, or three separate treatments are administered [95].
- Aspiration with or without cortisone injection has an average success rate of 35% to 50% [106].
- In a study of 50 patients, 74% were satisfied with aspiration of the ganglion and general advice [44].
- Although aspiration with triamcinolone acetonide injection plus wrist immobilization is an alternative method, surgery was the most successful form of treatment when considering the cure rate of dorsal wrist ganglion [84].
- In children aged <10 years, ganglions mainly occur on the volar wrist and can be treated expectantly, with 69% to 79% displaying spontaneous regression within a span of 12-18 months [33].
- While observation and/or splinting will likely be helpful in resolution of a majority of pediatric hand and wrist ganglions, surgical excision is indicated for those that are symptomatic, do not resolve after approximately 2 months of observation and/or splinting, or recur [31].
- An occult dorsal ganglion is best initially treated conservatively by immobilization and steroid injections directly into the dorsal capsule, which can also aid in diagnosis [64].
Operative Management: Dorsal Wrist Ganglion
- Failure to identify the pedicle and excise its attachment to the scapholunate ligament increases the likelihood of recurrence [1].
- Most dorsal ganglions can be approached through a transverse incision over the proximal carpal row [1].
- The diagnosis of ganglion cyst should be made before commitment to a transverse incision because this type of incision is not readily incorporated into a limb-sparing incision in the event of a subsequent diagnosis of a malignant soft tissue tumor [1].
- Typically, a dorsal ganglion appears between the extensor pollicis longus and extensor digitorum communis tendons [1].
- The main cyst and its pedicle are mobilized down to the underlying joint capsule [1].
- With the wrist in volar flexion, the joint capsule is opened along the border of the radius and scaphoid's proximal pole [1].
- The capsular incision is extended more laterally if any capsular ducts, which can be identified by small amounts of mucin drainage, are encountered during the dissection [1].
- The ganglion and its capsular attachments are tangentially excised off the scapholunate ligament [1].
- A small, mucin-filled duct is invariably seen piercing the transverse fibers of the scapholunate ligament [1].
- Synovial and capsular attachments along the distal margin of the scapholunate ligament are excised to give an unobstructed view of the head and neck of the capitate [1].
- The key to successful open treatment is excision of the ganglion stalk based at the scapholunate ligament and its associated dorsal-capsular attachments [106].
- Open ganglionectomy creates a defect in the capsule of 1 to 1.5 cm, which is left open [106].
- The rate of recurrence for open ganglionectomy can be as high as 40% [106].
- Stiffness has been reported from prolonged immobilization following open ganglionectomy [106].
- Excision of the posterior interosseous nerve at the level of the radiocarpal joint may help alleviate the pain and add to the patient’s postoperative comfort in cases of occult dorsal ganglion [64].
- Excising the ganglion alone might not alleviate all the patient’s preoperative pain if an occult dorsal ganglion is associated with underlying scapholunate diastasis [64].
- Dorsal ganglions occasionally occur in association with an underlying scapholunate diastasis, and they may be blamed for the carpal instability after their excision [64].
- In the treatment of dorsal wrist ganglion, surgery was the most successful form of treatment when considering the cure rate compared to aspiration with triamcinolone acetonide injection plus wrist immobilization [84].
- The quality of care would not be compromised by abandoning the practice of routine submission of surgical specimens for pathological examination after excision of the ganglion cyst in patients with the clinical diagnosis of wrist ganglion cyst [137].
- Following a dorsal incision distal to Lister’s tubercle, the extensor retinaculum between the tendons of the second and fourth extensor compartments is incised, the ganglion identified and its root followed to the dorsal capsule, and a small arthrotomy is performed over the scapholunate ligament [131].
- Complete excision of the ganglion along with its capsule is performed with local synovectomy [131].
- The capsule is either fenestrated or sutured, depending on the surgeon [131].
- After skin closure, a compressive dressing is applied and left in place for 3 days [131].
- Active mobilization of the wrist starts after the dressing is changed by the hand therapist [131].
- Sutures are removed 10 to 14 days postoperatively [131].
- Splints are not used on a regular basis after dorsal wrist ganglion excision [131].
- After 3 weeks, patients start with a stabilizing and strength programme under the guidance of the hand therapist [131].
Operative Management: Volar Wrist Ganglion
- The main cyst of a volar ganglion arising from the radiocarpal joint may be intertwined with bifurcating branches of the radial artery [11].
- The Allen test should be performed routinely and ulnar artery occlusion excluded before volar ganglion excision [11].
- The surgeon must be aware of the importance of preserving the radial artery, particularly in patients with a radial-dominant circulation [11].
- Longitudinal incisions allow for optimal visualization during volar ganglion excision [11].
- The radial artery is frequently intimately attached to the wall of the volar ganglion and may even be completely encircled by the ganglion [11].
- Loupe magnification aids in the dissection of the radial artery from the volar ganglion [11].
- The pedicle is traced to the volar joint capsule, usually the scaphotrapezial or radiocarpal ligament [11].
- The joint is opened and explored and the ganglion attachments are excised approximately 3 ± 4 mm [11].
- Once the ganglion has been excised, the surrounding tissues can be compressed digitally to rule out further mucin-filled pockets [11].
- Capsular closure is unnecessary and only delays early mobilization after volar ganglion excision [11].
- Motion of the wrist should begin within the first 2 weeks after volar ganglion surgery [11].
- Unexpected branches of the radial sensory or lateral antebrachial cutaneous nerves may be injured during volar ganglion excision and lead to troublesome neuromas [11].
- Extensions of the routine incision into the carpal canal must avoid injury to the palmar cutaneous branch of the median nerve [11].
- Injuries to the radial artery can be repaired microscopically [11].
- Some authors recommend leaving a portion of the cyst wall attached to the radial artery to avoid arterial injury [11].
- Stiffness of the wrist is less common than with dorsal ganglions but can occur if early motion is not encouraged [11].
- Curved incisions appear to consistently provide more attractive scars, especially near the volar wrist creases [11].
- Arthroscopic resection of radiocarpal volar ganglia is a reasonable alternative to open excision with decreased postoperative morbidity, easy technique, and high rate of good results [56].
- The best indication for arthroscopic volar wrist ganglionotomy is a sessile type of volar wrist ganglion arising from the radiocarpal joint and centered on the proximal wrist crease [12].
- Mobile ganglia with long pedicle are poor candidates for arthroscopic surgery [12].
- Preoperative ultrasound scanning helps to confirm the articular origin and nature of the cystic mass for volar ganglions [12].
- Arthroscopic drainage of a ganglion from the STT joint is feasible with the addition of new portals [12].
- A wrist arthrogram can be performed immediately prior to the arthroscopic intervention or as a separate investigative procedure to confirm the connection of the ganglion with the wrist joint [12].
- Ganglia arising from the interval between the RSC and the LRL ligament will show up at the more lateral aspect of the distal radius during arthrogram [12].
- Ganglia arising from the interval between the LRL and SRL ligaments will show up at a more central position of the distal radius during arthrogram [12].
- Ganglia arising from the midcarpal joint or STT joint will not be revealed by arthrogram of the radiocarpal joint unless one of the interosseous ligaments at the proximal carpal row is ruptured [12].
- For a right-handed surgeon operating on the right wrist, the scope entry site is typically 1-2 and the working portal is 3-4 [12].
- The author prefers to perform arthroscopic volar wrist ganglionotomy under PSLA without the use of a tourniquet to monitor any possible iatrogenic damage to the radial artery [12].
- Pressing the ganglion externally should demonstrate bulging of the origin of the ganglion as viewed intraarticularly [47].
- The ligament interval with abnormal synovitis should be shaved, but not the ligament itself, to abolish the abnormal check-valve of the ganglion [47].
- The cyst wall should not be shaved during arthroscopic volar ganglionotomy as the radial artery is at risk [47].
- The tip of the shaver should be palpated through the volar surface of the wrist to avoid accidental damage to the flexor tendons and radial artery [47].
- If the surgery is performed under PSLA without tourniquet, the radial pulse is checked intermittently to ensure its integrity [47].
- Overaggressive shaving may cause injury to the volar radiocarpal ligaments [47].
- Attempted shaving of the cyst wall may cause radial artery damage and bleeding [47].
- Inadequate instruction to the patient on massaging the ganglionotomy site at the postoperative period may lead to persistence of pseudorecurrence of the ganglion [47].
- No stitch is required for wound closure to optimize the scar appearance after arthroscopic volar ganglionotomy [47].
- Compressive bandaging is applied for 2 days to reduce saline swelling [47].
- The patient should be informed about the possibility of pseudorecurrence phenomenon of up to 3 weeks postoperative and be instructed to do daily regular massage at the ganglionotomy site [47].
- Further shaving of the stalk until a capsular defect of 5 to 10 mm is made, with an aim to abolish the pathologic valve phenomenon [47].
- One should avoid passing the shaver too anteriorly to endanger the superficial branch of the radial artery during STT ganglion decompression [47].
- The decompression of a ganglion arising from the STT interval is generally more difficult compared with the standard volar ganglion [47].
- A small arthroscope of 1.9 mm and small shaver of 2 mm are mandatory for STT interval ganglion decompression [47].
Operative Management: Arthroscopic Dorsal Wrist Ganglion
- Arthroscopic excision of dorsal wrist ganglia leads to a higher recurrence rate than open excision [25].
- The outcomes, recurrence, and complications rates after 4 years of follow-up support the use of arthroscopy as a treatment for dorsal wrist ganglion [29].
- The proposed classification of ganglia helps minimize the area of resection required in arthroscopic treatment [36].
- Arthroscopic treatment of a dorsal wrist ganglion is a good alternative to open surgery, though it is a difficult procedure requiring adequate experience [99].
- Arthroscopic resection of wrist ganglia is a safe technique allowing a satisfactory resection of the cyst and the adjoining joint capsule [101].
- Advancements in wrist arthroscopy have lowered the recurrence rates of dorsal wrist ganglions [124].
- The superficial branch of the radial nerve averages 16 mm (5 to 22 mm) from the 3-4 portal [27].
- The dorsal sensory branch of the ulnar nerve averages 8 mm (0 to 14 mm) from the 6R portal [27].
- The 1-2 portal carries a high risk of injury to the superficial branch of the radial nerve [27].
- The 6U portal carries a high risk of injury to the dorsal sensory branch of the ulnar nerve [27].
- Arthroscopy of the wrist typically is safe, with minor and transient complications [27].
- Nerve injury is a complication related to portal placement or suture of the TFCC, typically affecting the dorsal sensory branch of the radial or ulnar nerve [27].
- Infection is an uncommon complication of wrist arthroscopy [27].
- ECU tendinitis may be related to portal placement or the suture knot after TFCC repair [27].
- Tendon injury may result from improper portal placement [27].
- Metacarpophalangeal joint pain is typically caused by overdistraction and is transient [27].
- Wrist stiffness is an uncommon complication of uncertain etiology [27].
- The author prefers arthroscopic dorsal wrist ganglionotomy to be performed under PSLA as it minimizes the anesthetic risk to the patient [127].
- Tourniquet is not essential for arthroscopic dorsal wrist ganglionotomy as bleeding is rarely a problem [127].
- A 1.9 mm arthroscope is preferred to improve scar appearance in arthroscopic dorsal wrist ganglionotomy [127].
- Two portals are made at 1-2 and 6R for arthroscopic dorsal wrist ganglionotomy [127].
- Lidocaine is infiltrated around the stalk of the ganglion near 3-
Complications
Dorsal Wrist Ganglion Excision
- Patients whose occupation or activities require forceful wrist extension should be counseled on the considerable risk of residual pain and functional limitations after open dorsal wrist ganglion excision [26].
- Female patients with preoperative pain around dorsal wrist ganglia are the most likely to have residual pain after surgery [8].
- Surgical intervention for wrist ganglions has about a 10% recurrence rate, leaves scars, and carries some risk for adverse events [114].
Volar Wrist Ganglion Excision
- Unexpected branches of the radial sensory or lateral antebrachial cutaneous nerves may be injured during volar wrist ganglion excision, leading to troublesome neuromas [11].
- Injuries to the radial artery during volar wrist ganglion excision can be repaired microscopically [11].
- Wrist stiffness is less common with volar ganglion excision than with dorsal ganglion excision but can occur if early motion is not encouraged [11].
- Unpleasant scars are not an uncommon problem following volar wrist ganglion excision, particularly on the curved volar aspect of the wrist [11].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the ganglion being distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [120].
Arthroscopic Complications
- Nerve injury during wrist arthroscopy is related to portal placement or suture of the TFCC and typically affects the dorsal sensory branch of the radial or ulnar nerve [27].
- Improper portal placement during wrist arthroscopy may result in tendon injury [27].
- Wrist stiffness is an uncommon complication of wrist arthroscopy of uncertain etiology [27].
- Overaggressive shaving during arthroscopic volar wrist ganglionotomy may cause injury to the volar radiocarpal ligaments [47].
- Attempted shaving of the cyst wall during arthroscopic volar wrist ganglionotomy may cause radial artery damage and bleeding [47].
- Inadequate instruction to the patient on massaging the ganglionotomy site postoperatively may lead to persistence of pseudorecurrence of the ganglion [47].
General and Pediatric Considerations
- In children aged <10 years, 69% to 79% of volar wrist ganglions display spontaneous regression within a span of 12-18 months [33].
Recovery
Postoperative Care and Mobilization
- A bulky bandage and elevation of the hand are used to ensure early postoperative comfort following volar wrist ganglion excision [11].
- Wrist motion should begin within the first 2 weeks after volar wrist ganglion surgery [11].
- Capsular closure is unnecessary after volar wrist ganglion excision and only delays early mobilization [11].
- Wrist mobility and strength are close to normal by three months following arthroscopic resection of dorsal wrist ganglia [10].
Outcomes and Functional Recovery
- At 8-month follow-up, a patient with a dorsal wrist ganglion associated with extensor digitorum brevis manus remained pain free with no ganglion recurrence or functional limitations [118].
Complications and Adverse Events
- Stiffness of the wrist is less common than with dorsal ganglions but can occur if early motion is not encouraged after volar wrist ganglion excision [11].
- Unexpected branches of the radial sensory or lateral antebrachial cutaneous nerves may be injured during volar wrist ganglion excision and lead to troublesome neuromas [11].
- Unpleasant scars are not an uncommon problem after volar wrist ganglion excision, particularly on the curved volar aspect of the wrist [11].
- Arthroscopic resection of dorsal wrist ganglia has low morbidity, with unnoticeable scars [10].
Key Evidence
- [L4] Unlike previous surgical and pathological series, our study showed volar wrist ganglia are more common than dorsal wrist ganglia. [2] (10.1197/j.jht.2003.10.037)
- [L4] In our selected patient group (recalcitrant dorsal wrist pain in the area of the scapholunate interval), occult dorsal wrist ganglions had a high prevalence (11 of 14). [3] (10.1016/s0363-5023(05)80288-6)
- [L4] Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist. [4] (10.1016/j.jhsa.2023.07.002)
- [L4] The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings. [5] (10.1007/s11552-007-9032-8)
- [L2] Neither surgical excision nor aspiration provides a clear long-term benefit over the natural history of the dorsal wrist ganglion. [6] (10.1016/j.jhse.2007.05.007)
- [L4] There is a significant prevalence of asymptomatic wrist ganglia, with 51% of the 103 wrists scanned demonstrating ganglia. [7] (10.1016/j.jhsb.2005.02.012)
- [L4] Female patients who have preoperative pain around dorsal wrist ganglia were the most likely to have residual pain after surgery. [8] (10.1016/j.arthro.2013.04.002)
- [L4] Arthroscopic resection of dorsal wrist ganglia has low morbidity, with unnoticeable scars and wrist mobility and strength close to normal by three months. [10] (10.1016/j.main.2006.07.006)
- [L4] A systematic X-ray should be performed for painful dorsal wrist ganglia. [13] (10.1016/j.main.2003.12.005)
- [L4] There is no consensus within the literature regarding the best management of pediatric wrist ganglia, and no single treatment modality confers a particular advantage or disadvantage over another. [14] (10.1177/1558944720966716)
- [L4] Although a scapholunate origin is usual, ganglia may also arise from a variety of additional sites over the dorsal wrist capsule, particularly in the region of the capitate. [15] (10.1016/0266-7681_88_90135-0)
- [L4] Although a scapholunate origin is usual, ganglia may also arise from a variety of additional sites over the dorsal wrist capsule, particularly in the region of the capitate. [16] (10.1016/0266-7681(88)90135-0)
- [L4] We report 2 cases of ganglions arising from wrist joints that presented as painless masses in the center of the palm without signs or symptoms of median or ulnar nerve compression. [17] (10.1016/j.jhsa.2003.11.006)
- [L4] Surgical excision of primary wrist ganglia significantly reduces patient symptoms with low recurrence rates and high patient satisfaction. [18] (10.1177/1753193411434376)
- [L5] The case demonstrates that a dorsal wrist ganglion can present preoperatively as an anterior wrist ganglion. [19] (10.1016/0363-5023(94)90096-5)
- [L4] Arthroscopic resection was an effective treatment method for well-selected volar wrist ganglion arising from the radiocarpal joint in long run. [20] (10.1016/j.main.2006.07.028)
- [Paper] This method is safer and more reliable for treating volar wrist ganglia. [21] (10.1016/j.eats.2011.12.007)
- [L5] It is suggested that preoperative x-rays should be obtained as part of the routine workup for a dorsal wrist ganglion. [22] (10.1016/s0363-5023(83)80096-3)
- [L3] This study suggests that open excision of dorsal wrist ganglia leads to a lower recurrence rate than does arthroscopic excision. [25] (10.1177/15589447211003184)
- [L4] Patients whose occupation or activities require forceful wrist extension should be counseled on the considerable risk of residual pain and functional limitations that may occur after open dorsal wrist ganglion excision. [26] (10.1016/j.jhsa.2015.05.030)
- [L2] Ganglions in pediatric populations, which most commonly affect the dorsal wrist, demonstrate a female predilection. [28] (10.1016/j.jhsa.2021.02.026)
- [L4] The outcomes, recurrence, and complications rates after 4 years of follow-up presented in this study support the use of arthroscopy as a treatment for dorsal wrist ganglion. [29] (10.1177/1558944717743601)
- [L4] While observation and/or splinting will likely be helpful in resolution of a majority of pediatric hand and wrist ganglions, surgical excision is indicated for those that are symptomatic, do not resolve after approximately 2 months of observation and/or splinting, or recur. [31] (10.1007/s11552-008-9122-2)
- [L5] This anatomical configuration should be investigated if clinical signs do not improve following surgical decompression of the ulnar nerve at the wrist. [32] (10.1016/s1297-3203(02)00123-3)
- [L4] In children aged <10 years, ganglions mainly occur on the volar wrist and can be treated expectantly, with 69% to 79% displaying spontaneous regression within a span of 12-18 months. [33] (10.1016/j.jhsa.2021.12.015)
- [L3] Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes. [35] (10.1177/17531934251405730)
- [L4] The proposed classification of ganglia helps minimize the area of resection required. [36] (10.1054/jhsb.2001.0620)
- [L4] [37] (10.1053/jhsu.2001.26141)
- [L3] MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard. [38] (10.1177/1753193408092041)
- [L4] Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia. [39] (10.1016/j.arthro.2009.08.021)
- [L3] The incidence of dorsal wrist ganglia was higher in the military compared with the civilian population. [40] (10.1016/j.jhsg.2020.08.001)
- [L4] [42] (10.1016/j.jhsa.2015.05.025)
- [L4] [44] (10.1054/jhsb.2000.0504)
- [Paper] The complex nature of the wrist has plagued us clinically and hampered our ability to formulate concise, yet thorough, algorithmic approaches to evaluation and treatment. [45] (10.1016/s0894-1130(96)80065-2)
- [L4] This study demonstrates that approximately 65% of anterior wrist ganglia arise from the radioscaphoid/scapholunate interval, with 34% arising from the scaphotrapezial joint. [48] (10.1016/0363-5023(92)90358-v)
- [L1] The arthroscopic resection of radiocarpal volar ganglia is a reasonable alternative to open excision with decreased postoperative morbidity, easy technique, and high rate of good results. [56] (10.1080/02844310802210897)
- [L1] Open surgical excision offers significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions. [59] (10.1016/j.jhsa.2014.12.014)
- [L5] They argue that arthroscopy is not the gold standard for the diagnosis of carpal ganglia because the majority of the cyst is found either subcutaneously or at the point of the capsular attachment to the proximal carpal row, external to the wrist joint. [62] (10.1016/j.jhsa.2004.06.002)
- [L2] The systematic review and survey of Canadian hand surgeons reveal that hand surgeons are divided regarding the need to immobilize the wrist after dorsal wrist ganglion excision. [63] (10.1177/15589447211014631)
- [L4] [65] (10.2106/00004623-197254070-00009)
- [L5] A wrist joint should be considered biomechanically unstable when it is not able to bear loads and does not exhibit normal kinematics throughout its arc of motion. [67] (10.1053/jhsu.1999.0866)
- [L5] The longitudinal 'columnar' concept of wrist kinematics does not fit in with many of the recent findings related to carpal instabilities. [68] (10.1016/s0363-5023(83)80025-2)
- [L5] Traction (distraction) changes normal carpal kinematics and motion of the wrist combined with traction induces abnormal patterns of motion. [73] (10.1053/jhsu.1999.jhsu24a0113)
- [Paper] Although aspiration with triamcinolone acetonide injection plus wrist immobilization is an alternative method, surgery was the most successful form of treatment when considering the cure rate of dorsal wrist ganglion. [84] (10.1007/s12593-011-0039-6)
- [L5] The joints within the proximal carpal row govern 35% of the wrist extension-flexion arc and 33% of the wrist radial-ulnar deviation arc. [94] (10.1016/0363-5023(90)90101-v)
- [L2] Aspiration treatment of ganglion cysts of the wrist and hand can safely remove 85% of these tumors if one, two or three separate treatments are administered. [95] (10.1016/s0363-5023(87)80221-6)
- [L5] Wrist ligaments co-ordinate the positioning of the bones in the mid-range of carpal motions, and restrict further motion in extreme positions of the wrist joint. [97] (10.1016/0266-7681(93)90015-8)
- [L4] Arthroscopic treatment of a dorsal wrist ganglion is a good alternative to open surgery, though it is a difficult procedure requiring adequate experience. [99] (10.1054/jhsb.1999.0290)
- [L4] Arthroscopic resection of wrist ganglia is a safe technique allowing a satisfactory resection of the cyst and the adjoining joint capsule. [101] (10.1016/s0363-5023(03)80308-8)
- [L5] Distal radial fractures that result in a loss of normal palmar tilt lead to progressive load on the ulnocarpal and radioscaphoid articulations. [103] (10.1016/s0363-5023(87)80202-2)
- [L4] [106] (10.1016/s0749-0712(21)00020-2)
- [L4] MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes. [109] (10.1007/s11552-007-9083-x)
- [L5] The most significant effect on radiocarpal joint contact characteristics occurs with a depression of the scaphoid side of the joint. [110] (10.1016/s0363-5023(96)80003-7)
- [L5] Current best evidence suggests that about 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon, that most ganglions recur after aspiration, and that surgical intervention has about a 10% recurrence rate, leaves scars, and has some risk for adverse events. [114] (10.1016/j.jhsa.2010.11.048)
- [L5] At 8-month follow-up, the patient remained pain free with no ganglion recurrence or functional limitations. [118] (10.1142/s0218810417200222)
- [L3] The operation-related complications after arthroscopic volar wrist ganglionectomy are associated with its anatomical location: distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer. [120] (10.1186/s12891-025-08766-x)
- [L2] [131] (10.1177/17531934231153029)
- [L4] CNNs can detect ganglion cysts in wrist MRI. [136] (10.1186/s12891-025-09011-1)
- [L4] In patients with the clinical diagnosis of wrist ganglion cyst, the quality of care would not be compromised by abandoning the practice of routine submission of surgical specimens for pathological examination after excision of the ganglion cyst. [137] (10.1016/s0363-5023(10)60107-4)
- [L4] [149] (10.1080/028443101750523267)
- [L5] [151] (10.1016/s0363-5023(79)80111-2)
References
[1] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Dorsal Wrist Ganglion.
[2] The prevalence of wrist ganglia in an asymptomatic population: magnetic resonance imaging evaluation. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2003.10.037
[3] Evaluating dorsal wrist pain: MRI diagnosis of occult dorsal wrist ganglion. The Journal of Hand Surgery. 1995. DOI: 10.1016/s0363-5023(05)80288-6
[4] Natural History of Pediatric Hand and Wrist Ganglion Cysts: Longitudinal Follow-Up of a Prospective, Dual-Center Cohort. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.002
[5] The Use of Routine Wrist Radiography is Not Useful in the Evaluation of Patients with a Ganglion Cyst of the Wrist. HAND. 2007. DOI: 10.1007/s11552-007-9032-8
[6] The Natural History of Untreated Dorsal Wrist Ganglia and Patient Reported Outcome 6 Years after Intervention. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.05.007
[7] The Prevalence of Wrist Ganglia in an Asymptomatic Population: Magnetic Resonance Evaluation. Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsb.2005.02.012
[8] Arthroscopic Excision of Dorsal Wrist Ganglion: Factors Related to Recurrence and Postoperative Residual Pain. Arthroscopy. 2013. DOI: 10.1016/j.arthro.2013.04.002
[10] Traitement arthroscopique des kystes synoviaux dorsaux du poignet. Chirurgie de la Main. 2006. DOI: 10.1016/j.main.2006.07.006
[11] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Volar Wrist Ganglion.
[12] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Volar Wrist Ganglion.
[13] Les kystes synoviaux intra-osseux du semi-lunaire : problèmes diagnostiques. Chirurgie de la Main. 2004. DOI: 10.1016/j.main.2003.12.005
[14] Wrist Ganglion Cysts in Children: An Update and Review of the Literature. HAND. 2022. DOI: 10.1177/1558944720966716
[15] The Treatment of Dorsal Wrist Ganglia by Radical Excision. Journal of Hand Surgery. 1988. DOI: 10.1016/0266-7681_88_90135-0
[16] The treatment of dorsal wrist ganglia by radical excision. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90135-0
[17] Wrist joint ganglion presenting as a painless mass in the palm: report of 2 cases. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.11.006
[18] Patient outcomes following wrist ganglion excision surgery. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193411434376
[19] Dorsal wrist ganglion presenting as anterior wrist ganglion. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90096-5
[20] Résection des kystes synoviaux palmaires par arthroscopie. Chirurgie de la Main. 2006. DOI: 10.1016/j.main.2006.07.028
[21] Sonography‐Assisted Arthroscopic Resection of Volar Wrist Ganglia: A New Technique. Arthroscopy Techniques. 2012. DOI: 10.1016/j.eats.2011.12.007
[22] Rotatory subluxation of the scaphoid after excision of dorsal carpal ganglion and wrist manipulation—A case report. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80096-3
[23] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Carpmetacarpal Boss.
[25] Recurrence Rates of Dorsal Wrist Ganglion Cysts After Arthroscopic Versus Open Surgical Excision: A Retrospective Comparison. HAND. 2021. DOI: 10.1177/15589447211003184
[26] Outcomes of Open Dorsal Wrist Ganglion Excision in Active-Duty Military Personnel. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.05.030
[27] Aaos Comprehensive Orthopaedic Review 3. Wrist Arthroscopy > V. Complications.
[28] Clinical Presentation and Characteristics of Hand and Wrist Ganglion Cysts in Children. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.02.026
[29] Arthroscopic Resection of Dorsal Wrist Ganglion: Results and Rate of Recurrence Over a Minimum Follow-up of 4 Years. HAND. 2017. DOI: 10.1177/1558944717743601
[31] Pediatric Ganglion Cysts of the Hand and Wrist: An Epidemiologic Analysis. HAND. 2008. DOI: 10.1007/s11552-008-9122-2
[32] Compression de la branche profonde du nerf ulnaire par un kyste synovial. À propos d'un cas. Chirurgie de la Main. 2002. DOI: 10.1016/s1297-3203(02)00123-3
[33] Pediatric Ganglions of the Hand and Wrist: A Review of Current Literature. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.12.015
[35] Arthroscopic resection of dorsal wrist ganglions with or without midcarpal exploration. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251405730
[36] Arthroscopic Diagnosis and Treatment of Dorsal Wrist Ganglion. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2001.0620
[37] Longitudinal observation of pediatric hand and wrist ganglia. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.26141
[38] Magnetic Resonance Imaging in the Diagnosis of Occult Dorsal Wrist Ganglions. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408092041
[39] Arthroscopic Ganglionectomy Through an Intrafocal Cystic Portal for Wrist Ganglia. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.08.021
[40] Epidemiology of Symptomatic Dorsal Wrist Ganglia in Active Duty Military and Civilian Populations. Journal of Hand Surgery Global Online. 2020. DOI: 10.1016/j.jhsg.2020.08.001
[42] Intraneural Ganglions of the Hand and Wrist. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.05.025
[44] Ganglia: The Patient’s Perception. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.2000.0504
[45] The Mysterious Wrist. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80065-2
[47] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic Volar Wrist Ganglionotomy.
[48] Anterior wrist ganglia from the scaphotrapezial joint. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90358-v
[56] Articular ganglia of the volar aspect of the wrist: Arthroscopic resection compared with open excision. A prospective randomised study. Scandinavian Journal of Plastic and Reconstructive Surgery and Hand Surgery. 2008. DOI: 10.1080/02844310802210897
[59] Wrist Ganglion Treatment: Systematic Review and Meta-Analysis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.014
[62] Arthroscopic ganglionectomy?. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.06.002
[63] Immobilization of the Wrist After Dorsal Wrist Ganglion Excision: A Systematic Review and Survey of Current Practice. HAND. 2021. DOI: 10.1177/15589447211014631
[64] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Occult Dorsal Carpal Ganglion.
[65] Ganglions of the Wrist and Hand. The Journal of Bone & Joint Surgery. 1972. DOI: 10.2106/00004623-197254070-00009
[66] Exam Of The Hand Wrist 2Ed. Special techniques for imaging the hand and wrist.
[67] Position Statement: Definition of Carpal Instability. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0866
[68] Management of chronic rotary subluxation of the scaphoid by scapho-trapezio-trapezoid arthrodesis. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80025-2
[69] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[70] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[71] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[72] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[73] The effects of wrist distraction on carpal kinematics. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.jhsu24a0113
[78] Exam Of The Hand Wrist 2Ed. 1.2 SKELETON OF THE WRIST.
[79] Exam Of The Hand Wrist 2Ed. Extension of the wrist > Muscles of wrist extension.
[84] Surgical Excision Versus Aspiration Combined with Intralesional Triamcinolone Acetonide Injection Plus Wrist Immobilization Therapy in the Treatment of Dorsal Wrist Ganglion; A Randomized Controlled Trial. Journal of Hand and Microsurgery. 2011. DOI: 10.1007/s12593-011-0039-6
[94] Segmental motion of the proximal carpal row: Their global effect on the wrist motion. The Journal of Hand Surgery. 1990. DOI: 10.1016/0363-5023(90)90101-v
[95] Management of ganglion cysts of the hand by simple aspiration. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80221-6
[97] Kinematic Analysis of Relative Motion within the Proximal Carpal Row. Journal of Hand Surgery. 1993. DOI: 10.1016/0266-7681(93)90015-8
[99] Arthroscopic Resection of Dorsal Wrist Ganglia and Treatment of Recurrences. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.1999.0290
[101] Arthroscopic resection of wrist ganglia. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80308-8
[103] A biomechanical study of distal radial fractures. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80202-2
[106] ARTHROSCOPIC RESECTION OF DORSAL GANGLION OF THE WRIST. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00020-2
[109] Compression Neuropathy of the Radial Nerve Due to Ganglion Cysts. HAND. 2008. DOI: 10.1007/s11552-007-9083-x
[110] Effects of intra-articular distal radius depression on wrist joint contact characteristics. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80003-7
[114] Wrist Ganglions. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2010.11.048
[118] Dorsal Wrist Ganglion Associated with Extensor Digitorum Brevis Manus: Case Report and Review of the Literature. The Journal of Hand Surgery (Asian-Pacific Volume). 2017. DOI: 10.1142/s0218810417200222
[120] Anatomical location of volar wrist ganglion in preoperative MRI is a risk factor for operation-related complications after arthroscopic ganglionectomy. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08766-x
[124] Orthopaedic Knowledge Update Sports Medicine 6. Hand and Wrist Injuries > Summary.
[125] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Carpmetacarpal Boss > Ganglions of Extensor Tendons.
[127] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic Wrist Synovectomy > Dorsal Wrist Ganglion.
[131] Factors associated with self-reported pain and hand function following dorsal wrist ganglion excision. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231153029
[136] Automated detection of wrist ganglia in MRI using convolutional neural networks. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09011-1
[137] Necessity of Routine Pathological Examination following Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/s0363-5023(10)60107-4
[149] Arthroscopic findings in patients with painful wrist ganglia. Scandinavian Journal of Plastic and Reconstructive Surgery and Hand Surgery. 2001. DOI: 10.1080/028443101750523267
[151] The dorsal ganglion with anomalous muscles. The Journal of Hand Surgery. 1979. DOI: 10.1016/s0363-5023(79)80111-2