Patients › Shoulder
தோள்பட்டை மூட்டழற்சி (Shoulder Arthritis)
Shoulder arthritis causes pain, stiffness, and reduced range of motion — diagnosis and treatment options explored.
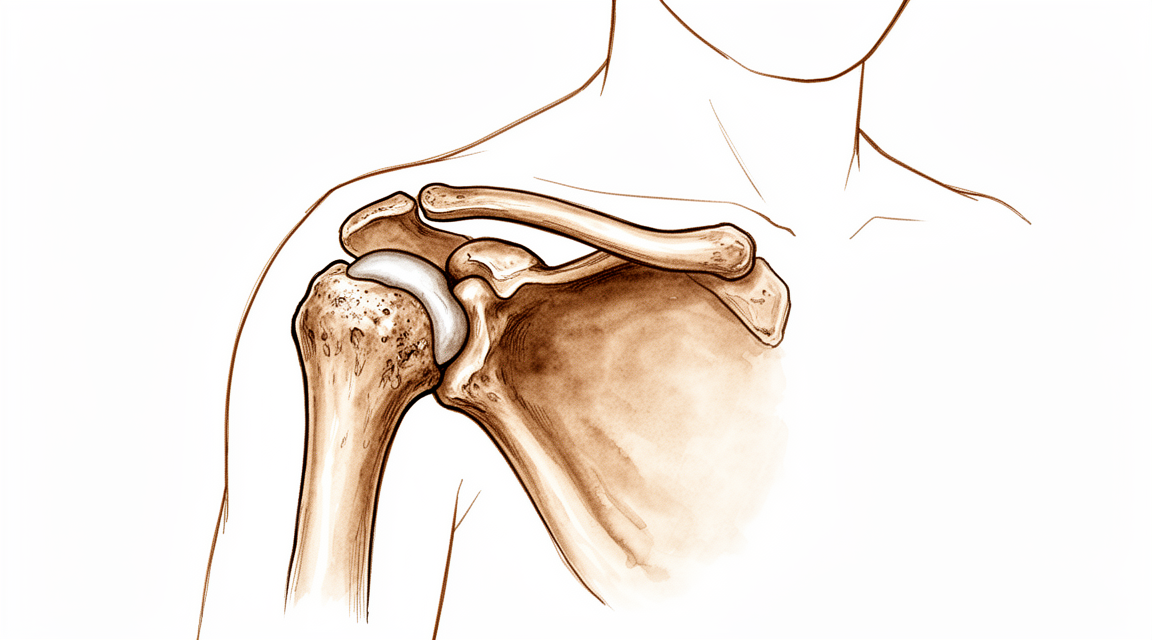
நீங்கள் உணர்வது
தோள்பட்டை மூட்டழற்சி (shoulder arthritis) என்பது, தோள்பட்டையின் முக்கியப் பந்து-குழி மூட்டில் (ball-and-socket joint) ஏற்படும் தேய்மான மூட்டழற்சி (wear-and-tear arthritis). வலி பொதுவாகத் திடீரென வராமல், ஆண்டுகளாகப் படிப்படியாக அதிகரிக்கிறது. அது தோள்பட்டைக்குள்ளேயே ஆழமாக இருக்கும்; மூட்டை நீங்கள் எவ்வளவு தூரம் அசைக்க முடியும் என்பதை மெல்ல மெல்லக் குறுக்கும் விறைப்பும் பொதுவாக அதனுடன் சேர்ந்து வருகிறது.
சில அசைவுகளும் நிலைகளும் அதை மோசமாக்குகின்றன. மேல்நோக்கிக் கை நீட்டுவது, கையைப் பக்கவாட்டில் தூக்குவது, அல்லது தோள்பட்டையின் வழியாக அழுத்தித் தள்ளுவது ஆகிய அனைத்தும் அதைத் தூண்டலாம். செயல்பாட்டுக்குப் பிறகு, பெரும்பாலும் மந்தமான வலி வந்து நீடிக்கிறது. இரவு நேரம் வலி அதிகரிக்கும் பொதுவான நேரம்; தோள்பட்டை தங்களைத் தூக்கத்திலிருந்து எழுப்புவதையோ, வசதியாகத் தூங்கும் நிலையை அமைத்துக்கொள்வதைக் கடினமாக்குவதையோ பலர் காண்கிறார்கள். காலையில் எழுந்தவுடன், மூட்டு விறைப்பாகவும் மெதுவாகவே தளர்வதாகவும் உணரப்படலாம்.
கை நீட்ட வேண்டிய அன்றாட வேலைகளே கடினமானவையாக மாறுகின்றன. தலைமுடி கழுவுவது, உங்களுக்குப் பின்னால் உள்ள விளக்கை அணைப்பது, அல்லது உடை அணியக் கையை மேலே தூக்கிச் சுற்றிக் கொண்டு செல்வது ஆகியவை உண்மையிலேயே சிரமமான வேலைகளாக மாறலாம். விறைப்புடன் சேர்ந்து பலவீனமும் பெரும்பாலும் மெல்ல மெல்ல நுழைகிறது; அதனால் பொருட்களைத் தூக்குவதும் சுமப்பதும் முன்பு போல நம்பகமாக உணரப்படுவதில்லை.
மூட்டழற்சியில் ஏற்படும் விறைப்பு, உறைந்த தோள்பட்டையின் (frozen shoulder) விறைப்பிலிருந்து வேறுபட்டது; உறைந்த தோள்பட்டை ஆண்டுகளில் அல்லாமல், வாரங்கள் முதல் மாதங்களுக்குள் உருவாகிறது. வேறு சில நிலைகளும் மூட்டழற்சியைப் போலவே தோன்றலாம்; ருமட்டாய்டு மூட்டழற்சியால் (rheumatoid arthritis) ஏற்படும் அழற்சியும் இதில் அடங்கும்; அது தோள்பட்டை வலியுடனும் வீக்கத்துடனும் சேர்த்து, பெரும்பாலும் களைப்பு, மற்ற மூட்டுகளில் வலி, எடை இழப்பு ஆகியவற்றையும் கொண்டுவருகிறது. உங்கள் நோய் வரலாற்றையும் பரிசோதனையையும் கொண்டு, சில சமயம் ஸ்கேன்கள் அல்லது இரத்தப் பரிசோதனைகளின் உதவியுடன், உங்கள் அறுவை சிகிச்சை நிபுணர் இவற்றை வேறுபடுத்தி அறிகிறார்.
சில அறிகுறிகளுக்கு விரைவான கவனம் தேவை. தோள்பட்டை சூடாகவும், சிவந்தும், வீங்கியும், கடுமையான வலியுடனும் ஆனால், குறிப்பாகக் காய்ச்சலும் இருந்தால், அதே நாளில் அவசர சிகிச்சைப் பிரிவில் சிகிச்சை பெற வேண்டும்; அதற்குப் பொது மருத்துவரின் (GP) பரிந்துரைக் கடிதம் தேவையில்லை. தோள்பட்டை அறிகுறிகள் தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், அல்லது கையைப் பயன்படுத்துவதையோ வேலை செய்வதையோ தடுத்தால், உங்கள் பொது மருத்துவரைப் (GP) பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள். அலுவலக நேரத்துக்குப் பிறகோ வார இறுதியிலோ கிளினிக்கைத் தொடர்பு கொள்ள முடியாவிட்டால், உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
உண்மையில் என்ன நடக்கிறது
உங்கள் தோள்பட்டை ஒரு பந்து-குழி மூட்டு. பந்து என்பது உங்கள் மேற்கை எலும்பின் உருண்டையான மேல்முனை; குழி என்பது உங்கள் தோள்பட்டை எலும்பில் (scapula) உள்ள ஆழமற்ற ஒரு தட்டு. குழி இயல்பாகவே சிறியது; அது தாங்கும் பந்தின் அளவில் சுமார் மூன்றில் ஒரு பங்கு. அதன் விளிம்பைச் சுற்றியுள்ள, லேப்ரம் (labrum) எனப்படும் ரப்பர் போன்ற குருத்தெலும்பு வளையம், பந்து அதன் இடத்திலேயே இருக்கும்படி குழியை ஆழப்படுத்துகிறது. இரு பரப்புகளையும் வழுவழுப்பான, வழுக்கும் தன்மையுள்ள ஒரு குருத்தெலும்பு (cartilage) அடுக்கு மூடியிருக்கிறது; இது இரண்டு எலும்புகளும் கிட்டத்தட்ட உராய்வே இல்லாமல் ஒன்றின் மீது ஒன்று சறுக்கிச் செல்ல உதவுகிறது.
மூட்டழற்சியில், அந்த வழுவழுப்பான குருத்தெலும்பு தேய்ந்து போகிறது. இரண்டு எலும்புகளுக்கும் இடையிலான அதிர்வுதாங்கி (shock absorber), எலும்புகள் ஒன்றோடொன்று அரைபடத் தொடங்கும் வரை மெலிந்து போவதாக இதைக் கற்பனை செய்துகொள்ளுங்கள். இதற்கு எதிர்வினையாக உடல், மூட்டின் விளிம்புகளில் கூடுதல் எலும்பை வளர்க்கிறது; இந்த எலும்பு முட்கள் (bony spurs) விறைப்பை மேலும் அதிகரிக்கின்றன. மூட்டின் உட்படலமும் அழற்சியடைந்து வீங்கலாம். எலும்பு எலும்பின் மீது அரைபடுவது, எலும்பு முட்கள், அழற்சி ஆகிய மூன்றும் சேர்ந்து, மேலே நீங்கள் படித்த ஆழமான வலியையும், குறுகிக்கொண்டே வரும் அசைவு வரம்பையும், இரவு வலியையும் விளக்குகின்றன.
தேய்மானம் எப்போதும் சீராக இருப்பதில்லை. மூட்டழற்சி உள்ள பல தோள்பட்டைகளில், பந்து குழியின் பின்பகுதியை நோக்கி நகர்கிறது; அதனால் குழியின் பின் விளிம்பு மற்ற பகுதிகளைவிட வேகமாகத் தேய்கிறது. காலப்போக்கில் மூட்டின் முன்பகுதியில் உள்ள திசுக்களும் இறுகுகின்றன; இது பந்தை மேலும் பின்னோக்கித் திருப்பி, தேய்ந்த பகுதியின் மீது சுமையை இன்னும் அதிகரிக்கிறது. மூட்டைச் சுற்றியுள்ள, சுழற்சி தசைநாண் பட்டை (rotator cuff) எனப்படும் தசைநாண்கள், இந்த வகை மூட்டழற்சியில் பொதுவாக இன்னும் சேதமடையாமலே இருக்கின்றன; இருப்பினும் மற்ற வகைகளில் அவை பாதிக்கப்படலாம்.
மூட்டழற்சி பல வழிகளில் தொடங்கலாம். பெரும்பாலானவற்றுக்கு ஒரே தெளிவான காரணம் என்று எதுவும் இல்லை; இருப்பினும் குடும்பப் போக்கு (family tendency) ஒரு பங்கு வகிக்கலாம். மற்றவை, பழைய எலும்பு முறிவு, மூட்டில் முன்பு செய்யப்பட்ட அறுவை சிகிச்சை, மீண்டும் மீண்டும் ஏற்படும் மூட்டு இடப்பெயர்வுகள் (dislocations), அல்லது ருமட்டாய்டு மூட்டழற்சி போன்ற அழற்சி நிலைகளைத் தொடர்ந்து ஏற்படுகின்றன; ருமட்டாய்டு மூட்டழற்சியில், உடலின் சொந்தப் பாதுகாப்பு அமைப்பே மூட்டின் உட்படலத்தைத் தாக்கி, குருத்தெலும்பை அழிக்கிறது. தொடக்கம் எதுவாக இருந்தாலும், மூட்டில் ஏற்படும் இறுதி விளைவு ஏறக்குறைய ஒன்றுதான்; அதுவே உங்கள் அறிகுறிகளை உண்டாக்குகிறது.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் பணியாற்றும் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் நிலைக்குப் பொருத்தமான, உடலில் மிகக் குறைவாகத் தலையிடும் சிகிச்சைகளிலிருந்தே தொடங்குகிறார். நோயாளிகள் பொதுவாக அவர்களது பொது மருத்துவரால் (GP) எங்கள் கிளினிக்குக்கு அனுப்பப்படுகிறார்கள்; ஒரு இயன்முறை சிகிச்சையாளர் எங்களைப் பார்க்கச் சொல்லியிருந்தாலும், Medicare திரும்பப்பெறுதலுக்குத் தகுதி பெற உங்கள் பொது மருத்துவரிடமிருந்து பரிந்துரைக் கடிதம் (referral) தேவைப்படும். உங்கள் முதல் சந்திப்பில், நோய் வரலாற்றைக் கேட்டறிந்து, தோள்பட்டையைப் பரிசோதித்து, தேவைப்படும் இடத்து ஸ்கேன் பரிசோதனைகளுக்கு (imaging) ஏற்பாடு செய்கிறோம். சிகிச்சையைத் திட்டமிட எக்ஸ்-ரேக்களே கிட்டத்தட்ட எப்போதும் போதுமானவை. சுழற்சி தசைநாண் பட்டையைச் சரிபார்ப்பது, அல்லது அறுவை சிகிச்சைக்கு முன் எலும்புத் தேய்மானத்தை அளவிடுவது போன்ற சில சந்தர்ப்பங்களில், CT அல்லது MRI ஸ்கேன் கூடுதல் விவரங்களைத் தருகிறது.
லேசானது முதல் மிதமானது வரையிலான மூட்டழற்சிக்கு, பொதுவாக முதலில் அறுவை சிகிச்சை அல்லாத கவனிப்பையே முயற்சிக்கிறோம். தோள்பட்டையை நீங்கள் பயன்படுத்தும் விதத்தை மாற்றுவது உதவுகிறது; எனவே எந்த அசைவுகளும் வேலைகளும் மூட்டுக்குச் சுமை தருகின்றன என்பதைப் பார்த்து, அவற்றைத் தவிர்க்கும் வழிகளைக் கண்டறிகிறோம். இயன்முறை சிகிச்சையின் (physiotherapy) நோக்கம், மூட்டை அசைவில் வைத்திருப்பதும் அதைச் சுற்றியுள்ள வலிமையைக் கட்டியெழுப்புவதும். அழற்சி எதிர்ப்பு மருந்து வலியைத் தணிக்கலாம்; மூட்டுக்குள் செலுத்தப்படும் கார்ட்டிசோன் ஊசி (cortisone injection) சில வாரங்கள் முதல் சில மாதங்கள் வரை அழற்சியைத் தணிக்கலாம். அறுவை சிகிச்சை பற்றிப் பேசுவதற்கு முன், இவற்றில் எதற்கும் போதுமான முயற்சிக் காலம் கொடுக்கிறோம்; ஏனெனில் அறுவை சிகிச்சை அல்லாத கவனிப்பை உண்மையாக முயற்சித்த பிறகு செய்யப்படும்போது அறுவை சிகிச்சை சிறப்பாகப் பலனளிக்கிறது.
அறுவை சிகிச்சை அல்லாத கவனிப்பு போதுமான முன்னேற்றத்தைத் தராமல், வலியோ விறைப்போ நீங்கள் செய்யக்கூடியவற்றைத் தொடர்ந்து கட்டுப்படுத்திக்கொண்டிருக்கும்போது, அறுவை சிகிச்சை பேச்சுக்கு வருகிறது. முக்கிய அறுவை சிகிச்சை தோள்பட்டை மூட்டு மாற்று அறுவை சிகிச்சை (shoulder replacement); அதில் பந்தின், குழியின் தேய்ந்த பரப்புகள் செயற்கைப் பாகங்களால் மாற்றியமைக்கப்படுகின்றன. எந்த வகையைப் பற்றி நாம் பேசுவோம் என்பது, உங்கள் வயது, உங்கள் சுழற்சி தசைநாண் பட்டையின் நிலை, குழியில் உள்ள எலும்பு ஆகியவற்றைப் பொறுத்தது; அந்தத் தேர்வை உங்களுடன் சேர்ந்து, இணைந்து எடுக்கும் முடிவாகவே மேற்கொள்கிறோம்.
என்ன எதிர்பார்க்கலாம்
மூட்டழற்சி பின்னோக்கிச் செல்வதில்லை. தேய்ந்த குருத்தெலும்பு மீண்டும் வளர்வதில்லை; எனவே அடிப்படையான தேய்மானம் அப்படியே இருக்கிறது. மாறுவது, தோள்பட்டை அன்றாடம் உங்களை எவ்வளவு தொந்தரவு செய்கிறது என்பதுதான்; அதை உங்களுக்குச் சாதகமாக மாற்ற முடியும்.
சிகிச்சை இல்லாவிட்டால், பொதுவாகத் திடீர்ச் சரிவாக அல்லாமல், ஆண்டுகளாக மெதுவான பின்னடைவே நிகழ்கிறது. வலியும் விறைப்பும் படிப்படியாக அதிகரிக்கும் போக்கு உள்ளது; தலைக்கு மேல் கை நீட்டுவது, அந்தப் பக்கமாகப் படுத்துத் தூங்குவது போன்ற, முன்பு நீங்கள் கவனித்த விஷயங்கள் பொதுவாக எளிதாவதற்குப் பதிலாகக் கடினமாகின்றன. சிலர் நீண்ட காலம் நிலையாக இருக்கிறார்கள்; ஆனால் சிகிச்சை பெறாத மூட்டழற்சித் தோள்பட்டையின் பொதுவான போக்கு கீழ்நோக்கியதே.
நன்கு நிர்வகிக்கப்படும் கவனிப்புடன், பெரும்பாலானோர் அதைவிட நன்றாக இருக்கிறார்கள். உங்கள் இயன்முறை சிகிச்சையாளரின் வழிகாட்டுதலுடன் மூட்டை அசைவில் வைத்திருப்பதும் அதைச் சுற்றியுள்ள வலிமையைக் கட்டியெழுப்புவதும், அறிகுறிகளைத் தணித்து, நீங்கள் நீண்ட காலம் அதிகம் செய்யக்கூடியவராக இருக்க உதவலாம். பலர் அறுவை சிகிச்சையே தேவைப்படாமல் தங்கள் மூட்டழற்சியைப் பல ஆண்டுகள் சமாளிக்கிறார்கள்.
அறுவை சிகிச்சையே சரியான தீர்வு என்று ஆனால், இதே பிரச்சினைக்குத் தோள்பட்டை மூட்டு மாற்று அறுவை சிகிச்சைக்கு நீண்ட கால அனுபவச் சான்று உண்டு. தோள்பட்டையின் முற்றிய மூட்டழற்சியில் வலியைக் குறைப்பதற்கும் செயல்பாட்டை மேம்படுத்துவதற்கும், மிக அதிக அளவில் முன்கூட்டியே கணிக்கக்கூடிய முடிவுகளைத் தரும் சிகிச்சை இதுவே. அறுவை சிகிச்சைக்குப் பிறகு ஒப்பீட்டளவில் குறுகிய காலத்துக்குள்ளேயே, தங்கள் தோள்பட்டை சிறப்பாகச் செயல்படுவதையும் தங்கள் ஒட்டுமொத்த உடல்நலம் மேம்பட்டிருப்பதையும் மக்கள் பொதுவாகக் கவனிக்கிறார்கள். முதல் இரண்டு ஆண்டுகளில் வலிமையும் மேம்படுகிறது; இருப்பினும் தோள்பட்டையின் முன்பகுதியில் உள்ள தசைநாண் எப்போதும் முழு இயல்பான வலிமைக்குத் திரும்புவதில்லை.
எந்தச் சிகிச்சையும் ஒரு உத்தரவாதம் அல்ல. பெரும்பாலானோர் உண்மையான நிவாரணம் பெறுகிறார்கள்; ஆனால் சிலருக்கு விறைப்போ பலவீனமோ நீடிக்கிறது; சிறுபான்மையினருக்குப் பிற்காலத்தில் மேலும் ஓர் அறுவை சிகிச்சை தேவைப்படுகிறது. உள்பொருத்துகள் (implants) செயற்கைப் பாகங்கள்; காலப்போக்கில் அவை தளர்ச்சியடையலாம் அல்லது தேயலாம்; நீங்கள் எவ்வளவு இளையவராகவும் சுறுசுறுப்பானவராகவும் இருக்கிறீர்களோ, அவ்வளவு அதிகமாக இது கவனத்தில் கொள்ள வேண்டிய விஷயம். உங்கள் தோள்பட்டைக்குக் குறிப்பாக, யதார்த்தமான ஒரு முடிவு எப்படி இருக்கும் என்பதை உங்கள் அறுவை சிகிச்சை நிபுணர் உங்களுடன் விரிவாகப் பேசுவார்.
தெரிந்துகொள்ள வேண்டிய ஒரு விஷயம்: எக்ஸ்-ரேயில் உங்கள் மூட்டழற்சி இன்னும் லேசானதாக இருந்தால், கடுமையான மூட்டழற்சியில் தருவதைவிட அறுவை சிகிச்சை குறைவான முன்னேற்றத்தையே தரும் போக்கு உள்ளது. அது அறுவை சிகிச்சையைத் தவிர்ப்பதற்கான காரணம் அல்ல; ஆனால் அதிலிருந்து நீங்கள் எதைப் பெற எதிர்பார்க்கிறீர்கள் என்பதில் தெளிவாக இருப்பதற்கான காரணம் அது.
உங்கள் தோள்பட்டை அறிகுறிகள் தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், அல்லது கையைப் பயன்படுத்துவதையோ வேலை செய்வதையோ தடுத்தால், உங்கள் பொது மருத்துவரைப் (GP) பாருங்கள் அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
மூட்டழற்சி உள்ள பெரும்பாலான தோள்பட்டைகள் திட்டமிட்ட ஒரு சந்திப்பு வரை காத்திருக்கலாம்; ஆனால் சில அறிகுறிகள் காத்திருக்கக் கூடாது. தோள்பட்டை சூடாகவும், சிவந்தும், வீங்கியும், கடுமையான வலியுடனும் ஆனால், குறிப்பாகக் காய்ச்சலும் இருந்தால், அன்றே அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். மூட்டில் ஏற்படும் தொற்றுக்கு நேரம் மிக முக்கியம்; அதற்குப் பொது மருத்துவரின் (GP) பரிந்துரைக் கடிதம் தேவையில்லை. அலுவலக நேரத்துக்குப் பிறகோ வார இறுதியிலோ கிளினிக்கைத் தொடர்பு கொள்ள முடியாவிட்டாலும் இதுவே பொருந்தும்: உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
தோள்பட்டை தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், அல்லது நீங்கள் வேலை செய்வதையோ கையைப் பயன்படுத்துவதையோ தடுத்தால், உங்கள் பொது மருத்துவரைப் (GP) பாருங்கள். வலியும் விறைப்பும் ஆண்டுகளாக அதிகரித்து, இப்போது தலைமுடி கழுவுவது, உடை அணிவது, அல்லது பின்னால் கை நீட்டுவது ஆகியவற்றைக் கட்டுப்படுத்தினால், நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
சில அமைப்புகளை விரைவில் நெருக்கமாகப் பார்க்க வேண்டும். அமைதியாக மெல்ல மெல்ல அதிகரித்த தோள்பட்டை வலி உள்ள வயதான பெண்களுக்கு, வேகமான, கடுமையான தேய்மானம் ஏற்படலாம். கௌட் (gout) நோய் இருந்த ஒருவருக்குக் கடுமையான எலும்பு அரிப்பு (erosion) இருந்தால், அது தோள்பட்டையிலேயே கௌட் இருப்பதைச் சுட்டுகிறது. மேலும், காய்ச்சலுடன் தோள்பட்டை சூடாகவும் வலியுடனும் இருந்தால், அது மேலே விவரிக்கப்பட்ட, அன்றே அவசர சிகிச்சை தேவைப்படும் அறிகுறி.
கழுத்து வலி, அல்லது முழங்கைக்குக் கீழே பரவும் மரத்துப்போதலும் கூச்ச உணர்வும் இருந்தால், அவற்றைப் பற்றியும் உங்கள் அறுவை சிகிச்சை நிபுணர் அறிய விரும்புவார்; ஏனெனில் இவை தோள்பட்டையிலிருந்து அல்லாமல் கழுத்திலிருந்து வரக்கூடும்.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
இந்தப் பகுதி, உங்கள் சொந்தச் சிகிச்சை முடிவுகளுக்குத் தேவையானதை விட ஆழமாகச் செல்கிறது. தோள்பட்டை மூட்டழற்சியில் இந்தக் கூடுதல் வாசிப்பு பயனுள்ளது; ஏனெனில் முக்கிய முடிவான 'எந்த வகை மூட்டு மாற்று அறுவை சிகிச்சை' என்பது சமீபத்தில் தெளிவான ஒரு பதிலாக இல்லாமல், ஒன்றைக் கொடுத்து இன்னொன்றைப் பெறும் உண்மையான தேர்வாக மாறியுள்ளது; மேலும் அந்தத் தேர்வு உங்கள் வயதைப் பொறுத்து வேறுபடுகிறது.
உடற்கூற்று வகையும் தலைகீழ் வகையும், 70 வயதுக்கு மேல்
உடற்கூற்று (anatomic) மூட்டு மாற்று அறுவை சிகிச்சை இயல்பான அமைப்பையே மீண்டும் உருவாக்குகிறது; அது சரியாக வேலை செய்யும் சுழற்சி தசைநாண் பட்டையை (rotator cuff) நம்பியிருக்கிறது. தலைகீழ் (reverse) மூட்டு மாற்று அறுவை சிகிச்சை பந்தையும் குழியையும் இடமாற்றி, தூக்கும் வேலையை டெல்டாய்டு (deltoid) தசையிடம் ஒப்படைக்கிறது; அதற்குச் சுழற்சி தசைநாண் பட்டையின் தேவை இல்லை. முன்பெல்லாம், தசைநாண் பட்டை இல்லாத தோள்பட்டைகளுக்கு மட்டுமே தலைகீழ் வகை ஒதுக்கப்பட்டிருந்தது; இப்போது அது மிகவும் பரவலாகப் பயன்படுத்தப்படுகிறது.
நல்ல நிலையில் உள்ள தசைநாண் பட்டையுடன் 70 வயதும் அதற்கு மேலும் உள்ள நோயாளிகளிடையே, 1,716 நோயாளிகளை உள்ளடக்கிய ஒப்பீடு தெளிவாகப் பிரிகிறது. உடற்கூற்று மூட்டு மாற்று அறுவை சிகிச்சை மேம்பட்ட சுழற்சி அசைவை, மருத்துவ ரீதியாக முக்கியமான குறைந்தபட்ச வேறுபாட்டையும் தாண்டி, வழங்கியது; உடை அணிதல், கழிப்பறைப் பயன்பாடு போன்ற செயல்களுக்கு இது உதவக்கூடும். அதே சமயம் தலைகீழ் வகை சிறந்த உள்பொருத்து நீடிப்பையும் குறைவான மறு அறுவை சிகிச்சை விகிதத்தையும் வழங்கியது [1].
இவை இரண்டு வெவ்வேறு நாணயங்கள். உடற்கூற்று வகை, அன்றாட வாழ்வில் நீங்கள் உணரக்கூடிய சுழற்சி அசைவை வாங்கித் தருகிறது; தலைகீழ் வகை நீடித்து உழைக்கும் தன்மையை வாங்கித் தருகிறது. இரண்டில் எதுவும் மற்றதை முழுமையாக மிஞ்சவில்லை; அதனால்தான் இது இப்போது தானாக அமையும் ஒரு தேர்வாக இல்லாமல், ஒரு கலந்துரையாடலாக இருக்கிறது.
இந்தச் சூழலில் தலைகீழ் வகையில் ஆரம்பச் சிக்கல்கள் அதிகம்
சாதாரண மூட்டழற்சிக்குத் தலைகீழ் வகை பயன்படுத்தப்படும்போது, நீடிப்பில் கிடைக்கும் இந்த நன்மைக்கு அருகிலேயே ஒரு விலையும் உண்டு. 8,846 நோயாளிகளிடையே, முதன்மைத் தோள்பட்டை மூட்டு மூட்டழற்சிக்கு (primary glenohumeral arthritis) உடற்கூற்று வகையுடன் ஒப்பிடும்போது தலைகீழ் வகையில் ஆரம்பச் சிக்கல்களின் விகிதம் அதிகமாக இருப்பது கண்டறியப்பட்டது — மூட்டு நிலையின்மை, தோள்பட்டை எலும்பு முறிவு, தொற்று மற்றும் அனைத்துக் காரணச் சிக்கல்கள் — ஆனால் அந்தப் பின்தொடர் காலத்தில் மறு அறுவை சிகிச்சை விகிதத்தில் வேறுபாடு இல்லை [2].
மேலே சொன்ன நீடிப்புக் கண்டுபிடிப்புடன் சேர்த்துப் படித்தால், தலைகீழ் வகை ஆரம்பத்தில் பிரச்சினை வரும் அதிக வாய்ப்பைக் கொடுத்து, பிற்பாடு பிரச்சினை வரும் குறைந்த வாய்ப்பைப் பெறுகிறது என்பதே தென்படும் அமைப்பு. இவற்றில் எது அதிக முக்கியம் என்பது, உள்பொருத்து எத்தனை ஆண்டுகள் தாங்க வேண்டும் என்பதைப் பெரிதும் பொறுத்தது.
பந்துடன் சேர்த்துக் குழியையும் மாற்றுவது
பகுதி மூட்டு மாற்று அறுவை சிகிச்சை (hemiarthroplasty) பந்தை மட்டும் மாற்றி, தேய்ந்த குழியை அப்படியே விட்டுவிடுகிறது. இது சிறிய அறுவை சிகிச்சை; காலப்போக்கில் தளர்ச்சி அடைவதற்கு மிகவும் வாய்ப்புள்ள பகுதியான கிளெனாய்டு பாகத்தை (glenoid component) இது தவிர்க்கிறது.
ஆய்வுச் சான்றுகள் அதற்குச் சாதகமாக இல்லை. முதன்மைத் தோள்பட்டை மூட்டுத் தேய்மான மூட்டழற்சியும் (primary glenohumeral osteoarthritis) பாதிக்கப்படாத தசைநாண் பட்டையும் உள்ள 1,317 நோயாளிகளிடையே, மருத்துவ விளைவு, மறு அறுவை சிகிச்சை அபாயம், அறுவை சிகிச்சைக்குப் பிந்தைய சிக்கல்கள் ஆகியவற்றில் பகுதி மூட்டு மாற்று அறுவை சிகிச்சையை விட முழு தோள்பட்டை மூட்டு மாற்று அறுவை சிகிச்சையே சாதகமானது [3].
இதற்கான விளக்கம்: தேய்ந்த குழி, புதிய பந்துக்கு எதிராக உரசித் தொடர்ந்து வலியை உருவாக்குகிறது. கிளெனாய்டு பாகத்தைத் தவிர்ப்பது, ஒரு நீண்ட கால தோல்வி வழியைத் தவிர்க்கிறது — ஆனால் அதற்காக ஒரு குறுகிய கால தோல்வி வழியை ஏற்றுக்கொள்கிறது.
இளம் வயது நோயாளிகளுக்குக் கணக்கு முற்றிலும் மாறுகிறது
சுமார் 60 வயதுக்குக் கீழ், ஒவ்வொரு வழியும் ஏதோ ஒரு குறிப்பிட்ட வகையில் திருப்தியற்றதாகவே இருக்கிறது; ஆய்வு இலக்கியம் இதைத் தீர்த்து வைக்காமல், நேர்மையாக அப்படியே பிரதிபலிக்கிறது. மூட்டு மாற்று அறுவை சிகிச்சைக்கு ஒருவரின் வாழ்நாளுக்குள் மறு அறுவை சிகிச்சை தேவைப்படும் வாய்ப்பு மிக அதிகம்; தோள்பட்டையின் மறு அறுவை சிகிச்சை முதல் அறுவை சிகிச்சையை விடக் கணிசமாகக் கடினமானது. மூட்டைப் பாதுகாக்கும் வழிகள் — துளை வழி அறுவை சிகிச்சையில் சிதைந்த திசுக்களை அகற்றுதல், மூட்டு உறையைத் தளர்த்துதல், எலும்பு முளைகளை (osteophytes) அகற்றுதல் — மூட்டழற்சியை நிறுத்துவதில்லை; ஆனால் மூட்டு மாற்று அறுவை சிகிச்சையைப் பிற்படுத்த முடியும், இளம் நோயாளிக்கு அதுவே தனியாக ஒரு பொருத்தமான இலக்காகும்.
மூட்டு நிலையின்மைக்கு அறுவை சிகிச்சை செய்துகொண்ட எவருக்கும் ஒரு கண்டுபிடிப்பு
தோள்பட்டையை நிலைப்படுத்தும் அறுவை சிகிச்சைக்குப் பிறகு ஸ்கேன்களில் மூட்டழற்சி தென்படுவது பொதுவானது; பெரும்பாலும் அது எந்த அறிகுறியையும் ஏற்படுத்துவதில்லை. துளை வழி பேங்கார்ட் சீரமைப்புக்குப் (arthroscopic Bankart repair) பிறகு, ஏதேனும் ஒரு மூட்டழற்சி மாற்றம் 60% பேருக்கும், நடுத்தர முதல் கடுமையான மாற்றம் 28% பேருக்கும் காணப்பட்டது; இருப்பினும் அது பொதுவாக அறிகுறிகளற்றது, அறியப்பட்ட அபாயக் காரணிகளுடன் குறிப்பிடத்தக்க தொடர்பு எதுவும் கண்டறியப்படவில்லை [4].
நீங்கள் நிலைப்படுத்தும் அறுவை சிகிச்சை செய்துகொண்டிருந்து, பிற்பாடு எடுக்கப்பட்ட ஸ்கேனில் மூட்டழற்சி இருப்பதாகக் குறிப்பிடப்பட்டால் — அந்தக் கண்டுபிடிப்பு பொதுவானது, பெரும்பாலும் அது அறிகுறிகளுக்கான காரணம் அல்ல, அது மட்டுமே ஏதாவது செய்வதற்கான காரணமும் அல்ல.
மேற்கோள்கள்
[1] Gupta MS, Krishan A, Rashid A, Lee MH. Reverse versus anatomic total shoulder arthroplasty in patients over 70 years with primary glenohumeral osteoarthritis: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2026;35(5):1370-86. https://doi.org/10.1016/j.jse.2025.10.015
[2] Givens JM, Malkani AL, Ong KL, Watson HN, Harreld KL. Complication rates following reverse and anatomic shoulder replacement in patients with primary glenohumeral arthritis. J Shoulder Elbow Surg. 2024;33(2):273-80. https://doi.org/10.1016/j.jse.2023.06.017
[3] Singh Jagdev B, McGrath J, Cole A, Gomaa A, Chong HH, Singh HP. Total shoulder arthroplasty vs. hemiarthroplasty in patients with primary glenohumeral arthritis with intact rotator cuff: meta-analysis using the revised Cochrane risk of bias tool. J Shoulder Elbow Surg. 2022;31(12):2657-70. https://doi.org/10.1016/j.jse.2022.07.012
[4] Yeo MH, Seah SJ, Ang G, Arce G, Lie D. Prevalence and risk factors for the development of glenohumeral osteoarthritis following arthroscopic Bankart repair: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2025;34(12):e1224-e1233. https://doi.org/10.1016/j.jse.2025.03.011
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Shoulder arthritis is common, and management strategies, especially in young patients, continue to evolve with significant improvements in implant design [2].
- Longevity remains a concern in more active patients with shoulder arthritis [2].
- The goal of the 2016 special issue on anatomic total shoulder arthroplasty was to provide an understanding of best practices and address current controversies in the field [4].
- In patients with primary glenohumeral degenerative joint disease, shoulder arthroplasty was effective within a relatively short time frame in improving patient assessment of both shoulder function and overall health status [5].
- Patients with glenohumeral osteoarthritis converted intraoperatively to reverse shoulder arthroplasty had outcomes comparable to those who underwent total shoulder arthroplasty [6].
- No treatment for the stiff shoulder has proved to be definitive [7].
- The literature supports many forms of treatment for the stiff shoulder, both operative and nonoperative [7].
- Treatment of advanced glenohumeral arthritis by total shoulder arthroplasty has historically provided the most predictable results for pain relief and improved function [8].
- Knowledge of the array of shoulder prostheses currently available and the indications for each, as well as the use of treatment algorithms, can lead to optimized patient outcomes [10].
- A clear standardised set of shoulder arthroplasty complication definitions is lacking [11].
- Reverse shoulder arthroplasty provides optimal outcomes with low complication rates across a short term of follow-up for glenohumeral osteoarthritis with an intact rotator cuff [13].
- Patients with mild radiographic signs of arthritis have about sevenfold higher odds of failing to achieve the minimum clinically important difference (MCID) after anatomic total shoulder replacement compared to patients with severe arthritis [15].
- The Western Ontario Osteoarthritis of the Shoulder Index (WOOS) is recommended for continued use in shoulder arthroplasty registries and observational studies [18].
- Total shoulder arthroplasty is a good procedure with a successful long-term record [19].
- Anatomic total shoulder arthroplasty (ATSA) is the benchmark for surgical treatment of glenohumeral arthritis with an intact cuff [20].
- Reverse total shoulder arthroplasty (RTSA) has gained popularity for rotator cuff arthropathy and other complex indications [20].
- Total shoulder arthroplasty did not provide a clinically important advantage over hemiarthroplasty in terms of patient-reported pain, function, nor adverse effects [39].
- The evidence regarding the comparison of total shoulder arthroplasty and hemiarthroplasty was of low quality [39].
- Under optimal circumstances, simultaneous shoulder arthroplasty is feasible [53].
- Reverse total shoulder arthroplasty (rTSA) provides comparable clinical outcomes across indications of irreparable rotator cuff tear, rotator cuff tear arthropathy, and primary osteoarthritis at 2 years [56].
- The broad applicability of rTSA is supported by comparable clinical outcomes across its various indications at 2 years [56].
- Registry data indicate a 2.5-year revision rate for resurfacing prostheses [62].
- The revision rate for resurfacing prostheses is more than three times the revision rate for stemmed hemiarthroplasty [62].
- Both augmented and standard anatomic total shoulder arthroplasty can provide satisfactory and sustained improvements in patient-reported outcomes in patients with acquired glenoid retroversion due to glenohumeral osteoarthritis [72].
- rTSA has seen a significant increase in utilization for glenohumeral osteoarthritis [168].
- Evidence suggests similar success in patient-reported outcomes and satisfaction for rTSA compared to anatomic total shoulder arthroplasty (aTSA) [168].
- aTSA may offer better range of motion compared to rTSA [168].
- rTSA demonstrates improved survivorship compared to aTSA [168].
- rTSA addresses common causes of failure such as rotator cuff failure and glenoid component loosening with improved survivorship compared to aTSA [168].
- Early results for meniscal allograft interposition arthroplasty for the arthritic shoulder appear promising [185].
- Meniscal allograft interposition arthroplasty does not preclude conversion to a total shoulder replacement or arthrodesis should this become necessary in the future [185].
- Acceptable results, similar to those of anatomic total shoulder arthroplasty, can be achieved with ream-and-run arthroplasty in challenging populations [190].
Anatomy & Pathophysiology
Bony Anatomy
- The glenoid cavity is a shallow socket approximately one-third the size of the humeral head [93].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [92].
- The subchondral bone of the glenoid is relatively flat, with articular concavity augmented by cartilage and a circumferential labrum [94].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [94].
- The humeral head is spherical with a diameter of 37 to 57 mm [92].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [92].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [92].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [92].
- The average neck-shaft angle is 45 degrees (±5 degrees), with a range of 30 to 50 degrees [101].
- Arthritic shoulders have a flatter neck-shaft angle close to 50 degrees [101].
- The radius of curvature of the humeral head is approximately 25 mm and is slightly larger in men than in women [101].
- The glenoid articular surface radius of curvature is 2 to 3 mm larger than that of the humeral head [101].
- The superior margin of the humeral head articular surface is normally superior to the top of the greater tuberosity by 8 to 10 mm [101].
- The distance from the lateral base of the coracoid process to the lateral margin of the greater tuberosity is called the lateral humeral offset [101].
- A significant decrease in lateral humeral offset reduces the lever arms for the deltoid and supraspinatus muscles, weakening abduction [101].
- A significant increase in lateral humeral offset causes excessive tension on soft tissues, resulting in loss of motion and likely accelerated polyethylene wear [101].
- Humeral articular malposition of more than 4 mm leads to increased subacromial contact [101].
- An offset of 8 mm in any direction significantly decreases passive range of motion [101].
- Proximal humeral retroversion is highly variable, ranging from 0 to 55 degrees depending on the measurement method [101].
- The scapula is anteverted on the chest wall approximately 30 degrees relative to the body [103].
- The humeral head is retroverted 30 degrees relative to the transepicondylar axis of the humerus [103].
- Primary glenohumeral osteoarthritis is associated with distinct global scapular morphologic characteristics [9].
- Three reproducible scapular rotation types were identified that remained mostly constant postoperatively [80].
- There are no significant side-dependent differences in the osseous anatomy of the glenohumeral joint [189].
Soft Tissue Anatomy
- The glenoid labrum is composed of dense fibrocartilaginous tissue and increases the depth of the socket by 50% around the humeral head [102].
- The glenoid articular surface and the labrum combine to create a socket that is approximately 9 mm deep in the superoinferior direction and 5 mm deep in the anteroposterior direction [102].
- Adding the glenoid labrum increases the glenoid surface to 75% of the humeral head vertically and 57% horizontally [102].
- The shoulder capsule is large and has twice the surface area of the humeral head [105].
- The shoulder capsule typically accepts approximately 28 to 35 mL of fluid, with a greater amount in women than in men [105].
- In patients with adhesive capsulitis, the shoulder capsule accepts only 5 mL or less of fluid [105].
- The coracohumeral ligament originates from the base and lateral border of the coracoid process and inserts on the greater tuberosity [105].
- The coracohumeral ligament appears to have a static suspensory function for the humeral head in the glenoid cavity when the arm is in the dependent position [105].
- The transverse humeral ligament consists of transverse fibers of capsule extending between the greater and lesser tuberosities to contain the long head of the biceps tendon [105].
- The rotator cuff tendons blend into the capsule over varying lengths and average approximately 2.5 cm [105].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula and communicates with the joint cavity between the superior and middle glenohumeral ligaments [95].
- The subscapular bursa often houses loose bodies in the shoulder and is a region where synovitis may be most intense [95].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [94].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [94].
- Laxity of the rotator interval results in inferior laxity (the sulcus sign), and contracture of the interval is seen with adhesive capsulitis [94].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [94].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [94].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation in 90° of abduction and external rotation [94].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [94].
- The superior glenohumeral ligament is the primary restraint to inferior humeral subluxation in 0 degrees of abduction [102].
- The middle glenohumeral ligament limits external rotation when the arm is in the lower and middle ranges of abduction but has little effect at 90 degrees of abduction [102].
- The anteroinferior glenohumeral ligament complex is the main stabilizer to anterior and posterior stresses when the shoulder is abducted 45 degrees or more [102].
- The tendons of the infraspinatus and supraspinatus muscles join approximately 15 mm proximal to their insertion and cannot be readily separated by blunt dissection [102].
- The supraspinatus and subscapularis tendons join as a sheath that surrounds the biceps tendon at the entrance of the bicipital groove [102].
- The coracoacromial ligament contributes to anterosuperior stability in rotator cuff deficiency and should be preserved with irreparable cuff tears to prevent anterosuperior escape [103].
Vascular and Neural Anatomy
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [92].
- The anterior humeral circumflex artery provides vascular inflow to the humeral head by way of its terminal anterolateral branch known as the artery of Laing or arcuate artery [92].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon and enters the humeral head at the interface of the bicipital groove and greater tuberosity [92].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [92].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [92].
- 64% of the humeral head blood supply arises from the posterior humeral circumflex artery [98].
- The axillary nerve is a terminal branch coming off the posterior cord of the brachial plexus just proximal to the coracoid process [97].
- The axillary nerve passes beneath the conjoined tendon anterior to the subscapularis 3 to 5 mm medial to the musculotendinous junction [97].
- The axillary nerve splits into the anterior and posterior branches within the quadrangular space [97].
- The anterior and middle deltoid muscle receives sole innervation from the anterior branch of the axillary nerve [97].
- Posterior deltoid muscle innervation varies, with supply only from the anterior branch in 2.3% of cases, from the posterior branch in 8.5%, and from both branches in 89.1% [97].
- The posterior branch of the axillary nerve branches to supply the teres minor muscle and then terminates as the superior lateral brachial cutaneous nerve [97].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the suprascapular nerve runs deep to the ligament [94].
- Entrapment of the suprascapular nerve at the superior transverse scapular ligament causes denervation of both the supraspinatus and the infraspinatus [94].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [94].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [94].
Pathophysiology
- Glenohumeral arthritis is defined as a condition in which the normal articular surfaces of the humeral head and glenoid are compromised by degeneration, inflammation, or injury [134].
- The rotator cuff compresses the humeral articular surface into the glenoid concavity, a mechanism referred to as "concavity compression" [134].
- If the glenoid concavity is compromised, the humeral head is no longer stabilized [134].
- In degenerative joint disease, articular cartilage fails from heavy use, cumulative minor traumatic episodes, underlying structural defects, anomalies in carticular composition, or a combination of these factors [134].
- Capsulorrhaphy arthropathy is a complication of prior repair for glenohumeral instability involving overtightening of the anterior capsule causing posterior humeral subluxation and/or prominent hardware causing excoriation of the humeral articular cartilage [134].
- In rheumatoid and other types of inflammatory arthritis, cartilage is uniformly destroyed by an autoimmune reaction with characteristic periarticular osteopenia, marginal erosions, and minimal osteophyte formation [134].
- Chondrolysis is an iatrogenic condition in which glenohumeral articular cartilage is destroyed, most commonly due to the toxic effects of local anesthetics infused by a pain pump after arthroscopic surgery [134].
- In avascular necrosis, the bone supporting the humeral articular cartilage collapses, often because of corticosteroid use, alcoholism, or prior trauma [134].
- In posttraumatic arthritis, the anatomy of the glenohumeral joint is distorted due to a prior fracture with malunion or nonunion [134].
- Rotator cuff tear arthropathy is the combination of an irreparable rotator cuff defect and glenohumeral arthritis, which may lead to anterosuperior escape and pseudoparalysis [134].
- Neurotropic arthropathy arises in association with syringomyelia, diabetes, or other causes of joint denervation [134].
- The etiology of stiff shoulder development remains elusive, with current research focused on immunologic basis and the role of cell signaling and inflammatory mediators [112].
- Frozen shoulder is primarily a capsular pathology with signs of inflammation, fibroblast proliferation, and neovascularization [112].
- There is a clear association of diabetes mellitus and Dupuytren’s contracture with frozen shoulder [112].
- Current research is focused on defining the role of matrix metalloproteinases (MMPs), tissue inhibitors of metalloproteinases (TIMPs), other cytokines, and cytogenetics in frozen shoulder [112].
- Rheumatoid arthritis is a systemic autoimmune disorder that affects multiple joints [54].
- Erosive pannus formation within the joint and the release of inflammatory cytokines result in cartilage damage, bone resorption, and soft-tissue degradation in rheumatoid arthritis [54].
- Up to 75% of patients with rheumatoid arthritis eventually develop rotator cuff pathology [54].
- Between 25% and 30% of patients with rheumatoid arthritis have full-thickness rotator cuff defects at the time of surgery [54].
- Of patients with rheumatoid arthritis for more than 5 years, 91% develop shoulder symptoms [54].
- Classic radiographic findings for inflammatory arthritis of the shoulder include osteopenia, marginal erosions, and cyst formation [54].
- Advanced inflammatory arthritis is characterized by concentric joint space narrowing and medial glenoid wear [54].
- Large, irreparable rotator cuff tears in inflammatory arthritis may result in superior migration of the humeral head, "acetabularization" of the acromion, and rounding of the greater tuberosity [54].
- Neer identified three types of shoulder rheumatoid arthritis based on radiographic findings: dry, wet, and resorptive [54].
- The dry form of rheumatoid arthritis presents with joint space narrowing, subchondral cysts, erosions with marginal osteophytes [54].
- The wet form of rheumatoid arthritis presents with marginal erosions and a pointed contour of the proximal humerus [54].
- The resorptive form of rheumatoid arthritis presents with rapid bone and cartilage loss with centralization (medialization to the level of the coracoid process) of the glenohumeral joint [54].
- In the wet form of rheumatoid arthritis, exuberant granulations with marginal erosion cause the ends of the bone to become pointed [59].
- Severe destruction of the glenoid in wet rheumatoid arthritis occurs due to granulation erosion, disuse osteopenia, and pressure erosion from the pointed end of the humerus [59].
- Centralization in rheumatoid arthritis is associated with severe bone loss and loss of the contour of the shoulder, resembling a Burgundy wine bottle without shoulders [59].
- Primary osteoarthritis of the shoulder has an unknown cause, but a genetic predisposition may be present [119].
- Secondary causes of shoulder osteoarthritis can be posttraumatic, postsurgical, or a result of persistent or recurrent shoulder instability [119].
- Posterior glenoid wear and posterior humeral head subluxation occur in up to 45% of shoulders affected by primary osteoarthritis [119].
- The anterior soft tissues, including the anterior capsule and the subscapularis, become contracted in primary osteoarthritis, limiting external rotation [119].
- Joint space narrowing and periarticular osteophyte formation occur most commonly on the inferior aspects of the humeral head in primary osteoarthritis, referred to as a "goat’s beard" [119].
- Full-thickness rotator cuff tears are rarely (5% to 10%) associated with primary osteoarthritis [119].
- Walch et al identified three types of glenoid morphology associated with primary glenohumeral osteoarthritis based on erosion and bone loss [119].
- Type A glenoid morphology in primary osteoarthritis is concentric wear with no subluxation, occurring in 59% of cases [119].
- Type B glenoid morphology in primary osteoarthritis involves posterior humeral subluxation, occurring in 32% of cases [119].
- Type C glenoid morphology in primary osteoarthritis involves glenoid retroversion greater than 25° from dysplasia, occurring in 9% of cases [119].
- Type D glenoid morphology involves any level of glenoid anteversion or with humeral head subluxation of less than 40% (anterior subluxation) [119].
- Progressive contracture of the anterior capsule limits external rotation and leads to obligate posterior humeral translation, increased force on the posterior glenoid, and eventual posterior glenoid erosion [131].
- An excessively tight anterior capsular repair can force the head of the humerus posteriorly, accentuating posterior subluxation [131].
- The manifestation of early glenohumeral arthritis in the young adult is a devastating occurrence with a multifactorial nature that compounds treatment difficulty [24].
- Untreated subscapularis tears can lead to dynamic anterior instability and glenohumeral arthrosis [122].
- The subscapularis forms the anterior portion of the transverse plane "force couple" of the rotator cuff, balancing forces to maintain glenohumeral congruency [122].
- Shoulders with rotator cuff tears require considerable compensatory deltoid function to prevent abduction motion loss [160].
- The biomechanical shoulder model is consistent with clinical observations regarding glenoid inclination and acromion index effects on humeral head translation and cartilage strain [45].
- Critical shoulder angle should be considered as a "combined shoulder angle" with balanced contributions of glenoid inclination and acromial angle in shoulder
Classification
Glenoid Morphology and Wear Patterns
- Pathoanatomic metrics with identified threshold values can be used to discriminate glenoid types in shoulders with primary glenohumeral osteoarthritis [17].
- An anatomic pattern of glenoid bone loss exists for different classes of glenohumeral arthritis [25].
- Shoulders presenting with posterior subluxation (B types) remained posteriorly subluxed over a decade, while concentric arthritis developed an eccentric pattern 20% of the time [64].
- A small lateral extension and less posterior rotation of the acromion is associated with shoulder osteoarthritis and is present in almost all types and subtypes of glenoid morphology [128].
- Patients with primary osteoarthritis and glenoid type A show barely any differences in scapular morphology and scapulothoracic orientation compared to a healthy control group [86].
- The Walch Classification was used to assess OA grade at the time of conversion to shoulder arthroplasty, with 55.1% of patients exhibiting A1-type OA, 18.4% A2, 16.3% B1, and 10% B2 [37].
- Preoperative imaging in a cohort of shoulders with glenoid bone loss showed 4 type A2 glenoids and 2 type C glenoids according to the Walch classification [42].
- The mean preoperative glenoid retroversion was 18.5° (range, 9.5°-30°) in shoulders with severe glenoid bone loss [42].
- The humeral subluxation index showed a mean preoperative measurement of 53.0% and a postoperative measurement of 53.1% in shoulders with glenoid bone loss [42].
- A well-centered glenoid has a humeral subluxation index value of 45% to 55% [42].
- Measurement of humeral subluxation in the glenoid hull plane may be more accurate than in the scapular plane [30].
- Subluxation was greater in B2 glenoids compared to non-B2 glenoids using both the scapular method and the modified method [207].
- The mean subluxation percentage was 73.5% (SD 15.1%) using the scapular method and 59.7% (SD 11.2%) using the modified method [207].
- A 3D classification system using combined humeroscapular alignment and glenoid erosion can be applied to describe degenerative glenohumeral arthritis comprehensively [113].
- Current classifications exhibit poor reliability in categorizing glenoid defects post-reverse shoulder arthroplasty removal [121].
Humeral Head Morphology
- Osteoarthritic humeral head morphology varies significantly from normal, with larger spherical diameters [183].
- Osteoarthritic humeral head morphology does not vary as a function of the Walch classification between symmetric and asymmetric glenoids [183].
- The Samilson and Prieto classification system grades an inferior humeral head osteophyte by millimeters of extension, with <3 mm as grade I, 3 to 7 mm as grade II, and >7 mm as grade III [205].
- A modified Samilson and Prieto classification includes an osteophyte between 8 and 12 mm as grade III and >12 mm as grade IV [205].
- Mild dislocation arthropathy is indicated by an inferior humeral or glenoid exostosis measuring less than 3 mm in height [203].
- Moderate dislocation arthropathy is indicated by an inferior humeral or glenoid exostosis measuring between 3 and 7 mm in height, with slight glenohumeral-joint irregularity [203].
- Severe dislocation arthropathy is indicated by an inferior humeral or glenoid exostosis measuring more than 7 mm in height, with narrowing of the glenohumeral joint and sclerosis [203].
Rheumatoid Arthritis Classifications
- Rheumatoid arthritis involvement is classified clinically as low-grade, intermediate, or severe [59].
- The dry form of rheumatoid arthritis is characterized by sclerosis, subchondral cysts, loss of joint space, minimal margin erosion, and marginal osteophytes [59].
- The wet form of rheumatoid arthritis is characterized by exuberant granulations with marginal erosion, causing the ends of the bone to become pointed [59].
- The wet and resorptive form of rheumatoid arthritis is associated with severe bone loss and central migration of the humerus [59].
- "Centralization" in rheumatoid arthritis is characterized by severe loss of bone, loss of shoulder contour, and a flattened point resembling a Burgundy wine bottle [59].
- The "ascending" form of rheumatoid arthritis is characterized by upward migration of the humeral head preceding glenoid wear, with the head retaining sphericity [200].
- The "centred" form of rheumatoid arthritis is characterized by the absence of upward migration and uniform wear of the glenoid throughout its height [200].
- The "destructive" form of rheumatoid arthritis is characterized by destruction of the humeral head, loss of sphericity, and a "champagne cork" appearance at the anatomical neck [200].
- Radiographic assessment of glenoid wear in rheumatoid arthritis on a true AP view is staged as stage 1 (subchondral bone intact or minimally deformed), stage 2 (wear reaching the foot of the coracoid), and stage 3 (wear beyond the foot of the coracoid) [59].
Septic Arthritis Classifications
- Septic arthritis is divided into four arthroscopic stages: Stage I (opacity of fluid, redness, no radiological alterations), Stage II (severe inflammation, fibrinous deposition, pus, no radiological alterations), Stage III (thickening of synovial membrane, compartment formation, no radiological alterations), and Stage IV (aggressive pannus with cartilage infiltration, subchondral osteolysis, osseous erosions) [156].
- The Tan et al. classification system for septic joints is based on anatomic type, host class, and clinical setting [156].
- Anatomic type I in the Tan et al. classification is periarticular soft-tissue infection without pyarthrosis [156].
- Anatomic type II in the Tan et al. classification is isolated septic arthritis [156].
- Anatomic type III in the Tan et al. classification is septic arthritis with soft-tissue extension but no osteomyelitis [156].
- Anatomic type IV in the Tan et al. classification is septic arthritis with contiguous osteomyelitis [156].
- Host class A in the Tan et al. classification represents a patient with a normal immune system [156].
- Host class B in the Tan et al. classification represents a compromised system, either locally (B_L) or systemically (B_S) [156].
- Host class C in the Tan et al. classification is reserved for patients where risks of aggressive treatment outweigh the negative aspects of infection [156].
- Clinical setting 1 in the Tan et al. classification includes less than 5 days of symptoms and a nonvirulent organism [156].
- Clinical setting 2 in the Tan et al. classification includes symptoms for 5 days or more, or a virulent organism [156].
Frozen Shoulder Classifications
- Primary frozen shoulder is defined by total elevation restricted to 135° or less, restriction localized to the humero-scapular joint, and no findings explaining the decreased range of motion [196].
- Secondary frozen shoulder is defined by decreased range of motion following a traumatic lesion, such as soft tissue injury or fractures [196].
- Stage 1 of frozen shoulder according to Reeves is characterized by pain with a duration of 10 to 36 weeks [196].
Periprosthetic Fracture Classifications
- The Wright and Cofield classification divides periprosthetic humeral fractures into type A (propagate proximally from the distal stem), type B (centered over the distal stem), and type C (located distal to the tip of the stem) [181].
Rotator Cuff and Muscle Atrophy Classifications
- The Goutallier classification grades fatty infiltration of rotator cuff musculature from Grade 0 (normal muscle) to Grade 4 (more fat than muscle) [194].
- Fuchs simplified the Goutallier classification into three categories by combining grades 0 and 1 as normal and grades 3 and 4 as advanced degeneration [194].
- Zanetti’s “tangent sign” is a binary method where a positive sign indicates significant muscular atrophy if the supraspinatus muscle belly fails to intersect a line drawn from the superior border of the coracoid to the superior border of the scapular spine [194].
- The Thomazeau “occupation ratio” considers cross-sectional area of the muscle belly relative to fossa size, with 0.6–1.0 indicating normal or slight atrophy, 0.4–0.6 indicating moderate atrophy, and <0.4 indicating severe atrophy [194].
- The Patte classification for full-thickness rotator cuff tears categorizes tears by extent (Groups I–IV), topography in the sagittal plane (Segments 1–6), topography in the frontal plane (Stages 1–3), trophic quality, and state of the long head of biceps [194].
- The Ellman and Gartsman classification categorizes full-thickness rotator cuff tears as Crescent (A), reverse L (B), L-shaped (C), trapezoidal (D), or massive (E) [194].
Acromioclavicular Joint Injury Classifications
- Grade I acromioclavicular sprains involve a mild force with only a few fibres of the acromioclavicular ligament and capsule involved, with no laxity [195].
- Grade II acromioclavicular sprains involve rupture of the capsule and acromioclavicular ligament, frequently referred to as subluxation, with no rupture of coracoclavicular ligaments [195].
- Grade III acromioclavicular sprains involve rupture of both the acromioclavicular and coracoclavicular ligaments, frequently referred to as dislocation [195].
- Grade III acromioclavicular separations are described as 100% displacement of the clavicle on radiographs compared with the contralateral side [198].
- Grade V acromioclavicular separations are described as exaggerated superior dislocation between 100% and 300% as seen radiographically [198].
Clinical Presentation
General Presentation and Epidemiology
- Shoulder arthritis is common, and management strategies continue to evolve with significant improvements in implant design, though longevity remains a concern in more active patients [2].
- The incidence of primary glenohumeral osteoarthritis was 0.4% in patients with orthopaedic complications and 4.6% in patients who had shoulder diseases [16].
- Increased age is the main determinant of radiological changes in shoulder osteoarthritis, as well as pain [65].
- The manifestation of early glenohumeral arthritis in the young adult is a devastating occurrence, and the multifactorial nature of this disease process compounds the difficulty in overall treatment [24].
- Glenohumeral arthrosis after anterior repair affects younger patients than typical glenohumeral osteoarthritis [63].
- Chronic renal disease may lead to a general arthropathy which can be quite disabling in the shoulder joints [73].
- Septic arthritis of the shoulder joint is rare but increases in incidence with age, and delays in diagnosis of greater than a month are frequent because systemic illness is relatively uncommon [12].
- Rapidly destructive arthrosis of the shoulder joints should be considered in the differential diagnosis of elderly women with insidious shoulder pain [26].
- Physicians and orthopedic surgeons should consider gouty shoulder arthritis when severe erosion is present in patients with a history of gout [74].
History Taking
- The history and physical examination are paramount for the diagnosis of a stiff shoulder, and ancillary studies may also be helpful in certain circumstances [7].
- Treatment should begin with a dialogue between the surgeon and the patient regarding the diagnosis, the probable natural history of the condition if untreated, and the potential risks and benefits of different treatment options [49].
- Patients with glenohumeral arthritis often present with pain and stiffness that usually occurs over years, whereas frozen shoulder onset occurs over weeks to months [130].
- A single true anteroposterior radiograph of the shoulder can easily differentiate idiopathic frozen shoulder from glenohumeral arthritis [130].
- Most patients with rheumatoid arthritis report generalized fatigue, pain in other joints, intermittent fever, and weight loss [54].
- Pain, swelling, progressive loss of motion, and weakness commonly are seen in the affected shoulder in rheumatoid arthritis [54].
- The history should define the mechanism of injury, including the position of the arm, the amount of force applied, and the point of force application [129].
- Injury with the arm in extension, abduction, and external rotation favors anterior dislocation [129].
- Electoshock, seizures, or a fall on the flexed and adducted arm are commonly associated with posterior dislocation [129].
- If instability is recurrent, the history defines the initial injury, the position or action that results in instability, how long the shoulder stays out of joint, and what means have been necessary to reduce the shoulder [129].
- The history solicits evidence of neurologic or rotator cuff problems after previous episodes of shoulder instability [129].
- Previous treatment of recurrent instability, as well as the effectiveness of this treatment, should be documented in the history [129].
- A comprehensive history is the first and arguably the most important aspect of a complex decision-making process in evaluating a patient with a suspected rotator cuff tear [135].
- The patient’s physiologic and chronologic age should be considered throughout history and examination [135].
- Degenerative tearing typically occurs in older patients, while a greater injury is required to tear the cuff of persons at the younger end of the age distribution [135].
- Traumatic glenohumeral dislocations in persons older than 40 years have a strong association with rotator cuff tears [135].
- Activity level and expectations of treatment are an essential part of the overall decision-making process and discussion with the patient [135].
- In all patients, prior treatment including physical therapy, injections, and previous surgery should be noted in the history [135].
- Any neck pain, numbness and tingling in the arm, symptoms radiating below the elbow, or medial scapular pain may be a sign of cervical radiculopathy [135].
Physical Examination
- Common findings during early stages of rheumatoid arthritis include localized warmth and limited range of motion with pain [54].
- In a more chronic condition of rheumatoid arthritis, crepitus and weakness also may be encountered [54].
- Periscapular atrophy may be noted if an associated rotator cuff tear is present in rheumatoid arthritis [54].
- Sternoclavicular or acromioclavicular joint tenderness occurs in about one-third of patients with glenohumeral involvement in rheumatoid arthritis [54].
- An acutely dislocated shoulder is usually very painful, and muscles are in spasm in an attempt to stabilize the joint [129].
- The humeral head may be palpable anteriorly in an acutely dislocated shoulder [129].
- The posterior and lateral aspect of the shoulder shows a hollow beneath the acromion in an acutely dislocated shoulder [129].
- The arm is held in slight abduction in an acutely dislocated shoulder [129].
- Passive and active motions are limited by pain in an acutely dislocated shoulder [129].
- An essential part of the physical examination of an anteriorly dislocated shoulder is assessment of the neurovascular status of the upper extremity and charting of the findings before reduction [129].
- Recognition of a posterior dislocation may be impaired by the lack of a striking deformity of the shoulder and by the fact that the shoulder is held in the traditional sling position of adduction and internal rotation [129].
- Limited external rotation of the shoulder, often to <0 degrees, is a classic feature of posterior dislocation [129].
- Limited elevation of the arm, often to <90 degrees, is a classic feature of posterior dislocation [129].
- Posterior prominence and rounding of the shoulder in comparison to the normal side is a classic feature of posterior dislocation [129].
- Flattening of the anterior aspect of the shoulder is a classic feature of posterior dislocation [129].
- Prominence of the coracoid process on the dislocated side is a classic feature of posterior dislocation [129].
- Asymmetry of the shoulder contours can often best be visualized by viewing the shoulders from above while standing behind the patient [129].
- Motion is limited in posterior dislocation because the head of the humerus is fixed on the posterior glenoid rim by muscle forces, or the head might actually be impaled on the glenoid rim [129].
- Patients with old, unreduced posterior dislocations of the shoulder can have 30 to 40 degrees of glenohumeral abduction and some humeral rotation as a result of enlargement of the groove [129].
- With long-standing disuse of the muscles about the shoulder, atrophy will be present, which accentuates the flattening of the anterior portion of the shoulder, the prominence of the coracoid, and the fullness of the posterior portion of the shoulder [129].
- The hallmark of a frozen shoulder is the corresponding loss of both passive and active range of motion [141].
- A major reason why practitioners that are not experienced with shoulder pathology miss the diagnosis of frozen shoulder is that they do not test range of motion [141].
- The examiner often moves directly to more provocative maneuvers to assess the rotator cuff, which are often positive in frozen shoulder patients [141].
- A complete cervical examination should be performed, including neurologic testing of the extremities, when evaluating a frozen shoulder [141].
- The shoulder should be inspected for signs of trauma or previous surgery, which may provide clues for the diagnosis of acquired stiffness [141].
- Important landmarks, such as the acromioclavicular joint and bicipital groove, are palpated for tenderness [141].
- Range of motion, both active and passive, should be tested in all planes and recorded as objectively as possible [141].
- Range of motion measurements should be repeated in the contralateral shoulder [141].
- It is essential to differentiate glenohumeral motion from humeroscapular motion as many patients with glenohumeral stiffness can compensate with scapulothoracic motion [141].
- Glenohumeral motion is best examined by examining the patient in the supine position with the arm free so that the scapula is being compressed against the chest wall through gravity [141].
- Alternatively, the examiner can stabilize the scapula with one hand while passively moving the arm with the other to differentiate glenohumeral motion [141].
- Strength testing of the rotator cuff is performed using standard manual motor testing as well as special tests (belly press, lift-off, lag signs, hornblower’s sign) [141].
- Provocative tests for impingement, acromioclavicular joint pathology, labral tears, instability, and biceps pathology may also be indicated depending on the history and clinical suspicion [141].
- Patients with frozen shoulder have what is often described as achy discomfort at rest and severe pain with attempted movements, especially sudden movements [141].
- Difficulty with sleeping is an almost universal complaint in patients with frozen shoulder [141].
- During the frozen phase of frozen shoulder, the pain tends to abate, but motion becomes severely limited in all planes [141].
- Even simple tasks, such as turning off the light and washing hair, become chores during the frozen phase of frozen shoulder [141].
- Sleeping is usually problematic during the frozen phase of frozen shoulder [141].
- In the final stage of frozen shoulder, range of motion slowly returns and residual discomfort generally resolves [141].
- Return of flexibility in the final stage of frozen shoulder can take months to years [141].
- Motion restrictions often persist in the final stage of frozen shoulder, but are generally mild and do not cause significant impairment [141].
- Shoulder dysfunction can often be associated with subtle or overt neurologic deficits [154].
- Some degree of neurologic testing in the form of isolated muscle strength testing, sensory testing, and reflex testing is needed to fully evaluate most shoulders [154].
- Every assessment of shoulder muscle strength must be performed bilaterally to allow the comparison of the relative strength between the involved and uninvolved shoulders [154].
- A comprehensive evaluation of muscle strength can identify weakness resulting from pain-related muscle inhibition [154].
- A comprehensive evaluation of muscle strength can reveal weakness not anticipated based on patient history and functional assessments [154].
- A comprehensive evaluation of muscle strength can demonstrate better strength than expected for a patient’s level of functional impairment [154].
- The position of testing is selected to best isolate the function of each individual muscle group so that groups of muscles are not tested in conjunction with each other [154].
- Isometric muscle testing with the involved joint and muscle in a position of optimal mechanical advantage results in the most consistent, reproducible assessment of strength [154].
- Full symmetrical muscle strength is assessed with the involved muscle in its position of maximal shortening because this position accentuates subtle weakness within the muscle that might otherwise go undetected in stronger patients [154].
- Muscle strength testing of the deltoid should independently assess the anterior, middle, and posterior bundles of the deltoid [154].
- The anterior bundle of the deltoid is assessed by placing the shoulder in 90 degrees of forward flexion with the elbow extended and the arm in neutral rotation [154].
- The middle bundle of the deltoid is assessed by placing the shoulder in 90 degrees of abduction with the elbow extended and the palm of the hand facing up [154].
- The position of external rotation in abduction rotates the greater tuberosity out from under the acromion, decreasing the likelihood of supraspinatus impingement within the subacromial space [154].
- The posterior bundle of the deltoid is tested by placing the shoulder in extension with the elbow flexed to 90 degrees [154].
- Applying force at the flexed elbow eliminates confusion that might arise from pushing at the wrist with the elbow extension, which can lead to breaking of the elbow extension and a misperception that the isometric posterior deltoid is weak [154].
- The biceps is tested with the shoulder in neutral rotation, the elbow flexed fully, and the palm in full supination [154].
- The brachialis is tested with the forearm placed in full pronation to prevent co-contraction of the biceps, which would bring the forearm into supination [154].
- The triceps is tested with the arm in 90 degrees of forward elevation with the elbow fully extended and the hand in full supination [154].
- The patient resists elbow flexion while the examiner attempts to flex the elbow by stabilizing the arm with one hand on the biceps and applying force at the wrist with the other hand for triceps testing [154].
- Superior trapezius and levator scapulae are tested by having the patient perform a shoulder shrug while the examiner attempts to hold the shoulders in a depressed position [154].
- Middle trapezius and rhomboids are tested by having the patient pinch the shoulder blades together while the examiner places several fingers along the medial border of the scapula [154].
- Although absolute strength testing of the middle trapezius and rhomboids is not possible with this maneuver, the quality of the contraction can generally be assessed by direct palpation of the involved rhomboids and middle trapezius [154].
Diagnostic Assessment and Imaging
- There is no reliable laboratory test or imaging modality for primary idiopathic frozen shoulder, which is ultimately a clinical diagnosis [130].
- Usually the patient’s history and examination provide the only information required to diagnose frozen shoulder [130].
- The diagnosis of frozen shoulder should be considered in patients that present with some degree of pain associated with the corresponding loss of both passive and active range of motion [130].
- It is essential to consider the patient’s age, gender, and additional risk factors when considering the diagnosis of idiopathic frozen shoulder [130].
- The most relevant risk factors for idiopathic frozen shoulder are age between 40 and 60 years, female sex, and having diabetes [130].
- If a patient lacks the three risk factors of age between 40 and 60 years, female sex, and diabetes, then other diagnoses should strongly be considered [130].
- A complete blood cell count, erythrocyte sedimentation rate, C-reactive protein level, uric acid level, rheumatoid factor, serum complement, HLA-B27 screening, and antinuclear antibody titer are helpful in confirming the diagnosis of inflammatory arthritis [54].
- Arthrocentesis may be helpful in the setting of an acutely painful shoulder to rule out septic arthritis and crystalline arthropathies [54].
- Fluid tests for arthrocentesis include cell count, Gram stain, culture, and crystal analysis [54].
- Milwaukee shoulder aspirates contain blood-tinged fluid with debris, hydroxyapatite crystals, and inflammatory cells with a preponderance of monocytes [54].
- The diagnosis of Milwaukee shoulder is confirmed by positive staining of the crystals with alizarin red [54].
- Gout can be diagnosed by the characteristic negatively birefringent, needle-shaped deposition of sodium urate crystals [54].
- Pseudogout joint fluid is characterized by positively birefringent, rhomboid-shaped calcium pyrophosphate dihydrate crystals [54].
- Large, irreparable rotator cuff tears may result in superior migration of the humeral head, “acetabularization” of the acromion, and rounding of the greater tuberosity [54].
- CT should be performed when large bony defects or deformities are present in inflammatory arthritis [54].
- MRI is useful for evaluating the integrity of the rotator cuff tendons and muscle quality in inflammatory arthritis [54].
- A preoperative radiographic examination of the cervical spine is mandatory for patients with inflammatory arthritis to assess cervical spine stability before intubation [54].
- Dry rheumatoid arthritis is characterized by joint space narrowing, subchondral cysts, erosions with marginal osteophytes [54].
- Wet rheumatoid arthritis is characterized by marginal erosions (sometimes quite extreme) and a pointed contour of the proximal humerus [54].
- Resorptive rheumatoid arthritis is characterized by rapid bone and cartilage loss with centralization (medialization to the level of the coracoid process) of the glenohumeral joint [54].
- Plain radiographs at the advanced stage of septic arthritis can show changes from joint space narrowing and bone destruction, but these are insensitive and nonspecific in the early stage [52].
- Clinical signs such as redness, limited range of motion, serologic markers, aspirated joint fluid analysis, and culture can support a diagnosis of septic arthritis of the shoulder joint, but it cannot reflect the severity of the disease [52].
- F-18-FDG PET/CT effectively differentiates septic shoulder arthritis from varying stages of osteoarthritis [68].
- To reduce the severity of septic shoulder infection, timely diagnosis and treatment are essential [117].
- Preoperatively, the history and physical examination are most important for evaluating painful glenoid arthrosis after humeral head replacement [139].
- Current X-ray images, including an axillary
Investigations
Plain Radiography and Standardized Views
- The purpose of shoulder imaging is to establish diagnosis, determine pathoanatomic severity, assist in surgical planning, and illustrate the condition to the patient [46].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder arthroplasty planning [46].
- CT scans may offer increased precision in measuring glenoid version, but this precision does not necessarily improve surgical quality or clinical outcome [46].
- The first key radiographic view is the anteroposterior (AP) view in the plane of the scapula, taken so the x-ray beam passes through the glenohumeral joint [46].
- The AP view in the scapular plane shows the superoinferior position of the humeral head relative to the glenoid, presence of osteophytes, joint space narrowing, medial displacement of the humerus, bone quality, loose bodies, and humeral head collapse or deformity [46].
- The second key radiographic view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [46].
- The axillary view is oriented so that both the spinoglenoid notch and the scapular neck are visible [46].
- The axillary view demonstrates glenohumeral relationships in the functional position of elevation, referred to as the "truth view" [46].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the functional axillary view [46].
- Joint space narrowing is most evident on the axillary truth view because arthritis usually involves the central aspect of the humeral head [46].
- The standardized axillary view can show posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [46].
- The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the plane of the scapula [46].
- The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the glenoid face [46].
- The degree of posterior subluxation can be measured by the point of contact of the humeral articular surface on the glenoid articular surface [46].
- The point of contact of the humeral articular surface on the glenoid reflects the degree of centering of the net humeral joint reaction force on the glenoid [46].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and "rocking horse" loosening of prosthetic glenoid components [46].
- The standard shoulder series should include a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [114].
- The true AP view in the scapular plane visualizes the anterior greater tuberosity in profile with the x-ray beam perpendicular to the plane of the scapula [114].
- The AP view is taken with the arm in internal rotation to visualize the posterior aspect of the greater tuberosity and the lesser tuberosity in profile [114].
- The axillary view is necessary for evaluating glenohumeral joint instability and determining humeral head position in the glenoid fossa [114].
- The axillary view may detect occult, locked posterior shoulder dislocation in a patient who exhibits a lack of passive external rotation [114].
- The axillary view is helpful in evaluating glenoid morphology in glenohumeral osteoarthritis [114].
- The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs associated with rotator cuff pathology [114].
- The scapular Y view is a reliable alternative for evaluating glenohumeral subluxation and dislocation [114].
- The acromiohumeral distance is normally 7 to 14 mm [114].
- The width of the glenohumeral joint space should be symmetric superiorly and inferiorly [114].
- The coracoclavicular distance is normally 1.1 to 1.3 cm [114].
- Neer classified acromial morphology as type I (flat), type II (curved), and type III (hooked) [114].
- Type III acromial morphology has been shown to have a correlation with the presence of rotator cuff disease, though no direct causal relationship has been demonstrated [114].
- The Neer trauma series consists of an AP view, a lateral view in the scapular plane, and a Velpeau modified axillary view [107].
- The lateral radiograph in the scapular plane is the tangential Y-view of the scapula [107].
- The combination of the three views in the Neer trauma series allows evaluation of the shoulder joint in three separate perpendicular planes [107].
- The axillary view is important for evaluating the glenoid articular surface and the relationship of the humeral head anteriorly and posteriorly [107].
- Radiographs at 6-month follow-up demonstrate a space between the humeral head and the glenoid in all cases of surgical treatment for glenohumeral arthritis in the young patient [21].
- A quantitative method using plain radiographs can determine the rate of medial migration of the humeral head after shoulder arthroplasty [224].
- Radiographic assessment of scapular notching is not reliable [220].
Computed Tomography (CT)
- CT imaging is frequently used to assess for bony lesions in recurrent instability cases or for preoperative templating for shoulder arthritis [111].
- CT with three-dimensional reconstructions is the advanced imaging study of choice for determining the extent of glenoid bone loss in the setting of shoulder instability [114].
- Three-dimensional CT reconstruction allows for reliable evaluation of the scapulohumeral relationship [219].
- 3D CT reconstruction reveals significant posterior translation of the humeral head in osteoarthritic shoulders compared to nonpathologic controls [219].
- This posterior translation supports the pathomechanism of glenoid component loosening [219].
- Patients with primary osteoarthritis and glenoid type A barely show differences in scapular morphology and scapulothoracic orientation compared to a healthy control group [86].
- Arthritic B2 glenoids are common, and their maximal erosion is usually posteroinferior [69].
- Three significantly differently oriented wear patterns (posterior-superior, posterior-central, and posterior-inferior) were distinguished in shoulders demonstrating posterior wear on axillary imaging [227].
- These data demonstrate an anatomic pattern of glenoid bone loss for different classes of glenohumeral arthritis [25].
- The critical shoulder angle is an effective radiographic parameter that is associated with rotator cuff tears and osteoarthritis [215].
- Surgeons may consider using reverse arthroplasty in cases of primary shoulder arthritis with a critical shoulder angle of 35 degrees or greater [87].
Magnetic Resonance Imaging (MRI)
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [111].
- T1-weighted MRI can reveal Hill-Sachs lesions and is often used with magnetic resonance arthrograms to provide a more detailed picture of the joint surfaces [111].
- T2-weighted MRI provides better visualization of full-thickness rotator cuff tears [111].
- MRI is useful for preoperative osseous imaging for total shoulder arthroplasty because it offers a more precise method of determining glenoid version compared with x-ray imaging [174].
- MRI effectively displays the pathologic changes that result from injuries and nontraumatic disorders that involve the acromioclavicular joint [197].
- The value of the routine use of MRI for the diagnosis and management of arthropathy of the acromioclavicular joint has been questioned [197].
- Degenerative findings of the acromioclavicular joint are just as likely to be present in asymptomatic persons [197].
- MRI is more sensitive for osteoarthritis of the acromioclavicular joint than conventional radiography [197].
- Reactive bone edema in the distal clavicle, medial acromion, or both is a more reliable predictor of acromioclavicular pathology than degenerative changes [197].
- Fluid in the acromioclavicular joint is a common MRI finding in patients with shoulder problems [197].
- Advancing age, acromioclavicular joint osteophytes, and glenohumeral joint fluid are notable associated findings that suggest a relationship between acromioclavicular joint fluid and osteoarthritis [197].
- Rapidly destructive arthrosis of the shoulder joints should be considered in the differential diagnosis of elderly women with insidious shoulder pain based on radiographic, magnetic resonance imaging, and histopathologic findings [26].
Arthrography
- Arthrography involves injection of contrast agent in conjunction with either an MRI or CT scan to enhance imaging of the joint [111].
- MR arthrography is considered the benchmark for evaluation of labral tears and is rarely indicated for evaluation of rotator cuff pathology [111].
- When MRI or MR arthrography is contraindicated, CT arthrography is indicated [111].
Ultrasonography
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [111].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [111].
- Ultrasonography can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [111].
- Ultrasonography can evaluate impingement in various positions and motions due to real-time imaging [111].
- Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [111].
- The sensitivity of ultrasonography for the detection of full-thickness rotator cuff tears is 98% [114].
- The specificity of ultrasonography for the detection of full-thickness rotator cuff tears is 80% [114].
- The positive predictive value of ultrasonography for the detection of full-thickness rotator cuff tears is 90% [114].
- The negative predictive value of ultrasonography for the detection of full-thickness rotator cuff tears is 95% [114].
- The accuracy of ultrasonography for the detection of full-thickness rotator cuff tears is 94% [114].
- The sensitivity of MRI for the detection of full-thickness rotator cuff tears is 100% [114].
- The specificity of MRI for the detection of full-thickness rotator cuff tears is 68% [114].
- The positive predictive value of MRI for the detection of full-thickness rotator cuff tears is 85% [114].
- The negative predictive value of MRI for the detection of full-thickness rotator cuff tears is 100% [114].
- The accuracy of MRI for the detection of full-thickness rotator cuff tears is 89% [114].
- Ultrasonography has proven utility for diagnosing septic arthritis of the acromioclavicular joint [197].
Outcome Assessment and Standardization
- There is a need for standardization of outcome assessment following treatment of shoulder arthritis [1].
- Cystic disease in the glenoid did not affect functional outcome or the presence of radiographic glenoid loosening in total shoulder arthroplasty with minimum 5-year follow-up [225].
- The study evaluated midterm clinical and radiographic outcomes of a cementless glenoid component, noting significant functional improvement but highlighting complications such as radiolucent lines, component loosening, and polyethylene wear [41].
- Radiolucencies were noted around the glenoid component and/or screws in 45% of shoulders in a study of uncemented glenoid components during total shoulder arthroplasty [43].
- Progressive radiolucencies, radiographic failure, and clinical loosening requiring revision remain a concern with cemented polyethylene glenoids [43].
- Radiolucencies between the cement-bone interface have been noted in 30 to 95% of cemented glenoids [43].
- At least one fifth of radiolucencies are progressive over time when using modern cement techniques [43].
- Glenoid component loosening of 4 to 15% has been reported clinically and radiographically at short and intermediate follow-up [43].
- In one long-term study, radiographic evidence of definite loosening was noted in 44% of the glenoid components [43].
- More bone imparted fewer overall component radiolucencies in a partially cemented pegged all-poly glenoid component [234].
Treatment
Non-Operative Management
- Nonoperative modalities should be utilized before surgical options, particularly for patients with moderate-to-mild disease [33].
- Any surgical treatment should be preceded by an adequate trial of conservative management that includes activity modification, physical therapy, antiinflammatory medication, and corticosteroid injections [47].
- Injectable viscosupplementation is an additional nonoperative treatment option, although there is a paucity of evidence that supports its use in the shoulder, and it is not currently approved by the U.S. Food and Drug Administration for injection in joints other than the knee [47].
- Frozen shoulder does not resolve spontaneously in a large number of patients [3].
- Treatment of stiff shoulder should be tailored to each individual patient to ensure the best possible outcome, as no treatment has proved to be definitive [7].
Arthroscopic Management
- The American Academy of Orthopaedic Surgeons clinical practice guidelines classify the use of arthroscopy for the treatment of glenohumeral arthritis as grade I, implying that they are unable to recommend for or against this option [47].
- A systematic review of the literature showed that arthroscopic debridement for glenohumeral arthritis lacks high-quality evidence to support its routine use [47].
- Arthroscopic débridement can be effective in mild to moderate glenohumeral arthritis, but durability of results is unpredictable [147].
- The best prognosis for arthroscopic débridement is in mild osteoarthritis with a centered humeral head and stiffness as the chief report [147].
- Arthroscopy provides an opportunity to diagnose and treat coexistent soft tissue pathology in patients with osteoarthritis, which may eliminate the need for arthroplasty [47].
- Arthroscopic intervention might be more suitable for elderly patients with significant medical comorbidities who are unable to tolerate the stresses involved with major surgery [47].
- Young patients with early onset arthritis might not be the best candidates for total shoulder arthroplasty due to concerns related to prosthesis longevity and/or high functional demands, making arthroscopic treatment a potential alternative [47].
- The authors recommend a systematic, inclusive approach to the array of pathologies encountered in the setting of early glenohumeral arthritis: the Comprehensive Arthroscopic Management (CAM) procedure [60].
- Arthroscopic debridement combined with localized antibiotic delivery using PMMA beads is an effective and safe treatment for septic shoulder arthritis [166].
Hemiarthroplasty and Resurfacing
- Hemiarthroplasty is an option for young and active patients with severe glenohumeral arthritis, but glenoid erosion and need for early revision have been challenges in this patient population [147].
- Hemiarthroplasty is associated with a high rate of glenoid erosion and revision, and its use should be limited to a young patient with severe glenohumeral arthritis and a high level of heavy activity [147].
- Copeland surface replacement arthroplasty provides good long-term symptomatic and functional results in the treatment of glenohumeral arthropathy in patients aged younger than 50 years in 81.6% of the patients [35].
- Registry data indicate a 2.5-year revision rate for resurfacing prostheses, which is more than three times the revision rate for stemmed hemiarthroplasty [62].
- Partial resurfacing prostheses create a major discontinuity in the deformation of the joint surface under load at the margin of the prosthesis due to a modulus of elasticity variation by a factor of 200,000 between the metal prosthesis and surrounding intact articular cartilage [62].
- Revision surgery was indicated in three of 11 patients (27%) undergoing arthroscopic partial shoulder resurfacing [44].
Anatomic Total Shoulder Arthroplasty
- Anatomic total shoulder arthroplasty is the benchmark for surgical treatment of glenohumeral arthritis with an intact rotator cuff [20].
- Anatomic total shoulder arthroplasty is the benchmark for primary glenohumeral arthritis with an intact rotator cuff and ample glenoid bone stock [147].
- Total shoulder arthroplasty generally provides superior results to hemiarthroplasty in terms of patient satisfaction, function, and strength, especially at longer-term follow-up [142].
- A Cochrane Database systematic review of seven studies found that total shoulder arthroplasty is associated with better shoulder function than hemiarthroplasty but does not provide any other significant clinical benefits [142].
- Total shoulder arthroplasty did not provide a clinically important advantage over hemiarthroplasty in terms of patient-reported pain, function, nor adverse effects; however, the evidence on this topic was of low quality [39].
- Treatment of end-stage glenohumeral arthritis refractory to conservative treatment in patients 30 to 50 years old in the United States with total shoulder arthroplasty, instead of hemiarthroplasty, would result in greater cost savings, avoid a substantial number of revision procedures, and result in greater years of satisfactory or excellent patient outcomes and greater QALYs gained [223].
- In elderly patients (≥64 years) with osteoarthritis, total shoulder arthroplasty was more cost-effective than hemiarthroplasty in improving quality of life [142].
- An economic decision model concluded that total shoulder arthroplasty was a more cost-effective intervention compared to hemiarthroplasty in young patients with shoulder arthritis [142].
- Results after total shoulder arthroplasty have been predictable in producing pain relief and functional improvements for patients with a variety of degenerative glenohumeral conditions, with good results reported in 65% to 95% of patients [142].
- The best functional results after total shoulder arthroplasty are obtained in patients with osteoarthritis because the rotator cuff usually is intact and of good quality and the bone stock is typically adequate [142].
- In patients with rheumatoid arthritis, the quality of the rotator cuff directly influences the functional result after total shoulder arthroplasty [142].
- Loosening of the glenoid component has been reported in almost half of shoulders at more than 10-year follow-up and is often associated with pain [142].
- Glenoid component loosening has averaged 4.3% over multiple studies [142].
- Results at long-term follow-up in several series have reported 85% component retention at 20 years of follow-up and revision rates for all causes averaging less than 10% [142].
- Patients undergoing total shoulder arthroplasty with an asymmetric glenoid component for osteoarthritis achieve satisfactory mid-term pain relief and improvement in function; however, instability is not always corrected [158].
- Patients achieved excellent functional outcomes and pain improvement after total shoulder arthroplasty with an augmented glenoid component [173].
- Both keeled and pegged glenoid components yield similar pain relief, functional gains, and shoulder motion across most patient-reported outcome measures in total shoulder arthroplasty for primary osteoarthritis [27].
- There was no clinically or statistically significant difference in the Oxford Shoulder Score results between cemented and uncemented glenoid fixation groups in total shoulder arthroplasty for degenerative arthritis [40].
- Stemless humeral components for total shoulder arthroplasty have been investigated and approved by the United States Food and Drug Administration (FDA) [151].
- Recent randomized controlled trials have reported clinical non-inferiority of stemless components relative to stemmed components in the setting of anatomic total shoulder arthroplasty [217].
- Improvements in patient-reported outcomes and range of motion in sports participants following stemless total shoulder arthroplasty support its efficacy for active patients with shoulder pathology [36].
- All 68 shoulders achieved satisfactory long-term results in a study of total shoulder replacement for primary glenohumeral osteoarthritis [31].
- Shoulder arthroplasty was effective within a relatively short time frame in improving the patients' assessment of both shoulder function and overall health status in patients with primary glenohumeral degenerative joint disease [5].
- Conversion total shoulder arthroplasty is effective for addressing painful glenoid arthrosis after primary humeral head replacement, with or without the need to change the humeral component [169].
Reverse Total Shoulder Arthroplasty
- Reverse total shoulder arthroplasty has gained popularity for rotator cuff arthropathy and other complex indications [20].
- Reverse total shoulder arthroplasty can address multiple issues including poor rotator cuff function, instability, and poor glenoid bone stock and is the treatment of choice in severe cuff tear arthropathy, and revision arthroplasty in elderly patients [147].
- The complication rate of reverse total shoulder arthroplasty is higher than anatomic total shoulder arthroplasty and patients commonly achieve less internal rotation postoperatively [147].
- Reverse total shoulder arthroplasty provides comparable clinical outcomes across indications of irreparable rotator cuff tear, rotator cuff tear arthropathy, and primary osteoarthritis at 2 years, supporting its broad applicability [56].
- The reverse total shoulder arthroplasty offers a treatment option for a problem that previously had no solution: the unstable, cuff-deficient shoulder [66].
- Complication rates are higher and functional improvement more modest when reverse shoulder arthroplasty is performed as a revision of a prior arthroplasty [66].
- Infection is one of the most common complications following reverse total shoulder arthroplasty and is probably related to many procedures being performed as revisions after multiple prior surgeries coupled with the dead space created when the humerus is displaced distally [66].
- Propionibacterium species is a frequently cultured organism from failed reverse total shoulders, which can present with loosening in the absence of the usual clinical signs of infection [66].
- Instability following reverse total shoulder arthroplasty can result from falls, suboptimal component selection, component malposition, bulky tissues in the posterior shoulder, leverage of the humeral component against the glenoid, or lack of a sufficient compressive effect by the deltoid [66].
- Early closed reduction can be successful for instability following reverse total shoulder arthroplasty [66].
- Recurrent or chronic instability following reverse total shoulder arthroplasty may require surgical revision [66].
- Stability following reverse total shoulder arthroplasty may be restored by changing to a larger diameter of curvature and increasing the thickness of the polyethylene humeral cup [66].
- The risk of humeral fracture is increased by revision surgery and by falls in reverse total shoulder arthroplasty [66].
- The risk of humeral fracture in reverse total shoulder arthroplasty is also increased when the humeral component fixation results in an abrupt transition between a cemented or press-fitted diaphyseal stem tip and osteopenic bone distal to the prosthesis [66].
- Shoulder arthritis management strategies, especially in young patients, continue to evolve with significant improvements in implant design, though longevity remains a concern in more active patients [2].
Outcomes and Assessment
- The present review highlights the need for standardization of outcome assessment following treatment of shoulder arthritis [1].
- The authors recommend the continued use of the Western Ontario Osteoarthritis of the Shoulder Index (WOOS) in shoulder arthroplasty registries and observational studies [18].
- The PROMIS Global-10 appears to have limited utility in the evaluation of patients with shoulder arthritis both preoperatively and after total shoulder arthroplasty [91].
- PROMIS Upper Extremity demonstrated excellent correlation (range: 0.68–0.84) with ASES, SST, and OSS at all postoperative time-points in patients undergoing total shoulder arthroplasty [165].
- The correlation of PROMIS Upper Extremity with legacy instruments was weaker (r 1–3) [165].
- There are a number of validated outcome measures available to assess shoulder function in addition to general physical and mental health measures in patients with shoulder arthritis before and after treatment [165].
- The study establishes a benchmark for early clinical value of new glenoid components by demonstrating significant improvement in patient-reported outcomes at 1 and 2 years post-surgery across a large multicenter cohort [164].
- The preferred management differed between shoulder and trauma surgeons for half of the common proximal humerus fracture presentations, highlighting the need for future research [67].
Infection Management
- All attempts should be made to provide the best infection prophylaxis, according to the available evidence, in patients undergoing shoulder arthroplasty [182].
- Propionibacterium acnes is a common cause of shoulder infection with rotator cuff repair, instability surgery, open reduction internal fixation, and shoulder arthroplasty [58].
- Preoperative blood work and aspiration are less reliable in determining whether a shoulder prosthesis is infected compared to hip or knee prostheses [58].
- Propionibacterium acnes can be slow growing and the average time to a positive culture can be greater than 5 days [58].
- It is imperative that a laboratory keep cultures for a minimum of 10 to 14 days to detect Propionibacterium acnes [58].
- Two-stage reimplantation remains the gold standard for chronic infections of shoulder arthroplasty [58].
- There has been some interest in one-stage exchange for infected shoulder arthroplasty due to the significant scarring that can be present at the time of a delayed reimplantation [58].
Complications
General Complication Rates and Definitions
- The overall complication rate after total shoulder arthroplasty is estimated to be approximately 15% [159].
- A study of over 400 total shoulder arthroplasties performed with cemented all-polyethylene glenoid components between 1990 and 2000 found a 12% complication rate [159].
- Reverse total shoulder arthroplasty initially resulted in relatively high complication rates of 50% [159].
- With improved techniques and better understanding of the device, the complication rate for reverse total shoulder arthroplasty has fallen to 6% recently reported [159].
- Complications after total shoulder arthroplasty tend to occur late in the postoperative course, specifically 5 to 10 years after surgery [159].
Component Loosening and Failure
- Component loosening is the most commonly reported complication after total shoulder arthroplasty, occurring in 6.31% of all shoulders in a review of 33 series [157].
- Glenoid component loosening occurred in 5.3% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Humeral component loosening occurred in 1.1% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Component loosening has been reported to occur approximately 8 years after surgery [159].
- Glenoid component failure remains a major cause of poor patient outcomes after total shoulder arthroplasty [77].
- Radiolucencies were noted around the glenoid component and/or screws in 45% of shoulders in a study of uncemented glenoid components [43].
- Radiographic evidence of definite loosening was noted in 44% of the glenoid components in one long-term study of cemented glenoids [43].
- Glenoid component survivorship with revision as the end point was 94.5% in a large multicenter study [123].
- In patients younger than 50 years, a report with a minimum 20-year follow-up found over 75% component retention for total shoulder arthroplasty [123].
- In a cohort of 34 shoulders treated with high-side glenoid reaming and anatomic total shoulder arthroplasty, 4 shoulders (11.8%) were considered to have a clinical or radiographic glenoid failure at a mean follow-up of 8.6 years [213].
- Total shoulder arthroplasty for B2 glenoids may have reasonable short-term results but is associated with high mid-term complication rates due to instability and loosening [146].
Instability and Dislocation
- Instability is the second most commonly reported complication after total shoulder arthroplasty, occurring in 4.9% of all shoulders in a review of 33 series [157].
- Superior instability occurred in 3% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Posterior instability occurred in 1% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Anterior instability occurred in 0.9% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Instability is one of the most common complications after reverse total shoulder arthroplasty [159].
- Instability after reverse total shoulder arthroplasty can result from falls, suboptimal component selection, component malposition, bulky tissues in the posterior shoulder, leverage of the humeral component against the glenoid, or lack of a sufficient compressive effect by the deltoid [66].
- The main cause of instability after unconstrained shoulder prosthesis is soft tissue deficiency [57].
Periprosthetic Fractures
- Periprosthetic fracture is the third most commonly reported complication after total shoulder arthroplasty, occurring in 1.8% of all shoulders in a review of 33 series [157].
- Intraoperative periprosthetic fractures occurred in 1.1% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Postoperative periprosthetic fractures occurred in 0.7% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Periprosthetic fractures have been reported to occur at 6 years after surgery [159].
- The risk of humeral fracture is increased by revision surgery and by falls after reverse total shoulder arthroplasty [66].
- The risk of humeral fracture is also increased when the humeral component fixation results in an abrupt transition between a cemented or press-fitted diaphyseal stem tip and osteopenic bone distal to the prosthesis [66].
Infection
- Infection is the fourth most commonly reported complication after total shoulder arthroplasty, occurring in 0.7% of all shoulders in a review of 33 series [157].
- Infection has been reported to occur at 12 years after surgery [159].
- Infection is one of the most common complications after reverse total shoulder arthroplasty [66].
- Septic arthritis of the shoulder joint is rare but increases in incidence with age [12].
- Delays in diagnosis of septic arthritis of the shoulder greater than a month are frequent because systemic illness is relatively uncommon [12].
- A history of prior nonshoulder periprosthetic joint infection is associated with a higher rate of complications and increased healthcare resource utilization after primary total shoulder arthroplasty [206].
Rotator Cuff and Soft Tissue Complications
- Rotator cuff tear is the fifth most commonly reported complication after total shoulder arthroplasty, occurring in 1.3% of all shoulders in a review of 33 series [157].
- Deltoid detachment occurred in 0.08% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Deltoid weakness or dysfunction is a reported complication after total shoulder arthroplasty [159].
- Fatty infiltration and muscle atrophy of the rotator cuff are observed in stemless total shoulder arthroplasty [211].
Neural Injury
- Neural injury occurred in 0.8% of shoulders in a review of 33 series of unconstrained total shoulder arthroplasties [157].
- Most nerve injuries following shoulder arthroplasty are neurapraxias that recover with time [157].
- If no recovery of nerve function is noted after 6 weeks, an electromyographic examination should be obtained and repeated at 3 months [157].
- If no recovery has occurred as evident by electromyography at 3 months, exploration of the nerve should be considered [157].
Other Complications
- Symptomatic acromioclavicular joint osteoarthritis occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years [55].
- Scapular notching is a common complication after reverse total shoulder arthroplasty [159].
- Hematoma formation is a reported complication after reverse total shoulder arthroplasty [159].
- Glenoid dissociation, such as baseplate failure or aseptic loosening, is a reported complication after reverse total shoulder arthroplasty [159].
- Acromial and scapular spine fractures are reported complications after reverse total shoulder arthroplasty [159].
- Loosening or dissociation of the humeral component is a reported complication after reverse total shoulder arthroplasty [159].
- Nerve injury is a reported complication after reverse total shoulder arthroplasty [159].
- Morbid obesity is associated with a higher rate of medical complications and higher costs in total shoulder arthroplasty [184].
- Diabetes is reported to correlate with a higher rate of perioperative medical complications in total shoulder arthroplasty [184].
- Hepatitis C is an independent factor correlating with increased complications, including infection and need for revision, in total shoulder arthroplasty [184].
- Perioperative mortality for shoulder arthroplasty is approximately 1% [184].
- Age below 65 years is significantly associated with an increased risk of revision after total shoulder arthroplasty for glenohumeral osteoarthritis [208].
- Previous shoulder surgery is significantly associated with an increased risk of revision after total shoulder arthroplasty for glenohumeral osteoarthritis [208].
- A critical shoulder angle of 35 degrees or greater suggests that surgeons may consider using reverse arthroplasty in cases of primary shoulder arthritis to mitigate revision risk [87].
Recovery
- Shoulder arthroplasty was effective within a relatively short time frame in improving patient assessment of both shoulder function and overall health status in patients with primary glenohumeral degenerative joint disease [5].
- Total shoulder arthroplasty has historically provided the most predictable results for pain relief and improved function in the treatment of advanced glenohumeral arthritis [8].
- All 68 shoulders treated with total shoulder replacement for primary glenohumeral osteoarthritis achieved satisfactory long-term results [31].
- At a mean of 41 month follow-up, primary anatomic total shoulder arthroplasty and reverse total shoulder arthroplasty patients with osteoarthritis and an intact rotator cuff with no previous history of shoulder surgery had similar clinical and radiographic outcomes [38].
- Cementless glenoid component total shoulder arthroplasty resulted in significant functional improvement but highlighted complications such as radiolucent lines, component loosening, and polyethylene wear [41].
- Significant strength improvement from baseline was observed at 2 years after shoulder arthroplasty, but subscapularis strength returned to normal in only a minority of patients [193].
- Patients in the proximal humerus fracture cohort were less likely to report persistent shoulder pain at all evaluated time points compared to the osteoarthritis cohort [78].
- Radiographs at 6 month follow-up demonstrated a space between the humeral head and the glenoid in all cases of surgical treatment for glenohumeral arthritis in the young patient [21].
- Cementless surface replacement arthroplasty provides good long-term symptomatic and functional results in the treatment of glenohumeral arthropathy in patients aged younger than 50 years in 81.6% of the patients [35].
- In a series of 7 shoulders undergoing reverse shoulder arthroplasty with patient-specific instrument-assisted structural glenoid bone grafting, integration of humeral head autograft was noted in all shoulders at a mean follow-up of 16 months [235].
- Five of 6 patients evaluated at a mean of 5.5 years postoperatively after arthroscopic synovectomy for shoulder arthropathy in chronic renal dialysis patients were still satisfied with the results of surgery and had continued to have improvement in both subjective and objective shoulder function [89].
- Two years after the operation for subchondral insufficiency fracture of the humeral head and glenoid resulting in rapidly destructive arthrosis, the shoulder prosthesis had not failed, and further progressive bone destruction had not occurred in the right shoulder or in the other joints [84].
Key Evidence
- [L1] The present review highlights the need for standardization of outcome assessment following treatment of shoulder arthritis. [1] (10.1177/1758573215622385)
- [L5] Shoulder arthritis is common, and management strategies, especially in young patients, continue to evolve with significant improvements in implant design, though longevity remains a concern in more active patients. [2] (10.1016/j.csm.2018.07.001)
- [L4] Frozen shoulder is a common epidemiological affliction that does not resolve spontaneously in a large number of patients. [3] (10.3389/fmed.2021.663703)
- [Paper] The goal of this special issue is to provide the reader with an understanding of the best practices in shoulder arthroplasty in 2016, and to address some of the current controversies in the field. [4] (10.1097/bte.0000000000000080)
- [L4] The data presented indicate that within a group of patients with primary glenohumeral degenerative joint disease, shoulder arthroplasty was effective within a relatively short time frame in improving the patients' assessment of both shoulder function and overall health status. [5] (10.1016/s1058-2746(95)80203-7)
- [L3] Patients with glenohumeral osteoarthritis converted intraoperatively to RSA had outcomes comparable to those who underwent total shoulder arthroplasty. [6] (10.1016/j.jse.2015.01.005)
- [Paper] Treatment of advanced glenohumeral arthritis by total shoulder arthroplasty has, historically, provided the most predictable results for pain relief and improved function. [8] (10.1016/s0894-1130(00)80038-1)
- [L4] Primary glenohumeral osteoarthritis is associated with distinct global scapular morphologic characteristics. [9] (10.1016/j.jse.2026.06.017)
- [L5] Knowledge of the array of shoulder prostheses currently available and the indications for each, as well as the use of treatment algorithms, can lead to optimized patient outcomes. [10] (10.5435/00124635-200907000-00002)
- [L1] A clear standardised set of shoulder arthroplasty complication definitions is lacking. [11] (10.1007/s00402-017-2635-9)
- [L5] Septic arthritis of the shoulder joint is rare but increases in incidence with age, and delays in diagnosis of greater than a month are frequent because systemic illness is relatively uncommon. [12] (10.1016/s1058-2746(09)80028-1)
- [L4] Reverse shoulder arthroplasty provides optimal outcomes with low complication rates across a short term of follow-up for glenohumeral osteoarthritis with an intact rotator cuff. [13] (10.1016/j.jse.2021.06.010)
- [Paper] Patients with mild radiographic signs of arthritis have about sevenfold higher odds of failing to achieve the minimum clinically important difference (MCID) after anatomic total shoulder replacement compared to patients with severe arthritis. [15] (10.1097/corr.0000000000002747)
- [L4] The incidence of primary glenohumeral osteoarthritis was 0.4% in the patients with orthopaedic complications and 4.6% in the patients who had shoulder diseases. [16] (10.1016/s1058-2746(99)90093-9)
- [L4] Pathoanatomic metrics with the identified threshold values can be used to discriminate glenoid types in shoulders with primary glenohumeral osteoarthritis. [17] (10.1016/j.jse.2021.03.140)
- [L4] The authors recommend the continued use of WOOS in shoulder arthroplasty registries and observational studies. [18] (10.1186/s12891-023-06578-5)
- [L5] Total shoulder arthroplasty is a good procedure with a successful long-term record. [19] (10.1097/bte.0b013e3181e0b319)
- [L4] Radiographs at 6 month follow-up demonstrate a space between the humeral head and the glenoid in all cases. [21] (10.1097/01.bte.0000135965.23606.f0)
- [Paper] [24] (10.1016/j.csm.2018.05.002)
- [L4] These data demonstrate an anatomic pattern of glenoid bone loss for different classes of glenohumeral arthritis. [25] (10.1007/s12306-016-0406-3)
- [L4] This condition should be considered in the differential diagnosis of elderly women with insidious shoulder pain. [26] (10.1016/j.jse.2014.10.020)
- [L2] Both designs yield similar pain relief, functional gains, and shoulder motion across most patient-reported outcome measures. [27] (10.5397/cise.2025.01480)
- [L4] Measurement in the glenoid hull plane may be more accurate than in the scapular plane. [30] (10.1016/j.jse.2017.01.027)
- [L4] All 68 shoulders achieved satisfactory long term results. [31] (10.1016/s1058-2746(96)80399-5)
- [L5] The article provides an overview of available treatments for shoulder osteoarthritis, noting that nonoperative modalities should be utilized before surgical options, particularly for patients with moderate-to-mild disease, while surgical treatments like arthroplasty are considered effective for severe cases. [33] (10.1155/2013/370231)
- [L4] CSRA provides good long-term symptomatic and functional results in the treatment of glenohumeral arthropathy in patients aged younger than 50 years in 81.6% of the patients. [35] (10.1016/j.jse.2014.11.035)
- [L4] Improvements in PROs and ROM in sports participants support its efficacy for active patients with shoulder pathology. [36] (10.1177/2325967126s00548)
- [L4] [37] (10.1177/23259671261451245)
- [L3] At a mean of 41 month follow-up, primary aTSA and rTSA patients with OA and an intact rotator cuff with no previous history of shoulder surgery had similar clinical and radiographic outcomes. [38] (10.5435/jaaos-d-22-00014)
- [L1] Total shoulder arthroplasty did not provide a clinically important advantage over hemiarthroplasty in terms of patient-reported pain, function, nor adverse effects; however, the evidence on this topic was of low quality. [39] (10.1097/corr.0000000000001523)
- [L3] There was no clinically or statistically significant difference in the Oxford Shoulder Score results between the two groups. [40] (10.1016/j.jse.2013.08.022)
- [L4] The study evaluated midterm clinical and radiographic outcomes of a cementless glenoid component, noting significant functional improvement but highlighting complications such as radiolucent lines, component loosening, and PE wear. [41] (10.1016/j.jse.2012.07.005)
- [L4] [42] (10.1016/j.jse.2015.12.010)
- [L4] [43] (10.1097/00132589-200412000-00002)
- [L4] [44] (10.1007/s00167-014-2981-x)
- [L5] The biomechanical shoulder model is consistent with clinical observations. [45] (10.1016/j.jse.2016.05.031)
- [L3] [52] (10.1016/j.jse.2019.05.010)
- [L5] Under optimal circumstances simultaneous shoulder arthroplasty is feasible. [53] (10.1016/s1058-2746(96)80400-9)
- [L4] Symptomatic ACJ OA occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years. [55] (10.1177/17585732221114796)
- [L3] rTSA provides comparable clinical outcomes across indications of irreparable rotator cuff tear, rotator cuff tear arthropathy, and primary osteoarthritis at 2 years, supporting its broad applicability. [56] (10.1016/j.jsea.2026.100080)
- [L4] The authors recommend a systematic, inclusive approach to the array of pathologies encountered in the setting of early glenohumeral arthritis: the Comprehensive Arthroscopic Management (CAM) procedure. [60] (10.1016/j.arthro.2022.01.033)
- [L4] It affects younger patients than typical glenohumeral osteoarthritis. [63] (10.1016/s1058-2746(95)80035-2)
- [L4] Shoulders presenting with posterior subluxation (B types) remained posteriorly subluxed, while concentric arthritis developed an eccentric pattern 20% of the time. [64] (10.1016/j.jse.2020.05.021)
- [L3] This study shows that increased age is the main determinant of radiological changes in shoulder OA, as well as pain. [65] (10.1186/s13018-022-03137-x)
- [L4] The preferred management differed between shoulder and trauma surgeons for half of the common PHF presentations, highlighting the need for future research. [67] (10.1016/j.jse.2021.11.016)
- [L3] F-18-FDG PET/CT effectively differentiates septic shoulder arthritis from varying stages of osteoarthritis. [68] (10.1016/j.jse.2025.01.047)
- [L4] Arthritic B2 glenoids are common, and their maximal erosion is usually posteroinferior. [69] (10.1016/j.jse.2015.01.007)
- [L3] Both augmented and standard anatomic total shoulder arthroplasty can provide satisfactory and sustained improvements in patient-reported outcomes in patients with acquired glenoid retroversion due to glenohumeral osteoarthritis. [72] (10.1016/j.jse.2021.12.016)
- [L3] Chronic renal disease may lead to a general arthropathy which can be quite disabling in the shoulder joints. [73] (10.1016/s1058-2746(95)80129-4)
- [Case_report] Physicians and orthopedic surgeons should consider gouty shoulder arthritis when severe erosion is present in patients with a history of gout. [74] (10.1186/s12891-021-04217-5)
- [L4] Glenoid component failure remains a major cause of poor patient outcomes after total shoulder arthroplasty. [77] (10.1016/j.jse.2017.09.029)
- [L3] Patients in the proximal humerus fracture (PHF) cohort were less likely to report persistent shoulder pain at all evaluated time points compared to the osteoarthritis (OA) cohort, suggesting that symptom relief following treatment of traumatic pathology may differ fundamentally from that of chronic degenerative disease. [78] (10.1016/j.jsea.2026.100012)
- [L3] Three reproducible scapular rotation types were identified that remained mostly constant postoperatively. [80] (10.1016/j.jse.2026.06.011)
- [L5] Two years after the operation, the shoulder prosthesis had not failed, and further progressive bone destruction had not occurred in the right shoulder or in the other joints. [84] (10.1016/s1058-2746(03)00042-9)
- [L4] Patients with primary OA and glenoid type A barely show differences in scapular morphology and scapulothoracic orientation compared to a healthy control group. [86] (10.1016/j.jseint.2025.101445)
- [L3] These data suggest that surgeons may consider using reverse arthroplasty in cases of primary shoulder arthritis with a critical shoulder angle of 35 degrees or greater. [87] (10.1016/j.jse.2021.08.003)
- [L4] Five of 6 patients evaluated at a mean of 5.5 years postoperatively were still satisfied with the results of surgery and had continued to have improvement in both subjective and objective shoulder function. [89] (10.1067/mse.2003.30)
- [L3] The Global-10 appears to have limited utility in the evaluation of patients with shoulder arthritis both preoperatively and after TSA. [91] (10.1016/j.jse.2020.10.021)
- [L3] The 3D classification system using combined humeroscapular alignment and glenoid erosion can be applied to describe the disease comprehensively. [113] (10.1177/23259671221110512)
- [L3] To reduce the severity of septic shoulder infection, timely diagnosis and treatment are essential. [117] (10.1016/j.jse.2021.05.020)
- [Paper] Current classifications exhibit poor reliability in categorizing glenoid defects post-reverse shoulder arthroplasty removal. [121] (10.1016/j.jseint.2024.08.170)
- [L3] A small lateral extension and less posterior rotation of the acromion is associated with shoulder osteoarthritis and is present in almost all types and subtypes of glenoid morphology. [128] (10.1016/j.jse.2021.01.018)
- [L3] [139] (10.1016/j.jse.2011.11.028)
- [L5] Total shoulder arthroplasty may have reasonable short-term results but is associated with high mid-term complication rates due to instability and loosening in B2 glenoids. [146] (10.1016/j.jse.2013.06.017)
- [L4] Patients undergoing total shoulder arthroplasty with an asymmetric glenoid component for osteoarthritis achieve satisfactory mid-term pain relief and improvement in function; however, instability is not always corrected. [158] (10.1007/s11999-007-0104-4)
- [L5] Shoulders with rotator cuff tears require considerable compensatory deltoid function to prevent abduction motion loss. [160] (10.1177/0363546518768276)
- [L4] The study establishes a benchmark for early clinical value of new glenoid components by demonstrating significant improvement in patient-reported outcomes at 1 and 2 years post-surgery across a large multicenter cohort. [164] (10.1007/s00264-018-4213-3)
- [L2] It demonstrated excellent correlation (range: 0.68–0.84) with ASES, SST, and OSS at all postoperative time-points, but the correlation was weaker (r 1–3 There are a number of validated outcome measures available to assess shoulder function in addition to general physical and mental health measures in patients with shoulder arthritis before and after treatment. [165] (10.1002/jor.25263)
- [L4] Arthroscopic debridement combined with localized antibiotic delivery using PMMA beads is an effective and safe treatment for septic shoulder arthritis. [166] (10.5397/cise.2024.00584)
- [L5] rTSA has seen a significant increase in utilization for glenohumeral osteoarthritis, with evidence suggesting similar success in patient-reported outcomes and satisfaction compared to anatomic total shoulder arthroplasty (aTSA), though aTSA may offer better range of motion. rTSA demonstrates improved survivorship compared to aTSA, particularly in addressing common causes of failure such as rotator cuff failure and glenoid component loosening. [168] (10.1016/j.jseint.2024.06.017)
- [L4] Conversion total shoulder arthroplasty is effective for addressing painful glenoid arthrosis after primary humeral head replacement, with or without the need to change the humeral component. [169] (10.1016/j.jse.2011.01.024)
- [L4] Patients achieved excellent functional outcomes and pain improvement after TSA with an augmented glenoid component. [173] (10.1016/j.jse.2022.12.004)
- [L3] MRI is useful for preoperative osseous imaging for total shoulder arthroplasty because it offers a more precise method of determining glenoid version compared with x-ray imaging. [174] (10.1016/j.jse.2012.10.036)
- [L5] All attempts should be made to provide the best infection prophylaxis, according to the available evidence, in patients undergoing shoulder arthroplasty. [182] (10.2106/jbjs.22.00004)
- [L4] Osteoarthritic humeral head morphology varies significantly from normal, with larger spherical diameters, but does not vary as a function of the Walch classification between symmetric and asymmetric glenoids. [183] (10.1016/j.jse.2015.08.047)
- [L5] Early results appear promising, and the procedure does not preclude conversion to a total shoulder replacement or arthrodesis should this become necessary in the future. [185] (10.1097/00132589-200112000-00004)
- [L4] There are no significant side-dependent differences in the osseous anatomy of the glenohumeral joint. [189] (10.1016/j.jse.2015.12.024)
- [L4] Acceptable results, similar to those of anatomic total shoulder arthroplasty, can be achieved with ream-and-run arthroplasty in this challenging population, though further studies objectively assessing activity level and psychosocial aspects of patient selection are needed. [190] (10.2106/jbjs.23.00034)
- [L4] Although significant strength improvement from baseline was observed at 2 years after shoulder arthroplasty, subscapularis strength returned to normal in only a minority of patients. [193] (10.1016/j.jse.2014.06.042)
- [L3] [205] (10.1016/j.jse.2016.07.007)
- [L3] [206] (10.5435/jaaos-d-21-00745)
- [L4] [207] (10.1097/bte.0b013e3181e5d742)
- [L3] Age below 65 years (HR 2.63) and previous shoulder surgery (HR 2.00) were also significantly associated with an increased risk of revision. [208] (10.1016/j.jseint.2025.101482)
- [L2] [211] (10.1016/j.jse.2017.12.021)
- [L4] [213] (10.1016/j.jse.2022.12.019)
- [L4] The CSA is an effective radiographic parameter that is associated with rotator cuff tears and osteoarthritis. [215] (10.1136/jisakos-2018-000255)
- [Paper] The discussion notes that recent randomized controlled trials have reported clinical non-inferiority of stemless components relative to stemmed components in the setting of anatomic total shoulder arthroplasty. [217] (10.1016/j.eats.2023.07.009)
- [L4] The study demonstrates that 3D CT reconstruction allows for reliable evaluation of the scapulohumeral relationship, revealing significant posterior translation of the humeral head in osteoarthritic shoulders compared to nonpathologic controls, which supports the pathomechanism of glenoid component loosening. [219] (10.1016/j.jse.2016.02.035)
- [L4] Radiographic assessment of scapular notching is also not reliable. [220] (10.1097/bte.0000000000000051)
- [L2] Treatment of end-stage glenohumeral arthritis refractory to conservative treatment in patients 30 to 50 years old in the United States with TSA, instead of hemiarthroplasty, would result in greater cost savings, avoid a substantial number of revision procedures, and result in greater years of satisfactory or excellent patient outcomes and greater QALYs gained. [223] (10.1007/s11999-016-4991-0)
- [L3] This is an inexpensive, practical, and reproducible method that can be used to determine the rate of medial migration of the humeral head on plain radiographs after shoulder arthroplasty. [224] (10.1016/j.jse.2010.03.010)
- [L3] Cystic disease did not affect functional outcome or the presence of radiographic glenoid loosening. [225] (10.1016/j.jse.2017.10.035)
- [L4] Three significantly differently oriented wear patterns (posterior-superior, posterior-central, and posterior-inferior) were distinguished in shoulders demonstrating posterior wear on axillary imaging. [227] (10.1016/j.jse.2021.04.028)
- [L4] More bone imparted fewer overall component radiolucencies. [234] (10.1016/j.jse.2010.05.025)
- [L4] In a series of 7 shoulders, integration of humeral head autograft was noted in all shoulders at a mean follow-up of 16 months. [235] (10.1097/bte.0000000000000123)
References
[1] Is there sufficient evidence to support intervention to manage shoulder arthritis?. Shoulder & Elbow. 2016. DOI: 10.1177/1758573215622385
[2] Shoulder Arthritis in the Young and Active Patient. Clinics in Sports Medicine. 2018. DOI: 10.1016/j.csm.2018.07.001
[3] A Comprehensive View of Frozen Shoulder: A Mystery Syndrome. Frontiers in Medicine. 2021. DOI: 10.3389/fmed.2021.663703
[4] Anatomic Total Shoulder Arthroplasty Special Edition Preface. Techniques in Shoulder & Elbow Surgery. 2016. DOI: 10.1097/bte.0000000000000080
[5] Effectiveness of shoulder arthroplasty in improving function & General health status. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80203-7
[6] Outcome and value of reverse shoulder arthroplasty for treatment of glenohumeral osteoarthritis: a matched cohort. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.01.005
[7] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > SUMMARY.
[8] Osteoarthritis and traumatic arthritis of the shoulder. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80038-1
[9] Morphological analysis of the scapula in healthy and osteoarthritic subjects. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.06.017
[10] Shoulder Arthroplasty: Prosthetic Options and Indications. Journal of the American Academy of Orthopaedic Surgeons. 2009. DOI: 10.5435/00124635-200907000-00002
[11] Towards standardised definitions of shoulder arthroplasty complications: a systematic review of terms and definitions. Archives of Orthopaedic and Trauma Surgery. 2017. DOI: 10.1007/s00402-017-2635-9
[12] Septic arthritis of the shoulder presenting as chronic anterior dislocation. Journal of Shoulder and Elbow Surgery. 1994. DOI: 10.1016/s1058-2746(09)80028-1
[13] Glenohumeral osteoarthritis with intact rotator cuff treated with reverse shoulder arthroplasty: a systematic review. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2021.06.010
[15] Editor’s Spotlight/Take 5: Patients With Mild Osteoarthritis Are Less Likely to Achieve a Clinically Important Improvement in Pain or Function After Anatomic Total Shoulder Arthroplasty. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002747
[16] Epidemiologic study of glenohumeral osteoarthritis with plain radiography. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90093-9
[17] Identification of threshold pathoanatomic metrics in primary glenohumeral osteoarthritis. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2021.03.140
[18] Western Ontario Osteoarthritis of the Shoulder Index (WOOS) - a validation for use in proximal humerus fractures treated with arthroplasty. BMC Musculoskeletal Disorders. 2023. DOI: 10.1186/s12891-023-06578-5
[19] Glenoid Exposure in Shoulder Arthroplasty. Techniques in Shoulder & Elbow Surgery. 2010. DOI: 10.1097/bte.0b013e3181e0b319
[20] Chapter 25 Shoulder Arthritis and Arthroplasty. 2020.
[21] Surgical Treatment for Glenohumeral Arthritis in the Young Patient. Techniques in Shoulder & Elbow Surgery. 2004. DOI: 10.1097/01.bte.0000135965.23606.f0
[24] Etiology of Shoulder Arthritis in Young Patients. Clinics in Sports Medicine. 2018. DOI: 10.1016/j.csm.2018.05.002
[25] Quantitative assessment and characterization of glenoid bone loss in a spectrum of patients with glenohumeral osteoarthritis. MUSCULOSKELETAL SURGERY. 2016. DOI: 10.1007/s12306-016-0406-3
[26] Rapidly destructive arthrosis of the shoulder joints: radiographic, magnetic resonance imaging, and histopathologic findings. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2014.10.020
[27] Keeled versus pegged glenoid components in total shoulder arthroplasty for primary osteoarthritis: a meta-analysis. Clinics in Shoulder and Elbow. 2026. DOI: 10.5397/cise.2025.01480
[30] Interest in the glenoid hull method for analyzing humeral subluxation in primary glenohumeral osteoarthritis. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.01.027
[31] Total shoulder replacement for the treatment of primary glenohumeral osteoarthritis. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80399-5
[33] Shoulder Osteoarthritis. Arthritis. 2013. DOI: 10.1155/2013/370231
[35] Surface replacement arthroplasty for glenohumeral arthropathy in patients aged younger than fifty years: results after a minimum ten-year follow-up. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2014.11.035
[36] Poster 256. Return to Sport Outcomes Following Stemless Total Shoulder Arthroplasty. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/2325967126s00548
[37] Rate of Shoulder Arthroplasty After Anterior Shoulder Instability Surgery: A Systematic Review. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671261451245
[38] Comparison of Reverse and Anatomic Total Shoulder Arthroplasty in Patients With an Intact Rotator Cuff and No Previous Surgery. Journal of the American Academy of Orthopaedic Surgeons. 2022. DOI: 10.5435/jaaos-d-22-00014
[39] Cochrane in CORR®: Shoulder Replacement Surgery For Osteoarthritis And Rotator Cuff Tear Arthropathy. Clinical Orthopaedics & Related Research. 2020. DOI: 10.1097/corr.0000000000001523
[40] Effect of glenoid cementation on total shoulder arthroplasty for degenerative arthritis of the shoulder: a review of the New Zealand National Joint Registry. Journal of Shoulder and Elbow Surgery. 2014. DOI: 10.1016/j.jse.2013.08.022
[41] Midterm results of a total shoulder prosthesis fixed with a cementless glenoid component. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2012.07.005
[42] Total shoulder arthroplasty using an inlay mini-glenoid component for glenoid deficiency: a 2-year follow-up of 9 shoulders in 7 patients. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.12.010
[43] Total Shoulder Arthroplasty With an Uncemented Glenoid Component. Techniques in Shoulder and Elbow Surgery. 2004. DOI: 10.1097/00132589-200412000-00002
[44] Arthroscopic partial shoulder resurfacing. Knee Surgery, Sports Traumatology, Arthroscopy. 2014. DOI: 10.1007/s00167-014-2981-x
[45] Effects of glenoid inclination and acromion index on humeral head translation and glenoid articular cartilage strain. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2016.05.031
[46] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[47] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > INDICATIONS FOR ARTHROSCOPIC TREATMENT.
[49] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > TREATMENT.
[52] Treatment of acute shoulder infection: can osseous lesion be a rudder in guideline for determining the method of débridement?. Journal of Shoulder and Elbow Surgery. 2019. DOI: 10.1016/j.jse.2019.05.010
[53] Simultaneous bilateral shoulder arthroplasty, a case report. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80400-9
[54] Aaos Comprehensive Orthopaedic Review 3. Arthritis and Arthroplasty of the Shoulder* > II. Inflammatory Arthritis.
[55] The incidence and treatment of symptomatic acromioclavicular joint osteoarthritis following total shoulder arthroplasty. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221114796
[56] Comparing the use of reverse total shoulder arthroplasty for glenohumeral osteoarthritis, irreparable rotator cuff tears, and rotator cuff tears with arthritis: a 2-year clinical outcome analysis using the Enovis AltiVate reverse. Journal of Shoulder and Elbow Arthroplasty. 2026. DOI: 10.1016/j.jsea.2026.100080
[57] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > TOTAL SHOULDER ARTHROPLASTY.
[58] Rockwood And Matsen S The Shoulder. Sepsis of the Shoulder: Molecular Mechanisms and Pathogenesis > EDITOR COMMENTARY.
[59] Classifications And Scores Of The Shoulder. 15.1 Variations in Involvement in rheumatoid arthritis [102]*.
[60] Comprehensive Arthroscopic Management of Shoulder Arthritis. Arthroscopy. 2022. DOI: 10.1016/j.arthro.2022.01.033
[62] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Techniques for Anatomic Arthroplasty > Prosthesis Selection for Anatomic Arthroplasty.
[63] Arthritis of dislocation surgery: Glenohumeral arthrosis after anterior repair. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80035-2
[64] Natural history of glenoid bone loss in primary glenohumeral osteoarthritis: how does bone loss progress over a decade?. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.05.021
[65] Radiological changes in shoulder osteoarthritis and pain sensation correlate with patients’ age. Journal of Orthopaedic Surgery and Research. 2022. DOI: 10.1186/s13018-022-03137-x
[66] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Results.
[67] Factors influencing surgical management of proximal humerus fractures: do shoulder and trauma surgeons differ?. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.11.016
[68] 18F-FDG PET/CT for the diagnosis of septic shoulder arthritis: metabolic uptake pattern and diagnostic performance. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.01.047
[69] Quantification of B2 glenoid morphology in total shoulder arthroplasty. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.01.007
[72] Mid- to long-term outcomes of augmented and nonaugmented anatomic shoulder arthroplasty in Walch B3 glenoids. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.12.016
[73] Shoulder arthropathy due to chronic renal disease. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80129-4
[74] Severe erosive lesion of the glenoid in gouty shoulder arthritis: a case report and review of the literature. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04217-5
[77] What can be learned from an analysis of 215 glenoid component failures?. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2017.09.029
[78] Complication rates following total shoulder arthroplasty for osteoarthritis versus proximal humerus fracture: a propensity-matched cohort comparison of 9,190 patients. Journal of Shoulder and Elbow Arthroplasty. 2026. DOI: 10.1016/j.jsea.2026.100012
[80] ‘‘The Global Glenoid Component Inclination: why scapulothoracic orientation should be considered when defining glenoid component inclination in reverse total shoulder arthroplasty’’. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.06.011
[84] Subchondral insufficiency fracture of the humeral head and glenoid resulting in rapidly destructive arthrosis: a case report. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/s1058-2746(03)00042-9
[86] Primary osteoarthritis of the shoulder - Are there differences in scapular morphology, orientation and rotator cuff action lines between patients and healthy controls?. JSES International. 2026. DOI: 10.1016/j.jseint.2025.101445
[87] The association between critical shoulder angle and revision following anatomic total shoulder arthroplasty: a matched case-control study. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.08.003
[89] Arthroscopic synovectomy for the management of shoulder arthropathy in chronic renal dialysis patients. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1067/mse.2003.30
[91] PROMIS Global-10 performs poorly relative to legacy shoulder instruments in patients undergoing total shoulder arthroplasty for glenohumeral arthritis. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.10.021
[92] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[93] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[94] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[95] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[97] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > EDITOR COMMENTARY.
[98] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > FRACTURES OF THE PROXIMAL HUMERUS.
[101] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > ANATOMY AND BIOMECHANICS.
[102] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > SHOULDER INJURIES > ANATOMY AND BIOMECHANICS.
[103] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[105] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Shoulder Capsule.
[107] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS AROUND THE SHOULDER.
[111] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[112] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > PATHOPHYSIOLOGY.
[113] A 3-Dimensional Classification for Degenerative Glenohumeral Arthritis Based on Humeroscapular Alignment. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671221110512
[114] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[117] Factors affecting the occurrence of osseous lesions in septic shoulder arthritis and the recurrence rate after arthroscopic surgery. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.05.020
[119] Aaos Comprehensive Orthopaedic Review 3. Arthritis and Arthroplasty of the Shoulder* > I. Osteoarthritis.
[121] Glenoid Defects In Revision Reverse Shoulder Arthroplasty: Are Current Classification Systems Appropriate?. JSES International. 2024. DOI: 10.1016/j.jseint.2024.08.170
[122] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > Subscapularis Tears.
[123] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > OSTEOARTHRITIS.
[128] Determination of predisposing scapular anatomy with a statistical shape model—Part II: shoulder osteoarthritis. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2021.01.018
[129] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > Clinical Findings.
[130] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > History.
[131] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Rheumatoid and Other Types of Inflammatory Arthritis.
[134] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > OVERVIEW.
[135] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > CLINICAL EVALUATION AND PHYSICAL EXAMINATION.
[139] Revision total shoulder arthroplasty for painful glenoid arthrosis after humeral head replacement: the nontraumatic shoulder. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2011.11.028
[141] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Physical Examination.
[142] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > OUTCOMES.
[146] Current concepts in the surgical management of primary glenohumeral arthritis with a biconcave glenoid. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2013.06.017
[147] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Arthritis and Arthroplasty > Summary.
[151] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > SURGICAL TECHNIQUE.
[154] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Neurologic Testing.
[156] Classifications And Scores Of The Shoulder. 16 Classification of septic arthritis.
[157] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > INTRAOPERATIVE COMPLICATIONS > Table 12.4.
[158] Augmented Glenoid Component for Bone Deficiency in Shoulder Arthroplasty. Clinical Orthopaedics & Related Research. 2008. DOI: 10.1007/s11999-007-0104-4
[159] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > COMPLICATIONS OF SHOULDER ARTHROPLASTY.
[160] Relationship Between Deltoid and Rotator Cuff Muscles During Dynamic Shoulder Abduction: A Biomechanical Study of Rotator Cuff Tear Progression. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518768276
[164] One and two-year clinical outcomes for a polyethylene glenoid with a fluted peg: one thousand two hundred seventy individual patients from eleven centers. International Orthopaedics. 2018. DOI: 10.1007/s00264-018-4213-3
[165] Performance and responsiveness to change of PROMIS UE in patients undergoing total shoulder arthroplasty. Journal of Orthopaedic Research. 2022. DOI: 10.1002/jor.25263
[166] Effectiveness of a combined arthroscopic and antibiotic-impregnated bead approach for septic shoulder arthritis management: a case series. Clinics in Shoulder and Elbow. 2025. DOI: 10.5397/cise.2024.00584
[168] Glenohumeral osteoarthritis and reverse shoulder replacement. JSES International. 2025. DOI: 10.1016/j.jseint.2024.06.017
[169] Revision total shoulder arthroplasty for painful glenoid arthrosis after humeral head replacement: the posttraumatic shoulder. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2011.01.024
[173] Factors associated with functional improvement after posteriorly augmented total shoulder arthroplasty. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2022.12.004
[174] Magnetic resonance scanning vs axillary radiography in the assessment of glenoid version for osteoarthritis. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2012.10.036
[181] Orthopaedic Knowledge Update Trauma. Periprosthetic Fractures > Upper Extremity Periprosthetic Fractures > Periprosthetic Fractures Associated With Shoulder Arthroplasty.
[182] Can We Improve Our Approach to Antibiotic Prophylaxis in Shoulder Arthroplasty?. Journal of Bone and Joint Surgery. 2022. DOI: 10.2106/jbjs.22.00004
[183] A comparison of normal and osteoarthritic humeral head size and morphology. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.08.047
[184] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > INDICATIONS.
[185] Meniscal Allograft Interposition Arthroplasty for the Arthritic Shoulder: Description of a New Surgical Technique. Techniques in Shoulder & Elbow Surgery. 2001. DOI: 10.1097/00132589-200112000-00004
[189] The osseous morphology of nondegenerated shoulders shows no side-related differences in elderly patients: an analysis of 102 computed tomography scans. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.12.024
[190] Can We Reliably Compare Outcomes of Ream-and-Run and Anatomic Total Shoulder Arthroplasty?. Journal of Bone and Joint Surgery. 2023. DOI: 10.2106/jbjs.23.00034
[193] The return of subscapularis strength after shoulder arthroplasty. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2014.06.042
[194] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > Muscle Atrophy and Fatty Infiltration.
[195] Classifications And Scores Of The Shoulder. 8.3 Classification of AC-joint injuries according to Allman [1].
[196] Classifications And Scores Of The Shoulder. Classifications of frozen shoulder.
[197] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > Magnetic Resonance Imaging.
[198] Rockwood And Matsen S The Shoulder. Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability > Acromioclavicular and Coracoclavicular Instability.
[200] Classifications And Scores Of The Shoulder. 15.4 Radiological classification of rheumatoid arthritis according to Lévigne and Franceschi [76]*.
[203] Classifications And Scores Of The Shoulder. 13.9 Radiographic classification of dislocation arthropathy of the shoulder according to Samilson and Prieto [117].
[205] Glenoid deformity in the coronal plane correlates with humeral head changes in osteoarthritis: a radiographic analysis. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2016.07.007
[206] Prior Nonshoulder Periprosthetic Joint Infection Increases the Risk of Surgical Site Infection, Sepsis, and All-Cause Revision After Primary Total Shoulder Arthroplasty. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-21-00745
[207] Humeral Head Posterior Subluxation on CT Scan: Validation and Comparison of 2 Methods of Measurement. Techniques in Shoulder & Elbow Surgery. 2010. DOI: 10.1097/bte.0b013e3181e5d742
[208] Survival Analysis of Total Shoulder Arthroplasty for Glenohumeral Osteoarthritis. Comparison of anatomical and reversed implants a registry study. JSES International. 2026. DOI: 10.1016/j.jseint.2025.101482
[211] Fatty infiltration and muscle atrophy of the rotator cuff in stemless total shoulder arthroplasty: a prospective cohort study. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2017.12.021
[213] Total shoulder arthroplasty in patients with a B2 glenoid addressed with corrective reaming: mean 8-year follow-up. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2022.12.019
[215] Critical shoulder angle is an effective radiographic parameter that is associated with rotator cuff tears and osteoarthritis: a systematic review. Journal of ISAKOS. 2019. DOI: 10.1136/jisakos-2018-000255
[217] Custom, 3‐Dimensional Patient‐Specific Instrumentation in Anatomic Total Shoulder Arthroplasty: Part 3—Prosthesis Placement, Subscapularis Repair, and Postoperative Rehabilitation. Arthroscopy Techniques. 2023. DOI: 10.1016/j.eats.2023.07.009
[219] A three-dimensional comparative study on the scapulohumeral relationship in normal and osteoarthritic shoulders. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2016.02.035
[220] Determining Center of Rotation and Scapular Notching in Reverse Total Shoulder Arthroplasty. Techniques in Shoulder & Elbow Surgery. 2015. DOI: 10.1097/bte.0000000000000051
[223] Economic Decision Model Suggests Total Shoulder Arthroplasty is Superior to Hemiarthroplasty in Young Patients with End-stage Shoulder Arthritis. Clinical Orthopaedics & Related Research. 2016. DOI: 10.1007/s11999-016-4991-0
[224] A quantitative method for determining medial migration of the humeral head after shoulder arthroplasty: preliminary results in assessing glenoid wear at a minimum of two years after hemiarthroplasty with concentric glenoid reaming. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.03.010
[225] Total shoulder arthroplasty with minimum 5-year follow-up: does the presence of subchondral cysts in the glenoid increase risk of failure?. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2017.10.035
[227] Biconcave glenoids show 3 differently oriented posterior erosion patterns. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2021.04.028
[234] Bone presence between the central peg's radial fins of a partially cemented pegged all poly glenoid component suggest few radiolucencies. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.05.025
[235] Patient-specific Instrument-assisted Structural Glenoid Bone Grafting in Reverse Shoulder Arthroplasty. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000123