Patients › Shoulder
காறை எலும்பின் வெளிமுனைக் கரைவு (Distal Clavicle Osteolysis)
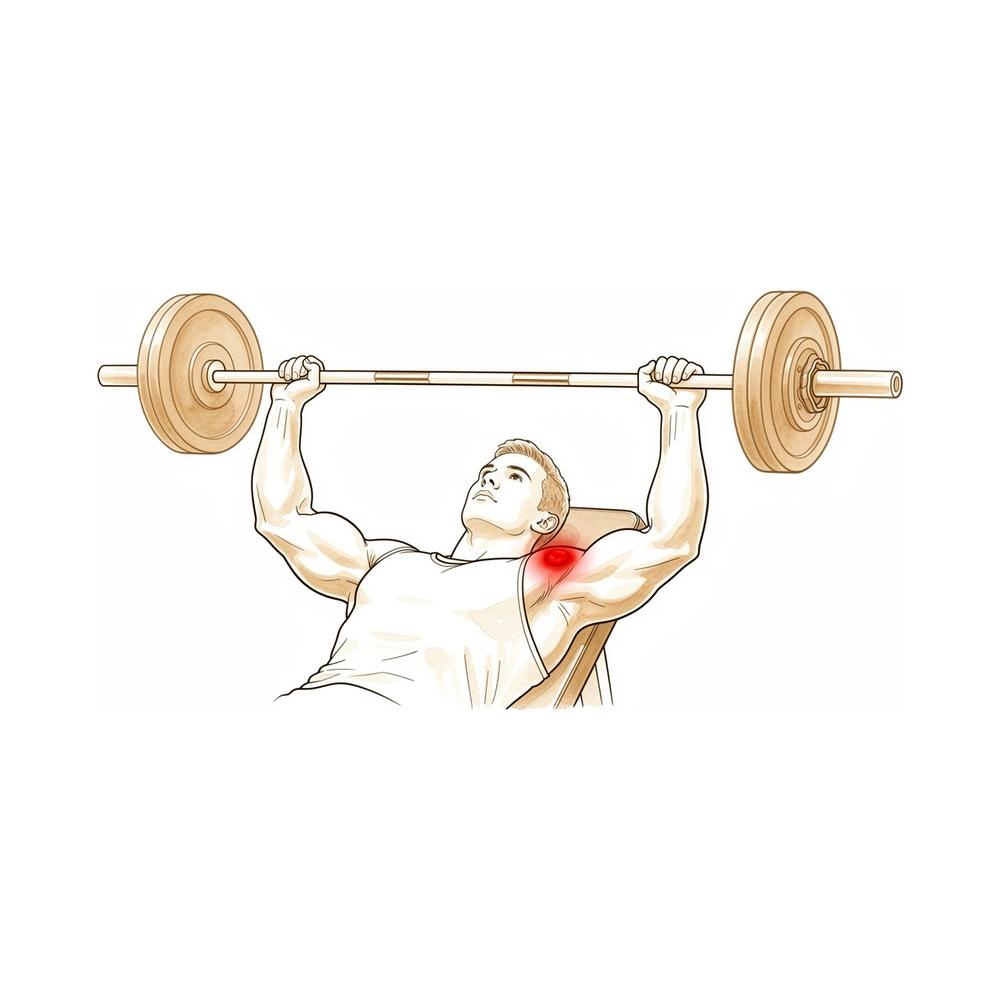
நீங்கள் உணர்வது
வலி உங்கள் காறை எலும்பின் (collarbone) வெளிமுனையில், அது உங்கள் தோள்பட்டையின் மேற்பகுதியைச் சந்திக்கும் இடத்திலேயே இருக்கும். அந்த இடம் அக்ரோமியோகிளாவிகுலர் மூட்டு (acromioclavicular joint) என்று அழைக்கப்படுகிறது. நீங்கள் கையைப் பயன்படுத்தும்போது, குறிப்பாகத் தள்ளுதல், தூக்குதல் அல்லது அழுத்துதல் (pressing) போன்ற அசைவுகளின்போது, இது மிக அதிகமாக வலிக்க முனைகிறது; நீங்கள் ஓய்வெடுக்கும்போது பொதுவாகத் தணிகிறது.
எடைப் பயிற்சி ஒரு பொதுவான தூண்டுதல். பெஞ்ச் பிரஸ் (bench press) மற்றும் பிற கனமான எடை தூக்குதல் இந்த மூட்டுக்கு நேரடியாகச் சுமை தருகின்றன; தெளிவான ஒரே காயத்துடன் தொடங்குவதைவிட, பல வாரப் பயிற்சியின்போது வலி பெரும்பாலும் படிப்படியாக அதிகரிக்கிறது. சிலர் தோள்பட்டைக் காயத்துக்குப் பிறகும் இதைக் கவனிக்கிறார்கள்; தோள்பட்டையின் மற்ற பகுதி தணிந்த பிறகும் நீண்ட காலம் வலி நீடிக்கும்.
இரவிலோ உடற்பயிற்சிக் கூடத்தில் ஒரு பயிற்சிக்குப் பிறகோ இந்த வலி அதிகரிக்கலாம். உங்கள் உடலின் குறுக்கே கையை எட்டுவது, நாற்காலியிலிருந்து கைகளால் அழுத்தி எழுவது, அந்தப் பக்கத்தில் ஷாப்பிங் பொருட்களைச் சுமப்பது அல்லது புல்வெட்டும் இயந்திரத்தைத் (lawnmower) தள்ளுவது — இவை அனைத்தும் வலியை அதிகரிக்கலாம். வலி தோள்பட்டையின் உச்சியிலேயே இருப்பதால், தொடக்கத்தில் அதைத் தசைப் பிடிப்பு (muscle strain) என்று தவறாக நினைப்பது எளிது.
இந்த நிலை வேறு தோள்பட்டைப் பிரச்சினைகளைப் போலவே பெரிதும் தோன்றலாம்; எனவே என்ன நடக்கிறது என்பதை உறுதிப்படுத்த ஸ்கேன்கள் பயன்படுத்தப்படுகின்றன. ஒப்பிடுவதற்காக இரு பக்கங்களிலும் எடுக்கப்படும், அந்த மூட்டுக்கான ஒரு சிறப்புக் கோண எக்ஸ்-ரேயும், ஒரு MRI ஸ்கேனும் காறை எலும்பின் முனையில் உள்ள மாற்றங்களைக் காட்ட முடியும்.
இந்த அறிகுறிகளைக் கவனித்து, அவற்றுக்கேற்ப நடவடிக்கை எடுங்கள்:
உங்கள் கை சூடாகவும், சிவந்தும், வீங்கியும், வலியுடனும் ஆனால், குறிப்பாகக் காய்ச்சலும் இருந்தால், அதே நாளில் அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். ஒரு காயத்துக்குப் பிறகு திடீரென உங்கள் கையில் உணர்வையோ அசைவையோ இழந்தால், அதே நாளில் அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
வலி தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களை எழுப்பினால், அல்லது வேலை செய்வதையோ கையைப் பயன்படுத்துவதையோ தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணர் மதிப்பீட்டைக் கேளுங்கள். அலுவலக நேரத்துக்குப் பிறகோ வார இறுதியிலோ கிளினிக்கைத் தொடர்புகொள்ள முடியாவிட்டால், உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
உண்மையில் என்ன நடக்கிறது
அக்ரோமியோகிளாவிகுலர் மூட்டு என்பது உங்கள் தோள்பட்டையின் மேற்பகுதியில் உள்ள ஒரு சிறிய மூட்டு; அங்கே உங்கள் காறை எலும்பின் வெளிமுனை, அக்ரோமியன் (acromion) எனப்படும் ஒரு எலும்புத் தட்டைச் சந்திக்கிறது. காறை எலும்பு உங்கள் கையை (arm) மார்பிலிருந்து விலக்கிப் பிடித்து வைக்கும் தாங்குகோலாகச் செயல்படுகிறது; அது தோள்பட்டை எலும்புடன் (shoulder blade) இணையும் இடங்களில் இந்தச் சிறிய மூட்டும் ஒன்று. நீங்கள் தூக்கும்போதும் அழுத்தும்போதும், அடியில் உள்ள உறுதியான தசைநார்ப் (ligament) பட்டை ஒன்று அந்த இரண்டு எலும்புகளையும் நேராக வரிசையில் வைத்திருக்கிறது.
இந்த நிலையில், காறை எலும்பின் வெளிமுனை சிதையத் தொடங்குகிறது. எலும்பு இவ்வாறு சிதைவதற்கான மருத்துவச் சொல் ஆஸ்டியோலைசிஸ் (osteolysis). உடல் வழக்கமாகத் தேய்ந்த எலும்பைப் புதிய எலும்பால் மாற்றுகிறது; ஆனால் இங்கே சிதைவு பழுதுபார்ப்பைவிட வேகமாக நடக்கிறது; இதனால் காறை எலும்பின் முனையில் உள்ள எலும்பு மென்மையாகி அரிக்கப்படுகிறது. அதற்கு மேலே உள்ள மூட்டுப் பகுதி நலமாகவே இருக்கிறது; பிரச்சினை காறை எலும்புப் பக்கத்தில் மட்டுமே உள்ளது.
மிகப் பொதுவான தூண்டுதல், திரும்பத் திரும்பக் கொடுக்கப்படும் கனமான சுமை; குறிப்பாக பெஞ்ச் பிரஸ் மற்றும் எடைப் பயிற்சி. ஒவ்வொரு அழுத்தமும் மூட்டின் இரண்டு எலும்புகளையும் ஒன்றோடொன்று மோதச் செய்கிறது; இது ஒரே சிறிய நிலப்பகுதியில் அது தேய்ந்துபோகும் வரை திரும்பத் திரும்ப மிதிப்பதைப் போன்றது. தோள்பட்டைக் காயத்துக்குப் பிறகும் இதே செயல்முறை தொடரலாம்; அப்போது முதல் அடிக்குப் பிறகு பல வாரங்கள் முதல் பல மாதங்கள் வரை வலி நீடிக்கிறது. அரிதாக, லேசான தொற்று (low-grade infection), அல்லது மூட்டு விலகலுக்குப் (dislocation) பிறகு காறை எலும்பைக் கீழே பிடித்து வைக்கப் பயன்படுத்தப்பட்ட உலோகத் தகடு இதைத் தூண்டலாம்.
எலும்பு அரிக்கப்படும்போது, மூட்டு அழற்சியடைந்து வீங்குகிறது; அதனால்தான் பல வாரப் பயிற்சியில் வலி அதிகரித்து, இரவில் தீவிரமடைகிறது. அரிக்கப்பட்ட முனை அக்ரோமியனுடன் இருந்த தனது வழுவழுப்பான பொருத்தத்தையும் இழக்கிறது; இதனால் அழுத்துதல், தூக்குதல், உடலின் குறுக்கே கையை எட்டுதல் ஆகியவை வெற்று எலும்பின் மீது உரசுகின்றன. உங்கள் தோள்பட்டையின் உச்சியில் நீங்கள் உணரும் வலி அதுதான்.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் பணியாற்றும் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் நிலைக்குப் பொருத்தமான, உடலில் மிகக் குறைவாகத் தலையிடும் சிகிச்சைகளிலிருந்தே தொடங்குகிறார். நோயாளிகள் பொதுவாக அவர்களுடைய GP (பொது மருத்துவர்) மூலம் எங்கள் கிளினிக்கிற்குப் பரிந்துரைக்கப்படுகின்றனர்; ஒரு இயன்முறை சிகிச்சையாளர் (physiotherapist) எங்களைப் பார்க்கும்படி பரிந்துரைத்திருந்தாலும், Medicare தள்ளுபடியைப் (rebate) பெறத் தகுதி பெற உங்கள் GP-யிடமிருந்து பரிந்துரைக் கடிதம் (referral) இன்னும் தேவைப்படும். உங்கள் மருத்துவ வரலாறு, பரிசோதனை, ஸ்கேன்கள் மூலம் நோயறிதலை உறுதிசெய்த பிறகு, மிக எளிமையானதிலிருந்து தொடங்கி, சிகிச்சைகளை வரிசையாகச் செய்து பார்க்கிறோம்.
முதல் படி, நீங்கள் மூட்டுக்குச் சுமை கொடுக்கும் விதத்தை மாற்றுவது. திரும்பத் திரும்பச் செய்யும் கனமான அழுத்தமே எலும்பைத் தேய்ப்பதால், வலியைத் தூண்டும் பயிற்சிகளைக் குறைப்பதோ மாற்றுவதோ எலும்பு அமைதியடைய ஒரு வாய்ப்பைத் தருகிறது. நீங்கள் இதைச் செய்யும்போது, அழற்சியைத் தணிப்பதும் உங்கள் தோள்பட்டையை வலுவாகவும் அசையும்படியும் வைத்திருப்பதுமே இயன்முறை சிகிச்சையின் (physiotherapy) நோக்கம். விளையாட்டுப் பருவத்தின் நடுவில் இருக்கும் விளையாட்டு வீரர்களுக்கு, சிகிச்சை பலனளிக்கும் வரை தொடர்ந்து விளையாட இந்த அணுகுமுறை அனுமதிக்கிறது. இதற்கு எவ்வளவு காலம் ஆகும் என்பது நீங்கள் பயிற்சி செய்யும் விதத்தை உண்மையிலேயே மாற்ற முடியுமா என்பதைப் பொறுத்தது; உங்கள் விளையாட்டுக்கோ வேலைக்கோ அதன் பொருள் என்ன என்பதை நாம் பேசித் தெளிவுபடுத்துவோம்.
அடுத்த கட்டம் மருந்துகள். சில நேரங்களில் NSAIDs என்று அழைக்கப்படும் அழற்சி எதிர்ப்பு மாத்திரைகள், மூட்டில் உள்ள வீக்கத்தையும் வலியையும் குறைக்கின்றன. மரத்துப்போகச் செய்யும் மருந்தையும், வலிமையான அழற்சி எதிர்ப்பு மருந்தான கார்டிசோனையும் (cortisone) சேர்த்து, நேரடியாக மூட்டுக்குள் ஊசி மூலம் செலுத்தவும் முடியும். இந்த ஊசி இரண்டு வேலைகளைச் செய்கிறது: அந்த மூட்டுதான் உங்கள் வலியின் மூலம் என்பதை உறுதிப்படுத்துகிறது; அதன் பிறகு சிறிது காலத்துக்கு அந்த வலியைத் தணிக்கவும் முடியும்.
இந்தப் படிகள் உங்களுக்குப் போதுமான நிவாரணம் தரவில்லை என்றால், அறுவை சிகிச்சை பற்றி நாம் பேசலாம். இந்த அறுவை சிகிச்சை உங்கள் காறை எலும்பின் வெளிமுனையிலிருந்து ஒரு சிறிய எலும்புத் துண்டை அகற்றுகிறது; இதனால் சொரசொரப்பான, அரிக்கப்பட்ட மேற்பரப்புகள் இனி ஒன்றோடொன்று உரசாது. சில மில்லிமீட்டர் எலும்பு மட்டுமே அகற்றப்படுகிறது; அருகிலுள்ள தசைநாண் (tendon) மீது ஒரு எலும்பு முள் (bone spur) அழுத்திக்கொண்டிருந்தால், அதையும் அதே நேரத்தில் சீர்செய்கிறோம். அறுவை சிகிச்சையில் என்ன அடங்கும், மீட்சி எப்படி இருக்கும், அது எதை மாற்ற முடியும், எதை மாற்ற முடியாது என்பவற்றை நாங்கள் விளக்குவோம்; அதன் மூலம் அது உங்களுக்குப் பொருத்தமானதா என்பதை நீங்கள் எங்களுடன் சேர்ந்து முடிவு செய்யலாம்.
என்ன எதிர்பார்க்கலாம்
பெரும்பாலானோருக்கு, இந்த நிலையை ஏற்படுத்திய சுமை நின்றவுடன் அது தணிகிறது. திரும்பத் திரும்பச் செய்யும் அழுத்துதலும் தூக்குதலும் குறையும்போது, உங்கள் காறை எலும்பின் முனையில் உள்ள எலும்பு தன்னைத்தானே மீண்டும் கட்டமைத்துக்கொள்ள முடியும். நேர்மையாகச் சொன்னால், இதில் ஒரு நிபந்தனை உள்ளது: நீங்கள் பயிற்சி செய்யும் அல்லது வேலை செய்யும் விதத்தை உண்மையிலேயே மாற்ற முடிந்தால்தான் சிகிச்சை பலனளிக்கிறது. அதே விதத்தில் மூட்டுக்குத் தொடர்ந்து சுமை கொடுத்தால், வலி நீடிக்கவோ மீண்டும் மீண்டும் வரவோ முனைகிறது.
அறுவை சிகிச்சை இல்லாத மீட்சி ஒரு விரைவான தீர்வு அல்ல. வலி பல வாரங்களில் அதிகரிக்கிறது; அது தணிவதற்குப் பொதுவாகப் பல வாரங்கள் முதல் பல மாதங்கள் வரை சுமையைக் குறைக்க வேண்டியிருக்கும். சிலர் இதற்குப் பதிலாகத் தோள்பட்டைக் காயத்துக்குப் பிறகு வலியைக் கவனிக்கிறார்கள்; அப்படியானால், தோள்பட்டையின் மற்ற பகுதி குணமடைந்த பிறகும் நீண்ட காலம் அது நீடிக்கலாம். நியாயமான கால அளவு ஓய்வெடுத்து, பயிற்சியை மாற்றிய பிறகும் வலி இருந்தால், அதைப் பொறுத்துக்கொண்டு தொடர்வதைவிடப் பரிசோதித்துக்கொள்வது நல்லது.
அறுவை சிகிச்சை அல்லாத கவனிப்பு உங்களுக்குப் போதுமான நிவாரணம் தரவில்லை என்றால், அறுவை சிகிச்சை ஒரு வாய்ப்பு. சொரசொரப்பான மேற்பரப்புகள் உரசுவதை நிறுத்த, இந்த அறுவை சிகிச்சை உங்கள் காறை எலும்பின் வெளிமுனையிலிருந்து ஒரு சிறிய எலும்புத் துண்டை அகற்றுகிறது. இதைச் செய்துகொண்டவர்கள் குறைவான வலியையும் மேம்பட்ட தோள்பட்டை அசைவையும் தெரிவிக்கிறார்கள்; பொதுவாக முடிவில் திருப்தியாகவும் இருக்கிறார்கள். துளை வழி (keyhole) முறை, திறந்த முறையைவிடக் குறைவான நீடித்த வலியையே விட்டுச்செல்ல முனைகிறது; அதன் மூலம் மக்கள் தங்கள் செயல்பாடுகளுக்கு விரைவாகத் திரும்புகிறார்கள்.
அறுவை சிகிச்சை வலியற்ற தோள்பட்டைக்கான உத்தரவாதம் அல்ல. சிறிய எண்ணிக்கையிலானோருக்கு, 4% முதல் 10% வரையிலானோருக்கு, பிற்காலத்தில் மற்றொரு அறுவை சிகிச்சை தேவைப்படுகிறது. மிகக் குறைவாகவோ மிக அதிகமாகவோ எலும்பு அகற்றப்பட்டிருந்தால், தோள்பட்டையில் கவனிக்கப்படாமல் போன வேறொரு பிரச்சினை இருந்தால், அல்லது குணமடையும்போது மூட்டில் புதிய எலும்பு உருவானால் இது நிகழலாம். நீங்கள் எதையும் முடிவு செய்வதற்கு முன், உங்கள் அறுவை சிகிச்சை நிபுணர் இந்த அபாயங்களை உங்களுடன் விரிவாகப் பேசுவார்.
நீங்கள் எந்த வழியைத் தேர்ந்தெடுத்தாலும், நோக்கம் ஒன்றே: அழற்சியைத் தணிப்பது, வழுவழுப்பான அசைவை மீட்டெடுப்பது, உங்கள் தோள்பட்டையின் உச்சியில் உள்ள அந்தக் கூர்மையான வலி இல்லாமல் மீண்டும் உங்கள் கையைப் பயன்படுத்த உதவுவது. உங்கள் அறிகுறிகள் தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களை எழுப்பினால், அல்லது வேலை செய்வதையோ கையைப் பயன்படுத்துவதையோ தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணர் மதிப்பீட்டைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
இந்த நிலையைத் தசைப் பிடிப்பு என்று தவறாக நினைப்பது எளிது; எனவே தொடக்கத்தில் இது பெரும்பாலும் கவனிக்கப்படாமல் போகிறது. தோள்பட்டைக் காயத்துக்குப் பிறகு, எலும்பு முறிவும் நிலையற்ற மூட்டும் இல்லை என்று உறுதிசெய்யப்பட்ட பின்னரும், உங்கள் காறை எலும்பின் வெளிமுனையில் வலி நீடித்தால், உங்கள் GP-யைப் பாருங்கள். பயிற்சியால் வலி தொடர்ந்து அதிகரித்தால், அல்லது ஓய்வெடுத்தும் சுமையை மாற்றியும் அது தணியவில்லை என்றால், நிபுணர் மதிப்பீட்டைக் கேளுங்கள். ஸ்கேன்கள் நோயறிதலை உறுதிப்படுத்த முடியும்: ஒப்பிடுவதற்காக இரு தோள்பட்டைகளிலும் எடுக்கப்படும் ஒரு சிறப்புக் கோண எக்ஸ்-ரே, காறை எலும்பு முனையின் ஆழத்தில் உள்ள வீக்கத்தைக் காட்டும் ஒரு MRI. இதைச் சரியாகக் கண்டறிவது முக்கியம்; ஏனெனில் இதே வலி வேறு தோள்பட்டைப் பிரச்சினைகளிலிருந்தும் வரலாம்; தவறான காரணத்தை நோக்கிய சிகிச்சை உதவாது. உங்கள் அறிகுறிகள் தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், இரவில் உங்களை எழுப்பினால், அல்லது வேலை செய்வதையோ கையைப் பயன்படுத்துவதையோ தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணர் மதிப்பீட்டைக் கேளுங்கள். அலுவலக நேரத்துக்குப் பிறகோ வார இறுதியிலோ கிளினிக்கைத் தொடர்புகொள்ள முடியாவிட்டால், உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
உங்கள் சொந்தச் சிகிச்சை முடிவுகளுக்குத் தேவையானதைவிட இந்தப் பகுதி மேலும் ஆழமாகச் செல்கிறது. டிஸ்டல் கிளாவிக்கிள் ஆஸ்டியோலைசிஸ் பற்றிக் கூடுதலாகப் படிப்பது பயனுள்ளது; ஏனெனில் அதன் காரணத்தை ஏறக்குறைய எப்போதும் கண்டறிய முடியும், பெரும்பாலானோர் அறுவை சிகிச்சை இல்லாமலேயே குணமடைகிறார்கள், கடினமான பகுதி என்னவென்றால், அதை ஏற்படுத்திய சுமையை உண்மையில் மாற்ற முடியுமா என்பதுதான்.
சுமையைப் பொதுவாகக் கண்டறிய முடியும்; அது பொதுவாக பெஞ்ச் பிரஸ் (bench press)
2026-இல் வெளியான ஒரு நோக்கெல்லை ஆய்வு (scoping review), 483 நோயாளிகளை உள்ளடக்கிய 8 ஆய்வுகளை ஒருங்கிணைத்து, 49.1% உடன் பெஞ்ச் பிரஸ் செய்வதே தூண்டும் செயல்பாடுகளில் மிகப் பொதுவானது என்றும், பொதுவான எடைப் பயிற்சி மேலும் 24.4% என்றும் கண்டறிந்தது [1]. 69.9% நோயாளிகளில், காறை எலும்பின் வெளிமுனையில் அல்லது அக்ரோமியோகிளாவிகுலர் மூட்டில் ஏற்படும் வலியே அவர்கள் முதலில் கொண்டுவந்த அறிகுறியாக இருந்தது [1]. இந்த நிலையை முதன்முதலில் வரையறுத்த ஆய்வுத் தொடரும் இதே போக்கைக் கண்டறிந்தது: ஆஸ்டியோலைசிஸ் கண்டறியப்பட்ட, திடீர்க் காயம் எதுவும் இல்லாத 46 ஆண்களில், 45 பேர் தங்கள் பயிற்சியின் ஒரு பகுதியாக எடை தூக்கினர் [2].
பெரும்பாலானவை அறுவை சிகிச்சை இல்லாமல் தணிகின்றன — ஆனால் சுமை உண்மையில் மாறினால் மட்டுமே
ஒருங்கிணைந்த ஆய்வில், பெரும்பாலான நோயாளிகள் அறுவை சிகிச்சை அல்லாத (conservative) கவனிப்பால் குணமடைந்தனர்; அறுவை சிகிச்சை அல்லாத சிகிச்சை தோல்வியடைந்த பிறகு 16% பேர் அறுவை சிகிச்சைக்குச் சென்றனர் [1]. ஒரு சிறிய குழுவினர், 4.4% (3 நோயாளிகள்), நோய் கட்டமைப்பு ரீதியாக முன்னேறியதாலோ, விளையாட்டு அல்லது தொழில் காரணங்களுக்காகத் தங்கள் சுமையை மாற்ற விரும்பாததாலோ அறுவை சிகிச்சைக்கு வந்தனர் [1]. அந்தக் கடைசிக் குழுவே இந்தப் பிரச்சினையின் நேர்மையான வடிவம்: தூண்டும் செயல்பாடு உண்மையிலேயே நிற்கும்போது அறுவை சிகிச்சை அல்லாத சிகிச்சை பலனளிக்கிறது; நோயறிதலைச் செய்வதில் சிரமம் இருப்பது அரிது.
எலும்பு அகற்றல் (resection) செய்யப்படும்போது, சிறிதளவு எலும்பே அகற்றப்படுகிறது; மீட்சி விரைவானது
எடை தூக்குபவர்களைக் கொண்ட ஒரு ஆய்வுத் தொடரில், சராசரியாக 4.5 mm அளவிலான வரம்புக்குட்பட்ட ஆர்த்ரோஸ்கோபிக் (arthroscopic) அகற்றல், சராசரியாக 3.2 நாட்களில் விளையாட்டுக்கும், 9.1 நாட்களில் அறுவை சிகிச்சைக்கு முந்தைய எடைப் பயிற்சித் திட்டத்துக்கும் திரும்ப அனுமதித்தது; அதன் பிறகு அனைத்து நோயாளிகளும் தொடர்ந்து பயிற்சி செய்து, தங்கள் சுமைகளை அதிகரித்தனர் [3]. குறைந்தது இரண்டு ஆண்டுகள் பின்தொடரப்பட்ட 59 நோயாளிகளைக் கொண்ட நவீன முன்னோக்கு ஆய்வுத் தொடர் (prospective series) ஒன்று, 24 மாதங்களுக்குள் வலி 10-க்கு 8.20-இலிருந்து 1.36-க்கு குறைந்ததாகவும், SPADI இயலாமை மதிப்பெண் 62.65-இலிருந்து 6.13-க்கு குறைந்ததாகவும், 1.72 மாதங்களில் விளையாட்டுக்கும் 3.02 மாதங்களில் வேலைக்கும் திரும்பியதாகவும் தெரிவித்தது [4]. முதல் ஆய்வுத் தொடரில், 21 நோயாளிகளுக்கு அகற்றல் செய்யப்பட்டது; பின்தொடரப்பட்ட 19 பேர் அனைவருக்கும் அது அறிகுறிகளைப் போக்கியது [2].
படமெடுப்பு அதை உறுதிப்படுத்துகிறது; மருத்துவ நிலைப்படம் மட்டும் அதைச் செய்வதில்லை
இந்த நிலையின் மருத்துவ அடையாளங்களும் அறிகுறிகளும் பிற தோள்பட்டை நோய்நிலைகளிலிருந்து வேறுபடுத்த முடியாதவையாக இருந்தன என்பதே அந்த ஆய்வின் சொந்த முடிவு [1]. MRI மிக அடிக்கடி பயன்படுத்தப்பட்ட பரிசோதனை; அது காறை எலும்பின் முனையில் எலும்பு மஜ்ஜை வீக்கத்தையும் (marrow oedema) குருத்தெலும்புக்குக் கீழான முறிவையும் (subchondral fracture) காட்டியது; அது பரிசோதனைக்குப் பதிலாக அல்லாமல், பரிசோதனையுடன் சேர்த்தே விளக்கப்பட வேண்டும் என்று ஆசிரியர்கள் வெளிப்படையாகக் கூறுகிறார்கள் [1]. நடைமுறையில், அதனால்தான் மருத்துவ வரலாறு — நீங்கள் எதைத் தூக்குகிறீர்கள், எவ்வளவு அடிக்கடி, எவ்வளவு கனமாக — ஸ்கேனுக்கு இணையான முக்கியத்துவம் பெறுகிறது.
மேற்கோள்கள்
[1] Wilkinson M, Groch N, Freestone C, et al. Risk factors and management of atraumatic distal clavicular osteolysis: a scoping review. Shoulder Elbow. 2026. https://doi.org/10.1177/17585732261479715 [2] Cahill BR. Osteolysis of the distal part of the clavicle in male athletes. J Bone Joint Surg Am. 1982;64(7):1053-58. https://doi.org/10.2106/00004623-198264070-00015 [3] Auge WK, Fischer RA. Arthroscopic distal clavicle resection for isolated atraumatic osteolysis in weight lifters. Am J Sports Med. 1998;26(2):189-92. https://doi.org/10.1177/03635465980260020701 [4] Leon JV, Hermans D, Venkatesha V, et al. Patient outcomes following arthroscopic distal clavicle excision: a prospective case series. JSES Int. 2023;7(6):2400-05. https://doi.org/10.1016/j.jseint.2023.07.014
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Clinical Presentation and Diagnosis
- Clinical signs and symptoms for atraumatic distal clavicular osteolysis are not distinguishable from other shoulder pathologies [1].
- Post-traumatic osteolysis of the distal clavicle should be considered if there is persistent pain after a shoulder injury and bony lesions or instabilities have been excluded [3].
- Osteolysis of the distal end of the clavicle is a rare condition that can occur during judo [5].
- Special care must be taken to properly identify the acromioclavicular joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure [22].
Etiology and Pathogenesis
- Propionibacterium acnes–mediated distal clavicular osteolysis is a documented etiology [2].
- Heterotopic bone formation is a more common cause of failure of acromioplasty or distal claviculectomy than is acknowledged by the literature [13].
- Subacromial osteolysis can occur following hook plate fixation for acromioclavicular dislocation [4].
- The risk of subacromial osteolysis following hook plate fixation is minimized by removing the implant within 5.5 months and preventing severe osteolysis by removal no more than 11.9 months after surgery [15].
- Maintaining the acromion-hook angle at 10 degrees or less is recommended to minimize the risk of subacromial osteolysis following hook plate fixation [15].
Surgical Management
- The combination of distal clavicle resection and antibiotics halted osteolysis in a patient with Propionibacterium acnes–mediated disease, who remained symptom-free at 10 months after surgery [2].
- Arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures in carefully selected patients with isolated acromioclavicular joint pathology [7].
- Arthroscopic and open distal clavicle excisions both provide significant pain reduction at 1 year with no significant difference in outcome measures between groups, except for VAS pain score improvement [9].
- Patients undergoing arthroscopic distal clavicle excision for acromioclavicular joint pathology can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [11].
- Limited distal clavicle excision of patients with acromioclavicular joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [14].
- Open and arthroscopic distal clavicle excision are both effective surgeries to treat recalcitrant acromioclavicular joint pain, providing similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up [32].
- Less residual pain was found using the arthroscopic technique compared to the open technique for distal clavicle excision [32].
- Both the direct superior approach and the indirect subacromial approach to arthroscopic distal clavicle resection result in successful clinical outcome with clinically insignificant difference at final follow-up [24].
- A well-performed distal clavicle excision will likely perform better than a poorly performed one, regardless of whether an open or arthroscopic approach is chosen [21].
- Portal placement remains paramount in both facilitating surgery and avoiding injury to adjacent extra-articular structures regardless of the technique chosen for distal clavicle resection [19].
- Intraoperative use of ultrasound and cannulated dilators allows surgeons to perform distal clavicle excisions in a more efficient, reproducible, and safer manner [33].
- The supraspinatus fossa portal technique provides a technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement [38].
- Coracoclavicular ligament reconstruction is an effective surgical approach for decreasing the incidence of subacromial osteolysis following hook plate fixation [4].
Surgical Technique and Biomechanics
- A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model, whereas excision with 2.5 mm of bone was successful in many specimens [16].
- Surgery for osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint may involve resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon [10].
Indications and Contraindications
- Routine distal clavicle resection in the setting of rotator cuff repair does not result in improved outcomes for patients with no difference being observed at 24 months post surgery [23].
- Distal clavicle resection in patients with rotator cuff tears did not result in better clinical outcome scores or shoulder range of motion and was not associated with a lower risk of reoperation [26].
- Routine distal clavicle excision is not absolutely necessary, even in patients with symptomatic acromioclavicular joint osteoarthritis [29].
Anatomy & Pathophysiology
Bony Anatomy
- The clavicle is the only long bone to ossify by intramembranous ossification [39].
- The clavicle serves as the primary stabilizer between the axial skeleton via the sternoclavicular joint and the appendicular skeleton via the acromioclavicular joint [39].
- The clavicle forms a unique S-shaped curve on the axial view [39].
- The distal clavicle is flat in the AP plane [39].
- The primary blood supply to the clavicle is periosteal, with no nutrient blood supply [39].
- The clavicle is subcutaneous, and its muscular envelope includes the platysma, pectoralis major, deltoid, and some of the strap muscles of the neck [39].
- In the transverse plane, the clavicle resembles an italic S [52].
- The greater radius of curvature of the clavicle occurs at its medial curve, which is anteriorly convex [52].
- The smaller lateral curve of the clavicle is posteriorly convex [52].
- The bone is somewhat rounded in its midsection and medially and relatively flat laterally [52].
- The medial end of the clavicle has a 30% incidence of a rhomboid fossa on its inferior surface where the costoclavicular ligaments insert [52].
- The medial end of the clavicle has a 2.5% incidence of actual articular surface facing inferiorly toward the first rib [52].
- The middle portion of the clavicle contains the subclavian groove where the subclavius muscle has a fleshy insertion [52].
- The lateral portion of the clavicle has the coracoclavicular process when present [52].
- The conoid ligament attaches to the clavicle at the conoid tubercle [52].
- The trapezoid ligament attaches at the trapezoid line, which lies in an anteroposterior direction just lateral to the conoid tubercle [52].
- The distance from the lateral edge of the clavicle to the medial edge of the conoid tubercle is approximately 45 mm in male and female specimens [52].
- The distance from the lateral edge of the clavicle to the center of the trapezoid tuberosity is approximately 25 mm in male and female specimens [52].
- The trapezius inserts on the posterosuperior surface of the distal end of the clavicle [52].
- The subclavius muscle has a fleshy insertion on the inferior surface of the middle third of the clavicle [52].
- The deltoid originates on the anterior portion of the inner surface of the lateral curve of the clavicle [52].
- The pectoralis major originates from the anterior portion of the medial two-thirds of the clavicle [52].
- The sternocleidomastoid largely originates on the posterior portion of the middle third of the clavicle [52].
- The sternohyoid originates on the clavicle just medial to the origin of the sternocleidomastoid [52].
- The subclavian vein and artery and brachial plexus lie posterior to the clavicle [52].
- The medial anterior curve of the clavicle is often described as an accommodation for the subclavian vein and artery and brachial plexus [52].
- The clavicle is one of the first bones to ossify, beginning from two primary ossification centers (medial and lateral) by 5 to 6 weeks of gestation [51].
- By 7 to 8 weeks of gestation, the clavicle has already assumed its overall contour and “S” shape [51].
- Most growth (80%) of the clavicle occurs from the medial physis [51].
- The lateral epiphysis of the clavicle forms and fuses at around 18 to 19 years of age [51].
- The medial epiphysis of the clavicle is the last in the body to ossify, at the age of 18 to 20 years [51].
- The medial epiphysis of the clavicle is the last to complete ossification, at the age of 23 to 25 years [51].
Ligaments and Soft Tissue Stabilizers
- The coracoclavicular ligaments consist of the conoid (medial) and trapezoid (lateral) components [39].
- The coracoclavicular ligaments are the primary stabilizers to superior (vertical) translation of the distal clavicle [39].
- The superior shoulder suspensory complex is a bone–soft-tissue ring that provides a stable connection of the glenoid and scapula to the clavicle [39].
- The superior shoulder suspensory complex is composed of four bony landmarks: distal clavicle, acromion, coracoid process, and glenoid neck [39].
- The superior shoulder suspensory complex includes the supporting ligamentous complexes of the AC joint and the CC ligaments [39].
- The acromion has three ossification centers: the meta-acromion (base), the mesoacromion (mid), and the preacromion (tip) [50].
- The coracoid process is the site of ligament attachments for the CC ligaments [50].
- The superior shoulder suspensory complex plays an important role in shoulder stability and biomechanics [50].
- The pectoralis major muscle originates from the clavicular shaft anteroinferiorly [56].
- The sternocleidomastoid originates superiorly on the clavicle [56].
- The pectoralis origin merges with the origin of the anterior deltoid laterally [56].
- The trapezius insertion blends superiorly with the deltoid origin at the lateral margin of the clavicle [56].
- The subclavius muscle inserts on the undersurface of the clavicle [56].
- The platysma usually envelopes the anterior and superior aspects of the clavicle and runs in the subcutaneous tissues [56].
- The supraclavicular nerves originate from cervical roots C3 and C4 [58].
- The supraclavicular nerves exit from a common trunk behind the posterior border of the sternocleidomastoid muscle [58].
- There are typically three major branches of the supraclavicular nerves (anterior, middle, and posterior) that cross the clavicle superficially from medial to lateral [58].
- The subclavian vein runs directly below the subclavius muscle and above the first rib [58].
- The subclavian artery and the brachial plexus lie more posteriorly than the subclavian vein, separated from the vein and clavicle by the scalenus anterior muscle medially [58].
- The brachial plexus is closest to the clavicle in its midportion [58].
- In the middle third of the clavicle, the subclavian artery is a mean of 17 mm from the clavicle [58].
- In the middle third of the clavicle, the subclavian vein is a mean of 13 mm from the clavicle [58].
- In the middle third of the clavicle, the subclavian vessels are located at an approximate angle of 60 degrees to the horizontal [58].
- Laterally, the subclavian artery is a mean of 63 mm from the clavicle [58].
- Laterally, the subclavian vein is a mean of 76 mm from the clavicle [58].
Pathophysiology
- Clinical signs and symptoms for atraumatic distal clavicular osteolysis were not distinguishable from other shoulder pathologies [1].
- Post-traumatic osteolysis of the distal clavicle occurs from several weeks to several months after injury to the acromioclavicular joint [17].
- In post-traumatic osteolysis, radiographs show no luxation or fracture initially [17].
- Shoulder pain in post-traumatic osteolysis develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [17].
- The process of osteolysis in post-traumatic distal clavicle osteolysis occurs only in the distal clavicle, and there is no osteolytic lesion in the acromion [17].
- Post-traumatic osteolysis of the distal clavicle was first described by Werder in 1950 [17].
- More than 100 cases of post-traumatic osteolysis have been reported [17].
- The pathogenesis of post-traumatic osteolysis remains unclear [17].
- Osteoclastic resorption has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Nervous system dysfunction has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Avascular necrosis has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Microfracture has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Synovial invasion has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Non-traumatic osteolysis of the acromial end of the clavicle should be considered in cases of pain in the shoulder in athletes [6].
- It is important to consider the possibility of post-traumatic osteolysis of the distal clavicle if there is persistent pain after a shoulder injury, and bony lesions or instabilities have been excluded [3].
- The combination of distal clavicle resection and antibiotics halted the osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis [2].
- The patient with Propionibacterium acnes–mediated distal clavicular osteolysis remained symptom free at 10 months after surgery [2].
- For all patients with atraumatic osteolysis of the distal clavicle, return to sports activities was dependent on changes in the way of training [8].
- Distal clavicle excision is a widely accepted surgical treatment for symptomatic acromioclavicular joint pathology, including osteoarthritis, post-traumatic degeneration, and osteolysis [47].
- Mechanisms of failure following distal clavicle excision include inadequate resection [47].
- Mechanisms of failure following distal clavicle excision include excessive bone removal resulting in instability [47].
- Mechanisms of failure following distal clavicle excision include unrecognized concomitant pathology [47].
- Mechanisms of failure following distal clavicle excision include iatrogenic disruption of the coracoclavicular ligaments [47].
- The reported incidence of reoperation following distal clavicle excision ranges from 4% to 10% [47].
- A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness [35].
- If the resection was 2.5 mm or less, abutment was likely to occur between the acromion and the clavicle, particularly inferiorly and posteriorly [53].
- Joint stiffness diminished with the amount of bone resected [53].
- Resection of more than 7.6 mm of the distal clavicle in men can violate the superior AC ligament [53].
- Resection of more than 5.2 mm of the distal clavicle in women can violate the superior AC ligament [53].
- Resection of less than 11.0 mm should never violate any portion of the trapezoid ligament in 98% of men or women [53].
- Resection of less than 24.0 mm should never violate any of the conoid ligament [53].
- Patients with a resection of more than 1.0 cm have more pain than patients with less than 1 cm of resection [53].
- The anterior-posterior load to clinical failure of the AC joint after 5 mm of resection from the distal clavicle and medial acromion is significantly greater than 1 cm of the resected distal clavicle alone [77].
- Intact acromioclavicular ligaments protect the coracoclavicular reconstruction by decreasing the in situ graft force [75].
- Inaccurate resection from lack of depth perception and inadequate visualization has been reported to lead to failure and revision surgery [28].
Classification
- Distal clavicular osteolysis presents as isolated pain at the distal clavicle and acromioclavicular joint that tends to worsen with activity [27].
- There are two forms of distal clavicular osteolysis: posttraumatic distal clavicular osteolysis caused by a direct traumatic injury, and atraumatic distal clavicular osteolysis attributable to repetitive stress [27].
- In adults, the most common risk factor for stress-induced distal clavicular osteolysis is weightlifting [27].
- Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than is generally recognized, with many cases potentially overlooked or misinterpreted [17].
- In post-traumatic osteolysis, radiographs initially show no luxation or fracture, followed by gradual development of shoulder pain, swelling of the acromioclavicular joint, and limitation of shoulder motion [17].
- The process of post-traumatic osteolysis occurs only in the distal clavicle, with no osteolytic lesion in the acromion [17].
- Hypothesized pathogenesis for post-traumatic osteolysis includes osteoclastic resorption, nervous system dysfunction, avascular necrosis, microfracture, and synovial invasion [17].
- Propionibacterium acnes–mediated distal clavicular osteolysis is a recognized etiology for the condition [2].
- Aseptic foreign-body reaction to Gore-Tex grafts used for clavicle-to-coracoid stabilization can result in clavicle osteolysis [20].
- Prolonged implant retention and higher-grade fracture types significantly increase the risk of subacromial osteolysis following hook plate fixation [78].
Clinical Presentation
Symptoms and Signs
- Patients with distal clavicular osteolysis present with isolated pain at the distal clavicle and acromioclavicular joint that tends to worsen with activity [27, 65].
- Post-traumatic osteolysis of the distal clavicle is characterized by shoulder pain that develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [17].
- In post-traumatic osteolysis, radiographs initially show no luxation or fracture [17].
- Persistent pain after a shoulder injury, after bony lesions or instabilities have been excluded, should prompt consideration of post-traumatic osteolysis of the distal clavicle [3].
- Non-traumatic osteolysis of the acromial end of the clavicle should be considered in cases of shoulder pain in athletes [6].
- Osteolysis of the distal end of the clavicle can occur during judo [5].
- A 58-year-old male carpenter presented with osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint [10].
Imaging Findings
- Radiographic findings for distal clavicular osteolysis may range from mild osteopenia to overt osteolysis [27, 65].
- The bilateral Zanca view is helpful for diagnosing distal clavicular osteolysis as it profiles the acromioclavicular joint and allows for comparison with the contralateral side [27, 65].
- MRI characteristics of distal clavicular osteolysis include distal clavicular bone marrow edema that is out of proportion to the edema at the acromion [27, 65].
- MRI characteristics of distal clavicular osteolysis include subchondral cystic change [27, 65].
- In advanced cases of distal clavicular osteolysis, periostitis may be observed at the distal clavicle on MRI [27, 65].
- The process of osteolysis in post-traumatic cases occurs only in the distal clavicle, with no osteolytic lesion in the acromion [17].
Risk Factors and Etiology
- Posttraumatic distal clavicular osteolysis is caused by a direct traumatic injury [27, 65].
- Atraumatic distal clavicular osteolysis is attributable to repetitive stress [27, 65].
- Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than generally recognized, with many cases potentially overlooked or misinterpreted [17].
- More than 100 cases of post-traumatic osteolysis have been reported since Werder first described the condition in 1950 [17].
- Propionibacterium acnes infection has been identified as a cause of distal clavicular osteolysis [2].
- Aseptic foreign-body reaction to Gore-Tex grafts can cause clavicle osteolysis [20].
- Bone osteolysis can occur following acromioclavicular joint reconstruction using synthetic ligament (Surgilig™) [31].
Investigations
Clinical Presentation and Diagnosis
- In post-traumatic osteolysis, radiographs typically show no luxation or fracture initially [17].
- The process of osteolysis in post-traumatic distal clavicle injury occurs only in the distal clavicle, with no osteolytic lesion in the acromion [17].
- A high index of suspicion is needed to diagnose complications such as osteolysis early before irretrievable bone loss [31].
Imaging and Anatomical Landmarks
- Special care must be taken to properly identify the AC joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure [22].
- The cross-sectional A-frame morphology of the superior cortex of the distal clavicle provides a reproducible landmark that is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle [49].
- The A-frame morphology of the distal clavicle can be used intraoperatively to determine when adequate resection has been completed [49].
Treatment
Non-Operative
- Activity modification, NSAIDs, and physical therapy are first-line treatments for distal clavicular osteolysis [27].
- Intra-articular injection of lidocaine and corticosteroids into the acromioclavicular joint is both diagnostic and therapeutic for distal clavicular osteolysis [27].
- Nonoperative treatment with injections, medication, and physical therapy is a good option for in-season athletes with distal clavicular osteolysis [27].
- The combination of distal clavicle resection and antibiotics halted osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis [2].
Operative
- Distal clavicle resection is the definitive operative treatment for distal clavicular osteolysis failing nonoperative management [27].
- Patients undergoing arthroscopic distal clavicle excision through the direct approach can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [11].
- Open and arthroscopic distal clavicle excision provide similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up, though less residual pain was found using the arthroscopic technique [32].
- A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model [16].
- A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness in a cadaveric model [35].
- Anterior acromioplasty is needed in cases with subacromial impingement during distal clavicle resection [18].
- SLAP lesion repair after initial distal clavicle resection successfully treated 15 patients, indicating that associated or underlying superior labral detachment may cause similar symptoms leading to misdiagnosis [25].
- The use of intraoperative ultrasound and cannulated dilators allows surgeons to perform distal clavicle excisions in a more efficient, reproducible, and safer manner [33].
- The introduction of the supraspinatus fossa portal technique provides a special technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement [38].
- Coracoclavicular ligament reconstruction is an effective surgical approach for decreasing the incidence of subacromial osteolysis following hook plate fixation for acromioclavicular dislocation [4].
- Removing the implant within 5.5 months minimizes osteolysis risk and no more than 11.9 months prevents severe osteolysis, while maintaining the acromion-hook angle at 10 degrees or less [15].
- Foreign-body reaction and osteolysis have been reported with the use of Gore-Tex graft to stabilize the clavicle to the coracoid [20].
Complications
Diagnostic and Pathologic Complications
- Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than generally recognized, with many cases overlooked or misinterpreted [17].
- In post-traumatic osteolysis, radiographs initially show no luxation or fracture, and shoulder pain develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [17].
- Heterotopic bone formation may be a more common cause of failure of acromioplasty or distal clavicectomy than acknowledged in the literature [30].
- Aseptic foreign-body reaction and clavicle osteolysis can occur following acromioclavicular reconstruction using Gore-Tex graft [20].
- A high index of suspicion is needed to diagnose complications such as osteolysis early before irretrievable bone loss occurs [31].
- Distal clavicle fracture is a complication of arthroscopic distal clavicle resection [22].
- Pre-existing distal clavicle stress fracture or osteolysis must be ruled out before performing the arthroscopic Mumford procedure [22].
Operative Complications and Failure Mechanisms
- Multiple mechanisms of failure following distal clavicle excision include inadequate resection, excessive bone removal resulting in instability, unrecognized concomitant pathology, and iatrogenic disruption of the coracoclavicular ligaments [47].
- A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model, whereas 2.5 mm resection was successful in many specimens [16].
- SLAP lesions can cause continued symptoms and failure of distal clavicle resection due to misdiagnosis of associated or underlying superior labral detachment [25].
- Resection of the lateral end of the clavicle following osteolysis is a described surgical management [6].
- Surgery for osteolysis of the distal clavicle progressing to osteoarthritic change can involve resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon [10].
Outcomes and Prognosis
- A subset of patients experience persistent pain, residual instability, or functional limitation following primary distal clavicle excision that ultimately requires additional surgical intervention [47].
- Outcomes following revision surgery for persistent pain and/or instability after distal clavicle excision remain poorly characterized and are primarily composed of small cohort studies [47].
- Return to sports activities for patients with atraumatic osteolysis of the distal clavicle was dependent on changes in the way of training [8].
- In carefully selected patients with isolated acromioclavicular joint pathology, arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures [7].
Recovery
Post-operative Outcomes and Return to Activity
- Patients undergoing arthroscopic distal clavicle excision, specifically through the direct approach, can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [11].
Surgical Technique and Biomechanics
Complications and Failure Modes
- The successful treatment of 15 patients by SLAP lesion repair after initial distal clavicle resection indicates that there may be misdiagnosis due to associated or underlying superior labral detachment causing similar symptoms [25].
- A high index of suspicion is needed to diagnose complications such as bone osteolysis following acromioclavicular joint reconstruction using synthetic ligament early before irretrievable bone loss [31].
- The combination of distal clavicle resection and antibiotics halted osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis, with the patient remaining symptom free at 10 months after surgery [2].
Key Evidence
- [L4] Clinical signs and symptoms for atraumatic distal clavicular osteolysis (ADCO) were not distinguishable from other shoulder pathologies. [1] (10.1177/17585732261479715)
- [Case_report] The combination of distal clavicle resection and antibiotics halted the osteolysis, and the patient has remained symptom free at 10 months after surgery. [2] (10.1016/j.jse.2015.03.004)
- [L4] It is important to consider the possibility of post-traumatic osteolysis of the distal clavicle if there is persistent pain after a shoulder injury, and bony lesions or instabilities have been excluded. [3] (10.1007/bf00573456)
- [L1] The current analysis suggests coracoclavicular ligament reconstruction as an effective surgical approach for decreasing the incidence of subacromial osteolysis. [4] (10.1016/j.jse.2024.03.018)
- [L5] Osteolysis of the distal end of the clavicle is a rare condition and it can occur during judo. [5] (10.1016/s1058-2746(96)80543-x)
- [L4] Non-traumatic osteolysis of the acromial end of the clavicle should be borne in mind in cases of pain in the shoulder in athletes. [6] (10.1016/0020-1383(87)90010-6)
- [L4] In carefully selected patients with isolated ACJ pathology, arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures. [7] (10.1016/j.jseint.2023.07.014)
- [L4] For all patients, return to sports activities was dependent on changes in the way of training. [8] (10.1016/s1058-2746(96)80377-6)
- [L1] Arthroscopic and open distal clavicle excisions both provide significant pain reduction at 1 year with no significant difference in outcome measures between groups, except for VAS pain score improvement. [9] (10.1016/j.jse.2006.10.006)
- [L5] A 58-year-old male carpenter with osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint underwent surgery involving resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon. [10] (10.1016/s1058-2746(95)80313-0)
- [L3] Among patients undergoing distal clavicle excision for acromioclavicular joint pathology, those having an arthroscopic procedure, specifically through the direct approach, can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure. [11] (10.1016/j.arthro.2009.12.007)
- [L4] This retrospective series suggests that heterotopic bone formation is a more common cause of failure of acromioplasty or distal claviculectomy than is acknowledged by the literature. [13] (10.1016/s1058-2746(05)80050-3)
- [L4] Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up. [14] (10.1016/j.otsr.2016.01.008)
- [L3] The authors recommend removing the implant within 5.5 months to minimize osteolysis risk and no more than 11.9 months to prevent severe osteolysis, while maintaining the acromion-hook angle at 10 degrees or less. [15] (10.1016/j.jse.2024.09.027)
- [Abstract] Although distal clavicle excision with 2.5 mm of bone was successful in many specimens, a 5 mm resection guaranteed no bone-to-bone abutment. [16] (10.1016/j.jse.2007.02.105)
- [L5] [17] (10.1067/mse.2002.122229)
- [L4] Additionally, the anterior acromioplasty is needed in the cases with subacromial impingement. [18] (10.1016/s1058-2746(96)80520-9)
- [Case_report] Regardless of the technique chosen for distal clavicle resection, portal placement remains paramount in both facilitating surgery and avoiding injury to adjacent extra-articular structures. [19] (10.1016/j.jse.2010.08.032)
- [L5] The case presented reports foreign-body reaction and osteolysis with the use of Gore-Tex graft to stabilize the clavicle to the coracoid. [20] (10.1016/j.jse.2004.01.027)
- [L5] A well-performed distal clavicle excision will likely perform better than a poorly performed one, regardless of whether an open or arthroscopic approach is chosen. [21] (10.1016/j.arthro.2018.03.004)
- [L4] Special care must be taken to properly identify the AC joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure. [22] (10.1016/j.arthro.2009.02.008)
- [L2] Routine distal clavicle resection in the setting of rotator cuff repair does not result in improved outcomes for patients with no difference being observed at 24 months post surgery. [23] (10.1177/1758573217741124)
- [L2] Both the direct superior approach and the indirect subacromial approach to the arthroscopic distal clavicle resection result in successful clinical outcome with clinically insignificant difference at final follow-up. [24] (10.1177/0363546506294855)
- [L4] The successful treatment of 15 patients by SLAP lesion repair after initial distal clavicle resection indicates that there may be misdiagnosis due to associated or underlying superior labral detachment causing similar symptoms. [25] (10.1016/s1058-2746(96)80319-3)
- [L1] Distal clavicle resection in patients with rotator cuff tears did not result in better clinical outcome scores or shoulder ROM and was not associated with a lower risk of reoperation. [26] (10.1097/corr.0000000000000424)
- [Paper] [28] (10.1016/j.eats.2020.10.010)
- [L2] Routine distal clavicle excision is not absolutely necessary, even in patients with symptomatic ACJ osteoarthritis. [29] (10.1007/s00167-020-06098-y)
- [L4] Heterotopic bone formation may be a more common cause of failure of acromioplasty or distal clavicectomy than acknowledged in the literature. [30] (10.1016/s1058-2746(96)80126-1)
- [L4] A high index of suspicion is needed to diagnose such complications early before irretrievable bone loss to osteolysis. [31] (10.1111/sae.12035)
- [L3] Open and arthroscopic distal clavicle excision are both effective surgeries to treat recalcitrant acromioclavicular joint pain, providing similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up, though less residual pain was found using the arthroscopic technique. [32] (10.1177/0363546511419633)
- [L5] The technique will allow surgeons to perform distal clavicle excisions in a more efficient, reproducible and safer manner. [33] (10.1016/j.eats.2024.103331)
- [L5] A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness. [35] (10.1016/j.arthro.2007.07.004)
- [Paper] The introduction of this technique provides a special technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement. [38] (10.1016/j.eats.2020.08.040)
- [L4] [47] (10.1016/j.jse.2026.08.016)
- [L5] The cross-sectional A-frame morphology of the superior cortex of the distal clavicle provides a reproducible landmark that is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle, which can be used intraoperatively to determine when adequate resection has been completed. [49] (10.1016/j.jse.2021.10.013)
- [L5] Intact acromioclavicular ligaments protect the coracoclavicular reconstruction by decreasing the in situ graft force. [75] (10.1177/0363546510374447)
- [L5] This cadaveric study demonstrates that the anterior-posterior load to clinical failure of the AC joint after 5 mm of resection from the distal clavicle and medial acromion is significantly greater than 1 cm of the resected distal clavicle alone. [77] (10.1177/0363546512469873)
- [L3] Prolonged implant retention and higher-grade fracture types significantly increase the risk of subacromial osteolysis (SAO). [78] (10.1186/s12891-026-09516-3)
References
[1] Risk factors and management of atraumatic distal clavicular osteolysis: A scoping review. Shoulder & Elbow. 2026. DOI: 10.1177/17585732261479715
[2] Propionibacterium acnes–mediated distal clavicular osteolysis: a case report. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.03.004
[3] Post-traumatic osteolysis of the distal clavicle. Archives of Orthopaedic and Trauma Surgery. 1996. DOI: 10.1007/bf00573456
[4] Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation: a systematic review and meta-analysis. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2024.03.018
[5] Post-traumatic osteolysis of the distal end of the clavicle in judo athlete: Case report. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80543-x
[6] Resection of the lateral end of the clavicle following osteolysis, with emphasis on non-traumatic osteolysis of the acromial end of the clavicle in athletes. Injury. 1987. DOI: 10.1016/0020-1383(87)90010-6
[7] Patient outcomes following arthroscopic distal clavicle excision: a prospective case series. JSES International. 2023. DOI: 10.1016/j.jseint.2023.07.014
[8] Atraumatic osteolysis of the distal clavicle. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80377-6
[9] Arthroscopic versus open distal clavicle excision: Comparative results at six months and one year from a randomized, prospective clinical trial. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2006.10.006
[10] Osteolysis of the distal end of the clavicle: A case report. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80313-0
[11] Open Versus Arthroscopic Distal Clavicle Resection. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.12.007
[13] Heterotopic ossification after acromioplasty and distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80050-3
[14] Limited distal clavicle excision of acromioclavicular joint osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2016.01.008
[15] Predictive value of implant removal time and acromion-hook angle on subacromial osteolysis following hook plate fixation for acromioclavicular dislocation. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.09.027
[16] Arthroscopic Distal Clavicle Resection: A Biomechanical Analysis In A Cadaver Model. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2007.02.105
[17] A case of post-traumatic osteolysis of the distal clavicle: Histologic lesion of the acromion. Journal of Shoulder and Elbow Surgery. 2002. DOI: 10.1067/mse.2002.122229
[18] The usefulness of distal clavicle resection for acromioclavicular joint disease. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80520-9
[19] Acromioclavicular dislocation after arthroscopic distal clavicle resection: a case report. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.08.032
[20] Failure of acromioclavicular reconstruction using Gore-Tex graft due to aseptic foreign-body reaction and clavicle osteolysis: A case report. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/j.jse.2004.01.027
[21] Editorial Commentary: The “Mumford” & Sons: For Distal Clavicle Excisions, What Are Our Young Surgeons Doing, and How Well Are They Doing It?. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.03.004
[22] Distal Clavicle Fracture as a Complication of Arthroscopic Distal Clavicle Resection. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.02.008
[23] Is routine distal clavicle resection necessary in rotator cuff repair surgery? A systematic review and meta-analysis. Shoulder & Elbow. 2017. DOI: 10.1177/1758573217741124
[24] Arthroscopic Distal Clavicle Resection in Athletes. The American Journal of Sports Medicine. 2007. DOI: 10.1177/0363546506294855
[25] The slap lesion as a cause of continued symptoms and failure of distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80319-3
[26] Does Distal Clavicle Resection Decrease Pain or Improve Shoulder Function in Patients With Acromioclavicular Joint Arthritis and Rotator Cuff Tears? A Meta-analysis. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000424
[27] Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability. 2016.
[28] Distal Clavicle Excision for Acromioclavicular Joint Osteoarthritis Using a Fluoroscopic Kirschner Wire Guide. Arthroscopy Techniques. 2021. DOI: 10.1016/j.eats.2020.10.010
[29] Acromioclavicular joint arthritis is not an indication for routine distal clavicle excision in arthroscopic rotator cuff repair. Knee Surgery, Sports Traumatology, Arthroscopy. 2020. DOI: 10.1007/s00167-020-06098-y
[30] Heterotopic ossification after acromioplasty and distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80126-1
[31] Bone Osteolysis Following Acromioclavicular Joint Reconstruction Using Synthetic Ligament (Surgilig™). Shoulder & Elbow. 2014. DOI: 10.1111/sae.12035
[32] Arthroscopic Versus Open Distal Clavicle Excision. The American Journal of Sports Medicine. 2011. DOI: 10.1177/0363546511419633
[33] Intraoperative Use of Ultrasound and Cannulated Dilators to Safely Identify and Access the Acromioclavicular Joint for Distal Clavicle Excision: A Technique Guide. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103331
[35] Arthroscopic Distal Clavicle Resection: A Biomechanical Analysis of Resection Length and Joint Compliance in a Cadaveric Model. Arthroscopy. 2007. DOI: 10.1016/j.arthro.2007.07.004
[38] Arthroscopic Distal Clavicle Resection Through the Supraspinatus Fossa Portal. Arthroscopy Techniques. 2020. DOI: 10.1016/j.eats.2020.08.040
[39] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Clavicle, Scapula, and Glenoid > I. Clavicular Fractures.
[47] Clinical Outcomes and Predictors of Dissatisfaction Following Revision Surgery After Distal Clavicle Excision. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.08.016
[49] Distal clavicle “A-frame” morphology: a reliable intraoperative guide for arthroscopic distal clavicle excision. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.10.013
[50] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Clavicle, Scapula, and Glenoid > II. Scapular and Glenoid Fractures.
[51] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > FRACTURES OF THE CLAVICLE.
[52] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Clavicle.
[53] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > Neurovascular Structures > EXCISION OF THE DISTAL CLAVICLE.
[56] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Muscular Anatomy of the Clavicle.
[58] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Neurovascular Anatomy of the Clavicle.
[65] Rockwood And Matsen S The Shoulder. Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability > Distal Clavicle Osteolysis > Indications.
[75] The Effect of Distal Clavicle Excision on in Situ Graft Forces in Coracoclavicular Ligament Reconstruction. The American Journal of Sports Medicine. 2010. DOI: 10.1177/0363546510374447
[77] The Biomechanical Stability of Distal Clavicle Excision Versus Symmetric Acromioclavicular Joint Resection. The American Journal of Sports Medicine. 2012. DOI: 10.1177/0363546512469873
[78] What is the optimal implant removal timing following hook plate fixation in distal clavicle fractures: a retrospective analysis from subacromial osteolysis cases. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09516-3