Patients › Shoulder
AC மூட்டுத் தேய்மான மூட்டழற்சி (AC Joint Osteoarthritis)
AC joint osteoarthritis causes localized shoulder pain with cross-body movements; treatment ranges from activity modification to surgery.
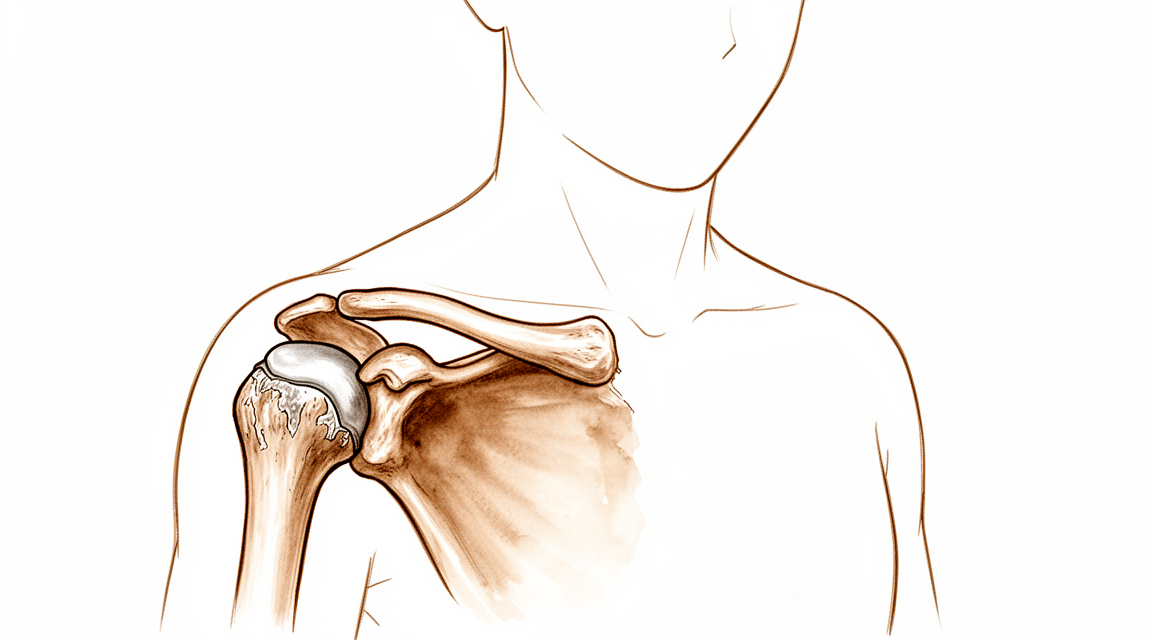
நீங்கள் உணர்வது
வலி உங்கள் தோள்பட்டையின் உச்சியிலேயே, உங்கள் காறை எலும்பு (collarbone) உங்கள் தோள்பட்டை எலும்பின் மிக உயர்ந்த பகுதியைச் சந்திக்கும் அந்தச் சிறிய மூட்டில் அமர்ந்திருக்கும். அது பெரும்பாலும் தோள்பட்டையின் முன்பக்கம் நோக்கியோ, உங்கள் கழுத்திலிருந்து தோள்பட்டை வரை செல்லும் தசைக்குள் மேல்நோக்கியோ பரவுகிறது. கனமான எதையாவது தூக்குவது வலியைக் கிளப்புகிறது; இரவில் அந்தப் பக்கமாகப் படுப்பது உங்களைத் தூக்கத்திலிருந்து எழுப்பலாம், அல்லது வசதியான நிலையைக் கண்டுபிடிப்பதைக் கடினமாக்கலாம்.
அந்த இடத்தில் நேரடியாக அழுத்தினால் பொதுவாகத் தொடுவலி தெரியும். உங்கள் கையை மார்புக்குக் குறுக்கே நீட்டுவதோ, அதைப் பக்கவாட்டில் முழுவதும் மேலே தூக்குவதோ, மூட்டில் வலியை ஏற்படுத்தும் போக்கு உள்ளது. தோள்பட்டையின் உச்சியில் சுமையை ஏற்றும் அன்றாட வேலைகள் சிரமமாகின்றன: பக்கவாட்டில் கடைப் பைகளைச் சுமப்பது, கனமான வாணலியை அடுப்பின் மீது தூக்கி வைப்பது, உயரமான அலமாரியை எட்டுவது, அல்லது சீட் பெல்ட்டை உடலின் குறுக்கே இழுப்பது.
வலி பெரும்பாலும் செயல்பாட்டின்போது அல்லாமல் அதற்குப் பிறகே அதிகரிக்கிறது; எனவே ஒரு நாள் முழுவதும் பொருட்களைத் தூக்குவதோ தலைக்கு மேல் கையை உயர்த்தி வேலை செய்வதோ, அன்று மாலையும் மறுநாள் காலையும் உங்களுக்கு வலியை விட்டுச்செல்லலாம். பாதிக்கப்பட்ட பக்கத்தில் இரவு வலி பொதுவானது; சிலர் மல்லாந்தோ மறுபக்கமாகவோ படுத்துத் தூங்க வேண்டியிருப்பதைக் காண்கிறார்கள்.
தெரிந்துகொள்ள வேண்டிய ஒரு விஷயம்: இந்த மூட்டில் ஏற்படும் மூட்டழற்சி, எந்த வலியையும் உணராத பலருக்கும் ஸ்கேன்களில் தெரிகிறது. எக்ஸ்-ரேயில் தேய்ந்ததாகத் தெரியும் இது போன்ற மூட்டுகளில் பெரும்பாலானவை அமைதியாகவே இருக்கின்றன; தேய்ந்ததாகத் தெரியும் மூட்டுடன் தோள்பட்டை வலி இருப்பது, அந்த மூட்டுதான் காரணம் என்று எப்போதும் பொருள்படாது. அதனால்தான், மூட்டுக்குள்ளேயே மரத்துப்போகச் செய்யும் மருந்தை ஊசி மூலம் செலுத்த உங்கள் அறுவை சிகிச்சை நிபுணர் பரிந்துரைக்கலாம். அதன் பிறகு சிறிது நேரத்துக்கு வலி தணிந்தால், உங்கள் பிரச்சினையின் மூலம் அந்த மூட்டுதான் என்பது மிகவும் சாத்தியம். தணியாவிட்டால், ஸ்கேனில் தெரியும் தேய்மானம் உங்களுக்கு வலியை ஏற்படுத்துவதில்லை என்பதே பெரும்பாலும் உண்மை; அதற்குச் சிகிச்சை அளிப்பது உதவ வாய்ப்பில்லை.
உங்கள் தோள்பட்டை வலி வாரக்கணக்கில் தணியாவிட்டால், மோசமாகிக்கொண்டே போனால், இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், அல்லது உங்கள் கையைப் பயன்படுத்துவதையோ வேலை செய்வதையோ தடுத்தால், உங்கள் குடும்ப மருத்துவரைப் (GP) பாருங்கள், அல்லது நிபுணரின் பரிசோதனையைக் கேளுங்கள்.
உண்மையில் என்ன நடக்கிறது
உங்கள் தோள்பட்டையில், உங்கள் காறை எலும்பின் வெளிமுனை தோள்பட்டை எலும்பின் நுனியைச் சந்திக்கும் ஒரு சிறிய மூட்டு உள்ளது. இதுவே AC மூட்டு; இது அக்ரோமியோகிளாவிகுலர் மூட்டு (acromioclavicular joint) என்பதன் சுருக்கம். இது அசையக்கூடிய ஒரு மூட்டு; இறுக்கமாகப் பற்றவைக்கப்பட்ட இணைப்பு அல்ல. சாதாரணமாகக் கையைப் பயன்படுத்தும்போது உங்கள் தோள்பட்டை எலும்பு சுழன்று சறுக்குகையில், இந்த மூட்டு சில மில்லிமீட்டர்கள் நகர்கிறது; உங்கள் தோள்பட்டை எலும்பும் காறை எலும்பும் இணைக்கப்பட்ட ஒரே பகுதியாகச் செயல்பட அது உதவுகிறது. வலுவான தசைநார்கள் (ligaments) அதை ஒன்றாகப் பிடித்து வைக்கின்றன; உங்கள் தோள்பட்டையின் மேற்பகுதியை மூடியுள்ள தசைகளும் அவற்றுக்கு உதவுகின்றன.
மூட்டுக்குள், இரண்டு எலும்புத் துண்டுகளுக்கு இடையே உள்ள ஒரு கேஸ்கெட் (gasket) போல, மெத்தையாகச் செயல்படும் ஒரு மெல்லிய வட்டு (disc) அமர்ந்திருக்கிறது. நடுத்தர வயதின் தொடக்கத்திலிருந்து இந்த வட்டு தேயத் தொடங்குகிறது; அதன் பின்னால் உள்ள மூட்டுப் பரப்புகளும் அதனுடன் சேர்ந்து தேய்கின்றன. அதுவே தேய்மான மூட்டழற்சி (wear-and-tear arthritis); இந்த மூட்டில் அது மிகவும் பொதுவானது. தேய்மானம் பொதுவாக உங்கள் இருபதுகளிலும் முப்பதுகளிலும் அமைதியாகத் தொடங்கி, ஆண்டுகள் செல்லச் செல்ல மெதுவாக முன்னேறுகிறது. கனமான பொருட்களையோ மீண்டும் மீண்டும் பொருட்களையோ தூக்குவது, குறிப்பாகத் தலைக்கு மேல் செய்யும் வேலை, அதைத் துரிதப்படுத்துகிறது. கீழே விழுந்ததால் முன்பு ஏற்பட்ட மூட்டுச் சுளுக்கோ மூட்டு விலகலோ (separation) — குணமடைந்துவிட்டதாகத் தோன்றிய லேசான ஒன்றாக இருந்தாலும்கூட — அதைத் துரிதப்படுத்தலாம்.
ஆனால் சிக்கல் என்னவென்றால், தேய்ந்ததாகத் தெரியும் மூட்டு எப்போதும் வலிப்பதில்லை. பலருக்கு ஸ்கேன்களில் தேய்மானம் தெரிந்தும் எந்த அறிகுறியும் இருப்பதில்லை; தேய்ந்ததாகத் தெரியும் மூட்டுகளில் பெரும்பாலானவை அமைதியாகவே இருக்கின்றன. எனவே, தேய்மானமோ, தேய்ந்து வெளிப்பட்ட பரப்புகளோ, அதைச் சுற்றியுள்ள அழற்சியோ அங்குள்ள திசுக்களை உண்மையில் எரிச்சலூட்டும்போது மட்டுமே, நீங்கள் உணரும் வலி அந்த மூட்டிலிருந்தே வருகிறது. அதனால்தான் உங்கள் அறிகுறிகள் தோள்பட்டையின் உச்சியிலேயே இருக்கின்றன; அதன் மீது சுமை ஏற்றிய பிறகு அதிகரிக்கின்றன.
இந்தப் பிரச்சினையின், அவ்வளவு பொதுவாக இல்லாத ஒரு வடிவம், காறை எலும்பின் வெளிமுனை எலும்பு இழப்பு (distal clavicle osteolysis) என்று அழைக்கப்படுகிறது. இதில், அழற்சி, எலும்பில் சிறிய முறிவுகள், எலும்பு இழப்பு ஆகியவற்றுடன், காறை எலும்பின் வெளிமுனையே சிதைகிறது. கனமான பொருட்களையோ மீண்டும் மீண்டும் பொருட்களையோ தூக்கும் இளைய ஆண்களிடையே இது பெரும்பாலும் காணப்படுகிறது; இது மூட்டில் அதே வகையான மூட்டழற்சிக்கு வழிவகுக்கிறது.
தேய்மானம் கடுமையானால், மூட்டுக்கு அருகில் எலும்பு முள்கள் (bone spurs) வளர்ந்து, உங்கள் தோள்பட்டையின் கூரைக்கு அடியில் செல்லும் தசைநாணின் மீது அழுத்தி, பிரச்சினையை மேலும் அதிகரிக்கலாம்.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் பணியாற்றும் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் நிலைக்குப் பொருத்தமான, உடலில் மிகக் குறைவாகத் தலையிடும் தேர்வுகளிலிருந்தே தொடங்குகிறார். நோயாளிகள் பொதுவாகத் தங்கள் குடும்ப மருத்துவரால் (GP) எங்கள் கிளினிக்குக்குப் பரிந்துரைக்கப்படுகிறார்கள்; ஒரு இயன்முறை சிகிச்சையாளர் எங்களைப் பார்க்கச் சொல்லியிருந்தாலும், Medicare திரும்பச் செலுத்தலுக்குத் தகுதி பெற உங்கள் குடும்ப மருத்துவரிடமிருந்து பரிந்துரைக் கடிதம் இன்னும் தேவைப்படும். கவனமாகக் கேட்டறியும் நோய் வரலாறு, உடல் பரிசோதனை, தேவைப்படும் இடத்தில் ஸ்கேன்கள் ஆகியவற்றின் மூலம் என்ன நடக்கிறது என்பதை நாங்கள் உறுதிப்படுத்துகிறோம். இது போன்ற நீண்ட காலப் பிரச்சினைக்கு, நாங்கள் பொதுவாக முதலில் அறுவை சிகிச்சை அல்லாத கவனிப்பையே முயற்சிக்கிறோம்; அது போதிய முன்னேற்றத்தைத் தராதபோது மட்டுமே அறுவை சிகிச்சையைப் பரிசீலிக்கிறோம்.
முதல் படிகள் நீங்களே எடுக்கக்கூடியவை. மூட்டுக்கு ஓய்வளிப்பது என்றால், உங்கள் தோள்பட்டையின் உச்சியில் சுமையை ஏற்றும் கனமான பொருட்களைத் தூக்குவதையும் தலைக்கு மேல் செய்யும் வேலையையும் குறைத்துக்கொள்வது. பரபரப்பான ஒரு நாளுக்குப் பிறகு வலி அதிகரிக்கும்போது, பனிக்கட்டி (ice) அதைத் தணிக்கலாம். இயன்முறை சிகிச்சை (physiotherapy), எரிச்சலடைந்த மூட்டைத் தணிப்பதையும், அன்றாட வேலைகள் அதன் மீது குறைவான அழுத்தத்தைச் செலுத்தும் வகையில் உங்கள் தோள்பட்டையைச் சுற்றியுள்ள வலிமையை வளர்ப்பதையும் நோக்கமாகக் கொண்டுள்ளது. வலி பெரும்பாலும் செயல்பாட்டின்போது அல்லாமல் அதற்குப் பிறகே அதிகரிப்பதால், இந்த மாற்றங்களை மதிப்பிடுவதற்கு முன் அவற்றுக்கு நியாயமான அவகாசம் கொடுங்கள்.
சுயகவனிப்பு போதவில்லை என்றால், வலி நிவாரணிகளும் அழற்சி எதிர்ப்பு மருந்துகளும் உதவலாம். அழற்சி எதிர்ப்பு மருந்துகள் என்பவை, வலியைக் குறைப்பதோடு மூட்டில் உள்ள அழற்சியையும் தணிக்கும் மாத்திரைகள். வலுவான அழற்சி எதிர்ப்பு மருந்தான கார்டிசோன் (cortisone) ஊசியையும் நாங்கள் மூட்டுக்குள்ளேயே போடுகிறோம். ஓர் ஊசி இரண்டு நோக்கங்களுக்குப் பயன்படலாம்: உங்கள் வலியின் மூலம் இந்த மூட்டுதான் என்பதை உறுதிப்படுத்த அது உதவுகிறது; சிகிச்சையாக வலியையும் தணிக்கலாம். ஊசி போட்டுக்கொள்ளும் 100 பேரில் சுமார் 47 பேருக்கு, ஓர் ஆண்டு கழித்தும் நல்ல பலன் நீடிக்கிறது.
இந்தச் சிகிச்சைகள் இருந்தும் வலி தொடரும்போது, அறுவை சிகிச்சை பரிசீலனைக்கு வருகிறது. இந்த அறுவை சிகிச்சை, உங்கள் காறை எலும்பின் வெளிமுனையிலிருந்து சில மில்லிமீட்டர் எலும்பை அகற்றுகிறது; அதாவது, தேய்ந்த மூட்டின் காறை எலும்புப் பக்கத்தில் உள்ள பாதியை. தேய்ந்த அந்தப் பரப்பு அகற்றப்பட்டவுடன், தேய்ந்து வெளிப்பட்ட இரு எலும்பு முனைகளும் இனி ஒன்றோடொன்று உரசுவதில்லை. இதை ஒரு கேமராவைப் பயன்படுத்திச் சிறிய வெட்டுகள் வழியாகவோ, ஒரு சிறிய திறந்த வெட்டின் வழியாகவோ செய்யலாம். இந்த மூட்டில் முன்பு விலகல் ஏற்பட்டு, அதனால் நீடித்த நிலையின்மை (instability) இருந்தால், அதைப் பற்றி உங்களுடன் கவனமாகப் பேசுவோம்; ஏனெனில் இந்த அறுவை சிகிச்சை எவ்வளவு நன்றாகப் பலனளிக்கும் என்பதை அது மாற்றுகிறது. உங்கள் தோள்பட்டை எதைச் செய்ய வேண்டும் என்று நீங்கள் விரும்புகிறீர்கள் என்பதையும், அறுவை சிகிச்சையில் என்ன அடங்கியுள்ளது என்பதையும் எடைபோட்டு, அறுவை சிகிச்சை உங்களுக்குச் சரியானதா என்பதை நாம் இணைந்தே முடிவு செய்கிறோம்.
என்ன எதிர்பார்க்கலாம்
பெரும்பாலானோருக்கு, ஸ்கேனில் தெரிந்தாலும் வலியை ஏற்படுத்தாத இந்த மூட்டின் தேய்மானம், வெறுமனே அமைதியாகவே இருக்கிறது. ஏழு ஆண்டுக் காலத்தில், தொடக்கத்தில் வலியின்றி இருந்த இது போன்ற மூட்டுகளில் 90% ஒருபோதும் அறிகுறிகளை உருவாக்கவில்லை. எனவே உங்கள் மூட்டு தேய்ந்ததாகத் தெரிந்தும் வலிக்கவில்லை என்றால், அது தொடர்ந்து அமைதியாகவே இருப்பதற்கு நல்ல வாய்ப்பு உள்ளது.
மூட்டு வலிக்கும்போது, அதன் போக்கு ஆளுக்கு ஆள் மாறுபடுகிறது. சிலருக்கு ஓய்வு, கனமான பொருட்களைத் தூக்குவதைக் குறைத்தல், இயன்முறை சிகிச்சை ஆகியவற்றால் வலி தணிகிறது. வேறு சிலருக்கு அது வந்து வந்து போகிறது; பரபரப்பான ஒரு நாளுக்குப் பிறகு அதிகரித்து, நீங்கள் மீண்டும் ஓய்வெடுக்கும்போது தணிகிறது. சிகிச்சை இல்லாவிட்டால், மூட்டில் உள்ள தேய்மானம் தானாகத் திரும்பிச் சரியாவதில்லை என்பதால், உங்கள் தோள்பட்டையின் உச்சியில் சுமை ஏற்றும் ஒவ்வொரு முறையும் வலி தொடரும் அல்லது மீண்டும் வரும் போக்கு உள்ளது.
அறுவை சிகிச்சை அல்லாத கவனிப்பு போதிய நிவாரணம் தராவிட்டால், மூட்டுக்குள் போடப்படும் கார்டிசோன் ஊசி சிலருக்கு உதவுகிறது. ஊசி போட்டுக்கொள்ளும் 100 பேரில் சுமார் 47 பேருக்கு, ஓர் ஆண்டு கழித்தும் நல்ல பலன் நீடிக்கிறது. அதாவது, ஏறக்குறையப் பாதிப் பேருக்கு அந்த ஆண்டுக்குள்ளேயே நிவாரணம் குறைந்துவிடுகிறது; ஊசியை மீண்டும் போட வேண்டியிருக்கலாம், அல்லது வேறு நடவடிக்கைகளைப் பரிசீலிக்க வேண்டியிருக்கலாம்.
இந்தச் சிகிச்சைகள் இருந்தும் வலி தொடர்ந்தால், உங்கள் காறை எலும்பின் வெளிமுனையிலிருந்து சில மில்லிமீட்டர் எலும்பை அகற்றுவது, உங்கள் அறுவை சிகிச்சை நிபுணர் உங்களுடன் பேசக்கூடிய ஒரு தேர்வு. தேய்ந்து வெளிப்பட்ட இரு பரப்புகளும் ஒன்றோடொன்று உரசுவதைத் தடுப்பதே இதன் நோக்கம். அந்த அறுவை சிகிச்சையிலிருந்து மீள வாரங்கள் முதல் மாதங்கள் வரை ஆகும்; உங்கள் இயன்முறை சிகிச்சையாளர் அதை வழிநடத்துவார்; மூட்டு அமைதியடையும்போது தோள்பட்டை உச்சியில் உள்ள வலி தணிவதைப் பெரும்பாலானோர் காண்கிறார்கள்.
வரும் மாதங்களில் நீங்கள் யதார்த்தமாக எதை எதிர்பார்க்கலாம் என்பது, நீங்கள் எந்த வழியைத் தேர்ந்தெடுக்கிறீர்கள் என்பதைப் பொறுத்தது. அறிவார்ந்த சுயகவனிப்பாலும் இயன்முறை சிகிச்சையாலும், பலர் தங்கள் வழக்கமான செயல்பாடுகளுக்குத் திரும்புகிறார்கள்; வலியும் அவர்கள் சமாளித்து வாழக்கூடிய அளவுக்குத் தணிகிறது. இந்த நடவடிக்கைகளை நியாயமாக முயற்சித்த பிறகும் மூட்டில் வலி தொடர்ந்து அதிகரித்தால், வலியைப் பொறுத்துக்கொண்டு தொடர்வதற்குப் பதிலாக, உங்கள் குடும்ப மருத்துவரிடம் மீண்டும் செல்வது, அல்லது நிபுணரின் பரிசோதனையைக் கேட்பது நல்லது.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
இது ஒரு தேய்மானப் பிரச்சினை; அவசர நிலை அல்ல; எனவே இந்த நிலையில், அதே நாளில் கவனிக்க வேண்டிய அபாய அறிகுறிகள் எதுவும் இல்லை. வலி தணிகிறதா என்பதே முக்கியம். கனமான பொருட்களைத் தூக்குவதிலிருந்து சில வாரங்கள் ஓய்வெடுத்த பிறகும் உங்கள் தோள்பட்டை உச்சியில் உள்ள வலி மேம்படாவிட்டால், அல்லது அந்தப் பக்கம் படுக்கும்போது அது தொடர்ந்து உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், உங்கள் குடும்ப மருத்துவரைப் பாருங்கள். வலி வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், நீங்கள் வேலை செய்வதையோ உங்கள் கையை வழக்கம்போல் பயன்படுத்துவதையோ தடுத்தால், அல்லது சுமையைக் குறைத்த பிறகும் தூக்குவதும் உடலின் குறுக்கே கையை நீட்டுவதும் தொடர்ந்து வலித்தால், நிபுணரின் பரிசோதனையைக் கேளுங்கள். உங்கள் தோள்பட்டை சூடாகவும், சிவந்தும், வீங்கியும், வலியுடனும் இருந்தால் — குறிப்பாகக் காய்ச்சலும் இருந்தால் — அது மூட்டழற்சி அல்ல; அதே நாளிலேயே அவசர சிகிச்சைப் பிரிவுக்குச் (emergency department) சென்று சிகிச்சை பெறுங்கள்.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
இந்தப் பகுதி, உங்கள் சொந்த சிகிச்சை முடிவுகளுக்குத் தேவையானதைவிட ஆழமாகச் செல்கிறது. AC மூட்டின் மூட்டழற்சியைப் பற்றிக் கூடுதலாகப் படிப்பது பயனுள்ளது — ஆனால் அசௌகரியமான ஒரு காரணத்துக்காக: ஸ்கேன்களில் இது மிகவும் பொதுவாகக் காணப்படுகிறது, தோள்பட்டை வலிக்கு இதுவே காரணம் என்று அடிக்கடி சொல்லப்படுகிறது, மேலும் இதற்குச் சிகிச்சை அளிப்பது பலனளிக்கிறது என்பதற்கான சான்று, இந்தத் தளத்தில் உள்ள கிட்டத்தட்ட வேறு எதையும்விடப் பலவீனமானது.
எதுவும் பலனளிக்கிறது என்பதைச் சான்றுகள் நிறுவவில்லை
முதன்மை AC மூட்டுத் தேய்மான மூட்டழற்சியின் (osteoarthritis) சிகிச்சை குறித்த ஒரு முறையான ஆய்வு (systematic review), 1,902 நோயாளிகளைத் தொகுத்து, அரிதாகவே இவ்வளவு வெளிப்படையாகச் சொல்லப்படும் ஒரு முடிவுக்கு வந்தது: அந்த ஆய்வுகள் சிகிச்சைக்கான அறிகுறி, தலையீடு மற்றும் தரம் ஆகியவற்றில் வேறுபட்டிருந்தன; மேலும் அறுவை சிகிச்சை அல்லாத தலையீடுகளோ அறுவை சிகிச்சைத் தலையீடுகளோ பயனுள்ளவை என்பதற்கான சான்றை அவை தரவில்லை [1].
எதுவும் பலனளிக்காது என்று சொல்வது இதற்குச் சமம் அல்ல. அதை நிரூபிக்கக்கூடிய சோதனைகள், அந்தக் கூற்றை அனுமதிக்கும் தரத்தில் செய்யப்படவில்லை என்பதே இதன் பொருள். காறை எலும்பின் வெளிமுனை அகற்றல் (distal clavicle excision) என்பது நீண்ட காலமாக நிலைபெற்ற ஒரு அறுவை சிகிச்சை; தேய்ந்த மூட்டுப் பரப்பை அகற்றினால் வலி நீங்கும் என்ற நியாயமான இயந்திரவியல் தர்க்கத்தின் அடிப்படையில் இது செய்யப்படுகிறது. ஆனால் "நீண்ட காலமாக நிலைபெற்றது, இயந்திரவியல்படி பொருத்தமானது" என்பது சான்று அல்ல; ஒரு முடிவு எடுக்கப்படும்போது இந்த வேறுபாட்டைத் தெரிந்துகொள்வது முக்கியம்.
மற்றொரு அறுவை சிகிச்சையுடன் இதைச் சேர்ப்பது அந்த அறுவை சிகிச்சையை மேம்படுத்துவதில்லை
மிக நேரடியான சோதனை, அதே நேரத்தில் வேறு ஏதாவது அறுவை சிகிச்சை செய்துகொண்ட நோயாளிகளிடமிருந்து வருகிறது. சுழற்சி தசைநாண் பட்டை (rotator cuff) கிழிவுகள் உள்ள 208 நோயாளிகளில், காறை எலும்பின் வெளிமுனை அகற்றலைச் சேர்த்ததால் சிறந்த மருத்துவ விளைவு மதிப்பெண்களோ சிறந்த அசைவு வரம்போ கிடைக்கவில்லை [2].
இது முக்கியம்; ஏனெனில் மூட்டு அகற்றப்படுவது பெரும்பாலும் சரியாக இந்தச் சூழ்நிலையில்தான்: அறுவை சிகிச்சை நிபுணர் ஏற்கெனவே தோள்பட்டைக்குள் இருக்கிறார், ஸ்கேனில் AC மூட்டு தேய்ந்ததுபோலத் தெரிகிறது, மேலும் சில மில்லிமீட்டர் எலும்பை அகற்றுவது விரைவானது. நோயாளிக்கு அளவிடத்தக்க பலன் எதுவும் இல்லை என்று சான்றுகள் சொல்கின்றன. உங்கள் தசைநாண் பட்டை பழுதுபார்ப்புடன் இதைக் கூடுதலாகச் சேர்க்கப் பரிந்துரைக்கப்பட்டால், அதைப் பற்றிக் கேட்பது நியாயமானது.
நுட்பம் என்பது சுவாரஸ்யமான கேள்வி அல்ல
திறந்த முறை அகற்றலும் ஆர்த்ரோஸ்கோபிக் (arthroscopic) முறை அகற்றலும் திரும்பத் திரும்ப ஒப்பிடப்பட்டுள்ளன; பதில் ஒரே மாதிரியாகவே உள்ளது: 319 நோயாளிகளில், இரு அணுகுமுறைகளிலும் ஒத்த செயல்பாட்டு மற்றும் மருத்துவ விளைவுகளே இருந்தன [3]; 429 நோயாளிகளைப் பற்றிய முந்தைய ஒப்பீடும் எந்த ஒன்றையும் உறுதியாக ஆதரிக்கவில்லை [4].
மிகவும் வேறுபட்ட இரண்டு நுட்ப அணுகுமுறைகள் ஒரே முடிவைத் தரும்போது, நேர்மையான ஊகம் இதுதான்: விளைவை நிர்ணயிப்பது நுட்பம் அல்ல, நோயாளியைத் தேர்ந்தெடுப்பதே.
இங்கே தேர்வு ஏன் இவ்வளவு கடினமானது
வயதாக ஆக, கிட்டத்தட்ட எல்லோருக்கும் AC மூட்டு தேய்கிறது. இது ஒரு சிறிய, அதிக சுமை ஏற்கும் மூட்டு; அதில் உள்ள மெல்லிய தட்டு சீக்கிரமே தேய்ந்துவிடுகிறது. எனவே, உங்கள் ஸ்கேனில் AC மூட்டுத் தேய்மானம் இருப்பதாகக் குறிப்பிடும் அறிக்கை, நடுத்தர வயதுக்குப் பிறகு ஒரு நோயறிதல் என்பதைவிட எதிர்பார்க்கப்படும் கண்டுபிடிப்புக்கே நெருக்கமானது.
அளவிடத்தக்க ஓர் அமைப்புரீதியான தொடர்பு உள்ளது: அறிகுறிகளுடன் கூடிய தேய்மான AC மூட்டுகளில், காறை எலும்பின் வெளிமுனையும் அக்ரோமியனும் இரண்டுமே விரிவடைந்திருக்கின்றன; ஆனால் அறிகுறிகள் இல்லாதவர்களில் இவ்விரண்டுக்கும் இடையிலான உறவு மாறாமலேயே உள்ளது [5]. அறிகுறிகளுடன் கூடிய தேய்மானமும் தற்செயலாகக் கண்டறியப்படும் தேய்மானமும் அமைப்பில் வேறுபடுகின்றன என்பதற்கு இது பயனுள்ள ஒரு குறிப்பு; ஆனால் இது குழு அளவிலான ஒரு கவனிப்பே தவிர, உங்கள் தோள்பட்டைக்குப் பயன்படுத்தக்கூடிய ஒரு பரிசோதனை அல்ல.
நடைமுறையில், இதனால்தான் மூட்டுக்குள் செலுத்தப்படும் நோயறிதல் ஊசிக்கு இங்கே உண்மையான முக்கியத்துவம் உள்ளது. AC மூட்டுக்குள் துல்லியமாகச் செலுத்தப்பட்ட உள்ளூர் மயக்க மருந்து (local anaesthetic) வலியை முற்றிலும் நீக்கினால், அந்த மூட்டுதான் வலியின் மூலமாக இருக்கக்கூடும். அது நீக்கவில்லை என்றால், ஸ்கேனில் தெரியும் தேய்மானம் வெறும் பார்வையாளராகவே இருக்கக்கூடும்; அதை அகற்றுவது உதவ வாய்ப்பில்லை. மேலே உள்ள சான்றுகள் எச்சரிக்கும் சூழ்நிலை இதுவே.
மேற்கோள்கள்
[1] Welch M, Rankin S, How Saw Keng M, Woods D. A systematic review of the treatment of primary acromioclavicular joint osteoarthritis. Shoulder Elbow. 2023;16(2):129-44. https://doi.org/10.1177/17585732231157090
[2] Wang J, Ma J, Zhu S, Jia H, Ma X. Does distal clavicle resection decrease pain or improve shoulder function in patients with rotator cuff tears? A meta-analysis. Clin Orthop Relat Res. 2018;476(12):2402-14. https://doi.org/10.1097/CORR.0000000000000424
[3] Hohmann E, Tetsworth K, Glatt V. Open versus arthroscopic acromioclavicular joint resection: a systematic review and meta-analysis. Arch Orthop Trauma Surg. 2019;139(5):685-94. https://doi.org/10.1007/s00402-019-03114-w
[4] Pensak M, Grumet RC, Slabaugh MA, Bach BR. Open versus arthroscopic distal clavicle resection. Arthroscopy. 2010;26(5):697-704. https://doi.org/10.1016/j.arthro.2009.12.007
[5] Bulkmans K, Peeters I, De Wilde L, Van Tongel A. The relationship of the acromion to the distal clavicle in normal and symptomatic degenerative acromioclavicular joints. Arch Orthop Trauma Surg. 2019;140(4):465-72. https://doi.org/10.1007/s00402-019-03258-9
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Asymptomatic acromioclavicular osteoarthritis remained asymptomatic in 90% of cases over a seven-year course [1].
- Treatment choice for acromioclavicular dislocation should not be influenced by the potential development of acromioclavicular osteoarthritis [2].
- Further characterisation is needed to identify patients in whom mild arthroscopic findings of acromioclavicular joint osteoarthritis are clinically significant and warrant resection [3].
- Persistent pain and osteoarthritis progression remain concerns following revision of failed open anterior stabilization of the shoulder [4].
- Both open and arthroscopic resection arthroplasty techniques provide predictable pain relief for symptomatic acromioclavicular osteoarthritis [5].
- Symptomatic acromioclavicular joint osteoarthritis occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years [6].
- Untreated acromioclavicular joint osteoarthritis, symptomatic or not, encountered during arthroscopic rotator cuff repair is associated with a low percentage of failure [8].
- Biplanar reconstruction with pectoralis minor tendon and coracoacromial ligament transfer aims to preserve the lateral portion of the clavicle whenever possible, limiting resection exclusively to cases of acromioclavicular joint osteoarthritis or irreducible joints [9].
- Radiographic acromioclavicular joint osteoarthritis is common in patients undergoing reverse shoulder arthroplasty [10].
- Clinicians should consider overreduction of the acromioclavicular joint because it may lead to favorable radiological results [11].
- A distinction between symptomatic and asymptomatic radiographic acromioclavicular osteoarthritis is unnecessary, as all patients were equally satisfied with the outcome following preoperative acromioclavicular injection [12].
- Open and arthroscopic acromioclavicular joint reconstruction techniques have no differences in loss of reduction, the complication rate, and the revision rate [13].
- Arthroscopic debridement of the acromioclavicular joint can produce a favorable result in young patients presenting with isolated acromioclavicular joint-related pain but with normal imaging [15].
- Limited distal clavicle excision of patients with acromioclavicular joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [17].
- All patients undergoing free tissue graft reconstruction of the acromioclavicular joint are satisfied with their surgery and demonstrate good reduction of the acromioclavicular joint on radiographs, although follow-up periods are less than 1 year [21].
- Additional research is needed to determine the main cause of pain and compare clinical outcomes of intra-articular versus extra-articular injections for isolated acromioclavicular osteoarthritis [23].
- Nanoscopic distal clavicle resection offers advantages including decreased morbidity, less risk to the acromioclavicular joint ligaments, and decreased loss and need for fluid [44].
Anatomy & Pathophysiology
Bony Anatomy and Joint Structure
- The acromioclavicular (AC) joint is a diarthrodial joint that supports the shoulder girdle through the clavicular “strut” [36].
- The AC joint serves as a primary link between the axial skeleton and the upper extremity [122].
- The AC joint is movable in all planes and is not a rigid structure [122].
- The normal AC joint is capable of translating 4 to 6 mm in the anterior, posterior, and superior planes under 70-N loads [122].
- The AC joint accommodates rotary motion of 5° to 8° during scapulothoracic motion and 40° to 45° with shoulder abduction and elevation [122].
- The scapula and clavicle are linked into a single segment referred to as the “claviscapula” [112].
Ligamentous Anatomy and Stability
- The AC and coracoclavicular (CC) ligaments are the static stabilizers of the AC joint, whereas the deltoid and trapezius muscles are the dynamic stabilizers [122].
- The horizontal plane stability of the clavicle is provided by the AC ligaments, specifically the posterior and superior portions [25].
- The AC and CC ligaments play a role in torque transduction and horizontal and vertical stability [112].
- Injury to the AC joint results in progressive disruption of the ligamentous support, beginning with the capsular ligaments and progressing to the CC ligaments [30].
Pathophysiology of Degeneration
- AC joint osteoarthritis is more common with advanced age following degeneration of the intra-articular disk [25].
- Arthritic deterioration of the AC joint starts in early middle age [25].
- AC joint osteoarthritis is more common in patients engaged in repetitive overhead or lifting activities [25].
- Previous low-grade AC joint separations can result in painful arthritis [25].
- The radiographic severity of AC joint arthritis does not always correlate with patient symptoms [25].
- Asymptomatic AC joint degeneration is frequent and does not always correlate with the presence of symptoms [36].
- Degeneration of the AC joint is classified as primary osteoarthritis, posttraumatic osteoarthritis, or distal clavicle osteolysis [123].
- The process of AC joint degeneration begins in the second decade of life and can progress to complete obliteration of the joint [123].
- Complete obliteration of the AC joint can lead to subclavicular spurring, which contributes to subacromial impingement of the supraspinatus [123].
- Asymptomatic AC osteoarthritis remained asymptomatic in 90% of cases over a seven-year course [1].
- Patients with loss of immediate postoperative reduction after AC joint dislocation more often developed radiologic and symptomatic AC osteoarthritis than those in whom the AC joint was anatomically restored [7].
- Kinematic changes associated with AC joint dislocation could be a potential source of pain and dysfunction in the shoulder [59].
- Scapular and clavicular kinematics are affected in AC separation models [60].
- Decoupling the claviscapular segment has deleterious effects on the functional integrity of the AC joint complex within scapulohumeral rhythm [112].
Distal Clavicle Osteolysis
- Distal clavicle osteolysis is characterized by localized hyperemia of the distal clavicle, resulting in inflammation, bone resorption, microfractures, and secondary arthritis of the AC joint [25].
- Distal clavicle osteolysis is more common in males and seen in younger patients [25].
- Distal clavicle osteolysis is associated with heavy lifting or repetitive motions [25].
- Osteolysis of the distal clavicle was first reported in conjunction with acute trauma [121].
- Intraarticular distal clavicle fractures and AC separations can lead to osteolysis [121].
- Other causes of distal clavicle osteolysis include rheumatoid arthritis, hyperparathyroidism, and repetitive microtrauma [121].
- The most common cause of distal clavicle osteolysis is repetitive microtrauma [121].
- Radiographic findings indicative of distal clavicle osteolysis include loss of subchondral bone detail, cystic reabsorption of the distal clavicle, and generalized osteopenia of the distal clavicle [121].
Classification
- Asymptomatic acromioclavicular osteoarthritis diagnosed by MRI remained asymptomatic in 90% of cases over a seven-year course [1].
- Treatment choice for acromioclavicular dislocation should not be influenced by the potential development of acromioclavicular osteoarthritis based on available evidence [2].
- Patients with loss of immediate postoperative reduction following arthroscopically assisted reduction of acute acromioclavicular joint dislocation more often developed radiologic and symptomatic acromioclavicular osteoarthritis than those in whom the joint was anatomically restored [7].
- Untreated acromioclavicular joint osteoarthritis, whether symptomatic or not, encountered during arthroscopic rotator cuff repair is associated with a low percentage of failure [8].
- Biplanar reconstruction with pectoralis minor tendon and coracoacromial ligament transfer aims to preserve the lateral portion of the clavicle, limiting resection exclusively to cases of acromioclavicular joint osteoarthritis or irreducible joints [9].
- Open and arthroscopic acromioclavicular joint reconstruction techniques have no differences in loss of reduction, complication rate, and revision rate based on available literature [13].
- A study evaluated three groups of patients: 84 acromioclavicular joints without clinical or radiological pathology, 39 patients with signs of osteoarthritis on CT without symptoms, and 30 patients with acromioclavicular joint pain [14].
- In the study of acromion-clavicle relationships, Group 2 included patients with signs of osteoarthritis on CT (joint space narrowing, osteophytes, and/or bone cyst) who were asymptomatic based on physical examination and negative cross-body adduction test [14].
- In the study of acromion-clavicle relationships, Group 3 included patients with acromioclavicular joint pain confirmed by tenderness and temporary pain relief with intra-articular injection, who were treated with open distal clavicle resection after failure of non-operative treatment [14].
- The occurrence of acromioclavicular joint osteoarthrosis was surprisingly frequent in a study of shoulder pain [18].
- Anatomic techniques that address both coracoclavicular ligaments and the acromioclavicular capsule are recommended to restore horizontal and vertical stability while allowing physiological rotation [19].
- The acromial center line to dorsal clavicle radiographic measurement and use of the Alexander view provides a more realistic appreciation of true acromioclavicular joint displacement, especially in defining watershed cases (IIIA/IIB/IV) [22].
- Osteolytic changes seemed to be associated with incongruity of the acromioclavicular joint but did not correlate with clinical results in a review of surgical treatment for acromioclavicular dislocation [24].
- A procedure for exact anatomical acromioclavicular joint reconstruction using acromioclavicular and coracoclavicular FiberWire cerclage shows good objective results with high Constant and Rowe scores for shoulder function [27].
- Preoperative radiographs were evaluated to determine whether there was any osteolysis of the distal clavicle in a study of preoperative factors associated with subsequent distal clavicle resection after rotator cuff repair [31].
- Preoperative radiographs were graded for severity of arthritis per the Petersson classification by two attending orthopaedic surgeons blinded to each other's grade in a study of preoperative factors associated with subsequent distal clavicle resection after rotator cuff repair [31].
- Type V acromioclavicular dislocations may be given a trial of conservative therapy [35].
- Non-operative reduction and stabilization of high-grade acromioclavicular joint separations seems to be a valuable treatment option [45].
- Evaluating the integrity of the capsuloligamentous structures stabilizing the acromioclavicular joint is reproducible and gives additional information on the severity of the injury, which might also influence the treatment decision [49].
- Severe chronic symptomatic acromioclavicular joint separations (Rockwood types III through V) can be repaired entirely by arthroscopy safely and effectively by transferring the coracoacromial ligament with a bone block in the distal clavicle [50].
- The treatment of Type III acromioclavicular joint separation has remained controversial, with many studies demonstrating good results with nonoperative management and most series failing to document the superiority of either operative or nonoperative management [51].
- Surgical management of acromioclavicular joint injuries is associated with a relatively high complication profile and common loss of reduction, though the revision surgery rate is low [53].
- Arthroscopically assisted treatment of acute acromioclavicular joint dislocation provides good clinical results and few complications, though the rate of recurrence and postoperative loss of reduction requires better definition of indications and improvement of surgical implants and technique [55].
- In every coracoclavicular loop repair, regardless of hole placement, complete acromioclavicular joint congruity is not restored [86].
- Given that more than 100 surgical stabilization techniques have been proposed for acromioclavicular joint injuries, a deeper understanding of the underlying anatomy integrated with biomechanical evidence may help guide the development of a standardized, evidence-based approach to treatment [88].
- Early and delayed surgical interventions of high-grade acromioclavicular joint dislocation provide equivalent clinical scores when combined coracoclavicular and acromioclavicular joint fixation is used for stabilization [95].
- Acromioclavicular joint osteoarthritis was graded using the Kellgren-Lawrence classification system in a retrospective cohort study of concomitant open distal clavicle excision after reverse total shoulder arthroplasty [101].
Clinical Presentation
History and Symptoms
- Patients report activity-related pain localized to the AC joint [25].
- Pain may radiate anteriorly or along the trapezius [25].
- Pain is reported with heavy lifting or when sleeping on the affected side [25].
- AC joint osteoarthrosis is a frequent cause of shoulder pain [18].
- In patients with rheumatoid arthritis, clinical symptoms and radiologic appearances are often poor indicators of the source of pain in the shoulder joint complex [64].
Physical Examination
- Point tenderness is seen at the AC joint [25].
- Horizontal stability of the AC joint should be assessed [25].
- Pain at the AC joint with terminal elevation and cross-body motion is often seen [25].
- The adduction sign, where pain is produced in the AC joint during maximal adduction of the internally rotated arm, was positive in all 20 patients with AC joint arthritis in one study [63].
- An average decrease of 5 cm in the distance from the ipsilateral antecubital fossa to the contralateral anterior shoulder was noted during cross-body adduction in patients with AC joint arthritis [63].
- Selective injection of anesthetic into the AC joint can confirm the diagnosis [25].
- Patients with ACJ pain showed clinical signs including AC joint tenderness to palpation and temporary pain relief with intra-articular injection [14].
Imaging
- An AP view and/or a Zanca view of the shoulder provides good visualization of the AC joint [25].
- Osteophyte formation, sclerotic reaction, and bone cysts are commonly seen on radiographs of the AC joint [25].
- Bone and joint edema on MRI correlate with AC joint pain [25].
- The radiographic severity of arthritis does not always correlate with patient symptoms [25].
- Radiographic ACJ osteoarthritis is common in patients undergoing reverse shoulder arthroplasty [10].
- Asymptomatic AC-OA remained asymptomatic in 90% of patients over a seven-year course [1].
- A distinction between symptomatic and asymptomatic radiographic AC OA may be unnecessary, as all patients were equally satisfied with the outcome in one study [12].
- Osteolytic changes seemed to be associated with incongruity of the AC joint but did not correlate with clinical results [24].
Investigations
Clinical Evaluation
- Patients with AC joint osteoarthritis report activity-related pain localized to the AC joint, with occasional radiation anteriorly or along the trapezius [25].
- Pain with heavy lifting or when sleeping on the affected side is reported in patients with AC joint osteoarthritis [25].
- Physical examination of the AC joint reveals point tenderness at the joint [25].
- Horizontal stability of the AC joint should be assessed during physical examination [25].
- Pain at the AC joint with terminal elevation and cross-body motion is often seen in patients with AC joint osteoarthritis [25].
- Selective injection of anesthetic into the AC joint can confirm the diagnosis of symptomatic AC osteoarthritis [25].
- A distinction between symptomatic and asymptomatic radiographic AC OA is unnecessary, as all patients were equally satisfied with the outcome following preoperative injection [12].
Imaging
- Patients with edema on MRI were more likely to present pain than patients without edema [92].
- Subchondral bone edema on histologic examination was more frequent in patients with pain [92].
- The AC-DC measurement and use of the Alexander view provides a more realistic appreciation of true AC joint displacement, especially in defining watershed cases (ie, IIIA/IIB/IV) [22].
- Preoperative radiographs are evaluated to determine whether there is any osteolysis of the distal clavicle [31].
- The Petersson classification is used to grade the severity of arthritis on preoperative radiographs [31].
- In a study of AC joint osteoarthrosis, the occurrence was surprisingly frequent [18].
Treatment
Non-Operative Management
- Rest, ice, and NSAIDs are used initially for AC joint osteoarthritis [25].
- Corticosteroid injections can be used for diagnostic or therapeutic purposes in AC joint osteoarthritis [25].
- AC injections offer a 1-year success rate of 47% [33].
- Conservative and surgical treatments are both effective in acromioclavicular joint osteoarthritis management [38].
- A distinction between symptomatic and asymptomatic radiographic AC OA is unnecessary, as all patients were equally satisfied with the outcome following injection [12].
- Additional research is needed to determine the main cause of pain and compare clinical outcomes of intra-articular versus extra-articular injections [23].
Operative Management: Distal Clavicle Resection
- Surgical indications for AC joint osteoarthritis include persistent pain and failure of nonsurgical treatment [25].
- Both open and arthroscopic resection arthroplasty techniques provide predictable pain relief for symptomatic AC osteoarthritis [5].
- Arthroscopic distal clavicle excision provides reliable pain relief in >90% of patients in the absence of instability [25].
- Previous traumatic instability is associated with persistent pain in 30% to 40% of cases following distal clavicle excision [25].
- One systematic review showed slightly better results with arthroscopic excision than with open distal clavicle excision [25].
- Direct comparison studies have shown similar or better results with arthroscopic excision than with open techniques [25].
- Biomechanical evidence suggests a resection of 5 mm is needed to prevent contact between the clavicle and the acromion in the absence of instability [25].
- Care should be taken to preserve the posterior and superior AC ligaments during arthroscopic distal clavicle excision [25].
- Between 5 and 10 mm of the distal clavicle should be resected during an open Mumford procedure [25].
- Meticulous repair of the deltotrapezial fascia is important during open distal clavicle resection [25].
- Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [17].
- Arthroscopic debridement of the AC joint can produce a favorable result in young patients presenting with isolated AC joint-related pain but with normal imaging [15].
- The nanoscopic distal clavicle resection technique offers advantages including decreased morbidity, less risk to the AC joint ligaments, and decreased loss and need for fluid [44].
- Patients with AC joint instability have poor results after distal clavicle resection [36].
- The optimal amount of distal clavicle resection remains elusive [36].
Operative Management: Concomitant Procedures and Specific Populations
- Preventive arthroscopic distal clavicle resection is not recommended in patients with radiological but asymptomatic ACJ arthritis and rotator cuff tears [34].
- Untreated ACJ osteoarthritis, symptomatic or not, encountered during arthroscopic rotator cuff repair is associated with a low percentage of failure [8].
- Further characterisation of patients in whom mild arthroscopic findings of OA of AC joint are clinically significant and warrant resection is needed [3].
- Symptomatic ACJ OA occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years [6].
- Osteoarthritis is associated with poorer final clinical outcomes after rotator cuff repair, and an unhealed or re-torn cuff increases the risk of osteoarthritis [26].
Operative Management: Reconstruction and Stabilization
- Open and arthroscopic AC joint reconstruction techniques have no differences in loss of reduction, the complication rate, and the revision rate based on the available literature [13].
- Treatment choice for AC dislocation should not be influenced by the potential development of AC OA [2].
- Achieving and maintaining satisfactory joint reduction is a factor of good prognosis, both radiologically and functionally, in AC dislocation treatment [7].
- Patients with loss of immediate postoperative reduction more often developed radiologic and symptomatic AC osteoarthritis than those in whom the AC joint was anatomically restored [7].
- Clinicians should consider overreduction of the AC joint because it may lead to favorable radiological results [11].
- Ensuring good initial recovery of the coracoclavicular distance and precise placement of the AC joints was important in maintaining the proper AC position at the final follow-up [46].
- Combined stabilization of the AC capsule and CC ligaments demonstrated the greatest capacity to restore native stability against translational and rotational loads [81].
- The biplanar reconstruction procedure aims to preserve the lateral portion of the clavicle whenever possible, limiting resection exclusively to cases of AC joint osteoarthritis or irreducible joints [9].
- Some persistent pain and osteoarthritis progression remain concerns following revision of failed open anterior stabilization of the shoulder [4].
Complications
Natural History and Progression
- Patients who experienced loss of immediate postoperative reduction after acute acromioclavicular dislocation more often developed radiologic and symptomatic acromioclavicular osteoarthritis than those in whom the joint was anatomically restored [7].
- Osteoarthritis is associated with poorer final clinical outcomes following rotator cuff repair [26].
- An unhealed or re-torn rotator cuff increases the risk of developing osteoarthritis [26].
- Severe acromioclavicular joint osteoarthritis is associated with acromial stress fractures after reverse shoulder arthroplasty [10].
Surgical Complications and Outcomes
- Treatment of acromioclavicular dislocation by synthetic ligament reconstruction carries a risk of significant early osteolysis [56].
- Complications such as anterior shoulder pain, acromioclavicular joint asymmetry, and activity-related weakness are common sequelae of coracoclavicular ligament reconstruction [43].
- Three patients with old acromioclavicular separations had prominence of the distal clavicle or symptoms due to residual hypermobility of the clavicle despite concurrent coracoclavicular stabilization [114, 115, 116, 117].
- A patient who did not undergo anterior acromioplasty despite subacromial impingement had unchanged impingement symptoms after distal clavicle resection [114, 115, 116, 117].
- Open and arthroscopic resection arthroplasty techniques for symptomatic acromioclavicular osteoarthritis each have a unique set of potential complications that may be minimized with improved understanding of anatomy, biomechanics, and meticulous surgical technique [5].
Recovery
Natural History and Prognosis
- Asymptomatic acromioclavicular osteoarthritis diagnosed by MRI remained asymptomatic in 90% of patients over a seven-year course [1].
- Osteolytic changes associated with incongruity of the acromioclavicular joint did not correlate with clinical results in a review of 39 patients [24].
- An unhealed or re-torn rotator cuff increases the risk of osteoarthritis following rotator cuff repair [26].
Impact of Joint Reduction and Stability
- Patients with loss of immediate postoperative reduction after arthroscopically assisted reduction of acute acromioclavicular joint dislocation more often developed radiologic and symptomatic acromioclavicular osteoarthritis than those in whom the joint was anatomically restored [7].
- Achieving and maintaining satisfactory joint reduction is a factor of good prognosis, both radiologically and functionally [7].
- Ensuring good initial recovery of the coracoclavicular distance and precise placement of the acromioclavicular joints was important in maintaining the proper acromioclavicular position at final follow-up [46].
Surgical Considerations Regarding Osteoarthritis
- Further characterisation of patients in whom mild arthroscopic findings of acromioclavicular joint osteoarthritis are clinically significant and warrant resection is needed [3].
- Biplanar reconstruction for chronic acromioclavicular joint dislocations aims to preserve the lateral portion of the clavicle, limiting resection exclusively to cases of acromioclavicular joint osteoarthritis or irreducible joints [9].
- The average angle from the central portion of the acromioclavicular joint anteriorly for a novel anterior portal for arthroscopic distal clavicle excision was 6 degrees, with a range of 0 to 15 degrees [29].
Non-Operative Management and Diagnostic Implications
- Acromioclavicular injections offer a 1-year success rate of 47% in patients with acromioclavicular osteoarthritis [33].
Key Evidence
- [L2] Asymptomatic AC-OA remained asymptomatic in 90% over 7 years. [1] (10.1016/j.jse.2019.04.004)
- [L4] Based on the available evidence, treatment choice for AC dislocation should not be influenced by the potential development of AC OA. [2] (10.2106/jbjs.rvw.24.00085)
- [L2] Further characterisation of patients in whom mild arthroscopic findings of OA of AC joint are clinically significant and warrant resection is needed. [3] (10.1007/s00167-014-3114-2)
- [L4] Some persistent pain and osteoarthritis progression remain concerns. [4] (10.1016/j.arthro.2009.04.073)
- [L5] Both open and arthroscopic resection arthroplasty techniques provide predictable pain relief for symptomatic AC osteoarthritis, though each has a unique set of potential complications that may be minimized with improved understanding of anatomy, biomechanics, and meticulous surgical technique. [5] (10.1177/0363546513485359)
- [L4] Symptomatic ACJ OA occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years. [6] (10.1177/17585732221114796)
- [L4] [7] (10.1016/j.otsr.2017.11.001)
- [L2] Untreated ACJ osteoarthritis, symptomatic or not, encountered during arthroscopic RCR is associated with a low percentage of failure. [8] (10.1007/s00167-020-06098-y)
- [L5] The procedure aims to preserve the lateral portion of the clavicle whenever possible, limiting resection exclusively to cases of AC joint osteoarthritis or irreducible joints. [9] (10.1016/j.eats.2024.103104)
- [L3] Radiographic ACJ osteoarthritis is common in patients undergoing RSA. [10] (10.1016/j.jseint.2021.11.008)
- [L3] Clinicians should consider overreduction of the AC joint because it may lead to favorable radiological results. [11] (10.1177/0363546519862850)
- [L4] The outcomes of this study seem to suggest that a distinction between symptomatic and asymptomatic radiographic AC OA is unnecessary, as all patients were equally satisfied with the outcome. [12] (10.5397/cise.2023.00073)
- [L1] Open and arthroscopic AC joint reconstruction techniques have no differences in loss of reduction, the complication rate, and the revision rate based on the available literature. [13] (10.1177/0363546518795147)
- [L3] [14] (10.1007/s00402-019-03258-9)
- [L4] Arthroscopic debridement of the AC joint can produce a favorable result in this difficult group of young patients presenting with isolated AC joint-related pain but with normal imaging. [15] (10.1097/bte.0b013e31816276cb)
- [L4] Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up. [17] (10.1016/j.otsr.2016.01.008)
- [L3] In this study the occurrence of AC joint osteoarthrosis was surprisingly frequent. [18] (10.1016/s1058-2746(96)80122-4)
- [L5] Anatomic techniques that address both coracoclavicular ligaments and the AC capsule are recommended to restore horizontal and vertical stability while allowing physiological rotation. [19] (10.1016/j.arthro.2019.01.038)
- [L4] Although the follow-up periods are less than 1 year, all patients are satisfied with their surgery and demonstrate good reduction of the AC joint on radiographs. [21] (10.1097/bte.0b013e31818a5dd9)
- [L4] The AC-DC measurement and use of the Alexander view provides the clinician with a more realistic appreciation of true AC joint displacement, especially in defining watershed cases (ie, IIIA/IIB/IV) and may better inform the decision-making process regarding management options and recommendations. [22] (10.1016/j.jse.2019.12.014)
- [L4] Additional research is needed to determine the main cause of pain and compare clinical outcomes of intra-articular versus extra-articular injections. [23] (10.5397/cise.2023.00311)
- [L4] Osteolytic changes seemed to be associated with incongruity of the AC joint, but did not correlate with clinical results. [24] (10.1016/0020-1383(83)90092-x)
- [L4] Osteoarthritis is associated with poorer final clinical outcomes, and an unhealed or re-torn cuff increases the risk of osteoarthritis. [26] (10.1016/j.otsr.2017.03.007)
- [L4] This procedure for an exact anatomical AC joint reconstruction shows good objective results with a high Constant and Rowe scores for shoulder function. [27] (10.1055/s-2008-1038577)
- [L4] The average angle from the central portion of the AC joint anteriorly was 6 degrees (range, 0 to 15 degrees). [29] (10.1097/bte.0000000000000033)
- [L3] [31] (10.1177/2325967119844295)
- [L4] AC injections offer a 1-year success rate of 47%. [33] (10.5397/cise.2023.00031)
- [L1] Preventive arthroscopic DCR is not recommended in patients with radiological but asymptomatic ACJ arthritis. [34] (10.1177/0363546514547254)
- [L4] This suggests that Type V AC dislocations may be given a trial of conservative therapy. [35] (10.1177/2325967115s00017)
- [L5] [36] (10.5435/00124635-199905000-00004)
- [L4] Conservative and surgical treatments are both effective in acromioclavicular joint osteoarthritis management. [38] (10.1007/s00167-020-06377-8)
- [L4] Most patients were ultimately treated surgically, although complications such as anterior shoulder pain, AC joint asymmetry, and activity-related weakness were common sequelae resulting in physical limitations and separation from military service. [43] (10.1177/03635465211036713)
- [L5] The technique offers advantages including decreased morbidity, less risk to the AC joint ligaments, and decreased loss and need for fluid. [44] (10.1016/j.eats.2021.12.006)
- [L4] Non-operative reduction and stabilization of high-grade AC joint separations seems to be a valuable treatment option. [45] (10.1007/s00402-020-03630-0)
- [L4] Ensuring good initial recovery of the CCD and precise placement of the AC joints was important in maintaining the proper AC position at the final follow-up. [46] (10.1016/j.arthro.2018.07.007)
- [L1] Evaluating the integrity of the capsuloligamentous structures stabilizing the AC joint is reproducible and gives additional information on the severity of the injury, which might also influence the treatment decision. [49] (10.1016/j.jse.2020.10.026)
- [L4] Severe chronic symptomatic AC joint separations (Rockwood types III through V) can be repaired entirely by arthroscopy safely and effectively by transferring the coracoacromial ligament with a bone block in the distal clavicle. [50] (10.1016/j.arthro.2009.08.008)
- [L5] [51] (10.1097/00132589-200603000-00004)
- [L4] Surgical management of AC joint injuries is associated with a relatively high complication profile and common loss of reduction, though the revision surgery rate is low. [53] (10.1016/j.jse.2023.03.019)
- [L4] [55] (10.1016/j.otsr.2010.10.004)
- [L4] Treatment of ACD by synthetic ligament reconstruction gave satisfactory results, notably in terms of recovery of strength, but evolution is not risk-free with onset of significant early osteolysis. [56] (10.1016/j.otsr.2010.06.004)
- [L5] The kinematic changes could be a potential source of pain and dysfunction in the shoulder with AC joint dislocation. [59] (10.1177/0363546512458571)
- [L5] Scapular and clavicular kinematics were affected in AC separation models. [60] (10.1016/j.jse.2013.01.004)
- [L4] [63] (10.1177/036354659302100113)
- [L4] Clinical symptoms and radiologic appearances are often poor indicators of the source of pain in the shoulder joint complex in patients with rheumatoid arthritis. [64] (10.1016/s1058-2746(09)80111-0)
- [L5] Combined stabilization of the AC capsule and CC ligaments demonstrated the greatest capacity to restore native stability against translational and rotational loads. [81] (10.1177/0363546518807908)
- [L5] In every CC loop repair, regardless of hole placement, complete AC joint congruity is not restored. [86] (10.1016/s1058-2746(03)00050-8)
- [L5] Given that more than 100 surgical stabilization techniques have been proposed for AC-joint injuries, a deeper understanding of the underlying anatomy, integrated with biomechanical evidence, may help to guide the development of a standardized, evidence-based approach to the treatment of AC-joint instability. [88] (10.2106/jbjs.25.01392)
- [L4] Patients with edema on MRI were more likely to present pain than patients without edema, and subchondral bone edema on histologic examination was more frequent in patients with pain. [92] (10.1016/j.jseint.2020.03.007)
- [L3] Early and delayed surgical interventions of high-grade AC joint dislocation provide equivalent clinical scores when combined CC and AC joint fixation is used for stabilization. [95] (10.1016/j.jse.2020.06.026)
- [L3] [101] (10.5397/cise.2023.00465)
- [L5] [112] (10.5435/jaaos-d-24-00360)
- [L4] [114] (10.1016/s1058-2746(96)80521-0)
- [L4] [115] (10.1016/s1058-2746(96)80520-9)
- [L4] [116] (10.1016/s1058-2746(96)80523-4)
- [L3] [117] (10.1016/s1058-2746(96)80522-2)
- [L4] [121] (10.1016/s1058-2746(10)80007-2)
- [L4] [122] (10.1302/2058-5241.3.170027)
- [L5] [123] (10.1016/s0278-5919(02)00102-3)
References
[1] Seven-year course of asymptomatic acromioclavicular osteoarthritis diagnosed by MRI. Journal of Shoulder and Elbow Surgery. 2019. DOI: 10.1016/j.jse.2019.04.004
[2] Choice of Acromioclavicular Dislocation Treatment Should Not Be Influenced by Risk of Development of Acromioclavicular Osteoarthritis. JBJS Reviews. 2024. DOI: 10.2106/jbjs.rvw.24.00085
[3] Outcome of distal clavicle resection in patients with acromioclavicular joint osteoarthritis and full‐thickness rotator cuff tear. Knee Surgery, Sports Traumatology, Arthroscopy. 2014. DOI: 10.1007/s00167-014-3114-2
[4] The Role of Arthroscopy in Revision of Failed Open Anterior Stabilization of the Shoulder. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.04.073
[5] Degenerative Joint Disease of the Acromioclavicular Joint. The American Journal of Sports Medicine. 2013. DOI: 10.1177/0363546513485359
[6] The incidence and treatment of symptomatic acromioclavicular joint osteoarthritis following total shoulder arthroplasty. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221114796
[7] Arthroscopically assisted reduction of acute acromioclavicular joint dislocation using a single double-button device: Medium-term clinical and radiological outcomes. Orthopaedics & Traumatology: Surgery & Research. 2018. DOI: 10.1016/j.otsr.2017.11.001
[8] Acromioclavicular joint arthritis is not an indication for routine distal clavicle excision in arthroscopic rotator cuff repair. Knee Surgery, Sports Traumatology, Arthroscopy. 2020. DOI: 10.1007/s00167-020-06098-y
[9] Biplanar Reconstruction With Pectoralis Minor Tendon and Coracoacromial Ligament Transfer for Chronic Acromioclavicular Joint Dislocations. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103104
[10] Severe acromioclavicular joint osteoarthritis is associated with acromial stress fractures after reverse shoulder arthroplasty. JSES International. 2022. DOI: 10.1016/j.jseint.2021.11.008
[11] Factors Predicting the Outcome After Arthroscopically Assisted Stabilization of Acute High-Grade Acromioclavicular Joint Dislocations. The American Journal of Sports Medicine. 2019. DOI: 10.1177/0363546519862850
[12] Diagnostic value of a preoperative acromioclavicular injection for symptomatic acromioclavicular osteoarthritis: a retrospective study of cross-sectional midterm outcomes. Clinics in Shoulder and Elbow. 2024. DOI: 10.5397/cise.2023.00073
[13] Current Concepts in the Operative Management of Acromioclavicular Dislocations: A Systematic Review and Meta-analysis of Operative Techniques. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518795147
[14] The relationship of the acromion to the distal clavicle in normal and symptomatic degenerated acromioclavicular joints. Archives of Orthopaedic and Trauma Surgery. 2019. DOI: 10.1007/s00402-019-03258-9
[15] Acromioclavicular Joint Arthroscopy and Debridement. Techniques in Shoulder & Elbow Surgery. 2008. DOI: 10.1097/bte.0b013e31816276cb
[17] Limited distal clavicle excision of acromioclavicular joint osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2016.01.008
[18] Osteoarthrosis of the acromioclavicular joint, an underestimated cause of shoulder pain. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80122-4
[19] Editorial Commentary: Why We Have To Respect The Anatomy In Acromioclavicular Joint Surgery And Why Clinical Shoulder Scores Might Not Give Us The Information We Need!. Arthroscopy. 2019. DOI: 10.1016/j.arthro.2019.01.038
[21] Free Tissue Graft Reconstruction of the Acromioclavicular Joint. Techniques in Shoulder & Elbow Surgery. 2008. DOI: 10.1097/bte.0b013e31818a5dd9
[22] Improved identification of unstable acromioclavicular joint injuries in a clinical population using the acromial center line to dorsal clavicle radiographic measurement. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.12.014
[23] Isolated acromioclavicular osteoarthritis and steroid injection. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00311
[24] Surgical treatment of acromioclavicular dislocation: A review of 39 patients. Injury. 1983. DOI: 10.1016/0020-1383(83)90092-x
[25] Aaos Comprehensive Orthopaedic Review 3. Disorders of the Acromioclavicular Joint > III. Atraumatic and Degenerative Conditions of the AC Joint.
[26] Osteoarthritis after rotator cuff repair: A 10-year follow-up study. Orthopaedics & Traumatology: Surgery & Research. 2017. DOI: 10.1016/j.otsr.2017.03.007
[27] Versorgung der Schultereckgelenksprengung mittels akromioklavikulärer und korakoklavikulärer FiberWire®-Cerclage. Zeitschrift für Orthopädie und Unfallchirurgie. 2008. DOI: 10.1055/s-2008-1038577
[29] A Novel and Reproducible Anterior Portal for Arthroscopic Distal Clavicle Excision. Techniques in Shoulder & Elbow Surgery. 2014. DOI: 10.1097/bte.0000000000000033
[30] Aaos Comprehensive Orthopaedic Review 3. Disorders of the Acromioclavicular Joint > II. Traumatic Conditions of the AC Joint.
[31] Preoperative Factors Associated With Subsequent Distal Clavicle Resection After Rotator Cuff Repair. Orthopaedic Journal of Sports Medicine. 2019. DOI: 10.1177/2325967119844295
[33] Mid- to long-term success rate and functional outcomes of acromioclavicular injections in patients with acromioclavicular osteoarthritis. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00031
[34] Is Arthroscopic Distal Clavicle Resection Necessary for Patients With Radiological Acromioclavicular Joint Arthritis and Rotator Cuff Tears?. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514547254
[35] Successful Conservative Therapy in Rockwood Type V Acromioclavicular Dislocations. Orthopaedic Journal of Sports Medicine. 2015. DOI: 10.1177/2325967115s00017
[36] Painful Conditions of the Acromioclavicular Joint. Journal of the American Academy of Orthopaedic Surgeons. 1999. DOI: 10.5435/00124635-199905000-00004
[38] No differences between conservative and surgical management of acromioclavicular joint osteoarthritis: a scoping review. Knee Surgery, Sports Traumatology, Arthroscopy. 2021. DOI: 10.1007/s00167-020-06377-8
[43] Coracoid or Clavicle Fractures Associated With Coracoclavicular Ligament Reconstruction. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211036713
[44] Nanoscopic Distal Clavicle Resection. Arthroscopy Techniques. 2022. DOI: 10.1016/j.eats.2021.12.006
[45] Can an acute high-grade acromioclavicular joint separation be reduced and stabilized without surgery? A surgeon’s experience. Archives of Orthopaedic and Trauma Surgery. 2020. DOI: 10.1007/s00402-020-03630-0
[46] Arthroscopic Coracoclavicular Fixation Using Multiple Low‐Profile Devices in Acute Acromioclavicular Joint Dislocation. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.07.007
[49] The ligamentous injury pattern in acute acromioclavicular dislocations and its impact on clinical and radiographic parameters. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.10.026
[50] All‐Arthroscopic Weaver‐Dunn‐Chuinard Procedure With Double‐Button Fixation for Chronic Acromioclavicular Joint Dislocation. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.08.008
[51] Primary and Revision Acromioclavicular Joint Reconstruction. Techniques in Shoulder and Elbow Surgery. 2006. DOI: 10.1097/00132589-200603000-00004
[53] Complications after operative treatment of high-grade acromioclavicular injuries. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2023.03.019
[55] Endoscopically assisted reconstruction of acute acromioclavicular joint dislocation using a synthetic ligament. Outcomes at 12 months. Orthopaedics & Traumatology: Surgery & Research. 2011. DOI: 10.1016/j.otsr.2010.10.004
[56] Acute grade III and IV acromioclavicular dislocations: Outcomes and pitfalls of reconstruction procedures using a synthetic ligament. Orthopaedics & Traumatology: Surgery & Research. 2010. DOI: 10.1016/j.otsr.2010.06.004
[59] The Function of the Acromioclavicular and Coracoclavicular Ligaments in Shoulder Motion. The American Journal of Sports Medicine. 2012. DOI: 10.1177/0363546512458571
[60] Acromioclavicular joint ligamentous system contributing to clavicular strut function: a cadaveric study. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2013.01.004
[63] Arthroscopic resection of the acromioclavicular joint. The American Journal of Sports Medicine. 1993. DOI: 10.1177/036354659302100113
[64] The source of shoulder pain in rheumatoid arthritis: Usefulness of local anesthetic injections. Journal of Shoulder and Elbow Surgery. 1994. DOI: 10.1016/s1058-2746(09)80111-0
[81] Primary Stability of an Acromioclavicular Joint Repair Is Affected by the Type of Additional Reconstruction of the Acromioclavicular Capsule. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518807908
[86] A cadaveric study examining acromioclavicular joint congruity after different methods of coracoclavicular loop repair. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1016/s1058-2746(03)00050-8
[88] Anatomical Nuance and Relevance: Reflections on the Trapezius and Acromioclavicular Joint Stability. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.25.01392
[92] Histologic and magnetic resonance image evaluation in acromioclavicular joint osteoarthritis. JSES International. 2020. DOI: 10.1016/j.jseint.2020.03.007
[95] Early and delayed acromioclavicular joint reconstruction provide equivalent outcomes. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.06.026
[101] Concomitant open distal clavicle excision is associated with greater improvement in range of motion without increased risk of acromial stress fracture after reverse total shoulder arthroplasty: a retrospective cohort study. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00465
[112] Effect of Acromioclavicular Joint Injuries on the Acromioclavicular Joint Complex and Scapulohumeral Rhythm: A Functional and Mechanical Perspective. Journal of the American Academy of Orthopaedic Surgeons. 2025. DOI: 10.5435/jaaos-d-24-00360
[114] Arthroscopic surgery for the throwing injury of the shoulder department of orthopaedic surgery school of medicine, fukuoka university. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80521-0
[115] The usefulness of distal clavicle resection for acromioclavicular joint disease. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80520-9
[116] Open reduction and internal fixation for fractures of the proximal humerus by rush pin and wire. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80523-4
[117] Natural history of rotator cuff tear using the evaluation of MR imaging. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80522-2
[121] Arthroscopic resection of the distal clavicle with a superior approach. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(10)80007-2
[122] Acromioclavicular joint injuries: diagnosis, classification and ligamentoplasty procedures. EFORT Open Reviews. 2018. DOI: 10.1302/2058-5241.3.170027
[123] Complications of the treatment of the acromioclavicular and sternoclavicular joint injuries, including instability. Clinics in Sports Medicine. 2003. DOI: 10.1016/s0278-5919(02)00102-3