Patients › Wrist
டி குவெர்வான் தசைநாண் உறை அழற்சி (De Quervain's Tenosynovitis)
Patient-facing topic on De Quervain's tenosynovitis (first dorsal compartment) — diagnosis, conservative management, and indications for de Quervain's release.
நீங்கள் உணர்வது
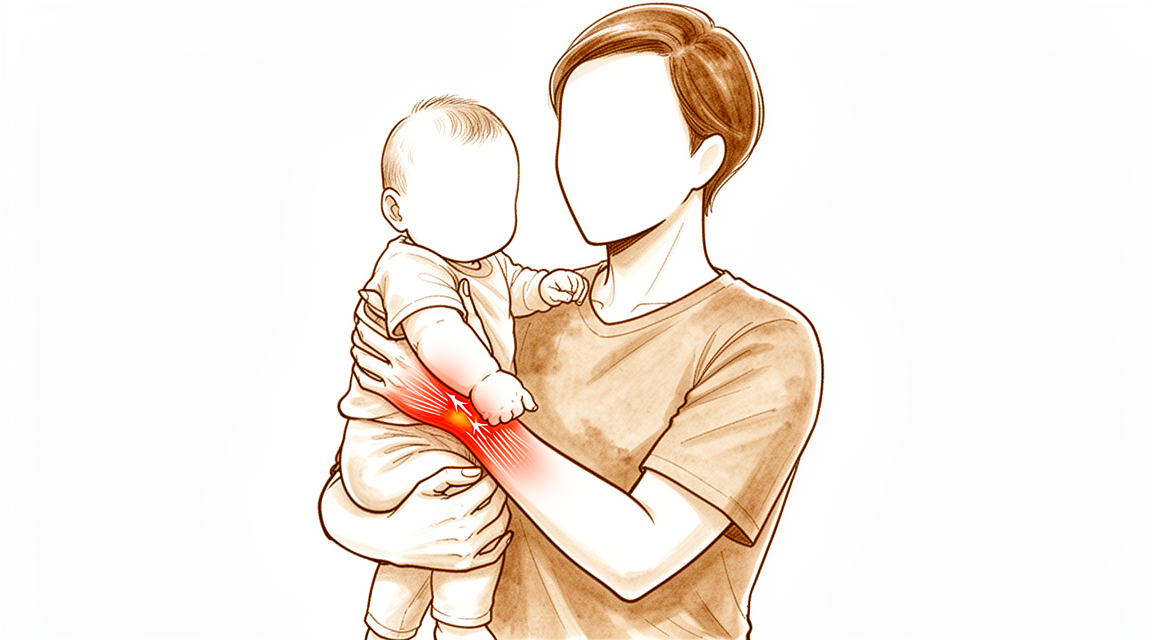
டி குவெர்வான் தசைநாண் உறை அழற்சி (De Quervain's tenosynovitis) என்பது, உங்கள் மணிக்கட்டின் கட்டைவிரல் பக்கத்தில் உள்ள இரண்டு தசைநாண்களில் ஏற்படும் ஒரு பிரச்சினை. அவை செல்லும் சுரங்கம் வீங்கி இறுக்கமாகிவிடுவதால், அதன் வழியாக நழுவும் தசைநாண்கள் வலிக்கின்றன. உங்கள் மணிக்கட்டின் கட்டைவிரல் பக்கத்தில், கட்டைவிரலின் அடிப்பகுதியில் உள்ள எலும்புப் புடைப்புக்கு அருகே, வலியையும் தொட்டால் வலிக்கும் தன்மையையும் உணர்கிறீர்கள். அதே இடத்தின் மேல் பெரும்பாலும் வீக்கமும் இருக்கும்.
சில அசைவுகள் வலியை மோசமாக்குகின்றன. மணிக்கட்டைச் சுண்டு விரல் பக்கம் நோக்கி வளைப்பது, மணிக்கட்டைக் கட்டைவிரல் பக்கம் நோக்கி வளைத்தபடி இறுக்கமாகப் பற்றிப் பிடிப்பது, அல்லது கட்டைவிரலையும் ஆள்காட்டி விரலையும் சேர்த்துக் கிள்ளுவது — இவை அனைத்தும் வலியைத் தூண்டலாம். இந்த அசைவுகளைப் பயன்படுத்தும் அன்றாட வேலைகள் கடினமாகின்றன: கெட்டிலைத் தூக்குவது, கதவுப் பிடியைத் திருப்புவது, ஒரு சிறு குழந்தையைத் தூக்குவது, ஒரு துணியைப் பிழிவது, அல்லது கத்தரிக்கோலைப் பயன்படுத்துவது. வலிக்கும் இடத்தை அழுத்தும்போது, தோலுக்கு அடியில் லேசான உரசல் அல்லது சடசடப்பு உணர்வைச் சிலர் கவனிக்கிறார்கள்.
பெரும்பாலானோருக்குக் கையைப் பயன்படுத்தும்போது வலி அதிகரிக்கிறது; ஓய்வில் தணிகிறது. கையை அதிகம் பயன்படுத்திய ஒரு நாளுக்குப் பிறகு அது மோசமாக இருக்கலாம். சிலர் இதைக் காலையில் எழுந்தவுடனோ இரவிலோ முதலில் கவனிக்கிறார்கள்.
ஒரு சிறு எண்ணிக்கையிலானோருக்கு (சுமார் 100 பேரில் 1 நபருக்கு), வலியுடன் சேர்த்துக் கட்டைவிரல் சிக்கிக்கொள்கிறது அல்லது பூட்டிக்கொள்கிறது. இதைக் குறிப்பிடுவது பயனுள்ளது; ஏனெனில் எந்தச் சிகிச்சைகள் நன்றாகப் பலனளிக்கும் என்பதை இது மாற்றக்கூடும்.
எப்போது உதவி நாட வேண்டும்
வலி தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே வந்தால், இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், அல்லது வேலை செய்யவோ கையைப் பயன்படுத்தவோ முடியாமல் தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணர் பரிசோதனையைக் கேளுங்கள்.
உங்கள் கை (hand) அல்லது முழுக் கை (arm) சூடாகி, சிவந்து, வீங்கி, வலித்தால் — குறிப்பாகக் காய்ச்சலுடன் — அன்றே அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். இது அன்றே சிகிச்சை தேவைப்படும் ஒரு தொற்றாக இருக்கலாம்; இதற்கு GP பரிந்துரைக் கடிதம் தேவையில்லை. உங்கள் விரல்களோ கையோ வெளிறியோ, குளிர்ந்தோ, வெண்மையாகவோ, நீலமாகவோ மாறினால், அல்லது ஒரு காயத்துக்குப் பிறகு திடீரென உணர்வையோ அசைவையோ இழந்தால், அன்றே செல்லுங்கள்.
கிளினிக்கைத் தொடர்புகொள்ள முடியாவிட்டால் — எடுத்துக்காட்டாக, அலுவலக நேரத்துக்குப் பிறகோ வார இறுதியிலோ — உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
உண்மையில் என்ன நடக்கிறது
இரண்டு தசைநாண்கள் உங்கள் கட்டைவிரலைக் கையிலிருந்து விலக்கி நகர்த்தி, அதை நேராக்குகின்றன. அவை உங்கள் மணிக்கட்டின் கட்டைவிரல் பக்கத்தில் உள்ள ஒரு குறுகிய சுரங்கத்தின் வழியாக அருகருகே செல்கின்றன. அந்தச் சுரங்கத்துக்கு உறுதியான ஒரு கூரை உள்ளது; இரண்டு கயிறுகளை இடம் மாறாமல் பிடித்து வைக்கும் ஒரு வழிகாட்டும் வளையம் போல, அது தசைநாண்களை எலும்புக்கு அருகில் பிடித்து வைக்கிறது.
பிரச்சினை என்னவென்றால், தசைநாண்களும் அவற்றின் சுரங்கமும் அழற்சியடைகின்றன. வீங்கிய உட்புறப் படலம், ஏற்கெனவே இறுக்கமான அந்த இடத்துக்குள் இடத்தை அடைத்துக்கொள்வதால், தசைநாண்கள் நழுவும்போது உரசுகின்றன. அந்த உராய்வு மேலும் வீக்கத்தையும் மேலும் வலியையும் ஏற்படுத்துகிறது; காலப்போக்கில் சுரங்கமே குறுகிவிடலாம். இந்தக் குறுகிய பாதையின் வழியான இரத்த ஓட்டம் குறைவு; இதனால் எரிச்சல் தானாகத் தணிவது கடினமாகிறது.
சிலருக்குப் பிறவியிலேயே சுரங்கத்துக்குள் ஒரு கூடுதல் சுவர் இருந்து, அதை இரண்டு தனித்தனிப் பாதைகளாகப் பிரிக்கிறது. இது முக்கியமானது; ஏனெனில் இரண்டு தசைநாண்களுக்குமே நழுவ இடம் தேவை. ஒரு தசைநாண் தனக்கென மூடப்பட்ட ஒரு தனிப் பாதையில் இருந்தால், முக்கியச் சுரங்கத்துக்குச் சிகிச்சை அளிக்கப்பட்ட பிறகும் அந்தப் பாதை இறுக்கமாகவே இருக்கலாம்.
நீங்கள் உணர்வதை இது விளக்குகிறது. உங்கள் மணிக்கட்டின் கட்டைவிரல் பக்கத்தில் உள்ள வலிக்கும் இடம் அந்தச் சுரங்கமே. பற்றிப் பிடிக்கும்போதும், கிள்ளும்போதும், தூக்கும்போதும் ஏற்படும் வலி, குறுகிய இடத்தின் வழியாகத் தசைநாண்கள் இழுபடுவதால் வருகிறது. தசைநாண்கள் சுதந்திரமாக நழுவ முடியாததால், கிள்ளிப் பிடிக்கும் வலிமையும் கட்டைவிரல் வலிமையும் குறையலாம். சிலர் கவனிக்கும் உரசல் உணர்வு, சொரசொரப்பான தசைநாண் மேற்பரப்பு தோலுக்கு அடியில் நகர்வதால் ஏற்படுகிறது.
வலியுடன் சேர்த்துக் கட்டைவிரல் சிக்கிக்கொண்டாலோ பூட்டிக்கொண்டாலோ, குறுகல் தசைநாணை ஒரு கணம் சிக்கவைக்கும் அளவுக்குத் தீவிரமாகிவிட்டது என்று பொருள். இது அதே பிரச்சினையின் மேலும் முன்னேறிய வடிவம்; எந்தச் சிகிச்சைகள் நன்றாகப் பலனளிக்கும் என்பதை இது மாற்றுவதால், இதை ஆரம்பத்திலேயே தெரிவிப்பது பயனுள்ளது.
இங்கே ஏற்படும் வலி, சுரங்கத்திலிருந்து அல்லாமல் அதன் அருகில் உள்ள அமைப்புகளிலிருந்தும் வரலாம்: கட்டைவிரலின் அடிப்பகுதியில் உள்ள மூட்டழற்சி (arthritis), முன்கையில் மேலே உள்ள எரிச்சலடைந்த தசைநாண்கள், அல்லது மணிக்கட்டின் இந்தப் பகுதியைக் கடந்து செல்லும் ஒரு மேலோட்டமான நரம்பு. இவற்றுக்கு வெவ்வேறு சிகிச்சைகள் தேவை; அதனால்தான் வலியின் சரியான மூலம் முக்கியமானது.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
Mater Private Hospital Rockhampton-இல் பணியாற்றும் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் நிலைக்குப் பொருந்தும் மிகக் குறைந்த ஊடுருவல் கொண்ட வழிகளிலிருந்து தொடங்குகிறார். நாங்கள் வழக்கமாக, நீங்கள் கையைப் பயன்படுத்தும் விதத்தில் மாற்றங்களுடனும், எரிச்சலைத் தணித்துத் தசைநாண்கள் மீதான சுமையைக் குறைக்கும் கை சிகிச்சையுடனும் (hand therapy) தொடங்குகிறோம். உங்கள் கட்டைவிரலையும் மணிக்கட்டையும் அசையாமல் வைத்திருக்கும் ஒரு சிம்பு (splint), தசைநாண்களுக்கு ஓய்வு தந்து, வலியை ஏற்படுத்தும் உராய்வைக் குறைக்கலாம். அடுத்த கட்டத்துக்குச் செல்வதற்கு முன் இந்தப் படிகளை முறையாக முயற்சித்துப் பாருங்கள்; நிலைமை மேம்படவில்லை என்றால் எங்களுக்குத் தெரிவியுங்கள்.
இந்த நிலைக்கு மிக வலுவான ஆதாரம் உள்ள சிகிச்சை கார்ட்டிசோன் ஊசி (cortisone injection) ஆகும். கார்ட்டிசோன் என்பது சுரங்கத்துக்குள் உள்ள வீக்கத்தை அமைதிப்படுத்தும் ஓர் அழற்சி எதிர்ப்பு மருந்து. ஒரே ஒரு ஊசி 82% நபர்களுக்கு அறிகுறிகளைத் தணிக்கிறது; அவர்களில் பாதிக்கும் மேற்பட்டோர் குறைந்தது 12 மாதங்களுக்கு அறிகுறிகள் இல்லாமல் இருக்கிறார்கள். ஊசியை வழிநடத்த அல்ட்ராசவுண்டைப் (ultrasound) பயன்படுத்துவது முடிவை மேம்படுத்தலாம்; நாங்கள் எதற்குச் சிகிச்சை அளிக்கிறோம் என்பதைத் துல்லியமாக உறுதிப்படுத்தவும் அது உதவுகிறது. மணிக்கட்டை அசையாமல் வைத்திருக்கும் ஒரு சிம்புடன் ஊசியைச் சேர்ப்பது, ஊசியை மட்டும் போடுவதைவிடச் சிறப்பாகப் பலனளிக்கிறது. உங்கள் அறிகுறிகள் திரும்பி வந்தால், இரண்டாவது ஊசி இன்னும் நியாயமான ஒரு தேர்வே; ஊசிகள் தோல்வியடைந்துவிட்டன என்பதற்கான அறிகுறி அல்ல. உங்களுக்கு நீரிழிவு நோய் இருந்தால், மற்றவர்களைவிட உங்களுக்கு ஒரே ஒரு ஊசி வெற்றியடையும் வாய்ப்பு குறைவு; ஆனால் ஒவ்வொரு அடுத்தடுத்த ஊசியும் அதற்கு முந்தைய ஊசியைப் போலவே தொடர்ந்து பலனளிக்கிறது.
பெரும்பாலானோருக்கு அறுவை சிகிச்சை தேவைப்படாது. அறுவை சிகிச்சையற்ற கவனிப்பு போதுமான முன்னேற்றத்தைத் தராதபோதோ, வலியுடன் சேர்த்துக் கட்டைவிரல் சிக்கிக்கொண்டு பூட்டிக்கொள்ளும்போதோ — இது பொதுவாகத் தானாகத் தணிவதில்லை — நாங்கள் அதைப் பரிசீலிக்கிறோம். தசைநாண்கள் மீண்டும் சுதந்திரமாக நழுவும்படி, இந்த அறுவை சிகிச்சை சுரங்கத்தின் இறுக்கமான கூரையை விடுவிக்கிறது. இது ஒரு சிறிய அறுவை சிகிச்சை; அதில் என்ன செய்யப்படுகிறது என்பதை விவரிக்கும் தனிப் பக்கம் ஒன்று உள்ளது.
என்ன எதிர்பார்க்கலாம்
பெரும்பாலானோருக்கு, இந்த நிலை தானாக விரைவில் மறைந்துவிடுவதில்லை. இது ஏற்படுபவர்களில் பெரும்பாலானோருக்கு, எதுவும் செய்யப்படாவிட்டால், ஒரு வருடம் கழித்தும் அறிகுறிகள் இருக்கின்றன; மேலும் வலி சீராக மங்கிப்போவதற்குப் பதிலாக, பயன்படுத்தும்போது அதிகரிக்கும் போக்கு உள்ளது. ஒரு சிறு எண்ணிக்கையிலானோருக்கு (சுமார் மூன்றில் ஒருவருக்கு) இறுதியில் இரண்டு வருடங்களுக்குள் அறுவை சிகிச்சை தேவைப்படும்; அது தேவைப்படுபவர்களில் பெரும்பாலானோர் முதல் வருடத்துக்குள்ளேயே அந்த நிலையை அடைகிறார்கள்.
சிகிச்சையுடன் கூடிய எதிர்காலப் போக்கு, நேர்மையாகச் சொன்னாலும் நல்லதே. ஒரே ஒரு கார்ட்டிசோன் ஊசி 70% நபர்களுக்கு அறிகுறிகளை முழுமையாகத் தணிக்கிறது; இரண்டாவது ஊசி மேலும் 10% நபர்களைக் குணப்படுத்துகிறது. மொத்தத்தில், இரண்டு ஊசிகளுக்குள் 73.4% நேரங்களில் ஊசிகள் வெற்றியடைகின்றன. அறுவை சிகிச்சை தேவைப்படும்போது, அது நன்றாகப் பலனளிக்கிறது: அதற்குப் பிறகு 88% நபர்கள் முழுமையாகத் திருப்தி அடைகிறார்கள்; 91% நிகழ்வுகளில் இந்த அறுவை சிகிச்சை பிரச்சினையைக் குணப்படுத்துகிறது.
மீட்சி எப்படி இருக்கும் என்பது நீங்கள் எந்த வழியைத் தேர்ந்தெடுக்கிறீர்கள் என்பதைப் பொறுத்தது. ஊசிக்குப் பிறகு, சுரங்கத்துக்குள் உள்ள வீக்கம் தணியும்போது, வலி பொதுவாக நாட்கள் முதல் வாரங்கள் வரையிலான காலத்தில் குறைகிறது. அறுவை சிகிச்சைக்குப் பிறகு தசைநாண்கள் மீண்டும் சுதந்திரமாக நழுவுகின்றன; திறந்த முறையைவிடச் சாவித்துளை (endoscopic) முறையில் முன்னேற்றம் பொதுவாக முன்னதாகவே வருகிறது. அறுவை சிகிச்சைக்குப் பிந்தைய கை சிகிச்சை, Extend Rehabilitation-இல் உள்ள Ruby Doolan-இடம் நடைபெறும். Ruby ஒரு கை சிகிச்சையாளர் (hand therapist): அவர் உங்கள் சிகிச்சையை வழிநடத்தி, உங்களுக்குத் தேவையான எந்தச் சிம்பையும் செய்து தருவார்.
சில விஷயங்களை முன்கூட்டியே தெரிந்துகொள்வது பயனுள்ளது. உங்களுக்கு நீரிழிவு நோய் அல்லது வளர்சிதை மாற்ற நோய்க்குறி (metabolic syndrome — உயர் இரத்த அழுத்தமும் வயிற்றைச் சுற்றிய எடையும் உள்ளிட்ட உடல்நலப் பிரச்சினைகளின் தொகுப்பு) இருந்தால், மற்றவர்களைவிட உங்களுக்கு ஊசிகள் வெற்றியடையும் வாய்ப்பு குறைவு. இந்த நிலையைப் பற்றி நீங்கள் எப்படி நினைக்கிறீர்கள் என்பதும் முக்கியம்: மிக மோசமானதையே எதிர்பார்ப்பவர்கள் அதிக வலியையும் குறைந்த செயல்திறனையும் தெரிவிக்கும் போக்கு உள்ளது; எனவே இந்த நிலை எதைக் குறிக்கிறது என்பது பற்றிய அச்சங்களைவிட, துல்லியமான எதிர்பார்ப்புகளைக் கொண்டிருப்பது உதவுகிறது.
உங்கள் அறிகுறிகள் தணியவில்லை என்றால், வாரக்கணக்கில் மோசமாகிக்கொண்டே வந்தால், இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பினால், அல்லது வேலை செய்யவோ கையைப் பயன்படுத்தவோ முடியாமல் தடுத்தால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணர் பரிசோதனையைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
இந்த நிலைக்கான எச்சரிக்கை அறிகுறிகளில் பெரும்பாலானவை மேலே முதல் பகுதியிலேயே விளக்கப்பட்டுள்ளன: தணியாத வலி, வாரக்கணக்கில் மோசமாகிக்கொண்டே வரும் வலி, இரவில் உங்களைத் தூக்கத்திலிருந்து எழுப்பும் வலி, அல்லது வேலை செய்யவோ கையைப் பயன்படுத்தவோ முடியாமல் தடுக்கும் வலி. இவற்றில் ஏதேனும் உங்களுக்குப் பொருந்தினால், உங்கள் GP-யைப் பாருங்கள் அல்லது நிபுணர் பரிசோதனையைக் கேளுங்கள்.
ஓர் அறிகுறியை இங்கே மீண்டும் குறிப்பிட வேண்டும். வலியுடன் சேர்த்து உங்கள் கட்டைவிரல் சிக்கிக்கொண்டாலோ பூட்டிக்கொண்டாலோ, நீங்கள் பார்க்கும் மருத்துவரிடம் அதைச் சொல்லுங்கள். பிரச்சினையின் இந்த வடிவம் ஓய்வாலோ சிம்பாலோ மட்டும் தணியும் போக்கு இல்லை; எந்தச் சிகிச்சைகள் நன்றாகப் பலனளிக்கும் என்பதையும் இது மாற்றுகிறது; எனவே அது மங்கிவிடுமா என்று காத்திருப்பதைவிட, ஆரம்பத்திலேயே தெரிவிப்பது பயனுள்ளது.
வலி வழக்கமான இடத்திலிருந்து சற்று விலகி இருந்தாலும் — எடுத்துக்காட்டாக, முன்கையில் இன்னும் மேலே, அல்லது கட்டைவிரலின் அடிப்பகுதிக்கு மேல் — இதே அறிவுரை பொருந்தும். வேறு பல நிலைமைகள் இதைப் போலவே தோன்றலாம்; அவை வெவ்வேறு சிகிச்சைகளுக்குப் பலனளிக்கின்றன. கவனமான பரிசோதனை உங்களுக்கு எது உள்ளது என்பதைக் கண்டறியும்.
உங்கள் கை (hand) அல்லது முழுக் கை (arm) சூடாகி, சிவந்து, வீங்கி, வலித்தால் — குறிப்பாகக் காய்ச்சலுடன் — அல்லது உங்கள் விரல்கள் வெளிறியோ, குளிர்ந்தோ, வெண்மையாகவோ, நீலமாகவோ மாறினால், அன்றே அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
உங்கள் சொந்த சிகிச்சை முடிவுகளுக்குத் தேவையானதைவிட இந்தப் பகுதி மேலும் ஆழமாகச் செல்கிறது. டி குவெர்வான் தசைநாண் உறை அழற்சியைப் பற்றிய இந்தக் கூடுதல் வாசிப்பு மதிப்புள்ளது; ஏனெனில் மற்றபடி நம்பகமான ஓர் அறுவை சிகிச்சைக்குப் பிறகு ஏற்படும் அதிருப்திக்குப் பெரும்பாலும் காரணமாக அமையும் ஒரு சிறிய உடற்கூற்று வேறுபாடு உள்ளது; மேலும் அறுவை சிகிச்சையற்ற சிகிச்சையின் சிறந்த பலன், இரண்டு சிகிச்சைகளுக்கு இடையே ஒன்றைத் தேர்ந்தெடுப்பதால் அல்ல, அவ்விரண்டையும் சேர்ப்பதால் கிடைக்கிறது.
இரண்டையும் சேர்ப்பது, தனித்தனியாக ஒன்றைச் செய்வதைவிடச் சிறந்தது
முதல் முதுகுப்புறப் பகுதி (first dorsal compartment), மணிக்கட்டின் கட்டைவிரல் பக்கத்தில் உள்ள ஒரு சுரங்கத்துக்குள் இரண்டு தசைநாண்களை வைத்திருக்கிறது. அந்தச் சுரங்கத்தில் உள்ள அழற்சியைத் தணிப்பதும், அதன் வழியாகச் செல்லும் சுமையைக் குறைப்பதும்தான் சிகிச்சையின் நோக்கம்.
823 நோயாளிகளை உள்ளடக்கிய ஒரு வலையமைப்பு மெட்டா-பகுப்பாய்வு (network meta-analysis), குறுகிய காலம் அசைவின்றி வைத்திருப்பதுடன் சேர்ந்த கார்ட்டிகோஸ்டீராய்டு ஊசியே முதன்மையான, பலனளிக்கும் சிகிச்சையாக இருக்கிறது என்று முடிவுசெய்தது; உடல்வெளி அதிர்வலை சிகிச்சை (extracorporeal shockwave therapy) இரண்டாம் நிலை வழியாகும் [1]. இதன் கூறுகளை நேரடியாகப் பார்த்தால், ஆதரவுக் கருவியையும் (orthosis) கார்ட்டிகோஸ்டீராய்டு ஊசியையும் சேர்த்த அணுகுமுறைகள், இவ்விரண்டில் ஏதேனும் ஒன்றைத் தனியாகச் செய்வதைவிடப் பலனளிக்கின்றன [2].
"முதலில் ஒரு சிம்பை முயற்சியுங்கள், அது தோல்வியுற்றால் ஓர் ஊசி" என்பதைவிட இது மிகவும் குறிப்பான வழிகாட்டுதல். இரண்டையும் சேர்த்துச் செய்வதையே ஆதாரங்கள் ஆதரிக்கின்றன — ஊசிக்குப் பிறகு ஒரு குறிப்பிட்ட குறுகிய காலத்துக்குச் சிம்பு அணிய வேண்டும்.
இரண்டாவது ஊசியும் இன்னும் மதிப்புள்ளதே
அறிகுறிகள் திரும்பி வரும்போது, ஊசிகள் தோல்வியடைந்துவிட்டன என்று முடிவுசெய்து அறுவை சிகிச்சைக்கு நகர்வதே உடனடி எதிர்வினையாக இருக்கிறது. ஒரு பெரிய நோயாளிக் குழுவின் தரவுகள் வேறுவிதமாகச் சொல்கின்றன: பல ஊசிகளுடன் வெற்றி விகிதம் குறைகிறது என்றாலும், மீண்டும் போடப்படும் ஊசிகள் அதிக வெற்றி விகிதத்தைக் கொண்டுள்ளன, அவை நடைமுறைக்கு உகந்த மருத்துவ வழியாகும் [3].
திரும்பத் திரும்பச் செய்யும்போது வெற்றி குறைவது எதிர்பார்க்கப்படுவதே. ஆனால் குறைந்த வெற்றி விகிதம் என்பது பயனற்றது என்பதற்குச் சமம் அல்ல; இரண்டாவது ஊசி என்பது காலத்தை இழுத்தடிக்கும் உத்தி அல்ல, நியாயமான ஒரு படியாகவே இருக்கிறது.
அறுவை சிகிச்சைக்குப் பிந்தைய ஏமாற்றங்களில் பெரும்பாலானவற்றை விளக்கும் உடற்கூற்று வேறுபாடு
முதல் முதுகுப்புறப் பகுதியை விடுவிப்பது பலனளிக்கிறது; அது ஏமாற்றம் தரும் இடங்களில் பொதுவாக ஒரு குறிப்பிட்ட காரணம் இருக்கிறது. முழுமையற்ற விடுவிப்பு, தசைநாண் நழுவல் (subluxation), நரம்புக் காயம், அல்லது வெறுமனே மீட்சிக்கு எடுக்கும் காலம் ஆகியவற்றால் அதிருப்தி ஏற்படலாம்; மேலும், கண்டறியப்படாமலும் விடுவிக்கப்படாமலும் விடப்பட்ட extensor pollicis brevis உள்ளுறை (subsheath), அதிருப்திக்கான தனித்த ஒரு காரணமாகும் [4].
இதை விரிவாக விளக்க வேண்டும்; ஏனெனில் இந்தப் பகுதியில் உள்ள மிகவும் பயனுள்ள ஒரே தகவல் இதுதான். கணிசமான விகிதத்தினருக்கு இந்தப் பகுதி ஒரு சுரங்கம் அல்ல, இரண்டு; அதில் extensor pollicis brevis தசைநாண் மற்றொன்றின் பக்கத்தில் தனக்கென்ற தனி உறைக்குள் செல்கிறது. முதன்மைப் பகுதியைத் திறந்துவிட்டு நின்றுவிடும் ஒரு விடுவிப்பு, அந்த இரண்டாவது உறையைத் தொடாமலேயே விட்டுவிடுகிறது; அதற்குள் இருக்கும் தசைநாணும் தொடர்ந்து அழுத்தப்பட்டபடியே இருக்கிறது. மணிக்கட்டு திறக்கப்படுகிறது, அறுவை சிகிச்சை விவரித்தபடியே முடிக்கப்படுகிறது, ஆனால் அறிகுறிகள் தொடர்கின்றன.
பட்டியலிடப்பட்ட மற்ற இரண்டு காரணங்களும் ஏன் முக்கியம் என்பதற்கும் இதுவே விளக்கம்: மிக அகலமாக விடுவித்தால், மணிக்கட்டு அசைவின்போது தசைநாண்கள் பள்ளத்திலிருந்து வெளியே நழுவ (subluxate) வழிவகுக்கும்; அது வலியுடன் கூடிய ஒரு படக்கென்ற அசைவை ஏற்படுத்தும். மேலும், ரேடியல் நரம்பின் மேலோட்டக் கிளை (superficial branch of the radial nerve) அறுவை சிகிச்சை செய்யும் இடத்தின் மீதேயே குறுக்கே செல்கிறது. வழியில் ஒரு நரம்பு இருக்க, இந்தப் பகுதியை முழுமையாகத் திறக்க வேண்டும், ஆனால் அளவுக்கு அதிகமாக அல்ல; அதனால்தான் வெளிப்பார்வைக்குச் சிறியதாகத் தோன்றும் ஓர் அறுவை சிகிச்சைக்கும், பெரிய அறுவை சிகிச்சைக்குத் தேவைப்படும் அதே கவனம் தேவைப்படுகிறது.
மணிக்கட்டின் கட்டைவிரல் பக்க வலி எல்லாமே டி குவெர்வான் அல்ல
இந்தப் பகுதியில் ஏற்படும் வலிக்குத் தெரிந்துகொள்ளத் தகுந்த வேறு சில சாத்தியங்களும் உள்ளன; ஏனெனில் அவற்றுக்கான சிகிச்சைகள் வேறுபடுகின்றன: கட்டைவிரலின் அடிப்பகுதியில் ஏற்படும் மூட்டழற்சி, முன்கையில் சில சென்டிமீட்டர்கள் மேலே ஏற்படும் இன்டர்செக்ஷன் சிண்ட்ரோம் (intersection syndrome), மற்றும் ரேடியல் நரம்பு எரிச்சல் — இவை அனைத்துமே ஒன்றுடன் ஒன்று ஒன்றிப்போகும் பகுதியில் வலியை ஏற்படுத்தக்கூடும். அந்தப் பகுதியின் மீதே நேரடியாகக் குவிந்திருக்கும் தொடுவலியும், கட்டைவிரலை உள்ளங்கைக்குள் மடக்கி வைத்து மணிக்கட்டைச் சுண்டு விரல் பக்கம் சாய்க்கும்போது (ulnar deviation) அதே வலி மீண்டும் தோன்றுவதும்தான், அண்டை அமைப்புகளையல்ல, தசைநாண் உறையையே சுட்டிக்காட்டுகின்றன.
மேற்கோள்கள்
[1] Chong HH, Pradhan A, Dhingra M, Liong W, Hau MY, Shah R. Advancements in de Quervain tenosynovitis management: a comprehensive network meta-analysis of randomized controlled trials. J Hand Surg Am. 2024;49(6):557-69. https://doi.org/10.1016/j.jhsa.2024.03.003
[2] Cavaleri R, Schabrun SM, Te M, Chipchase LS. Hand therapy versus corticosteroid injections in the treatment of de Quervain's disease: a systematic review and meta-analysis. J Hand Ther. 2016;29(1):3-11. https://doi.org/10.1016/j.jht.2015.10.004
[3] Hassan K, Sohn A, Shi L, Lee M, Wolf JM. De Quervain tenosynovitis: an evaluation of the epidemiology and utility of multiple injections using a national database. J Hand Surg Am. 2022;47(3):284.e1-284.e6. https://doi.org/10.1016/j.jhsa.2021.04.018
[4] Rogozinski B, Lourie GM. Dissatisfaction after first dorsal compartment release for de Quervain tendinopathy. J Hand Surg Am. 2016;41(1):117-9. https://doi.org/10.1016/j.jhsa.2015.09.003
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Anatomy and Diagnosis
- Anatomical variations in the first extensor compartment are clinically relevant to the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- Wrist radiography does not influence the management of patients presenting with de Quervain tendinopathy [6].
- The tethered thumb sign is a clinical maneuver that supports the diagnosis of de Quervain tenosynovitis and assists in determining an effective treatment algorithm [12].
- Ultrasound can be used as a diagnostic tool in the management of de Quervain’s disease [18].
Non-Operative Treatment
- Corticosteroid injection is the only available nonsurgical treatment that can potentially modify the course of de Quervain's tenosynovitis and is the preferred initial treatment [2].
- Corticosteroid injection with a short duration of immobilization remains the primary and effective treatment for de Quervain tenosynovitis [28].
- Corticosteroid injections lead to treatment success 73.4% of the time within 2 injections [22].
- Although the success rate for the treatment of De Quervain's tenosynovitis decreases with multiple injections, repeat injections have a high rate of success and are a viable clinical option [46].
- Corticosteroid injection for De Quervain tenosynovitis is not as effective in patients with metabolic syndrome compared with age- and sex-matched controls in terms of functional outcomes and treatment failure [5].
- Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients [40].
- The effectiveness of each additional corticosteroid injection does not appear to diminish in patients with diabetes mellitus [40].
- Ultrasound-guided triamcinolone injection should be considered to improve the treatment outcome for de Quervain's disease [18].
Operative Treatment
- Surgical release of De Quervain's tenosynovitis remains the gold standard treatment [10].
- Surgical intervention is effective as definitive therapy for de Quervain's tenosynovitis, with a cure rate of 91% and 88% of patients indicating full satisfaction [11].
- The release of the first extensor compartment for refractory de Quervain's disease results in good clinical outcomes with minimal morbidity [24].
- Longitudinal incision offers the advantage of easy identification of the compartment, more complete releases of tendon sheath and peritendinous adhesions, and less risk of palmar subluxation of tendons [10].
- The longitudinal incision for release of the first extensor compartment is a safe and effective technique that provides good exposure, protects vital structures, prevents possible tendon subluxation in the postoperative period, and is cosmetically acceptable [17].
- Endoscopic release for de Quervain's tenosynovitis seems to provide earlier improvement after surgery, with fewer superficial radial nerve complications and greater scar satisfaction, when compared with open release [33].
- One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures [31].
- Endoscopic release of the extensor compartment is an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time [41].
- Pulley reconstruction should be considered part of the surgical treatment for de Quervain tenosynovitis and gives satisfactory medium-term results [4].
Prognosis and Patient Factors
- Patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management [7].
- Patients who scored lower than 40 for physical function or higher than 60 for pain interference had significantly increased odds of eventually undergoing surgical release for de Quervain tenosynovitis [34].
- The failure of an operation in De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignoring of another syndrome in the proximity [13].
- Addressing misconceptions about de Quervain's tenosynovitis regarding consequences for patients and symptom duration allows patients to make informed decisions about treatment [9].
Anatomy & Pathophysiology
Anatomical Variations
- The first dorsal compartment of the wrist exhibits immense anatomical variation, including commonly found supernumerary tendons or tendon slips [107].
- Variation in tendon insertion is present in the population of the first dorsal compartment [107].
- Septa or aberrant compartments are present in the first dorsal compartment [107].
- Bilateral variations are present in the population regarding the anatomy of the first dorsal compartment [107].
- The superficial branch of the radial nerve is expected to be encountered in more than 50% of patients undergoing surgery for De Quervain's tenosynovitis [94].
Pathophysiology
- De Quervain's syndrome is defined as a condition where the abductor pollicis longus and extensor pollicis brevis tendons in the first dorsal compartment become inflamed through friction within a tight osteoligamentous tunnel [3].
- Compromised blood flow and nutrition in the first dorsal compartment lead to the development of adhesions and tendon stenosis [3].
- De Quervain's syndrome may involve myxoid degeneration, defined as a degenerative process where connective tissues are replaced by a gelatinous or mucoid substance [3].
- The pathophysiology of De Quervain's disease does not involve inflammation, with histopathological examination showing predominant degenerative changes such as myxoid degeneration and fibrocartilagenous metaplasia [38].
- De Quervain's tenosynovitis is caused by impaired gliding of the abductor pollicis longus and extensor pollicis brevis tendons [38].
- Impaired gliding in De Quervain's tenosynovitis is most probably caused by thickening of the extensor retinaculum of the wrist [38].
- De Quervain's syndrome may not be an isolated pathology and may be associated with trauma, extensor carpi ulnaris involvement, ligament instability, or repetitive strain [3].
- Operative treatment for distal radius fractures confers a slightly greater risk of developing De Quervain tenosynovitis within 1 year of injury or surgery [105].
Clinical Presentation & Assessment
- De Quervain's tenosynovitis is characterized by pain, tenderness, and swelling over the thumb side of the wrist at the radial styloid process [38].
- The condition is especially associated with sideward movements of the wrist and often leads to impairment of thumb function [38].
- The tethered thumb sign is a clinical maneuver that can support the diagnosis of De Quervain tenosynovitis and assist in determining an effective treatment algorithm [12].
- Subjects with stenosing tenosynovitis demonstrate a significant decrease in maximum velocity in slow fist tasks [81].
- In vivo extensor pollicis brevis tendon excursion measures have been quantified, and wrist position has been found to have an influence on excursion [73].
- The proportion of wrists with a positive extensor pollicis brevis entrapment test was significantly higher among those with two compartments (18 of 22) than among those with one compartment (0 of 4) [97].
Etiology & Risk Factors
- Women are more affected by De Quervain tenosynovitis than men, potentially due to manual work such as housekeeping activities and child rearing influencing first compartment dynamics [72].
- Training intensity is a major factor in determining De Quervain disease in volleyball players, with patients in the higher intensity group showing a mean training time quotient of 155 compared to 74 in the lower intensity group [72].
- The close association of work and repetitive trauma with De Quervain’s disease has been observed, although the exact relationship is controversial [21].
- Recent studies have disputed the view that repetitive work is causative of De Quervain’s disease, with one review of 100 patients finding no increased incidence in the dominant hand [21].
- A study of workers in a car plant reported 544 cases of tenosynovitis but only 2 cases of De Quervain’s disease [21].
- Repetitive work is less contentious as a factor in aggravating symptoms, as tendon movement within a stenosed sheath during activity logically causes pain [21].
- The process of tendon movement within a stenosed sheath may cause tendon damage through wear and tear, potentially leading to tendon rupture [21].
Complications & Associated Pathology
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has never been reported in the literature prior to the 2006 case report [21].
- Volar subluxation of the tendons of the first dorsal compartment can occur after surgery for De Quervain's stenosing tenosynovitis [48].
- Volar tendon subluxation after De Quervain's release can be treated with a distally based flap of the brachioradialis tendon to prevent tendon prolapse [48].
- Symptomatic palmar tendon subluxation after surgical release for De Quervain's disease can be avoided by leaving a palmarly based flap of extensor retinaculum [15].
- Dorsal tendon dislocation after De Quervain's release can occur if the patient overstresses the wrist through forceful extension [80].
- Repeat provocative testing for volar tendon subluxation following De Quervain’s release revealed volar tendon translation with wrist flexion, with no pain reported [85].
- Osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, with correct diagnosis often requiring histological examination when clinical presentation and X-rays are not typical [45].
Classification
Anatomical Variations and Subcompartmentalization
- The prevalence of a septated first dorsal compartment is considerably higher than previously reported, most notably in patients with De Quervain tenosynovitis [52].
- In a prospective study of 87 wrists, 22 of 30 patients (73%) who failed non-operative treatment and underwent operative release were found to have a separate compartment for the extensor pollicis brevis [55].
- The prevalence of a separate compartment for the extensor pollicis brevis in patients failing non-operative treatment is significantly higher than that in the general population, as shown in anatomical studies of cadavers [55].
- The persistence of an intracompartmental septum between the abductor pollicis longus and extensor pollicis brevis tendons has been described in a mean 43% of wrists in cadaveric studies, with a wide variation ranging from 20 to 75% [39].
- When the extensor pollicis brevis tendon resides in a subcompartment, it is likely to do so particularly in patients with de Quervain's disease [53].
- Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides important information about anatomic variations within the first extensor compartment [50].
- The presence of an intracompartmental septum detected by ultrasound is associated with the failure of ultrasound-guided steroid injection in de Quervain’s syndrome [39].
Diagnostic Mimics and Associated Pathologies
- Extensor pollicis longus tenosynovitis caused by the extensor pollicis longus's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease [30].
- An osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, with correct diagnosis often requiring histological examination when clinical presentation and X-rays are not typical [45].
- A hemangioma of the extensor pollicis brevis in the first dorsal compartment is an unusual cause of bilateral de Quervain's disease [14].
- De Quervain’s syndrome may not be an isolated pathology, with potential associations to trauma, extensor carpi ulnaris involvement, ligament instability, and repetitive strain [3].
- Failure of surgical treatment in De Quervain tenosynovitis can be attributed to anatomical variations, the involvement of the radial superficial nerve, and the ignorance of another syndrome in the proximity [13].
- The complexities of de Quervain's tendinitis and the diagnosis and treatment of associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in working women [8].
Clinical Presentation and Physical Examination
- Triggering or locking in extension is an uncommon symptom in de Quervain’s stenosing tenosynovitis, with a prevalence of 1.3% based on a review of 827 consecutive patients [20].
- A new test for evaluating the first extensor compartment is a useful clinical tool in the diagnosis of De Quervain's tenosynovitis [36].
- Ultrasound can be used as a diagnostic tool in the management of de Quervain’s disease, in addition to improving treatment outcomes [18].
Epidemiology and Risk Factors
- In a young, active population, the unadjusted incidence rate of de Quervain’s tenosynovitis was 0.94 per 1000 person-years [54].
- The adjusted incidence rate ratio for females compared to male patients was 4.45 (95% CI 4.28, 4.62) when controlling for race, age, service, and rank [54].
- The highest incidence rate of de Quervain’s tenosynovitis was seen in the ≥40-year-old group, with an incidence rate of 1.37 per 1000 person-years [54].
- The adjusted incidence rate ratio for the ≥40-year-old group compared to the <20-year-old group was 3.65 (95% CI 3.26, 4.09) [54].
- Non-white race is a risk factor for de Quervain’s tenosynovitis, with an adjusted incidence rate ratio of 1.31 (95% CI 1.21, 1.42) for black race and 1.17 (95% CI 1.05, 1.25) for others compared to white race [54].
- De Quervain’s syndrome affects around 1.3% of women and 0.5% of men in a population of adults of working age [39].
Pathophysiology
- De Quervain’s syndrome is defined as a condition where the abductor pollicis longus and extensor pollicis brevis tendons in the first dorsal compartment become inflamed through friction, leading to compromised blood flow, nutrition, adhesions, and tendon stenosis [3].
- De Quervain’s syndrome may represent a myxoid degeneration, defined as a degenerative process in which connective tissues are replaced by a gelatinous or mucoid substance [3].
- The role of repetitive work in the causation of de Quervain’s disease is controversial, with some studies disputing it as a primary cause while acknowledging it may aggravate symptoms [21].
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has never been reported in the literature prior to the 2006 report [21].
Clinical Presentation
Symptoms and Signs
- Patients typically complain of soreness and tenderness on the radial side of the distal radius that is exacerbated by ulnar deviation of the thumb [59].
- Symptoms are also exacerbated by a strong grasp combined with flexion and radial deviation of the wrist or by a firm pinching together of the index finger and thumb [59].
- Physical examination reveals tenderness and swelling directly over the first dorsal compartment [59].
Diagnostic Testing
- De Quervain disease is diagnosed clinically and no imaging studies are required [64].
- Wrist radiography does not influence management of patients presenting with de Quervain tendinopathy [6].
- In a study of 200 patients, no radiographic findings altered the course of treatment in patients with isolated de Quervain's tenosynovitis [62].
- Wrist imaging is required only in the presence of associated processes that may need to be evaluated, such as previous distal radius or scaphoid fracture, arthritis of the thumb, and instability of the wrist [64].
- Ultrasound can be useful as a diagnostic tool in the management of de Quervain’s disease [18].
- Ultrasound is a worthwhile preoperative investigation in case of de Quervain's disease [51].
- The wrist hyperflexion and abduction of the thumb (WHAT) test is a more specific and sensitive test to diagnose de Quervain tenosynovitis than the Eichhoff’s Test [59].
- Finkelstein's test is superior to Eichhoff's test in the investigation of de Quervain's disease [63].
- A new clinical maneuver, the tethered thumb sign, can support the diagnosis of de Quervain tenosynovitis and assist in determining an effective treatment algorithm [12].
Differential Diagnosis and Mimics
- Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease [30].
- Congenital synostosis between the scaphoid and the trapezium can cause tenosynovitis simulating de Quervain's disease [43].
- The failure of surgical treatment in De Quervain tenosynovitis can be due to anatomical variations, the involvement of the radial superficial nerve, and the ignoring of another syndrome in the proximity [13].
- In cases with symptoms of de Quervain's syndrome where the constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised [27].
Patient Factors and Perception
- Providers should remain cognizant that patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management [7].
- Most informed patients initially elect symptomatic treatment for de Quervain's disease, and most experience symptom resolution within one year [32].
- More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression [25].
- Addressing misconceptions about de Quervain's tenosynovitis in terms of the consequences for patients and how long their symptoms will last should allow patients to make informed decisions about the treatment that best matches their values [9].
Investigations
Clinical Examination
- Finkelstein's test is described as a descriptive error that can produce a false positive [16].
- A staged description of the Finkelstein test has been proposed to address diagnostic accuracy issues [16].
- A new clinical test for evaluating the first extensor compartment is a useful tool in the diagnosis of De Quervain's tenosynovitis [36].
- In cases where symptoms suggest de Quervain's syndrome but constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised [27].
Imaging
- Deferring routine wrist radiography does not affect the management of de Quervain tendinopathy patients [6].
- Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides information about anatomic variations within the first extensor compartment [50].
- Ultrasound is a worthwhile preoperative investigation in cases of de Quervain's disease [51].
- Radial styloid abnormalities do not affect the outcome of management for de Quervain's disease [19].
- An osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, and correct diagnosis may require histological examination when clinical presentation and X-rays are atypical [45].
- Congenital synostosis between the scaphoid and the trapezium can cause tenosynovitis that simulates de Quervain's disease [43].
- Extensor pollicis longus tenosynovitis caused by an unusual course through the first extensor compartment is a rare condition that mimics de Quervain’s disease [30].
Anatomical Variations
- Anatomical variations in the first extensor compartment are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- The presence of an intracompartmental septum does not significantly affect clinical outcomes or complications following endoscopic release for de Quervain's syndrome [42].
- When the extensor pollicis brevis tendon is associated with thumb interphalangeal joint extension, it is likely to reside in a subcompartment of the first dorsal compartment, particularly in patients with de Quervain's disease [53].
- De Quervain's disease may be secondary to extensor pollicis brevis entrapment [29].
Patient Factors and Perception
- Addressing misconceptions about the consequences of de Quervain's tenosynovitis and symptom duration allows patients to make informed decisions about treatment [9].
- Growth hormone abuse is associated with a more recalcitrant form of de Quervain tenosynovitis that does not respond well to nonsurgical treatment, increasing the likelihood of surgical decompression [79].
Treatment
Non-Operative Management
- One or two local injections of 1 ml triamcinolone acetonide 10 mg/ml provided by general practitioners leads to short-term improvement in participants with de Quervain's tenosynovitis compared to placebo [26].
- Corticosteroid injections are a useful treatment for de Quervain's tenosynovitis, leading to treatment success 73.4% of the time within 2 injections [22].
- A single cortisone injection was effective in alleviating symptoms of de Quervain tendinopathy in 82% of patients, with over half remaining symptom-free for at least 12 months [67].
- The combined technique of corticosteroid injection and thumb spica casting was better than injection alone in the treatment of de Quervain tenosynovitis in terms of treatment success and functional outcomes [68].
- Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients, but the effectiveness of each additional injection does not appear to diminish [40].
- Ultrasound should be considered to improve the treatment outcome of corticosteroid injections and can also be useful as a diagnostic tool in the management of de Quervain’s disease [18].
- Pain and clinical outcomes significantly improved after corticosteroid injection in de Quervain's disease [49].
- Preliminary results indicate that betamethasone is a superior treatment for De Quervain's tenosynovitis compared to ketorolac injection [70].
- Splinting has not been shown to provide long-lasting relief beyond allowing the joints to rest in an immobilized position [65].
- Iontophoresis with dexamethasone may improve functional outcomes, while therapeutic pulsed ultrasound may be effective in decreasing pain in patients with de Quervain's tenosynovitis [69].
Operative Management
- The release of the first extensor compartment for refractory de Quervain's disease resulted in good clinical outcomes with minimal morbidity [24].
- An oblique incision coursing along the extensor brevis tendon is preferred for surgical release, though transverse, oblique, or longitudinal incisions are also satisfactory [35].
- The longitudinal incision for release of the first extensor compartment offers the advantage of easy identification of the compartment, more complete releases of tendon sheath and peritendinous adhesions, and less risk of palmar subluxation of tendons [10].
- The first dorsal compartment should be opened on its dorsoulnar side during surgical release [35].
- A volarly based retinacular flap must remain over the released tendons to prevent volar tendon subluxation [35].
- Symptomatic palmar tendon subluxation after surgical release can be avoided by leaving a palmarly based flap of extensor retinaculum to prevent palmar subluxation of the tendons with wrist flexion [15].
- Volar subluxation of the tendons of the first dorsal compartment after surgery can be treated with a distally based flap of the brachioradialis tendon [48].
- One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures in patients with de Quervain's disease who are unresponsive to non-operative treatments [31].
- Endoscopic release of the extensor compartment seems to be an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time [41].
- Pulley reconstruction should be considered part of the surgical treatment for de Quervain tenosynovitis as it gives satisfactory medium-term results [4].
- The failure of an operation in De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignorance of another syndrome in the proximity [13].
- Anatomical variations are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- Anatomic variations are frequently encountered in recalcitrant cases of de Quervain tenosynovitis, including multiple slips of APL and EPB in its own separate compartment [83].
- First dorsal compartment release during volar approach for distal radius fracture fixation reduces symptoms in patients with pre-existing De Quervain disease compared with no release [75].
Complications
Surgical Complications
- Surgical failure in De Quervain tenosynovitis is attributed to anatomical variations, involvement of the radial superficial nerve, and the failure to diagnose another syndrome in the proximity [13].
- Symptomatic palmar tendon subluxation is a complication of surgical release that can be avoided by leaving a palmarly based flap of extensor retinaculum [15].
- The longitudinal incision for release of the first extensor compartment prevents possible tendon subluxation in the postoperative period [17].
- Endoscopic release for de Quervain's tenosynovitis is associated with fewer superficial radial nerve complications compared with open release [33].
- The longitudinal incision offers a less risk of palmar subluxation of tendons compared to other approaches [10].
Tendon and Structural Complications
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has been reported, with pathogenesis potentially linked to ongoing tendon damage from wear and tear within the stenosed sheath [21].
- Longitudinal split tears of the extensor pollicis brevis tendon have been reported in cases of de Quervain's tenosynovitis [16].
Diagnostic and Associated Pathology
- De Quervain's syndrome may be associated with trauma, extensor carpi ulnaris involvement, ligament instability, or repetitive strain, indicating it may not be an isolated pathology [3].
- Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a rare condition that mimics de Quervain’s disease [30].
- In cases where constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised to avoid diagnostic error [27].
- The complexities of de Quervain's tendinitis and associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in working women [8].
Recovery
Non-Operative Management
- A single injection of steroid gives complete and lasting relief in 70% of patients with de Quervain's disease, and a further 10% will be cured by a second injection [91].
Operative Management
- Only 34.9% of patients with new stenosing tenosynovitis required surgery within a 2-year follow-up period, with most progressing to surgery within 1 year of presentation [93].
Surgical Technique and Complications
- Pulley reconstruction as part of the surgical treatment for de Quervain tenosynovitis gives satisfactory medium-term results and should be considered part of the surgical treatment [4].
Patient Factors and Prognosis
- More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression of de Quervain's tenosynovitis [25].
Key Evidence
- [L4] These variations are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis. [1] (10.1016/j.bjps.2016.08.020)
- [L4] According to the limited evidence available, injection of corticosteroids is the only available nonsurgical treatment that can potentially modify the course of de Quervain's tenosynovitis and is therefore the preferred initial treatment. [2] (10.1016/j.jhsa.2008.12.030)
- [L4] [3] (10.1177/1758998315599796)
- [L4] The authors believe the technique gives satisfactory medium-term results and should be considered part of the surgical treatment for de Quervain tenosynovitis. [4] (10.1055/s-0035-1556862)
- [L3] Although considerable improvements in symptom severity and hand function will likely occur in patients with metabolic syndrome, corticosteroid injection for De Quervain tenosynovitis is not as effective in these patients compared with age- and sex-matched controls in terms of functional outcomes and treatment failure. [5] (10.1177/1753193417694112)
- [L3] Wrist radiography does not influence management of patients presenting with de Quervain tendinopathy. [6] (10.1055/s-0037-1606124)
- [L4] Providers should remain cognizant that patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management. [7] (10.1016/j.jhsg.2024.01.009)
- [L4] The complexities of de Quervain's tendinitis and the diagnosis and treatment of associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in these groups of working women. [8] (10.1016/s0363-5023(87)80204-6)
- [L3] Addressing misconceptions about de Quervain's tenosynovitis in terms of the consequences for patients and how long their symptoms will last should allow patients to make informed decisions about the treatment that best matches their values. [9] (10.1097/corr.0000000000001577)
- [L4] Surgical release of De Quervain's tenosynovitis remains the gold standard treatment, and longitudinal incision offers advantage of easy identification of compartment, more complete releases of tendon sheath and peritendinous adhesions and less risk of palmar subluxation of tendons. [10] (10.1007/s12306-018-0585-1)
- [L4] Surgical intervention is effective as definitive therapy for de Quervain's tenosynovitis, with a cure rate of 91% and 88% of patients indicating full satisfaction. [11] (10.1053/jhsu.1999.1071)
- [L4] We can conclude that the failure of an operation in the De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignoration of another syndrome in the proximity. [13] (10.1177/1558944716660555gr)
- [L5] [14] (10.1016/s0363-5023(96)80112-2)
- [L5] This complication can be avoided by leaving a palmarly based flap of extensor retinaculum to prevent palmar subluxation of the tendons with wrist flexion. [15] (10.1016/s0363-5023(84)80017-9)
- [L4] [16] (10.1016/j.jhsa.2014.09.024)
- [L4] In our experience, the longitudinal incision for release of the first extensor compartment for de Quervain tenosynovitis is a safe and effective technique that provides good exposure, protects vital structures, prevents possible tendon subluxation in the postoperative period, and is cosmetically acceptable. [17] (10.1097/01.bth.0000181105.24124.c0)
- [L4] Therefore, ultrasound should not only be considered to improve the treatment outcome, but can also be useful as a diagnostic tool in the management of de Quervain’s disease. [18] (10.1016/j.main.2013.09.002)
- [L4] Though considered as a manifestation of de Quervain's disease by some authors, styloid abnormalities do not affect the outcome of management as proved in this study. [19] (10.1007/s11552-010-9258-8)
- [L4] Triggering or locking in extension is an uncommon symptom in de Quervain’s stenosing tenosynovitis, with a prevalence of 1.3% based on a review of 827 consecutive patients. [20] (10.1053/jhsu.1999.1311)
- [L4] [21] (10.1016/j.jhsb.2005.09.020)
- [L3] This study indicates that corticosteroid injections are a useful treatment for de Quervain's tenosynovitis, leading to treatment success 73.4% of the time within 2 injections. [22] (10.1177/1558944716681976)
- [L4] The release of the first extensor compartment for refractory de Quervain's disease resulted in good clinical outcomes with minimal morbidity. [24] (10.4055/cios.2014.6.4.405)
- [L3] More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression of de Quervain's tenosynovitis. [25] (10.1097/corr.0000000000000992)
- [L1] One or two local injections of 1 ml triamcinolonacetonide 10 mg/ml provided by general practitioners leads to improvement in the short term in participants with de Quervain's tenosynovitis when compared to placebo. [26] (10.1186/1471-2474-10-131)
- [L4] In cases with symptoms of de Quervain's syndrome where the constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised. [27] (10.2106/00004623-194931040-00019)
- [L1] Corticosteroid injection with a short duration of immobilization remains the primary and effective treatment for de Quervain tenosynovitis. [28] (10.1016/j.jhsa.2024.03.003)
- [L4] We conclude that de Quervain's disease is secondary to EPB entrapment. [29] (10.1016/s0363-5023(98)80160-3)
- [L5] Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease. [30] (10.1016/j.jhsa.2003.11.012)
- [L4] One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures in patients with de Quervain's disease who are unresponsive to non-operative treatments. [31] (10.1016/j.aott.2018.10.004)
- [L4] Most informed patients initially elect symptomatic treatment for de Quervain's disease, and most experience symptom resolution within one year. [32] (10.1007/s12593-009-0018-3)
- [L1] Endoscopic release for de Quervain's tenosynovitis seems to provide earlier improvement after surgery, with fewer superficial radial nerve complications and greater scar satisfaction, when compared with open release. [33] (10.1302/0301-620x.95b7.31486)
- [L4] Patients who scored lower than 40 for physical function or higher than 60 for pain interference had significantly increased odds of eventually undergoing surgical release for de Quervain tenosynovitis. [34] (10.1016/j.jhsa.2023.07.005)
- [L3] The new test is a useful clinical tool in the diagnosis of De Quervain's tenosynovitis. [36] (10.1016/j.main.2011.10.017)
- [L1] [38] (10.1002/14651858.cd005616.pub2)
- [L3] [39] (10.1177/1753193415611414)
- [L4] Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients, but the effectiveness of each additional injection does not appear to diminish. [40] (10.1016/j.jhsa.2022.02.018)
- [L4] Endoscopic release of the extensor compartment seems to be an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time. [41] (10.1016/j.bjps.2011.05.015)
- [L4] The presence of a septum does not significantly affect clinical outcomes or complications following endoscopic release for de Quervain's syndrome. [42] (10.1177/17531934231214137)
- [L5] We describe a case of nonsyndromic congenital fusion of the scaphoid and the trapezium as a cause of tendinitis simulating de Quervain's stenosing tenosynovitis, an association not previously reported. [43] (10.1016/s1297-3203(00)73478-0)
- [L5] As the clinical presentation and X-rays of the wrist were not typical of an osteoid osteoma, only the histological examination led to the correct diagnosis. [45] (10.1016/0266-7681(92)90100-g)
- [L2] Although the success rate for the treatment of De Quervain's tenosynovitis decreases with multiple injections, repeat injections have a high rate of success and are a viable clinical option. [46] (10.1016/j.jhsa.2021.04.018)
- [L4] [48] (10.1016/s0363-5023(10)80007-3)
- [L1] Pain and clinical outcomes significantly improved after corticosteroid injection in de Quervain's disease. [49] (10.1016/j.otsr.2019.11.015)
- [L5] Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides important information about anatomic variations within the first extensor compartment. [50] (10.1136/bcr-2021-242173)
- [L4] Ultrasound is a worthwhile preoperative investigation in case of de Quervain's disease. [51] (10.1007/s12593-009-0001-z)
- [L3] The prevalence of a septated first dorsal compartment is considerably higher than previously reported, most notably in patients with De Quervain tenosynovitis. [52] (10.1177/1558944718810864)
- [L4] When it does, particularly in patients with de Quervain's disease, it is likely to reside in a subcompartment of the first dorsal compartment. [53] (10.1016/j.jhsa.2008.12.015)
- [L2] [54] (10.1016/j.jhsa.2008.08.020)
- [L2] [59] (10.1177/1753193412475043)
- [L4] [62] (10.1055/s-0040-1716522)
- [L3] [63] (10.1055/s-0038-1626690)
- [L5] [64] (10.5435/00124635-200712000-00009)
- [L4] [65] (10.1007/s11552-014-9649-3)
- [L4] A single cortisone injection was effective in alleviating symptoms of de Quervain tendinopathy in 82% of patients, with over half remaining symptom-free for at least 12 months. [67] (10.1016/j.jhsa.2014.12.027)
- [L2] The combined technique of corticosteroid injection and thumb spica casting was better than injection alone in the treatment of de Quervain tenosynovitis in terms of treatment success and functional outcomes. [68] (10.1016/j.jhsa.2013.10.013)
- [L4] This study demonstrated that iontophoresis with dexamethasone may improve functional outcomes, while therapeutic pulsed ultrasound may be effective in decreasing pain in patients with de Quervain's tenosynovitis. [69] (10.1016/j.jht.2014.08.032)
- [L1] Preliminary results indicate that betamethasone is a superior treatment for De Quervain's tenosynovitis. [70] (10.1016/j.jhsa.2017.06.086)
- [L4] [72] (10.1177/0363546504268134)
- [L4] In vivo EPB tendon excursion measures have been quantified, and wrist position has been found to have an influence on excursion. [73] (10.1016/j.jht.2017.12.004)
- [L1] The current results demonstrated a significantly greater reduction in de Quervain disease symptoms in the release group compared with the no release group during the short-term follow-up. [75] (10.1016/j.jhsg.2024.03.009)
- [L3] Our results suggest that growth hormone abuse is associated with a more recalcitrant form of de Quervain tenosynovitis that does not respond well to nonsurgical treatment, thus leading to increased likelihood of surgical decompression. [79] (10.1177/0363546509337993)
- [L5] The patient overstressed his wrist through forceful extension during over-zealous weightlifting. [80] (10.1177/1753193419871862)
- [L3] Those subjects demonstrate a significant decrease in maximum velocity in slow fist tasks, highlighting the need for comprehensive assessment to ascertain the full extent of functional limitations that can occur in the setting of hand pathology. [81] (10.1177/1558944717729218)
- [L4] Repeat provocative testing revealed volar tendon translation with wrist flexion, with no pain reported. [85] (10.1097/bth.0000000000000054)
- [L4] A single injection of steroid gives complete and lasting relief in 70% of patients with de Quervain's disease, and a further 10% will be cured by a second injection. [91] (10.1016/s0363-5023(09)91110-8)
- [L2] Only 34.9% of patients with new stenosing tenosynovitis required surgery within a 2-year follow-up period, with most progressing to surgery within 1 year of presentation. [93] (10.1016/j.jhsa.2017.06.088)
- [L2] The anatomical findings are consistent with previous studies, with an expectation to encounter the superficial branch of the radial nerve in more than 50% of patients. [94] (10.1055/s-0039-1688700)
- [L3] The proportion of wrists with a positive EPB entrapment test was significantly higher among those with 2 compartments (18 of 22) than among those with 1 compartment (0 of 4). [97] (10.1053/jhsu.2002.35309)
- [Paper] Operative treatment for distal radius fractures confers a slightly greater risk of developing DeQuervain tenosynovitis within 1 year of injury or surgery. [105] (10.1177/15589447251366456)
- [Paper] There is immense anatomical variation present in the first dorsal compartment of the wrist, supernumerary tendons/tendon slips are commonly found, there is variation of insertion present in the population, septum/aberrant compartment is also present, and bilateral variations are present in the population. [107] (10.1007/s12593-012-0073-z)
References
[1] Surgical anatomy of the first extensor compartment: A systematic review and comparison of normal cadavers vs. De Quervain syndrome patients. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2017. DOI: 10.1016/j.bjps.2016.08.020
[2] Nonsurgical Treatment for de Quervain's Tenosynovitis. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.12.030
[3] De Quervain’s syndrome: It may not be an isolated pathology. Hand Therapy. 2015. DOI: 10.1177/1758998315599796
[4] Pulley Reconstruction As Part of the Surgical Treatment for de Quervain Disease: Surgical Technique with Medium-Term Results. Journal of Wrist Surgery. 2015. DOI: 10.1055/s-0035-1556862
[5] RETRACTED: Effects of metabolic syndrome on the functional outcomes of corticosteroid injection for De Quervain tenosynovitis. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193417694112
[6] Deferring Routine Wrist Radiography Does Not Affect Management of de Quervain Tendinopathy Patients. Journal of Wrist Surgery. 2017. DOI: 10.1055/s-0037-1606124
[7] De Quervain’s Tenosynovitis: As Seen from the Perspective of the Patient. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.01.009
[8] de Quervain's release in working women: A report of failures, complications, and associated diagnoses. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80204-6
[9] Are Patient Expectations and Illness Perception Associated with Patient-reported Outcomes from Surgical Decompression in de Quervain’s Tenosynovitis?. Clinical Orthopaedics & Related Research. 2020. DOI: 10.1097/corr.0000000000001577
[10] Functional outcome of De Quervain’s tenosynovitis with longitudinal incision in surgically treated patients. MUSCULOSKELETAL SURGERY. 2019. DOI: 10.1007/s12306-018-0585-1
[11] Patient satisfaction and outcomes of surgery for de Quervain's tenosynovitis. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1071
[12] Tethered_Thumb_Sign_A_Unique_Observation_in_the_Physical_Examination_of_de_Querv_S0363502313005340. n.d..
[13] Failure of Surgical Treatment in the De Quervain Tenosynovitis. HAND. 2016. DOI: 10.1177/1558944716660555gr
[14] Hemangioma of the extensor pollicis brevis in the first dorsal compartment: An unusual cause of bilateral de Quervain's disease. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80112-2
[15] Symptomatic palmar tendon subluxation after surgical release for de Quervain's disease: A case report. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80017-9
[16] Longitudinal Split Tear of the Extensor Pollicis Brevis Tendon: Report of 2 Cases. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.09.024
[17] Longitudinal Incision in Surgical Release of De Quervain Disease. Techniques in Hand & Upper Extremity Surgery. 2005. DOI: 10.1097/01.bth.0000181105.24124.c0
[18] The role of ultrasound-guided triamcinolone injection in the treatment of De Quervain's disease: Treatment and a diagnostic tool?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.09.002
[19] Does Radial Styloid Abnormality in de Quervain's Disease Affect the Outcome of Management?. HAND. 2010. DOI: 10.1007/s11552-010-9258-8
[20] Extensor triggering in de Quervain's stenosing tenosynovitis. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1311
[21] Abductor Pollicis Longus Tendon Rupture in De Quervain’s Disease. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.09.020
[22] Effectiveness of Corticosteroid Injections for Treatment of de Quervain’s Tenosynovitis. HAND. 2016. DOI: 10.1177/1558944716681976
[24] Surgical Release of the First Extensor Compartment for Refractory de Quervain's Tenosynovitis: Surgical Findings and Functional Evaluation Using DASH Scores. Clinics in Orthopedic Surgery. 2014. DOI: 10.4055/cios.2014.6.4.405
[25] Which Psychological Variables Are Associated With Pain and Function Before Surgery for de Quervain’s Tenosynovitis? A Cross-sectional Study. Clinical Orthopaedics & Related Research. 2019. DOI: 10.1097/corr.0000000000000992
[26] Randomised controlled trial of local corticosteroid injections for de Quervain's tenosynovitis in general practice. BMC Musculoskeletal Disorders. 2009. DOI: 10.1186/1471-2474-10-131
[27] AN UNUSUAL FORM OF DE QUERVAINʼS SYNDROME. The Journal of Bone & Joint Surgery. 1949. DOI: 10.2106/00004623-194931040-00019
[28] Advancements in de Quervain Tenosynovitis Management: A Comprehensive Network Meta-Analysis. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.03.003
[29] Limited surgical treatment of de quervain's disease: Decompression of only the extensor pollicis brevis subcompartment. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80160-3
[30] Extensor pollicis longus tenosynovitis mimicking de quervain’s disease because of its course through the first extensor compartment: a report of 2 cases. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.11.012
[31] One portal endoscopic release of the first extensor compartment in de Quervain's disease. Acta Orthopaedica et Traumatologica Turcica. 2020. DOI: 10.1016/j.aott.2018.10.004
[32] Patient-centered care of de Quervain’s disease. Journal of Hand and Microsurgery. 2009. DOI: 10.1007/s12593-009-0018-3
[33] Endoscopicversusopen release in patients with de Quervain’s tenosynovitis. The Bone & Joint Journal. 2013. DOI: 10.1302/0301-620x.95b7.31486
[34] Association of Patient-Reported Outcomes Measurement Information System Measures With Injection and Surgical Treatment Response in Patients With De Quervain Tenosynovitis. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.005
[35] Campbell S Operative Orthopaedics 4 Volume Set. EXCISION OF NECROTIC MUSCLES COMBINED WITH NEUROLYSIS OF MEDIAN AND ULNAR NERVES FOR SEVERE CONTRACTURE > SURGICAL TREATMENT OF DE QUERVAIN DISEASE.
[36] Évaluation de la première loge des extenseurs à fin diagnostique : un nouveau test dans le diagnostic de la ténosynovite de De Quervain. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.017
[38] Corticosteroid injection for de Quervain's tenosynovitis. Cochrane Database of Systematic Reviews. 2009. DOI: 10.1002/14651858.cd005616.pub2
[39] Presence of an intracompartmental septum detected by ultrasound is associated with the failure of ultrasound-guided steroid injection in de Quervain’s syndrome. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193415611414
[40] Effectiveness of Corticosteroid Injections in Diabetic Patients With De Quervain Tenosynovitis. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.02.018
[41] Does endoscopic release of the first extensor compartment have benefits over open release in de Quervain’s disease?. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2011. DOI: 10.1016/j.bjps.2011.05.015
[42] Prediction of an intracompartmental septum and its effect on outcomes of endoscopic release for de Quervain’s syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231214137
[43] Congenital synostosis between the scaphoid and the trapezium as a cause of tenosynovitis simulating de Quervain's disease. Chirurgie de la Main. 2000. DOI: 10.1016/s1297-3203(00)73478-0
[45] Osteoid Osteoma of the Radial Styloid Mimicking Stenosing Tenosynovitis. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90100-g
[46] De Quervain Tenosynovitis: An Evaluation of the Epidemiology and Utility of Multiple Injections Using a National Database. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.04.018
[48] Tendon subluxation after de Quervain's release: Treatment by brachioradialis tendon flap. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80007-3
[49] Prospective randomized comparison of ultrasonography-guided and blind corticosteroid injection for de Quervain's disease. Orthopaedics & Traumatology: Surgery & Research. 2020. DOI: 10.1016/j.otsr.2019.11.015
[50] Type II de Quervain’s disease: depicting subcompartmentalisation with ultrasound. BMJ Case Reports. 2021. DOI: 10.1136/bcr-2021-242173
[51] Preoperative ultrasound in de Quervain’s disease: an investigation worth doing. Journal of Hand and Microsurgery. 2009. DOI: 10.1007/s12593-009-0001-z
[52] Prevalence of a Septated First Dorsal Compartment Among Patients With and Without De Quervain Tenosynovitis: An In Vivo Anatomical Study. HAND. 2018. DOI: 10.1177/1558944718810864
[53] Thumb Interphalangeal Joint Extension By the Extensor Pollicis Brevis: Association With a Subcompartment and de Quervain's Disease. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.12.015
[54] Incidence of de Quervain's Tenosynovitis in a Young, Active Population. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.08.020
[55] Treatment of de Quervain tenosynovitis. A prospective study of the results of injection of steroids and immobilization in a splint.. The Journal of bone and joint surgery. American volume. 1991.
[59] The wrist hyperflexion and abduction of the thumb (WHAT) test: a more specific and sensitive test to diagnose de Quervain tenosynovitis than the Eichhoff’s Test. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193412475043
[62] Are Plain X-Rays Necessary in the Diagnosis of De Quervain's Tenosynovitis?. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1716522
[63] Finkelstein's Test Is Superior to Eichhoff's Test in the Investigation of de Quervain's Disease. Journal of Hand and Microsurgery. 2018. DOI: 10.1055/s-0038-1626690
[64] de Quervain Tenosynovitis of the Wrist. Journal of the American Academy of Orthopaedic Surgeons. 2007. DOI: 10.5435/00124635-200712000-00009
[65] De Quervain's Tenosynovitis: A Review of the Rehabilitative Options. HAND. 2014. DOI: 10.1007/s11552-014-9649-3
[67] de Quervain Tendinopathy: Survivorship and Prognostic Indicators of Recurrence Following A Single Corticosteroid Injection. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.027
[68] Corticosteroid Injection With or Without Thumb Spica Cast for de Quervain Tenosynovitis. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.10.013
[69] Effective Conservative Treatments for De Quervain's Tenosynovitis: A Retrospective Study. Journal of Hand Therapy. 2016. DOI: 10.1016/j.jht.2014.08.032
[70] Betamethasone Versus Ketorolac Injection for the Treatment of De Quervain's Tenosynovitis: A Double-Blind Randomized Clinical Trial. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.086
[72] De Quervain Disease in Volleyball Players. The American Journal of Sports Medicine. 2005. DOI: 10.1177/0363546504268134
[73] Ultrasound assessment of extensor pollicis brevis tendon excursion in different wrist positions in healthy people. Journal of Hand Therapy. 2019. DOI: 10.1016/j.jht.2017.12.004
[75] First Dorsal Compartment Release During Volar Approach for Distal Radius Fracture Fixation Reduces Symptoms in Patients With Pre-Existing De Quervain Disease. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.03.009
[79] Abuse of Growth Hormone Increases the Risk of Persistent de Quervain Tenosynovitis. The American Journal of Sports Medicine. 2009. DOI: 10.1177/0363546509337993
[80] Dorsal tendon dislocation after de Quervain's release and its surgical management: a case report. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419871862
[81] Dynamic Functional Assessment of Hand Motion Using an Animation Glove: The Effect of Stenosing Tenosynovitis. HAND. 2017. DOI: 10.1177/1558944717729218
[83] Miller S Review Of Orthopaedics. 2. Flexor tendon injury > 5. de Quervain tenosynovitis (Fig. 7.35).
[85] Radial Ridge Excision for Symptomatic Volar Tendon Subluxation Following de Quervain’s Release. Techniques in Hand & Upper Extremity Surgery. 2014. DOI: 10.1097/bth.0000000000000054
[91] De Quervain's disease: Surgical or nonsurgical treatment. The Journal of Hand Surgery. 1990. DOI: 10.1016/s0363-5023(09)91110-8
[93] A Prospective Study of Risk Modeling for Stenosing Tenosynovitis. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.088
[94] A Prospective Evaluation of the Anatomy of the First Dorsal Compartment in Patients Requiring Surgery for De Quervain's Tenosynovitis. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1688700
[97] The extensor pollicis brevis entrapment test in the treatment of de Quervain's disease. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.35309
[105] Incidence of DeQuervain Tenosynovitis After Distal Radius Fractures. HAND. 2025. DOI: 10.1177/15589447251366456
[107] A Cadaveric Study of the First Dorsal Compartment of the Wrist and Its Content Tendons: Anatomical Variations in the Indian Population. Journal of Hand and Microsurgery. 2012. DOI: 10.1007/s12593-012-0073-z