Patients › Wrist
மணிக்கட்டு மூட்டு நுண்ணோக்கி அறுவை சிகிச்சை (Wrist Arthroscopy)
Diagnostic and therapeutic wrist arthroscopy — what it is, when it's used, and recovery.
இந்த அறுவை சிகிச்சை ஏன் பரிந்துரைக்கப்பட்டுள்ளது
Mater Private Hospital Rockhampton-இல் பணியாற்றும் மேல் அவயவ (upper-limb) அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்கள் நிலைக்குப் பொருத்தமான, குறைந்த அளவு ஊடுருவும் வழிகளிலிருந்தே தொடங்குகிறார். நோயாளிகள் பொதுவாக அவர்களின் GP (குடும்ப மருத்துவர்) மூலம் எங்கள் கிளினிக்குக்குப் பரிந்துரைக்கப்படுகிறார்கள்; ஒரு இயன்முறை சிகிச்சையாளர் (physiotherapist) எங்களைச் சந்திக்கச் சொல்லியிருந்தாலும், Medicare தள்ளுபடியைப் (rebate) பெறத் தகுதி பெற உங்கள் GP-யிடமிருந்து பரிந்துரைக் கடிதம் இன்னும் தேவைப்படும். உங்கள் சந்திப்பின்போது, உங்கள் வலிக்கு என்ன காரணம் என்பதைக் கண்டறிய, உங்கள் உடல்நல வரலாற்றைக் கவனமாகக் கேட்டறிந்து, உங்கள் மணிக்கட்டைப் பரிசோதித்து, தேவைப்படும் இடத்துப் படமெடுப்புக்கு (imaging) ஏற்பாடு செய்வோம்.
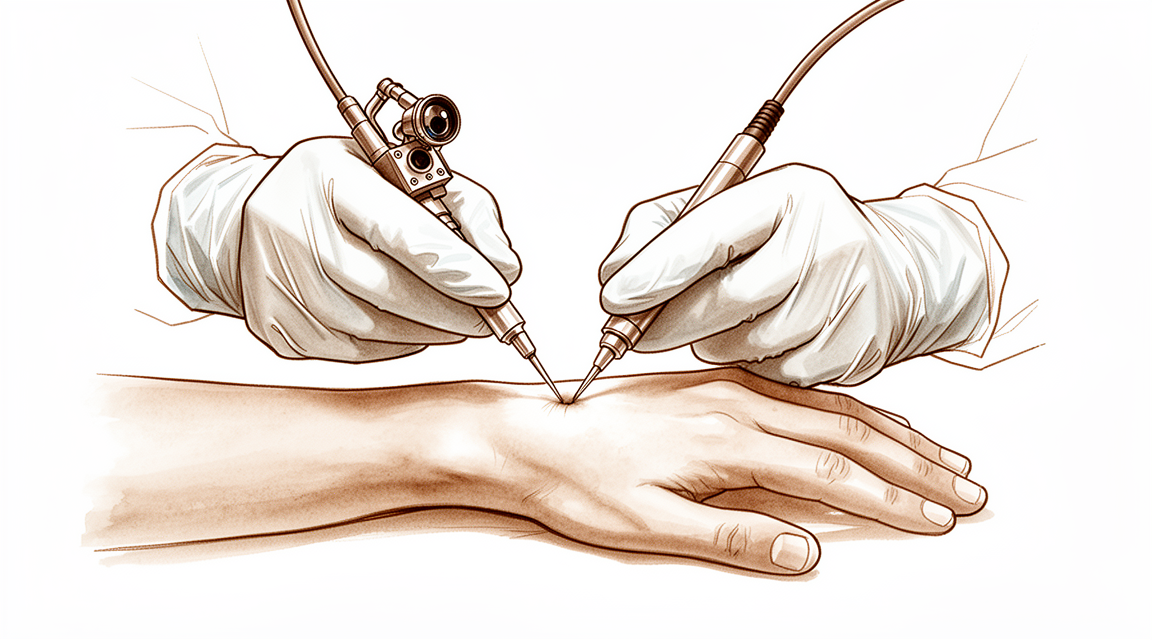
மணிக்கட்டு மூட்டு நுண்ணோக்கி அறுவை சிகிச்சை (wrist arthroscopy) என்பது, மூட்டுப் பரப்புகளையும் மென்திசுக்களையும் நெருக்கமாகப் பார்க்க, மணிக்கட்டு மூட்டுக்கு உள்ளே ஒரு சிறிய கேமராவைப் பயன்படுத்தும் ஓர் அறுவை சிகிச்சை. மணிக்கட்டு வலி 3 மாதங்களுக்கு மேல் நீடித்து, செயல்களை மாற்றிக்கொள்வது, கை சிகிச்சை (hand therapy), சிம்பு (splint) அணிவது அல்லது ஊசி மருந்துகள் போன்ற அறுவை சிகிச்சை அல்லாத சிகிச்சையால் தணியாமல், ஸ்கேன்களும் பரிசோதனையும் போதுமான அளவு தெளிவான விடையைத் தராதபோது இதை நாங்கள் பொதுவாகப் பரிந்துரைக்கிறோம். எலும்பு முறிவுக்கோ தசைநார் (ligament) காயத்துக்கோ பிறகு, மூட்டுப் பரப்புகளையும் மென்திசுக்களையும் சரிபார்க்கவும், சில பிரச்சினைகளுக்கு அதே அமர்வில் சிகிச்சை அளிக்கவும் இது பரிந்துரைக்கப்படலாம். விறைப்பு, சில வகை மூட்டழற்சி (arthritis), நீண்ட காலமாக நீடிக்கும் தசைநார்ப் பிரச்சினைகள் ஆகியவற்றுக்கும் இந்த அறுவை சிகிச்சை உதவக்கூடும். தொடர்ந்து நீடிக்கும் மணிக்கட்டு வலிக்காக இந்த அறுவை சிகிச்சையைச் செய்துகொண்டவர்கள், ஒரு ஆண்டில் சராசரியாகச் சுமார் 50% அளவு முன்னேற்றம் அடைந்தார்கள்; இருப்பினும் பெரும்பாலானோருக்குத் தொடர்ந்து சிறிது வலியும் செயல்பாட்டுக் குறைபாடும் இருந்தது. குறைவான வலி, மேம்பட்ட அசைவு, மேலும் உறுதியான மணிக்கட்டு ஆகியவையே முக்கிய நோக்கம்; இது உங்களுடன் சேர்ந்தே முடிவு செய்யப்படுகிறது.
அறுவை சிகிச்சைக்கு முன்
அறுவை சிகிச்சை நாளுக்கு முன் உங்கள் அறுவை சிகிச்சை நிபுணர் உங்களுக்குத் தெளிவான அறிவுறுத்தல்களைத் தருவார்; நடைமுறை விஷயங்களை இங்கே விளக்குகிறோம். உங்கள் அறுவை சிகிச்சைக்கு ஏழு மணி நேரம் முன்பிருந்து உண்பதையும் குடிப்பதையும் நிறுத்த வேண்டும். அறுவை சிகிச்சை அரங்கின் பட்டியல் முன்கூட்டியே நகர்ந்தால் உங்கள் அறுவை சிகிச்சையை முன்னதாகச் செய்ய முடியும் என்பதற்காகவே, வழக்கமான ஆறு மணி நேரத்துக்குப் பதிலாக ஏழு மணி நேரம் கேட்கிறோம். நீங்கள் தற்போது எடுத்துக்கொள்ளும் மருந்துகளின் பட்டியலைக் கொண்டுவாருங்கள்; அவற்றில் ஏதேனும் முன்கூட்டியே தற்காலிகமாக நிறுத்தப்பட வேண்டுமா என்பதை உங்கள் அறுவை சிகிச்சை நிபுணர் சொல்வார். அறுவை சிகிச்சைக்குப் பிறகு வீட்டுக்கு வாகனத்தில் அழைத்துச் செல்ல ஒருவரை ஏற்பாடு செய்யுங்கள்; தளர்வான, வசதியான ஆடைகளை அணியுங்கள். எக்ஸ்-ரே, MRI அல்லது அல்ட்ராசவுண்ட் போன்ற படமெடுப்புகள் அறுவை சிகிச்சையைத் திட்டமிட உதவுகின்றன; இது பொதுவாக உங்கள் சந்திப்பின்போதே ஏற்பாடு செய்யப்படுகிறது. உங்களுக்கு வேறு உடல்நலப் பிரச்சினைகள் இருந்தால், இரத்தப் பரிசோதனைகள் அல்லது மயக்க மருந்து நிபுணரின் (anaesthetist) பரிசோதனை தேவைப்படலாம்.
அறுவை சிகிச்சை நாளில்
உங்கள் அறுவை சிகிச்சை நாளில், மருத்துவமனையின் அறுவை சிகிச்சை அனுமதிப் பிரிவுக்கு (surgical admissions unit) வருவீர்கள். அங்கே உங்கள் வருகை பதிவு செய்யப்பட்டு, நீங்கள் அறுவை சிகிச்சை அரங்குக்குத் தயார்படுத்தப்படுவீர்கள். பின்னர் மயக்க மருந்து நிபுணரைச் சந்திப்பீர்கள்; உங்கள் மயக்க மருந்தையும் வலி நிவாரணத்தையும் கவனித்துக்கொள்ளும் மருத்துவர் அவர். இந்த அறுவை சிகிச்சை முழு மயக்க மருந்தின் (general anaesthetic) கீழ் செய்யப்படுகிறது. அறுவை சிகிச்சையின்போது நீங்கள் முழுமையாகத் தூக்கத்தில் இருப்பீர்கள். அறுவை சிகிச்சைக்குப் பிந்தைய வலி நிவாரணத்துக்காக, சில நோயாளிகளுக்குப் பகுதி நரம்புத் தடுப்பு ஊசியும் (regional nerve block) போடப்படலாம்; உங்கள் தனிப்பட்ட சூழ்நிலையைப் பொறுத்து மயக்க மருந்து நிபுணர் அன்றைய தினம் முடிவு செய்வார்.
பின்னர் நீங்கள் அறுவை சிகிச்சை அரங்குக்கு அழைத்துச் செல்லப்படுவீர்கள்; அங்கே அறுவை சிகிச்சை செய்யப்படும். அது முடிந்ததும், மீட்புப் பகுதியில் (recovery area) நீங்கள் கண் விழிப்பீர்கள். மயக்க மருந்தின் விளைவு குறையும் வரை அங்கே செவிலியர்கள் உங்களைக் கண்காணிப்பார்கள். உங்கள் நிலை சீரானதும், செய்த சிகிச்சையையும் உங்கள் மீட்சியையும் பொறுத்து, நீங்கள் வார்டுக்குச் செல்வீர்கள் அல்லது வீட்டுக்குச் செல்வீர்கள்.
அறுவை சிகிச்சையில் என்ன செய்யப்படுகிறது
மணிக்கட்டு மூட்டு நுண்ணோக்கி அறுவை சிகிச்சை ஒரு சிறு துளை (keyhole) அறுவை சிகிச்சை. உங்கள் அறுவை சிகிச்சை நிபுணர் மணிக்கட்டைச் சுற்றி சில சிறிய வெட்டுகளைப் போடுகிறார்; மூட்டின் உட்புறத்தை ஒரு திரையில் பார்க்க முடியும்படி, அவற்றில் ஒன்றின் வழியாக ஒரு சிறிய கேமரா செலுத்தப்படுகிறது. அறுவை சிகிச்சையின்போது உங்கள் கை (arm) அசையாமல் பிடித்து வைக்கப்படுகிறது; உங்கள் விரல்கள் மென்மையான விரல்ப் பிடிப்புகளில் (finger traps) மெதுவாகத் தொங்கவிடப்படுகின்றன; மணிக்கட்டின் மீது கொடுக்கப்படும் சீரான இழுவிசை மூட்டை விரித்து, சிகிச்சை செய்வதற்கான இடத்தை உருவாக்குகிறது. காட்சி தெளிவாக இருக்க, உப்பு நீர் மூட்டின் வழியாகப் பாய்கிறது.
கேமரா உள்ளே சென்றதும், உங்கள் அறுவை சிகிச்சை நிபுணர் மூட்டுப் பரப்புகளையும் மென்திசுக்களையும் நெருக்கமாகப் பார்க்க முடியும்; எலும்புகளை மூடியிருக்கும் குருத்தெலும்பு (cartilage), மணிக்கட்டின் சிறிய எலும்புகளை ஒன்றாகப் பிடித்து வைத்திருக்கும் தசைநார்கள் (ligaments) ஆகியவை இதில் அடங்கும். அடுத்து என்ன செய்யப்படுகிறது என்பது, என்ன கண்டறியப்படுகிறது என்பதைப் பொறுத்தது. குருத்தெலும்பு அல்லது எலும்பின் தளர்ந்த துண்டுகளை அகற்ற முடியும். மூட்டின் அழற்சியடைந்த உள்படலத் திசுவை வெட்டி அகற்ற முடியும். ஒரு நீர்க்கட்டியையோ (cyst) தடித்த திசுப் பட்டையையோ சரிசெய்ய முடியும். மணிக்கட்டின் சுண்டு விரல் பக்கத்தில் உள்ள முக்கோணக் குருத்தெலும்பு (triangular cartilage) உட்பட, கிழிந்த தசைநார்களை வெட்டிச் சீராக்கவோ பழுதுபார்க்கவோ முடியும். ஓர் எலும்பு முறிந்திருந்தால், கேமராவின் பார்வையில் அதன் துண்டுகளைத் துல்லியமாக வரிசைப்படுத்தி, அவை குணமாகும்வரை திருகாணிகள் (screws) அல்லது கம்பிகள் (pins) கொண்டு பிடித்து வைக்க முடியும். காயத்துக்கோ முந்தைய அறுவை சிகிச்சைக்கோ பிறகு மணிக்கட்டு விறைத்துப்போயிருந்தால், அதைத் தளர்த்த இறுக்கமான திசுவை விடுவிக்க முடியும்.
இறுதியில், சிறிய வெட்டுகள் தையல்களால் மூடப்படுகின்றன. மணிக்கட்டின் மேல் ஒரு கட்டு (dressing) போடப்படுகிறது; உங்கள் கை (hand) பொதுவாக ஒரு கட்டுத்துணியில் (bandage) அல்லது சிம்பில் (splint) தாங்கப்படுகிறது. கட்டு சுமார் 10 நாட்கள் அப்படியே இருக்கும்; இடைப்பட்ட காலத்தில் காயங்களை எப்படிப் பராமரிப்பது என்பதை நாங்கள் உங்களுக்குச் சொல்வோம்.
அறுவை சிகிச்சைக்குப் பிறகு
மீட்புப் பகுதியில் நீங்கள் கண் விழிப்பீர்கள்; மயக்க மருந்தின் விளைவு குறையும்போது அங்கே செவிலியர்கள் உங்களைக் கவனித்துக்கொள்வார்கள். இது பொதுவாக ஒரே நாள் சிகிச்சை (day case) என்பதால், அதே நாளில் வீட்டுக்குச் செல்வீர்கள் என்று எதிர்பார்க்கலாம்; எப்போதாவது சில நோயாளிகள் ஒரு இரவு தங்குவதும் உண்டு. உங்கள் மணிக்கட்டில் ஒரு கட்டு போடப்பட்டிருக்கும்; உங்கள் கை (hand) ஒரு கட்டுத்துணியில் அல்லது சிம்பில் தாங்கப்பட்டிருக்கலாம். கட்டைச் சுமார் 10 நாட்கள் அப்படியே வைத்திருக்கிறோம்; நாங்கள் சொன்னால் தவிர, அதற்கு முன் அதை அகற்ற வேண்டாம். உங்களைப் பார்க்கும்போது நாங்கள் அதை மாற்றுவோம் அல்லது அகற்றுவோம். நீங்கள் வீட்டுக்குச் செல்வதற்கு முன் உங்களுக்கான வலி நிவாரணம் திட்டமிடப்படுகிறது; அறிவுறுத்தப்பட்டபடி அதை எடுத்துக்கொள்ளுங்கள். உங்களுக்கு நரம்புத் தடுப்பு ஊசி (nerve block) போடப்பட்டிருந்தால், முதல் 24 மணி நேரத்தில் மரத்துப்போதலும் பலவீனமும் எதிர்பார்க்கப்படுபவையே. சுமார் 24 மணி நேரத்தில் அதன் விளைவு நீங்கிய பிறகும் உங்கள் விரல்கள் மரத்துப்போயே இருந்தால், அல்லது அவற்றை அசைக்க முடியாவிட்டால், கிளினிக்கை அழையுங்கள். முதல் 24 மணி நேரம் உங்களுடன் யாராவது தங்கும்படி கேட்டுக்கொள்ளுங்கள். உங்களுக்குக் காய்ச்சல் இருந்தால், காயத்தைச் சுற்றி சிவப்பு பரவினால், அதிலிருந்து நீரோ சீழோ கசிந்தால், அல்லது வலி மருந்துகளை எடுத்தும் வலி தொடர்ந்து மோசமாகிக்கொண்டே போனால், அதே நாளில் கிளினிக்கை அழையுங்கள். உங்கள் விரல்களோ கையோ (hand) வெளிறி, குளிர்ந்து, வெள்ளையாகவோ, நீலமாகவோ, கருமையாகவோ மாறினால், அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்; ஏனெனில் இது இரத்த ஓட்டப் பிரச்சினையாக இருக்கலாம். வீக்கம் தணிய உதவ, ஓய்வெடுக்கும்போது உங்கள் கையை (hand) உயர்த்தி வையுங்கள். பெரும்பாலானோர் அறுவை சிகிச்சை நாளிலிருந்தே வீட்டுக்குள் இயல்பாக நடமாடுகிறார்கள்; நீங்கள் படுக்கையிலேயே ஓய்வெடுக்க வேண்டியதில்லை.
மீட்சி
முதல் சில நாட்களுக்கு உங்கள் மணிக்கட்டு வலியுடனும் வீங்கியும் இருக்கும்; உங்கள் விரல்கள் விறைப்பாக உணரப்படலாம். ஓய்வெடுக்கும்போது உங்கள் கையை (hand) உயர்த்தி வைப்பது வீக்கம் தணிய உதவும். அறிவுறுத்தப்பட்டபடி வலி நிவாரணியை எடுத்துக்கொள்ளுங்கள்; நாட்கள் செல்லச் செல்ல அசௌகரியம் சீராகக் குறையும் என்று எதிர்பார்க்கலாம்.
பெரும்பாலானோர் அறுவை சிகிச்சை நாளிலிருந்தே வீட்டுக்குள் இயல்பாக நடமாடுகிறார்கள். தொடக்கத்தில், கனமான பொருட்களைத் தூக்குவதையும் வாகனம் ஓட்டுவதையும் கவனித்துக்கொள்ள உங்களுக்கு ஒருவர் தேவைப்படுவார். சிம்பு ஏதேனும் இருந்தால் அது அகற்றப்பட்டு, ஸ்டீயரிங் சக்கரத்தை வசதியாகப் பிடிக்க முடிந்ததும், நீங்கள் மீண்டும் வாகனம் ஓட்டலாம்; மேல் அவயவ அறுவை சிகிச்சைக்குப் பிறகு வாகனம் ஓட்டுதல் என்ற எங்கள் பக்கம் இதை மேலும் விரிவாக விளக்குகிறது. கட்டு சுமார் 10 நாட்கள் அப்படியே இருக்கும்; உங்களைப் பார்க்கும்போது காயங்களைச் சரிபார்ப்போம்.
உங்கள் மணிக்கட்டை மீண்டும் அசையவைப்பதில் கை சிகிச்சை (hand therapy) பெரும் பங்கு வகிக்கிறது. உங்கள் மறுவாழ்வு Extend Rehabilitation-இல் Ruby Doolan-உடன் நடைபெறும். Ruby ஒரு கை சிகிச்சையாளர் (hand therapist): அவர் உங்கள் பயிற்சிகளுக்கு வழிகாட்டி, இடையில் உங்களுக்குத் தேவைப்படும் எந்தச் சிம்பையும் செய்து தருவார். தொடக்கத்தில், மென்மையான அசைவிலும் வீக்கத்தைக் கட்டுப்படுத்துவதிலும் கவனம் செலுத்தப்படுகிறது. மணிக்கட்டு அமைதியடைய அடைய, பயிற்சிகள் படிப்படியாகப் பற்றிப் பிடித்தல், தூக்குதல், அன்றாட வேலைகளுக்கு உங்கள் கையை (hand) பயன்படுத்துதல் வரை முன்னேறுகின்றன. மீட்சி படிப்படியான ஒரு முறையைப் பின்பற்றுகிறது; வாரங்கள் செல்லச் செல்ல, மணிக்கட்டுக்கும் விரல்களுக்கும் இடையிலான ஒருங்கிணைந்த அசைவு தொடர்ந்து மேம்படுகிறது.
நீங்கள் எவ்வளவு விரைவாக வேலைக்கோ, விளையாட்டுக்கோ, உடற்பயிற்சிக் கூடத்துக்கோ திரும்புவீர்கள் என்பது, உங்கள் மணிக்கட்டுக்குள் என்ன கண்டறியப்பட்டு பழுதுபார்க்கப்பட்டது என்பதையும், உங்கள் வேலையையும் பொழுதுபோக்குகளையும் பொறுத்தது. உங்கள் கால அளவு மற்றவர்களுடையதிலிருந்து மாறுபடலாம்; ஒவ்வொரு கட்டத்திலும் நாங்களும் உங்கள் சிகிச்சையாளரும் உங்களுக்கு வழிகாட்டுவோம்.
என்ன தவறு நேரலாம்
பெரும்பாலான நோயாளிகள் நன்றாக இருக்கிறார்கள், ஆனால் எப்போதாவது பிரச்சினைகள் ஏற்படலாம். எந்தப் பிரச்சினையையும் முன்கூட்டியே கண்டறிய, உங்கள் அறுவை சிகிச்சை நிபுணரும் குழுவும் உங்களை நெருக்கமாகக் கண்காணிக்கிறார்கள்.
இந்த அறுவை சிகிச்சைக்குப் பிறகு தொற்று ஏற்படுவது அசாதாரணமானது; ஆனால் அது ஏற்பட்டால் முக்கியமானது. உங்களுக்குக் காய்ச்சல் இருந்தால், காயத்தைச் சுற்றி சிவப்பு பரவினால், அல்லது அதிலிருந்து நீரோ சீழோ கசிந்தால், அதே நாளில் கிளினிக்கை அழையுங்கள். வலி மருந்துகளை எடுத்தும் வலி தொடர்ந்து மோசமாகிக்கொண்டே போனால், அப்போதும் அதே நாளில் கிளினிக்கை அழையுங்கள். மணிக்கட்டுக்குள் ஆழமாக ஏற்படும் கடுமையான தொற்றில், சில சமயங்களில் மேலும் ஓர் அறுவை சிகிச்சை தேவைப்படுகிறது; இது மிகவும் அரிது.
அறுவை சிகிச்சையின்போது உங்கள் விரல்களைப் பிடித்து வைக்கும் விரல்ப் பிடிப்புகள் (finger traps), அதன் பிறகு உங்கள் விரல் மூட்டுகளில் வலியை ஏற்படுத்தலாம்; அல்லது ஒரு விரலில் உள்ள மென்திசுவையோ சிறிய நரம்புகளையோ கன்றச் செய்யலாம். பெரும்பாலான சமயங்களில் இது தானாகவே தணிந்துவிடும். ஒரு விரல் இன்னும் வலித்தாலோ வித்தியாசமாக உணரப்பட்டாலோ, உங்கள் அடுத்த மறுபரிசோதனையின்போது அதைத் தெரிவியுங்கள்.
அறுவை சிகிச்சையின்போது மூட்டை நிரப்பப் பயன்படுத்தப்படும் நீர், எப்போதாவது முன்கையின் திசுக்களுக்குள் கசியலாம். முன்கையில் வேகமாக அதிகரிக்கும் வீக்கத்தையும், அதனுடன் இறுக்கத்தையும், தொடர்ந்து அதிகரிக்கும் வலியையும் கவனியுங்கள். இதை நீங்கள் கவனித்தால், உடனடியாகக் கிளினிக்கை அழையுங்கள்.
மணிக்கட்டுக்கு அருகிலுள்ள நரம்புகள் அறுவை சிகிச்சையின்போது எரிச்சலடையலாம் அல்லது காயமடையலாம். சுமார் 24 மணி நேரத்தில் நரம்புத் தடுப்பு ஊசியின் விளைவு நீங்கிய பிறகு, மரத்துப்போன உணர்வையோ, கூச்ச உணர்வையோ, அல்லது வேறுபட்ட உணர்வு தரும் ஒரு தோல் பகுதியையோ நீங்கள் கவனிக்கலாம். நரம்புத் தடுப்பு ஊசிக்குப் பிறகு முதல் 24 மணி நேரத்தில் மரத்துப்போதலும் பலவீனமும் எதிர்பார்க்கப்படுபவையே. மரத்துப்போதல் அதற்கு மேலும் நீடித்தால், அல்லது தடுப்பு ஊசியின் விளைவு நீங்கிய பிறகும் உங்கள் விரல்களையோ கையையோ (hand) அசைக்க முடியாவிட்டால், கிளினிக்கை அழையுங்கள். கிளினிக்கைத் தொடர்பு கொள்ள முடியாவிட்டால், உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
விவரங்கள் வேண்டுமென்றால், இந்தப் பக்கத்தில் உள்ள சிக்கல்கள் அட்டவணை வழக்கமான விகிதங்களைப் பட்டியலிடுகிறது.
எப்போது எங்களை அழைக்க வேண்டும்
பெரும்பாலானோர் எந்தப் பிரச்சினையும் இல்லாமல் குணமடைகிறார்கள்; ஆனால் எதைக் கவனிக்க வேண்டும் என்பதைத் தெரிந்துகொள்வது உதவும். உங்களுக்குக் காய்ச்சல் இருந்தால், காயத்தைச் சுற்றி சிவப்பு பரவினால், அதிலிருந்து நீரோ சீழோ கசிந்தால், அல்லது வலி மருந்துகளை எடுத்தும் வலி தொடர்ந்து மோசமாகிக்கொண்டே போனால், அதே நாளில் கிளினிக்கை அழையுங்கள். சுமார் 24 மணி நேரத்தில் நரம்புத் தடுப்பு ஊசியின் விளைவு நீங்கிய பிறகும் உங்கள் விரல்கள் மரத்துப்போயே இருந்தால், அல்லது அவற்றை அசைக்க முடியாவிட்டால், கிளினிக்கை அழையுங்கள். உங்கள் கெண்டைக்கால் (calf) வீங்கினால் அல்லது வலித்தால், உங்களுக்கு மூச்சுத் திணறல் அல்லது நெஞ்சு வலி ஏற்பட்டால், அல்லது உங்கள் விரல்களோ கையோ (hand) வெளிறி, குளிர்ந்து, வெள்ளையாகவோ, நீலமாகவோ, கருமையாகவோ மாறினால், அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். இவை இரத்த உறைவின் அல்லது இரத்த ஓட்டப் பிரச்சினையின் அறிகுறிகளாக இருக்கலாம். கிளினிக்கைத் தொடர்பு கொள்ள முடியாவிட்டால், உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
இந்த நிலை பற்றி மேலும் எங்கே படிக்கலாம்
இந்தப் பக்கம் அறுவை சிகிச்சையைப் பற்றியது மட்டுமே. இது சிகிச்சையளிக்கும் நிலை, அறுவை சிகிச்சை எப்போது உதவுகிறது, எப்போது உதவுவதில்லை என்பது பற்றி ஆய்வுச் சான்றுகள் என்ன காட்டுகின்றன என்பது உட்பட, மணிக்கட்டு தசைநார்க் காயங்கள் (Wrist Ligament Injuries) பக்கத்தில் விரிவாக விளக்கப்பட்டுள்ளது.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Wrist arthroscopy is a valuable means of diagnosis and treatment of wrist disorders [2].
- Wrist arthroscopy is a safe procedure with a low rate of major and minor complications [3].
- Wrist arthroscopy provides views of and access to the intraarticular spaces of the wrist that are otherwise difficult to achieve without widely open approaches [4].
- The indications for wrist arthroscopy are growing with the description of volar portals for the radiocarpal and scaphotrapezial trapezoid joint [1].
- Volar portals for wrist arthroscopy have certain advantages over the standard dorsal portals for visualizing dorsal capsular structures as well as the palmar aspects of the carpal ligaments [15].
- The routine use of wrist arthroscopy as a replacement or supplement to arthrography cannot be justified [5].
- Wrist arthroscopy may be recommended in cases of chronic wrist pain where the clinical suspicion is strong and the operating team is well-versed with the technique [6].
- Postoperative infection after wrist arthroscopy is uncommon but clinically relevant, particularly in elderly, male patients with systemic comorbidities or undergoing synovectomy [7].
- Arthroscopic arthrolysis is a suitable and promising surgical option for the treatment of wrist stiffness after trauma or surgery [8].
- In a prospective comparative study, the arthroscopically guided procedure for intra-articular distal radius fracture was superior to the conventional open procedure [12].
- Arthroscopic exploration of the extensor carpi ulnaris and its subsheath using standard wrist arthroscopy is relatively simple to perform without the need of a further portal [11].
- Complete avulsion of the distal posterior interosseous nerve during wrist arthroscopy is a possible cause of persistent pain after arthroscopy [10].
- It is questioned whether distal posterior interosseous nerve avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation [10].
- A simple, effective, and cost-efficient solution exists to overcome oversized finger traps for wrist arthroscopy distraction [9].
- The concept to use a physical model for wrist arthroscopy training is well perceived and indicates the potential for continued development [14].
Anatomy & Pathophysiology
Bony Anatomy
- The wrist includes the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones and their proximal and distal articulations and attached ligaments [38].
- The carpus comprises eight ossicles traditionally separated into two rows: the proximal row (scaphoid, lunate, triquetrum, pisiform) and the distal row (trapezium, trapezoid, capitate, hamate) [39].
- The distal radius articular surface has two concave facets for the scaphoid and lunate, separated by the scapholunate ridge [39].
- The sigmoid notch along the ulnar border of the distal radius is a shallow concavity for the articulating ulnar head at the distal radioulnar joint [39].
- The distal ulna is covered with hyaline cartilage on its dorsal, lateral, palmar, and distal surfaces [39].
- The ulnar styloid projects distally, and at its base, the fovea is the insertion for the triangular fibrocartilaginous complex (TFCC) [39].
- The scaphoid's primary vascular supply is a branch of the radial artery at the dorsal ridge, with smaller vessels entering the palmar tubercle to supply the distal 30% [39].
- The lunate has a dorsal and palmar vascular supply in 80% of wrists, while 20% have only a palmar supply [39].
- The capitate head often relies on a retrograde vascular supply [39].
- The pisiform is a sesamoid bone within the flexor carpi ulnaris tendon and serves as the origin for the abductor digiti minimi [39].
- The distal radial articular surface has a double obliquity of 12–15 degrees in the lateral view and 15–20 degrees in the anteroposterior view [43].
- The carpal articular surface has a smaller diameter of curvature than the radius, with stability in the medial and palmar aspects dependent on ligamentous and capsular resistance [43].
- The scaphoid presents a long axis inclined by 45 degrees to the long axis of the radius [43].
- The triquetrum is not in contact with the ulnar head; a fibro-cartilage disc, the triangular ligament, separates the two bones [43].
Ligaments and Soft Tissue Anatomy
- The triangular fibrocartilage complex (TFCC) consists of the central meniscus homolog, dorsal and volar radioulnar ligaments, the floor of the extensor carpi ulnaris tendon sheath, and volar ulnocarpal ligaments [39].
- The TFCC arises from the radial border of the distal radius and inserts into the base of the ulnar styloid and distal ulna through the ligamentum subcruentum [39].
- The dorsal and volar radioulnar ligaments are the primary stabilizers of the distal radioulnar joint [39].
- Only the peripheral 10% to 40% of the volar, ulnar, and dorsal TFCC has a vascular supply [39].
- The scapholunate interosseous ligament is C-shaped in the sagittal plane, with the dorsal third being the thickest and strongest portion [39].
- The volar portion of the lunotriquetral ligament is the thickest [39].
- The extrinsic wrist ligaments include the dorsal intercarpal ligament and the dorsal radiocarpal ligament [39].
- The dorsal radiocarpal ligament originates at the dorsal lip of the distal radius adjacent to Lister's tubercle and inserts into the lunate and triquetrum [39].
- The dorsal intercarpal ligament arises from the triquetrum and attaches to the scaphoid, trapezoid, and capitate [39].
- The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches [41].
- The dorsal intercarpal arch is the largest of the dorsal arches and supplies the distal carpal row and, through anastomoses, the lunate and triquetrum [41].
- The deep palmar arch at the level of the metacarpal bases is consistent and communicates with the dorsal basal metacarpal arch and palmar metacarpal arteries [41].
- The extensor carpi ulnaris tendon rotates around the ulnar head, situated on the ulnar side of the styloid in pronation and on the radial side in supination [44].
- The extensor carpi radialis brevis is the primary wrist extensor with a moment arm of 16.30 mm, compared to 12.50 mm for the extensor carpi radialis longus [44].
Kinematics and Biomechanics
- The wrist functions as a two-joint system linking the hand to the forearm around the highly mobile bones of the proximal carpal row [40].
- With axial loading through the neutral wrist, approximately 80% of forces are transmitted through the distal radius (60% scaphoid facet, 40% lunate facet) and 20% through the distal ulna [39].
- With wrist flexion, 60% of the motion is midcarpal and 40% is radiocarpal [39].
- With wrist extension, 33% of the motion is midcarpal and 66% is radiocarpal [39].
- The proximal carpal row has no muscular or tendinous attachments and is an intercalary segment [39].
- With ulnar deviation, the proximal row extends relative to the forearm/distal row, while with radial deviation, the proximal row flexes [39].
- The dart-thrower's path of radial extension to ulnar flexion defines the transition between flexion and extension of the scaphoid and lunate [40].
- Dart-thrower's motion occurs almost exclusively through the midcarpal joint [40].
Pathophysiology of Wrist Disorders
- Scapholunate advanced collapse (SLAC) wrist pathophysiology involves scapholunate interosseous ligament injury leading to palmar flexion of the scaphoid and extension of the lunate (DISI) [36].
- In SLAC wrist, the radioscaphoid joint becomes incongruous, leading to altered contact forces and arthrosis at the radioscaphoid and capitolunate joints [36].
- The radiolunate joint is typically spared in SLAC wrist due to its spheroid shape [36].
- Ulnocarpal impingement is a degenerative condition resulting from a discrepancy in the relative length of the distal articular surfaces of the radius and ulna (positive ulnar variance) [36].
- Posttraumatic causes of ulnocarpal impingement include distal radius fracture with shortening, Galeazzi or Essex-Lopresti fracture, and childhood epiphyseal plate injuries [36].
- Congenital causes of ulnocarpal impingement include dyschondroplasia (Madelung deformity) and naturally occurring positive ulnar variance [36].
- In rheumatoid arthritis, the classic pattern of wrist deformity involves destabilization of the carpus caused by attenuation of extrinsic wrist ligaments, resulting in ulnar-palmar translocation and wrist supination [49].
- Three main pathophysiological factors drive rheumatoid wrist deformation: cartilage destruction, synovial expansion, and ligamentous laxity [49].
- In juvenile arthritis, uncontrolled joint synovitis stretches essential ligaments and erodes cartilage and bone, resulting in a progressive shift of the carpus ulnarward and volarward [50].
- The dorsal wrist ganglion is the prototype of hand and wrist ganglions, accounting for 60% to 70% of all hand and wrist ganglions [23].
- The main cyst of a dorsal wrist ganglion is usually located directly over the scapholunate ligament [23].
- A small, mucin-filled duct invariably pierces the transverse fibers of the scapholunate ligament, connecting the underlying scapholunate joint with the main ganglion cyst [23].
TFCC Tear Classification
- The Palmer classification categorizes triangular fibrocartilage complex (TFCC) tears into traumatic (class 1) or degenerative (class 2) [24].
- Subtypes within the Palmer classification are based on the specific location within the TFCC [24].
- The class and location of a TFCC tear have important implications for treatment [24].
- Class 1A traumatic TFCC injuries are characterized by central perforation or tear [24].
- Class 1B traumatic TFCC injuries are characterized by ulnar avulsion with or without ulnar styloid fracture [24].
- Class 1C traumatic TFCC injuries are characterized by distal avulsion involving the origins of the ulnolunate and ulnotriquetral ligaments [24].
- Class 1D traumatic TFCC injuries are characterized by radial avulsion involving the dorsal and/or volar radioulnar ligaments [24].
- Class 2A degenerative TFCC tears are characterized by TFCC wear or thinning [24].
- Class 2B degenerative TFCC tears are characterized by Class 2A findings plus lunate and/or ulnar chondromalacia [24].
- Class 2C degenerative TFCC tears are characterized by TFCC perforation plus lunate and/or ulnar chondromalacia [24].
- Class 2D degenerative TFCC tears are characterized by Class 2C findings plus lunotriquetral ligament disruption [24].
- Class 2E degenerative TFCC tears are characterized by Class 2D findings plus ulnocarpal and distal radioulnar joint arthritis [24].
- Arthroscopy is the gold standard for the detection of TFCC tears [24].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting the central portion with a small probe [24].
- The arthroscopic hook test can be used to demonstrate peripheral detachment of the TFCC [24].
- The arthroscopic suction test can show laxity of the TFCC when peripherally scarred in or foveal detachment when the distal radioulnar joint is clinically unstable [24].
Clinical Presentation
Diagnostic Indications
- Indications for diagnostic wrist arthroscopy include chronic wrist pain of uncertain etiology with more than 3 months interval, unresponsive to conservative treatment [21, 37].
- Indications for diagnostic wrist arthroscopy include assessment of acute ligamentous injuries, including scapholunate, lunotriquetral, and triangular fibrocartilage complex (TFCC) injuries [21].
- Indications for diagnostic wrist arthroscopy include evaluation of carpal instability [21].
- Indications for diagnostic wrist arthroscopy include assessment of chondral lesions [21].
- Indications for diagnostic wrist arthroscopy include evaluation of associated soft tissue injury in fracture conditions, including distal radius, scaphoid, ulnar styloid, and other carpal bone fractures [21].
- Indications for diagnostic wrist arthroscopy include assessment of scaphoid healing in delayed union and nonunion [21].
- Indications for diagnostic wrist arthroscopy include staging of posttraumatic arthritis, including scapholunate advanced collapse (SLAC), scaphoid nonunion advanced collapse (SNAC), and distal radius fractures [21].
- Indications for diagnostic wrist arthroscopy include evaluation of monoarticular arthritis and synovial biopsy [21].
- Indications for diagnostic wrist arthroscopy include evaluation of Kienböck disease [21, 37].
- Patients without positive provocative sign on examination seldom yield positive findings at wrist arthroscopy [37].
- Arthroscopic findings need to correlate with clinical examination [37].
Clinical Examination Principles
- The natural inclination to study radiographs or special imaging studies and reports prior to a thorough history and physical examination should be avoided, as this introduces cognitive bias which can affect thinking and decision making [34].
- Physical examination always needs to be preceded by a thorough investigation of the patient’s medical history, with special emphasis on the mechanism of injury and acuity [34].
- The patient should be asked details about the location, duration, and characteristics of any pain, including aggravating and relieving factors and previous treatments [34].
- With chronic problems, it is important to inquire about the patient’s jobs and hobbies, and whether there has been exposure to repetitive stress, vibrating tools, or potentially dangerous instruments [34].
- Elucidating a history of ligamentous laxity or multiple joint instabilities, especially in younger patients presenting with chronic wrist pain, is important [34].
- Such an evaluation should also include an assessment of the patient's stress coping skills [34].
- Swelling is generally moderate in wrist dislocations, and bone displacements may be evident only if the patient is seen immediately after experiencing trauma [34].
- If there has been a delay since the accident, swelling may have increased substantially, making visualization of the displaced bones more difficult [34].
- Skin abrasions, contusions, or ecchymosed areas may be helpful in determining the mechanism of injury and the potential areas of damage [34].
- Range of motion is usually limited by pain in acute injuries, whereas it may be reduced or normal in more chronic cases [34].
- In chronic cases, passive assessment of mobility is valuable not only in determining the presence of abnormal motion or crepitus but also in reproducing the patient’s pain [34].
- The physician should record the motion in the contralateral, uninjured wrist for comparative purposes [34].
- Palpation for areas of maximal tenderness is one of the most useful tools in the diagnosis of wrist pathology, especially in patients with chronic dysfunctions [34].
- In acute dislocations, tenderness is seldom elicited at specific points but rather in a diffuse manner due to extensive soft tissue damage [34].
- Palpation should always be performed in a methodical way, starting from the basal joint of the thumb and proceeding across the proximal carpal row from the scaphoid to the triquetrum and continuing from the hamate back across the distal row and CMC joints [34].
- A careful assessment of neural and vascular status is imperative, with particular attention being paid to the median and ulnar nerves [34].
- The median and ulnar nerves may be injured by direct contusion at the moment of impact, by compression from displaced bones or by swelling within the carpal canal [34].
- A thorough set of provocative maneuvers should be performed to rule out alternative or even concurrent diagnoses [34].
- The examination should begin in a nontender area and proceed rotationally around the carpus, ending at the most symptomatic area [34].
- Bilateral grip and pinch strength are useful to uncover underlying pathology in chronic cases [34].
- Strength may be diminished due to muscle atrophy, pain inhibition, or learned behaviors [34].
- Rapid alternating grip assessment may be helpful in determining voluntary effort [34].
- A local injection of anesthetic to a painful joint or selected tendon sheath may help normalize the dynamometer readings and narrow the diagnostic spectrum [34].
- Sensory testing should always accompany an examination of suspected nerve compression, using threshold or density testing [34].
Specific Provocative Maneuvers
- The ligamentous habitus of a given individual must be assessed using information from the normal wrist because of the wide variation in mobility and laxity [54].
- The Watson test, or scaphoid shift test, is designed to show scaphoid instability [54].
- In the Watson test, the examiner puts one hand on the radial border of the distal forearm with the thumb on the palmar aspect of the scaphoid while moving the patient’s hand to bring about ulnar then radial deviation of the wrist [54].
- The Watson test causes a dorsal subluxation of the scaphoid, accompanied by a painful click [54].
- A positive Watson shift test results when the scaphoid subluxates dorsally out of the scaphoid fossa and relocates when pressure is released [36].
- The ballotment tests, or shear tests, consist of demonstrating abnormal movements between adjacent bones by exerting pressure in opposite directions [54].
- The scapholunate ballotment test involves stressing of the scapholunate joint by volar pressure on the tubercle of the scaphoid and dorsal pressure on the lunate [54].
- If there is any ligament damage, pressure on these two bones causes a painful shearing of the scapholunate joint [54].
- Instability of the lunotriquetral joint can be demonstrated by Reagan’s test, which involves dorsal pressure on the lunate and volar pressure on the triquetrum [54].
- The midcarpal joint "pivot shift" test consists of supinating and volar subluxing the distal row of the carpus [54].
- The pivot shift test is performed by placing the patient elbow upon a firm surface, holding the elbow at 90 degrees, putting the hand into a fully supine position and holding the distal forearm firmly [54].
- The hand is moved into full radial deviation and then the ulnar side of the carpus is forced into further supination and a volar subluxed position [54].
- The wrist must not be flexed during the pivot shift test [54].
- The hand, still with the displacing force applied, is gently moved from radial to full ulnar deviation [54].
- The normal wrist will notch into a less supinated position as the head of the capitate engages the lunate, because of the restraint of the anterior capsule and triquetrolunate interosseous ligaments [54].
- Rupture, attenuation or excess laxity allow the capitate to drift out of the lunate [54].
- Triquetral hamate instability is demonstrated with the wrist straight with ulnar deviation [54].
- After a range of about 20 degrees, triquetral hamate instability produces a firm block [54].
- If one forces a sharp click accompanied by discrete posterior movement of the wrist, the proximal row of the carpus has moved from the VISI position to that of DISI, thus allowing a complete ulnar deviation of the wrist joint [54].
- The radio-carpal and midcarpal joint anteroposterior drawer test involves one hand holding the patient’s hand by the metacarpals to apply axial traction while the other hand stabilizes the patient’s forearm [54].
- While holding this traction, anteroposterior force is applied and a drawer is elicited at the radio-carpal, then the midcarpal joint [54].
- The ability to push the midcarpal joint volarward is present to a varying degree in most normal asymptomatic patients [54].
- A marked drawer test is a sign of congenital laxity [54].
- An exaggeration of the normal ulna head prominence is seen in dorsal subluxation or articular effusion [54].
- The prominence of the ulna head may be temporarily reduced by direct pressure over the ulna head [54].
- In the rheumatoid wrist, the ulna head prominence is further exaggerated by a supination deformity of the carpus [54].
- If the hand is held in full ulnar deviation and the ulna head is held forward by the examiner’s thumb, significant pain may be precipitated by this movement alone, suggesting DRUJ pathology [54].
- Pain precipitated by pronosupination while the ulna head is pressed volarward and the pisiform pressed dorsally is usually indicative of some form of ulnar impingement or abutment syndrome [54].
- The diagnosis of DRUJ arthrosis is confirmed by improvement in rotation and grip strength with injection of a local anesthetic into the DRUJ [36].
- Clinical findings for DRUJ arthrosis include pain that increases with proximal rotation of the forearm and compression of the ulna against the radius [36].
- Symptoms of ulnocarpal impingement include pain on the dorsal side of the DRUJ and an intermittent clicking sensation [36].
- Pain in ulnocarpal impingement is exacerbated by forearm rotation and ulnar deviation [36].
- Pain in ulnocarpal impingement occurs with axial loading of the ulnar side of the wrist [36].
- Pain in ulnocarpal impingement occurs with dorsal and palmar displacement of the distal ulna, with the wrist in ulnar deviation (positive ballottement test) [36].
- Symptoms of SLAC wrist include reduced grip and pinch strength [36].
- Symptoms of SLAC wrist include stiffness with extension and radial deviation [36].
- Symptoms of SLAC wrist include localized tenderness at the radioscaphoid articulation [36].
- Symptoms of SLAC wrist include decreased wrist motion on extension and radial deviation [36].
Imaging and Preoperative Evaluation
- After the history and physical examination, radiographic evaluation is helpful in determining the diagnosis, prognosis, and management of wrist problems [32].
- MRI should be added for evaluation of the triangular fibrocartilage; the distal radioulnar joint (DRUJ); and vascularity of the various carpal bones, extrinsic ligaments, joint surfaces, and surrounding soft tissues to confirm clinical suspicion and correlate with physical examination findings [32].
- A high rate of false-positive findings on MR images of normal subjects has been reported [32].
- A dedicated wrist coil provides enhanced resolution of wrist structures [32].
- Routine radiographic series for the wrist consist of four views: posteroanterior, lateral, oblique, and ulnar-deviated posteroanterior scaphoid view [32].
- Spot views of the carpal bones for detail (carpal tunnel view) are a useful radiographic technique [32].
- Fluoroscopic spot views of the wrist are a useful radiographic technique [32].
- A series of views for instability includes anteroposterior clenched fist, posteroanterior in neutral, radial, and ulnar deviation, lateral in neutral and full flexion and extension, semipronated oblique 30 degrees from the posteroanterior, and semisupinated oblique 30 degrees from the lateral [32].
- Diagnostic ultrasound is a useful radiographic technique for evaluating a painful wrist [32].
- Cine or video fluoroscopy is a useful radiographic technique for evaluating a painful wrist [32].
- Bone scanning is a useful radiographic technique for evaluating a painful wrist [32].
- Arthrography of the wrist (triple injection when indicated) is a useful radiographic technique [32].
- CT is a useful radiographic technique for evaluating a painful wrist [32].
- MRI is a useful radiographic technique for evaluating a painful wrist [32].
- The authors do not feel that the routine use of wrist arthroscopy as a replacement or supplement to arthrography can be justified [5].
- Perform repeated clinical examinations for chronic wrist pain as part of preoperative evaluation [37].
Investigations
Diagnostic Role and Indications
- Arthroscopic assessment of intercarpal ligament injuries and instability is considered by many the “gold standard” for evaluation of these conditions [31].
- Arthroscopy is the gold standard for detection of triangular fibrocartilage complex (TFCC) tears [24].
- Arthroscopy has been found to be more accurate than arthrography in identifying the location and size of triangular fibrocartilage and interosseous ligament injuries [31].
- Arthroscopy is more accurate than triple-injection cinearthrography in detecting tears of the dorsal sensory branch of the ulnar nerve during arthroscopic repair of the triangular fibrocartilage [31].
- Indications for wrist arthroscopy include the evaluation of ligamentous injuries, examination of joint articular surfaces, removal of loose bodies, biopsy of synovium, irrigation and debridement of joints, and confirmation and supplementation of wrist arthrography [31].
Arthroscopic Tests
Imaging Modalities
- MRI should be added for evaluation of the triangular fibrocartilage, the distal radioulnar joint, and vascularity of the various carpal bones, extrinsic ligaments, joint surfaces, and surrounding soft tissues to confirm clinical suspicion and correlate with physical examination findings [32].
- With proper technique, injuries to the triangular fibrocartilage complex can be demonstrated with MRI [46].
- Perforations in the triangular fibrocartilage complex appear as linear defects or gaps filled with hyperintense fluid on coronal gradient-echo or T2-weighted pulse sequences [46].
- The addition of arthrographic contrast improves the visualization of carpal ligaments on MR images [46].
- MRI is useful in detecting additional marrow abnormalities in osteonecrosis, as seen in the lunate in Kienböck disease or in the scaphoid after fracture [46].
- Asymmetry of marrow signal in proximal and distal fragments of a fractured scaphoid is suggestive of proximal pole ischemia [46].
- MRI has a limited role in the evaluation of carpal tunnel syndrome, which remains a clinical diagnosis [46].
- Axial imaging with T2 weighting can clearly display masses within the confines of the carpal tunnel, as well as edema and swelling of the median nerve [46].
- MRI provides earlier detection of synovitis and erosive bone changes associated with rheumatoid arthritis than do radiographs [46].
- MRI has an expanding role in the evaluation of inflammatory arthritis [46].
- MRI has gained a greater role in the evaluation of acute wrist trauma, where bone marrow edema may reveal fractures of the carpal bones or distal radius that are radiographically occult [46].
- MRI is controversial for TFCC pathology, but newer innovations suggest value in detection and localization of TFCC pathology [24].
Radiographic Techniques
- Spot views of the carpal bones are used for detail, including the carpal tunnel view [32].
- Arthrography of the wrist, including triple injection when indicated, is a useful radiographic technique [32].
Preoperative Assessment
- The natural inclination to study radiographs or special imaging studies and reports prior to a thorough history and physical examination should be avoided, as this introduces cognitive bias [34].
Treatment
Indications and Diagnostic Role
Operative Technique and Setup
- The patient is positioned supine on the operating table with a traction device applied to distract the wrist joint [21].
- Traction force of 10 to 12 lb is applied through plastic finger traps over the index and middle fingers, or more preferably, the middle three fingers [21].
- Overdistraction or use of wire finger traps may cause postoperative finger joint pain or localized contusion to soft tissue or digital nerves [21].
- Nylon finger traps are more comfortable and atraumatic to the patient, especially in awake cases [21].
- For arthroscopy over the scaphotrapeziotrapezoid joint, an additional trap and traction can be put on the thumb [21].
- When an overhead traction boom is employed, countertraction is provided by securing the arm to the hand table, and the operated limb is draped free up to the elbow level [21].
- When a dedicated wrist traction device is being used, the limb is draped up to the axilla level and the lower arm is wrapped to the basal plate of the device close to the elbow level [21].
- A traction device should be sterilizable and allow flexible positioning of the wrist intraoperatively in varying degrees of extension, flexion, and radial and ulnar deviation [21].
- Tourniquet use is optional and is often unnecessary, especially for diagnostic and uncomplicated therapeutic procedures performed under local anesthesia without sedation [21].
- Joint visibility is maintained by saline inflow, as the small volume of the wrist makes fluid distention rather impractical compared to the knee or shoulder joint [21].
- The main maneuver in creating the working space is controlled traction, while saline maintains a clear view by removing intraarticular debris through the outflow portal [21].
- The hydrostatic pressure generated by saline irrigation serves a hemostatic role when arthroscopy is performed without a tourniquet [21].
- Continuous irrigation is achieved with a 3 L bag of normal saline suspended 1.5 m above the patient and instilled under gravity [21].
- Caution should be used to avoid extravasation of fluid that may lead to compartment syndrome [21].
Therapeutic Procedures
- In the treatment of central triangular fibrocartilage complex tears, partial excision using the holmium:Yttrium-aluminum-garnet laser has been performed over a five-year experience [13].
- Arthroscopically guided procedure for intra-articular distal radius fracture was found to be superior to the conventional open procedure based on a prospective comparative study [12].
- Ablative procedures in wrist arthroscopy include TFCC debridement, debridement of ligament tears, synovectomy, wrist ganglionectomy, removal of loose body, capsulotomy/capsulectomy, lavage, and arthrolysis [21].
- Ablative bony procedures in wrist arthroscopy include scaphoidectomy, radial styloidectomy, wafer procedure, proximal row carpectomy, and proximal hamate excision [21].
- Ablative cartilage procedures in wrist arthroscopy include debridement of chondral and osteochondral lesions [21].
- Reparative soft tissue procedures in wrist arthroscopy include peripheral TFCC tear repair, TFCC foveal avulsion repair, scapholunate ligament injury repair, and lunotriquetral ligament injury repair [21].
- Reparative bony tissue procedures in wrist arthroscopy include arthroscopic-assisted reduction and internal fixation (ARIF) for distal radius fracture and scaphoid fracture [21].
- Reparative cartilage procedures in wrist arthroscopy include drill/abrasion chondroplasty [21].
- Reconstructive soft tissue procedures in wrist arthroscopy include arthroscopic TFCC reconstruction with tendon graft and arthroscopic-assisted scapholunate ligament reconstruction with tendon graft [21].
- Reconstructive bony procedures in wrist arthroscopy include arthroscopic bone grafting for scaphoid nonunion, limited carpal fusion, intraosseous bone cyst, and intraosseous ganglion [21].
- Reconstructive cartilage tissue procedures in wrist arthroscopy include osteochondral grafting [21].
Complications and Safety
- DPIN avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation [10].
Complications
- Overdistraction during wrist arthroscopy distraction can cause postoperative finger joint pain [21].
- Use of wire finger traps for wrist arthroscopy distraction may cause localized contusion to soft tissue or digital nerves [21].
- Nylon finger traps are more comfortable and atraumatic to the patient than other traction methods, especially in awake cases [21].
- Extravasation of fluid during wrist arthroscopy may lead to compartment syndrome [21].
- Postoperative infection after wrist arthroscopy is uncommon but clinically relevant [7].
- Postoperative infection risk after wrist arthroscopy is particularly elevated in elderly, male patients with systemic comorbidities or those undergoing synovectomy [7].
- Complete avulsion of the distal posterior interosseous nerve can occur during wrist arthroscopy [10].
- Distal posterior interosseous nerve avulsion is a possible cause of persistent pain after wrist arthroscopy [10].
- Inadvertent damage to the dorsal branch of the ulnar nerve can be avoided by placing the 6R portal in the proximal fifth (19%) of a line drawn from the ulnar styloid to the fourth dorsal web space [22].
Recovery
- Postoperative infection risk is particularly relevant in elderly, male patients with systemic comorbidities or undergoing synovectomy [7].
Key Evidence
- [Paper] The indications for wrist arthroscopy are growing with the description of volar portals for the radiocarpal and scaphotrapezial trapezoid joint. [1] (10.1097/00130911-200603000-00007)
- [L4] From these data it appears that wrist arthroscopy is a valuable means of diagnosis and treatment of wrist disorders. [2] (10.1016/s0266-7681(96)80100-8)
- [L4] Wrist arthroscopy is a safe procedure with a low rate of major and minor complications. [3] (10.1016/j.jhsa.2003.12.020)
- [L5] Wrist arthroscopy can be a useful tool in one’s armamentarium in the diagnosis and treatment of wrist pathology, providing views of and access to the intraarticular spaces of the wrist that are otherwise difficult to achieve without widely open approaches. [4] (10.1016/j.eats.2024.103223)
- [L4] The authors do not feel that the routine use of wrist arthroscopy as a replacement or supplement to arthrography can be justified. [5] (10.1016/0266-7681(94)90256-9)
- [L4] It may be recommended in cases of chronic wrist pain where the clinical suspicion is strong and the operating team is well-versed with the technique. [6] (10.1177/1558944716660555ig)
- [L3] Postoperative infection after wrist arthroscopy is uncommon but clinically relevant, particularly in elderly, male patients with systemic comorbidities or undergoing synovectomy. [7] (10.1016/j.otsr.2026.104771)
- [L4] Arthroscopic arthrolysis is a suitable and promising surgical option for the treatment of wrist stiffness after trauma or surgery. [8] (10.1016/s0363-5023(03)80309-x)
- [L5] We present a simple, effective, and cost-efficient solution to overcome oversized finger traps for wrist arthroscopy distraction. [9] (10.1016/j.eats.2025.103662)
- [L5] An alternate question is whether DPIN avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation. [10] (10.1053/jhsu.1999.0240)
- [L5] They found this arthroscopic exploration relatively simple to perform without the need of a further portal. [11] (10.1177/1753193420948404)
- [L3] On the basis of our prospective comparative study, we found that the arthroscopically guided procedure was superior to the conventional open procedure. [12] (10.1016/j.jhsb.2006.03.177)
- [L4] [13] (10.1053/jhsu.2001.20157)
- [Paper] The concept to use a physical model for wrist arthroscopy training is well perceived, and indicates the potential for continued development. [14] (10.1016/j.main.2015.10.087)
- [L5] Volar portals for wrist arthroscopy have certain advantages over the standard dorsal portals for visualizing dorsal capsular structures as well as the palmar aspects of the carpal ligaments. [15] (10.1097/00130911-200412000-00006)
- [L5] Inadvertent damage to the dorsal branch of the ulnar nerve can be avoided if care is taken to place the 6R portal in the ‘‘safe area’’ found within the proximal fifth (19%) of a line drawn from the ulnar styloid to the fourth dorsal web space. [22] (10.1016/j.jhsb.2005.10.005)
References
[1] Uses and Abuses of Wrist Arthroscopy. Techniques in Hand & Upper Extremity Surgery. 2006. DOI: 10.1097/00130911-200603000-00007
[2] The Value of Wrist Arthroscopy. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(96)80100-8
[3] Complications of wrist arthroscopy. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.12.020
[4] Wrist Arthroscopy: Positioning, Portal Placement, and Diagnostic Evaluation. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103223
[5] Wrist Arthroscopy. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90256-9
[6] Wrist Arthroscopy as a Diagnostic Tool in Chronic Wrist Pain. HAND. 2016. DOI: 10.1177/1558944716660555ig
[7] Incidence and risk factors of postoperative infection after wrist arthroscopy: an 11-year nationwide population-based cohort study in South Korea. Orthopaedics & Traumatology: Surgery & Research. 2026. DOI: 10.1016/j.otsr.2026.104771
[8] Arthroscopic wrist arthrolysis. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80309-x
[9] Tip to Overcome Oversized Finger Traps in Wrist Arthroscopy Distraction. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2025.103662
[10] Complete avulsion of the distal posterior interosseous nerve during wrist arthroscopy: A possible cause of persistent pain after arthroscopy. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0240
[11] Visualization of the extensor carpi ulnaris and its subsheath using standard wrist arthroscopy. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420948404
[12] 2.3 Wrist arthroscopy in intra-articular distal radius fracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2006. DOI: 10.1016/j.jhsb.2006.03.177
[13] The holmium:Yttrium-aluminum-garnet laser in wrist arthroscopy: A five-year experience in the treatment of central triangular fibrocartilage complex tears by partial excision. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.20157
[14] Development of a wrist arthroscopy simulator. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2015.10.087
[15] Clinical Applications of Volar Portals in Wrist Arthroscopy. Techniques in Hand & Upper Extremity Surgery. 2004. DOI: 10.1097/00130911-200412000-00006
[21] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > SURGICAL TECHNIQUE FOR DIAGNOSTIC ARTHROSCOPY > Setup.
[22] The Anatomy of the Dorsal Cutaneous Branch of the Ulnar Nerve – a Safe Zone for Positioning of the 6r Portal in Wrist Arthroscopy. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.10.005
[23] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Dorsal Wrist Ganglion.
[24] Miller S Review Of Orthopaedics. DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[31] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ARTHROSCOPY OF THE WRIST.
[32] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > RADIOGRAPHIC TECHNIQUES.
[34] Green S Operative Hand Surgery. Diagnosis and Treatment > Assessment of the Symptomatic Wrist.
[36] Aaos Comprehensive Orthopaedic Review 3. Arthritides of the Hand and Wrist* > IV. Posttraumatic Arthritis.
[37] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Diagnostic Wrist Arthroscopy.
[38] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[39] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[40] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[41] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[43] Exam Of The Hand Wrist 2Ed. 1.2 SKELETON OF THE WRIST.
[44] Exam Of The Hand Wrist 2Ed. Extension of the wrist > Muscles of wrist extension.
[46] Campbell S Operative Orthopaedics 4 Volume Set. WRIST AND ELBOW.
[49] Green S Operative Hand Surgery. WRIST INVOLVEMENT IN RA.
[50] Tachdjian S Pediatric Orthopaedics From The Texas Scottish Rite Hospital For Children E Book. Wrist Involvement.
[54] Exam Of The Hand Wrist 2Ed. Examination.