Patients › Shoulder
தோள்பட்டைக்கு அருகிலுள்ள மேற்கை எலும்பு முறிவு (Proximal Humerus Fracture)
Proximal humerus fractures — Neer classification, sling management, and surgical options.
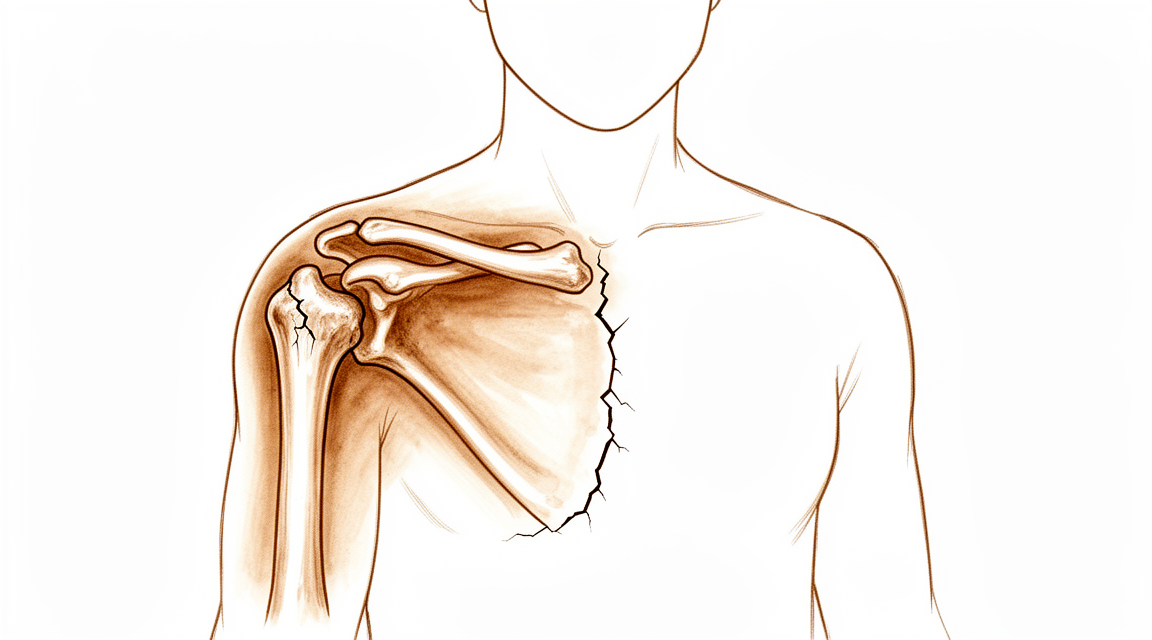
நீங்கள் உணர்வது
தோள்பட்டைக்கு அருகிலுள்ள மேற்கை எலும்பு முறிவு (proximal humerus fracture) என்பது, தோள்பட்டைக்குச் சற்றுக் கீழே, கை (arm) எலும்பின் மேல்பகுதியில் ஏற்படும் முறிவு. இது பொதுவாகக் கீழே விழும்போது ஏற்படுகிறது; பெரும்பாலும் தோள்பட்டையின் மீதோ நீட்டிய கையின் மீதோ விழும்போது. இந்த முறிவு காலப்போக்கில் மெதுவாக அல்லாமல், திடீரென ஏற்படுகிறது.
நீங்கள் முதலில் உணர்வது, கையின் மேல்பகுதியிலும் தோள்பட்டையிலும் வலி. அது பெரும்பாலும் நீங்கள் விழுந்த கணத்திலேயே தொடங்குகிறது. அடுத்த ஓரிரு நாட்களில் தோள்பட்டை வீங்கி, கருநீலம் (bruising) தோன்றலாம்; அந்தக் கருநீலம் கையின் கீழ்நோக்கிப் பரவலாம். முறிந்த துண்டுகள் இடம் நகர்ந்திருந்தால், உங்கள் கை வடிவம் மாறியதுபோலத் தோன்றலாம். கையை அசைக்க நீங்கள் விரும்பமாட்டீர்கள்; எளிய வேலைகளும் கடினமாகின்றன: உடை அணிவது, அலமாரிக்குள் கையை நீட்டுவது, கடைப் பையைத் தூக்கிச் செல்வது, அல்லது படுக்கையில் அந்தப் பக்கமாகப் புரண்டு படுப்பது.
ஆரம்ப நாட்களில் வலி பெரும்பாலும் இரவில் அதிகமாக இருக்கும்; வசதியான நிலையைக் கண்டுபிடிப்பது கடினமாக இருக்கலாம். தொடக்கத்தில் கையை அசைப்பது வலிக்கும். முதல் சில வாரங்களில், எலும்பு குணமடையத் தொடங்கும்போது, வலி பொதுவாகப் படிப்படியாகத் தணிகிறது. தோள்பட்டை அசையாமல் இருந்ததால், வலி தணியும் நேரத்தில் அது பெரும்பாலும் விறைப்பாக உணரப்படுகிறது.
இந்த முறிவுகளில் பெரும்பாலானவை 70 வயதுக்கு மேற்பட்ட பெண்களில் ஏற்படுகின்றன; வயதாவதால் மெலிந்து எளிதில் உடையக்கூடியதாக மாறிய எலும்புகளில் இவை பொதுவானவை (இது எலும்புத் துளைநோய் — osteoporosis — எனப்படுகிறது). இதற்கு முன் உங்களுக்கு ஓர் எலும்பு முறிந்திருந்தால், அல்லது இந்த எலும்பு முறிந்தால், எதிர்காலத்தில் மற்றொரு முறிவு ஏற்படும் வாய்ப்பு அதிகம் என்பதை அது சுட்டிக்காட்டலாம். அதை உங்கள் பொது மருத்துவரிடம் (GP) தெரிவிப்பது பயனுள்ளது; அவர் உங்கள் எலும்பு ஆரோக்கியத்தைப் பரிசோதிக்க முடியும்.
சில முறிவுகள் பல துண்டுகளாக இருக்கின்றன; சில இடம் நகர்ந்துவிடுகின்றன. உங்கள் அறுவை சிகிச்சை நிபுணர், உடல் பரிசோதனை மற்றும் எக்ஸ்-ரேக்கள் மூலம் — சில நேரங்களில் CT ஸ்கேனுடன் — முறிவின் வடிவத்தைக் கண்டறிகிறார்; CT ஸ்கேன் என்பது எலும்பை இன்னும் தெளிவாகக் காட்டும் ஒரு விரிவான ஸ்கேன். இந்த முறிவுகளில் பெரும்பாலானவை அறுவை சிகிச்சை இல்லாமலேயே குணமடைகின்றன; இவ்வாறு சிகிச்சையளிக்கப்படுவனவற்றில் 90%-க்கும் மேற்பட்டவற்றில் எலும்பு ஒன்றுசேர்கிறது.
அதே நாளில் சிகிச்சை தேவைப்படும் சில அறிகுறிகளைக் கவனியுங்கள். உங்கள் கையோ (hand) விரல்களோ வெளிறி, குளிர்ந்து, வெள்ளையாக அல்லது நீலமாக மாறினால், அல்லது காயத்துக்குப் பிறகு கையில் (arm) திடீரென உணர்வு அல்லது அசைவு இழப்பு ஏற்பட்டால், அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். முறிவின் மேல் தோல் கிழிந்திருந்தாலோ, எலும்பு வெளியே தெரிந்தாலோ இதுவே பொருந்தும்.
உண்மையில் என்ன நடக்கிறது
உங்கள் கை எலும்பின் மேல்பகுதி, உங்கள் தோள்பட்டை எலும்பில் (shoulder blade) உள்ள ஆழமற்ற ஒரு குழியில் அமரும் ஓர் உருண்டையின் வடிவில் உள்ளது. அந்தக் குழி சிறியது — உருண்டையின் அளவில் சுமார் மூன்றில் ஒரு பங்கு; எனவே மூட்டு சுதந்திரமாக அசைகிறது, ஆனால் அதை நிலையாகப் பிடித்து வைக்க மென்திசுக்களையே நம்பியிருக்கிறது. நான்கு தசைநாண்கள் உருண்டையைச் சுற்றிப் படர்ந்து, பெரிய தசைகள் கையைத் தூக்கும்போது அதைக் கீழ்நோக்கி அழுத்திப் பிடிக்கின்றன. எலும்பு முறியும்போது, அந்தக் கூட்டுச் செயல்பாடு சீர்குலைகிறது.
விழும்போது ஏற்படும் விசை கை எலும்பைக் குழிக்கு எதிராகத் தள்ளுவதால் பொதுவாக இந்த முறிவு ஏற்படுகிறது; அந்தக் குழி, அதைச் சுற்றியுள்ள எலும்பைவிடக் கடினமானது. பட்டடைக்கல்லின் (anvil) மீது அடிக்கும் சுத்தியல் போல எலும்பு செயல்பட்டு, அது மிகவும் பலவீனமாக உள்ள இடத்தில் முறிகிறது. பிறகு, முறிந்த துண்டுகள் அவற்றுடன் இணைந்துள்ள தசைநாண்களால் இழுக்கப்படுகின்றன. ஒவ்வொரு தசைநாணும் தன் துண்டைத் தன் சொந்தத் திசையில் இழுக்கிறது; அதனால்தான் சில முறிவுகள் இடம் நகர்ந்த பல துண்டுகளாக முடிகின்றன.
துண்டுகள் இருக்க வேண்டிய இடத்துக்கு அருகிலேயே இருந்தாலும்கூட, சில காலம் தோள்பட்டை இயல்பாகச் செயல்படுவது நின்றுவிடுகிறது. மூட்டைச் சுற்றியுள்ள தசைநாண்கள் செயல்பட, அவை வழுவழுப்பாக வழுக்கிச் செல்லும் பரப்புகள் தேவை; வீக்கமும் முறிந்த எலும்பும் அதைச் சீர்குலைக்கின்றன. தசைநாண் எலும்பின் மீது வழுக்கிச் செல்ல உதவும் உள்வரிப் பைகள் (lining sacs) தடித்து வடுவாகலாம்; தோள்பட்டை விறைப்பதற்கு இது ஒரு காரணம். உங்கள் அறுவை சிகிச்சை நிபுணர் பாதுகாப்பானது என்று சொன்னவுடன், கையை ஆரம்பத்திலேயே அசைப்பது அந்த வடு உருவாவதைக் கட்டுப்படுத்த உதவுகிறது.
உடலில் எங்கும் முறிந்த எலும்பு குணமடைவது போலவே, இதுவும் மீண்டும் ஒன்றாகப் பின்னிக்கொண்டு குணமடைகிறது. முறிவின் குறுக்கே புதிய எலும்பு உருவாகி, வாரங்கள் முதல் மாதங்கள் வரையிலான காலத்தில் உறுதியாகிறது. ஒரு தசைநாண் ஓர் எலும்புத் துண்டுடன் சேர்ந்து பிய்ந்து வந்திருந்தால், அந்தத் துண்டு மீண்டும் தன் இடத்தில் ஒன்றுசேரும்போது தசைநாணும் குணமடைகிறது. சற்றுக் கோணலாகக் குணமடைவதைத் தோள்பட்டை பொறுத்துக்கொள்கிறது; ஏனெனில் அது எடை தாங்கும் மூட்டு அல்ல, சுற்றியுள்ள தசைகளே வேலையின் பெரும்பகுதியைச் செய்கின்றன.
சில முறிவு வடிவங்கள் நிலைமையை மாற்றுகின்றன. உருண்டையின் அடிப்பகுதியிலேயே ஏற்படும் முறிவு அதன் இரத்த ஓட்டத்தைத் துண்டித்துவிடலாம்; இது குணமடைதலைப் பாதிக்கிறது. அதைவிடக் கீழே ஏற்படும் முறிவுகள் பொதுவாக இரத்த ஓட்டத்தைப் பாதிப்பதில்லை. துண்டுகள் மோசமாக இடம் நகர்ந்திருந்தாலோ நிலையற்றவையாக (unstable) இருந்தாலோ, அல்லது உருண்டையே உடைந்து பிளந்திருந்தாலோ, அறுவை சிகிச்சை பரிசீலிக்கப்படுவதற்கான வாய்ப்பு அதிகம்.
இதற்கு நாங்கள் என்ன செய்ய முடியும்
மாட்டர் பிரைவேட் மருத்துவமனை ரொக்ஹாம்ப்டனில் (Mater Private Hospital Rockhampton) மேல் அவயவ அறுவை சிகிச்சை நிபுணரான டாக்டர் கியரன் ஹிர்பரா, உங்களுக்கு ஏற்பட்ட குறிப்பிட்ட காயத்திற்கு ஏற்றவாறு சிகிச்சையை அமைக்கிறார். சில முறிவுகள் அறுவை சிகிச்சை இல்லாமலேயே குணமடைகின்றன; மற்றவற்றுக்குக் காயம் ஏற்பட்ட சிறிது காலத்திலேயே அறுவை சிகிச்சை தேவைப்படுகிறது; எனவே தாமதமின்றி மதிப்பீடு செய்துகொள்வது முக்கியம். எலும்பு எத்தனை துண்டுகளாக உள்ளது, அவை எவ்வளவு தூரம் இடம் நகர்ந்துள்ளன, முறிவு நிலையானதா (stable), உங்கள் கை என்ன செய்ய வேண்டியுள்ளது என்பவற்றை நாங்கள் பார்க்கிறோம். உங்கள் சொந்த உடல்நலமும், எவ்வளவு வலியைப் பொறுத்துக்கொள்ள நீங்கள் தயாராக இருக்கிறீர்கள் என்பதும்கூட அந்த முடிவின் ஒரு பகுதி.
இந்த முறிவுகளில் பல — துண்டுகள் இடம் நகர்ந்த சிலவும் உட்பட — அறுவை சிகிச்சை இல்லாமலேயே சிகிச்சையளிக்கப்படுகின்றன. அறுவை சிகிச்சையற்ற பராமரிப்பு என்றால், எலும்பு ஒன்றுசேரும்போது கையை அசையாமல் வைத்திருக்க ஒரு கைத்தாங்கி (sling) — சிம்பு (splint) அல்லது மாவுக்கட்டு (cast) அல்ல. இது உங்களைத் தனியே விட்டுவிடுவது அல்ல: நாங்கள் உங்களைத் தவறாமல் சந்தித்து, முறிவு ஏற்றுக்கொள்ளத்தக்க நிலையில் குணமடைகிறதா என்பதை உறுதிப்படுத்த மீண்டும் எக்ஸ்-ரேக்கள் மூலம் அதைச் சரிபார்க்கிறோம். எலும்பு தயாராகிவிட்டது என்று உங்கள் அறுவை சிகிச்சை நிபுணர் சொன்னவுடன், ஒரு பிசியோதெரபிஸ்ட் படிப்படியாக நீங்கள் மீண்டும் அசைவுக்குத் திரும்ப வழிகாட்டுகிறார்: முதலில் உதவியுடன் கூடிய மென்மையான அசைவு, பிறகு எலும்பு உறுதியாகும்போது நீங்களே செய்யும் செயலூக்க அசைவு (active movement). இவ்வாறு சிகிச்சையளிக்கப்படுவனவற்றில் பத்தில் ஒன்பதுக்கும் மேற்பட்டவற்றில் எலும்பு ஒன்றுசேர்கிறது; உறுதியாகக் குணமடைய ஆகும் சராசரிக் காலம் 14 வாரங்கள். எலும்பு மெதுவாக ஒன்றுசேர அல்லது ஒன்றுசேராமல் போக 7% வாய்ப்பு உள்ளது; இவ்வாறு சிகிச்சையளிக்கப்படுபவர்களில் சுமார் 5.6% பேருக்கு இறுதியில் அறுவை சிகிச்சை தேவைப்படுகிறது.
சில காயங்களுக்கு, அறுவை சிகிச்சை தொடக்கத்திலிருந்தே பரிந்துரைக்கப்படுகிறது: மோசமாக இடம் நகர்ந்த, நிலையற்ற முறிவுகள்; மூட்டின் உருண்டையே உடைந்து பிளந்த முறிவுகள்; முறிவுடன் மூட்டும் இடம்விலகி வெளியே வந்துவிட்ட முறிவு-இடப்பெயர்வுகள் (fracture-dislocations); கை அதிகம் செய்ய வேண்டியுள்ள இளைய அல்லது அதிகச் சுறுசுறுப்பான நபர்களின் காயங்கள். அறுவை சிகிச்சை, குணமடையும்போது துண்டுகளைச் சிறந்த நிலையில் பிடித்து வைப்பதை நோக்கமாகக் கொண்டது; அல்லது, வயதான நோயாளிகளில் சில கடுமையான முறிவு வடிவங்களுக்கு, மூட்டை மாற்றுவதை நோக்கமாகக் கொண்டது. சில சூழ்நிலைகளில் இந்தத் தேர்வு உண்மையிலேயே பகிர்ந்து எடுக்கப்படும் முடிவு: அறுவை சிகிச்சையற்ற பராமரிப்பு சாத்தியமாக இருக்கலாம்; ஆனால் வழியில் ஏற்படும் வலியோ, தோள்பட்டையின் இறுதி நிலையோ உங்களுக்கு ஏற்றுக்கொள்ளத்தக்கதாக இல்லாமல் போகலாம். எதுவும் முடிவு செய்யப்படுவதற்கு முன், இரண்டு வழிகளையும் பற்றி நாம் சேர்ந்து விரிவாகப் பேசுவோம்.
நீங்கள் எந்த வழியைத் தேர்ந்தெடுத்தாலும், முதல் வாரங்கள் ஒரேமாதிரியானவை. ஆரம்பத்தில் வலிக் கட்டுப்பாடு முக்கியம்; நீங்கள் தூங்கவும் அன்றாட வேலைகளைச் சமாளிக்கவும் உதவும் நிலைகளையும் எளிய வழிமுறைகளையும் கண்டுபிடிக்க நாங்கள் உங்களுக்கு உதவுவோம். எலும்பு குணமடையும்போது, தூக்குவதையும் திடீர் அசைவுகளையும் தவிர்த்து, நீங்கள் கையைப் பாதுகாக்கிறீர்கள். உங்கள் காயத்துக்கு ஏற்ற சரியான கட்டத்தில், உங்கள் பிசியோதெரபிஸ்ட்டின் வழிகாட்டலில் இயன்முறை சிகிச்சை தொடங்குகிறது; சிகிச்சையில் உங்கள் கட்டுப்பாட்டில் மிக அதிகமாக உள்ள பகுதி அதுவே.
நோயாளிகள் பொதுவாக அவர்களது பொது மருத்துவரால் (GP) எங்கள் கிளினிக்கிற்குப் பரிந்துரைக்கப்படுகிறார்கள்; ஒரு பிசியோதெரபிஸ்ட் உங்களை எங்களிடம் வரச் சொல்லியிருந்தாலும், மெடிகேர் (Medicare) திருப்பிச் செலுத்தலுக்குத் தகுதி பெற உங்கள் பொது மருத்துவரிடமிருந்து ஒரு பரிந்துரைக் கடிதம் இன்னும் தேவைப்படும்.
என்ன எதிர்பார்க்கலாம்
எலும்பு மெதுவாகவே ஒன்றுசேர்கிறது. அறுவை சிகிச்சை இல்லாமல் சிகிச்சை பெறும் பெரும்பாலானோருக்கு, உறுதியாகக் குணமடைய ஆகும் சராசரிக் காலம் 14 வாரங்கள்; பத்தில் ஒன்பதுக்கும் மேற்பட்டவற்றில் எலும்பு ஒன்றுசேர்கிறது. முதல் வாரங்களில் வலி படிப்படியாகத் தணிகிறது; இருப்பினும் அது தணியும் நேரத்தில் தோள்பட்டை பெரும்பாலும் விறைப்பாக உணரப்படுகிறது. அடுத்து வரும் மாதங்களில், ஒரு பிசியோதெரபிஸ்ட் படிப்படியாக நீங்கள் அசைவுக்குத் திரும்ப வழிகாட்டுகிறார்; எலும்பு உறுதியாகும்போது, உடை அணிவது, லேசான பொருட்களைத் தூக்கிச் செல்வது போன்ற அன்றாட வேலைகள் திரும்புகின்றன.
உங்களுக்கு அறுவை சிகிச்சை செய்யப்பட்டால், முதல் வாரங்கள் ஒரேமாதிரியானவை: குணமடையும்போது கையைப் பாதுகாப்பது, பிறகு உங்கள் பிசியோதெரபிஸ்ட்டுடன் படிப்படியான அசைவு. தோள்பட்டை மீண்டும் நிலையாக உணர மாதங்கள் ஆகலாம்; வழியில் விறைப்பு பொதுவானது. குணமடையும்போது அறுவை சிகிச்சை துண்டுகளைச் சிறந்த நிலையில் பிடித்து வைக்கிறது; ஆனால் அதற்கே உரிய அபாயங்களும் உள்ளன — பின்னர் மற்றொரு அறுவை சிகிச்சை தேவைப்படும் அதிக வாய்ப்பு உட்பட. வயதான நோயாளிகளில் சில கடுமையான முறிவு வடிவங்களுக்கு, மூட்டு மாற்று அறுவை சிகிச்சை சிறந்த நீண்டகால விளைவை நோக்கமாகக் கொண்டது; இருப்பினும் மூட்டு மாற்றிலிருந்து மீள்வது தனக்கே உரிய ஒரு செயல்முறை.
சில விஷயங்களை நேர்மையாகத் தெரிந்துகொள்வது பயனுள்ளது. எலும்பு மெதுவாக ஒன்றுசேர அல்லது ஒன்றுசேராமல் போக வாய்ப்பு உள்ளது; அறுவை சிகிச்சை இல்லாமல் சிகிச்சை பெறும் சிலருக்கு இறுதியில் அறுவை சிகிச்சை தேவைப்படுகிறது. சற்றுக் கோணலான நிலையில் குணமடையும் தோள்பட்டை பெரும்பாலும் இன்னும் நன்றாகச் செயல்படுகிறது; ஏனெனில் அந்த மூட்டு எடை தாங்குவதில்லை, சுற்றியுள்ள தசைகளே வேலையின் பெரும்பகுதியைச் செய்கின்றன. எந்த வழியிலும் மிகப் பொதுவான புகார் விறைப்புதான்; அதனால்தான் அசைவுப் பயிற்சிகள் முக்கியம்.
இந்தக் காயத்திலிருந்து மீள்வது பொதுவாக வாரங்களில் அல்ல, மாதங்களில் அளவிடப்படுகிறது. பெரும்பாலானோர் கையை அன்றாடம் வசதியாகப் பயன்படுத்தும் திறனை மீண்டும் பெறுகிறார்கள்; இருப்பினும் சிலருக்கு நீடிக்கும் விறைப்போ வலியோ இருக்கும். உங்கள் அறிகுறிகள் தணியாவிட்டால், வாரக்கணக்கில் மோசமாகிக்கொண்டே போனால், அல்லது கையைப் பயன்படுத்துவதைத் தடுத்தால், உங்கள் பொது மருத்துவரை (GP) பாருங்கள் அல்லது சிறப்பு நிபுணர் மதிப்பாய்வைக் கேளுங்கள்.
எப்போது மருத்துவரைப் பார்க்க வேண்டும்
காயத்துக்குப் பிறகு உங்கள் கை தெளிவாக வடிவம் மாறியதுபோலத் தோன்றினால், முறிவின் மேல் தோல் கிழிந்திருந்தால், எலும்பு வெளியே தெரிந்தால், அல்லது உங்கள் கையோ (hand) விரல்களோ வெளிறி, குளிர்ந்து, வெள்ளையாக அல்லது நீலமாக மாறினால், உடனடியாக அவசர சிகிச்சையை நாடுங்கள். காயத்துக்குப் பிறகு கையில் (arm) திடீரென உணர்வு அல்லது அசைவு இழப்பு ஏற்பட்டாலும், அதே நாளில் அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள். கிளினிக்கைத் தொடர்புகொள்ள முடியாவிட்டால், உங்களுக்கு அருகிலுள்ள அவசர சிகிச்சைப் பிரிவுக்குச் செல்லுங்கள்.
வலி தணியாவிட்டால், அல்லது எலும்பு குணமடையும்போது வீக்கம், அசைவு அல்லது கையின் பயன்பாடு வாரத்துக்கு வாரம் மேம்படாவிட்டால், உங்கள் பொது மருத்துவரை (GP) பாருங்கள் அல்லது சிறப்பு நிபுணர் மதிப்பாய்வைக் கேளுங்கள். வாரக்கணக்கில் மோசமாகும், இரவில் உங்களை எழுப்பும், அல்லது வேலை செய்வதையோ கையைப் பயன்படுத்துவதையோ தடுக்கும் அறிகுறிகளும் மதிப்பாய்வுக்கு உரியவை.
ஆழமான விளக்கம்
Advanced reading: the deeper science (optional)
உங்கள் சொந்தச் சிகிச்சை முடிவுகளுக்குத் தேவையானதைவிட இந்தப் பகுதி மேலும் ஆழமாகச் செல்கிறது. வாழ்க்கையின் பிற்பகுதியில் ஏற்படும் தோள்பட்டை முறிவு இந்தக் கூடுதல் வாசிப்புக்குத் தகுதியானது; ஏனெனில், ஆய்வுச் சான்றுகளும் அன்றாட மருத்துவ நடைமுறையும் ஒத்துப்போகாத, எலும்பியல் துறையின் மிகத் தெளிவான நிலைகளில் இதுவும் ஒன்று; மேலும், மிகத் தீவிரமானது போலத் தோன்றும் சிகிச்சைதான் சிறந்த கையைத் தருகிறது என்பதும் இங்கே உண்மையல்ல.
வயதான பெரும்பாலான நோயாளிகளுக்கு, அறுவை சிகிச்சை பலனை மேம்படுத்துவதில்லை
இந்த ஒப்பீடு மீண்டும் மீண்டும் செய்யப்பட்டுள்ளது. 1,743 நோயாளிகளைத் தொகுத்து ஆய்ந்த ஒரு முறையான மதிப்பாய்வு, இடம் நகர்ந்த மேற்கை எலும்பின் மேற்பகுதி முறிவு உள்ள, 65 வயதுக்கு மேற்பட்ட சராசரி நோயாளிக்கு அறுவை சிகிச்சை அல்லாத சிகிச்சையையே பரிந்துரைத்தது; கண்காணிப்பு ஆய்வுகளின் தொகுக்கப்பட்ட விளைவுகள், சீரற்ற ஒதுக்கீட்டு மருத்துவச் சோதனைகளின் விளைவுகளுடன் ஒத்திருந்ததையும் அது சுட்டிக்காட்டியது [1]. 486 நோயாளிகளைக் கொண்ட அதற்கு முந்தைய மதிப்பாய்வு ஒன்று, அறுவை சிகிச்சை மூலம் கையாளப்பட்ட முறிவுகளுக்கும் அறுவை சிகிச்சை அல்லாத முறையில் கையாளப்பட்ட முறிவுகளுக்கும் இடையே பலன்களில் நிரூபிக்கக்கூடிய வேறுபாடு எதுவும் இல்லை என்பதை ஏற்கெனவே கண்டறிந்திருந்தது [2].
இது நம் உள்ளுணர்வுக்கு மாறானது; ஏனெனில் இடம் நகர்ந்த மேற்கை எலும்பின் மேற்பகுதி முறிவின் எக்ஸ்-ரே பார்க்கப் பயமுறுத்துவதாக இருக்கும். எலும்பு பல துண்டுகளாக, தெளிவாக இடம் மாறிக் கிடக்கும். இவ்வளவு கண்கூடாகத் தவறாக இருக்கும் ஒன்றைச் சரிசெய்தே ஆக வேண்டும் என்பதே நோயாளியின் — மேலும் பெரும்பாலும் மருத்துவரின் — உள்ளுணர்வு.
எலும்பின் நிலை சரியாக இல்லாவிட்டாலும் தோள்பட்டை அதை வழக்கத்துக்கு மாறாகப் பொறுத்துக்கொள்கிறது என்பதையே மருத்துவச் சோதனைகள் காட்டுகின்றன. இது எடை தாங்கும் மூட்டு அல்ல; அதைச் சுற்றியுள்ள சுழற்சி தசைநாண் பட்டையும் டெல்டாய்டு (deltoid) தசையும்தான் பெரும்பாலான வேலையைச் செய்கின்றன; மேலும் துண்டுகளை மென்திசு பிடித்து வைத்து, அவற்றுக்கு இரத்த ஓட்டத்தையும் தொடர்ந்து தருகிறது. சற்றுக் கோணலாகக் குணமடையும் தோள்பட்டை, அறுவை சிகிச்சையால் நிலைப்படுத்தப்பட்ட தோள்பட்டையைப் போலவே அசைவதும் உணரப்படுவதும் அடிக்கடி நிகழ்கிறது; அதுவும் காயமோ, உள்பொருத்தோ, கீழே சொல்லப்பட்டுள்ள அபாயங்களோ இல்லாமலேயே.
அந்த மருத்துவச் சோதனை சான்றுகளை மாற்றியது, நடைமுறையை அல்ல
இதைச் சற்று நிதானமாக யோசித்துப் பார்க்க வேண்டும். இடம் நகர்ந்த மேற்கை எலும்பின் மேற்பகுதி முறிவுகளுக்கு, அறுவை சிகிச்சைக்கும் அறுவை சிகிச்சை அல்லாத சிகிச்சைக்கும் இடையே ஒப்பிட்டுச் சோதித்த பெரிய சீரற்ற ஒதுக்கீட்டு மருத்துவச் சோதனையே PROFHER; அறுவை சிகிச்சையால் எந்தப் பலனும் இல்லை என்பதை அது கண்டறிந்தது [6].
அது வெளியிடப்பட்ட பிறகு நடைமுறை உண்மையில் மாறியதா என்பதை 116,868 நோயாளிகளைக் கொண்ட ஆய்வு ஒன்று பின்னர் ஆராய்ந்தது. மாறவில்லை: அறுவை சிகிச்சை மூலமான சிகிச்சையின் விகிதங்களில் PROFHER குறிப்பிடத்தக்க தாக்கத்தை ஏற்படுத்தவில்லை; ஆண்டுக்கான அறுவை சிகிச்சை விகிதத்தில் குறிப்பிடத்தக்க மாற்றம் எதுவும் இல்லை [3].
இது உங்கள் தோள்பட்டையைப் பற்றிய கண்டுபிடிப்பு அல்ல, மருத்துவத் துறையைப் பற்றியது; ஒரு நோயாளி இதை அறிந்திருப்பது நியாயமானதே. இந்த முறிவுக்கு உங்களுக்கு அறுவை சிகிச்சை பரிந்துரைக்கப்பட்டால், கேட்க வேண்டிய சரியான கேள்வி 'அறுவை சிகிச்சை எப்போதாவது பொருத்தமானதா' என்பது அல்ல — சில சமயங்களில் அது தெளிவாகப் பொருத்தமானதுதான் — மாறாக, உங்கள் முறிவிலும் உங்கள் கையிலும் குறிப்பாக எது, அது பலன் தருவதாக நிரூபிக்கப்படாத குழுவிலிருந்து உங்களை வெளியே நிறுத்துகிறது என்பதுதான்.
அறுவை சிகிச்சை தேர்ந்தெடுக்கப்படும்போது, செய்யப்படும் அறுவை சிகிச்சை மாறியுள்ளது
அறுவை சிகிச்சை ஒருபோதும் சரியல்ல என்று மேலே சொன்னவற்றில் எதுவும் பொருள்படவில்லை. உருண்டையைப் பிளக்கும் முறிவுகள் (head-splitting fractures), முறிவுடன் கூடிய மூட்டு விலகல்கள், திறந்த காயங்கள், மேலும் அதிகத் தேவைகள் கொண்ட இளம் நோயாளிகள் — இவை அனைத்தும் முற்றிலும் வேறான நிலைகள்.
வயதான நோயாளிக்கு அறுவை சிகிச்சை செய்யப்படும்போது, தலைகீழ் முழுத் தோள்பட்டை மூட்டு மாற்று அறுவை சிகிச்சையை (reverse total shoulder replacement) நோக்கியே இந்தத் துறை உறுதியாக நகர்ந்துள்ளது. 228,523 நோயாளிகளைத் தொகுத்து ஆய்ந்தபோது, இந்த முறிவுகள் உள்ள வயதான நோயாளிகளில், பாதி மூட்டு மாற்று அறுவை சிகிச்சையை (hemiarthroplasty) விடத் தலைகீழ் முழுத் தோள்பட்டை மூட்டு மாற்று அறுவை சிகிச்சை சிறந்த செயல்பாட்டுப் பலன்களையும் சிக்கல் விகிதங்களையும் தந்தது; தகடு பொருத்தும் முறையை (plate fixation) விட மறு அறுவை சிகிச்சை தேவைப்படும் நிலையிலும் அது மேலானதாக இருந்தது [4].
இதன் பின்னணியில் உள்ள தர்க்கம் இதுதான்: தலைகீழ் மூட்டு மாற்று அறுவை சிகிச்சை, எலும்பு மேடுகள் (tuberosities) சரியான நிலையில் குணமடைவதைச் சார்ந்திருப்பதில்லை; எலும்புத் துளைநோய் (osteoporosis) உள்ள தோள்பட்டையில் நம்பகமற்றதாக இருப்பது சரியாக அந்த எலும்பு மேடுகளின் குணமடைதல்தான். பழைய அறுவை சிகிச்சைகளை முன்கூட்டிக் கணிக்க முடியாததாக ஆக்கிய அந்தக் காரணியையே இது நீக்கிவிடுகிறது.
உங்கள் மீட்சியை உண்மையில் எது முன்கூட்டிக் காட்டுகிறது
பெரும்பாலும் முறிவின் வடிவம் அல்ல. மீட்சியை முன்கூட்டிக் காட்டும் உயிரியல்–உளவியல்–சமூகக் காரணிகளை ஆராய்ந்த, 4,323 நோயாளிகளைக் கொண்ட ஒரு முறையான மதிப்பாய்வு, அறுவை சிகிச்சைக்கு முந்தைய செயல்பாட்டு நிலை — அதாவது காயத்துக்கு முன் அந்தக் கையும் அந்த நபரும் எவ்வளவு நன்றாகச் செயல்பட்டுக்கொண்டிருந்தார்கள் என்பது — செயல்பாட்டு மீட்சியை முன்கூட்டிக் காட்டுகிறது என்று கண்டறிந்தது [5].
இதைச் சரியாகப் புரிந்துகொள்வது முக்கியம். மீட்சி என்பது மனப்பான்மையைப் பொறுத்தது என்று இதற்குப் பொருளல்ல. நீங்கள் எங்கே போய்ச் சேர்வீர்கள் என்பதை மிக வலுவாக முன்கூட்டிக் காட்டும் ஒற்றைக் காரணி, நீங்கள் எங்கிருந்து தொடங்கினீர்கள் என்பதே; இது யதார்த்தமான எதிர்பார்ப்புகளுக்கும், தோள்பட்டை விறைப்பாக உணரப்பட்டு முன்னேற்றமே கண்ணுக்குத் தெரியாமல் இருக்கும் மாதங்களில் மறுவாழ்வுப் பயிற்சியைத் தீவிரமாக எடுத்துக்கொள்வதற்கும் ஆதரவான வாதம்.
மேற்கோள்கள்
[1] Beks RB, Ochen Y, Frima H, Smeeing DP, van der Meijden O, Timmers TK, et al. Operative versus nonoperative treatment of proximal humeral fractures: a systematic review, meta-analysis, and comparison of observational studies and randomized controlled trials. J Shoulder Elbow Surg. 2018;27(8):1526-34. https://doi.org/10.1016/j.jse.2018.03.009
[2] Nanidis TG, Majed A, Liddle AD, Constantinides VA, Sivagnanam P, Tekkis PP, et al. Conservative versus operative management of complex proximal humeral fractures: a meta-analysis. Shoulder Elbow. 2010;2(3):166-74. https://doi.org/10.1111/j.1758-5740.2010.00075.x
[3] Cheesman JS, Englert CH, Yang Q, Yoo JU, Nazir OF, Mirarchi AJ. Impact of PROFHER on trends in proximal humerus fracture treatment in the United States. Shoulder Elbow. 2025;18(3):476-84. https://doi.org/10.1177/17585732251359178
[4] Mekhail J, Mullan R, Cross JL, Jahagirdar O, Luo X, Salameh M. Outcomes of reverse total shoulder arthroplasty vs. other surgical fixation methods for proximal humerus fractures: a systematic review and meta-analysis. JSES Rev Rep Tech. 2026;6(2):100644. https://doi.org/10.1016/j.xrrt.2025.100644
[5] Varahra A, MacDermid JC, Szekeres M. A systematic review of biopsychosocial prognostic factors of recovery after a proximal humerus fracture. J Hand Ther. 2023;36(4):825-44. https://doi.org/10.1016/j.jht.2023.06.005
[6] Rangan A, Handoll H, Brealey S, Jefferson L, Keding A, Martin BC, et al. Surgical vs nonsurgical treatment of adults with displaced fractures of the proximal humerus: the PROFHER randomized clinical trial. JAMA. 2015;313(10):1037-47. https://doi.org/10.1001/jama.2015.1629
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Non-Operative Management
- Non-operative management is associated with good outcomes in the majority of proximal humerus fractures in adults [1].
- Patients with proximal humerus fractures that would have normally necessitated surgical treatment showed favorable outcomes following nonsurgical treatment [2].
- Most proximal humeral fractures in elderly patients can be treated nonoperatively with good functional outcomes [10].
- Over the past decade, most older adults who sustain proximal humerus fractures continue to receive nonoperative treatment [6].
- Most one-part proximal humerus fractures are amenable to non-operative treatment with positive outcomes reported in the vast majority of cases [16].
- Most pediatric patients with proximal humerus fractures have favorable results, and complications are infrequent [17].
Operative Management
- Percutaneous treatment of selected proximal humeral fractures results in predictable union and good clinical results with a low rate of complications [32].
- Nail fixation for proximal humerus fractures is a very good technique if the indication is well defined [47].
- The selection of reverse total shoulder arthroplasty over other surgical options is a current, reasonable, and safe option to treat proximal humerus fractures, particularly in those with higher Neer grades and/or in older patients [55].
- Hemiarthroplasty and reverse prosthesis are indicated for complex proximal humerus fractures in patients no younger than 70 years of age [8].
- Patients with a proximal humerus fracture undergoing reverse total shoulder arthroplasty have significantly worse perioperative outcomes, including higher rates of complications, longer hospital stays, and higher costs, compared to patients with other indications [156].
Treatment Considerations and Evidence Gaps
- Treatment algorithms and outcomes following proximal humerus fractures in patients less than or equal to 60 years of age are distinctly different from that of a more elderly population [4].
- Both age and gender have an association with the definitive treatment patients received for proximal humerus fractures over the last decade [5].
- The available literature does not demonstrate a clear clinical benefit of operative treatment over nonoperative management of proximal humeral fractures in adult patients younger than 65 years [21].
- Evidence-based recommendations to guide treatment of proximal humerus fractures are lacking, and no good evidence exists whether surgery is clearly superior to nonoperative treatment [34].
- No single fixation method is a panacea for proximal humeral fractures; choice of implant and method should be selected according to individual patient and fracture pattern characteristics based on clearly defined indications and contraindications [51].
- Prospective clinical trials with longer-term follow-up are required for definitive assessment of the ideal fixation construct for surgical management of two-part proximal humerus fractures [24].
- Besides age, most randomized controlled trials on surgical management of proximal humerus fractures do not include patient-specific variables within their inclusion and exclusion criteria [23].
- There are conflicting opinions on what outcome measure is best to assess function following the treatment of proximal humerus fractures [11].
- The development of an evidence-based clinical protocol for the treatment of proximal humerus fractures is long overdue, requiring a thoughtful, all-inclusive, randomized multicenter trial to determine the best treatment options [60].
- Guidelines and treatment algorithms for native humerus fractures may not be generalizable for those of pathologic origin [70].
Outcomes and Complications
- Mortality at 1 year for fragility proximal humerus fractures is universally high regardless of risk factors [18].
- After surgical treatment, patients with pathologic humerus fractures had significantly higher complication rates compared with native humerus fractures [70].
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humerus comprises four main parts: the humeral head, greater tuberosity (GT), lesser tuberosity (LT), and humeral shaft [76].
- The articular head of the proximal humerus is spherical with a diameter of 37 to 57 mm [76].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [76].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [76].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [76].
- The anatomic neck is located at the junction of the articular surface and the tuberosities [76].
- The surgical neck represents an indistinct region, or metadiaphyseal junction, below the tuberosities but above the humeral shaft [76].
- The greater tuberosity is located in a posterior-superior location with respect to the humeral shaft [76].
- The lesser tuberosity is located on the anterior aspect of the proximal humerus [76].
- The bicipital groove lies between the greater and lesser tuberosities and serves as a pathway for the long head of the biceps [76].
- The distal aspect of the bicipital groove is internally rotated with respect to the proximal portion [76].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [76].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [76].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [79].
- The proximal humerus has three centers of ossification: the humeral head (4 to 6 months), the greater tuberosity (1 to 3 years), and the lesser tuberosity (3 to 5 years) [79].
- The proximal humeral ossification centers fuse to the shaft at age 17 to 20 years [79].
- The humeral head is retroverted 30 degrees relative to the transepicondylar axis of the humerus [90].
- Head height is approximately 5.6 cm above the superior border of the pectoralis major tendon [90].
- The anatomic neck is directly below the humeral head and serves as an attachment for the shoulder capsule [90].
- The surgical neck is more distal than the anatomic neck and is more often involved in fractures [90].
- The transverse humeral ligament is an important stabilizer of the biceps tendon [90].
- The articular surface of the humeral head is essentially spherical, with an arc of approximately 160 degrees covered by articular cartilage [88].
- The radius of curvature of the humeral head is approximately 25 mm and is slightly larger in men than in women [88].
- The average neck-shaft angle is 45 degrees (±5 degrees), with a range of 30 to 50 degrees [88].
- The superior margin of the humeral head articular surface is normally superior to the top of the greater tuberosity by 8 to 10 mm [88].
- The distance from the lateral base of the coracoid process to the lateral margin of the greater tuberosity is called the lateral humeral offset [88].
- Proximal humeral retroversion is highly variable, ranging from 0 to 55 degrees depending on the method used for measurement [88].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [77].
- The neck-shaft angle measures an average of 135 degrees [77].
- The humeral head is retroverted an average of 30 degrees [77].
- The proximal humeral physis closes by 14 to 17 years of age in girls and by 16 to 18 years in boys [83].
- Humeral retroversion averages 65 degrees in infants and young children and gradually decreases, approaching adult values by 11 years of age [83].
- Eighty percent of subsequent humeral growth comes from the proximal humeral physis, accounting for approximately 40% of the growth of the entire upper extremity [83].
- The periosteum is thicker and stronger in the posteromedial portion of the proximal humerus compared to the anterolateral portion, which is often quite thin [83].
- The proximal humeral physis is irregularly shaped, with its apex located on the posteromedial portion of the proximal humerus [83].
Soft Tissue & Vascular Anatomy
- The greater tuberosity serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons of the rotator cuff [76].
- The lesser tuberosity serves as the attachment site for the subscapularis tendon [76].
- The rotator cuff consists of four muscles: the subscapularis, supraspinatus, infraspinatus, and teres minor [77].
- The teres major is not a rotator cuff muscle [77].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [77].
- The deltoid and pectoralis major muscles, along with the rotator cuff, cause predictable displacement of fractures around the proximal humerus [77].
- The subscapularis originates from the anterior scapula and inserts anteriorly onto the lesser tuberosity [83].
- The greater tuberosity provides attachment superiorly and posteriorly for the supraspinatus, infraspinatus, and teres minor [83].
- The deltoid courses from the clavicle and acromion superiorly into a common tendinous insertion onto the lateral upper third of the humeral shaft [83].
- The pectoralis major inserts anteriorly onto the lateral wall of the bicipital groove and forms the roof of the distal continuation of the bicipital tunnel [83].
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [76].
- The posterior humeral circumflex artery travels with the axillary nerve, enters the quadrilateral space posteriorly, and anastomoses with a branch of the anterior circumflex to supply the posterior cuff [76].
- The anterior humeral circumflex artery arises from the axillary artery at the inferior border of the subscapularis [76].
- The anterior humeral circumflex artery provides vascular inflow to the humeral head by way of its terminal anterolateral branch known as the artery of Laing (also known as the arcuate artery) [76].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon and enters the humeral head at the interface of the bicipital groove and greater tuberosity [76].
- The major blood supply to the humeral head is through the ascending branch of the anterior humeral circumflex artery, which penetrates the head at the bicipital groove and becomes the arcuate artery [77].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [79].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [79].
- Quantitative assessment has shown that 64% of the humeral head blood supply arises from the posterior humeral circumflex artery [83].
- The brachial plexus and axillary artery lie anterior to the coracoid process of the scapula and humeral head [77].
- The axillary nerve circles the humeral neck just inferior to the glenohumeral joint as it courses posteriorly [83].
- The axillary nerve is a terminal branch coming off the posterior cord of the brachial plexus just proximal to the coracoid process [82].
- The axillary nerve passes beneath the conjoined tendon anterior to the subscapularis 3 to 5 mm medial to the musculotendinous junction and then adjacent to the inferior capsule before entering the quadrilateral space posteriorly [82].
- The axillary nerve splits into the anterior and posterior branches within the quadrangular space [82].
- The anterior and middle deltoid muscle receives sole innervation from the anterior branch of the axillary nerve [82].
- Posterior deltoid muscle innervation varies, with supply only from the anterior branch in 2.3% of cases, from the posterior branch in 8.5%, and from both branches in 89.1% [82].
- The posterior branch of the axillary nerve branches to supply the teres minor muscle and then terminates as the superior lateral brachial cutaneous nerve [82].
- The subacromial bursa separates the rotator cuff tendons from the coracoacromial arch, allowing them to glide [84].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula and communicates with the joint cavity between the superior and middle glenohumeral ligaments [80].
- The subscapular bursa often houses loose bodies in the shoulder and is a region in which synovitis of the shoulder may be most intense [80].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [79].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [79].
- The tendons of the infraspinatus and supraspinatus muscles join approximately 15 mm proximal to their insertion and cannot be readily separated by blunt dissection [89].
- The infraspinatus and teres minor fuse near their musculotendinous junctions [89].
- The supraspinatus and subscapularis tendons join as a sheath that surrounds the biceps tendon at the entrance of the bicipital groove [89].
- The roof of the biceps sheath consists of a portion of the supraspinatus tendon, and a sheet of the subscapularis tendon forms the floor [89].
- The coracohumeral ligament is a thick band of fibrous tissue extending from the coracoid process along the surface of the capsule to the tuberosities between the supraspinatus and subscapularis tendons [89].
Pathophysiology & Biomechanics
- Stability and function of the glenohumeral joint are provided by the interaction of structures that promote a near global range of motion and purposeful function [76].
- External loads transferred to the shoulder girdle are initially offset by joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion [76].
- Moderate and large loads are counterbalanced by the deltoid and rotator cuff and by the capsulolabral and bone structures, respectively [76].
- Proximal humerus fractures alter complex interactions of the shoulder girdle, resulting in pain, decreased range of motion and stiffness, and disability [76].
- Following a fracture of the proximal humerus, displacement of each "part" occurs in a predictable manner based on the deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [76].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement [76].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement [76].
- The pectoralis major inserts on the humeral shaft and displaces it medially [76].
- A fracture involving the anatomic neck is prognostically worse than fractures involving other regions of the proximal humerus with respect to the potential disruption of the vascular supply to the humeral head and the subsequent development of avascular necrosis [76].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [76].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [76].
- Fractures of the anatomic neck have a poor prognosis because of complete disruption of the blood supply to the head [77].
- Surgical neck fractures are common, and with these, the blood supply to the head is preserved [77].
- Displaced proximal humerus fractures can impede normal movement of structures passing underneath the coracoacromial arch, causing impingement and disruption of normal glenohumeral motion [76].
- In displaced and nondisplaced proximal humerus fractures, the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that can limit normal glenohumeral motion [76].
- Early range of motion exercises after a fracture have been hypothesized to decrease the formation of such adhesions [76].
- The glenoid bone is generally harder and denser than the proximal humerus and acts as an 'anvil' on which the proximal humerus is impacted during injury [64].
- The combination of the direction of the blow to the humerus, quality of bone in the proximal humerus, and the pull of the soft tissues produces various types of fracture patterns [64].
- Medical comorbidities increase the risk for fracture and type of fracture sustained [64].
- Proximal humerus fractures are seen in a greater frequency in patients with a depleted neuromuscular response [64].
- The close anatomical relationship between the proximal humerus, axillary artery, and brachial plexus predisposes these structures to combined injury patterns that can threaten limb viability [43].
- The incidence of neurovascular injury is increased in fracture-dislocations [27].
- The axillary nerve is most commonly injured in proximal humerus fractures [27].
- An axillary nerve injury from proximal humeral fracture or fracture-dislocation would result in paralysis of the deltoid muscle and anesthesia over the “badge” region at the lateral proximal arm [77].
- The brachial plexus is prone to injury when the proximal humerus is injured in fractures or dislocations, or during traction [83].
- Adhesions in the humeroscapular motion interface can limit shoulder mobility, with examples including scarring after proximal humerus fracture trauma [82].
- The humeroscapular motion interface lies between the inner structures of the proximal humerus, rotator cuff, coracohumeral ligament, and biceps tendon sheath and the superficial layer of the acromion, deltoid, coracoacromial ligament, coracoid process, and conjoined tendon [82].
- Smooth, unrestricted motion at the humeroscapular motion interface is vital to shoulder mobility [82].
- The axillary nerve has an intimate relationship within the humeroscapular motion interface [82].
- Positioning the arm in abduction and internal rotation may help mitigate deforming muscular forces in proximal humerus fractures [132].
- Bone quality significantly impacts implant anchorage in osteosynthesis of proximal humerus fractures [144].
- Biomechanical changes associated with inferior tuberosity positioning after hemiarthroplasty may explain diminished function in patients with proximal humerus fractures [117].
- Anatomic reconstruction of tuberosity fragments produced results indistinguishable from normal shoulder controls in biomechanical studies [143].
- The double plate strategy can increase the stability of the medial column of the proximal humerus and enhance the overall biomechanical property of the repaired proximal humerus [153].
- Varus-displacing forces to the humeral head were superiorly reduced in settings utilizing a specific proximal anchoring point for intramedullary nailing [149].
- The Humerusblock NG allows for angular stable dynamic fixation of two-part proximal humeral fractures [161].
- Proper technique for internal fixation of the proximal humerus requires an understanding of osseous and neurovascular anatomy, with biomechanical studies showing that locked plating provides stable fixation [166].
- The biphasic plate concept is aimed at improving the biomechanics of locked plating [174].
- A biomechanically efficient nail without increased neurological risks can improve the pullout strength of the screws to provide more secure fixation of proximal humeral fractures [165].
Classification
Classification Systems and Reliability
- The Neer classification categorizes displaced proximal humerus fractures from two to four parts according to anatomic segments [169].
- In the Neer classification, displacement is defined as separation of a fragment greater than 1 cm or angulation of a fragment greater than 45° [169].
- Fracture lines in nondisplaced segments are not included in the Neer classification [169].
- The AO classification is based on the vascular supply of the articular segments [169].
- The AO classification is divided into three categories (A, B, C) of increasing severity, with each category further split into numerical subgroupings [169].
- Evaluation of classification systems for fractures of the proximal humerus using plain radiographs has yielded low interobserver reliability [41].
- The Mayo-FJD classification system for proximal humerus fractures allows high intraobserver and interobserver agreement using both radiographs and computed tomography [129].
- Reported mean kappa values for interobserver agreement on the AO classification have varied between 0.26 and 0.53 [173].
- Mean kappa values for interobserver agreement on the AO classification decreased from 0.53 for AO Types to 0.2 for AO Groups [173].
- Morphologic classification of proximal humerus fractures as the sole basis for treatment algorithms and surgical success should be scrutinized [59].
- Current diagnosis coding practices do not adequately capture the fracture complexity needed to conduct subgroup analysis for proximal humerus fractures [163].
Epidemiology and Demographics
- Proximal humerus fractures are osteoporotic injuries with increasing incidence due to aging populations [12].
- In a cohort of 688 patients, 49.2% of fractures were grouped into AO-OTA type A, 43.1% into type B, and 7.7% into type C [177].
- In a cohort of 688 patients, 24.3% of proximal humeral fractures were non-displaced or minimally displaced according to the Neer classification [177].
- In a cohort of 688 patients, 32.3% of proximal humeral fractures were two-part displaced according to the Neer classification [177].
- In a cohort of 688 patients, 30.9% of proximal humeral fractures were three-part according to the Neer classification [177].
- In a cohort of 688 patients, 6.9% of proximal humeral fractures were four-part according to the Neer classification [177].
- In a cohort of 688 patients, 5.6% of proximal humeral fractures were associated with a glenohumeral dislocation according to the Neer classification [177].
- There was no statistically significant association between gender and the AO-OTA classification or the Neer classification [177].
- There was no statistically significant association between the type of trauma and the AO-OTA classification or the Neer classification [177].
- There was no statistically significant association between the diagnosis of osteoporosis and the AO-OTA classification or the Neer classification [177].
- There was a statistically significant association between the AO-OTA and Neer classifications and age grouped by decades [177].
- There was a statistically significant association between the AO-OTA and Neer classifications and the type of treatment performed [177].
Clinical Evaluation and Imaging
- Accurate clinical evaluation, imaging, and classification are paramount for informed treatment decisions regarding proximal humerus fractures [12].
- The use of artificial intelligence can accurately detect and classify proximal humerus fractures on plain shoulder AP radiographs [69].
- The type of proximal humerus fracture depends on the amount and direction of applied force, the quality of bone, and the position of the shoulder at the time of injury [181].
- Neer defined significant displacement as greater than 1 cm of translation, or angulation greater than 45° for any of the major fracture fragments [181].
- The AO/ASIF group labeled valgus impaction injuries as Type C (C2.1, C2.2) fractures of the proximal humerus in their classification system [181].
Clinical Presentation
History and Mechanism
- The fracture results most commonly from an indirect mechanism, such as a fall on the outstretched upper extremity [27].
- Other indirect mechanisms, such as seizures or electrical shocks, are uncommon [27].
- Direct mechanisms from a blow to the shoulder occur much less frequently than the indirect mechanism [27].
- When obtaining a history from a patient with a suspected proximal humerus fracture, it is important to record the hand dominance, occupation, and mechanism of injury [27].
Physical Examination
- Gross deformity is not often appreciated because of the soft tissues surrounding the proximal humerus [27].
- Swelling and tenderness to palpation are typically present in patients with proximal humerus fractures [27].
- Ecchymosis extending distally along the extremity and along the chest wall is often present a few days following injury [27].
- Assessment of fracture stability is an important part of the examination [27].
- With one hand palpating the humeral head, the humeral shaft should be gently internally and externally rotated to assess stability [27].
- If the proximal and distal fragments move as a unit, the fracture is considered stable [27].
- A thorough neurovascular examination is crucial due to the close proximity of the brachial plexus and the axillary artery [27].
- Deltoid motor function and sensation over the lateral aspect of the shoulder should be assessed during the neurovascular examination [27].
Epidemiology and Risk Factors
- Proximal humerus fractures are now typically osteoporotic fractures in women over 70, with prevalence increasing due to an aging population in poor general condition [45].
- The incidence of proximal humerus fracture increased from 104.7/100,000 in 2008 to 124.7/100,000 in 2012 in women [115].
- The incidence of proximal humerus fracture increased from 45.3/100,000 in 2008 to 52.0/100,000 in 2012 in men [115].
- Proximal humerus fracture increased by 40.5% over the 5 year of study from 10,135 in 2008 to 14,238 in 2012 [115].
- The number of individuals 50 years or older in the general population increased 19.5% from 13,103,814 in 2008 to 15,657,674 in 2012 [115].
- The incidence of proximal humerus fracture in women (19.1%) was more increased than that in men (14.8%) from 2008 to 2012 [115].
- Combined fractures with femoral or vertebral fractures are associated with significantly higher mortality and morbidity compared with isolated proximal humerus fractures [130].
Complications and Prognosis
- Complications associated with proximal humerus fractures are varied and can be categorized as occurring at the time of initial injury, during operative management, or as delayed sequelae [13].
- Neurovascular injuries associated with proximal humerus fractures represent a rare yet clinically significant complication with potential for devastating functional outcomes [43].
- The multifactorial etiology of neurovascular injuries encompasses direct trauma from displaced fracture fragments and indirect injury due to the close anatomical relationship between the proximal humerus, axillary artery, and brachial plexus [43].
- Most nerve injuries, particularly involving the axillary nerve, demonstrate favorable outcomes with conservative management [43].
- Vascular injuries associated with proximal humerus fractures demand urgent multidisciplinary intervention to restore perfusion and prevent irreversible ischemia [43].
- Axillary artery injury associated with a proximal humerus fracture is a rare occurrence but can have profound consequences [131].
- There is a substantial mortality in patients with a proximal humerus fracture [14].
- Surviving patients with proximal humerus fractures frequently have persistent symptoms that can be predicted as early as after 1 year [14].
Investigations
Imaging Modalities and Protocols
- At least two X-ray views should be obtained for proximal humerus fractures: an anteroposterior view in the plane of the glenoid and an axillary projection with the arm in abduction [93].
- The recommended radiographic series for proximal humerus fractures is the Neer trauma series, consisting of an AP view, a lateral view in the scapular plane, and a Velpeau modified axillary view [95].
- The combination of the three views in the Neer trauma series allows evaluation of the shoulder joint in three separate perpendicular planes [95].
- The axillary view is important for evaluating the glenoid articular surface and the relationship of the humeral head anteriorly and posteriorly [95].
- Computed tomography (CT) is helpful for planning fracture surgery and shoulder joint replacement [93].
- On occasion, CT scanning may be necessary for detailing bony anatomy in proximal humerus fractures [95].
- CT imaging is frequently used to evaluate fractures of the shoulder [100].
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head or a bone tumour [93].
- MRI can identify labral tears and rotator cuff tears, although accuracy for these is enhanced by combining the scan with arthrography [93].
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [100].
- T2-weighted MRI provides better visualization of full thickness rotator cuff tears [100].
- Ultrasound is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [93].
- Ultrasound can be useful in guiding injections or barbotage [93].
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [100].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [100].
- Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [100].
- Zero-echo time (ZTE) MRI presents a viable alternative to CT in the evaluation of proximal humerus fractures [170].
Classification and Diagnostic Accuracy
- Evaluation of the classification systems for fractures of the proximal humerus with plain radiographs has yielded low interobserver reliability [41].
- Computed tomography scan was more specific than radiographs in the assessment of proximal humerus fracture sequelae [44].
- Convolutional neural networks (CNNs) proficiently rule out proximal humerus fractures on plain radiographs [190].
- ChatGPT-5 is highly inaccurate at identifying proximal humerus fractures on shoulder x-rays, characterizing fracture patterns, and providing accurate interpretations [207].
- The routine use of 3D-printed models may not be beneficial for classifying proximal humeral fracture patterns beyond the information gained from currently available imaging modalities [203].
- The use of 3D-printed models as the sole determinant for recommending surgical intervention should be avoided at this time [203].
Clinical Evaluation and Associated Injuries
- Accurate clinical evaluation, imaging, and classification are paramount for informed treatment decisions in proximal humerus fractures [12].
- Rotator cuff injuries can be expected with fractures of the tuberosities but can also result from strictly soft-tissue injuries such as shoulder dislocations [95].
- Evaluation of the integrity of the rotator cuff may be difficult in the acute setting [95].
- Ultrasound, MRI, arthrogram, or arthroscopy may be valuable in making a diagnosis of rotator cuff injury in the acute setting [95].
- Axillary artery injuries generally result from fractures or fracture-dislocations in which a medial bone spike injures or penetrates the axillary artery [95].
- The index of suspicion for axillary artery injury is high if the arm shows significant color differences compared with the uninjured arm [95].
- Pulses should be palpated and evaluated by Doppler studies when axillary artery injury is suspected [95].
- In addition to palpation and anteroposterior and lateral humeral x-ray, bilateral anteroposterior shoulders x-ray is suggested routinely to confirm the shoulder location in children with shoulder dislocation combined with proximal humerus fracture [205].
Treatment
Non-Operative Management
- In the vast majority of cases, proximal humerus fractures may be treated nonoperatively [3].
- A majority of patients with proximal humeral fractures underwent non-operative treatment [22].
- Nonsurgical treatment should have a more prominent role in the treatment of proximal humeral fractures [57].
- Approximately 80% of proximal humerus fractures are minimally displaced low energy injuries and are at low risk for future displacement, nonunion, or avascular necrosis, and have a high union rate with conservative management [65].
- Nonsurgical management of proximal humerus fractures decreased during the study period [110].
- There was no statistical difference in functional outcomes between non-displaced, 2-part and 3-part fractures of the proximal humerus treated non-operatively [114].
- Patients with non-operatively managed proximal humerus fractures continue to improve up to, and beyond 6 months post-injury [114].
- Non-operative treatment (NOT) involves a period of immobilization, such as an arm sling, followed by physiotherapy and exercise [116].
- Non-operative treatment is generally the accepted treatment option for minimally displaced fractures and often used also for people with displaced fractures [116].
- In a randomized controlled trial, there was no significant difference in clinical outcomes at 2 years between surgery and non-operative treatment in patients 60 years of age or older with displaced 2-part fractures of the proximal humerus [29].
- The ProFHER trial showed that conservative management is as effective as surgical intervention for displaced proximal humerus fractures [104].
- Prolonged sling use in conservatively managed displaced proximal humerus fractures can be associated with increased pain, stiffness, risk of falls, delayed return to function, and burden on healthcare systems [104].
- Supervised rehabilitation is comparable to a single advice session after nonoperative treatment of displaced proximal humerus fracture [126].
- Nonoperative treatment is recommended for the average elderly patient (aged > 65 years) with a displaced proximal humeral fracture [178].
- Proximal humerus fractures in children have tremendous potential for remodeling, making non-operative management the treatment of choice for most fractures [138].
Operative Management: Indications and General Principles
- Patients who have sustained an open fracture, vascular injuries, or those that have repairable neurologic injuries, are usually indicated for acute operative intervention [65].
- Operative fixation can provide stability if there is a need for any vascular or nerve repair procedures [65].
- Patients who have preexisting neurologic impairment on the side of injury resulting from a stroke or a traumatic spine injury, or who lead very inactive lifestyles, may not benefit from any acute intervention and can be managed nonoperatively [65].
- Patients who are medically unstable can be treated conservatively or treated in a delayed fashion once they are more physiologically stable [65].
- Consensus when managing proximal humerus fractures is limited to specific scenarios, whereas lack of consensus still exists in others [15].
- Surgical treatment of proximal humerus fractures remains far from straightforward, with unpredictable outcomes where factors associated with poor results include being a woman, four-part fracture dislocation, and absence of metaphyseal head extension [28].
- Delaying surgery for proximal humerus fracture is likely to increase inpatient morbidity, postoperative length of stay and non-routine discharge [167].
- The results of a prospective, randomized controlled trial will provide Level 1 evidence to guide decision-making in the treatment of proximal humerus fractures in the elderly population [103].
- Besides age, most RCTs on surgical management of proximal humerus fractures do not include patient-specific variables within their inclusion and exclusion criteria [23].
Operative Management: Internal Fixation (ORIF)
- The early, published results to date are encouraging in the treatment of three-part proximal humerus fractures [35].
- MIPO is a safe and effective option for the treatment of proximal humerus fractures, with good functional recovery and fewer complications, which are typically technique dependent [133].
- Although the less-invasive surgical procedure is a feasible treatment option in proximal humeral fractures with acceptable complications and considerable improvement during the first six months, a lengthy recovery time is required [140].
- Osteosynthesis of the proximal humerus in osteoporotic bone typically produces inferior results to that in younger subjects with better bone stock [109].
- In a study of the PlantTan Fixator Plate, there were no cases of infection, impingement, avascular necrosis or malunion in the population under 70 years of age [109].
- In a study of the PlantTan Fixator Plate, there was a significant proportion of patients with avascular necrosis and implant migration in the group over 70 years [109].
- Open reduction internal fixation (ORIF) is one of the common operative treatments for displaced and unstable fractures and those with more complex fracture patterns [116].
- In a network meta-analysis, the rank of treatments in terms of high Constant score was: RSA, ORIF, IN, NOT and HA [116].
- In a network meta-analysis, the rank for reduction in total incidence of complications was: RSA, NOT, HA, IN and ORIF [116].
- In a network meta-analysis, the rank for lowering the risk of additional surgery was: RSA, NOT, HA, IN and ORIF [116].
Operative Management: Arthroplasty
- Reverse total shoulder replacement is a promising treatment for geriatrics with three- and four-part proximal humerus fractures aiming for a better long-term functional outcome [26].
- The selection of RTSA over other surgical options is a current, reasonable, and safe option to treat proximal humerus fractures, particularly in those with higher Neer grades and/or in older patients [55].
- While the main potential advantage of the pyrolytic carbon head (PCH)—reduced glenoid erosion—will require further investigation with longer follow-up, this is the first study to demonstrate the safety and short-term outcomes of the PCH in treating proximal humerus fractures [61].
- These findings should be considered when treatment is selected for acute three- and four-part proximal humerus fractures [72].
- In a network meta-analysis, RSA had significantly the highest Constant score and lower total incidence of complications than ORIF, HA and IN [116].
- In a network meta-analysis, RSA resulted in a lower incidence of additional surgery than ORIF and IN [116].
- RSA had the highest probability for improving functional outcome and reduction in the total incidence of complications and requiring additional surgery among the five interventions for treating adults with displaced proximal humeral fracture [116].
- RTSA is an effective treatment option for selected patients with acute proximal humerus fractures [135].
- RTSA has shown to provide reproducible functional outcomes and is a good treatment option for elderly patients with 3-part and 4-part proximal humerus fractures [136].
- A meta-analysis demonstrates no significant differences in clinical outcomes or complication rates between standard components and fracture-specific components in RSA, suggesting comparable performance in the treatment of proximal humerus fractures [134].
Rehabilitation and Post-Treatment Care
- There is substantial variation in the literature regarding the optimal management for PHFs, with studies supporting nonoperative management, ORIF, and arthroplasty [127].
- The inconsistency between studies may in part be explained by heterogeneity in rehabilitation protocols, which are seldom evaluated [127].
- There is some evidence that early intensive mobilization yields similar outcomes compared to later or conventional mobilization after operative treatment (both plate fixation and hemiarthroplasty) and conservative treatment [127].
- It has remained unclear how other aspects of rehabilitation impact outcomes such as sling usage and timing of physical therapy [127].
- Participants allocated to nonsurgical treatment in the ProFHER trial were given a sling for the injured arm for as long as deemed necessary (3 weeks was suggested), followed by active rehabilitation [123].
- Rehabilitation care in the ProFHER trial was provided by physiotherapists in inpatient, outpatient, and community settings [123].
Complications
General Classification and Epidemiology
- Complications associated with proximal humerus fractures are categorized as occurring at the time of initial injury, during operative management, or as delayed sequelae [13].
- Proximal humerus fractures are typically osteoporotic fractures in women over 70, with prevalence increasing due to an aging population in poor general condition [45].
Mortality and Morbidity
- There is substantial mortality in patients with a proximal humerus fracture, and surviving patients frequently have persistent symptoms that can be predicted as early as after 1 year [14].
- The adjusted one-year mortality rate following a proximal humerus fracture was 13.05%, which is significantly higher than other upper extremity fractures but lower than hip fractures [68].
Non-Operative Complications
- The prevalence of nonunion after proximal humeral fracture is higher than previously reported, with most patients having a very low risk but a smaller subgroup at much higher risk [74].
Operative Complications: Osteosynthesis
- Fixation of proximal humerus fractures with proximal humerus locking plates is associated with a high rate of complications and reoperation [151].
- Selective Glenohumeral External Rotation Deficit (SGERD) is a new shoulder evaluation symptom identified as a sequela of post-ORIF deltoid adhesions after treatment of the proximal humerus fracture [71].
- Predictive models constructed using machine learning techniques demonstrated favorable discrimination and satisfactory-to-excellent performance in forecasting prolonged length of stay and serious adverse complications occurring within 30 days of surgical intervention for proximal humerus fracture [66].
- Percutaneous proximal humerus fixation offers less complications compared to other methods [158].
- After one-year, long-term follow-up of fixed proximal humerus fractures may be unnecessary for those without symptoms [48].
Operative Complications: Arthroplasty
- Hemiarthroplasty for the treatment of complex proximal humerus fractures yields variable long-term clinical outcomes and high rates of failure, with the majority due to greater tuberosity malunion or nonunion [63].
- Low arthroplasty survival is observed after treatment for proximal humerus fracture sequelae, as reported by the Nordic Arthroplasty Register Association [7].
- Hemiarthroplasty outcomes for acute proximal humerus fractures and fracture sequelae did not differ significantly, supporting the use of hemiarthroplasty in both settings with modest clinical outcomes [150].
- The main potential advantage of pyrolytic carbon head hemiarthroplasty—reduced glenoid erosion—will require further investigation with longer follow-up [61].
Pathologic Fractures
- After surgical treatment, patients with pathologic humerus fractures had significantly higher complication rates compared with native humerus fractures, suggesting that guidelines and treatment algorithms for native humerus fractures may not be generalizable for those of pathologic origin [70].
Recovery
Non-operative Management
- A multicenter randomized controlled trial found no significant difference in clinical outcomes at 2 years between surgery and non-operative treatment in patients 60 years of age or older with displaced 2-part fractures of the proximal humerus [29].
Operative Management
- Minimally invasive treatment of displaced proximal humeral fractures in patients younger than 70 years using the Humerusblock yields good midterm clinical and radiological results [37].
- The locking plate provides satisfactory functional outcomes after a mid-term follow-up in patients with displaced proximal humerus fractures [50].
- Double-plating of proximal humeral fractures yields good clinical mid- to long-term results in complex and highly unstable fractures [141].
- Timing of surgery did not impact outcomes of patients who underwent ORIF for proximal humerus fractures [206].
- Early operative intervention does not appear to decrease the rate of development of avascular necrosis after proximal humeral fracture [211].
Arthroplasty
- Long-term treatment with reverse shoulder arthroplasty (RSA) for displaced 3- or 4-part proximal humerus fractures provides better functional outcomes compared to nonoperative treatment, a difference attributed to the deterioration of functional outcomes of the nonoperative treatment over time [56].
- Functional outcomes of proximal humerus fractures treated with reverse shoulder arthroplasty improve with surgical experience, and outcomes become less variable after approximately 20 procedures [67].
- Patients in the proximal humerus fracture cohort were less likely to report persistent shoulder pain at all evaluated time points compared to the osteoarthritis cohort [201].
Prognosis and Complications
- Surviving patients with a proximal humerus fracture frequently have persistent symptoms that can be predicted as early as after 1 year [14].
- Post-traumatic osteonecrosis of the proximal humerus is a challenging problem commonly seen following multi-fragmentary fractures, affecting long-term functional recovery [147].
- If patients do not follow the usual course of improvement after a proximal humerus fracture from a superior traction mechanism, consideration should be given to associated superior labral tears that may require surgical intervention [210].
Follow-up and Assessment
Key Evidence
- [L4] Non-operative management is associated with good outcomes in the majority of proximal humerus fractures in adults. [1] (10.5312/wjo.v5.i5.685)
- [L4] Patients with proximal humerus fractures that would have normally necessitated surgical treatment showed favorable outcomes following nonsurgical treatment. [2] (10.1097/bte.0000000000000174)
- [L4] In the vast majority of cases, proximal humerus fractures may be treated nonoperatively. [3] (10.1155/2012/861598)
- [L4] Treatment algorithms and outcomes following proximal humerus fractures in patients less than or equal to 60 years of age are distinctly different from that of a more elderly population. [4] (10.1016/j.xrrt.2023.01.002)
- [L3] Both age and gender have an association with the definitive treatment patients received for proximal humerus fractures over the last decade. [5] (10.1016/j.jseint.2021.11.007)
- [L4] Over the past decade, most older adults who sustain proximal humerus fractures continue to receive nonoperative treatment. [6] (10.1016/j.jseint.2021.08.006)
- [L3] These results are pertinent when deciding on the treatment of proximal humerus fracture sequelae. [7] (10.1080/17453674.2020.1793548)
- [L4] They are indicated for complex proximal humerus fractures in patients no younger than 70 years of age. [8] (10.1016/j.otsr.2008.09.002)
- [L5] Most proximal humeral fractures in elderly patients can be treated nonoperatively with good functional outcomes. [10] (10.2106/jbjs.l.01293)
- [L4] Additionally, there are conflicting opinions on what outcome measure is best to assess function following the treatment of proximal humerus fractures. [11] (10.1007/s00264-017-3569-0)
- [L3] Our results suggest that there is a substantial mortality in patients with a proximal humerus fracture, as we have previously reported, and that surviving patients frequently have persistent symptoms that can be predicted as early as after 1 year. [14] (10.1080/17453670510041295)
- [L5] Consensus when managing proximal humerus fractures is limited to specific scenarios, whereas lack of consensus still exists in others. [15] (10.1016/j.jse.2024.12.005)
- [L5] Most pediatric patients with proximal humerus fractures have favorable results, and complications are infrequent. [17] (10.5435/jaaos-d-14-00033)
- [L3] Mortality at 1 year for fragility proximal humerus fractures is universally high regardless of risk factors. [18] (10.1016/j.jse.2022.03.006)
- [L1] The available literature does not demonstrate a clear clinical benefit of operative treatment over nonoperative management of proximal humeral fractures in adult patients younger than 65 years. [21] (10.1016/j.xrrt.2021.04.014)
- [L3] A majority of patients with proximal humeral fractures underwent non-operative treatment. [22] (10.1186/s12891-019-2812-9)
- [L2] Besides age, most RCTs on surgical management of proximal humerus fractures do not include patient-specific variables within their inclusion and exclusion criteria. [23] (10.1016/j.xrrt.2025.07.023)
- [L3] However, prospective clinical trials with longer-term follow-up are required for definitive assessment of the ideal fixation construct for surgical management of two-part proximal humerus fractures. [24] (10.1016/j.injury.2013.08.024)
- [L3] It is a promising treatment for geriatrics with three- and four-part proximal humerus fractures aiming for a better long-term functional outcome. [26] (10.1186/s12891-023-06669-3)
- [L5] [27] (10.1097/00132589-200212000-00003)
- [L5] Surgical treatment of proximal humerus fractures remains far from straightforward, with unpredictable outcomes where factors associated with poor results include being a woman, four-part fracture dislocation, and absence of metaphyseal head extension. [28] (10.1097/corr.0000000000002242)
- [L1] This trial found no significant difference in clinical outcomes at 2 years between surgery and non-operative treatment in patients 60 years of age or older with displaced 2-part fractures of the proximal humerus. [29] (10.1371/journal.pmed.1002855)
- [L4] Percutaneous treatment of selected proximal humeral fractures results in predictable union and good clinical results with a low rate of complications. [32] (10.1016/j.jse.2006.09.006)
- [L4] Evidence-based recommendations to guide treatment of proximal humerus fractures are lacking, and no good evidence exists whether surgery is clearly superior to nonoperative treatment. [34] (10.1016/j.ocl.2008.06.003)
- [L5] The early, published results to date are encouraging in the treatment of three-part proximal humerus fractures. [35] (10.1097/00132589-200206000-00007)
- [L4] Minimally invasive treatment of displaced proximal humeral fractures in patients younger than 70 years using the Humerusblock yields good midterm clinical and radiological results. [37] (10.1016/j.injury.2015.05.017)
- [L5] Evaluation of the classification systems for fractures of the proximal humerus with plain radiographs has yielded low interobserver reliability. [41] (10.1016/j.ocl.2008.05.002)
- [L5] [43] (10.1016/j.xrrt.2026.100825)
- [L2] Computed tomography scan was more specific than radiographs in the assessment of proximal humerus fracture sequelae. [44] (10.1177/17585732221150785)
- [L2] Proximal humerus fractures are now typically osteoporotic fractures in women over 70, with prevalence increasing due to an aging population in poor general condition. [45] (10.1016/j.otsr.2012.05.013)
- [Paper] Nail fixation for proximal humerus fractures is a very good technique if the indication is well defined. [47] (10.1097/bte.0b013e31817303af)
- [L3] After one-year, long-term follow-up of fixed proximal humerus fractures may be unnecessary for those without symptoms. [48] (10.1007/s00590-021-03099-6)
- [L4] The locking plate provides satisfactory functional outcomes after a mid-term follow-up in patients with displaced proximal humerus fractures. [50] (10.1007/s00590-010-0655-z)
- [L4] No single fixation method is a panacea for proximal humeral fractures; choice of implant and method should be selected according to individual patient and fracture pattern characteristics based on clearly defined indications and contraindications. [51] (10.1016/j.injury.2010.10.016)
- [L5] The selection of RTSA over other surgical options is a current, reasonable, and safe option to treat proximal humerus fractures, particularly in those with higher Neer grades and/or in older patients. [55] (10.1097/corr.0000000000002430)
- [L1] Long-term treatment with RSA for displaced 3- or 4-part proximal humerus fractures provides better functional outcomes compared to nonoperative treatment, a difference attributed to the deterioration of functional outcomes of the nonoperative treatment over time. [56] (10.1016/j.jse.2024.09.032)
- [L3] Nonsurgical treatment should have a more prominent role in the treatment of proximal humeral fractures. [57] (10.1016/j.jse.2011.01.025)
- [L2] Morphologic classification of proximal humerus fractures as the sole basis for treatment algorithms and surgical success should be scrutinized. [59] (10.1016/j.jseint.2022.02.006)
- [L5] The development of an evidence-based clinical protocol for the treatment of proximal humerus fractures is long overdue, requiring a thoughtful, all-inclusive, randomized multicenter trial to determine the best treatment options. [60] (10.1016/j.injury.2014.05.017)
- [L2] While the main potential advantage of the PCH—reduced glenoid erosion—will require further investigation with longer follow-up, this is the first study to demonstrate the safety and short-term outcomes of the PCH in treating proximal humerus fractures. [61] (10.1016/j.jse.2025.07.032)
- [L5] Hemiarthroplasty for the treatment of complex proximal humerus fractures yields variable long-term clinical outcomes and high rates of failure, with the majority due to greater tuberosity malunion or nonunion. [63] (10.1016/j.xrrt.2025.100616)
- [L5] [64] (10.1007/978-3-319-08951-5_2)
- [L4] [65] (10.1007/s12178-012-9130-2)
- [L3] Predictive models constructed using ML techniques demonstrated favorable discrimination and satisfactory-to-excellent performance in forecasting prolonged LOS and serious adverse complications occurring within 30 days of surgical intervention for proximal humerus fracture. [66] (10.1016/j.jseint.2024.02.005)
- [L4] Functional outcomes of proximal humerus fractures treated with reverse shoulder arthroplasty improve with surgical experience, and outcomes become less variable after approximately 20 procedures. [67] (10.1016/j.jseint.2021.07.008)
- [L3] The adjusted one-year mortality rate following a proximal humerus fracture was 13.05%, which is significantly higher than other upper extremity fractures but lower than hip fractures. [68] (10.1016/j.jse.2015.11.031)
- [L4] The use of artificial intelligence can accurately detect and classify proximal humerus fractures on plain shoulder AP radiographs. [69] (10.1080/17453674.2018.1453714)
- [L3] After surgical treatment, patients with pathologic humerus fractures had significantly higher complication rates compared with native humerus fractures, suggesting that guidelines and treatment algorithms for native humerus fractures may not be generalizable for those of pathologic origin. [70] (10.1016/j.jse.2020.10.024)
- [L4] These observations allow the identification of a new shoulder evaluation symptom: Selective Glenohumeral External Rotation Deficit (SGERD). [71] (10.1186/s12891-020-03634-2)
- [L4] These findings should be considered when treatment is selected for acute three- and four-part proximal humerus fractures. [72] (10.1016/s1058-2746(05)80020-5)
- [L3] The prevalence of nonunion after proximal humeral fracture is higher than previously reported, with most patients having a very low risk but a smaller subgroup at much higher risk. [74] (10.2106/jbjs.20.01139)
- [L1] The results of this trial will provide Level 1 evidence to guide decision-making in the treatment of proximal humerus fractures in the elderly population. [103] (10.1186/s12891-018-2223-3)
- [L4] [104] (10.1177/17585732241239011)
- [L4] [109] (10.1016/j.injury.2005.05.030)
- [L4] Nonsurgical management of proximal humerus fractures decreased during the study period. [110] (10.1016/j.jhsa.2020.03.022)
- [L5] [114] (10.1016/j.injury.2004.11.026)
- [L4] [115] (10.11005/jbm.2015.22.1.17)
- [L1] [116] (10.1371/journal.pone.0166801)
- [Abstract] These biomechanical changes may explain diminished function in patients with inferior tuberosity positioning after hemiarthroplasty for proximal humerus fractures. [117] (10.1016/j.jse.2007.02.027)
- [L1] [123] (10.1001/jama.2015.1629)
- [L1] [126] (10.1016/j.jse.2025.11.013)
- [L4] [127] (10.1177/17585732231182374)
- [L4] The Mayo-FJD classification system for proximal humerus fractures seems to allow high intraobserver and interobserver agreement using both radiographs and computed tomography. [129] (10.1016/j.jse.2023.02.035)
- [L3] Combined fractures with femoral or vertebral fractures are associated with significantly higher mortality and morbidity compared with isolated proximal humerus fractures. [130] (10.1016/j.jse.2025.04.013)
- [L5] Axillary artery injury associated with a proximal humerus fracture is a rare occurrence but can have profound consequences. [131] (10.1016/s1058-2746(98)90058-1)
- [L5] These findings suggest that positioning the arm in abduction and internal rotation may help mitigate deforming muscular forces in proximal humerus fractures. [132] (10.5397/cise.2022.00885)
- [L4] MIPO is a safe and effective option for the treatment of proximal humerus fractures, with good functional recovery and fewer complications, which are typically technique dependent. [133] (10.1016/j.aott.2016.10.003)
- [L1] This meta-analysis demonstrates no significant differences in clinical outcomes or complication rates between standard components and fracture-specific components in RSA, suggesting comparable performance in the treatment of proximal humerus fractures. [134] (10.1302/0301-620x.107b9.bjj-2024-1508.r2)
- [Abstract] RTSA is an effective treatment option for selected patients with acute proximal humerus fractures. [135] (10.1016/j.jse.2014.06.021)
- [L4] RTSA has shown to provide reproducible functional outcomes and is a good treatment option for elderly patients with 3-part and 4-part proximal humerus fractures. [136] (10.1097/bot.0000000000000607)
- [L3] Although the less-invasive surgical procedure is a feasible treatment option in proximal humeral fractures with acceptable complications and considerable improvement during the first six months, a lengthy recovery time is required. [140] (10.1186/s12891-015-0618-y)
- [Abstract] Double-plating of proximal humeral fractures yields good clinical mid- to long-term results in complex and highly unstable fractures. [141] (10.1016/j.jse.2022.01.036)
- [L5] In contrast, anatomic reconstruction produced results indistinguishable from normal shoulder controls. [143] (10.1067/mse.2001.113962)
- [L4] The paper reviews the biology and biomechanics of osteosynthesis for proximal humerus fractures, emphasizing that bone quality significantly impacts implant anchorage. [144] (10.1007/s00068-007-7089-2)
- [L4] Post-traumatic osteonecrosis of the proximal humerus is a challenging problem commonly seen following multi-fragmentary fractures, affecting long-term functional recovery. [147] (10.1016/j.injury.2015.06.026)
- [L5] Varus-displacing forces to the humeral head were superiorly reduced in this setting. [149] (10.1007/s00264-017-3498-y)
- [L3] Hemiarthroplasty outcomes for acute proximal humerus fractures and fracture sequelae did not differ significantly, supporting the use of hemiarthroplasty in both settings with modest clinical outcomes. [150] (10.1016/j.jseint.2022.10.009)
- [L4] Fixation of proximal humerus fractures with proximal humerus locking plates is associated with a high rate of complications and reoperation. [151] (10.1016/j.injury.2010.11.058)
- [L5] The double plate strategy can increase the stability of the medial column of the proximal humerus, and enhance the overall biomechanical property of the repaired proximal humerus. [153] (10.1186/s12891-024-08216-0)
- [Abstract] Patients with a proximal humerus fracture undergoing reverse total shoulder arthroplasty have significantly worse perioperative outcomes, including higher rates of complications, longer hospital stays, and higher costs, compared to patients with other indications. [156] (10.1016/j.jse.2015.05.005)
- [L4] This study explains positive experience with percutaneous proximal humerus fixation, suggesting it offers less complications compared to other methods, and encourages continuing the technique with longer term follow-up. [158] (10.1016/j.jse.2021.03.017)
- [L5] The Humerusblock NG allows for angular stable dynamic fixation of two-part proximal humeral fractures. [161] (10.1007/s00402-012-1503-x)
- [L3] Current diagnosis coding practices do not adequately capture the fracture complexity needed to conduct subgroup analysis for proximal humerus fractures. [163] (10.1016/j.jse.2023.08.022)
- [L5] The study introduces a biomechanically efficient nail without increased neurological risks to improve the pullout strength of the screws to provide more secure fixation of proximal humeral fractures. [165] (10.1016/j.clinbiomech.2015.12.005)
- [L5] Proper technique for internal fixation of the proximal humerus requires an understanding of osseous and neurovascular anatomy, with biomechanical studies showing that locked plating provides stable fixation. [166] (10.5435/jaaos-d-20-00558)
- [Abstract] Delaying surgery for proximal humerus fracture is likely to increase inpatient morbidity, postoperative length of stay and non-routine discharge. [167] (10.1016/j.jse.2014.11.011)
- [L5] [169] (10.21037/aoj-20-42)
- [L4] ZTE MRI presents a viable alternative to CT in the evaluation of proximal humerus fractures (PHF). [170] (10.1016/j.jseint.2024.08.111)
- [L2] [173] (10.1016/j.injury.2011.08.025)
- [L5] The biphasic plate concept is aimed at improving the biomechanics of locked plating. [174] (10.1016/j.injury.2020.04.032)
- [L4] [177] (10.1186/s13018-021-02551-x)
- [L1] We recommend nonoperative treatment for the average elderly patient (aged > 65 years) with a displaced proximal humeral fracture. [178] (10.1016/j.jse.2018.03.009)
- [L5] [181] (10.1097/01.blo.0000194675.64387.33)
- [L3] CNNs proficiently rule out proximal humerus fractures on plain radiographs. [190] (10.1302/0301-620x.106b11.bjj-2024-0264.r1)
- [L3] Patients in the proximal humerus fracture (PHF) cohort were less likely to report persistent shoulder pain at all evaluated time points compared to the osteoarthritis (OA) cohort, suggesting that symptom relief following treatment of traumatic pathology may differ fundamentally from that of chronic degenerative disease. [201] (10.1016/j.jsea.2026.100012)
- [L5] The routine use of 3D-printed models may not be beneficial for classifying proximal humeral fracture patterns beyond the information gained from currently available imaging modalities, and their use as the sole determinant for recommending surgical intervention should be avoided at this time. [203] (10.1097/corr.0000000000002017)
- [L5] In addition to palpation and anteroposterior and lateral humeral x-ray, we suggest adding bilateral anteroposterior shoulders xray routinely to confirm the shoulder location. [205] (10.1097/md.0000000000008977)
- [L3] Timing of surgery did not impact outcomes of patients who underwent ORIF for proximal humerus fractures. [206] (10.1016/j.jse.2025.02.019)
- [L4] This study demonstrates that ChatGPT-5 is highly inaccurate at identifying proximal humerus fractures on shoulder x-rays, characterizing fracture patterns, and providing accurate interpretations. [207] (10.1016/j.jseint.2025.101426)
- [L4] If patients do not follow the usual course of improvement after a proximal humerus fracture from a superior traction mechanism, consideration should be given to associated superior labral tears that may require surgical intervention. [210] (10.1016/j.arthro.2006.08.010)
- [L4] Early operative intervention does not appear to decrease the rate of development of avascular necrosis after proximal humeral fracture. [211] (10.1007/s12306-016-0425-0)
References
[1] Management of proximal humerus fractures in adults. World Journal of Orthopedics. 2014. DOI: 10.5312/wjo.v5.i5.685
[2] Clinical Results of Conservative Treatment of Severe Proximal Humerus Fractures Requiring Surgical Treatment in Old Patients. Techniques in Shoulder & Elbow Surgery. 2019. DOI: 10.1097/bte.0000000000000174
[3] Evaluation and Management of Proximal Humerus Fractures. Advances in Orthopedics. 2012. DOI: 10.1155/2012/861598
[4] Proximal humerus fracture management and outcomes are distinctly different for individuals 60 years of age or younger: a systematic review. JSES Reviews, Reports, and Techniques. 2023. DOI: 10.1016/j.xrrt.2023.01.002
[5] How age and gender influence proximal humerus fracture management in patients older than fifty years. JSES International. 2022. DOI: 10.1016/j.jseint.2021.11.007
[6] Trending a decade of proximal humerus fracture management in older adults. JSES International. 2022. DOI: 10.1016/j.jseint.2021.08.006
[7] Low arthroplasty survival after treatment for proximal humerus fracture sequelae: 3,245 shoulder replacements from the Nordic Arthroplasty Register Association. Acta Orthopaedica. 2020. DOI: 10.1080/17453674.2020.1793548
[8] Three or four parts complex proximal humerus fractures: Hemiarthroplasty versus reverse prosthesis: A comparative study of 40 cases. Orthopaedics & Traumatology: Surgery & Research. 2009. DOI: 10.1016/j.otsr.2008.09.002
[10] Proximal Humeral Fracture Treatment in Adults. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.l.01293
[11] Orthopaedic surgeons’ opinions surrounding the management of proximal humerus fractures: an international survey. International Orthopaedics. 2017. DOI: 10.1007/s00264-017-3569-0
[12] 1. Clinical Evaluation, Imaging, and Classification of Proximal Humerus Fractures. 2011.
[13] 6. Complications of Proximal Humerus Fractures: Evaluation and Management. 2011.
[14] Long-term outcome of a proximal humerus fracture predicted after 1 year. Acta Orthopaedica. 2005. DOI: 10.1080/17453670510041295
[15] Consensus statement on the treatment of proximal humerus fractures: a Delphi approach by the Neer Circle of the American Shoulder and Elbow Surgeons. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.12.005
[16] 2. Non-operative Management of Proximal Humerus Fractures: Indications, Protocols, and Outcomes. 2011.
[17] Evaluation and Management of Pediatric Proximal Humerus Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-14-00033
[18] Morbidity and mortality of fragility proximal humerus fractures: a retrospective cohort study of patients presenting to a level one trauma center. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.03.006
[21] Analyzing outcomes after proximal humerus fractures in patients <65 years: a systematic review and meta-analysis. JSES Reviews, Reports, and Techniques. 2021. DOI: 10.1016/j.xrrt.2021.04.014
[22] Readmissions, revisions, and mortality after treatment for proximal humeral fractures in three large states. BMC Musculoskeletal Disorders. 2019. DOI: 10.1186/s12891-019-2812-9
[23] Randomized controlled trials investigating proximal humerus fractures lack consensus in inclusion criteria. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.07.023
[24] A comprehensive update on current fixation options for two-part proximal humerus fractures. Injury. 2014. DOI: 10.1016/j.injury.2013.08.024
[26] Rehabilitation progress following reverse total shoulder replacement and internal fixation for geriatric three and four-part proximal humerus fractures – a propensity score matched comparison. BMC Musculoskeletal Disorders. 2023. DOI: 10.1186/s12891-023-06669-3
[27] Decision Making for the Treatment of Proximal Humerus Fractures. Techniques in Shoulder and Elbow Surgery. 2002. DOI: 10.1097/00132589-200212000-00003
[28] CORR Insights®: What Factors Are Associated With Poor Shoulder Function and Serious Complications After Internal Fixation of Three-part and Four-part Proximal Humerus Fracture-dislocations?. Clinical Orthopaedics & Related Research. 2022. DOI: 10.1097/corr.0000000000002242
[29] Operative versus non-operative treatment for 2-part proximal humerus fracture: A multicenter randomized controlled trial. PLOS Medicine. 2019. DOI: 10.1371/journal.pmed.1002855
[32] Outcomes after percutaneous reduction and fixation of proximal humeral fractures. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2006.09.006
[34] Open Reduction and Internal Fixation of Proximal Humerus Fractures. Orthopedic Clinics of North America. 2008. DOI: 10.1016/j.ocl.2008.06.003
[35] Operative Fixation of Three-Part Proximal Humerus Fractures. Techniques in Shoulder and Elbow Surgery. 2002. DOI: 10.1097/00132589-200206000-00007
[37] Midterm outcome and complications after minimally invasive treatment of displaced proximal humeral fractures in patients younger than 70 years using the Humerusblock. Injury. 2015. DOI: 10.1016/j.injury.2015.05.017
[41] Classification and Imaging of Proximal Humerus Fractures. Orthopedic Clinics of North America. 2008. DOI: 10.1016/j.ocl.2008.05.002
[43] Neurovascular Injuries Associated with Proximal Humerus Fractures: A Review of the Current Literature. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100825
[44] Computed tomography improves the diagnostic accuracy but not the interobserver reliability of the Boileau classification of proximal humerus fracture sequelae. Shoulder & Elbow. 2023. DOI: 10.1177/17585732221150785
[45] Epidemiology of proximal humerus fractures managed in a trauma center. Orthopaedics & Traumatology: Surgery & Research. 2012. DOI: 10.1016/j.otsr.2012.05.013
[47] Nail Fixation of Proximal Humerus Fractures. Techniques in Shoulder & Elbow Surgery. 2008. DOI: 10.1097/bte.0b013e31817303af
[48] No change in outcome ten years following locking plate repair of displaced proximal humerus fractures. European Journal of Orthopaedic Surgery & Traumatology. 2021. DOI: 10.1007/s00590-021-03099-6
[50] Results of 131 consecutive operated patients with a displaced proximal humerus fracture: an analysis with more than two years follow-up. European Journal of Orthopaedic Surgery & Traumatology. 2010. DOI: 10.1007/s00590-010-0655-z
[51] New trends in fixation of proximal humeral fractures: A review. Injury. 2011. DOI: 10.1016/j.injury.2010.10.016
[55] CORR Insights®: Short-term Complications for Proximal Humerus Fracture Surgery Have Decreased: An Analysis of the National Surgical Quality Improvement Program Database. Clinical Orthopaedics & Related Research. 2022. DOI: 10.1097/corr.0000000000002430
[56] Long-term outcomes of reverse shoulder arthroplasty versus nonoperative treatment for 3- or 4-part proximal humerus fractures in elderly patients: results from a prior randomized clinical trial. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.09.032
[57] Locking plate versus nonsurgical treatment for proximal humeral fractures: better midterm outcome with nonsurgical treatment. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2011.01.025
[59] The reliability of the Neer classification for proximal humerus fractures: a survey of orthopedic shoulder surgeons. JSES International. 2022. DOI: 10.1016/j.jseint.2022.02.006
[60] Proximal humerus fractures: Is there more than one way to skin a cat?. Injury. 2014. DOI: 10.1016/j.injury.2014.05.017
[61] Pyrolytic carbon head hemiarthroplasty vs. cobalt-chromium head for proximal humerus fractures: a short-term follow-up study. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.07.032
[63] Long-term outcomes of hemiarthroplasty for complex proximal humerus fractures: a systematic review of clinical studies with minimum 10-year follow-up. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2025.100616
[64] Nonoperative Treatment of Proximal Humerus Fractures. Proximal Humerus Fractures. 2014. DOI: 10.1007/978-3-319-08951-5_2
[65] Proximal humerus fractures. Current Reviews in Musculoskeletal Medicine. 2012. DOI: 10.1007/s12178-012-9130-2
[66] Preoperative factors predict prolonged length of stay, serious adverse complications, and readmission following operative intervention of proximal humerus fractures: a machine learning analysis of a national database. JSES International. 2024. DOI: 10.1016/j.jseint.2024.02.005
[67] Surgical learning curve in reverse shoulder arthroplasty for proximal humerus fractures. JSES International. 2021. DOI: 10.1016/j.jseint.2021.07.008
[68] Mortality after proximal humerus fractures. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.11.031
[69] Automated detection and classification of the proximal humerus fracture by using deep learning algorithm. Acta Orthopaedica. 2018. DOI: 10.1080/17453674.2018.1453714
[70] Morbidity and mortality of surgically treated pathologic humerus fractures compared to native humerus fractures. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.10.024
[71] Selective Glenohumeral external rotation deficit – sequelae of post-ORIF deltoid adhesions after treatment of the proximal humerus fracture. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03634-2
[72] Late prosthetic shoulder arthroplasty for displaced proximal humerus fractures. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80020-5
[74] Prediction of Nonunion After Nonoperative Treatment of a Proximal Humeral Fracture. Journal of Bone and Joint Surgery. 2021. DOI: 10.2106/jbjs.20.01139
[76] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[77] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[79] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[80] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[82] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > EDITOR COMMENTARY.
[83] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > FRACTURES OF THE PROXIMAL HUMERUS.
[84] Apley And Solomon S Concise System Of Orthopaedics And Trauma. DISORDERS OF THE ROTATOR CUFF.
[88] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > ANATOMY AND BIOMECHANICS.
[89] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > SHOULDER INJURIES > ANATOMY AND BIOMECHANICS.
[90] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[93] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[95] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS AROUND THE SHOULDER.
[100] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[103] Open reduction internal fixation vs non-operative management in proximal humerus fractures: a prospective, randomized controlled trial protocol. BMC Musculoskeletal Disorders. 2018. DOI: 10.1186/s12891-018-2223-3
[104] How long is the arm immobilised after a conservatively managed displaced proximal humerus fracture and does early mobilisation effect complication rates: A systematic review. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241239011
[109] Early experience with the PlantTan Fixator Plate for 2 and 3 part fractures of the proximal humerus. Injury. 2005. DOI: 10.1016/j.injury.2005.05.030
[110] Cost-Minimization Analysis and Treatment Trends of Surgical and Nonsurgical Treatment of Proximal Humerus Fractures. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2020.03.022
[114] Proximal humerus fracture in the Osteoprotic bone: should one use a nail or plate device? - a biomechanical study. Injury. 2005. DOI: 10.1016/j.injury.2004.11.026
[115] Incidence and Mortality after Proximal Humerus Fractures Over 50 Years of Age in South Korea: National Claim Data from 2008 to 2012. Journal of Bone Metabolism. 2015. DOI: 10.11005/jbm.2015.22.1.17
[116] Effectiveness and Safety of Interventions for Treating Adults with Displaced Proximal Humeral Fracture: A Network Meta-Analysis and Systematic Review. PLOS ONE. 2016. DOI: 10.1371/journal.pone.0166801
[117] Biomechanical Assessment Of Inferior Tuberosity Placement During Hemiarthroplasty For 4-Part Proximal Humerus Fractures. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2007.02.027
[123] Surgical vs Nonsurgical Treatment of Adults With Displaced Fractures of the Proximal Humerus. JAMA. 2015. DOI: 10.1001/jama.2015.1629
[126] Supervised rehabilitation comparable to single advice session after nonoperative treatment of displaced proximal humerus fracture: a randomized controlled trial. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.11.013
[127] Rehabilitation protocols in proximal humerus fracture management: A systematic review. Shoulder & Elbow. 2023. DOI: 10.1177/17585732231182374
[129] The Mayo-FJD Classification System For Proximal Humerus Fractures: Intra And Interobserver Agreement. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2023.02.035
[130] Combined proximal humerus fractures are associated with greater mortality and morbidity compared with isolated fractures: a retrospective cohort study. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.04.013
[131] Axillary artery injury as a complication of proximal humerus fractures. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90058-1
[132] Biomechanical investigation of arm position on deforming muscular forces in proximal humerus fractures. Clinics in Shoulder and Elbow. 2022. DOI: 10.5397/cise.2022.00885
[133] Minimally invasive plate osteosynthesis with PHILOS plate for proximal humerus fractures. Acta Orthopaedica et Traumatologica Turcica. 2020. DOI: 10.1016/j.aott.2016.10.003
[134] Standard compared with fracture-specific components in reverse shoulder arthroplasty for proximal humerus fractures. The Bone & Joint Journal. 2025. DOI: 10.1302/0301-620x.107b9.bjj-2024-1508.r2
[135] Reverse Total Shoulder Arthroplasty for Acute Proximal Humerus Fracture: Is There a Benefit in Using a Fracture-Specific Stem?. Journal of Shoulder and Elbow Surgery. 2014. DOI: 10.1016/j.jse.2014.06.021
[136] Reverse Total Shoulder Arthroplasty for a 4-Part Proximal Humerus Fracture. Journal of Orthopaedic Trauma. 2016. DOI: 10.1097/bot.0000000000000607
[138] 24. Proximal Humerus Fractures in the Adolescent Patient: Diagnosis, Management, and Complications. 2009.
[140] Mid-term results of a less-invasive locking plate fixation method for proximal humeral fractures: a prospective observational study. BMC Musculoskeletal Disorders. 2015. DOI: 10.1186/s12891-015-0618-y
[141] Three-Dimensional Measurement Of Bone Fragment Displacement In Proximal Humerus Fractures: A Computerized Analysis. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.01.036
[143] Biomechanical effects of malposition of tuberosity fragments on the humeral prosthetic reconstruction for four-part proximal humerus fractures. Journal of Shoulder and Elbow Surgery. 2001. DOI: 10.1067/mse.2001.113962
[144] Biology and Biomechanics in Osteosynthesis of Proximal Humerus Fractures. European Journal of Trauma and Emergency Surgery. 2007. DOI: 10.1007/s00068-007-7089-2
[147] Post-traumatic osteonecrosis of the proximal humerus. Injury. 2015. DOI: 10.1016/j.injury.2015.06.026
[149] Biomechanical evaluation of straight antegrade nailing in proximal humeral fractures: the rationale of the “proximal anchoring point”. International Orthopaedics. 2017. DOI: 10.1007/s00264-017-3498-y
[150] Hemiarthroplasty for proximal humerus fractures and for fracture sequelae: did not differ in their outcomes. JSES International. 2023. DOI: 10.1016/j.jseint.2022.10.009
[151] A systematic review of locking plate fixation of proximal humerus fractures. Injury. 2011. DOI: 10.1016/j.injury.2010.11.058
[153] Biomechanical study of two different fixation methods for the treatment of Neer III proximal humerus fractures. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-08216-0
[156] Reverse Total Shoulder Arthroplasty Patients with a Proximal Humerus Fracture Have Significantly Worse Perioperative Outcomes than Other Indications: An Analysis of 5644 Cases. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.05.005
[158] Revisiting Percutaneous Fixation for Proximal Humerus Fractures. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2021.03.017
[161] The Humerusblock NG: a new concept for stabilization of proximal humeral fractures and its biomechanical evaluation. Archives of Orthopaedic and Trauma Surgery. 2012. DOI: 10.1007/s00402-012-1503-x
[163] ICD-10 diagnosis codes in electronic health records do not adequately capture fracture complexity for proximal humerus fractures. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2023.08.022
[165] Anatomical and biomechanical evaluation of an intramedullary nail for fractures of proximal humerus fractures based on tuberosity fixation. Clinical Biomechanics. 2016. DOI: 10.1016/j.clinbiomech.2015.12.005
[166] Principles of Locking Plate Fixation of Proximal Humerus Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-20-00558
[167] Does the Timing of Surgery for Proximal Humerus Fracture Affect Inpatient Outcomes?. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2014.11.011
[169] Locking plate fixation for proximal humerus fractures—when do I use a fibular strut?. Annals of Joint. 2020. DOI: 10.21037/aoj-20-42
[170] "Preliminary Study Of Integrating ZTE MRI In Proximal Humerus Fractures: Bridging The Gap Between CT And MRI". JSES International. 2024. DOI: 10.1016/j.jseint.2024.08.111
[173] Benefits and harms of locking plate osteosynthesis in intraarticular (OTA Type C) fractures of the proximal humerus: A systematic review. Injury. 2012. DOI: 10.1016/j.injury.2011.08.025
[174] Biphasic Plating – In vivo study of a novel fixation concept to enhance mechanobiological fracture healing. Injury. 2020. DOI: 10.1016/j.injury.2020.04.032
[177] Epidemiology of proximal humerus fractures. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02551-x
[178] Operative versus nonoperative treatment of proximal humeral fractures: a systematic review, meta-analysis, and comparison of observational studies and randomized controlled trials. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2018.03.009
[181] Evaluation and Management of Valgus Impacted Four-part Proximal Humerus Fractures. Clinical Orthopaedics & Related Research. 2006. DOI: 10.1097/01.blo.0000194675.64387.33
[190] Detection, classification, and characterization of proximal humerus fractures on plain radiographs. The Bone & Joint Journal. 2024. DOI: 10.1302/0301-620x.106b11.bjj-2024-0264.r1
[201] Complication rates following total shoulder arthroplasty for osteoarthritis versus proximal humerus fracture: a propensity-matched cohort comparison of 9,190 patients. Journal of Shoulder and Elbow Arthroplasty. 2026. DOI: 10.1016/j.jsea.2026.100012
[203] CORR Insights®: 3D-printed Handheld Models Do Not Improve Recognition of Specific Characteristics and Patterns of Three-part and Four-part Proximal Humerus Fractures. Clinical Orthopaedics & Related Research. 2021. DOI: 10.1097/corr.0000000000002017
[205] Shoulder dislocation combined with proximal humerus fracture in children. Medicine. 2017. DOI: 10.1097/md.0000000000008977
[206] Delays beyond 5 days to surgery does not affect outcome following plate and screw fixation of proximal humerus fractures. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.019
[207] Bot vs. doc—who is better at reading proximal humerus fracture x-rays?. JSES International. 2026. DOI: 10.1016/j.jseint.2025.101426
[210] SLAP Tear Associated With a Minimally Displaced Proximal Humerus Fracture. Arthroscopy. 2007. DOI: 10.1016/j.arthro.2006.08.010
[211] Rate of avascular necrosis and time to surgery in proximal humerus fractures. MUSCULOSKELETAL SURGERY. 2016. DOI: 10.1007/s12306-016-0425-0