Patients › General-Health
பிரேஸ்கள், சிம்புகள் மற்றும் தாங்கிகள் (Braces, Splints and Supports)
When braces, splints and supports help upper-limb conditions, the main types, how to use them, and what the evidence shows for sprains, tendon problems, arthritis and after surgery.
அது என்ன
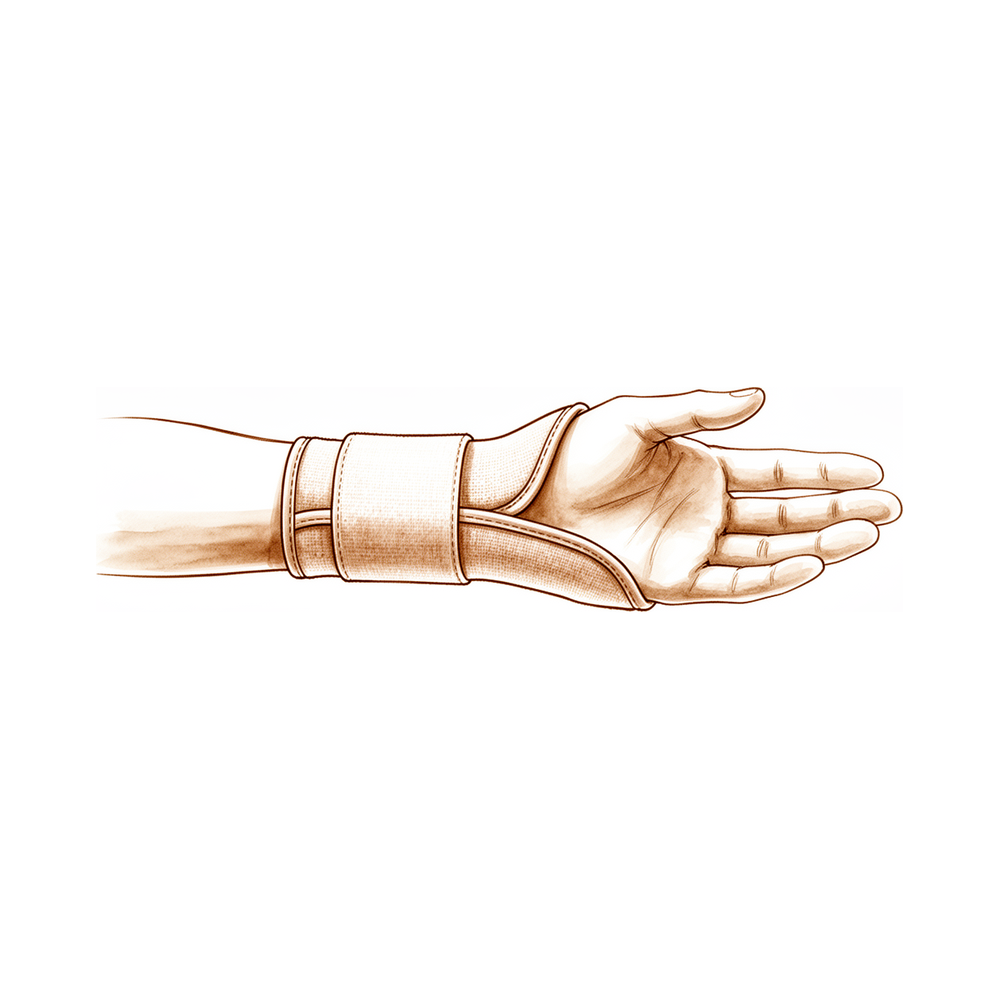
பிரேஸ் (brace), சிம்பு (splint) அல்லது தாங்கி (support) என்பது, உங்கள் உடலின் ஒரு பகுதியை அசையாமல் பிடித்து வைக்கும், அல்லது அது அசையும் விதத்தை வழிநடத்தும் ஒரு சாதனம். சிம்புகள் பொதுவாக உறுதியானவை; அவை ஒரு மூட்டை ஒரே நிலையில் பிடித்து வைக்கின்றன. பிரேஸ்களும் தாங்கிகளும் பெரும்பாலும் அந்தப் பகுதியைப் பாதுகாக்கும் அதேநேரம் சிறிது அசைவை அனுமதிக்கின்றன. அவை கை (hand), மணிக்கட்டு, முழங்கை, தோள்பட்டைப் பிரச்சினைகளுக்கும், சில சமயங்களில் முழங்காலில் கிழிந்த முன்புறச் சிலுவைத் தசைநார் (ACL) போன்ற காயங்களுக்கும் பயன்படுத்தப்படுகின்றன; அங்கே பிரேஸ் அணியும் திட்டம், அறுவை சிகிச்சைக்குப் பதிலான ஒரு தேர்வாக உள்ளது [1].
மூட்டுகளையும் மென்திசுக்களையும் ஒரு நிலையான நிலையில் பிடித்து வைப்பதன் மூலம் சிம்புகள் செயல்படுகின்றன. பிளாஸ்டர் சிம்புகள் (plaster splints) இதை மென்மையாகவும் துல்லியமாகவும் செய்கின்றன; இது காலப்போக்கில் விறைப்பான திசுவை மீண்டும் வடிவமைக்க உதவுகிறது [2]. ஒரு காயத்தின் ஆரம்பக் கட்டத்தில், எல்லா அசைவையும் நிறுத்தாமலேயே அழற்சியுள்ள திசுக்களுக்கு ஒரு பிரேஸ் தாங்கலாக இருக்க முடியும்; இது குணமாவதற்கு உதவுகிறது [3]. சில சிம்புகள் இயங்கும் (dynamic) வகையைச் சேர்ந்தவை; அதாவது, நீங்கள் பயிற்சி செய்துகொண்டிருக்கும் ஓர் அசைவை நோக்கி, சுருள்வில்களோ ரப்பர் பட்டைகளோ ஒரு மூட்டை இழுக்கின்றன. மற்றவை நிலையான (static) வகையைச் சேர்ந்தவை; அவை வெறுமனே அசையாமல் பிடித்து வைக்கின்றன. ஒவ்வொரு வடிவமைப்புக்கும் அதற்கே உரிய பலங்களும் பலவீனங்களும் உள்ளன [4].
ஒரு காயத்துக்குப் பிறகோ, அறுவை சிகிச்சைக்குப் பிறகோ, அல்லது விறைப்பு மற்றும் நரம்புப் பிரச்சினைகளுக்கோ உங்களுக்குச் சிம்பு வழங்கப்படலாம். கை (hand) மற்றும் மேல் அவயவப் பிரச்சினைகள் போன்ற சில நிலைகளுக்கு, மறுவாழ்வில் சிம்பு அணிவது ஒரு வழக்கமான நடைமுறையாக ஏற்றுக்கொள்ளப்பட்டுள்ளது [5]. ஒரு சிம்பைப் பகலிலோ, இரவிலோ, அல்லது இரண்டு நேரங்களிலுமோ அணிய வேண்டியிருக்கலாம். சில வடிவமைப்புகள் எளிமையானவை; அவற்றுக்குப் பராமரிப்பு ஏறக்குறைய தேவையே இல்லை [6]. பலவற்றைக் குறைந்த செலவிலான பொருட்களிலிருந்து செய்ய முடியும் [7].
சிம்புகள் எப்போதுமே தீர்வாக இருப்பதில்லை. கை (hand) எலும்பு முறிவுகள் பற்றிய ஓர் ஆய்வில், பிளாஸ்டர் மாவுக்கட்டை (plaster cast) விடக் குறைவானவர்களே பிரேஸைத் தொடர்ந்து அணிந்தனர்; பிரேஸ் குழுவில் அதிகமானவர்களுக்குச் சிக்கல்கள் ஏற்பட்டன [8]. உங்கள் காயத்துக்குச் சிம்பு, மாவுக்கட்டு (cast) அல்லது அறுவை சிகிச்சை ஆகியவற்றில் எது சிறப்பாகப் பொருந்தும் என்பதை உங்கள் மருத்துவர் எடைபோடுவார்.
இது பலனளிக்கிறதா?
நேர்மையான பதில்: சிம்பு எதற்காகப் பயன்படுத்தப்படுகிறது என்பதைப் பொறுத்தது. சில நிலைகளுக்கு உறுதியான சான்றுகள் உள்ளன. மற்றவற்றுக்கு, இதுவரை மிகக் குறைவான நல்ல ஆய்வுகளே உள்ளன; உங்கள் மருத்துவர் அனுபவத்தையும் வழக்கமான நடைமுறையையும் நம்பியிருப்பார்.
சில கண்டுபிடிப்புகள் தெளிவானவை. கட்டைவிரலின் அடிப்பகுதியில் மூட்டுவாதம் உள்ளவர்களில், ஆரம்பத்திலேயே சிம்புடன் நன்றாக உணர்ந்தவர்களுக்கு, ஆறு மாதங்கள் கழித்து அவர்களின் அறிகுறிகளில் 54% முதல் 61% வரை முன்னேற்றம் இருந்தது [9]. உடைந்த கை (hand) எலும்புகளுக்கு, சிறிது அசைவை அனுமதிக்கும் ஒரு செயல்பாட்டு பிரேஸ் (functional brace), வழக்கமான சிம்பை விட எலும்புகளை மேலும் நேராகப் பிடித்து வைத்தது [10]. விரலின் பின்புறத்தில் (மேல்புறத்தில்) தசைநாண் கிழிந்தவர்களில், ஒரு வகை இயங்கும் சிம்பைப் பயன்படுத்தியவர்கள், பிற முறைகளில் சிகிச்சை பெற்றவர்களை விடச் சிறப்பாக முன்னேறினர் [11]. மேலும், புறங்கையின் மேல் தசைநாண் காயம் உள்ளவர்கள், அசையாமல் பிடித்து வைக்கும் சிம்பை விட, அசைவை அனுமதிக்கும் சிம்புடன் எட்டு வாரங்கள் முன்னதாகவே முழுச் செயல்பாடுகளுக்குத் திரும்பினர் [12].
மற்ற கண்டுபிடிப்புகள் மேலும் கலவையானவை. டிரிக்கர் விரலுக்கான (trigger finger) சிம்புகள் பலனளிக்கக்கூடும்; கார்ட்டிசோன் ஊசி (cortisone injection) போட்டுக்கொள்ள விரும்பாதவர்களுக்கு அவை பொருத்தமானவை [13]. ஆனால் சிம்புடன் கூடிய விரல் பயிற்சிகள் பற்றிய ஓர் ஆய்வால், அவை அறுவை சிகிச்சை அல்லாத பிற சிகிச்சைகளை விடச் சிறந்தவை என்று காட்ட முடியவில்லை [14]. டுப்யூட்ரென் சுருக்கத்துக்கு (Dupuytren's contracture), சிம்புகளும் அவற்றை அணியும் திட்டங்களும் ஒரு மருத்துவமனைக்கும் மற்றொன்றுக்கும் இடையே மிகப் பரவலாக வேறுபடுவதால், எது சிறப்பாகப் பலனளிக்கிறது என்று அறிவது கடினம் [15]. டுப்யூட்ரென் அறுவை சிகிச்சைக்குப் பிறகு மாதக்கணக்கில் சிம்பு அணிவது நீண்ட காலத்தில் விரலை மேலும் நேராக வைத்திருக்கிறதா என்பதும் தெரியவில்லை [16, 17].
உண்மையான இடைவெளிகள் உள்ளன. சில தசைநாண் சீரமைப்புகளுக்கு, சிம்பு அணியும் முறைகளை ஒப்பிடும் நல்ல சோதனைகள் இல்லை; எனவே சிறந்த அணுகுமுறை இன்னும் தீர்மானிக்கப்படவில்லை [18]. சில சிம்புகள் தோல்வியடையவும் கூடும். ஓர் ஆய்வில், கடுமையான விரல் மூட்டு எலும்பு முறிவு உள்ள சிலருக்கு, அவர்களின் சிம்பு மூட்டைச் சரியான இடத்தில் பிடித்து வைக்காததால் அறுவை சிகிச்சை தேவைப்பட்டது [19].
உங்கள் குறிப்பிட்ட நிலைக்குச் சான்றுகள் என்ன சொல்கின்றன, எதைச் சொல்லவில்லை என்பதை உங்கள் மருத்துவர் உங்களுக்கு விளக்குவார்.
அபாயங்கள் என்ன?
பிரேஸ்கள் மற்றும் சிம்புகளால் ஏற்படும் பெரும்பாலான பிரச்சினைகள் உள்ளூர் அளவிலானவை; அதாவது, அவை சாதனத்தின் கீழ் உள்ள தோலையும் திசுக்களையும் பாதிக்கின்றன. உராயும் அல்லது அளவுக்கு மீறி அழுத்தும் சிம்பு புண்ணை ஏற்படுத்தலாம்; சில வடிவமைப்புகள் மற்றவற்றை விட இயல்பாகவே அதிக வசதியானவை. ஒரு புதிய வகை விரல் சிம்பு, மாவுக்கட்டை விட மிகவும் வசதியானதாகக் கண்டறியப்பட்டது; ஆனால் அதை அணிந்தவர்கள் அதை இன்னும் தொல்லையாகவே உணர்ந்தனர் [20]. ஒரு சிம்பு அசௌகரியமாக இருந்தால், உங்கள் சிகிச்சையாளரிடமோ (therapist) மருத்துவரிடமோ சொல்லுங்கள்; ஏனெனில் அதன் பொருத்தத்தில் செய்யப்படும் சிறிய மாற்றங்கள் பெரும்பாலும் உதவுகின்றன.
சிம்புகள் தங்கள் வேலையைச் செய்யத் தவறவும் கூடும். ஓர் ஆய்வில், கடுமையான விரல் மூட்டு எலும்பு முறிவு உள்ள மூன்று பேருக்கு, அவர்களின் சிம்பு உடைந்த எலும்புகளைச் சரியான இடத்தில் பிடித்து வைக்காததால் பின்னர் அறுவை சிகிச்சை தேவைப்பட்டது; அதனால் அவர்களின் விளைவுகளும் மோசமாக இருந்தன [19]. இதனால்தான் பரிசோதனைகளுக்காக மீண்டும் வருமாறு உங்களிடம் கேட்கப்படும்; அப்போது சிம்பு இன்னும் எல்லாவற்றையும் இருக்க வேண்டிய இடத்தில் பிடித்து வைத்திருக்கிறதா என்பதைக் குழு உறுதிசெய்ய முடியும்.
திட்டத்தைத் தொடர்ந்து பின்பற்றுவதும் முக்கியம். கை (hand) எலும்பு முறிவுகள் பற்றிய ஓர் ஆய்வில், பிளாஸ்டர் மாவுக்கட்டில் இருந்தவர்களில் 81% பேர் தங்கள் சிகிச்சையை முடித்தனர்; ஆனால் பிரேஸ் வழங்கப்பட்டவர்களில் 41% பேர் மட்டுமே முடித்தனர்; பிரேஸ் குழுவிலிருந்து விலகியவர்களில் 60% பேர் சிக்கல்களால் விலகினர் [8]. குழந்தைகள் சிம்புகளைக் கழற்றிவிடலாம்; மாற்றியமைக்கப்பட்ட ஒரு கட்டைவிரல் சிம்பு வடிவமைப்பு இதைத் தடுக்க உதவியதாக ஒரு மருத்துவமனை கண்டறிந்தது [21].
தெரிந்தவற்றில் உண்மையான இடைவெளிகளும் உள்ளன. சில தசைநாண் சீரமைப்புகளுக்கு, சிம்பு அணியும் முறைகளை ஒப்பிடும் நல்ல சோதனைகள் இல்லை; எனவே ஒவ்வொரு அணுகுமுறையின் அபாயங்களும் முழுமையாகத் தீர்மானிக்கப்படவில்லை [18]. டுப்யூட்ரென் சுருக்கத்துக்கு, அறுவை சிகிச்சைக்குப் பிறகு மாதக்கணக்கில் சிம்பு அணிவது விரலை மேலும் நேராக வைத்திருக்கிறதா, அல்லது அது விரலை மடக்கும் திறனில் ஏதேனும் இழப்பை ஏற்படுத்துகிறதா என்பது தெரியவில்லை [16, 17]. இந்த அபாயங்களில் எவை உங்கள் காயத்துக்குப் பொருந்தும், எந்த எச்சரிக்கை அறிகுறிகளைக் கவனிக்க வேண்டும் என்பதை உங்கள் மருத்துவர் விளக்குவார்.
இது உங்களுக்குப் பொருத்தமானதா?
உங்கள் பிரச்சினை அறுவை சிகிச்சையை விடச் சீரான தாங்கலுக்குப் பதிலளிக்கும் வகையைச் சேர்ந்ததாக இருந்தால், ஒரு சிம்பு அல்லது பிரேஸ் உங்களுக்குப் பொருந்தலாம். சில கை (hand) மற்றும் மணிக்கட்டுக் காயங்கள், ஒரு விரல் மூட்டில் விறைப்பு, கட்டைவிரலின் அடிப்பகுதியில் மூட்டுவாதம், சில நரம்புப் பிரச்சினைகள் ஆகியவை இதில் அடங்கும். பல கை மற்றும் மேல் அவயவ நிலைகளுக்குச் சிம்பு அணிவது ஒரு வழக்கமான நடைமுறையாக ஏற்றுக்கொள்ளப்பட்டுள்ளது [5]. சிலர் அறுவை சிகிச்சையைத் தள்ளிப்போடவோ தவிர்க்கவோ சிம்பைத் தேர்ந்தெடுக்கின்றனர். கட்டைவிரல் மூட்டுவாதத்துக்கு, அருகிலுள்ள மூட்டுகளை அசைய விட்டுவிட்டுக் கட்டைவிரலை மட்டும் பிடித்து வைக்கும் ஒரு சிறிய சிம்பு, அறுவை சிகிச்சை வேண்டாம் என்று முடிவு செய்பவர்களுக்கான ஒரு தேர்வு [22].
ஒவ்வொரு காயத்துக்கும் ஒவ்வொரு நபருக்கும் சிம்பு பொருத்தமானதல்ல. சில வடிவமைப்புகள், உங்கள் காயத்துக்குப் பொருந்தாத ஒரு நிலையில் மூட்டைப் பிடித்து வைக்கின்றன. உதாரணமாக, அருகிலுள்ள ஒரு மூட்டு முழுமையாக நேராகப் பிடித்து வைக்கப்பட வேண்டியிருக்கும்போது, அசைவை அனுமதிக்கும் விரல் சிம்பைப் பயன்படுத்தக்கூடாது [23]. சில சிம்புகள் உடைந்த எலும்புகளைச் சரியான இடத்தில் பிடித்து வைக்கவும் தவறுகின்றன; ஓர் ஆய்வில் சிலருக்கு இதனால் பின்னர் அறுவை சிகிச்சை தேவைப்பட்டது [19]. உங்கள் காயம், உங்கள் வேலை, சிம்பு அணியும் திட்டத்தை நீங்கள் எந்த அளவுக்குப் பின்பற்றக்கூடும் என்பவற்றின் அடிப்படையில், சிம்பை மாவுக்கட்டுடனோ அறுவை சிகிச்சையுடனோ ஒப்பிட்டு உங்கள் மருத்துவர் எடைபோடுவார்.
நீங்கள் எதிர்பார்ப்பதை விட வசதியும் பொருத்தமும் அதிக முக்கியம். அணிய எளிதாக இருக்கும் சிம்பையே நீங்கள் உண்மையில் தொடர்ந்து அணிவீர்கள்; உங்கள் கையை (hand) பயன்படுத்த அனுமதிக்கும் வடிவமைப்புகள் சிறந்த பின்பற்றலுக்கு வழிவகுக்கின்றன [24]. ஒரு சிம்பு சரியாக உணரப்படவில்லை என்றால், அதைச் சொல்லுங்கள். சிறிய மாற்றங்கள் பெரும்பாலும் பிரச்சினையைச் சரிசெய்கின்றன.
இது உங்கள் மருத்துவருடன் பகிர்ந்து எடுக்கப்படும் முடிவாக இருக்க வேண்டும். என்ன தவறு நேரலாம் என்பதை மேலே உள்ள அபாயங்கள் பகுதி விளக்குகிறது; அவற்றில் எவை உங்களுக்குப் பொருந்தும் என்பதை உங்கள் மருத்துவர் விளக்குவார்.
சுருக்கமாக
பல கை (hand), மணிக்கட்டு, முழங்கைப் பிரச்சினைகளுக்கு, குறிப்பாக நீங்கள் அறுவை சிகிச்சையைத் தவிர்க்கவோ தள்ளிப்போடவோ விரும்பினால், ஒரு பிரேஸ் அல்லது சிம்பைப் பரிசீலிப்பது பயனுள்ளது. சில வடிவமைப்புகள் எளிமையானவை, வசதியானவை; அருகிலுள்ள மூட்டுகளைத் தொடர்ந்து பயன்படுத்த அவை உங்களை அனுமதிக்கின்றன [22, 25]. சில நிலைகளுக்குச் சான்றுகள் மற்றவற்றை விட வலுவானவை; எனவே உங்கள் நிலைக்கு என்ன தெரியும் என்று கேளுங்கள். மிக முக்கியமான ஒன்று பொருத்தமும் தொடர்ந்து பின்பற்றுதலும்: சரியாக உணரப்படும் சிம்பையே நீங்கள் உண்மையில் அணிவீர்கள்; அறிவுறுத்தப்பட்டபடி அதை அணிவதே பலனைத் தருகிறது.
மேற்கோள்கள்
[1] Short-term Outcomes of the Cross Brace Protocol for ACL Rupture Management: A Prospective Cohort Study. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967126s00013
[2] Plaster of Paris: The forgotten hand splinting material. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015014
[3] REHABILITATION CONCEPTS AND SUPPORTIVE DEVICES FOR OVERUSE INJURIES OF THE UPPER EXTREMITIES. Clinics in Sports Medicine. 2001. DOI: 10.1016/s0278-5919(05)70273-8
[4] Force analysis of the belly gutter and capener splints. Journal of Hand Therapy. 1999. DOI: 10.1016/s0894-1130(99)80074-x
[5] The influence of splinting on healing tissues. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80014-8
[6] A modification of the kleinert splint for mobilisation of digital flexor tendons. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90007-6
[7] Examples of simply fabricated, custom-made splints for the hand. The Journal of Hand Surgery. 1981. DOI: 10.1016/s0363-5023(81)80008-1
[8] Functional Fracture Bracing in Metacarpal Fractures: The Galveston Metacarpal Brace versus a Plaster-of-Paris Bandage in a Prospective Study. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80327-9
[9] Splinting in the treatment of arthritis of the first carpometacarpal joint. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.jhsu24a0086
[10] Functional bracing of fractures of the second through fifth metacarpals. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80179-x
[11] The pipflex splint for treatment of mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90126-x
[12] Results of acute zone III extensor tendon injuries treated with dynamic extension splinting. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80082-6
[13] Trigger fingers and thumb: When to splint, inject, or operate. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90124-8
[14] Effectiveness of Proximal Interphalangeal Joint Orthosis and Therapeutic Exercise in the Management of Trigger Finger: A Prospective Case Series. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101038
[15] A Review of Attitudes to Splintage in Dupuytren's Contracture. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90208-j
[16] A review of attitudes to splintage in Dupuytren's contracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90182-3
[17] A Review of Attitudes to Splintage in Dupuytren’s Contracture. Journal of Hand Surgery. 1987. DOI: 10.1016/0266-7681_87_90182-3
[18] Splints, with or without wrist immobilization, following surgical repair of flexor tendon lesions of the hand: A systematic review. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.05.004
[19] Dorsal Fracture Subluxation of the Proximal Interphalangeal Joints Treated by Extension Block Splintage. Journal of Hand Surgery. 1992. DOI: 10.1016/s0266-7681(05)80249-9
[20] A new method of extension-block splinting for the proximal interphalangeal joint—Preliminary report. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80118-3
[21] Modification to a pediatric thumb splint. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.014
[22] The biomechanics of a thumb carpometacarpal immobilization splint: Design and fitting. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80006-x
[23] Dynamic flexion splint for the distal interphalangeal joint. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00041-3
[24] Low Profile Extension Splint for Active Extensor Lag of the Proximal Interphalangeal Joint. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2007.04.008
[25] Design of an orthosis with straight spring for extension mobilization of flexion contracture of the proximal interphalangeal joint. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.01.005
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Splint design plays a more significant role in dynamic extensor splinting than previously expected [1].
- The Swing Design Dynamic Traction Splint offers similar benefits to previously reported splints and is simple and compact in design [2].
- Topics selected for a special issue on splinting are intended to advance the artistry of splinting toward an evidence-based practice approach [3].
- The application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in this rehabilitation arena [4].
- The clamshell splint with otoform lining has proven equally effective for other conditions requiring immobilization [5].
- In a single-subject experiment on radial nerve palsy, only splint 3 met the criteria of improving function and being worn by the patient [6].
- To the authors' knowledge, the optimal orthosis for the complete median and radial nerve-injured war casualty has not been previously described [7].
- The conclusion that sling immobilization is 'not inferior' to brace immobilization after arthroscopic rotator cuff repair cannot be attributed solely to the type of immobilization [8].
- A modification of the Kleinert splint for mobilisation of digital flexor tendons is easy to make and requires virtually no maintenance due to its simplicity [9].
- Many splints can be constructed with material that is inexpensive, available, and often discarded [10].
- The modified Kleinert splint appears to be producing improved results and to be gaining more widespread acceptance [11].
- The patient for whom the adjustable first webspace splint was initially developed has recovered a very satisfying webspace thanks to the splint [12].
- The types of splint and programmes for using them in Dupuytren's contracture varied widely [19].
- Force analysis of the belly gutter and capener splints clearly indicates theoretical advantages and disadvantages of the dynamic and static splint designs [22].
- In a prospective study of metacarpal fractures, only 41% of patients from the metacarpal-brace group completed the treatment, compared to 81% in the plaster-cast group [24].
- In a prospective study of metacarpal fractures, 60% of exclusions in the brace group were due to complications [24].
- Dynamic flexion splinting for the distal interphalangeal joint is contraindicated in situations that require the PIP to be held in full extension [33].
- The concept of a straight spring for an orthosis for extension mobilization of flexion contracture of the proximal interphalangeal joint was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient [34].
- The only drawback to Plaster of Paris splints was that if changes were needed, a whole new splint had to be fabricated [39].
- To date, selection of the proper splint for managing joint stiffness has been empirical [41].
- A volar splint has clear limitations regarding immobilization, which is of relevance in clinical practice [63].
- An ulnar boost splint for midcarpal instability follows recommendations to support the pisotriquetral area [64].
How It Works
- The application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in rehabilitation [4].
- The optimal orthosis for the complete median and radial nerve-injured war casualty has not been previously described to the authors' knowledge [7].
- The modified Kleinert splint for mobilisation of digital flexor tendons is easy to make and requires virtually no maintenance due to its simplicity [9].
- Many hand splints can be constructed with material that is inexpensive, available, and often discarded [10].
- The modified Kleinert splint appears to be producing improved results and is gaining more widespread acceptance [11].
- The adjustable first webspace splint allowed the patient for whom it was initially developed to recover a very satisfying webspace [12].
- Therapeutic hand splint texts focus on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions [13].
- A silicone splint has value as both a protective splint following injury and prophylactically for diving injuries of the thumb [14].
- Limited results from an underpowered study suggest splinting may not be required postoperatively for isolated digital nerve injuries in the hand [15].
- Studies involving smaller numbers of subjects can contribute greatly to substantiating the effectiveness of splinting if performed with the highest level of study design and use standardized outcome measures [16].
- James traction splinting interventions for PIP fractures have been highlighted in two case studies at military treatment facilities [17].
- Three patients with dorsal fracture subluxation of the proximal interphalangeal joints initially managed with splintage proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome [18].
- A static gutter splint may be worn at night to maintain gains achieved in the day for distal interphalangeal joint flexion contractures [20].
- Braces during the early phase of overuse injuries of the upper extremities provide support to inflamed tissues without complete immobilization, facilitating healing [21].
- Force analysis clearly indicates theoretical advantages and disadvantages of dynamic and static splint designs for belly gutter and capener splints [22].
- Low-profile dynamic splints assist therapists in the prescription of splints for certain patients and enable them to monitor progress closely [23].
- Only 41% of patients from the metacarpal-brace group completed treatment compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications [24].
- A newly developed buddy splint corrects the mechanical and kinesiologic disadvantages of current buddy strapping systems [25].
- The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than dynamic or static progressive splinting [26].
- The objective of providing reduction and stability to the thumb metacarpophalangeal joint and improving function was achieved with a three-point static splint for chronic volar subluxation [27].
- The objective of providing reduction and stability to the MP joint and improving function was achieved with the Ambulatory Arm Elevator Sling (Hands Up) [28].
- It is necessary to determine whether patients treated with static splintage for several months after operation for Dupuytren's contracture achieve better extension at 12 to 18 months and if there is any loss of flexion in this group [30, 31].
- The modified Kleinert controlled mobilization splint has theoretical advantages over the usual Kleinert splint and may be of clinical use [42].
- Creation of splint designs should be based on mechanical fact rather than on mode-of-the-day bias [43].
- A better position for splintage of mallet finger deformities is slight flexion, as hyperextension provided by a splint is likely to cause the subluxation to appear [44].
- Surgery and the postoperative regimen of rigid night splints and web-retaining gloves for day wear has allowed arrest or minimal progression of contractures in compliant patients with recessive dystrophic epidermolysis bullosa in short-term follow-up of an average of 17 months [46].
- The Cross Brace Protocol provides an additional non-operative option for ACL injuries and may be associated with satisfactory anatomical and functional healing for certain patient groups [47].
What the Evidence Shows
General Principles and Materials
- Splint design plays a more significant role than previously expected [1].
- Woodcast splints are used in clinical practice with good results and high patient acceptability [38].
- The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than does dynamic or static progressive splinting [26].
- Studies involving smaller numbers of subjects can contribute greatly to the evidence base so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions [16].
- The lack of high-quality evidence means that randomized clinical trials need to be performed to guide rehabilitation choices for splints with or without wrist immobilization following surgical repair of flexor tendon lesions [65].
Fractures and Dislocations
- Functional bracing of fractures of the second through fifth metacarpals resulted in a final angulation averaging 15° in the brace group compared to 31° in the splint group [49].
- The objective of providing reduction and stability to the MP joint and improving function was achieved with an ambulatory arm elevator sling [28].
Tendon Injuries
- A new dynamic splint for postoperative treatment of flexor tendon injury produced results that were significantly better than after treatment in the traditional splint [52].
- Patients with acute zone III extensor tendon injuries treated with dynamic extension splinting returned to full activities with good-to-excellent results 8 weeks earlier instead of at 16 to 18 weeks compared to static splinting [60].
- A modification of the Kleinert splint for mobilisation of digital flexor tendons is easy to make and requires virtually no maintenance [9].
Nerve Injuries and Palsy
- In a single-subject experiment on splinting for radial nerve palsy, only splint 3 met the criteria of improving function and being worn by the patient [6].
- Although an underpowered study on postoperative splinting for isolated digital nerve injuries in the hand suggests splinting may not be required postoperatively, these limited results are based on a small sample [15].
Contractures and Stiffness
- The functional arc of motion or very close to it was achieved using patient-adjusted static elbow splints after failure of conservative treatment for elbow contractures [62].
- In Dupuytren's contracture, the types of splint and programmes for using them varied widely [19].
- It is necessary to determine whether patients treated with static splintage for several months after Dupuytren's contracture operation achieve better extension at 12 to 18 months and if there is any loss of flexion in this group [30, 31].
Trigger Finger
- Splinting offers an alternative for patients who have a strong objection to cortisone injection for trigger fingers and thumb [37].
- A low-profile ring splint for trigger finger is easily fabricated and functional, and the treatment protocol requires minimal therapy visits [58].
- A prospective case series on proximal interphalangeal joint orthosis and therapeutic exercise for trigger finger demonstrates feasibility and short-term clinical improvement but cannot establish superiority over other conservative treatments due to the absence of a control group [50].
Arthritis and Overuse
- All patients with arthritis of the first carpometacarpal joint who had initial improvement in their symptoms with splinting had between 54% and 61% average improvement in symptom severity 6 months after splinting [55].
Specific Splint Designs and Applications
- The Swing Design Dynamic Traction Splint for intra-articular fractures of the digits offers similar benefits to splints reported previously in the literature and is simple and compact in design [2].
- An adjustable first webspace splint was developed for a patient who recovered a very satisfying webspace thanks to the splint [12].
- A supination splint worn distal to the elbow is clinically effective in increasing supination passive range of motion [53].
- The results of treatment with the pipflex splint for mallet finger in 25 patients are superior to those resulting from other methods of splintage [61].
- The significantly superior results of the double-T splint for maintaining the safe position in a palmar splint are worth the additional 50 g weight [59].
- A modification to a pediatric thumb splint has aided in preventing children in the clinic from removing their splints [35].
- A new power source in dynamic splinting with lower force-extension ratios has helped to improve range of motion within the splint, although further controlled trials are needed to confirm this [40].
- Relative motion orthoses may improve outcomes in a variety of hand conditions, however, high-quality studies that contribute to the evidence base for its use are needed [29].
Practical Considerations
Design and Biomechanics
- The text focuses on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions [13].
- A straight spring concept for an orthosis was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient [34].
- Lower force-extension ratios in dynamic splinting have helped to improve range of motion within the splint, although further controlled trials are needed to confirm this [40].
- Low-profile dynamic splints assist therapists in the prescription of splints for certain patients and enable them to monitor their progress closely [23].
Materials and Fabrication
- The Reston foam splint is a very comfortable, safe, versatile, and simple splint that is much cheaper and more readily available than conventional manufactured splints [56].
- Further studies are suggested for comparing time and cost effectiveness between commercially available splinting materials [32].
- A modified Kleinert splint is easy to make and, because of its simplicity, requires virtually no maintenance [9].
- A static progressive wrist extension splint is easy to fabricate, cost-effective, and relatively comfortable [48].
Clinical Application and Outcomes
- Only splint 3 met the criteria of improving function and being worn by the patient in a single-subject experiment for radial nerve palsy [6].
- A modified Kleinert splint appears to be producing improved results and to be gaining more widespread acceptance [11].
- The patient for whom an adjustable first webspace splint was initially developed has recovered a very satisfying webspace thanks to the splint [12].
- Studies involving smaller numbers of subjects can contribute greatly to substantiating the effectiveness of splinting, so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions [16].
- Three patients initially managed with extension block splintage for dorsal fracture subluxation of the proximal interphalangeal joints proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome [18].
- A static gutter splint may be worn at night to maintain gains achieved in the day for distal interphalangeal joint flexion contracture [20].
- A dynamic flexion splint for the distal interphalangeal joint is contraindicated in situations that require the proximal interphalangeal joint to be held in full extension [33].
- A splint modification has aided in preventing children in a clinic from removing their pediatric thumb splints [35].
- If patients with minimally displaced distal radial fractures can be treated safely using a removable splint, this will save them time and inconvenience in terms of additional visits to the hospital, and save the healthcare system money [45].
- An alternative flexion splinting protocol requires only the flexion splint as opposed to the traditional extension splint followed by flexion splinting; therefore, the cost of splint fabrication is reduced and the instructions to patients for following their splinting programs are simplified [51].
- A thumb carpometacrotacarpal immobilization splint allows unrestricted use of adjacent joints and is a cost-effective, efficient treatment option for those patients who elect to postpone or exclude surgical reconstruction for thumb CMC joint pain [54].
- Although the authors found an extension-block splint for the proximal interphalangeal joint annoying, it was much more comfortable than an extension-block cast [57].
Key Evidence
- [Paper] This shows that splint design plays a more significant role than previously expected. [1] (10.1016/0363-5023(92)90404-d)
- [L4] It offers similar benefits to splints reported previously in the literature, and is simple and compact in design. [2] (10.1197/j.jht.2005.11.001)
- [L5] The topics selected for inclusion in this special issue are intended to advance the artistry of splinting toward an evidence-based practice approach. [3] (10.1053/hanthe.2002.v15.015009)
- [L5] Currently, the application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in this rehabilitation arena. [4] (10.1016/s0894-1130(98)80014-8)
- [L5] The splint has proven equally effective for other conditions requiring immobilization. [5] (10.1016/s0894-1130(97)80046-4)
- [L5] Only splint 3 met the criteria of improving function and being worn by the patient. [6] (10.1016/s0894-1130(01)80053-3)
- [L5] To the authors' knowledge the optimal orthosis for this situation has not been previously described. [7] (10.1016/s0894-1130(12)80275-4)
- [L5] They argue that the conclusion that sling immobilization is 'not inferior' to brace immobilization cannot be attributed solely to the type of immobilization. [8] (10.1002/arj.70326)
- [L4] The splint is easy to make and, because of its simplicity, requires virtually no maintenance. [9] (10.1016/0266-7681(87)90007-6)
- [L5] The examples given show that many splints can be constructed with material that is inexpensive, available, and often discarded. [10] (10.1016/s0363-5023(81)80008-1)
- [L5] The modified splint appears to be producing improved results and to be gaining more widespread acceptance. [11] (10.1016/s0363-5023(88)80070-4)
- [L5] The patient for whom the splint was initially developed has recovered a very satisfying webspace thanks to the splint. [12] (10.1016/s0894-1130(96)80091-3)
- [Paper] The text focuses on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions. [13] (10.1016/s0894-1130(02)70027-6)
- [L5] Our clinical opinion is that it has value as both a protective splint following injury and as well as prophylacticly. [14] (10.1197/j.jht.2006.07.029)
- [L1] Although this study is underpowered, these limited results suggest splinting may not be required postoperatively. [15] (10.1197/j.jht.2007.04.010)
- [Paper] While studies that include large numbers of subjects are needed to substantiate the effectiveness of splinting, studies involving smaller numbers of subjects can contribute greatly as well, so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions. [16] (10.1053/hanthe.2002.v15.0150131)
- [L4] The authors present two case studies highlighting James traction splinting interventions and corresponding outcomes at military treatment facilities. [17] (10.1197/j.jht.2007.08.019)
- [L3] Three patients initially managed with splintage proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome. [18] (10.1016/s0266-7681(05)80249-9)
- [L5] The types of splint and programmes for using them varied widely. [19] (10.1016/0266-7681(92)90208-j)
- [L5] A static gutter splint may be worn at night to maintain gains achieved in the day. [20] (10.1016/s0894-1130(01)80009-0)
- [L5] Braces during the early phase provide support to inflamed tissues without complete immobilization, facilitating healing. [21] (10.1016/s0278-5919(05)70273-8)
- [L3] It clearly indicates theoretical advantages and disadvantages of the dynamic and static splint designs. [22] (10.1016/s0894-1130(99)80074-x)
- [Paper] This will assist therapists in the prescription of splints for certain patients and enable them to monitor their progress closely. [23] (10.1016/s0894-1130(12)80332-2)
- [L1] Only 41% of the patients from the metacarpal-brace group completed the treatment, compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications. [24] (10.1016/s0894-1130(12)80327-9)
- [Paper] This newly developed buddy splint corrects the mechanical and kinesiologic disadvantages of current buddy strapping systems. [25] (10.1016/s0894-1130(12)80041-x)
- [L5] The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than does dynamic or static progressive splinting. [26] (10.1053/hanthe.2002.v15.015014)
- [L5] The objective of providing reduction and stability to the MP joint and improving function was achieved with this splint. [27] (10.1016/s0894-1130(12)80062-7)
- [Paper] The objective of providing reduction and stability to the MP joint and improving function was achieved with this splint. [28] (10.1016/s0894-1130(12)80064-0)
- [Paper] RM orthoses may improve outcomes in a variety of hand conditions; however, high-quality studies that contribute to the evidence base for its use are needed. [29] (10.1016/j.jht.2016.07.001)
- [L5] In particular, we need to know whether patients treated with static splintage for several months after operation achieve better extension at 12 to 18 months and, if so, is there any loss of flexion in this group? [30] (10.1016/0266-7681(87)90182-3)
- [L5] In particular, we need to know whether patients treated with static splintage for several months after operation achieve better extension at 12 to 18 months and, if so, is there any loss of flexion in this group? [31] (10.1016/0266-7681_87_90182-3)
- [L4] Further studies are suggested for comparing time and cost effectiveness between commercially available splinting materials. [32] (10.1016/s0894-1130(98)80060-4)
- [L5] This splinting tack is contraindicated in situations that require the PIP to be held in full extension. [33] (10.1016/s0894-1130(03)00041-3)
- [Paper] The concept of a straight spring for this orthosis was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient. [34] (10.1016/j.jht.2020.01.005)
- [L5] This splint modification has aided in preventing children in our clinic from removing their splints. [35] (10.1197/j.jht.2004.04.014)
- [L4] Splinting offers an alternative for patients who have a strong objection to cortisone injection. [37] (10.1016/0363-5023(92)90124-8)
- [L5] Woodcast splints are used in clinical practice with good results and high patient acceptability. [38] (10.1097/bth.0000000000000210)
- [Paper] The only drawback to these splints was that if changes were needed, a whole new splint had to be fabricated. [39] (10.1016/s0894-1130(12)80157-8)
- [L4] It is their initial impression that the lower force-extension ratios have helped to improve range of motion within the splint, although further controlled trials are needed to confirm this. [40] (10.1016/s0894-1130(89)80022-5)
- [L5] To date, selection of the proper splint for managing joint stiffness has been empirical. [41] (10.1053/hanthe.2002.v15.015015)
- [L5] The modified splint has theoretical advantages over the usual Kleinert splint and it may be of clinical use—further trials are in progress. [42] (10.1016/s0266-7681(84)80039-x)
- [Paper] Creation of splint designs should be based on mechanical fact rather than on mode-of-the-day bias. [43] (10.1016/s0894-1130(12)80309-7)
- [L5] The author suggests that a better position for splintage is slight flexion, as hyperextension provided by a splint is likely to cause the subluxation to appear. [44] (10.1016/s0363-5023(85)80277-x)
- [L2] If patients can be treated safely using a removable splint, this will save them time and inconvenience in terms of additional visits to the hospital, and save the healthcare system money. [45] (10.1302/0301-620x.107b1.bjj-2024-0634.r1)
- [L4] Surgery and the postoperative regimen of rigid night splints and web-retaining gloves for day wear has allowed arrest or minimal progression of contractures in compliant patients in short-term follow-up study of an average of 17 months. [46] (10.1016/s0363-5023(96)80210-3)
- [L2] The Cross Brace Protocol provides an additional non-operative option for ACL injuries and may be associated with satisfactory anatomical and functional healing for certain patient groups. [47] (10.1177/2325967126s00013)
- [L5] Based on clinical experience, the authors have found this splint is easy to fabricate, cost-effective, and relatively comfortable. [48] (10.1016/s0894-1130(02)80009-6)
- [L2] Final angulation averaged 15° in the brace group compared to 31° in the splint group. [49] (10.1016/s0363-5023(87)80179-x)
- [L4] Because of the absence of a control group, these findings demonstrate feasibility and short-term clinical improvement but cannot establish superiority over other conservative treatments. [50] (10.1016/j.jhsg.2026.101038)
- [L4] This protocol requires only the flexion splint as opposed to the traditional extension splint followed by flexion splinting; therefore, the cost of splint fabrication is reduced and the instructions to patients for following their splinting programs are simplified. [51] (10.1016/s0894-1130(96)80022-6)
- [L4] Results were significantly better than after treatment in the traditional splint. [52] (10.1016/s0363-5023(89)80025-5)
- [L4] Results indicate the supination splint is clinically effective in increasing supination PROM. [53] (10.1016/s0894-1130(03)00034-6)
- [L5] This small splint allows unrestricted use of adjacent joints and is a cost-effective, efficient treatment option for those patients who elect to postpone or exclude surgical reconstruction for thumb CMC joint pain. [54] (10.1016/s0894-1130(00)80006-x)
- [L4] All patients who had initial improvement in their symptoms with splinting had between 54% and 61% average improvement in symptom severity 6 months after splinting. [55] (10.1053/jhsu.1999.jhsu24a0086)
- [L5] The Reston foam splint is a very comfortable, safe, versatile, and simple splint that is much cheaper and more readily available than conventional manufactured splints. [56] (10.1016/s0363-5023(89)80029-2)
- [L4] Although the authors found the splint annoying, it was much more comfortable than an extension-block cast. [57] (10.1016/s0363-5023(80)80118-3)
- [L4] This low-profile ring splint is easily fabricated and functional and the treatment protocol requires minimal therapy visits. [58] (10.1197/j.jht.2008.05.001)
- [L2] The significantly superior results of the double-T splint are worth this additional 50 g. [59] (10.1016/s0266-7681(05)80214-1)
- [L2] When results were compared with the results of our method of static splinting used prior to this prospective study, patients returned to full activities with good-to-excellent results 8 weeks earlier instead of at 16 to 18 weeks. [60] (10.1016/s0363-5023(10)80082-6)
- [L4] The results of treatment in 25 patients are superior in our hands to those resulting from other methods of splintage. [61] (10.1016/0266-7681(88)90126-x)
- [L4] The functional arc of motion or very close to it was achieved using patient-adjusted static splints after failure of conservative treatment. [62] (10.1016/s1058-2746(95)80215-0)
- [L4] A volar splint has clear limitations regarding immobilization, which is of relevance in clinical practice. [63] (10.1177/1753193416686039)
- [L5] The splint follows recommendations to support the pisotriquetral area. [64] (10.1197/j.jht.2004.04.013)
- [L5] The lack of high-quality evidence means that randomized clinical trials need to be performed to guide rehabilitation choices. [65] (10.1016/j.hansur.2019.05.004)
References
[1] Electrophysiologic basis of dynamic extensor splinting. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90404-d
[2] Swing Design Dynamic Traction Splinting for the Treatment of Intra-articular Fractures of the Digits. Journal of Hand Therapy. 2006. DOI: 10.1197/j.jht.2005.11.001
[3] The splinting issue. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015009
[4] The influence of splinting on healing tissues. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80014-8
[5] The clamshell splint with otoform lining. Journal of Hand Therapy. 1997. DOI: 10.1016/s0894-1130(97)80046-4
[6] Splinting and radial nerve palsy: A single-subject experiment. Journal of Hand Therapy. 2001. DOI: 10.1016/s0894-1130(01)80053-3
[7] Orthosis for the Complete Median and Radial Nerve-injured War Casualty. Journal of Hand Therapy. 1992. DOI: 10.1016/s0894-1130(12)80275-4
[8] Regarding “Sling Is Not Inferior to Brace Immobilization After Arthroscopic Rotator Cuff Repair: A Randomized Controlled Trial”. Arthroscopy. 2026. DOI: 10.1002/arj.70326
[9] A modification of the kleinert splint for mobilisation of digital flexor tendons. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90007-6
[10] Examples of simply fabricated, custom-made splints for the hand. The Journal of Hand Surgery. 1981. DOI: 10.1016/s0363-5023(81)80008-1
[11] Kleinert splint. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80070-4
[12] Adjustable First Webspace Splint. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80091-3
[13] Therapeutic Hand Splints: A Rational Approach. Volume 1: Mechanical and Biomechanical Considerations. Journal of Hand Therapy. 2002. DOI: 10.1016/s0894-1130(02)70027-6
[14] A Silicone Splint to Prevent Diving Injuries of the Thumb. Journal of Hand Therapy. 2006. DOI: 10.1197/j.jht.2006.07.029
[15] Postoperative Splinting for Isolated Digital Nerve Injuries in the Hand. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2007.04.010
[16] Outcomes, treatment effectiveness, efficacy, and evidence-based practice: Examples from the world of splinting. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.0150131
[17] James Traction Splinting for PIP Fractures. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2007.08.019
[18] Dorsal Fracture Subluxation of the Proximal Interphalangeal Joints Treated by Extension Block Splintage. Journal of Hand Surgery. 1992. DOI: 10.1016/s0266-7681(05)80249-9
[19] A Review of Attitudes to Splintage in Dupuytren's Contracture. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90208-j
[20] A flexion contracture splint for the distal interphalangeal joint. Journal of Hand Therapy. 2001. DOI: 10.1016/s0894-1130(01)80009-0
[21] REHABILITATION CONCEPTS AND SUPPORTIVE DEVICES FOR OVERUSE INJURIES OF THE UPPER EXTREMITIES. Clinics in Sports Medicine. 2001. DOI: 10.1016/s0278-5919(05)70273-8
[22] Force analysis of the belly gutter and capener splints. Journal of Hand Therapy. 1999. DOI: 10.1016/s0894-1130(99)80074-x
[23] Low-profile Dynamic Splints: A Solution to the Friction Problem. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80332-2
[24] Functional Fracture Bracing in Metacarpal Fractures: The Galveston Metacarpal Brace versus a Plaster-of-Paris Bandage in a Prospective Study. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80327-9
[25] Buddy Splint. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80041-x
[26] Plaster of Paris: The forgotten hand splinting material. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015014
[27] Three-Point Static Splint for Chronic Volar Subluxation of the Thumb Metacarpophalangeal Joint. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80062-7
[28] Ambulatory Arm Elevator Sling (Hands Up). Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80064-0
[29] Relative motion orthoses in the management of various hand conditions: A scoping review. Journal of Hand Therapy. 2016. DOI: 10.1016/j.jht.2016.07.001
[30] A review of attitudes to splintage in Dupuytren's contracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90182-3
[31] A Review of Attitudes to Splintage in Dupuytren’s Contracture. Journal of Hand Surgery. 1987. DOI: 10.1016/0266-7681_87_90182-3
[32] Comparison study of quickcast versus a traditional thermoplastic in the fabrication of a resting hand splint. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80060-4
[33] Dynamic flexion splint for the distal interphalangeal joint. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00041-3
[34] Design of an orthosis with straight spring for extension mobilization of flexion contracture of the proximal interphalangeal joint. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.01.005
[35] Modification to a pediatric thumb splint. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.014
[37] Trigger fingers and thumb: When to splint, inject, or operate. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90124-8
[38] An Eco-conscious Alternative Material for Splinting in Hand Surgery. Techniques in Hand & Upper Extremity Surgery. 2018. DOI: 10.1097/bth.0000000000000210
[39] Plaster of Paris Splints. Journal of Hand Therapy. 1995. DOI: 10.1016/s0894-1130(12)80157-8
[40] A new power source in dynamic splinting: Clinical experience and results. Journal of Hand Therapy. 1989. DOI: 10.1016/s0894-1130(89)80022-5
[41] A proposed decision hierarchy for splinting the stiff joint, with an emphasis on force application parameters. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015015
[42] A Modified Kleinert Controlled Mobilization Splint Following Flexor Tendon Repair. Journal of Hand Surgery. 1984. DOI: 10.1016/s0266-7681(84)80039-x
[43] Splints: Mechanics versus Convention. Journal of Hand Therapy. 1995. DOI: 10.1016/s0894-1130(12)80309-7
[44] Molded polythene splint for mallet finger deformities. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80277-x
[45] Do patients with minimally displaced distal radial fractures need a plaster cast?. The Bone & Joint Journal. 2025. DOI: 10.1302/0301-620x.107b1.bjj-2024-0634.r1
[46] Surgical treatment and postoperative splinting of recessive dystrophic epidermolysis bullosa. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80210-3
[47] Short-term Outcomes of the Cross Brace Protocol for ACL Rupture Management: A Prospective Cohort Study. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967126s00013
[48] Static progressive wrist extension splint. Journal of Hand Therapy. 2002. DOI: 10.1016/s0894-1130(02)80009-6
[49] Functional bracing of fractures of the second through fifth metacarpals. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80179-x
[50] Effectiveness of Proximal Interphalangeal Joint Orthosis and Therapeutic Exercise in the Management of Trigger Finger: A Prospective Case Series. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101038
[51] Effect of an alternative flexion splinting protocol on mid-joint rom. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80022-6
[52] A new dynamic splint for postoperative treatment of flexor tendon injury. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80025-5
[53] A Supination Splint Worn Distal to the Elbow:. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00034-6
[54] The biomechanics of a thumb carpometacarpal immobilization splint: Design and fitting. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80006-x
[55] Splinting in the treatment of arthritis of the first carpometacarpal joint. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.jhsu24a0086
[56] A simple, comfortable, conforming, and adaptable splint. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80029-2
[57] A new method of extension-block splinting for the proximal interphalangeal joint—Preliminary report. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80118-3
[58] Effectiveness of Splinting for the Treatment of Trigger Finger. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2008.05.001
[59] Maintaining the Safe Position in a Palmar Splint. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(05)80214-1
[60] Results of acute zone III extensor tendon injuries treated with dynamic extension splinting. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80082-6
[61] The pipflex splint for treatment of mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90126-x
[62] Patient-adjusted static elbow splints for elbow contractures: A preliminary report. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80215-0
[63] Helicoidal splinting after wrist surgery: a laboratory study. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416686039
[64] An ulnar boost splint for midcarpal instability. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.013
[65] Splints, with or without wrist immobilization, following surgical repair of flexor tendon lesions of the hand: A systematic review. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.05.004