Clinicians › Shoulder
Distal Clavicle Osteolysis
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Distal clavicle osteolysis is a rare condition that may present atraumatically or following specific activities such as judo [6]. Clinical signs and symptoms are not distinguishable from other shoulder pathologies [1], requiring careful differentiation. Post-traumatic osteolysis should be considered when persistent pain follows a shoulder injury and bony lesions or instabilities have been excluded [3]. Etiologies include Propionibacterium acnes–mediated infection [2] and subacromial osteolysis following hook plate fixation for acromioclavicular dislocation [4]. Heterotopic bone formation is a more common cause of failure for acromioplasty or distal claviculectomy than acknowledged in the literature [14]. Pre-operative assessment must identify the acromioclavicular joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure [16].
Surgical management typically involves distal clavicle excision, which provides significant pain reduction and improved range of motion in patients with isolated acromioclavicular joint pathology [8, 15]. Arthroscopic and open approaches yield similar long-term outcomes regarding patient satisfaction and shoulder function, though arthroscopic techniques may offer faster return to activities and less residual pain [10, 12, 33]. A well-performed excision is superior to a poorly performed one regardless of approach [22]. For Propionibacterium acnes–mediated disease, the combination of distal clavicle resection and antibiotics halts osteolysis [2]. Routine distal clavicle resection is not indicated for rotator cuff repairs or isolated rotator cuff tears, as it does not improve outcomes or reduce reoperation risk [23, 26]. Furthermore, routine excision is not absolutely necessary even in symptomatic acromioclavicular joint osteoarthritis [30].
Technical considerations emphasize that portal placement is paramount for facilitating surgery and avoiding injury to adjacent structures [20]. Intraoperative ultrasound and cannulated dilators enhance efficiency and safety [27]. A 5 mm resection guarantees no bone-to-bone abutment in cadaver models, whereas 2.5 mm excision is successful in many specimens [17]. Complications include distal clavicle fracture and acromioclavicular dislocation [16, 20]. Specific technical options, such as the supraspinatus fossa portal technique, allow convenient removal of the posterior edge of the distal clavicle to prevent impingement [37].
Anatomy & Pathophysiology
Bony Anatomy
The clavicle is the only long bone to ossify by intramembranous ossification [39]. It serves as the primary stabilizer between the axial skeleton via the sternoclavicular joint and the appendicular skeleton via the acromioclavicular joint [39]. The primary blood supply to the clavicle is periosteal, with no nutrient blood supply [39]. In the transverse plane, the clavicle resembles an italic S, with the greater radius of curvature at its medial curve which is anteriorly convex [51]. The smaller lateral curve of the clavicle is posteriorly convex [51]. The bone is somewhat rounded in its midsection and medially and relatively flat laterally [51]. The distal clavicle is flat in the anteroposterior plane [39].
The lateral end of the clavicle features a conoid tubercle and a trapezoid line located in an anteroposterior direction just lateral to the conoid tubercle [51]. The distance from the lateral edge of the clavicle to the medial edge of the conoid tubercle is approximately 45 mm in male and female specimens [51]. The distance from the lateral edge of the clavicle to the center of the trapezoid tuberosity is approximately 25 mm in male and female specimens [51]. The cross-sectional A-frame morphology of the superior cortex of the distal clavicle is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle [38].
The clavicle begins ossification from two primary centers by 5 to 6 weeks of gestation and assumes its overall contour and S shape by 7 to 8 weeks [50]. The lateral epiphysis of the clavicle forms and fuses at around 18 to 19 years of age [50]. The medial epiphysis of the clavicle is the last in the body to ossify at 18 to 20 years and completes ossification at 23 to 25 years [50].
Ligaments and Soft Tissue
The coracoclavicular ligaments consist of the conoid (medial) and trapezoid (lateral) components [39]. These ligaments are the primary stabilizers to superior vertical translation of the distal clavicle [39]. The superior shoulder suspensory complex is a bone–soft tissue ring providing a stable connection of the glenoid and scapula to the clavicle [39]. It is composed of the distal clavicle, acromion, coracoid process, and glenoid neck, along with the supporting ligamentous complexes of the acromioclavicular joint and coracoclavicular ligaments [39].
Muscular attachments around the clavicle include the trapezius muscle, which inserts on the posterosuperior surface of the distal end of the clavicle [51]. The subclavius muscle has a fleshy insertion on the inferior surface of the middle third of the clavicle [51]. The deltoid originates on the anterior portion of the inner surface of the lateral curve of the clavicle [51]. The pectoralis major originates from the anterior portion of the medial two-thirds of the clavicle [51]. The sternocleidomastoid largely originates on the posterior portion of the middle third of the clavicle [51]. The sternohyoid originates on the clavicle just medial to the origin of the sternocleidomastoid [51].
Vascular and neural structures are closely related to the clavicle. The subclavian vein runs directly below the subclavius muscle and above the first rib [57]. The subclavian artery and brachial plexus lie more posteriorly, separated from the vein and clavicle by the scalenus anterior muscle medially [57]. The brachial plexus is closest to the clavicle in its midportion [57].
Pathophysiology
Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than generally recognized, with many cases overlooked or misinterpreted [18]. More than 100 cases of post-traumatic osteolysis have been reported since Werder first described it in 1950 [18]. This condition occurs from several weeks to several months after injury to the acromioclavicular joint [18]. Initial radiographs for post-traumatic osteolysis typically show no luxation or fracture [18]. Shoulder pain in post-traumatic osteolysis develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [18]. The process of osteolysis in post-traumatic cases occurs only in the distal clavicle, with no osteolytic lesion in the acromion [18]. The pathogenesis of post-traumatic osteolysis remains unclear, with hypotheses including osteoclastic resorption, nervous system dysfunction, avascular necrosis, microfracture, and synovial invasion [18]. Non-traumatic osteolysis of the acromial end of the clavicle should be considered in cases of shoulder pain in athletes [7].
Specific etiologies and surgical considerations influence the presentation and management of distal clavicle osteolysis. Propionibacterium acnes–mediated distal clavicular osteolysis can be halted by the combination of distal clavicle resection and antibiotics [2]. Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation is associated with the implant, with coracoclavicular ligament reconstruction suggested as an effective approach to decrease its incidence [4]. Removing the hook plate implant within 5.5 months minimizes osteolysis risk, and removal no more than 11.9 months prevents severe osteolysis [5]. Maintaining the acromion-hook angle at 10 degrees or less is recommended to prevent severe osteolysis following hook plate fixation [5].
Operative resection volumes significantly impact joint stability and complications. Distal clavicle resection of 2.5 mm or less is likely to result in abutment between the acromion and the clavicle, particularly inferiorly and posteriorly [52]. Joint stiffness diminishes with the amount of bone resected during distal clavicle excision [52]. Resection of more than 7.6 mm of the distal clavicle in men and 5.2 mm in women via an arthroscopic approach can violate the superior acromioclavicular ligament [52]. Resection of less than 11.0 mm should never violate any portion of the trapezoid ligament in 98% of men or women [52]. Resection of less than 24.0 mm should never violate any of the conoid ligament [52]. A 5-mm distal clavicle resection guarantees no abutment but decreases joint stiffness [35]. The anterior-posterior load to clinical failure of the acromioclavicular joint after 5 mm of resection from the distal clavicle and medial acromion is significantly greater than 1 cm of resected distal clavicle alone [75]. Intact acromioclavicular ligaments protect coracoclavicular reconstruction by decreasing the in situ graft force [73]. Patients with a distal clavicle resection of more than 1.0 cm have more pain than patients with less than 1 cm of resection [52]. Inaccurate resection from lack of depth perception and inadequate visualization has been reported as a cause of failure and revision surgery in distal clavicle excision [29].
Classification
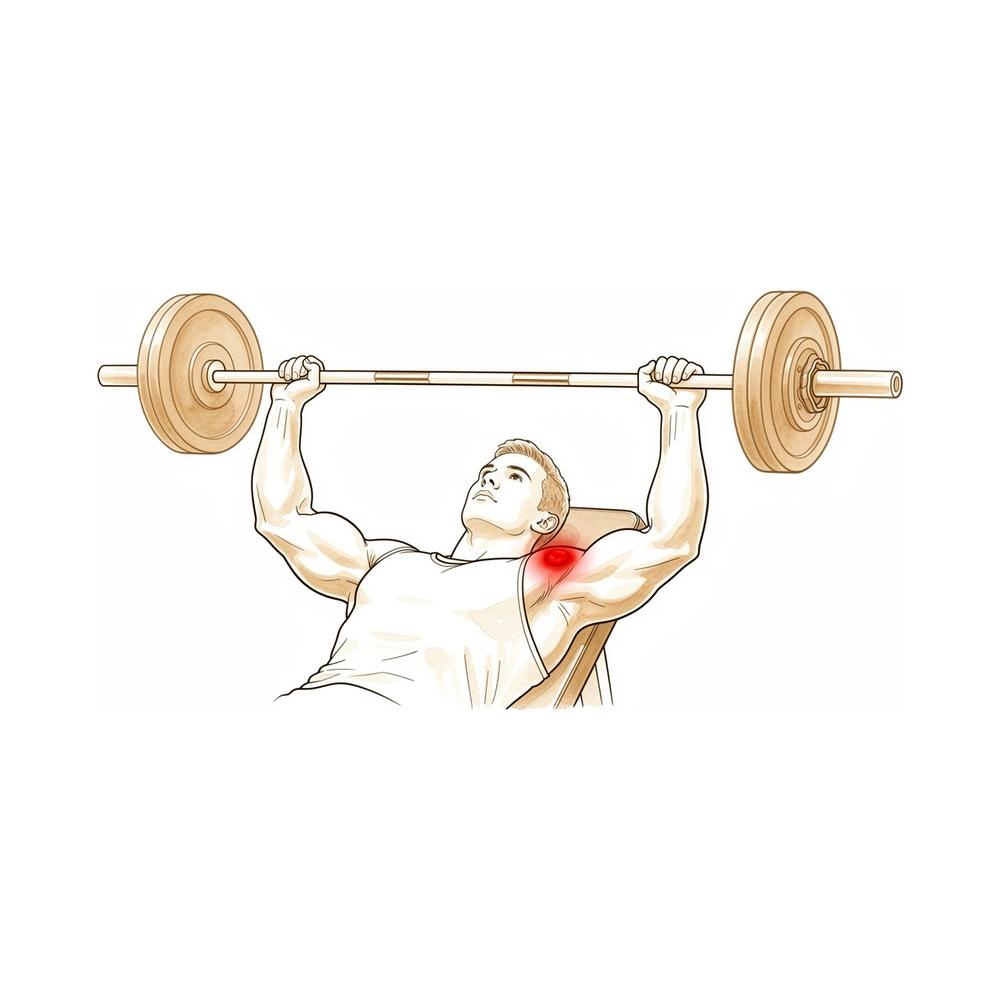
Distal clavicular osteolysis presents as isolated pain at the distal clavicle and acromioclavicular joint that tends to worsen with activity [28]. The condition is classified into two primary forms based on etiology: posttraumatic distal clavicular osteolysis, which results from direct traumatic injury, and atraumatic distal clavicular osteolysis, which is attributable to repetitive stress [28]. In the atraumatic form, weightlifting is the most common risk factor in adults [28].
Posttraumatic Distal Clavicular Osteolysis: In posttraumatic cases, initial radiographs ordinarily show no luxation or fracture [18]. The osteolytic process is confined to the distal clavicle, with no osteolytic lesion present in the acromion [18]. Hypothesized pathogenic mechanisms for this form include osteoclastic resorption, nervous system dysfunction, avascular necrosis, microfracture, and synovial invasion [18].
Other Considerations: Several distinct etiologies and iatrogenic factors are recognized in the classification of distal clavicular osteolysis. Propionibacterium acnes–mediated infection is a recognized etiology [2]. An aseptic foreign-body reaction to Gore-Tex graft can cause clavicle osteolysis [21]. Additionally, subacromial osteolysis following hook plate fixation is significantly increased by prolonged implant retention and higher-grade fracture types [76].
Clinical Presentation
Patients with distal clavicular osteolysis present with isolated pain at the distal clavicle and acromioclavicular joint that tends to worsen with activity [28, 64]. This condition can occur during judo [6].
Radiographic Findings: Imaging findings may range from mild osteopenia to overt osteolysis [28, 64]. The bilateral Zanca view is helpful for diagnosis as it profiles the acromioclavicular joint and allows comparison with the contralateral side [28, 64].
MRI Characteristics: Magnetic resonance imaging reveals distal clavicular bone marrow edema that is out of proportion to the edema at the acromion [28, 64]. Subchondral cystic change is also a characteristic finding [28, 64]. In advanced cases, periostitis may be observed at the distal clavicle on MRI [28, 64].
Investigations
Plain radiography: Initial radiographs for post-traumatic osteolysis demonstrate no luxation or fracture [18]. The osteolytic process is confined to the distal clavicle, with no corresponding osteolytic lesion in the acromion [18].
Other Considerations: A high index of suspicion is required to diagnose bone osteolysis following acromioclavicular joint reconstruction using synthetic ligament, specifically before irretrievable bone loss occurs [32]. Special care must be taken to rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure [16]. Intraoperatively, the cross-sectional A-frame morphology of the superior cortex of the distal clavicle provides a reproducible landmark that is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle, which can be used to determine when adequate resection has been completed [38]. A novel anterior portal technique for arthroscopic distal clavicle excision yields a safe corridor for instrument placement that does not disrupt important stabilizers of the glenohumeral or AC joints [36].
Treatment
Non-Operative
Activity modification, NSAIDs, and physical therapy constitute the first-line treatment for distal clavicular osteolysis [28]. Intra-articular injection of lidocaine and corticosteroids into the acromioclavicular joint serves as both a diagnostic and therapeutic intervention [28]. For in-season athletes, nonoperative management utilizing injections, medication, and physical therapy remains a viable option [28]. In cases of atraumatic distal clavicle osteolysis, return to sports activities depends on modifications to the patient's training regimen [9].
Operative
Indications: Distal clavicle resection is the definitive operative treatment for distal clavicular osteolysis that has failed nonoperative management [28].
Surgical Approach / Technique: Open and arthroscopic distal clavicle excision yield similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up, although the arthroscopic technique is associated with less residual pain [33]. Portal placement is paramount in facilitating surgery and avoiding injury to adjacent extra-articular structures, regardless of the specific technique chosen for resection [20]. Arthroscopic distal clavicle resection through the supraspinatus fossa portal offers a technical option for patients in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement [37]. Anterior acromioplasty is required in cases presenting with subacromial impingement during distal clavicle resection [19].
Resection Extent: In a cadaver model, a 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment [17]. A 5-mm distal clavicle resection also guaranteed no abutment while decreasing joint stiffness in a cadaveric model [35].
Other Considerations: The combination of distal clavicle resection and antibiotics halted osteolysis in a patient with Propionibacterium acnes–mediated distal clavicular osteolysis, with the patient remaining symptom-free at 10 months post-surgery [2]. In a patient with osteolysis progressing to osteoarthritic change in the acromioclavicular joint, resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon were performed [11]. SLAP lesion repair following initial distal clavicle resection successfully treated 15 patients, indicating that associated or underlying superior labral detachment may cause similar symptoms leading to misdiagnosis [25]. Coracoclavicular ligament reconstruction is an effective surgical approach for decreasing the incidence of subacromial osteolysis following hook plate fixation for acromioclavicular dislocation [4]. Removing the implant within 5.5 months minimizes osteolysis risk, and removal within no more than 11.9 months prevents severe osteolysis, while maintaining the acromion-hook angle at 10 degrees or less [5].
Complications
Diagnostic and Pre-operative Considerations
Post-traumatic osteolysis of the distal clavicle occurs more often than generally recognized, with many cases potentially overlooked or misinterpreted [18]. It should be considered if persistent pain remains after a shoulder injury and bony lesions or instabilities have been excluded [3]. A high index of suspicion is required to diagnose bone osteolysis following acromioclavicular joint reconstruction using synthetic ligament early, before irretrievable bone loss occurs [32]. Pre-existing distal clavicle stress fracture or osteolysis must be ruled out before performing the arthroscopic Mumford procedure to avoid iatrogenic fracture [16].
Iatrogenic and Surgical Complications
Heterotopic bone formation: This is a more common cause of failure of acromioplasty or distal claviculectomy than acknowledged in the literature [14]. It may also be a more common cause of failure of acromioclavicular joint surgery than acknowledged in the literature [31].
Osteolysis and foreign-body reaction: Aseptic foreign-body reaction and clavicle osteolysis can occur following acromioclavicular reconstruction using Gore-Tex graft [21]. Bone osteolysis can occur following acromioclavicular joint reconstruction using synthetic ligament (Surgilig™) [32].
Fracture: Distal clavicle fracture is a reported complication of arthroscopic distal clavicle resection [16].
Reoperation and failure mechanisms: The reported incidence of reoperation following distal clavicle excision ranges from 4% to 10% [47]. Mechanisms of failure following distal clavicle excision include inadequate resection, excessive bone removal resulting in instability, unrecognized concomitant pathology, and iatrogenic disruption of the coracoclavicular ligaments [47]. Misdiagnosis due to associated or underlying superior labral detachment (SLAP lesion) causing similar symptoms can lead to failure of distal clavicle resection [25]. A well-performed distal clavicle excision is likely to perform better than a poorly performed one, regardless of whether an open or arthroscopic approach is chosen [22].
Post-operative Outcomes and Recovery
Return to activity: Return to sports activities following treatment for atraumatic osteolysis of the distal clavicle was dependent on changes in the way of training [9]. Patients undergoing arthroscopic distal clavicle excision via the direct approach can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [12].
Functional outcomes: Limited distal clavicle excision for acromioclavicular joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [15]. The combination of distal clavicle resection and antibiotics halted osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis, with the patient remaining symptom-free at 10 months after surgery [2].
Recovery
Post-operative Activity and Return to Sport: Arthroscopic distal clavicle excision through the direct approach allows for a faster return to activities compared with the open procedure [12].
Surgical Outcomes and Pain Management: Open and arthroscopic distal clavicle excision provide similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up [33]. Less residual pain was found using the arthroscopic technique compared to the open technique for distal clavicle excision [33]. In carefully selected patients with isolated ACJ pathology, arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures [8]. Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [15].
Surgical Technique and Biomechanics: A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model, whereas a 2.5 mm resection was successful in many specimens [17].
Key Evidence
- [L4] Clinical signs and symptoms for atraumatic distal clavicular osteolysis (ADCO) were not distinguishable from other shoulder pathologies. [1] (10.1177/17585732261479715)
- [Case_report] The combination of distal clavicle resection and antibiotics halted the osteolysis, and the patient has remained symptom free at 10 months after surgery. [2] (10.1016/j.jse.2015.03.004)
- [L4] It is important to consider the possibility of post-traumatic osteolysis of the distal clavicle if there is persistent pain after a shoulder injury, and bony lesions or instabilities have been excluded. [3] (10.1007/bf00573456)
- [L1] The current analysis suggests coracoclavicular ligament reconstruction as an effective surgical approach for decreasing the incidence of subacromial osteolysis. [4] (10.1016/j.jse.2024.03.018)
- [L3] The authors recommend removing the implant within 5.5 months to minimize osteolysis risk and no more than 11.9 months to prevent severe osteolysis, while maintaining the acromion-hook angle at 10 degrees or less. [5] (10.1016/j.jse.2024.09.027)
- [L5] Osteolysis of the distal end of the clavicle is a rare condition and it can occur during judo. [6] (10.1016/s1058-2746(96)80543-x)
- [L4] Non-traumatic osteolysis of the acromial end of the clavicle should be borne in mind in cases of pain in the shoulder in athletes. [7] (10.1016/0020-1383(87)90010-6)
- [L4] In carefully selected patients with isolated ACJ pathology, arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures. [8] (10.1016/j.jseint.2023.07.014)
- [L4] For all patients, return to sports activities was dependent on changes in the way of training. [9] (10.1016/s1058-2746(96)80377-6)
- [L1] Arthroscopic and open distal clavicle excisions both provide significant pain reduction at 1 year with no significant difference in outcome measures between groups, except for VAS pain score improvement. [10] (10.1016/j.jse.2006.10.006)
- [L5] A 58-year-old male carpenter with osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint underwent surgery involving resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon. [11] (10.1016/s1058-2746(95)80313-0)
- [L3] Among patients undergoing distal clavicle excision for acromioclavicular joint pathology, those having an arthroscopic procedure, specifically through the direct approach, can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure. [12] (10.1016/j.arthro.2009.12.007)
- [L4] This retrospective series suggests that heterotopic bone formation is a more common cause of failure of acromioplasty or distal claviculectomy than is acknowledged by the literature. [14] (10.1016/s1058-2746(05)80050-3)
- [L4] Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up. [15] (10.1016/j.otsr.2016.01.008)
- [L4] Special care must be taken to properly identify the AC joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure. [16] (10.1016/j.arthro.2009.02.008)
- [Abstract] Although distal clavicle excision with 2.5 mm of bone was successful in many specimens, a 5 mm resection guaranteed no bone-to-bone abutment. [17] (10.1016/j.jse.2007.02.105)
- [L5] [18] (10.1067/mse.2002.122229)
- [L4] Additionally, the anterior acromioplasty is needed in the cases with subacromial impingement. [19] (10.1016/s1058-2746(96)80520-9)
- [Case_report] Regardless of the technique chosen for distal clavicle resection, portal placement remains paramount in both facilitating surgery and avoiding injury to adjacent extra-articular structures. [20] (10.1016/j.jse.2010.08.032)
- [L5] The case presented reports foreign-body reaction and osteolysis with the use of Gore-Tex graft to stabilize the clavicle to the coracoid. [21] (10.1016/j.jse.2004.01.027)
- [L5] A well-performed distal clavicle excision will likely perform better than a poorly performed one, regardless of whether an open or arthroscopic approach is chosen. [22] (10.1016/j.arthro.2018.03.004)
- [L2] Routine distal clavicle resection in the setting of rotator cuff repair does not result in improved outcomes for patients with no difference being observed at 24 months post surgery. [23] (10.1177/1758573217741124)
- [L2] Both the direct superior approach and the indirect subacromial approach to the arthroscopic distal clavicle resection result in successful clinical outcome with clinically insignificant difference at final follow-up. [24] (10.1177/0363546506294855)
- [L4] The successful treatment of 15 patients by SLAP lesion repair after initial distal clavicle resection indicates that there may be misdiagnosis due to associated or underlying superior labral detachment causing similar symptoms. [25] (10.1016/s1058-2746(96)80319-3)
- [L1] Distal clavicle resection in patients with rotator cuff tears did not result in better clinical outcome scores or shoulder ROM and was not associated with a lower risk of reoperation. [26] (10.1097/corr.0000000000000424)
- [L5] The technique will allow surgeons to perform distal clavicle excisions in a more efficient, reproducible and safer manner. [27] (10.1016/j.eats.2024.103331)
- [Paper] [29] (10.1016/j.eats.2020.10.010)
- [L2] Routine distal clavicle excision is not absolutely necessary, even in patients with symptomatic ACJ osteoarthritis. [30] (10.1007/s00167-020-06098-y)
- [L4] Heterotopic bone formation may be a more common cause of failure of acromioplasty or distal clavicectomy than acknowledged in the literature. [31] (10.1016/s1058-2746(96)80126-1)
- [L4] A high index of suspicion is needed to diagnose such complications early before irretrievable bone loss to osteolysis. [32] (10.1111/sae.12035)
- [L3] Open and arthroscopic distal clavicle excision are both effective surgeries to treat recalcitrant acromioclavicular joint pain, providing similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up, though less residual pain was found using the arthroscopic technique. [33] (10.1177/0363546511419633)
- [L5] A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness. [35] (10.1016/j.arthro.2007.07.004)
- [L4] The technique was validated using cadaveric dissection and yields a method of establishing the anterior portal for distal clavicle excision with a safe corridor for placement of instruments in a reliable manner that does not disrupt the important stabilizers of the glenohumeral or AC joints. [36] (10.1097/bte.0000000000000033)
- [Paper] The introduction of this technique provides a special technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement. [37] (10.1016/j.eats.2020.08.040)
- [L5] The cross-sectional A-frame morphology of the superior cortex of the distal clavicle provides a reproducible landmark that is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle, which can be used intraoperatively to determine when adequate resection has been completed. [38] (10.1016/j.jse.2021.10.013)
- [L4] [47] (10.1016/j.jse.2026.08.016)
- [L5] Intact acromioclavicular ligaments protect the coracoclavicular reconstruction by decreasing the in situ graft force. [73] (10.1177/0363546510374447)
- [L5] This cadaveric study demonstrates that the anterior-posterior load to clinical failure of the AC joint after 5 mm of resection from the distal clavicle and medial acromion is significantly greater than 1 cm of the resected distal clavicle alone. [75] (10.1177/0363546512469873)
- [L3] Prolonged implant retention and higher-grade fracture types significantly increase the risk of subacromial osteolysis (SAO). [76] (10.1186/s12891-026-09516-3)
See Also
- Rotator Cuff
- Clavicle Fracture
- AC Joint Osteoarthritis
References
[1] Risk factors and management of atraumatic distal clavicular osteolysis: A scoping review. Shoulder & Elbow. 2026. DOI: 10.1177/17585732261479715
[2] Propionibacterium acnes–mediated distal clavicular osteolysis: a case report. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.03.004
[3] Post-traumatic osteolysis of the distal clavicle. Archives of Orthopaedic and Trauma Surgery. 1996. DOI: 10.1007/bf00573456
[4] Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation: a systematic review and meta-analysis. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2024.03.018
[5] Predictive value of implant removal time and acromion-hook angle on subacromial osteolysis following hook plate fixation for acromioclavicular dislocation. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.09.027
[6] Post-traumatic osteolysis of the distal end of the clavicle in judo athlete: Case report. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80543-x
[7] Resection of the lateral end of the clavicle following osteolysis, with emphasis on non-traumatic osteolysis of the acromial end of the clavicle in athletes. Injury. 1987. DOI: 10.1016/0020-1383(87)90010-6
[8] Patient outcomes following arthroscopic distal clavicle excision: a prospective case series. JSES International. 2023. DOI: 10.1016/j.jseint.2023.07.014
[9] Atraumatic osteolysis of the distal clavicle. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80377-6
[10] Arthroscopic versus open distal clavicle excision: Comparative results at six months and one year from a randomized, prospective clinical trial. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2006.10.006
[11] Osteolysis of the distal end of the clavicle: A case report. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80313-0
[12] Open Versus Arthroscopic Distal Clavicle Resection. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.12.007
[14] Heterotopic ossification after acromioplasty and distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80050-3
[15] Limited distal clavicle excision of acromioclavicular joint osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2016.01.008
[16] Distal Clavicle Fracture as a Complication of Arthroscopic Distal Clavicle Resection. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.02.008
[17] Arthroscopic Distal Clavicle Resection: A Biomechanical Analysis In A Cadaver Model. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2007.02.105
[18] A case of post-traumatic osteolysis of the distal clavicle: Histologic lesion of the acromion. Journal of Shoulder and Elbow Surgery. 2002. DOI: 10.1067/mse.2002.122229
[19] The usefulness of distal clavicle resection for acromioclavicular joint disease. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80520-9
[20] Acromioclavicular dislocation after arthroscopic distal clavicle resection: a case report. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.08.032
[21] Failure of acromioclavicular reconstruction using Gore-Tex graft due to aseptic foreign-body reaction and clavicle osteolysis: A case report. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/j.jse.2004.01.027
[22] Editorial Commentary: The “Mumford” & Sons: For Distal Clavicle Excisions, What Are Our Young Surgeons Doing, and How Well Are They Doing It?. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.03.004
[23] Is routine distal clavicle resection necessary in rotator cuff repair surgery? A systematic review and meta-analysis. Shoulder & Elbow. 2017. DOI: 10.1177/1758573217741124
[24] Arthroscopic Distal Clavicle Resection in Athletes. The American Journal of Sports Medicine. 2007. DOI: 10.1177/0363546506294855
[25] The slap lesion as a cause of continued symptoms and failure of distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80319-3
[26] Does Distal Clavicle Resection Decrease Pain or Improve Shoulder Function in Patients With Acromioclavicular Joint Arthritis and Rotator Cuff Tears? A Meta-analysis. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000424
[27] Intraoperative Use of Ultrasound and Cannulated Dilators to Safely Identify and Access the Acromioclavicular Joint for Distal Clavicle Excision: A Technique Guide. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103331
[28] Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability. 2016.
[29] Distal Clavicle Excision for Acromioclavicular Joint Osteoarthritis Using a Fluoroscopic Kirschner Wire Guide. Arthroscopy Techniques. 2021. DOI: 10.1016/j.eats.2020.10.010
[30] Acromioclavicular joint arthritis is not an indication for routine distal clavicle excision in arthroscopic rotator cuff repair. Knee Surgery, Sports Traumatology, Arthroscopy. 2020. DOI: 10.1007/s00167-020-06098-y
[31] Heterotopic ossification after acromioplasty and distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80126-1
[32] Bone Osteolysis Following Acromioclavicular Joint Reconstruction Using Synthetic Ligament (Surgilig™). Shoulder & Elbow. 2014. DOI: 10.1111/sae.12035
[33] Arthroscopic Versus Open Distal Clavicle Excision. The American Journal of Sports Medicine. 2011. DOI: 10.1177/0363546511419633
[35] Arthroscopic Distal Clavicle Resection: A Biomechanical Analysis of Resection Length and Joint Compliance in a Cadaveric Model. Arthroscopy. 2007. DOI: 10.1016/j.arthro.2007.07.004
[36] A Novel and Reproducible Anterior Portal for Arthroscopic Distal Clavicle Excision. Techniques in Shoulder & Elbow Surgery. 2014. DOI: 10.1097/bte.0000000000000033
[37] Arthroscopic Distal Clavicle Resection Through the Supraspinatus Fossa Portal. Arthroscopy Techniques. 2020. DOI: 10.1016/j.eats.2020.08.040
[38] Distal clavicle “A-frame” morphology: a reliable intraoperative guide for arthroscopic distal clavicle excision. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.10.013
[39] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Clavicle, Scapula, and Glenoid > I. Clavicular Fractures.
[47] Clinical Outcomes and Predictors of Dissatisfaction Following Revision Surgery After Distal Clavicle Excision. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.08.016
[50] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > FRACTURES OF THE CLAVICLE.
[51] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Clavicle.
[52] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > Neurovascular Structures > EXCISION OF THE DISTAL CLAVICLE.
[57] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Neurovascular Anatomy of the Clavicle.
[64] Rockwood And Matsen S The Shoulder. Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability > Distal Clavicle Osteolysis > Indications.
[73] The Effect of Distal Clavicle Excision on in Situ Graft Forces in Coracoclavicular Ligament Reconstruction. The American Journal of Sports Medicine. 2010. DOI: 10.1177/0363546510374447
[75] The Biomechanical Stability of Distal Clavicle Excision Versus Symmetric Acromioclavicular Joint Resection. The American Journal of Sports Medicine. 2012. DOI: 10.1177/0363546512469873
[76] What is the optimal implant removal timing following hook plate fixation in distal clavicle fractures: a retrospective analysis from subacromial osteolysis cases. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09516-3