Patients › Wrist
ਪ੍ਰੌਕਸੀਮਲ ਰੋਅ ਕਾਰਪੈਕਟਮੀ (proximal row carpectomy)
A wrist salvage operation for an arthritic wrist (SLAC/SNAC) that keeps useful movement — how it works, recovery, and how it compares with fusion.
ਇਹ ਓਪਰੇਸ਼ਨ ਕਿਉਂ ਸੁਝਾਇਆ ਗਿਆ ਹੈ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਜੋ ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ ਹਨ, ਤੁਹਾਡੀ ਹਾਲਤ ਦੇ ਅਨੁਕੂਲ ਸਭ ਤੋਂ ਘੱਟ ਚੀਰ-ਫਾੜ ਵਾਲੇ ਇਲਾਜਾਂ ਨਾਲ ਸ਼ੁਰੂ ਕਰਦੇ ਹਨ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ 'ਤੇ ਉਨ੍ਹਾਂ ਦਾ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਡੇ ਕੋਲ ਆਉਣ ਦਾ ਸੁਝਾਅ ਦਿੱਤਾ ਹੈ, ਤਾਂ ਵੀ ਮੈਡੀਕੇਅਰ ਰਿਬੇਟ (Medicare rebate) ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ (ਭੇਜਣ ਦੀ ਚਿੱਠੀ) ਦੀ ਲੋੜ ਪਵੇਗੀ। ਤੁਹਾਡੀ ਮੁਲਾਕਾਤ ਵੇਲੇ ਅਸੀਂ ਤੁਹਾਡੀ ਬਿਮਾਰੀ ਦਾ ਪਿਛੋਕੜ ਪੁੱਛਦੇ ਹਾਂ, ਤੁਹਾਡੇ ਗੁੱਟ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਤੁਹਾਡੇ ਦਰਦ ਦਾ ਕਾਰਨ ਪਤਾ ਕਰਨ ਲਈ ਲੋੜ ਪੈਣ 'ਤੇ ਐਕਸ-ਰੇ ਜਾਂ ਸਕੈਨਾਂ ਦਾ ਪ੍ਰਬੰਧ ਕਰਦੇ ਹਾਂ। ਗੁੱਟ ਦੇ ਗਠੀਏ (ਆਰਥਰਾਈਟਿਸ) ਵਰਗੀ ਲੰਮੇ ਸਮੇਂ ਤੋਂ ਚੱਲ ਰਹੀ ਸਮੱਸਿਆ ਲਈ ਅਸੀਂ ਆਮ ਤੌਰ 'ਤੇ ਪਹਿਲਾਂ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਿਨਾਂ ਇਲਾਜ ਅਜ਼ਮਾਉਂਦੇ ਹਾਂ: ਤੁਹਾਡੇ ਹੱਥ ਵਰਤਣ ਦੇ ਢੰਗ ਵਿੱਚ ਤਬਦੀਲੀ, ਹੈਂਡ ਥੈਰੇਪੀ ਅਤੇ ਸਪਲਿੰਟ। ਜਦੋਂ ਇਸ ਨਾਲ ਤੁਹਾਨੂੰ ਕਾਫ਼ੀ ਸੁਧਾਰ ਨਹੀਂ ਮਿਲਦਾ, ਤਾਂ ਅਸੀਂ ਸਰਜਰੀ ਬਾਰੇ ਸੋਚਦੇ ਹਾਂ।
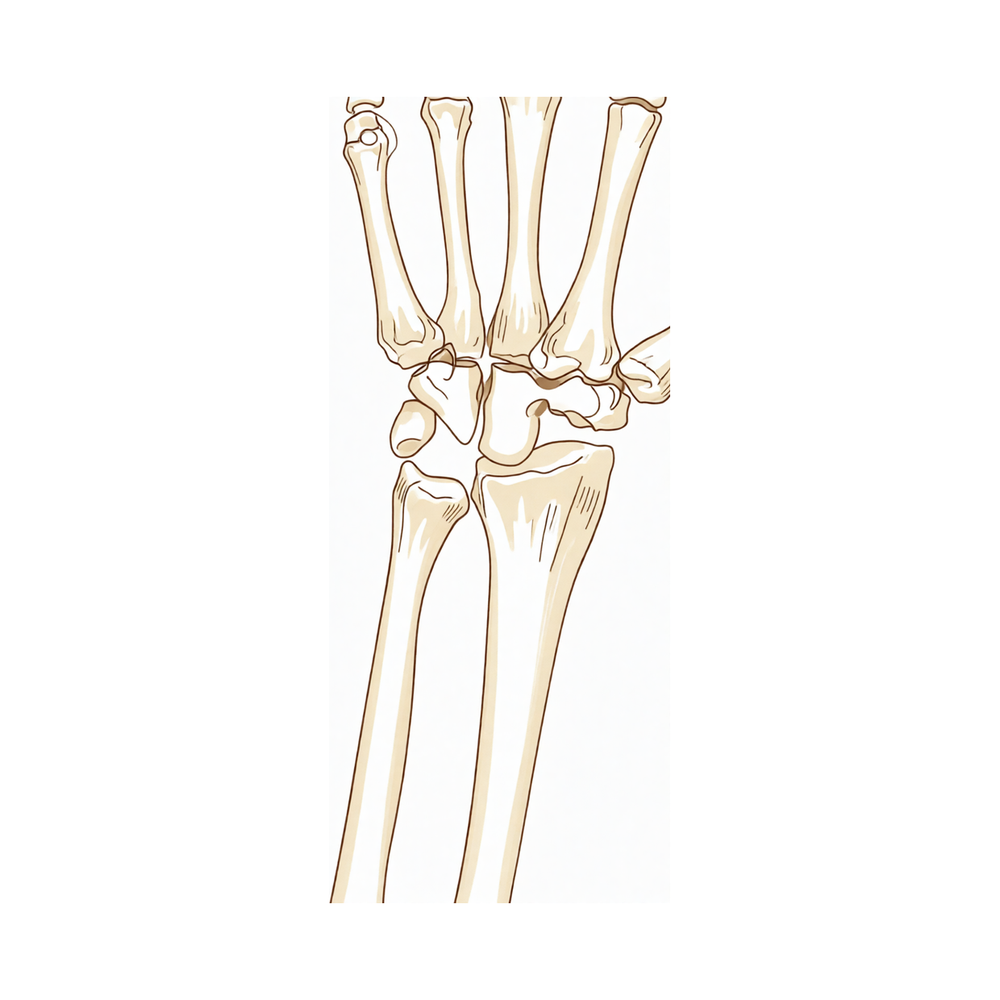
ਇਸ ਓਪਰੇਸ਼ਨ ਨੂੰ ਪ੍ਰੌਕਸੀਮਲ ਰੋਅ ਕਾਰਪੈਕਟਮੀ (proximal row carpectomy, ਗੁੱਟ ਦੀਆਂ ਹੱਡੀਆਂ ਦੀ ਪਹਿਲੀ ਕਤਾਰ ਕੱਢਣਾ) ਕਿਹਾ ਜਾਂਦਾ ਹੈ। ਇਸ ਦਾ ਮਤਲਬ ਹੈ ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਦੀਆਂ ਉਹ ਦੋ ਜਾਂ ਤਿੰਨ ਛੋਟੀਆਂ ਹੱਡੀਆਂ ਕੱਢਣਾ ਜੋ ਗਠੀਏ ਕਾਰਨ ਘਿਸ ਗਈਆਂ ਹਨ। ਇਹ ਆਮ ਤੌਰ 'ਤੇ ਗੁੱਟ ਦੇ ਘਿਸਾਈ ਵਾਲੇ ਗਠੀਏ ਲਈ ਸੁਝਾਇਆ ਜਾਂਦਾ ਹੈ, ਜਿਸ ਵਿੱਚ ਸਕੈਫ਼ੋਲਿਊਨੇਟ ਐਡਵਾਂਸਡ ਕੋਲੈਪਸ (scapholunate advanced collapse) ਨਾਮਕ ਇੱਕ ਕਿਸਮ ਵੀ ਸ਼ਾਮਲ ਹੈ, ਅਤੇ ਵਧੀ ਹੋਈ ਕੀਨਬੌਕ ਦੀ ਬਿਮਾਰੀ (Kienböck disease) ਲਈ ਵੀ, ਜਿਸ ਵਿੱਚ ਗੁੱਟ ਦੀ ਇੱਕ ਛੋਟੀ ਹੱਡੀ ਨੂੰ ਖ਼ੂਨ ਪਹੁੰਚਣਾ ਬੰਦ ਹੋ ਜਾਂਦਾ ਹੈ। ਅਸੀਂ ਇਸ ਦੀ ਸਿਫ਼ਾਰਸ਼ ਉਦੋਂ ਕਰਦੇ ਹਾਂ ਜਦੋਂ ਗੁੱਟ ਦੀਆਂ ਬਾਕੀ ਸਤਹਾਂ ਉੱਤੇ ਕਾਰਟੀਲੇਜ (cartilage, ਜੋੜ ਵਿੱਚ ਹੱਡੀਆਂ ਦੇ ਸਿਰਿਆਂ ਉੱਤੇ ਚਿਕਨੀ ਪਰਤ) ਅਜੇ ਵੀ ਤੰਦਰੁਸਤ ਹੋਵੇ, ਜਿਸ ਦੀ ਜਾਂਚ ਅਸੀਂ ਤੁਹਾਡੇ ਸਕੈਨਾਂ ਉੱਤੇ ਕਰਦੇ ਹਾਂ। ਇਸ ਦਾ ਮਕਸਦ ਤੁਹਾਡੇ ਗੁੱਟ ਨੂੰ ਹਿੱਲਦਾ ਰੱਖਦਿਆਂ ਤੁਹਾਡੇ ਦਰਦ ਤੋਂ ਰਾਹਤ ਦੇਣਾ ਹੈ। ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਦੇ ਗੁੱਟ ਵਿੱਚ ਕੰਮ ਦੇ ਲਾਇਕ ਹਿਲਜੁਲ ਅਤੇ ਪਕੜ ਦੀ ਤਾਕਤ ਬਣੀ ਰਹਿੰਦੀ ਹੈ, ਅਤੇ ਬਹੁਤ ਸਾਰੇ ਲੋਕ ਕੰਮ ਉੱਤੇ ਵਾਪਸ ਚਲੇ ਜਾਂਦੇ ਹਨ।
ਓਪਰੇਸ਼ਨ ਤੋਂ ਪਹਿਲਾਂ
ਓਪਰੇਸ਼ਨ ਤੋਂ ਪਹਿਲਾਂ, ਅਸੀਂ ਤੁਹਾਨੂੰ ਆਪਣੇ ਓਪਰੇਸ਼ਨ ਦੇ ਸਮੇਂ ਤੋਂ ਸੱਤ ਘੰਟੇ ਪਹਿਲਾਂ ਖਾਣਾ-ਪੀਣਾ ਬੰਦ ਕਰਨ ਲਈ ਕਹਿੰਦੇ ਹਾਂ। ਅਸੀਂ ਛੇ ਦੀ ਬਜਾਏ ਸੱਤ ਘੰਟੇ ਇਸ ਲਈ ਕਹਿੰਦੇ ਹਾਂ ਤਾਂ ਜੋ ਜੇ ਓਪਰੇਸ਼ਨ ਸੂਚੀ ਸਮੇਂ ਤੋਂ ਪਹਿਲਾਂ ਚੱਲ ਰਹੀ ਹੋਵੇ ਤਾਂ ਤੁਹਾਡੀ ਸਰਜਰੀ ਪਹਿਲਾਂ ਕੀਤੀ ਜਾ ਸਕੇ। ਤੁਹਾਡਾ ਸਰਜਨ ਤੁਹਾਨੂੰ ਦੱਸੇਗਾ ਕਿ ਤੁਹਾਡੀਆਂ ਆਮ ਦਵਾਈਆਂ ਵਿੱਚੋਂ ਕਿਹੜੀਆਂ ਅਤੇ ਕਦੋਂ ਬੰਦ ਕਰਨੀਆਂ ਹਨ, ਅਤੇ ਜੋ ਕੁਝ ਵੀ ਤੁਸੀਂ ਲੈਂਦੇ ਹੋ, ਉਸ ਦੀ ਲਿਖਤੀ ਸੂਚੀ ਨਾਲ ਲਿਆਉਣਾ ਮਦਦਗਾਰ ਹੁੰਦਾ ਹੈ। ਬਾਅਦ ਵਿੱਚ ਤੁਹਾਨੂੰ ਗੱਡੀ ਵਿੱਚ ਘਰ ਲਿਜਾਣ ਲਈ ਕਿਸੇ ਦਾ ਪ੍ਰਬੰਧ ਕਰੋ, ਅਤੇ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਦਿਨ ਢਿੱਲੇ, ਆਰਾਮਦਾਇਕ ਕੱਪੜੇ ਪਾਓ। ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਨੂੰ ਹੋਰ ਕਿਸੇ ਤਿਆਰੀ ਦੀ ਲੋੜ ਨਹੀਂ ਹੁੰਦੀ। ਜੇ ਤੁਹਾਨੂੰ ਹੋਰ ਡਾਕਟਰੀ ਸਮੱਸਿਆਵਾਂ ਹਨ, ਤਾਂ ਤੁਹਾਨੂੰ ਖ਼ੂਨ ਦੇ ਟੈਸਟਾਂ ਜਾਂ ਅਨੱਸਥੀਟਿਸਟ (ਬੇਹੋਸ਼ੀ ਵਾਲਾ ਡਾਕਟਰ) ਨਾਲ ਮੁਲਾਕਾਤ ਦੀ ਲੋੜ ਪੈ ਸਕਦੀ ਹੈ। ਓਪਰੇਸ਼ਨ ਦੀ ਯੋਜਨਾ ਬਣਾਉਣ ਲਈ, ਅਤੇ ਉਸ ਕਾਰਟੀਲੇਜ ਦੀ ਸਿਹਤ ਜਾਂਚਣ ਲਈ ਜਿਸ ਉੱਤੇ ਇਹ ਓਪਰੇਸ਼ਨ ਨਿਰਭਰ ਕਰਦਾ ਹੈ, ਅਸੀਂ ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਐਕਸ-ਰੇ ਅਤੇ MRI ਸਕੈਨ ਵਰਤਦੇ ਹਾਂ।
ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਦਿਨ
ਤੁਸੀਂ ਹਸਪਤਾਲ ਦੇ ਸਰਜੀਕਲ ਦਾਖ਼ਲਾ ਵਿਭਾਗ ਵਿੱਚ ਪਹੁੰਚੋਗੇ, ਜਿੱਥੇ ਤੁਹਾਡਾ ਦਾਖ਼ਲਾ ਕੀਤਾ ਜਾਂਦਾ ਹੈ ਅਤੇ ਓਪਰੇਸ਼ਨ ਥੀਏਟਰ ਲਈ ਤਿਆਰ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਤੁਸੀਂ ਅਨੱਸਥੀਟਿਸਟ ਨੂੰ ਮਿਲੋਗੇ, ਜੋ ਤੁਹਾਡੇ ਅਨੱਸਥੀਸੀਆ ਅਤੇ ਦਰਦ ਤੋਂ ਰਾਹਤ ਦੀ ਦੇਖਭਾਲ ਕਰਦਾ ਹੈ। ਇਹ ਓਪਰੇਸ਼ਨ ਜਨਰਲ ਅਨੱਸਥੀਸੀਆ (ਬੇਹੋਸ਼ੀ ਵਾਲੀ ਦਵਾਈ) ਹੇਠ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਦਰਦ ਤੋਂ ਰਾਹਤ ਲਈ ਕਦੇ-ਕਦੇ ਰੀਜਨਲ ਨਰਵ ਬਲਾਕ (ਨਸ ਨੂੰ ਸੁੰਨ ਕਰਨ ਵਾਲਾ ਟੀਕਾ) ਵੀ ਦਿੱਤਾ ਜਾਂਦਾ ਹੈ; ਅਨੱਸਥੀਟਿਸਟ ਉਸੇ ਦਿਨ ਤੁਹਾਡੇ ਨਾਲ ਇਸ ਬਾਰੇ ਗੱਲ ਕਰੇਗਾ। ਫਿਰ ਤੁਹਾਨੂੰ ਓਪਰੇਸ਼ਨ ਥੀਏਟਰ ਵਿੱਚ ਲਿਜਾਇਆ ਜਾਂਦਾ ਹੈ, ਜਿੱਥੇ ਓਪਰੇਸ਼ਨ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਓਪਰੇਸ਼ਨ ਪੂਰਾ ਹੋਣ 'ਤੇ ਤੁਹਾਨੂੰ ਰਿਕਵਰੀ ਵਾਲੀ ਥਾਂ ਵਿੱਚ ਹੋਸ਼ ਆਉਂਦੀ ਹੈ, ਜਿੱਥੇ ਅਨੱਸਥੀਸੀਆ ਦਾ ਅਸਰ ਉਤਰਨ ਤੱਕ ਨਰਸਾਂ ਤੁਹਾਡੀ ਨਿਗਰਾਨੀ ਕਰਦੀਆਂ ਹਨ। ਜਦੋਂ ਤੁਹਾਡੀ ਹਾਲਤ ਸਥਿਰ ਹੋ ਜਾਂਦੀ ਹੈ, ਤਾਂ ਓਪਰੇਸ਼ਨ ਅਤੇ ਤੁਹਾਡੇ ਠੀਕ ਹੋਣ ਦੇ ਅਨੁਸਾਰ ਤੁਸੀਂ ਜਾਂ ਤਾਂ ਵਾਰਡ ਵਿੱਚ ਜਾਓਗੇ ਜਾਂ ਘਰ ਜਾਓਗੇ।
ਓਪਰੇਸ਼ਨ ਵਿੱਚ ਕੀ ਕੀਤਾ ਜਾਂਦਾ ਹੈ
ਤੁਹਾਡਾ ਸਰਜਨ ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਪਿਛਲੇ ਪਾਸੇ, ਤੁਹਾਡੀ ਬਾਂਹ ਦੀ ਸੇਧ ਵਿੱਚ, ਇੱਕੋ ਚੀਰਾ ਦਿੰਦਾ ਹੈ। ਇਸ ਚੀਰੇ ਰਾਹੀਂ ਤੁਹਾਡਾ ਸਰਜਨ ਗੁੱਟ ਦੇ ਜੋੜ ਤੱਕ ਪਹੁੰਚਦਾ ਹੈ ਅਤੇ ਉਹ ਦੋ ਜਾਂ ਤਿੰਨ ਛੋਟੀਆਂ ਹੱਡੀਆਂ ਕੱਢਦਾ ਹੈ ਜੋ ਗਠੀਏ ਕਾਰਨ ਘਿਸ ਗਈਆਂ ਹਨ। ਇਸ ਨਾਲ ਤੁਹਾਡੇ ਗੁੱਟ ਅਤੇ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ (forearm) ਵਿਚਕਾਰ ਇੱਕ ਨਵਾਂ, ਸਰਲ ਜੋੜ ਬਣ ਜਾਂਦਾ ਹੈ, ਜਿੱਥੇ ਬਾਕੀ ਸਤਹਾਂ ਉੱਤੇ ਤੰਦਰੁਸਤ ਕਾਰਟੀਲੇਜ ਕੱਢੀਆਂ ਗਈਆਂ ਹੱਡੀਆਂ ਦਾ ਕੰਮ ਸੰਭਾਲ ਲੈਂਦੀ ਹੈ।
ਓਪਰੇਸ਼ਨ ਦਾ ਇੱਕ ਮਹੱਤਵਪੂਰਨ ਹਿੱਸਾ ਟਿਸ਼ੂ ਦੇ ਉਸ ਪਟੇ ਨੂੰ ਬਚਾ ਕੇ ਰੱਖਣਾ ਹੈ ਜੋ ਗੁੱਟ ਦੇ ਆਰ-ਪਾਰ ਜਾਂਦਾ ਹੈ ਅਤੇ ਇਸ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਵਿੱਚ ਮਦਦ ਕਰਦਾ ਹੈ। ਤੁਹਾਡਾ ਸਰਜਨ ਇਸ ਪਟੇ ਨੂੰ ਸਹੀ-ਸਲਾਮਤ ਰੱਖਦਾ ਹੈ, ਕਿਉਂਕਿ ਜਦੋਂ ਗੁੱਟ ਠੀਕ ਹੁੰਦਾ ਹੈ ਅਤੇ ਹਿੱਲਦਾ ਹੈ, ਤਾਂ ਇਹ ਉਸ ਨੂੰ ਸਹਾਰਾ ਦਿੰਦਾ ਹੈ।
ਫਿਰ ਚੀਰੇ ਨੂੰ ਟਾਂਕਿਆਂ ਨਾਲ ਬੰਦ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਉੱਤੇ ਪੱਟੀ ਕੀਤੀ ਜਾਂਦੀ ਹੈ, ਅਤੇ ਇਹ ਲਗਭਗ 10 ਦਿਨ ਲੱਗੀ ਰਹਿੰਦੀ ਹੈ।
ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ
ਤੁਹਾਨੂੰ ਰਿਕਵਰੀ ਵਾਲੀ ਥਾਂ ਵਿੱਚ ਹੋਸ਼ ਆਵੇਗੀ, ਫਿਰ ਤੁਹਾਨੂੰ ਵਾਰਡ ਵਿੱਚ ਲਿਜਾਇਆ ਜਾਵੇਗਾ। ਇਸ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਜ਼ਿਆਦਾਤਰ ਮਰੀਜ਼ ਇੱਕ ਰਾਤ ਹਸਪਤਾਲ ਵਿੱਚ ਰਹਿੰਦੇ ਹਨ, ਹਾਲਾਂਕਿ ਕੁਝ ਉਸੇ ਦਿਨ ਘਰ ਜਾ ਸਕਦੇ ਹਨ। ਨਰਸਾਂ ਦਰਦ ਦੀ ਦਵਾਈ ਨਾਲ ਤੁਹਾਨੂੰ ਆਰਾਮ ਵਿੱਚ ਰੱਖਣਗੀਆਂ, ਅਤੇ ਜੇ ਤੁਹਾਡਾ ਦਰਦ ਕਾਬੂ ਵਿੱਚ ਨਹੀਂ ਹੈ ਤਾਂ ਤੁਸੀਂ ਕਿਸੇ ਵੀ ਵੇਲੇ ਉਹਨਾਂ ਨੂੰ ਦੱਸ ਸਕਦੇ ਹੋ। ਤੁਹਾਡਾ ਗੁੱਟ ਨਰਮ ਪੱਟੀ ਵਿੱਚ ਹੋਵੇਗਾ। ਤੁਹਾਨੂੰ ਸਲਿੰਗ (ਬਾਂਹ ਨੂੰ ਸਹਾਰਾ ਦੇਣ ਵਾਲੀ ਪੱਟੀ), ਜਾਂ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦੇ ਅਗਲੇ ਪਾਸੇ ਅੱਧਾ ਪਲੱਸਤਰ (cast) ਵੀ ਲੱਗਾ ਹੋ ਸਕਦਾ ਹੈ; ਕੁਝ ਲੋਕਾਂ ਨੂੰ ਇਹਨਾਂ ਵਿੱਚੋਂ ਇੱਕ ਜਾਂ ਦੋਵੇਂ ਲੱਗਦੇ ਹਨ, ਅਤੇ ਕੁਝ ਨੂੰ ਕੋਈ ਵੀ ਨਹੀਂ। ਅਸੀਂ ਪੱਟੀ ਲਗਭਗ 10 ਦਿਨ ਲੱਗੀ ਰਹਿਣ ਦਿੰਦੇ ਹਾਂ; ਕਿਰਪਾ ਕਰਕੇ ਉਸ ਤੋਂ ਪਹਿਲਾਂ ਇਸ ਨੂੰ ਨਾ ਉਤਾਰੋ, ਜਦੋਂ ਤੱਕ ਅਸੀਂ ਤੁਹਾਨੂੰ ਅਜਿਹਾ ਕਰਨ ਲਈ ਨਾ ਕਹੀਏ। ਜਦੋਂ ਅਸੀਂ ਤੁਹਾਨੂੰ ਮਿਲਦੇ ਹਾਂ ਤਾਂ ਅਸੀਂ ਇਸ ਨੂੰ ਬਦਲਦੇ ਜਾਂ ਉਤਾਰਦੇ ਹਾਂ। ਜਿਵੇਂ ਹੀ ਤੁਸੀਂ ਆਪਣੇ ਪੈਰਾਂ ਉੱਤੇ ਸਥਿਰ ਮਹਿਸੂਸ ਕਰੋ, ਤੁਸੀਂ ਉੱਠ ਕੇ ਤੁਰ-ਫਿਰ ਸਕਦੇ ਹੋ। ਕਿਰਪਾ ਕਰਕੇ ਪਹਿਲੇ 24 ਘੰਟਿਆਂ ਲਈ ਕਿਸੇ ਨੂੰ ਆਪਣੇ ਨਾਲ ਰਹਿਣ ਦਾ ਪ੍ਰਬੰਧ ਕਰੋ।
ਸਿਹਤਯਾਬੀ
ਪਹਿਲੇ ਕੁਝ ਦਿਨ ਤੁਹਾਡਾ ਗੁੱਟ ਦੁਖੇਗਾ ਅਤੇ ਸੁੱਜਿਆ ਰਹੇਗਾ, ਅਤੇ ਤੁਹਾਡੇ ਹੱਥ ਦਾ ਪੁੱਠਾ ਪਾਸਾ ਨੀਲ ਪਏ ਵਰਗਾ ਅਤੇ ਖਿੱਚਿਆ ਹੋਇਆ ਮਹਿਸੂਸ ਹੋ ਸਕਦਾ ਹੈ। ਆਰਾਮ ਕਰਨਾ, ਆਪਣੇ ਹੱਥ ਨੂੰ ਸਿਰਹਾਣਿਆਂ ਉੱਤੇ ਉੱਚਾ ਰੱਖਣਾ, ਅਤੇ ਤੁਹਾਨੂੰ ਦਿੱਤੀ ਗਈ ਦਰਦ ਦੀ ਦਵਾਈ, ਇਹ ਸਭ ਮਦਦ ਕਰਦੇ ਹਨ। ਸੋਜ ਆਮ ਤੌਰ 'ਤੇ ਅਗਲੇ ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਹੌਲੀ-ਹੌਲੀ ਘਟ ਜਾਂਦੀ ਹੈ।
ਤੁਸੀਂ ਸਲਿੰਗ ਨਾਲ, ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦੇ ਅਗਲੇ ਪਾਸੇ ਅੱਧੇ ਪਲੱਸਤਰ ਨਾਲ, ਦੋਵਾਂ ਨਾਲ, ਜਾਂ ਕਿਸੇ ਦੇ ਵੀ ਬਿਨਾਂ ਘਰ ਜਾ ਸਕਦੇ ਹੋ। ਤੁਹਾਡੇ ਕੋਲ ਜੋ ਵੀ ਹੋਵੇ, ਜਿਵੇਂ ਹੀ ਤੁਸੀਂ ਸਥਿਰ ਮਹਿਸੂਸ ਕਰੋ, ਤੁਸੀਂ ਉੱਠ ਕੇ ਤੁਰ-ਫਿਰ ਸਕਦੇ ਹੋ। ਨਹਾਉਣ-ਧੋਣ, ਕੱਪੜੇ ਪਾਉਣ ਅਤੇ ਖਾਣਾ ਖਾਣ ਲਈ ਤੁਸੀਂ ਉਹ ਹੱਥ ਵਰਤੋਗੇ ਜਿਸ ਦਾ ਓਪਰੇਸ਼ਨ ਨਹੀਂ ਹੋਇਆ, ਅਤੇ ਸ਼ੁਰੂ ਵਿੱਚ ਘਰ ਦੇ ਭਾਰੀ ਕੰਮਾਂ ਲਈ ਤੁਹਾਨੂੰ ਮਦਦ ਦੀ ਲੋੜ ਪਵੇਗੀ। ਜਦੋਂ ਤੱਕ ਅਸੀਂ ਪੱਟੀ ਦੀ ਜਾਂਚ ਨਹੀਂ ਕਰਦੇ, ਇਸ ਨੂੰ ਸੁੱਕਾ ਅਤੇ ਸਹੀ-ਸਲਾਮਤ ਰੱਖੋ।
ਸਰਜਰੀ ਤੋਂ ਛੇਤੀ ਬਾਅਦ ਐਕਸਟੈਂਡ ਰੀਹੈਬਿਲੀਟੇਸ਼ਨ (Extend Rehabilitation) ਵਿੱਚ ਰੂਬੀ ਡੂਲਨ ਨਾਲ ਹੈਂਡ ਥੈਰੇਪੀ ਸ਼ੁਰੂ ਹੁੰਦੀ ਹੈ। ਰੂਬੀ ਇੱਕ ਹੈਂਡ ਥੈਰੇਪਿਸਟ ਹੈ: ਉਹ ਤੁਹਾਡੀਆਂ ਕਸਰਤਾਂ ਵਿੱਚ ਤੁਹਾਡੀ ਅਗਵਾਈ ਕਰਦੀ ਹੈ ਅਤੇ ਤੁਹਾਨੂੰ ਲੋੜੀਂਦਾ ਕੋਈ ਵੀ ਸਪਲਿੰਟ ਬਣਾਉਂਦੀ ਹੈ। ਸ਼ੁਰੂ ਵਿੱਚ ਧਿਆਨ ਹੌਲੀ ਹਿਲਜੁਲ ਅਤੇ ਸੋਜ ਘਟਾਉਣ ਉੱਤੇ ਹੁੰਦਾ ਹੈ। ਜਿਵੇਂ-ਜਿਵੇਂ ਦਰਦ ਘਟਦਾ ਹੈ, ਤੁਹਾਡੀਆਂ ਕਸਰਤਾਂ ਹੌਲੀ-ਹੌਲੀ ਚੀਜ਼ਾਂ ਫੜਨ, ਚੁੱਕਣ ਅਤੇ ਰੋਜ਼ਾਨਾ ਦੇ ਕੰਮਾਂ ਲਈ ਹੱਥ ਵਰਤਣ ਵੱਲ ਵਧਦੀਆਂ ਹਨ। ਬਹੁਤ ਸਾਰੇ ਲੋਕ ਦੇਖਦੇ ਹਨ ਕਿ ਜਿਵੇਂ-ਜਿਵੇਂ ਹਫ਼ਤੇ ਲੰਘਦੇ ਹਨ, ਗੁੱਟ ਵਧੇਰੇ ਖੁੱਲ੍ਹ ਕੇ ਹਿੱਲਦਾ ਹੈ ਅਤੇ ਰੋਜ਼ਾਨਾ ਦੇ ਕੰਮ ਸੌਖੇ ਲੱਗਦੇ ਹਨ।
ਜਦੋਂ ਤੁਸੀਂ ਬਿਨਾਂ ਦਰਦ ਦੇ ਚੀਜ਼ਾਂ ਫੜ ਸਕੋ ਅਤੇ ਆਪਣਾ ਹੱਥ ਵਰਤ ਸਕੋ, ਤਾਂ ਤੁਸੀਂ ਹੋਰ ਕੰਮ ਕਰ ਸਕਦੇ ਹੋ: ਪਹਿਲਾਂ ਡੈਸਕ ਦਾ ਕੰਮ ਅਤੇ ਹਲਕੇ ਕੰਮ, ਫਿਰ ਸਿਹਤਯਾਬੀ ਦੇ ਬਾਅਦ ਵਾਲੇ ਸਮੇਂ ਵਿੱਚ ਭਾਰੀ ਕੰਮ, ਖੇਡ ਅਤੇ ਜਿੰਮ। ਜੇ ਤੁਸੀਂ ਗੱਡੀ ਚਲਾਉਣਾ ਚਾਹੁੰਦੇ ਹੋ, ਤਾਂ ਉਦੋਂ ਤੱਕ ਉਡੀਕ ਕਰੋ ਜਦੋਂ ਤੱਕ ਤੁਹਾਡੀ ਸਲਿੰਗ ਜਾਂ ਪਲੱਸਤਰ ਉਤਰ ਨਾ ਜਾਵੇ, ਤੁਸੀਂ ਦੋਵਾਂ ਹੱਥਾਂ ਨਾਲ ਸਟੀਅਰਿੰਗ ਫੜ ਕੇ ਐਮਰਜੈਂਸੀ ਵਿੱਚ ਗੱਡੀ ਇੱਕਦਮ ਰੋਕ ਨਾ ਸਕੋ, ਅਤੇ ਤੁਸੀਂ ਤਾਕਤਵਰ ਦਰਦ ਨਿਵਾਰਕ ਦਵਾਈਆਂ ਲੈਣੀਆਂ ਬੰਦ ਨਾ ਕਰ ਦਿਓ। ਸਾਡਾ ਸਫ਼ਾ ਉੱਪਰਲੇ ਅੰਗ ਦੀ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਗੱਡੀ ਚਲਾਉਣਾ ਦੇਖੋ।
ਠੀਕ ਹੋਣਾ ਹਰ ਵਿਅਕਤੀ ਵਿੱਚ ਵੱਖਰਾ ਹੁੰਦਾ ਹੈ। ਤੁਹਾਡੀ ਸਮਾਂ-ਸੀਮਾ ਵੱਖਰੀ ਹੋ ਸਕਦੀ ਹੈ, ਅਤੇ ਅਸੀਂ ਹਰ ਕਦਮ 'ਤੇ ਤੁਹਾਡੀ ਅਗਵਾਈ ਕਰਾਂਗੇ।
ਕੀ ਗ਼ਲਤ ਹੋ ਸਕਦਾ ਹੈ
ਜ਼ਿਆਦਾਤਰ ਮਰੀਜ਼ ਠੀਕ ਰਹਿੰਦੇ ਹਨ, ਪਰ ਕਦੇ-ਕਦਾਈਂ ਸਮੱਸਿਆਵਾਂ ਹੋ ਸਕਦੀਆਂ ਹਨ। ਤੁਹਾਡਾ ਸਰਜਨ ਅਤੇ ਟੀਮ ਕਿਸੇ ਵੀ ਸਮੱਸਿਆ ਨੂੰ ਛੇਤੀ ਫੜਨ ਲਈ ਤੁਹਾਡੀ ਧਿਆਨ ਨਾਲ ਨਿਗਰਾਨੀ ਕਰਦੇ ਹਨ।
ਇਹ ਓਪਰੇਸ਼ਨ ਕੁਝ ਅਜਿਹੀਆਂ ਸਮੱਸਿਆਵਾਂ ਤੋਂ ਬਚਾਉਂਦਾ ਹੈ ਜੋ ਗੁੱਟ ਦੇ ਹੋਰ ਓਪਰੇਸ਼ਨਾਂ ਵਿੱਚ ਹੋ ਸਕਦੀਆਂ ਹਨ। ਕਿਉਂਕਿ ਕੋਈ ਵੀ ਹੱਡੀਆਂ ਆਪਸ ਵਿੱਚ ਜੋੜੀਆਂ ਨਹੀਂ ਜਾਂਦੀਆਂ, ਇਸ ਲਈ ਹੱਡੀਆਂ ਦੇ ਨਾ ਜੁੜਨ ਦਾ ਖ਼ਤਰਾ ਨਹੀਂ ਹੁੰਦਾ। ਤੁਹਾਨੂੰ ਧਾਤ ਕੱਢਣ ਲਈ ਕਿਸੇ ਹੋਰ ਓਪਰੇਸ਼ਨ ਦੀ ਲੋੜ ਵੀ ਨਹੀਂ ਪਵੇਗੀ, ਕਿਉਂਕਿ ਕੋਈ ਧਾਤ ਪਾਈ ਹੀ ਨਹੀਂ ਜਾਂਦੀ। ਕੁੱਲ ਮਿਲਾ ਕੇ, ਮੁੱਖ ਬਦਲਵੇਂ ਓਪਰੇਸ਼ਨ, ਯਾਨੀ ਪਾਰਸ਼ਲ ਰਿਸਟ ਫਿਊਜ਼ਨ (partial wrist fusion, ਗੁੱਟ ਦੀਆਂ ਕੁਝ ਹੱਡੀਆਂ ਨੂੰ ਪੱਕੇ ਤੌਰ 'ਤੇ ਆਪਸ ਵਿੱਚ ਜੋੜਨਾ) ਦੇ ਮੁਕਾਬਲੇ, ਇਸ ਓਪਰੇਸ਼ਨ ਵਿੱਚ ਸਰਜਰੀ ਨਾਲ ਜੁੜੀਆਂ ਸਮੱਸਿਆਵਾਂ ਘੱਟ ਹੁੰਦੀਆਂ ਹਨ।
ਸਾਲਾਂ ਦੌਰਾਨ ਧਿਆਨ ਰੱਖਣ ਵਾਲੀ ਮੁੱਖ ਗੱਲ ਗੁੱਟ ਦੇ ਬਾਕੀ ਬਚੇ ਹਿੱਸੇ ਵਿੱਚ ਘਿਸਾਈ ਵਾਲਾ ਗਠੀਆ ਹੈ। ਤੁਹਾਨੂੰ ਦੁਖਣ ਵਾਲਾ ਦਰਦ ਜਾਂ ਅਕੜਾਅ ਹੌਲੀ-ਹੌਲੀ ਮੁੜ ਵਧਦਾ ਮਹਿਸੂਸ ਹੋ ਸਕਦਾ ਹੈ, ਜਾਂ ਗੁੱਟ ਹਿਲਾਉਣ ਵੇਲੇ ਰਗੜ ਦਾ ਅਹਿਸਾਸ ਹੋ ਸਕਦਾ ਹੈ। ਜੇ ਅਜਿਹਾ ਹੋਵੇ, ਤਾਂ ਆਪਣੀ ਅਗਲੀ ਜਾਂਚ ਵੇਲੇ ਇਸ ਬਾਰੇ ਦੱਸੋ। ਜੇ ਉਸ ਜੋੜ ਵਿੱਚ ਗਠੀਆ ਕਾਫ਼ੀ ਜ਼ਿਆਦਾ ਦਰਦ ਦੇਣ ਲੱਗੇ, ਤਾਂ ਹੋਰ ਸਰਜਰੀ ਬਾਰੇ ਸੋਚਿਆ ਜਾ ਸਕਦਾ ਹੈ, ਜਿਸ ਵਿੱਚ ਪੂਰੇ ਗੁੱਟ ਨੂੰ ਪੱਕੇ ਤੌਰ 'ਤੇ ਆਕੜਾਉਣਾ ਵੀ ਸ਼ਾਮਲ ਹੈ।
ਇਸ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਪਕੜ ਦੀ ਤਾਕਤ ਆਮ ਤੌਰ 'ਤੇ ਇੱਕ ਆਮ ਗੁੱਟ ਦੀ ਤਾਕਤ ਦੇ 60 ਅਤੇ 80% ਦੇ ਵਿਚਕਾਰ ਕਿਤੇ ਹੁੰਦੀ ਹੈ। ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਨੂੰ ਇਹ ਰੋਜ਼ਾਨਾ ਦੇ ਕੰਮਾਂ ਲਈ ਕਾਫ਼ੀ ਲੱਗਦੀ ਹੈ, ਪਰ ਭਾਰੀ ਕੰਮ ਉੱਤੇ ਵਾਪਸ ਜਾਣ ਦੀ ਯੋਜਨਾ ਬਣਾਉਣ ਤੋਂ ਪਹਿਲਾਂ ਇਹ ਜਾਣ ਲੈਣਾ ਚੰਗਾ ਹੈ।
ਕੁਝ ਸਮੱਸਿਆਵਾਂ ਉੱਤੇ ਛੇਤੀ ਕਾਰਵਾਈ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ ਜਾਂ ਹੱਥ ਫਿੱਕੇ, ਠੰਢੇ, ਸਫ਼ੈਦ, ਨੀਲੇ ਜਾਂ ਗੂੜ੍ਹੇ ਰੰਗ ਦੇ ਪੈ ਜਾਣ, ਤਾਂ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ, ਕਿਉਂਕਿ ਇਹ ਖ਼ੂਨ ਦੇ ਵਹਾਅ ਵਿੱਚ ਸਮੱਸਿਆ ਦੀ ਨਿਸ਼ਾਨੀ ਹੋ ਸਕਦੀ ਹੈ। ਜੇ ਤੁਹਾਨੂੰ ਬੁਖ਼ਾਰ ਹੋਵੇ, ਜ਼ਖ਼ਮ ਤੋਂ ਲਾਲੀ ਬਾਹਰ ਵੱਲ ਫੈਲੇ, ਜਾਂ ਉਸ ਵਿੱਚੋਂ ਤਰਲ ਜਾਂ ਪਾਕ ਰਿਸੇ, ਤਾਂ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਦਰਦ ਦੀਆਂ ਦਵਾਈਆਂ ਦੇ ਬਾਵਜੂਦ ਤੁਹਾਡਾ ਦਰਦ ਵਧਦਾ ਹੀ ਜਾਵੇ, ਤਾਂ ਵੀ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਾ ਹੋ ਸਕੇ, ਜਿਵੇਂ ਕੰਮ ਦੇ ਸਮੇਂ ਤੋਂ ਬਾਅਦ ਜਾਂ ਹਫ਼ਤੇ ਦੇ ਅਖ਼ੀਰ 'ਤੇ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਨਰਵ ਬਲਾਕ ਤੋਂ ਬਾਅਦ ਪਹਿਲੇ 24 ਘੰਟਿਆਂ ਵਿੱਚ ਸੁੰਨਪਨ ਜਾਂ ਕਮਜ਼ੋਰੀ ਉਮੀਦ ਅਨੁਸਾਰ ਹੈ ਅਤੇ ਕੋਈ ਸਮੱਸਿਆ ਨਹੀਂ ਹੈ। ਬਲਾਕ ਦਾ ਅਸਰ ਉਤਰਨ ਤੋਂ ਬਾਅਦ, ਜੇ ਤੁਹਾਡਾ ਹੱਥ ਸੁੰਨ ਹੀ ਰਹੇ ਜਾਂ ਤੁਸੀਂ ਆਪਣੀਆਂ ਉਂਗਲਾਂ ਨਾ ਹਿਲਾ ਸਕੋ, ਤਾਂ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ।
ਜੇ ਤੁਸੀਂ ਵੇਰਵੇ ਚਾਹੁੰਦੇ ਹੋ ਤਾਂ ਇਸ ਪੰਨੇ ਉੱਤੇ ਪੇਚੀਦਗੀਆਂ ਵਾਲੀ ਸਾਰਣੀ ਵਿੱਚ ਆਮ ਦਰਾਂ ਦਿੱਤੀਆਂ ਗਈਆਂ ਹਨ।
ਸਾਨੂੰ ਕਦੋਂ ਫ਼ੋਨ ਕਰਨਾ ਹੈ
ਇਸ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਜ਼ਿਆਦਾਤਰ ਸਮੱਸਿਆਵਾਂ ਬਹੁਤ ਘੱਟ ਹੁੰਦੀਆਂ ਹਨ, ਪਰ ਕੁਝ ਨਿਸ਼ਾਨੀਆਂ ਉੱਤੇ ਛੇਤੀ ਕਾਰਵਾਈ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਜੇ ਤੁਹਾਡੀ ਪਿੰਨੀ (ਲੱਤ ਦੀ ਪਿੰਨੀ, calf) ਵਿੱਚ ਸੋਜ ਜਾਂ ਦਰਦ ਹੋਵੇ, ਜਾਂ ਸਾਹ ਚੜ੍ਹੇ ਜਾਂ ਛਾਤੀ ਵਿੱਚ ਦਰਦ ਹੋਵੇ, ਤਾਂ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ, ਕਿਉਂਕਿ ਇਹ ਖ਼ੂਨ ਦੇ ਗਤਲੇ ਦੀਆਂ ਨਿਸ਼ਾਨੀਆਂ ਹੋ ਸਕਦੀਆਂ ਹਨ। ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ ਜਾਂ ਹੱਥ ਫਿੱਕੇ, ਠੰਢੇ, ਸਫ਼ੈਦ, ਨੀਲੇ ਜਾਂ ਗੂੜ੍ਹੇ ਰੰਗ ਦੇ ਪੈ ਜਾਣ, ਤਾਂ ਵੀ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਜੇ ਤੁਹਾਨੂੰ ਬੁਖ਼ਾਰ ਹੋਵੇ, ਤੁਹਾਡੇ ਜ਼ਖ਼ਮ ਦੇ ਆਲੇ-ਦੁਆਲੇ ਲਾਲੀ ਫੈਲੇ, ਜਾਂ ਉਸ ਵਿੱਚੋਂ ਤਰਲ ਜਾਂ ਪਾਕ ਰਿਸੇ, ਤਾਂ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਦਰਦ ਦੀਆਂ ਦਵਾਈਆਂ ਦੇ ਬਾਵਜੂਦ ਤੁਹਾਡਾ ਦਰਦ ਵਧਦਾ ਹੀ ਜਾਵੇ, ਤਾਂ ਵੀ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਤੁਹਾਡੇ ਨਰਵ ਬਲਾਕ ਦਾ ਅਸਰ ਉਤਰਨ ਤੋਂ ਬਾਅਦ, ਜੋ ਆਮ ਤੌਰ 'ਤੇ ਲਗਭਗ 24 ਘੰਟਿਆਂ ਦੇ ਅੰਦਰ ਹੁੰਦਾ ਹੈ, ਜੇ ਤੁਹਾਡਾ ਹੱਥ ਸੁੰਨ ਹੀ ਰਹੇ ਜਾਂ ਤੁਸੀਂ ਆਪਣੀਆਂ ਉਂਗਲਾਂ ਨਾ ਹਿਲਾ ਸਕੋ, ਤਾਂ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਾ ਹੋ ਸਕੇ, ਜਿਵੇਂ ਕੰਮ ਦੇ ਸਮੇਂ ਤੋਂ ਬਾਅਦ ਜਾਂ ਹਫ਼ਤੇ ਦੇ ਅਖ਼ੀਰ 'ਤੇ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਇਸ ਸਥਿਤੀ ਬਾਰੇ ਹੋਰ ਕਿੱਥੇ ਪੜ੍ਹੀਏ
ਇਹ ਪੰਨਾ ਆਪਣੇ ਆਪ ਓਪਰੇਸ਼ਨ ਬਾਰੇ ਹੈ। ਜਿਸ ਹਾਲਤ ਦਾ ਇਹ ਇਲਾਜ ਕਰਦਾ ਹੈ, ਅਤੇ ਇਹ ਵੀ ਕਿ ਸਬੂਤ ਕੀ ਦੱਸਦੇ ਹਨ ਕਿ ਸਰਜਰੀ ਕਦੋਂ ਮਦਦ ਕਰਦੀ ਹੈ ਅਤੇ ਕਦੋਂ ਨਹੀਂ, ਇਸ ਬਾਰੇ SLAC ਅਤੇ SNAC ਗੁੱਟ ਵਾਲੇ ਪੰਨੇ ਉੱਤੇ ਹੋਰ ਵਿਸਥਾਰ ਨਾਲ ਦੱਸਿਆ ਗਿਆ ਹੈ।
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- The arthroscopic classification of Kienbock's disease allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion [1].
- The proximal carpal row should be studied as one system [2].
- X-ray findings of degenerative changes at the lunocapitate and radiolunate joint need not contraindicate a proximal row carpectomy [6].
- At long-term followup, all patients older than thirty-five years of age at the time of a proximal row carpectomy had maintained a satisfactory range of motion, grip strength, and pain relief and were satisfied with the result [7].
- Proximal row carpectomy is not an alternative after longstanding scapholunate dissociation (SLAC-Wrist) because of the high incidence of degenerative changes in the midcarpal joint [10].
- Proximal row carpectomy has a confirmed role and long-term efficacy in the treatment of wrist osteoarthritis and severe carpal trauma [11].
- Proximal row carpectomy in the acute setting of perilunate dislocation has medium-term results as good as ORIF with a shorter operating time [12].
- RCPI® is an interesting alternative and can be associated with proximal row carpectomy in advanced wrist osteoarthritis [13].
- Proximal row carpectomy with interposition arthroplasty is an effective motion-sparing procedure for patients with proximal capitate and/or lunate fossa arthritis, improving pain and function [14].
- Given the absence of high-quality comparative trials, procedure selection should be individualized, balancing disease severity, carpal stability requirements, and patient-specific functional demands [18].
- Current evidence shows no difference in postoperative total wrist arc range of motion, grip strength (as compared to contralateral), or Mayo Wrist Score with regard to surgical approach for acute perilunate injuries [32].
Anatomy & Pathophysiology
Bony Anatomy
- The wrist includes the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones and their proximal and distal articulations and attached ligaments [65].
- The proximal carpal row consists of the scaphoid, lunate, triquetrum, and pisiform [65].
- The distal carpal row consists of the trapezium, trapezoid, capitate, and hamate [65].
- The capitate is the largest carpal bone [65].
- The pisiform and trapezoid are the smallest carpal bones [65].
- The capitate articulates with seven other carpal bones [65].
- The pisiform articulates with one other carpal bone, the triquetrum [65].
- The radiocarpal joints are formed by the articulation of the distal radius with the scaphoid and lunate through their respective concave facets on the distal radius and the triquetrum on the triangular fibrocartilage [65].
- The distal concave articular surfaces of the proximal carpal row form the midcarpal articulations with the distal row [65].
- The distal radius articular surface has two concave facets, the scaphoid and lunate facets, separated by the scapholunate, or anterior-posterior, ridge [72].
- The sigmoid notch along the ulnar border of the distal radius is a shallow concavity for the articulating ulnar head at the distal radioulnar joint [72].
- The distal ulna is covered with hyaline cartilage on its dorsal, lateral, palmar, and distal surfaces [72].
- The ulnar styloid projects distally; at its base, the fovea is the insertion for the triangular fibrocartilaginous complex (TFCC) [72].
- The primary vascular supply to the scaphoid is a branch of the radial artery at the dorsal ridge [72].
- A group of smaller vessels enters the palmar tubercle of the scaphoid and supplies the distal 30% [72].
- The transverse carpal ligament attaches to the palmar tubercle of the scaphoid [72].
- A dorsal and a palmar vascular supply is found in 80% of wrists for the lunate; in 20% of wrists, only a palmar supply is found [72].
- The lunate is broader palmarly than dorsally [72].
- The triquetrum articulates with the hamate distally, the lunate radially, and the pisiform volarly [72].
- The triquetrum is stabilized to the fovea of the ulna through the ulnotriquetral ligament [72].
- The hamate consists of the body and the hook (hamulus) of the hamate [72].
- The hook of the hamate serves as an attachment for the transverse carpal ligament and for the origins of the flexor digiti minimi and opponens digiti minimi [72].
- The head of the capitate often relies on a retrograde vascular supply [72].
- Two ridges separate the distal articular surface of the capitate into three facets for articulation with the metacarpals of the index, long, and ring fingers [72].
- The trapezoid has two distal facets, which articulate with the metacarpal of the index finger [72].
- The trapezium has a saddle-shaped articulation with the base of the thumb metacarpal [72].
- The trapezium has a palmar groove for the flexor carpi radialis (FCR), bordered laterally by a palmar tuberosity and the attachment for the transverse carpal ligament [72].
- The pisiform is a sesamoid bone within the flexor carpi ulnaris (FCU) tendon [72].
- The pisiform is the origin for the abductor digiti minimi [72].
- The concave elliptical distal radius is oriented in the sagittal plane with an average of 11 degrees of volar tilt [69].
- In the frontal plane, the average radial inclination of the distal radius is 23 degrees [69].
- Radial length is measured from the tip of the radial styloid to the ulnar articular surface and averages 13 mm [69].
- The distal ulna has an ulnar styloid, which contains attachments to the triangular fibrocartilage complex, including the meniscus homolog, the volar and dorsal ulnar carpal ligaments, and the ulnar collateral ligament at the wrist [69].
- The triangular fibrocartilage attaches to the base of the ulnar styloid and separates the hyaline cartilage–covered ulnar head from the styloid [65].
- The distal ulnar convexity articulates at the lesser sigmoid notch of the distal radius [65].
- The sigmoid notch articular surface accommodates the ulnar head through two thirds of its arc [65].
- There is about a 20-degree inclination of the distal ulna at its articulation with the radius [65].
- The ulnar styloid lies dorsal to the ulnar head and extends distally [65].
Ligaments
- The chondroligamentous supports attaching the distal radius and ulnar side of the carpus to the distal ulna are designated as the triangular fibrocartilage complex (TFCC) [65].
- The TFCC includes the ulnar collateral ligament, the dorsal and volar radioulnar ligaments, the articular disc, the meniscal homologue, the extensor carpi ulnaris sheath, and the ulnolunate and ulnotriquetral ligament [65].
- The interosseous ligaments include the scapholunate and lunotriquetral interosseous ligaments connecting the proximal carpal row [65].
- The interosseous ligaments include the ligaments connecting the trapezium to the trapezoid, the trapezoid to the capitate, and the capitate to the hamate in the distal carpal row [65].
- The extrinsic or crossing ligaments include the radial collateral ligament from the radial styloid to the scaphoid waist [65].
- The extrinsic or crossing ligaments include the ulnar collateral ligament from the base of the ulnar styloid attaching to the pisiform [65].
- The extrinsic or crossing ligaments include the transverse carpal ligament [65].
- The volar extrinsic or crossing ligaments include the radioscapocapitate ligament, the radiolunotriquetral ligament, and the radioscapolunate ligament on the radial side [65].
- The volar extrinsic or crossing ligaments include the ulnolunate and ulnotriquetral components of the TFCC on the ulnar side [65].
- On the palmar side of the carpus, between the radiolunotriquetral ligament and the radioscapocapitate ligament, is a relatively thin area, the space of Poirier, overlying the palmar surface of the lunate [65].
- The dorsal radiocarpal ligament attaches along the dorsal radial articular margin of the lunate fossa, from the Lister tubercle to the lesser sigmoid notch [65].
- The dorsal radiocarpal ligament spans the lunotriquetral joint and inserts on the dorsal surface of the triquetrum [65].
- The dorsal intercarpal ligament is attached to the distal, dorsal surface of the triquetrum and passes across the midcarpal joint to attach to the dorsal surfaces of the scaphoid waist and the trapezoid [65].
- Extrinsic carpal ligaments connect the radius or the ulna to the carpus [70].
- In general, the volar ligaments are stronger than the dorsal ligaments [70].
- The radioscaphocapitate (RSC) ligament connects to the waist of the scaphoid, around which the scaphoid rotates, and limits ulnar translation of carpus [70].
- The long radiolunate ligament helps to limit ulnar translocation of the carpus [70].
- The short radiolunate ligament helps control lunate position [70].
- The radioscapholunate ligament is a vascular conduit, not a true ligament, also known as the ligament of Testut [70].
- The ulnolunate ligament attaches to the palmar radioulnar ligament and lunate [70].
- The ulnocapitate ligament attaches to the ulnar head and originates from the volar margin of the ulnar fovea; it is the most superficial or palmar [70].
- The ulnotriquetral ligament attaches to the palmar radioulnar ligament and triquetrum [70].
- The dorsal radiocarpal ligament (DRC) or dorsal radiotriquetral ligament has a trapezoidal shape and passes from the dorsal rim of the distal radius to the lunate and the triquetrum [70].
- Fibers of the dorsal radiocarpal ligament insert onto the dorsal lunotriquetral interosseous ligament [70].
- The dorsal radiocarpal ligament is associated with dorsal and volar intercalated segmental stabilities [70].
- Damage to the dorsal radiocarpal ligament, when in conjunction with other intrinsic ligament injuries, confers further carpal instability [70].
- The scapholunate interosseous ligament (SLIL) is a major stabilizer of the wrist and the most commonly injured wrist ligament [70].
- The scapholunate interosseous ligament is C-shaped and consists of dorsal, palmar, and interosseous portions with the dorsal portion being the strongest/thickest [70].
- The scapholunate interosseous ligament provides a flexion force on the lunate given its attachment to the scaphoid [70].
- The lunotriquetral interosseous ligament (LTIL) is C-shaped, where the volar portion is the thickest/strongest [70].
- The lunotriquetral interosseous ligament provides an extension moment on the lunate given its attachment to the triquetrum [70].
- The capitohamate ligament is a thick ligament, 5 × 5 mm in cross section, with extensions to the third or fourth metacarpals [70].
- The dorsal intercarpal ligament (DIC) passes from the dorsal tubercle of the triquetrum to the distal pole of the scaphoid [70].
- With the DRC ligament, the DIC ligament reinforces the elastic dorsal wrist capsule and helps stabilize the scapholunate articulation with a contribution to the dorsal SLIL from its deep fibers [70].
- The space of Poirier is an area adjacent to the proximal capitate without ligamentous attachment, situated ulnar to the RSC ligament and radial to the long radiolunate in the floor of the carpal tunnel [70].
- The space of Poirier is a weak area that is vulnerable to instability; the distal carpal row separates from the lunate through this space during a perilunate dislocation [70].
- The scapholunate interosseous ligament is C-shaped in the sagittal plane, and the dorsal third of the ligament is the thickest, strongest portion of the ligament [72].
- The volar portion of the lunotriquetral ligament is the thickest [72].
- The TFCC is formed by the central meniscus homolog, the dorsal and volar radioulnar ligaments, the floor of the extensor carpi ulnaris (ECU) tendon sheath, and the volar ulnocarpal ligaments [72].
- The TFCC arises from the radial border of the distal radius and inserts into the base of the ulnar styloid and distal ulna through the ligamentum subcruentum [72].
- The dorsal and volar radioulnar ligaments are the primary stabilizers of the distal radioulnar joint [72].
- Only the peripheral 10% to 40% of the volar, ulnar, and dorsal TFCC has a vascular supply [72].
- The dorsal radio-carpal ligament and the dorso-ulnar component of the triangular fibro-cartilage complex are the strongest of the dorsal ligaments of the wrist [91].
- The scapho-lunate ligament is much weaker and plays no important role during normal movements of the wrist [89].
- The dorsal subregion of the lunotriquetral ligament provided 62.3% ± 27.1% of the rotational resistance [46].
- The palmar subregion of the lunotriquetral ligament resisted 67.3% ± 14.1% of palmar translation [46].
- The flexor retinaculum consists of three distinct and continuous segments that extend from the level of the distal part of the radius to the level of the distal aspect of the base of the third metacarpal [44].
Vascular Anatomy
- The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches with longitudinal connections [75].
- The dorsal radiocarpal arch is located at the radiocarpal joint and supplies the lunate and triquetrum [75].
- The dorsal intercarpal arch is located between the proximal and distal carpal rows, is the largest, and supplies the distal carpal row and, through anastomoses with the radiocarpal arch, the lunate and triquetrum [75].
- The basal metacarpal arch is located at the base of the metacarpals, is the most variable, and supplies the distal carpal row [75].
- The palmar radiocarpal arch is located at the level of the radiocarpal joint on the palmar surfaces of the lunate and triquetrum [75].
- The intercarpal arch is located between the proximal and distal carpal rows, is the most variable, and does not contribute to nutrient vessels in the carpus [75].
- The deep palmar arch is located at the level of the metacarpal bases, is consistent, and communicates with the dorsal basal metacarpal arch and the palmar metacarpal arteries [75].
Kinematics & Biomechanics
- The wrist can essentially be considered to be a two-joint system linking the hand (described as the distal carpal row and the metacarpals) to the forearm (radius and ulna) around the highly mobile bones of the proximal carpal row [73].
- The two principle articulations are the radiocarpal and midcarpal joints, situated proximal and distal to the mobile proximal carpal row [73].
- The eight carpal bones that comprise the wrist joint represent the most complex articular system in the human body—each capable of moving in different degrees or directions dependent on the position, motion, and force generation of the hand in space [66].
- The human wrist is a magnificent engineering mechanism that allows precise positioning of the hand and optimization of power and prehensile tasks throughout a nearly hemispherical arc of wrist motion [66].
- Injuries to this finely tuned mechanism can lead to instability, resulting in a painful lack of motion, strength, and function [66].
- The bones of the wrist are composed of multiple articulations—the RC joint, midcarpal (MC) joint, pisotriquetral joint, trapeziometacarpal joint, and carpometacarpal joints [70].
- The wrist joint’s motion planes include flexion, extension, radial deviation, ulnar deviation, and circumduction; there is minimal carpal motion with pronosupination [70].
- Approximately 62° of wrist extension occurs through the RC joint and 62% of wrist flexion occurs through the MC joint [70].
- The MC joint is mostly responsible for 20° and 40° of radial and ulnar deviation, respectively, and is responsible for the “dart thrower’s motion” which involves moving from radial extension into ulnar flexion positioning of the wrist [70].
- The radius bears 80% of the axial load transmitted through the RC joint, while the ulna bears 20% in neutral ulnar variance [70].
- The proximal row of carpal bones form an intercalated segment between the distal carpal row and the distal radius and are bound into a functional unit by the SLIL and LTIL [70].
- The distal row is rigid, with little motion between its bones due to stout intercarpal ligaments, and thus they act as a functional unit with the scaphoid bridging both rows [70].
- During wrist flexion from neutral, the distal row flexes and ulnarly deviates slightly while the scaphoid also pronates [70].
- During wrist flexion from neutral, the proximal row flexes differentially, with more rotation through the scaphoid, followed by the triquetrum and the lunate [70].
- During wrist flexion from neutral, the proximal row translates dorsally [70].
- During wrist extension from neutral, the distal row extends and radially deviates slightly while the scaphoid also supinates [70].
- During wrist extension from neutral, the proximal row extends differentially, with more motion in the scaphoid
Classification
- Arthroscopic assessment and classification of Kienbock's disease allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion [1].
- The success of trapeziectomies depends on the stabilization of the first metacarpal base against the distal pole of the scaphoid [3].
- Early recognition of uncommon carpal disruptions may guide appropriate surgical treatment and improve long-term functional outcomes [4].
- Proximal row carpectomy seems to be no alternative after longstanding scapholunate dissociation (SLAC-Wrist) because of the high incidence of degenerative changes in the midcarpal joint [10].
- Arthritis due to scapholunate advanced collapse follows a predictable pattern in the wrist [20].
- High anatomic resolution allows the diagnosis of scapholunate dissociation with exact evaluation of changes in wrist morphology [25].
- Arthroscopic classification of scapholunate instability is much more precise and close to the reality than radiographic classification [36].
- The grade of carpal destruction was classified from the preoperative X-rays of the wrists according to Larsen et al.’s (1977) technique [26].
- According to Larsen et al.'s classification, arthrodesis is indicated in patients with classifications II, III, and IV [27].
- Normal I or severe destructive radiological abnormality V should not be considered for arthrodesis [27].
- All injuries were classified according to the Herzberg Initial Severity Classification for PLDs and PLFDs [51].
Clinical Presentation
Diagnostic Evaluation and Imaging
- Arthroscopic classification of Kienbock's disease allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion [1].
- High anatomic resolution of MR tomography allows the diagnosis of scapholunate dissociation with exact evaluation of changes in wrist morphology [25].
- Arthroscopic classification of scapholunate instability is more precise and close to reality than radiographic classification [36].
- In patients with continued pain over the radial side of the carpus, attention should be given to the other carpal bones and the distal radius and not just the scaphoid [52].
- Os Styloideum is an infrequent pathology and must be suspected in patients with persistent pain in the dorsal aspect of the hand or wrist [95].
Clinical Findings and Symptoms
- Symptoms of ulnar carpal instability include pain, weakness, and limited motion of the wrist [27].
- Dorsal prominence of the ulnar head is present in ulnar carpal instability, and tenosynovitis of the dorsal extensor compartments is usually present as well [27].
- Metacarpophalangeal joints are frequently affected in ulnar carpal instability, with palmar subluxation and ulnar drift [27].
- Some patients with ulnar carpal instability experience extensor tendon rupture [27].
- Synovitis of the carpometacarpal joints and progressive metacarpophalangeal pathology with muscular imbalance produce a pathologic palmar descent of the fourth and fifth metacarpal heads in ulnar carpal translation [27].
- The clinical sign of pathologic palmar descent of the fourth and fifth metacarpal heads is always present in ulnar carpal translation [27].
- This clinical sign increases when the patient makes a fist or grasps [27].
- Pain and functional disability at the level of the distal radioulnar joint were the main indications for surgery in patients undergoing resection of the distal ulna [26].
- Postoperatively, recovery of the wrist was rapid, though extension of the fingers remained poor for over 3 months in a case of unusual carpometacarpal fracture-dislocation [17].
Preoperative Assessment Considerations
- Although the simultaneous occurrence of arthritis of the wrist and the base of the thumb is rare, it is imperative to carry out a preoperative clinical and radiological assessment of the wrist when managing trapeziometacarpal osteoarthritis [45].
- To be successful with wrist arthroscopy and mitigate iatrogenic injury, a clear understanding of the topographical and 3-dimensional spatial anatomic relationships in the wrist as well as a patient’s unique anatomic variances is critical [31].
- The complex nature of the wrist has plagued clinicians and hampered the ability to formulate concise, yet thorough, algorithmic approaches to evaluation and treatment [24].
Investigations
Imaging Modalities
- MRI is the modality of choice for imaging radiographically occult fractures of the hand and wrist [71].
- High-resolution MRI aids in the evaluation of ligament injuries of the wrist [78].
- A static magnetic field strength of at least 1.5 T using a dedicated wrist coil is recommended for analyzing interosseous, intrinsic, and extrinsic ligament insertions [78].
- The volar extrinsic, scapholunate interosseous, dorsal intercarpal, and lunotriquetral ligaments are best visualized using 1 mm slices in the coronal plane [78].
- Dynamic fluoroscopy shows abnormal motion between the scaphoid and lunate and changes in the kinematics of the midcarpal joint [78].
- Live fluoroscopic imaging shows whether a DISI is reducible, providing information for treatment planning [78].
- CT scanning enables the 3D analysis of carpal dysfunction [78].
- CT is more useful than plain X-rays for evaluating partial carpal arthrodesis [94].
- Trispiral tomography is an important x-ray technique in the diagnosis and management of a variety of problems of the carpal bones and their joints [106].
- MRI has an expanding role in the evaluation of acute wrist trauma, where bone marrow edema may reveal fractures that are radiographically occult [81].
- MRI is useful in detecting additional marrow abnormalities in osteonecrosis, as seen in the lunate in Kienböck disease [81].
- Asymmetry of marrow signal in proximal and distal fragments of a fractured scaphoid is suggestive of proximal pole ischemia [81].
- MRI provides earlier detection of synovitis and erosive bone changes associated with rheumatoid arthritis than do radiographs [81].
- The primary advantages of MRI compared with CT and radiography are improved tissue characterization, especially of soft tissues such as ligamentous structures and synovium, and the lack of ionizing radiation [71].
- 3T MRI is much preferred for hand and wrist imaging, especially for imaging small fields of view [71].
- MR arthrography can be performed for evaluation of the triangular fibrocartilage and intercarpal ligament tears, but this is generally unnecessary with the increasing availability of high field MRI [71].
- Dynamic contrast enhancement has been used with inconsistent results to assess for the presence of avascular necrosis in the lunate or scaphoid after injury [71].
Arthroscopy
- Arthroscopy is considered by many to be the diagnostic intervention of choice for determining the degree of injury to the wrist [78].
- Arthroscopy can assess the condition of the cartilage, ability to reduce the carpus, and any other associated injuries [78].
- The degree of intrinsic and extrinsic ligament injury can be identified from arthroscopic evaluation [78].
- The main use of the wrist arthroscope is for diagnosis and to enable the treating physician to visualize the articular cartilage of the distal radius, proximal scaphoid, proximal lunate, and proximal triquetrum [58].
- In a comparative study, there was no difference between radiocarpal or midcarpal visualization and surgeon-rated ease of use between needle arthroscopy and conventional arthroscopy [105].
- Diagnostic confidence was the same between needle arthroscopy and conventional arthroscopy groups [105].
Preoperative Assessment and Classification
- The classification of Kienbock's disease allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion [1].
Treatment
Indications and Contraindications
- Proximal row carpectomy is indicated for Kienbock's disease when tailored to anatomical findings [1].
- Proximal row carpectomy is a reliable intervention for Kienbock's disease that provides useful function with reasonable strength [55].
- Proximal row carpectomy is confirmed as effective for the treatment of wrist osteoarthritis and severe carpal trauma [11].
- Proximal row carpectomy is not an alternative for longstanding scapholunate dissociation (SLAC-Wrist) due to the high incidence of degenerative changes in the midcarpal joint [10].
- Degenerative changes at the lunocapitate and radiolunate joint do not contraindicate a proximal row carpectomy [6].
- Procedure selection for wrist osteoarthritis should be individualized based on disease severity, carpal stability requirements, and patient-specific functional demands due to the absence of high-quality comparative trials [18].
Outcomes and Functional Expectations
- Patients can expect 50–70% of normal wrist range of motion after a proximal row carpectomy [8].
- Patients can expect 60–90% grip strength after a proximal row carpectomy [8].
- At long-term follow-up, all patients older than thirty-five years of age at the time of proximal row carpectomy maintained satisfactory range of motion, grip strength, and pain relief [7].
- Proximal row carpectomy with interposition arthroplasty is an effective motion-sparing procedure for patients with proximal capitate and/or lunate fossa arthritis [14].
- Proximal row carpectomy with interposition arthroplasty improves pain and function in patients with advanced wrist arthritis [14].
- In the acute setting of perilunate dislocation, proximal row carpectomy has medium-term results as good as open reduction internal fixation (ORIF) [12].
- Proximal row carpectomy in the acute setting of perilunate dislocation has a shorter operating time than ORIF [12].
- Current evidence shows no difference in postoperative total wrist arc range of motion between surgical approaches for acute perilunate injuries [32].
- Current evidence shows no difference in grip strength compared to the contralateral side between surgical approaches for acute perilunate injuries [32].
- Current evidence shows no difference in Mayo Wrist Score between surgical approaches for acute perilunate injuries [32].
Surgical Techniques and Adjuncts
- RCPI® can be associated with proximal row carpectomy in the management of advanced wrist osteoarthritis [13].
- RCPI® is an interesting alternative to standard proximal row carpectomy in advanced wrist osteoarthritis [13].
Complications
Radiographic and Structural Changes
- In a series of 30 proximal row carpectomies through a palmar approach, radiographic findings included reduction in articular space and subchondral sclerosis in the radiocapitate articulation [28].
- In that same palmar approach series, radiographic findings were classified as 5 normal, 5 mild, 9 moderate, and 6 fair [28].
- No statistically significant correlation was found between radiographic findings and clinical outcome in the palmar approach proximal row carpectomy series [28].
- Cineradiography confirmed complete stability of the new articulation during movements of AP and PA stressing, flexion/extension, and radial/ulnar wrist deviation in the palmar approach series [28].
Functional Outcomes and Limitations
- At long-term follow-up, all patients older than thirty-five years of age at the time of proximal row carpectomy maintained a satisfactory range of motion, grip strength, and pain relief [7].
- In a series of 19 patients undergoing distal scaphoid resection arthroplasty for degenerative arthritis secondary to scaphoid nonunion, increased range of wrist motion in all planes was observed in 85% [5].
- In that same series, grip strength improved by 134% [5].
- In that same series, 13 patients experienced complete relief of pain [5].
- In a series of 30 proximal row carpectomies through a palmar approach, pain scores decreased from 8 to 1 [28].
- In that same series, flexion/extension range of motion increased from 85 to 94 degrees [28].
- In that same series, radial/ulnar deviation increased from 39 to 46 degrees [28].
- In that same series, grip strength increased from 22 kg to 33 kg [28].
- Nineteen percent of patients in the palmar approach series returned to previous work within 2 months on average [28].
Contraindications and Failure Modes
- A mid-term study showed a high overall failure rate of 44.4% for all-dorsal scapholunate augmented reconstruction [109].
Acute Trauma and Revision Context
- Rates of median nerve symptoms were high and resolved in most cases (92%) after reduction of perilunate dislocations [117].
Recovery
- At long-term follow-up, all patients older than thirty-five years of age at the time of proximal row carpectomy were satisfied with the result [7].
- In a series of 19 patients undergoing distal scaphoid resection arthroplasty for degenerative arthritis secondary to scaphoid nonunion, grip improved by 134% [5].
- In a series of 19 patients undergoing distal scaphoid resection arthroplasty for degenerative arthritis secondary to scaphoid nonunion, 13 patients experienced complete relief of pain [5].
- Proximal row carpectomy with interposition arthroplasty improves pain and function in patients with proximal capitate and/or lunate fossa arthritis [14].
- Proximal row carpectomy in the acute setting of perilunate dislocation has medium-term results as good as ORIF [12].
Key Evidence
- [L4] The classification allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion. [1] (10.1097/00130911-200603000-00003)
- [L5] The proximal carpal row should be studied as one system. [2] (10.1016/0363-5023(93)90046-6)
- [L5] The success of trapeziectomies depends on the stabilization of the first metacarpal base against the distal pole of the scaphoid. [3] (10.1016/j.jhsa.2005.01.015)
- [L5] Early recognition of uncommon carpal disruptions may guide appropriate surgical treatment and improve long-term functional outcomes. [4] (10.1177/15589447261475382)
- [L4] The results of this procedure in 19 patients revealed increased range of wrist motion in all planes in 85%; grip improved by 134%, and 13 patients experienced complete relief of pain. [5] (10.1097/00130911-200206000-00009)
- [L4] X-ray findings of degenerative changes at the lunocapitate and radiolunate joint need not contraindicate a proximal row carpectomy. [6] (10.1016/s0363-5023(96)80147-x)
- [L4] At the time of long-term followup, all patients older than thirty-five years of age at the time of a proximal row carpectomy had maintained a satisfactory range of motion, grip strength, and pain relief and were satisfied with the result. [7] (10.2106/jbjs.e.00261)
- [Paper] The patient can expect 50–70% of normal wrist range of motion and 60–90% grip strength after a PRC. [8] (10.1097/00130911-199903000-00005)
- [L4] Proximal row carpectomy seems to be no alternative after longstanding scapholunate dissociation (SLAC-Wrist) because of the high incidence of degenerative changes in the midcarpal joint. [10] (10.1016/0266-7681(94)90353-0)
- [L4] This study confirms the role and long-term efficacy of proximal row carpectomy in the treatment of wrist osteoarthritis and severe carpal trauma. [11] (10.1016/j.hansur.2016.10.058)
- [L3] Proximal row carpectomy in the acute setting of perilunate dislocation has medium-term results as good as ORIF with a shorter operating time. [12] (10.1016/j.hansur.2016.10.140)
- [L4] RCPI® is an interesting alternative and can be associated with proximal row carpectomy in advanced wrist osteoarthritis. [13] (10.1016/j.otsr.2023.103783)
- [L4] Proximal row carpectomy with interposition arthroplasty is an effective motion-sparing procedure for patients with proximal capitate and/or lunate fossa arthritis, improving pain and function. [14] (10.1177/15589447241298721)
- [L5] Postoperatively recovery of the wrist was rapid, though extension of the fingers remained poor for over 3 months. [17] (10.1016/0020-1383(94)90161-9)
- [L1] Given the absence of high-quality comparative trials, procedure selection should be individualized, balancing disease severity, carpal stability requirements, and patient-specific functional demands. [18] (10.1007/s00402-026-06423-z)
- [L5] Arthritis due to scapholunate advanced collapse follows a predictable pattern in the wrist. [20] (10.1097/00130911-199712000-00003)
- [Paper] The complex nature of the wrist has plagued us clinically and hampered our ability to formulate concise, yet thorough, algorithmic approaches to evaluation and treatment. [24] (10.1016/s0894-1130(96)80065-2)
- [L4] High anatomic resolution allows the diagnosis of scapholunate dissociation with exact evaluation of changes in wrist morphology. [25] (10.1016/0266-7681(94)90351-4)
- [L4] [26] (10.1016/j.jhsb.2003.10.007)
- [L4] [27] (10.1097/00130911-200006000-00006)
- [L4] [28] (10.1016/s0363-5023(03)80411-2)
- [L5] To be successful with wrist arthroscopy and mitigate iatrogenic injury, a clear understanding of the topographical and 3-dimensional spatial anatomic relationships in the wrist as well as a patient’s unique anatomic variances is critical. [31] (10.1016/j.eats.2024.103223)
- [L1] Current evidence shows no difference in postoperative total wrist arc range of motion, grip strength (as compared to contralateral), or Mayo Wrist Score with regard to surgical approach. [32] (10.1177/15589447241231291)
- [L4] The goal of this work is to show that arthroscopic classification of scapholunate instability is much more precise and close to the reality than radiographic classification. [36] (10.1016/s0363-5023(03)80340-4)
- [L5] The flexor retinaculum consists of three distinct and continuous segments that extend from the level of the distal part of the radius to the level of the distal aspect of the base of the third metacarpal. [44] (10.1016/0363-5023(93)90251-w)
- [L5] Although the simultaneous occurrence of arthritis of the wrist and the base of the thumb is rare, it is nonetheless imperative to carry out a preoperative clinical and radiological assessment of the wrist when managing trapeziometacarpal osteoarthritis. [45] (10.1016/j.hansur.2020.08.013)
- [L5] The dorsal subregion provided 62.3% ± 27.1% of the rotational resistance, and the palmar subregion resisted 67.3% ± 14.1% of palmar translation. [46] (10.1016/s0363-5023(05)80460-5)
- [L4] In patients with continued pain over the radial side of the carpus, attention should be given to the other carpal bones and the distal radius and not just the scaphoid. [52] (10.1016/0020-1383(95)00081-j)
- [L4] La carpectomie proximale est une intervention fiable donnant une fonction utile avec une force raisonnable. [55] (10.1016/j.hansur.2017.10.089)
- [Paper] The main use of this instrument is for diagnosis and to enable the treating physician to visualize the articular cartilage of the distal radius, proximal scaphoid, proximal lunate, and proximal triquetrum. [58] (10.1016/s0363-5023(85)80133-7)
- [L5] The scapho-lunate ligament is much weaker and plays no important role during normal movements of the wrist. [89] (10.1016/0266-7681(93)90200-y)
- [L5] The dorsal radio-carpal ligament and the dorso-ulnar component of the triangular fibro-cartilage complex are the strongest of the dorsal ligaments of the wrist. [91] (10.1016/0266-7681(89)90025-9)
- [L4] We conclude that CT is more useful than plain X-rays for evaluating partial carpal arthrodesis. [94] (10.1016/s0266-7681(97)80367-1)
- [L4] Os Styloideum is an infrequent pathology and must be suspected in patients with persistent pain in the dorsal aspect of the hand or wrist. [95] (10.1177/15589447251317232)
- [L2] In this study, there was no difference between radiocarpal or midcarpal visualization and surgeon-rated ease of use, while diagnostic confidence was the same between two groups. [105] (10.1177/15589447241265982)
- [L5] Trispiral tomography is an important x-ray technique in the diagnosis and management of a variety of problems of the carpal bones and their joints. [106] (10.1016/s0363-5023(88)80044-3)
- [L4] Rates of median nerve symptoms were high and resolved in most cases (92%) after reduction. [117] (10.1177/15589447251317236)
References
[1] Arthroscopic Assessment and Classification of Kienbock's Disease. Techniques in Hand & Upper Extremity Surgery. 2006. DOI: 10.1097/00130911-200603000-00003
[2] Kinematics of the wrist and its ligaments. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90046-6
[3] Excision of the Trapezium for Osteoarthritis of the Trapeziometacarpal Joint. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.01.015
[4] Capitate Fracture-Dislocation: An Unusual Pattern of Carpal Injury. HAND. 2026. DOI: 10.1177/15589447261475382
[5] Distal Scaphoid Resection Arthroplasty for the Treatment of Patients With Degenerative Arthritis Secondary to Scaphoid Nonunion. Techniques in Hand and Upper Extremity Surgery. 2002. DOI: 10.1097/00130911-200206000-00009
[6] Proximal row carpectomy with partial capitate resection. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80147-x
[7] Proximal Row Carpectomy. Journal of Bone and Joint Surgery. 2005. DOI: 10.2106/jbjs.e.00261
[8] Proximal Row Carpectomy. Techniques in Hand & Upper Extremity Surgery. 1999. DOI: 10.1097/00130911-199903000-00005
[10] Advanced Carpal Collapse after Longstanding Scaphoid Nonunion (SNAC-Wrist) and Longstanding Scapho-Lunate Dissociation (SLAC-Wrist)—Where are the Differences?. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90353-0
[11] Trapézectomies secondaires après l’échec d’arthroplastie, résultats par rapport aux trapézectomies primaires. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.058
[12] Luxations périlunaires du carpe en phase aiguë : ORIF versus résection première rangée. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.140
[13] Comparison of proximal row carpectomy with RCPI® versus proximal row carpectomy with Eaton's capsular interposition in the management of advanced wrist osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2024. DOI: 10.1016/j.otsr.2023.103783
[14] Outcomes of Proximal Row Carpectomy With Interposition Arthroplasty for Advanced Wrist Arthritis. HAND. 2024. DOI: 10.1177/15589447241298721
[17] An unusual carpometacarpal fracture—dislocation. Injury. 1994. DOI: 10.1016/0020-1383(94)90161-9
[18] Conservative and surgical treatment of wrist osteoarthritis: a systematic review. Archives of Orthopaedic and Trauma Surgery. 2026. DOI: 10.1007/s00402-026-06423-z
[20] Midcarpal Arthrodesis. Techniques in Hand & Upper Extremity Surgery. 1997. DOI: 10.1097/00130911-199712000-00003
[24] The Mysterious Wrist. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80065-2
[25] MR Tomographic Diagnosis of Scapholunate Dissociation. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90351-4
[26] Radiographic Changes after Resection of the Distal Ulna in Rheumatoid Arthritis. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.10.007
[27] A New Method for Radiolunate Arthrodesis in Ulnar Translocation of the Carpus in the Rheumatoid Wrist. Techniques in Hand & Upper Extremity Surgery. 2000. DOI: 10.1097/00130911-200006000-00006
[28] Proximal row carpectomy through volar approach. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80411-2
[31] Wrist Arthroscopy: Positioning, Portal Placement, and Diagnostic Evaluation. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103223
[32] A Comparison of Outcomes in Acute Perilunate Injuries: Systematic Review and Meta-Analysis of Treatment Approaches. HAND. 2024. DOI: 10.1177/15589447241231291
[36] Correlation radiography-arthroscopy in the scapholunate instability. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80340-4
[44] Anatomy of the flexor retinaculum. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90251-w
[45] Trapeziometacarpal osteoarthritis and arthritis of the wrist. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.08.013
[46] Lunotriquetral ligament properties: A comparison of three anatomic subregions. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(05)80460-5
[51] 10.1177-15589447251397017. n.d..
[52] The suspected scaphoid fracture and isotope bone imaging. Injury. 1995. DOI: 10.1016/0020-1383(95)00081-j
[55] La résection de la première rangée du carpe dans la maladie de Kienböck. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.10.089
[58] Wrist arthroscope. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80133-7
[65] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[66] Green S Operative Hand Surgery. INTRODUCTION.
[69] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS OF THE DISTAL AND MID-FOREARM.
[70] Aaos Comprehensive Orthopaedic Review 3. Carpal Instability* > II. Anatomy and Biomechanics (See Chapter 92).
[71] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Imaging: Advances in Imaging of the Hand and Upper Extremity > Magnetic Resonance Imaging.
[72] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[73] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[75] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[78] Green S Operative Hand Surgery. Advanced Imaging.
[81] Campbell S Operative Orthopaedics 4 Volume Set. WRIST AND ELBOW.
[89] The Distal Ligamentous Complex of the Scaphoid and the Scapho-Lunate Ligament. An Anatomic, Histological and Biomechanical study. Journal of Hand Surgery. 1993. DOI: 10.1016/0266-7681(93)90200-y
[91] The Dorsal Carpal Ligaments: Their Anatomy and Function. Journal of Hand Surgery. 1989. DOI: 10.1016/0266-7681(89)90025-9
[94] Computed Tomography in Partial Carpal Arthrodesis. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80367-1
[95] Os Styloideum and Third Metacarpal Partial Coalition Nonunion After Traumatic Fracture: A Report of Three Cases. HAND. 2025. DOI: 10.1177/15589447251317232
[105] Needle Arthroscopy Versus Conventional Arthroscopy in the Evaluation of Carpal Pathology: A Comparative Study. HAND. 2024. DOI: 10.1177/15589447241265982
[106] Trispiral tomography for the evaluation of wrist problems. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80044-3
[109] 10.1177-15589447251391375. n.d..
[117] Perilunate Dislocation Reduction Technique and Results. HAND. 2025. DOI: 10.1177/15589447251317236