Patients › Wrist
TFCC ਦੀ ਸੱਟ
TFCC injuries — pain on the ulnar side of the wrist, often with clicking, and treatment options.
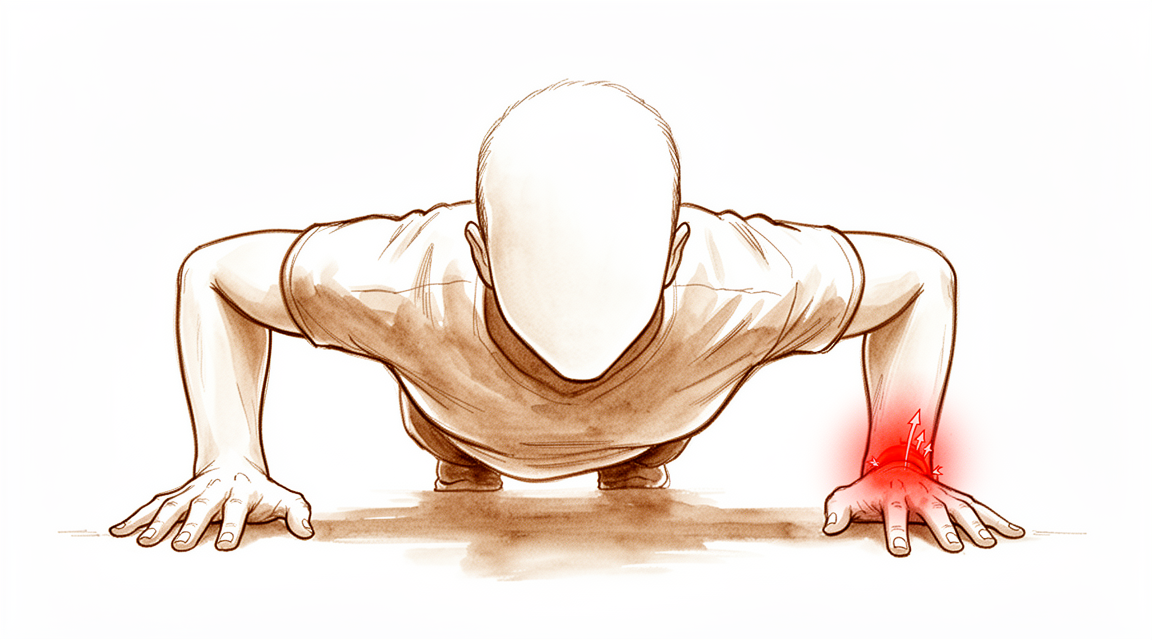
ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ
ਦਰਦ ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ ਹੁੰਦਾ ਹੈ, ਜਿਸ ਨੂੰ ਅਲਨਰ ਪਾਸਾ (ulnar side) ਕਿਹਾ ਜਾਂਦਾ ਹੈ। ਜਦੋਂ ਤੁਸੀਂ ਉਸ ਪਾਸੇ ਉੱਤੇ ਭਾਰ ਪਾਉਂਦੇ ਹੋ ਤਾਂ ਇਹ ਅਕਸਰ ਭੜਕ ਉੱਠਦਾ ਹੈ: ਕੁਰਸੀ ਤੋਂ ਹੱਥਾਂ ਦੇ ਜ਼ੋਰ ਨਾਲ ਉੱਠਣਾ, ਮਰਤਬਾਨ ਨੂੰ ਘੁੱਟ ਕੇ ਫੜਨਾ, ਜਾਂ ਕੋਈ ਭਾਰੀ ਚੀਜ਼ ਫੜੀ ਹੋਣ ਵੇਲੇ ਦਰਵਾਜ਼ੇ ਦਾ ਹੈਂਡਲ ਘੁਮਾਉਣਾ। ਮਰੋੜਨ ਵਾਲੀਆਂ ਹਰਕਤਾਂ, ਜਿਵੇਂ ਕੱਪੜਾ ਨਿਚੋੜਨਾ ਜਾਂ ਪੇਚਕਸ (screwdriver) ਵਰਤਣਾ, ਵੀ ਦਰਦ ਛੇੜ ਸਕਦੀਆਂ ਹਨ।
ਕੁਝ ਲੋਕ ਦੇਖਦੇ ਹਨ ਕਿ ਗੁੱਟ ਡਾਵਾਂਡੋਲ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ, ਜਿਵੇਂ ਇਹ ਜਵਾਬ ਦੇ ਜਾਵੇਗਾ, ਜਾਂ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ (forearm) ਨੂੰ ਘੁਮਾਉਣ ਵੇਲੇ ਇਸ ਵਿੱਚ ਖੜਾਕ (clunk) ਹੁੰਦਾ ਹੈ। ਦੂਜਿਆਂ ਨੂੰ ਅਜਿਹਾ ਦਰਦ ਰਹਿੰਦਾ ਹੈ ਜੋ ਟਿਕਿਆ ਰਹਿੰਦਾ ਹੈ ਪਰ ਸਕੈਨਾਂ ਉੱਤੇ ਕੋਈ ਸਾਫ਼ ਕਾਰਨ ਨਹੀਂ ਦਿਸਦਾ, ਅਤੇ ਗੁੱਟ ਦੇ ਇਸ ਹਿੱਸੇ ਵਿੱਚ ਇਹ ਆਮ ਗੱਲ ਹੈ। ਕੰਮ-ਕਾਜ ਤੋਂ ਬਾਅਦ ਦੁਖਣ ਵੱਧ ਹੋ ਸਕਦੀ ਹੈ, ਅਤੇ ਇਹ ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਜਾਂ ਸਵੇਰੇ ਉੱਠਦਿਆਂ ਹੀ ਤੰਗ ਕਰ ਸਕਦੀ ਹੈ।
ਰੋਜ਼ਾਨਾ ਜੀਵਨ ਵਿੱਚ, ਉਹ ਕੰਮ ਔਖੇ ਹੋ ਜਾਂਦੇ ਹਨ ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਘੁੱਟ ਕੇ ਫੜਨਾ ਅਤੇ ਮਰੋੜਨਾ ਪੈਂਦਾ ਹੈ: ਫਸਿਆ ਹੋਇਆ ਢੱਕਣ ਖੋਲ੍ਹਣਾ, ਉਸ ਪਾਸੇ ਦੇ ਹੱਥ ਨਾਲ ਸੌਦੇ ਦਾ ਭਾਰੀ ਥੈਲਾ ਚੁੱਕਣਾ, ਜਾਂ ਨੀਵੀਂ ਸੀਟ ਤੋਂ ਉੱਠਣ ਲਈ ਹੱਥ ਉੱਤੇ ਟੇਕ ਲਾਉਣਾ। ਜਿਸ ਕੰਮ ਵਿੱਚ ਔਜ਼ਾਰ ਵਰਤਣੇ ਪੈਂਦੇ ਹਨ ਜਾਂ ਗੁੱਟ ਉੱਤੇ ਵਾਰ-ਵਾਰ ਜ਼ੋਰ ਪੈਂਦਾ ਹੈ, ਉਹ ਦਰਦ ਨੂੰ ਜਾਰੀ ਰੱਖ ਸਕਦਾ ਹੈ।
ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾ ਦਿੰਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਆਪਣਾ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਅਸਲ ਵਿੱਚ ਕੀ ਹੋ ਰਿਹਾ ਹੈ
ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਅੰਦਰ, ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ, ਇੱਕ ਬਣਤਰ ਹੁੰਦੀ ਹੈ ਜਿਸ ਨੂੰ ਟ੍ਰਾਈਐਂਗੂਲਰ ਫ਼ਾਈਬ੍ਰੋਕਾਰਟੀਲੇਜ ਕੰਪਲੈਕਸ (triangular fibrocartilage complex), ਜਾਂ TFCC, ਕਹਿੰਦੇ ਹਨ। ਇਸ ਨੂੰ ਇੱਕ ਝਟਕਾ-ਸੋਖਕ (shock absorber) ਵਾਂਗ ਸਮਝੋ ਜਿਸ ਨਾਲ ਰੱਸੀਆਂ ਬੱਝੀਆਂ ਹੋਣ। ਝਟਕਾ-ਸੋਖਕ ਸਖ਼ਤ, ਚਿਕਨੀ ਕਾਰਟੀਲੇਜ (cartilage) ਦੀ ਇੱਕ ਡਿਸਕ ਹੈ, ਜੋ ਤੁਹਾਡੀ ਅਲਨਾ (ulna, ਉਸ ਪਾਸੇ ਦੀ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦੀ ਹੱਡੀ) ਦੇ ਸਿਰੇ ਅਤੇ ਤੁਹਾਡੇ ਗੁੱਟ ਦੀਆਂ ਛੋਟੀਆਂ ਹੱਡੀਆਂ ਦੇ ਵਿਚਕਾਰ ਹੁੰਦੀ ਹੈ। ਰੱਸੀਆਂ ਲਿਗਾਮੈਂਟ (ligaments, ਹੱਡੀ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੇ ਬੰਧਨ) ਹਨ, ਜੋ ਉਸ ਡਿਸਕ ਨੂੰ ਅਲਨਾ ਨਾਲ ਬੰਨ੍ਹ ਕੇ ਰੱਖਦੇ ਹਨ ਅਤੇ ਉਸ ਜੋੜ ਨੂੰ ਟਿਕਾਈ ਰੱਖਦੇ ਹਨ ਜਿੱਥੇ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦੀਆਂ ਦੋਵੇਂ ਹੱਡੀਆਂ ਗੁੱਟ ਕੋਲ ਮਿਲਦੀਆਂ ਹਨ।
TFCC ਇੱਕੋ ਵੇਲੇ ਦੋ ਕੰਮ ਕਰਦਾ ਹੈ। ਇਹ ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਅਲਨਰ ਪਾਸੇ ਤੋਂ ਲੰਘਣ ਵਾਲੇ ਭਾਰ ਨੂੰ ਗੱਦੀ ਵਾਂਗ ਸਹਾਰਦਾ ਹੈ, ਅਤੇ ਜਦੋਂ ਤੁਸੀਂ ਆਪਣੀ ਹਥੇਲੀ ਨੂੰ ਉੱਪਰ ਅਤੇ ਹੇਠਾਂ ਵੱਲ ਘੁਮਾਉਂਦੇ ਹੋ ਤਾਂ ਬਾਂਹ ਦੇ ਉਸ ਜੋੜ ਨੂੰ ਜੋੜੀ ਰੱਖਦਾ ਹੈ। ਇਹ ਦੋਹਰੀ ਭੂਮਿਕਾ ਉੱਪਰ ਦੱਸੇ ਦੋ ਪੈਟਰਨਾਂ ਨੂੰ ਸਮਝਾਉਂਦੀ ਹੈ। ਜਦੋਂ ਗੱਦੀ ਵਾਲਾ ਹਿੱਸਾ ਪਾਟ ਜਾਂਦਾ ਹੈ, ਤਾਂ ਉਸ ਪਾਸੇ ਉੱਤੇ ਭਾਰ ਪਾਉਣ ਨਾਲ ਦਰਦ ਹੁੰਦਾ ਹੈ: ਕੁਰਸੀ ਤੋਂ ਹੱਥਾਂ ਦੇ ਜ਼ੋਰ ਨਾਲ ਉੱਠਣਾ, ਘੁੱਟ ਕੇ ਫੜਨਾ, ਮਰੋੜਨਾ। ਜਦੋਂ ਰੱਸੀਆਂ ਅਲਨਾ ਉੱਤੇ ਆਪਣੀ ਜੁੜਨ ਵਾਲੀ ਥਾਂ ਤੋਂ ਪਾਟ ਕੇ ਉੱਖੜ ਜਾਂਦੀਆਂ ਹਨ, ਤਾਂ ਜੋੜ ਦਾ ਆਪਣਾ ਸਹਾਰਾ ਖ਼ਤਮ ਹੋ ਜਾਂਦਾ ਹੈ, ਇਸ ਲਈ ਗੁੱਟ ਇਵੇਂ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ ਜਿਵੇਂ ਜਵਾਬ ਦੇ ਜਾਵੇਗਾ, ਜਾਂ ਬਾਂਹ ਘੁਮਾਉਣ ਵੇਲੇ ਇਸ ਵਿੱਚ ਖੜਾਕ ਹੁੰਦਾ ਹੈ। ਦੂਜਾ ਪੈਟਰਨ ਵੱਧ ਮਾਇਨੇ ਰੱਖਦਾ ਹੈ, ਕਿਉਂਕਿ ਲਿਗਾਮੈਂਟ ਵਾਲਾ ਹਿੱਸਾ ਹੀ ਜੋੜ ਨੂੰ ਜੋੜੀ ਰੱਖਦਾ ਹੈ।
ਇਸ ਥਾਂ ਬਾਰੇ ਇੱਕ ਹੋਰ ਗੱਲ ਜਾਣਨ ਯੋਗ ਹੈ। ਸਿਰਫ਼ TFCC ਦੇ ਬਾਹਰਲੇ ਕਿਨਾਰੇ ਨੂੰ ਖ਼ੂਨ ਮਿਲਦਾ ਹੈ, ਲਗਭਗ ਇਸ ਦੇ ਬਾਹਰਲੇ 10% ਤੋਂ 40% ਹਿੱਸੇ ਨੂੰ। ਅੰਦਰਲੇ ਹਿੱਸੇ ਨੂੰ ਲਗਭਗ ਕੋਈ ਖ਼ੂਨ ਨਹੀਂ ਮਿਲਦਾ। ਖ਼ੂਨ ਹੀ ਠੀਕ ਹੋਣ ਦੀ ਸਮਰੱਥਾ ਲਿਆਉਂਦਾ ਹੈ, ਇਸ ਲਈ ਕਿਨਾਰੇ ਦੇ ਨੇੜੇ ਦੇ ਪਾਟਣਾਂ ਦੇ ਜੁੜਨ ਦੀ ਅਸਲ ਸੰਭਾਵਨਾ ਹੁੰਦੀ ਹੈ, ਜਦਕਿ ਵਿਚਕਾਰਲੇ ਪਾਟਣ ਆਮ ਤੌਰ 'ਤੇ ਆਪਣੇ ਆਪ ਠੀਕ ਨਹੀਂ ਹੁੰਦੇ। ਇਸੇ ਕਰਕੇ ਇੱਥੇ ਦਾ ਪਾਟਣ ਦੁਖਦਾ ਵੀ ਰਹਿ ਸਕਦਾ ਹੈ: ਨੁਕਸਾਨਿਆ ਟਿਸ਼ੂ ਅਜਿਹੀ ਥਾਂ ਹੁੰਦਾ ਹੈ ਜਿੱਥੇ ਸਰੀਰ ਲਈ ਉਸ ਦੀ ਮੁਰੰਮਤ ਕਰਨਾ ਔਖਾ ਹੁੰਦਾ ਹੈ, ਅਤੇ ਹਰ ਵਾਰ ਫੜਨ ਜਾਂ ਮਰੋੜਨ ਨਾਲ ਉਸ ਉੱਤੇ ਭਾਰ ਪੈਂਦਾ ਰਹਿੰਦਾ ਹੈ।
ਇਸ ਲਈ ਦਰਦ, ਖੜਾਕ ਅਤੇ ਗੁੱਟ ਦਾ ਜਵਾਬ ਦੇਣਾ ਵੱਖੋ-ਵੱਖਰੀਆਂ ਸਮੱਸਿਆਵਾਂ ਨਹੀਂ ਹਨ। ਇਹ ਉਦੋਂ ਹੁੰਦਾ ਹੈ ਜਦੋਂ ਗੱਦੀ ਅਤੇ ਸਹਾਰੇ ਦਾ ਦੋਹਰਾ ਕੰਮ ਕਰਨ ਵਾਲੀ ਬਣਤਰ, ਜਿਸ ਉੱਤੇ ਤੁਹਾਡੇ ਹੱਥ ਦੀ ਹਰ ਹਰਕਤ ਨਾਲ ਭਾਰ ਪੈਂਦਾ ਹੈ, ਆਪਣੇ ਦੋਵੇਂ ਕੰਮ ਨਹੀਂ ਕਰ ਰਹੀ ਹੁੰਦੀ।
ਅਸੀਂ ਇਸ ਬਾਰੇ ਕੀ ਕਰ ਸਕਦੇ ਹਾਂ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਜੋ ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ ਹਨ, ਤੁਹਾਡੀ ਹਾਲਤ ਲਈ ਢੁਕਵੇਂ ਸਭ ਤੋਂ ਘੱਟ ਚੀਰ-ਫਾੜ ਵਾਲੇ ਵਿਕਲਪਾਂ ਤੋਂ ਸ਼ੁਰੂਆਤ ਕਰਦੇ ਹਨ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ 'ਤੇ ਉਹਨਾਂ ਦਾ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਡੇ ਕੋਲ ਆਉਣ ਦੀ ਸਲਾਹ ਦਿੱਤੀ ਹੈ, ਤਾਂ ਵੀ ਮੈਡੀਕੇਅਰ ਰਿਬੇਟ (Medicare rebate) ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ (referral) ਦੀ ਲੋੜ ਪਵੇਗੀ। ਉਸ ਪਹਿਲੀ ਮੁਲਾਕਾਤ ਵਿੱਚ ਅਸੀਂ ਤੁਹਾਡੀ ਤਕਲੀਫ਼ ਦਾ ਪੂਰਾ ਵੇਰਵਾ ਲੈਂਦੇ ਹਾਂ, ਤੁਹਾਡੇ ਗੁੱਟ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਇਹ ਪਤਾ ਕਰਨ ਲਈ ਕਿ ਕੀ ਪਾਟਿਆ ਹੈ, ਜਿੱਥੇ ਲੋੜ ਹੋਵੇ ਇਮੇਜਿੰਗ (ਐਕਸ-ਰੇ ਜਾਂ ਸਕੈਨ) ਦਾ ਪ੍ਰਬੰਧ ਕਰਦੇ ਹਾਂ।
TFCC ਦੇ ਕੁਝ ਪਾਟਣ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਿਨਾਂ ਸ਼ਾਂਤ ਹੋ ਜਾਂਦੇ ਹਨ। ਸਪਲਿੰਟ ਗੁੱਟ ਨੂੰ ਸਥਿਰ ਰੱਖ ਸਕਦਾ ਹੈ ਅਤੇ ਦੁਖਦੀ ਥਾਂ ਤੋਂ ਭਾਰ ਹਟਾ ਸਕਦਾ ਹੈ, ਜਦੋਂ ਕਿ ਬਾਹਰਲੇ ਕਿਨਾਰੇ ਨੂੰ, ਯਾਨੀ ਉਸ ਹਿੱਸੇ ਨੂੰ ਜਿਸ ਨੂੰ ਖ਼ੂਨ ਮਿਲਦਾ ਹੈ, ਜੁੜਨ ਦਾ ਮੌਕਾ ਮਿਲਦਾ ਹੈ। ਹੈਂਡ ਥੈਰੇਪੀ ਦਾ ਮਕਸਦ ਦਰਦ ਨੂੰ ਸ਼ਾਂਤ ਕਰਨਾ ਅਤੇ ਤਾਕਤ ਅਤੇ ਪਕੜ ਮੁੜ ਬਣਾਉਣਾ ਹੈ ਤਾਂ ਜੋ ਗੁੱਟ ਫਿਰ ਤੋਂ ਰੋਜ਼ਾਨਾ ਦਾ ਭਾਰ ਸਹਿ ਸਕੇ। ਇਹ ਕਾਰਗਰ ਹੋ ਰਿਹਾ ਹੈ ਜਾਂ ਨਹੀਂ, ਇਸ ਦਾ ਫ਼ੈਸਲਾ ਕਰਨ ਤੋਂ ਪਹਿਲਾਂ ਅਸੀਂ ਆਮ ਤੌਰ 'ਤੇ ਇਸ ਨੂੰ ਕਈ ਹਫ਼ਤਿਆਂ ਦਾ ਪੂਰਾ ਮੌਕਾ ਦਿੰਦੇ ਹਾਂ।
ਦਰਦ ਨਿਵਾਰਕ ਗੋਲੀਆਂ ਅਤੇ ਸੋਜਸ਼-ਰੋਧੀ ਦਵਾਈਆਂ (anti-inflammatories) ਪਾਟਣ ਦੇ ਸ਼ਾਂਤ ਹੋਣ ਦੌਰਾਨ ਤੁਹਾਨੂੰ ਹਿੱਲਦੇ-ਜੁਲਦੇ ਰਹਿਣ ਵਿੱਚ ਮਦਦ ਕਰ ਸਕਦੀਆਂ ਹਨ। ਇਹ ਟਿਸ਼ੂ ਦੀ ਮੁਰੰਮਤ ਨਹੀਂ ਕਰਦੀਆਂ, ਬੱਸ ਦਿਨਾਂ ਨੂੰ ਵੱਧ ਆਰਾਮਦਾਇਕ ਬਣਾਉਂਦੀਆਂ ਹਨ।
ਜੇ ਉਸ ਤੋਂ ਬਾਅਦ ਵੀ ਦਰਦ ਜਾਂ ਖੜਾਕ ਤੁਹਾਨੂੰ ਸੀਮਤ ਕਰਦਾ ਹੈ, ਤਾਂ ਅਸੀਂ ਸਰਜਰੀ ਬਾਰੇ ਗੱਲ ਕਰਦੇ ਹਾਂ। ਆਮ ਪਹਿਲਾ ਕਦਮ ਦੂਰਬੀਨ ਵਾਲੀ (ਆਰਥਰੋਸਕੋਪਿਕ) ਸਰਜਰੀ ਹੈ, ਜਿਸ ਨੂੰ ਗੁੱਟ ਦੀ ਆਰਥਰੋਸਕੋਪੀ (wrist arthroscopy) ਕਹਿੰਦੇ ਹਨ। ਸਰਜਨ ਬਹੁਤ ਛੋਟੇ ਕੈਮਰੇ ਨਾਲ ਛੋਟੇ ਚੀਰਿਆਂ ਰਾਹੀਂ ਜੋੜ ਦੇ ਅੰਦਰ ਦੇਖਦਾ ਹੈ, ਅਤੇ TFCC ਦੇ ਪਾਟਣ ਦੀ ਪੁਸ਼ਟੀ ਕਰਨ ਅਤੇ ਨਾਲ ਹੀ ਲਿਗਾਮੈਂਟਾਂ ਅਤੇ ਜੋੜ ਦੀਆਂ ਸਤ੍ਹਾਵਾਂ ਦੀ ਜਾਂਚ ਕਰਨ ਦਾ ਇਹ ਸਭ ਤੋਂ ਸਹੀ ਤਰੀਕਾ ਹੈ। ਕੁਝ ਪਾਟਣਾਂ ਨੂੰ ਉਨ੍ਹਾਂ ਹੀ ਛੋਟੇ ਚੀਰਿਆਂ ਰਾਹੀਂ ਸਾਫ਼ ਕਰ ਕੇ ਪੱਧਰਾ ਕੀਤਾ ਜਾਂ ਉਨ੍ਹਾਂ ਦੀ ਮੁਰੰਮਤ ਕੀਤੀ ਜਾ ਸਕਦੀ ਹੈ। ਜਿੱਥੇ ਗੱਦੀ ਘਿਸ ਚੁੱਕੀ ਹੋਵੇ ਅਤੇ ਗੁੱਟ ਦੇ ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ ਉੱਤੇ ਵਾਧੂ ਭਾਰ ਪੈ ਰਿਹਾ ਹੋਵੇ, ਉੱਥੇ ਇੱਕ ਪ੍ਰਕਿਰਿਆ ਰਾਹੀਂ ਅਲਨਾ ਦੇ ਸਿਰੇ ਤੋਂ ਥੋੜ੍ਹਾ ਜਿਹਾ ਹਿੱਸਾ ਛਿੱਲ ਕੇ ਉਸ ਪਾਸੇ ਦਾ ਦਬਾਅ ਘਟਾਇਆ ਜਾ ਸਕਦਾ ਹੈ। ਪਾਟਣ ਨੂੰ ਸਾਫ਼ ਕਰਨ, ਉਸ ਦੀ ਮੁਰੰਮਤ ਕਰਨ, ਜਾਂ ਟੈਂਡਨ (tendon, ਪੱਠੇ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀ ਮਜ਼ਬੂਤ ਤੰਦ) ਦੇ ਟੁਕੜੇ (graft) ਨਾਲ ਉਸ ਨੂੰ ਦੁਬਾਰਾ ਬਣਾਉਣ ਵਿਚਕਾਰ ਚੋਣ ਇਸ ਗੱਲ ਉੱਤੇ ਨਿਰਭਰ ਕਰਦੀ ਹੈ ਕਿ ਪਾਟਣ ਕਿੱਥੇ ਹੈ ਅਤੇ ਕਿੰਨੇ ਸਮੇਂ ਤੋਂ ਹੈ।
ਇਹ ਮਿਲ ਕੇ ਕੀਤਾ ਜਾਣ ਵਾਲਾ ਫ਼ੈਸਲਾ ਹੈ। ਅਸੀਂ ਸਮਝਾਉਂਦੇ ਹਾਂ ਕਿ ਹਰ ਵਿਕਲਪ ਵਿੱਚ ਕੀ ਸ਼ਾਮਲ ਹੈ ਅਤੇ ਇਹ ਕੀ ਬਦਲ ਸਕਦਾ ਹੈ ਅਤੇ ਕੀ ਨਹੀਂ, ਅਤੇ ਤੁਸੀਂ ਫ਼ੈਸਲਾ ਕਰਦੇ ਹੋ ਕਿ ਤੁਹਾਡੇ ਗੁੱਟ ਅਤੇ ਤੁਹਾਡੀ ਜ਼ਿੰਦਗੀ ਲਈ ਕੀ ਢੁਕਵਾਂ ਹੈ।
ਕੀ ਉਮੀਦ ਰੱਖੀਏ
ਬਹੁਤ ਸਾਰੇ ਲੋਕਾਂ ਵਿੱਚ, TFCC ਦਾ ਪਾਟਣ ਸਮੇਂ ਅਤੇ ਸਹੀ ਦੇਖਭਾਲ ਨਾਲ ਸ਼ਾਂਤ ਹੋ ਜਾਂਦਾ ਹੈ। ਬਾਹਰਲੇ ਕਿਨਾਰੇ ਦੇ ਨੇੜੇ ਦੇ ਪਾਟਣਾਂ ਦੇ, ਜਿੱਥੇ ਖ਼ੂਨ ਮਿਲਦਾ ਹੈ, ਆਪਣੇ ਆਪ ਜਾਂ ਸਪਲਿੰਟ ਨਾਲ ਜੁੜਨ ਦੀ ਅਸਲ ਸੰਭਾਵਨਾ ਹੁੰਦੀ ਹੈ। ਗੱਦੀ ਦੇ ਵੱਧ ਅੰਦਰ ਵਾਲੇ ਪਾਟਣ ਆਮ ਤੌਰ 'ਤੇ ਆਪਣੇ ਆਪ ਠੀਕ ਨਹੀਂ ਹੁੰਦੇ, ਪਰ ਜਦੋਂ ਗੁੱਟ ਨੂੰ ਆਰਾਮ ਦਿੱਤਾ ਜਾਵੇ ਅਤੇ ਇਸ ਉੱਤੇ ਘੱਟ ਭਾਰ ਪਾਇਆ ਜਾਵੇ, ਤਾਂ ਫਿਰ ਵੀ ਦਰਦ ਘਟ ਸਕਦਾ ਹੈ।
ਠੀਕ ਹੋਣਾ ਇੱਕਦਮ ਨਹੀਂ, ਹੌਲੀ-ਹੌਲੀ ਹੁੰਦਾ ਹੈ। ਜ਼ਿਆਦਾਤਰ ਲੋਕ ਦੇਖਦੇ ਹਨ ਕਿ ਦੁਖਣ ਦਿਨਾਂ ਦੀ ਬਜਾਏ ਹਫ਼ਤਿਆਂ ਵਿੱਚ ਘਟਦੀ ਹੈ, ਅਤੇ ਜਿਵੇਂ-ਜਿਵੇਂ ਗੁੱਟ ਸ਼ਾਂਤ ਹੁੰਦਾ ਹੈ, ਪਕੜ ਅਤੇ ਮਰੋੜਨ ਦੀ ਤਾਕਤ ਵਾਪਸ ਆਉਂਦੀ ਹੈ। ਜੇ ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ ਦੇ ਸਿਰਫ਼ ਇਕੱਲੇ ਪਾਟਣ ਲਈ ਤੁਹਾਡੀ ਦੂਰਬੀਨ ਵਾਲੀ ਸਰਜਰੀ ਹੁੰਦੀ ਹੈ, ਤਾਂ ਕੰਮ ਉੱਤੇ ਵਾਪਸ ਜਾਣ ਦਾ ਔਸਤ ਸਮਾਂ 5.5 ਹਫ਼ਤੇ ਹੈ। ਖਿਡਾਰੀਆਂ ਨੂੰ ਆਪਣੀ ਖੇਡ ਵਿੱਚ ਵਾਪਸ ਆਉਣ ਵਿੱਚ ਵੱਧ ਸਮਾਂ ਲੱਗ ਸਕਦਾ ਹੈ, ਖ਼ਾਸ ਕਰਕੇ ਜੇ ਗੁੱਟ ਦੇ ਉਸੇ ਪਾਸੇ ਹੋਰ ਸੱਟਾਂ ਵੀ ਹੋਣ। ਇੱਕ ਪੈਟਰਨ ਜਾਣਨ ਯੋਗ ਹੈ: ਜੇ ਅਲਨਾ ਦਾ ਸਿਰਾ ਗੁੱਟ ਵਿੱਚ ਦੱਬ ਕੇ ਦਰਦ ਕਰ ਰਿਹਾ ਸੀ, ਤਾਂ ਖੇਡ ਵਿੱਚ ਵਾਪਸ ਜਾਣ ਉੱਤੇ ਉਹ ਦਰਦ ਅਕਸਰ ਮੁੜ ਆ ਜਾਂਦਾ ਹੈ।
ਜੇ ਪਾਟਣ ਨੂੰ ਇਵੇਂ ਹੀ ਛੱਡ ਦਿੱਤਾ ਜਾਵੇ, ਤਾਂ ਅੱਗੇ ਦੀ ਤਸਵੀਰ ਇਸ ਗੱਲ ਉੱਤੇ ਨਿਰਭਰ ਕਰਦੀ ਹੈ ਕਿ ਕਿਹੜਾ ਹਿੱਸਾ ਨੁਕਸਾਨਿਆ ਗਿਆ ਹੈ। ਕਿਨਾਰੇ ਦਾ ਪਾਟਣ ਸ਼ਾਂਤ ਹੋ ਸਕਦਾ ਹੈ। ਵਿਚਕਾਰਲਾ ਪਾਟਣ, ਜਾਂ ਅਜਿਹਾ ਪਾਟਣ ਜਿਸ ਵਿੱਚ ਲਿਗਾਮੈਂਟ ਵਾਲੀਆਂ ਰੱਸੀਆਂ ਢਿੱਲੀਆਂ ਹੋ ਕੇ ਉੱਖੜ ਗਈਆਂ ਹੋਣ, ਅਕਸਰ ਹਰ ਵਾਰ ਫੜਨ ਅਤੇ ਮਰੋੜਨ ਨਾਲ ਦੁਖਦਾ ਰਹਿੰਦਾ ਹੈ, ਕਿਉਂਕਿ ਉਹ ਟਿਸ਼ੂ ਅਜਿਹੀ ਥਾਂ ਹੁੰਦਾ ਹੈ ਜਿੱਥੇ ਸਰੀਰ ਲਈ ਉਸ ਦੀ ਮੁਰੰਮਤ ਕਰਨਾ ਔਖਾ ਹੁੰਦਾ ਹੈ। ਗੁੱਟ ਦੇ ਜਵਾਬ ਦੇਣ ਦਾ ਅਹਿਸਾਸ ਵੀ ਬਣਿਆ ਰਹਿ ਸਕਦਾ ਹੈ।
ਸਰਜਰੀ ਬਿਨਾਂ ਦਰਦ ਵਾਲੇ ਗੁੱਟ ਦਾ ਵਾਅਦਾ ਨਹੀਂ ਕਰਦੀ। ਲੰਬੇ ਸਮੇਂ ਤੋਂ ਚੱਲ ਰਹੇ ਗੁੱਟ ਦੇ ਦਰਦ ਲਈ ਦੂਰਬੀਨ ਵਾਲੀ ਸਰਜਰੀ ਕਰਵਾਉਣ ਵਾਲੇ ਲੋਕਾਂ ਵਿੱਚ ਇੱਕ ਸਾਲ ਬਾਅਦ ਔਸਤਨ ਲਗਭਗ 50% ਸੁਧਾਰ ਹੋਇਆ, ਅਤੇ ਉਸ ਵੇਲੇ ਜ਼ਿਆਦਾਤਰ ਨੂੰ ਅਜੇ ਵੀ ਕੁਝ ਦਰਦ ਅਤੇ ਅਕੜਾਅ ਸੀ। ਸਰਜਰੀ ਜੋ ਕੰਮ ਚੰਗੀ ਤਰ੍ਹਾਂ ਕਰਦੀ ਹੈ, ਉਹ ਹੈ ਠੀਕ-ਠੀਕ ਪੁਸ਼ਟੀ ਕਰਨਾ ਕਿ ਕੀ ਪਾਟਿਆ ਹੈ ਅਤੇ ਜਿਸ ਦੀ ਮੁਰੰਮਤ ਹੋ ਸਕਦੀ ਹੈ ਉਸ ਦੀ ਮੁਰੰਮਤ ਕਰਨਾ, ਜਿਸ ਦਾ ਮਤਲਬ ਆਮ ਤੌਰ 'ਤੇ ਘੱਟ ਦਰਦ ਅਤੇ ਅਜਿਹਾ ਗੁੱਟ ਹੁੰਦਾ ਹੈ ਜੋ ਫਿਰ ਤੋਂ ਰੋਜ਼ਾਨਾ ਦਾ ਭਾਰ ਸਹਿ ਸਕੇ।
ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾ ਦਿੰਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਆਪਣਾ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਡਾਕਟਰ ਨੂੰ ਕਦੋਂ ਮਿਲਣਾ ਚਾਹੀਦਾ ਹੈ
TFCC ਦੇ ਜ਼ਿਆਦਾਤਰ ਪਾਟਣ ਐਮਰਜੈਂਸੀ ਨਹੀਂ ਹੁੰਦੇ। ਕੁਝ ਹਾਲਾਤ ਐਮਰਜੈਂਸੀ ਹੁੰਦੇ ਹਨ। ਜੇ ਤੁਹਾਡਾ ਗੁੱਟ ਗਰਮ, ਲਾਲ, ਸੁੱਜਿਆ ਹੋਇਆ ਅਤੇ ਦਰਦ ਵਾਲਾ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ, ਕਿਉਂਕਿ ਇਹ ਲਾਗ (ਇਨਫੈਕਸ਼ਨ) ਵੱਲ ਇਸ਼ਾਰਾ ਕਰਦਾ ਹੈ ਜਿਸ ਦਾ ਉਸੇ ਦਿਨ ਇਲਾਜ ਹੋਣਾ ਚਾਹੀਦਾ ਹੈ। ਇਹੀ ਗੱਲ ਉਦੋਂ ਵੀ ਲਾਗੂ ਹੁੰਦੀ ਹੈ ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ ਜਾਂ ਹੱਥ ਫਿੱਕੇ, ਠੰਢੇ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੇ ਪੈ ਜਾਣ, ਜਾਂ ਜੇ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਾਅਦ ਅਚਾਨਕ ਹੱਥ ਵਿੱਚ ਮਹਿਸੂਸ ਕਰਨ ਦੀ ਸ਼ਕਤੀ ਜਾਂ ਹਿਲਜੁਲ ਚਲੀ ਜਾਵੇ। ਬਾਕੀ ਸਭ ਲਈ, ਸਮੇਂ ਦੀ ਗੱਲ ਤੇਜ਼ੀ ਦੀ ਨਹੀਂ, ਸਗੋਂ ਇਸ ਦੀ ਹੈ ਕਿ ਤਕਲੀਫ਼ ਕਿੰਨੀ ਦੇਰ ਤੋਂ ਟਿਕੀ ਹੋਈ ਹੈ। ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜੇ ਗੁੱਟ ਦੇ ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ ਦਾ ਦਰਦ 3 ਮਹੀਨਿਆਂ ਤੋਂ ਵੱਧ ਸਮੇਂ ਤੋਂ ਹੈ ਅਤੇ ਆਰਾਮ, ਸਪਲਿੰਟ ਜਾਂ ਹੈਂਡ ਥੈਰੇਪੀ ਨਾਲ ਨਹੀਂ ਘਟਿਆ। ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਲਦੀ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ ਜੇ ਹਥੇਲੀ ਨੂੰ ਉੱਪਰ ਅਤੇ ਹੇਠਾਂ ਵੱਲ ਘੁਮਾਉਣ ਵੇਲੇ ਗੁੱਟ ਡਾਵਾਂਡੋਲ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ, ਜਵਾਬ ਦੇ ਜਾਂਦਾ ਹੈ ਜਾਂ ਇਸ ਵਿੱਚ ਖੜਾਕ ਹੁੰਦਾ ਹੈ, ਕਿਉਂਕਿ ਇਸ ਤੋਂ ਲੱਗਦਾ ਹੈ ਕਿ TFCC ਦਾ ਲਿਗਾਮੈਂਟ ਵਾਲਾ ਹਿੱਸਾ ਪਾਟ ਕੇ ਢਿੱਲਾ ਹੋ ਗਿਆ ਹੈ। ਅਜਿਹਾ ਦਰਦ ਜੋ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਤੋਂ ਰੋਕਦਾ ਹੈ, ਰਾਤ ਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾਉਂਦਾ ਹੈ, ਜਾਂ ਜਿਸ ਵਿੱਚ ਸਕੈਨ ਸਾਫ਼ ਆਉਂਦੇ ਹਨ ਪਰ ਦੁਖਣ ਜਾਰੀ ਰਹਿੰਦੀ ਹੈ, ਉਸ ਲਈ ਵੀ ਮਾਹਰ ਦੀ ਰਾਇ ਲੈਣੀ ਬਣਦੀ ਹੈ, ਕਿਉਂਕਿ ਇਸ ਥਾਂ ਨੂੰ ਅਕਸਰ ਉਸ ਤੋਂ ਵੱਧ ਨੇੜਿਓਂ ਦੇਖਣ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ ਜਿੰਨਾ ਸਿਰਫ਼ ਸਕੈਨ ਦਿਖਾ ਸਕਦੇ ਹਨ।
ਵਿਸਥਾਰ ਵਿੱਚ
Advanced reading: the deeper science (optional)
ਇਹ ਹਿੱਸਾ ਤੁਹਾਡੇ ਆਪਣੇ ਇਲਾਜ ਦੇ ਫ਼ੈਸਲਿਆਂ ਲਈ ਲੋੜ ਤੋਂ ਵੱਧ ਵਿਸਥਾਰ ਵਿੱਚ ਜਾਂਦਾ ਹੈ। ਟ੍ਰਾਈਐਂਗੂਲਰ ਫ਼ਾਈਬ੍ਰੋਕਾਰਟੀਲੇਜ ਕੰਪਲੈਕਸ ਦੀ ਸੱਟ ਬਾਰੇ ਵਾਧੂ ਪੜ੍ਹਨਾ ਇਸ ਲਈ ਲਾਹੇਵੰਦ ਹੈ ਕਿਉਂਕਿ ਜਿਨ੍ਹਾਂ ਸਰਜੀਕਲ ਤਰੀਕਿਆਂ ਬਾਰੇ ਸਭ ਤੋਂ ਵੱਧ ਬਹਿਸ ਹੁੰਦੀ ਹੈ, ਉਹਨਾਂ ਦੇ ਨਤੀਜਿਆਂ ਵਿੱਚ ਕੋਈ ਸਪਸ਼ਟ ਫ਼ਰਕ ਸਾਹਮਣੇ ਨਹੀਂ ਆਇਆ, ਜਦਕਿ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਦੀ ਦੇਖਭਾਲ ਦਾ ਇੱਕ ਵੇਰਵਾ, ਜਿਸ ਵੱਲ ਬਹੁਤ ਘੱਟ ਧਿਆਨ ਦਿੱਤਾ ਜਾਂਦਾ ਹੈ, ਮਾਇਨੇ ਰੱਖਦਾ ਜਾਪਦਾ ਹੈ।
ਇਹ ਬਣਤਰ ਅਸਲ ਵਿੱਚ ਕੀ ਕਰਦੀ ਹੈ
TFCC ਕਾਰਟੀਲੇਜ ਦੀ ਇੱਕ ਡਿਸਕ ਹੈ ਜਿਸ ਦੇ ਆਲੇ-ਦੁਆਲੇ ਲਿਗਾਮੈਂਟਾਂ ਦਾ ਇੱਕ ਝੂਲੇ ਵਰਗਾ ਘੇਰਾ ਹੁੰਦਾ ਹੈ, ਅਤੇ ਇਹ ਅਲਨਾ (ulna, ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਵਿੱਚ ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ ਦੀ ਹੱਡੀ) ਦੇ ਸਿਰੇ ਅਤੇ ਕਾਰਪਲ ਹੱਡੀਆਂ (carpal bones, ਗੁੱਟ ਦੀਆਂ ਛੋਟੀਆਂ ਹੱਡੀਆਂ) ਦੇ ਵਿਚਕਾਰ ਹੁੰਦੀ ਹੈ। ਇਹ ਇੱਕੋ ਵੇਲੇ ਦੋ ਕੰਮ ਕਰਦੀ ਹੈ: ਇਹ ਗੁੱਟ ਦੇ ਅਲਨਰ ਪਾਸੇ ਤੋਂ ਲੰਘਣ ਵਾਲੇ ਭਾਰ ਨੂੰ ਗੱਦੀ ਵਾਂਗ ਸਹਾਰਦੀ ਹੈ, ਅਤੇ ਇਹ ਗੁੱਟ ਕੋਲ ਬਾਂਹ ਦੀਆਂ ਦੋ ਹੱਡੀਆਂ ਦੇ ਵਿਚਕਾਰਲੇ ਜੋੜ, ਯਾਨੀ ਡਿਸਟਲ ਰੇਡੀਓਅਲਨਰ ਜੋੜ (distal radioulnar joint), ਨੂੰ ਟਿਕਾਈ ਰੱਖਦੀ ਹੈ।
ਇਹ ਦੋਹਰੀ ਭੂਮਿਕਾ ਦੱਸਦੀ ਹੈ ਕਿ ਇੱਥੇ ਦੀਆਂ ਸੱਟਾਂ ਦੋ ਵੱਖਰੇ ਢੰਗਾਂ ਨਾਲ ਸਾਹਮਣੇ ਕਿਉਂ ਆਉਂਦੀਆਂ ਹਨ। ਜਿਹੜਾ ਪਾਟਣ ਮੁੱਖ ਤੌਰ 'ਤੇ ਡਿਸਕ ਨੂੰ ਪ੍ਰਭਾਵਿਤ ਕਰਦਾ ਹੈ, ਉਹ ਭਾਰ ਪੈਣ ਉੱਤੇ, ਕੁਰਸੀ ਤੋਂ ਧੱਕਾ ਲਾ ਕੇ ਉੱਠਣ ਵੇਲੇ, ਅਤੇ ਕੁਝ ਫੜਨ ਅਤੇ ਮਰੋੜਨ ਵੇਲੇ ਦਰਦ ਕਰਦਾ ਹੈ। ਜਿਹੜਾ ਪਾਟਣ ਡੂੰਘੇ ਰੇਸ਼ਿਆਂ ਨੂੰ ਅਲਨਾ ਉੱਤੇ ਉਹਨਾਂ ਦੀ ਜੁੜਨ ਵਾਲੀ ਥਾਂ, ਯਾਨੀ ਫ਼ੋਵੀਅਲ (foveal) ਜੁੜਨ-ਥਾਂ, ਤੋਂ ਵੱਖ ਕਰ ਦਿੰਦਾ ਹੈ, ਉਹ ਅਸਥਿਰਤਾ ਪੈਦਾ ਕਰਦਾ ਹੈ, ਜਿਸ ਵਿੱਚ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਨੂੰ ਘੁਮਾਉਣ ਵੇਲੇ ਲੱਗਦਾ ਹੈ ਕਿ ਗੁੱਟ ਜਵਾਬ ਦੇ ਰਿਹਾ ਹੈ ਜਾਂ ਉਸ ਵਿੱਚ ਖੜਾਕ ਹੁੰਦਾ ਹੈ। ਦੂਜੀ ਕਿਸਮ ਜ਼ਿਆਦਾ ਮਾਇਨੇ ਰੱਖਦੀ ਹੈ, ਕਿਉਂਕਿ ਲਿਗਾਮੈਂਟ ਵਾਲਾ ਇਹ ਜੁੜਾਅ ਹੀ ਜੋੜ ਨੂੰ ਇਕੱਠਾ ਜਕੜ ਕੇ ਰੱਖਦਾ ਹੈ।
MRI ਸਹੀ ਹੈ, ਪਰ ਇੱਕ ਸ਼ਰਤ ਨਾਲ ਜੋ ਜਾਣਨ ਯੋਗ ਹੈ
ਸਮੱਸਿਆ ਦੀ ਪਛਾਣ ਕਾਫ਼ੀ ਹੱਦ ਤੱਕ ਇਮੇਜਿੰਗ (ਸਕੈਨ) ਉੱਤੇ ਨਿਰਭਰ ਕਰਦੀ ਹੈ। 1,298 ਮਰੀਜ਼ਾਂ ਵਿੱਚ MRI ਦੀ ਕੁੱਲ ਸ਼ੁੱਧਤਾ ਤਸੱਲੀਬਖ਼ਸ਼ ਸੀ, ਅਤੇ ਕਿਨਾਰੇ ਵਾਲੇ (peripheral) ਪਾਟਣਾਂ ਲਈ ਇਕੱਠੇ ਕੀਤੇ ਅੰਕੜਿਆਂ ਵਿੱਚ ਸ਼ੁੱਧਤਾ ਮੁਕਾਬਲਤਨ ਉੱਚੀ ਸੀ, ਅਤੇ ਢੁਕਵੀਆਂ ਸੈਟਿੰਗਾਂ ਨਾਲ ਕੀਤੇ MRI ਨੂੰ ਪਾਟਣ ਦੀਆਂ ਵੱਖ-ਵੱਖ ਕਿਸਮਾਂ ਦੀ ਪਛਾਣ ਲਈ ਇੱਕ ਆਦਰਸ਼ ਤਰੀਕਾ ਦੱਸਿਆ ਗਿਆ [1]।
ਸ਼ਰਤ "ਕਿਨਾਰੇ ਵਾਲੇ" ਸ਼ਬਦ ਵਿੱਚ ਹੈ। MRI ਕੰਪਲੈਕਸ ਦੇ ਬਾਹਰਲੇ ਹਿੱਸੇ ਵਿੱਚ ਸਭ ਤੋਂ ਵਧੀਆ ਕੰਮ ਕਰਦਾ ਹੈ, ਜਿੱਥੇ ਖ਼ੂਨ ਦੀ ਸਪਲਾਈ ਬਿਹਤਰ ਹੈ, ਅਤੇ ਮੁਰੰਮਤ ਹੋ ਸਕਣ ਵਾਲੇ ਪਾਟਣ ਉੱਥੇ ਹੀ ਹੁੰਦੇ ਹਨ। ਵਿਚਕਾਰਲੇ ਅਤੇ ਘਿਸਾਈ ਨਾਲ ਹੋਏ ਪਾਟਣਾਂ ਨੂੰ, ਅਤੇ ਫ਼ੋਵੀਅਲ ਜੁੜਾਅ ਦੀ ਠੀਕ-ਠੀਕ ਹਾਲਤ ਨੂੰ, ਪਰਖਣਾ ਜ਼ਿਆਦਾ ਔਖਾ ਹੈ, ਇਸੇ ਲਈ ਸਕੈਨ ਦੇ ਨਾਲ-ਨਾਲ ਜਾਂਚ ਦੇ ਨਤੀਜਿਆਂ ਅਤੇ ਕਈ ਵਾਰ ਦੂਰਬੀਨ ਵਾਲੀ ਜਾਂਚ (arthroscopy) ਦਾ ਵੀ ਅਹਿਮ ਵਜ਼ਨ ਹੁੰਦਾ ਹੈ।
ਤਰੀਕਿਆਂ ਦੀ ਤੁਲਨਾ ਵਿੱਚ ਕੋਈ ਸਪਸ਼ਟ ਫ਼ਰਕ ਨਹੀਂ ਨਿਕਲਦਾ
ਓਪਰੇਸ਼ਨ ਬਾਰੇ ਦੋ ਬਹਿਸਾਂ ਵਾਰ-ਵਾਰ ਉੱਠਦੀਆਂ ਹਨ, ਅਤੇ ਦੋਵਾਂ ਵਿੱਚੋਂ ਕੋਈ ਵੀ ਨਿੱਬੜੀ ਨਹੀਂ।
ਆਮ ਮਿਲਣ ਵਾਲੇ ਕਿਨਾਰੇ ਵਾਲੇ, ਅਲਨਰ ਪਾਸੇ ਦੇ ਪਾਟਣ ਲਈ, 240 ਮਰੀਜ਼ਾਂ ਦੀ ਇੱਕ ਸਿਸਟੇਮੈਟਿਕ ਰਿਵਿਊ (systematic review, ਕਈ ਅਧਿਐਨਾਂ ਦੀ ਵਿਉਂਤਬੱਧ ਸਮੀਖਿਆ) ਵਿੱਚ ਦੂਰਬੀਨ ਵਾਲੀ ਬਨਾਮ ਖੁੱਲ੍ਹੀ ਸਰਜਰੀ ਨਾਲ ਮੁਰੰਮਤ ਬਾਰੇ ਪੱਕੇ ਸਿੱਟੇ ਕੱਢਣ ਲਈ ਉੱਚ-ਗੁਣਵੱਤਾ ਵਾਲੇ ਸਬੂਤਾਂ ਦੀ ਘਾਟ ਮਿਲੀ, ਅਤੇ ਅਜਿਹਾ ਕੋਈ ਵਿਗਿਆਨਕ ਸਬੂਤ ਨਹੀਂ ਮਿਲਿਆ ਜੋ ਇੱਕ ਤਰੀਕੇ ਨੂੰ ਦੂਜੇ ਨਾਲੋਂ ਬਿਹਤਰ ਦਰਸਾਏ [2]।
ਫ਼ੋਵੀਅਲ ਮੁਰੰਮਤ ਲਈ, 904 ਮਰੀਜ਼ਾਂ ਵਿੱਚ ਸਿਊਚਰ ਐਂਕਰ (suture anchor, ਹੱਡੀ ਵਿੱਚ ਲਗਾਇਆ ਜਾਣ ਵਾਲਾ ਛੋਟਾ ਕਿੱਲ, ਜਿਸ ਨਾਲ ਟਾਂਕੇ ਬੰਨ੍ਹ ਕੇ ਟਿਸ਼ੂ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਿਆ ਜਾਂਦਾ ਹੈ) ਦੀ ਤੁਲਨਾ ਹੱਡੀ ਵਿੱਚੋਂ ਆਰ-ਪਾਰ ਲੰਘਾਏ ਟਾਂਕਿਆਂ (transosseous suture) ਨਾਲ ਕੀਤੀ ਗਈ, ਅਤੇ ਦੋਵਾਂ ਨਾਲ ਕੰਮਕਾਜ ਦੇ ਨਤੀਜਿਆਂ, ਦਰਦ ਅਤੇ ਪਕੜ ਦੀ ਤਾਕਤ ਵਿੱਚ ਸੁਧਾਰ ਹੋਇਆ ਅਤੇ ਦੁਬਾਰਾ ਓਪਰੇਸ਼ਨ ਦੀ ਦਰ ਘੱਟ ਰਹੀ, ਹਾਲਾਂਕਿ ਹਿਲਜੁਲ ਦੀ ਹੱਦ (range of motion) ਦੀ ਤੁਲਨਾ ਅਨਿਰਣਾਇਕ ਰਹੀ [3]।
ਇੱਕਸਾਰ ਸੁਨੇਹਾ ਇਹ ਹੈ ਕਿ ਮੁਰੰਮਤ ਨਾਲ ਜੁੜਾਅ ਮੁੜ ਬਹਾਲ ਹੋਣਾ ਚਾਹੀਦਾ ਹੈ; ਇਸ ਲਈ ਵਰਤੇ ਜਾਂਦੇ ਸਾਜ਼ੋ-ਸਾਮਾਨ ਨਾਲ ਨਤੀਜਾ ਬਦਲਦਾ ਸਾਬਤ ਨਹੀਂ ਹੋਇਆ।
ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਦਾ ਉਹ ਵੇਰਵਾ ਜੋ ਮਾਇਨੇ ਰੱਖਦਾ ਜਾਪਦਾ ਹੈ
ਇੱਥੇ ਸਬੂਤ ਵੱਧ ਸਪਸ਼ਟ ਫ਼ਰਕ ਦਿਖਾਉਂਦੇ ਹਨ, ਅਤੇ ਇਹ ਅਮਲੀ ਤੌਰ 'ਤੇ ਕੰਮ ਦੇ ਹਨ। 288 ਮਰੀਜ਼ਾਂ ਵਿੱਚ ਫ਼ੋਵੀਅਲ TFCC ਮੁਰੰਮਤ ਤੋਂ ਬਾਅਦ ਬਾਂਹ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਦੇ ਵੱਖ-ਵੱਖ ਢੰਗਾਂ ਦੀ ਤੁਲਨਾ ਵਿੱਚ, ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਸਥਿਰ ਰੱਖਣ ਵਿੱਚ ਕੂਹਣੀ ਦੀ ਹਿਲਜੁਲ ਰੋਕਣ ਨਾਲੋਂ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦਾ ਘੁੰਮਣਾ ਰੋਕਣਾ ਜ਼ਿਆਦਾ ਲਾਹੇਵੰਦ ਹੋ ਸਕਦਾ ਹੈ, ਅਤੇ ਕੂਹਣੀ ਨੂੰ ਮੋੜਨ ਅਤੇ ਸਿੱਧਾ ਕਰਨ ਉੱਤੇ ਲਾਈ ਵਾਧੂ ਰੋਕ ਨੇ ਕੋਈ ਇੱਕਸਾਰ ਫ਼ਾਇਦਾ ਨਹੀਂ ਦਿਖਾਇਆ [4]।
ਇਹ ਸਿੱਧਾ ਸਰੀਰ ਦੀ ਬਣਤਰ ਤੋਂ ਨਿਕਲਦਾ ਹੈ। ਮੁਰੰਮਤ ਕੀਤੇ ਹਿੱਸੇ ਉੱਤੇ ਭਾਰ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦੇ ਘੁੰਮਣ ਨਾਲ ਪੈਂਦਾ ਹੈ, ਕੂਹਣੀ ਮੋੜਨ ਨਾਲ ਨਹੀਂ, ਇਸ ਲਈ ਸਪਲਿੰਟ ਨੂੰ ਹਥੇਲੀ ਦੇ ਉੱਪਰ ਵੱਲ ਅਤੇ ਹੇਠਾਂ ਵੱਲ ਘੁੰਮਣ ਨੂੰ ਕਾਬੂ ਕਰਨਾ ਚਾਹੀਦਾ ਹੈ। ਇਸ ਨੂੰ ਅਸਿੱਧੇ ਢੰਗ ਨਾਲ ਲਾਗੂ ਕਰਨ ਲਈ ਅਕਸਰ ਕੂਹਣੀ ਤੋਂ ਉੱਪਰ ਤੱਕ ਦਾ ਪਲੱਸਤਰ (cast) ਵਰਤਿਆ ਜਾਂਦਾ ਹੈ, ਜੋ ਕੂਹਣੀ ਨੂੰ ਘੁੰਮਣ ਤੋਂ ਰੋਕਦਾ ਹੈ, ਅਤੇ ਇਹ ਸਬੂਤ ਦੱਸਦੇ ਹਨ ਕਿ ਕੂਹਣੀ ਵਾਲਾ ਹਿੱਸਾ ਉਹ ਨਹੀਂ ਜੋ ਅਸਲ ਕੰਮ ਕਰਦਾ ਹੈ। ਮਰੀਜ਼ ਲਈ, ਕੂਹਣੀ ਨੂੰ ਖੁੱਲ੍ਹਾ ਛੱਡਣ ਵਾਲੀ ਬ੍ਰੇਸ (ਸਹਾਰਾ ਦੇਣ ਵਾਲਾ ਪਟਾ) ਵਿੱਚ ਛੇ ਹਫ਼ਤੇ ਬਿਤਾਉਣਾ, ਕੂਹਣੀ ਤੋਂ ਉੱਪਰ ਤੱਕ ਦੇ ਪਲੱਸਤਰ ਵਿੱਚ ਛੇ ਹਫ਼ਤੇ ਬਿਤਾਉਣ ਨਾਲੋਂ ਕਾਫ਼ੀ ਵੱਖਰਾ ਤਜਰਬਾ ਹੈ।
ਹਵਾਲੇ
[1] Wang ZX, Chen SL, Wang QQ, Liu B, Zhu J, Shen J. The performance of magnetic resonance imaging in the detection of triangular fibrocartilage complex injury: a meta-analysis. J Hand Surg Eur Vol. 2015;40(5):477-84. https://doi.org/10.1177/1753193414567425
[2] Robba V, Fowler A, Karantana A, Grindlay D, Lindau T. Open versus arthroscopic repair of 1B ulnar-sided triangular fibrocartilage complex tears: a systematic review. Hand (N Y). 2019;15(4):456-64. https://doi.org/10.1177/1558944718815244
[3] Ma H, Wang J, Yang C. Effectiveness of suture anchor and transosseous suture technique in arthroscopic triangular fibrocartilage complex foveal repair: a systematic review and meta-analysis. J Orthop Surg Res. 2024;19(1). https://doi.org/10.1186/s13018-024-04530-4
[4] Lee J, Lee T, Lee S, Lim H, Chang E, Park MO, et al. Postoperative immobilization after foveal triangular fibrocartilage complex repair: a systematic review and meta-analysis. J Hand Surg Am. 2026;51(5):512.e1-512.e11. https://doi.org/10.1016/j.jhsa.2026.01.029
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Diagnosis and Assessment
- Careful history and physical examination are required to determine whether a TFCC tear is symptomatic [6].
- It is important to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary [6].
- Acute TFCC injuries require differentiation between those causing distal radioulnar joint instability and those that do not [7].
- TFCC injury should be considered with all distal radial fractures [16].
- 1B TFCC injury is most common in patients with distal radius fractures and concomitant TFCC injury [5].
Natural History and Prognosis
- About 40% of patients sustaining a TFCC tear without distal radioulnar joint instability still had pain and disability at 1 year [8].
Surgical Outcomes
- Surgical treatment of TFCC tears and concomitant pathology in the pediatric and adolescent population results in decreased pain, improved motion and stability, and excellent functional outcomes in the majority of patients [3].
- In a series of pediatric and adolescent patients, there was marked improvement in pain, function, and range of motion in patients with TFCC tears and coexisting pathology [1].
- Arthroscopic treatment of TFCC lesions leads to satisfactory functional outcomes [4].
- Current evidence demonstrates that TFCC repair achieves good clinical outcomes, with low complication rates [23].
- There was no statistical difference in clinical outcomes after open versus arthroscopic TFCC repair [27].
- Arthroscopic debridement alone appears to be an effective and safe initial treatment for patients with traumatic central TFCC tears [32].
- With appropriate indications and patient selection, arthroscopic foveal repair of the TFCC may restore distal radioulnar joint stability and provide satisfactory results without significant complications [68].
- In high-demand athletes, arthroscopic repair of TFCC tears is becoming the treatment of choice to obtain optimum physiologic strength, complete range of motion, stability, and the shortest possible postoperative period [44].
- Open surgical TFCC repair is a safe and reliable therapeutic procedure in children and adolescent populations [56].
- TFCC capsular reattachment could be performed with an arthroscopically assisted technique, providing good long-term results [19].
Surgical Techniques and Variability
- Arthroscopic-assisted repair techniques have revolutionized surgical management, providing detailed visualization and facilitating the repair of TFCC injuries and associated pathologies with minimally invasive techniques [9].
- TFCC repair varies substantially from surgeon-to-surgeon, suggesting repairs are discretionary and preference sensitive [15].
- A systematic review demonstrates a current lack of high-quality evidence required to draw firm conclusions on the merits of arthroscopic versus open repair of 1B TFCC tears [17].
- A systematic review did not demonstrate strong evidence regarding the association between ulnar variance and outcomes after TFCC repair [31].
Anatomy & Pathophysiology
Anatomical Structures and Blood Supply
- The TFCC is a group of interrelated anatomic structures that are integral to stability of the distal radioulnar joint (DRUJ) [35].
- The TFCC acts in forearm rotation as the primary stabilizer of the DRUJ while also providing a smooth articular surface and partially absorbing the axial load from the radiocarpal joint [63].
- The central 80–85% of the articular disk is avascular, resulting in minimal healing potential for tears in this area [55].
- The outer 10% to 40% of the articular disk is well perfused, suggesting a healing potential for injured areas upon repair [49].
- The ulnar attachment of the TFCC is a three-dimensional complex consisting of proximal radioulnar ligaments, a distal hammock structure (fibrocartilage disk, meniscus homologue, and ulnocarpal ligaments), and a functional ulnar collateral ligament (UCL) [49].
- The distal hammock structure and the UCL constitute the distal component of the TFCC (dc-TFCC), while the radioulnar ligament represents the proximal component (pc-TFCC) [49].
- The palmar and dorsal radioulnar ligaments span from the dorsal and volar corners of the distal radius to a broad area of the fovea at the base of the ulnar styloid [49].
- The deep foveal components of the radioulnar ligaments are considered the true stabilizers of the DRUJ [49].
- The triangular fibrocartilage is less stiff in neutral forearm rotation, and its palmar and dorsal parts have material properties similar to those of the radiocarpal ligaments [88].
Classification and Pathology
- Palmer classification categorizes TFCC tears into traumatic (Class 1) or degenerative (Class 2) based on mechanism and location [20, 21, 49, 55].
- Class 1A injuries are central perforations or tears of the articular disk [20, 21, 55].
- Class 1B injuries are ulnar avulsions of the TFCC with or without an ulnar styloid fracture [20, 21, 55].
- Class 1C injuries are distal avulsions involving the origins of the ulnolunate and ulnotriquetral ligaments [20, 21].
- Class 1D injuries are radial avulsions involving the dorsal and/or volar radioulnar ligaments [20, 21].
- Class 2 injuries represent degeneration of the central portion of the TFCC and are associated with ulnocarpal impaction syndrome [55].
- Class 2A involves TFCC wear or thinning, progressing through Class 2E which includes ulnocarpal and DRUJ arthritis [20, 21].
- A foveal tear is a partial tear of the ulnar insertion where the foveal insertion is disrupted but some styloid insertion remains intact [132].
- The foveal insertion has a greater effect on DRUJ stability than the styloid insertion due to its closer relationship to the rotational axis of the forearm [132].
- Degenerative TFCC tears occur as a result of chronic excessive loading through the ulnocarpal joint along with natural tissue degeneration [126].
- Cadaveric examinations found TFCC perforations and chondromalacia of the ulnar head, lunate, and triquetrum in 30% to 70% of specimens [126].
Injury Mechanisms and Clinical Presentation
- Traumatic TFCC injuries may occur from falls on an outstretched hand or hyper-rotational injuries to the forearm [35].
- Repetitive forceful movement of the wrist from supination to pronation can cause overload stress affecting components of the TFCC [35].
- Injuries to the TFCC typically occur with extension and pronation of the axially loaded wrist [49].
- The most common mechanism of injury is a fall on an outstretched hand [49].
- Traumatic radial-sided tears of the TFCC typically occur during acute rotational injuries involving combined axial load with a distraction injury to the ulnar border of the forearm [126].
- Patients with peripheral TFCC tears complain of deep diffuse pain across the ulnar side of the wrist, weakness when gripping, and a clicking sensation with forearm rotation [49].
- Pain in peripheral TFCC tears is accentuated by passive pronation and supination of the wrist [49].
- A dorsally prominent ulnar head in relation to the radius can be seen in foveal detachments [49].
- Ballottement of the DRUJ reveals increased translation of the joint associated with pain in peripheral tears [49].
- A class 1A tear typically manifests as ulnar-sided wrist pain aggravated by power grip, especially with ulnar deviation or forearm rotation [43].
- Class 1A tears are confined to the disc, located 2 to 3 mm ulnar to its radial attachment, and oriented volar to dorsal [43].
- Class 1B injuries may present with point tenderness volar to the ulnar styloid, coinciding anatomically with the fovea (fovea sign) [60].
- A fracture through the base of the ulnar styloid that disrupts both deep and superficial limbs of the TFCC is more predictive of DRUJ instability than fractures through the shaft or tip [60].
- Deep TFCC fiber tears may contribute to decreased wrist rotational positioning sense and have biomechanical importance in DRUJ stability [50].
Biomechanical Effects of Deformity
- Radial shortening causes the greatest disturbance in DRUJ kinematics and the most distortion of the triangular fibrocartilage [74].
- Decreased radial inclination and dorsal angulation cause intermediate changes in DRUJ kinematics, while dorsal displacement produces minimal changes [74].
- Radial deformity does not produce DRUJ dislocation but provides biomechanical evidence of a relationship between radial malunion and persistent symptoms [74].
- Changes in ulnar variance due to ulnar lengthening or radial shortening dramatically alter force transmission through the distal ulna [90].
Classification
Palmer Classification System
- The Palmer classification divides TFCC injuries into traumatic (Class 1) and degenerative (Class 2) categories [20].
- Subtypes within the Palmer classification are based on the specific location of the tear within the TFCC [20].
- The class and location of a TFCC tear have important implications for treatment [20].
- Palmer created a classification system that divides TFCC injuries into Type I (traumatic) or Type II (degenerative) lesions [53].
- Traumatic injuries are categorized based on the location of the pathology [55].
- Degenerative tears represent the spectrum of lesions found with ulnocarpal impaction syndrome [55].
Class 1 (Traumatic) Subtypes
- Class 1A injuries are characterized by central perforation or tear of the TFCC [20].
- Class 1A injuries are characterized by central articular disc perforation [53].
- Class 1B injuries are characterized by ulnar avulsion with or without ulnar styloid fracture [20].
- Class 1B injuries are characterized by ulnar-sided avulsion with or without ulnar styloid fracture [53].
- Class 1C injuries are characterized by distal avulsion involving the origins of the ulnolunate and ulnotriquetral ligaments [20].
- Class 1C injuries are characterized by distal avulsion with disruption from distal ulnocarpal ligaments [53].
- Class 1D injuries are characterized by radial avulsion involving the dorsal and/or volar radioulnar ligaments [20].
- Class 1D injuries are characterized by radial-sided avulsion with or without sigmoid notch fracture [53].
- Class 1D injuries involve avulsion of the articular disk and the dorsal and palmar radioulnar ligaments [55].
- Class 1D injuries render the distal radioulnar joint (DRUJ) unstable [55].
- Type IA lesions are perforations of the thin, avascular articular disc and represent the most common type of traumatic tear [53].
- Traumatic tears of the articular disk commonly occur along the origin of the articular disk from the radius, which are class 1A injuries [55].
- Class 1B lesions describe traumatic avulsion of the TFCC insertion onto the ulna [55].
- Class 1B injuries are seen with or without fractures of the ulnar styloid [55].
- Avulsions of the TFCC ulnar attachment often create DRUJ instability [55].
- Class 1C lesions involve disruption of the TFCC distally through the ulnolunate and ulnotriquetral ligaments [55].
- The area of the TFCC involved in Class 1C lesions is well vascularized, giving these lesions greater potential to heal [55].
- Class 1D injuries are less common and involve radial avulsion of the entire TFCC from its attachment to the radius at the sigmoid notch [55].
Class 2 (Degenerative) Subtypes
- Class 2A is characterized by TFCC wear or thinning [20].
- Class 2B is characterized by TFCC wear plus lunate and/or ulnar chondromalacia [20].
- Class 2C is characterized by TFCC perforation plus lunate and/or ulnar chondromalacia [20].
- Class 2D is characterized by TFCC perforation, lunate and/or ulnar chondromalacia, and lunotriquetral ligament disruption [20].
- Class 2E is characterized by TFCC perforation, lunate and/or ulnar chondromalacia, lunotriquetral ligament disruption, and ulnocarpal and DRUJ arthritis [20].
- Type IIA is characterized by TFCC wear [53].
- Type IIB is characterized by TFCC wear with lunate and/or ulnar chondromalacia [53].
- Type IIC is characterized by TFCC perforation with lunate and/or ulnar chondromalacia [53].
- Type IID is characterized by TFCC perforation with lunate and/or ulnar chondromalacia and lunotriquetral ligament perforation [53].
- Type IIE is characterized by TFCC perforation with lunate and/or ulnar chondromalacia, lunotriquetral ligament perforation, and ulnocarpal arthritis [53].
Alternative Classifications
- Atzei proposed a treatment-oriented classification for Palmer 1B type peripheral tears [109].
- The Atzei classification distinguishes repairable lesions of the single distal component of the TFCC (Class 1) from those of the proximal component, which includes foveal insertions of DRUJ ligaments [121].
- Atzei Class 2 represents a complete tear pattern involving both the distal and proximal components of the TFCC [121].
- Atzei Class 3 represents an isolated tear of the proximal component of the TFCC [121].
- Atzei Class 4 represents nonrepairable lesions [121].
- Atzei Class 5 represents tears associated with DRUJ arthritis [121].
- The Atzei classification highlights clinical and arthroscopic criteria to categorize five classes of TFCC peripheral tears on a treatment-oriented system [47].
- In the pediatric population, traumatic (Class 1) injuries represent the vast majority of TFCC tears, while degenerative (Class 2) tears are far less common [24].
- There is an apparent increased prevalence of Palmer 1B tears in pediatric patients compared with adults [24].
- Palmer 1B tears represent the most common variety of TFCC injuries in children and adolescents [24].
- Tears of the radial attachment (Palmer 1D) represent the second most common type of TFCC injuries in children and adolescents [24].
- The Melone classification system does not predict the presence of TFCC lesions [102].
- Frykman Type VI and VIII fractures show a significantly higher incidence of TFCC tears [102].
Diagnostic Correlates for Classification
- Arthroscopy is the gold standard for detection of TFCC tears [20].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting the central portion with a small probe [20].
- The arthroscopic hook test can be used to demonstrate peripheral detachment of the TFCC [20].
- The arthroscopic suction test can show laxity of the TFCC when peripherally scarred in or foveal detachment when the DRUJ is clinically unstable [20].
- Classification of central triangular fibrocartilage complex lesions as traumatic or degenerative depends on the information provided upon viewing the lesion at arthroscopy [28].
- In more detailed classification of TFCC injuries, such as pc-TFCC tears classified by Atzei's classification, the diagnostic accuracy of MRI remains lower compared to wrist arthroscopy [36].
- Diagnostic accuracy for TFCC injuries was highest for central TFCC injuries [39].
- The presence of ulnar styloid fracture associated with distal radius fracture predicted the presence of frequently occurring traumatic triangular fibrocartilage complex injury and TFCC 1B injury [14].
Clinical Presentation
General Presentation and Diagnosis
- TFCC tears are a common cause of ulnar-sided wrist pain in athletes [10].
- Ulnar-sided wrist pain in athletes can be caused by injury to the TFCC [35].
- Wrist arthroscopy is considered the benchmark for the diagnosis and management of TFCC injuries [110].
- Wrist arthroscopy allows the direct evaluation of the TFCC and surrounding ligaments [110].
- Arthroscopy is effective in obtaining both correct diagnosis and treatment of peripheral TFCC tear [33].
- The more experienced observer had more sensitive, specific, and accurate interpretations than the less experienced observer in predicting the presence and location of a TFCC tear [13].
- There is a high rate of abnormal TFCC identified on MRI in patients without corresponding ulnar-sided wrist symptoms [34].
- The presence of an abnormal TFCC on MRI may be of questionable clinical meaning, because there is a high incidence of TFCC abnormalities in asymptomatic subjects, particularly those over the age of 50 [62].
- MR arthrography is more sensitive and specific method in terms of the diagnosis of TFCC tears compared to conventional wrist MRI [54].
- Diagnostic accuracy was highest for central TFCC injuries [39].
- The technique is best used in young patients with indeterminate physical examinations and normal radiography in whom intrinsic ligament or TFCC tears are suspected to assist decision making regarding the performance of arthroscopy [64].
Pediatric and Adolescent Presentation
- In the pediatric population, traumatic (class 1) injuries represent the vast majority of TFCC tears [24].
- Degenerative (class 2) tears of the TFCC are far less common in the pediatric population [24].
- Palmer 1B tears from the ulnar attachment with or without associated ulnar styloid fractures represent the most common variety of TFCC injuries in children and adolescents [24].
- Tears of the radial attachment (Palmer 1D tears) represent the second most common type of TFCC injuries in children and adolescents [24].
- If radial-sided tears (Palmer 1D) are mistaken for a central traumatic tear (Palmer 1A), simple debridement alone may result in persistent pain, instability, and functional limitations [24].
Association with Distal Radius Fractures
- 1B TFCC injury is most common in patients with distal radius fracture and concomitant TFCC injury [5].
- Disability outcomes were worse in patients with distal radial fracture where TFCC was injured [41].
Natural History and Chronic Findings
- About 40% of patients sustaining TFCC tear without DRUJ instability still had pain and disability at 1 year [8].
- Nonsurgical treatment is moderately successful for treating patients with TFCC tears without DRUJ instability [22].
- A higher frequency of accompanying ECU tendon and/or DRUJ disorders was found in patients with chronic TFCC tears as compared to the control group [40].
- Deep TFCC fiber tear may contribute to decreased wrist rotational positioning sense and may have biomechanical importance in distal radioulnar joint stability [50].
Investigations
Clinical Examination and Provocative Tests
- Careful history and physical examination are required to determine whether a TFCC tear is symptomatic and to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary [6].
- A positive ulnar fovea sign was reported to be 90% sensitive and 88% specific in detecting a split tear of the ulnotriquetral ligament [70].
- Load-bearing RaUl measurement is a simple method to diagnose an unstable distal radioulnar joint in patients with TFCC injury [59].
Magnetic Resonance Imaging (MRI)
- MRI interpretation of TFCC lesions is more sensitive, specific, and accurate when performed by a more experienced observer compared to a less experienced observer [13].
- The sensitivity, specificity, and accuracy of 3.0T wrist MRI for the TFCC is consistently higher compared with those of 1.5T wrist MRI [119].
- High-resolution magnetic resonance imaging permits accurate depiction and localization of tears of the triangular fibrocartilage complex [133].
- High-resolution MRI using a microscopy surface coil allowed assessment of each TFCC component and showed a higher accuracy for diagnosing injuries to the radial attachment and the disc of the TFC compared with previous studies [113].
- MRI is controversial, but newer innovations suggest value in detection and localization of TFCC pathology [20].
MR Arthrography
- MR arthrography is a more sensitive and specific method in terms of the diagnosis of TFCC tears compared to conventional wrist MRI [54].
Computed Tomography (CT) and Arthrography
- CT scan is effective for evaluating DRUJ instability [135].
- Since ulnar-sided contrast leakage is more common in patients with peripheral TFCC injuries, distinction between an atypical configuration of the prestyloid recess and actual leakage is important in CT arthrography of the wrist [42].
- Radial multiplanar reconstructions are important for the assessment of triangular fibrocartilage complex injury in CT arthrography of the wrist [61].
- Single-injection wrist arthrography is superior to routine MRI for the detection of full-thickness triangular fibrocartilage tears [136].
Arthroscopy
Association with Distal Radius Fractures
Treatment
Non-Operative Management
- All Class 1 (acute traumatic) TFCC injuries are initially managed with immobilization and NSAIDs [20].
- Initial treatment for Class 1B injuries involves protective above-elbow immobilization for 4 to 6 weeks toward the forearm in neutral rotation [60].
- Nonoperative management of traumatic TFCC injuries with above-elbow immobilization is a viable treatment method, particularly in patients without DRUJ subluxation [123].
- Moritomo and colleagues reported that 46% of patients with avulsion of the TFCC from the fovea were pain-free after conservative treatment [49].
- Non-operative treatment is the first line of treatment for most DRUJ problems, with exceptions including some unstable distal ulnar fractures and early marked painful block to forearm rotation [125].
- In the year of natural recovery following a distal radius fracture, management options for ongoing ulnar-sided wrist pain include activity modification, splints or straps, and oral analgesics, typically NSAIDs [125].
- Steroid injections are given to treat ongoing wrist pain after distal radius fractures, with 90% of patients reporting some improvement in symptoms when reviewed at 6–8 weeks after injection [125].
- Patients with persistent pain after distal radius fractures should be supported and encouraged to wait for spontaneous improvement in symptoms over at least 1 year from injury, assuming there is no gross bone malalignment [125].
- There is no good evidence that early treatment improves the outcome of DRUJ instability, so it is worth waiting for a prolonged period, typically at least 12 months, before addressing it [125].
- The mean DASH scores showed no difference across all groups, calling into question the clinical need to pursue operative treatment via K-wire stabilization or TFCC repair over conservative treatment via cast immobilization for acute DRUJ instability following distal radius fracture [129].
Surgical Indications and Decision Making
- Careful history and physical examination are required to determine whether a TFCC tear is symptomatic, and it is important to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary [6].
- Acute TFCC injuries require differentiation between those causing distal radioulnar joint instability and those that do not, with management ranging from nonsurgical immobilization to arthroscopic or open surgical repair depending on the specific injury pattern and stability [7].
- Surgical treatment is indicated for Class 1 TFCC injuries with failure of nonoperative treatment [20].
- Indications for surgical intervention include specific ulnar-sided wrist pain not relieved by conservative management for 3 months, especially in the presence of symptomatic instability of the DRUJ [49].
- Surgery is indicated for Class 1B injuries with persistent symptoms or evidence of DRUJ instability [60].
- Arthroscopy remains the gold standard in diagnosing and assessing the type and extent of the TFCC tear [49].
- A recent study in magnetic resonance arthrography performed with wrist traction applied demonstrated high accuracy of TFCC tear detection of 98% [49].
- Some studies have demonstrated that MRI missed over half of TFCC tears, as later confirmed on wrist arthroscopy [122].
- An MRI finding showing greater than 10% subluxation of the DRUJ on axial MRI has been shown to have increased sensitivity and specificity for TFCC tear and DRUJ instability [122].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting central portion with a small probe [20].
Arthroscopic Debridement (Class 1A and Degenerative)
- Class 1A (central) TFCC tears are inherently stable and treated with débridement if persistently symptomatic because this area of the TFCC is devoid of vascularity and unable to heal [20].
- A 2-mm peripheral rim should be maintained during debridement of Class 1A tears [20].
- Indications for arthroscopic TFCC debridement include acute traumatic Palmer type 1A TFCC, degenerative central tear of TFCC with ulnar neutral or negative variance, and failure to respond to conservative treatment with splint and medication for more than 3 months [26].
- Resection of unstable flaps is sufficient when the remaining margins are smooth and stable, and the peripheral 2 to 3 mm must be preserved to protect the radioulnar ligaments [26].
- A thorough synovectomy of the ulnocarpal joint and DRUJ is essential for early pain control as the pain mainly originates from the inflamed synovium over the capsule which is richly innervated [26].
- Excessive use of RF energy can lead to thermal chondral damage [26].
- Overaggressive debridement can cause DRUJ instability [26].
- Failure to diagnose ulnar impaction syndrome may lead to continued pain [26].
- No restriction of wrist and forearm motion is required postoperatively after arthroscopic TFCC debridement [26].
- Although clinical outcome scores showed significant improvement after arthroscopic debridement for central TFCC tears, wearing type tears and greater ulnar plus variance were associated with dissatisfaction and poorer postoperative outcomes after the procedure [117].
- Removal of a perforated TFC is contraindicated in the presence of radiocarpal or distal radioulnar arthritis [58].
- Patients who underwent debridement for any Type 1 Palmer class returned to work at a rate of 92%, but only 44% were free of pain [63].
Arthroscopic and Open Repair (Class 1B, 1C, 1D)
- Class 1B (peripheral) TFCC tears are amenable to arthroscopic or open repair because the rim is well vascularized [20].
- Concurrent fractures of ulnar styloid with persistent instability are either excised or fixed during repair of Class 1B tears [20].
- Class 1C (rare) TFCC tears are amenable to arthroscopic or open repair [20].
- Class 1D TFCC tears are frequently associated with distal radius fractures and often respond to reduction of the radius [20].
- Repair of a traumatic TFCC tear within 3 months of injury allows a patient to regain 80% of wrist ROM and grip strength [20].
- Arthroscopic-assisted repair techniques provide detailed visualization and facilitate the repair of TFCC injuries and associated pathologies with minimally invasive techniques [9].
- Arthroscopic transosseous foveal repair of the TFCC resulted in improvements in grip strength and functional outcomes with low complication and reoperation rates [45].
- The refixation of the TFCC after shortening of the ulnar head for traumatic avulsion class 1B of the TFCC is effective in restoring its function [29].
- Arthroscopic exploration and surgical treatment of peripheral ulnar TFCC lesions allow for satisfactory results regarding mobility and patient satisfaction [116].
- For 1B lesions that underwent repair, 68.3% were able to return to work and 41% had persistent pain [63].
- Coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in patients with peripheral ulnar-side TFCC tears [30].
- The technique of arthroscopic transosseous repair using a modified outside-in technique allows for low-profile fixation for distal radioulnar joint instability and provides excellent biomechanical fixation [48].
- The combined HS and suture repair effectively restores stability to both the DRUJ and UCJ in patients with TFCC-related ulnocarpal instability, considerably reducing pain and preserving range of motion [111].
- This technique provides a minimally invasive and anatomically guided solution for restoring DRUJ stability in chronic TFCC injuries [71].
Pediatric and Adolescent Considerations
- If Palmer 1D tears are mistaken for a central traumatic tear (Palmer 1A), simple debridement alone may result in persistent pain, instability, and functional limitations [24].
- In this series, there was marked improvement in pain, function, and range of motion in patients with TFCC tears and coexisting pathology [1].
- Unlike in adults, in whom Palmer 1A (central) tears are most common, pediatric patients commonly have Palmer 1B (ulnar peripheral) tears, in some studies up to 79% of the patients [122].
- Given the improved vascularity at the periphery of the TFCC, many of these tears are amenable to repair, rather than solely débridement [122].
- 1B TFCC injury is most common in patients with DRF and concomitant TFCC injury [5].
- The most frequent ligament tear in distal fractures of the radius in young adults was the triangular fibrocartilage complex in 39 cases (78%), with a statistical correlation to ulnar styloid fractures [72].
Reconstruction and Salvage Procedures
- TFCC reconstruction with tendon graft is indicated in irreparable TFCC injuries with symptomatic DRUJ instability, neglected chronic injuries, or after suboptimal healing following nonoperative or surgical repair [38].
- Skeletal malalignment that may be responsible for the DRUJ instability should be addressed concomitantly, including ulnar incongruity, malunion of the sigmoid notch, and dorsal tilt or coronal shift of the radius [38].
- Osteoarthritis of the DRUJ and an axial instability of the forearm due to interosseous membrane injury are contraindications to TFCC reconstruction [38].
- The results of a study suggest that arthroscopic TFCC reconstruction using the free PL tendon is an effective method for treating chronic and irreparable TFCC tears with DRUJ instability [66].
- Hemiresection or interposition arthroplasty maintains the ulnar insertion of the TFCC and prevents radioulnar impingement by soft tissue (ECU tendon or capsular flap) interposition [20].
- The Sauvé-Kapandji procedure involves DRUJ arthrodesis with creation of a proximal pseudarthrosis at the ulnar neck [20].
- Ulnar head or total joint implant arthroplasty maintains the relationship between the radius and the ulnar [20].
- Results of ulnar head or total joint implant arthroplasty show good pain relief at the risk of ulnar head instability, aseptic loosening, and no appreciable change in pronosupination in comparison with preoperative values [20].
- One-bone forearm through elimination of forearm rotation represents the ultimate salvage operation for persistent pain/complications by fusing the proximal ulnar to the distal radius shaft [20].
- A complication of TFCC treatment is painful proximal ulna stump instability and convergence of the radius upon the ulna [20].
Postoperative Rehabilitation
- Traumatic tears of the peripheral portions of the TFCC may be surgically repaired and are immobilized immediately postoperatively in a long arm cast to prevent forearm rotation and wrist motion that would stress the repair [127].
- After the first 10 days to 2 weeks following surgery, the cast may be changed to a thermoplastic splint that continues the immobilization of the forearm and wrist [127].
- Splinting generally continues for 4 to 6 weeks following surgery [127].
- Elbow range of motion may be permitted at 4 weeks, generally under the supervision of the therapist [127].
- At 6 weeks, immobilization is discontinued and the patient may use a wrist and forearm splint for intermittent support and protection [127].
- The focus of therapy at 6 weeks is on the gradual mobilization of the forearm and wrist [127].
- A reverse sugar tong cast with forearm in neutral rotation is preferred to long-arm cast to allow early elbow motion after TFCC reconstruction with tendon graft [37].
- Change to reverse sugar tong splint after 3 weeks and allow early midrange forearm rotation after TFCC reconstruction with tendon graft [37].
- Allow full range active forearm rotation after full 6 weeks, start passive motion after full 8 weeks after TFCC reconstruction with tendon graft [37].
- Specific neuromuscular potential training exercises and proprioceptive hand and wrist exercises are included in the rehabilitation program to recuperate functional wrist range of motion in association with fine and gross motor prehensile strength without provoking wrist instability due to overstretching of the newly reconstructed ligament [118].
Complications
Post-traumatic and Associated Pathology
- TFCC tears are associated with positive ulnar variance in up to 81% of cases [69].
- TFCC tears are associated with lunotriquetral ligament perforation in 70% to 76% of cases [69].
- TFCC tears are associated with chondromalacia of the distal ulna or of the ulnar carpal bones in up to 100% of cases [69].
- In patients with distal radius fractures, the most frequent ligament tear was the triangular fibrocartilage complex, occurring in 39 of 50 cases (78%) [72].
- In patients with distal radius fractures, there was a statistical correlation between TFCC tears and ulnar styloid fractures [72].
- In patients with distal radius fractures, chondral lesions were found in 16 of 50 patients (32%) [72].
- In patients with distal radius fractures, the scapholunate ligament was partially or totally torn in 27 of 50 cases (54%) [72].
- In patients with chronic TFCC tears, there is a higher frequency of accompanying extensor carpi ulnaris tendon and/or distal radioulnar joint disorders compared to a control group [40].
- Disability outcomes were worse in patients with distal radial fracture where the TFCC was injured [41].
- Coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in patients undergoing arthroscopic repair of peripheral ulnar-side TFCC tears [30].
Natural History and Untreated Outcomes
- Nonsurgical treatment is moderately successful for treating patients with TFCC tears without distal radioulnar joint instability [22].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, instability of the distal radioulnar joint was found in 19 patients at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, distal radioulnar joint instability was painful in 13 patients at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, 10 of 11 patients with complete peripheral TFCC tears had distal radioulnar joint instability at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, 7 of 32 patients with partial or no peripheral tears had distal radioulnar joint instability at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, patients with distal radioulnar joint instability had a worse Gartland and Werley wrist score [130].
- Traumatic linear TFCC tears do not necessarily lead to significant degenerative arthritis of the ulnar head or lunate [73].
Surgical Complications and Contraindications
- Removal of a perforated triangular fibrocartilage is contraindicated in the presence of radiocarpal or distal radioulnar arthritis [58].
- Arthroscopic transosseous foveal repair of the TFCC resulted in low complication and reoperation rates [45].
Recovery
Natural History and Non-Operative Outcomes
- About 40% of patients sustaining a TFCC tear without distal radioulnar joint (DRUJ) instability still had pain and disability at 1 year [8].
Surgical Outcomes and Functional Recovery
- Arthroscopic TFCC reconstruction using the free PL tendon is an effective method for treating chronic and irreparable TFCC tears with DRUJ instability [66].
Return to Work and Activity
- In the first year after open TFCC reinsertion, 91% of the patients returned to work, including 50% within 12 weeks [137].
- Eighty-four per cent of patients had a good or excellent range of motion of the injured wrist and this resulted in an early return to former activity [140].
Complications and Associated Pathology
- Coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in patients with ulnar-plus variance [30].
- Ulnar variance may be changed after a TFCC tear; it decreased after TFCC foveal repair but increased again over time, which could be one of the causes of ulnar impaction syndrome and ulnar-sided wrist pain [139].
Key Evidence
- [L4] In this series, there was marked improvement in pain, function, and range of motion in patients with TFCC tears and coexisting pathology. [1] (10.1016/s0363-5023(98)80048-8)
- [L4] Surgical treatment of TFCC tears and concomitant pathology in the pediatric and adolescent population results in decreased pain, improved motion and stability, and excellent functional outcomes in the majority of patients. [3] (10.1016/j.jhsa.2019.06.019)
- [L4] Arthroscopic treatment of TFCC lesions leads to satisfactory functional outcomes. [4] (10.1055/s-0039-3400454)
- [L3] 1B TFCC injury is most common in patients with DRF and concomitant TFCC injury. [5] (10.1186/s13018-023-04438-5)
- [L4] Careful history and physical examination are required to determine whether a TFCC tear is symptomatic, and it is important to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary. [6] (10.5435/jaaos-d-20-00998)
- [L5] Acute TFCC injuries require differentiation between those causing distal radioulnar joint instability and those that do not, with management ranging from nonsurgical immobilization to arthroscopic or open surgical repair depending on the specific injury pattern and stability. [7] (10.5435/00124635-200806000-00004)
- [L4] About 40% of patients sustaining TFCC tear without DRUJ instability still had pain and disability at 1 year. [8] (10.1016/j.jhsa.2018.06.064)
- [L5] Arthroscopic-assisted repair techniques have revolutionized surgical management, providing detailed visualization and facilitating the repair of TFCC injuries and associated pathologies with minimally invasive techniques. [9] (10.1016/j.jhsg.2024.03.011)
- [L5] Tears of the triangular fibrocartilage complex (TFCC) are a common cause of ulnar-sided wrist pain in athletes. [10] (10.1016/s0894-1130(12)80104-9)
- [L3] The more experienced observer had more sensitive, specific, and accurate interpretations than the less experienced observer in predicting the presence and location of a TFCC tear. [13] (10.1053/jhsu.2001.24966)
- [L4] The presence of ulnar styloid fracture associated with distal radius fracture predicted the presence of frequently occurring traumatic triangular fibrocartilage complex injury and TFCC 1B injury. [14] (10.1016/j.arthro.2020.05.025)
- [L4] TFCC repair varies substantially from surgeon-to-surgeon, suggesting repairs are discretionary and preference sensitive. [15] (10.1055/s-0038-1625953)
- [L4] TFCC injury should be considered with all distal radial fractures. [16] (10.1177/1558944716660555bh)
- [L4] This SR demonstrates a current lack of high-quality evidence required to draw firm conclusions on the merits of arthroscopic versus open repair of 1B TFCC tears. [17] (10.1177/1558944718815244)
- [L5] TFCC capsular reattachment could be performed with an arthroscopically assisted technique, providing good long-term results. [19] (10.1016/j.hcl.2017.06.005)
- [L3] Nonsurgical treatment is moderately successful for treating patients with TFCC tears without DRUJ instability. [22] (10.1097/corr.0000000000000533)
- [L4] Current evidence demonstrates that TFCC repair achieves good clinical outcomes, with low complication rates. [23] (10.1055/s-0040-1718913)
- [L5] [24] (10.1016/j.hcl.2005.09.002)
- [L3] There was no statistical difference in clinical outcomes after open versus arthroscopic TFCC repair. [27] (10.1016/j.jhsa.2008.01.020)
- [L2] Classification of central triangular fibrocartilage complex lesions as traumatic or degenerative depends on the information provided upon viewing the lesion at arthroscopy. [28] (10.1177/1753193416684658)
- [L4] The refixation of the TFCC after shortening of the ulnar head for traumatic avulsion class 1B of the TFCC is effective in restoring its function. [29] (10.1016/s0266-7681(05)80046-4)
- [L4] However, coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in these patients. [30] (10.1016/j.arthro.2020.05.012)
- [L4] This systematic review did not demonstrate strong evidence regarding the association between ulnar variance and outcomes after TFCC repair. [31] (10.1142/s2424835518300025)
- [L3] Arthroscopic debridement alone appears to be an effective and safe initial treatment for patients with traumatic central TFCC tears. [32] (10.1302/0301-620x.106b4.bjj-2023-0642.r3)
- [L4] Arthroscopy is effective in obtaining both correct diagnosis and treatment of peripheral TFCC tear. [33] (10.2174/1874325001711010525)
- [L4] There is a high rate of abnormal TFCC identified on MRI in patients without corresponding ulnar-sided wrist symptoms. [34] (10.1177/15589447241277846)
- [L5] [35] (10.1016/j.csm.2019.12.008)
- [L4] In more detailed classification of TFCC injuries, such as pc-TFCC tears classified by Atzei's classification, the diagnostic accuracy of MRI remains lower compared to wrist arthroscopy. [36] (10.1186/s12891-023-07140-z)
- [L1] Diagnostic accuracy was highest for central TFCC injuries. [39] (10.1055/s-0038-1629911)
- [L3] We found a higher frequency of accompanying ECU tendon and/or DRUJ disorders in patients with chronic TFCC tears as compared to the control group. [40] (10.1016/j.jhsa.2016.07.040)
- [L2] Disability outcomes were worse in patients with distal radial fracture where TFCC was injured. [41] (10.1016/j.jht.2017.09.002)
- [L4] Since ulnar-sided contrast leakage is more common in patients with peripheral TFCC injuries, distinction between an atypical configuration of the prestyloid recess and actual leakage is important in CT arthrography of the wrist. [42] (10.1186/s12891-022-05241-9)
- [L4] In high-demand athletes, arthroscopic repair of TFCC tears is becoming the treatment of choice to obtain optimum physiologic strength, complete range of motion, stability, and the shortest possible postoperative period. [44] (10.1016/j.hcl.2009.05.011)
- [L1] Arthroscopic transosseous foveal repair of the TFCC resulted in improvements in grip strength and functional outcomes with low complication and reoperation rates. [45] (10.1016/j.arthro.2020.12.209)
- [L2] The classification highlights clinical and arthroscopic criteria to categorize five classes of TFCC peripheral tears on a treatment-oriented system. [47] (10.1177/1753193416687479)
- [L5] The technique allows for low-profile fixation for distal radioulnar joint instability and provides excellent biomechanical fixation. [48] (10.1016/j.eats.2024.103349)
- [L3] Deep TFCC fiber tear may contribute to decreased wrist rotational positioning sense and may have biomechanical importance in distal radioulnar joint stability. [50] (10.1016/j.jhsa.2018.01.022)
- [L5] [53] (10.1016/j.hcl.2012.05.014)
- [L3] MR arthrography is more sensitive and specific method in terms of the diagnosis of TFCC tears compared to conventional wrist MRI. [54] (10.1016/j.injury.2019.07.032)
- [L5] [55] (10.1016/s0894-1130(96)80071-8)
- [L4] This study emphasizes that open surgical TFCC repair is a safe and reliable therapeutic procedure in children and adolescent populations. [56] (10.1142/s2424835518500509)
- [L4] Removal of a perforated TFC is contraindicated in the presence of radiocarpal or distal radioulnar arthritis. [58] (10.1016/s0363-5023(84)80104-5)
- [L2] Load-bearing RaUl measurement is a simple method to diagnose an unstable distal radioulnar joint in patients with TFCC injury. [59] (10.1016/j.jhsa.2022.01.008)
- [L3] [61] (10.1186/s12891-020-03321-2)
- [L3] The presence of an abnormal TFCC on MRI may be of questionable clinical meaning, because there is a high incidence of TFCC abnormalities in asymptomatic subjects, particularly those over the age of 50. [62] (10.1016/j.jhsa.2011.10.006)
- [Paper] [63] (10.1055/s-0040-1713580)
- [L5] The technique is best used in young patients with indeterminate physical examinations and normal radiography in whom intrinsic ligament or TFCC tears are suspected to assist decision making regarding the performance of arthroscopy. [64] (10.1016/j.jhsa.2006.03.015)
- [L4] The results of this study suggest that arthroscopic TFCC reconstruction using the free PL tendon is an effective method for treating chronic and irreparable TFCC tears with DRUJ instability. [66] (10.1186/s13018-021-02827-2)
- [L4] With appropriate indications and patient selection, arthroscopic foveal repair of the TFCC may restore DRUJ stability and provide satisfactory results without significant complications. [68] (10.1055/s-0035-1544226)
- [L4] [69] (10.1016/0363-5023(92)90325-j)
- [L5] This technique provides a minimally invasive and anatomically guided solution for restoring DRUJ stability in chronic TFCC injuries. [71] (10.1002/atn2.70005)
- [L4] [72] (10.1016/s0266-7681(97)80364-6)
- [L5] Traumatic linear TFCC tears do not necessarily lead to significant degenerative arthritis of the ulnar head or lunate. [73] (10.1016/0266-7681(94)90078-7)
- [L5] [74] (10.1016/0363-5023(93)90098-n)
- [Paper] The study showed that the triangular fibrocartilage is less stiff in neutral forearm rotation and that the palmar and dorsal parts have material properties similar to those of the radiocarpal ligaments. [88] (10.1016/s0363-5023(10)80075-9)
- [L5] Changes in ulnar variance of a forearm due to ulnar lengthening or radial shortening do, however, dramatically alter the force transmission. [90] (10.1016/0363-5023(92)90342-m)
- [L3] The Melone classification system does not predict the presence of TFCC lesions, while Frykman Type VI and VIII fractures show a significantly higher incidence of TFCC tears. [102] (10.1177/1753193408090106)
- [L5] [109] (10.1177/1753193409100120)
- [L5] [110] (10.5435/jaaos-d-16-00407)
- [L4] The combined HS and suture repair effectively restores stability to both the DRUJ and UCJ in patients with TFCC-related ulnocarpal instability, considerably reducing pain and preserving range of motion. [111] (10.1016/j.jhsg.2025.100806)
- [L3] High-resolution MRI using a microscopy surface coil allowed assessment of each TFCC component and showed a higher accuracy for diagnosing injuries to the radial attachment and the disc of the TFC compared with previous studies. [113] (10.1016/j.jhsa.2006.05.001)
- [L4] Arthroscopic exploration and surgical treatment of peripheral ulnar TFCC lesions allow for satisfactory results regarding mobility and patient satisfaction. [116] (10.1016/j.hansur.2016.10.110)
- [L4] Although clinical outcome scores showed significant improvement after arthroscopic debridement for central TFCC tears, wearing type tears and greater ulnar plus variance were associated with dissatisfaction and poorer postoperative outcomes after the procedure. [117] (10.1016/j.arthro.2018.05.044)
- [L4] [118] (10.1016/j.jhse.2007.02.170)
- [L3] The sensitivity, specificity, and accuracy of 3.0T wrist MRI for the TFCC is consistently higher compared with those of 1.5T wrist MRI, suggesting improved capability for detection of TFCC injuries. [119] (10.1016/j.jhsa.2008.02.028)
- [L2] [121] (10.1016/j.arthro.2021.03.005)
- [L5] [122] (10.5435/jaaos-d-21-01029)
- [L3] Nonoperative management of traumatic TFCC injuries with above-elbow immobilization is a viable treatment method, particularly in patients without DRUJ subluxation. [123] (10.1302/0301-620x.103b8.bjj-2020-2310.r2)
- [L5] [125] (10.1177/17531934221140238)
- [L4] [126] (10.1177/15589447221084125)
- [L5] [127] (10.1097/00130911-199709000-00009)
- [L2] However, the mean DASH scores showed no difference across all groups, calling into question the clinical need to pursue operative treatment via K-wire stabilization or TFCC repair over conservative treatment via cast immobilization. [129] (10.1016/j.jhsg.2021.02.005)
- [Paper] [130] (10.1016/j.jhsa.2006.08.015)
- [L5] [132] (10.1097/bth.0b013e3181bd8319)
- [L2] High-resolution magnetic resonance imaging permits accurate depiction and localization of tears of the triangular fibrocartilage complex. [133] (10.2106/00004623-199711000-00009)
- [L2] This finding confirms the efficacy of CT scan for evaluating DRUJ instability. [135] (10.1016/j.ijsu.2011.08.005)
- [L3] Although future advances in MRI technology will probably improve its usefulness, single-injection wrist arthrography currently is superior to routine MRI for the detection of fullthickness triangular fibrocartilage tears. [136] (10.1016/s0266-7681(98)80068-5)
- [L3] In the first year after open TFCC reinsertion, 91% of the patients returned to work, including 50% within 12 weeks. [137] (10.1016/j.hansur.2021.03.012)
- [L4] Ulnar variance may be changed after a TFCC tear; it decreased after TFCC foveal repair but increased again over time, which could be one of the causes of ulnar impaction syndrome and ulnar-sided wrist pain. [139] (10.1055/s-0038-1668153)
- [L4] Eighty-four per cent of patients had a good or excellent range of motion of the injured wrist and this resulted in an early return to former activity. [140] (10.1016/j.jhsb.2006.03.101)
References
[1] Triangular fibrocartilage injuries in pediatric and adolescent patients. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80048-8
[3] Early Results of Surgical Treatment of Triangular Fibrocartilage Complex Tears in Children and Adolescents. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.06.019
[4] Patient-Reported Outcomes following Arthroscopic Triangular Fibrocartilage Complex Repair. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-3400454
[5] Association between imaging parameter changes and triangular fibrocartilage complex injury after distal radius fractures. Journal of Orthopaedic Surgery and Research. 2023. DOI: 10.1186/s13018-023-04438-5
[6] Open and Arthroscopic Triangular Fibrocartilage Complex (TFCC) Repair. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-20-00998
[7] Management of Acute Triangular Fibrocartilage Complex Injury of the Wrist. Journal of the American Academy of Orthopaedic Surgeons. 2008. DOI: 10.5435/00124635-200806000-00004
[8] The Natural Course of Triangular Fibrocartilage Complex Tear without Distal Radioulnar Joint Instability. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.064
[9] Arthroscopic-Assisted Repair of the Triangular Fibrocartilage Complex. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.03.011
[10] Arthroscopic management of the athlete. Journal of Hand Therapy. 1991. DOI: 10.1016/s0894-1130(12)80104-9
[13] The effect of observer experience on magnetic resonance imaging interpretation and localization of triangular fibrocartilage complex lesions. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.24966
[14] The Presence and the Location of an Ulnar Styloid Fracture Associated With Distal Radius Fracture Predict the Presence of Triangular Fibrocartilage Complex 1B Injury. Arthroscopy: The Journal of Arthroscopic & Related Surgery. 2020. DOI: 10.1016/j.arthro.2020.05.025
[15] Variation in Repair of the Triangular Fibrocartilage Complex. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1625953
[16] The Correlation of Fracture Patterns of Distal Radius Fractures and Triangular Fibrocartilage Complex Injures. HAND. 2016. DOI: 10.1177/1558944716660555bh
[17] Open Versus Arthroscopic Repair of 1B Ulnar-Sided Triangular Fibrocartilage Complex Tears: A Systematic Review. HAND. 2019. DOI: 10.1177/1558944718815244
[19] Arthroscopic Management of Triangular Fibrocartilage Complex Peripheral Injury. Hand Clinics. 2017. DOI: 10.1016/j.hcl.2017.06.005
[20] Miller S Review Of Orthopaedics. DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[21] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[22] What is the Natural History of the Triangular Fibrocartilage Complex Tear Without Distal Radioulnar Joint Instability?. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000533
[23] Surgical Repair of Triangular Fibrocartilage Complex Tears: A Systematic Review. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1718913
[24] Pediatric Distal Radius Fractures and Triangular Fibrocartilage Complex Injuries. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2005.09.002
[26] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic TFCC Debridement.
[27] Clinical Comparison of Arthroscopic Versus Open Repair of Triangular Fibrocartilage Complex Tears. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.01.020
[28] Diagnosing central lesions of the triangular fibrocartilage as traumatic or degenerative: a review of clinical accuracy. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416684658
[29] A New Technique of Reattachment after Traumatic Avulsion of the TFCC at Its Ulnar Insertion. Journal of Hand Surgery. 1995. DOI: 10.1016/s0266-7681(05)80046-4
[30] What Is the Effect of the Ulnar‐Plus Variance on the Outcomes of Arthroscopic Repair of the Peripheral Ulnar‐Side Triangular Fibrocartilage Complex Tear?. Arthroscopy. 2020. DOI: 10.1016/j.arthro.2020.05.012
[31] Triangular Fibrocartilage Complex Repair and Ulna Variance: A Systematic Review. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518300025
[32] Prognostic factors for clinical outcomes after arthroscopic treatment of traumatic central tears of the triangular fibrocartilage complex. The Bone & Joint Journal. 2024. DOI: 10.1302/0301-620x.106b4.bjj-2023-0642.r3
[33] Results of Arthroscopic Repair of Peripheral Triangular Fibrocartilage Complex Tear With Exploration of Dorsal Sensory Branch of Ulnar Nerve. The Open Orthopaedics Journal. 2017. DOI: 10.2174/1874325001711010525
[34] Incidental Triangular Fibrocartilage Complex Changes on Wrist MRI. HAND. 2024. DOI: 10.1177/15589447241277846
[35] Ulnar-Sided Wrist Pain in the Athlete. Clinics in Sports Medicine. 2020. DOI: 10.1016/j.csm.2019.12.008
[36] Diagnostic value of MRI in traumatic triangular fibrocartilage complex injuries: a retrospective study. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-023-07140-z
[37] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic TFCC Reconstruction With Tendon Graft.
[38] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > TFCC Reconstruction with Tendon Graft.
[39] TFCC Injuries: Meta-Analysis and Comparison of Diagnostic Imaging Modalities. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1629911
[40] The Factors Correlated with the Extensor Carpi Ulnaris Tendon and Distal Radioulnar Joint Disorder in Patients with Chronic Triangular Fibrocartilage Tears. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2016.07.040
[41] Outcomes of surgically treated distal radial fractures with associated triangular fibrocartilage complex injury. Journal of Hand Therapy. 2019. DOI: 10.1016/j.jht.2017.09.002
[42] Evaluation of prestyloid recess morphology and ulnar-sided contrast leakage in CT arthrography of the wrist. BMC Musculoskeletal Disorders. 2022. DOI: 10.1186/s12891-022-05241-9
[43] Green S Operative Hand Surgery. Chronic Perilunate Instability (SL Plus LT Instability) > Palmer’s Classification of TFCC Lesions > Class 1A Tear.
[44] Repair of Arthroscopic Triangular Fibrocartilage Complex Tears in Athletes. Hand Clinics. 2009. DOI: 10.1016/j.hcl.2009.05.011
[45] Arthroscopic Transosseous Repair of Foveal Tears of the Triangular Fibrocartilage Complex: A Systematic Review of Clinical Outcomes. Arthroscopy. 2020. DOI: 10.1016/j.arthro.2020.12.209
[47] Classification of ulnar triangular fibrocartilage complex tears. A treatment algorithm for Palmer type IB tears. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416687479
[48] Arthroscopic Triangular Fibrocartilage Complex Repair Using Modified Outside‐In Technique. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2024.103349
[49] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > TFCC Repair > Classification, Functional Anatomy, Clinical Features, and Indication for Repair.
[50] The Effect of Triangular Fibrocartilage Complex Tear on Wrist Proprioception. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.01.022
[53] Triangular Fibrocartilage Complex Injuries in the Elite Athlete. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.014
[54] Comparison between conventional MRI and MR arthrography in the diagnosis of triangular fibrocartilage tears and correlation with arthroscopic findings. Injury. 2019. DOI: 10.1016/j.injury.2019.07.032
[55] The Distal Radiou1nar joint. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80071-8
[56] TFCC Lesions in Children and Adolescents: Open Treatment. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518500509
[58] Isolated tears of the triangular fibrocartilage of the wrist: Results of partial excision. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80104-5
[59] Load-Bearing Radioulnar Distances to Evaluate an Unstable Distal Radioulnar Joint in Patients With Triangular Fibrocartilage Complex Tears. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.01.008
[60] Green S Operative Hand Surgery. Chronic Perilunate Instability (SL Plus LT Instability) > Palmer’s Classification of TFCC Lesions > Class 1B Tear.
[61] The importance of radial multiplanar reconstructions for assessment of triangular fibrocartilage complex injury in CT arthrography of the wrist. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03321-2
[62] Prevalence of Triangular Fibrocartilage Complex Abnormalities on MRI Scans of Asymptomatic Wrists. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.10.006
[63] A Systematic Review and Analysis of Palmer Type I Triangular Fibrocartilage Complex Injuries: Outcomes of Treatment. Journal of Hand and Microsurgery. 2020. DOI: 10.1055/s-0040-1713580
[64] Magnetic Resonance Arthrography of the Wrist: Case Presentation and Discussion. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.03.015
[66] Arthroscopic triangular fibrocartilage complex reconstruction with free tendon graft for chronic distal radioulnar joint instability. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02827-2
[68] Arthroscopic Foveal Repair of the Triangular Fibrocartilage Complex. Journal of Wrist Surgery. 2015. DOI: 10.1055/s-0035-1544226
[69] Wafer distal ulna resection for triangular fibrocartilage tears and/or ulna impaction syndrome. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90325-j
[70] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic Repair of Class 1B TFCC Tears.
[71] Arthroscopic‐Assisted Suture Tape–Reinforced Triangular Fibrocartilage Complex Repair and Distal Radioulnar Ligament Augmentation Using a Modified Adams‐Berger Technique. Arthroscopy Techniques. 2026. DOI: 10.1002/atn2.70005
[72] Intraarticular Lesions in Distal Fractures of the Radius in Young Adults. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80364-6
[73] Wear Patterns of the Articular Cartilage and Triangular Fibrocartilaginous Complex of the Wrist: A Cadaveric Study. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90078-7
[74] Effects of radial deformity on distal radioulnar joint mechanics. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90098-n
[88] The distal radioulnar ligaments: A biomechanical study. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80075-9
[90] Force transmission through the distal ulna: Effect of ulnar variance, lunate fossa angulation, and radial and palmar tilt of the distal radius. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90342-m
[102] The Value of Plain X-Rays in Predicting TFCC Injury after Distal Radial Fractures. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408090106
[109] New trends in arthroscopic management of type 1-B TFCC injuries with DRUJ instability. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193409100120
[110] Evaluation of Ulnar-sided Wrist Pain. Journal of the American Academy of Orthopaedic Surgeons. 2017. DOI: 10.5435/jaaos-d-16-00407
[111] Extensor Retinaculum Capsulorrhaphy and Suture Repair for Ulnocarpal and Distal Radioulnar Joint Instability: One-Year Results. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2025.100806
[113] Comparison Between High-Resolution MRI With a Microscopy Coil and Arthroscopy in Triangular Fibrocartilage Complex Injury. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.05.001
[116] Résultats des réinsertions du TFCC sous arthroscopie. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.110
[117] RETRACTED: Prognostic Factors of Arthroscopic Debridement for Central Triangular Fibrocartilage Complex Tears in Adults Younger Than 45 Years: A Retrospective Case Series Analysis. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.05.044
[118] A-0263Session 16:Ulnar sided wrist pain. Journal of Hand Surgery: European Volume. 2007. DOI: 10.1016/j.jhse.2007.02.170
[119] Diagnostic Comparison of 1.5 Tesla and 3.0 Tesla Preoperative MRI of the Wrist in Patients With Ulnar-Sided Wrist Pain. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.02.028
[121] The Hook Test Is More Accurate Than the Trampoline Test to Detect Foveal Tears of the Triangular Fibrocartilage Complex of the Wrist. Arthroscopy: The Journal of Arthroscopic & Related Surgery. 2021. DOI: 10.1016/j.arthro.2021.03.005
[122] Pediatric Ulnar-sided Wrist Pain: A Review of the Current Literature. Journal of the American Academy of Orthopaedic Surgeons. 2022. DOI: 10.5435/jaaos-d-21-01029
[123] Predictors for poor outcome for conservatively treated traumatic triangular fibrocartilage complex tears. The Bone & Joint Journal. 2021. DOI: 10.1302/0301-620x.103b8.bjj-2020-2310.r2
[125] The distal radioulnar joint after distal radial fractures: when and how do we need to treat pain, stiffness or instability?. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934221140238
[126] Radial Sided Triangular Fibrocartilage Complex Tears: A Comprehensive Review. HAND. 2022. DOI: 10.1177/15589447221084125
[127] Rehabilitation Following Surgery for the Distal Radioulnar Joint. Techniques in Hand & Upper Extremity Surgery. 1997. DOI: 10.1097/00130911-199709000-00009
[129] Management of Acute Distal Radioulnar Joint Instability Following a Distal Radius Fracture: A Systematic Review and Meta-Analysis. Journal of Hand Surgery Global Online. 2021. DOI: 10.1016/j.jhsg.2021.02.005
[130] Arthroscopic Management of Distal Radius Fractures. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.08.015
[132] Advantages of Open Repair of a Foveal Tear of the Triangular Fibrocartilage Complex Via a Palmar Surgical Approach. Techniques in Hand & Upper Extremity Surgery. 2009. DOI: 10.1097/bth.0b013e3181bd8319
[133] The Utility of High-Resolution Magnetic Resonance Imaging in the Evaluation of the Triangular Fibrocartilage Complex of the Wrist. The Journal of Bone and Joint Surgery (American Volume)*. 1997. DOI: 10.2106/00004623-199711000-00009
[135] DRUJ instability after distal radius fracture: A comparison between cases with and without ulnar styloid fracture. International Journal of Surgery. 2011. DOI: 10.1016/j.ijsu.2011.08.005
[136] Arthrography is Superior to Magnetic Resonance Imaging for Diagnosing Injuries of the Triangular Fibrocartilage. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80068-5
[137] Factors associated with return to work after open reinsertion of the triangular fibrocartilage. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.03.012
[139] Changes in Ulnar Variance after a Triangular Fibrocartilage Complex Tear. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1668153
[140] 5.3 Volar locking compression plate technique for dorsally displaced fractures of the distal radius – our first clinical results. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2006. DOI: 10.1016/j.jhsb.2006.03.101