Patients › Wrist
ਡੀ ਕੁਏਰਵੇਨ ਟੈਨੋਸਾਈਨੋਵਾਈਟਿਸ
Patient-facing topic on De Quervain's tenosynovitis (first dorsal compartment) — diagnosis, conservative management, and indications for de Quervain's release.
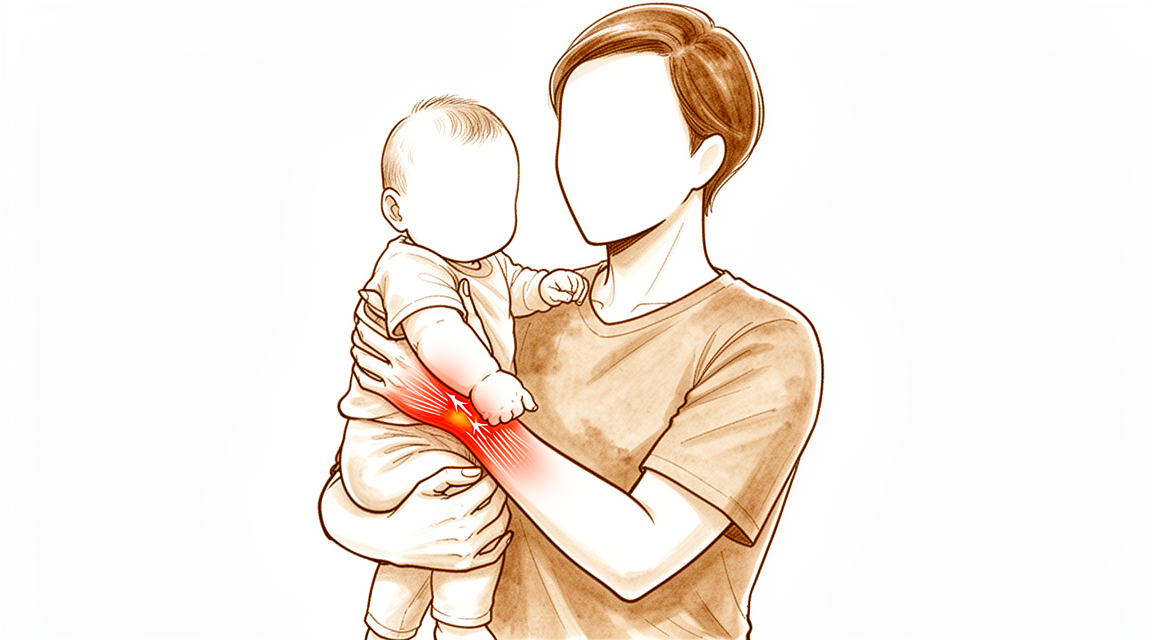
ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ
ਡੀ ਕੁਏਰਵੇਨ ਟੈਨੋਸਾਈਨੋਵਾਈਟਿਸ (De Quervain's tenosynovitis) ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਦੋ ਟੈਂਡਨਾਂ (tendon, ਪੱਠੇ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀ ਮਜ਼ਬੂਤ ਤੰਦ) ਦੀ ਸਮੱਸਿਆ ਹੈ। ਜਿਸ ਸੁਰੰਗ ਵਿੱਚੋਂ ਉਹ ਲੰਘਦੇ ਹਨ, ਉਹ ਸੁੱਜ ਕੇ ਤੰਗ ਹੋ ਜਾਂਦੀ ਹੈ, ਇਸ ਲਈ ਉਸ ਵਿੱਚੋਂ ਖਿਸਕਦੇ ਟੈਂਡਨਾਂ ਵਿੱਚ ਦਰਦ ਹੁੰਦਾ ਹੈ। ਤੁਹਾਨੂੰ ਆਪਣੇ ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ, ਅੰਗੂਠੇ ਦੇ ਮੁੱਢ ਕੋਲ ਹੱਡੀ ਦੇ ਉੱਭਾਰ ਦੇ ਨੇੜੇ, ਦੁਖਣ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ ਅਤੇ ਦਬਾਉਣ ਉੱਤੇ ਪੀੜ ਹੁੰਦੀ ਹੈ। ਅਕਸਰ ਉਸੇ ਥਾਂ ਉੱਤੇ ਸੋਜ ਵੀ ਹੁੰਦੀ ਹੈ।
ਕੁਝ ਖ਼ਾਸ ਹਰਕਤਾਂ ਦਰਦ ਨੂੰ ਵਧਾ ਦਿੰਦੀਆਂ ਹਨ। ਗੁੱਟ ਨੂੰ ਛੋਟੀ ਉਂਗਲ ਵੱਲ ਮੋੜਨਾ, ਗੁੱਟ ਨੂੰ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਵੱਲ ਮੋੜਦੇ ਹੋਏ ਜ਼ੋਰ ਨਾਲ ਫੜਨਾ, ਜਾਂ ਅੰਗੂਠੇ ਅਤੇ ਸ਼ਹਾਦਤ ਦੀ ਉਂਗਲ ਨਾਲ ਚੂੰਢੀ ਭਰਨਾ, ਇਹ ਸਭ ਦਰਦ ਛੇੜ ਸਕਦੇ ਹਨ। ਰੋਜ਼ਾਨਾ ਦੇ ਉਹ ਕੰਮ ਔਖੇ ਹੋ ਜਾਂਦੇ ਹਨ ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਇਹ ਹਰਕਤਾਂ ਹੁੰਦੀਆਂ ਹਨ: ਕੇਤਲੀ ਚੁੱਕਣਾ, ਦਰਵਾਜ਼ੇ ਦਾ ਹੈਂਡਲ ਘੁਮਾਉਣਾ, ਛੋਟੇ ਬੱਚੇ ਨੂੰ ਚੁੱਕਣਾ, ਕੱਪੜਾ ਨਿਚੋੜਨਾ, ਜਾਂ ਕੈਂਚੀ ਵਰਤਣਾ। ਕੁਝ ਲੋਕਾਂ ਨੂੰ ਦੁਖਦੀ ਥਾਂ ਨੂੰ ਦਬਾਉਣ ਉੱਤੇ ਚਮੜੀ ਹੇਠਾਂ ਰੇਤ ਵਰਗੀ ਰੜਕ ਮਹਿਸੂਸ ਹੁੰਦੀ ਹੈ।
ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਨੂੰ ਲੱਗਦਾ ਹੈ ਕਿ ਦਰਦ ਵਰਤੋਂ ਨਾਲ ਭੜਕਦਾ ਹੈ ਅਤੇ ਆਰਾਮ ਨਾਲ ਸ਼ਾਂਤ ਹੋ ਜਾਂਦਾ ਹੈ। ਹੱਥ ਨਾਲ ਬਹੁਤ ਕੰਮ ਵਾਲੇ ਦਿਨ ਤੋਂ ਬਾਅਦ ਇਹ ਵੱਧ ਹੋ ਸਕਦਾ ਹੈ। ਕੁਝ ਲੋਕਾਂ ਨੂੰ ਇਹ ਸਵੇਰੇ ਉੱਠਦੇ ਹੀ ਜਾਂ ਰਾਤ ਨੂੰ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ।
ਥੋੜ੍ਹੇ ਜਿਹੇ ਲੋਕਾਂ (ਲਗਭਗ 100 ਵਿੱਚੋਂ 1) ਨੂੰ ਲੱਗਦਾ ਹੈ ਕਿ ਦਰਦ ਦੇ ਨਾਲ-ਨਾਲ ਉਨ੍ਹਾਂ ਦਾ ਅੰਗੂਠਾ ਅਟਕਦਾ ਜਾਂ ਫਸਦਾ ਵੀ ਹੈ। ਇਹ ਦੱਸਣਾ ਫ਼ਾਇਦੇਮੰਦ ਹੈ, ਕਿਉਂਕਿ ਇਸ ਨਾਲ ਇਹ ਬਦਲ ਸਕਦਾ ਹੈ ਕਿ ਕਿਹੜੇ ਇਲਾਜ ਚੰਗਾ ਕੰਮ ਕਰਦੇ ਹਨ।
ਮਦਦ ਕਦੋਂ ਲੈਣੀ ਹੈ
ਜੇ ਦਰਦ ਠੀਕ ਨਹੀਂ ਹੋ ਰਿਹਾ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਿਹਾ ਹੈ, ਰਾਤ ਨੂੰ ਤੁਹਾਡੀ ਨੀਂਦ ਖੋਲ੍ਹ ਦਿੰਦਾ ਹੈ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦਾ ਹੈ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਜੇ ਤੁਹਾਡੇ ਹੱਥ ਜਾਂ ਬਾਂਹ ਵਿੱਚ ਗਰਮੀ, ਲਾਲੀ, ਸੋਜ ਅਤੇ ਦਰਦ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹ ਲਾਗ (ਇਨਫੈਕਸ਼ਨ) ਹੋ ਸਕਦੀ ਹੈ ਜਿਸ ਦੀ ਉਸੇ ਦਿਨ ਦੇਖਭਾਲ ਦੀ ਲੋੜ ਹੈ, ਅਤੇ ਤੁਹਾਨੂੰ ਜੀਪੀ ਦੇ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਨਹੀਂ ਹੈ। ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ ਜਾਂ ਹੱਥ ਫਿੱਕੇ, ਠੰਢੇ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੇ ਪੈ ਜਾਣ, ਜਾਂ ਸੱਟ ਤੋਂ ਬਾਅਦ ਅਚਾਨਕ ਤੁਹਾਡੀ ਛੋਹ ਮਹਿਸੂਸ ਕਰਨ ਦੀ ਸਮਰੱਥਾ ਜਾਂ ਹਿਲਜੁਲ ਚਲੀ ਜਾਵੇ, ਤਾਂ ਵੀ ਉਸੇ ਦਿਨ ਜਾਓ।
ਜੇ ਤੁਸੀਂ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਹੀਂ ਕਰ ਸਕਦੇ, ਉਦਾਹਰਨ ਲਈ ਕਲੀਨਿਕ ਦੇ ਸਮੇਂ ਤੋਂ ਬਾਅਦ ਜਾਂ ਹਫ਼ਤੇ ਦੇ ਅਖ਼ੀਰ (ਸ਼ਨੀਵਾਰ-ਐਤਵਾਰ) ਨੂੰ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਅਸਲ ਵਿੱਚ ਕੀ ਹੋ ਰਿਹਾ ਹੈ
ਦੋ ਟੈਂਡਨ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਨੂੰ ਹੱਥ ਤੋਂ ਦੂਰ ਲਿਜਾਂਦੇ ਹਨ ਅਤੇ ਇਸ ਨੂੰ ਸਿੱਧਾ ਕਰਦੇ ਹਨ। ਉਹ ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਇੱਕ ਤੰਗ ਸੁਰੰਗ ਵਿੱਚੋਂ ਨਾਲ-ਨਾਲ ਲੰਘਦੇ ਹਨ। ਸੁਰੰਗ ਦੀ ਇੱਕ ਸਖ਼ਤ ਛੱਤ ਹੁੰਦੀ ਹੈ ਜੋ ਟੈਂਡਨਾਂ ਨੂੰ ਹੱਡੀ ਦੇ ਨੇੜੇ ਰੱਖਦੀ ਹੈ, ਜਿਵੇਂ ਕੋਈ ਛੱਲਾ ਦੋ ਰੱਸੀਆਂ ਨੂੰ ਆਪਣੀ ਥਾਂ 'ਤੇ ਟਿਕਾ ਕੇ ਰੱਖਦਾ ਹੈ।
ਸਮੱਸਿਆ ਇਹ ਹੈ ਕਿ ਟੈਂਡਨਾਂ ਅਤੇ ਉਨ੍ਹਾਂ ਦੀ ਸੁਰੰਗ ਵਿੱਚ ਸੋਜਸ਼ (inflammation) ਹੋ ਜਾਂਦੀ ਹੈ। ਸੁੱਜੀ ਹੋਈ ਅੰਦਰਲੀ ਪਰਤ ਪਹਿਲਾਂ ਹੀ ਤੰਗ ਥਾਂ ਦੇ ਅੰਦਰ ਜਗ੍ਹਾ ਘੇਰ ਲੈਂਦੀ ਹੈ, ਇਸ ਲਈ ਖਿਸਕਦੇ ਸਮੇਂ ਟੈਂਡਨ ਰਗੜ ਖਾਂਦੇ ਹਨ। ਉਹ ਰਗੜ ਹੋਰ ਸੋਜ ਅਤੇ ਹੋਰ ਦਰਦ ਪੈਦਾ ਕਰਦੀ ਹੈ, ਅਤੇ ਸਮੇਂ ਨਾਲ ਸੁਰੰਗ ਖ਼ੁਦ ਵੀ ਤੰਗ ਹੋ ਸਕਦੀ ਹੈ। ਇਸ ਤੰਗ ਰਸਤੇ ਵਿੱਚ ਖ਼ੂਨ ਦੀ ਸਪਲਾਈ ਘੱਟ ਹੁੰਦੀ ਹੈ, ਜਿਸ ਕਾਰਨ ਚਿੜੇ ਹੋਏ (irritated) ਟੈਂਡਨਾਂ ਦਾ ਆਪਣੇ ਆਪ ਸ਼ਾਂਤ ਹੋਣਾ ਔਖਾ ਹੋ ਜਾਂਦਾ ਹੈ।
ਕੁਝ ਲੋਕਾਂ ਦੀ ਬਣਤਰ ਵਿੱਚ ਸੁਰੰਗ ਦੇ ਅੰਦਰ ਇੱਕ ਵਾਧੂ ਕੰਧ ਹੁੰਦੀ ਹੈ, ਜੋ ਇਸ ਨੂੰ ਦੋ ਵੱਖਰੇ ਰਸਤਿਆਂ ਵਿੱਚ ਵੰਡ ਦਿੰਦੀ ਹੈ। ਇਹ ਇਸ ਲਈ ਮਾਇਨੇ ਰੱਖਦਾ ਹੈ ਕਿਉਂਕਿ ਦੋਵਾਂ ਟੈਂਡਨਾਂ ਨੂੰ ਖਿਸਕਣ ਲਈ ਥਾਂ ਚਾਹੀਦੀ ਹੈ। ਜੇ ਇੱਕ ਟੈਂਡਨ ਆਪਣੇ ਵੱਖਰੇ, ਬੰਦ ਰਸਤੇ ਵਿੱਚ ਹੈ, ਤਾਂ ਮੁੱਖ ਸੁਰੰਗ ਦਾ ਇਲਾਜ ਹੋਣ ਦੇ ਬਾਵਜੂਦ ਉਹ ਰਸਤਾ ਤੰਗ ਰਹਿ ਸਕਦਾ ਹੈ।
ਇਸ ਨਾਲ ਸਮਝ ਆਉਂਦਾ ਹੈ ਕਿ ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰ ਰਹੇ ਹੋ। ਤੁਹਾਡੇ ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਦੁਖਦੀ ਥਾਂ ਖ਼ੁਦ ਸੁਰੰਗ ਹੀ ਹੈ। ਪਕੜਨ, ਚੂੰਢੀ ਭਰਨ ਅਤੇ ਚੁੱਕਣ ਵੇਲੇ ਹੋਣ ਵਾਲਾ ਦਰਦ ਟੈਂਡਨਾਂ ਦੇ ਤੰਗ ਹੋਈ ਥਾਂ ਵਿੱਚੋਂ ਖਿੱਚ ਕੇ ਲੰਘਣ ਕਾਰਨ ਹੁੰਦਾ ਹੈ। ਚੂੰਢੀ ਅਤੇ ਅੰਗੂਠੇ ਦੀ ਤਾਕਤ ਘਟ ਸਕਦੀ ਹੈ ਕਿਉਂਕਿ ਟੈਂਡਨ ਆਜ਼ਾਦੀ ਨਾਲ ਨਹੀਂ ਖਿਸਕ ਸਕਦੇ। ਕੁਝ ਲੋਕਾਂ ਨੂੰ ਜੋ ਰੜਕ ਮਹਿਸੂਸ ਹੁੰਦੀ ਹੈ, ਉਹ ਚਮੜੀ ਹੇਠਾਂ ਹਿੱਲਦੀ ਟੈਂਡਨ ਦੀ ਖੁਰਦਰੀ ਹੋਈ ਸਤ੍ਹਾ ਹੈ।
ਜਦੋਂ ਦਰਦ ਦੇ ਨਾਲ-ਨਾਲ ਅੰਗੂਠਾ ਅਟਕਦਾ ਜਾਂ ਫਸਦਾ ਵੀ ਹੈ, ਤਾਂ ਤੰਗੀ ਏਨੀ ਵਧ ਚੁੱਕੀ ਹੁੰਦੀ ਹੈ ਕਿ ਟੈਂਡਨ ਪਲ ਭਰ ਲਈ ਫਸ ਜਾਂਦਾ ਹੈ। ਇਹ ਉਸੇ ਸਮੱਸਿਆ ਦਾ ਵਧਿਆ ਹੋਇਆ ਰੂਪ ਹੈ, ਅਤੇ ਇਸ ਬਾਰੇ ਛੇਤੀ ਦੱਸਣਾ ਫ਼ਾਇਦੇਮੰਦ ਹੈ ਕਿਉਂਕਿ ਇਸ ਨਾਲ ਇਹ ਬਦਲ ਜਾਂਦਾ ਹੈ ਕਿ ਕਿਹੜੇ ਇਲਾਜ ਚੰਗਾ ਕੰਮ ਕਰਦੇ ਹਨ।
ਇੱਥੇ ਦਰਦ ਸੁਰੰਗ ਦੀ ਬਜਾਏ ਇਸ ਦੇ ਗੁਆਂਢੀ ਹਿੱਸਿਆਂ ਤੋਂ ਵੀ ਆ ਸਕਦਾ ਹੈ: ਅੰਗੂਠੇ ਦੇ ਮੁੱਢ ਵਿੱਚ ਗਠੀਆ (ਆਰਥਰਾਈਟਿਸ), ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ (forearm) ਵਿੱਚ ਹੋਰ ਉੱਪਰ ਚਿੜੇ ਹੋਏ ਟੈਂਡਨ, ਜਾਂ ਗੁੱਟ ਦੇ ਇਸ ਹਿੱਸੇ ਨੂੰ ਪਾਰ ਕਰਨ ਵਾਲੀ ਚਮੜੀ ਦੇ ਨੇੜੇ ਦੀ ਇੱਕ ਨਸ (nerve)। ਇਹਨਾਂ ਦੇ ਇਲਾਜ ਵੱਖਰੇ ਹੁੰਦੇ ਹਨ, ਇਸੇ ਲਈ ਦਰਦ ਦਾ ਸਹੀ ਸਰੋਤ ਮਾਇਨੇ ਰੱਖਦਾ ਹੈ।
ਅਸੀਂ ਇਸ ਬਾਰੇ ਕੀ ਕਰ ਸਕਦੇ ਹਾਂ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਜੋ ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ ਹਨ, ਤੁਹਾਡੀ ਹਾਲਤ ਦੇ ਅਨੁਕੂਲ ਸਭ ਤੋਂ ਘੱਟ ਚੀਰ-ਫਾੜ ਵਾਲੇ ਇਲਾਜਾਂ ਤੋਂ ਸ਼ੁਰੂ ਕਰਦੇ ਹਨ। ਅਸੀਂ ਆਮ ਤੌਰ 'ਤੇ ਤੁਹਾਡੇ ਹੱਥ ਵਰਤਣ ਦੇ ਤਰੀਕੇ ਵਿੱਚ ਤਬਦੀਲੀਆਂ ਅਤੇ ਹੈਂਡ ਥੈਰੇਪੀ ਨਾਲ ਸ਼ੁਰੂ ਕਰਦੇ ਹਾਂ, ਤਾਂ ਜੋ ਚਿੜੇ ਹੋਏ ਟੈਂਡਨ ਸ਼ਾਂਤ ਹੋਣ ਅਤੇ ਟੈਂਡਨਾਂ ਉੱਤੇ ਭਾਰ ਘਟੇ। ਅੰਗੂਠੇ ਅਤੇ ਗੁੱਟ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਵਾਲਾ ਸਪਲਿੰਟ ਟੈਂਡਨਾਂ ਨੂੰ ਆਰਾਮ ਦੇ ਸਕਦਾ ਹੈ ਅਤੇ ਦਰਦ ਪੈਦਾ ਕਰ ਰਹੀ ਰਗੜ ਨੂੰ ਘਟਾ ਸਕਦਾ ਹੈ। ਅੱਗੇ ਵਧਣ ਤੋਂ ਪਹਿਲਾਂ ਇਹਨਾਂ ਕਦਮਾਂ ਨੂੰ ਪੂਰਾ ਮੌਕਾ ਦਿਓ, ਅਤੇ ਜੇ ਹਾਲਤ ਵਿੱਚ ਸੁਧਾਰ ਨਹੀਂ ਹੋ ਰਿਹਾ ਤਾਂ ਸਾਨੂੰ ਦੱਸੋ।
ਇਸ ਹਾਲਤ ਲਈ ਸਭ ਤੋਂ ਮਜ਼ਬੂਤ ਸਬੂਤ ਵਾਲਾ ਇਲਾਜ ਕੋਰਟੀਸੋਨ ਟੀਕਾ (ਸਟੀਰੌਇਡ ਟੀਕਾ) ਹੈ। ਕੋਰਟੀਸੋਨ ਸੋਜਸ਼ ਘਟਾਉਣ ਵਾਲੀ ਦਵਾਈ ਹੈ ਜੋ ਸੁਰੰਗ ਦੇ ਅੰਦਰਲੀ ਸੋਜ ਨੂੰ ਸ਼ਾਂਤ ਕਰਦੀ ਹੈ। ਇੱਕ ਟੀਕਾ 82% ਲੋਕਾਂ ਦੇ ਲੱਛਣਾਂ ਤੋਂ ਰਾਹਤ ਦਿੰਦਾ ਹੈ, ਅਤੇ ਉਨ੍ਹਾਂ ਵਿੱਚੋਂ ਅੱਧੇ ਤੋਂ ਵੱਧ ਘੱਟੋ-ਘੱਟ 12 ਮਹੀਨਿਆਂ ਤੱਕ ਲੱਛਣਾਂ ਤੋਂ ਮੁਕਤ ਰਹਿੰਦੇ ਹਨ। ਟੀਕਾ ਲਗਾਉਣ ਵੇਲੇ ਅਲਟਰਾਸਾਊਂਡ ਦੀ ਸੇਧ ਲੈਣ ਨਾਲ ਨਤੀਜਾ ਬਿਹਤਰ ਹੋ ਸਕਦਾ ਹੈ, ਅਤੇ ਇਸ ਨਾਲ ਸਾਨੂੰ ਇਸ ਗੱਲ ਦੀ ਪੁਸ਼ਟੀ ਕਰਨ ਵਿੱਚ ਵੀ ਮਦਦ ਮਿਲਦੀ ਹੈ ਕਿ ਅਸੀਂ ਬਿਲਕੁਲ ਕਿਸ ਚੀਜ਼ ਦਾ ਇਲਾਜ ਕਰ ਰਹੇ ਹਾਂ। ਟੀਕੇ ਦੇ ਨਾਲ ਗੁੱਟ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਵਾਲਾ ਸਪਲਿੰਟ ਵਰਤਣਾ ਸਿਰਫ਼ ਟੀਕੇ ਨਾਲੋਂ ਬਿਹਤਰ ਕੰਮ ਕਰਦਾ ਹੈ। ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਵਾਪਸ ਆ ਜਾਂਦੇ ਹਨ, ਤਾਂ ਦੂਜਾ ਟੀਕਾ ਫਿਰ ਵੀ ਇੱਕ ਠੀਕ ਵਿਕਲਪ ਹੈ, ਨਾ ਕਿ ਇਸ ਗੱਲ ਦੀ ਨਿਸ਼ਾਨੀ ਕਿ ਟੀਕੇ ਨਾਕਾਮ ਹੋ ਗਏ ਹਨ। ਜੇ ਤੁਹਾਨੂੰ ਸ਼ੂਗਰ (ਡਾਇਬਟੀਜ਼) ਹੈ, ਤਾਂ ਦੂਜੇ ਲੋਕਾਂ ਦੇ ਮੁਕਾਬਲੇ ਇੱਕ ਟੀਕੇ ਦੇ ਕਾਮਯਾਬ ਹੋਣ ਦੀ ਸੰਭਾਵਨਾ ਘੱਟ ਹੁੰਦੀ ਹੈ, ਪਰ ਹਰ ਅਗਲਾ ਟੀਕਾ ਪਿਛਲੇ ਟੀਕੇ ਜਿੰਨਾ ਹੀ ਅਸਰ ਕਰਦਾ ਰਹਿੰਦਾ ਹੈ।
ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਨੂੰ ਸਰਜਰੀ ਦੀ ਲੋੜ ਨਹੀਂ ਪਵੇਗੀ। ਅਸੀਂ ਇਸ ਬਾਰੇ ਉਦੋਂ ਵਿਚਾਰ ਕਰਦੇ ਹਾਂ ਜਦੋਂ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਇਲਾਜ ਨਾਲ ਕਾਫ਼ੀ ਸੁਧਾਰ ਨਹੀਂ ਹੋਇਆ, ਜਾਂ ਜਦੋਂ ਦਰਦ ਦੇ ਨਾਲ-ਨਾਲ ਅੰਗੂਠਾ ਅਟਕਦਾ ਅਤੇ ਫਸਦਾ ਵੀ ਹੈ, ਜੋ ਆਮ ਤੌਰ 'ਤੇ ਆਪਣੇ ਆਪ ਠੀਕ ਨਹੀਂ ਹੁੰਦਾ। ਓਪਰੇਸ਼ਨ ਸੁਰੰਗ ਦੀ ਤੰਗ ਛੱਤ ਨੂੰ ਰਿਲੀਜ਼ ਕਰ ਦਿੰਦਾ ਹੈ (release, ਕੱਟ ਕੇ ਖੋਲ੍ਹਣਾ) ਤਾਂ ਜੋ ਟੈਂਡਨ ਫਿਰ ਤੋਂ ਆਜ਼ਾਦੀ ਨਾਲ ਖਿਸਕ ਸਕਣ। ਇਹ ਇੱਕ ਛੋਟਾ ਓਪਰੇਸ਼ਨ ਹੈ, ਅਤੇ ਇਸ ਵਿੱਚ ਕੀ ਕੀਤਾ ਜਾਂਦਾ ਹੈ ਇਹ ਦੱਸਣ ਵਾਲਾ ਇਸ ਦਾ ਆਪਣਾ ਵੱਖਰਾ ਸਫ਼ਾ ਹੈ।
ਕੀ ਉਮੀਦ ਰੱਖੀਏ
ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਲਈ, ਇਹ ਹਾਲਤ ਆਪਣੇ ਆਪ ਛੇਤੀ ਗ਼ਾਇਬ ਨਹੀਂ ਹੁੰਦੀ। ਜਿਨ੍ਹਾਂ ਲੋਕਾਂ ਨੂੰ ਇਹ ਹੁੰਦੀ ਹੈ, ਜੇ ਕੁਝ ਨਾ ਕੀਤਾ ਜਾਵੇ ਤਾਂ ਉਨ੍ਹਾਂ ਵਿੱਚੋਂ ਜ਼ਿਆਦਾਤਰ ਨੂੰ ਇੱਕ ਸਾਲ ਬਾਅਦ ਵੀ ਲੱਛਣ ਰਹਿੰਦੇ ਹਨ, ਅਤੇ ਦਰਦ ਹੌਲੀ-ਹੌਲੀ ਘਟਣ ਦੀ ਬਜਾਏ ਆਮ ਤੌਰ 'ਤੇ ਵਰਤੋਂ ਨਾਲ ਭੜਕਦਾ ਹੈ। ਥੋੜ੍ਹੇ ਜਿਹੇ ਲੋਕਾਂ (ਲਗਭਗ ਤਿੰਨ ਵਿੱਚੋਂ ਇੱਕ) ਨੂੰ ਅਖ਼ੀਰ ਦੋ ਸਾਲਾਂ ਦੇ ਅੰਦਰ ਸਰਜਰੀ ਦੀ ਲੋੜ ਪਵੇਗੀ, ਅਤੇ ਜਿਨ੍ਹਾਂ ਨੂੰ ਇਸ ਦੀ ਲੋੜ ਪੈਂਦੀ ਹੈ ਉਨ੍ਹਾਂ ਵਿੱਚੋਂ ਜ਼ਿਆਦਾਤਰ ਪਹਿਲੇ ਸਾਲ ਦੇ ਅੰਦਰ ਹੀ ਉਸ ਮੋੜ 'ਤੇ ਪਹੁੰਚ ਜਾਂਦੇ ਹਨ।
ਇਲਾਜ ਨਾਲ ਨਤੀਜੇ ਚੰਗੇ ਹਨ, ਅਤੇ ਇਹ ਗੱਲ ਇਮਾਨਦਾਰੀ ਨਾਲ ਦੱਸੀ ਜਾ ਸਕਦੀ ਹੈ। ਇੱਕ ਕੋਰਟੀਸੋਨ ਟੀਕਾ 70% ਲੋਕਾਂ ਦੇ ਲੱਛਣ ਪੂਰੀ ਤਰ੍ਹਾਂ ਠੀਕ ਕਰ ਦਿੰਦਾ ਹੈ, ਅਤੇ ਹੋਰ 10% ਦੂਜੇ ਟੀਕੇ ਨਾਲ ਠੀਕ ਹੋ ਜਾਂਦੇ ਹਨ। ਕੁੱਲ ਮਿਲਾ ਕੇ, ਦੋ ਟੀਕਿਆਂ ਦੇ ਅੰਦਰ ਟੀਕੇ 73.4% ਵਾਰ ਕਾਮਯਾਬ ਹੁੰਦੇ ਹਨ। ਜਦੋਂ ਸਰਜਰੀ ਦੀ ਲੋੜ ਪੈਂਦੀ ਹੈ, ਤਾਂ ਇਹ ਚੰਗਾ ਕੰਮ ਕਰਦੀ ਹੈ: 88% ਲੋਕ ਬਾਅਦ ਵਿੱਚ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸੰਤੁਸ਼ਟ ਹੁੰਦੇ ਹਨ, ਅਤੇ ਓਪਰੇਸ਼ਨ 91% ਮਾਮਲਿਆਂ ਵਿੱਚ ਸਮੱਸਿਆ ਨੂੰ ਠੀਕ ਕਰ ਦਿੰਦਾ ਹੈ।
ਠੀਕ ਹੋਣ ਦਾ ਅਨੁਭਵ ਇਸ ਗੱਲ 'ਤੇ ਨਿਰਭਰ ਕਰਦਾ ਹੈ ਕਿ ਤੁਸੀਂ ਕਿਹੜਾ ਰਾਹ ਚੁਣਦੇ ਹੋ। ਟੀਕੇ ਤੋਂ ਬਾਅਦ, ਜਿਵੇਂ-ਜਿਵੇਂ ਸੁਰੰਗ ਦੇ ਅੰਦਰ ਦੀ ਸੋਜ ਸ਼ਾਂਤ ਹੁੰਦੀ ਹੈ, ਦੁਖਣ ਆਮ ਤੌਰ 'ਤੇ ਦਿਨਾਂ ਤੋਂ ਹਫ਼ਤਿਆਂ ਵਿੱਚ ਘਟ ਜਾਂਦਾ ਹੈ। ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਟੈਂਡਨ ਫਿਰ ਤੋਂ ਆਜ਼ਾਦੀ ਨਾਲ ਖਿਸਕਦੇ ਹਨ, ਅਤੇ ਆਮ ਤੌਰ 'ਤੇ ਖੁੱਲ੍ਹੇ ਤਰੀਕੇ ਨਾਲੋਂ ਦੂਰਬੀਨ ਵਾਲੇ (ਐਂਡੋਸਕੋਪਿਕ) ਤਰੀਕੇ ਨਾਲ ਸੁਧਾਰ ਛੇਤੀ ਆਉਂਦਾ ਹੈ। ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਹੈਂਡ ਥੈਰੇਪੀ ਐਕਸਟੈਂਡ ਰੀਹੈਬਿਲੀਟੇਸ਼ਨ (Extend Rehabilitation) ਵਿੱਚ ਰੂਬੀ ਡੂਲਨ (Ruby Doolan) ਨਾਲ ਹੁੰਦੀ ਹੈ। ਰੂਬੀ ਇੱਕ ਹੈਂਡ ਥੈਰੇਪਿਸਟ ਹੈ: ਉਹ ਤੁਹਾਡੀ ਥੈਰੇਪੀ ਦੀ ਅਗਵਾਈ ਕਰਦੀ ਹੈ ਅਤੇ ਜਿਸ ਵੀ ਸਪਲਿੰਟ ਦੀ ਲੋੜ ਹੋਵੇ ਉਹ ਬਣਾਉਂਦੀ ਹੈ।
ਕੁਝ ਗੱਲਾਂ ਪਹਿਲਾਂ ਤੋਂ ਜਾਣ ਲੈਣੀਆਂ ਚੰਗੀਆਂ ਹਨ। ਜੇ ਤੁਹਾਨੂੰ ਸ਼ੂਗਰ ਜਾਂ ਮੈਟਾਬੋਲਿਕ ਸਿੰਡਰੋਮ (metabolic syndrome, ਸਿਹਤ ਸਮੱਸਿਆਵਾਂ ਦਾ ਇੱਕ ਸਮੂਹ ਜਿਸ ਵਿੱਚ ਹਾਈ ਬਲੱਡ ਪ੍ਰੈਸ਼ਰ ਅਤੇ ਢਿੱਡ ਦੁਆਲੇ ਭਾਰ ਸ਼ਾਮਲ ਹਨ) ਹੈ, ਤਾਂ ਦੂਜੇ ਲੋਕਾਂ ਦੇ ਮੁਕਾਬਲੇ ਤੁਹਾਡੇ ਲਈ ਟੀਕਿਆਂ ਦੇ ਕਾਮਯਾਬ ਹੋਣ ਦੀ ਸੰਭਾਵਨਾ ਘੱਟ ਹੈ। ਤੁਸੀਂ ਇਸ ਹਾਲਤ ਬਾਰੇ ਕਿਵੇਂ ਸੋਚਦੇ ਹੋ, ਇਹ ਵੀ ਮਾਇਨੇ ਰੱਖਦਾ ਹੈ: ਜੋ ਲੋਕ ਸਭ ਤੋਂ ਬੁਰੇ ਦੀ ਉਮੀਦ ਕਰਦੇ ਹਨ ਉਹ ਆਮ ਤੌਰ 'ਤੇ ਵੱਧ ਦਰਦ ਅਤੇ ਘੱਟ ਕੰਮਕਾਜ ਦੱਸਦੇ ਹਨ, ਇਸ ਲਈ ਇਸ ਹਾਲਤ ਦੇ ਮਤਲਬ ਬਾਰੇ ਡਰਾਂ ਦੀ ਬਜਾਏ ਸਹੀ ਉਮੀਦਾਂ ਰੱਖਣਾ ਮਦਦਗਾਰ ਹੈ।
ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਠੀਕ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਰਾਤ ਨੂੰ ਤੁਹਾਡੀ ਨੀਂਦ ਖੋਲ੍ਹ ਦਿੰਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਡਾਕਟਰ ਨੂੰ ਕਦੋਂ ਮਿਲਣਾ ਚਾਹੀਦਾ ਹੈ
ਇਸ ਹਾਲਤ ਦੀਆਂ ਜ਼ਿਆਦਾਤਰ ਚੇਤਾਵਨੀ ਨਿਸ਼ਾਨੀਆਂ ਉੱਪਰ ਪਹਿਲੇ ਭਾਗ ਵਿੱਚ ਪਹਿਲਾਂ ਹੀ ਦੱਸੀਆਂ ਗਈਆਂ ਹਨ: ਦਰਦ ਜੋ ਠੀਕ ਨਹੀਂ ਹੋ ਰਿਹਾ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਿਹਾ ਹੈ, ਰਾਤ ਨੂੰ ਤੁਹਾਡੀ ਨੀਂਦ ਖੋਲ੍ਹ ਦਿੰਦਾ ਹੈ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦਾ ਹੈ। ਜੇ ਇਹਨਾਂ ਵਿੱਚੋਂ ਕੋਈ ਵੀ ਗੱਲ ਤੁਹਾਡੇ ਉੱਤੇ ਲਾਗੂ ਹੁੰਦੀ ਹੈ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਇੱਕ ਨਿਸ਼ਾਨੀ ਦਾ ਇੱਥੇ ਦੁਬਾਰਾ ਜ਼ਿਕਰ ਕਰਨਾ ਬਣਦਾ ਹੈ। ਜੇ ਦਰਦ ਦੇ ਨਾਲ-ਨਾਲ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਅਟਕਦਾ ਜਾਂ ਫਸਦਾ ਵੀ ਹੈ, ਤਾਂ ਜਿਸ ਵੀ ਡਾਕਟਰ ਨੂੰ ਮਿਲੋ ਉਸ ਨੂੰ ਦੱਸੋ। ਸਮੱਸਿਆ ਦਾ ਇਹ ਰੂਪ ਆਮ ਤੌਰ 'ਤੇ ਸਿਰਫ਼ ਆਰਾਮ ਜਾਂ ਸਪਲਿੰਟ ਨਾਲ ਠੀਕ ਨਹੀਂ ਹੁੰਦਾ, ਅਤੇ ਇਸ ਨਾਲ ਇਹ ਬਦਲ ਜਾਂਦਾ ਹੈ ਕਿ ਕਿਹੜੇ ਇਲਾਜ ਚੰਗਾ ਕੰਮ ਕਰਦੇ ਹਨ, ਇਸ ਲਈ ਇਹ ਦੇਖਣ ਲਈ ਉਡੀਕ ਕਰਨ ਦੀ ਬਜਾਏ ਕਿ ਕੀ ਇਹ ਆਪਣੇ ਆਪ ਘਟ ਜਾਂਦਾ ਹੈ, ਛੇਤੀ ਦੱਸਣਾ ਫ਼ਾਇਦੇਮੰਦ ਹੈ।
ਇਹੀ ਸਲਾਹ ਉਦੋਂ ਵੀ ਲਾਗੂ ਹੁੰਦੀ ਹੈ ਜੇ ਦਰਦ ਆਮ ਥਾਂ ਤੋਂ ਥੋੜ੍ਹਾ ਹਟ ਕੇ ਹੈ, ਉਦਾਹਰਨ ਲਈ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਵਿੱਚ ਹੋਰ ਉੱਪਰ ਜਾਂ ਅੰਗੂਠੇ ਦੇ ਮੁੱਢ ਉੱਤੇ। ਕਈ ਹੋਰ ਹਾਲਤਾਂ ਇਸ ਵਰਗੀਆਂ ਲੱਗ ਸਕਦੀਆਂ ਹਨ, ਅਤੇ ਉਹਨਾਂ ਉੱਤੇ ਵੱਖਰੇ ਇਲਾਜ ਅਸਰ ਕਰਦੇ ਹਨ। ਧਿਆਨ ਨਾਲ ਕੀਤੀ ਜਾਂਚ ਨਾਲ ਪਤਾ ਲੱਗ ਜਾਂਦਾ ਹੈ ਕਿ ਤੁਹਾਨੂੰ ਕਿਹੜੀ ਹਾਲਤ ਹੈ।
ਜੇ ਤੁਹਾਡੇ ਹੱਥ ਜਾਂ ਬਾਂਹ ਵਿੱਚ ਗਰਮੀ, ਲਾਲੀ, ਸੋਜ ਅਤੇ ਦਰਦ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਜਾਂ ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ ਫਿੱਕੀਆਂ, ਠੰਢੀਆਂ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੀਆਂ ਪੈ ਜਾਣ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਵਿਸਥਾਰ ਵਿੱਚ
Advanced reading: the deeper science (optional)
ਇਹ ਹਿੱਸਾ ਤੁਹਾਡੇ ਆਪਣੇ ਇਲਾਜ ਦੇ ਫ਼ੈਸਲਿਆਂ ਲਈ ਲੋੜ ਤੋਂ ਵੱਧ ਡੂੰਘਾਈ ਵਿੱਚ ਜਾਂਦਾ ਹੈ। ਡੀ ਕੁਏਰਵੇਨ ਟੈਨੋਸਾਈਨੋਵਾਈਟਿਸ ਬਾਰੇ ਵਾਧੂ ਪੜ੍ਹਨਾ ਇਸ ਲਈ ਫ਼ਾਇਦੇਮੰਦ ਹੈ ਕਿਉਂਕਿ ਇੱਕ ਛੋਟਾ ਬਣਤਰੀ ਫ਼ਰਕ ਇੱਕ ਅਜਿਹੇ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਦੀ ਜ਼ਿਆਦਾਤਰ ਨਾਖ਼ੁਸ਼ੀ ਦਾ ਕਾਰਨ ਬਣਦਾ ਹੈ ਜੋ ਹੋਰ ਤਾਂ ਭਰੋਸੇਯੋਗ ਹੈ, ਅਤੇ ਕਿਉਂਕਿ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲਾ ਸਭ ਤੋਂ ਵਧੀਆ ਨਤੀਜਾ ਦੋ ਇਲਾਜਾਂ ਵਿੱਚੋਂ ਇੱਕ ਚੁਣਨ ਨਾਲ ਨਹੀਂ, ਸਗੋਂ ਦੋਵਾਂ ਨੂੰ ਇਕੱਠੇ ਕਰਨ ਨਾਲ ਮਿਲਦਾ ਹੈ।
ਦੋਵੇਂ ਇਲਾਜ ਇਕੱਠੇ, ਕਿਸੇ ਇੱਕ ਨਾਲੋਂ ਬਿਹਤਰ
ਪਹਿਲਾ ਡੋਰਸਲ ਕੰਪਾਰਟਮੈਂਟ (first dorsal compartment) ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਇੱਕ ਸੁਰੰਗ ਵਿੱਚ ਦੋ ਟੈਂਡਨਾਂ ਨੂੰ ਰੱਖਦਾ ਹੈ। ਇਲਾਜ ਦਾ ਮਕਸਦ ਉਸ ਸੁਰੰਗ ਵਿੱਚ ਸੋਜਸ਼ ਨੂੰ ਸ਼ਾਂਤ ਕਰਨਾ ਅਤੇ ਉਸ ਵਿੱਚੋਂ ਲੰਘਣ ਵਾਲੇ ਭਾਰ ਨੂੰ ਘਟਾਉਣਾ ਹੈ।
823 ਮਰੀਜ਼ਾਂ ਦੇ ਇੱਕ ਨੈੱਟਵਰਕ ਮੈਟਾ-ਐਨਾਲਿਸਿਸ (network meta-analysis, ਕਈ ਅਧਿਐਨਾਂ ਦਾ ਸਾਂਝਾ ਵਿਸ਼ਲੇਸ਼ਣ) ਦਾ ਸਿੱਟਾ ਸੀ ਕਿ ਥੋੜ੍ਹੇ ਸਮੇਂ ਲਈ ਜੋੜ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਦੇ ਨਾਲ ਕੋਰਟੀਕੋਸਟੀਰੌਇਡ ਟੀਕਾ ਮੁੱਖ ਅਤੇ ਅਸਰਦਾਰ ਇਲਾਜ ਬਣਿਆ ਹੋਇਆ ਹੈ, ਅਤੇ ਸਰੀਰ ਦੇ ਬਾਹਰੋਂ ਦਿੱਤੀ ਜਾਣ ਵਾਲੀ ਸ਼ੌਕਵੇਵ ਥੈਰੇਪੀ (extracorporeal shockwave therapy) ਇੱਕ ਦੂਜੇ ਦਰਜੇ ਦਾ ਵਿਕਲਪ ਹੈ [1]। ਹਿੱਸਿਆਂ ਨੂੰ ਸਿੱਧੇ ਤੌਰ 'ਤੇ ਦੇਖੀਏ ਤਾਂ, ਸਪਲਿੰਟ (orthosis) ਅਤੇ ਕੋਰਟੀਕੋਸਟੀਰੌਇਡ ਟੀਕੇ ਨੂੰ ਮਿਲਾ ਕੇ ਕੀਤੇ ਇਲਾਜ, ਦੋਵਾਂ ਵਿੱਚੋਂ ਕਿਸੇ ਇੱਕ ਇਲਾਜ ਨਾਲੋਂ ਵੱਧ ਅਸਰਦਾਰ ਹਨ [2]।
ਇਹ "ਪਹਿਲਾਂ ਸਪਲਿੰਟ ਅਜ਼ਮਾਓ, ਜੇ ਉਹ ਕੰਮ ਨਾ ਕਰੇ ਤਾਂ ਟੀਕਾ" ਨਾਲੋਂ ਵੱਧ ਸਪਸ਼ਟ ਹਦਾਇਤ ਹੈ। ਸਬੂਤ ਦੋਵਾਂ ਨੂੰ ਇਕੱਠੇ ਕਰਨ ਦੀ ਹਮਾਇਤ ਕਰਦੇ ਹਨ, ਜਿਸ ਵਿੱਚ ਟੀਕੇ ਤੋਂ ਬਾਅਦ ਇੱਕ ਤੈਅ ਥੋੜ੍ਹੇ ਸਮੇਂ ਲਈ ਸਪਲਿੰਟ ਪਾਇਆ ਜਾਂਦਾ ਹੈ।
ਦੂਜਾ ਟੀਕਾ ਲਗਵਾਉਣਾ ਹਾਲੇ ਵੀ ਫ਼ਾਇਦੇਮੰਦ ਹੈ
ਜਦੋਂ ਲੱਛਣ ਵਾਪਸ ਆ ਜਾਂਦੇ ਹਨ, ਤਾਂ ਝੱਟ ਇਹ ਸਿੱਟਾ ਕੱਢ ਲਿਆ ਜਾਂਦਾ ਹੈ ਕਿ ਟੀਕੇ ਨਾਕਾਮ ਹੋ ਗਏ ਹਨ ਅਤੇ ਸਰਜਰੀ ਵੱਲ ਵਧਿਆ ਜਾਂਦਾ ਹੈ। ਪਰ ਮਰੀਜ਼ਾਂ ਦੇ ਇੱਕ ਵੱਡੇ ਸਮੂਹ ਦੇ ਅੰਕੜੇ ਕੁਝ ਹੋਰ ਦੱਸਦੇ ਹਨ: ਹਾਲਾਂਕਿ ਕਈ ਟੀਕਿਆਂ ਨਾਲ ਕਾਮਯਾਬੀ ਦੀ ਦਰ ਘਟਦੀ ਹੈ, ਦੁਬਾਰਾ ਲਾਏ ਟੀਕਿਆਂ ਦੀ ਕਾਮਯਾਬੀ ਦੀ ਦਰ ਉੱਚੀ ਹੁੰਦੀ ਹੈ ਅਤੇ ਇਹ ਇੱਕ ਵਿਹਾਰਕ ਇਲਾਜ ਵਿਕਲਪ ਹਨ [3]।
ਦੁਹਰਾਉਣ ਨਾਲ ਕਾਮਯਾਬੀ ਦਾ ਘਟਣਾ ਉਮੀਦ ਅਨੁਸਾਰ ਹੈ। ਪਰ ਘੱਟ ਕਾਮਯਾਬੀ ਦਰ ਦਾ ਮਤਲਬ ਬੇਕਾਰ ਹੋਣਾ ਨਹੀਂ ਹੈ, ਅਤੇ ਦੂਜਾ ਟੀਕਾ ਸਿਰਫ਼ ਸਮਾਂ ਟਾਲਣ ਦਾ ਤਰੀਕਾ ਨਹੀਂ, ਸਗੋਂ ਇੱਕ ਠੀਕ ਕਦਮ ਬਣਿਆ ਰਹਿੰਦਾ ਹੈ।
ਉਹ ਬਣਤਰੀ ਫ਼ਰਕ ਜੋ ਸਰਜਰੀ ਤੋਂ ਹੋਣ ਵਾਲੀ ਜ਼ਿਆਦਾਤਰ ਨਿਰਾਸ਼ਾ ਦੀ ਵਿਆਖਿਆ ਕਰਦਾ ਹੈ
ਪਹਿਲੇ ਡੋਰਸਲ ਕੰਪਾਰਟਮੈਂਟ ਦੀ ਰਿਲੀਜ਼ ਅਸਰਦਾਰ ਹੈ, ਅਤੇ ਜਿੱਥੇ ਇਹ ਨਿਰਾਸ਼ ਕਰਦੀ ਹੈ ਉੱਥੇ ਆਮ ਤੌਰ 'ਤੇ ਕੋਈ ਖ਼ਾਸ ਕਾਰਨ ਹੁੰਦਾ ਹੈ। ਨਾਖ਼ੁਸ਼ੀ ਅਧੂਰੀ ਰਿਲੀਜ਼, ਟੈਂਡਨ ਦੇ ਆਪਣੀ ਥਾਂ ਤੋਂ ਅੱਧਾ ਖਿਸਕਣ (subluxation), ਨਸ ਨੂੰ ਸੱਟ, ਜਾਂ ਸਿਰਫ਼ ਠੀਕ ਹੋਣ ਵਿੱਚ ਲੱਗਣ ਵਾਲੇ ਸਮੇਂ ਕਾਰਨ ਹੋ ਸਕਦੀ ਹੈ, ਅਤੇ ਐਕਸਟੈਂਸਰ ਪੌਲੀਸਿਸ ਬ੍ਰੇਵਿਸ (extensor pollicis brevis) ਦਾ ਅਣਪਛਾਤਾ ਅਤੇ ਨਾ ਖੋਲ੍ਹਿਆ ਗਿਆ ਵੱਖਰਾ ਗਿਲਾਫ਼ ਨਾਖ਼ੁਸ਼ੀ ਦਾ ਇੱਕ ਵੱਖਰਾ ਸਰੋਤ ਹੈ [4]।
ਇਸ ਨੂੰ ਖੋਲ੍ਹ ਕੇ ਸਮਝਣਾ ਜ਼ਰੂਰੀ ਹੈ ਕਿਉਂਕਿ ਇਸ ਹਿੱਸੇ ਵਿੱਚ ਇਹੀ ਸਭ ਤੋਂ ਲਾਭਦਾਇਕ ਤੱਥ ਹੈ। ਲੋਕਾਂ ਦੇ ਇੱਕ ਕਾਫ਼ੀ ਵੱਡੇ ਹਿੱਸੇ ਵਿੱਚ ਇਹ ਕੰਪਾਰਟਮੈਂਟ ਇੱਕ ਸੁਰੰਗ ਨਹੀਂ ਸਗੋਂ ਦੋ ਹੁੰਦਾ ਹੈ, ਜਿਸ ਵਿੱਚ ਐਕਸਟੈਂਸਰ ਪੌਲੀਸਿਸ ਬ੍ਰੇਵਿਸ ਟੈਂਡਨ ਦੂਜੇ ਟੈਂਡਨ ਦੇ ਨਾਲ-ਨਾਲ ਆਪਣੇ ਵੱਖਰੇ ਗਿਲਾਫ਼ ਵਿੱਚ ਚੱਲਦਾ ਹੈ। ਜੋ ਰਿਲੀਜ਼ ਮੁੱਖ ਕੰਪਾਰਟਮੈਂਟ ਨੂੰ ਖੋਲ੍ਹ ਕੇ ਰੁਕ ਜਾਂਦੀ ਹੈ, ਉਹ ਦੂਜੇ ਗਿਲਾਫ਼ ਨੂੰ ਬੰਦ ਹੀ ਛੱਡ ਦਿੰਦੀ ਹੈ, ਅਤੇ ਉਸ ਦੇ ਅੰਦਰਲਾ ਟੈਂਡਨ ਦੱਬਿਆ ਹੀ ਰਹਿੰਦਾ ਹੈ। ਗੁੱਟ ਖੋਲ੍ਹਿਆ ਜਾਂਦਾ ਹੈ, ਓਪਰੇਸ਼ਨ ਦੱਸੇ ਅਨੁਸਾਰ ਪੂਰਾ ਕੀਤਾ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਲੱਛਣ ਫਿਰ ਵੀ ਬਣੇ ਰਹਿੰਦੇ ਹਨ।
ਇਸੇ ਕਰਕੇ ਦੱਸੇ ਗਏ ਦੂਜੇ ਦੋ ਕਾਰਨ ਵੀ ਅਹਿਮ ਹਨ: ਬਹੁਤ ਜ਼ਿਆਦਾ ਖੋਲ੍ਹਣ ਨਾਲ ਗੁੱਟ ਹਿਲਾਉਣ ਵੇਲੇ ਟੈਂਡਨ ਆਪਣੀ ਖਾਂਚ ਵਿੱਚੋਂ ਅੱਧੇ ਬਾਹਰ ਖਿਸਕ ਸਕਦੇ ਹਨ, ਜਿਸ ਨਾਲ ਦਰਦ ਵਾਲਾ ਕੜੱਕ ਵਾਲਾ ਝਟਕਾ ਲੱਗਦਾ ਹੈ, ਅਤੇ ਰੇਡੀਅਲ ਨਸ ਦੀ ਉੱਪਰਲੀ ਸ਼ਾਖ਼ਾ ਓਪਰੇਸ਼ਨ ਵਾਲੀ ਥਾਂ ਦੇ ਬਿਲਕੁਲ ਉੱਪਰੋਂ ਲੰਘਦੀ ਹੈ। ਕੰਪਾਰਟਮੈਂਟ ਨੂੰ ਪੂਰੀ ਤਰ੍ਹਾਂ ਖੋਲ੍ਹਣਾ ਜ਼ਰੂਰੀ ਹੈ ਪਰ ਹੱਦੋਂ ਵੱਧ ਨਹੀਂ, ਅਤੇ ਰਸਤੇ ਵਿੱਚ ਇੱਕ ਨਸ ਵੀ ਹੁੰਦੀ ਹੈ, ਇਸੇ ਲਈ ਦੇਖਣ ਵਿੱਚ ਛੋਟੇ ਜਿਹੇ ਇਸ ਓਪਰੇਸ਼ਨ ਨੂੰ ਵੀ ਕਿਸੇ ਵੱਡੇ ਓਪਰੇਸ਼ਨ ਜਿੰਨੀ ਹੀ ਸਾਵਧਾਨੀ ਚਾਹੀਦੀ ਹੈ।
ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਦਾ ਹਰ ਦਰਦ ਡੀ ਕੁਏਰਵੇਨ ਨਹੀਂ ਹੁੰਦਾ
ਇਸ ਥਾਂ ਦੇ ਦਰਦ ਦੇ ਹੋਰ ਸੰਭਾਵੀ ਕਾਰਨ ਜਾਣਨੇ ਚੰਗੇ ਹਨ, ਕਿਉਂਕਿ ਉਹਨਾਂ ਦੇ ਇਲਾਜ ਵੱਖਰੇ ਹੁੰਦੇ ਹਨ: ਅੰਗੂਠੇ ਦੇ ਮੁੱਢ ਵਿੱਚ ਗਠੀਆ (ਆਰਥਰਾਈਟਿਸ), ਬਾਂਹ ਵਿੱਚ ਕੁਝ ਸੈਂਟੀਮੀਟਰ ਹੋਰ ਉੱਪਰ ਇੰਟਰਸੈਕਸ਼ਨ ਸਿੰਡਰੋਮ (intersection syndrome), ਅਤੇ ਰੇਡੀਅਲ ਨਸ ਦਾ ਚਿੜ ਜਾਣਾ, ਇਹ ਸਾਰੇ ਮਿਲਦੀ-ਜੁਲਦੀ ਥਾਂ ਵਿੱਚ ਦਰਦ ਪੈਦਾ ਕਰ ਸਕਦੇ ਹਨ। ਕੰਪਾਰਟਮੈਂਟ ਦੇ ਬਿਲਕੁਲ ਉੱਪਰ ਇੱਕ ਥਾਂ 'ਤੇ ਸੀਮਤ ਦੁਖਣਾ, ਅਤੇ ਅੰਗੂਠੇ ਨੂੰ ਹਥੇਲੀ ਵਿੱਚ ਦਬਾ ਕੇ ਗੁੱਟ ਨੂੰ ਛੋਟੀ ਉਂਗਲ ਵਾਲੇ ਪਾਸੇ ਮੋੜਨ (ulnar deviation) ਨਾਲ ਦਰਦ ਦਾ ਦੁਬਾਰਾ ਪੈਦਾ ਹੋਣਾ, ਇਹੀ ਗੱਲਾਂ ਗੁਆਂਢੀ ਹਿੱਸਿਆਂ ਦੀ ਬਜਾਏ ਟੈਂਡਨ ਦੇ ਗਿਲਾਫ਼ ਵੱਲ ਇਸ਼ਾਰਾ ਕਰਦੀਆਂ ਹਨ।
ਹਵਾਲੇ
[1] Chong HH, Pradhan A, Dhingra M, Liong W, Hau MY, Shah R. Advancements in de Quervain tenosynovitis management: a comprehensive network meta-analysis of randomized controlled trials. J Hand Surg Am. 2024;49(6):557-69. https://doi.org/10.1016/j.jhsa.2024.03.003
[2] Cavaleri R, Schabrun SM, Te M, Chipchase LS. Hand therapy versus corticosteroid injections in the treatment of de Quervain's disease: a systematic review and meta-analysis. J Hand Ther. 2016;29(1):3-11. https://doi.org/10.1016/j.jht.2015.10.004
[3] Hassan K, Sohn A, Shi L, Lee M, Wolf JM. De Quervain tenosynovitis: an evaluation of the epidemiology and utility of multiple injections using a national database. J Hand Surg Am. 2022;47(3):284.e1-284.e6. https://doi.org/10.1016/j.jhsa.2021.04.018
[4] Rogozinski B, Lourie GM. Dissatisfaction after first dorsal compartment release for de Quervain tendinopathy. J Hand Surg Am. 2016;41(1):117-9. https://doi.org/10.1016/j.jhsa.2015.09.003
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Anatomy and Diagnosis
- Anatomical variations in the first extensor compartment are clinically relevant to the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- Wrist radiography does not influence the management of patients presenting with de Quervain tendinopathy [6].
- The tethered thumb sign is a clinical maneuver that supports the diagnosis of de Quervain tenosynovitis and assists in determining an effective treatment algorithm [12].
- Ultrasound can be used as a diagnostic tool in the management of de Quervain’s disease [18].
Non-Operative Treatment
- Corticosteroid injection is the only available nonsurgical treatment that can potentially modify the course of de Quervain's tenosynovitis and is the preferred initial treatment [2].
- Corticosteroid injection with a short duration of immobilization remains the primary and effective treatment for de Quervain tenosynovitis [28].
- Corticosteroid injections lead to treatment success 73.4% of the time within 2 injections [22].
- Although the success rate for the treatment of De Quervain's tenosynovitis decreases with multiple injections, repeat injections have a high rate of success and are a viable clinical option [46].
- Corticosteroid injection for De Quervain tenosynovitis is not as effective in patients with metabolic syndrome compared with age- and sex-matched controls in terms of functional outcomes and treatment failure [5].
- Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients [40].
- The effectiveness of each additional corticosteroid injection does not appear to diminish in patients with diabetes mellitus [40].
- Ultrasound-guided triamcinolone injection should be considered to improve the treatment outcome for de Quervain's disease [18].
Operative Treatment
- Surgical release of De Quervain's tenosynovitis remains the gold standard treatment [10].
- Surgical intervention is effective as definitive therapy for de Quervain's tenosynovitis, with a cure rate of 91% and 88% of patients indicating full satisfaction [11].
- The release of the first extensor compartment for refractory de Quervain's disease results in good clinical outcomes with minimal morbidity [24].
- Longitudinal incision offers the advantage of easy identification of the compartment, more complete releases of tendon sheath and peritendinous adhesions, and less risk of palmar subluxation of tendons [10].
- The longitudinal incision for release of the first extensor compartment is a safe and effective technique that provides good exposure, protects vital structures, prevents possible tendon subluxation in the postoperative period, and is cosmetically acceptable [17].
- Endoscopic release for de Quervain's tenosynovitis seems to provide earlier improvement after surgery, with fewer superficial radial nerve complications and greater scar satisfaction, when compared with open release [33].
- One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures [31].
- Endoscopic release of the extensor compartment is an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time [41].
- Pulley reconstruction should be considered part of the surgical treatment for de Quervain tenosynovitis and gives satisfactory medium-term results [4].
Prognosis and Patient Factors
- Patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management [7].
- Patients who scored lower than 40 for physical function or higher than 60 for pain interference had significantly increased odds of eventually undergoing surgical release for de Quervain tenosynovitis [34].
- The failure of an operation in De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignoring of another syndrome in the proximity [13].
- Addressing misconceptions about de Quervain's tenosynovitis regarding consequences for patients and symptom duration allows patients to make informed decisions about treatment [9].
Anatomy & Pathophysiology
Anatomical Variations
- The first dorsal compartment of the wrist exhibits immense anatomical variation, including commonly found supernumerary tendons or tendon slips [107].
- Variation in tendon insertion is present in the population of the first dorsal compartment [107].
- Septa or aberrant compartments are present in the first dorsal compartment [107].
- Bilateral variations are present in the population regarding the anatomy of the first dorsal compartment [107].
- The superficial branch of the radial nerve is expected to be encountered in more than 50% of patients undergoing surgery for De Quervain's tenosynovitis [94].
Pathophysiology
- De Quervain's syndrome is defined as a condition where the abductor pollicis longus and extensor pollicis brevis tendons in the first dorsal compartment become inflamed through friction within a tight osteoligamentous tunnel [3].
- Compromised blood flow and nutrition in the first dorsal compartment lead to the development of adhesions and tendon stenosis [3].
- De Quervain's syndrome may involve myxoid degeneration, defined as a degenerative process where connective tissues are replaced by a gelatinous or mucoid substance [3].
- The pathophysiology of De Quervain's disease does not involve inflammation, with histopathological examination showing predominant degenerative changes such as myxoid degeneration and fibrocartilagenous metaplasia [38].
- De Quervain's tenosynovitis is caused by impaired gliding of the abductor pollicis longus and extensor pollicis brevis tendons [38].
- Impaired gliding in De Quervain's tenosynovitis is most probably caused by thickening of the extensor retinaculum of the wrist [38].
- De Quervain's syndrome may not be an isolated pathology and may be associated with trauma, extensor carpi ulnaris involvement, ligament instability, or repetitive strain [3].
- Operative treatment for distal radius fractures confers a slightly greater risk of developing De Quervain tenosynovitis within 1 year of injury or surgery [105].
Clinical Presentation & Assessment
- De Quervain's tenosynovitis is characterized by pain, tenderness, and swelling over the thumb side of the wrist at the radial styloid process [38].
- The condition is especially associated with sideward movements of the wrist and often leads to impairment of thumb function [38].
- The tethered thumb sign is a clinical maneuver that can support the diagnosis of De Quervain tenosynovitis and assist in determining an effective treatment algorithm [12].
- Subjects with stenosing tenosynovitis demonstrate a significant decrease in maximum velocity in slow fist tasks [81].
- In vivo extensor pollicis brevis tendon excursion measures have been quantified, and wrist position has been found to have an influence on excursion [73].
- The proportion of wrists with a positive extensor pollicis brevis entrapment test was significantly higher among those with two compartments (18 of 22) than among those with one compartment (0 of 4) [97].
Etiology & Risk Factors
- Women are more affected by De Quervain tenosynovitis than men, potentially due to manual work such as housekeeping activities and child rearing influencing first compartment dynamics [72].
- Training intensity is a major factor in determining De Quervain disease in volleyball players, with patients in the higher intensity group showing a mean training time quotient of 155 compared to 74 in the lower intensity group [72].
- The close association of work and repetitive trauma with De Quervain’s disease has been observed, although the exact relationship is controversial [21].
- Recent studies have disputed the view that repetitive work is causative of De Quervain’s disease, with one review of 100 patients finding no increased incidence in the dominant hand [21].
- A study of workers in a car plant reported 544 cases of tenosynovitis but only 2 cases of De Quervain’s disease [21].
- Repetitive work is less contentious as a factor in aggravating symptoms, as tendon movement within a stenosed sheath during activity logically causes pain [21].
- The process of tendon movement within a stenosed sheath may cause tendon damage through wear and tear, potentially leading to tendon rupture [21].
Complications & Associated Pathology
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has never been reported in the literature prior to the 2006 case report [21].
- Volar subluxation of the tendons of the first dorsal compartment can occur after surgery for De Quervain's stenosing tenosynovitis [48].
- Volar tendon subluxation after De Quervain's release can be treated with a distally based flap of the brachioradialis tendon to prevent tendon prolapse [48].
- Symptomatic palmar tendon subluxation after surgical release for De Quervain's disease can be avoided by leaving a palmarly based flap of extensor retinaculum [15].
- Dorsal tendon dislocation after De Quervain's release can occur if the patient overstresses the wrist through forceful extension [80].
- Repeat provocative testing for volar tendon subluxation following De Quervain’s release revealed volar tendon translation with wrist flexion, with no pain reported [85].
- Osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, with correct diagnosis often requiring histological examination when clinical presentation and X-rays are not typical [45].
Classification
Anatomical Variations and Subcompartmentalization
- The prevalence of a septated first dorsal compartment is considerably higher than previously reported, most notably in patients with De Quervain tenosynovitis [52].
- In a prospective study of 87 wrists, 22 of 30 patients (73%) who failed non-operative treatment and underwent operative release were found to have a separate compartment for the extensor pollicis brevis [55].
- The prevalence of a separate compartment for the extensor pollicis brevis in patients failing non-operative treatment is significantly higher than that in the general population, as shown in anatomical studies of cadavers [55].
- The persistence of an intracompartmental septum between the abductor pollicis longus and extensor pollicis brevis tendons has been described in a mean 43% of wrists in cadaveric studies, with a wide variation ranging from 20 to 75% [39].
- When the extensor pollicis brevis tendon resides in a subcompartment, it is likely to do so particularly in patients with de Quervain's disease [53].
- Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides important information about anatomic variations within the first extensor compartment [50].
- The presence of an intracompartmental septum detected by ultrasound is associated with the failure of ultrasound-guided steroid injection in de Quervain’s syndrome [39].
Diagnostic Mimics and Associated Pathologies
- Extensor pollicis longus tenosynovitis caused by the extensor pollicis longus's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease [30].
- An osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, with correct diagnosis often requiring histological examination when clinical presentation and X-rays are not typical [45].
- A hemangioma of the extensor pollicis brevis in the first dorsal compartment is an unusual cause of bilateral de Quervain's disease [14].
- De Quervain’s syndrome may not be an isolated pathology, with potential associations to trauma, extensor carpi ulnaris involvement, ligament instability, and repetitive strain [3].
- Failure of surgical treatment in De Quervain tenosynovitis can be attributed to anatomical variations, the involvement of the radial superficial nerve, and the ignorance of another syndrome in the proximity [13].
- The complexities of de Quervain's tendinitis and the diagnosis and treatment of associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in working women [8].
Clinical Presentation and Physical Examination
- Triggering or locking in extension is an uncommon symptom in de Quervain’s stenosing tenosynovitis, with a prevalence of 1.3% based on a review of 827 consecutive patients [20].
- A new test for evaluating the first extensor compartment is a useful clinical tool in the diagnosis of De Quervain's tenosynovitis [36].
- Ultrasound can be used as a diagnostic tool in the management of de Quervain’s disease, in addition to improving treatment outcomes [18].
Epidemiology and Risk Factors
- In a young, active population, the unadjusted incidence rate of de Quervain’s tenosynovitis was 0.94 per 1000 person-years [54].
- The adjusted incidence rate ratio for females compared to male patients was 4.45 (95% CI 4.28, 4.62) when controlling for race, age, service, and rank [54].
- The highest incidence rate of de Quervain’s tenosynovitis was seen in the ≥40-year-old group, with an incidence rate of 1.37 per 1000 person-years [54].
- The adjusted incidence rate ratio for the ≥40-year-old group compared to the <20-year-old group was 3.65 (95% CI 3.26, 4.09) [54].
- Non-white race is a risk factor for de Quervain’s tenosynovitis, with an adjusted incidence rate ratio of 1.31 (95% CI 1.21, 1.42) for black race and 1.17 (95% CI 1.05, 1.25) for others compared to white race [54].
- De Quervain’s syndrome affects around 1.3% of women and 0.5% of men in a population of adults of working age [39].
Pathophysiology
- De Quervain’s syndrome is defined as a condition where the abductor pollicis longus and extensor pollicis brevis tendons in the first dorsal compartment become inflamed through friction, leading to compromised blood flow, nutrition, adhesions, and tendon stenosis [3].
- De Quervain’s syndrome may represent a myxoid degeneration, defined as a degenerative process in which connective tissues are replaced by a gelatinous or mucoid substance [3].
- The role of repetitive work in the causation of de Quervain’s disease is controversial, with some studies disputing it as a primary cause while acknowledging it may aggravate symptoms [21].
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has never been reported in the literature prior to the 2006 report [21].
Clinical Presentation
Symptoms and Signs
- Patients typically complain of soreness and tenderness on the radial side of the distal radius that is exacerbated by ulnar deviation of the thumb [59].
- Symptoms are also exacerbated by a strong grasp combined with flexion and radial deviation of the wrist or by a firm pinching together of the index finger and thumb [59].
- Physical examination reveals tenderness and swelling directly over the first dorsal compartment [59].
Diagnostic Testing
- De Quervain disease is diagnosed clinically and no imaging studies are required [64].
- Wrist radiography does not influence management of patients presenting with de Quervain tendinopathy [6].
- In a study of 200 patients, no radiographic findings altered the course of treatment in patients with isolated de Quervain's tenosynovitis [62].
- Wrist imaging is required only in the presence of associated processes that may need to be evaluated, such as previous distal radius or scaphoid fracture, arthritis of the thumb, and instability of the wrist [64].
- Ultrasound can be useful as a diagnostic tool in the management of de Quervain’s disease [18].
- Ultrasound is a worthwhile preoperative investigation in case of de Quervain's disease [51].
- The wrist hyperflexion and abduction of the thumb (WHAT) test is a more specific and sensitive test to diagnose de Quervain tenosynovitis than the Eichhoff’s Test [59].
- Finkelstein's test is superior to Eichhoff's test in the investigation of de Quervain's disease [63].
- A new clinical maneuver, the tethered thumb sign, can support the diagnosis of de Quervain tenosynovitis and assist in determining an effective treatment algorithm [12].
Differential Diagnosis and Mimics
- Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease [30].
- Congenital synostosis between the scaphoid and the trapezium can cause tenosynovitis simulating de Quervain's disease [43].
- The failure of surgical treatment in De Quervain tenosynovitis can be due to anatomical variations, the involvement of the radial superficial nerve, and the ignoring of another syndrome in the proximity [13].
- In cases with symptoms of de Quervain's syndrome where the constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised [27].
Patient Factors and Perception
- Providers should remain cognizant that patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management [7].
- Most informed patients initially elect symptomatic treatment for de Quervain's disease, and most experience symptom resolution within one year [32].
- More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression [25].
- Addressing misconceptions about de Quervain's tenosynovitis in terms of the consequences for patients and how long their symptoms will last should allow patients to make informed decisions about the treatment that best matches their values [9].
Investigations
Clinical Examination
- Finkelstein's test is described as a descriptive error that can produce a false positive [16].
- A staged description of the Finkelstein test has been proposed to address diagnostic accuracy issues [16].
- A new clinical test for evaluating the first extensor compartment is a useful tool in the diagnosis of De Quervain's tenosynovitis [36].
- In cases where symptoms suggest de Quervain's syndrome but constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised [27].
Imaging
- Deferring routine wrist radiography does not affect the management of de Quervain tendinopathy patients [6].
- Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides information about anatomic variations within the first extensor compartment [50].
- Ultrasound is a worthwhile preoperative investigation in cases of de Quervain's disease [51].
- Radial styloid abnormalities do not affect the outcome of management for de Quervain's disease [19].
- An osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, and correct diagnosis may require histological examination when clinical presentation and X-rays are atypical [45].
- Congenital synostosis between the scaphoid and the trapezium can cause tenosynovitis that simulates de Quervain's disease [43].
- Extensor pollicis longus tenosynovitis caused by an unusual course through the first extensor compartment is a rare condition that mimics de Quervain’s disease [30].
Anatomical Variations
- Anatomical variations in the first extensor compartment are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- The presence of an intracompartmental septum does not significantly affect clinical outcomes or complications following endoscopic release for de Quervain's syndrome [42].
- When the extensor pollicis brevis tendon is associated with thumb interphalangeal joint extension, it is likely to reside in a subcompartment of the first dorsal compartment, particularly in patients with de Quervain's disease [53].
- De Quervain's disease may be secondary to extensor pollicis brevis entrapment [29].
Patient Factors and Perception
- Addressing misconceptions about the consequences of de Quervain's tenosynovitis and symptom duration allows patients to make informed decisions about treatment [9].
- Growth hormone abuse is associated with a more recalcitrant form of de Quervain tenosynovitis that does not respond well to nonsurgical treatment, increasing the likelihood of surgical decompression [79].
Treatment
Non-Operative Management
- One or two local injections of 1 ml triamcinolone acetonide 10 mg/ml provided by general practitioners leads to short-term improvement in participants with de Quervain's tenosynovitis compared to placebo [26].
- Corticosteroid injections are a useful treatment for de Quervain's tenosynovitis, leading to treatment success 73.4% of the time within 2 injections [22].
- A single cortisone injection was effective in alleviating symptoms of de Quervain tendinopathy in 82% of patients, with over half remaining symptom-free for at least 12 months [67].
- The combined technique of corticosteroid injection and thumb spica casting was better than injection alone in the treatment of de Quervain tenosynovitis in terms of treatment success and functional outcomes [68].
- Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients, but the effectiveness of each additional injection does not appear to diminish [40].
- Ultrasound should be considered to improve the treatment outcome of corticosteroid injections and can also be useful as a diagnostic tool in the management of de Quervain’s disease [18].
- Pain and clinical outcomes significantly improved after corticosteroid injection in de Quervain's disease [49].
- Preliminary results indicate that betamethasone is a superior treatment for De Quervain's tenosynovitis compared to ketorolac injection [70].
- Splinting has not been shown to provide long-lasting relief beyond allowing the joints to rest in an immobilized position [65].
- Iontophoresis with dexamethasone may improve functional outcomes, while therapeutic pulsed ultrasound may be effective in decreasing pain in patients with de Quervain's tenosynovitis [69].
Operative Management
- The release of the first extensor compartment for refractory de Quervain's disease resulted in good clinical outcomes with minimal morbidity [24].
- An oblique incision coursing along the extensor brevis tendon is preferred for surgical release, though transverse, oblique, or longitudinal incisions are also satisfactory [35].
- The longitudinal incision for release of the first extensor compartment offers the advantage of easy identification of the compartment, more complete releases of tendon sheath and peritendinous adhesions, and less risk of palmar subluxation of tendons [10].
- The first dorsal compartment should be opened on its dorsoulnar side during surgical release [35].
- A volarly based retinacular flap must remain over the released tendons to prevent volar tendon subluxation [35].
- Symptomatic palmar tendon subluxation after surgical release can be avoided by leaving a palmarly based flap of extensor retinaculum to prevent palmar subluxation of the tendons with wrist flexion [15].
- Volar subluxation of the tendons of the first dorsal compartment after surgery can be treated with a distally based flap of the brachioradialis tendon [48].
- One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures in patients with de Quervain's disease who are unresponsive to non-operative treatments [31].
- Endoscopic release of the extensor compartment seems to be an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time [41].
- Pulley reconstruction should be considered part of the surgical treatment for de Quervain tenosynovitis as it gives satisfactory medium-term results [4].
- The failure of an operation in De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignorance of another syndrome in the proximity [13].
- Anatomical variations are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- Anatomic variations are frequently encountered in recalcitrant cases of de Quervain tenosynovitis, including multiple slips of APL and EPB in its own separate compartment [83].
- First dorsal compartment release during volar approach for distal radius fracture fixation reduces symptoms in patients with pre-existing De Quervain disease compared with no release [75].
Complications
Surgical Complications
- Surgical failure in De Quervain tenosynovitis is attributed to anatomical variations, involvement of the radial superficial nerve, and the failure to diagnose another syndrome in the proximity [13].
- Symptomatic palmar tendon subluxation is a complication of surgical release that can be avoided by leaving a palmarly based flap of extensor retinaculum [15].
- The longitudinal incision for release of the first extensor compartment prevents possible tendon subluxation in the postoperative period [17].
- Endoscopic release for de Quervain's tenosynovitis is associated with fewer superficial radial nerve complications compared with open release [33].
- The longitudinal incision offers a less risk of palmar subluxation of tendons compared to other approaches [10].
Tendon and Structural Complications
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has been reported, with pathogenesis potentially linked to ongoing tendon damage from wear and tear within the stenosed sheath [21].
- Longitudinal split tears of the extensor pollicis brevis tendon have been reported in cases of de Quervain's tenosynovitis [16].
Diagnostic and Associated Pathology
- De Quervain's syndrome may be associated with trauma, extensor carpi ulnaris involvement, ligament instability, or repetitive strain, indicating it may not be an isolated pathology [3].
- Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a rare condition that mimics de Quervain’s disease [30].
- In cases where constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised to avoid diagnostic error [27].
- The complexities of de Quervain's tendinitis and associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in working women [8].
Recovery
Non-Operative Management
- A single injection of steroid gives complete and lasting relief in 70% of patients with de Quervain's disease, and a further 10% will be cured by a second injection [91].
Operative Management
- Only 34.9% of patients with new stenosing tenosynovitis required surgery within a 2-year follow-up period, with most progressing to surgery within 1 year of presentation [93].
Surgical Technique and Complications
- Pulley reconstruction as part of the surgical treatment for de Quervain tenosynovitis gives satisfactory medium-term results and should be considered part of the surgical treatment [4].
Patient Factors and Prognosis
- More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression of de Quervain's tenosynovitis [25].
Key Evidence
- [L4] These variations are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis. [1] (10.1016/j.bjps.2016.08.020)
- [L4] According to the limited evidence available, injection of corticosteroids is the only available nonsurgical treatment that can potentially modify the course of de Quervain's tenosynovitis and is therefore the preferred initial treatment. [2] (10.1016/j.jhsa.2008.12.030)
- [L4] [3] (10.1177/1758998315599796)
- [L4] The authors believe the technique gives satisfactory medium-term results and should be considered part of the surgical treatment for de Quervain tenosynovitis. [4] (10.1055/s-0035-1556862)
- [L3] Although considerable improvements in symptom severity and hand function will likely occur in patients with metabolic syndrome, corticosteroid injection for De Quervain tenosynovitis is not as effective in these patients compared with age- and sex-matched controls in terms of functional outcomes and treatment failure. [5] (10.1177/1753193417694112)
- [L3] Wrist radiography does not influence management of patients presenting with de Quervain tendinopathy. [6] (10.1055/s-0037-1606124)
- [L4] Providers should remain cognizant that patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management. [7] (10.1016/j.jhsg.2024.01.009)
- [L4] The complexities of de Quervain's tendinitis and the diagnosis and treatment of associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in these groups of working women. [8] (10.1016/s0363-5023(87)80204-6)
- [L3] Addressing misconceptions about de Quervain's tenosynovitis in terms of the consequences for patients and how long their symptoms will last should allow patients to make informed decisions about the treatment that best matches their values. [9] (10.1097/corr.0000000000001577)
- [L4] Surgical release of De Quervain's tenosynovitis remains the gold standard treatment, and longitudinal incision offers advantage of easy identification of compartment, more complete releases of tendon sheath and peritendinous adhesions and less risk of palmar subluxation of tendons. [10] (10.1007/s12306-018-0585-1)
- [L4] Surgical intervention is effective as definitive therapy for de Quervain's tenosynovitis, with a cure rate of 91% and 88% of patients indicating full satisfaction. [11] (10.1053/jhsu.1999.1071)
- [L4] We can conclude that the failure of an operation in the De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignoration of another syndrome in the proximity. [13] (10.1177/1558944716660555gr)
- [L5] [14] (10.1016/s0363-5023(96)80112-2)
- [L5] This complication can be avoided by leaving a palmarly based flap of extensor retinaculum to prevent palmar subluxation of the tendons with wrist flexion. [15] (10.1016/s0363-5023(84)80017-9)
- [L4] [16] (10.1016/j.jhsa.2014.09.024)
- [L4] In our experience, the longitudinal incision for release of the first extensor compartment for de Quervain tenosynovitis is a safe and effective technique that provides good exposure, protects vital structures, prevents possible tendon subluxation in the postoperative period, and is cosmetically acceptable. [17] (10.1097/01.bth.0000181105.24124.c0)
- [L4] Therefore, ultrasound should not only be considered to improve the treatment outcome, but can also be useful as a diagnostic tool in the management of de Quervain’s disease. [18] (10.1016/j.main.2013.09.002)
- [L4] Though considered as a manifestation of de Quervain's disease by some authors, styloid abnormalities do not affect the outcome of management as proved in this study. [19] (10.1007/s11552-010-9258-8)
- [L4] Triggering or locking in extension is an uncommon symptom in de Quervain’s stenosing tenosynovitis, with a prevalence of 1.3% based on a review of 827 consecutive patients. [20] (10.1053/jhsu.1999.1311)
- [L4] [21] (10.1016/j.jhsb.2005.09.020)
- [L3] This study indicates that corticosteroid injections are a useful treatment for de Quervain's tenosynovitis, leading to treatment success 73.4% of the time within 2 injections. [22] (10.1177/1558944716681976)
- [L4] The release of the first extensor compartment for refractory de Quervain's disease resulted in good clinical outcomes with minimal morbidity. [24] (10.4055/cios.2014.6.4.405)
- [L3] More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression of de Quervain's tenosynovitis. [25] (10.1097/corr.0000000000000992)
- [L1] One or two local injections of 1 ml triamcinolonacetonide 10 mg/ml provided by general practitioners leads to improvement in the short term in participants with de Quervain's tenosynovitis when compared to placebo. [26] (10.1186/1471-2474-10-131)
- [L4] In cases with symptoms of de Quervain's syndrome where the constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised. [27] (10.2106/00004623-194931040-00019)
- [L1] Corticosteroid injection with a short duration of immobilization remains the primary and effective treatment for de Quervain tenosynovitis. [28] (10.1016/j.jhsa.2024.03.003)
- [L4] We conclude that de Quervain's disease is secondary to EPB entrapment. [29] (10.1016/s0363-5023(98)80160-3)
- [L5] Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease. [30] (10.1016/j.jhsa.2003.11.012)
- [L4] One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures in patients with de Quervain's disease who are unresponsive to non-operative treatments. [31] (10.1016/j.aott.2018.10.004)
- [L4] Most informed patients initially elect symptomatic treatment for de Quervain's disease, and most experience symptom resolution within one year. [32] (10.1007/s12593-009-0018-3)
- [L1] Endoscopic release for de Quervain's tenosynovitis seems to provide earlier improvement after surgery, with fewer superficial radial nerve complications and greater scar satisfaction, when compared with open release. [33] (10.1302/0301-620x.95b7.31486)
- [L4] Patients who scored lower than 40 for physical function or higher than 60 for pain interference had significantly increased odds of eventually undergoing surgical release for de Quervain tenosynovitis. [34] (10.1016/j.jhsa.2023.07.005)
- [L3] The new test is a useful clinical tool in the diagnosis of De Quervain's tenosynovitis. [36] (10.1016/j.main.2011.10.017)
- [L1] [38] (10.1002/14651858.cd005616.pub2)
- [L3] [39] (10.1177/1753193415611414)
- [L4] Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients, but the effectiveness of each additional injection does not appear to diminish. [40] (10.1016/j.jhsa.2022.02.018)
- [L4] Endoscopic release of the extensor compartment seems to be an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time. [41] (10.1016/j.bjps.2011.05.015)
- [L4] The presence of a septum does not significantly affect clinical outcomes or complications following endoscopic release for de Quervain's syndrome. [42] (10.1177/17531934231214137)
- [L5] We describe a case of nonsyndromic congenital fusion of the scaphoid and the trapezium as a cause of tendinitis simulating de Quervain's stenosing tenosynovitis, an association not previously reported. [43] (10.1016/s1297-3203(00)73478-0)
- [L5] As the clinical presentation and X-rays of the wrist were not typical of an osteoid osteoma, only the histological examination led to the correct diagnosis. [45] (10.1016/0266-7681(92)90100-g)
- [L2] Although the success rate for the treatment of De Quervain's tenosynovitis decreases with multiple injections, repeat injections have a high rate of success and are a viable clinical option. [46] (10.1016/j.jhsa.2021.04.018)
- [L4] [48] (10.1016/s0363-5023(10)80007-3)
- [L1] Pain and clinical outcomes significantly improved after corticosteroid injection in de Quervain's disease. [49] (10.1016/j.otsr.2019.11.015)
- [L5] Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides important information about anatomic variations within the first extensor compartment. [50] (10.1136/bcr-2021-242173)
- [L4] Ultrasound is a worthwhile preoperative investigation in case of de Quervain's disease. [51] (10.1007/s12593-009-0001-z)
- [L3] The prevalence of a septated first dorsal compartment is considerably higher than previously reported, most notably in patients with De Quervain tenosynovitis. [52] (10.1177/1558944718810864)
- [L4] When it does, particularly in patients with de Quervain's disease, it is likely to reside in a subcompartment of the first dorsal compartment. [53] (10.1016/j.jhsa.2008.12.015)
- [L2] [54] (10.1016/j.jhsa.2008.08.020)
- [L2] [59] (10.1177/1753193412475043)
- [L4] [62] (10.1055/s-0040-1716522)
- [L3] [63] (10.1055/s-0038-1626690)
- [L5] [64] (10.5435/00124635-200712000-00009)
- [L4] [65] (10.1007/s11552-014-9649-3)
- [L4] A single cortisone injection was effective in alleviating symptoms of de Quervain tendinopathy in 82% of patients, with over half remaining symptom-free for at least 12 months. [67] (10.1016/j.jhsa.2014.12.027)
- [L2] The combined technique of corticosteroid injection and thumb spica casting was better than injection alone in the treatment of de Quervain tenosynovitis in terms of treatment success and functional outcomes. [68] (10.1016/j.jhsa.2013.10.013)
- [L4] This study demonstrated that iontophoresis with dexamethasone may improve functional outcomes, while therapeutic pulsed ultrasound may be effective in decreasing pain in patients with de Quervain's tenosynovitis. [69] (10.1016/j.jht.2014.08.032)
- [L1] Preliminary results indicate that betamethasone is a superior treatment for De Quervain's tenosynovitis. [70] (10.1016/j.jhsa.2017.06.086)
- [L4] [72] (10.1177/0363546504268134)
- [L4] In vivo EPB tendon excursion measures have been quantified, and wrist position has been found to have an influence on excursion. [73] (10.1016/j.jht.2017.12.004)
- [L1] The current results demonstrated a significantly greater reduction in de Quervain disease symptoms in the release group compared with the no release group during the short-term follow-up. [75] (10.1016/j.jhsg.2024.03.009)
- [L3] Our results suggest that growth hormone abuse is associated with a more recalcitrant form of de Quervain tenosynovitis that does not respond well to nonsurgical treatment, thus leading to increased likelihood of surgical decompression. [79] (10.1177/0363546509337993)
- [L5] The patient overstressed his wrist through forceful extension during over-zealous weightlifting. [80] (10.1177/1753193419871862)
- [L3] Those subjects demonstrate a significant decrease in maximum velocity in slow fist tasks, highlighting the need for comprehensive assessment to ascertain the full extent of functional limitations that can occur in the setting of hand pathology. [81] (10.1177/1558944717729218)
- [L4] Repeat provocative testing revealed volar tendon translation with wrist flexion, with no pain reported. [85] (10.1097/bth.0000000000000054)
- [L4] A single injection of steroid gives complete and lasting relief in 70% of patients with de Quervain's disease, and a further 10% will be cured by a second injection. [91] (10.1016/s0363-5023(09)91110-8)
- [L2] Only 34.9% of patients with new stenosing tenosynovitis required surgery within a 2-year follow-up period, with most progressing to surgery within 1 year of presentation. [93] (10.1016/j.jhsa.2017.06.088)
- [L2] The anatomical findings are consistent with previous studies, with an expectation to encounter the superficial branch of the radial nerve in more than 50% of patients. [94] (10.1055/s-0039-1688700)
- [L3] The proportion of wrists with a positive EPB entrapment test was significantly higher among those with 2 compartments (18 of 22) than among those with 1 compartment (0 of 4). [97] (10.1053/jhsu.2002.35309)
- [Paper] Operative treatment for distal radius fractures confers a slightly greater risk of developing DeQuervain tenosynovitis within 1 year of injury or surgery. [105] (10.1177/15589447251366456)
- [Paper] There is immense anatomical variation present in the first dorsal compartment of the wrist, supernumerary tendons/tendon slips are commonly found, there is variation of insertion present in the population, septum/aberrant compartment is also present, and bilateral variations are present in the population. [107] (10.1007/s12593-012-0073-z)
References
[1] Surgical anatomy of the first extensor compartment: A systematic review and comparison of normal cadavers vs. De Quervain syndrome patients. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2017. DOI: 10.1016/j.bjps.2016.08.020
[2] Nonsurgical Treatment for de Quervain's Tenosynovitis. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.12.030
[3] De Quervain’s syndrome: It may not be an isolated pathology. Hand Therapy. 2015. DOI: 10.1177/1758998315599796
[4] Pulley Reconstruction As Part of the Surgical Treatment for de Quervain Disease: Surgical Technique with Medium-Term Results. Journal of Wrist Surgery. 2015. DOI: 10.1055/s-0035-1556862
[5] RETRACTED: Effects of metabolic syndrome on the functional outcomes of corticosteroid injection for De Quervain tenosynovitis. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193417694112
[6] Deferring Routine Wrist Radiography Does Not Affect Management of de Quervain Tendinopathy Patients. Journal of Wrist Surgery. 2017. DOI: 10.1055/s-0037-1606124
[7] De Quervain’s Tenosynovitis: As Seen from the Perspective of the Patient. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.01.009
[8] de Quervain's release in working women: A report of failures, complications, and associated diagnoses. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80204-6
[9] Are Patient Expectations and Illness Perception Associated with Patient-reported Outcomes from Surgical Decompression in de Quervain’s Tenosynovitis?. Clinical Orthopaedics & Related Research. 2020. DOI: 10.1097/corr.0000000000001577
[10] Functional outcome of De Quervain’s tenosynovitis with longitudinal incision in surgically treated patients. MUSCULOSKELETAL SURGERY. 2019. DOI: 10.1007/s12306-018-0585-1
[11] Patient satisfaction and outcomes of surgery for de Quervain's tenosynovitis. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1071
[12] Tethered_Thumb_Sign_A_Unique_Observation_in_the_Physical_Examination_of_de_Querv_S0363502313005340. n.d..
[13] Failure of Surgical Treatment in the De Quervain Tenosynovitis. HAND. 2016. DOI: 10.1177/1558944716660555gr
[14] Hemangioma of the extensor pollicis brevis in the first dorsal compartment: An unusual cause of bilateral de Quervain's disease. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80112-2
[15] Symptomatic palmar tendon subluxation after surgical release for de Quervain's disease: A case report. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80017-9
[16] Longitudinal Split Tear of the Extensor Pollicis Brevis Tendon: Report of 2 Cases. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.09.024
[17] Longitudinal Incision in Surgical Release of De Quervain Disease. Techniques in Hand & Upper Extremity Surgery. 2005. DOI: 10.1097/01.bth.0000181105.24124.c0
[18] The role of ultrasound-guided triamcinolone injection in the treatment of De Quervain's disease: Treatment and a diagnostic tool?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.09.002
[19] Does Radial Styloid Abnormality in de Quervain's Disease Affect the Outcome of Management?. HAND. 2010. DOI: 10.1007/s11552-010-9258-8
[20] Extensor triggering in de Quervain's stenosing tenosynovitis. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1311
[21] Abductor Pollicis Longus Tendon Rupture in De Quervain’s Disease. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.09.020
[22] Effectiveness of Corticosteroid Injections for Treatment of de Quervain’s Tenosynovitis. HAND. 2016. DOI: 10.1177/1558944716681976
[24] Surgical Release of the First Extensor Compartment for Refractory de Quervain's Tenosynovitis: Surgical Findings and Functional Evaluation Using DASH Scores. Clinics in Orthopedic Surgery. 2014. DOI: 10.4055/cios.2014.6.4.405
[25] Which Psychological Variables Are Associated With Pain and Function Before Surgery for de Quervain’s Tenosynovitis? A Cross-sectional Study. Clinical Orthopaedics & Related Research. 2019. DOI: 10.1097/corr.0000000000000992
[26] Randomised controlled trial of local corticosteroid injections for de Quervain's tenosynovitis in general practice. BMC Musculoskeletal Disorders. 2009. DOI: 10.1186/1471-2474-10-131
[27] AN UNUSUAL FORM OF DE QUERVAINʼS SYNDROME. The Journal of Bone & Joint Surgery. 1949. DOI: 10.2106/00004623-194931040-00019
[28] Advancements in de Quervain Tenosynovitis Management: A Comprehensive Network Meta-Analysis. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.03.003
[29] Limited surgical treatment of de quervain's disease: Decompression of only the extensor pollicis brevis subcompartment. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80160-3
[30] Extensor pollicis longus tenosynovitis mimicking de quervain’s disease because of its course through the first extensor compartment: a report of 2 cases. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.11.012
[31] One portal endoscopic release of the first extensor compartment in de Quervain's disease. Acta Orthopaedica et Traumatologica Turcica. 2020. DOI: 10.1016/j.aott.2018.10.004
[32] Patient-centered care of de Quervain’s disease. Journal of Hand and Microsurgery. 2009. DOI: 10.1007/s12593-009-0018-3
[33] Endoscopicversusopen release in patients with de Quervain’s tenosynovitis. The Bone & Joint Journal. 2013. DOI: 10.1302/0301-620x.95b7.31486
[34] Association of Patient-Reported Outcomes Measurement Information System Measures With Injection and Surgical Treatment Response in Patients With De Quervain Tenosynovitis. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.005
[35] Campbell S Operative Orthopaedics 4 Volume Set. EXCISION OF NECROTIC MUSCLES COMBINED WITH NEUROLYSIS OF MEDIAN AND ULNAR NERVES FOR SEVERE CONTRACTURE > SURGICAL TREATMENT OF DE QUERVAIN DISEASE.
[36] Évaluation de la première loge des extenseurs à fin diagnostique : un nouveau test dans le diagnostic de la ténosynovite de De Quervain. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.017
[38] Corticosteroid injection for de Quervain's tenosynovitis. Cochrane Database of Systematic Reviews. 2009. DOI: 10.1002/14651858.cd005616.pub2
[39] Presence of an intracompartmental septum detected by ultrasound is associated with the failure of ultrasound-guided steroid injection in de Quervain’s syndrome. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193415611414
[40] Effectiveness of Corticosteroid Injections in Diabetic Patients With De Quervain Tenosynovitis. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.02.018
[41] Does endoscopic release of the first extensor compartment have benefits over open release in de Quervain’s disease?. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2011. DOI: 10.1016/j.bjps.2011.05.015
[42] Prediction of an intracompartmental septum and its effect on outcomes of endoscopic release for de Quervain’s syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231214137
[43] Congenital synostosis between the scaphoid and the trapezium as a cause of tenosynovitis simulating de Quervain's disease. Chirurgie de la Main. 2000. DOI: 10.1016/s1297-3203(00)73478-0
[45] Osteoid Osteoma of the Radial Styloid Mimicking Stenosing Tenosynovitis. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90100-g
[46] De Quervain Tenosynovitis: An Evaluation of the Epidemiology and Utility of Multiple Injections Using a National Database. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.04.018
[48] Tendon subluxation after de Quervain's release: Treatment by brachioradialis tendon flap. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80007-3
[49] Prospective randomized comparison of ultrasonography-guided and blind corticosteroid injection for de Quervain's disease. Orthopaedics & Traumatology: Surgery & Research. 2020. DOI: 10.1016/j.otsr.2019.11.015
[50] Type II de Quervain’s disease: depicting subcompartmentalisation with ultrasound. BMJ Case Reports. 2021. DOI: 10.1136/bcr-2021-242173
[51] Preoperative ultrasound in de Quervain’s disease: an investigation worth doing. Journal of Hand and Microsurgery. 2009. DOI: 10.1007/s12593-009-0001-z
[52] Prevalence of a Septated First Dorsal Compartment Among Patients With and Without De Quervain Tenosynovitis: An In Vivo Anatomical Study. HAND. 2018. DOI: 10.1177/1558944718810864
[53] Thumb Interphalangeal Joint Extension By the Extensor Pollicis Brevis: Association With a Subcompartment and de Quervain's Disease. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.12.015
[54] Incidence of de Quervain's Tenosynovitis in a Young, Active Population. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.08.020
[55] Treatment of de Quervain tenosynovitis. A prospective study of the results of injection of steroids and immobilization in a splint.. The Journal of bone and joint surgery. American volume. 1991.
[59] The wrist hyperflexion and abduction of the thumb (WHAT) test: a more specific and sensitive test to diagnose de Quervain tenosynovitis than the Eichhoff’s Test. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193412475043
[62] Are Plain X-Rays Necessary in the Diagnosis of De Quervain's Tenosynovitis?. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1716522
[63] Finkelstein's Test Is Superior to Eichhoff's Test in the Investigation of de Quervain's Disease. Journal of Hand and Microsurgery. 2018. DOI: 10.1055/s-0038-1626690
[64] de Quervain Tenosynovitis of the Wrist. Journal of the American Academy of Orthopaedic Surgeons. 2007. DOI: 10.5435/00124635-200712000-00009
[65] De Quervain's Tenosynovitis: A Review of the Rehabilitative Options. HAND. 2014. DOI: 10.1007/s11552-014-9649-3
[67] de Quervain Tendinopathy: Survivorship and Prognostic Indicators of Recurrence Following A Single Corticosteroid Injection. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.027
[68] Corticosteroid Injection With or Without Thumb Spica Cast for de Quervain Tenosynovitis. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.10.013
[69] Effective Conservative Treatments for De Quervain's Tenosynovitis: A Retrospective Study. Journal of Hand Therapy. 2016. DOI: 10.1016/j.jht.2014.08.032
[70] Betamethasone Versus Ketorolac Injection for the Treatment of De Quervain's Tenosynovitis: A Double-Blind Randomized Clinical Trial. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.086
[72] De Quervain Disease in Volleyball Players. The American Journal of Sports Medicine. 2005. DOI: 10.1177/0363546504268134
[73] Ultrasound assessment of extensor pollicis brevis tendon excursion in different wrist positions in healthy people. Journal of Hand Therapy. 2019. DOI: 10.1016/j.jht.2017.12.004
[75] First Dorsal Compartment Release During Volar Approach for Distal Radius Fracture Fixation Reduces Symptoms in Patients With Pre-Existing De Quervain Disease. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.03.009
[79] Abuse of Growth Hormone Increases the Risk of Persistent de Quervain Tenosynovitis. The American Journal of Sports Medicine. 2009. DOI: 10.1177/0363546509337993
[80] Dorsal tendon dislocation after de Quervain's release and its surgical management: a case report. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419871862
[81] Dynamic Functional Assessment of Hand Motion Using an Animation Glove: The Effect of Stenosing Tenosynovitis. HAND. 2017. DOI: 10.1177/1558944717729218
[83] Miller S Review Of Orthopaedics. 2. Flexor tendon injury > 5. de Quervain tenosynovitis (Fig. 7.35).
[85] Radial Ridge Excision for Symptomatic Volar Tendon Subluxation Following de Quervain’s Release. Techniques in Hand & Upper Extremity Surgery. 2014. DOI: 10.1097/bth.0000000000000054
[91] De Quervain's disease: Surgical or nonsurgical treatment. The Journal of Hand Surgery. 1990. DOI: 10.1016/s0363-5023(09)91110-8
[93] A Prospective Study of Risk Modeling for Stenosing Tenosynovitis. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.088
[94] A Prospective Evaluation of the Anatomy of the First Dorsal Compartment in Patients Requiring Surgery for De Quervain's Tenosynovitis. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1688700
[97] The extensor pollicis brevis entrapment test in the treatment of de Quervain's disease. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.35309
[105] Incidence of DeQuervain Tenosynovitis After Distal Radius Fractures. HAND. 2025. DOI: 10.1177/15589447251366456
[107] A Cadaveric Study of the First Dorsal Compartment of the Wrist and Its Content Tendons: Anatomical Variations in the Indian Population. Journal of Hand and Microsurgery. 2012. DOI: 10.1007/s12593-012-0073-z