Patients › Hand
ਬੂਟੋਨੀਅਰ ਡਿਫ਼ਾਰਮਿਟੀ (Boutonnière Deformity, ਉਂਗਲ ਦਾ ਵਿੰਗਾ ਹੋ ਜਾਣਾ)
Extensor central-slip injury at the middle finger joint; early splinting prevents the zigzag deformity, established cases need surgery.
ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ
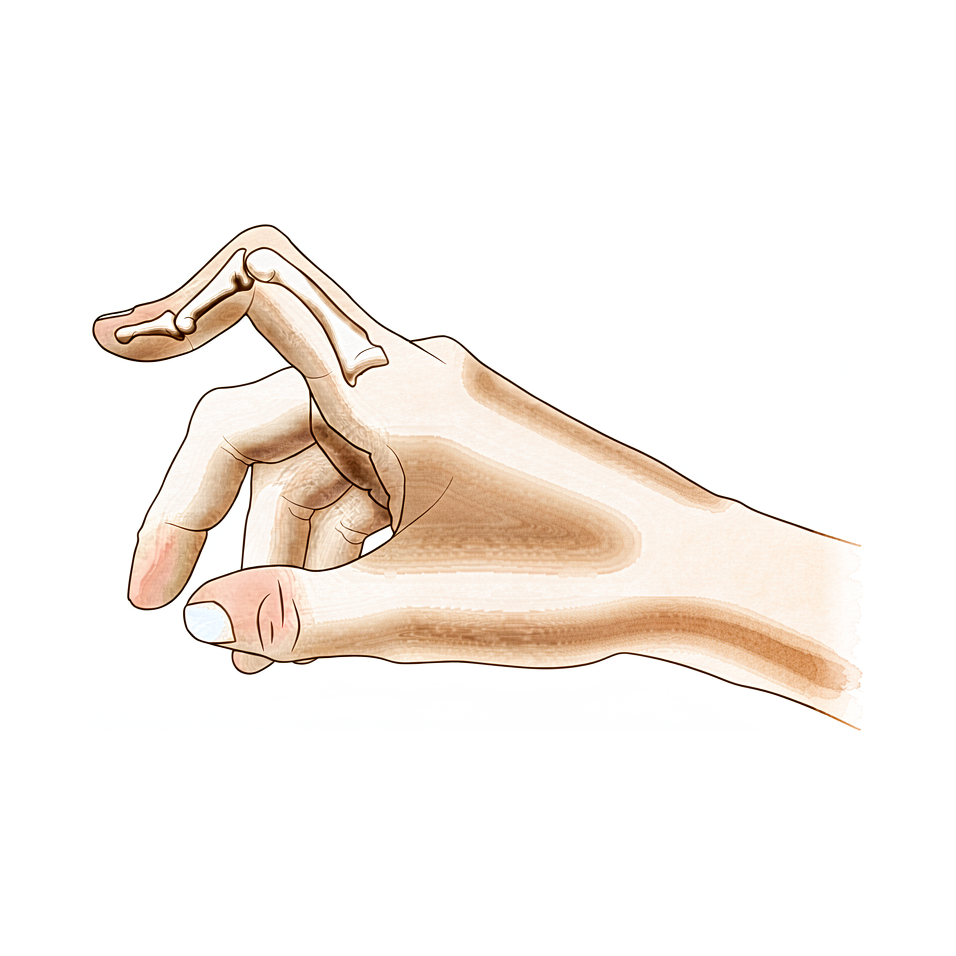
ਬੂਟੋਨੀਅਰ ਡਿਫ਼ਾਰਮਿਟੀ (boutonnière deformity, ਉਂਗਲ ਦਾ ਇੱਕ ਖ਼ਾਸ ਤਰ੍ਹਾਂ ਵਿੰਗਾ ਹੋ ਜਾਣਾ) ਵਿੱਚ ਤੁਹਾਡੀ ਉਂਗਲ ਦਾ ਵਿਚਕਾਰਲਾ ਜੋੜ ਹੇਠਾਂ ਤੁਹਾਡੀ ਹਥੇਲੀ ਵੱਲ ਮੁੜ ਜਾਂਦਾ ਹੈ ਅਤੇ ਪੋਟਾ ਉਲਟੇ ਪਾਸੇ ਪਿੱਛੇ ਵੱਲ ਮੁੜ ਜਾਂਦਾ ਹੈ। ਵਿਚਕਾਰਲੇ ਜੋੜ ਉੱਤੇ ਉਂਗਲ ਸੁੱਜੀ ਹੋਈ ਦਿਸ ਸਕਦੀ ਹੈ, ਅਤੇ ਉੱਥੇ ਦਰਦ ਵੀ ਹੋ ਸਕਦਾ ਹੈ। ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਕਰਨਾ ਔਖਾ ਹੋ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਤੁਸੀਂ ਜਿੰਨੀ ਜ਼ਿਆਦਾ ਕੋਸ਼ਿਸ਼ ਕਰਦੇ ਹੋ, ਉਂਗਲ ਓਨਾ ਹੀ ਜ਼ਿਆਦਾ ਅੜਦੀ ਜਾਪਦੀ ਹੈ।
ਮੁਸ਼ਕਲ ਸਭ ਤੋਂ ਵੱਧ ਉਨ੍ਹਾਂ ਕੰਮਾਂ ਵਿੱਚ ਦਿਸਦੀ ਹੈ ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਉਂਗਲ ਨੂੰ ਸਿੱਧਾ ਕਰਕੇ ਫਿਰ ਮੋੜਨਾ ਪੈਂਦਾ ਹੈ। ਸਿੱਕਾ ਚੁੱਕਣਾ, ਕੱਪ ਨੂੰ ਉਸਦੇ ਹੈਂਡਲ ਤੋਂ ਫੜਨਾ, ਟਾਈਪ ਕਰਨਾ, ਕਮੀਜ਼ ਦੇ ਬਟਨ ਲਾਉਣਾ ਜਾਂ ਚਾਬੀ ਘੁਮਾਉਣਾ, ਇਹ ਸਭ ਅਟਪਟੇ ਹੋ ਸਕਦੇ ਹਨ। ਪਕੜ ਆਪ ਅਕਸਰ ਫਿਰ ਵੀ ਕੰਮ ਕਰਦੀ ਰਹਿੰਦੀ ਹੈ, ਇਸੇ ਲਈ ਬਹੁਤ ਸਾਰੇ ਲੋਕ ਮਦਦ ਲੈਣ ਤੋਂ ਪਹਿਲਾਂ ਹਫ਼ਤਿਆਂ ਤੱਕ ਇਸ ਉਂਗਲ ਨਾਲ ਗੁਜ਼ਾਰਾ ਕਰਦੇ ਰਹਿੰਦੇ ਹਨ।
ਜੇ ਵਿੰਗ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਣਿਆ ਹੈ, ਤਾਂ ਹੱਥ ਵਰਤਣ ਤੋਂ ਬਾਅਦ ਵਿਚਕਾਰਲਾ ਜੋੜ ਦੁਖ ਸਕਦਾ ਹੈ, ਅਤੇ ਉਂਗਲ ਦੇ ਖੁੱਲ੍ਹਣ ਤੋਂ ਪਹਿਲਾਂ ਸਵੇਰੇ ਅਕੜਾਅ ਜ਼ਿਆਦਾ ਹੋ ਸਕਦਾ ਹੈ। ਰਾਇਮੇਟਾਇਡ ਆਰਥਰਾਈਟਿਸ (rheumatoid arthritis) ਵਿੱਚ, ਇਹੀ ਮੁੜੀ ਹੋਈ ਸ਼ਕਲ ਹੌਲੀ-ਹੌਲੀ ਬਣਦੀ ਹੈ, ਕਿਉਂਕਿ ਜੋੜ ਦੀ ਅੰਦਰਲੀ ਪਰਤ ਮਹੀਨਿਆਂ ਤੱਕ ਸੋਜਸ਼ (inflammation) ਵਾਲੀ ਅਤੇ ਸੁੱਜੀ ਹੋਈ ਰਹਿੰਦੀ ਹੈ।
ਕੁਝ ਨਿਸ਼ਾਨੀਆਂ ਵੱਲ ਛੇਤੀ ਧਿਆਨ ਦੇਣ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਜੇ ਤੁਹਾਡੀ ਉਂਗਲ ਜਾਂ ਹੱਥ ਗਰਮ, ਲਾਲ, ਸੁੱਜਿਆ ਹੋਇਆ ਅਤੇ ਦਰਦ ਭਰਿਆ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹੀ ਗੱਲ ਉਦੋਂ ਵੀ ਲਾਗੂ ਹੁੰਦੀ ਹੈ ਜੇ ਕੋਈ ਉਂਗਲ ਫਿੱਕੀ, ਠੰਢੀ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੀ ਪੈ ਜਾਵੇ, ਜਾਂ ਜੇ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਾਅਦ ਅਚਾਨਕ ਉਸ ਵਿੱਚ ਤੁਹਾਡਾ ਅਹਿਸਾਸ ਜਾਂ ਹਿਲਜੁਲ ਖ਼ਤਮ ਹੋ ਜਾਵੇ। ਜੇ ਇਸਦੀ ਬਜਾਏ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਜਗਾ ਦਿੰਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਆਪਣਾ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਦੀ ਜਾਂਚ ਲਈ ਕਹੋ।
ਅਸਲ ਵਿੱਚ ਕੀ ਹੋ ਰਿਹਾ ਹੈ
ਹਰ ਉਂਗਲ ਦੇ ਪੁੱਠੇ ਪਾਸੇ ਟੈਂਡਨਾਂ (tendons, ਮਾਸਪੇਸ਼ੀ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀਆਂ ਮਜ਼ਬੂਤ ਤੰਦਾਂ) ਦਾ ਇੱਕ ਸਮੂਹ ਚੱਲਦਾ ਹੈ ਜੋ ਜੋੜਾਂ ਨੂੰ ਸਿੱਧਾ ਕਰਦਾ ਹੈ। ਇਨ੍ਹਾਂ ਨੂੰ ਉਂਗਲ ਦੇ ਪੁੱਠੇ ਪਾਸੇ ਇੱਕ ਹੁੱਡ (ਢੱਕਣ) ਹੇਠਾਂ ਚੱਲਦੀਆਂ ਰੱਸੀਆਂ ਵਾਂਗ ਸਮਝੋ। ਜੋ ਰੱਸੀ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਕਰਦੀ ਹੈ ਉਸਨੂੰ ਸੈਂਟਰਲ ਸਲਿੱਪ (central slip) ਕਹਿੰਦੇ ਹਨ, ਅਤੇ ਇਹ ਵਿਚਕਾਰਲੀ ਹੱਡੀ ਦੇ ਮੁੱਢ ਨਾਲ ਜੁੜੀ ਹੁੰਦੀ ਹੈ। ਦੋ ਹੋਰ ਤੰਦਾਂ, ਜਿਨ੍ਹਾਂ ਨੂੰ ਲੇਟਰਲ ਬੈਂਡ (lateral bands) ਕਹਿੰਦੇ ਹਨ, ਇਸਦੇ ਨਾਲ-ਨਾਲ ਚੱਲਦੀਆਂ ਹਨ ਅਤੇ ਵਿਚਕਾਰਲੇ ਜੋੜ ਅਤੇ ਪੋਟੇ, ਦੋਵਾਂ ਨੂੰ ਸਿੱਧਾ ਕਰਨ ਵਿੱਚ ਮਦਦ ਕਰਦੀਆਂ ਹਨ।
ਬੂਟੋਨੀਅਰ ਡਿਫ਼ਾਰਮਿਟੀ ਵਿੱਚ, ਸੈਂਟਰਲ ਸਲਿੱਪ ਪਾਟ ਕੇ ਜਾਂ ਖਿੱਚੀ ਜਾ ਕੇ ਵਿਚਕਾਰਲੀ ਹੱਡੀ ਤੋਂ ਵੱਖ ਹੋ ਜਾਂਦੀ ਹੈ। ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਹੁਣ ਖਿੱਚ ਕੇ ਸਿੱਧਾ ਨਹੀਂ ਕੀਤਾ ਜਾ ਸਕਦਾ, ਇਸ ਲਈ ਉਹ ਮੁੜੀ ਹੋਈ ਸਥਿਤੀ ਵਿੱਚ ਡਿੱਗ ਜਾਂਦਾ ਹੈ। ਫਿਰ ਦੋਵੇਂ ਲੇਟਰਲ ਬੈਂਡ ਜੋੜ ਦੇ ਉੱਪਰੋਂ ਖਿਸਕ ਕੇ ਹਥੇਲੀ ਵੱਲ ਹੇਠਾਂ ਸਰਕ ਜਾਂਦੇ ਹਨ। ਜਦੋਂ ਉਹ ਜੋੜ ਦੇ ਘੁੰਮਣ ਵਾਲੇ ਧੁਰੇ ਤੋਂ ਹੇਠਾਂ ਆ ਜਾਂਦੇ ਹਨ, ਤਾਂ ਉਹੀ ਤੰਦਾਂ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਕਰਨ ਦੀ ਥਾਂ ਮੋੜਨ ਲੱਗ ਪੈਂਦੀਆਂ ਹਨ, ਅਤੇ ਪੋਟੇ ਨੂੰ ਉਲਟੇ ਪਾਸੇ ਪਿੱਛੇ ਵੱਲ ਖਿੱਚਦੀਆਂ ਹਨ। ਇਸੇ ਕਰਕੇ ਉਂਗਲ ਉੱਪਰ ਦੱਸੇ ਮੁੜੇ ਹੋਏ ਵਿਚਕਾਰਲੇ ਜੋੜ ਅਤੇ ਪਿੱਛੇ ਵੱਲ ਮੁੜੇ ਪੋਟੇ ਵਾਲੀ ਸ਼ਕਲ ਵਿੱਚ ਟਿਕ ਜਾਂਦੀ ਹੈ, ਅਤੇ ਇਸੇ ਕਰਕੇ ਇਸਨੂੰ ਸਿੱਧਾ ਕਰਨ ਦੀ ਹਰ ਕੋਸ਼ਿਸ਼ ਨਾਲ ਤੰਦਾਂ ਤੁਹਾਡੇ ਖ਼ਿਲਾਫ਼ ਹੋਰ ਜ਼ੋਰ ਨਾਲ ਖਿੱਚਦੀਆਂ ਜਾਪਦੀਆਂ ਹਨ।
ਇਹ ਸ਼ਕਲ ਬਣਨ ਲਈ ਇੱਕ ਤੋਂ ਵੱਧ ਹਿੱਸੇ ਦਾ ਨੁਕਸਾਨ ਹੋਣਾ ਜ਼ਰੂਰੀ ਹੈ। ਵਿੰਗ ਬਣਨ ਤੋਂ ਪਹਿਲਾਂ ਸੈਂਟਰਲ ਸਲਿੱਪ, ਉਂਗਲ ਦੇ ਪੁੱਠੇ ਪਾਸੇ ਦੋਵਾਂ ਤੰਦਾਂ ਨੂੰ ਆਪਸ ਵਿੱਚ ਬੰਨ੍ਹਣ ਵਾਲਾ ਲਿਗਾਮੈਂਟ (ligament, ਟਿਸ਼ੂ ਦਾ ਮਜ਼ਬੂਤ ਬੰਧਨ), ਅਤੇ ਹਰ ਚੀਜ਼ ਨੂੰ ਆਪਣੀ ਥਾਂ ਰੱਖਣ ਵਾਲੇ ਹੁੱਡ ਦੇ ਰੇਸ਼ੇ, ਇਨ੍ਹਾਂ ਸਭ ਨੂੰ ਸੱਟ ਲੱਗੀ ਹੋਣੀ ਜ਼ਰੂਰੀ ਹੈ। ਇਕੱਲੀ ਸੈਂਟਰਲ ਸਲਿੱਪ ਦਾ ਪਾਟਣਾ ਪੂਰੇ ਵਿੰਗ ਤੋਂ ਬਿਨਾਂ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਕਮਜ਼ੋਰ ਛੱਡ ਸਕਦਾ ਹੈ, ਅਤੇ ਇਹ ਇੱਕ ਕਾਰਨ ਹੈ ਕਿ ਛੇਤੀ ਇਲਾਜ ਮਾਇਨੇ ਰੱਖਦਾ ਹੈ: ਇਹ ਵਿੰਗ ਨੂੰ ਬਣਨ ਤੋਂ ਪੂਰੀ ਤਰ੍ਹਾਂ ਰੋਕ ਸਕਦਾ ਹੈ।
ਇਹੀ ਅੰਤਲਾ ਨਤੀਜਾ ਵੱਖ-ਵੱਖ ਸ਼ੁਰੂਆਤਾਂ ਤੋਂ ਆ ਸਕਦਾ ਹੈ। ਕੋਈ ਸੱਟ, ਜਿਵੇਂ ਉਂਗਲ ਉੱਤੇ ਜ਼ੋਰ ਦੀ ਸੱਟ ਜਾਂ ਜੋੜ ਦੇ ਪੁੱਠੇ ਪਾਸੇ ਕੋਈ ਕੱਟ, ਇਹ ਕਰ ਸਕਦੀ ਹੈ, ਅਤੇ ਰਾਇਮੇਟਾਇਡ ਆਰਥਰਾਈਟਿਸ ਦੀ ਲਗਾਤਾਰ ਰਹਿਣ ਵਾਲੀ ਸੋਜਸ਼ ਵੀ, ਜੋ ਹੌਲੀ-ਹੌਲੀ ਇਨ੍ਹਾਂ ਹੀ ਬਣਤਰਾਂ ਨੂੰ ਘਸਾ ਕੇ ਤੋੜ ਦਿੰਦੀ ਹੈ। ਕੋਈ ਉਂਗਲ ਟੈਂਡਨ ਦੀ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਿਨਾਂ ਵੀ ਇਸ ਤਰ੍ਹਾਂ ਦੀ ਦਿਸ ਸਕਦੀ ਹੈ, ਜਦੋਂ ਸਮੱਸਿਆ ਇਸਦੀ ਬਜਾਏ ਜੋੜ ਦੇ ਹਥੇਲੀ ਵਾਲੇ ਪਾਸੇ ਹੁੰਦੀ ਹੈ, ਅਤੇ ਉਸ ਕਿਸਮ ਦਾ ਇਲਾਜ ਵੱਖਰਾ ਹੁੰਦਾ ਹੈ, ਇਸੇ ਲਈ ਪਹਿਲਾਂ ਇਹ ਪਤਾ ਲਾਉਣਾ ਜ਼ਰੂਰੀ ਹੈ ਕਿ ਤੁਹਾਨੂੰ ਕਿਹੜੀ ਕਿਸਮ ਹੈ।
ਅਸੀਂ ਇਸ ਬਾਰੇ ਕੀ ਕਰ ਸਕਦੇ ਹਾਂ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਜੋ ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ ਹਨ, ਸਭ ਤੋਂ ਘੱਟ ਚੀਰ-ਫਾੜ ਵਾਲੇ ਉਨ੍ਹਾਂ ਵਿਕਲਪਾਂ ਤੋਂ ਸ਼ੁਰੂ ਕਰਦੇ ਹਨ ਜੋ ਤੁਹਾਡੀ ਹਾਲਤ ਲਈ ਢੁਕਵੇਂ ਹੋਣ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ ’ਤੇ ਉਨ੍ਹਾਂ ਦਾ ਜੀਪੀ ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਡੇ ਕੋਲ ਆਉਣ ਦੀ ਸਲਾਹ ਦਿੱਤੀ ਹੈ, ਤਾਂ ਵੀ Medicare ਰਿਬੇਟ (ਸਰਕਾਰੀ ਵਾਪਸੀ ਰਕਮ) ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਪਵੇਗੀ। ਕਲੀਨਿਕ ਵਿੱਚ ਅਸੀਂ ਤੁਹਾਡੀ ਤਕਲੀਫ਼ ਦਾ ਪੂਰਾ ਵੇਰਵਾ ਲੈਂਦੇ ਹਾਂ, ਤੁਹਾਡੇ ਹੱਥ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਇਹ ਸਮਝਣ ਲਈ ਕਿ ਕੀ ਹੋ ਰਿਹਾ ਹੈ, ਲੋੜ ਹੋਵੇ ਤਾਂ ਸਕੈਨ ਦਾ ਪ੍ਰਬੰਧ ਕਰਦੇ ਹਾਂ। ਕਿਉਂਕਿ ਇਹ ਵਿੰਗ ਕਈ ਵੱਖ-ਵੱਖ ਸ਼ੁਰੂਆਤਾਂ ਤੋਂ ਆ ਸਕਦਾ ਹੈ, ਕੋਈ ਵੀ ਇਲਾਜ ਕਰਨ ਤੋਂ ਪਹਿਲਾਂ ਇਹ ਤੈਅ ਕੀਤਾ ਜਾਂਦਾ ਹੈ ਕਿ ਤੁਹਾਨੂੰ ਕਿਹੜੀ ਕਿਸਮ ਹੈ।
ਪਹਿਲਾ ਕਦਮ ਆਮ ਤੌਰ ’ਤੇ ਸਪਲਿੰਟ ਅਤੇ ਹੈਂਡ ਥੈਰੇਪੀ (ਹੱਥ ਦੀ ਕਸਰਤ ਵਾਲਾ ਇਲਾਜ) ਹੁੰਦਾ ਹੈ। ਹਾਲੀਆ ਸੱਟ ਲਈ, ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਪਲਿੰਟ ਵਿੱਚ ਸਿੱਧਾ ਰੱਖਣਾ ਵਿੰਗ ਨੂੰ ਬਣਨ ਤੋਂ ਪੂਰੀ ਤਰ੍ਹਾਂ ਰੋਕ ਸਕਦਾ ਹੈ, ਅਤੇ ਇਹ ਜਿੰਨੀ ਛੇਤੀ ਸ਼ੁਰੂ ਹੋਵੇ ਓਨਾ ਹੀ ਚੰਗਾ ਹੈ: ਜਿਨ੍ਹਾਂ ਲੋਕਾਂ ਦਾ ਇਲਾਜ ਸੱਟ ਦੇ ਛੇ ਹਫ਼ਤਿਆਂ ਦੇ ਅੰਦਰ ਹੁੰਦਾ ਹੈ, ਉਨ੍ਹਾਂ ਦੇ ਨਤੀਜੇ ਬਾਅਦ ਵਿੱਚ ਇਲਾਜ ਕਰਵਾਉਣ ਵਾਲਿਆਂ ਨਾਲੋਂ ਬਿਹਤਰ ਰਹਿੰਦੇ ਹਨ। ਸਪਲਿੰਟ ਸਿਰਫ਼ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਰੱਖਦਾ ਹੈ। ਤੁਹਾਡਾ ਪੋਟਾ, ਤੁਹਾਡਾ ਨਕਲ (knuckle, ਉਂਗਲ ਦੇ ਮੁੱਢ ਵਾਲਾ ਜੋੜ) ਅਤੇ ਤੁਹਾਡੀਆਂ ਬਾਕੀ ਉਂਗਲਾਂ ਹਿੱਲਦੀਆਂ ਰਹਿੰਦੀਆਂ ਹਨ, ਕਿਉਂਕਿ ਪੂਰੀ ਉਂਗਲ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਨਾਲ ਪੋਟੇ ਨੂੰ ਆਕੜਨ ਦਾ ਮੌਕਾ ਮਿਲ ਜਾਂਦਾ ਹੈ। ਜੋ ਵਿੰਗ ਕੁਝ ਸਮੇਂ ਤੋਂ ਬਣਿਆ ਹੋਇਆ ਹੈ, ਉਸ ਲਈ ਅਸੀਂ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਜਿੰਨਾ ਹੋ ਸਕੇ ਓਨਾ ਸਿੱਧਾ ਕਰਨ ਲਈ ਪਲੱਸਤਰ (cast) ਵਰਤ ਸਕਦੇ ਹਾਂ, ਜਿਸ ਤੋਂ ਬਾਅਦ ਤਿੰਨ ਮਹੀਨੇ ਇੱਕ ਅਜਿਹਾ ਸਪਲਿੰਟ ਪਾਇਆ ਜਾਂਦਾ ਹੈ ਜੋ ਉਂਗਲ ਦੇ ਕੰਮ ਕਰਦਿਆਂ ਤੁਹਾਨੂੰ ਉਸਨੂੰ ਮੋੜਨ ਦਿੰਦਾ ਹੈ। ਸਰਜਰੀ ਬਾਰੇ ਸੋਚਣ ਤੋਂ ਪਹਿਲਾਂ ਇਹ ਤਰੀਕਾ ਅਜ਼ਮਾਉਣਾ ਬਣਦਾ ਹੈ।
ਜਦੋਂ ਸਪਲਿੰਟ ਅਤੇ ਥੈਰੇਪੀ ਨਾਲ ਕਾਫ਼ੀ ਸੁਧਾਰ ਨਾ ਹੋਇਆ ਹੋਵੇ, ਤਾਂ ਸਰਜਰੀ ਬਾਰੇ ਸੋਚਿਆ ਜਾ ਸਕਦਾ ਹੈ। ਓਪਰੇਸ਼ਨ ਵਿੱਚ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਕਰਨ ਵਾਲੇ ਟੈਂਡਨ ਨੂੰ ਦੁਬਾਰਾ ਬਣਾਇਆ ਜਾਂਦਾ ਹੈ, ਕਈ ਵਾਰ ਤੁਹਾਡੀ ਆਪਣੀ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ (forearm) ਤੋਂ ਲਏ ਟੈਂਡਨ ਦੇ ਇੱਕ ਛੋਟੇ ਟੁਕੜੇ ਨੂੰ ਗ੍ਰਾਫਟ (graft) ਵਜੋਂ ਵਰਤ ਕੇ। ਕੁਝ ਮਾਮਲਿਆਂ ਵਿੱਚ, ਹਥੇਲੀ ਵੱਲ ਖਿਸਕ ਚੁੱਕੇ ਟੈਂਡਨਾਂ ਨੂੰ ਵਾਪਸ ਜੋੜ ਦੇ ਉੱਪਰ ਉਨ੍ਹਾਂ ਦੀ ਸਹੀ ਥਾਂ ’ਤੇ ਲਿਆਂਦਾ ਜਾਂਦਾ ਹੈ। ਹਰ ਹਾਲਤ ਵਿੱਚ ਮਕਸਦ ਇੱਕੋ ਹੈ: ਤੁਸੀਂ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਮੁੜ ਸਿੱਧਾ ਕਰ ਸਕੋ ਅਤੇ ਉਂਗਲ ਦੇ ਅਟਕਣ ਜਾਂ ਹੇਠਾਂ ਮੁੜਨ ਤੋਂ ਬਿਨਾਂ ਇਸਨੂੰ ਵਰਤ ਸਕੋ। ਇਸ ਓਪਰੇਸ਼ਨ ਦਾ ਆਪਣਾ ਵੱਖਰਾ ਪੰਨਾ ਹੈ, ਅਤੇ ਕੋਈ ਵੀ ਫ਼ੈਸਲਾ ਕਰਨ ਤੋਂ ਪਹਿਲਾਂ ਅਸੀਂ ਗੱਲ ਕਰਾਂਗੇ ਕਿ ਤੁਹਾਡੀ ਖ਼ਾਸ ਉਂਗਲ ਲਈ ਇਸ ਵਿੱਚ ਕੀ-ਕੀ ਸ਼ਾਮਲ ਹੈ।
ਕੀ ਉਮੀਦ ਰੱਖੀਏ
ਅੱਗੇ ਕੀ ਹੋਵੇਗਾ, ਇਹ ਬਹੁਤ ਹੱਦ ਤੱਕ ਸਮੇਂ ’ਤੇ ਨਿਰਭਰ ਕਰਦਾ ਹੈ। ਜੇ ਛੇਤੀ ਫੜੀ ਜਾਵੇ, ਤਾਂ ਬੂਟੋਨੀਅਰ ਡਿਫ਼ਾਰਮਿਟੀ ਨੂੰ ਅਕਸਰ ਪੱਕਾ ਹੋਣ ਤੋਂ ਪਹਿਲਾਂ ਰੋਕਿਆ ਜਾ ਸਕਦਾ ਹੈ। ਸੱਟ ਤੋਂ ਛੇਤੀ ਬਾਅਦ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਪਲਿੰਟ ਵਿੱਚ ਸਿੱਧਾ ਰੱਖਣ ਨਾਲ ਵਿੰਗ ਨੂੰ ਬਣਨ ਤੋਂ ਪੂਰੀ ਤਰ੍ਹਾਂ ਰੋਕਿਆ ਜਾ ਸਕਦਾ ਹੈ, ਅਤੇ ਜਿਨ੍ਹਾਂ ਲੋਕਾਂ ਦਾ ਇਲਾਜ ਛੇ ਹਫ਼ਤਿਆਂ ਦੇ ਅੰਦਰ ਹੁੰਦਾ ਹੈ, ਉਨ੍ਹਾਂ ਦੇ ਨਤੀਜੇ ਬਾਅਦ ਵਿੱਚ ਇਲਾਜ ਕਰਵਾਉਣ ਵਾਲਿਆਂ ਨਾਲੋਂ ਬਿਹਤਰ ਰਹਿੰਦੇ ਹਨ। ਜੇ ਇਸਨੂੰ ਉਵੇਂ ਹੀ ਛੱਡ ਦਿੱਤਾ ਜਾਵੇ, ਤਾਂ ਵਿੰਗ ਇੱਕੋ ਜਿਹਾ ਰਹਿਣ ਦੀ ਥਾਂ ਆਮ ਤੌਰ ’ਤੇ ਵਿਗੜਦਾ ਜਾਂਦਾ ਹੈ, ਕਿਉਂਕਿ ਆਪਣੀ ਥਾਂ ਤੋਂ ਖਿਸਕੇ ਟੈਂਡਨ ਉਂਗਲ ਨੂੰ ਉਸਦੀ ਮੁੜੀ ਹੋਈ ਸ਼ਕਲ ਵਿੱਚ ਹੋਰ ਅੱਗੇ ਖਿੱਚਦੇ ਰਹਿੰਦੇ ਹਨ। ਜੋ ਸੱਟ ਮਾਮੂਲੀ ਲੱਗਦੀ ਸੀ, ਉਹ ਹਫ਼ਤਿਆਂ ਬਾਅਦ ਇੱਕ ਆਕੜੀ ਹੋਈ, ਪੱਕੀ ਜੰਮੀ ਉਂਗਲ ਦਾ ਕਾਰਨ ਬਣ ਸਕਦੀ ਹੈ।
ਜੋ ਵਿੰਗ ਕੁਝ ਸਮੇਂ ਤੋਂ ਬਣਿਆ ਹੋਇਆ ਹੈ, ਉਸ ਲਈ ਵੀ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਇਲਾਜ ਦੀ ਅਸਲ ਭੂਮਿਕਾ ਹੈ। ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਜਿੰਨਾ ਹੋ ਸਕੇ ਓਨਾ ਸਿੱਧਾ ਕਰਨ ਲਈ ਪਲੱਸਤਰ, ਅਤੇ ਉਸ ਤੋਂ ਬਾਅਦ ਤਿੰਨ ਮਹੀਨੇ ਇੱਕ ਅਜਿਹਾ ਸਪਲਿੰਟ ਜੋ ਵਰਤੋਂ ਦੌਰਾਨ ਤੁਹਾਨੂੰ ਉਂਗਲ ਮੋੜਨ ਦਿੰਦਾ ਹੈ, ਚੰਗਾ ਕੰਮ ਕਰ ਸਕਦਾ ਹੈ। ਉਂਗਲ ਇਸ ਤਰੀਕੇ ਨਾਲ ਉਦੋਂ ਸੁਧਰਦੀ ਹੈ ਜਦੋਂ ਪਲੱਸਤਰ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਲਗਭਗ ਸਿੱਧਾ ਕਰ ਸਕੇ ਅਤੇ ਤੁਸੀਂ ਉਨ੍ਹਾਂ ਤਿੰਨ ਮਹੀਨਿਆਂ ਦੌਰਾਨ ਸਪਲਿੰਟ ਪਾ ਕੇ ਆਪਣੇ ਹੱਥ ਨੂੰ ਸਰਗਰਮੀ ਨਾਲ ਵਰਤੋ, ਅਤੇ ਨਾਲ-ਨਾਲ ਉਂਗਲ ਦਾ ਮੁੜਨਾ ਵੀ ਵਾਪਸ ਆਉਂਦਾ ਜਾਵੇ। ਅੰਗੂਠੇ ਦੀਆਂ ਸੱਟਾਂ ਲਈ, ਨਕਲ ਨੂੰ ਸਪਲਿੰਟ ਵਿੱਚ ਸਿੱਧਾ ਰੱਖਣਾ ਮਦਦ ਕਰ ਸਕਦਾ ਹੈ, ਜੇ ਇਹ ਵਿੰਗ ਬਣਨ ਤੋਂ ਪਹਿਲਾਂ ਸ਼ੁਰੂ ਹੋ ਜਾਵੇ।
ਸਰਜਰੀ ਦਾ ਮਕਸਦ ਇਹ ਹੈ ਕਿ ਤੁਸੀਂ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਮੁੜ ਸਿੱਧਾ ਕਰ ਸਕੋ। ਲੰਬੇ ਸਮੇਂ ਤੋਂ ਚੱਲ ਰਹੇ ਵਿੰਗ ਨੂੰ ਠੀਕ ਕਰਨ ਲਈ ਟੈਂਡਨ ਗ੍ਰਾਫਟ (tendon graft, ਲਾਇਆ ਗਿਆ ਟੈਂਡਨ ਦਾ ਟੁਕੜਾ) ਕਰਵਾਉਣ ਵਾਲੇ 18 ਲੋਕਾਂ ਦੇ ਇੱਕ ਰਿਪੋਰਟ ਕੀਤੇ ਸਮੂਹ ਵਿੱਚੋਂ, 16 ਦੇ ਨਤੀਜੇ ਚੰਗੇ ਜਾਂ ਬਹੁਤ ਵਧੀਆ ਰਹੇ। ਇੱਕ ਨਵੀਂ ਤਕਨੀਕ, ਜੋ ਉਂਗਲ ਨੂੰ ਛੇਤੀ ਹਿਲਾਉਣਾ ਸ਼ੁਰੂ ਕਰਵਾਉਂਦੀ ਹੈ, 11 ਮਾਮਲਿਆਂ ਵਿੱਚ ਕਾਰਗਰ ਰਹੀ ਦੱਸੀ ਗਈ ਹੈ। ਸਰਜਰੀ ਇਸ ਵਿੰਗ ਦੀ ਜਮਾਂਦਰੂ ਕਿਸਮ ਵਿੱਚ ਵੀ ਮਦਦ ਕਰ ਸਕਦੀ ਹੈ, ਜਿੱਥੇ ਇਹ ਜਨਮ ਤੋਂ ਹੀ ਮੌਜੂਦ ਹੁੰਦਾ ਹੈ।
ਇਹ ਇਮਾਨਦਾਰੀ ਨਾਲ ਕਹਿਣਾ ਬਣਦਾ ਹੈ ਕਿ ਹਰ ਸੁਧਾਰ ਟਿਕਿਆ ਨਹੀਂ ਰਹਿੰਦਾ। ਰਾਇਮੇਟਾਇਡ ਆਰਥਰਾਈਟਿਸ ਤੋਂ ਪ੍ਰਭਾਵਿਤ ਉਂਗਲਾਂ ਲਈ, ਬਾਅਦ ਵਾਲੇ ਪੜਾਵਾਂ ਵਿੱਚ ਹੋ ਸਕਦਾ ਹੈ ਕਿ ਸਿਰਫ਼ ਨਰਮ ਟਿਸ਼ੂ ਦੀ ਸਰਜਰੀ ਸੁਧਾਰ ਕਾਇਮ ਨਾ ਰੱਖ ਸਕੇ, ਅਤੇ ਲੰਮੇ ਸਮੇਂ ਦੇ ਨਤੀਜਿਆਂ ਬਾਰੇ ਪਹਿਲਾਂ ਤੋਂ ਕਹਿਣਾ ਔਖਾ ਹੁੰਦਾ ਹੈ। ਜਦੋਂ ਵਿੰਗ ਮੁੜ ਆ ਜਾਵੇ ਜਾਂ ਬਣਿਆ ਰਹੇ, ਤਾਂ ਕੋਈ ਵੱਖਰਾ ਓਪਰੇਸ਼ਨ ਬਿਹਤਰ ਹੱਲ ਹੋ ਸਕਦਾ ਹੈ। ਸ਼ੁਰੂਆਤ ਭਾਵੇਂ ਕੋਈ ਵੀ ਹੋਵੇ, ਹਕੀਕੀ ਟੀਚਾ ਇੱਕ ਅਜਿਹੀ ਉਂਗਲ ਹੈ ਜਿਸਨੂੰ ਤੁਸੀਂ ਸਿੱਧਾ ਕਰ ਸਕੋ ਅਤੇ ਵਰਤ ਸਕੋ, ਨਾ ਕਿ ਬਿਲਕੁਲ ਆਮ ਉਂਗਲ ਦਾ ਵਾਅਦਾ।
ਡਾਕਟਰ ਨੂੰ ਕਦੋਂ ਮਿਲਣਾ ਚਾਹੀਦਾ ਹੈ
ਬੂਟੋਨੀਅਰ ਡਿਫ਼ਾਰਮਿਟੀ ਵਿੱਚ ਛੇਤੀ ਧਿਆਨ ਦੇਣ ਦਾ ਫ਼ਾਇਦਾ ਹੁੰਦਾ ਹੈ, ਇਸ ਲਈ ਇਹ ਜਾਣਨਾ ਚੰਗਾ ਹੈ ਕਿ ਕਦੋਂ ਕਦਮ ਚੁੱਕਣਾ ਹੈ। ਜੇ ਤੁਹਾਡੀ ਉਂਗਲ ਨੂੰ ਸੱਟ ਲੱਗੀ ਹੈ ਅਤੇ ਵਿਚਕਾਰਲਾ ਜੋੜ ਸਿੱਧਾ ਨਹੀਂ ਹੁੰਦਾ, ਜਾਂ ਸੱਟ ਤੋਂ ਕੁਝ ਦਿਨ ਬਾਅਦ ਵੀ ਉਂਗਲ ਮੁੜੀ ਹੋਈ ਅਤੇ ਸੁੱਜੀ ਹੋਈ ਰਹਿੰਦੀ ਹੈ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਅਤੇ ਮਾਹਰ ਡਾਕਟਰ ਦੀ ਜਾਂਚ ਲਈ ਕਹੋ। ਸਪਲਿੰਟ ਜਿੰਨੀ ਛੇਤੀ ਸ਼ੁਰੂ ਹੁੰਦਾ ਹੈ, ਵਿੰਗ ਨੂੰ ਪੱਕਾ ਹੋਣ ਤੋਂ ਪਹਿਲਾਂ ਰੋਕਣ ਦੀ ਸੰਭਾਵਨਾ ਓਨੀ ਹੀ ਵਧੀਆ ਹੁੰਦੀ ਹੈ।
ਕੁਝ ਨਿਸ਼ਾਨੀਆਂ ਲਈ ਹੋਰ ਛੇਤੀ ਦੇਖਭਾਲ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਜੇ ਤੁਹਾਡੀ ਉਂਗਲ ਜਾਂ ਹੱਥ ਗਰਮ, ਲਾਲ, ਸੁੱਜਿਆ ਹੋਇਆ ਅਤੇ ਦਰਦ ਭਰਿਆ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਤਾਂ ਉਸੇ ਦਿਨ ਕਿਸੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹੀ ਗੱਲ ਉਦੋਂ ਵੀ ਲਾਗੂ ਹੁੰਦੀ ਹੈ ਜੇ ਕੋਈ ਉਂਗਲ ਫਿੱਕੀ, ਠੰਢੀ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੀ ਪੈ ਜਾਵੇ, ਜਾਂ ਜੇ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਾਅਦ ਅਚਾਨਕ ਉਸ ਵਿੱਚ ਤੁਹਾਡਾ ਅਹਿਸਾਸ ਜਾਂ ਹਿਲਜੁਲ ਖ਼ਤਮ ਹੋ ਜਾਵੇ। ਜੇ ਸੱਟ ਵਾਲੇ ਜੋੜ ਉੱਤੇ ਚਮੜੀ ਫਟੀ ਹੋਈ ਹੋਵੇ, ਜਾਂ ਉਂਗਲ ਦੀ ਸ਼ਕਲ ਸਾਫ਼ ਤੌਰ ’ਤੇ ਵਿਗੜੀ ਹੋਈ ਦਿਸੇ, ਤਾਂ ਵੀ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਜੇ ਇਸਦੀ ਬਜਾਏ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਜਗਾ ਦਿੰਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਆਪਣਾ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਦੀ ਜਾਂਚ ਲਈ ਕਹੋ। ਜੇ ਤੁਸੀਂ ਕੰਮਕਾਜੀ ਸਮੇਂ ਤੋਂ ਬਾਅਦ ਜਾਂ ਹਫ਼ਤੇ ਦੇ ਅਖ਼ੀਰ ਵਿੱਚ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਹੀਂ ਕਰ ਸਕਦੇ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਵਿਸਥਾਰ ਵਿੱਚ
Advanced reading: the deeper science (optional)
ਇਹ ਹਿੱਸਾ ਤੁਹਾਡੇ ਆਪਣੇ ਇਲਾਜ ਦੇ ਫ਼ੈਸਲਿਆਂ ਲਈ ਲੋੜ ਤੋਂ ਵੱਧ ਡੂੰਘਾਈ ਵਿੱਚ ਜਾਂਦਾ ਹੈ। ਬੂਟੋਨੀਅਰ ਡਿਫ਼ਾਰਮਿਟੀ ਵਾਧੂ ਪੜ੍ਹਨ ਦੇ ਯੋਗ ਹੈ ਕਿਉਂਕਿ ਦਰਦ ਕਰਦੀ, ਸੁੱਜੀ ਹੋਈ, ਮੁੜੀ ਹੋਈ ਉਂਗਲ ਦਾ ਜੋ ਇਲਾਜ ਸੁਭਾਵਿਕ ਹੀ ਮਨ ਵਿੱਚ ਆਉਂਦਾ ਹੈ, ਯਾਨੀ ਇਸ ਨੂੰ ਆਰਾਮ ਦੇਣਾ ਅਤੇ ਟਿਕਾ ਕੇ ਰੱਖਣਾ, ਉਹੀ ਇੱਕ ਚੀਜ਼ ਹੈ ਜਿਸ ਦੀ ਸਬੂਤ ਖ਼ਾਸ ਤੌਰ ’ਤੇ ਹਿਮਾਇਤ ਨਹੀਂ ਕਰਦੇ।
ਛੇਤੀ ਹਿਲਾਉਣਾ, ਲੰਬੇ ਸਮੇਂ ਤੱਕ ਜਾਮ ਰੱਖਣਾ ਨਹੀਂ
ਸੈਂਟਰਲ ਸਲਿੱਪ ਦੀ ਸੱਟ ਦੇ ਇਲਾਜਾਂ ਦੇ ਇੱਕ ਸਿਸਟਮੈਟਿਕ ਰਿਵਿਊ (systematic review) ਨੇ ਪਾਇਆ ਕਿ ਸਬੂਤ ਸੀਮਤ ਹਨ, ਅਤੇ ਖੁੱਲ੍ਹੀਆਂ (ਜ਼ਖ਼ਮ ਵਾਲੀਆਂ) ਅਤੇ ਬੰਦ ਦੋਵੇਂ ਤਰ੍ਹਾਂ ਦੀਆਂ ਸੱਟਾਂ ਲਈ ਵੱਖ-ਵੱਖ ਤਰੀਕਿਆਂ ਦੀ ਭੂਮਿਕਾ ਚੰਗੀ ਤਰ੍ਹਾਂ ਸਮਰਥਿਤ ਨਹੀਂ ਹੈ [1]। ਇਸ ਸੀਮਾ ਦੇ ਅੰਦਰ, ਵੱਖ-ਵੱਖ ਅਧਿਐਨਾਂ ਦੇ ਸਬੂਤ ਝਿਜਕ ਨਾਲ ਛੇਤੀ ਹਿਲਾਉਣ ਦੀ ਹਿਮਾਇਤ ਕਰਦੇ ਹਨ ਅਤੇ ਲੰਬੇ ਸਮੇਂ ਤੱਕ ਜਾਮ ਰੱਖਣ ਦੀ ਹਿਮਾਇਤ ਨਹੀਂ ਕਰਦੇ [1]।
ਇਹ ਗੱਲ ਸਾਫ਼-ਸਾਫ਼ ਕਹਿਣ ਯੋਗ ਹੈ ਕਿਉਂਕਿ ਇਹ ਸੁਭਾਵਿਕ ਪ੍ਰਤੀਕਿਰਿਆ ਦੇ ਉਲਟ ਜਾਂਦੀ ਹੈ। ਫ਼ਰਕ ਇਸ ਗੱਲ ਵਿੱਚ ਹੈ ਕਿ ਠੀਕ ਹੋ ਰਹੀ ਸੈਂਟਰਲ ਸਲਿੱਪ ਦੀ ਰਾਖੀ ਕਰਨਾ, ਜਿਸ ਲਈ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਰੱਖਣਾ ਜ਼ਰੂਰੀ ਹੈ, ਅਤੇ ਪੂਰੀ ਉਂਗਲ ਨੂੰ ਜਾਮ ਕਰ ਦੇਣਾ, ਜਿਸ ਨਾਲ ਪੋਟੇ ਵਾਲਾ ਜੋੜ ਸਿੱਧੀ ਹਾਲਤ ਵਿੱਚ ਆਕੜ ਜਾਂਦਾ ਹੈ ਅਤੇ ਪੂਰੀ ਉਂਗਲ ਸਖ਼ਤ ਹੋ ਜਾਂਦੀ ਹੈ। ਸਪਲਿੰਟ ਦਾ ਮਕਸਦ ਇੱਕ ਜੋੜ ਨੂੰ ਟਿਕਾ ਕੇ ਰੱਖਣਾ ਹੈ ਜਦੋਂ ਕਿ ਬਾਕੀ ਜੋੜ ਹਿੱਲਦੇ ਰਹਿਣ।
ਵਿੰਗ ਇੱਕੋ ਜਿਹਾ ਰਹਿਣ ਦੀ ਥਾਂ ਵਿਗੜਦਾ ਕਿਉਂ ਹੈ
ਬੂਟੋਨੀਅਰ ਇੱਕ ਵਧਦਾ ਜਾਣ ਵਾਲਾ ਵਿੰਗ ਹੈ, ਜੋ ਅਸਾਧਾਰਨ ਗੱਲ ਹੈ ਅਤੇ ਸਮਝਣ ਯੋਗ ਹੈ। ਸੈਂਟਰਲ ਸਲਿੱਪ ਵਿਚਕਾਰਲੀ ਹੱਡੀ ਦੇ ਮੁੱਢ ਨਾਲ ਜੁੜਦੀ ਹੈ ਅਤੇ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਕਰਦੀ ਹੈ। ਜਦੋਂ ਇਹ ਨਾਕਾਮ ਹੋ ਜਾਂਦੀ ਹੈ, ਉਹ ਜੋੜ ਮੁੜ ਕੇ ਡਿੱਗ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਦੋਵੇਂ ਲੇਟਰਲ ਬੈਂਡ (lateral bands, ਪਾਸੇ ਵਾਲੀਆਂ ਤੰਦਾਂ), ਜੋ ਆਮ ਤੌਰ ’ਤੇ ਜੋੜ ਦੇ ਧੁਰੇ ਤੋਂ ਉੱਪਰ ਚੱਲਦੀਆਂ ਹਨ, ਉਸ ਤੋਂ ਹੇਠਾਂ ਖਿਸਕ ਜਾਂਦੀਆਂ ਹਨ।
ਜਦੋਂ ਉਹ ਧੁਰੇ ਤੋਂ ਹੇਠਾਂ ਆ ਜਾਂਦੀਆਂ ਹਨ, ਤਾਂ ਉਹੀ ਟੈਂਡਨ ਜੋ ਪਹਿਲਾਂ ਵਿਚਕਾਰਲੇ ਜੋੜ ਨੂੰ ਸਿੱਧਾ ਕਰਨ ਵਿੱਚ ਮਦਦ ਕਰਦੇ ਸਨ, ਉਸ ਨੂੰ ਮੋੜਨ ਲੱਗ ਪੈਂਦੇ ਹਨ, ਅਤੇ ਨਾਲ ਹੀ ਪੋਟੇ ਨੂੰ ਹੱਦੋਂ ਵੱਧ ਪਿੱਛੇ ਵੱਲ (hyperextension) ਖਿੱਚਦੇ ਹਨ। ਇਸ ਤਰ੍ਹਾਂ ਵਿੰਗ ਆਪਣੇ ਆਪ ਨੂੰ ਹੋਰ ਪੱਕਾ ਕਰਦਾ ਜਾਂਦਾ ਹੈ: ਉਂਗਲ ਨੂੰ ਸਿੱਧਾ ਕਰਨ ਦੀ ਹਰ ਕੋਸ਼ਿਸ਼ ਉਨ੍ਹਾਂ ਬਣਤਰਾਂ ਨੂੰ ਕੱਸ ਦਿੰਦੀ ਹੈ ਜੋ ਹੁਣ ਇਸ ਨੂੰ ਮੁੜਿਆ ਹੋਇਆ ਰੱਖ ਰਹੀਆਂ ਹਨ। ਇਸੇ ਕਰਕੇ ਮਾਮੂਲੀ ਲੱਗਣ ਵਾਲੀ ਸੱਟ ਹਫ਼ਤਿਆਂ ਬਾਅਦ ਪੱਕਾ ਜੰਮਿਆ ਵਿੰਗ ਪੈਦਾ ਕਰ ਸਕਦੀ ਹੈ, ਅਤੇ ਇਸੇ ਕਰਕੇ ਸਾਦੇ ਸਪਲਿੰਟ ਦਾ ਮੌਕਾ ਸ਼ੁਰੂਆਤੀ ਸਮੇਂ ਵਿੱਚ ਹੀ ਹੁੰਦਾ ਹੈ।
ਉਹ ਵਿੰਗ ਜੋ ਬੂਟੋਨੀਅਰ ਨਹੀਂ ਹੈ
ਇੱਕ ਉਂਗਲ ਸੈਂਟਰਲ ਸਲਿੱਪ ਦੀ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਿਨਾਂ ਵੀ ਇਹੀ ਸ਼ਕਲ ਅਪਣਾ ਸਕਦੀ ਹੈ, ਅਤੇ ਇਲਾਜ ਬਿਲਕੁਲ ਵੱਖਰੇ ਹੁੰਦੇ ਹਨ। ਬੂਟੋਨੀਅਰ ਅਤੇ ਸੂਡੋਬੂਟੋਨੀਅਰ (pseudoboutonnière, ਨਕਲੀ ਬੂਟੋਨੀਅਰ) ਵਿੰਗ ਆਪਣੀ ਅੰਦਰੂਨੀ ਬਣਤਰ ਦੀ ਖ਼ਰਾਬੀ, ਪਛਾਣ ਅਤੇ ਇਲਾਜ ਵਿੱਚ ਵੱਖਰੇ ਹਨ [2], ਸੂਡੋ ਕਿਸਮ ਵਿਚਕਾਰਲੇ ਜੋੜ ਉੱਤੇ ਵੋਲਰ ਪਲੇਟ (volar plate, ਜੋੜ ਦੇ ਹਥੇਲੀ ਵਾਲੇ ਪਾਸੇ ਦੀ ਸਖ਼ਤ ਗੱਦੀ) ਦੀ ਸੱਟ ਤੋਂ ਪੈਦਾ ਹੁੰਦੀ ਹੈ, ਜਿੱਥੇ ਪੋਟੇ ਵਾਲਾ ਜੋੜ ਹੱਦੋਂ ਵੱਧ ਪਿੱਛੇ ਖਿੱਚੇ ਜਾਣ ਦੀ ਥਾਂ ਦੂਜੇ ਵੱਲੋਂ ਮੋੜੇ ਜਾਣ ’ਤੇ ਆਮ ਵਾਂਗ ਮੁੜਦਾ ਹੈ।
ਮਰੀਜ਼ ਦੇ ਕੋਲ ਹੀ ਇਨ੍ਹਾਂ ਵਿੱਚ ਫ਼ਰਕ ਕਰਨਾ ਪੋਟੇ ਉੱਤੇ ਨਿਰਭਰ ਕਰਦਾ ਹੈ। ਅਸਲੀ ਬੂਟੋਨੀਅਰ ਵਿੱਚ ਪੋਟਾ ਹੱਦੋਂ ਵੱਧ ਪਿੱਛੇ ਵੱਲ ਰਹਿੰਦਾ ਹੈ ਅਤੇ ਮੋੜੇ ਜਾਣ ਦਾ ਵਿਰੋਧ ਕਰਦਾ ਹੈ, ਖ਼ਾਸ ਕਰਕੇ ਜਦੋਂ ਵਿਚਕਾਰਲਾ ਜੋੜ ਸਿੱਧਾ ਕੀਤਾ ਹੋਵੇ; ਸੂਡੋਬੂਟੋਨੀਅਰ ਵਿੱਚ ਇਹ ਆਸਾਨੀ ਨਾਲ ਮੁੜ ਜਾਂਦਾ ਹੈ। ਸੂਡੋਬੂਟੋਨੀਅਰ ਉੱਤੇ ਇਸ ਤਰ੍ਹਾਂ ਸਪਲਿੰਟ ਲਾਉਣਾ ਜਿਵੇਂ ਇਹ ਅਸਲੀ ਹੋਵੇ, ਗ਼ਲਤ ਜੋੜ ਦਾ ਇਲਾਜ ਕਰਨਾ ਹੈ।
ਇਹ ਸੱਟਾਂ ਦੇ ਉਸ ਪਰਿਵਾਰ ਦਾ ਹਿੱਸਾ ਹੈ ਜਿਸ ਦੀ ਪਛਾਣ ਇਸ ਗੱਲ ਤੋਂ ਹੁੰਦੀ ਹੈ ਕਿ ਟੈਂਡਨ ਕਿੱਥੇ ਨਾਕਾਮ ਹੁੰਦਾ ਹੈ
ਬੂਟੋਨੀਅਰ, ਮੈਲੇਟ ਫ਼ਿੰਗਰ (mallet finger) ਅਤੇ ਸੈਜਿਟਲ ਬੈਂਡ (sagittal band) ਦੀ ਸੱਟ ਦੇ ਨਾਲ, ਸਿੱਧਾ ਕਰਨ ਵਾਲੇ ਢਾਂਚੇ ਦੀਆਂ ਤਿੰਨ ਬੰਦ (ਬਿਨਾਂ ਜ਼ਖ਼ਮ ਵਾਲੀਆਂ) ਸੱਟਾਂ ਵਿੱਚੋਂ ਇੱਕ ਹੈ, ਜਿਨ੍ਹਾਂ ਦੀ ਵੰਡ ਇਸ ਗੱਲ ਤੋਂ ਹੁੰਦੀ ਹੈ ਕਿ ਢਾਂਚਾ ਕਿਸ ਹਿੱਸੇ (zone) ਵਿੱਚ ਨਾਕਾਮ ਹੁੰਦਾ ਹੈ [3]। ਤਿੰਨੋਂ ਸੱਟ ਦੇ ਕੁਝ ਦਿਨਾਂ ਦੇ ਅੰਦਰ ਅਸਧਾਰਨ ਢੰਗ ਨਾਲ ਟਿਕੀ ਸੁੱਜੀ ਹੋਈ ਉਂਗਲ ਵਜੋਂ ਸਾਹਮਣੇ ਆ ਸਕਦੀਆਂ ਹਨ, ਅਤੇ ਹਰ ਇੱਕ ਲਈ ਸਪਲਿੰਟ ਦੀ ਵੱਖਰੀ ਸਥਿਤੀ ਚਾਹੀਦੀ ਹੈ, ਜੋ ਇਸ ਗੱਲ ਦਾ ਵਿਹਾਰਕ ਕਾਰਨ ਹੈ ਕਿ ਹਫ਼ਤਿਆਂ ਦੇ ਸਪਲਿੰਟ ਨਾਲ ਬੱਝਣ ਤੋਂ ਪਹਿਲਾਂ ਪੱਕੀ ਪਛਾਣ ਤੱਕ ਪਹੁੰਚਣਾ ਜ਼ਰੂਰੀ ਹੈ।
ਹਵਾਲੇ
[1] Geoghegan L, Wormald JCR, Adami RZ, Rodrigues JN. Central slip extensor tendon injuries: a systematic review of treatments. J Hand Surg Eur Vol. 2019;44(8):825-32. https://doi.org/10.1177/1753193419845311
[2] Hanson ZC, Thompson RG, Andrews JR, Lourie GM. Boutonniere versus pseudoboutonniere deformities: pathoanatomy, diagnosis, and treatment. J Hand Surg Am. 2023;48(5):489-97. https://doi.org/10.1016/j.jhsa.2022.10.019
[3] Lin JD, Strauch RJ. Closed soft tissue extensor mechanism injuries (mallet, boutonniere, and sagittal band). J Hand Surg Am. 2014;39(5):1005-11. https://doi.org/10.1016/j.jhsa.2013.11.018
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A staged technique for the repair of traumatic boutonniere deformity allows the surgeon to divide the deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- Differentiating a true boutonniere deformity from a pseudoboutonniere injury is critical in determining clinical management [2].
- A retrospective study of fifty-four longstanding post-burn boutonnière deformities was carried out to evaluate the problems associated with the surgical procedures [3].
- An understanding of the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities [4].
- Early treatment of central slip injuries can prevent the deformity [5].
- Transection of the terminal extensor tendon is a useful procedure for salvage of the boutonniere deformity [6].
- No boutonniere deformities were produced in a series of 20 patients who had chronic mallet finger deformity treated with central slip tenotomy [7].
- Reconstruction of the central slip by the transverse retinacular ligament is not indicated for boutonnière deformities with severe contracture of the lateral band [8].
- The best indication for reconstruction of the central slip by the transverse retinacular ligament is in cases in which the central slip is defective and conservative treatment is not effective [8].
- Similar results occurred for chronic boutonniere deformity using serial casting for adequate extension followed by 3 months of relative motion flexion (RMF) orthotic use, which should be attempted prior to surgical intervention [9].
- A new surgical technique with early mobilization is an effective and simplified treatment of Boutonniere deformity [10].
- The natural history of the boutonnière deformity in rheumatoid arthritis is outlined, and a simple method of repair is described [11].
- Chronic boutonniere deformity will respond to relative motion flexion splinting if serial casting can place the proximal interphalangeal joint in less than -20° extension, and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion [12].
- The Y-shaped tendon graft can be a useful procedure for the correction of chronic boutonniere deformity [13].
- In a patient series of 18 patients, the Y-shaped tendon graft provided good or excellent results in 16 patients [13].
- Extension splinting of the metacarpophalangeal (MP) joint may be effective if traumatic thumb injuries are treated before development of a boutonnière deformity [14].
- Congenital boutonniere deformity is understood as various embryonic developmental failures [15].
- A reliable surgical option for congenital boutonniere deformity involves central slip reconstruction [15].
- Extensor tenotomy to correct a boutonnière deformity of long standing markedly lessened disability with restoration of flexion of the distal joint [16].
- In chronic boutonniere deformity, when the lateral bands are deficient or damaged, the cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results [17].
- Extension splinting may be effective if traumatic thumb injuries are treated before deformity development [18].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a traumatic thumb boutonnière deformity is established [18].
- The prevalence of boutonnière deformity without rheumatoid arthritis or trauma is approximately 13% [19].
- Current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries, are summarized [20].
- Long-term results following soft tissue reconstruction for boutonniere finger deformity in rheumatoid arthritis are unreliable [24].
- Recurrent or persistent deformity in rheumatoid arthritis is best treated with a salvage procedure [24].
Anatomy & Pathophysiology
Extensor Mechanism Anatomy
- The extensor mechanism of the finger at the level of the proximal interphalangeal (PIP) joint consists of both intrinsic and extrinsic contributions [28].
- The extensor tendon entering the digit is the continuation of the extensor digitorum communis (EDC), with contributions from the extensor indicis proprius in the index finger and the extensor digiti quinti in the small finger [28].
- In 30% of cases, the EDC has a separate insertion into the base of the proximal phalanx, but extension of the metacarpophalangeal (MP) joint typically occurs through the pull of the sagittal bands [28].
- The principal bony insertion of the extrinsic digital extensors is on the dorsal proximal aspect of the middle phalanx [32].
- Metacarpophalangeal joint extension is provided by extrinsic extensor force transmitted through the sagittal bands [32].
- Distal interphalangeal joint extension is achieved through conjoined lateral bands composed of tendinous slips from both extrinsic and intrinsic tendons [32].
- The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the MP joint [41].
- At the level of the middle of the proximal phalanx, transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [41].
- Oblique fibers (spiral fibers) from the lateral bands sweep over the distal third of the proximal phalanx to insert onto the lateral tubercles at the base of the middle phalanx, extending the middle phalanx [41].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [41].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon, which inserts at the base of the distal phalanx to extend it [41].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [41].
- The flexor digiti quinti brevis is structurally and functionally similar to the deep head of the dorsal interossei, forming the ulnar lateral band of the little finger [41].
Pathophysiology & Biomechanics
- A boutonniere deformity requires subluxation of the lateral bands volar to the axis of rotation of the PIP joint [22].
- Damage to the central slip alone does not cause a boutonniere deformity [22].
- A boutonniere deformity occurs only when the central slip, triangular ligament, and transverse and oblique fibers of the interosseous hood are all damaged [22].
- Detachment of the central slip from the middle phalanx produces a decrease in extension of the PIP joint [22].
- When the transverse and oblique fibers of the interosseous hood are divided in addition to the central slip, extension at the PIP joint is further decreased [22].
- Early treatment of central slip injuries can prevent the development of the deformity [5].
- The extensor mechanism is a complex structure that demands a delicate balance from intrinsic and extrinsic tendons of the hand [28].
- Injury to the extensor mechanism can disrupt this delicate balance, leading to significant sequelae [28].
- Understanding the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities [4].
Classification
- A staged management plan allows the surgeon to divide traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem [1].
- The choice of surgical procedure for rheumatoid boutonniere deformity is dependent on accurate staging of the deformity, which is based on the flexibility of the proximal interphalangeal joint and the state of the articular cartilage [23].
- In a cadaveric model, damage to the central slip alone does not cause a boutonniere deformity [22].
- The boutonniere deformity requires subluxation of the lateral bands volar to the axis of rotation of the PIP joint [22].
- In a cadaveric model, the central slip, triangular ligament, and oblique fibers need to all be damaged to cause subluxation of the lateral bands which leads to an acute boutonniere deformity [29].
- Anterior dislocation of the proximal interphalangeal joint is associated with ruptures of the central slip of the extensor mechanism and results in boutonnière deformity unless repaired [27].
- The incidence of uncorrectable swan-neck and boutonniere deformities is estimated to be between 8% and 16% during the first 2 years after the onset of systemic disease in rheumatoid arthritis [23].
- The prevalence of boutonniere deformities in patients with established rheumatoid arthritis is approximately 36% [23].
Clinical Presentation
Diagnostic Differentiation and Classification
- The surgeon can divide the boutonniere deformity into various categories to use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
Etiology and Pathomechanics
- The cause of boutonniere deformity in rheumatoid arthritis is chronic synovitis of the proximal interphalangeal joint [23].
- Combined injury of the central slip, triangular ligament, and transverse and oblique fibers of the interosseous hood causes a boutonniere deformity [22].
Prevalence and Natural History
- A swan-neck or boutonniere deformity occurs in approximately half of patients with rheumatoid arthritis [23].
- The incidence of uncorrectable swan-neck and boutonniere deformities is estimated to be between 8% and 16% during the first 2 years after the onset of systemic disease [23].
- The prevalence of finger deformities in patients with established rheumatoid arthritis is approximately 36% for boutonniere deformities [23].
- The natural history of the boutonnière deformity in rheumatoid arthritis is outlined in the literature [11].
Clinical Assessment and Testing
- The central slip tenodesis test detects disruption of the central slip before the boutonniere deformity becomes established [34].
- The central slip tenodesis test is applicable in uncooperative children and unconscious patients [34].
- Treating swan neck and boutonniere deformities of the PIP joint requires understanding the cause, biomechanical changes, and articular status [26].
Investigations
Clinical Examination and Diagnostic Tests
- A careful physical examination is essential to direct care and future testing if indicated [31].
- Diagnostic tests such as imaging and serum laboratory studies are useful in the determination of pathology but can be expensive, time consuming, and often nonspecific [31].
Biomechanical and Pathomechanical Assessment
Imaging and Advanced Modalities
- A computational 3D model validation reassures the reliability of research in understanding the pathomechanics of boutonniere deformity [21].
Treatment
Non-Operative
- Early treatment of central slip injuries can prevent the development of boutonniere deformity [5].
- Extension splinting of the metacarpophalangeal joint may be effective for traumatic thumb boutonniere deformity if treated before the deformity develops [14].
- Extension splinting may be effective for traumatic thumb boutonniere deformity if treated before deformity development [18].
- Chronic boutonniere deformity responds to relative motion flexion splinting if serial casting places the proximal interphalangeal joint in less than -20° extension and the patient actively uses a relative motion flexion orthosis for 3 months [12].
- Serial casting for adequate extension followed by 3 months of relative motion flexion orthotic use should be attempted prior to surgical intervention for chronic boutonniere deformity [9].
- The use of relative motion flexion orthoses is effective in increasing active distal interphalangeal joint flexion and improving proximal interphalangeal joint extension in patients with Burton stage 1 chronic boutonniere deformity [30].
- Conservative treatment of closed central slip injuries involves immobilization of the proximal interphalangeal, distal interphalangeal, and metacarpophalangeal joints in full extension for four weeks followed by a Capener spring splint for two further weeks [92].
- In a review of 115 central slip injuries, 17 of 24 patients treated conservatively achieved an outcome of less than a 20° extension deficit at the proximal interphalangeal joint and more than 80% return of proximal interphalangeal joint flexion [92].
- Patients treated for central slip injuries within six weeks of injury had better outcomes than those treated later [92].
Operative
- A staged technique allows the surgeon to divide traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- Reconstruction of the central slip by the transverse retinacular ligament is best indicated in cases in which the central slip is defective and conservative treatment is not effective [8].
- A simple method of repair for the rheumatoid boutonnière deformity is described in the literature [11].
- In a patient series, the Y-shaped tendon graft provided good or excellent results in 16 of 18 patients with chronic boutonniere deformity [13].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a traumatic boutonnière deformity of the thumb is established [18].
- The cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results for chronic boutonniere deformity when the lateral bands are deficient or damaged [17].
- A reliable surgical option involving central slip reconstruction is suggested for the congenital form of boutonniere deformity [15].
- A simple staged procedure using a central slip facilitation device is a valid alternative in the management of severe Dupuytren's proximal interphalangeal joint contracture, demonstrating reliable, reproducible correction of the deformity and acceptable patient outcomes [38].
Complications
- In a patient series of 18 patients, the Y-shaped tendon graft provided good or excellent results in 16 of 18 patients for the correction of chronic boutonniere deformity [13].
- Extension splinting of the MP joint may be effective if traumatic thumb injuries are treated before development of a boutonnière deformity [14].
- The case extends understanding of congenital boutonniere deformity as various embryonic developmental failures and suggests a reliable surgical option involving central slip reconstruction [15].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a boutonnière deformity is established in the thumb [18].
- This article summarizes current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries [20].
- This validation reassures the reliability of the research in understanding the pathomechanics of boutonniere deformity [21].
- In a cadaver model, detachment of the central slip from the middle phalanx produced a decrease in extension of the PIP joint [22].
- When the transverse and oblique fibers of the interosseous hood were also divided after central slip detachment, extension at the PIP joint was further decreased [22].
- A boutonniere deformity occurred only when all 3 structures (central slip, transverse and oblique fibers of the interosseous hood, and triangular ligament) were damaged [22].
- Division of the central slip leads to loss of extension at the PIP joint [22].
- The prevalence of finger deformities in patients with established rheumatoid arthritis is approximately 14% for swan-neck deformities and 36% for boutonniere deformities [23].
- In the later stages of both swan-neck and boutonniere deformities, soft-tissue procedures alone may not result in lasting operative correction [23].
- Long-term results following soft tissue reconstruction are unreliable [24].
- Recurrent or persistent deformity is best treated with a salvage procedure [24].
- Treating swan neck and boutonniere deformities of the PIP joint is a difficult challenge that requires understanding the cause, biomechanical changes, and articular status [26].
- Anterior dislocation of the proximal interphalangeal joint is associated with ruptures of the central slip of the extensor mechanism [27].
- Anterior dislocation of the proximal interphalangeal joint results in boutonnière deformity unless repaired [27].
Recovery
Non-Operative Management
- Serial casting for adequate extension followed by 3 months of relative motion flexion (RMF) orthotic use should be attempted prior to surgical intervention for chronic boutonniere deformity [9].
- Chronic boutonniere deformity responds to relative motion flexion splinting if serial casting places the proximal interphalangeal joint in less than -20° extension and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion [12].
- Extension splinting of the metacarpophalangeal joint may be effective for traumatic thumb boutonniere injuries if treated before the development of a boutonnière deformity [14].
Operative Management
- A staged technique allows the surgeon to divide the traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- The Y-shaped tendon graft provided good or excellent results in 16 of 18 patients for the correction of chronic boutonniere deformity [13].
- Reconstruction of the central slip by the transverse retinacular ligament is indicated in cases in which the central slip is defective and conservative treatment is not effective, but is not indicated for boutonnière deformities with severe contracture of the lateral band [8].
- A simple method of repair for the correction of the rheumatoid boutonnière deformity has been described [11].
- A new surgical technique with early mobilization for chronic boutonniere deformity was reported to be an effective and simplified treatment in 11 cases [10].
- Central slip reconstruction is a reliable surgical option for the congenital form of boutonniere deformity [15].
Outcomes and Prognosis
- Early treatment of central slip injuries can prevent the boutonniere deformity [5].
- Long-term results following soft tissue reconstruction for boutonniere finger deformity in rheumatoid arthritis are unreliable, and recurrent or persistent deformity is best treated with a salvage procedure [24].
- In the later stages of rheumatoid boutonniere deformities, soft-tissue procedures alone may not result in lasting operative correction [23].
- A patient with boutonniere deformity of the second toe after planter dislocation of the proximal interphalangeal joint reported neither deformity nor difficulty when last seen 22 months after the operation [95].
Key Evidence
- [L4] With this plan of management, the surgeon is able to divide the boutonniere deformity into various categories and then use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery. [1] (10.1016/s0363-5023(83)80009-4)
- [L5] Differentiating a true boutonniere deformity from a pseudoboutonniere injury is critical in determining clinical management. [2] (10.1016/j.jhsa.2022.10.019)
- [L4] A retrospective study of fifty-four longstanding post-burn boutonnière deformities was carried out to evaluate the problems associated with the surgical procedures. [3] (10.1016/0266-7681(86)90006-9)
- [L5] An understanding of the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities. [4] (10.5435/jaaos-d-14-00272)
- [L5] The paper outlines the anatomy, pathoanatomy, and treatment concepts for boutonniere deformity, emphasizing that early treatment of central slip injuries can prevent the deformity. [5] (10.1016/s0749-0712(21)00060-3)
- [L4] Transection of the terminal extensor tendon is a useful procedure for salvage of the boutonniere deformity. [6] (10.1016/s0749-0712(21)00065-2)
- [L4] No boutonniere deformities were produced in this series of 20 patients who had chronic mallet finger deformity. [7] (10.1016/s0363-5023(87)80205-8)
- [L4] This procedure is not indicated for boutonnière deformities with severe contracture of the lateral band; its best indication is in cases in which the central slip is defective and conservative treatment is not effective. [8] (10.1016/0266-7681(90)90080-n)
- [L4] Similar results occurred for chronic boutonniere deformity using serial casting for adequate extension followed by 3 months of RMF orthotic use, which should be attempted prior to surgical intervention. [9] (10.1016/j.jht.2023.02.005)
- [L4] Our technique is an effective and simplified treatment of Boutonniere deformity. [10] (10.1097/bth.0000000000000152)
- [L4] The natural history of the boutonnière deformity in rheumatoid arthritis is outlined, and a simple method of repair is described. [11] (10.2106/00004623-196951070-00009)
- [L4] Chronic boutonniere deformity will respond to relative motion flexion splinting if serial casting can place the proximal interphalangeal joint in less than -20° extension, and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion. [12] (10.1097/sap.0000000000002307)
- [L4] The Y-shaped tendon graft can be a useful procedure for the correction of chronic boutonniere deformity; in our patient series, this provided good or excellent results in 16 of 18 patients. [13] (10.1016/j.jhsa.2021.01.003)
- [L4] Extension splinting of the MP joint may be effective if these injuries are treated before development of a boutonnière deformity. [14] (10.1016/s0266-7681(00)80024-8)
- [Case_report] The case extends understanding of congenital boutonniere deformity as various embryonic developmental failures and suggests a reliable surgical option involving central slip reconstruction. [15] (10.1016/j.jhsa.2014.05.030)
- [L4] In chronic boutonniere deformity, when the lateral bands are deficient or damaged, the cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results. [17] (10.1016/j.jhsa.2017.04.010)
- [L4] Extension splinting may be effective if treated before deformity development, but surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a boutonnière deformity is established. [18] (10.1054/jhsb.1999.0303)
- [L3] The prevalence of boutonnière deformity without rheumatoid arthritis or trauma is approximately 13%. [19] (10.1177/1753193417704610)
- [L5] This article summarizes current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries. [20] (10.1016/j.jhsa.2013.11.018)
- [L5] This validation reassures the reliability of the research in understanding the pathomechanics of boutonniere deformity. [21] (10.1186/s13018-025-06329-3)
- [L5] [22] (10.1016/j.jhsa.2017.07.011)
- [L5] [23] (10.5435/00124635-199903000-00002)
- [L5] Long-term results following soft tissue reconstruction are unreliable, and recurrent or persistent deformity is best treated with a salvage procedure. [24] (10.1016/j.jhsa.2011.05.029)
- [L4] Treating swan neck and boutonniere deformities of the PIP joint is a difficult challenge that requires understanding the cause, biomechanical changes, and articular status. [26] (10.1016/j.hcl.2017.12.006)
- [Paper] [28] (10.1016/j.hcl.2012.05.044)
- [Paper] In a cadaveric model, the central slip, triangular ligament, and oblique fibers need to all be damaged to cause subluxation of the lateral bands which leads to an acute boutonniere deformity. [29] (10.1016/s0363-5023(12)60014-8)
- [L4] The use of RMFO is effective in increasing active distal interphalangeal joint flexion and improving PIP extension in patients with Burton stage 1 chronic boutonniere deformity. [30] (10.1016/j.jhsa.2022.08.007)
- [Paper] The test detects disruption of the central slip before the boutonniere deformity becomes established and is applicable in uncooperative children and unconscious patients. [34] (10.1016/0266-7681(94)90057-4)
- [L4] The simple staged procedure is a valid alternative in the management of severe Dupuytren's PIPJ contracture, demonstrating reliable, reproducible correction of the deformity and acceptable patient outcomes. [38] (10.1177/1753193412439673)
- [L4] [92] (10.1177/1758998318822663)
- [Case_report] The patient reported neither deformity nor difficulty when last seen 22 months after the operation. [95] (10.1007/s00402-009-0816-x)
References
[1] A staged technique for the repair of the traumatic boutonniere deformity. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80009-4
[2] Boutonniere Versus Pseudoboutonniere Deformities: Pathoanatomy, Diagnosis, and Treatment. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.019
[3] Reconstructive surgery of the post-burn boutonnière deformity. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90006-9
[4] Posttraumatic Boutonnière and Swan Neck Deformities. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-14-00272
[5] BOUTONNIERE DEFORMITY. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00060-3
[6] TREATMENT OF THE CHRONIC BOUTONNIERE DEFORMITY BY EXTENSOR TENOTOMY. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00065-2
[7] Central slip tenotomy for chronic mallet finger deformity. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80205-8
[8] Reconstruction of the Central Slip by the Transverse Retinacular Ligament for Boutonnière Deformity. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681(90)90080-n
[9] The relative motion concept in acute and chronic boutonniere deformity: Invited commentary. Journal of Hand Therapy. 2023. DOI: 10.1016/j.jht.2023.02.005
[10] Chronic Boutonniere Deformities, Supple, or Stiff: A New Surgical Technique With Early Mobilization in 11 Cases. Techniques in Hand & Upper Extremity Surgery. 2017. DOI: 10.1097/bth.0000000000000152
[11] Correction of the Rheumatoid Boutonnière Deformity. The Journal of Bone & Joint Surgery. 1969. DOI: 10.2106/00004623-196951070-00009
[12] A Paradigm Shift in Managing Acute and Chronic Boutonniere Deformity. Annals of Plastic Surgery. 2020. DOI: 10.1097/sap.0000000000002307
[13] Y-Shaped Tendon Graft—A Technique in the Reconstruction of Posttraumatic Chronic Boutonniere Deformity. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.01.003
[14] Traumatic Boutonnière Deformity of the Thumb. Journal of Hand Surgery. 2000. DOI: 10.1016/s0266-7681(00)80024-8
[15] Restoration of the Central Slip in Congenital Form of Boutonniere Deformity: Case Report. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.05.030
[16] Extensor Tenotomy for Chronic Boutonniere Deformity of the Finger: REPORT OF TWO CASES.. The Journal of Bone and Joint Surgery. American Volume. 1965.
[17] Chronic Boutonniere Deformity: Cross-Lateral Band Technique Using Palmaris Longus Autograft. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.04.010
[18] TRAUMATIC BOUTONNIÈRE DEFORMITY OF THE THUMB. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2000. DOI: 10.1054/jhsb.1999.0303
[19] Thumb boutonnière deformity without rheumatoid arthritis or trauma. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193417704610
[20] Closed Soft Tissue Extensor Mechanism Injuries (Mallet, Boutonniere, and Sagittal Band). The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.11.018
[21] Assessment of the ligamentous stress distribution in the pathomechanics of the boutonniere deformity through a computational 3D model. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06329-3
[22] Biomechanics of the Acute Boutonniere Deformity. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.07.011
[23] Operative Correction of Swan-Neck and Boutonniere Deformities in the Rheumatoid Hand. Journal of the American Academy of Orthopaedic Surgeons. 1999. DOI: 10.5435/00124635-199903000-00002
[24] Treatment of Boutonniere Finger Deformity in Rheumatoid Arthritis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.05.029
[26] Treating the Proximal Interphalangeal Joint in Swan Neck and Boutonniere Deformities. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.006
[27] Anterior dislocation of the proximal interphalangeal joint. A cause of rupture of the central slip of the extensor mechanism.. The Journal of bone and joint surgery. American volume. 1970.
[28] Boutonnière and Pulley Rupture in Elite Athletes. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.044
[29] Biomechanics of the Acute Boutonniere Deformity. The Journal of Hand Surgery. 2012. DOI: 10.1016/s0363-5023(12)60014-8
[30] The Use of Relative Motion Flexion Orthoses for Chronic Boutonniere Deformity. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.08.007
[31] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[32] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[34] The Central Slip Tenodesis Test for Early Diagnosis of Potential Boutonnière Deformities. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90057-4
[38] Management of severe Dupuytren’s contracture of the proximal interphalangeal joint with use of a central slip facilitation device. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412439673
[41] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[92] Therapeutic management of closed central slip injuries: Outcome of a service evaluation. Hand Therapy. 2019. DOI: 10.1177/1758998318822663
[95] Boutonniere deformity of the second toe after planter dislocation of proximal interphalangeal joint: a case report. Archives of Orthopaedic and Trauma Surgery. 2009. DOI: 10.1007/s00402-009-0816-x