Patients › Hand
ਪਾਇਰੋਕਾਰਬਨ ਇੰਟਰਪੋਜ਼ੀਸ਼ਨ ਆਰਥਰੋਪਲਾਸਟੀ (ਪਾਇਰੋਕਾਰਬਨ ਇੰਪਲਾਂਟ ਨਾਲ ਜੋੜ ਦੀ ਨਵੀਂ ਸਤਹ)
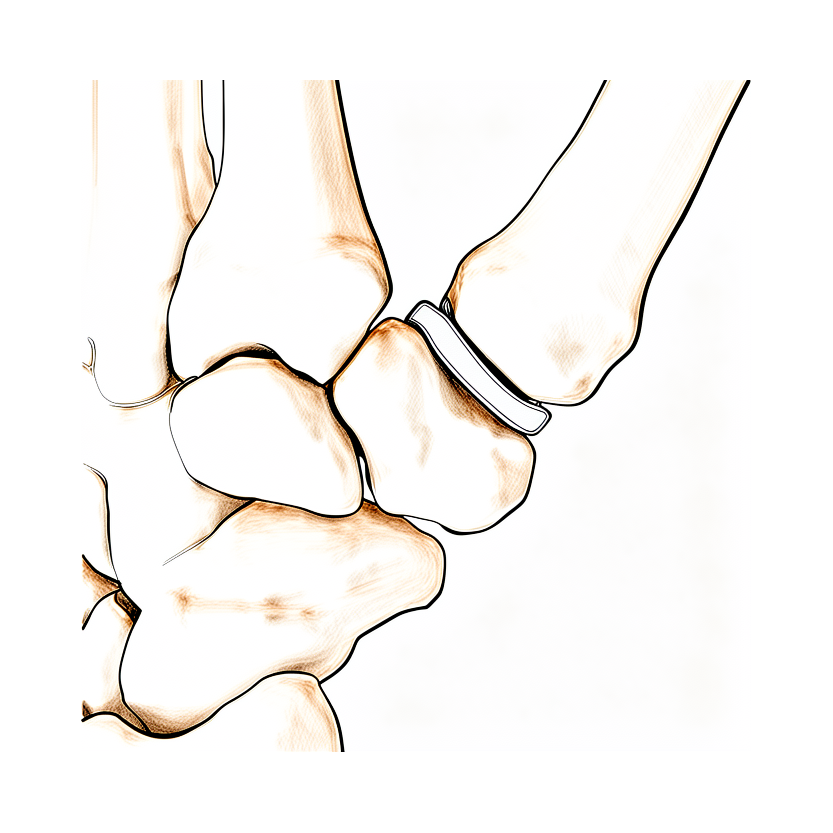
ਇਹ ਓਪਰੇਸ਼ਨ ਕਿਉਂ ਸੁਝਾਇਆ ਗਿਆ ਹੈ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਜੋ ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ ਹਨ, ਤੁਹਾਡੀ ਹਾਲਤ ਲਈ ਢੁਕਵੇਂ ਸਭ ਤੋਂ ਘੱਟ ਚੀਰ-ਫਾੜ ਵਾਲੇ ਇਲਾਜਾਂ ਤੋਂ ਸ਼ੁਰੂਆਤ ਕਰਦੇ ਹਨ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ 'ਤੇ ਉਨ੍ਹਾਂ ਦਾ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਡੇ ਕੋਲ ਆਉਣ ਦੀ ਸਲਾਹ ਦਿੱਤੀ ਹੈ, ਤਾਂ ਵੀ ਮੈਡੀਕੇਅਰ ਰਿਬੇਟ (Medicare rebate, ਸਰਕਾਰ ਵੱਲੋਂ ਖ਼ਰਚੇ ਦੀ ਵਾਪਸੀ) ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ (ਡਾਕਟਰ ਵੱਲੋਂ ਭੇਜਣ ਦੀ ਚਿੱਠੀ) ਲੈਣਾ ਪਵੇਗਾ। ਤੁਹਾਡੀ ਮੁਲਾਕਾਤ ਵੇਲੇ ਅਸੀਂ ਤੁਹਾਡੀ ਤਕਲੀਫ਼ ਬਾਰੇ ਪੂਰੀ ਜਾਣਕਾਰੀ ਲੈਂਦੇ ਹਾਂ, ਤੁਹਾਡੇ ਹੱਥ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਬਿਮਾਰੀ ਦੀ ਪਛਾਣ ਦੀ ਪੁਸ਼ਟੀ ਕਰਨ ਲਈ ਲੋੜ ਹੋਵੇ ਤਾਂ ਐਕਸ-ਰੇ ਜਾਂ ਸਕੈਨ ਕਰਵਾਉਂਦੇ ਹਾਂ।
ਇਸ ਓਪਰੇਸ਼ਨ ਵਿੱਚ ਕਿਸੇ ਛੋਟੇ ਜੋੜ ਦੀ ਘਿਸੀ ਹੋਈ ਸਤਹ ਨੂੰ ਕਾਰਬਨ ਦੇ ਇੱਕ ਚਿਕਨੇ, ਖ਼ਾਸ ਸ਼ਕਲ ਵਾਲੇ ਟੁਕੜੇ ਨਾਲ ਬਦਲਿਆ ਜਾਂਦਾ ਹੈ। ਇਹ ਆਮ ਤੌਰ 'ਤੇ ਲੰਬੇ ਸਮੇਂ ਤੋਂ ਚੱਲ ਰਹੇ ਗਠੀਏ (ਆਰਥਰਾਈਟਿਸ) ਲਈ ਸੁਝਾਇਆ ਜਾਂਦਾ ਹੈ, ਜੋ ਕੰਮਕਾਜ ਵਿੱਚ ਤਬਦੀਲੀ, ਹੈਂਡ ਥੈਰੇਪੀ (ਹੱਥ ਦੀ ਵਿਸ਼ੇਸ਼ ਥੈਰੇਪੀ) ਜਾਂ ਸਪਲਿੰਟ ਨਾਲ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋਇਆ। ਅਸੀਂ ਆਮ ਤੌਰ 'ਤੇ ਪਹਿਲਾਂ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲਾ ਇਲਾਜ ਅਜ਼ਮਾਉਂਦੇ ਹਾਂ ਅਤੇ ਸਰਜਰੀ ਬਾਰੇ ਉਦੋਂ ਸੋਚਦੇ ਹਾਂ ਜਦੋਂ ਉਸ ਨਾਲ ਕਾਫ਼ੀ ਸੁਧਾਰ ਨਾ ਹੋਇਆ ਹੋਵੇ। ਕੁਝ ਬਣਤਰ ਸੰਬੰਧੀ ਸਮੱਸਿਆਵਾਂ ਵਿੱਚ, ਸਰਜਰੀ ਸ਼ੁਰੂ ਤੋਂ ਹੀ ਸੁਝਾਈ ਜਾ ਸਕਦੀ ਹੈ।
ਓਪਰੇਸ਼ਨ ਦਾ ਮਕਸਦ ਜੋੜ ਨੂੰ ਹਿੱਲਦਾ ਰੱਖਦੇ ਹੋਏ ਦਰਦ ਘਟਾਉਣਾ ਹੈ। ਇਸ ਦਾ ਮਕਸਦ ਅੰਗੂਠੇ ਦੀ ਕੁਦਰਤੀ ਉਚਾਈ ਬਣਾਈ ਰੱਖਣਾ ਅਤੇ ਚੂੰਢੀ ਤੇ ਪਕੜ ਦੀ ਤਾਕਤ ਨੂੰ ਬਚਾ ਕੇ ਰੱਖਣਾ ਵੀ ਹੈ। ਅੰਗੂਠੇ ਦੀ ਜੜ੍ਹ ਵਾਲੇ ਜੋੜ ਲਈ, ਦਰਮਿਆਨੇ ਸਮੇਂ ਦੀ ਜਾਂਚ (medium-term follow-up) ਵੇਲੇ 91% ਇੰਪਲਾਂਟ ਅਜੇ ਵੀ ਚੰਗੀ ਤਰ੍ਹਾਂ ਕੰਮ ਕਰ ਰਹੇ ਹੁੰਦੇ ਹਨ। ਅਸੀਂ ਤੁਹਾਡੇ ਨਾਲ ਇਸ ਵਿਕਲਪ ਬਾਰੇ ਗੱਲ ਕਰਾਂਗੇ ਅਤੇ ਮਿਲ ਕੇ ਫ਼ੈਸਲਾ ਕਰਾਂਗੇ ਕਿ ਕੀ ਇਹ ਤੁਹਾਡੇ ਹੱਥ ਅਤੇ ਤੁਹਾਡੇ ਟੀਚਿਆਂ ਲਈ ਢੁਕਵਾਂ ਹੈ।
ਓਪਰੇਸ਼ਨ ਤੋਂ ਪਹਿਲਾਂ
ਆਪਣੇ ਓਪਰੇਸ਼ਨ ਤੋਂ ਪਹਿਲਾਂ ਦੇ ਸੱਤ ਘੰਟਿਆਂ ਵਿੱਚ ਕੁਝ ਵੀ ਨਾ ਖਾਓ ਅਤੇ ਨਾ ਪੀਓ। ਅਸੀਂ ਛੇ ਦੀ ਬਜਾਏ ਸੱਤ ਘੰਟੇ ਇਸ ਲਈ ਕਹਿੰਦੇ ਹਾਂ ਤਾਂ ਜੋ ਜੇ ਓਪਰੇਸ਼ਨਾਂ ਦੀ ਸੂਚੀ ਜਲਦੀ ਚੱਲ ਰਹੀ ਹੋਵੇ ਤਾਂ ਤੁਹਾਡੀ ਸਰਜਰੀ ਪਹਿਲਾਂ ਕੀਤੀ ਜਾ ਸਕੇ। ਤੁਹਾਡੇ ਸਰਜਨ ਤੁਹਾਨੂੰ ਦੱਸਣਗੇ ਕਿ ਤੁਹਾਡੀਆਂ ਨਿਯਮਤ ਦਵਾਈਆਂ ਵਿੱਚੋਂ ਕਿਹੜੀਆਂ ਰੋਕਣੀਆਂ ਹਨ ਅਤੇ ਕਦੋਂ, ਅਤੇ ਤੁਸੀਂ ਜੋ ਵੀ ਲੈਂਦੇ ਹੋ ਉਸ ਸਭ ਦੀ ਲਿਖਤੀ ਸੂਚੀ ਨਾਲ ਲਿਆਉਣਾ ਮਦਦਗਾਰ ਹੁੰਦਾ ਹੈ। ਬਾਅਦ ਵਿੱਚ ਤੁਹਾਨੂੰ ਗੱਡੀ ਵਿੱਚ ਘਰ ਲਿਜਾਣ ਲਈ ਕਿਸੇ ਦਾ ਪ੍ਰਬੰਧ ਕਰੋ, ਅਤੇ ਢਿੱਲੇ, ਆਰਾਮਦਾਇਕ ਕੱਪੜੇ ਪਾਓ। ਓਪਰੇਸ਼ਨ ਦੀ ਯੋਜਨਾ ਬਣਾਉਣ ਲਈ ਆਮ ਤੌਰ 'ਤੇ ਸਾਨੂੰ ਸਿਰਫ਼ ਐਕਸ-ਰੇ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ, ਹਾਲਾਂਕਿ ਕਦੇ-ਕਦੇ MRI ਜਾਂ ਅਲਟਰਾਸਾਊਂਡ ਸਕੈਨ ਵੀ ਵਰਤਿਆ ਜਾਂਦਾ ਹੈ। ਜੇ ਤੁਹਾਨੂੰ ਹੋਰ ਬਿਮਾਰੀਆਂ ਵੀ ਹਨ, ਤਾਂ ਹੋ ਸਕਦਾ ਹੈ ਤੁਹਾਨੂੰ ਖ਼ੂਨ ਦੇ ਟੈਸਟਾਂ ਦੀ ਜਾਂ ਅਨੱਸਥੀਟਿਸਟ (ਬੇਹੋਸ਼ੀ ਵਾਲਾ ਡਾਕਟਰ, ਜੋ ਅਨੱਸਥੀਸੀਆ ਦਿੰਦਾ ਹੈ) ਨਾਲ ਮੁਲਾਕਾਤ ਦੀ ਲੋੜ ਪਵੇ। ਜ਼ਿਆਦਾਤਰ ਮਰੀਜ਼ਾਂ ਨੂੰ ਇਨ੍ਹਾਂ ਦੋਵਾਂ ਵਿੱਚੋਂ ਕਿਸੇ ਦੀ ਵੀ ਲੋੜ ਨਹੀਂ ਪੈਂਦੀ।
ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਦਿਨ
ਤੁਸੀਂ ਹਸਪਤਾਲ ਦੇ ਸਰਜੀਕਲ ਦਾਖ਼ਲਾ ਵਿਭਾਗ ਵਿੱਚ ਪਹੁੰਚਦੇ ਹੋ, ਜਿੱਥੇ ਤੁਹਾਡਾ ਦਾਖ਼ਲਾ ਕੀਤਾ ਜਾਂਦਾ ਹੈ ਅਤੇ ਤੁਹਾਨੂੰ ਓਪਰੇਸ਼ਨ ਥੀਏਟਰ ਲਈ ਤਿਆਰ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਤੁਸੀਂ ਅਨੱਸਥੀਟਿਸਟ, ਯਾਨੀ ਤੁਹਾਡੇ ਅਨੱਸਥੀਸੀਆ ਦੀ ਦੇਖ-ਰੇਖ ਕਰਨ ਵਾਲੇ ਡਾਕਟਰ, ਨੂੰ ਮਿਲੋਗੇ। ਇਹ ਓਪਰੇਸ਼ਨ ਜਨਰਲ ਅਨੱਸਥੀਸੀਆ (ਬੇਹੋਸ਼ੀ ਵਾਲੀ ਦਵਾਈ) ਹੇਠ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਓਪਰੇਸ਼ਨ ਦੌਰਾਨ ਤੁਸੀਂ ਪੂਰੀ ਤਰ੍ਹਾਂ ਬੇਹੋਸ਼ ਹੋਵੋਗੇ। ਕੁਝ ਮਰੀਜ਼ਾਂ ਨੂੰ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਦਰਦ ਤੋਂ ਰਾਹਤ ਲਈ ਨਾਲ ਰੀਜਨਲ ਨਰਵ ਬਲਾਕ (ਨਸ ਨੂੰ ਸੁੰਨ ਕਰਨ ਵਾਲਾ ਟੀਕਾ) ਵੀ ਦਿੱਤਾ ਜਾ ਸਕਦਾ ਹੈ; ਇਸ ਦਾ ਫ਼ੈਸਲਾ ਅਨੱਸਥੀਟਿਸਟ ਉਸੇ ਦਿਨ ਤੁਹਾਡੇ ਨਿੱਜੀ ਹਾਲਾਤ ਦੇਖ ਕੇ ਕਰਦੇ ਹਨ।
ਫਿਰ ਤੁਹਾਨੂੰ ਓਪਰੇਸ਼ਨ ਥੀਏਟਰ ਵਿੱਚ ਲਿਜਾਇਆ ਜਾਂਦਾ ਹੈ, ਜਿੱਥੇ ਓਪਰੇਸ਼ਨ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਬਾਅਦ ਵਿੱਚ ਤੁਸੀਂ ਰਿਕਵਰੀ ਵਾਲੀ ਥਾਂ (ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਨਿਗਰਾਨੀ ਵਾਲਾ ਕਮਰਾ) ਵਿੱਚ ਜਾਗਦੇ ਹੋ, ਜਿੱਥੇ ਅਨੱਸਥੀਸੀਆ ਦਾ ਅਸਰ ਉਤਰਨ ਤੱਕ ਨਰਸਾਂ ਤੁਹਾਡੀ ਦੇਖ-ਰੇਖ ਕਰਦੀਆਂ ਹਨ। ਜਦੋਂ ਤੁਹਾਡੀ ਹਾਲਤ ਸਥਿਰ ਹੋ ਜਾਂਦੀ ਹੈ, ਤਾਂ ਪ੍ਰਕਿਰਿਆ ਅਤੇ ਤੁਹਾਡੇ ਠੀਕ ਹੋਣ ਦੇ ਹਿਸਾਬ ਨਾਲ, ਤੁਸੀਂ ਜਾਂ ਤਾਂ ਵਾਰਡ ਵਿੱਚ ਜਾਂਦੇ ਹੋ ਜਾਂ ਘਰ ਜਾਂਦੇ ਹੋ।
ਓਪਰੇਸ਼ਨ ਵਿੱਚ ਕੀ ਕੀਤਾ ਜਾਂਦਾ ਹੈ
ਤੁਹਾਡੇ ਸਰਜਨ ਹੱਥ ਦੇ ਜਿਸ ਹਿੱਸੇ ਦਾ ਓਪਰੇਸ਼ਨ ਹੋ ਰਿਹਾ ਹੈ ਉਸ ਉੱਤੇ ਇੱਕੋ ਚੀਰਾ ਲਗਾਉਂਦੇ ਹਨ। ਇਸ ਖੁੱਲ੍ਹੀ ਥਾਂ ਰਾਹੀਂ, ਉਹ ਜੋੜ ਦੀਆਂ ਘਿਸੀਆਂ ਹੋਈਆਂ, ਖ਼ਰਾਬ ਸਤਹਾਂ ਕੱਢ ਦਿੰਦੇ ਹਨ। ਘਿਸੀਆਂ ਸਤਹਾਂ ਦੀ ਥਾਂ ਉੱਤੇ, ਉਹ ਕਾਰਬਨ ਦਾ ਇੱਕ ਚਿਕਨਾ, ਖ਼ਾਸ ਸ਼ਕਲ ਵਾਲਾ ਟੁਕੜਾ ਲਗਾਉਂਦੇ ਹਨ ਜੋ ਹੱਡੀਆਂ ਦੇ ਵਿਚਕਾਰ ਬੈਠਦਾ ਹੈ। ਇਹ ਵਿੱਥ-ਭਰਾਊ ਟੁਕੜਾ (spacer) ਜੋੜ ਦੀ ਘਿਸੀ ਹੋਈ ਸਤਹ ਦਾ ਕੰਮ ਸੰਭਾਲ ਲੈਂਦਾ ਹੈ, ਤਾਂ ਜੋ ਹੱਡੀਆਂ ਇੱਕ-ਦੂਜੇ ਉੱਤੇ ਰਗੜਨ ਦੀ ਬਜਾਏ ਸੁਖਾਲੇ ਢੰਗ ਨਾਲ ਖਿਸਕਣ।
ਹੱਥ ਦੀ ਜੜ੍ਹ ਵਿੱਚ ਅੰਗੂਠੇ ਦੇ ਜੋੜ ਲਈ, ਤੁਹਾਡੇ ਸਰਜਨ ਹੱਡੀਆਂ ਦੇ ਵਿਚਕਾਰ ਵਿੱਥ-ਭਰਾਊ ਟੁਕੜਾ ਰੱਖ ਕੇ ਅੰਗੂਠੇ ਦੀ ਕੁਦਰਤੀ ਉਚਾਈ ਬਣਾਈ ਰੱਖਦੇ ਹਨ। ਫਿਰ ਜੋੜ ਦੀ ਮੁਰੰਮਤ ਕੀਤੀ ਜਾਂਦੀ ਹੈ ਅਤੇ ਉਸ ਨੂੰ ਸਹਾਰਾ ਦਿੱਤਾ ਜਾਂਦਾ ਹੈ ਤਾਂ ਜੋ ਇਹ ਚੰਗੀ ਸਥਿਤੀ ਵਿੱਚ ਠੀਕ ਹੋਵੇ। ਠੀਕ ਹੋਣ ਦੌਰਾਨ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਨੂੰ ਸਿੱਧੀ ਸਥਿਤੀ ਵਿੱਚ ਸਥਿਰ ਰੱਖਿਆ ਜਾ ਸਕਦਾ ਹੈ।
ਚੀਰੇ ਨੂੰ ਟਾਂਕਿਆਂ ਨਾਲ ਬੰਦ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। ਜ਼ਖ਼ਮ ਉੱਤੇ ਪੱਟੀ ਕੀਤੀ ਜਾਂਦੀ ਹੈ, ਅਤੇ ਸਾਡੀ ਟੀਮ ਤੁਹਾਨੂੰ ਦੱਸੇਗੀ ਕਿ ਪਹਿਲੇ ਦਿਨਾਂ ਵਿੱਚ ਇਸ ਦੀ ਦੇਖਭਾਲ ਕਿਵੇਂ ਕਰਨੀ ਹੈ।
ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ
ਇਸ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਾਅਦ ਜ਼ਿਆਦਾਤਰ ਮਰੀਜ਼ ਇੱਕ ਰਾਤ ਹਸਪਤਾਲ ਵਿੱਚ ਰਹਿੰਦੇ ਹਨ, ਹਾਲਾਂਕਿ ਕੁਝ ਉਸੇ ਦਿਨ ਘਰ ਜਾ ਸਕਦੇ ਹਨ। ਤੁਸੀਂ ਰਿਕਵਰੀ ਵਾਲੀ ਥਾਂ ਵਿੱਚ ਜਾਗਦੇ ਹੋ, ਫਿਰ ਵਾਰਡ ਵਿੱਚ ਚਲੇ ਜਾਂਦੇ ਹੋ। ਨਰਸਾਂ ਤੁਹਾਨੂੰ ਆਰਾਮ ਵਿੱਚ ਰੱਖਣਗੀਆਂ ਅਤੇ ਲੋੜ ਪੈਣ 'ਤੇ ਤੁਹਾਨੂੰ ਦਰਦ ਦੀ ਦਵਾਈ ਦੇਣਗੀਆਂ। ਤੁਹਾਡਾ ਹੱਥ ਪੱਟੀ ਅਤੇ ਸਪਲਿੰਟ ਵਿੱਚ ਹੋਵੇਗਾ, ਜੋ ਠੀਕ ਹੋਣ ਦੌਰਾਨ ਓਪਰੇਸ਼ਨ ਵਾਲੀ ਥਾਂ ਦੀ ਰੱਖਿਆ ਕਰਦੇ ਹਨ। ਜਿਵੇਂ ਹੀ ਤੁਸੀਂ ਸਥਿਰ ਮਹਿਸੂਸ ਕਰੋ, ਤੁਸੀਂ ਬਿਸਤਰੇ ਤੋਂ ਉੱਠ ਕੇ ਤੁਰ-ਫਿਰ ਸਕਦੇ ਹੋ। ਕਿਰਪਾ ਕਰਕੇ ਘਰ ਵਿੱਚ ਪਹਿਲੇ 24 ਘੰਟਿਆਂ ਲਈ ਕਿਸੇ ਨੂੰ ਆਪਣੇ ਕੋਲ ਰਹਿਣ ਦਾ ਪ੍ਰਬੰਧ ਕਰੋ। ਅਸੀਂ ਪੱਟੀ ਲਗਭਗ 10 ਦਿਨ ਲੱਗੀ ਰਹਿਣ ਦਿੰਦੇ ਹਾਂ; ਕਿਰਪਾ ਕਰਕੇ ਉਸ ਤੋਂ ਪਹਿਲਾਂ ਇਸ ਨੂੰ ਨਾ ਉਤਾਰੋ, ਜਦੋਂ ਤੱਕ ਅਸੀਂ ਤੁਹਾਨੂੰ ਨਾ ਕਹੀਏ। ਜਦੋਂ ਅਸੀਂ ਤੁਹਾਨੂੰ ਮਿਲਦੇ ਹਾਂ ਤਾਂ ਅਸੀਂ ਇਸ ਨੂੰ ਬਦਲਦੇ ਜਾਂ ਉਤਾਰਦੇ ਹਾਂ।
ਸਿਹਤਯਾਬੀ
ਪਹਿਲੇ ਦਿਨਾਂ ਅਤੇ ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਤੁਹਾਡੇ ਹੱਥ ਵਿੱਚ ਕੁਝ ਦਰਦ ਅਤੇ ਸੋਜ ਦੀ ਉਮੀਦ ਰੱਖੋ। ਇਹ ਠੀਕ ਹੋਣ ਦਾ ਇੱਕ ਆਮ ਹਿੱਸਾ ਹੈ ਅਤੇ ਹੌਲੀ-ਹੌਲੀ ਘਟ ਜਾਂਦਾ ਹੈ। ਆਰਾਮ ਕਰਨ ਵੇਲੇ ਹੱਥ ਨੂੰ ਉੱਚਾ ਰੱਖਣ ਨਾਲ ਮਦਦ ਮਿਲਦੀ ਹੈ, ਅਤੇ ਜੋ ਦਰਦ ਦੀ ਦਵਾਈ ਅਸੀਂ ਤੁਹਾਨੂੰ ਦਿੰਦੇ ਹਾਂ ਉਹ ਤਕਲੀਫ਼ ਨੂੰ ਘਟਾਏਗੀ। ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਦਾ ਸਭ ਤੋਂ ਤੇਜ਼ ਦਰਦ ਸ਼ੁਰੂ ਵਿੱਚ ਹੀ ਲੰਘ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਉਸ ਤੋਂ ਬਾਅਦ ਆਰਾਮ ਲਗਾਤਾਰ ਵਧਦਾ ਜਾਂਦਾ ਹੈ।
ਤੁਹਾਡਾ ਹੱਥ ਪੱਟੀ ਅਤੇ ਸਪਲਿੰਟ ਵਿੱਚ ਹੋਵੇਗਾ, ਜੋ ਠੀਕ ਹੋਣ ਦੌਰਾਨ ਜੋੜ ਦੀ ਰੱਖਿਆ ਕਰਦੇ ਹਨ। ਅਸੀਂ ਪੱਟੀ ਲਗਭਗ 10 ਦਿਨ ਲੱਗੀ ਰਹਿਣ ਦਿੰਦੇ ਹਾਂ ਅਤੇ ਜਦੋਂ ਅਸੀਂ ਤੁਹਾਨੂੰ ਮਿਲਦੇ ਹਾਂ ਤਾਂ ਇਸ ਨੂੰ ਬਦਲਦੇ ਜਾਂ ਉਤਾਰਦੇ ਹਾਂ। ਹੱਥ ਦੀ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਮੁੜ-ਵਸੇਬਾ (rehabilitation) ਹੈਂਡ ਥੈਰੇਪੀ ਹੁੰਦੀ ਹੈ, ਫਿਜ਼ੀਓਥੈਰੇਪੀ ਨਹੀਂ। ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਤੁਹਾਡੀ ਹੈਂਡ ਥੈਰੇਪੀ Extend Rehabilitation ਵਿਖੇ ਰੂਬੀ ਡੂਲਨ ਨਾਲ ਹੁੰਦੀ ਹੈ। ਰੂਬੀ ਇੱਕ ਹੈਂਡ ਥੈਰੇਪਿਸਟ ਹਨ: ਜਿਵੇਂ-ਜਿਵੇਂ ਤੁਹਾਡਾ ਹੱਥ ਠੀਕ ਹੁੰਦਾ ਹੈ, ਉਹ ਤੁਹਾਡੀਆਂ ਕਸਰਤਾਂ ਵਿੱਚ ਤੁਹਾਡੀ ਅਗਵਾਈ ਕਰਨਗੇ ਅਤੇ ਤੁਹਾਨੂੰ ਲੋੜੀਂਦਾ ਕੋਈ ਵੀ ਸਪਲਿੰਟ ਬਣਾਉਣਗੇ। ਸ਼ੁਰੂ ਵਿੱਚ, ਕਸਰਤਾਂ ਹਲਕੀਆਂ ਹੁੰਦੀਆਂ ਹਨ ਅਤੇ ਉਨ੍ਹਾਂ ਦਾ ਧਿਆਨ ਸੋਜ ਨੂੰ ਘੱਟ ਰੱਖਣ ਉੱਤੇ ਹੁੰਦਾ ਹੈ। ਜਿਵੇਂ-ਜਿਵੇਂ ਹਰਕਤ ਵਾਪਸ ਆਉਂਦੀ ਹੈ, ਉਹ ਹੌਲੀ-ਹੌਲੀ ਵਧਦੀਆਂ ਹਨ ਤਾਂ ਜੋ ਮੋੜਨ, ਸਿੱਧਾ ਕਰਨ ਅਤੇ ਪਕੜਨ ਦੀ ਸਮਰੱਥਾ ਮੁੜ ਆ ਸਕੇ।
ਤੁਸੀਂ ਆਪਣੇ ਸਪਲਿੰਟ ਦੀਆਂ ਹੱਦਾਂ ਵਿੱਚ ਰਹਿੰਦੇ ਹੋਏ ਘਰ ਦੇ ਹਲਕੇ ਰੋਜ਼ਾਨਾ ਕੰਮ ਕਰ ਸਕੋਗੇ। ਜਦੋਂ ਤੱਕ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਹੱਥ ਨੂੰ ਸਥਿਰ ਰੱਖਿਆ ਗਿਆ ਹੈ, ਤੁਸੀਂ ਉਸ ਹੱਥ ਨਾਲ ਨਾ ਕੁਝ ਪਕੜ ਸਕੋਗੇ, ਨਾ ਚੂੰਢੀ ਭਰ ਸਕੋਗੇ ਅਤੇ ਨਾ ਹੀ ਭਾਰ ਚੁੱਕ ਸਕੋਗੇ। ਸਪਲਿੰਟ ਉਤਰਨ ਅਤੇ ਤੁਹਾਡੇ ਸਰਜਨ ਵੱਲੋਂ ਇਜਾਜ਼ਤ ਮਿਲਣ ਤੋਂ ਬਾਅਦ, ਤੁਸੀਂ ਹੱਥ ਨੂੰ ਪਹਿਲਾਂ ਨਾਲੋਂ ਵਧੇਰੇ ਆਮ ਵਾਂਗ ਵਰਤਣਾ ਸ਼ੁਰੂ ਕਰ ਸਕਦੇ ਹੋ, ਅਤੇ ਉਸ ਤੋਂ ਬਾਅਦ ਗੱਡੀ ਚਲਾਉਣਾ ਵੀ ਸ਼ੁਰੂ ਹੋ ਸਕਦਾ ਹੈ। ਵੇਰਵਿਆਂ ਲਈ ਸਾਡਾ ਪੰਨਾ ਉੱਪਰਲੇ ਅੰਗ ਦੀ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਗੱਡੀ ਚਲਾਉਣਾ ਦੇਖੋ।
ਸਿਹਤਯਾਬੀ ਹਰ ਵਿਅਕਤੀ ਵਿੱਚ ਵੱਖਰੀ ਹੁੰਦੀ ਹੈ। ਤੁਹਾਡਾ ਸਮਾਂ ਵੱਖਰਾ ਹੋ ਸਕਦਾ ਹੈ, ਅਤੇ ਤੁਹਾਡੇ ਸਰਜਨ ਅਤੇ ਥੈਰੇਪਿਸਟ ਹਰ ਕਦਮ ਉੱਤੇ ਤੁਹਾਡੀ ਅਗਵਾਈ ਕਰਨਗੇ।
ਕੀ ਗ਼ਲਤ ਹੋ ਸਕਦਾ ਹੈ
ਜ਼ਿਆਦਾਤਰ ਮਰੀਜ਼ ਠੀਕ ਰਹਿੰਦੇ ਹਨ, ਪਰ ਕਦੇ-ਕਦਾਈਂ ਸਮੱਸਿਆਵਾਂ ਹੋ ਸਕਦੀਆਂ ਹਨ। ਤੁਹਾਡੇ ਸਰਜਨ ਅਤੇ ਟੀਮ ਤੁਹਾਡੀ ਧਿਆਨ ਨਾਲ ਨਿਗਰਾਨੀ ਕਰਦੇ ਹਨ ਤਾਂ ਜੋ ਕਿਸੇ ਵੀ ਸਮੱਸਿਆ ਨੂੰ ਛੇਤੀ ਫੜਿਆ ਜਾ ਸਕੇ।
ਕਦੇ-ਕਦੇ ਇੰਪਲਾਂਟ ਆਪਣੀ ਥਾਂ ਬਦਲ ਲੈਂਦਾ ਹੈ ਜਾਂ ਹੱਡੀ ਵਿੱਚ ਧਸ ਜਾਂਦਾ ਹੈ। ਤੁਸੀਂ ਜੋੜ ਵਿੱਚ ਨਵਾਂ ਦਰਦ, ਅਜਿਹਾ ਅਹਿਸਾਸ ਕਿ ਉਂਗਲ ਜਾਂ ਅੰਗੂਠਾ ਸਿੱਧਾ ਨਹੀਂ ਬੈਠਾ, ਜਾਂ ਇਸ ਦੇ ਹਿੱਲਣ ਦੇ ਢੰਗ ਵਿੱਚ ਬਦਲਾਅ ਦੇਖ ਸਕਦੇ ਹੋ। ਜੇ ਤੁਸੀਂ ਇਨ੍ਹਾਂ ਵਿੱਚੋਂ ਕੁਝ ਵੀ ਦੇਖੋ, ਤਾਂ ਆਪਣੀ ਅਗਲੀ ਜਾਂਚ ਵੇਲੇ ਇਸ ਬਾਰੇ ਦੱਸੋ।
ਇੰਪਲਾਂਟ ਢਿੱਲਾ ਵੀ ਹੋ ਸਕਦਾ ਹੈ। ਇਹ ਆਮ ਤੌਰ 'ਤੇ ਅਜਿਹੇ ਦਰਦ ਵਾਂਗ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ ਜੋ ਕਾਫ਼ੀ ਸਮੇਂ ਦੇ ਚੰਗੇ ਸੁਧਾਰ ਤੋਂ ਬਾਅਦ ਵਾਪਸ ਆ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਅਕਸਰ ਪਕੜਨ ਜਾਂ ਚੂੰਢੀ ਭਰਨ ਵੇਲੇ ਵਧ ਜਾਂਦਾ ਹੈ। ਜੇ ਅਜਿਹਾ ਹੋਵੇ ਤਾਂ ਆਪਣੇ ਸਰਜਨ ਨੂੰ ਦੱਸੋ।
ਜੋੜ ਵਿੱਚ ਅਕੜਾਅ ਆ ਸਕਦਾ ਹੈ। ਹੋ ਸਕਦਾ ਹੈ ਉਂਗਲ ਜਾਂ ਅੰਗੂਠਾ ਪਹਿਲਾਂ ਜਿੰਨਾ ਨਾ ਮੁੜੇ ਜਾਂ ਸਿੱਧਾ ਨਾ ਹੋਵੇ, ਅਤੇ ਜੋੜ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਵਾਲਾ ਟੈਂਡਨ (tendon, ਪੱਠੇ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀ ਮਜ਼ਬੂਤ ਤੰਦ) ਦਾਗ਼ ਵਾਲੇ ਟਿਸ਼ੂ (scar tissue) ਨਾਲ ਚਿਪਕ ਸਕਦਾ ਹੈ। ਆਪਣੀ ਜਾਂਚ ਵੇਲੇ ਇਸ ਬਾਰੇ ਦੱਸੋ ਤਾਂ ਜੋ ਤੁਹਾਡੇ ਥੈਰੇਪਿਸਟ ਤੁਹਾਡੀਆਂ ਕਸਰਤਾਂ ਵਿੱਚ ਬਦਲਾਅ ਕਰ ਸਕਣ।
ਜੋੜ ਅਸਥਿਰ ਹੋ ਸਕਦਾ ਹੈ ਜਾਂ ਪਹਿਲਾਂ ਵਾਲਾ ਟੇਢਾਪਣ ਵਾਪਸ ਆ ਸਕਦਾ ਹੈ। ਤੁਸੀਂ ਦੇਖ ਸਕਦੇ ਹੋ ਕਿ ਉਂਗਲ ਮੁੜ ਆਪਣੀ ਸੇਧ ਤੋਂ ਬਾਹਰ ਵੱਲ ਖਿਸਕ ਰਹੀ ਹੈ। ਆਪਣੀ ਅਗਲੀ ਮੁਲਾਕਾਤ ਵੇਲੇ ਇਸ ਬਾਰੇ ਗੱਲ ਕਰੋ।
ਲਾਗ (ਇਨਫੈਕਸ਼ਨ) ਆਮ ਨਹੀਂ ਹੁੰਦੀ, ਪਰ ਇਸ ਵੱਲ ਛੇਤੀ ਧਿਆਨ ਦੇਣ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਜੇ ਤੁਹਾਨੂੰ ਬੁਖ਼ਾਰ ਹੈ, ਜ਼ਖ਼ਮ ਦੇ ਆਲੇ-ਦੁਆਲੇ ਫੈਲਦੀ ਲਾਲੀ ਹੈ, ਜਾਂ ਜ਼ਖ਼ਮ ਵਿੱਚੋਂ ਤਰਲ ਜਾਂ ਪਾਕ ਰਿਸ ਰਹੀ ਹੈ, ਤਾਂ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਦਰਦ ਨਿਵਾਰਕ ਦਵਾਈਆਂ ਦੇ ਬਾਵਜੂਦ ਦਰਦ ਵਧਦਾ ਹੀ ਜਾ ਰਿਹਾ ਹੈ, ਤਾਂ ਵੀ ਤੁਹਾਨੂੰ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰਨਾ ਚਾਹੀਦਾ ਹੈ।
ਇਸ ਤਰ੍ਹਾਂ ਦੀ ਸਰਜਰੀ ਦੌਰਾਨ ਨੇੜਲੀਆਂ ਬਣਤਰਾਂ ਚਿੜ ਸਕਦੀਆਂ ਹਨ (irritated) ਜਾਂ ਉਨ੍ਹਾਂ ਨੂੰ ਸੱਟ ਲੱਗ ਸਕਦੀ ਹੈ। ਅੰਗੂਠੇ ਦੇ ਨੇੜੇ ਦੀ ਇੱਕ ਨਸ (nerve) ਸੰਵੇਦਨਸ਼ੀਲ ਹੋ ਸਕਦੀ ਹੈ, ਜਿਸ ਨਾਲ ਚਮੜੀ ਵਿੱਚ ਝਰਨਾਹਟ ਜਾਂ ਬਦਲਿਆ ਹੋਇਆ ਅਹਿਸਾਸ ਹੋ ਸਕਦਾ ਹੈ। ਗੁੱਟ ਦੇ ਅੰਗੂਠੇ ਵਾਲੇ ਪਾਸੇ ਦੀ ਧਮਣੀ (artery), ਜਾਂ ਗੁੱਟ ਦੇ ਅਗਲੇ ਪਾਸੇ ਦਾ ਕੋਈ ਟੈਂਡਨ, ਪ੍ਰਭਾਵਿਤ ਹੋ ਸਕਦਾ ਹੈ। ਜੇ ਨਰਵ ਬਲਾਕ ਦਾ ਅਸਰ ਖ਼ਤਮ ਹੋਣ ਤੋਂ ਬਾਅਦ, ਲਗਭਗ 24 ਘੰਟਿਆਂ ਉੱਤੇ, ਤੁਹਾਨੂੰ ਸੁੰਨਪਨ ਮਹਿਸੂਸ ਹੋਵੇ ਜਾਂ ਤੁਸੀਂ ਆਪਣੀਆਂ ਉਂਗਲਾਂ ਨਾ ਹਿਲਾ ਸਕੋ, ਤਾਂ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਨਰਵ ਬਲਾਕ ਤੋਂ ਬਾਅਦ ਪਹਿਲੇ 24 ਘੰਟਿਆਂ ਵਿੱਚ ਸੁੰਨਪਨ ਅਤੇ ਕਮਜ਼ੋਰੀ ਹੋਣਾ ਉਮੀਦ ਮੁਤਾਬਕ ਹੈ।
ਹੱਥ ਦੀ ਕੋਈ ਹੱਡੀ ਕਦੇ-ਕਦਾਈਂ ਸਰਜਰੀ ਦੌਰਾਨ ਜਾਂ ਉਸ ਤੋਂ ਬਾਅਦ ਟੁੱਟ ਸਕਦੀ ਹੈ। ਇਸ ਨਾਲ ਅਚਾਨਕ ਦਰਦ ਅਤੇ ਸੋਜ ਹੁੰਦੀ ਹੈ। ਜੇ ਅਜਿਹਾ ਹੋਵੇ ਤਾਂ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ।
ਜੇ ਇੰਪਲਾਂਟ ਨਾਕਾਮ ਹੋ ਜਾਵੇ ਅਤੇ ਉਸ ਨੂੰ ਬਚਾਇਆ ਨਾ ਜਾ ਸਕੇ, ਤਾਂ ਹੋਰ ਓਪਰੇਸ਼ਨ ਮਦਦ ਕਰ ਸਕਦੇ ਹਨ। ਇੰਪਲਾਂਟ ਨੂੰ ਕੱਢ ਕੇ ਜੋੜ ਦਾ ਕਿਸੇ ਹੋਰ ਤਰੀਕੇ ਨਾਲ ਇਲਾਜ ਕੀਤਾ ਜਾ ਸਕਦਾ ਹੈ, ਜਿਸ ਨਾਲ ਭਰੋਸੇਯੋਗ ਢੰਗ ਨਾਲ ਦਰਦ ਘਟਦਾ ਹੈ। ਬਹੁਤ ਘੱਟ ਮਾਮਲਿਆਂ ਵਿੱਚ ਜੋੜ ਦੀਆਂ ਹੱਡੀਆਂ ਨੂੰ ਆਪਸ ਵਿੱਚ ਜੋੜਿਆ ਜਾ ਸਕਦਾ ਹੈ (fusion), ਯਾਨੀ ਜੋੜ ਨੂੰ ਪੱਕੇ ਤੌਰ 'ਤੇ ਅਕੜਾ ਦਿੱਤਾ ਜਾਂਦਾ ਹੈ, ਜਾਂ ਉਂਗਲ ਨੂੰ ਕੱਢਣ ਦੀ ਲੋੜ ਪੈ ਸਕਦੀ ਹੈ।
ਜੇ ਤੁਸੀਂ ਵੇਰਵੇ ਚਾਹੁੰਦੇ ਹੋ, ਤਾਂ ਇਸ ਪੰਨੇ ਉੱਤੇ ਪੇਚੀਦਗੀਆਂ ਵਾਲੀ ਸਾਰਣੀ ਆਮ ਦਰਾਂ ਦੱਸਦੀ ਹੈ।
ਸਾਨੂੰ ਕਦੋਂ ਫ਼ੋਨ ਕਰਨਾ ਹੈ
ਜ਼ਿਆਦਾਤਰ ਸਮੱਸਿਆਵਾਂ ਸ਼ੁਰੂ ਵਿੱਚ ਹੀ ਸਾਹਮਣੇ ਆ ਜਾਂਦੀਆਂ ਹਨ, ਅਤੇ ਛੇਤੀ ਕਦਮ ਚੁੱਕਣ ਨਾਲ ਉਨ੍ਹਾਂ ਨੂੰ ਸੁਲਝਾਉਣਾ ਸੌਖਾ ਹੋ ਜਾਂਦਾ ਹੈ। ਜੇ ਤੁਹਾਨੂੰ ਬੁਖ਼ਾਰ ਹੈ, ਜ਼ਖ਼ਮ ਦੇ ਆਲੇ-ਦੁਆਲੇ ਫੈਲਦੀ ਲਾਲੀ ਹੈ, ਜਾਂ ਜ਼ਖ਼ਮ ਵਿੱਚੋਂ ਤਰਲ ਜਾਂ ਪਾਕ ਰਿਸ ਰਹੀ ਹੈ, ਤਾਂ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਦਰਦ ਨਿਵਾਰਕ ਦਵਾਈਆਂ ਦੇ ਬਾਵਜੂਦ ਦਰਦ ਵਧਦਾ ਹੀ ਜਾ ਰਿਹਾ ਹੈ, ਤਾਂ ਵੀ ਉਸੇ ਦਿਨ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਜੇ ਨਰਵ ਬਲਾਕ ਦਾ ਅਸਰ ਖ਼ਤਮ ਹੋਣ ਤੋਂ ਬਾਅਦ, ਲਗਭਗ 24 ਘੰਟਿਆਂ ਉੱਤੇ, ਤੁਹਾਨੂੰ ਸੁੰਨਪਨ ਮਹਿਸੂਸ ਹੋਵੇ ਜਾਂ ਤੁਸੀਂ ਆਪਣੀਆਂ ਉਂਗਲਾਂ ਨਾ ਹਿਲਾ ਸਕੋ, ਤਾਂ ਕਲੀਨਿਕ ਨੂੰ ਫ਼ੋਨ ਕਰੋ। ਨਰਵ ਬਲਾਕ ਤੋਂ ਬਾਅਦ ਪਹਿਲੇ 24 ਘੰਟਿਆਂ ਵਿੱਚ ਸੁੰਨਪਨ ਅਤੇ ਕਮਜ਼ੋਰੀ ਹੋਣਾ ਉਮੀਦ ਮੁਤਾਬਕ ਹੈ।
ਜੇ ਤੁਹਾਨੂੰ ਪਿੰਨੀ (ਲੱਤ ਦੀ ਪਿੰਨੀ, calf) ਵਿੱਚ ਸੋਜ ਜਾਂ ਦਰਦ ਹੈ, ਜਾਂ ਸਾਹ ਚੜ੍ਹਦਾ ਹੈ ਜਾਂ ਛਾਤੀ ਵਿੱਚ ਦਰਦ ਹੈ, ਤਾਂ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹ ਖ਼ੂਨ ਦੇ ਗਤਲੇ ਦੀਆਂ ਨਿਸ਼ਾਨੀਆਂ ਹੋ ਸਕਦੀਆਂ ਹਨ। ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ, ਹੱਥ ਜਾਂ ਅੰਗੂਠਾ ਫਿੱਕਾ, ਠੰਢਾ, ਸਫ਼ੈਦ, ਨੀਲਾ ਜਾਂ ਗੂੜ੍ਹੇ ਰੰਗ ਦਾ ਪੈ ਜਾਵੇ, ਤਾਂ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹ ਖ਼ੂਨ ਦੇ ਵਹਾਅ (circulation) ਦੀ ਸਮੱਸਿਆ ਹੋ ਸਕਦੀ ਹੈ।
ਜੇ ਤੁਸੀਂ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਹੀਂ ਕਰ ਸਕਦੇ, ਜਿਵੇਂ ਕਲੀਨਿਕ ਦੇ ਸਮੇਂ ਤੋਂ ਬਾਅਦ ਜਾਂ ਹਫ਼ਤੇ ਦੇ ਅਖ਼ੀਰ ਵਿੱਚ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਇਸ ਸਥਿਤੀ ਬਾਰੇ ਹੋਰ ਕਿੱਥੇ ਪੜ੍ਹੀਏ
ਇਹ ਪੰਨਾ ਆਪਣੇ ਆਪ ਓਪਰੇਸ਼ਨ ਬਾਰੇ ਹੈ। ਜਿਸ ਸਥਿਤੀ ਦਾ ਇਹ ਇਲਾਜ ਕਰਦਾ ਹੈ, ਅਤੇ ਇਸ ਬਾਰੇ ਸਬੂਤ ਕੀ ਦਿਖਾਉਂਦੇ ਹਨ ਕਿ ਸਰਜਰੀ ਕਦੋਂ ਮਦਦ ਕਰਦੀ ਹੈ ਅਤੇ ਕਦੋਂ ਨਹੀਂ, ਇਸ ਦਾ ਵਿਸਥਾਰ ਅੰਗੂਠੇ ਦੀ ਜੜ੍ਹ ਦਾ ਗਠੀਆ ਪੰਨੇ ਉੱਤੇ ਦਿੱਤਾ ਗਿਆ ਹੈ।
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a study with minimum 8-year follow-up [1].
- Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate [4].
- The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition [6].
- The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis [7].
- Arthroplasty is recommended for patients with post-trauma painful PIP joints [8].
- Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years [9].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity [10].
- The results of pyrolytic carbon PIPJ arthroplasty in review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
- A study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs was conducted [11].
- The PyroDisk interposition arthroplasty confirmed good 5-year clinical results [12, 13].
- PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis [15].
- All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty [16].
- The encouraging mid-term clinical results of the interposition implant (APSI) in the context of proximal pole scaphoid pseudarthrosis make this technique a proven alternative, without precluding a definitive therapeutic option in case of failure [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Anatomy & Pathophysiology
Bony Anatomy
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [28].
- The radial ray or first ray is the shortest, made up of only three bones: a metacarpal and two phalanges [28].
- The trapezium is clearly angled out in front of the carpal plane so that the first metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [28].
- The thumb metacarpal is the shortest, while the index metacarpal is by far the longest [28].
- The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal, whereas they are located at the distal ends of the other metacarpals [28].
- The thumb metacarpal is independent and articulates with the trapezium [35].
- The index metacarpal is the most firmly fixed [35].
- The ring metacarpal has about 10 degrees of mobility in flexion and extension [35].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [35].
Soft Tissue & Vascular Anatomy
- The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [27].
- The first (most radial) compartment contains the abductor pollicis longus and the extensor pollicis brevis [27].
- The second extensor compartment contains the extensor carpi radialis longus and the extensor carpi radialis brevis [27].
- The third compartment contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [27].
- The fourth extensor compartment contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [27].
- The fifth compartment contains the extensor digiti quinti [27].
- The sixth compartment contains the extensor carpi ulnaris tendon, which inserts at the base of the little finger metacarpal [27].
- The extrinsic finger flexors are the flexor digitorum profundus and the flexor digitorum superficialis [27].
- The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx [27].
- The flexor digitorum superficialis acts as a flexor of the proximal interphalangeal and metacarpophalangeal joints [27].
- There are seven interosseous muscles, four dorsal and three volar [32].
- The dorsal interossei are abductors [32].
- The volar interossei are adductors [32].
- The middle finger has two dorsal interossei (abductors) and no volar interossei (adductors) because the central axis of the hand lies within it [32].
- The "princeps pollicis" artery is the terminal branch of the radial artery and crosses the first intermetacarpal space [36].
- The princeps pollicis runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [36].
- The princeps pollicis divides into two terminal rami, namely the collateral palmar arteries of the thumb, at the level of the cutaneous flexion crease of the metacarpophalangeal joint [36].
- An arcade located deep in the flexor tendon joins together the two arteries at the level of the distal metaphysis of the first phalanx [36].
- The dorsal arteries of the thumb originate from the palmar arteries (princeps, commissural or anastomoses of the superficial arcade) at the level of the first metacarpal [36].
Functional Mechanics
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration [28].
- The thumb ray is more mobile, shorter, and more proximal than the other rays, allowing it to project in front of the plane of the palm to oppose itself to the other four rays [28].
- The skeleton of the hand presents a longitudinal and transverse concavity, giving it the shape of a cup with a palmar concavity when the thumb is placed next to the index finger [28].
- The transverse axis of the palm forms an acute angle of approximately 75 degrees with the longitudinal axis [28].
- The metacarpal arch is endowed with a great deal of adaptability because of the mobility of the peripheral metacarpals [35].
- The heads of the second and third metacarpals are fixed [35].
- The mobility of the ulnar metacarpals allows "flexion" of 10 degrees for the fourth metacarpal, and "flexion" of 20 degrees for the fifth metacarpal [35].
- The keystones of the longitudinal arches are the metacarpophalangeal articulations, whose thick anterior glenoid capsules, the volar plates, prevent hyperextension [35].
- The dorsal skin slides distally to allow metacarpophalangeal joint flexion [40].
- Interphalangeal flexion is accomplished by means of a special arrangement of skin folds on the dorsum of each articulation [40].
- The gliding mechanism for tendons in narrow crowded areas is assured by the synovial sheath, which allows a considerable amplitude of movement [40].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [40].
- The position of each articulation depends on the equilibrium of forces acting at that level, and this equilibrium is subject to the position of the immediately proximal articulation [40].
- Single articular movements around a fixed perpendicular axis simply do not exist in the hand [40].
- Almost all movements in the hand are around oblique and variable axes, resulting in combined movements permitting optimal orientation of the phalanges at the time of prehension [40].
Indications and Disease Staging
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan resurfacing implant is a valid option for treating scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- The pyrocarbon implant is indicated for the treatment of STT arthrosis [15].
- The pyrocarbon interposition implant (APSI) is an alternative for the treatment of proximal pole scaphoid pseudarthrosis [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT osteoarthritis who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Patient Selection and Demographics
- Active patients under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint are candidates for anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation [9].
- Pyrocarbon disc interposition is used for the treatment of CMC1 osteoarthritis grade 2 to 3 [11].
- Total trapezectomy associated with the placement of a NuGrip pyrocarbon implant is a procedure for the replacement of the TMC joint [22].
Comparative Classification and Efficacy
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
Clinical Presentation
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal osteoarthritis [1].
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan implant is used for trapeziometacarpal osteoarthritis [4].
- The Pyrocardan implant is used for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant is used for advanced trapeziometacarpal arthritis [6].
- The Pyrocardan resurfacing implant is used for scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- Pyrocarbon PIP arthroplasty is used for post-trauma painful joints [8].
- Anatomic pyrolytic carbon resurfacing hemiarthroplasty is used for Eaton-Littler stage III osteoarthritis of the thumb CMC joint in patients under 65 years of age [9].
- Pyrolytic carbon implants are used for proximal interphalangeal joint (PIPJ) arthroplasty [10].
- Pyrocarbon disc interposition is used for CMC1 osteoarthritis grade 2 to 3 [11].
- PyroDisk interposition arthroplasty is used for trapeziometacarpal osteoarthritis [12].
- PyroDisk interposition is indicated for patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The pyrocarbon implant is used for STT arthrosis [15].
- Pyrolytic interpositional arthroplasty is used for TMC arthritis [16].
- Pi2 pyrocarbon spacer arthroplasty is used for carpometacarpal joint osteoarthritis [17].
- The interposition implant (APSI) is used for pseudarthrosis of the proximal pole of the scaphoid [18].
- A pyrocarbon implant is used for Kienböck disease [19].
- Total trapeziectomy associated with the placement of a pyrocarbon type Nugrip implant is used after replacement of the TMC joint [22].
- The Pyrocardan implant is used for stage 2 trapeziometacarpal osteoarthritis [23].
- The Pi2 pyrocarbon implant is used in total trapeziectomy and suspension ligamentoplasty [24].
- The Pi2 pyrocarbon implant is used in destructions of the capitolunate joint space [25].
Investigations
- Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [26].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining hand pathology but can be expensive, time-consuming, and often nonspecific [26].
- A systematic method to approaching the physical examination of the hand is essential due to the number of structures in a small space [26].
Treatment
Trapeziometacarpal Joint Osteoarthritis
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a minimum 8-year follow-up study [1].
- Partial trapeziectomy with pyrocarbon arthroplasty provides excellent pain relief and high patient satisfaction for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis that can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate for trapeziometacarpal osteoarthritis [4].
- Long-term follow-up data for pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 is available in a study involving more than 150 thumbs [11].
- Interposition arthroplasty with PyroDisk confirmed good 5-year clinical results [12, 13].
- The modified procedure of partial trapeziectomy and pyrocarbon interpositional arthroplasty improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength [29].
- Pyrocarbon interposition arthroplasty for trapeziometacarpal osteoarthritis does not preclude subsequent conventional arthroplasty techniques in the event of failure [23].
Scaphotrapeziotrapezoid Joint Osteoarthritis
- The Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis, evidenced by good functional and radiographic outcomes and the absence of surgical complications [7].
- The good results, simple surgical procedure, absence of complications, and lack of need for fixation or ligamentoplasty confirm the advantages of the pyrocarbon implant in the treatment of STT arthrosis [15].
Other Indications
- Pyrocarbon PIP arthroplasty is recommended for post-trauma painful joints [8].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure with the potential to achieve pain relief, stability, satisfactory ROM, and correction of deformity, though results were unpredictable and may not be superior to other methods of arthroplasty [10].
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis, especially in opposition with a mean Kapandji score of 9.60, with no major aggravation of metacarpophalangeal extension [17].
- The interposition implant (APSI) for proximal scaphoid pseudarthrosis provides encouraging mid-term clinical results and serves as a proven alternative without precluding a definitive therapeutic option in case of failure [18].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant, and the average grip strength was 76.5% of the contralateral side [19].
Complications
- The Pyrocardan implant has a high complication rate [4].
- The Pyrocardan resurfacing implant for STT osteoarthritis was associated with the absence of surgical complications [7].
- The pyrocarbon implant for STT arthrosis was associated with the absence of complications [15].
Recovery
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty, especially in opposition, with a mean Kapandji score of 9.60 [17].
- There was no major aggravation of metacarpophalangeal extension following Pi2 pyrocarbon spacer arthroplasty [17].
- The average grip strength was 76.5% of the contralateral side after pyrocarbon implant treatment for Kienböck disease [19].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant [19].
Key Evidence
- [L4] Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity. [1] (10.1177/1753193420906805)
- [L3] Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction. [2] (10.1177/1753193413519384)
- [L4] PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint. [3] (10.1097/bth.0b013e318271aab7)
- [L4] The study concludes that the Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate. [4] (10.1016/j.hansur.2016.09.004)
- [L4] The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray. [5] (10.1016/j.hansur.2018.10.044)
- [L4] The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition. [6] (10.1016/j.jhsa.2014.07.011)
- [L3] The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan1 resurfacing implant is a valid option for treating STT osteoarthritis. [7] (10.1016/j.hansur.2017.01.003)
- [L4] We recommend arthroplasty for this group of patients. [8] (10.1016/s0363-5023(03)80384-2)
- [L3] Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years. [9] (10.1142/s2424835518500443)
- [L4] The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty. [10] (10.1016/j.jhsa.2006.02.018)
- [L4] This is the first study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs. [11] (10.1016/j.jhsa.2018.06.086)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [12] (10.1177/1558944716660555n)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [13] (10.1177/1558944716660555m)
- [L4] PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous. [14] (10.1177/1753193420981552)
- [L4] The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis. [15] (10.1016/j.main.2005.04.010)
- [L3] All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty. [16] (10.1155/2019/7961507)
- [L3] Range of motion improved, especially in opposition (mean Kapandji score, 9.60), with no major aggravation of metacarpophalangeal extension. [17] (10.1016/j.hansur.2016.05.002)
- [L4] Les résultats cliniques encourageants à moyen terme de l’implant d’interposition (APSI), dans le cadre d’une pseudarthrose du pôle proximal du scaphoïde, font de cette technique une alternative probante, sans interdire une option thérapeutique définitive en cas d’échec. [18] (10.1016/j.main.2011.10.031)
- [L5] There were no changes in range of motion after surgery and the average grip strength was 76.5% of the contralateral side. [19] (10.1016/j.main.2014.09.002)
- [Case_report] The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis. [20] (10.1016/j.jhsg.2026.100964)
- [L4] La trapézectomie totale associée à la mise en place d'un implant en pyrocarbone type Nugrip après le remplacement de l'articulation TMC semble être une procédure attrayante. [22] (10.1016/j.hansur.2018.10.166)
- [L3] Il ne coupe pas les ponts en cas d'éventuel échec à des techniques d'arthroplastie plus conventionnelles. [23] (10.1016/j.main.2011.10.132)
- [L3] The implant Pi2 seems to contribute keeping trapezial height, without functional advantages and with a risk of dislocation. [24] (10.1016/j.main.2013.04.003)
- [L4] Cette technique a l'avantage de préserver les mobilités médio-carpiennes et les ligaments extrinsèques du poignet. [25] (10.1016/j.hansur.2016.10.125)
- [L4] The modified procedure improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength. [29] (10.1177/1753193414553368)
References
[1] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420906805
[2] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413519384
[3] PyroCarbon Implant Hemiarthroplasty for Trapeziometacarpal Arthritis. Techniques in Hand & Upper Extremity Surgery. 2013. DOI: 10.1097/bth.0b013e318271aab7
[4] Early outcomes of Pyrocardan® implants for trapeziometacarpal osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.09.004
[5] L’implant en Pyrocarbone (Pyrocardan®) dans le traitement de l’arthrose carpo-métacarpienne ulnaire post-traumatique. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.044
[6] Pyrocarbon Interposition (PyroDisk) Implant for Trapeziometacarpal Osteoarthritis: Minimum 5-Year Follow-Up. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.07.011
[7] Treatment of scaphotrapeziotrapezoid osteoarthritis with the Pyrocardan® implant: Results with a minimum follow-up of 2 years. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.01.003
[8] Pyrocarbon PIP arthroplasty for post trauma painful joints. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80384-2
[9] Anatomic Pyrocarbon Hemiarthroplasty for Thumb Carpometacarpal Osteoarthritis in Patients under 65 Years: Mid Term Results. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518500443
[10] Pyrolytic Carbon Proximal Interphalangeal Joint Resurfacing Arthroplasty. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.02.018
[11] Long-Term Follow-Up After Pyrocarbon Disc Interposition for Thumb CMC Osteoarthritis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.086
[12] Pyrocarbon Interposition Arthroplasty of the Trapeziometacarpal Joint With the PyroDisk. HAND. 2016. DOI: 10.1177/1558944716660555n
[13] PyroDisk Interposition Implant for Trapeziometacarpal Osteoarthritis. HAND. 2016. DOI: 10.1177/1558944716660555m
[14] Re: Smeraglia F, et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. J Hand Surg Eur. 2020, 45: 472–6. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/1753193420981552
[15] Traitement de l'arthrose S.T.T. par un Implant en pyrocarbone. Premiers résultats. Chirurgie de la Main. 2005. DOI: 10.1016/j.main.2005.04.010
[16] Tendon versus Pyrocarbon Interpositional Arthroplasty in the Treatment of Trapeziometacarpal Osteoarthritis. BioMed Research International. 2019. DOI: 10.1155/2019/7961507
[17] A ten-year prospective outcome study of Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.05.002
[18] Pseudarthrose du scaphoïde : résection proximale et interposition d’un implant en pyrocarbone, à propos de 20 cas. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.031
[19] Le traitement de la maladie de Kienböck par un implant en pyrocarbone : fait clinique. Chirurgie de la Main. 2014. DOI: 10.1016/j.main.2014.09.002
[20] Game, Set… Revision! A Case Report of a Tennis Player Who Smashed His Scaphotrapeziotrapezoid-Joint Pyrocardan Implant Twice. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.100964
[22] Reprise de prothèses totales trapézo-métacarpiennes par un implant en Pyrocarbone type NuGrip. À propos de 6 cas. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.166
[23] L’implant pyrocardan : interposition libre en pyrocarbone trapezometacarpienne pour l’arthrose de stade 2. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.132
[24] Trapézectomie totale et ligamentoplastie de suspension : une interposition par un implant Pi2® en pyrocarbone a-t-elle un intérêt ?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.04.003
[25] Utilisation de l’implant en pyrocarbone de type Pi2 dans les destructions de l’interligne articulaire capito-lunaire. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.125
[26] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[27] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[28] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[29] Re: Mariconda et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. J Hand Surg Eur. 2014, 39: 604–610. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414553368
[32] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[35] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[36] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[40] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.