Patients › Hand
ਅੰਗੂਠੇ ਦੇ UCL (ਅਲਨਰ ਕੋਲੈਟਰਲ ਲਿਗਾਮੈਂਟ) ਦੀ ਸੱਟ
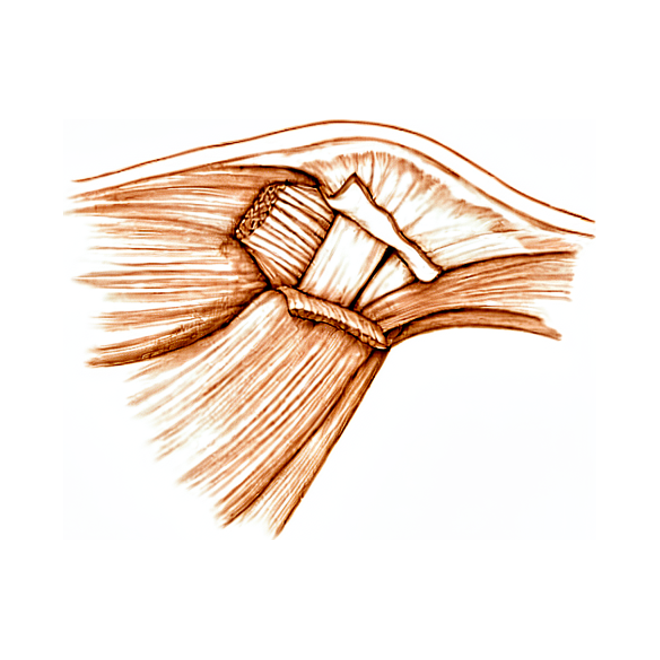
ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ
ਅੰਗੂਠੇ ਦੇ UCL (ਅਲਨਰ ਕੋਲੈਟਰਲ ਲਿਗਾਮੈਂਟ) ਦੀ ਸੱਟ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਦੇ ਅੰਦਰਲੇ ਕਿਨਾਰੇ ਵਾਲੇ ਲਿਗਾਮੈਂਟ (ligament, ਹੱਡੀ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲਾ ਬੰਧਨ) ਨੂੰ ਪ੍ਰਭਾਵਿਤ ਕਰਦੀ ਹੈ, ਉਸ ਜੋੜ ਉੱਤੇ ਜਿੱਥੇ ਅੰਗੂਠਾ ਤੁਹਾਡੇ ਹੱਥ ਨਾਲ ਮਿਲਦਾ ਹੈ। ਇਹ ਸੱਟ ਆਮ ਤੌਰ ਉੱਤੇ ਉਦੋਂ ਲੱਗਦੀ ਹੈ ਜਦੋਂ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਝਟਕੇ ਨਾਲ ਪਾਸੇ ਵੱਲ ਮੁੜ ਜਾਂਦਾ ਹੈ, ਅਕਸਰ ਫੈਲੇ ਹੋਏ ਹੱਥ ਭਾਰ ਡਿੱਗਣ ਵੇਲੇ। ਸਕੀਇੰਗ (skiing) ਵਿੱਚ ਇਹ ਉਦੋਂ ਹੋ ਸਕਦੀ ਹੈ ਜੇ ਤੁਸੀਂ ਸਕੀ ਦੀ ਸੋਟੀ ਫੜੀ ਹੋਈ ਹਾਲਤ ਵਿੱਚ ਹੀ ਡਿੱਗ ਪੈਂਦੇ ਹੋ, ਅਤੇ ਸਨੋਬੋਰਡਿੰਗ (snowboarding) ਕਰਨ ਵਾਲਿਆਂ ਦੇ ਅੰਗੂਠੇ ਨੂੰ ਡਿੱਗਣ ਅਤੇ ਮੁੜਨ ਦੌਰਾਨ ਸੱਟ ਲੱਗ ਸਕਦੀ ਹੈ।
ਦਰਦ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਦੇ ਅੰਦਰਲੇ ਕਿਨਾਰੇ ਉੱਤੇ, ਹਥੇਲੀ ਦੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਜੋੜ ਉੱਤੇ ਹੁੰਦਾ ਹੈ। ਇਹ ਆਮ ਤੌਰ ਉੱਤੇ ਅਚਾਨਕ ਸੱਟ ਨਾਲ ਸ਼ੁਰੂ ਹੁੰਦਾ ਹੈ, ਅਤੇ ਨਾਲ ਹੀ ਉਸ ਥਾਂ ਉੱਤੇ ਸੋਜ ਹੁੰਦੀ ਹੈ ਅਤੇ ਛੂਹਣ ਨਾਲ ਦਰਦ ਹੁੰਦਾ ਹੈ। ਚੂੰਢੀ ਭਰਨ, ਕੋਈ ਚੀਜ਼ ਫੜਨ ਅਤੇ ਹਰ ਉਸ ਕੰਮ ਨਾਲ ਦਰਦ ਹੋਵੇਗਾ ਜੋ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਨੂੰ ਪਾਸੇ ਵੱਲ ਧੱਕਦਾ ਹੈ। ਰੋਜ਼ਾਨਾ ਦੇ ਉਹ ਕੰਮ ਔਖੇ ਹੋ ਜਾਂਦੇ ਹਨ ਜੋ ਅੰਗੂਠੇ ਉੱਤੇ ਇਸ ਤਰ੍ਹਾਂ ਭਾਰ ਪਾਉਂਦੇ ਹਨ: ਚਾਬੀ ਘੁਮਾਉਣਾ, ਮਰਤਬਾਨ ਖੋਲ੍ਹਣਾ, ਭਾਰੀ ਪਤੀਲੇ ਨੂੰ ਉਸ ਦੇ ਕੰਢੇ ਤੋਂ ਫੜਨਾ। ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਅਸਥਿਰ ਵੀ ਮਹਿਸੂਸ ਹੋ ਸਕਦਾ ਹੈ, ਜਿਵੇਂ ਕਿਸੇ ਚੀਜ਼ ਨਾਲ ਦਬਾਉਣ ਉੱਤੇ ਇਹ ਜਵਾਬ ਦੇ ਜਾਂਦਾ ਹੋਵੇ।
ਕੁਝ ਲੋਕ ਅੰਗੂਠੇ ਦੇ ਜੋੜ ਦੇ ਅੰਦਰਲੇ ਕਿਨਾਰੇ ਉੱਤੇ ਇੱਕ ਛੋਟੀ, ਸਖ਼ਤ ਗੰਢ ਦੇਖਦੇ ਹਨ। ਦੂਜੇ ਅੰਗੂਠੇ ਦੇ ਮੁਕਾਬਲੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਥੋੜ੍ਹਾ ਟੇਢਾ ਪਿਆ ਜਾਂ ਥੋੜ੍ਹਾ ਘੁੰਮਿਆ ਹੋਇਆ ਵੀ ਹੋ ਸਕਦਾ ਹੈ। ਜੇ ਸੱਟ ਕੁਝ ਸਮਾਂ ਪਹਿਲਾਂ ਲੱਗੀ ਸੀ, ਤਾਂ ਦਰਦ ਘੱਟ ਸਪਸ਼ਟ ਹੋ ਸਕਦਾ ਹੈ, ਪਰ ਚੂੰਢੀ ਭਰਨ ਜਾਂ ਫੜਨ ਵੇਲੇ ਅੰਗੂਠਾ ਫਿਰ ਵੀ ਕਮਜ਼ੋਰ ਜਾਂ ਢਿੱਲਾ ਮਹਿਸੂਸ ਹੋ ਸਕਦਾ ਹੈ।
ਇਨ੍ਹਾਂ ਨਿਸ਼ਾਨੀਆਂ ਉੱਤੇ ਨਜ਼ਰ ਰੱਖੋ ਅਤੇ ਉਸੇ ਦਿਨ ਕਾਰਵਾਈ ਕਰੋ: ਕੋਈ ਉਂਗਲ, ਹੱਥ ਜਾਂ ਬਾਂਹ ਜੋ ਗਰਮ, ਲਾਲ, ਸੁੱਜੀ ਹੋਈ ਅਤੇ ਦਰਦ ਵਾਲੀ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ; ਸੱਟ ਵਾਲੇ ਜੋੜ ਉੱਤੇ ਫਟੀ ਹੋਈ ਚਮੜੀ, ਹੱਡੀ ਦਿਖਾਈ ਦੇਣਾ, ਜਾਂ ਸਾਫ਼ ਦਿਸਦਾ ਟੇਢਾਪਣ; ਅੰਗੂਠਾ ਜਾਂ ਹੱਥ ਜੋ ਫਿੱਕਾ, ਠੰਢਾ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲਾ ਪੈ ਜਾਵੇ; ਜਾਂ ਸੱਟ ਤੋਂ ਬਾਅਦ ਅਚਾਨਕ ਸੁੰਨ ਹੋ ਜਾਣਾ ਜਾਂ ਹਿਲਾ ਨਾ ਸਕਣਾ। ਇਨ੍ਹਾਂ ਲਈ ਤੁਰੰਤ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਵਿੱਚ ਇਲਾਜ ਦੀ ਲੋੜ ਹੈ, ਅਤੇ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਦੇ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਨਹੀਂ ਹੈ।
ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾ ਦਿੰਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਆਪਣਾ ਹੱਥ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਸਪੈਸ਼ਲਿਸਟ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਅਸਲ ਵਿੱਚ ਕੀ ਹੋ ਰਿਹਾ ਹੈ
ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਦੇ ਅੰਦਰਲੇ ਕਿਨਾਰੇ ਦੇ ਨਾਲ-ਨਾਲ, ਜਿੱਥੇ ਇਹ ਹੱਥ ਨਾਲ ਜੁੜਦਾ ਹੈ, ਲਿਗਾਮੈਂਟ ਦੀ ਇੱਕ ਮਜ਼ਬੂਤ ਪੱਟੀ ਹੁੰਦੀ ਹੈ ਜਿਸ ਨੂੰ ਅਲਨਰ ਕੋਲੈਟਰਲ ਲਿਗਾਮੈਂਟ (ulnar collateral ligament) ਕਹਿੰਦੇ ਹਨ। ਇਸ ਨੂੰ ਤੰਬੂ ਦੇ ਬਾਂਸ ਨੂੰ ਸਿੱਧਾ ਟਿਕਾ ਕੇ ਰੱਖਣ ਵਾਲੀ ਰੱਸੀ ਵਾਂਗ ਸਮਝੋ: ਜਦੋਂ ਤੁਸੀਂ ਚੂੰਢੀ ਭਰਦੇ ਹੋ ਜਾਂ ਕੋਈ ਚੀਜ਼ ਫੜਦੇ ਹੋ, ਤਾਂ ਇਹ ਅੰਗੂਠੇ ਦੇ ਜੋੜ ਨੂੰ ਪਾਸੇ ਵੱਲ ਮੁੜਨ ਤੋਂ ਰੋਕਦਾ ਹੈ। ਹਰ ਵਾਰ ਜਦੋਂ ਤੁਸੀਂ ਆਪਣਾ ਅੰਗੂਠਾ ਕਿਸੇ ਉਂਗਲ ਨਾਲ ਦਬਾਉਂਦੇ ਹੋ, ਇਹ ਪੱਟੀ ਭਾਰ ਸਹਿੰਦੀ ਹੈ। ਇਸੇ ਕਰਕੇ ਇੱਥੇ ਪਾਟਣ ਹੋਣ ਨਾਲ ਬਿਲਕੁਲ ਇਨ੍ਹਾਂ ਕੰਮਾਂ ਵਿੱਚ ਕਮਜ਼ੋਰੀ ਅਤੇ ਦਰਦ ਹੁੰਦਾ ਹੈ।
ਜਦੋਂ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਜ਼ੋਰ ਨਾਲ ਪਾਸੇ ਵੱਲ ਧੱਕਿਆ ਜਾਂਦਾ ਹੈ, ਤਾਂ ਇਹ ਪੱਟੀ ਖਿੱਚੀ ਜਾ ਸਕਦੀ ਹੈ, ਅੰਸ਼ਕ ਤੌਰ ਉੱਤੇ ਪਾਟ ਸਕਦੀ ਹੈ, ਜਾਂ ਆਰ-ਪਾਰ ਪਾਟ ਸਕਦੀ ਹੈ। ਡਾਕਟਰ ਇਸ ਨੂੰ ਇਸ ਹਿਸਾਬ ਨਾਲ ਦਰਜਾ ਦਿੰਦੇ ਹਨ ਕਿ ਇਹ ਕਿੰਨਾ ਪਾਟਿਆ ਹੈ: ਖਿਚਾਅ ਜਾਂ ਅੰਸ਼ਕ ਪਾਟਣ, ਅਤੇ ਪੂਰਾ ਪਾਟਣ ਜਿਸ ਵਿੱਚ ਲਿਗਾਮੈਂਟ ਹੱਡੀ ਤੋਂ ਵੱਖ ਹੋ ਜਾਂਦਾ ਹੈ। ਕਈ ਵਾਰ ਲਿਗਾਮੈਂਟ ਹੱਡੀ ਦੇ ਇੱਕ ਛੋਟੇ ਟੁਕੜੇ ਸਮੇਤ ਹੱਡੀ ਤੋਂ ਉੱਖੜ ਜਾਂਦਾ ਹੈ। ਅੰਸ਼ਕ ਪਾਟਣ ਆਮ ਤੌਰ ਉੱਤੇ ਸਪਲਿੰਟ (splint) ਵਿੱਚ ਠੀਕ ਹੋ ਸਕਦਾ ਹੈ। ਪੂਰਾ ਪਾਟਣ ਅਕਸਰ ਇਸ ਤਰ੍ਹਾਂ ਠੀਕ ਨਹੀਂ ਹੋ ਸਕਦਾ, ਕਿਉਂਕਿ ਪਾਟਿਆ ਸਿਰਾ ਪਲਟ ਕੇ ਪਿੱਛੇ ਮੁੜ ਸਕਦਾ ਹੈ ਅਤੇ ਜੋੜ ਦੇ ਉੱਪਰ ਪਈ ਟਿਸ਼ੂ ਦੀ ਇੱਕ ਪਰਤ ਦੇ ਹੇਠ ਫਸ ਸਕਦਾ ਹੈ। ਜਦੋਂ ਇਹ ਹੋ ਜਾਂਦਾ ਹੈ, ਤਾਂ ਲਿਗਾਮੈਂਟ ਉਸ ਹੱਡੀ ਤੋਂ ਦੂਰ ਪਿਆ ਰਹਿ ਜਾਂਦਾ ਹੈ ਜਿਸ ਨਾਲ ਇਸ ਨੇ ਦੁਬਾਰਾ ਜੁੜਨਾ ਹੈ, ਇਸ ਲਈ ਇਹ ਆਪਣੇ ਆਪ ਦੁਬਾਰਾ ਨਹੀਂ ਜੁੜ ਸਕਦਾ।
ਜੇ ਪਾਟਣ ਦਾ ਇਲਾਜ ਨਾ ਕੀਤਾ ਜਾਵੇ, ਤਾਂ ਜੋੜ ਢਿੱਲਾ ਰਹਿੰਦਾ ਹੈ। ਪਾਸੇ ਵੱਲ ਭਾਰ ਪੈਣ ਉੱਤੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਵਾਰ-ਵਾਰ ਜਵਾਬ ਦਿੰਦਾ ਰਹਿੰਦਾ ਹੈ, ਅਤੇ ਸਾਲਾਂ ਦੌਰਾਨ ਇਹ ਲਗਾਤਾਰ ਹਿਲਜੁਲ ਜੋੜ ਨੂੰ ਘਿਸਾ ਸਕਦੀ ਹੈ ਅਤੇ ਗਠੀਏ (ਆਰਥਰਾਈਟਿਸ) ਦਾ ਕਾਰਨ ਬਣ ਸਕਦੀ ਹੈ। ਇਸੇ ਕਰਕੇ ਇਸ ਸੱਟ ਨੂੰ ਗੰਭੀਰਤਾ ਨਾਲ ਲਿਆ ਜਾਂਦਾ ਹੈ, ਭਾਵੇਂ ਇਹ ਇੱਕ ਆਮ ਜਿਹੀ ਮੋਚ ਵਰਗੀ ਲੱਗੇ।
ਅਸੀਂ ਇਸ ਬਾਰੇ ਕੀ ਕਰ ਸਕਦੇ ਹਾਂ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ, ਇਲਾਜ ਨੂੰ ਤੁਹਾਡੀ ਖ਼ਾਸ ਸੱਟ ਦੇ ਹਿਸਾਬ ਨਾਲ ਚੁਣਦੇ ਹਨ। ਅੰਗੂਠੇ ਦੇ ਲਿਗਾਮੈਂਟ ਦੇ ਕੁਝ ਪਾਟਣ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਿਨਾਂ ਠੀਕ ਹੋ ਜਾਂਦੇ ਹਨ, ਅਤੇ ਕੁਝ ਨੂੰ ਛੇਤੀ ਸਰਜਰੀ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ, ਇਸ ਲਈ ਬਿਨਾਂ ਦੇਰੀ ਜਾਂਚ ਕਰਵਾਉਣਾ ਅਹਿਮ ਹੈ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ ਉੱਤੇ ਉਨ੍ਹਾਂ ਦਾ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਨੂੰ ਮਿਲਣ ਦਾ ਸੁਝਾਅ ਦਿੱਤਾ ਹੈ, ਤਾਂ ਵੀ ਮੈਡੀਕੇਅਰ (Medicare) ਦੀ ਛੋਟ ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਪਵੇਗੀ। ਕਲੀਨਿਕ ਵਿੱਚ ਅਸੀਂ ਤੁਹਾਡੀ ਸੱਟ ਦਾ ਪੂਰਾ ਹਾਲ ਪੁੱਛਦੇ ਹਾਂ, ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਜਿੱਥੇ ਲੋੜ ਹੋਵੇ ਉੱਥੇ ਸਕੈਨ ਦਾ ਪ੍ਰਬੰਧ ਕਰਦੇ ਹਾਂ। ਇਨ੍ਹਾਂ ਵਿੱਚ ਐਕਸ-ਰੇ, ਅਲਟਰਾਸਾਊਂਡ ਸਕੈਨ ਜਾਂ MRI ਸ਼ਾਮਲ ਹੋ ਸਕਦੇ ਹਨ; MRI ਇੱਕ ਮਜ਼ਬੂਤ ਚੁੰਬਕ ਨਾਲ ਲਿਗਾਮੈਂਟ ਦੀਆਂ ਵਿਸਥਾਰ ਵਾਲੀਆਂ ਤਸਵੀਰਾਂ ਲੈਂਦਾ ਹੈ। ਇਹ ਸਕੈਨ ਦਿਖਾਉਂਦੇ ਹਨ ਕਿ ਕੀ ਲਿਗਾਮੈਂਟ ਪੂਰੀ ਤਰ੍ਹਾਂ ਆਰ-ਪਾਰ ਪਾਟ ਗਿਆ ਹੈ ਅਤੇ ਕੀ ਪਾਟਿਆ ਸਿਰਾ ਪਲਟ ਕੇ ਆਪਣੀ ਥਾਂ ਤੋਂ ਹਟ ਗਿਆ ਹੈ।
ਜੇ ਪਾਟਣ ਅੰਸ਼ਕ ਹੈ, ਜਾਂ ਲਿਗਾਮੈਂਟ ਹੱਡੀ ਦੇ ਇੱਕ ਛੋਟੇ ਟੁਕੜੇ ਸਮੇਤ ਹੱਡੀ ਤੋਂ ਉੱਖੜ ਗਿਆ ਹੈ ਪਰ ਉਹ ਟੁਕੜਾ ਆਪਣੀ ਥਾਂ ਤੋਂ ਨਹੀਂ ਹਿੱਲਿਆ, ਤਾਂ ਅਸੀਂ ਆਮ ਤੌਰ ਉੱਤੇ 4 ਹਫ਼ਤਿਆਂ ਤੱਕ ਅੰਗੂਠੇ ਨੂੰ ਪਲੱਸਤਰ (cast) ਵਿੱਚ ਸਥਿਰ ਰੱਖਦੇ ਹਾਂ। ਉਸ ਤੋਂ ਬਾਅਦ ਤੁਸੀਂ 3 ਹੋਰ ਹਫ਼ਤਿਆਂ ਲਈ ਉਤਾਰਿਆ ਜਾ ਸਕਣ ਵਾਲਾ ਸਪਲਿੰਟ ਪਾਉਂਦੇ ਹੋ ਅਤੇ ਹਿਲਜੁਲ ਦੀਆਂ ਨਰਮ ਕਸਰਤਾਂ ਸ਼ੁਰੂ ਕਰਦੇ ਹੋ। ਐਕਸਟੈਂਡ ਰੀਹੈਬਿਲੀਟੇਸ਼ਨ (Extend Rehabilitation) ਵਿਖੇ ਤੁਹਾਡੀ ਹੈਂਡ ਥੈਰੇਪਿਸਟ, ਰੂਬੀ ਡੂਲਨ (Ruby Doolan), ਇਨ੍ਹਾਂ ਕਸਰਤਾਂ ਦੀ ਸੇਧ ਦਿੰਦੀ ਹੈ ਅਤੇ ਤੁਹਾਨੂੰ ਲੋੜੀਂਦਾ ਕੋਈ ਵੀ ਸਪਲਿੰਟ ਬਣਾਉਂਦੀ ਹੈ। ਜਿਸ ਪੂਰੇ ਪਾਟਣ ਵਿੱਚ ਪਾਟਿਆ ਸਿਰਾ ਪਲਟ ਕੇ ਆਪਣੀ ਥਾਂ ਤੋਂ ਨਹੀਂ ਹਟਿਆ, ਉਸ ਵਿੱਚ ਆਮ ਤੌਰ ਉੱਤੇ ਪਹਿਲਾਂ ਜੋੜ ਨੂੰ ਸਥਿਰ ਰੱਖ ਕੇ ਦੇਖਿਆ ਜਾਂਦਾ ਹੈ, ਯਾਨੀ ਲਿਗਾਮੈਂਟ ਨੂੰ ਦੁਬਾਰਾ ਜੁੜਨ ਦਾ ਮੌਕਾ ਦੇਣ ਲਈ 4 ਤੋਂ 6 ਹਫ਼ਤਿਆਂ ਤੱਕ ਜੋੜ ਨੂੰ ਬਿਨਾਂ ਹਿਲਾਏ ਰੱਖਿਆ ਜਾਂਦਾ ਹੈ।
ਸਰਜਰੀ ਬਾਰੇ ਉਦੋਂ ਸੋਚਿਆ ਜਾਂਦਾ ਹੈ ਜਦੋਂ ਪਾਟਣ ਪੂਰਾ ਅਤੇ ਅਸਥਿਰ ਹੋਵੇ, ਜਦੋਂ ਪਾਟੇ ਲਿਗਾਮੈਂਟ ਦਾ ਸਿਰਾ ਪਲਟ ਕੇ ਆਪਣੀ ਥਾਂ ਤੋਂ ਹਟ ਗਿਆ ਹੋਵੇ, ਜਾਂ ਜਦੋਂ ਹੱਡੀ ਦਾ ਕੋਈ ਟੁਕੜਾ ਆਪਣੀ ਸੇਧ ਤੋਂ ਹਿੱਲ ਗਿਆ ਹੋਵੇ। ਇਨ੍ਹਾਂ ਹਾਲਤਾਂ ਵਿੱਚ ਲਿਗਾਮੈਂਟ ਆਪਣੇ ਆਪ ਹੱਡੀ ਨਾਲ ਦੁਬਾਰਾ ਜੁੜ ਕੇ ਠੀਕ ਨਹੀਂ ਹੋ ਸਕਦਾ, ਇਸ ਲਈ ਓਪਰੇਸ਼ਨ ਰਾਹੀਂ ਇਸ ਨੂੰ ਦੁਬਾਰਾ ਜੋੜਿਆ ਜਾਂਦਾ ਹੈ। ਜੇ ਸੱਟ ਕੁਝ ਸਮਾਂ ਪਹਿਲਾਂ ਲੱਗੀ ਸੀ ਅਤੇ ਲਿਗਾਮੈਂਟ ਦੀ ਹੁਣ ਸਿੱਧੀ ਮੁਰੰਮਤ ਨਹੀਂ ਹੋ ਸਕਦੀ, ਤਾਂ ਅਸੀਂ ਤੁਹਾਡੀ ਆਪਣੀ ਬਾਂਹ ਤੋਂ ਜਾਂ ਦਾਨ ਕੀਤੇ ਟਿਸ਼ੂ ਤੋਂ ਲਏ ਟੈਂਡਨ (tendon, ਪੱਠੇ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀ ਮਜ਼ਬੂਤ ਤੰਦ) ਦੀ ਇੱਕ ਪੱਟੀ ਵਰਤ ਕੇ ਲਿਗਾਮੈਂਟ ਨੂੰ ਦੁਬਾਰਾ ਬਣਾ ਸਕਦੇ ਹਾਂ। ਇਸ ਓਪਰੇਸ਼ਨ ਦਾ ਆਪਣਾ ਵੱਖਰਾ ਪੰਨਾ ਹੈ, ਅਤੇ ਤੁਹਾਡੇ ਕੋਈ ਵੀ ਫ਼ੈਸਲਾ ਕਰਨ ਤੋਂ ਪਹਿਲਾਂ ਅਸੀਂ ਤੁਹਾਡੇ ਨਾਲ ਗੱਲ ਕਰਾਂਗੇ ਕਿ ਇਸ ਵਿੱਚ ਕੀ ਕੁਝ ਸ਼ਾਮਲ ਹੈ।
ਕੀ ਉਮੀਦ ਰੱਖੀਏ
ਇਲਾਜ ਨਾਲ, ਅੰਗੂਠੇ ਦੇ ਲਿਗਾਮੈਂਟ ਦੇ ਜ਼ਿਆਦਾਤਰ ਪਾਟਣ ਚੰਗੀ ਤਰ੍ਹਾਂ ਠੀਕ ਹੋ ਜਾਂਦੇ ਹਨ। ਸਪਲਿੰਟ ਜਾਂ ਪਲੱਸਤਰ ਵਿੱਚ ਸਥਿਰ ਰੱਖਿਆ ਅੰਸ਼ਕ ਪਾਟਣ ਆਮ ਤੌਰ ਉੱਤੇ ਠੀਕ ਹੋ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਵਿੱਚ ਚੂੰਢੀ ਭਰਨ ਅਤੇ ਫੜਨ ਦੀ ਤਾਕਤ ਵਾਪਸ ਆ ਜਾਂਦੀ ਹੈ। ਜੇ ਤੁਹਾਨੂੰ ਓਪਰੇਸ਼ਨ ਦੀ ਲੋੜ ਹੈ, ਤਾਂ ਨਤੀਜੇ ਆਮ ਤੌਰ ਉੱਤੇ ਚੰਗੇ ਹੁੰਦੇ ਹਨ: ਜ਼ਿਆਦਾਤਰ ਲੋਕਾਂ ਦੇ ਅੰਗੂਠੇ ਦੀ ਹਿਲਜੁਲ, ਚੂੰਢੀ ਅਤੇ ਪਕੜ ਦੀ ਤਾਕਤ ਬਣੀ ਰਹਿੰਦੀ ਹੈ, ਅਤੇ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਸਮੱਸਿਆਵਾਂ ਘੱਟ ਹੀ ਹੁੰਦੀਆਂ ਹਨ। ਜਿਨ੍ਹਾਂ ਲੋਕਾਂ ਦੀ ਇਹ ਸਰਜਰੀ ਹੋਈ, ਉਹ ਆਪਣੇ ਪਹਿਲਾਂ ਵਾਲੇ ਪੱਧਰ ਉੱਤੇ ਖੇਡਾਂ ਖੇਡਣ ਲਈ ਵਾਪਸ ਗਏ ਹਨ, ਅਤੇ ਪੇਸ਼ੇਵਰ ਖਿਡਾਰੀਆਂ ਨੇ ਬਾਅਦ ਵਿੱਚ ਲਗਭਗ ਉੱਨੇ ਹੀ ਮੈਚ ਖੇਡੇ ਅਤੇ ਉਨ੍ਹਾਂ ਦਾ ਕਰੀਅਰ ਲਗਭਗ ਉੱਨਾ ਹੀ ਲੰਬਾ ਰਿਹਾ।
ਸਿਹਤਯਾਬੀ ਲਈ ਸਬਰ ਚਾਹੀਦਾ ਹੈ। ਪਹਿਲਾਂ ਤੁਹਾਡੇ ਅੰਗੂਠੇ ਨੂੰ ਸਥਿਰ ਰੱਖਿਆ ਜਾਵੇਗਾ, ਕਿਉਂਕਿ ਸ਼ੁਰੂਆਤੀ ਅਕੜਾਅ ਹੀ ਉਹ ਮੁੱਖ ਚੀਜ਼ ਹੈ ਜਿਸ ਤੋਂ ਬਾਅਦ ਵਿੱਚ ਬਚਣਾ ਹੈ। ਜਦੋਂ ਹਿਲਜੁਲ ਦੀ ਇਜਾਜ਼ਤ ਮਿਲ ਜਾਵੇ, ਤਾਂ ਨਰਮ, ਹੌਲੀ-ਹੌਲੀ ਵਧਣ ਵਾਲੀਆਂ ਕਸਰਤਾਂ ਅਹਿਮ ਹਨ: ਠੀਕ ਹੋ ਰਹੇ ਲਿਗਾਮੈਂਟ ਉੱਤੇ ਹੌਲੀ-ਹੌਲੀ ਭਾਰ ਪਾਉਣਾ ਅਤੇ ਇਸ ਨੂੰ ਖਿੱਚਣਾ ਹਿਲਜੁਲ ਅਤੇ ਕੰਮਕਾਜ ਨੂੰ ਸੁਧਾਰਦਾ ਹੈ। ਮਰੀਜ਼ਾਂ ਵੱਲੋਂ ਦੱਸੇ ਨਤੀਜੇ ਸਰਜਰੀ ਤੋਂ ਤਿੰਨ ਅਤੇ 12 ਮਹੀਨੇ ਬਾਅਦ, ਸਰਜਰੀ ਤੋਂ ਪਹਿਲਾਂ ਦੇ ਮੁਕਾਬਲੇ, ਕਾਫ਼ੀ ਸੁਧਰ ਜਾਂਦੇ ਹਨ। ਜੇ ਤੁਹਾਡੀ ਸੱਟ ਕੁਝ ਸਮਾਂ ਪਹਿਲਾਂ ਲੱਗੀ ਸੀ, ਤਾਂ ਵੀ ਮੁਰੰਮਤ ਕਾਰਗਰ ਹੁੰਦੀ ਹੈ, ਹਾਲਾਂਕਿ ਦੇਰ ਨਾਲ ਕੀਤੀ ਮੁਰੰਮਤ ਨਾਲ ਆਮ ਤੌਰ ਉੱਤੇ ਛੇਤੀ ਕੀਤੀ ਮੁਰੰਮਤ ਦੇ ਮੁਕਾਬਲੇ ਅੰਗੂਠੇ ਦੀ ਹਿਲਜੁਲ ਥੋੜ੍ਹੀ ਜ਼ਿਆਦਾ ਘਟਦੀ ਹੈ।
ਇਲਾਜ ਤੋਂ ਬਿਨਾਂ, ਹਾਲਤ ਵੱਖਰੀ ਹੈ। ਚਾਰ ਵਿੱਚੋਂ ਤਿੰਨ ਪੂਰੇ ਪਾਟਣ ਆਪਣੇ ਆਪ ਠੀਕ ਨਹੀਂ ਹੁੰਦੇ, ਆਰਾਮ ਦੇਣ ਦੇ ਬਾਵਜੂਦ ਵੀ। ਜੋੜ ਢਿੱਲਾ ਰਹਿੰਦਾ ਹੈ, ਭਾਰ ਪੈਣ ਉੱਤੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਜਵਾਬ ਦਿੰਦਾ ਰਹਿੰਦਾ ਹੈ, ਅਤੇ ਚੂੰਢੀ ਕਮਜ਼ੋਰ ਅਤੇ ਦਰਦ ਵਾਲੀ ਰਹਿੰਦੀ ਹੈ। ਸਾਲਾਂ ਦੌਰਾਨ, ਇਹ ਲਗਾਤਾਰ ਢਿੱਲਾਪਣ ਜੋੜ ਨੂੰ ਘਿਸਾ ਦਿੰਦਾ ਹੈ: ਜਿਨ੍ਹਾਂ ਲੋਕਾਂ ਦੇ ਪੁਰਾਣੇ (chronic) ਪਾਟਣ ਦੀ ਬਾਅਦ ਵਿੱਚ ਮੁਰੰਮਤ ਕੀਤੀ ਗਈ, ਉਨ੍ਹਾਂ ਵਿੱਚੋਂ 88% ਦੇ ਅੰਗੂਠੇ ਦੇ ਜੋੜ ਵਿੱਚ ਪਹਿਲਾਂ ਹੀ ਕੁਝ ਗਠੀਆ ਸੀ। ਸੱਟ ਲੱਗਣ ਵੇਲੇ ਵੱਡੀ ਉਮਰ ਦਾ ਸੰਬੰਧ ਉਸ ਜੋੜ ਵਿੱਚ ਵਧੇਰੇ ਗੰਭੀਰ ਗਠੀਏ ਨਾਲ ਹੈ।
ਅੱਗੇ ਦੀ ਯੋਜਨਾ ਬਣਾਉਂਦੇ ਸਮੇਂ ਕੁਝ ਗੱਲਾਂ ਜਾਣਨ ਯੋਗ ਹਨ। ਜੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਗਰਮ, ਲਾਲ, ਸੁੱਜਿਆ ਹੋਇਆ ਅਤੇ ਦਰਦ ਵਾਲਾ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ; ਜੀਪੀ ਦੇ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਨਹੀਂ ਹੈ। ਜੇ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ ਜਾਂ ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਸਪੈਸ਼ਲਿਸਟ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ।
ਡਾਕਟਰ ਨੂੰ ਕਦੋਂ ਮਿਲਣਾ ਚਾਹੀਦਾ ਹੈ
ਕਿਸੇ ਵੀ ਅਜਿਹੀ ਸੱਟ ਤੋਂ ਬਾਅਦ ਜਿਸ ਵਿੱਚ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਜ਼ੋਰ ਨਾਲ ਪਾਸੇ ਵੱਲ ਮੁੜ ਗਿਆ ਹੋਵੇ, ਛੇਤੀ ਹੀ ਆਪਣੇ ਅੰਗੂਠੇ ਦੀ ਜਾਂਚ ਕਰਵਾਓ, ਭਾਵੇਂ ਇਹ ਇੱਕ ਆਮ ਜਿਹੀ ਮੋਚ ਲੱਗੇ। ਪੂਰੇ ਪਾਟਣ ਦੀ ਜਿੰਨੀ ਛੇਤੀ ਜਾਂਚ ਹੁੰਦੀ ਹੈ, ਤੁਹਾਡੇ ਕੋਲ ਓਨੇ ਹੀ ਜ਼ਿਆਦਾ ਵਿਕਲਪ ਹੁੰਦੇ ਹਨ, ਕਿਉਂਕਿ ਬਹੁਤ ਦੇਰ ਤੱਕ ਛੱਡੇ ਪਾਟਣ ਲਈ ਵੱਡੇ ਓਪਰੇਸ਼ਨ ਦੀ ਲੋੜ ਪੈ ਸਕਦੀ ਹੈ ਜਾਂ ਇਸ ਨਾਲ ਲੰਬੇ ਸਮੇਂ ਤੱਕ ਰਹਿਣ ਵਾਲਾ ਅਕੜਾਅ ਅਤੇ ਕਮਜ਼ੋਰੀ ਰਹਿ ਸਕਦੀ ਹੈ। ਸਪੈਸ਼ਲਿਸਟ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ ਜੇ ਚੂੰਢੀ ਭਰਨ ਜਾਂ ਫੜਨ ਵੇਲੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਅਜੇ ਵੀ ਜਵਾਬ ਦੇ ਜਾਂਦਾ ਹੈ, ਜੇ ਕੁਝ ਹਫ਼ਤਿਆਂ ਬਾਅਦ ਵੀ ਚੂੰਢੀ ਕਮਜ਼ੋਰ ਜਾਂ ਦਰਦ ਵਾਲੀ ਰਹਿੰਦੀ ਹੈ, ਜਾਂ ਜੇ ਤੁਹਾਨੂੰ ਜੋੜ ਦੇ ਅੰਦਰਲੇ ਕਿਨਾਰੇ ਉੱਤੇ ਇੱਕ ਛੋਟੀ, ਸਖ਼ਤ ਗੰਢ ਮਹਿਸੂਸ ਹੁੰਦੀ ਹੈ। ਜੇ ਸੱਟ ਕੁਝ ਸਮਾਂ ਪਹਿਲਾਂ ਲੱਗੀ ਸੀ ਅਤੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਢਿੱਲਾ ਹੈ ਜਾਂ ਘਿਸ ਰਿਹਾ ਹੈ, ਤਾਂ ਵੀ ਜਾਂਚ ਕਰਵਾਉਣੀ ਫ਼ਾਇਦੇਮੰਦ ਹੈ। ਅਤੇ ਜੇ ਤੁਹਾਡਾ ਅੰਗੂਠਾ ਗਰਮ, ਲਾਲ, ਸੁੱਜਿਆ ਹੋਇਆ ਅਤੇ ਦਰਦ ਵਾਲਾ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਵਿਸਥਾਰ ਵਿੱਚ
Advanced reading: the deeper science (optional)
ਇਹ ਹਿੱਸਾ ਤੁਹਾਡੇ ਆਪਣੇ ਇਲਾਜ ਦੇ ਫ਼ੈਸਲਿਆਂ ਲਈ ਲੋੜੀਂਦੀ ਜਾਣਕਾਰੀ ਤੋਂ ਅੱਗੇ ਜਾਂਦਾ ਹੈ। ਅੰਗੂਠੇ ਦੇ ਅਲਨਰ ਕੋਲੈਟਰਲ ਲਿਗਾਮੈਂਟ ਦੀ ਸੱਟ ਬਾਰੇ ਵਾਧੂ ਪੜ੍ਹਨਾ ਫ਼ਾਇਦੇਮੰਦ ਹੈ ਕਿਉਂਕਿ ਸਾਰਾ ਫ਼ੈਸਲਾ ਸਰੀਰ ਦੀ ਬਣਤਰ ਬਾਰੇ ਇੱਕੋ ਸਵਾਲ ਉੱਤੇ ਟਿਕਿਆ ਹੈ: ਕੀ ਪਾਟਿਆ ਲਿਗਾਮੈਂਟ ਪਲਟ ਕੇ ਪਹੁੰਚ ਤੋਂ ਬਾਹਰ ਚਲਾ ਗਿਆ ਹੈ, ਅਤੇ ਕਿਉਂਕਿ ਹੁਣ ਇਸ ਗੱਲ ਦਾ ਸਾਫ਼ ਜਵਾਬ ਹੈ ਕਿ ਇਸ ਦਾ ਨਿਬੇੜਾ ਕਰਨ ਲਈ ਕਿਹੜਾ ਸਕੈਨ ਵਰਤਣਾ ਹੈ।
ਸਟੈਨਰ ਲੀਜ਼ਨ, ਅਤੇ ਇਹ ਸਭ ਕੁਝ ਕਿਉਂ ਬਦਲ ਦਿੰਦਾ ਹੈ
ਅਲਨਰ ਕੋਲੈਟਰਲ ਲਿਗਾਮੈਂਟ ਹਰ ਚੂੰਢੀ ਅਤੇ ਪਕੜ ਦੇ ਪਾਸੇ ਵਾਲੇ ਜ਼ੋਰ ਦੇ ਖ਼ਿਲਾਫ਼ ਅੰਗੂਠੇ ਨੂੰ ਸਥਿਰ ਰੱਖਦਾ ਹੈ। ਜਦੋਂ ਇਹ ਆਪਣੀ ਜੁੜਨ ਵਾਲੀ ਥਾਂ ਤੋਂ ਪਾਟਦਾ ਹੈ, ਤਾਂ ਆਮ ਤੌਰ ਉੱਤੇ ਇਹ ਉੱਥੇ ਹੀ ਰਹਿੰਦਾ ਹੈ ਜਿੱਥੇ ਇਹ ਠੀਕ ਹੋ ਸਕਦਾ ਹੈ।
ਕਈ ਵਾਰ ਅਜਿਹਾ ਨਹੀਂ ਹੁੰਦਾ। ਟੈਂਡਨ ਦੀ ਇੱਕ ਪਰਤ, ਜਿਸ ਨੂੰ ਐਡਕਟਰ ਐਪੋਨਿਊਰੋਸਿਸ (adductor aponeurosis) ਕਹਿੰਦੇ ਹਨ, ਲਿਗਾਮੈਂਟ ਦੇ ਉੱਪਰ ਪਈ ਹੁੰਦੀ ਹੈ, ਅਤੇ ਜੇ ਪਾਟਿਆ ਸਿਰਾ ਸੁੰਗੜ ਕੇ ਉਸ ਪਰਤ ਦੇ ਉੱਪਰੋਂ ਪਿੱਛੇ ਚਲਾ ਜਾਵੇ, ਤਾਂ ਐਪੋਨਿਊਰੋਸਿਸ ਲਿਗਾਮੈਂਟ ਅਤੇ ਹੱਡੀ ਦੇ ਵਿਚਕਾਰ ਆ ਜਾਂਦਾ ਹੈ। ਇਹ ਸਟੈਨਰ ਲੀਜ਼ਨ (Stener lesion) ਹੈ, ਅਤੇ ਇਸੇ ਕਰਕੇ ਇਸ ਸੱਟ ਦਾ ਇਲਾਜ ਜ਼ਿਆਦਾਤਰ ਮੋਚਾਂ ਤੋਂ ਵੱਖਰਾ ਕੀਤਾ ਜਾਂਦਾ ਹੈ: ਲਿਗਾਮੈਂਟ ਹੁਣ ਉਸ ਹੱਡੀ ਨੂੰ ਛੂਹ ਨਹੀਂ ਰਿਹਾ ਜਿਸ ਨਾਲ ਜੁੜ ਕੇ ਇਸ ਨੇ ਠੀਕ ਹੋਣਾ ਹੈ, ਇਸ ਲਈ ਕਿੰਨਾ ਵੀ ਸਪਲਿੰਟ ਲਗਾਇਆ ਜਾਵੇ, ਇਹ ਦੁਬਾਰਾ ਨਹੀਂ ਜੁੜੇਗਾ।
ਇਲਾਜ ਬਾਰੇ ਸਭ ਕੁਝ ਇਸ ਗੱਲ ਤੋਂ ਨਿਕਲਦਾ ਹੈ ਕਿ ਇਹ ਹੋਇਆ ਹੈ ਜਾਂ ਨਹੀਂ।
ਇਸ ਦਾ ਜਵਾਬ ਦੇਣ ਲਈ ਅਲਟਰਾਸਾਊਂਡ ਕਾਫ਼ੀ ਹੈ
ਕਿਉਂਕਿ ਫ਼ੈਸਲਾ ਹਾਂ-ਜਾਂ-ਨਾਂਹ ਵਾਲਾ ਅਤੇ ਅਹਿਮ ਨਤੀਜਿਆਂ ਵਾਲਾ ਹੈ, ਸਕੈਨ ਦਾ ਸਵਾਲ ਅਸਧਾਰਨ ਤੌਰ ਉੱਤੇ ਚੰਗੀ ਤਰ੍ਹਾਂ ਪਰਿਭਾਸ਼ਿਤ ਹੈ — ਅਤੇ ਇਸ ਦਾ ਜਵਾਬ ਮਿਲ ਚੁੱਕਾ ਹੈ। 422 ਮਰੀਜ਼ਾਂ ਵਿੱਚ, ਅਲਟਰਾਸਾਊਂਡ ਅਤੇ MRI ਦੋਵੇਂ ਸਟੈਨਰ ਲੀਜ਼ਨ ਲੱਭਣ ਵਿੱਚ ਉੱਚੀ ਸ਼ੁੱਧਤਾ ਦਿਖਾਉਂਦੇ ਹਨ, ਅਤੇ ਅਲਟਰਾਸਾਊਂਡ ਪਹਿਲੀ ਪਸੰਦ ਦੇ ਸਕੈਨ ਵਜੋਂ ਢੁਕਵਾਂ ਹੈ [1]।
ਇਹ ਅਮਲੀ ਤੌਰ ਉੱਤੇ ਕੰਮ ਦੀ ਜਾਣਕਾਰੀ ਹੈ। ਅਲਟਰਾਸਾਊਂਡ MRI ਨਾਲੋਂ ਤੇਜ਼, ਸਸਤਾ ਅਤੇ ਵੱਧ ਆਸਾਨੀ ਨਾਲ ਮਿਲਣ ਵਾਲਾ ਹੈ, ਅਤੇ ਜਿੱਥੇ ਤਜਰਬੇਕਾਰ ਸਕੈਨ ਕਰਨ ਵਾਲਾ ਮੌਜੂਦ ਹੋਵੇ, ਉੱਥੇ ਜੋ ਇਹ ਪਹਿਲਾਂ ਹੀ ਦਿਖਾ ਚੁੱਕਾ ਹੈ ਉਸ ਦੀ ਪੁਸ਼ਟੀ ਲਈ ਇਸ ਤੋਂ ਬਾਅਦ MRI ਕਰਵਾਉਣ ਦੀ ਲੋੜ ਨਹੀਂ। ਇਹ ਹਿਲਜੁਲ ਦੌਰਾਨ ਵੀ ਦੇਖ ਸਕਦਾ ਹੈ: ਸਕੈਨ ਦੌਰਾਨ ਅੰਗੂਠੇ ਉੱਤੇ ਜ਼ੋਰ ਪਾ ਕੇ ਜਾਂਚ ਕੀਤੀ ਜਾ ਸਕਦੀ ਹੈ।
ਜਿੱਥੇ ਸਟੈਨਰ ਲੀਜ਼ਨ ਨਹੀਂ ਹੈ, ਉੱਥੇ ਢਿੱਲਾਪਨ ਫ਼ੈਸਲਾ ਕਰਦਾ ਹੈ
ਬ੍ਰਿਟਿਸ਼ ਸੋਸਾਇਟੀ ਫ਼ਾਰ ਸਰਜਰੀ ਆਫ਼ ਦ ਹੈਂਡ (British Society for Surgery of the Hand) ਦੀ ਗਾਈਡਲਾਈਨ ਇਹ ਰਾਹ ਸਾਫ਼-ਸਾਫ਼ ਦੱਸਦੀ ਹੈ। ਤਾਜ਼ਾ ਸੱਟਾਂ ਵਾਲੇ ਮਰੀਜ਼ਾਂ ਦੀ ਜਾਂਚ ਸੱਟ ਦੇ ਹਾਲ, ਡਾਕਟਰੀ ਜਾਂਚ ਅਤੇ ਐਕਸ-ਰੇ ਨਾਲ ਹੋਣੀ ਚਾਹੀਦੀ ਹੈ। ਜਿਨ੍ਹਾਂ ਦੇ ਜੋੜ ਵਿੱਚ ਖ਼ਾਸ ਢਿੱਲਾਪਨ ਨਹੀਂ, ਉਨ੍ਹਾਂ ਦਾ ਇਲਾਜ ਬਿਨਾਂ ਸਰਜਰੀ ਕੀਤਾ ਜਾ ਸਕਦਾ ਹੈ, ਜਦਕਿ ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਖ਼ਾਸ ਢਿੱਲਾਪਨ ਹੈ, ਉਨ੍ਹਾਂ ਦਾ ਇਲਾਜ ਸਾਂਝੇ ਫ਼ੈਸਲੇ ਤੋਂ ਬਾਅਦ ਜਾਂ ਤਾਂ ਬਿਨਾਂ ਸਰਜਰੀ ਸਥਿਰ ਰੱਖ ਕੇ ਜਾਂ ਸਰਜਰੀ ਰਾਹੀਂ ਮੁਰੰਮਤ ਕਰਕੇ ਕੀਤਾ ਜਾ ਸਕਦਾ ਹੈ [2]।
ਦੋ ਗੱਲਾਂ ਉਭਾਰਨ ਯੋਗ ਹਨ। ਪਹਿਲੀ ਇਹ ਕਿ ਐਕਸ-ਰੇ ਵੱਡੇ ਸਕੈਨਾਂ ਤੋਂ ਪਹਿਲਾਂ ਆਉਂਦੇ ਹਨ, ਕੁਝ ਹੱਦ ਤੱਕ ਐਵਲਸ਼ਨ ਫ੍ਰੈਕਚਰ (avulsion fracture, ਲਿਗਾਮੈਂਟ ਨਾਲ ਹੱਡੀ ਦਾ ਟੁਕੜਾ ਉੱਖੜ ਜਾਣਾ) ਨੂੰ ਬਾਹਰ ਕਰਨ ਲਈ, ਜੋ ਇਲਾਜ ਨੂੰ ਫਿਰ ਬਦਲ ਦਿੰਦਾ ਹੈ। ਦੂਜੀ ਇਹ ਕਿ ਖ਼ਾਸ ਢਿੱਲੇਪਨ ਵਿੱਚ ਵੀ ਸਰਜਰੀ ਲਾਜ਼ਮੀ ਨਹੀਂ ਹੈ: ਗਾਈਡਲਾਈਨ ਸਾਫ਼ ਤੌਰ ਉੱਤੇ ਇਸ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਅਤੇ ਮੁਰੰਮਤ ਵਿਚਕਾਰ ਇੱਕ ਸਾਂਝੇ ਫ਼ੈਸਲੇ ਵਜੋਂ ਰੱਖਦੀ ਹੈ, ਜੋ ਓਪਰੇਸ਼ਨ ਨੂੰ ਇੱਕੋ-ਇੱਕ ਰਾਹ ਦੱਸਣ ਨਾਲੋਂ ਵੱਧ ਈਮਾਨਦਾਰ ਰੁਖ਼ ਹੈ।
ਗ਼ਲਤੀ ਹੋਣ ਦੇ ਨਤੀਜੇ ਖ਼ਾਸ ਕਿਉਂ ਹਨ
ਕੰਮ ਨਾ ਕਰ ਰਿਹਾ ਅਲਨਰ ਕੋਲੈਟਰਲ ਲਿਗਾਮੈਂਟ ਆਰਾਮ ਵੇਲੇ ਦਰਦ ਜਾਂ ਜ਼ਿਆਦਾਤਰ ਕੰਮਾਂ ਵਿੱਚ ਮੁਸ਼ਕਲ ਪੈਦਾ ਨਹੀਂ ਕਰਦਾ। ਇਹ ਅਜਿਹਾ ਅੰਗੂਠਾ ਬਣਾਉਂਦਾ ਹੈ ਜੋ ਪਾਸੇ ਵਾਲੇ ਭਾਰ ਹੇਠ ਜਵਾਬ ਦੇ ਜਾਂਦਾ ਹੈ, ਜਿਵੇਂ ਚਾਬੀ ਘੁਮਾਉਣਾ, ਮਰਤਬਾਨ ਖੋਲ੍ਹਣਾ, ਭਾਰੇ ਪਤੀਲੇ ਨੂੰ ਕੰਢੇ ਤੋਂ ਫੜਨਾ, ਕਿਉਂਕਿ ਚੂੰਢੀ ਦਬਾਉਣ ਲਈ ਇੱਕ ਸਥਿਰ ਟੇਕ ਉੱਤੇ ਨਿਰਭਰ ਕਰਦੀ ਹੈ।
ਇਲਾਜ ਤੋਂ ਬਿਨਾਂ, ਲੰਬੇ ਸਮੇਂ ਦੀ ਅਸਥਿਰਤਾ ਸਾਲਾਂ ਦੌਰਾਨ ਉਸ ਜੋੜ ਵਿੱਚ ਗਠੀਏ ਵੱਲ ਲੈ ਜਾਂਦੀ ਹੈ। ਇਸੇ ਕਰਕੇ ਜੋ ਸੱਟ ਸਾਧਾਰਨ ਮੋਚ ਵਰਗੀ ਲੱਗਦੀ ਹੈ, ਉਸ ਦੀ ਵੀ ਠੋਸ ਜਾਂਚ ਹੋਣੀ ਚਾਹੀਦੀ ਹੈ: ਇਸ ਨੂੰ ਨਜ਼ਰਅੰਦਾਜ਼ ਕਰਨ ਦੀ ਕੀਮਤ ਬਾਅਦ ਦੇ ਹਫ਼ਤਿਆਂ ਵਿੱਚ ਮਹਿਸੂਸ ਨਹੀਂ ਹੁੰਦੀ, ਜਦੋਂ ਅੰਗੂਠਾ ਸ਼ਾਂਤ ਹੋ ਜਾਂਦਾ ਹੈ ਅਤੇ ਠੀਕ ਲੱਗਦਾ ਹੈ, ਸਗੋਂ ਬਹੁਤ ਬਾਅਦ ਵਿੱਚ।
ਹਵਾਲੇ
[1] Qamhawi Z, Shah K, Kiernan G, Furniss D, Teh J, Azzopardi C. Diagnostic accuracy of ultrasound and magnetic resonance imaging in detecting Stener lesions of the thumb: systematic review and meta-analysis. J Hand Surg Eur Vol. 2021;46(9):946-53. https://doi.org/10.1177/1753193421993015
[2] Dean B, Rodrigues J, Riley N, Rabey N, Donnison E, Challen K, et al. Guideline on managing thumb ulnar collateral ligament injuries: the British Society for Surgery of the Hand. J Hand Surg Eur Vol. 2024;49(10):1195-201. https://doi.org/10.1177/17531934241274612
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Diagnosis and Imaging
- Ultrasonography has evolved as a reliable adjunct to clinical examination in the evaluation of the ulnar collateral ligament (UCL) of the thumb [1].
- MRI evaluation reveals greater details enabling better understanding and management of ulnar collateral ligament injuries of the thumb metacarpophalangeal (MCP) joint [2].
- A 4-stage, treatment-oriented classification of thumb UCL injury is based on the degree of UCL displacement, with correlation with the likelihood of success with either immobilization or operative intervention [10].
- The presence of a displaced fleck sign has implications for offering surgery to patients with thumb UCL injuries because of a high likelihood of a Stener lesion [17].
Clinical Indications and Natural History
- Valgus laxity greater than 30 degrees or more than 15 degrees more than in the noninjured thumb with the MCP joint in extension is an indication for operative management [3].
- Untreated ulnar collateral ligament injury of the thumb metacarpophalangeal joint can lead to long-term pain and functional limitations [5].
- 75% of cases with complete rupture of the ulnar collateral ligament of the thumb will fail to heal with conservative treatment [13].
- The rate of surgery for acute thumb MP UCL injury varies based on patient characteristics and the individual treating surgeon [6].
Treatment Outcomes
- Surgical management of thumb UCL injuries produces overall favorable results [4].
- Patient-reported outcomes improve significantly at three and 12 months after open surgical repair of the thumb UCL compared to baseline [24].
- Patients with both acute and chronic thumb UCL injuries have similarly acceptable functional outcomes, postoperative pain, and satisfaction [11].
- Return-to-play rates after surgical treatment of thumb UCL injuries are high, with reassuring return to preinjury level of play with few complications [9].
- Thumb ulnar collateral ligament injuries can be safely and effectively managed by football position demands [14].
- Players who underwent thumb UCL repair played in a similar number of games per season and had similar career lengths in the MLB as controls [16].
- Treatment of a thumb UCL complete rupture (Grade III) using a custom-made hinged splint shows promise in the conservative management of compliant patients [19].
Surgical Techniques and Rehabilitation
- A controlled active motion therapy protocol after suture anchor repair of a ruptured UCL of the thumb is safe from a biomechanical point of view [8].
- Intraosseous suture anchor repair is a safe and effective method for repair of complete tears of the ulnar collateral ligament of the thumb MP joint [12].
- Both pull-out sutures and bone anchor techniques are safe and effective for treating thumb ulnar collateral ligament injuries [23].
- Thumb UCL repair with suture tape augmentation demonstrates short-term outcomes comparable to what has been reported for other methods of repair [26].
- Mini hook plate fixation could be an alternative treatment technique for thumb UCL avulsion fractures [21].
- The surgical treatment of an ulnar collateral ligament lesion of the thumb using the Fiji Anchor can lead to an excellent clinical outcome with a minor complication rate [48].
- An accelerated rehabilitation protocol has been clinically applied in athletes following thumb MCP UCL repair with suture tape augmentation [22].
- The patient is placed in the supine position with a small bump on which to rest the thumb for open repair of the UCL [28].
- The surgeon should position themselves between the shoulder and head to allow easier access to the ulnar aspect of the thumb during UCL repair [28].
- A lazy S approach is used on the ulnar aspect of the thumb for UCL repair [28].
- Careful identification of the radial sensory nerve is required during UCL repair, with prior documentation of sensibility [28].
- The adductor aponeurosis is incised on the ulnar side during UCL repair [28].
- The site of rupture for the UCL is identified as distal off the phalanx, midsubstance, or proximal [28].
- Nonabsorbable suture with pullout button, bone anchors, or figure-of-eight imbrication of midsubstance repair are options for repairing the UCL [28].
- Motion is limited for the first 4 to 6 weeks depending on chronicity of the injury, with more chronic injuries immobilized longer [28].
- Guided therapy at 6 weeks in a removable splint is part of the postoperative protocol for UCL repair [28].
Anatomy & Pathophysiology
Bony Anatomy and Joint Mechanics
- The thumb metacarpophalangeal (MCP) articulation is of a condylar type [52].
- Flexion of the thumb MCP joint is always accompanied by radial deviation and pronation, which stretches the ulnar metacarpophalangeal ligament [52].
- The stability of the thumb MCP joint is considered more important than movement from a functional viewpoint [52].
- The carpometacarpal ray of the thumb is anterior to the plane of the other metacarpals and makes an angle of about 47 degrees with the second ray [52].
- The distal articular surface of the trapezium is likened to a saddle whose concave curvature lies in a dorsopalmar direction [52].
- The corresponding surface on the base of the first metacarpal presents a grooved surface in the radioulnar direction [52].
- The trapeziometacarpal joint has two longitudinal axes and two degrees of freedom [52].
- The shape of the trapeziometacarpal articular surface does not make for good stability except in anteposition and pronation when the two surfaces are congruent [52].
- The necessary stability of the trapeziometacarpal joint is provided by a complex ligamentous system which does not limit mobility [52].
- This ligamentous system essentially consists of a strong ulnar ligament from the base of the first metacarpal to the second metacarpal and to the trapezoid [52].
- The ulnar ligament of the trapeziometacarpal joint is the structure that resists in a Bennett fracture [52].
- The radial side of the trapeziometacarpal joint has a much weaker ligament [52].
- There is an intrinsic instability at the level of the trapeziometacarpal joint where the pressure is very high [52].
- This pressure is proportional to the force of the grip at the distal end of the thumb and to the length of the lever arm [52].
- Cooney and Chao (1977) found that joint compression forces during simple pinch averaged 3.0 kg of force at the interphalangeal joint, 5.4 kg at the metacarpophalangeal joint, and 12.0 kg at the carpometacarpal joint [52].
- Compression forces of up to 120 kg may occur at the carpometacarpal joint during strong grasp [52].
- Stability of the trapeziometacarpal joint is dynamically provided by a single structure, the tendon of the abductor pollicis longus [52].
- The abductor pollicis longus tendon has stabilizing function only when the first metacarpal is abducted [52].
- In adduction, the long abductor increases the risk of subluxation of the trapeziometacarpal joint [52].
Ligamentous Anatomy and Injury Patterns
- The ulnar collateral ligament (UCL) serves as the primary stabilizer against valgus stress at the thumb MCP joint [20].
- The UCL plays an essential role in pinch strength, grasping function, and dexterity [20].
- The mechanism of injury to the UCL is sudden, forced radial deviation (abduction), often resulting from a fall on an outstretched hand with the thumb abducted [44].
- In skiing, if a person falls while gripping the ski pole, the handle abducts the thumb [44].
- Associated injuries to UCL tears include tears of the dorsal capsule and ulnar aspect of the volar plate [44].
- Associated injuries to UCL tears occasionally include a rent in the adductor aponeurosis [44].
- Volar subluxation of the MCP joint may result from concomitant tears of the dorsal capsule and UCL [44].
- Distal tears of the UCL at its insertion in the proximal phalangeal base are more common than proximal tears from the metacarpal [44].
- Ruptures within the substance of the ligament occasionally occur [44].
- The collateral ligaments of the thumb MP joint afford lateral stability and resist volar subluxation [44].
- If one collateral ligament is torn, the proximal phalanx tends to rotate volarly on the side of the tear, with the opposite intact ligament serving as the axis [44].
- In the case of an isolated UCL rupture, the proximal phalanx rotates in supination around the intact radial collateral ligament [44].
- An avulsion fracture of the ulnar base of the proximal phalanx at the insertion of the ligament is the most common fracture pattern associated with UCL injuries [44].
- Typically, the avulsion fracture fragment is small and includes little of the articular surface [44].
- Fractures involving more than 10% of the articular surface can occur and may require fixation if they are displaced 2 mm or more and associated with articular incongruity [44].
- Avulsion fractures from the metacarpal head and intraarticular shearing fractures of the volar surface of the radial condyle of the metacarpal head have also been reported [44].
- A rare but potentially problematic fracture pattern involves a rupture of the UCL from the proximal phalanx and a simultaneous articular shear fracture of the proximal phalangeal base [44].
- In the skeletally immature individual, isolated rupture of the UCL without a Salter fracture of the proximal phalanx is rare but does occur [44].
- The UCL ruptures off the base of the proximal phalanx [62].
- The avulsed ligament, with or without a bony fragment, can become displaced above the adductor aponeurosis, preventing healing [62].
- This displacement is known as a Stener lesion [62].
- In 25 of 39 patients with complete ruptures of the UCL, Stener found the adductor aponeurosis interposed between the ruptured ulnar collateral ligament and its site of insertion on the base of the proximal phalanx [47].
- On clinical examination, a prominent lump can be palpated that represents the ulnar collateral ligament being proximally and superficially displaced by the adductor aponeurosis [47].
- Pathologic rotation of the thumb may be evident in Stener lesions [47].
- If left uncorrected, a Stener lesion prevents proper healing and leads to chronic instability and subsequent arthrosis [47].
- Other injuries associated with tears of the UCL include avulsion fractures, dorsal capsular tears, and volar plate tears [47].
- The adductor aponeurosis interposition prevents direct ligament healing without surgery [42].
- The UCL is typically avulsed distally [35].
- Although the injury is often at the distal portion where it attaches to the proximal volar aspect of the phalanx, midsubstance and metacarpal-based tears can occur [35].
- The anatomic attachment site for a distal avulsion of the UCL is 25% dorsal from the volar surface of the proximal phalanx [94].
- A single anchor is placed volar to the axis of the joint for distal avulsion repair [94].
- The radial collateral ligament (RCL) ruptures from its origin, from its insertion, or at the midsubstance [62].
- RCL ruptures are frequently associated with dorsal or dorsoradial capsular tears and with extensor pollicis brevis avulsions or tears [62].
- No equivalent of the Stener lesion exists for the RCL [62].
- RCL ruptures seem susceptible to chronic instability [62].
- The radial-based abductor cannot create a Stener-type lesion [63].
Pathophysiology and Biomechanics
- Sequential tearing of the thumb UCL leads to progressive instability of the MCP joint [7].
- Untreated complete ruptures may result in chronic instability, weakness of pinch, pain, and functional impairment [20].
- Causes of chronic instability of the UCL include an untreated acute tear, failure to recognize a Stener lesion, or progressive attenuation of the ligament [100].
- Patients with chronic instability usually present with pain, swelling, and weakness of the involved thumb [100].
- The pain tends to be exacerbated by forceful pinch and activities requiring torsional motions of the hand, such as unscrewing jar tops [100].
- Holding large objects like a half-gallon container of milk may be painful and may cause a feeling of instability or lack of power because of the thumb’s inability to resist counterpressure [100].
- Chronic instability is manifested by gross instability to valgus stress with no endpoint [100].
- Crepitus with active motion suggests degenerative disease in chronic UCL instability [100].
- The resting posture of the thumb should be observed for volar subluxation or radial deviation of the MP joint in chronic instability [100].
- Biomechanically, there are no treatments of repair or reconstruction using native tissues that provide equivalent strength to the preinjured ligament [105].
- No static ligament reconstruction restores the normal stability characteristics of the thumb UCL [15].
- Single- and double-bundle UCL reconstructions of the thumb MCP joint have comparable biomechanical properties in regard to joint congruity under valgus load [40].
- The reconstruction tunnel positioning of triangular configuration with apex proximal stabilizes the thumb MCP joint while maintaining flexion/extension range of motion [60].
- Although both suture tape and suture anchor constructs recapitulate native joint stiffness, repair with suture tape demonstrated the greatest biomechanical strength in stiffness and load-to-failure [90].
- In round joints, only the non-anatomic Glickel procedure restores normal range of motion and stability [111].
- In flat joints, the Glickel procedure and a modified Fairhurst configuration with origins dorsal in the metacarpal head restore range of motion and stability [111].
- Nonanatomic repositioning of the UCL might affect joint motion [30].
- Palmar placement of the UCL origin on the metacarpal increased radial deviation from a mean of 18° to a mean of 27° compared with the intact joint [30].
- Proximal placement of the UCL origin on the metacarpal decreased radial deviation from a mean of 18° to a mean of 10° compared with the intact joint [30].
- Dorsal placement of the UCL insertion on the phalanx increased radial deviation from a mean of 18° to a mean of 25° compared with the intact joint [30].
- Distal positioning of the UCL insertion on the phalanx decreased radial deviation from a mean of 18° to a mean of 11° compared with the intact joint [30].
- Performing a physical examination to assess the amount of instability of an ulnar collateral ligament injury did not create a Stener lesion if the exam was performed in a controlled, gentle manner with the thumb held without rotation [112].
- It was possible to create a Stener lesion when the thumb was tested in a flexed and supinated position, but only if there was sectioning of the proper UCL, the accessory UCL, and the origin of the ulnar sagittal band at the adductor aponeurosis [112].
- Supination and flexion of the thumb provided less stability when both components of the UCL were sectioned [112].
- Pronation and supination play a role in stability of the thumb MCP joint [112].
Classification
- The BSSH BEST guideline defines significant UCL laxity as no firm endpoint, OR > 20 degrees laxity vs. the other side, OR > 30 degrees laxity [39].
- The term ‘Stener lesion’ is used to describe when the ligament is completely torn and is displaced superficial to the adductor aponeurosis [18].
- In a Stener lesion, the ruptured ligament becomes displaced superficial to the adductor aponeurosis and is unable to heal anatomically without surgical intervention [20].
- Presence of a displaced fleck sign has implications for offering surgery to patients with thumb UCL injuries because of a high likelihood of a Stener lesion [17].
Clinical Presentation
Symptoms and Signs
- Patients commonly report pain, swelling, and ecymosis around the thumb metacarpophalangeal joint [47].
- Tenderness is greatest over the ulnar aspect of the thumb metacarpophalangeal joint [47].
- A prominent lump can be palpated representing the ulnar collateral ligament being proximally and superficially displaced by the adductor aponeurosis in the presence of a Stener lesion [47].
- Pathologic rotation of the thumb may be evident in cases of Stener lesion [47].
- Incomplete acute tears and nondisplaced avulsion fractures are managed with a thumb spica cast for up to 4 weeks, followed by removable protective splinting for 3 more weeks with active range-of-motion exercises [42].
- Skier's thumb can lead to chronic pain and instability when diagnosed incorrectly [83].
Clinical Examination
- The metacarpophalangeal joint is generally examined by applying a radial force in extension and with approximately 30° of MCPJ flexion to relax the palmar plate [18].
- Physical examination is performed with a valgus stress applied in neutral rotation to the thumb in both extension (testing the accessory ligament) and 30° to 35° flexion (proper ligament) [42].
- An injured thumb that shows more than 30 degrees of instability compared with the uninjured side indicates a complete rupture [47].
- Valgus instability of more than 30°—or more than 10° compared with the contralateral thumb in both flexion and extension—indicates complete rupture of the proper and accessory UCL [80].
- Instability of the MCP joint in flexion indicates rupture of the proper UCL only [80].
- Comparison with the uninjured contralateral thumb is unreliable in many individuals due to significant variation between right and left thumbs [32].
- New evidence suggests that a lack of definite end point rather than comparison with the uninjured side should be used to define complete UCL rupture [42].
- If a hard endpoint is not encountered and there is increased deviation (>20 degrees) at the MP joint, surgery is recommended [35].
- For those patients with significant guarding, a digital block may be necessary to carry out the stress test [35].
- The ulnar side of the joint should be palpated for a Stener lesion, where both the proper and accessory ligament are retracted and lie on the adductor aponeurosis [42].
- Physical examination is required to determine stability with injuries to the ulnar structures of the thumb metacarpophalangeal joint [31].
- Clinical examination is recommended to assess for significant laxity of the UCL, defined as no firm endpoint, or > 20 degrees laxity vs. the other side, or > 30 degrees laxity [39].
Imaging and Diagnostic Tests
- Plain radiographs should be obtained prior to any stress examinations to avoid displacing an otherwise nondisplaced fracture [42].
- Plain radiographs should be obtained prior to any stress examinations to exclude obvious fractures and dislocation or subluxation [58].
- Anteroposterior stress radiographs can be obtained of both thumbs for comparison purposes [47].
- Stress radiographs are useful for identifying Stener lesions, however, these are often uncomfortable for the patient and guarding may lead to false-negative results [42].
- Fluoroscopy can aid the diagnosis to see if the joint becomes incongruent and to measure the deviation compared to the contralateral limb [35].
- Ultrasonography has evolved as a reliable adjunct to clinical examination in evaluation of the UCL of the thumb [1].
- MRI evaluation reveals greater details enabling better understanding and management of ulnar collateral ligament injuries of the thumb MCP joint [2].
- Ultrasound had a positive predictive value for rupture of 94% when compared with the operative finding [58].
- The overall agreement between specialist clinic examination and ultrasound for injury to the ulnar collateral ligament was 85% (kappa 0.647) [58].
- Senior House Officers in the A&E department were able to correctly diagnose only 45% of the ruptures of the ulnar collateral ligament [58].
- In a study of 49 patients, ultrasound identified Stener lesions with a sensitivity of 36% and specificity of 61% [51].
- MRI and US of suspected UCL injury did not demonstrate good enough sensitivity for the authors to recommend their implementation and use in clinical situations [51].
- A magnetic resonance imaging scan is recommended for additional preoperative planning because it provides a detailed assessment of tear location, injury grade, and ligament quality [80].
- Clinical assessment of a thumb ulnar collateral ligament injury should be supplemented with radiographs, as underlying pathology, such as an enchondroma, may be a factor [61].
Investigations
Clinical Examination
- The MCP joint is generally examined by applying a radial force in extension and with approximately 30° of MCP joint flexion to relax the palmar plate, which is thought to isolate the UCL proper [18].
- Careful stress testing of the injured and uninjured side in both extension and flexion can often elucidate those with a significant tear of their UCL/RCL [35].
- The absence of a normal “endpoint” with radial stress is a key diagnostic finding signifying a complete ligament tear [35].
- For patients with significant guarding, a digital block may be necessary to carry out the stress test [35].
- Patients with a soft endpoint, incongruent joint, or Stener lesion require surgical intervention [35].
Imaging
- Ultrasonography (US) has evolved as a reliable adjunct to clinical examination in evaluation of the UCL of the thumb [1].
- Diagnostic ultrasound is a useful, noninvasive tool for assessing the extent of rupture of the ulnar collateral ligament [114].
- Ultrasound or MRI can be helpful to gather more information when it is difficult to ascertain if there is a Stener lesion based on palpation [35].
- Ultrasound and MRI findings do not have 100% accuracy and their findings should only be one component of the decision-making algorithm [35].
Treatment
Non-Operative Management
- A thumb spica cast or functional brace is recommended for 4 to 6 weeks for incomplete ruptures of the ulnar collateral ligament [47].
- Tears of the UCL of the thumb MCP joint without a Stener lesion are believed to heal with 4 to 6 weeks of immobilization [62].
- In patients having less than 30 degrees of laxity of the UCL, less than a 15-degree differential in laxity compared with the contralateral side, and a discrete endpoint to joint opening, nonoperative treatment consists of immobilization of the MP joint for 4 weeks in neutral alignment and slight flexion [104].
- Untreated ulnar collateral ligament (UCL) injury of the thumb metacarpophalangeal joint can lead to long-term pain and functional limitations [5].
Indications for Surgery
- Injuries that are unstable (usually 30° more opening with radial stress than the opposite uninjured side) are believed to have Stener lesions and are treated surgically [62].
- Complete tears require open repair with suture anchors or bone tunnels placed at the site of the avulsion, which most commonly is the proximal phalanx [42].
- The tear will not heal in the setting of a Stener lesion because of adductor aponeurosis interposition [42].
- Acute complete rupture of the ulnar collateral ligament should be surgically repaired [47].
- Ulnar collateral ligament retraction more than 3 mm and interposed soft tissue are reasonable guides to surgical intervention [47].
Operative Techniques
- Repair of the UCL of the thumb is one of the most common ligamentous repairs in the hand, with options including a pullout suture and button, bone anchors, or a combination of the two with local tissue augmentation or imbrication [63].
- A K-wire across the joint is often employed to allow proper ligament tensioning and to maintain joint stability postoperatively [63].
- The surgical approach involves a lazy S incision on the ulnar aspect of the thumb, with careful identification and retraction of the dorsal sensory branch of the radial nerve [28].
- The adductor aponeurosis is incised longitudinally to allow repair after the collateral ligament repair [28].
- Direct repair of the ligament should be obtained with the use of one or two bone anchors, preferably small metallic anchors with stout nonabsorbable suture material [35].
- Additional sutures are used to augment the repair to the volar plate distally and capsule dorsally [35].
- The capsule and adductor aponeurosis should be repaired in separate layers [35].
- For chronic tears with excessive laxity, the adductor insertion can be advanced to increase dynamic stability [35].
- Both pull-out suture and bone anchor techniques are safe and effective for treating thumb ulnar collateral ligament injuries [23].
- In a biomechanical model, thumb UCL repair with suture tape augmentation demonstrated greater maximum and clinical failure loads compared with nonaugmented repair at time 0 [41].
- Arthroscopic treatment of acute complete thumb metacarpophalangeal ulnar collateral ligament tears resulted in key pinch, tip pinch, grip strength, and range of motion equal to or greater than in the thumb on the unaffected side in most cases [46].
Chronic Injury and Reconstruction
- If the diagnosis is delayed for 1 month or longer, fibrosis makes ligament identification and repair more difficult, although repair can be done by dissecting out the ligament from within the fibrotic mass and reattaching it appropriately [47].
- The detached tendinous insertion of the adductor muscle can be advanced and reattached to furnish a dynamic reinforcement in delayed repairs [47].
- If the repair is done several months after the injury, a graft can be used [47].
- Chronic ruptures of the UCL can be challenging to reconstruct, but most often there is enough local tissue present to allow for direct repair with the existing native ligament [35].
- Graft reconstruction of the UCL can often be accomplished with either an autograft palmaris/plantaris tendon or with an allograft [35].
- Newer techniques for chronic reconstruction involve the use of 3.0-mm drills, the graft, fibertape, and interference screws [35].
- An X or Y type configuration is often needed to appropriately reconstruct the surface area of the ligament to prevent recurrent instability in chronic cases [35].
- If a Y construct is used for chronic reconstruction, the single limb is placed distally and the dual limb proximally to prevent iatrogenic injury [35].
- A K-wire is highly recommended in chronic reconstruction to allow adequate healing and provide sufficient stability to permit early mobilization of the adjacent IP and CMC joints [35].
- The pin is typically removed in the office at 6 weeks following chronic reconstruction [35].
- Nonbiological ligament reconstruction of the thumb ulnar collateral ligament generates short-term outcomes comparable with those of biological reconstruction, potentially allowing for expedited recovery and rehabilitation [45].
- Patient-reported outcomes, including pain and function, improved after thumb UCL reconstruction with a tendon autograft [36].
- Increased time from injury to treatment (beyond 6 weeks) may decrease the likelihood of direct repair [104].
- If no local tissue is available for chronic repair, UCL reconstruction is most commonly performed with a free tendon graft [104].
- The graft is tensioned at 45 degrees of flexion with some ulnar deviation placed on the MCP joint during reconstruction [104].
- A relative contraindication to ligament reconstruction is marked volar subluxation and/or supination of the MP joint [104].
- The only absolute contraindication to reconstruction is osteoarthritis of the MP joint, in which case arthrodesis is a very dependable option [104].
Outcomes and Rehabilitation
- Collegiate football athletes treated for thumb UCL injuries with suture anchor repair had quick return to play, reliable return to the same level of activity, and excellent long-term clinical outcomes [33].
- Complications are rare and most patients show preservation of motion, key pinch, and grip strength [25].
- Thumb MCP joint collateral ligament injuries have a good outcome with appropriate diagnosis and treatment [34].
- There was no significant change in pinch strength in patients with chronic UCL reconstructions, but significantly better results were achieved in grip strength, flexion, extension, ulnar and radial deviation [29].
- This is the first clinical application of an accelerated rehabilitation protocol in athletes following thumb MCP UCL repair [22].
- Strenuous activity is avoided for 3 months, with unrestricted return to sport usually at 2 to 3 months [42].
- Limit motion for the first 4 to 6 weeks depending on chronicity of the injury; more chronic injuries are immobilized longer [28].
- Guided therapy at 6 weeks in a removable splint is part of the postoperative protocol [28].
- A thumb spica cast is worn for 4 weeks postoperatively after reconstruction, followed by hand therapy and protection for an additional 5 weeks in a splint [104].
Complications
Non-Operative
Operative
- Long-term dangers and the cost effectiveness of the procedure using the Fiji Anchor® are not known yet [48].
- Thumb spica casting risks placing additional stress upon adjacent joints and causing adjacent injury [37].
Recovery
Outcomes and Function
- Recovery of pinch grip strength measured using two point palmar pinch is on average within 92 per cent of expected values after normalization for dominance [66].
Return to Sport and Work
- Players who underwent thumb UCL surgery played in a similar number of games per season and had similar career lengths in the NFL as controls [67].
Rehabilitation Protocols
Key Evidence
- [L4] Ultrasonography (US) has evolved as a reliable adjunct to clinical examination in evaluation of the UCL of the thumb. [1] (10.1148/rg.264055117)
- [L4] MRI evaluation reveals greater details enabling better understanding and management of ulnar collateral ligament injuries of the thumb MCP joint. [2] (10.1016/s0363-5023(09)60139-8)
- [L5] Valgus laxity greater than 30 degrees or more than 15 degrees more than in the noninjured thumb with the MCP joint in extension is an indication for operative management. [3] (10.5435/00124635-199707000-00006)
- [L1] Surgical management of thumb UCL injuries produces overall favorable results. [4] (10.5435/jaaosglobal-d-25-00082)
- [L5] Untreated ulnar collateral ligament (UCL) injury of the thumb metacarpophalangeal joint can lead to long-term pain and functional limitations. [5] (10.2106/jbjs.k.01024)
- [L3] The rate of surgery for acute thumb MP UCL injury varies based on patient characteristics and the individual treating surgeon. [6] (10.1177/1558944716681974)
- [L5] Sequential tearing of the thumb UCL leads to progressive instability of the MCP joint. [7] (10.1177/1558944719868518)
- [L5] A controlled active motion therapy protocol after suture anchor repair of a ruptured UCL of the thumb is safe from a biomechanical point of view. [8] (10.1016/j.jhsa.2004.04.017)
- [L4] Return-to-play rates after surgical treatment of thumb UCL injuries are high, with reassuring return to preinjury level of play with few complications. [9] (10.1016/j.jhsg.2023.03.005)
- [L4] Our 4-stage, treatment-oriented classification of thumb UCL injury is based on the degree of UCL displacement, with correlation with the likelihood of success with either immobilization or operative intervention. [10] (10.1016/j.jhsa.2014.08.033)
- [L3] Patients with both acute and chronic thumb UCL injuries have similarly acceptable functional outcomes, postoperative pain, and satisfaction. [11] (10.1016/j.jhsg.2022.02.008)
- [L3] The authors concluded that this is a safe and effective method for repair of complete tears of the ulnar collateral ligament of the thumb MP joint. [12] (10.1016/s0363-5023(97)80113-x)
- [L5] 75% of cases with complete rupture of the ulnar collateral ligament of the thumb will fail to heal with conservative treatment. [13] (10.1007/s11552-008-9145-8)
- [L4] Thumb ulnar collateral ligament injuries can be safely and effectively managed by football position demands. [14] (10.1177/2325967114s00092)
- [L5] No static ligament reconstruction restores the normal stability characteristics of the thumb UCL. [15] (10.1016/j.jhsa.2004.09.012)
- [L3] Players who underwent thumb UCL repair played in a similar number of games per season and had similar career lengths in the MLB as controls. [16] (10.1177/2325967117747268)
- [L4] Presence of a displaced fleck sign has implications for offering surgery to patients with thumb UCL injuries because of a high likelihood of a Stener lesion. [17] (10.1016/j.jhsa.2024.12.003)
- [L1] [18] (10.1177/17531934241274612)
- [L4] Treatment of a thumb UCL complete rupture (Grade III) using a custom-made hinged splint shows promise in the conservative management of compliant patients. [19] (10.1016/j.jht.2009.10.001)
- [L4] [20] (10.1016/j.injury.2026.113711)
- [L4] It could be an alternative treatment technique for thumb UCL avulsion fractures. [21] (10.1016/j.otsr.2019.01.008)
- [L4] This is the first clinical application of an accelerated rehabilitation protocol in athletes following thumb MCP UCL repair. [22] (10.1016/j.jht.2022.07.007)
- [L3] Both repair methods are safe and effective for treating thumb ulnar collateral ligament injuries. [23] (10.1097/prs.0b013e3181882163)
- [L2] Patient-reported outcomes improve significantly at three and 12 months after open surgical repair of the thumb UCL compared to baseline. [24] (10.1016/j.jhsa.2023.05.003)
- [L5] Complications are rare and most patients show preservation of motion, key pinch, and grip strength. [25] (10.1016/j.ocl.2014.11.007)
- [L4] Thumb UCL repair with suture tape augmentation demonstrates short-term outcomes comparable to what has been reported for other methods of repair. [26] (10.1142/s2424835520500046)
- [L3] There was no significant change in pinch strength in patients with chronic UCL reconstructions, but significantly better results were achieved in grip strength, flexion, extension, ulnar and radial deviation. [29] (10.1016/j.hansur.2020.03.002)
- [L5] [30] (10.1053/jhsu.1999.0283)
- [L5] This suggests that physical examination is required to determine stability with injuries to the ulnar structures of the thumb metacarpophalangeal joint. [31] (10.1016/s0363-5023(98)80158-5)
- [L4] Comparison with the uninjured contralateral thumb is unreliable in many individuals due to significant variation between right and left thumbs. [32] (10.1177/1753193408100957)
- [L4] Collegiate football athletes treated for thumb UCL injuries with suture anchor repair had quick return to play, reliable return to the same level of activity, and excellent long-term clinical outcomes. [33] (10.1016/j.jhsa.2014.06.132)
- [L5] Thumb MCP joint collateral ligament injuries have a good outcome with appropriate diagnosis and treatment. [34] (10.1016/j.csm.2014.09.004)
- [L4] Patient-reported outcomes, including pain and function, improved after thumb UCL reconstruction with a tendon autograft. [36] (10.1016/j.jhsa.2024.05.005)
- [L4] Thumb spica casting protects the surgically repaired thumb UCL and allows for earlier return to play, but risks placing additional stress upon adjacent joints and causing adjacent injury. [37] (10.1177/1558944718788644)
- [L5] [39] (10.1177/17531934241311826)
- [L5] Single- and double-bundle UCL reconstructions of the thumb MCP joint have comparable biomechanical properties in regard to joint congruity under valgus load. [40] (10.1177/1558944717744338)
- [L5] In this model, thumb UCL repair with suture tape augmentation demonstrated greater maximum and clinical failure loads compared with nonaugmented repair at time 0, that is, without any biological healing. [41] (10.1016/j.jhsa.2018.02.002)
- [L4] Nonbiological ligament reconstruction of the thumb ulnar collateral ligament generates short-term outcomes comparable with those of BLR, potentially allowing for expedited recovery and rehabilitation. [45] (10.1016/j.jhsa.2024.01.008)
- [L4] In most cases, key pinch, tip pinch, grip strength, and range of motion were equal to or greater than in the thumb on the unaffected side. [46] (10.1016/s0363-5023(05)80156-x)
- [Paper] The surgical treatment of an ulnar collateral ligament lesion of the thumb using the Fiji Anchor® can lead to an excellent clinical outcome with a minor complication rate; however, long-term dangers and the cost effectiveness of the procedure are not known yet. [48] (10.1007/s00402-020-03625-x)
- [L4] [51] (10.1177/1753193420932496)
- [L2] [58] (10.1054/jhsb.1999.0283)
- [L5] The reconstruction tunnel positioning of triangular configuration with apex proximal stabilizes the thumb MCP joint while maintaining flexion/extension range of motion. [60] (10.1016/j.jhsa.2005.05.004)
- [L5] This case highlights that clinical assessment of a thumb ulnar collateral ligament injury should be supplemented with radiographs, as underlying pathology, such as an enchondroma, may be a factor. [61] (10.1177/17531934251315313)
- [L4] Recovery of pinch grip strength measured using two point palmar pinch is on average within 92 per cent of expected values after normalization for dominance. [66] (10.1016/0020-1383(94)90179-1)
- [L4] Players who underwent thumb UCL surgery played in a similar number of games per season and had similar career lengths in the NFL as controls. [67] (10.1177/1558944718760001)
- [L5] [80] (10.1016/j.eats.2025.103957)
- [L5] Skier's thumb is an often-encountered injury and can lead to chronic pain and instability when diagnosed incorrectly. [83] (10.1186/1865-1380-6-31)
- [L5] Although both ST and SA constructs recapitulate native joint stiffness, repair with ST demonstrated the greatest biomechanical strength in stiffness and load-to-failure. [90] (10.1016/j.jhsa.2021.09.028)
- [L5] Biomechanically, there are no treatments of repair or reconstruction using native tissues that provide equivalent strength to the preinjured ligament. [105] (10.5435/jaaos-d-22-00112)
- [L5] In round joints, only the non-anatomic Glickel procedure restores normal ROM and stability, while in flat joints, the Glickel procedure and a modified Fairhurst configuration with origins dorsal in the metacarpal head restore ROM and stability. [111] (10.1177/17531934231164260)
- [L5] [112] (10.1142/s0218810417500411)
- [L5] Diagnostic ultrasound is a useful, noninvasive tool for assessing the extent of rupture of the ulnar collateral ligament. [114] (10.1016/0363-5023(94)90025-6)
References
[1] US Diagnosis of UCL Tears of the Thumb and Stener Lesions: Technique, Pattern-based Approach, and Differential Diagnosis. RadioGraphics. 2006. DOI: 10.1148/rg.264055117
[2] MRI Classification of Ulnar Collateral Ligament Injuries of the Thumb MCP Joint. The Journal of Hand Surgery. 2009. DOI: 10.1016/s0363-5023(09)60139-8
[3] Injuries to the Ulnar Collateral Ligament of the Thumb Metacarpophalangeal Joint. Journal of the American Academy of Orthopaedic Surgeons. 1997. DOI: 10.5435/00124635-199707000-00006
[4] Surgical Management of Thumb Ulnar Collateral Ligament Injuries: A Systematic Review and Meta-analysis of 614 Patients With a Minimum 1 Year Follow-up. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-25-00082
[5] Management of Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries. Journal of Bone and Joint Surgery. 2012. DOI: 10.2106/jbjs.k.01024
[6] Variation in the Rate of Surgery for Ulnar Collateral Ligament Injury of the Metacarpophalangeal Joint of the Thumb. HAND. 2016. DOI: 10.1177/1558944716681974
[7] Biomechanical Analysis of Thumb Ulnar Collateral Ligament Tear Kinematics. HAND. 2019. DOI: 10.1177/1558944719868518
[8] A biomechanical modeling of injury, repair, and rehabilitation of ulnar collateral ligament injuries of the thumb. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.017
[9] Return to Play After Thumb Ulnar Collateral Ligament Injuries Managed Surgically in Athletes—A Systematic Review. Journal of Hand Surgery Global Online. 2023. DOI: 10.1016/j.jhsg.2023.03.005
[10] Gamekeeper’s Thumb—A Treatment-Oriented Magnetic Resonance Imaging Classification. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.08.033
[11] A Comparison of Acute Versus Chronic Thumb Ulnar Collateral Ligament Surgery Using Primary Suture Anchor Repair and Local Soft Tissue Advancement. Journal of Hand Surgery Global Online. 2022. DOI: 10.1016/j.jhsg.2022.02.008
[12] Repair of acute ulnar collateral ligament injuries of the thumb metacarpophalangeal joint with an intraosseous suture anchor. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80113-x
[13] Injury to the Ulnar Collateral Ligament of the Thumb. HAND. 2008. DOI: 10.1007/s11552-008-9145-8
[14] Return to Play and Long-Term Clinical Outcomes after Suture Anchor Repair of Thumb Ulnar Collateral Ligament Injuries in Collegiate Football Athletes. Orthopaedic Journal of Sports Medicine. 2014. DOI: 10.1177/2325967114s00092
[15] Reconstruction of the ulnar collateral ligament of the thumb metacarpophalangeal joint: A cadaver study. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2004.09.012
[16] Performance and Return to Sport After Thumb Ulnar Collateral Ligament Repair in Major League Baseball Players. Orthopaedic Journal of Sports Medicine. 2018. DOI: 10.1177/2325967117747268
[17] The Displaced Fleck Sign: Description of a Radiographic Finding Consistent with Grade III Thumb Ulnar Collateral Ligament Tears with Stener Lesions. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.12.003
[18] Guideline on managing thumb ulnar collateral ligament injuries: the British Society of Surgery for the Hand Evidence for Surgical Treatment (BEST) findings and recommendations. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241274612
[19] Treatment of Grade III Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries with Early Controlled Motion Using a Hinged Splint. Journal of Hand Therapy. 2010. DOI: 10.1016/j.jht.2009.10.001
[20] Return to Duty After Suture Anchor Repair of Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries in Active Duty Soldiers. Injury. 2026. DOI: 10.1016/j.injury.2026.113711
[21] Mini hook plate fixation for thumb ulnar collateral ligament avulsion fracture: A technical report. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2019.01.008
[22] Accelerated rehabilitation following thumb ulnar collateral ligament repair with suture tape augmentation: A case series of professional basketball players. Journal of Hand Therapy. 2023. DOI: 10.1016/j.jht.2022.07.007
[23] Repair of Acute Ulnar Collateral Ligament Injuries of the Thumb Metacarpophalangeal Joint: A Retrospective Comparison of Pull-Out Sutures and Bone Anchor Techniques. Plastic and Reconstructive Surgery. 2008. DOI: 10.1097/prs.0b013e3181882163
[24] Patient-Reported Outcomes and Function After Surgical Repair of the Ulnar Collateral Ligament of the Thumb. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.05.003
[25] Ulnar Collateral Ligament Injuries of the Thumb. Orthopedic Clinics of North America. 2015. DOI: 10.1016/j.ocl.2014.11.007
[26] Thumb Ulnar Collateral Ligament Repair with Suture Tape Augmentation. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520500046
[28] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Open Repair of the Ulnar or Radial Collateral Ligament of the MCP Joint of the Thumb: Preoperative Planning Checklist.
[29] The effects of rehabilitation on the outcomes of surgically treated acute and chronic thumb metacarpophalangeal ulnar collateral ligament ruptures. Hand Surgery and Rehabilitation. 2020. DOI: 10.1016/j.hansur.2020.03.002
[30] The effect of thumb metacarpophalangeal ulnar collateral ligament attachment site on joint range of motion: An in vitro study. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0283
[31] The stener lesion revisited: A case report. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80158-5
[32] Clinical Testing of Ulnar Collateral Ligament Injuries of the Thumb. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193408100957
[33] Return to Football and Long-Term Clinical Outcomes After Thumb Ulnar Collateral Ligament Suture Anchor Repair in Collegiate Athletes. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.132
[34] Thumb Ulnar Collateral and Radial Collateral Ligament Injuries. Clinics in Sports Medicine. 2015. DOI: 10.1016/j.csm.2014.09.004
[35] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Thumb MCP Ligament Repair.
[36] Patient-Reported and Clinical Outcomes After Tendon Autograft Reconstruction of the Thumb Ulnar Collateral Ligament. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.05.005
[37] Early Return to Play With Thumb Spica Gauntlet Casting for Ulnar Collateral Ligament Injuries Complicated by Adjacent Joint Dislocations in Collegiate Football Linemen. HAND. 2018. DOI: 10.1177/1558944718788644
[39] Re. Dean B, Rodrigues J, Riley N, Rabey N, Donnison E, Challen K, Bradford S; BSSH BEST UCL Guideline Development Group. Guideline on managing thumb ulnar collateral ligament injuries: the British Society of Surgery for the Hand Evidence for Surgical Treatment (BEST) findings and recommendations. J Hand Surg Eur. 2024, 49: 1195–201. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934241311826
[40] Single-Bundle vs Double-Bundle (Anatomical) Reconstruction of the Thumb Ulnar Collateral Ligament: Biomechanical Study. HAND. 2017. DOI: 10.1177/1558944717744338
[41] Suture Tape Augmentation of the Thumb Ulnar Collateral Ligament Repair: A Biomechanical Study. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.002
[42] Orthopaedic Knowledge Update Sports Medicine 6. Hand and Wrist Injuries > Hand Injuries > Skier’s Thumb.
[44] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Acute Ulnar Collateral Ligament Injuries (Skier’s Thumb).
[45] Biological Versus Nonbiological Reconstruction of the Ulnar Collateral Ligament of the Thumb Metacarpophalangeal Joint: A Retrospective Study. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.01.008
[46] Arthroscopic treatment of acute complete thumb metacarpophalangeal ulnar collateral ligament tears. The Journal of Hand Surgery. 1995. DOI: 10.1016/s0363-5023(05)80156-x
[47] Campbell S Operative Orthopaedics 4 Volume Set. FRACTURES, DISLOCATIONS, AND LIGAMENTOUS INJURIES OF THE HAND AND WRIST > THUMB METACARPOPHALANGEAL JOINT ULNAR COLLATERAL LIGAMENT RUPTURE.
[48] Clinical results of the BoneWelding®Fiji® anchor for the treatment of Stener lesions of the thumb. Archives of Orthopaedic and Trauma Surgery. 2020. DOI: 10.1007/s00402-020-03625-x
[51] The value of magnetic resonance imaging and ultrasound in diagnosing displaced rupture of the thumb ulnar collateral ligament. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420932496
[52] Exam Of The Hand Wrist 2Ed. Movements of the thumb.
[58] The Use of Ultrasound in the Diagnosis of Injuries of the Ulnar Collateral Ligament of the Thumb. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.1999.0283
[60] Thumb Metacarpophalangeal Ulnar Collateral Ligament Injuries: A Biomechanical Simulation Study of Four Static Reconstructions. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.05.004
[61] Clinical thumb ulnar collateral ligament injury owing to a pathological fracture through an enchondroma of the proximal phalanx. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251315313
[62] Aaos Comprehensive Orthopaedic Review 3. Hand Trauma > VI. Thumb Metacarpophalangeal Ligament Injuries and Dislocations.
[63] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Open Repair of the Ulnar or Radial Collateral Ligament of the MCP Joint of the Thumb.
[66] Gamekeeper's thumb: a quantitative evaluation of acute surgical repair. Injury. 1994. DOI: 10.1016/0020-1383(94)90179-1
[67] Performance and Return to Sport After Thumb Ulnar Collateral Ligament Surgery in National Football League Players. HAND. 2018. DOI: 10.1177/1558944718760001
[80] Thumb Ulnar Collateral Ligament Repair Using Suture Anchors and Suture Tape Augmentation. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2025.103957
[83] Rupture of the ulnar collateral ligament of the thumb – a review. International Journal of Emergency Medicine. 2013. DOI: 10.1186/1865-1380-6-31
[90] Biomechanical Comparison of 3 Thumb Ulnar Collateral Ligament Repair Methods. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2021.09.028
[94] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Types of Operations > Technique of open repair of the thumb metacarpophalangeal ulnar collateral ligament..
[100] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Chronic Ulnar Collateral Ligament Injuries (Gamekeeper’s Thumb) > Preoperative Evaluation.
[104] Green S Operative Hand Surgery. Dislocations and Ligament Injuries of the Digits > Chronic Ulnar Collateral Ligament Injuries (Gamekeeper’s Thumb) > Types of Operations.
[105] Thumb Metacarpophalangeal Joint Ulnar Collateral Ligament Injuries: Management and Biomechanical Evaluation. Journal of the American Academy of Orthopaedic Surgeons. 2023. DOI: 10.5435/jaaos-d-22-00112
[111] Thumb metacarpophalangeal joint morphology and reconstruction of the ruptured ulnar collateral ligament. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231164260
[112] Can Physical Examination Create a Stener Lesion?. The Journal of Hand Surgery (Asian-Pacific Volume). 2017. DOI: 10.1142/s0218810417500411
[114] Ultrasonographic detection of thumb ulnar collateral ligament injuries: A cadaveric study. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90025-6