Patients › Shoulder
ਸਬਐਕਰੋਮੀਅਲ ਇੰਪਿੰਜਮੈਂਟ ਅਤੇ ਬਰਸਾਈਟਿਸ
Subacromial impingement — causes of shoulder pain with overhead activity, diagnosis, and treatment options.
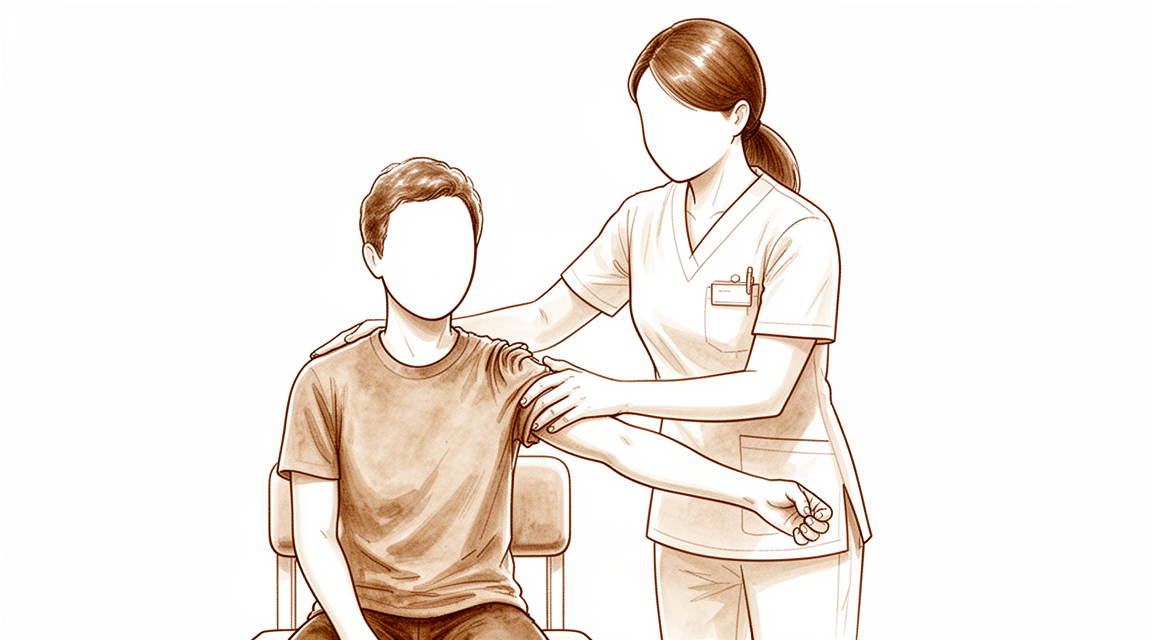
ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ
ਸਬਐਕਰੋਮੀਅਲ ਇੰਪਿੰਜਮੈਂਟ (subacromial impingement, ਮੋਢੇ ਦੀ ਹੱਡੀ ਦੀ ਛੱਤ ਹੇਠਾਂ ਟੈਂਡਨਾਂ ਦਾ ਦੱਬੇ ਜਾਣਾ) ਦਾ ਮੁੱਖ ਲੱਛਣ ਮੋਢੇ ਦੇ ਅਗਲੇ ਪਾਸੇ ਦਰਦ ਹੈ। ਇਹ ਅਕਸਰ ਉਦੋਂ ਹੁੰਦਾ ਹੈ ਜਦੋਂ ਤੁਸੀਂ ਬਾਂਹ ਚੁੱਕਦੇ ਹੋ, ਸਿਰ ਤੋਂ ਉੱਪਰ ਹੱਥ ਵਧਾਉਂਦੇ ਹੋ, ਜਾਂ ਬਾਂਹ ਨੂੰ ਸਰੀਰ ਤੋਂ ਦੂਰ ਰੱਖ ਕੇ ਵਰਤਦੇ ਹੋ। ਬਹੁਤ ਸਾਰੇ ਲੋਕ ਮੋਢੇ ਅਤੇ ਬਾਂਹ ਵਿੱਚ ਕਮਜ਼ੋਰੀ ਵੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹਨ।
ਦਰਦ ਅਕਸਰ ਇੱਕ ਖ਼ਾਸ ਪੈਟਰਨ ਵਿੱਚ ਹੁੰਦਾ ਹੈ। ਇਹ "ਪੇਨਫੁੱਲ ਆਰਕ" (painful arc, ਦਰਦ ਵਾਲਾ ਘੇਰਾ) ਦੌਰਾਨ ਭੜਕ ਸਕਦਾ ਹੈ, ਯਾਨੀ ਹਰਕਤ ਦਾ ਉਹ ਹਿੱਸਾ ਜਿਸ ਵਿੱਚ ਬਾਂਹ ਚੁੱਕਣ ਨਾਲ ਦਰਦ ਹੁੰਦਾ ਹੈ, ਪਾਸੇ ਵੱਲ ਬਾਹਰ ਜਾਂ ਤੁਹਾਡੇ ਸਾਹਮਣੇ ਲਗਭਗ 40 ਅਤੇ 120 ਡਿਗਰੀ ਦੇ ਵਿਚਕਾਰ। ਇਸ ਹਿੱਸੇ ਤੋਂ ਬਾਹਰ ਹਰਕਤ ਅਕਸਰ ਸੌਖੀ ਹੁੰਦੀ ਹੈ। ਰਾਤ ਨੂੰ ਦਰਦ ਆਮ ਹੈ, ਅਤੇ ਸਰਗਰਮੀ ਤੋਂ ਬਾਅਦ ਜਾਂ ਸਵੇਰੇ ਜਾਗਣ ਵੇਲੇ ਮੋਢਾ ਦੁਖ ਸਕਦਾ ਹੈ। ਜੋ ਕੰਮ ਔਖੇ ਹੋ ਜਾਂਦੇ ਹਨ ਉਨ੍ਹਾਂ ਵਿੱਚ ਧੋਤੇ ਕੱਪੜੇ ਸੁਕਾਉਣ ਲਈ ਟੰਗਣਾ, ਉੱਚੇ ਸ਼ੈਲਫ਼ ਤੱਕ ਹੱਥ ਪਹੁੰਚਾਉਣਾ, ਜਾਂ ਕੇਤਲੀ ਚੁੱਕਣਾ ਸ਼ਾਮਲ ਹਨ।
ਤੁਹਾਡੇ ਮੋਢੇ ਦੀ ਹਿੱਲਣ ਦੀ ਹੱਦ ਆਮ ਤੌਰ ਤੇ ਆਮ ਵਾਂਗ ਰਹਿੰਦੀ ਹੈ, ਯਾਨੀ ਤੁਸੀਂ ਅਜੇ ਵੀ ਮੋਢੇ ਨੂੰ ਉਸਦੇ ਪੂਰੇ ਘੇਰੇ ਵਿੱਚ ਹਿਲਾ ਸਕਦੇ ਹੋ, ਭਾਵੇਂ ਉਸ ਘੇਰੇ ਦੇ ਕੁਝ ਹਿੱਸਿਆਂ ਵਿੱਚ ਦਰਦ ਹੁੰਦਾ ਹੈ। ਮੋਢੇ ਦੇ ਅਗਲੇ ਪਾਸੇ ਛੂਹਣ ਨਾਲ ਦੁਖਣਾ ਆਮ ਗੱਲ ਹੈ।
ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਜਗਾਉਂਦੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਬਾਂਹ ਵਰਤਣ ਤੋਂ ਰੋਕਦੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਦੀ ਜਾਂਚ ਲਈ ਕਹੋ।
ਮੋਢੇ ਦੀਆਂ ਹੋਰ ਸਮੱਸਿਆਵਾਂ ਵੀ ਇਸ ਵਰਗੀਆਂ ਮਹਿਸੂਸ ਹੋ ਸਕਦੀਆਂ ਹਨ, ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਫ੍ਰੋਜ਼ਨ ਸ਼ੋਲਡਰ (ਜੰਮਿਆ ਹੋਇਆ ਮੋਢਾ), ਰੋਟੇਟਰ ਕਫ਼ ਦਾ ਪੂਰੀ ਮੋਟਾਈ ਦਾ ਪਾਟਣਾ (ਟੈਂਡਨ ਦਾ ਆਰ-ਪਾਰ ਪਾਟ ਜਾਣਾ; ਟੈਂਡਨ, tendon, ਪੱਠੇ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀ ਮਜ਼ਬੂਤ ਤੰਦ), ਅਤੇ ਅਸਥਿਰਤਾ (instability, ਮੋਢਾ ਜੋ ਖਿਸਕਦਾ ਹੈ ਜਾਂ ਢਿੱਲਾ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ) ਸ਼ਾਮਲ ਹਨ। ਧਿਆਨ ਨਾਲ ਕੀਤੀ ਜਾਂਚ ਇਹ ਤੈਅ ਕਰਦੀ ਹੈ ਕਿ ਤੁਹਾਨੂੰ ਇਨ੍ਹਾਂ ਵਿੱਚੋਂ ਕਿਹੜੀ ਸਮੱਸਿਆ ਹੈ।
ਅਸਲ ਵਿੱਚ ਕੀ ਹੋ ਰਿਹਾ ਹੈ
ਤੁਹਾਡਾ ਮੋਢਾ ਹੱਡੀ ਦੀ ਇੱਕ ਮਿਹਰਾਬ (arch) ਦੇ ਹੇਠਾਂ ਹੁੰਦਾ ਹੈ। ਇਹ ਮਿਹਰਾਬ ਐਕਰੋਮੀਅਨ (acromion, ਮੋਢੇ ਦੇ ਉੱਪਰ ਹੱਡੀ ਦੀ ਛੱਤ) ਤੋਂ ਬਣਦੀ ਹੈ, ਜੋ ਮੋਢੇ ਦੇ ਉੱਪਰ ਹੱਡੀ ਦਾ ਇੱਕ ਛੱਜਾ ਹੈ ਅਤੇ ਇੱਕ ਲਿਗਾਮੈਂਟ (ligament, ਹੱਡੀ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲਾ ਬੰਧਨ) ਰਾਹੀਂ ਸਾਹਮਣੇ ਵਾਲੀ ਇੱਕ ਹੋਰ ਹੱਡੀ ਨਾਲ ਜੁੜਿਆ ਹੁੰਦਾ ਹੈ। ਉਸ ਮਿਹਰਾਬ ਦੇ ਹੇਠਲੀ ਖ਼ਾਲੀ ਥਾਂ ਵਿੱਚੋਂ ਤੁਹਾਡੇ ਰੋਟੇਟਰ ਕਫ਼ ਦੇ ਟੈਂਡਨ ਖਿਸਕਦੇ ਹੋਏ ਲੰਘਦੇ ਹਨ, ਯਾਨੀ ਚਾਰ ਟੈਂਡਨਾਂ ਦਾ ਉਹ ਸਮੂਹ ਜੋ ਹਿੱਲਣ ਵੇਲੇ ਜੋੜ ਦੀ ਗੇਂਦ ਨੂੰ ਵਿਚਕਾਰ ਟਿਕਾ ਕੇ ਰੱਖਦਾ ਹੈ, ਅਤੇ ਤਰਲ ਨਾਲ ਭਰੀ ਇੱਕ ਛੋਟੀ ਗੱਦੀ ਵੀ, ਜਿਸਨੂੰ ਸਬਐਕਰੋਮੀਅਲ ਬਰਸਾ (subacromial bursa) ਕਹਿੰਦੇ ਹਨ। ਬਰਸਾ ਕੁਝ ਹੱਦ ਤੱਕ ਗੈਸਕਟ (ਵਾਸ਼ਰ) ਵਾਂਗ ਕੰਮ ਕਰਦਾ ਹੈ, ਜਿਸ ਨਾਲ ਟੈਂਡਨ ਹੱਡੀ ਨਾਲ ਰਗੜ ਖਾਣ ਦੀ ਬਜਾਏ ਉਸਦੇ ਹੇਠਾਂ ਸੁਚਾਰੂ ਢੰਗ ਨਾਲ ਖਿਸਕਦੇ ਹਨ।
ਇਸ ਹਾਲਤ ਵਿੱਚ, ਉਸ ਗੱਦੀ ਵਿੱਚ ਸੋਜਸ਼ (inflammation) ਆ ਜਾਂਦੀ ਹੈ ਅਤੇ ਇਹ ਸੁੱਜ ਜਾਂਦੀ ਹੈ, ਅਤੇ ਟੈਂਡਨ ਵੀ ਮੋਟੇ ਹੋ ਸਕਦੇ ਹਨ। ਮੋਟਾ ਟੈਂਡਨ ਮਿਹਰਾਬ ਦੇ ਹੇਠਾਂ ਦੀ ਤੰਗ ਥਾਂ ਦਾ ਵੱਧ ਹਿੱਸਾ ਘੇਰ ਲੈਂਦਾ ਹੈ, ਇਸ ਲਈ ਖਿਸਕਣ ਲਈ ਘੱਟ ਥਾਂ ਬਚਦੀ ਹੈ। ਇਹ ਉਸ ਨਾਲ ਮੇਲ ਖਾਂਦਾ ਹੈ ਜੋ ਤੁਸੀਂ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ: ਬਾਂਹ ਚੁੱਕਣ ਵੇਲੇ ਮੋਢੇ ਦੇ ਅਗਲੇ ਪਾਸੇ ਦਰਦ, ਜੋ ਪਹਿਲਾਂ ਦੱਸੇ ਪੇਨਫੁੱਲ ਆਰਕ ਵਿੱਚ ਸਭ ਤੋਂ ਵੱਧ ਹੁੰਦਾ ਹੈ, ਕਿਉਂਕਿ ਠੀਕ ਉਸੇ ਸਮੇਂ ਮਿਹਰਾਬ ਦੇ ਹੇਠਾਂ ਦੀ ਥਾਂ ਸਭ ਤੋਂ ਤੰਗ ਹੁੰਦੀ ਹੈ। ਇਹ ਥਾਂ ਉਦੋਂ ਸਭ ਤੋਂ ਭੀੜੀ ਹੁੰਦੀ ਹੈ ਜਦੋਂ ਤੁਹਾਡੀ ਬਾਂਹ ਲਗਭਗ 90 ਡਿਗਰੀ ਤੱਕ, ਮੋਟੇ ਤੌਰ ਤੇ ਮੋਢੇ ਦੇ ਬਰਾਬਰ, ਚੁੱਕੀ ਹੋਈ ਹੋਵੇ।
ਇਹ ਜਾਣਨਾ ਲਾਹੇਵੰਦ ਹੈ ਕਿ ਮਿਹਰਾਬ ਅਤੇ ਟੈਂਡਨਾਂ ਵਿਚਕਾਰ ਕੁਝ ਰਗੜ ਹਰ ਮੋਢੇ ਵਿੱਚ ਹੁੰਦੀ ਹੈ, ਤੰਦਰੁਸਤ ਮੋਢਿਆਂ ਵਿੱਚ ਵੀ। ਕੁਝ ਖ਼ਾਸ ਹਰਕਤਾਂ ਨਾਲ, ਜਿਵੇਂ ਪਾਸੇ ਵੱਲ ਜਾਂ ਪਿੱਛੇ ਵੱਲ ਹੱਥ ਵਧਾਉਣਾ, ਦਬਾਅ ਬਸ ਵਧ ਜਾਂਦਾ ਹੈ। ਇਸ ਬਾਰੇ ਵੀ ਬਹਿਸ ਹੈ ਕਿ ਕੀ ਟੈਂਡਨ ਦੇ ਉੱਪਰਲੀ ਹੱਡੀ ਦੀ ਸ਼ਕਲ ਸੱਚਮੁੱਚ ਇਸਦਾ ਕਾਰਨ ਹੈ, ਕਿਉਂਕਿ ਹੱਡੀ ਦੀ ਸ਼ਕਲ ਅਤੇ ਟੈਂਡਨ ਦੀਆਂ ਸਮੱਸਿਆਵਾਂ ਵਿਚਕਾਰ ਸੰਬੰਧ ਅਜੇ ਤੈਅ ਨਹੀਂ ਹੋਇਆ। ਬਹੁਤ ਸਾਰੇ ਮਾਹਰ ਹੁਣ ਇਸ ਹਾਲਤ ਨੂੰ ਸਬਐਕਰੋਮੀਅਲ ਪੇਨ ਸਿੰਡਰੋਮ (subacromial pain syndrome, ਮੋਢੇ ਦੀ ਹੱਡੀ ਦੀ ਛੱਤ ਹੇਠਾਂ ਦਾ ਦਰਦ) ਕਹਿੰਦੇ ਹਨ, ਜੋ ਇਹ ਦੱਸਦਾ ਹੈ ਕਿ ਦਰਦ ਕਿੱਥੇ ਹੁੰਦਾ ਹੈ, ਬਿਨਾਂ ਇਹ ਦਾਅਵਾ ਕੀਤੇ ਕਿ ਇਹ ਕਿਉਂ ਹੁੰਦਾ ਹੈ।
ਇਸ ਕਰਕੇ, ਇਲਾਜ ਆਮ ਤੌਰ ਤੇ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਿਨਾਂ, ਕਸਰਤ ਅਤੇ ਹੋਰ ਗ਼ੈਰ-ਸਰਜੀਕਲ ਉਪਾਵਾਂ ਨਾਲ ਸ਼ੁਰੂ ਹੁੰਦਾ ਹੈ। ਮਿਹਰਾਬ ਦੇ ਹੇਠਲੇ ਪਾਸੇ ਤੋਂ ਹੱਡੀ ਘਸਾਉਣ ਵਾਲੀ ਸਰਜਰੀ, ਜਿਸਨੂੰ ਸਬਐਕਰੋਮੀਅਲ ਡੀਕੰਪ੍ਰੈਸ਼ਨ (subacromial decompression, ਹੱਡੀ ਦੀ ਛੱਤ ਹੇਠਾਂ ਥਾਂ ਖੋਲ੍ਹਣਾ) ਕਹਿੰਦੇ ਹਨ, ਕੁਝ ਚੁਣੇ ਹੋਏ ਮਰੀਜ਼ਾਂ ਦੇ ਛੋਟੇ ਸਮੂਹ ਨੂੰ ਪੇਸ਼ ਕੀਤੀ ਜਾ ਸਕਦੀ ਹੈ ਜਿਨ੍ਹਾਂ ਦਾ ਦਰਦ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋਇਆ। ਸਾਫ਼ ਦੱਸਣਾ ਬਣਦਾ ਹੈ ਕਿ ਜਿਨ੍ਹਾਂ ਟ੍ਰਾਇਲਾਂ ਨੇ ਇਸ ਓਪਰੇਸ਼ਨ ਦੀ ਤੁਲਨਾ ਸ਼ੈਮ (sham, ਦਿਖਾਵੇ ਦਾ ਓਪਰੇਸ਼ਨ) ਪ੍ਰਕਿਰਿਆ ਨਾਲ ਕੀਤੀ, ਜਿਸ ਵਿੱਚ ਸਰਜਨ ਮੋਢੇ ਦੇ ਅੰਦਰ ਦੇਖਦਾ ਹੈ ਪਰ ਕੋਈ ਹੱਡੀ ਨਹੀਂ ਕੱਢਦਾ, ਉਨ੍ਹਾਂ ਨੂੰ ਖ਼ੁਦ ਹੱਡੀ ਕੱਢਣ ਤੋਂ ਬਹੁਤ ਥੋੜ੍ਹਾ ਵਾਧੂ ਫ਼ਾਇਦਾ ਮਿਲਿਆ।
ਅਸੀਂ ਇਸ ਬਾਰੇ ਕੀ ਕਰ ਸਕਦੇ ਹਾਂ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ, ਤੁਹਾਡੀ ਹਾਲਤ ਦੇ ਅਨੁਕੂਲ ਸਭ ਤੋਂ ਘੱਟ ਚੀਰ-ਫਾੜ ਵਾਲੇ ਇਲਾਜਾਂ ਤੋਂ ਸ਼ੁਰੂਆਤ ਕਰਦੇ ਹਨ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ ਤੇ ਉਨ੍ਹਾਂ ਦਾ ਜੀਪੀ ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਨੂੰ ਮਿਲਣ ਦੀ ਸਲਾਹ ਦਿੱਤੀ ਹੈ, ਤਾਂ ਵੀ ਮੈਡੀਕੇਅਰ (Medicare) ਰਿਬੇਟ ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਪਵੇਗੀ। ਤੁਹਾਡੀ ਪਹਿਲੀ ਮੁਲਾਕਾਤ ਵੇਲੇ ਅਸੀਂ ਤੁਹਾਡੀ ਤਕਲੀਫ਼ ਦਾ ਪੂਰਾ ਵੇਰਵਾ ਲੈਂਦੇ ਹਾਂ, ਤੁਹਾਡੇ ਮੋਢੇ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਜਿੱਥੇ ਲੋੜ ਹੋਵੇ ਉੱਥੇ ਇਮੇਜਿੰਗ (ਐਕਸ-ਰੇ ਜਾਂ ਸਕੈਨ) ਦਾ ਪ੍ਰਬੰਧ ਕਰਦੇ ਹਾਂ। ਇਸ ਵਰਗੀ ਲੰਮੇ ਸਮੇਂ ਤੋਂ ਚੱਲ ਰਹੀ ਸਮੱਸਿਆ ਲਈ, ਅਸੀਂ ਆਮ ਤੌਰ ਤੇ ਪਹਿਲਾਂ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲਾ ਇਲਾਜ ਅਜ਼ਮਾਉਂਦੇ ਹਾਂ ਅਤੇ ਸਰਜਰੀ ਬਾਰੇ ਸਿਰਫ਼ ਉਦੋਂ ਸੋਚਦੇ ਹਾਂ ਜਦੋਂ ਉਸ ਨਾਲ ਕਾਫ਼ੀ ਸੁਧਾਰ ਨਾ ਹੋਇਆ ਹੋਵੇ।
ਪਹਿਲਾ ਕਦਮ ਬਾਂਹ ਵਰਤਣ ਦਾ ਢੰਗ ਬਦਲਣਾ ਅਤੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨਾਲ ਮੋਢੇ ਦੀ ਤਾਕਤ ਬਣਾਉਣਾ ਹੈ। ਮਕਸਦ ਚਿੜੇ ਹੋਏ (irritated) ਟਿਸ਼ੂ ਨੂੰ ਸ਼ਾਂਤ ਕਰਨਾ ਅਤੇ ਆਰਾਮਦਾਇਕ ਹਰਕਤ ਵਾਪਸ ਲਿਆਉਣਾ ਹੈ, ਦਰਦ ਸਹਿ ਕੇ ਜ਼ੋਰ ਲਾਉਣਾ ਨਹੀਂ। ਇਸ ਬਾਰੇ ਰਾਇ ਬਣਾਉਣ ਤੋਂ ਪਹਿਲਾਂ ਇਸਨੂੰ ਕਈ ਮਹੀਨਿਆਂ ਤੱਕ ਪੂਰਾ ਮੌਕਾ ਦਿਓ। ਤੁਹਾਡੇ ਆਮ ਇਲਾਜ ਦੇ ਉੱਤੋਂ ਮੋਢੇ ਨੂੰ ਮਜ਼ਬੂਤ ਕਰਨ ਵਾਲੀਆਂ ਕਸਰਤਾਂ ਦੀ ਵੱਡੀ ਮਾਤਰਾ ਜੋੜਨ ਨਾਲ ਨਤੀਜੇ ਬਿਹਤਰ ਨਹੀਂ ਹੁੰਦੇ, ਇਸ ਲਈ ਨਿਯਮਤ ਅਤੇ ਚੰਗੀ ਅਗਵਾਈ ਹੇਠ ਕੀਤੀ ਕਸਰਤ ਹੀ ਅਸਲ ਮਾਇਨੇ ਰੱਖਦੀ ਹੈ।
ਦਰਦ ਨਿਵਾਰਕ ਦਵਾਈਆਂ ਅਤੇ ਸੋਜਸ਼-ਰੋਧੀ ਦਵਾਈਆਂ (anti-inflammatories) ਕਸਰਤਾਂ ਦੇ ਅਸਰ ਕਰਨ ਦੌਰਾਨ ਤੁਹਾਨੂੰ ਹਿੱਲਦੇ-ਜੁਲਦੇ ਰਹਿਣ ਵਿੱਚ ਮਦਦ ਕਰ ਸਕਦੀਆਂ ਹਨ। ਅਸੀਂ ਇਸ ਹਾਲਤ ਲਈ ਕੋਰਟੀਸੋਨ ਦੇ ਟੀਕਿਆਂ ਦੀ ਵਰਤੋਂ ਨਹੀਂ ਕਰਦੇ।
ਜੇ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਇਲਾਜ ਨੂੰ ਸੱਚਮੁੱਚ ਅਜ਼ਮਾਉਣ ਤੋਂ ਬਾਅਦ ਵੀ ਦਰਦ ਤੁਹਾਨੂੰ ਰੋਕਦਾ ਹੈ, ਤਾਂ ਅਸੀਂ ਸਰਜਰੀ ਬਾਰੇ ਗੱਲ ਕਰਦੇ ਹਾਂ। ਇਹ ਓਪਰੇਸ਼ਨ ਸਬਐਕਰੋਮੀਅਲ ਡੀਕੰਪ੍ਰੈਸ਼ਨ ਹੈ, ਜਿਸ ਵਿੱਚ ਟੈਂਡਨਾਂ ਨੂੰ ਵਧੇਰੇ ਥਾਂ ਦੇਣ ਲਈ ਮਿਹਰਾਬ ਦੇ ਹੇਠਲੇ ਪਾਸੇ ਤੋਂ ਹੱਡੀ ਘਸਾਈ ਜਾਂਦੀ ਹੈ, ਅਤੇ ਨਾਲ ਹੀ ਸੋਜਸ਼ ਵਾਲਾ ਬਰਸਾ ਕੱਢ ਦਿੱਤਾ ਜਾਂਦਾ ਹੈ। ਇਹ ਫ਼ੈਸਲਾ ਤੁਸੀਂ ਸਾਡੇ ਨਾਲ ਮਿਲ ਕੇ ਕਰਦੇ ਹੋ, ਇਹ ਤੋਲ ਕੇ ਕਿ ਓਪਰੇਸ਼ਨ ਵਿੱਚ ਕੀ ਹੁੰਦਾ ਹੈ ਅਤੇ ਇਹ ਕੀ ਬਦਲ ਸਕਦਾ ਹੈ ਅਤੇ ਕੀ ਨਹੀਂ।
ਕੀ ਉਮੀਦ ਰੱਖੀਏ
ਬਹੁਤੇ ਲੋਕਾਂ ਵਿੱਚ ਇਹ ਹਾਲਤ ਸਰਜਰੀ ਨਾਲ ਨਹੀਂ, ਸਗੋਂ ਸਮੇਂ ਅਤੇ ਨਿਯਮਤ ਕਸਰਤ ਨਾਲ ਸ਼ਾਂਤ ਹੋ ਜਾਂਦੀ ਹੈ। ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਇਲਾਜ ਬਾਰੇ ਰਾਇ ਬਣਾਉਣ ਤੋਂ ਪਹਿਲਾਂ ਇਸਨੂੰ ਕਈ ਮਹੀਨਿਆਂ ਤੱਕ ਪੂਰਾ ਮੌਕਾ ਦਿਓ। ਬਹੁਤ ਸਾਰੇ ਲੋਕਾਂ ਵਿੱਚ ਇੰਨਾ ਸੁਧਾਰ ਹੋ ਜਾਂਦਾ ਹੈ ਕਿ ਉਹ ਓਪਰੇਸ਼ਨ ਤੋਂ ਬਿਨਾਂ ਆਪਣੀਆਂ ਆਮ ਸਰਗਰਮੀਆਂ ਵਿੱਚ ਵਾਪਸ ਆ ਜਾਂਦੇ ਹਨ। ਜੇ ਕਸਰਤ ਅਤੇ ਹੋਰ ਗ਼ੈਰ-ਸਰਜੀਕਲ ਉਪਾਵਾਂ ਨੂੰ ਸੱਚਮੁੱਚ ਅਜ਼ਮਾਉਣ ਤੋਂ ਬਾਅਦ ਵੀ ਦਰਦ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋਇਆ, ਤਾਂ ਸਰਜਰੀ ਬਾਰੇ ਗੱਲ ਹੋ ਸਕਦੀ ਹੈ, ਪਰ ਇਸਦੀ ਤੁਲਨਾ ਸ਼ੈਮ ਪ੍ਰਕਿਰਿਆ ਨਾਲ ਕਰਨ ਵਾਲੇ ਟ੍ਰਾਇਲਾਂ ਨੂੰ ਖ਼ੁਦ ਹੱਡੀ ਕੱਢਣ ਤੋਂ ਬਹੁਤ ਥੋੜ੍ਹਾ ਵਾਧੂ ਫ਼ਾਇਦਾ ਮਿਲਿਆ।
ਇਸ ਹਾਲਤ ਤੋਂ ਠੀਕ ਹੋਣਾ ਸੋਚ-ਸਮਝ ਕੇ ਸੰਭਾਲਿਆ ਜਾਂਦਾ ਹੈ, ਕਾਹਲੀ ਨਾਲ ਨਹੀਂ। ਓਪਰੇਸ਼ਨ ਕਰਵਾਉਣ ਵਾਲੇ ਬਹੁਤੇ ਲੋਕ 6 ਹਫ਼ਤਿਆਂ ਦੇ ਅੰਦਰ ਕੰਮ ਉੱਤੇ ਵਾਪਸ ਆ ਜਾਂਦੇ ਹਨ, ਅਤੇ 90% ਤੋਂ ਵੱਧ ਲੋਕ 4 ਹਫ਼ਤਿਆਂ ਦੇ ਅੰਦਰ ਗੱਡੀ ਚਲਾਉਣ ਲੱਗ ਪੈਂਦੇ ਹਨ, ਪਰ ਮੋਢੇ ਦੀ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਘੱਟੋ-ਘੱਟ ਛੇ ਹਫ਼ਤਿਆਂ ਤੱਕ ਗੱਡੀ ਨਾ ਚਲਾਓ, ਅਤੇ ਉਦੋਂ ਹੀ ਚਲਾਓ ਜਦੋਂ ਤੁਹਾਡਾ ਸਰਜਨ ਇਜਾਜ਼ਤ ਦੇਵੇ। ਬਹੁਤੇ ਲੋਕ ਆਪਣੀਆਂ ਪਹਿਲਾਂ ਵਾਲੀਆਂ ਖੇਡਾਂ ਵਿੱਚ ਵੀ ਵਾਪਸ ਆ ਜਾਂਦੇ ਹਨ, ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਸਿਰ ਤੋਂ ਉੱਪਰ ਦੀਆਂ ਖੇਡਾਂ ਖੇਡਣ ਵਾਲਿਆਂ ਵਿੱਚੋਂ 90% ਅਤੇ ਮੋਢੇ ਉੱਤੇ ਘੱਟ ਜ਼ੋਰ ਪਾਉਣ ਵਾਲੀਆਂ ਜਾਂ ਟੱਕਰ ਵਾਲੀਆਂ (contact) ਖੇਡਾਂ ਖੇਡਣ ਵਾਲੇ ਸਾਰੇ ਲੋਕ ਸ਼ਾਮਲ ਹਨ। ਮਰੀਜ਼ ਨੂੰ ਆਪਣੇ ਮੋਢੇ ਦਾ ਕੰਮਕਾਜ ਜਿਵੇਂ ਮਹਿਸੂਸ ਹੁੰਦਾ ਹੈ, ਉਸਨੂੰ ਠੀਕ ਹੋਣ ਵਿੱਚ ਔਸਤਨ ਤਕਰੀਬਨ 3 ਮਹੀਨੇ ਲੱਗਦੇ ਹਨ। ਕੋਰਾਕੋਐਕਰੋਮੀਅਲ ਲਿਗਾਮੈਂਟ (coracoacromial ligament), ਯਾਨੀ ਮਿਹਰਾਬ ਹੇਠਲਾ ਟਿਸ਼ੂ ਦਾ ਪਟਾ, ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਮੁਕਾਬਲਤਨ ਜਲਦੀ ਮੁੜ ਬਣ ਸਕਦਾ ਹੈ, ਪਰ ਇਸਨੂੰ ਆਪਣੀ ਤਾਕਤ ਵਾਪਸ ਲੈਣ ਵਿੱਚ ਸਮਾਂ ਲੱਗਦਾ ਹੈ।
ਜੇ ਇਸ ਹਾਲਤ ਦਾ ਇਲਾਜ ਨਾ ਕੀਤਾ ਜਾਵੇ, ਤਾਂ ਕੁਝ ਲੋਕਾਂ ਨੂੰ ਆਉਂਦਾ-ਜਾਂਦਾ ਦਰਦ ਹੁੰਦਾ ਰਹਿੰਦਾ ਹੈ, ਖ਼ਾਸ ਕਰਕੇ ਸਿਰ ਤੋਂ ਉੱਪਰ ਦੀਆਂ ਸਰਗਰਮੀਆਂ ਨਾਲ। ਖ਼ਾਸ ਕਸਰਤਾਂ ਵਾਲਾ ਇਲਾਜ ਸਰਜਰੀ ਦੀ ਲੋੜ ਘਟਾ ਸਕਦਾ ਹੈ, ਅਤੇ ਇਸਦੇ ਨਤੀਜੇ 10 ਸਾਲਾਂ ਬਾਅਦ ਵੀ ਕਾਇਮ ਰਹਿੰਦੇ ਹਨ। ਵ੍ਹਿਪਲੈਸ਼ (whiplash, ਝਟਕੇ ਨਾਲ ਗਰਦਨ ਨੂੰ ਲੱਗੀ ਸੱਟ) ਵਾਲੇ ਲੋਕਾਂ ਵਿੱਚ ਨਤੀਜੇ ਹੌਲੀ ਅਤੇ ਕੁੱਲ ਮਿਲਾ ਕੇ ਮਾੜੇ ਹੁੰਦੇ ਹਨ। ਸਰਜਰੀ ਦੌਰਾਨ ਮਿਲੇ ਰੋਟੇਟਰ ਕਫ਼ ਦੇ ਅੰਸ਼ਕ ਪਾਟਣ ਦਾ ਇਲਾਜ ਕਰਨ ਦੀ ਸ਼ਾਇਦ ਲੋੜ ਨਾ ਪਵੇ, ਕਿਉਂਕਿ ਦੋਵਾਂ ਗਰੁੱਪਾਂ ਦਾ ਆਖ਼ਰੀ ਨਤੀਜਾ ਮਿਲਦਾ-ਜੁਲਦਾ ਸੀ।
ਡਾਕਟਰ ਨੂੰ ਕਦੋਂ ਮਿਲਣਾ ਚਾਹੀਦਾ ਹੈ
ਇੱਥੇ ਦੱਸਿਆ ਮੋਢੇ ਦਾ ਜ਼ਿਆਦਾਤਰ ਦਰਦ ਐਮਰਜੈਂਸੀ ਨਹੀਂ ਹੁੰਦਾ, ਪਰ ਕੁਝ ਨਿਸ਼ਾਨੀਆਂ ਵੱਲ ਜਲਦੀ ਧਿਆਨ ਦੇਣ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਜੇ ਤੁਹਾਡੀ ਬਾਂਹ ਗਰਮ, ਲਾਲ, ਸੁੱਜੀ ਹੋਈ ਅਤੇ ਦਰਦ ਵਾਲੀ ਹੋ ਜਾਵੇ, ਖ਼ਾਸ ਕਰਕੇ ਬੁਖ਼ਾਰ ਦੇ ਨਾਲ, ਜਾਂ ਜੇ ਤੁਹਾਡੀਆਂ ਉਂਗਲਾਂ ਜਾਂ ਹੱਥ ਫਿੱਕੇ, ਠੰਢੇ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੇ ਪੈ ਜਾਣ, ਤਾਂ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹੀ ਗੱਲ ਉਦੋਂ ਵੀ ਲਾਗੂ ਹੁੰਦੀ ਹੈ ਜੇ ਕਿਸੇ ਸੱਟ ਤੋਂ ਬਾਅਦ ਤੁਹਾਡੀ ਬਾਂਹ ਵਿੱਚ ਅਚਾਨਕ ਅਹਿਸਾਸ ਜਾਂ ਹਰਕਤ ਖ਼ਤਮ ਹੋ ਜਾਵੇ।
ਜੇ ਦਰਦ ਸ਼ਾਂਤ ਨਹੀਂ ਹੋ ਰਿਹਾ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਿਹਾ ਹੈ, ਤੁਹਾਨੂੰ ਰਾਤ ਨੂੰ ਜਗਾਉਂਦਾ ਹੈ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਬਾਂਹ ਵਰਤਣ ਤੋਂ ਰੋਕਦਾ ਹੈ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ। ਜੇ ਕਈ ਮਹੀਨਿਆਂ ਬਾਅਦ ਵੀ ਸਾਦੇ ਉਪਾਵਾਂ ਨਾਲ ਮਦਦ ਨਹੀਂ ਮਿਲੀ, ਜਾਂ ਜੇ ਦਰਦ ਦਾ ਪੈਟਰਨ ਪਹਿਲਾਂ ਦੱਸੇ ਪੇਨਫੁੱਲ ਆਰਕ ਵਰਗਾ ਲੱਗਦਾ ਹੈ, ਤਾਂ ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਾਂਚ ਦੀ ਮੰਗ ਕਰੋ।
ਮਾਹਰ ਡਾਕਟਰ ਦੀ ਜਾਂਚ ਕੋਈ ਵੀ ਫ਼ੈਸਲਾ ਲੈਣ ਤੋਂ ਪਹਿਲਾਂ ਹੋਰ ਕਾਰਨਾਂ, ਜਿਵੇਂ ਰੋਟੇਟਰ ਕਫ਼ ਦਾ ਪਾਟਣਾ ਜਾਂ ਫ੍ਰੋਜ਼ਨ ਸ਼ੋਲਡਰ, ਨੂੰ ਪਰਖ ਕੇ ਬਾਹਰ ਵੀ ਕਰ ਸਕਦੀ ਹੈ।
ਵਿਸਥਾਰ ਵਿੱਚ
Advanced reading: the deeper science (optional)
ਇਹ ਹਿੱਸਾ ਤੁਹਾਡੇ ਆਪਣੇ ਇਲਾਜ ਬਾਰੇ ਫ਼ੈਸਲਿਆਂ ਲਈ ਲੋੜੀਂਦੀ ਜਾਣਕਾਰੀ ਤੋਂ ਅੱਗੇ ਜਾਂਦਾ ਹੈ। ਸਬਐਕਰੋਮੀਅਲ ਇੰਪਿੰਜਮੈਂਟ ਬਾਰੇ ਵਾਧੂ ਪੜ੍ਹਨਾ ਇਸ ਲਈ ਫ਼ਾਇਦੇਮੰਦ ਹੈ ਕਿਉਂਕਿ ਇਹ ਮੋਢੇ ਦੀ ਉਹ ਸਮੱਸਿਆ ਹੈ ਜਿਸ ਵਿੱਚ ਸਰਜਰੀ ਨੂੰ ਵੱਡੇ ਰੈਂਡਮਾਈਜ਼ਡ ਟ੍ਰਾਇਲਾਂ (randomised trials, ਮਰੀਜ਼ਾਂ ਨੂੰ ਬੇਤਰਤੀਬੀ ਨਾਲ ਗਰੁੱਪਾਂ ਵਿੱਚ ਵੰਡ ਕੇ ਕੀਤੀ ਖੋਜ) ਵਿੱਚ ਦੋ ਵਾਰ ਇੱਕ ਪਲੇਸਬੋ ਓਪਰੇਸ਼ਨ (placebo, ਨਕਲੀ ਓਪਰੇਸ਼ਨ) ਦੇ ਮੁਕਾਬਲੇ ਪਰਖਿਆ ਗਿਆ ਹੈ, ਅਤੇ ਨਤੀਜੇ ਨੇ ਦੁਨੀਆ ਭਰ ਵਿੱਚ ਇਲਾਜ ਦਾ ਤਰੀਕਾ ਬਦਲ ਦਿੱਤਾ।
ਦੋ ਟ੍ਰਾਇਲ ਜਿਨ੍ਹਾਂ ਨੇ ਓਪਰੇਸ਼ਨ ਦੀ ਤੁਲਨਾ ਓਪਰੇਸ਼ਨ ਕਰਨ ਦੇ ਦਿਖਾਵੇ ਨਾਲ ਕੀਤੀ
ਜ਼ਿਆਦਾਤਰ ਸਰਜੀਕਲ ਸਬੂਤ ਇੱਕ ਓਪਰੇਸ਼ਨ ਦੀ ਤੁਲਨਾ ਕਿਸੇ ਹੋਰ ਓਪਰੇਸ਼ਨ ਨਾਲ, ਜਾਂ ਕੋਈ ਇਲਾਜ ਨਾ ਕਰਨ ਨਾਲ ਕਰਦੇ ਹਨ। ਬਹੁਤ ਘੱਟ ਵਾਰ ਕੋਈ ਟ੍ਰਾਇਲ ਓਪਰੇਸ਼ਨ ਦੀ ਤੁਲਨਾ ਸ਼ੈਮ (sham, ਦਿਖਾਵੇ ਦਾ ਓਪਰੇਸ਼ਨ) ਨਾਲ ਕਰਦਾ ਹੈ: ਮਰੀਜ਼ ਨੂੰ ਅਨੱਸਥੀਸੀਆ ਦਿੱਤਾ ਜਾਂਦਾ ਹੈ, ਆਰਥਰੋਸਕੋਪ (arthroscope, ਜੋੜ ਵਿੱਚ ਪਾਇਆ ਜਾਣ ਵਾਲਾ ਕੈਮਰਾ) ਅੰਦਰ ਪਾਇਆ ਜਾਂਦਾ ਹੈ, ਕੋਈ ਡੀਕੰਪ੍ਰੈਸ਼ਨ ਨਹੀਂ ਕੀਤਾ ਜਾਂਦਾ, ਅਤੇ ਨਾ ਮਰੀਜ਼ ਨੂੰ ਅਤੇ ਨਾ ਹੀ ਨਤੀਜਾ ਮਾਪਣ ਵਾਲੇ ਨੂੰ ਪਤਾ ਹੁੰਦਾ ਹੈ ਕਿ ਕਿਹੜਾ ਕੀਤਾ ਗਿਆ ਸੀ। ਇਹ ਢਾਂਚਾ ਸਰਜਰੀ ਕਰਵਾਉਣ ਦੇ ਪਲੇਸਬੋ ਅਸਰ ਨੂੰ ਹਟਾ ਦਿੰਦਾ ਹੈ, ਜੋ ਕਾਫ਼ੀ ਵੱਡਾ ਹੁੰਦਾ ਹੈ।
CSAW ਟ੍ਰਾਇਲ ਨੇ 313 ਮਰੀਜ਼ਾਂ ਨੂੰ ਬੇਤਰਤੀਬੀ ਨਾਲ ਤਿੰਨ ਗਰੁੱਪਾਂ ਵਿੱਚ ਵੰਡਿਆ: ਦੂਰਬੀਨ ਵਾਲਾ ਸਬਐਕਰੋਮੀਅਲ ਡੀਕੰਪ੍ਰੈਸ਼ਨ, ਸਿਰਫ਼ ਜਾਂਚ ਲਈ ਦੂਰਬੀਨ ਪਾਉਣਾ (ਆਰਥਰੋਸਕੋਪੀ), ਅਤੇ ਕੋਈ ਇਲਾਜ ਨਹੀਂ। ਦੋਵੇਂ ਸਰਜਰੀ ਵਾਲੇ ਗਰੁੱਪਾਂ ਦੇ ਨਤੀਜੇ ਬਿਨਾਂ ਇਲਾਜ ਵਾਲੇ ਗਰੁੱਪ ਨਾਲੋਂ ਬਿਹਤਰ ਰਹੇ, ਪਰ ਇਹ ਫ਼ਰਕ ਡਾਕਟਰੀ ਤੌਰ ਤੇ ਅਹਿਮ ਨਹੀਂ ਸੀ, ਅਤੇ ਡੀਕੰਪ੍ਰੈਸ਼ਨ ਨੇ ਸਿਰਫ਼ ਆਰਥਰੋਸਕੋਪੀ ਦੇ ਮੁਕਾਬਲੇ ਕੋਈ ਵਾਧੂ ਫ਼ਾਇਦਾ ਨਹੀਂ ਦਿੱਤਾ [1]।
FIMPACT ਟ੍ਰਾਇਲ ਵੀ ਆਜ਼ਾਦ ਤੌਰ ਤੇ ਇਸੇ ਨਤੀਜੇ ਉੱਤੇ ਪਹੁੰਚਿਆ। ਇੰਪਿੰਜਮੈਂਟ ਸਿੰਡਰੋਮ ਵਾਲੇ ਮਰੀਜ਼ਾਂ ਵਿੱਚ, ਦੂਰਬੀਨ ਵਾਲੇ ਸਬਐਕਰੋਮੀਅਲ ਡੀਕੰਪ੍ਰੈਸ਼ਨ ਨੇ 24 ਮਹੀਨਿਆਂ ਉੱਤੇ ਜਾਂਚ ਵਾਲੀ ਆਰਥਰੋਸਕੋਪੀ ਦੇ ਮੁਕਾਬਲੇ ਕੋਈ ਫ਼ਾਇਦਾ ਨਹੀਂ ਦਿੱਤਾ [2]।
ਦੋ ਚੰਗੀ ਤਰ੍ਹਾਂ ਕੀਤੇ ਗਏ ਟ੍ਰਾਇਲ, ਦੋ ਦੇਸ਼, ਇੱਕੋ ਜਵਾਬ: ਓਪਰੇਸ਼ਨ ਦਾ ਹੱਡੀ ਕੱਢਣ ਵਾਲਾ ਹਿੱਸਾ ਉਹ ਹਿੱਸਾ ਨਹੀਂ ਜਿਸ ਨਾਲ ਸੁਧਾਰ ਹੋ ਰਿਹਾ ਸੀ। ਲੋਕਾਂ ਨੂੰ ਜੋ ਵੀ ਫ਼ਾਇਦਾ ਹੋਇਆ, ਉਹ ਕਿਸੇ ਅਜਿਹੀ ਚੀਜ਼ ਤੋਂ ਆਇਆ ਜੋ ਸ਼ੈਮ ਪ੍ਰਕਿਰਿਆ ਨੇ ਵੀ ਦਿੱਤੀ ਸੀ।
ਇਸ ਦਾ ਕੀ ਮਤਲਬ ਹੈ ਅਤੇ ਕੀ ਨਹੀਂ
ਇਸ ਦਾ ਮਤਲਬ ਇਹ ਨਹੀਂ ਕਿ ਦਰਦ ਕਾਲਪਨਿਕ ਹੈ, ਜਾਂ ਕਿ ਕੁਝ ਵੀ ਮਦਦ ਨਹੀਂ ਕਰਦਾ। ਇਸ ਦਾ ਮਤਲਬ ਹੈ ਕਿ ਮਕੈਨੀਕਲ ਵਿਆਖਿਆ, ਯਾਨੀ ਇਹ ਕਿ ਹੱਡੀ ਦਾ ਇੱਕ ਉਭਾਰ ਟੈਂਡਨ ਨਾਲ ਰਗੜ ਖਾਂਦਾ ਹੈ ਅਤੇ ਉਸ ਨੂੰ ਛਿੱਲ ਕੇ ਹਟਾਉਣ ਨਾਲ ਸਮੱਸਿਆ ਠੀਕ ਹੋ ਜਾਂਦੀ ਹੈ, ਫ਼ਾਇਦੇ ਦੇ ਕਾਰਨ ਵਜੋਂ ਸਬੂਤਾਂ ਨਾਲ ਸਾਬਤ ਨਹੀਂ ਹੁੰਦੀ।
ਇਸ ਦਾ ਅਸਰ ਇਸ ਗੱਲ ਉੱਤੇ ਪੈਂਦਾ ਹੈ ਕਿ ਇਸ ਸਮੱਸਿਆ ਨੂੰ ਕਿਵੇਂ ਬਿਆਨ ਕੀਤਾ ਜਾਂਦਾ ਹੈ। "ਇੰਪਿੰਜਮੈਂਟ" ਸ਼ਬਦ ਵਿੱਚ ਹੀ ਮਕੈਨੀਕਲ ਸਿਧਾਂਤ ਸਮਾਇਆ ਹੋਇਆ ਹੈ, ਇਸੇ ਲਈ ਬਹੁਤ ਸਾਰਾ ਡਾਕਟਰੀ ਸਾਹਿਤ ਹੁਣ "ਸਬਐਕਰੋਮੀਅਲ ਪੇਨ ਸਿੰਡਰੋਮ" (subacromial pain syndrome) ਸ਼ਬਦ ਵਰਤਣ ਲੱਗ ਪਿਆ ਹੈ: ਇਹ ਦੱਸਦਾ ਹੈ ਕਿ ਦਰਦ ਕਿੱਥੇ ਹੁੰਦਾ ਹੈ, ਨਾ ਕਿ ਇਹ ਕਿਉਂ ਹੁੰਦਾ ਹੈ ਇਸ ਬਾਰੇ ਕੋਈ ਅਣ-ਸਾਬਤ ਦਾਅਵਾ ਕਰਦਾ ਹੈ।
ਤਾਂ ਫਿਰ ਕੀ ਬਚਦਾ ਹੈ
ਮੁੱਖ ਭਾਰ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਵਾਲੇ ਇਲਾਜ ਉੱਤੇ ਹੈ, ਅਤੇ ਤੁਲਨਾ ਕਰਨ ਵਾਲੇ ਸਬੂਤ ਇੰਨੇ ਮਿਲੇ-ਜੁਲੇ ਹਨ ਕਿ ਇਨ੍ਹਾਂ ਨੂੰ ਧਿਆਨ ਨਾਲ ਪੜ੍ਹਨਾ ਚਾਹੀਦਾ ਹੈ। 3,643 ਮਰੀਜ਼ਾਂ ਦੇ ਇੱਕ ਨੈੱਟਵਰਕ ਵਿਸ਼ਲੇਸ਼ਣ ਵਿੱਚ, ਐਕਰੋਮੀਓਪਲਾਸਟੀ (acromioplasty, ਐਕਰੋਮੀਅਨ ਦੀ ਹੱਡੀ ਛਿੱਲਣਾ) ਅਤੇ ਫਿਜ਼ੀਓਥੈਰੇਪੀ ਦੇ ਨਾਲ ਦੂਰਬੀਨ ਵਾਲੇ ਡੀਕੰਪ੍ਰੈਸ਼ਨ ਨੇ ਦਰਦ, ਮਰੀਜ਼ਾਂ ਵੱਲੋਂ ਦੱਸੇ ਗਏ ਮਾਪਾਂ ਅਤੇ ਹਰਕਤ ਦੀ ਹੱਦ ਵਿੱਚ ਬਿਹਤਰ ਨਤੀਜੇ ਦਿਖਾਏ, ਜਦਕਿ ਕੋਰਟੀਕੋਸਟੀਰੌਇਡ ਟੀਕੇ ਨੇ ਤਿੰਨੇ ਖੇਤਰਾਂ ਵਿੱਚ ਮਾੜੇ ਨਤੀਜੇ ਦਿਖਾਏ, ਅਤੇ ਲੇਖਕਾਂ ਨੇ ਕਾਫ਼ੀ ਲੱਛਣਾਂ ਵਾਲੇ ਮਰੀਜ਼ਾਂ ਲਈ ਫਿਜ਼ੀਓਥੈਰੇਪੀ ਦੀ ਸਿਫ਼ਾਰਸ਼ ਕੀਤੀ [3]।
ਸ਼ੈਮ ਨਾਲ ਤੁਲਨਾ ਕਰਨ ਵਾਲੇ ਟ੍ਰਾਇਲਾਂ ਦੇ ਨਾਲ ਰੱਖ ਕੇ ਦੇਖੀਏ ਤਾਂ ਵਾਜਬ ਨਿਚੋੜ ਇਹ ਹੈ ਕਿ ਢਾਂਚਾਗਤ ਕਸਰਤ ਹੀ ਮੁੱਖ ਇਲਾਜ ਹੈ; ਟੀਕਾ ਥੋੜ੍ਹੇ ਸਮੇਂ ਲਈ ਦਰਦ ਤੋਂ ਰਾਹਤ ਦੇ ਸਕਦਾ ਹੈ ਪਰ ਲੰਮੇ ਸਮੇਂ ਵਿੱਚ ਚੰਗਾ ਕੰਮ ਨਹੀਂ ਕਰਦਾ; ਅਤੇ ਇਹ ਨਹੀਂ ਦਿਖਾਇਆ ਗਿਆ ਕਿ ਸਰਜਰੀ ਕੈਮਰਾ ਅੰਦਰ ਪਾਉਣ ਨਾਲ ਮਿਲਣ ਵਾਲੇ ਅਸਰ ਤੋਂ ਵੱਧ ਕੁਝ ਜੋੜਦੀ ਹੈ।
ਜਿੱਥੇ ਸਰਜਰੀ ਦੀ ਅਜੇ ਵੀ ਭੂਮਿਕਾ ਹੈ
ਇਹ ਸਭ ਕੁਝ ਰੋਟੇਟਰ ਕਫ਼ ਦੇ ਅਸਲੀ, ਮੁਰੰਮਤ ਹੋਣ ਯੋਗ ਪਾਟਣ ਉੱਤੇ ਲਾਗੂ ਨਹੀਂ ਹੁੰਦਾ, ਜੋ ਆਪਣੇ ਵੱਖਰੇ ਸਬੂਤਾਂ ਵਾਲੀ ਇੱਕ ਵੱਖਰੀ ਬਿਮਾਰੀ ਹੈ ਅਤੇ ਜਿਸ ਬਾਰੇ ਰੋਟੇਟਰ ਕਫ਼ ਵਾਲੇ ਸਫ਼ੇ ਉੱਤੇ ਦੱਸਿਆ ਗਿਆ ਹੈ। ਉੱਪਰ ਦਿੱਤੇ ਟ੍ਰਾਇਲ ਉਨ੍ਹਾਂ ਮੋਢਿਆਂ ਬਾਰੇ ਹਨ ਜਿਨ੍ਹਾਂ ਦੇ ਦਰਦ ਦਾ ਕਾਰਨ ਇੰਪਿੰਜਮੈਂਟ ਮੰਨਿਆ ਗਿਆ, ਨਾ ਕਿ ਪਾਟੇ ਹੋਏ ਟੈਂਡਨ ਵਾਲੇ ਮੋਢਿਆਂ ਬਾਰੇ। ਇਨ੍ਹਾਂ ਦੋਹਾਂ ਵਿੱਚ ਫ਼ਰਕ ਪਛਾਣਨਾ ਹੀ ਉਹ ਕਾਰਨ ਹੈ ਜਿਸ ਕਰਕੇ ਇੱਥੇ ਧਿਆਨ ਨਾਲ ਕੀਤੀ ਜਾਂਚ ਓਪਰੇਸ਼ਨ ਦੀ ਚੋਣ ਨਾਲੋਂ ਜ਼ਿਆਦਾ ਅਹਿਮ ਹੈ।
ਹਵਾਲੇ
[1] Beard DJ, Rees JL, Cook JA, Rombach I, Cooper C, Merritt N, et al. Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. Lancet. 2018;391(10118):329-38. https://doi.org/10.1016/S0140-6736(17)32457-1
[2] Paavola M, Malmivaara A, Taimela S, Kanto K, Inkinen J, Kalske J, et al. Subacromial decompression versus diagnostic arthroscopy for shoulder impingement: randomised, placebo surgery controlled clinical trial. BMJ. 2018;362:k2860. https://doi.org/10.1136/bmj.k2860
[3] Lavoie-Gagne O, Farah G, Lu Y, Mehta N, Parvaresh KC, Forsythe B. Physical therapy combined with subacromial cortisone injection is a first-line treatment whereas acromioplasty with physical therapy is best if conservative management fails for impingement syndrome: a systematic review and network meta-analysis. Arthroscopy. 2022;38(8):2511-24. https://doi.org/10.1016/j.arthro.2022.02.008
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Chronic subacromial bursitis can present as a soft tissue tumor mimic [1].
- Management of subacromial impingement syndrome includes physical therapy, injections, and surgery for some patients [2].
- There remains a need for high-quality studies of the pathology, etiology, and management of subacromial impingement syndrome [2].
- Current randomized, controlled trial evidence shows no difference in outcomes of shoulder function or pain between surgical and conservative treatment for subacromial impingement syndrome [6].
- Arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy at 24 months for patients with shoulder impingement syndrome [7].
- Arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy or exercise therapy at 5 years for patients with shoulder impingement syndrome [10].
- Arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy or exercise therapy on return to work in patients with shoulder impingement syndrome [11].
- Subacromial pain syndrome should preferably be treated non-operatively [12].
- Subacromial injection with corticosteroids is indicated for persistent or recurrent symptoms of subacromial pain syndrome [12].
- Adding a large dose of shoulder strengthening to current nonoperative care for patients with subacromial impingement did not result in superior shoulder-specific patient-reported outcomes [13].
- For patients who have a long-term disease course, operative treatments may be considered [19].
- Standard ASD surgery is preferred over arthroscopic bursectomy and the open surgical technique for subacromial decompression for patients with a long-term disease course [19].
- Ultrasound guidance is not superior in the subacromial bursa and glenohumeral joint injections in pain or function [21].
- ASD in the treatment of subacromial impingement yields good long-term results [24].
- Ultrasonography provides substantial benefit in detecting and determining the involvement of the shoulder in a patient with septic or tuberculous bursitis of the subacromial bursa [27].
- Five randomized trials found that formal subacromial decompression does not result in improved clinical outcomes up to 2 years after rotator cuff repair [30].
- There is no evidence from the available RCTs for differences in outcome in pain and shoulder function between conservatively and surgically treated patients with subacromial impingement syndrome [31].
- Preserving the subacromial bursa during rotator cuff surgery may lead to better rotator cuff healing when secondary pain is manageable [33].
- Conservative treatment can be recommended as a first choice of treatment of shoulder impingement in first or second grade because of surgery's higher costs and susceptibility for complications compared with costs and risks of conservative treatment [35].
- Surgical groups had better outcomes for shoulder pain and function compared with no treatment, but this difference was not clinically important [37].
- The SUPPORT trial aims to determine how to optimise outcomes for subacromial impingement syndrome through exercise and corticosteroid injection strategies [52].
- Arthroscopic subacromial decompression is a valid treatment, reducing pain and improving quality of life for patients selected for surgery according to the Danish national guidelines [60].
- Arthroscopic subacromial decompression is of little or no benefit over placebo surgery in the treatment of pain due to subacromial impingement [61].
- The surgical option for subacromial impingement should not be ruled out in cases of failure of medical management associated with unfavorable acromion morphology [61].
Anatomy & Pathophysiology
Bony Anatomy
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [70].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [70].
- The acromion has three ossification centers: the metacromion (base), the mesoacromion (middle), and the preacromion (tip) [73].
- Failure of fusion of the acromial ossification centers results in os acromiale [73].
- The relationship between acromial anatomy and rotator cuff disease remains controversial [73].
- The classification of acromial morphology as flat, curved, or hooked is challenged by poor interobserver reliability [73].
- A system incorporating more objective classification criteria and acknowledging the continuous nature of acromial morphologic types may improve interobserver reliability [51].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [73].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [73].
- The subchondral bone of the glenoid is relatively flat, with the articular concavity augmented by cartilage and a circumferential labrum [73].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [70].
- The articular head of the humerus is spherical with a diameter of 37 to 57 mm [70].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [70].
- The humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [70].
- The head is inclined approximately 130 degrees with respect to the humeral shaft [70].
- The bicipital groove lies between the greater and lesser tuberosities and serves as a pathway for the long head of the biceps [70].
- The distal aspect of the bicipital groove is internally rotated with respect to the proximal portion [70].
- The greater tuberosity serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [70].
- The lesser tuberosity serves as the attachment site for the subscapularis tendon [70].
- The acromion is a massive structure overlying the humeral head in humans, reflecting the increasing role of the deltoid muscle in shoulder function [80].
- The coracoid process has undergone an increase in size over time [80].
- With the shoulder in 90 degrees of abduction, the coracoid extension over the glenohumeral joint can mechanically limit anterior translation of the humerus relative to the glenoid [80].
Soft Tissue Anatomy
- The rotator cuff consists of four muscles: subscapularis, supraspinatus, infraspinatus, and teres minor [71].
- The rotator cuff serves as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [71].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [71].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [73].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [73].
- Laxity of the rotator interval results in inferior laxity (the sulcus sign) [73].
- Contracture of the rotator interval is seen with adhesive capsulitis [73].
- The coracohumeral ligament restricts external rotation in adduction and is a static restraint to inferior and posterior translation in adduction and external rotation [73].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [73].
- The superior glenohumeral ligament and coracohumeral ligament form a pulley that provides restraint against medial subluxation of the long head of the biceps tendon [73].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [73].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation of the glenohumeral joint in 90° of abduction and external rotation [73].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [73].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula [74].
- The subscapular bursa communicates with the joint cavity between the superior and middle glenohumeral ligaments [74].
- The subscapular bursa protects the tendon of the subscapularis at the point where it passes under the base of the coracoid process and over the neck of the scapula [74].
- The subscapular bursa is linked to the coracoid process by a suspensory ligament [74].
- In 28% of dissected specimens, the subscapular bursae merged with the subcoracoid bursae, forming a unique wide bursa [74].
- The subscapular bursa often houses loose bodies in the shoulder [74].
- The subscapular bursa is a region in which synovitis of the shoulder may be most intense [74].
- The humeroscapular motion interface lies between the inner structures of the proximal humerus, rotator cuff, coracohumeral ligament, and biceps tendon sheath and the superficial layer of the acromion, deltoid, coracoacromial ligament, coracoid process, and conjoined tendon [76].
- Smooth, unrestricted motion at the humeroscapular motion interface is vital to shoulder mobility [76].
- The axillary nerve has an intimate relationship within the humeroscapular motion interface [76].
- The axillary nerve is a terminal branch coming off the posterior cord of the brachial plexus just proximal to the coracoid process [76].
- The axillary nerve passes beneath the conjoined tendon anterior to the subscapularis 3 to 5 mm medial to the musculotendinous junction [76].
- The axillary nerve is adjacent to the inferior capsule before entering the quadrilateral space posteriorly [76].
- The axillary nerve splits into anterior and posterior branches within the quadrangular space [76].
- The anterior and middle deltoid muscle receives sole innervation from the anterior branch of the axillary nerve [76].
- The posterior deltoid muscle innervation varies, with supply only from the anterior branch in 2.3% of cases, from the posterior branch in 8.5%, and from both branches in 89.1% [76].
- The posterior branch of the axillary nerve branches to supply the teres minor muscle and then terminates as the superior lateral brachial cutaneous nerve [76].
- The coracoacromial ligament can be anatomically described as two distinct bands - anterolateral and posteromedial - in the majority of cases [119].
- The acromial branch of the thoracoacromial artery runs on the medial aspect of the coracoacromial ligament [84].
- The coracoacromial ligament contributes to anterosuperior stability in rotator cuff deficiency [84].
- The coracoacromial ligament should be preserved with irreparable cuff tears to prevent anterosuperior escape [84].
- The coracoacromial ligament is the arthroscopic landmark for a complete release of the rotator interval for adhesive capsulitis [84].
Bursae and Synovial Structures
- The subacromial bursa separates the rotator cuff tendons from the coracoacromial arch, allowing them to glide [78].
- The subacromial bursa receives nociceptive stimuli and proprioception and seems to regulate appropriate shoulder movement [115].
- The subacromial bursa is lined by the humeroscapular motion interface [76].
- Adhesions in the humeroscapular motion interface can limit shoulder mobility, as seen in subacromial adhesions in cuff disease and after proximal humerus fracture [76].
- The subacromial and subdeltoid bursae can become thickened and fibrotic, forming adhesions that limit normal glenohumeral motion [70].
- Pigmented villonodular synovitis of the subacromial bursa is a documented pathology [45].
- Hematogenous abscess of the subacromial/subdeltoid bursa is a documented pathology [63].
Pathophysiology
- Subacromial impingement is the most common cause of shoulder pain, accounting for 50%–74% of shoulder cases in general practice [9].
- The pathophysiology of impingement syndrome may have both extrinsic and intrinsic components [46].
- The extrinsic theory of impingement is mechanical and related to the anatomy of the coracoacromial arch [46].
- Patients with a flat (type-I) acromion had better results than those with a curved (type-II) or hooked (type-III) acromion in non-operative treatment [46].
- There was a decreased prevalence of type-I acromial morphology and an increased prevalence of type-III acromial morphology in a population of patients with rotator cuff lesions [46].
- The outcome for patients with a type-II acromion was not significantly different than that for patients with a type-III acromion [46].
- Neer divided the impingement process into three stages [46].
- Stage I of impingement is characterized by acute bursitis with subacromial edema and hemorrhage [46].
- Stage I of impingement is usually observed in patients who are thirty years old or less [46].
- Stage II of impingement is characterized by inflammation of the rotator cuff, with partial-thickness tears possible [46].
- Stage II occurs as the subacromial bursa loses its ability to lubricate and protect the underlying rotator cuff due to continued irritation from abnormal contact with the acromion [46].
- Stage III of impingement results in a full-thickness tear of the rotator cuff due to wear of the anterior aspect of the acromion on the greater tuberosity and supraspinatus tendon [46].
- The progressive process of impingement can be interrupted with an acromioplasty [46].
- Imaging abnormalities of the acromioclavicular joint and subacromial space are common in asymptomatic shoulders [14].
- There is no between-group difference in acromiohumeral distance (AHD) in neutral shoulder position, shoulder abduction at 45° or 60° in adults with subacromial pain syndrome [38].
- The superior migration of the humeral head is a probable result of cuff failure, either partial or complete [124].
- Lack of force on the subscapularis and infraspinatus/teres minor muscles resulted in a significant 61% increase in mean coracoacromial pressures [105].
- Lack of force on all rotator cuff muscles resulted in a significant 35% increase in mean coracoacromial pressures [107].
- Results demonstrated no significant effect of posterior tilting and external rotation on subacromial clearance [112].
- Primary imbalance of rotational musculature of the shoulder is an etiological factor implicated in the impingement syndrome not modified by anterior acromioplasty [111].
- In involved shoulders with impingement syndrome, there was decreased muscle torque in the external rotators in internally rotated positions compared to the uninvolved side [20].
- The aetiology of anterior-superior internal impingement appears to be related to the pulley lesion and instability of the long head of the biceps tendon [53].
- Anterior-superior internal impingement can be caused by trauma or degenerative factors [53].
- Anterior-superior internal impingement produces anterior shoulder pain in middle-aged patients, particularly when performing overhead activities [53].
- Internal impingement between the glenoid and the humeral head may be a significant mechanism in the development of rotator cuff pathosis [117].
- The intraoperative finding of contact of the rotator cuff to the posterosuperior glenoid with the arm in abduction and external rotation can occur in a wide spectrum of shoulder disease and is not limited to the throwing athlete [118].
- Impingement of the undersurface of the cuff on the posterosuperior glenoid labrum may be a cause of painful structural disease of the shoulder in the thrower [132].
- Whether coracoid impingement exists as a distinct syndrome has yet to be fully established [34].
- Lesions of the biceps and the subscapularis should not be attributed to coracoid impingement syndrome [34].
- A weak rotator interval can induce impingement by the soft tissues around the coracoid process [34].
- Closure of the rotator interval, with or without coracoidoplasty, led to improvements in all 14 cases of coracoid impingement studied [34].
- The physiopathologic mechanism for coracoid impingement is not satisfactorily explained [34].
- The physiopathologic mechanism for subacromial impingement is unclear [34].
- Coracoid impingement of the subscapularis tendon seems to be the result of a functional problem, mainly anterior instability of the shoulder joint leading to a functional narrowing of the coracohumeral distance [110].
- Subacromial impingement syndrome is increasingly questioned as a useful diagnosis, with an emerging consensus that symptoms may arise from a number of shoulder pathologies associated with the soft tissues occupying the subacromial space [104].
- Traditionally, extrinsic factors were proposed as causing compression and abrasion of the bursal side of the rotator cuff, mechanically encroached between the acromion (or coracoid) and humeral head [104].
- Intrinsic rotator cuff pathology is suggested as more causative of symptoms than the traditional extrinsic model [104].
- Cadaver studies have demonstrated that rotator cuff pathology occurs more frequently within the internal substance or on the joint side of the tendon [104].
- Lifestyle factors such as sleep behaviors and shoulder usage patterns are associated with subacromial impingement syndrome [66].
- Pain catastrophising levels determine if patients with long-standing subacromial impingement benefit from more resistance exercise [9].
Classification
- Stage I of the impingement process is characterized by acute bursitis with subacromial edema and hemorrhage [46].
- Stage I of the impingement process is usually observed in patients who are thirty years old or less [46].
- Stage II of the impingement process is characterized by inflammation of the rotator cuff and possible partial-thickness tears [46].
- Stage III of the impingement process results in a full-thickness tear of the rotator cuff [46].
- The extrinsic theory of impingement syndrome is mechanical and related to the anatomy of the coracoacromial arch [46].
- A comprehensive classification of individualized impingements occurring around the anterior aspect of the shoulder has been proposed to address conflicting theories [5].
- In a study of 552 patients, the impingement group was subdivided into three groups according to severity [49].
- Group 1 in the severity classification consisted of subacromial impingement alone with a positive impingement test, bursitis or cuff tendonitis, but no tear [49].
- Group 2 in the severity classification consisted of partial rotator cuff tears, including bursal-side and joint-side partial tears [49].
- Group 3 in the severity classification consisted of full-thickness rotator cuff tears regardless of size [49].
- Calcium deposits in the shoulder were classified by size, with large deposits defined as 1.5 cm or longer in their greatest profile [120].
Clinical Presentation
Epidemiology and Prevalence
- Each month, one in every six adults experiences shoulder pain lasting more than 1 week [9].
Diagnostic Challenges and Comorbidities
- Patients presenting with signs and symptoms of subacromial pain syndrome have a high prevalence of conflicting and concomitant diagnoses [4].
- Examination of the cervical spine in patients with subacromial shoulder pain is variable in randomized controlled trials [55].
- Night pain is a common complaint of patients presenting with impingement of the shoulder but cannot be used in isolation as a diagnostic predictor for the presence of a rotator cuff tear [100].
- Accurate diagnosis of the etiology of a patient's shoulder pain and proper injection technique are important in achieving satisfactory clinical outcomes [54].
Clinical Testing and Physical Examination
- A Cochrane review includes 33 studies evaluating a total of 4002 shoulders in 3852 patients regarding physical tests for shoulder impingements and local lesions of bursa, tendon or labrum [3].
- The provocative tests for subacromial impingement also appear to elicit contact consistent with internal impingement [109].
- A quantified measurement test enables the clinician to quantify the subacromial space [28].
- In the involved shoulders of patients with impingement syndrome, there was decreased muscle torque in the external rotators in internally rotated positions compared to the uninvolved side [20].
Imaging and Pathology
- Supraspinatus pathology as defined by magnetic resonance imaging indicates that these pathologic conditions are nonspecific findings related to age and not to shoulder impingement [15].
- The subacromial space width is smaller in nearly all rotator cuff pathologies, but becomes even smaller as the severity of the condition increases and is smaller in the case of a complete cuff tear [57].
- Women aged between 30 and 60 years with subacromial pain syndrome and a calcific deposit of >1.5 cm in length have the highest chance of suffering from symptomatic calcific tendinopathy of the rotator cuff [40].
- Synovitis in the subacromial space was milder and not associated with any clinical parameters in patients with rotator cuff tears [16].
- Subacromial osteolysis has a relatively high and variable incidence, and the primary factor influencing the reported incidence is the radiological assessment method [23].
- Detailed diagnoses could be made as patients were kept at rest by subacromial blocking during MRI by infusing mylocain and Gd-DTPA into the subacromial bursa [36].
Atypical Presentations
- Chronic subacromial bursitis can present as an unusual case mimicking a soft tissue tumor [1].
- Two cases of synovial chondromatosis of the subacromial bursa were documented in patients who had undergone years of daily work that involved positioning the arms overhead, which may have created persistent subacromial impingement [29].
Investigations
Clinical Examination and Diagnostic Challenges
- A Cochrane review of physical tests for shoulder impingements and local lesions included 33 studies evaluating a total of 4002 shoulders in 3852 patients [3].
Plain Radiography
- At least two X-ray views should be obtained for shoulder imaging: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [87].
- The standard shoulder series should include orthogonal views of the shoulder, including a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [95].
- The true AP view in the scapular plane visualizes the anterior greater tuberosity in profile and can reveal proximal humeral migration [95].
- The axillary view enables determination of the humeral head position in the glenoid fossa and may detect occult, locked posterior shoulder dislocation [95].
- The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs, which have been closely associated with the presence of rotator cuff pathology [95].
- The acromiohumeral distance is normally 7 to 14 mm [95].
- Neer classified acromial morphology as type I (flat), type II (curved), and type III (hooked) [95].
- Type III acromial morphology has been shown to have a correlation with the presence of rotator cuff disease, although no direct causal relationship has been demonstrated [95].
- The Neer classification of acromial morphology has shown relatively poor interobserver reliability [95].
- Due to the low certainty of evidence and significant variation among study populations, further research is needed to clarify prevalence estimates of imaging abnormalities in asymptomatic shoulders [14].
Magnetic Resonance Imaging (MRI)
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [94].
- T2-weighted MRI provides better visualization of full thickness rotator cuff tears [94].
- MR imaging in shoulder abduction can be a help in evaluating the pathoanatomy of impingement syndrome [58].
- In a study of patients with impingement syndrome, the subacromial space was significantly smaller than in healthy persons [130].
- Supraspinatus pathology as defined by magnetic resonance imaging is a nonspecific finding related to age and not to shoulder impingement [15].
- The acromiohumeral distance is significantly smaller on MRI compared to AP radiographs in shoulders with an intact rotator cuff [125].
- The acromiohumeral distance on MRI should not be used as a decision criterion to assess glenohumeral centering or subacromial space width in shoulders with an intact rotator cuff [125].
- No correlation was found between abnormal findings on MR images of the shoulder after surgery and the postoperative clinical presentation of patients [128].
- MRI accuracy in identifying labral and rotator cuff tears in the literature ranges from 70% to 100% [92].
- Magnetic resonance arthrography (MRA) has greater diagnostic test accuracy for glenoid labral lesions than MRI, with MRA sensitivity of 88% and specificity of 93% versus MRI sensitivity of 76% and specificity of 87% [92].
- MRA is considered the benchmark for evaluation of labral tears and is rarely indicated for evaluation of rotator cuff pathology [94].
- When MRI or MR arthrography is contraindicated, CT arthrography is indicated [94].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [87].
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [94].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [94].
- Ultrasonography can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [94].
- Ultrasonography can evaluate impingement in various positions and motions due to real-time imaging capabilities [94].
- Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [94].
- The subacromial space width is smaller in nearly all rotator cuff pathologies, becoming even smaller as the severity of the condition increases and smallest in the case of a complete cuff tear [57].
- Ultrasonography is not superior to non-guided techniques for subacromial bursa and glenohumeral joint injections in terms of pain or function [21].
- Ultrasonography is superior to non-guided techniques for bicipital groove injections [21].
- A machine learning-based ultrasomics approach may be helpful in the preliminary screening of shoulder pain [67].
- Ultrasonography has a sensitivity of 98%, specificity of 80%, positive predictive value of 90%, negative predictive value of 95%, and accuracy of 94% for the detection of full-thickness rotator cuff tears [95].
- Ultrasonography is useful in detecting and determining the involvement of the shoulder in patients with septic or tuberculous bursitis of the subacromial bursa [27].
- MRI showed no rotator cuff tear and localized subacromial hemorrhage in a patient on anticoagulation therapy [134].
Arthroscopy and Other Modalities
- Arthroscopy is useful for diagnosing and treating subacromial impingement, intra-articular lesions, detachment of the glenoid labrum, and rotator cuff tears [87].
- Both changes in the acromion showed impingement at both sites in 13 shoulders during bursoscopy [8].
- The presence of subacromial plicae observed in living subjects at bursoscopy is in agreement with previously published anatomic studies [22].
- Subacromial friction could be seldom observed in shoulder disease except in pure impingement syndrome [18].
- Detailed diagnoses could be made using MRI by infusing mylocain and Gd-DTPA into the subacromial bursa as patients were kept at rest by subacromial blocking [36].
- A test enabling the clinician to quantify the subacromial space has been described [28].
- Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation has a relatively high and variable incidence, with the primary factor influencing the reported incidence being the radiological assessment method [23].
Treatment
Non-Operative Management
- Conservative treatment can be recommended as a first choice of treatment for shoulder impingement in first or second grade due to surgery's higher costs and susceptibility for complications [35].
- Conservative treatment is considered the first choice in the treatment of subacromial impingement syndrome, with complaints relieved when conservative methods are regularly applied [26].
- Most UK management regimes for subacromial impingement employ a minimum period of 12 weeks of conservative management incorporating physiotherapy and at least 2 subacromial steroid injections [17].
- A systematic review found no clinically meaningful differences in pain or function at any 3-, 6-months, 1-, 2-, 5- or ≥10-years follow up when comparing surgery plus physiotherapy versus physiotherapy alone [50].
- The level of pain catastrophising determines if patients with long-standing subacromial impingement benefit from more resistance exercise [9].
Injections
- Ultrasound guidance is not superior in subacromial bursa and glenohumeral joint injections regarding pain or function [21].
- A systematic review indicates there is little reproducible evidence to support the efficacy of subacromial corticosteroid injection in managing rotator cuff disease [108].
Operative Management
- Arthroscopic subacromial decompression is of little or no benefit over placebo surgery in the treatment of pain due to subacromial impingement, although the surgical option should not be ruled out in cases of failure of medical management associated with unfavorable acromion morphology [61].
- For patients who have a long-term disease course, operative treatments may be considered, with standard ASD surgery preferred over arthroscopic bursectomy and the open surgical technique for subacromial decompression [19].
- Major improvements in pain/function were seen at mid- to long-term after isolated arthroscopic subacromial decompression and combined decompression/rotator cuff repair [41].
- Subacromial continuous infusion of local anesthetic does not provide a clinically significant benefit compared with placebo as part of a multimodal analgesia regime after arthroscopic subacromial surgical procedures [123].
Complications
Diagnostic and Pathologic Mimics
- Synovial chondromatosis of the subacromial bursa is a documented complication associated with persistent overhead work [29].
- Pigmented villonodular synovitis of the subacromial bursa is a rare pathological entity [45].
- Pseudotumoral calcified bursitis of the shoulder can occur in patients with hemodialysis [62].
- Subacromial plicae are present in living subjects and have been described as a cause of impingement [22].
Imaging and Diagnostic Findings
- Supraspinatus pathology defined by magnetic resonance imaging is a nonspecific finding related to age rather than shoulder impingement [15].
- Subacromial synovitis is milder and not associated with any clinical parameters in the context of rotator cuff tears [16].
Post-Surgical Complications
- Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation has a relatively high and variable incidence [23].
- The primary factor influencing the reported incidence of subacromial osteolysis following hook plate fixation is the radiological assessment method [23].
- Subacromial notching following reverse shoulder arthroplasty with a 135° inlay humeral component and a lateralized glenoid is not associated with functional outcomes or range of motion at short-term follow-up [39].
- Subacromial pain pumps used for arthroscopic shoulder procedures are safe in the short-term [131].
Treatment-Related Outcomes and Risks
- Surgical treatment carries higher costs and susceptibility for complications compared with conservative treatment [35].
- Arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy at 24 months [7].
- Formal subacromial decompression does not result in improved clinical outcomes up to 2 years after rotator cuff repair [30].
- There is no evidence from available randomized controlled trials for differences in outcome in pain and shoulder function between conservatively and surgically treated patients with subacromial impingement syndrome [31].
- Adding a large dose of shoulder strengthening exercises to nonoperative care for 16 weeks did not significantly improve long-term outcomes in terms of shoulder disability, health-related quality of life, sick leave, or surgery rates at 1 year [64].
- There was no significant difference regarding shoulder function or adverse effects between intra-articular and subacromial corticosteroid injection in frozen shoulder [44].
Recovery
Non-Operative Management
- Conservative treatment is considered the first choice for subacromial impingement syndrome, with complaints relieved when conservative methods are regularly applied [26].
- Scapular focused interventions showed a between-group difference in shoulder abduction range of motion in the short term only [56].
Operative Management
- For patients with a long-term disease course, operative treatments may be considered, with standard ASD surgery preferred over arthroscopic bursectomy and the open surgical technique for subacromial decompression [19].
- Major improvements in pain and function were seen at mid- to long-term after isolated arthroscopic subacromial decompression and combined decompression/rotator cuff repair [41].
Post-Operative Complications and Findings
- Subacromial osteolysis has a relatively high and variable incidence following hook plate fixation for acromioclavicular dislocation, with the primary factor influencing the reported incidence being the radiological assessment method [23].
- When subacromial notching occurs following reverse shoulder arthroplasty, it is not associated with functional outcomes or range of motion at short-term follow-up [39].
- There was no evidence of progression of intrinsic rotator cuff pathologic conditions at a mean follow-up of 4.5 years after acromioplasty without repair for partial-thickness rotator cuff tears [69].
Clinical Presentation and Diagnosis
- Less than half of patients in secondary care adhere to clinical guidelines for subacromial pain syndrome and have acceptable symptoms after treatment [25].
- There was no between-group difference in acromiohumeral distance in neutral shoulder position, shoulder abduction at 45° or 60° in adults with subacromial pain syndrome [38].
Key Evidence
- [L5] This article documents an unusual presentation of chronic subacromial bursitis. [1] (10.1016/s1058-2746(00)90014-4)
- [L5] Management of subacromial impingement syndrome includes physical therapy, injections, and surgery for some patients, but there remains a need for high-quality studies of the pathology, etiology, and management of the condition. [2] (10.5435/00124635-201111000-00006)
- [L1] The review includes 33 studies evaluating a total of 4002 shoulders in 3852 patients. [3] (10.1002/14651858.cd007427.pub2)
- [L3] Patients presenting with signs and symptoms of subacromial pain syndrome have a high prevalence of conflicting and concomitant diagnoses. [4] (10.1177/23259671251332942)
- [L4] The article proposes a comprehensive classification of all individualized impingements occurring around the anterior aspect of the shoulder, including newly described entities, to address conflicting theories and improve understanding of their etiologic factors, diagnosis, and treatment. [5] (10.1007/s00264-017-3515-1)
- [L1] Current randomized, controlled trial evidence shows no difference in outcomes of shoulder function or pain between surgical and conservative treatment for subacromial impingement syndrome. [6] (10.2106/jbjs.9202.ebo579)
- [L1] In this controlled trial involving patients with a shoulder impingement syndrome, arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy at 24 months. [7] (10.1136/bmj.k2860)
- [L4] Both changes in the acromion showed impingement at both sites in 13 shoulders. [8] (10.1016/s1058-2746(96)80549-0)
- [L1] [9] (10.1136/bjsports-2022-106383)
- [L1] Arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy or exercise therapy at 5 years for patients with shoulder impingement syndrome. [10] (10.1136/bjsports-2020-102216)
- [L1] Arthroscopic subacromial decompression provided no benefit over diagnostic arthroscopy or exercise therapy on return to work in patients with shoulder impingement syndrome. [11] (10.1186/s12891-021-04768-7)
- [Paper] SAPS should preferably be treated non-operatively, with subacromial injection with corticosteroids indicated for persistent or recurrent symptoms. [12] (10.3109/17453674.2014.920991)
- [L1] Adding a large dose of shoulder strengthening to current nonoperative care for patients with subacromial impingement did not result in superior shoulder-specific patient-reported outcomes. [13] (10.1177/03635465211016008)
- [L2] Due to the low certainty of evidence and significant variation among study populations, further research is needed to clarify these prevalence estimates and to guide evidence-based management of shoulder abnormalities. [14] (10.1186/s13018-024-05378-4)
- [L4] This finding indicates that these pathologic conditions are nonspecific findings related to age and not to shoulder impingement. [15] (10.1016/s1058-2746(99)90090-3)
- [L4] Synovitis in the subacromial space was milder and not associated with any clinical parameters. [16] (10.1177/23259671231207818)
- [L4] Variation exists in the management regimes offered to patients with subacromial impingement, but most employ a minimum period of 12 weeks of conservative management incorporating physiotherapy and at least 2 subacromial steroid injections. [17] (10.1177/1758573215571010)
- [Paper] Consequently, the subacromial friction could be seldom observed in the shoulder disease except pure impingement syndrome. [18] (10.1016/s1058-2746(98)90106-9)
- [L1] For patients who have a long-term disease course, operative treatments may be considered, with standard ASD surgery preferred over arthroscopic bursectomy and the open surgical technique for subacromial decompression. [19] (10.1097/md.0000000000000510)
- [L4] In the involved shoulders there was also a decreased musle torque in the externa? rotators in internally rotated positions compared to the uninvolved side. [20] (10.1016/s1058-2746(96)80130-3)
- [L1] Ultrasound guidance is not superior in the subacromial bursa and glenohumeral joint injections in pain or function. [21] (10.1016/j.arthro.2021.12.013)
- [L4] The findings of this study, describing the presence of subacromial plicae observed in living subjects at bursoscopy, are in agreement with previously published anatomic studies. [22] (10.1016/j.jse.2006.03.009)
- [L1] Subacromial osteolysis has a relatively high and variable incidence, and the primary factor influencing the reported incidence is the radiological assessment method. [23] (10.1016/j.jse.2024.03.018)
- [L3] ASD in the treatment of subacromial impingement yields good long-term results. [24] (10.1016/j.jse.2007.06.020)
- [L3] [25] (10.1016/j.msksp.2021.102322)
- [L4] We believe that conservative should be the first choice in the treatment of subacromial impingement syndrome and we noted that the complaints were relieved when the conservative treatment methods are regularly applied. [26] (10.1016/s1058-2746(96)80423-x)
- [L5] This case illustrates the substantial benefit of ultrasonography in detecting and determining the involvement of the shoulder in a patient with septic or tuberculous bursitis of the subacromial bursa. [27] (10.1016/s1058-2746(03)00093-4)
- [L4] This test enables the clinician to quantify the subacromial space. [28] (10.1016/s1058-2746(03)00038-7)
- [L5] Both patients had undergone years of daily work that involved positioning the arms overhead, which may have created persistent subacromial impingement. [29] (10.1067/mse.2001.111964)
- [L1] Five randomized trials found that formal subacromial decompression does not result in improved clinical outcomes up to 2 years after rotator cuff repair. [30] (10.1016/j.arthro.2012.06.003)
- [L1] According to the best-evidence synthesis, there is no evidence from the available RCTs for differences in outcome in pain and shoulder function between conservatively and surgically treated patients with SIS. [31] (10.1016/j.jse.2009.01.010)
- [L5] Preserving the subacromial bursa during rotator cuff surgery may lead to better rotator cuff healing when secondary pain is manageable. [33] (10.1530/eor-2024-0183)
- [L4] [34] (10.1016/s1058-2746(99)90005-8)
- [L1] Because of surgery's higher costs and susceptibility for complications compared with costs and risks of conservative treatment, conservative treatment can be recommended as a first choice of treatment of shoulder impingement in first or second grade. [35] (10.3109/09638288.2014.907364)
- [L4] Detailed diagnoses could be made as the patients were kept at rest by subacromial blocking. [36] (10.1016/s1058-2746(95)80307-6)
- [L1] Surgical groups had better outcomes for shoulder pain and function compared with no treatment but this difference was not clinically important. [37] (10.1016/s0140-6736(17)32457-1)
- [L1] There was no between group difference in acromiohumeral distance (AHD) in neutral shoulder position, shoulder abduction at 45° or 60°. [38] (10.1038/s41598-020-76704-z)
- [L3] When subacromial notching occurs, it is not associated with functional outcomes or range of motion at short-term follow-up. [39] (10.1016/j.jseint.2024.01.009)
- [L3] This study demonstrates that women aged between 30 and 60 years with subacromial pain syndrome and a calcific deposit of >1.5 cm in length have the highest chance of suffering from symptomatic calcific tendinopathy of the rotator cuff. [40] (10.1016/j.jse.2015.02.024)
- [L3] Major improvements in pain/function were seen at mid- to long-term after isolated arthroscopic subacromial decompression and combined decompression/rotator cuff repair. [41] (10.1016/j.jor.2018.03.004)
- [L1] There was no significant difference regarding the shoulder function or adverse effects. [44] (10.1016/j.ijsu.2019.06.008)
- [L5] At a 3 1/2 year follow-up the patient was functioning well, although she still reported occasional discomfort and had shoulder elevation to 160°. [45] (10.1016/s1058-2746(97)90010-0)
- [L3] [46] (10.2106/00004623-199705000-00013)
- [L3] [49] (10.1197/j.jht.2006.11.009)
- [L1] [50] (10.1371/journal.pone.0216961)
- [L4] It is concluded that a system that incorporates more objective classification criteria and acknowledges the continuous nature of acromial morphologic types may improve interobserver reliability and validate the system's use in making clinical and surgical judgments. [51] (10.1016/s1058-2746(05)80037-0)
- [L2] This protocol paper presents the rationale, design, methods, and operational aspects of the SUPPORT trial, which aims to determine how to optimise outcomes for subacromial impingement syndrome through exercise and corticosteroid injection strategies. [52] (10.1186/1471-2474-15-81)
- [L4] [53] (10.1007/s00167-010-1232-z)
- [L5] Accurate diagnosis of the etiology of a patient's shoulder pain and proper injection technique are important in achieving satisfactory clinical outcomes. [54] (10.1016/j.jse.2007.07.009)
- [L1] Examination of the cervical spine in patients with subacromial shoulder pain is variable in randomized controlled trials. [55] (10.1177/1758573218798023)
- [L1] A between-group difference in shoulder abduction ROM in the short term only was found. [56] (10.1080/09593985.2018.1423656)
- [L4] The subacromial space width is smaller in nearly all rotator cuff pathologies, but becomes even smaller as the severity of the condition increases and is smaller in the case of a complete cuff tear. [57] (10.1016/j.ultras.2003.11.015)
- [L4] MR imaging in shoulder abduction can be a help in evaluating the pathoanatomy of impingement syndrome. [58] (10.1016/s1058-2746(96)80509-x)
- [L4] Arthroscopic subacromial decompression is a valid treatment, reducing pain and improving quality of life for patients selected for surgery according to the Danish national guidelines. [60] (10.1016/j.jse.2017.03.028)
- [L1] Arthroscopic subacromial decompression is of little or no benefit over placebo surgery in the treatment of pain due to subacromial impingement, although the surgical option should not be ruled out in cases of failure of medical management associated with unfavorable acromion morphology. [61] (10.1016/j.otsr.2019.10.002)
- [L5] After 2 years of follow-up, the patient had regained full use of the shoulder and there was no sign of recurrence. [62] (10.1016/s1058-2746(98)90041-6)
- [L5] The patient had full shoulder mobility and strength at 6 months and no symptoms, recurrence, or abnormal x-ray evaluation five years later. [63] (10.1016/s1058-2746(98)90228-2)
- [L1] Adding a large dose of shoulder strengthening exercises to nonoperative care for 16 weeks did not significantly improve long-term outcomes in terms of shoulder disability, health-related quality of life, sick leave, or surgery rates at 1 year. [64] (10.1177/23259671251374314)
- [L1] This evidence supports the development of strategies aimed at improving sleep behaviors and optimizing shoulder usage patterns as effective measures to prevent SIS. [66] (10.1186/s12891-024-07345-w)
- [L4] This noninvasive and low-cost approach may be helpful in the preliminary screening of shoulder pain. [67] (10.1002/jum.15914)
- [L4] There was no evidence of progression of intrinsic rotator cuff pathologic conditions at a mean follow-up of 4.5 years. [69] (10.1177/03635465020300021801)
- [L3] Night pain is a common complaint of patients presenting with impingement of the shoulder but cannot be used in isolation as a diagnostic predictor for the presence of a rotator cuff tear. [100] (10.1111/j.1758-5740.2011.00133.x)
- [L1] [104] (10.1177/1758573216660038)
- [L5] Lack of force on the subscapularis and infraspinatus/teres minor muscles resulted in a significant sixty-one percent increase in mean coracoacromial pressures. [105] (10.1016/s1058-2746(95)80184-7)
- [L5] Lack of force on the subscapularis and infraspinatus/teres minor muscles resulted in a significant 61% increase in mean coracoacromial pressures, while lack of force on all rotator cuff muscles resulted in a significant 35% increase. [107] (10.1016/s1058-2746(05)80039-4)
- [L1] This systematic review of the available literature indicates that there is little reproducible evidence to support the efficacy of subacromial corticosteroid injection in managing rotator cuff disease. [108] (10.5435/00124635-200701000-00002)
- [L5] The provocative tests for subacromial impingement also appear to elicit contact consistent with internal impingement. [109] (10.1016/s1058-2746(00)90008-9)
- [L5] Instead, it seems to be the result of a functional problem, mainly anterior instability of the shoulder joint leading to a functional narrowing of the coracohumeral distance. [110] (10.1016/j.jse.2003.12.007)
- [L4] These data demonstrate primary imbalance of rotatotional musculature of the shoulder is an etiological factor implicated in the impingement syndrome not modified by anterior acromioplasty. [111] (10.1016/s1058-2746(95)80091-3)
- [L5] Results demonstrated no significant effect of posterior tilting and external rotation on subacromial clearance. [112] (10.1016/j.jse.2004.09.001)
- [L5] The subacromial bursa receives nociceptive stimuli and proprioception and seems to regulate appropriate shoulder movement. [115] (10.1016/s1058-2746(96)80069-3)
- [L5] It appears that internal impingement between the glenoid and the humeral head may also be a significant mechanism in the development of rotator cuff pathosis. [117] (10.1067/mse.2000.105449)
- [L3] The intraoperative finding of contact of the rotator cuff to the posterosuperior glenoid with the arm in abduction and external rotation can occur in a wide spectrum of shoulder disease and is not limited to the throwing athlete. [118] (10.1016/s1058-2746(99)90076-9)
- [L5] In the majority of cases, the coracoacromial ligament can be anatomically described as two distinct bands - anterolateral & posteromedial. [119] (10.1016/s1058-2746(96)80286-2)
- [L4] [120] (10.1001/jama.1941.02820220019004)
- [L1] Subacromial continuous infusion of local anesthetic does not provide a clinically significant benefit compared with placebo as part of a multimodal analgesia regime after arthroscopic subacromial surgical procedures. [123] (10.1016/j.jse.2019.11.010)
- [L4] The superior migration of the humeral head is a probable result of cuff failure, either partial or complete. [124] (10.1016/s1058-2746(05)80004-7)
- [L4] The acromiohumeral distance is significantly smaller in the MRI in comparison to AP radiographs in shoulders with an intact rotator cuff and should not be used as a decision criterion on MRI to assess glenohumeral centering or subacromial space width. [125] (10.1007/s00167-020-06090-6)
- [L4] No correlation was found between the abnormal findings on the MR images of the shoulder after surgery and the postoperative clinical presentation of the patients. [128] (10.1016/s1058-2746(96)80212-6)
- [L4] In this study evidence was found that the subacromial space of patients with impingment syndrome is significantly smaller than in healthy persons. [130] (10.1016/s1058-2746(95)80066-2)
- [L4] Subacromial pain pumps used for arthroscopic shoulder procedures are safe in the short-term. [131] (10.1016/j.jse.2008.03.011)
- [L4] [132] (10.1016/s1058-2746(09)80065-7)
- [L5] The MRI showed no rotator cuff tear and localized the subacromial hemorrhage. [134] (10.1067/mse.2000.109411)
References
[1] Subacromial bursitis mimicking a soft tissue tumor. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1016/s1058-2746(00)90014-4
[2] Subacromial Impingement Syndrome. American Academy of Orthopaedic Surgeon. 2011. DOI: 10.5435/00124635-201111000-00006
[3] Physical tests for shoulder impingements and local lesions of bursa, tendon or labrum that may accompany impingement. Cochrane Database of Systematic Reviews. 2013. DOI: 10.1002/14651858.cd007427.pub2
[4] The Challenge of Diagnosing Patients Presenting With Signs and Symptoms of Subacromial Pain Syndrome: A Descriptive Study of 741 Patients Seen in a Secondary Care Setting. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/23259671251332942
[5] Redefining anterior shoulder impingement: a literature review. International Orthopaedics. 2017. DOI: 10.1007/s00264-017-3515-1
[6] Current Evidence Fails to Show Differences in Effectiveness Between Conservative and Surgical Treatment of Subacromial Impingement Syndrome. The Journal of Bone & Joint Surgery. 2010. DOI: 10.2106/jbjs.9202.ebo579
[7] Subacromial decompression versus diagnostic arthroscopy for shoulder impingement: randomised, placebo surgery controlled clinical trial. BMJ. 2018. DOI: 10.1136/bmj.k2860
[8] The role of the bursoscopy in subacromial impingement syndrome. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80549-0
[9] Level of pain catastrophising determines if patients with long-standing subacromial impingement benefit from more resistance exercise: predefined secondary analyses from a pragmatic randomised controlled trial (the SExSI Trial). British Journal of Sports Medicine. 2023. DOI: 10.1136/bjsports-2022-106383
[10] Subacromial decompression versus diagnostic arthroscopy for shoulder impingement: a 5-year follow-up of a randomised, placebo surgery controlled clinical trial. British Journal of Sports Medicine. 2020. DOI: 10.1136/bjsports-2020-102216
[11] Return to work after subacromial decompression, diagnostic arthroscopy, or exercise therapy for shoulder impingement: a randomised, placebo-surgery controlled FIMPACT clinical trial with five-year follow-up. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04768-7
[12] Guideline for diagnosis and treatment of subacromial pain syndrome. Acta Orthopaedica. 2014. DOI: 10.3109/17453674.2014.920991
[13] Effectiveness of Adding a Large Dose of Shoulder Strengthening to Current Nonoperative Care for Subacromial Impingement: A Pragmatic, Double-Blind Randomized Controlled Trial (SExSI Trial). The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211016008
[14] Imaging abnormalities of the acromioclavicular joint and subacromial space are common in asymptomatic shoulders: a systematic review. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05378-4
[15] Is supraspinatus pathology as defined by magnetic resonance imaging associated with clinical sign of shoulder impingement?. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90090-3
[16] Clinical Implication of Glenohumeral and Subacromial Synovitis in Rotator Cuff Tears. Orthopaedic Journal of Sports Medicine. 2023. DOI: 10.1177/23259671231207818
[17] Current UK practices in the management of subacromial impingement. Shoulder & Elbow. 2015. DOI: 10.1177/1758573215571010
[18] 7 Dynamic subacromial pressure in shoulder diseases. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90106-9
[19] Treatments for Shoulder Impingement Syndrome. Medicine. 2015. DOI: 10.1097/md.0000000000000510
[20] Muscle strength in patients with impingement syndrome of the shoulder. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80130-3
[21] Ultrasound Guidance Is Not Superior in Subacromial Bursa and Intraarticular Injections but Superior in Bicipital Groove: A Meta-analysis of Randomized Controlled Trials. Arthroscopy: The Journal of Arthroscopic & Related Surgery. 2022. DOI: 10.1016/j.arthro.2021.12.013
[22] Subacromial plica as a cause of impingement in the shoulder. Journal of Shoulder and Elbow Surgery. 2006. DOI: 10.1016/j.jse.2006.03.009
[23] Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation: a systematic review and meta-analysis. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2024.03.018
[24] Small full-thickness tears do well ten to thirteen years after arthroscopic subacromial decompression. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2007.06.020
[25] Less than half of patients in secondary care adheres to clinical guidelines for subacromial pain syndrome and have acceptable symptoms after treatment: A Danish nationwide cohort study of 3306 patients. Musculoskeletal Science and Practice. 2021. DOI: 10.1016/j.msksp.2021.102322
[26] Conservative treatment methods and results in subacromial impingement syndrome. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80423-x
[27] Tuberculous bursitis of the subacromial bursa. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/s1058-2746(03)00093-4
[28] Quantified measurement of subacromial impingement. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1016/s1058-2746(03)00038-7
[29] Two cases of synovial chondromatosis of the subacromial bursa. Journal of Shoulder and Elbow Surgery. 2001. DOI: 10.1067/mse.2001.111964
[30] The Changing Role of Acromioplasty. Arthroscopy. 2012. DOI: 10.1016/j.arthro.2012.06.003
[31] Conservative or surgical treatment for subacromial impingement syndrome? A systematic review. Journal of Shoulder and Elbow Surgery. 2009. DOI: 10.1016/j.jse.2009.01.010
[33] Removal or retention: evolving views on possible roles of the subacromial bursa in rotator cuff disease. EFORT Open Reviews. 2025. DOI: 10.1530/eor-2024-0183
[34] Rotator interval lesions and their relation to coracoid impingement syndrome. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90005-8
[35] Conservative treatment or surgery for shoulder impingement: systematic review and meta-analysis. Disability and Rehabilitation. 2014. DOI: 10.3109/09638288.2014.907364
[36] MRI by infusing mylocain and Gd-DTPA into the subacromial bursa. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80307-6
[37] Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. The Lancet. 2018. DOI: 10.1016/s0140-6736(17)32457-1
[38] No relationship between the acromiohumeral distance and pain in adults with subacromial pain syndrome: a systematic review and meta-analysis. Scientific Reports. 2020. DOI: 10.1038/s41598-020-76704-z
[39] Rates of subacromial notching are low following reverse shoulder arthroplasty with a 135° inlay humeral component and a lateralized glenoid. JSES International. 2024. DOI: 10.1016/j.jseint.2024.01.009
[40] Prevalence of calcific deposits within the rotator cuff tendons in adults with and without subacromial pain syndrome: clinical and radiologic analysis of 1219 patients. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.02.024
[41] Long-term results after surgical treatment of subacromial pain syndrome with or without rotator cuff tear. Journal of Orthopaedics. 2018. DOI: 10.1016/j.jor.2018.03.004
[44] Comparison of intra-articular and subacromial corticosteroid injection in frozen shoulder: A meta-analysis of randomized controlled trials. International Journal of Surgery. 2019. DOI: 10.1016/j.ijsu.2019.06.008
[45] Pigmented villonodular synovitis of the subacromial bursa. Journal of Shoulder and Elbow Surgery. 1997. DOI: 10.1016/s1058-2746(97)90010-0
[46] Non-Operative Treatment of Subacromial Impingement Syndrome. The Journal of Bone and Joint Surgery (American Volume)*. 1997. DOI: 10.2106/00004623-199705000-00013
[49] Diagnostic Accuracy of Clinical Tests for the Different Degrees of Subacromial Impingement Syndrome. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2006.11.009
[50] The effectiveness of surgical vs conservative interventions on pain and function in patients with shoulder impingement syndrome. A systematic review and meta-analysis. PLOS ONE. 2019. DOI: 10.1371/journal.pone.0216961
[51] Reliability of radiographic assessment of acromial morphology. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80037-0
[52] Subacromial impingement syndrome and pain: protocol for a randomised controlled trial of exercise and corticosteroid injection (the SUPPORT trial). BMC Musculoskeletal Disorders. 2014. DOI: 10.1186/1471-2474-15-81
[53] Anterior‐superior internal impingement of the shoulder: an evidence‐based review. Knee Surgery, Sports Traumatology, Arthroscopy. 2010. DOI: 10.1007/s00167-010-1232-z
[54] Subacromial corticosteroid injections. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2007.07.009
[55] Screening of the cervical spine in subacromial shoulder pain: A systematic review. Shoulder & Elbow. 2018. DOI: 10.1177/1758573218798023
[56] Scapular focused interventions to improve shoulder pain and function in adults with subacromial pain: A systematic review and meta-analysis. Physiotherapy Theory and Practice. 2018. DOI: 10.1080/09593985.2018.1423656
[57] Sonographic evaluation of subacromial space. Ultrasonics. 2004. DOI: 10.1016/j.ultras.2003.11.015
[58] Magnetic resonance imaging of the shoulder in abduction for the evaluation of impingement syndrome. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80509-x
[60] Acromioplasty in patients selected for operation by national guidelines. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.03.028
[61] Is acromioplasty justifiable?. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2019.10.002
[62] Surgical removal of pseudotumoral calcified bursitis of the shoulder in a patient with hemodialysis. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90041-6
[63] Hematogenous abscess of the subacromial/subdeltoid bursa in a child. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90228-2
[64] The Effect of Adding a Large Dose of Shoulder Strengthening to Nonoperative Care for Subacromial Impingement on Shoulder Disability, Quality of Life, Sick Days, and Surgery Rates: 1-Year Results From a Pragmatic, Double-Blind Randomized Controlled Trial (SExSI). Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/23259671251374314
[66] Lifestyle factors and subacromial impingement syndrome of the shoulder: potential associations in finnish participants. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07345-w
[67] Machine
[69] The Partial-Thickness Rotator Cuff Tear: Is Acromioplasty without Repair Sufficient?. The American Journal of Sports Medicine. 2002. DOI: 10.1177/03635465020300021801
[70] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[71] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[73] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[74] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[76] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > EDITOR COMMENTARY.
[78] Apley And Solomon S Concise System Of Orthopaedics And Trauma. DISORDERS OF THE ROTATOR CUFF.
[80] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Development of Individual Regions.
[84] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[87] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[92] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Magnetic Resonance Imaging and Arthrography.
[94] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[95] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[100] Night Pain is not a useful Diagnostic Indicator of Cuff Tear in Patients with Symptoms of Subacromial Impingement. Shoulder & Elbow. 2011. DOI: 10.1111/j.1758-5740.2011.00133.x
[104] Electromyographic activity of the shoulder muscles during rehabilitation exercises in subjects with and without subacromial pain syndrome: a systematic review. Shoulder & Elbow. 2016. DOI: 10.1177/1758573216660038
[105] Impingement pressures underneath the coracoacromial vault. A biomechanical analysis. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80184-7
[107] Coracoacromial pressure recordings in a cadaveric model. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80039-4
[108] The Efficacy of Subacromial Corticosteroid Injection in the Treatment of Rotator Cuff Disease: A Systematic Review. Journal of the American Academy of Orthopaedic Surgeons. 2007. DOI: 10.5435/00124635-200701000-00002
[109] Anatomy of provocative tests for impingement syndrome of the shoulder. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1016/s1058-2746(00)90008-9
[110] The coracoid impingement of the subscapularis tendon: A cadaver study. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/j.jse.2003.12.007
[111] Isokinetic evaluation of rotational strength in normal shoulders and shoulders with impingement syndrome. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80091-3
[112] Contact forces in the subacromial space: Effects of scapular orientation. Journal of Shoulder and Elbow Surgery. 2005. DOI: 10.1016/j.jse.2004.09.001
[115] Sensory nerve supply in the human subacromial bursa. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80069-3
[117] Internal impingement in the shoulder. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1067/mse.2000.105449
[118] Internal impingement of the shoulder: A clinical and arthroscopic analysis. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90076-9
[119] The coracoacromial ligament: Anatomy, morphology and a study of acromial enthesopathy. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80286-2
[120] CALCIUM DEPOSITS IN THE SHOULDER AND SUBACROMIAL BURSITIS. Journal of the American Medical Association. 1941. DOI: 10.1001/jama.1941.02820220019004
[123] Subacromial analgesia via continuous infusion catheter vs. placebo following arthroscopic shoulder surgery: a systematic review and meta-analysis of randomized trials. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.11.010
[124] Radiologic measurement of superior displacement of the humeral head in the impingement syndrome. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(05)80004-7
[125] The acromiohumeral distance in the MRI should not be used as a decision criterion to assess subacromial space width in shoulders with an intact rotator cuff. Knee Surgery, Sports Traumatology, Arthroscopy. 2020. DOI: 10.1007/s00167-020-06090-6
[128] Preoperative and postoperative MRI of the shoulder. A correlation with neer acromionplasty. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80212-6
[130] Magnetic resonance imaging for the evaluation of the impingement syndrome. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80066-2
[131] Subacromial pain pump use with arthroscopic shoulder surgery: A short-term prospective study of complications in 583 patients. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2008.03.011
[132] Impingement of the deep surface of the supraspinatus tendon on the posterosuperior glenoid rim: An arthroscopic study. Journal of Shoulder and Elbow Surgery. 1992. DOI: 10.1016/s1058-2746(09)80065-7
[134] Atraumatic subacromial bursal hemorrhage in a patient on anticoagulation therapy. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1067/mse.2000.109411