Patients › Elbow
ਓਲੇਕ੍ਰੈਨਨ ਫ੍ਰੈਕਚਰ (ਕੂਹਣੀ ਦੀ ਨੋਕ ਦਾ ਟੁੱਟਣਾ)
Olecranon fractures — patterns, non-operative care, and tension-band or plate fixation.
ਤੁਸੀਂ ਕੀ ਮਹਿਸੂਸ ਕਰਦੇ ਹੋ
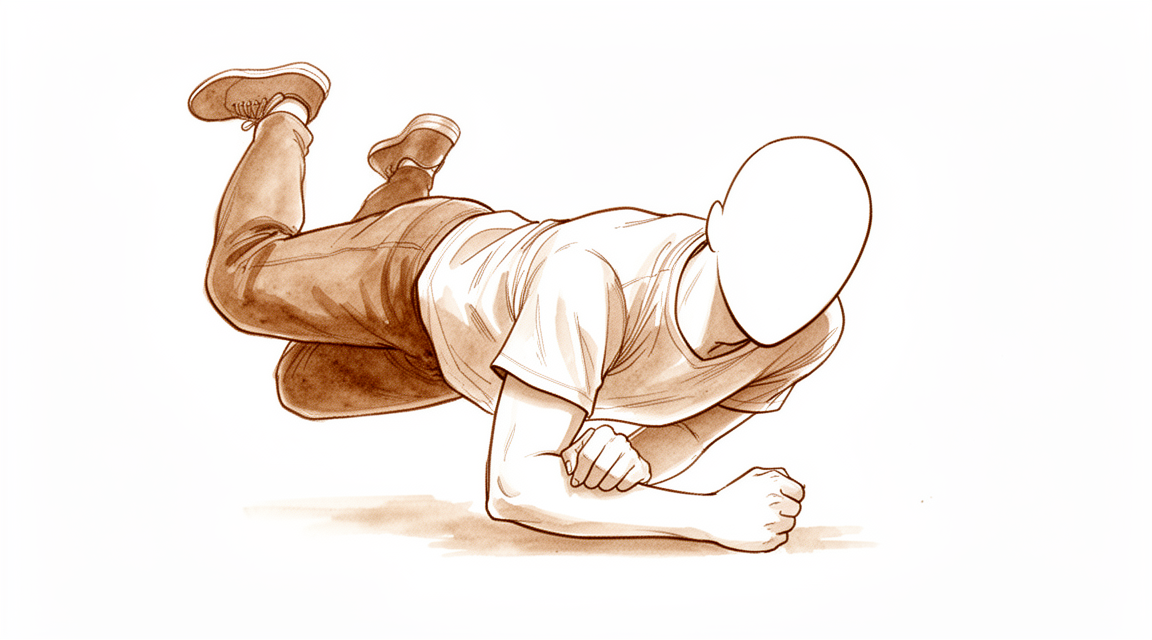
ਓਲੇਕ੍ਰੈਨਨ ਫ੍ਰੈਕਚਰ (olecranon fracture) ਤੁਹਾਡੀ ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਵਾਲੀ ਹੱਡੀ ਦੀ ਨੋਕ ਦਾ ਟੁੱਟਣਾ ਹੈ। ਇਹ ਆਮ ਤੌਰ 'ਤੇ ਦੋ ਵਿੱਚੋਂ ਇੱਕ ਤਰੀਕੇ ਨਾਲ ਹੁੰਦਾ ਹੈ। ਜਵਾਨ ਲੋਕਾਂ ਵਿੱਚ ਇਹ ਜ਼ਿਆਦਾਤਰ ਜ਼ੋਰ ਨਾਲ ਡਿੱਗਣ ਜਾਂ ਕੂਹਣੀ ਉੱਤੇ ਸਿੱਧੀ ਸੱਟ ਲੱਗਣ ਤੋਂ ਬਾਅਦ ਹੁੰਦਾ ਹੈ। ਵੱਡੀ ਉਮਰ ਦੇ ਲੋਕਾਂ ਵਿੱਚ ਇਹ ਅਕਸਰ ਖੜ੍ਹੇ-ਖੜ੍ਹੇ ਸਾਧਾਰਨ ਤਰੀਕੇ ਨਾਲ ਡਿੱਗ ਪੈਣ ਤੋਂ ਹੁੰਦਾ ਹੈ। ਬਾਂਹ ਨੂੰ ਅਚਾਨਕ, ਜ਼ੋਰ ਨਾਲ ਸਿੱਧਾ ਕਰਨ ਨਾਲ ਵੀ ਕੂਹਣੀ ਦੀ ਨੋਕ ਤੋਂ ਹੱਡੀ ਦਾ ਇੱਕ ਟੁਕੜਾ ਖਿੱਚ ਕੇ ਵੱਖ ਹੋ ਸਕਦਾ ਹੈ।
ਤੁਹਾਨੂੰ ਆਮ ਤੌਰ 'ਤੇ ਦਰਦ ਬਿਲਕੁਲ ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਮਹਿਸੂਸ ਹੋਵੇਗਾ, ਅਤੇ ਇਹ ਸਾਰੀ ਕੂਹਣੀ ਦੀ ਬਜਾਏ ਅਕਸਰ ਇੱਕੋ ਥਾਂ ਉੱਤੇ ਦੁਖਦਾ ਹੈ। ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਸੋਜ ਆਮ ਗੱਲ ਹੈ ਅਤੇ ਇਹ ਕਾਫ਼ੀ ਜ਼ਿਆਦਾ ਹੋ ਸਕਦੀ ਹੈ। ਕਿਉਂਕਿ ਹੱਡੀ ਦੀ ਉਹ ਨੋਕ ਚਮੜੀ ਦੇ ਬਿਲਕੁਲ ਹੇਠਾਂ ਹੁੰਦੀ ਹੈ, ਤੁਸੀਂ ਕਈ ਵਾਰ ਚਮੜੀ ਦੇ ਉੱਪਰੋਂ ਟੁੱਟੀ ਥਾਂ ਦਾ ਕਿਨਾਰਾ ਮਹਿਸੂਸ ਕਰ ਸਕਦੇ ਹੋ। ਜੇ ਡਿੱਗਣ ਨਾਲ ਚਮੜੀ ਫਟ ਗਈ ਸੀ, ਤਾਂ ਜ਼ਖ਼ਮ ਆਮ ਤੌਰ 'ਤੇ ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਹੁੰਦਾ ਹੈ, ਜਿੱਥੇ ਇਹ ਜ਼ਮੀਨ ਨਾਲ ਟਕਰਾਈ ਸੀ। ਬਾਂਹ ਨੂੰ ਵਰਤਣਾ ਔਖਾ ਹੋ ਸਕਦਾ ਹੈ, ਅਤੇ ਕਿਸੇ ਚੀਜ਼ ਦੇ ਵਿਰੁੱਧ ਇਸ ਨੂੰ ਸਿੱਧਾ ਕਰਨਾ, ਜਿਵੇਂ ਕੁਰਸੀ ਤੋਂ ਬਾਹਾਂ ਦੇ ਜ਼ੋਰ ਨਾਲ ਉੱਠਣਾ, ਕਮਜ਼ੋਰ ਜਾਂ ਨਾਮੁਮਕਿਨ ਲੱਗ ਸਕਦਾ ਹੈ।
ਪਹਿਲੇ ਦਿਨਾਂ ਵਿੱਚ, ਕੂਹਣੀ ਨੂੰ ਹਿਲਾਉਣ ਦੀ ਕੋਸ਼ਿਸ਼ ਕਰਨ ਵੇਲੇ ਦਰਦ ਅਕਸਰ ਵੱਧ ਹੁੰਦਾ ਹੈ, ਅਤੇ ਇਹ ਤੁਹਾਡੀ ਨੀਂਦ ਖ਼ਰਾਬ ਕਰ ਸਕਦਾ ਹੈ। ਰੋਜ਼ਾਨਾ ਦੇ ਉਹ ਕੰਮ ਜਿਨ੍ਹਾਂ ਵਿੱਚ ਕੂਹਣੀ ਮੁੜਦੀ ਹੈ ਜਾਂ ਉਸ ਉੱਤੇ ਭਾਰ ਪੈਂਦਾ ਹੈ, ਜਿਵੇਂ ਕੇਤਲੀ ਚੁੱਕਣਾ, ਕੱਪੜੇ ਪਾਉਣਾ, ਜਾਂ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ (forearm) ਦੇ ਭਾਰ ਟਿਕਣਾ, ਆਮ ਤੌਰ 'ਤੇ ਦੁਖਣਗੇ। ਸੋਜ ਅਤੇ ਨੀਲ ਪਹਿਲੇ ਦੋ ਕੁ ਹਫ਼ਤਿਆਂ ਵਿੱਚ ਘਟ ਜਾਂਦੇ ਹਨ, ਅਤੇ ਜਿਵੇਂ-ਜਿਵੇਂ ਹੱਡੀ ਜੁੜਨੀ ਸ਼ੁਰੂ ਹੁੰਦੀ ਹੈ, ਦਰਦ ਹੌਲੀ-ਹੌਲੀ ਘਟਦਾ ਜਾਂਦਾ ਹੈ।
ਕੁਝ ਹਾਲਤਾਂ ਵਿੱਚ ਫ਼ੌਰੀ ਇਲਾਜ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ। ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ ਜੇ ਕੂਹਣੀ ਉੱਤੇ ਚਮੜੀ ਫਟੀ ਹੋਵੇ, ਜੇ ਹੱਡੀ ਦਿਸ ਰਹੀ ਹੋਵੇ, ਜਾਂ ਜੇ ਬਾਂਹ ਸਾਫ਼ ਤੌਰ 'ਤੇ ਆਪਣੀ ਸ਼ਕਲ ਤੋਂ ਵਿਗੜੀ ਹੋਈ ਦਿਸੇ। ਇਹੀ ਗੱਲ ਲਾਗੂ ਹੁੰਦੀ ਹੈ ਜੇ ਤੁਹਾਡਾ ਹੱਥ ਜਾਂ ਉਂਗਲਾਂ ਫਿੱਕੀਆਂ, ਠੰਢੀਆਂ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੀਆਂ ਪੈ ਜਾਣ, ਜਾਂ ਜੇ ਸੱਟ ਤੋਂ ਬਾਅਦ ਤੁਹਾਡੀ ਬਾਂਹ ਅਚਾਨਕ ਸੁੰਨ ਹੋ ਜਾਵੇ ਜਾਂ ਹਿਲਣੋਂ ਰਹਿ ਜਾਵੇ। ਜੇ ਲੱਛਣ ਠੀਕ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਜਾਂ ਰਾਤ ਨੂੰ ਤੁਹਾਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾ ਰਹੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ। ਜੇ ਤੁਸੀਂ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਹੀਂ ਕਰ ਸਕਦੇ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਅਸਲ ਵਿੱਚ ਕੀ ਹੋ ਰਿਹਾ ਹੈ
ਤੁਹਾਡੀ ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਹੱਡੀ ਦੀ ਨੋਕ ਨੂੰ ਓਲੇਕ੍ਰੈਨਨ (olecranon) ਕਹਿੰਦੇ ਹਨ। ਇਹ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਦੀਆਂ ਹੱਡੀਆਂ ਵਿੱਚੋਂ ਇੱਕ ਦਾ ਉੱਪਰਲਾ ਸਿਰਾ ਹੈ, ਅਤੇ ਇਹ ਕਬਜ਼ੇ ਦੀ ਟੋਪੀ ਵਾਂਗ ਕੰਮ ਕਰਦਾ ਹੈ। ਜਦੋਂ ਤੁਸੀਂ ਆਪਣੀ ਬਾਂਹ ਸਿੱਧੀ ਕਰਦੇ ਹੋ, ਤਾਂ ਉਹ ਟੋਪੀ ਡੌਲੇ ਦੀ ਹੱਡੀ (upper arm bone) ਦੇ ਸਿਰੇ ਉੱਤੇ ਬਣੇ ਇੱਕ ਖਾਂਚੇ ਵਿੱਚ ਫਿਸਲਦੀ ਹੈ। ਇਹ ਫ੍ਰੈਕਚਰ ਇਸ ਲਈ ਅਹਿਮ ਹੈ ਕਿਉਂਕਿ ਇਸ ਹੱਡੀ ਨਾਲ ਕੀ ਜੁੜਿਆ ਹੋਇਆ ਹੈ: ਤੁਹਾਡੀ ਟ੍ਰਾਈਸੈਪਸ (triceps), ਯਾਨੀ ਡੌਲੇ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਦੀ ਮਾਸਪੇਸ਼ੀ, ਦਾ ਟੈਂਡਨ (tendon, ਪੱਠੇ ਨੂੰ ਹੱਡੀ ਨਾਲ ਜੋੜਨ ਵਾਲੀ ਮਜ਼ਬੂਤ ਤੰਦ) ਬਿਲਕੁਲ ਉਸੇ ਥਾਂ ਉੱਤੇ ਜੁੜਿਆ ਹੁੰਦਾ ਹੈ। ਇਹੀ ਟੈਂਡਨ ਤੁਹਾਨੂੰ ਭਾਰ ਦੇ ਵਿਰੁੱਧ ਕੂਹਣੀ ਸਿੱਧੀ ਕਰਨ ਦਿੰਦਾ ਹੈ।
ਇਸ ਨੂੰ ਇੱਕ ਅਜਿਹੇ ਦਰਵਾਜ਼ੇ ਵਾਂਗ ਸਮਝੋ ਜਿਸ ਨੂੰ ਇੱਕ ਮਜ਼ਬੂਤ ਸਪਰਿੰਗ ਖਿੱਚ ਕੇ ਬੰਦ ਰੱਖਦਾ ਹੈ। ਓਲੇਕ੍ਰੈਨਨ ਉਹ ਕੁੰਡਾ ਹੈ ਜਿਸ ਨਾਲ ਉਹ ਸਪਰਿੰਗ ਬੰਨ੍ਹਿਆ ਹੁੰਦਾ ਹੈ। ਜਦੋਂ ਹੱਡੀ ਟੁੱਟਦੀ ਹੈ, ਤਾਂ ਸਪਰਿੰਗ ਖਿੱਚਦਾ ਰਹਿੰਦਾ ਹੈ, ਅਤੇ ਇਹ ਟੁੱਟੇ ਟੁਕੜੇ ਨੂੰ ਉੱਪਰ ਵੱਲ ਅਤੇ ਦੂਰ ਘਸੀਟ ਲੈਂਦਾ ਹੈ, ਜਿਸ ਨਾਲ ਜੋੜ ਦੀ ਸਤ੍ਹਾ ਵਿੱਚ ਇੱਕ ਖੱਪਾ ਰਹਿ ਜਾਂਦਾ ਹੈ। ਇਸੇ ਲਈ ਇਸ ਵੇਲੇ ਤੁਹਾਡੀ ਬਾਂਹ ਆਮ ਵਾਂਗ ਕੰਮ ਨਹੀਂ ਕਰਦੀ: ਮਾਸਪੇਸ਼ੀ ਅਜੇ ਵੀ ਤਾਕਤਵਰ ਹੈ, ਪਰ ਉਹ ਤੁਹਾਡੀ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ ਨੂੰ ਹਿਲਾਉਣ ਦੀ ਬਜਾਏ ਹੱਡੀ ਦੇ ਇੱਕ ਢਿੱਲੇ ਟੁਕੜੇ ਨੂੰ ਖਿੱਚ ਰਹੀ ਹੈ। ਜ਼ੋਰ ਦੇ ਵਿਰੁੱਧ ਬਾਂਹ ਸਿੱਧੀ ਕਰਨਾ ਕਮਜ਼ੋਰ ਜਾਂ ਨਾਮੁਮਕਿਨ ਹੋ ਜਾਂਦਾ ਹੈ।
ਹੱਡੀ ਮੁੜ ਆਪਸ ਵਿੱਚ ਜੁੜ ਕੇ ਠੀਕ ਹੁੰਦੀ ਹੈ, ਅਤੇ ਟੁੱਟ ਕੇ ਵੱਖ ਹੋਇਆ ਟੁਕੜਾ, ਜਿਸ ਨਾਲ ਉਸ ਦਾ ਟੈਂਡਨ ਜੁੜਿਆ ਹੋਵੇ, ਹੱਡੀ ਜੁੜਨ ਦੇ ਨਾਲ-ਨਾਲ ਮੁੜ ਜੁੜ ਸਕਦਾ ਹੈ। ਪਰ ਇਹ ਚੰਗੀ ਤਰ੍ਹਾਂ ਹੋਣ ਲਈ ਟੁਕੜਿਆਂ ਦਾ ਸਹੀ ਥਾਂ ਉੱਤੇ ਹੋਣਾ ਜ਼ਰੂਰੀ ਹੈ। ਜਦੋਂ ਟੁੱਟੀ ਹੱਡੀ ਆਪਣੀ ਥਾਂ ਤੋਂ ਨਹੀਂ ਖਿਸਕੀ, ਤਾਂ ਟੁਕੜਿਆਂ ਨੂੰ ਜੁੜਨ ਤੱਕ ਸਿਰਫ਼ ਸਥਿਰ ਰੱਖਿਆ ਜਾ ਸਕਦਾ ਹੈ। ਜਦੋਂ ਟੁਕੜੇ ਖਿੱਚੇ ਜਾ ਕੇ ਵੱਖ ਹੋ ਗਏ ਹੋਣ, ਜਾਂ ਜਦੋਂ ਜੋੜ ਦੀ ਸਤ੍ਹਾ ਕਈ ਟੁਕੜਿਆਂ ਵਿੱਚ ਟੁੱਟ ਗਈ ਹੋਵੇ, ਤਾਂ ਕੂਹਣੀ ਅਸਥਿਰ ਹੋ ਸਕਦੀ ਹੈ, ਅਤੇ ਅਜਿਹੇ ਫ੍ਰੈਕਚਰਾਂ ਵਿੱਚ ਆਮ ਤੌਰ 'ਤੇ ਜੁੜਨ ਦੌਰਾਨ ਟੁਕੜਿਆਂ ਨੂੰ ਥਾਂ ਸਿਰ ਟਿਕਾ ਕੇ ਰੱਖਣ ਲਈ ਸਰਜਰੀ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ।
ਸਰਜਨ ਇਹਨਾਂ ਫ੍ਰੈਕਚਰਾਂ ਦਾ ਦਰਜਾ ਇਸ ਆਧਾਰ ਉੱਤੇ ਤੈਅ ਕਰਦੇ ਹਨ ਕਿ ਟੁਕੜੇ ਕਿੰਨੀ ਦੂਰ ਹਿੱਲੇ ਹਨ ਅਤੇ ਕੀ ਕੂਹਣੀ ਦਾ ਜੋੜ ਸਥਿਰ ਰਹਿੰਦਾ ਹੈ। ਦਰਜਾ ਇੱਕ ਵਾਲਾ ਫ੍ਰੈਕਚਰ ਆਪਣੀ ਥਾਂ ਤੋਂ ਨਹੀਂ ਖਿਸਕਿਆ ਹੁੰਦਾ। ਦਰਜਾ ਦੋ ਵਾਲਾ ਖਿਸਕ ਗਿਆ ਹੁੰਦਾ ਹੈ ਪਰ ਜੋੜ ਅਜੇ ਵੀ ਕੰਮ ਕਰਦਾ ਹੈ। ਦਰਜਾ ਤਿੰਨ ਦਾ ਮਤਲਬ ਹੈ ਕਿ ਕੂਹਣੀ ਦਾ ਜੋੜ ਖ਼ੁਦ ਅਸਥਿਰ ਹੈ। ਖਿਸਕੇ ਹੋਏ ਅਤੇ ਅਸਥਿਰ ਦਰਜਿਆਂ ਵਾਲੇ ਫ੍ਰੈਕਚਰਾਂ ਨੂੰ ਹੀ ਸਭ ਤੋਂ ਜ਼ਿਆਦਾ ਵਾਰ ਸਰਜਰੀ ਦੀ ਲੋੜ ਪੈਂਦੀ ਹੈ।
ਇਹਨਾਂ ਵਿੱਚੋਂ ਜ਼ਿਆਦਾਤਰ ਫ੍ਰੈਕਚਰ ਚੰਗੀ ਤਰ੍ਹਾਂ ਜੁੜ ਜਾਂਦੇ ਹਨ, ਹਾਲਾਂਕਿ ਕੂਹਣੀ ਦੇ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧਾ ਹੋਣ ਵਿੱਚ ਥੋੜ੍ਹੀ ਕਮੀ ਰਹਿ ਜਾਣਾ ਆਮ ਹੈ।
ਅਸੀਂ ਇਸ ਬਾਰੇ ਕੀ ਕਰ ਸਕਦੇ ਹਾਂ
ਡਾ. ਕੀਰਨ ਹਿਰਪਰਾ, ਜੋ ਮਾਟਰ ਪ੍ਰਾਈਵੇਟ ਹਸਪਤਾਲ ਰੌਕਹੈਂਪਟਨ ਵਿੱਚ ਉੱਪਰਲੇ ਅੰਗ (ਮੋਢੇ ਤੋਂ ਹੱਥ ਤੱਕ ਦੀ ਬਾਂਹ) ਦੇ ਸਰਜਨ ਹਨ, ਇਲਾਜ ਨੂੰ ਤੁਹਾਡੀ ਖ਼ਾਸ ਸੱਟ ਮੁਤਾਬਕ ਚੁਣਦੇ ਹਨ। ਇਹਨਾਂ ਵਿੱਚੋਂ ਕੁਝ ਫ੍ਰੈਕਚਰ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਦੇ ਜੁੜ ਜਾਂਦੇ ਹਨ, ਅਤੇ ਹੋਰਾਂ ਨੂੰ ਸੱਟ ਤੋਂ ਜਲਦੀ ਬਾਅਦ ਸਰਜਰੀ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ, ਇਸ ਲਈ ਬਿਨਾਂ ਦੇਰੀ ਜਾਂਚ ਕਰਵਾਉਣੀ ਅਹਿਮ ਹੈ। ਮਰੀਜ਼ਾਂ ਨੂੰ ਆਮ ਤੌਰ 'ਤੇ ਉਨ੍ਹਾਂ ਦਾ ਜੀਪੀ (ਫ਼ੈਮਿਲੀ ਡਾਕਟਰ) ਸਾਡੇ ਕਲੀਨਿਕ ਵਿੱਚ ਭੇਜਦਾ ਹੈ; ਜੇ ਕਿਸੇ ਫਿਜ਼ੀਓਥੈਰੇਪਿਸਟ ਨੇ ਤੁਹਾਨੂੰ ਸਾਡੇ ਕੋਲ ਆਉਣ ਦੀ ਸਲਾਹ ਦਿੱਤੀ ਹੈ, ਤਾਂ ਵੀ ਮੈਡੀਕੇਅਰ ਰਿਬੇਟ (Medicare ਵੱਲੋਂ ਵਾਪਸ ਮਿਲਣ ਵਾਲੀ ਰਕਮ) ਦੇ ਯੋਗ ਹੋਣ ਲਈ ਤੁਹਾਨੂੰ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਰੈਫ਼ਰਲ ਦੀ ਲੋੜ ਪਵੇਗੀ। ਕਲੀਨਿਕ ਵਿੱਚ ਅਸੀਂ ਤੁਹਾਡਾ ਇਤਿਹਾਸ ਲੈਂਦੇ ਹਾਂ, ਤੁਹਾਡੀ ਬਾਂਹ ਦੀ ਜਾਂਚ ਕਰਦੇ ਹਾਂ, ਅਤੇ ਜਿੱਥੇ ਲੋੜ ਹੋਵੇ ਉੱਥੇ ਇਮੇਜਿੰਗ (ਐਕਸ-ਰੇ ਵਰਗੀਆਂ ਤਸਵੀਰਾਂ) ਦਾ ਪ੍ਰਬੰਧ ਕਰਦੇ ਹਾਂ।
ਜੇ ਫ੍ਰੈਕਚਰ ਆਪਣੀ ਥਾਂ ਤੋਂ ਨਹੀਂ ਖਿਸਕਿਆ, ਜਾਂ ਸਿਰਫ਼ ਥੋੜ੍ਹਾ ਜਿਹਾ ਖਿਸਕਿਆ ਹੈ, ਅਤੇ ਤੁਹਾਡੀ ਕੂਹਣੀ ਸਥਿਰ ਹੈ, ਤਾਂ ਅਸੀਂ ਜੁੜਨ ਦੌਰਾਨ ਇਸ ਨੂੰ ਸਥਿਰ ਰੱਖਣ ਦੀ ਸਲਾਹ ਦੇ ਸਕਦੇ ਹਾਂ। ਇਸ ਦਾ ਮਤਲਬ ਹੈ ਕੁਝ ਸਮੇਂ ਲਈ ਸਪਲਿੰਟ ਜਾਂ ਪਲੱਸਤਰ (cast), ਅਤੇ ਵਾਰ-ਵਾਰ ਐਕਸ-ਰੇ ਕਰ ਕੇ ਜਾਂਚ, ਤਾਂ ਜੋ ਪੱਕਾ ਹੋ ਸਕੇ ਕਿ ਟੁਕੜੇ ਆਪਣੀ ਥਾਂ ਉੱਤੇ ਰਹਿਣ। ਇਹ ਰਾਹ ਵੱਡੀ ਉਮਰ ਦੇ ਮਰੀਜ਼ਾਂ ਲਈ, ਅਤੇ ਉਹਨਾਂ ਲੋਕਾਂ ਲਈ ਆਮ ਹੈ ਜਿਨ੍ਹਾਂ ਦੀ ਬਾਂਹ ਭਾਰੀ ਕੰਮ ਦੀ ਬਜਾਏ ਰੋਜ਼ਾਨਾ ਦੇ ਕੰਮਾਂ ਲਈ ਵਰਤੀ ਜਾਂਦੀ ਹੈ। ਇਸ ਨਾਲ ਓਪਰੇਸ਼ਨ ਅਤੇ ਉਸ ਨਾਲ ਜੁੜੇ ਖ਼ਤਰਿਆਂ ਤੋਂ ਬਚਾਅ ਹੁੰਦਾ ਹੈ। ਇਸ ਦਾ ਨੁਕਸਾਨ ਇਹ ਹੈ ਕਿ ਅਖ਼ੀਰ ਵਿੱਚ ਕੂਹਣੀ ਸ਼ਾਇਦ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧੀ ਨਾ ਹੋਵੇ, ਅਤੇ ਕੁਝ ਲੋਕਾਂ ਲਈ ਇਹ ਗੱਲ ਮੰਨਣੀ ਔਖੀ ਹੁੰਦੀ ਹੈ। ਹਿਲਜੁਲ ਤੁਹਾਡੇ ਹੈਂਡ ਥੈਰੇਪਿਸਟ ਨਾਲ ਪੜਾਅਵਾਰ ਵਾਪਸ ਲਿਆਂਦੀ ਜਾਂਦੀ ਹੈ, ਜੋ ਲੋੜ ਪੈਣ ਉੱਤੇ ਤੁਹਾਡੇ ਲਈ ਸਪਲਿੰਟ ਵੀ ਬਣਾਏਗਾ।
ਜੇ ਟੁਕੜੇ ਖਿੱਚੇ ਜਾ ਕੇ ਵੱਖ ਹੋ ਗਏ ਹਨ, ਜਾਂ ਕੂਹਣੀ ਦਾ ਜੋੜ ਅਸਥਿਰ ਹੈ, ਤਾਂ ਅਸੀਂ ਆਮ ਤੌਰ 'ਤੇ ਸ਼ੁਰੂ ਤੋਂ ਹੀ ਸਰਜਰੀ ਦੀ ਸਲਾਹ ਦੇਵਾਂਗੇ। ਇਸ ਦਾ ਮਕਸਦ ਟੁਕੜਿਆਂ ਨੂੰ ਸਹੀ ਥਾਂ ਉੱਤੇ ਟਿਕਾ ਕੇ ਰੱਖਣਾ ਹੈ ਤਾਂ ਜੋ ਹੱਡੀ ਜੁੜ ਸਕੇ ਅਤੇ ਤੁਸੀਂ ਜਲਦੀ ਹਿਲਜੁਲ ਸ਼ੁਰੂ ਕਰ ਸਕੋ। ਹੱਡੀ ਨੂੰ ਕਿਵੇਂ ਟਿਕਾ ਕੇ ਰੱਖਣਾ ਹੈ, ਇਸ ਦੀ ਚੋਣ ਫ੍ਰੈਕਚਰ ਦੀ ਬਣਤਰ ਉੱਤੇ ਨਿਰਭਰ ਕਰਦੀ ਹੈ, ਅਤੇ ਕੋਈ ਇੱਕ ਤਰੀਕਾ ਹਰ ਫ੍ਰੈਕਚਰ ਲਈ ਢੁਕਵਾਂ ਨਹੀਂ ਹੁੰਦਾ। ਕਈ ਵਾਰ ਦੋਵੇਂ ਰਾਹ ਸੱਚਮੁੱਚ ਖੁੱਲ੍ਹੇ ਹੁੰਦੇ ਹਨ, ਉਦਾਹਰਨ ਲਈ ਖਿਸਕੇ ਹੋਏ ਫ੍ਰੈਕਚਰ ਵਾਲੇ ਕਿਸੇ ਵੱਡੀ ਉਮਰ ਦੇ ਮਰੀਜ਼ ਵਿੱਚ। ਅਸੀਂ ਉਹਨਾਂ ਗੱਲਾਂ ਬਾਰੇ ਗੱਲ ਕਰਾਂਗੇ ਜੋ ਤੁਹਾਡੇ ਲਈ ਅਹਿਮ ਹਨ: ਤੁਸੀਂ ਕਿੰਨਾ ਦਰਦ ਸਹਿਣ ਲਈ ਤਿਆਰ ਹੋ, ਅਤੇ ਕੀ ਸਿੱਧਾ ਕਰਨ ਦੀਆਂ ਆਖ਼ਰੀ ਕੁਝ ਡਿਗਰੀਆਂ ਗੁਆਉਣਾ ਤੁਹਾਨੂੰ ਪਰੇਸ਼ਾਨ ਕਰੇਗਾ।
ਤੁਸੀਂ ਜਿਹੜਾ ਵੀ ਰਾਹ ਚੁਣੋ, ਪਹਿਲੇ ਹਫ਼ਤੇ ਮਿਲਦੇ-ਜੁਲਦੇ ਹੁੰਦੇ ਹਨ। ਜਦੋਂ ਤੱਕ ਸੋਜ ਘਟਦੀ ਹੈ, ਦਰਦ ਤੋਂ ਰਾਹਤ ਤੁਹਾਨੂੰ ਆਰਾਮ ਵਿੱਚ ਰੱਖਦੀ ਹੈ। ਹੱਡੀ ਜੁੜਨ ਦੌਰਾਨ ਸੱਟ ਨੂੰ ਬਚਾ ਕੇ ਰੱਖਣ ਦੀ ਲੋੜ ਹੁੰਦੀ ਹੈ, ਅਤੇ ਅਸੀਂ ਤੁਹਾਨੂੰ ਦੱਸਾਂਗੇ ਕਿ ਤੁਸੀਂ ਬਾਂਹ ਨਾਲ ਕੀ ਕਰ ਸਕਦੇ ਹੋ ਅਤੇ ਕੀ ਨਹੀਂ ਕਰ ਸਕਦੇ। ਤੁਹਾਡਾ ਹੈਂਡ ਥੈਰੇਪਿਸਟ ਸਹੀ ਪੜਾਅ ਉੱਤੇ ਤੁਹਾਡੀ ਹਿਲਜੁਲ ਵਿੱਚ ਅਗਵਾਈ ਕਰੇਗਾ, ਸ਼ੁਰੂ ਵਿੱਚ ਹੌਲੀ-ਹੌਲੀ, ਅਤੇ ਜਿਵੇਂ-ਜਿਵੇਂ ਹੱਡੀ ਜੁੜਦੀ ਹੈ ਉਵੇਂ-ਉਵੇਂ ਵਧਾਉਂਦੇ ਹੋਏ। ਇਹਨਾਂ ਵਿੱਚੋਂ ਜ਼ਿਆਦਾਤਰ ਫ੍ਰੈਕਚਰ ਚੰਗੀ ਤਰ੍ਹਾਂ ਜੁੜ ਜਾਂਦੇ ਹਨ, ਹਾਲਾਂਕਿ ਕੂਹਣੀ ਦੇ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧਾ ਹੋਣ ਵਿੱਚ ਥੋੜ੍ਹੀ ਕਮੀ ਰਹਿ ਜਾਣਾ ਆਮ ਹੈ। ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਚਮੜੀ ਦੇ ਬਿਲਕੁਲ ਹੇਠਾਂ ਪਿਆ ਧਾਤ ਦਾ ਸਾਮਾਨ (metalwork) ਤਕਲੀਫ਼ ਦੇ ਸਕਦਾ ਹੈ, ਅਤੇ ਕੁਝ ਲੋਕਾਂ ਨੂੰ ਬਾਅਦ ਵਿੱਚ ਇਸ ਨੂੰ ਕੱਢਣ ਲਈ ਇੱਕ ਛੋਟੇ ਓਪਰੇਸ਼ਨ ਦੀ ਲੋੜ ਪੈਂਦੀ ਹੈ।
ਕੀ ਉਮੀਦ ਰੱਖੀਏ
ਇਹਨਾਂ ਵਿੱਚੋਂ ਜ਼ਿਆਦਾਤਰ ਫ੍ਰੈਕਚਰ ਚੰਗੀ ਤਰ੍ਹਾਂ ਜੁੜ ਜਾਂਦੇ ਹਨ। ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧਾ ਹੋਣ ਵਿੱਚ ਥੋੜ੍ਹੀ ਕਮੀ ਆਮ ਹੈ, ਅਤੇ ਜ਼ਿਆਦਾਤਰ ਲੋਕ ਆਪਣੀ ਬਾਂਹ ਨੂੰ ਚੰਗੀ ਤਰ੍ਹਾਂ ਵਰਤ ਸਕਦੇ ਹਨ। ਗੁੰਝਲਦਾਰ ਫ੍ਰੈਕਚਰਾਂ ਦੀ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਲੰਮੇ ਸਮੇਂ ਦੇ ਨਤੀਜੇ ਚੰਗੇ ਹੁੰਦੇ ਹਨ, ਭਾਵੇਂ ਬਾਅਦ ਦੇ ਐਕਸ-ਰੇ ਉੱਤੇ ਜੋੜ ਵਿੱਚ ਘਿਸਾਈ ਵਾਲਾ ਕੁਝ ਗਠੀਆ (ਆਰਥਰਾਈਟਿਸ) ਦਿਸਣ ਲੱਗ ਪਵੇ।
ਜੇ ਤੁਹਾਡੇ ਫ੍ਰੈਕਚਰ ਨੂੰ ਸਪਲਿੰਟ ਜਾਂ ਪਲੱਸਤਰ ਵਿੱਚ ਸਥਿਰ ਰੱਖਿਆ ਜਾਂਦਾ ਹੈ, ਤਾਂ ਹੱਡੀ ਦਿਨਾਂ ਵਿੱਚ ਨਹੀਂ ਸਗੋਂ ਹਫ਼ਤਿਆਂ ਵਿੱਚ ਜੁੜਦੀ ਹੈ। ਤੁਹਾਡੇ ਵਾਰ-ਵਾਰ ਐਕਸ-ਰੇ ਹੋਣਗੇ ਤਾਂ ਜੋ ਪੱਕਾ ਹੋ ਸਕੇ ਕਿ ਟੁਕੜੇ ਆਪਣੀ ਸਹੀ ਥਾਂ ਉੱਤੇ ਹੀ ਰਹਿਣ। ਇਹ ਰਾਹ ਵੱਡੀ ਉਮਰ ਦੇ ਮਰੀਜ਼ਾਂ ਲਈ ਅਤੇ ਉਹਨਾਂ ਲੋਕਾਂ ਲਈ ਢੁਕਵਾਂ ਹੈ ਜਿਨ੍ਹਾਂ ਦੀ ਬਾਂਹ ਭਾਰੀ ਕੰਮ ਦੀ ਬਜਾਏ ਰੋਜ਼ਾਨਾ ਦੇ ਕੰਮ ਕਰਦੀ ਹੈ। ਉਸ ਸਮੂਹ ਵਿੱਚ ਥੋੜ੍ਹੇ ਸਮੇਂ ਅਤੇ ਲੰਮੇ ਸਮੇਂ, ਦੋਵਾਂ ਵਿੱਚ ਨਤੀਜੇ ਤਸੱਲੀਬਖ਼ਸ਼ ਹੁੰਦੇ ਹਨ। ਇਸ ਦਾ ਨੁਕਸਾਨ ਇਹ ਹੈ ਕਿ ਅਖ਼ੀਰ ਵਿੱਚ ਕੂਹਣੀ ਸ਼ਾਇਦ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧੀ ਨਾ ਹੋਵੇ।
ਜੇ ਤੁਹਾਡੀ ਸਰਜਰੀ ਹੁੰਦੀ ਹੈ, ਤਾਂ ਹੱਡੀ ਜੁੜਨ ਦੌਰਾਨ ਉਸ ਨੂੰ ਧਾਤ ਨਾਲ ਥਾਂ ਸਿਰ ਟਿਕਾ ਕੇ ਰੱਖਿਆ ਜਾਂਦਾ ਹੈ। ਹਿਲਜੁਲ ਜਲਦੀ ਸ਼ੁਰੂ ਹੁੰਦੀ ਹੈ ਅਤੇ ਤੁਹਾਡੇ ਹੈਂਡ ਥੈਰੇਪਿਸਟ ਨਾਲ ਪੜਾਅਵਾਰ ਵਧਦੀ ਹੈ। ਤੁਸੀਂ ਜਿਹੜਾ ਵੀ ਰਾਹ ਚੁਣੋ, ਇਸ ਸੱਟ ਤੋਂ ਬਾਅਦ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧਾ ਹੋਣ ਵਿੱਚ ਕੁਝ ਕਮੀ ਦੀ ਉਮੀਦ ਹੁੰਦੀ ਹੈ। ਖਿਸਕੇ ਹੋਏ ਫ੍ਰੈਕਚਰ ਲਈ ਸਰਜਰੀ ਕਰਵਾਉਣ ਵਾਲੇ ਲੋਕਾਂ ਬਾਰੇ ਇੱਕ ਲੰਮੇ ਸਮੇਂ ਦੀ ਪੜਤਾਲ ਵਿੱਚ, ਸੱਟ ਤੋਂ 25 ਸਾਲ ਬਾਅਦ ਤੱਕ 96% ਲੋਕਾਂ ਦੇ ਨਤੀਜੇ ਚੰਗੇ ਜਾਂ ਬਹੁਤ ਵਧੀਆ ਸਨ।
ਠੀਕ ਹੋਣਾ ਤੁਹਾਡੇ ਆਮ ਕੰਮਾਂ ਵੱਲ ਹੌਲੀ-ਹੌਲੀ ਵਾਪਸੀ ਹੈ। ਪਹਿਲਾਂ ਹਲਕੇ ਰੋਜ਼ਾਨਾ ਕੰਮ ਵਾਪਸ ਆਉਂਦੇ ਹਨ, ਫਿਰ ਜਿਵੇਂ-ਜਿਵੇਂ ਹੱਡੀ ਮਜ਼ਬੂਤ ਹੁੰਦੀ ਹੈ, ਭਾਰ ਚੁੱਕਣਾ ਅਤੇ ਬਾਂਹ ਦੀ ਭਾਰੀ ਵਰਤੋਂ। ਤੁਸੀਂ ਕਿੰਨੀ ਜਲਦੀ ਗੱਡੀ ਚਲਾ ਸਕਦੇ ਹੋ, ਕੰਮ ਕਰ ਸਕਦੇ ਹੋ ਜਾਂ ਖੇਡ ਸਕਦੇ ਹੋ, ਇਹ ਤੁਹਾਡੇ ਕੰਮ, ਤੁਹਾਡੀ ਬਾਂਹ ਅਤੇ ਹੱਡੀ ਦੇ ਜੁੜਨ ਉੱਤੇ ਨਿਰਭਰ ਕਰਦਾ ਹੈ, ਅਤੇ ਅਸੀਂ ਹਰ ਪੜਾਅ ਬਾਰੇ ਤੁਹਾਡੇ ਨਾਲ ਗੱਲ ਕਰਾਂਗੇ।
ਜੋ ਗੱਲਾਂ ਗ਼ਲਤ ਹੋ ਸਕਦੀਆਂ ਹਨ, ਉਹਨਾਂ ਬਾਰੇ ਜਾਣਨਾ ਚੰਗਾ ਹੈ। ਧਾਤ ਦਾ ਸਾਮਾਨ ਕੂਹਣੀ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਚਮੜੀ ਦੇ ਬਿਲਕੁਲ ਹੇਠਾਂ ਹੁੰਦਾ ਹੈ, ਅਤੇ ਇਹ ਇੰਨੀ ਤਕਲੀਫ਼ ਦੇ ਸਕਦਾ ਹੈ ਕਿ ਕੁਝ ਲੋਕ ਬਾਅਦ ਵਿੱਚ ਇਸ ਨੂੰ ਕਢਵਾਉਣ ਦਾ ਫ਼ੈਸਲਾ ਕਰਦੇ ਹਨ। ਇਸ ਸਰਜਰੀ ਤੋਂ ਬਾਅਦ ਇਹ ਵਾਰ-ਵਾਰ ਸਾਹਮਣੇ ਆਉਣ ਵਾਲੀ ਸਮੱਸਿਆ ਹੈ। ਹੋਰ ਸਮੱਸਿਆਵਾਂ, ਜਿਵੇਂ ਹੱਡੀ ਦਾ ਗ਼ਲਤ ਸਥਿਤੀ ਵਿੱਚ ਜੁੜਨਾ ਜਾਂ ਕੂਹਣੀ ਦਾ ਅਕੜੀ ਰਹਿ ਜਾਣਾ, ਘੱਟ ਆਮ ਹਨ। ਜੇ ਤੁਹਾਡੇ ਲੱਛਣ ਠੀਕ ਨਹੀਂ ਹੋ ਰਹੇ, ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਜਾਂ ਰਾਤ ਨੂੰ ਤੁਹਾਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾ ਰਹੇ ਹਨ, ਤਾਂ ਆਪਣੇ ਜੀਪੀ ਨੂੰ ਮਿਲੋ ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ। ਜੇ ਤੁਸੀਂ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਹੀਂ ਕਰ ਸਕਦੇ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਡਾਕਟਰ ਨੂੰ ਕਦੋਂ ਮਿਲਣਾ ਚਾਹੀਦਾ ਹੈ
ਫ਼ੌਰੀ ਇਲਾਜ ਲਓ ਜੇ ਤੁਹਾਡੀ ਕੂਹਣੀ ਸਾਫ਼ ਤੌਰ 'ਤੇ ਆਪਣੀ ਸ਼ਕਲ ਤੋਂ ਵਿਗੜੀ ਹੋਈ ਦਿਸੇ, ਜੇ ਸੱਟ ਵਾਲੀ ਥਾਂ ਉੱਤੇ ਚਮੜੀ ਫਟੀ ਹੋਵੇ, ਜਾਂ ਜੇ ਤੁਹਾਡਾ ਹੱਥ ਜਾਂ ਉਂਗਲਾਂ ਫਿੱਕੀਆਂ, ਠੰਢੀਆਂ, ਸਫ਼ੈਦ ਜਾਂ ਨੀਲੀਆਂ ਪੈ ਜਾਣ। ਸੱਟ ਤੋਂ ਬਾਅਦ ਜੇ ਬਾਂਹ ਅਚਾਨਕ ਸੁੰਨ ਹੋ ਜਾਵੇ ਜਾਂ ਹਿਲਣੋਂ ਰਹਿ ਜਾਵੇ, ਤਾਂ ਵੀ ਉਸੇ ਦਿਨ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ। ਇਹਨਾਂ ਨਿਸ਼ਾਨੀਆਂ ਦਾ ਮਤਲਬ ਹੈ ਕਿ ਸੱਟ ਦੀ ਤੁਰੰਤ ਜਾਂਚ ਹੋਣੀ ਚਾਹੀਦੀ ਹੈ।
ਬਾਕੀ ਸਭ ਹਾਲਤਾਂ ਵਿੱਚ, ਸ਼ੁਰੂਆਤ ਆਪਣੇ ਜੀਪੀ ਤੋਂ ਕਰੋ। ਉਹ ਤੁਹਾਡੀ ਬਾਂਹ ਦੀ ਜਾਂਚ ਕਰ ਸਕਦੇ ਹਨ ਅਤੇ ਐਕਸ-ਰੇ ਦਾ ਪ੍ਰਬੰਧ ਕਰ ਸਕਦੇ ਹਨ, ਜੋ ਇਸ ਕਿਸਮ ਦੇ ਫ੍ਰੈਕਚਰ ਨੂੰ ਦਿਖਾਉਣ ਲਈ ਆਮ ਤੌਰ 'ਤੇ ਕਾਫ਼ੀ ਹੁੰਦੇ ਹਨ। ਜੇ ਤੁਹਾਡਾ ਜੀਪੀ ਸਮਝਦਾ ਹੈ ਕਿ ਮਾਹਰ ਡਾਕਟਰ ਨੂੰ ਇਲਾਜ ਸੰਭਾਲਣਾ ਚਾਹੀਦਾ ਹੈ, ਤਾਂ ਉਹ ਤੁਹਾਨੂੰ ਜਾਂਚ ਲਈ ਰੈਫ਼ਰ ਕਰਨਗੇ।
ਦੁਬਾਰਾ ਆਓ, ਜਾਂ ਮਾਹਰ ਡਾਕਟਰ ਤੋਂ ਜਾਂਚ ਕਰਵਾਉਣ ਲਈ ਕਹੋ, ਜੇ ਦਰਦ ਘੱਟ ਨਹੀਂ ਹੋ ਰਿਹਾ, ਜਾਂ ਜੇ ਹੱਡੀ ਜੁੜਨ ਦੌਰਾਨ ਤੁਹਾਡੀ ਬਾਂਹ ਦੀ ਸੋਜ, ਹਿਲਜੁਲ ਜਾਂ ਵਰਤੋਂ ਹਫ਼ਤਾ-ਦਰ-ਹਫ਼ਤਾ ਬਿਹਤਰ ਨਹੀਂ ਹੋ ਰਹੀ। ਜੋ ਲੱਛਣ ਹਫ਼ਤਿਆਂ ਦੌਰਾਨ ਵਿਗੜ ਰਹੇ ਹਨ, ਰਾਤ ਨੂੰ ਤੁਹਾਨੂੰ ਨੀਂਦ ਤੋਂ ਜਗਾ ਰਹੇ ਹਨ, ਜਾਂ ਤੁਹਾਨੂੰ ਕੰਮ ਕਰਨ ਜਾਂ ਬਾਂਹ ਵਰਤਣ ਤੋਂ ਰੋਕ ਰਹੇ ਹਨ, ਉਹਨਾਂ ਦੀ ਵੀ ਦੁਬਾਰਾ ਜਾਂਚ ਹੋਣੀ ਚਾਹੀਦੀ ਹੈ। ਜੇ ਤੁਸੀਂ ਕਲੀਨਿਕ ਨਾਲ ਸੰਪਰਕ ਨਹੀਂ ਕਰ ਸਕਦੇ, ਤਾਂ ਆਪਣੇ ਸਭ ਤੋਂ ਨੇੜਲੇ ਐਮਰਜੈਂਸੀ ਵਿਭਾਗ ਜਾਓ।
ਵਿਸਥਾਰ ਵਿੱਚ
Advanced reading: the deeper science (optional)
ਇਹ ਹਿੱਸਾ ਤੁਹਾਡੇ ਆਪਣੇ ਇਲਾਜ ਦੇ ਫ਼ੈਸਲਿਆਂ ਲਈ ਲੋੜ ਤੋਂ ਜ਼ਿਆਦਾ ਡੂੰਘਾਈ ਵਿੱਚ ਜਾਂਦਾ ਹੈ। ਓਲੇਕ੍ਰੈਨਨ ਫ੍ਰੈਕਚਰ ਬਾਰੇ ਵਾਧੂ ਪੜ੍ਹਨਾ ਇੱਕ ਅਜਿਹੀ ਖੋਜ ਕਾਰਨ ਲਾਭਦਾਇਕ ਹੈ ਜੋ ਫ੍ਰੈਕਚਰ ਸਰਜਰੀ ਦੇ ਆਮ ਤਰਕ ਨੂੰ ਉਲਟਾ ਦਿੰਦੀ ਹੈ: ਵੱਡੀ ਉਮਰ ਦੇ ਮਰੀਜ਼ਾਂ ਵਿੱਚ, ਓਲੇਕ੍ਰੈਨਨ ਦੇ ਥਾਂ ਤੋਂ ਹਿੱਲੇ ਫ੍ਰੈਕਚਰ ਨੂੰ ਬਿਨਾਂ ਜੋੜੇ ਛੱਡਿਆ ਜਾ ਸਕਦਾ ਹੈ, ਅਤੇ ਕੂਹਣੀ ਫਿਰ ਵੀ ਕੰਮ ਕਰਦੀ ਹੈ।
ਥਾਂ ਤੋਂ ਹਿੱਲਿਆ ਫ੍ਰੈਕਚਰ ਜਿਸ ਨੂੰ ਜੋੜਨ ਦੀ ਲੋੜ ਨਹੀਂ
ਓਲੇਕ੍ਰੈਨਨ ਵਿੱਚੋਂ ਲੰਘਦਾ ਫ੍ਰੈਕਚਰ ਟ੍ਰਾਈਸੈਪਸ (triceps, ਬਾਂਹ ਦੇ ਪਿਛਲੇ ਪਾਸੇ ਦੀ ਮਾਸਪੇਸ਼ੀ) ਨੂੰ ਬਾਂਹ ਦੇ ਹੇਠਲੇ ਹਿੱਸੇ (forearm) ਤੋਂ ਵੱਖ ਕਰ ਦਿੰਦਾ ਹੈ, ਇਸ ਲਈ ਆਮ ਤਰਕ ਇਹ ਹੈ ਕਿ ਇਸ ਨੂੰ ਮੁੜ ਜੋੜਨਾ ਜ਼ਰੂਰੀ ਹੈ ਨਹੀਂ ਤਾਂ ਕੂਹਣੀ ਜ਼ੋਰ ਦੇ ਵਿਰੁੱਧ ਸਿੱਧੀ ਨਹੀਂ ਹੋ ਸਕਦੀ। 70 ਸਾਲ ਤੋਂ ਵੱਡੀ ਉਮਰ ਦੇ ਮਰੀਜ਼ਾਂ ਵਿੱਚ, ਇਹ ਤਰਕ ਟਿਕਦਾ ਨਹੀਂ। ਇੱਕ ਸਿਸਟਮੈਟਿਕ ਸਮੀਖਿਆ (systematic review) ਵਿੱਚ ਪਾਇਆ ਗਿਆ ਕਿ ਇਸ ਸਮੂਹ ਵਿੱਚ ਓਲੇਕ੍ਰੈਨਨ ਦੇ ਥਾਂ ਤੋਂ ਹਿੱਲੇ ਫ੍ਰੈਕਚਰਾਂ ਦਾ ਬਿਨਾਂ ਓਪਰੇਸ਼ਨ ਦੇ ਅਸਰਦਾਰ ਢੰਗ ਨਾਲ ਇਲਾਜ ਕੀਤਾ ਜਾ ਸਕਦਾ ਹੈ, ਜਿਸ ਨਾਲ ਮਰੀਜ਼ਾਂ ਦੀ ਸੰਤੁਸ਼ਟੀ ਉੱਚੀ ਰਹਿੰਦੀ ਹੈ ਅਤੇ ਕੰਮ ਚਲਾਉਣ ਯੋਗ ਹਿਲਜੁਲ ਮਿਲਦੀ ਹੈ [1]।
ਜੋ ਗੁਆਇਆ ਜਾਂਦਾ ਹੈ ਉਹ ਮਾਪਿਆ ਜਾ ਸਕਦਾ ਹੈ: ਐਕਸਟੈਂਸ਼ਨ ਲੈਗ (extension lag), ਯਾਨੀ ਕੂਹਣੀ ਨੂੰ ਪੂਰੀ ਤਰ੍ਹਾਂ ਸਿੱਧਾ ਨਾ ਕਰ ਸਕਣਾ, ਅਤੇ ਸਿੱਧਾ ਕਰਨ ਦੀ ਤਾਕਤ ਵਿੱਚ ਕਮੀ। ਜਿਸ ਤੋਂ ਬਚਿਆ ਜਾਂਦਾ ਹੈ ਉਹ ਹੈ ਪਤਲੀ, ਅਕਸਰ ਨਾਜ਼ੁਕ ਚਮੜੀ ਵਿੱਚ ਚਮੜੀ ਦੇ ਬਿਲਕੁਲ ਹੇਠਾਂ ਵਾਲੀ ਹੱਡੀ ਉੱਤੇ ਜ਼ਖ਼ਮ, ਅਤੇ ਉਸ ਚਮੜੀ ਦੇ ਹੇਠਾਂ ਧਾਤ ਦਾ ਸਾਮਾਨ। ਕਿਉਂਕਿ ਓਲੇਕ੍ਰੈਨਨ ਨੂੰ ਜੋੜਨ ਤੋਂ ਬਾਅਦ ਦੂਜੇ ਓਪਰੇਸ਼ਨ ਦਾ ਸਭ ਤੋਂ ਆਮ ਕਾਰਨ ਉੱਭਰਿਆ ਹੋਇਆ ਧਾਤ ਦਾ ਸਾਮਾਨ ਹੁੰਦਾ ਹੈ, ਇਸ ਤੋਂ ਬਚਣ ਨਾਲ ਸਭ ਤੋਂ ਆਮ ਪੇਚੀਦਗੀ ਪੂਰੀ ਤਰ੍ਹਾਂ ਖ਼ਤਮ ਹੋ ਜਾਂਦੀ ਹੈ।
ਕਿਸੇ ਵੱਡੀ ਉਮਰ ਦੇ ਵਿਅਕਤੀ ਲਈ, ਜਿਸ ਦੀ ਬਾਂਹ ਜ਼ੋਰ ਨਾਲ ਧੱਕਣ ਦੀ ਬਜਾਏ ਰੋਜ਼ਾਨਾ ਦੇ ਕੰਮਾਂ ਲਈ ਵਰਤੀ ਜਾਂਦੀ ਹੈ, ਅਜਿਹੀ ਕੂਹਣੀ ਜੋ ਆਖ਼ਰੀ ਕੁਝ ਡਿਗਰੀਆਂ ਤੱਕ ਸਿੱਧੀ ਨਹੀਂ ਹੁੰਦੀ, ਜ਼ਖ਼ਮ ਦੀ ਪੇਚੀਦਗੀ ਨਾਲੋਂ ਛੋਟਾ ਬੋਝ ਹੈ। ਕਿਸੇ ਜਵਾਨ ਜਾਂ ਜ਼ਿਆਦਾ ਮੰਗ ਵਾਲੇ ਮਰੀਜ਼ ਲਈ ਇਹ ਅਜਿਹਾ ਨਹੀਂ ਹੈ, ਇਸੇ ਲਈ ਇਹ ਖੋਜ ਆਮ ਨਹੀਂ ਸਗੋਂ ਉਮਰ ਨਾਲ ਖ਼ਾਸ ਤੌਰ 'ਤੇ ਜੁੜੀ ਹੋਈ ਹੈ।
ਜਿੱਥੇ ਹੱਡੀ ਜੋੜੀ ਜਾਂਦੀ ਹੈ, ਉੱਥੇ ਇੰਪਲਾਂਟ ਦੀ ਚੋਣ ਵਿੱਚ ਫ਼ਰਕ ਸਾਹਮਣੇ ਆਇਆ ਹੈ
ਥਾਂ ਤੋਂ ਹਿੱਲੇ ਪਰ ਸਧਾਰਨ ਆਮ ਫ੍ਰੈਕਚਰ ਲਈ, ਦੋ ਇੰਪਲਾਂਟਾਂ ਵਿੱਚ ਮੁਕਾਬਲਾ ਹੈ: ਤਾਰਾਂ ਨਾਲ ਬਣਿਆ ਟੈਂਸ਼ਨ ਬੈਂਡ (tension band, ਤਾਰਾਂ ਨਾਲ ਹੱਡੀ ਨੂੰ ਕੱਸ ਕੇ ਜੋੜਨਾ) ਅਤੇ ਇੱਕ ਪਲੇਟ। ਮੇਯੋ ਟਾਈਪ II (Mayo type II) ਫ੍ਰੈਕਚਰਾਂ ਵਾਲੇ 827 ਮਰੀਜ਼ਾਂ ਵਿੱਚ, ਟੈਂਸ਼ਨ ਬੈਂਡ ਵਾਇਰਿੰਗ ਨਾਲੋਂ ਪਲੇਟ ਨਾਲ ਜੋੜਨ ਨੇ ਬਿਹਤਰ ਅਸਰ ਅਤੇ ਸੁਰੱਖਿਆ ਦਿਖਾਈ, ਅਤੇ ਲੇਖਕਾਂ ਨੇ ਦੱਸਿਆ ਕਿ ਥੋੜ੍ਹੇ ਅਧਿਐਨ ਸ਼ਾਮਲ ਕੀਤੇ ਗਏ ਸਨ ਅਤੇ ਅਜੇ ਵੀ ਵਧੇਰੇ ਉੱਚ-ਗੁਣਵੱਤਾ ਵਾਲੇ ਰੈਂਡਮਾਈਜ਼ਡ ਟ੍ਰਾਇਲਾਂ (randomised trials) ਦੀ ਲੋੜ ਹੈ [2]। 472 ਮਰੀਜ਼ਾਂ ਦੀ 2025 ਦੀ ਇੱਕ ਸਮੀਖਿਆ, ਜਿਸ ਵਿੱਚ ਜੋੜਨ ਦੀਆਂ ਆਧੁਨਿਕ ਤਕਨੀਕਾਂ ਦੀ ਤੁਲਨਾ ਰਵਾਇਤੀ ਟੈਂਸ਼ਨ ਬੈਂਡ ਵਾਇਰਿੰਗ ਨਾਲ ਕੀਤੀ ਗਈ, ਵੀ ਇਸੇ ਦਿਸ਼ਾ ਵੱਲ ਇਸ਼ਾਰਾ ਕਰਦੀ ਹੈ [3]।
ਇਹ ਇਸ ਸਾਈਟ ਉੱਤੇ ਉਨ੍ਹਾਂ ਥੋੜ੍ਹੀਆਂ ਥਾਵਾਂ ਵਿੱਚੋਂ ਇੱਕ ਹੈ ਜਿੱਥੇ ਤਕਨੀਕਾਂ ਦੀ ਤੁਲਨਾ ਮੋਢੇ ਉਚਕਾਉਣ ਦੀ ਬਜਾਏ ਇੱਕ ਸਾਫ਼ ਦਿਸ਼ਾ ਦਿੰਦੀ ਹੈ। ਲੇਖਕਾਂ ਨੇ ਖ਼ੁਦ ਸਬੂਤਾਂ ਦੇ ਆਧਾਰ ਦੀਆਂ ਜਿਨ੍ਹਾਂ ਕਮੀਆਂ ਵੱਲ ਧਿਆਨ ਦਿਵਾਇਆ ਹੈ, ਉਨ੍ਹਾਂ ਨੂੰ ਦੇਖਦੇ ਹੋਏ ਇਸ ਨੂੰ ਹਲਕੇ ਹੱਥੀਂ ਹੀ ਲੈਣਾ ਚਾਹੀਦਾ ਹੈ।
ਗਠੀਆ ਹੋ ਜਾਂਦਾ ਹੈ, ਅਤੇ ਜ਼ਿਆਦਾਤਰ ਕੋਈ ਫ਼ਰਕ ਨਹੀਂ ਪਾਉਂਦਾ
ਜਦੋਂ ਲੰਮੇ ਸਮੇਂ ਬਾਅਦ ਦੀਆਂ ਇਮੇਜਿੰਗ ਖੋਜਾਂ ਨੂੰ ਪ੍ਰਸੰਗ ਤੋਂ ਬਿਨਾਂ ਦੱਸਿਆ ਜਾਂਦਾ ਹੈ ਤਾਂ ਉਹ ਡਰਾਉਣੀਆਂ ਲੱਗ ਸਕਦੀਆਂ ਹਨ। ਇਕੱਲੇ ਓਲੇਕ੍ਰੈਨਨ ਫ੍ਰੈਕਚਰਾਂ ਤੋਂ ਬਾਅਦ, 41 ਮਹੀਨਿਆਂ ਦੀ ਮੱਧਮ (median) ਨਿਗਰਾਨੀ ਉੱਤੇ ਸੱਟ ਤੋਂ ਬਾਅਦ ਵਾਲੇ ਓਸਟੀਓਆਰਥਰਾਈਟਿਸ (ਜੋੜਾਂ ਦਾ ਘਿਸਣਾ) ਦੀ ਮੱਧਮ ਦਰ 19% ਸੀ, ਅਤੇ ਮਰੀਜ਼ਾਂ ਵੱਲੋਂ ਦੱਸੇ ਅੰਤਿਮ ਨਤੀਜੇ ਫ੍ਰੈਕਚਰ ਦੀ ਕਿਸਮ ਜਾਂ ਗਠੀਏ ਦੀ ਮੌਜੂਦਗੀ ਦੀ ਪਰਵਾਹ ਕੀਤੇ ਬਿਨਾਂ ਚੰਗੇ ਤੋਂ ਸ਼ਾਨਦਾਰ ਤੱਕ ਸਨ [4]।
ਉਸ ਵਾਕ ਦੇ ਦੋਵੇਂ ਹਿੱਸੇ ਅਹਿਮ ਹਨ। ਇਸ ਸੱਟ ਤੋਂ ਬਾਅਦ ਨਿਗਰਾਨੀ ਵਾਲੇ ਐਕਸ-ਰੇ ਉੱਤੇ ਗਠੀਆ ਆਮ ਹੈ। ਇਸ ਸਮੇਂ ਦੇ ਅੰਦਰ, ਇਸ ਦਾ ਇਸ ਗੱਲ ਨਾਲ ਵੀ ਜ਼ਿਆਦਾਤਰ ਕੋਈ ਸਬੰਧ ਨਹੀਂ ਹੁੰਦਾ ਕਿ ਲੋਕ ਆਪਣੀ ਕੂਹਣੀ ਦੇ ਕੰਮਕਾਜ ਬਾਰੇ ਕੀ ਦੱਸਦੇ ਹਨ। ਐਕਸ-ਰੇ ਉੱਤੇ ਦਿਸਣ ਵਾਲੀ ਚੀਜ਼ ਆਪਣੇ ਆਪ ਕੋਈ ਡਾਕਟਰੀ ਸਮੱਸਿਆ ਨਹੀਂ ਹੁੰਦੀ, ਅਤੇ ਇਕੱਲੀ ਇਹ ਗੱਲ ਹੋਰ ਇਲਾਜ ਸ਼ੁਰੂ ਕਰਨ ਦਾ ਕਾਰਨ ਨਹੀਂ ਬਣਨੀ ਚਾਹੀਦੀ।
ਹਵਾਲੇ
[1] Alvara CA, Biedron G, Dunn JC. Nonoperative management of olecranon fractures in elderly patients: a systematic review. Hand (N Y). 2020;17(4):734-9. https://doi.org/10.1177/1558944720944261
[2] Jia Y, Liu A, Guo T, Chen J, Yu W, Zhai J. Efficacy and safety of tension band wire versus plate for Mayo II olecranon fractures: a systematic review and meta-analysis. J Orthop Surg Res. 2022;17(1). https://doi.org/10.1186/s13018-022-03262-7
[3] Wang C, Li C. Modern fixation techniques versus traditional tension band wiring for olecranon fractures: a systematic review and meta-analysis. J Orthop Surg Res. 2025;20(1). https://doi.org/10.1186/s13018-025-06061-y
[4] Wiersma JP, de Klerk HH, Priester-Vink S, Doornberg JN, Bhasyam AR, van den Bekerom MP. Incidence of post-traumatic osteoarthritis in olecranon fractures and the role of fracture type: a systematic review. J Shoulder Elbow Surg. 2026. https://doi.org/10.1016/j.jse.2026.02.024
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
General Outcomes and Complications
- A majority of olecranon fractures heal uneventfully with good or excellent results, with a small loss of motion expected [11].
- 96% of individuals with a closed displaced fracture of the olecranon treated by open reduction and internal fixation had excellent or good outcomes up to 25 years after the fracture [4].
- Surgical treatment of olecranon fractures is associated with a high rate of complications [18].
- Patients undergoing revisions beyond implant removal after olecranon fracture fixation had poorer functional outcomes [18].
- No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method for olecranon fractures [18].
- The incidence of post-traumatic osteoarthritis following isolated olecranon fractures is 19% at a median follow-up of 41 months [22].
Operative Management
- No single technique is suitable for the management of all olecranon fractures [21].
- Low-profile double-plate osteosynthesis is a safe and effective alternative treatment for olecranon fractures with excellent subjective and objective clinical outcome measures [1].
- Plating of the olecranon leads to predictable union, though the most common complication was lack of full extension in 39% of patients [16].
- Both Kirschner wire tension band and anatomical locking plate procedures effectively treat Mayo type II olecranon fractures [9].
- Current randomized evidence suggests that tension band wiring and plate fixation may yield similar functional outcomes for displaced olecranon fractures, based on a limited number of randomized controlled trials [24].
- Tension band wiring remains an effective treatment for appropriately selected olecranon fractures and outperformed plate osteosynthesis in one cohort [40].
- The timing of fixation of displaced olecranon fractures does not significantly increase the rate of early complications or reoperation [15].
- Excision of the olecranon fragment with repair of the triceps mechanism is supported as a preferred method of treatment due to significantly less morbidity compared with internal fixation [65].
Non-Operative Management
- Close radiographic follow-up is recommended for nonsurgically treated olecranon fractures in children [2].
- Some isolated displaced (>2 mm) olecranon fractures in elderly patients can be successfully treated nonoperatively [6].
- Satisfactory short-term and long-term outcomes were found following the nonoperative management of isolated displaced olecranon fractures in older, lower-demand patients [13].
- Displaced olecranon fractures in patients older than 70 years may be effectively managed with nonoperative measures to produce high satisfaction and functional range of motion [23].
- Nonoperative management of olecranon fractures in elderly patients offers comparable functional outcomes to surgical intervention while significantly reducing exposure to potential complications and healthcare costs [41].
- Nonoperative treatment is a reasonable option for displaced stable olecranon fractures in elderly patients [29].
Elderly Population Specifics
- Olecranon fractures in the elderly have higher than expected 1-year mortality rates [5].
- Patients with olecranon fractures have essentially similar demographic characteristics compared to patients with distal radius fractures [10].
- The literature on the treatment of olecranon fractures in elderly patients is limited [7].
Anatomy & Pathophysiology
Bony Anatomy
- The olecranon and the coronoid process form the greater sigmoid notch, which articulates with the trochlea of the distal humerus [37].
- The intrinsic anatomy of the ulnohumeral articulation allows flexion/extension movement of the elbow joint and provides stability for the elbow [37].
- The olecranon serves as the insertion for the triceps tendon, which blends with the periosteum of the proximal ulna [37].
- The exposed, subcutaneous position of the olecranon renders it vulnerable to direct trauma and violent muscular contractions from the triceps [37].
- In children, the olecranon is predominantly cartilage, particularly in younger children, which reduces the chance of fracture occurring with a direct blow [48].
- In children, the thick periosteum and relatively thin metaphyseal cortex of the olecranon predispose it to minimally displaced greenstick fractures [48].
- Radiographic measurements of normal elbows guide the surgeon to obtain a more reliable length of the olecranon and maintain articular geometry during fixation [69].
Mechanisms of Injury
- Olecranon fractures can result from a direct blow, a fall on an outstretched hand with the elbow in flexion, or high-energy trauma associated with radial head fractures or elbow dislocation [37].
- Sudden and violent triceps muscle contraction can produce an avulsion fracture of varying size of the olecranon tip [37].
- A bimodal distribution of olecranon fractures is seen in young patients with high-energy trauma and elderly patients with low-energy trauma such as a fall from standing [37].
- Olecranon fractures typically occur as low-energy falls from standing in older patients or high-energy injury mechanisms in younger patients [38].
- The bone typically fails from a direct blow to the elbow or as a tensile force from the pull of the triceps tendon [38].
- Regardless of the mechanism of injury, the triceps acts as the main deforming mechanism pulling the fractured fragment proximally, creating a gap at the articular surface, and an incompetent extensor mechanism [38].
- In children, olecranon fractures are usually the result of a hyperextension injury [48].
- In children, flexion injuries are usually caused by a fall on an outstretched hand with the elbow flexed, resulting from a strong eccentric contraction of the triceps pulling the olecranon over the fulcrum of the distal humerus [48].
- In children, shear injuries result from a force to the proximal ulna just anterior to the humeral condyles, causing the olecranon to fracture through metaphyseal bone with anterior displacement of the distal fragment [48].
- Olecranon fractures commonly occur with a direct blow, generally resulting in comminuted fractures, or as an avulsion injury with triceps contracture [54].
- Contraction of the triceps often results in transverse or short oblique types of olecranon fractures [54].
- In children, hyperextension injuries are frequently associated with other elbow injuries, where the direction of the associated coronal plane force determines the corresponding injuries [48].
- In children, a valgus hyperextension force may produce an associated radial neck or medial epicondyle fracture [48].
- In children, a varus hyperextension injury may be associated with lateral dislocation of the radial head or a Bado type III Monteggia lesion [48].
- In children, flexion injuries are generally transverse (perpendicular to the axis of the ulna), displaced posteriorly rather than anteriorly, and rarely associated with other injuries [48].
Associated Injuries
- Olecranon fractures typically occur in isolation; however, given the subcutaneous location of the injury, there is a risk to soft tissues as well as risk of the fracture being open [38].
- In an epidemiologic study of olecranon fractures, 22% of patients had injuries to the ipsilateral limb and 6.4% of fractures were open [38].
- In children, olecranon fractures are associated with other elbow injuries (usually the medial epicondyle) in 20% to 50% of cases [48].
Classification
- The Mayo classification is the most common classification used for olecranon fractures, based on the amount of fracture displacement, the presence of comminution, and stability of the ulnohumeral joint [38].
- In the Mayo classification, Type I fractures are nondisplaced, Type II fractures are displaced, and Type III fractures have an unstable ulnohumeral joint [38].
- In the Mayo classification, modifier A indicates simple (noncomminuted) fractures and modifier B indicates comminuted fractures [38].
- The Mayo classification is simple to use, can help guide fracture management, and has good interobserver reliability [38].
- Displaced olecranon fracture lines entered along the medial side of the trochlear notch and exited at the base of the coronoid, while minimally displaced fractures entered and exited the trochlear notch at the base of the coronoid [38].
- The Schatzker and Colton classification attempted to classify olecranon fractures based on different fracture pattern morphology; however, its application was limited [38].
- A proposed fragment-specific classification system for complex olecranon fractures is anatomically based and considers the deforming forces from ligaments and tendons [64].
- In a study of 2462 fractures, the distribution included a larger share of comminuted central fractures (29%) compared to a single-center report from Scotland [8].
- In a study of 2462 fractures, an almost threefold larger share of distal olecranon fractures was observed compared to the 6.2% reported in a Scottish study of 64 olecranon fractures [8].
- In a study of 2462 fractures, the distribution differed from a single-center report from Scotland where 74% of the fractures were simple central fractures and 81% were central fractures [8].
Classification
Classification Systems and Reproducibility
- The Mayo classification is the most commonly used classification system in clinical practice for olecranon fractures [43].
- The Mayo classification consists of 3 types with a modifier to indicate comminution [43].
- Type I fractures in the Mayo classification are nondisplaced [43].
- Type II fractures in the Mayo classification are displaced [43].
- Type III fractures in the Mayo classification have accompanying injuries [43].
- The Mayo classification was designed to simplify categorization of olecranon fractures but does not achieve this goal due to poor reproducibility [27].
- Multiple classification systems for olecranon fractures exist, including AO, Mayo, Schatzker and Colton, but none are widely accepted or provide direct and reliable advice on operative strategies [88].
- The low reproducibility rates of existing olecranon fracture classification systems raise questions about their use in clinical and research contexts [88].
- The Colton classification had the best intra- and inter-observer agreement among the Mayo, AO/OTA, and Colton & Schatzker classifications [111].
- The AO classification subsumes olecranon fractures to proximal forearm injuries [88].
- Schatzker and Colton divide olecranon fractures into groups by quantity of fragments and fracture lines [88].
Fracture Morphology and Distribution
- Quantitative 3-dimensional computed tomography analysis further clarified the fracture morphology of Mayo type I, II, and III fractures [62].
- In a study of 2462 fractures from the Swedish Fracture Register, 29% of olecranon fractures were comminuted central fractures [8].
- The share of distal olecranon fractures in the Swedish Fracture Register was almost threefold larger than the 6.2% reported in a Scottish study of 64 olecranon fractures [8].
- In a study of 64 olecranon fractures, the most frequent injury according to the AO fracture classification was the 21-B1.1 type [94].
- In a study of 64 olecranon fractures, a simple isolated displaced olecranon fracture (Mayo type 2A) was the most common according to the Mayo classification [94].
- In a study of 44 patients treated with tension band wiring, Type IIA fractures were the most common pattern, accounting for 91% of cases [107].
- In a study of 57 patients treated with a shape-memory alloy concentrator, the Mayo classification system was used to distinguish fracture displacement, presence of comminution, and ulnohumeral stability [60].
- Mayo type III fractures are categorized into anterior and posterior olecranon fracture-dislocations based on the radio-ulnar relationship [106].
- Articular impaction is a common feature of geriatric olecranon fractures [32].
Pediatric and Adolescent Considerations
- Fracture of the olecranon in a child is often only part of a complex injury to the bone and soft tissues around the elbow [30].
- The olecranon apophyseal ossification system, when combined with age and sex, successfully predicts peak height velocity within a year in 90% of cases [93].
Clinical Presentation
Mechanisms and Epidemiology
- The triceps acts as the main deforming mechanism pulling the fractured fragment proximally, creating a gap at the articular surface, and an incompetent extensor mechanism [38].
- The incidence of olecranon fractures increased by 29% over a 20-year study period in Denmark [12].
- In a Swedish study of 2462 fractures, 29% were comminuted central fractures and the share of distal olecranon fractures was almost threefold larger than in a Scottish study [8].
- In a Swedish study, high-energy injury mechanisms accounted for 5.7% of female and 11.6% of male patients overall, while low-energy mechanisms accounted for 87.4% of female and 77.8% of male patients overall [8].
- Fractures of the ipsilateral olecranon associated with the radial neck are not as rare as previously reported [42].
Physical Examination
- Pain is usually localized to the posterior part of the elbow [37].
- Given the subcutaneous location of the olecranon, the fracture itself may be palpable [37].
- Extensive posterior swelling is typical [37].
- A careful examination of the integrity of the extensor mechanism with gravity eliminated can aid surgical decision making [37].
- If present, open wounds are typically posterior and result from the direct impact of the posterior surface of the elbow against an unyielding structure [37].
- The affected extremity from shoulder to hand should be thoroughly examined for any soft tissue compromise [38].
- There is a low suspicion for open fractures given the subcutaneous nature of the olecranon [38].
- The elbow will often present with a large fluid collection subcutaneously over the olecranon [38].
- Examination of the extensor mechanism both with and without gravity eliminated should be performed to assess competency [38].
Imaging
- Plain radiographs are usually sufficient for isolated fractures of the olecranon [37].
- A true lateral radiograph is necessary to accurately identify the plane of the fracture and the number of fracture fragments [37].
- The examiner should assess for fracture comminution and impaction on radiographs [37].
- In more complex cases, CT may help delineate the comminution or impaction better, but this is not routinely required [37].
- Anteroposterior and lateral radiographs of the elbow are required for olecranon fractures [38].
- If there is concern for a radial head fracture, a radiocapitellar view of the elbow can be obtained [38].
- In the setting of an elbow dislocation, post-reduction radiographs should be obtained [38].
- Computed tomography (CT) can be used for preoperative planning for comminuted fractures of the olecranon if there is an associated radial head or coronoid fracture, but this is not routinely utilized [38].
Classification
- The Mayo classification is based on the amount of fracture displacement, the presence of comminution, and stability of the ulnohumeral joint [38].
- The modifier A (simple) and B (comminuted) in the Mayo classification indicate the presence of comminution [38].
- The Schatzker and Colton classification attempted to classify olecranon fractures based on different fracture pattern morphology, but its application was limited [38].
Prognosis and Outcomes
- A majority of olecranon fractures heal uneventfully with good or excellent results with a small loss of motion to be expected [11].
- Primary elbow instability and fracture morphology are prognostic factors for elbow function and development of arthrosis after operative treatment of olecranon fractures [45].
- The median incidence of post-traumatic osteoarthritis following isolated olecranon fractures is 19% at a median follow-up of 41 months [22].
- Patients aged 50 years or more with olecranon fracture should be evaluated for osteoporosis and fracture risks for secondary prevention of subsequent fractures [36].
Investigations
Clinical Examination
- The history may help distinguish a triceps avulsion from an actual direct blow to the elbow [37].
- Extensive posterior swelling is typical of olecranon fractures [37].
- Open wounds, if present, are typically posterior and result from the direct impact of the posterior surface of the elbow against an unyielding structure [37].
- The affected extremity from shoulder to hand should be thoroughly examined to identify associated ipsilateral injuries [38].
- The arm should be examined for soft tissue compromise, with a low suspicion for open fractures maintained given the subcutaneous nature of the olecranon [38].
Imaging
- In more complex cases, CT may help delineate comminution or impaction better, though this is not routinely required [37].
- Quantitative analysis of olecranon fractures via CT further clarified fracture morphology of Mayo type I, II, and III fractures [62].
Classification
- The distribution of olecranon fractures in a Swedish register study showed a larger share of comminuted central fractures (29%) compared to a single-center report from Scotland [8].
- The Swedish register study observed an almost threefold larger share of distal olecranon fractures than the 6.2% reported in a Scottish study of 64 olecranon fractures [8].
Pediatric Specifics
- Olecranon fractures are associated with other elbow injuries (usually the medial epicondyle) in 20% to 50% of pediatric cases [48].
- In younger children, the olecranon is predominantly cartilage, which reduces the chance of a fracture occurring with a direct blow [48].
- The thick periosteum and relatively thin metaphyseal cortex of the pediatric olecranon predispose it to minimally displaced greenstick fractures [48].
Treatment
General Principles and Indications
- Conventional indications for surgical treatment of olecranon fractures include open fractures, displaced fractures, and fractures causing disruption to the extensor mechanism affecting the insertion of the triceps muscle into the olecranon [28].
- The aims of treatment for all olecranon fractures are restoration of function and stability to the elbow joint to allow early mobilization, while minimizing associated complications [113].
- Fixation must be secure enough to permit early motion to avoid significant stiffness of the elbow joint [20].
- Good results overall are to be expected after surgical management of olecranon fractures [43].
Non-Operative Management
- Mayo type I stable undisplaced fractures can be managed effectively with nonoperative management [113].
- Some authors suggest splinting the elbow in 45° to 90° of flexion for three to four weeks followed by supervised mobilization for stable undisplaced fractures [113].
- Early active mobilization is recommended where pain allows, and time in a cast should be minimized to reduce stiffness [113].
- The acceptable degree of fracture displacement for nonoperative management is commonly quoted as < 2 mm of articular displacement on the lateral radiograph [113].
- Aggregate data support the non-operative treatment of isolated undisplaced olecranon fractures in children with good results [33].
- Nonoperative management of isolated displaced olecranon fractures in older, lower-demand patients yields satisfactory short-term and long-term outcomes [13].
Operative Management: Techniques and Outcomes
- There are four common methods in the surgical management of olecranon fractures: tension band wiring, plate fixation, intramedullary fixation, and excision of the proximal fractured fragment with re-attachment of triceps tendon [28].
- Both operative procedures (Kirschner wire tension band and anatomical locking plate) effectively treat Mayo type II olecranon fractures [9].
- Current randomized evidence suggests that tension band wiring (TBW) and plate fixation (PF) may yield similar functional outcomes for displaced olecranon fractures, based on a limited number of RCTs [24].
- Among active patients with a simple isolated, displaced fracture of the olecranon, no difference was found between TBW and plate fixation in patient-reported outcome at 1 year following surgery [35].
- Plate fixation has better efficacy and safety for Mayo II olecranon fractures compared to tension band wiring [51].
- TBW remains an effective treatment for appropriately selected olecranon fractures and outperformed plate osteosynthesis in one cohort [40].
- Internal fixation by cable pin system (CPS) is associated with a shorter healing time, fewer complications, and better function than TBW [34].
- Low-profile double-plate osteosynthesis is a safe and effective alternative treatment of olecranon fractures with excellent subjective and objective clinical outcome measures [1].
- Low-profile double-plate osteosynthesis for treating olecranon fractures resulted in good clinical outcomes [85].
- Suture tension band fixation reduces hardware complications in olecranon fractures [3].
- In all patients treated with percutaneously placed K-wires and absorbable tension-band sutures for displaced olecranon fractures, fracture united within 6 weeks and full painless range of movement was regained within 6 months [47].
- Fractures through an ununited olecranon apophysis are successfully treated with plate and screw fixation with bone grafting [71].
- The Nickel-Titanium olecranon memory connector (OMC) can be an effective alternative to treat olecranon fractures [77].
- The study supports the rationale for excision of the fragment of the olecranon with repair of the triceps mechanism as the preferred method of treatment due to significantly less morbidity compared with internal fixation [65].
- Functional results after at least 2 years were equally good with tension band and screwing techniques, but there was a considerably higher rate of separation at the fracture after screwing than after inserting a tension band [46].
Complications and Risk Factors
- Patients undergoing revisions beyond implant removal had poorer functional outcomes after olecranon fracture fixation [18].
- No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method for olecranon fracture fixation [18].
- Patients who have operative fixation of a fracture of the olecranon can be counseled that most patients keep their implants, that only 3% experience implant migration, and that technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [25].
- Risk factors associated with a poorer outcome following operative treatment of displaced olecranon fractures are patient factors, fracture morphology, and associated elbow instability or fractures [113].
Complications
General Outcomes and Mortality
- ORIF for olecranon fractures demonstrates low short-term complication rates [101].
- Specific comorbidities such as smoking and ascites were associated with increased risk of short-term complications following ORIF for olecranon fractures [101].
Hardware and Fixation Complications
- Symptomatic hardware requiring removal is a recurring and frequent problem in olecranon fracture management [43].
- The most common complication following plating of the olecranon was lack of full extension in 39% of patients [16].
- Only 3% of patients who undergo operative fixation of an olecranon fracture experience implant migration [25].
- Technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [25].
- Internal fixation by cable pin system (CPS) is associated with fewer complications than tension band wiring (TBW) for olecranon fractures [34].
- Suture tension band fixation reduces hardware complications in olecranon fractures compared to traditional techniques [3].
Long-Term and Specific Complications
- Articular impaction in olecranon fractures is associated with worse postoperative outcomes [67].
- Inadequate reduction of articular impaction contributes to increased step-off and poorer function in olecranon fractures [67].
Recovery
General Outcomes
- Articular impaction in olecranon fractures is associated with worse postoperative outcomes, with inadequate impaction reduction contributing to increased step-off and poorer function [67].
Operative Recovery
- Surgical treatment of olecranon fractures is associated with a high rate of complications, and patients undergoing revisions beyond implant removal had poorer functional outcomes [18].
- No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method following open reduction and fixation of olecranon fractures [18].
- Both tension band wiring and plate fixation yield excellent or good clinical outcomes with minimal loss of physical capacity, little pain, and disability in the majority of patients with simple and comminuted displaced olecranon fractures [68].
- Among active patients with a simple isolated, displaced fracture of the olecranon, no difference was found between tension band wiring and plate fixation in the patient-reported outcome at 1 year following surgery [35].
- Internal fixation by cable pin system is an effective method for olecranon fracture and is associated with a shorter healing time, fewer complications, and better function than tension band wiring [34].
- Tension band wiring remains an effective treatment for appropriately selected olecranon fractures and in one cohort outperformed plate osteosynthesis [40].
- Both Kirschner wire tension band combined with anatomical locking plate and standard operative procedures effectively treat Mayo type II olecranon fractures [9].
Non-Operative Recovery
- Close radiographic follow-up for nonsurgically treated olecranon fractures is recommended due to the risk of further displacement after initial nonsurgical treatment in children [2].
- All 10 cases of olecranon fractures in children treated with a sling were free of symptoms and had a full range of elbow movement at 3 weeks [17].
Elderly-Specific Outcomes
Key Evidence
- [L3] Low-profile double-plate osteosynthesis is a safe and effective alternative treatment of olecranon fractures with excellent subjective and objective clinical outcome measures. [1] (10.1016/j.otsr.2019.08.019)
- [L4] Close radiographic follow-up for nonsurgically treated olecranon fractures is recommended. [2] (10.5435/jaaos-d-25-00821)
- [L3] Future studies should focus on the long-term outcomes of this technique, as compared to traditional and more established techniques to treat olecranon fractures. [3] (10.1016/j.jseint.2026.101734)
- [L3] 96% of individuals with a closed displaced fracture of the olecranon treated by open reduction and internal fixation had excellent or good outcomes up to 25 years after the fracture. [4] (10.1067/mse.2002.124548)
- [L3] Olecranon fractures in the elderly have higher than expected 1 year mortality rates. [5] (10.1177/1758573221994860)
- [L4] Some isolated displaced (>2 mm) olecranon fractures in elderly patients can be successfully treated nonoperatively. [6] (10.1016/j.ocl.2016.08.011)
- [L4] The literature on the treatment of olecranon fractures in elderly patients is limited. [7] (10.1007/s11678-018-0488-7)
- [L4] [8] (10.1007/s00068-021-01765-2)
- [L3] Both operative procedures effectively treat Mayo type II olecranon fractures. [9] (10.1186/s12891-025-08843-1)
- [L3] Patients with olecranon fractures have essentially similar demographic characteristics compared to patients with distal radius fractures. [10] (10.1177/17585732221124301)
- [L4] A majority of olecranon fractures heal uneventfully with good/excellent results with a small loss of motion to be expected. [11] (10.1016/j.hcl.2015.07.003)
- [L3] The incidence of olecranon fractures increased by 29% over the 20-year study period. [12] (10.1186/s13018-025-05970-2)
- [L4] We found satisfactory short-term and long-term outcomes following the nonoperative management of isolated displaced olecranon fractures in older, lower-demand patients. [13] (10.2106/jbjs.l.01137)
- [L3] The timing of fixation of displaced olecranon fractures does not significantly increase the rate of early complications or reoperation. [15] (10.1016/j.jhsg.2023.09.002)
- [L3] Plating of the olecranon leads to predictable union, though the most common complication was lack of full extension in 39% of patients. [16] (10.1016/j.injury.2016.04.015)
- [L4] All 10 cases treated with a sling were free of symptoms and had a full range of elbow movement at 3 weeks. [17] (10.1016/0020-1383(75)90056-x)
- [L4] Surgical treatment of olecranon fractures is associated with a high rate of complications, and patients undergoing revisions beyond implant removal had poorer functional outcomes; however, no significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method. [18] (10.1016/j.xrrt.2025.08.004)
- [L5] Fixation must be secure enough to permit early motion to avoid significant stiffness of the elbow joint. [20] (10.5435/00124635-200007000-00007)
- [Paper] No one technique is suitable for the management of all olecranon fractures. [21] (10.1016/j.injury.2008.12.013)
- [L4] This review identified a median OA incidence of 19% at a median follow-up of 41 months following isolated olecranon fractures. [22] (10.1016/j.jse.2026.02.024)
- [L4] Displaced olecranon fractures in patients older than 70 years may be effectively managed with nonoperative measures to produce high satisfaction and functional range of motion. [23] (10.1177/1558944720944261)
- [L1] Current randomized evidence suggests that TBW and PF may yield similar functional outcomes for displaced olecranon fractures; however, these findings are based on a limited number of RCTs, with several secondary outcomes derived from only 2 studies. [24] (10.1016/j.xrrt.2026.100817)
- [L3] Patients who have operative fixation of a fracture of the olecranon can be counseled that most patients keep their implants, that only 3% experience implant migration, and that technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal. [25] (10.1007/s11999-015-4488-2)
- [L5] The Mayo classification was designed to simplify categorization of olecranon fractures but does not achieve this goal due to poor reproducibility. [27] (10.1097/corr.0000000000000614)
- [L1] [28] (10.1002/14651858.cd010144.pub2)
- [L1] This supports nonoperative treatment as a reasonable option for displaced stable olecranon fractures in elderly patients. [29] (10.2106/jbjs.24.00655)
- [L4] Fracture of the olecranon in a child is often only part of a complex injury to the bone and soft tissues around the elbow. [30] (10.1016/0020-1383(80)90009-1)
- [L4] Articular impaction is a common feature of geriatric olecranon fractures. [32] (10.5435/jaaos-d-20-01293)
- [L4] Aggregate data support the non-operative treatment of isolated undisplaced olecranon fractures with good results, and support the operative treatment of fractures displaced ≥4 mm. [33] (10.1302/2058-5241.5.190082)
- [L1] Internal fixation by CPS is an effective method for olecranon fracture and is associated with a shorter healing time, fewer complications and better function than TBW. [34] (10.1177/147323001204000324)
- [L1] Among active patients with a simple isolated, displaced fracture of the olecranon, no difference was found between TBW and plate fixation in the patient-reported outcome at 1 year following surgery. [35] (10.2106/jbjs.16.00773)
- [L4] Our results suggest that patients aged 50 years or more with olecranon fracture should be evaluated for osteoporosis and fracture risks for secondary prevention of subsequent fractures. [36] (10.11005/jbm.2017.24.3.175)
- [L4] TBW remains an effective treatment for appropriately selected olecranon fractures and in this cohort outperformed plate osteosynthesis. [40] (10.1007/s00590-015-1724-0)
- [L5] Nonoperative management of olecranon fractures in elderly patients offers comparable functional outcomes to surgical intervention while significantly reducing exposure to potential complications and healthcare costs. [41] (10.1016/j.injury.2025.112579)
- [L3] Fractures of the ipsilateral olecranon associated with the radial neck are not so rare as previously reported. [42] (10.1186/s13018-021-02373-x)
- [L4] [43] (10.1016/j.jhsa.2012.12.036)
- [L3] Primary elbow instability and fracture morphology are prognostic factors for elbow function and development of arthrosis after operative treatment of olecranon fractures. [45] (10.1016/j.injury.2003.12.002)
- [L4] [46] (10.1016/0020-1383(87)90386-x)
- [L4] In all patients, fracture was united within 6 weeks and all patients regained full painless range of movement of elbow within 6 months. [47] (10.1097/bte.0b013e318254642f)
- [L1] Plate has better efficacy and safety for Mayo II olecranon fractures. [51] (10.1186/s13018-022-03262-7)
- [L4] [60] (10.1186/s13018-020-01982-2)
- [L4] Quantitative analysis of olecranon fractures further clarified fracture morphology of Mayo type I, II, and III fractures. [62] (10.1016/j.jse.2015.10.002)
- [L4] This proposed classification system is anatomically based and considers the deforming forces from ligaments and tendons. [64] (10.1016/j.jse.2023.12.021)
- [L3] The study supports the rationale for excision of the fragment of the olecranon with repair of the triceps mechanism as the preferred method of treatment of fractures of the olecranon due to significantly less morbidity compared with internal fixation. [65] (10.2106/00004623-198163050-00005)
- [L3] Articular impaction in olecranon fractures is associated with worse postoperative outcomes, with inadequate impaction reduction contributing to increased step-off and poorer function. [67] (10.1302/0301-620x.108b1.bjj-2025-0444.r1)
- [L3] Both TBW and plate fixation yield excellent/good clinical outcomes with minimal loss of physical capacity, little pain and disability in the majority of patients with simple and comminuted displaced olecranon fractures. [68] (10.1007/s00402-014-2021-9)
- [L4] The authors conclude that these measurements guide the surgeon to obtain a more reliable length of the olecranon and maintain articular geometry during fixation. [69] (10.1002/ca.20431)
- [L5] Fractures through an ununited olecranon apophysis are successfully treated with plate and screw fixation with bone grafting. [71] (10.1142/s2424835520720017)
- [L2] The study showed that OMC could be an effective alternative to treat olecranon fractures. [77] (10.1007/s00264-013-1878-5)
- [L3] Low-profile double-plate osteosynthesis for treating olecranon fractures resulted in good clinical outcomes. [85] (10.1016/j.jse.2020.01.091)
- [L4] [88] (10.1016/j.jor.2019.09.017)
- [L3] When combined with age and sex, the olecranon system successfully predicts PHV within a year in 90% of cases, establishing a single lateral view of the olecranon as a simple alternative to more complex grading systems. [93] (10.2106/jbjs.20.01856)
- [L3] [94] (10.1016/j.injury.2011.10.017)
- [L4] ORIF for olecranon fractures demonstrates low short-term complication rates; however, specific comorbidities such as smoking and ascites were associated with increased risk. [101] (10.1016/j.jseint.2025.06.017)
- [Paper] [106] (10.1007/s00402-016-2593-7)
- [L4] [107] (10.1016/j.jhsa.2013.05.012)
- [L4] [111] (10.1016/j.injury.2024.111496)
- [L4] [113] (10.1302/0301-620x.105b2.bjj-2022-0703.r1)
References
[1] Clinical evaluation of double-plate osteosynthesis for olecranon fractures: A retrospective case-control study. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2019.08.019
[2] Further Displacement After Initial Nonsurgical Treatment of Minimally Displaced Olecranon Fractures in Children. Journal of the American Academy of Orthopaedic Surgeons. 2026. DOI: 10.5435/jaaos-d-25-00821
[3] Suture tension band fixation reduces hardware complications in olecranon fractures: a comparative study. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101734
[4] Comparison of tension-band and figure-of-eight wiring techniques for treatment of olecranon fractures. Journal of Shoulder and Elbow Surgery. 2002. DOI: 10.1067/mse.2002.124548
[5] Complications and mortality associated with olecranon fractures in the elderly: a retrospective cohort comparison from a large level one trauma centre. Shoulder & Elbow. 2021. DOI: 10.1177/1758573221994860
[6] Controversies in Fractures of the Proximal Ulna. Orthopedic Clinics of North America. 2017. DOI: 10.1016/j.ocl.2016.08.011
[7] Nonoperative treatment of olecranon fractures in the elderly—a systematic review. Obere Extremität. 2018. DOI: 10.1007/s11678-018-0488-7
[8] Epidemiology, classification and treatment of olecranon fractures in adults: an observational study on 2462 fractures from the Swedish Fracture Register. European Journal of Trauma and Emergency Surgery. 2021. DOI: 10.1007/s00068-021-01765-2
[9] Efficacy evaluation of Kirschner wire tension band combined with anatomical locking plate in the treatment of Mayo type II olecranon fractures. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08843-1
[10] Mortality and subsequent fractures of patients with olecranon fractures compared to other upper extremity osteoporotic fractures. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221124301
[11] Olecranon Fractures. Hand Clinics. 2015. DOI: 10.1016/j.hcl.2015.07.003
[12] Epidemiology and Treatment of Olecranon Fractures: a nationwide register-based analysis of 27,880 cases in Denmark from 1999 to 2018. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05970-2
[13] Nonoperative Management of Displaced Olecranon Fractures in Low-Demand Elderly Patients. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.l.01137
[15] Timing of Olecranon Fracture Fixation Does Not Affect Early Complication or Reoperation Rates. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2023.09.002
[16] Outcomes after plating of olecranon fractures: A multicenter evaluation. Injury. 2016. DOI: 10.1016/j.injury.2016.04.015
[17] Olecranon fractures in children. Injury. 1975. DOI: 10.1016/0020-1383(75)90056-x
[18] Risk factors for complications and poor function after open reduction and fixation of olecranon fractures. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.08.004
[20] Olecranon Fractures: Treatment Options. Journal of the American Academy of Orthopaedic Surgeons. 2000. DOI: 10.5435/00124635-200007000-00007
[21] Olecranon fractures. Injury. 2009. DOI: 10.1016/j.injury.2008.12.013
[22] Incidence of Post-traumatic Osteoarthritis in Olecranon Fractures and the Role of Instability and Comminution in its Development: A Systematic Review. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.024
[23] Nonoperative Management of Olecranon Fractures in Elderly Patients: A Systematic Review. HAND. 2020. DOI: 10.1177/1558944720944261
[24] Comparative efficacy and safety of tension band wiring versus plate fixation for olecranon fractures: a meta-analysis and trial sequential analysis of randomized clinical trials. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100817
[25] Factors Associated With Reoperation After Fixation of Displaced Olecranon Fractures. Clinical Orthopaedics & Related Research. 2016. DOI: 10.1007/s11999-015-4488-2
[27] Classifications in Brief: Mayo Classification of Olecranon Fractures. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000614
[28] Surgical interventions for treating fractures of the olecranon in adults. Cochrane Database of Systematic Reviews. 2014. DOI: 10.1002/14651858.cd010144.pub2
[29] Surgery for Olecranon Fractures in the Elderly (SOFIE). Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00655
[30] Fractures of the olecranon in children. Injury. 1980. DOI: 10.1016/0020-1383(80)90009-1
[32] Incidence and Management of Articular Impaction in Geriatric Olecranon Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-20-01293
[33] Paediatric olecranon fractures: a systematic review. EFORT Open Reviews. 2020. DOI: 10.1302/2058-5241.5.190082
[34] Randomized Prospective Study of Olecranon Fracture Fixation: Cable Pin System versus Tension Band Wiring. Journal of International Medical Research. 2040. DOI: 10.1177/147323001204000324
[35] Plate Versus Tension-Band Wire Fixation for Olecranon Fractures. Journal of Bone and Joint Surgery. 2017. DOI: 10.2106/jbjs.16.00773
[36] Olecranon Fractures Have Features of Osteoporotic Fracture. Journal of Bone Metabolism. 2017. DOI: 10.11005/jbm.2017.24.3.175
[37] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Elbow > II. Olecranon Fractures.
[38] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Assessment of Olecranon Fractures.
[40] Outcome after olecranon fracture repair: Does construct type matter?. European Journal of Orthopaedic Surgery & Traumatology. 2015. DOI: 10.1007/s00590-015-1724-0
[41] How should displaced olecranon fractures in the elderly be treated - nonoperatively or operatively?. Injury. 2025. DOI: 10.1016/j.injury.2025.112579
[42] Management strategies of pediatric ipsilateral olecranon with associated radial neck fractures based on multicenter experience. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02373-x
[43] Olecranon Fractures. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.12.036
[45] Olecranon fractures in adults: factors influencing outcome. Injury. 2004. DOI: 10.1016/j.injury.2003.12.002
[46] The complications of surgical treatment of displaced fractures of the olecranon. Injury. 1987. DOI: 10.1016/0020-1383(87)90386-x
[47] Outcome of Open Reduction and Internal Fixation With Percutaneously Placed K-wires and Absorbable Tension-band Sutures for Displaced Olecranon Fractures in Children. Techniques in Shoulder & Elbow Surgery. 2012. DOI: 10.1097/bte.0b013e318254642f
[48] Tachdjian S Pediatric Orthopaedics From The Texas Scottish Rite Hospital For Children E Book. Pigmented Villonodular Synovitis and Giant Cell Tumor of the Tendon Sheath > Olecranon Fractures.
[51] Efficacy and safety of tension band wire versus plate for Mayo II olecranon fractures: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2022. DOI: 10.1186/s13018-022-03262-7
[54] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > OLECRANON FRACTURES (ICD-9:813.01).
[60] Application of a novel shape-memory alloy concentrator in displaced olecranon fractures: a report of the technique and mid-term clinical results. Journal of Orthopaedic Surgery and Research. 2020. DOI: 10.1186/s13018-020-01982-2
[62] Quantitative 3-dimensional computed tomography analysis of olecranon fractures. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.10.002
[64] A novel fragment specific classification of complex olecranon fractures: 3-dimensional model design, radiological validation, and proposed surgical algorithm. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2023.12.021
[65] Operative treatment of olecranon fractures. Excision or open reduction with internal fixation.. The Journal of Bone & Joint Surgery. 1981. DOI: 10.2106/00004623-198163050-00005
[67] Articular impaction of olecranon fracture is associated with poor postoperative clinical outcome. The Bone & Joint Journal. 2026. DOI: 10.1302/0301-620x.108b1.bjj-2025-0444.r1
[68] Simple and comminuted displaced olecranon fractures: a clinical comparison between tension band wiring and plate fixation techniques. Archives of Orthopaedic and Trauma Surgery. 2014. DOI: 10.1007/s00402-014-2021-9
[69] Radiographic measurements of normal elbows: Clinical relevance to olecranon fractures. Clinical Anatomy. 2006. DOI: 10.1002/ca.20431
[71] Olecranon Fracture through Persistent Olecranon Apophysis in a 21-Year-Old Male: A Case Report and Systematic Review of the Literature. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520720017
[77] Design and application of Nickel-Titanium olecranon memory connector in treatment of olecranon fractures: a prospective randomized controlled trial. International Orthopaedics. 2013. DOI: 10.1007/s00264-013-1878-5
[85] Can low-profile double-plate osteosynthesis for olecranon fractures reduce implant removal? A retrospective multicenter study. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.01.091
[88] Plate fixation and tension band wiring after isolated olecranon fracture comparison of outcome and complications. Journal of Orthopaedics. 2020. DOI: 10.1016/j.jor.2019.09.017
[93] The Relationship of Olecranon Apophyseal Ossification and Sanders Hand Scores with the Timing of Peak Height Velocity in Adolescents. Journal of Bone and Joint Surgery. 2021. DOI: 10.2106/jbjs.20.01856
[94] The epidemiology of fractures of the proximal ulna. Injury. 2012. DOI: 10.1016/j.injury.2011.10.017
[101] Short-term complications of open reduction and internal fixation of olecranon fractures: a national database study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.06.017
[106] Fracture line distribution of olecranon fractures. Archives of Orthopaedic and Trauma Surgery. 2016. DOI: 10.1007/s00402-016-2593-7
[107] Use of Kirschner Wires With Eyelets for Tension Band Wiring of Olecranon Fractures. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.05.012
[111] Olecranon fractures: An old fixation device for a new surgical technique. Injury. 2024. DOI: 10.1016/j.injury.2024.111496
[113] Olecranon fractures. The Bone & Joint Journal. 2023. DOI: 10.1302/0301-620x.105b2.bjj-2022-0703.r1