Patients › Hand
Boutonnière Deformity
Extensor central-slip injury at the middle finger joint; early splinting prevents the zigzag deformity, established cases need surgery.
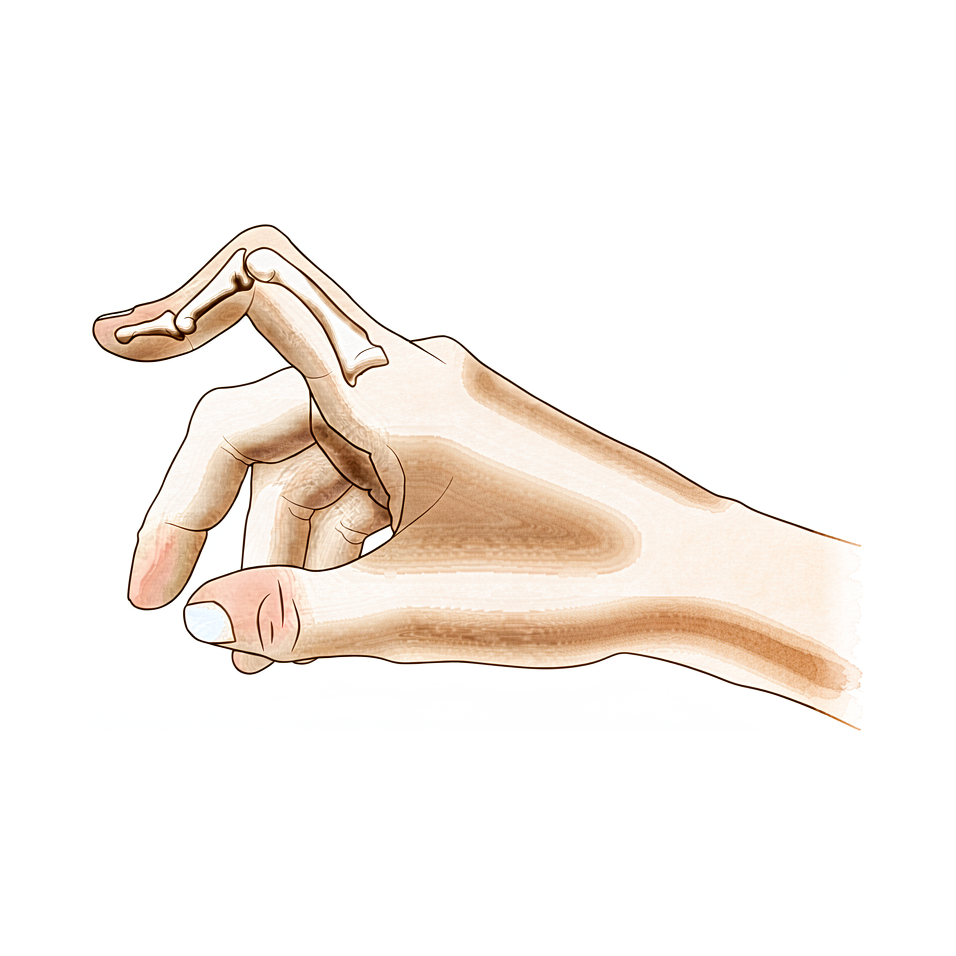
What you're feeling
With a boutonnière deformity, the middle joint of your finger bends down towards your palm and the fingertip bends back the other way. The finger may look swollen over the middle joint, and it can be painful there as well. Straightening the middle joint becomes hard, and the harder you try, the more the finger seems to resist.
The trouble shows up most in tasks that need the finger to straighten and then bend again. Picking up a coin, holding a cup by its handle, typing, buttoning a shirt or turning a key can all become awkward. Grip itself often still works, which is why many people put up with the finger for weeks before seeking help.
If the deformity came from an injury, the middle joint may ache after you use the hand, and the stiffness can be worse in the morning before the finger loosens up. In rheumatoid arthritis, the same bent posture develops slowly as the lining of the joint stays inflamed and swollen over months.
A few signs need fast attention. If your finger or hand becomes hot, red, swollen and painful, especially with a fever, go to the emergency department the same day. The same applies if a finger turns pale, cold, white or blue, or if you suddenly lose feeling or movement in it after an injury. If the symptoms are instead not settling, are getting worse over weeks, wake you at night, or stop you working or using your hand, see your GP or ask for a specialist review.
What's actually happening
Down the back of each finger runs a set of tendons that straighten the joints. Think of them as ropes running under a hood on the back of the finger. The rope that straightens the middle joint is called the central slip, and it anchors onto the base of the middle bone. Two more cords, called lateral bands, run alongside it and help straighten both the middle joint and the fingertip.
With a boutonnière deformity, the central slip has torn or stretched away from the middle bone. The middle joint can no longer be pulled straight, so it drops into a bent position. The two lateral bands then slide off the top of the joint and slip down towards the palm. Once they sit below the joint's pivot point, those same cords start bending the middle joint instead of straightening it, and they pull the fingertip back the other way. That is why the finger settles into the bent middle joint and arched tip described above, and why every attempt to straighten it seems to make the cords pull harder against you.
It takes more than one damaged part to produce this posture. The central slip, the ligament that ties the two cords together over the back of the finger, and the fibres of the hood that hold everything in place all need to be injured before the deformity develops. A tear of the central slip on its own may leave the middle joint weak without the full deformity, which is one reason early treatment matters: it can stop the deformity from forming at all.
The same end result can come from different starting points. An injury such as a blow to the finger or a cut over the back of the joint can do it, and so can the ongoing inflammation of rheumatoid arthritis, which slowly wears through the same structures. A finger can also look like this without any tendon injury at all, when the problem sits on the palm side of the joint instead, and that version is treated differently, which is why working out which one you have comes first.
What we can do about it
Dr Kieran Hirpara, an upper-limb surgeon at Mater Private Hospital Rockhampton, starts with the least invasive options that suit your condition. Patients are generally referred to our clinic by their GP; if a physiotherapist has suggested you see us, you will still need a referral from your GP in order to be eligible for the Medicare rebate. At the clinic we take a history, examine your hand, and arrange imaging if it is needed to work out what is going on. Because this deformity can come from several different starting points, sorting out which one you have comes before any treatment.
The first step is usually splinting and hand therapy. For a recent injury, splinting the middle joint straight can stop the deformity from forming at all, and the sooner it starts the better: people treated within six weeks of injury do better than those treated later. The splint holds only the middle joint straight. Your fingertip, your knuckle and your other fingers keep moving, because holding the whole finger still lets the fingertip stiffen. For a deformity that has been there a while, we may use casting to straighten the middle joint as far as possible, followed by three months of a splint that lets you bend the finger while it works. This approach is worth trying before surgery is considered.
When splinting and therapy have not given enough improvement, surgery may be considered. The operation rebuilds the tendon that straightens the middle joint, sometimes using a small piece of tendon from your own forearm as a graft. In some cases the tendons that have slipped towards the palm are repositioned back over the joint where they belong. The aim is the same in each case: to let you straighten the middle joint again and use the finger without it catching or bending down. The operation has its own page, and we will talk through what it involves for your particular finger before any decision is made.
What to expect
The outlook depends a lot on timing. Caught early, a boutonnière deformity can often be stopped before it settles in. Splinting the middle joint straight soon after an injury can prevent the deformity from forming at all, and people treated within six weeks do better than those treated later. Left alone, the deformity tends to get worse rather than stay the same, because the tendons that have slipped out of place keep pulling the finger further into its bent posture. An injury that looked minor can produce a stiff, fixed finger weeks later.
For a deformity that has been there a while, non-operative treatment still has a real role. Casting to straighten the middle joint as far as possible, followed by three months of a splint that lets you bend the finger while you use it, can work well. The finger responds to this approach when the casting can get the middle joint close to straight and you actively use your hand in the splint over those three months, with flexion recovering along the way. For thumb injuries, splinting the knuckle straight can help if it starts before the deformity develops.
Surgery aims to let you straighten the middle joint again. In one reported group of 18 people who had a tendon graft to correct a long-standing deformity, 16 had good or excellent results. A newer technique that gets the finger moving early was reported to work in 11 cases. Surgery can also help the congenital form of this deformity, where it has been present since birth.
It is honest to say that not every correction lasts. For fingers affected by rheumatoid arthritis, soft-tissue surgery alone may not hold in the later stages, and long-term results are less predictable. When a deformity comes back or persists, a different procedure may be the better answer. Whatever the starting point, the realistic goal is a finger you can straighten and use, not a promise of a perfectly normal finger.
When to see someone
A boutonnière deformity rewards early attention, so it is worth knowing when to act. If you have hurt your finger and the middle joint will not straighten, or the finger sits bent and swollen days after an injury, see your GP and ask for a specialist review. The sooner splinting starts, the better the chance of stopping the deformity before it settles in.
A few signs need faster care. Go to an emergency department the same day if your finger or hand becomes hot, red, swollen and painful, especially with a fever. The same applies if a finger turns pale, cold, white or blue, or if you suddenly lose feeling or movement in it after an injury. If broken skin sits over an injured joint, or the finger looks obviously deformed, go as well.
If symptoms are instead not settling, are getting worse over weeks, wake you at night, or stop you working or using your hand, see your GP or ask for a specialist review. If you cannot reach the clinic out of hours or on a weekend, go to your nearest emergency department.
In more depth
Advanced reading: the deeper science (optional)
This section goes further than you need for your own treatment decisions. Boutonnière deformity is worth the extra reading because the instinctive treatment for a painful, swollen, bent finger, rest it and keep it still, is the one thing the evidence specifically does not support.
Early mobilisation, not prolonged immobilisation
A systematic review of treatments for central slip injury found the evidence base limited, with the roles of different strategies for both open and closed injuries not well supported [1]. Within that limitation, the evidence from individual studies tentatively supports early mobilisation and does not support prolonged immobilisation [1].
That is worth stating plainly because it runs against the reflex. The distinction is between protecting the healing central slip, which requires the middle joint to be held straight, and immobilising the whole finger, which allows the fingertip joint to stiffen in extension and the whole digit to become rigid. The splint is intended to hold one joint while the others keep moving.
Why the deformity gets worse rather than staying still
Boutonnière is a progressive deformity, which is unusual and worth understanding. The central slip attaches to the base of the middle bone and straightens the middle joint. When it fails, that joint drops into flexion, and the two lateral bands, which normally run above the joint's axis, slip below it.
Once they are below the axis, the same tendons that previously helped straighten the middle joint begin to bend it, while pulling the fingertip into hyperextension. The deformity therefore self-reinforces: every attempt to straighten the finger tightens the structures now holding it bent. This is why an injury that looked minor can produce a fixed deformity weeks later, and why the window for simple splinting is early.
The deformity that is not a boutonnière
A finger can adopt the same posture without a central slip injury at all, and the treatments differ entirely. Boutonnière and pseudoboutonnière deformities differ in pathoanatomy, diagnosis and management [2], the pseudo variety arising from a volar plate injury at the middle joint, where the fingertip joint retains normal passive flexion rather than being drawn into hyperextension.
Distinguishing them at the bedside rests on the fingertip. In a true boutonnière the tip is held hyperextended and resists being bent, particularly with the middle joint straightened; in a pseudoboutonnière it flexes freely. Splinting a pseudoboutonnière as though it were the real thing addresses the wrong joint.
It belongs to a family of injuries defined by where the tendon fails
Boutonnière sits alongside mallet finger and sagittal band injury as one of three closed extensor mechanism injuries, categorised by the zone in which the mechanism fails [3]. All three can present as a swollen finger held abnormally within days of an injury, and each requires a different splint position, which is the practical reason a definite diagnosis is worth reaching before committing to weeks of splinting.
References for the advanced reading
- Geoghegan L, Wormald JCR, Adami RZ, Rodrigues JN. Central slip extensor tendon injuries: a systematic review of treatments. J Hand Surg Eur Vol. 2019;44(8):825-32.
- Hanson ZC, Thompson RG, Andrews JR, Lourie GM. Boutonniere versus pseudoboutonniere deformities: pathoanatomy, diagnosis, and treatment. J Hand Surg Am. 2023;48(5):489-97.
- Lin JD, Strauch RJ. Closed soft tissue extensor mechanism injuries (mallet, boutonniere, and sagittal band). J Hand Surg Am. 2014;39(5):1005-11.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A staged technique for the repair of traumatic boutonniere deformity allows the surgeon to divide the deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- Differentiating a true boutonniere deformity from a pseudoboutonniere injury is critical in determining clinical management [2].
- A retrospective study of fifty-four longstanding post-burn boutonnière deformities was carried out to evaluate the problems associated with the surgical procedures [3].
- An understanding of the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities [4].
- Early treatment of central slip injuries can prevent the deformity [5].
- Transection of the terminal extensor tendon is a useful procedure for salvage of the boutonniere deformity [6].
- No boutonniere deformities were produced in a series of 20 patients who had chronic mallet finger deformity treated with central slip tenotomy [7].
- Reconstruction of the central slip by the transverse retinacular ligament is not indicated for boutonnière deformities with severe contracture of the lateral band [8].
- The best indication for reconstruction of the central slip by the transverse retinacular ligament is in cases in which the central slip is defective and conservative treatment is not effective [8].
- Similar results occurred for chronic boutonniere deformity using serial casting for adequate extension followed by 3 months of relative motion flexion (RMF) orthotic use, which should be attempted prior to surgical intervention [9].
- A new surgical technique with early mobilization is an effective and simplified treatment of Boutonniere deformity [10].
- The natural history of the boutonnière deformity in rheumatoid arthritis is outlined, and a simple method of repair is described [11].
- Chronic boutonniere deformity will respond to relative motion flexion splinting if serial casting can place the proximal interphalangeal joint in less than -20° extension, and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion [12].
- The Y-shaped tendon graft can be a useful procedure for the correction of chronic boutonniere deformity [13].
- In a patient series of 18 patients, the Y-shaped tendon graft provided good or excellent results in 16 patients [13].
- Extension splinting of the metacarpophalangeal (MP) joint may be effective if traumatic thumb injuries are treated before development of a boutonnière deformity [14].
- Congenital boutonniere deformity is understood as various embryonic developmental failures [15].
- A reliable surgical option for congenital boutonniere deformity involves central slip reconstruction [15].
- Extensor tenotomy to correct a boutonnière deformity of long standing markedly lessened disability with restoration of flexion of the distal joint [16].
- In chronic boutonniere deformity, when the lateral bands are deficient or damaged, the cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results [17].
- Extension splinting may be effective if traumatic thumb injuries are treated before deformity development [18].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a traumatic thumb boutonnière deformity is established [18].
- The prevalence of boutonnière deformity without rheumatoid arthritis or trauma is approximately 13% [19].
- Current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries, are summarized [20].
- Long-term results following soft tissue reconstruction for boutonniere finger deformity in rheumatoid arthritis are unreliable [24].
- Recurrent or persistent deformity in rheumatoid arthritis is best treated with a salvage procedure [24].
Anatomy & Pathophysiology
Extensor Mechanism Anatomy
- The extensor mechanism of the finger at the level of the proximal interphalangeal (PIP) joint consists of both intrinsic and extrinsic contributions [28].
- The extensor tendon entering the digit is the continuation of the extensor digitorum communis (EDC), with contributions from the extensor indicis proprius in the index finger and the extensor digiti quinti in the small finger [28].
- In 30% of cases, the EDC has a separate insertion into the base of the proximal phalanx, but extension of the metacarpophalangeal (MP) joint typically occurs through the pull of the sagittal bands [28].
- The principal bony insertion of the extrinsic digital extensors is on the dorsal proximal aspect of the middle phalanx [32].
- Metacarpophalangeal joint extension is provided by extrinsic extensor force transmitted through the sagittal bands [32].
- Distal interphalangeal joint extension is achieved through conjoined lateral bands composed of tendinous slips from both extrinsic and intrinsic tendons [32].
- The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the MP joint [41].
- At the level of the middle of the proximal phalanx, transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [41].
- Oblique fibers (spiral fibers) from the lateral bands sweep over the distal third of the proximal phalanx to insert onto the lateral tubercles at the base of the middle phalanx, extending the middle phalanx [41].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [41].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon, which inserts at the base of the distal phalanx to extend it [41].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [41].
- The flexor digiti quinti brevis is structurally and functionally similar to the deep head of the dorsal interossei, forming the ulnar lateral band of the little finger [41].
Pathophysiology & Biomechanics
- A boutonniere deformity requires subluxation of the lateral bands volar to the axis of rotation of the PIP joint [22].
- Damage to the central slip alone does not cause a boutonniere deformity [22].
- A boutonniere deformity occurs only when the central slip, triangular ligament, and transverse and oblique fibers of the interosseous hood are all damaged [22].
- Detachment of the central slip from the middle phalanx produces a decrease in extension of the PIP joint [22].
- When the transverse and oblique fibers of the interosseous hood are divided in addition to the central slip, extension at the PIP joint is further decreased [22].
- Early treatment of central slip injuries can prevent the development of the deformity [5].
- The extensor mechanism is a complex structure that demands a delicate balance from intrinsic and extrinsic tendons of the hand [28].
- Injury to the extensor mechanism can disrupt this delicate balance, leading to significant sequelae [28].
- Understanding the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities [4].
Classification
- A staged management plan allows the surgeon to divide traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem [1].
- The choice of surgical procedure for rheumatoid boutonniere deformity is dependent on accurate staging of the deformity, which is based on the flexibility of the proximal interphalangeal joint and the state of the articular cartilage [23].
- In a cadaveric model, damage to the central slip alone does not cause a boutonniere deformity [22].
- The boutonniere deformity requires subluxation of the lateral bands volar to the axis of rotation of the PIP joint [22].
- In a cadaveric model, the central slip, triangular ligament, and oblique fibers need to all be damaged to cause subluxation of the lateral bands which leads to an acute boutonniere deformity [29].
- Anterior dislocation of the proximal interphalangeal joint is associated with ruptures of the central slip of the extensor mechanism and results in boutonnière deformity unless repaired [27].
- The incidence of uncorrectable swan-neck and boutonniere deformities is estimated to be between 8% and 16% during the first 2 years after the onset of systemic disease in rheumatoid arthritis [23].
- The prevalence of boutonniere deformities in patients with established rheumatoid arthritis is approximately 36% [23].
Clinical Presentation
Diagnostic Differentiation and Classification
- The surgeon can divide the boutonniere deformity into various categories to use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
Etiology and Pathomechanics
- The cause of boutonniere deformity in rheumatoid arthritis is chronic synovitis of the proximal interphalangeal joint [23].
- Combined injury of the central slip, triangular ligament, and transverse and oblique fibers of the interosseous hood causes a boutonniere deformity [22].
Prevalence and Natural History
- A swan-neck or boutonniere deformity occurs in approximately half of patients with rheumatoid arthritis [23].
- The incidence of uncorrectable swan-neck and boutonniere deformities is estimated to be between 8% and 16% during the first 2 years after the onset of systemic disease [23].
- The prevalence of finger deformities in patients with established rheumatoid arthritis is approximately 36% for boutonniere deformities [23].
- The natural history of the boutonnière deformity in rheumatoid arthritis is outlined in the literature [11].
Clinical Assessment and Testing
- The central slip tenodesis test detects disruption of the central slip before the boutonniere deformity becomes established [34].
- The central slip tenodesis test is applicable in uncooperative children and unconscious patients [34].
- Treating swan neck and boutonniere deformities of the PIP joint requires understanding the cause, biomechanical changes, and articular status [26].
Investigations
Clinical Examination and Diagnostic Tests
- A careful physical examination is essential to direct care and future testing if indicated [31].
- Diagnostic tests such as imaging and serum laboratory studies are useful in the determination of pathology but can be expensive, time consuming, and often nonspecific [31].
Biomechanical and Pathomechanical Assessment
Imaging and Advanced Modalities
- A computational 3D model validation reassures the reliability of research in understanding the pathomechanics of boutonniere deformity [21].
Treatment
Non-Operative
- Early treatment of central slip injuries can prevent the development of boutonniere deformity [5].
- Extension splinting of the metacarpophalangeal joint may be effective for traumatic thumb boutonniere deformity if treated before the deformity develops [14].
- Extension splinting may be effective for traumatic thumb boutonniere deformity if treated before deformity development [18].
- Chronic boutonniere deformity responds to relative motion flexion splinting if serial casting places the proximal interphalangeal joint in less than -20° extension and the patient actively uses a relative motion flexion orthosis for 3 months [12].
- Serial casting for adequate extension followed by 3 months of relative motion flexion orthotic use should be attempted prior to surgical intervention for chronic boutonniere deformity [9].
- The use of relative motion flexion orthoses is effective in increasing active distal interphalangeal joint flexion and improving proximal interphalangeal joint extension in patients with Burton stage 1 chronic boutonniere deformity [30].
- Conservative treatment of closed central slip injuries involves immobilization of the proximal interphalangeal, distal interphalangeal, and metacarpophalangeal joints in full extension for four weeks followed by a Capener spring splint for two further weeks [92].
- In a review of 115 central slip injuries, 17 of 24 patients treated conservatively achieved an outcome of less than a 20° extension deficit at the proximal interphalangeal joint and more than 80% return of proximal interphalangeal joint flexion [92].
- Patients treated for central slip injuries within six weeks of injury had better outcomes than those treated later [92].
Operative
- A staged technique allows the surgeon to divide traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- Reconstruction of the central slip by the transverse retinacular ligament is best indicated in cases in which the central slip is defective and conservative treatment is not effective [8].
- A simple method of repair for the rheumatoid boutonnière deformity is described in the literature [11].
- In a patient series, the Y-shaped tendon graft provided good or excellent results in 16 of 18 patients with chronic boutonniere deformity [13].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a traumatic boutonnière deformity of the thumb is established [18].
- The cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results for chronic boutonniere deformity when the lateral bands are deficient or damaged [17].
- A reliable surgical option involving central slip reconstruction is suggested for the congenital form of boutonniere deformity [15].
- A simple staged procedure using a central slip facilitation device is a valid alternative in the management of severe Dupuytren's proximal interphalangeal joint contracture, demonstrating reliable, reproducible correction of the deformity and acceptable patient outcomes [38].
Complications
- In a patient series of 18 patients, the Y-shaped tendon graft provided good or excellent results in 16 of 18 patients for the correction of chronic boutonniere deformity [13].
- Extension splinting of the MP joint may be effective if traumatic thumb injuries are treated before development of a boutonnière deformity [14].
- The case extends understanding of congenital boutonniere deformity as various embryonic developmental failures and suggests a reliable surgical option involving central slip reconstruction [15].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a boutonnière deformity is established in the thumb [18].
- This article summarizes current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries [20].
- This validation reassures the reliability of the research in understanding the pathomechanics of boutonniere deformity [21].
- In a cadaver model, detachment of the central slip from the middle phalanx produced a decrease in extension of the PIP joint [22].
- When the transverse and oblique fibers of the interosseous hood were also divided after central slip detachment, extension at the PIP joint was further decreased [22].
- A boutonniere deformity occurred only when all 3 structures (central slip, transverse and oblique fibers of the interosseous hood, and triangular ligament) were damaged [22].
- Division of the central slip leads to loss of extension at the PIP joint [22].
- The prevalence of finger deformities in patients with established rheumatoid arthritis is approximately 14% for swan-neck deformities and 36% for boutonniere deformities [23].
- In the later stages of both swan-neck and boutonniere deformities, soft-tissue procedures alone may not result in lasting operative correction [23].
- Long-term results following soft tissue reconstruction are unreliable [24].
- Recurrent or persistent deformity is best treated with a salvage procedure [24].
- Treating swan neck and boutonniere deformities of the PIP joint is a difficult challenge that requires understanding the cause, biomechanical changes, and articular status [26].
- Anterior dislocation of the proximal interphalangeal joint is associated with ruptures of the central slip of the extensor mechanism [27].
- Anterior dislocation of the proximal interphalangeal joint results in boutonnière deformity unless repaired [27].
Recovery
Non-Operative Management
- Serial casting for adequate extension followed by 3 months of relative motion flexion (RMF) orthotic use should be attempted prior to surgical intervention for chronic boutonniere deformity [9].
- Chronic boutonniere deformity responds to relative motion flexion splinting if serial casting places the proximal interphalangeal joint in less than -20° extension and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion [12].
- Extension splinting of the metacarpophalangeal joint may be effective for traumatic thumb boutonniere injuries if treated before the development of a boutonnière deformity [14].
Operative Management
- A staged technique allows the surgeon to divide the traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- The Y-shaped tendon graft provided good or excellent results in 16 of 18 patients for the correction of chronic boutonniere deformity [13].
- Reconstruction of the central slip by the transverse retinacular ligament is indicated in cases in which the central slip is defective and conservative treatment is not effective, but is not indicated for boutonnière deformities with severe contracture of the lateral band [8].
- A simple method of repair for the correction of the rheumatoid boutonnière deformity has been described [11].
- A new surgical technique with early mobilization for chronic boutonniere deformity was reported to be an effective and simplified treatment in 11 cases [10].
- Central slip reconstruction is a reliable surgical option for the congenital form of boutonniere deformity [15].
Outcomes and Prognosis
- Early treatment of central slip injuries can prevent the boutonniere deformity [5].
- Long-term results following soft tissue reconstruction for boutonniere finger deformity in rheumatoid arthritis are unreliable, and recurrent or persistent deformity is best treated with a salvage procedure [24].
- In the later stages of rheumatoid boutonniere deformities, soft-tissue procedures alone may not result in lasting operative correction [23].
- A patient with boutonniere deformity of the second toe after planter dislocation of the proximal interphalangeal joint reported neither deformity nor difficulty when last seen 22 months after the operation [95].
Key Evidence
- [L4] With this plan of management, the surgeon is able to divide the boutonniere deformity into various categories and then use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery. [1] (10.1016/s0363-5023(83)80009-4)
- [L5] Differentiating a true boutonniere deformity from a pseudoboutonniere injury is critical in determining clinical management. [2] (10.1016/j.jhsa.2022.10.019)
- [L4] A retrospective study of fifty-four longstanding post-burn boutonnière deformities was carried out to evaluate the problems associated with the surgical procedures. [3] (10.1016/0266-7681(86)90006-9)
- [L5] An understanding of the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities. [4] (10.5435/jaaos-d-14-00272)
- [L5] The paper outlines the anatomy, pathoanatomy, and treatment concepts for boutonniere deformity, emphasizing that early treatment of central slip injuries can prevent the deformity. [5] (10.1016/s0749-0712(21)00060-3)
- [L4] Transection of the terminal extensor tendon is a useful procedure for salvage of the boutonniere deformity. [6] (10.1016/s0749-0712(21)00065-2)
- [L4] No boutonniere deformities were produced in this series of 20 patients who had chronic mallet finger deformity. [7] (10.1016/s0363-5023(87)80205-8)
- [L4] This procedure is not indicated for boutonnière deformities with severe contracture of the lateral band; its best indication is in cases in which the central slip is defective and conservative treatment is not effective. [8] (10.1016/0266-7681(90)90080-n)
- [L4] Similar results occurred for chronic boutonniere deformity using serial casting for adequate extension followed by 3 months of RMF orthotic use, which should be attempted prior to surgical intervention. [9] (10.1016/j.jht.2023.02.005)
- [L4] Our technique is an effective and simplified treatment of Boutonniere deformity. [10] (10.1097/bth.0000000000000152)
- [L4] The natural history of the boutonnière deformity in rheumatoid arthritis is outlined, and a simple method of repair is described. [11] (10.2106/00004623-196951070-00009)
- [L4] Chronic boutonniere deformity will respond to relative motion flexion splinting if serial casting can place the proximal interphalangeal joint in less than -20° extension, and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion. [12] (10.1097/sap.0000000000002307)
- [L4] The Y-shaped tendon graft can be a useful procedure for the correction of chronic boutonniere deformity; in our patient series, this provided good or excellent results in 16 of 18 patients. [13] (10.1016/j.jhsa.2021.01.003)
- [L4] Extension splinting of the MP joint may be effective if these injuries are treated before development of a boutonnière deformity. [14] (10.1016/s0266-7681(00)80024-8)
- [Case_report] The case extends understanding of congenital boutonniere deformity as various embryonic developmental failures and suggests a reliable surgical option involving central slip reconstruction. [15] (10.1016/j.jhsa.2014.05.030)
- [L4] In chronic boutonniere deformity, when the lateral bands are deficient or damaged, the cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results. [17] (10.1016/j.jhsa.2017.04.010)
- [L4] Extension splinting may be effective if treated before deformity development, but surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a boutonnière deformity is established. [18] (10.1054/jhsb.1999.0303)
- [L3] The prevalence of boutonnière deformity without rheumatoid arthritis or trauma is approximately 13%. [19] (10.1177/1753193417704610)
- [L5] This article summarizes current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries. [20] (10.1016/j.jhsa.2013.11.018)
- [L5] This validation reassures the reliability of the research in understanding the pathomechanics of boutonniere deformity. [21] (10.1186/s13018-025-06329-3)
- [L5] [22] (10.1016/j.jhsa.2017.07.011)
- [L5] [23] (10.5435/00124635-199903000-00002)
- [L5] Long-term results following soft tissue reconstruction are unreliable, and recurrent or persistent deformity is best treated with a salvage procedure. [24] (10.1016/j.jhsa.2011.05.029)
- [L4] Treating swan neck and boutonniere deformities of the PIP joint is a difficult challenge that requires understanding the cause, biomechanical changes, and articular status. [26] (10.1016/j.hcl.2017.12.006)
- [Paper] [28] (10.1016/j.hcl.2012.05.044)
- [Paper] In a cadaveric model, the central slip, triangular ligament, and oblique fibers need to all be damaged to cause subluxation of the lateral bands which leads to an acute boutonniere deformity. [29] (10.1016/s0363-5023(12)60014-8)
- [L4] The use of RMFO is effective in increasing active distal interphalangeal joint flexion and improving PIP extension in patients with Burton stage 1 chronic boutonniere deformity. [30] (10.1016/j.jhsa.2022.08.007)
- [Paper] The test detects disruption of the central slip before the boutonniere deformity becomes established and is applicable in uncooperative children and unconscious patients. [34] (10.1016/0266-7681(94)90057-4)
- [L4] The simple staged procedure is a valid alternative in the management of severe Dupuytren's PIPJ contracture, demonstrating reliable, reproducible correction of the deformity and acceptable patient outcomes. [38] (10.1177/1753193412439673)
- [L4] [92] (10.1177/1758998318822663)
- [Case_report] The patient reported neither deformity nor difficulty when last seen 22 months after the operation. [95] (10.1007/s00402-009-0816-x)
References
[1] A staged technique for the repair of the traumatic boutonniere deformity. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80009-4
[2] Boutonniere Versus Pseudoboutonniere Deformities: Pathoanatomy, Diagnosis, and Treatment. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.019
[3] Reconstructive surgery of the post-burn boutonnière deformity. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90006-9
[4] Posttraumatic Boutonnière and Swan Neck Deformities. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-14-00272
[5] BOUTONNIERE DEFORMITY. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00060-3
[6] TREATMENT OF THE CHRONIC BOUTONNIERE DEFORMITY BY EXTENSOR TENOTOMY. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00065-2
[7] Central slip tenotomy for chronic mallet finger deformity. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80205-8
[8] Reconstruction of the Central Slip by the Transverse Retinacular Ligament for Boutonnière Deformity. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681(90)90080-n
[9] The relative motion concept in acute and chronic boutonniere deformity: Invited commentary. Journal of Hand Therapy. 2023. DOI: 10.1016/j.jht.2023.02.005
[10] Chronic Boutonniere Deformities, Supple, or Stiff: A New Surgical Technique With Early Mobilization in 11 Cases. Techniques in Hand & Upper Extremity Surgery. 2017. DOI: 10.1097/bth.0000000000000152
[11] Correction of the Rheumatoid Boutonnière Deformity. The Journal of Bone & Joint Surgery. 1969. DOI: 10.2106/00004623-196951070-00009
[12] A Paradigm Shift in Managing Acute and Chronic Boutonniere Deformity. Annals of Plastic Surgery. 2020. DOI: 10.1097/sap.0000000000002307
[13] Y-Shaped Tendon Graft—A Technique in the Reconstruction of Posttraumatic Chronic Boutonniere Deformity. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.01.003
[14] Traumatic Boutonnière Deformity of the Thumb. Journal of Hand Surgery. 2000. DOI: 10.1016/s0266-7681(00)80024-8
[15] Restoration of the Central Slip in Congenital Form of Boutonniere Deformity: Case Report. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.05.030
[16] Extensor Tenotomy for Chronic Boutonniere Deformity of the Finger: REPORT OF TWO CASES.. The Journal of Bone and Joint Surgery. American Volume. 1965.
[17] Chronic Boutonniere Deformity: Cross-Lateral Band Technique Using Palmaris Longus Autograft. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.04.010
[18] TRAUMATIC BOUTONNIÈRE DEFORMITY OF THE THUMB. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2000. DOI: 10.1054/jhsb.1999.0303
[19] Thumb boutonnière deformity without rheumatoid arthritis or trauma. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193417704610
[20] Closed Soft Tissue Extensor Mechanism Injuries (Mallet, Boutonniere, and Sagittal Band). The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.11.018
[21] Assessment of the ligamentous stress distribution in the pathomechanics of the boutonniere deformity through a computational 3D model. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06329-3
[22] Biomechanics of the Acute Boutonniere Deformity. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.07.011
[23] Operative Correction of Swan-Neck and Boutonniere Deformities in the Rheumatoid Hand. Journal of the American Academy of Orthopaedic Surgeons. 1999. DOI: 10.5435/00124635-199903000-00002
[24] Treatment of Boutonniere Finger Deformity in Rheumatoid Arthritis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.05.029
[26] Treating the Proximal Interphalangeal Joint in Swan Neck and Boutonniere Deformities. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.006
[27] Anterior dislocation of the proximal interphalangeal joint. A cause of rupture of the central slip of the extensor mechanism.. The Journal of bone and joint surgery. American volume. 1970.
[28] Boutonnière and Pulley Rupture in Elite Athletes. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.044
[29] Biomechanics of the Acute Boutonniere Deformity. The Journal of Hand Surgery. 2012. DOI: 10.1016/s0363-5023(12)60014-8
[30] The Use of Relative Motion Flexion Orthoses for Chronic Boutonniere Deformity. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.08.007
[31] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[32] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[34] The Central Slip Tenodesis Test for Early Diagnosis of Potential Boutonnière Deformities. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90057-4
[38] Management of severe Dupuytren’s contracture of the proximal interphalangeal joint with use of a central slip facilitation device. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412439673
[41] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[92] Therapeutic management of closed central slip injuries: Outcome of a service evaluation. Hand Therapy. 2019. DOI: 10.1177/1758998318822663
[95] Boutonniere deformity of the second toe after planter dislocation of proximal interphalangeal joint: a case report. Archives of Orthopaedic and Trauma Surgery. 2009. DOI: 10.1007/s00402-009-0816-x