Patients › Elbow
远端肱二头肌撕裂
Distal biceps rupture causes sudden elbow pain, bruising, and weakness—often needing surgical repair.
您正在感受到的症状
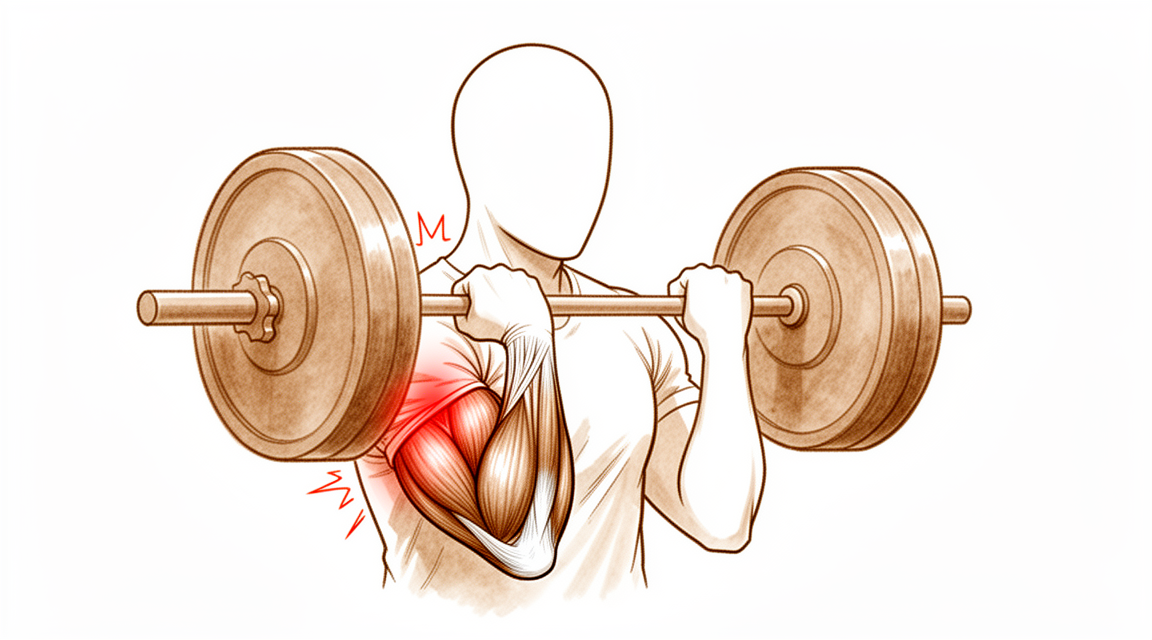
远端肱二头肌腱断裂发生在某个瞬间,而不是在数月内逐渐形成。它通常源于对屈曲 90 度的手臂突然施加的、出乎意料的伸直力量,例如接住正在掉落的重物,或在手臂被拉直时用力抓握。许多人在受伤时会感觉到或听到肘部前方“啪”的一声。肌腱通常从其在一块前臂骨上的附着点撕脱。您可能会注意到肌肉的形状发生改变,因为它沿手臂向上回缩,并在上臂中段附近聚拢。
受伤后,肘部前方很可能立即出现疼痛和肿胀。瘀伤很常见,可能在接下来的一两天内出现在肘部和前臂周围。弯曲和旋转手臂会引起疼痛,因此您可能会发现自己避免提起水壶、转动门把手或用力握住方向盘。对抗阻力将手掌向上翻转(例如使用螺丝刀)通常是最困难的动作。有些人仍然能够弯曲肘部,因为其他肌肉会协助完成这一动作,这可能使损伤感觉没有实际那么严重。
在最初的几天和几周内,疼痛通常在活动时加重,夜间也可能出现酸痛。随着身体开始在撕裂的肌腱周围愈合,疼痛会逐渐缓解。肿胀和瘀伤会在几周内消退,但力量的丧失不会自行恢复,因为肌腱已从骨头上撕脱,无法自行重新附着到原来的位置。
一些警示信号需要迅速处理。如果受伤后您的手或手指变得苍白、冰冷、发白或发蓝,或者手部突然失去感觉或无法活动,请当天前往急诊科。如果疼痛没有缓解、在数周内逐渐加重,或在夜间将您痛醒,请咨询您的全科医生或要求专科医生评估。
实际发生了什么
肱二头肌沿上臂前侧向下走行,在即将到达肘部之前变成一条强韧的索状结构,即肌腱。这条肌腱附着在一块前臂骨(桡骨)上的一个小骨突上。它的作用是旋转前臂,使手掌向上翻转,并协助弯曲肘部。
当肌腱撕裂时,它会从骨头上的那个骨突处撕脱,并沿手臂向上回缩。肌肉本身仍然健康,但已不再与它所带动的骨头相连,因此其牵拉力量无处发挥。手掌向上翻转是受影响最大的动作,因为没有其他肌肉能够接替这项工作。屈肘功能通常恢复得较好,因为肱二头肌下方的另一块肌肉会协助完成这一动作。
想象一根固定在绞盘上的绳子。如果绳子从卷筒上断开,绞盘的马达仍在运转,但什么也转不动。绳子不会自己漂回去重新系上。它需要被重新固定。
如果不加处理,撕裂的断端不会重新长回骨头上原来的位置。缺口会被瘢痕组织填充,瘢痕组织虽然能把结构连在一起,却无法恢复力量。手术会将肌腱断端重新附着到其原来的附着点,使连接能够再次牢固愈合。
这种撕裂通常发生在四十多岁至六十多岁男性的优势手臂上,最常见于手臂弯曲、掌心朝上时的一次用力过猛,例如举重。肌腱几乎总是从骨头上完全撕脱,而不是沿其长度纵向劈裂,不过也可能发生部分撕裂,即仍有部分肌腱保持附着。
我们能做什么
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会根据您的具体损伤情况匹配治疗方案。部分远端肱二头肌腱撕裂可以不通过手术进行处理,而另一些则需要在撕裂发生后尽快手术,因此及时评估非常重要。患者通常由其全科医生(GP)转诊至我们的诊所;如果理疗师建议您就诊,您仍需获得全科医生的转诊才能符合 Medicare 报销资格。在诊所,我们会采集病史、检查双侧肘部,并在有帮助时安排影像学检查。X 光通常是第一项检查,MRI 扫描可以确认肌腱是否撕裂以及撕裂的严重程度。
对于完全撕裂,即肌腱已完全从骨头上撕脱的情况,我们从一开始就建议手术。对于工作或运动需要强力旋转前臂的人(例如体力劳动者和运动员),手术通常是正确的选择。手术会将肌腱重新附着到其原来的附着点,使力量和功能得以恢复。使用小型纽扣固定进行修复可以恢复接近正常的力量和功能,而且手术的严重并发症发生率较低。修复后的大多数轻微问题是局部麻木,会随着时间推移而消退。修复在受伤后尽早进行效果最好,理想情况下在约 3 周内,因为肌腱会沿手臂向上回缩,其原来所在的空间会被瘢痕覆盖。延迟修复偶尔可行,但难度要大得多,可能需要使用肌腱移植物来恢复长度。
对于部分撕裂,即仍有部分肌腱保持附着的情况,非手术治疗有时是合理的选择。这包括用吊带或夹板让手臂休息,在撕裂愈合期间加以保护,并在手部治疗师的指导下分阶段恢复活动。选择这条路意味着以牺牲一部分力量来换取避免手术,这种权衡是您与我们之间真正的共同决定。如果掌心向上翻转时的无力对您的工作或日常生活来说无法接受,手术可能更适合您。
无论您选择哪种方案,最初几周的基本要点都是相同的:控制疼痛、在愈合期间保护手臂,以及在适当阶段进行手部治疗。术后,您的手部治疗师会指导您的康复并为您制作所需的任何夹板;Extend Rehabilitation 的 Ruby Doolan 会在术后不久开始为您进行康复治疗,早期轻柔的活动通常耐受良好。
预期情况
远端肱二头肌腱断裂后的愈合是一个缓慢积累的过程,而不是一蹴而就。肌腱需要时间重新长回骨头上,力量会在数月而非数天内逐渐恢复。在最初几周,重点是在愈合期间保护手臂,疼痛和肿胀会像受伤后最初几天那样逐渐缓解。
如果您接受手术,大多数人都能重返工作岗位且工作职责无需任何调整,平均重返工作时间约为 14 周。重返运动所需时间更长。约 95% 的运动员能够重返运动,82% 能恢复到受伤前的竞技水平,所需时间约为 40 周,具体取决于运动项目。弯曲和旋转手臂的力量可以恢复到接近正常的水平。有些人会注意到与受伤前相比略有差别,尤其是在反复旋转时。
如果您的撕裂采用非手术治疗,在愈合期间会用吊带或夹板让手臂休息,并在手部治疗师的指导下分阶段逐步恢复活动。这种方案会使掌心向上翻转时留下一定程度的持久无力,这正是本页前文讨论过的权衡。
大多数人恢复良好,但如实了解可能出现的问题也很重要。修复术后的主要风险包括神经损伤(最常见的是一小片麻木区域,会随时间推移而消退)、肘部僵硬,以及修复处再次撕裂。修复处再次撕裂的几率较低,为 1.5%,一旦发生,通常是在术后 3 周内。有时可能会有新骨横跨前臂形成并限制旋转,不过出现这种情况时,力量仍可得以保持,没有可测量的差异。
一些信号需要迅速处理。如果受伤后您的手或手指变得苍白、冰冷、发白或发蓝,或者手部突然失去感觉或无法活动,请当天前往急诊科。如果疼痛或僵硬没有缓解、在数周内逐渐加重,或使您无法使用手臂,请咨询您的全科医生或要求专科医生评估。
何时就医
如果您的手臂明显畸形、损伤部位有开放性伤口,或者肢体完全无法使用,请寻求紧急医疗救治。如果受伤后您的手或手指变得苍白、冰冷、发白或发蓝,或者手部突然失去感觉或无法活动,请当天前往急诊科。本页前文已介绍过这些信号。
其他情况请先咨询您的全科医生。如果疼痛没有缓解,或者随着愈合进展,肿胀、活动或力量没有逐周改善,请咨询您的全科医生或要求专科医生评估。如果肘部前方突然出现“啪”的一声并伴有肌肉形状改变,值得尽快就医检查,因为在受伤后约 3 周内进行修复效果最好。
深入探讨
Advanced reading: the deeper science (optional)
本节内容超出了您自身治疗决策所需的范围。远端肱二头肌断裂值得额外阅读,因为它是本网站上少数几种手术能明确恢复无手术愈合所无法恢复的功能的损伤之一,这使得权衡取舍异常具体,且并发症数据异常相关。
在此,手术确实改变了功能
本站大多数比较的结论都是“无显著差异”。这一项并非如此。汇总 2,481 名患者,与保守治疗相比,手术治疗产生了更优的肘部和前臂力量及耐力, 以及更好的 DASH 评分和 Mayo 肘关节功能评分 [1]。
原因在于解剖学而非统计学。肱二头肌远端是前臂的主要旋后肌,即该肌肉在对抗阻力时将手掌向上旋转。当肌腱从桡骨上撕脱时,它会沿上臂向上回缩,无论周围其他组织如何愈合,该肌肉都无法再产生这种旋转。肘关节屈曲部分由肱肌代偿,因此屈肘功能恢复得相对较好;而旋后功能没有类似的替补肌肉。
这就是为什么功能缺失在耐力而非单次最大用力中表现得最为明显。 反复旋转动作、使用螺丝刀、转动门把手、长时间驾驶时操控方向盘,正是在这些场景中能感受到差异。
并发症率是决策的另一半
一项能够可靠恢复肌力的手术终究仍是一台手术,且该手术具有明确界定的特征。在涵盖 3,091 例患者的最大规模分析中,主要并发症发生率为 4.6% [2]。
发生的大多数情况轻微且暂时,前臂背侧因牵拉小感觉神经导致的麻木最为常见,且通常可恢复。主要并发症是那些塑造手术技术的关键因素:永久性神经损伤、异位骨化(在前臂形成新骨并限制旋转)以及再断裂。
两种入路,其权衡是真实存在的
修复手术可通过肘部前方的单一切口完成,或通过前方和后方两个较小的切口完成。两种入路从不同方向到达同一骨骼,且各自规避了不同的风险。
在 2,622 名患者中,功能评分无显著差异。单切口入路提供了更大的屈曲和前臂旋前活动范围,并降低了异位骨化和再次手术的风险,而双切口入路在其他指标上更具优势 [3]。一项针对 2,833 名患者的 2025 年荟萃分析发现了相似的模式:单切口与更优的客观功能及更少的结构性并发症相关,双切口则与降低特定感觉神经损伤的风险相关 [4]。
综合来看,选择在于前方的神经与后方的骨骼之间。两种入路均无错误,且两组作者均呼吁在问题被视为定论之前,开展更高质量的随机对照试验。
为何此处时机的重要性高于其他部位
由于肌腱回缩及其原占据空间发生瘢痕化,延迟处理会使再固定更加困难;当直接修复已不再可行时,必须采用移植物进行重建。这正是肱二头肌远端撕裂比大多数肌腱损伤需更紧急处理的实际原因,也是为何肘部前方突发疼痛性弹响并伴有肌肉形态可见改变时,值得及时评估而非采取观望等待策略的原因。
非手术治疗仍是一个合理的选择,尤其适用于对功能要求较低的手臂,以及不需要强力反复旋后动作的人群。这是一种有意为之的决定,旨在接受可测量的功能缺损,而非同一结果的次等版本。
参考文献
[1] Looney AM, Day J, Bodendorfer BM, Wang D, Fryar CM, Murphy JP, et al. 远端肱二头肌腱断裂的手术治疗与非手术治疗:系统综述与荟萃分析. J Shoulder Elbow Surg. 2022;31(4):e169-e189. https://doi.org/10.1016/j.jse.2021.12.001
[2] Amarasooriya M, Bain GI, Roper T, Bryant K, Iqbal K, Phadnis J. 远端肱二头肌腱修复术后的并发症:系统综述. Am J Sports Med. 2020;48(12):3103-11. https://doi.org/10.1177/0363546519899933
[3] Castioni D, Mercurio M, Fanelli D, Cosentino O, Gasparini G, Galasso O. 单切口与双切口技术在治疗远端肱二头肌腱断裂中的应用:比较性研究的系统综述与荟萃分析. Bone Joint J. 2020;102-B(12):1608-17. https://doi.org/10.1302/0301-620X.102B12.BJJ-2020-0822.R2
[4] Awad G, Boutros M, Hajj Youssef M, Elhassan B. 比较单切口与双切口技术在远端肱二头肌腱修复中的应用:系统综述与荟萃分析. Shoulder Elbow. 2025. https://doi.org/10.1177/17585732251399838
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Distal biceps tendon injuries typically occur in middle-aged, higher-demand patients who often require surgical reconstruction to optimize outcome and performance [24].
- Surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications regardless of approach or technique [8, 9, 11, 12].
- Distal biceps repair is associated with a 7.5% major complication rate and a 4.5% reoperation rate [7].
- A systematic review indicates a major complication rate of 4.6% after distal biceps repair [31].
- Patients should be counseled that 1 in 5 patients will have a minor complication and 1 in 20 patients will have a major complication after surgery on the distal biceps tendon [14].
- The overall frequency of reported complications is higher for single-incision distal biceps repair than for double-incision repair [1].
- Nerve injury is the most common complication following distal biceps tendon repair [38].
- The early complication rate following partial distal biceps tendon repair was 20.5% [23].
- Surgical treatment of chronic distal biceps injuries yields favorable objective and subjective outcomes [3].
- Although there may be a slightly higher immediate complication rate for chronic distal biceps ruptures, functional outcomes remain comparable with those seen in the patient population with acute distal biceps [6].
- Patients who underwent distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair [18].
- Even in the setting of a distal biceps reconstruction with graft augmentation, patients can expect low complications and good functional results [10].
- Surgical repair of the distal biceps insertion reliably regains both supination and flexion strength in appropriate patients [55].
- Athletes sustaining distal biceps tendon rupture have a high postoperative return to sport rate, independently of selected surgical technique or rehabilitation program [50].
- Surgical management of distal biceps tears was a predictor of improved patient-reported outcomes only for patients with complete tears [16].
Anatomy & Pathophysiology
Anatomy
- The biceps brachii is the primary supinator and a secondary flexor of the elbow [52].
- The short head of the biceps muscle arises from the coracoid process of the scapula [52].
- The long head of the biceps originates from the supraglenoid tubercle of the scapula and the glenoid labrum [52].
- The long head merges with the short head to form the distal biceps tendon and its medial extension, the lacertus fibrosus [52].
- The distal biceps tendon rotates 90 degrees such that the medial side of the tendon attaches to the distal portion of the radial tuberosity [52].
- The distal biceps tendon is a paratenon-covered extrasynovial tendon with three zones of blood supply [120].
- Zone 1 of the distal biceps tendon blood supply receives vessels from the brachial artery via branches extending past the musculotendinous junction to supply the bulk of the tendon [120].
- Zone 3 of the distal biceps tendon blood supply receives contributions from the posterior interosseous recurrent artery and is limited to the tendon enthesis on the radial tuberosity [120].
- Zone 2 of the distal biceps tendon is covered in a significantly thinner paratenon and receives vessels from both Zone 1 and Zone 3 sources through its extratendinous paratenon cover [120].
- The junction among the three zones of blood supply in the distal biceps tendon may be a transition area where tendon repair mechanisms are limited [120].
- The narrow passage between the lateral ulnar border and the radial tuberosity decreases by roughly 50% in pronation as compared with supination [120].
- The brachialis tendon is an intramuscular tendon at the level of the antecubital fossa and cannot be hooked away from an underlying muscle belly [37].
- The normal lacertus fibrosus often remains intact even with biceps rupture and must be discriminated from the biceps tendon during examination [34].
Pathophysiology
- Distal biceps injuries frequently occur in middle-aged males after an eccentric load to the elbow in flexion [17].
- Distal biceps tendon ruptures typically occur in the dominant arm of males during the fifth to sixth decade of life [37].
- The incidence of distal biceps tendon ruptures is 1.2 per 100,000 persons per year [37].
- Distal biceps tendon ruptures are associated with a traumatic event causing a sudden, eccentric load to a flexed and supinated forearm [37].
- Common risk factors for distal biceps tendon rupture include anabolic steroid use, body building, and smoking [37].
- Distal biceps tendon ruptures were most commonly observed in weightlifting with a slightly flexed or isometrically extended elbow and forearm supination [98].
- In a series of competitive strength athletes, the most common strength sport activities leading to distal biceps tendon rupture were deadlifting (20%) and biceps curls (13%) [119].
- Outside of sporting activities, the most common mechanisms of injury for distal biceps tendon rupture were lifting (34%) or carrying (11%) a heavy object and falling onto the outstretched arm (13%) [119].
- A hypovascular zone near the tendon insertion on the tuberosity can limit repair mechanisms in this area [52].
- A 50% narrowing of the space available for the tendon between the radius and ulna occurs in pronation as opposed to supination [52].
- Preexisting inflammatory or degenerative changes involving the distal biceps tendon predispose to rupture from the radial tuberosity [120].
- The junction among the three zones of blood supply in the distal biceps tendon is more prone to attritional injury and rupture [120].
- Rupture of the distal insertion of the biceps tendon necessarily completely eliminates the function of the muscle [52].
- Distal biceps tendon rupture has been found to result in a 30–50% decrease in supination endurance and strength [52].
- Distal biceps tendon rupture has been found to result in an approximate 20% decrease in flexion strength [52].
- Partial distal biceps tendon tears encompass a spectrum of disease from tendinopathic micro-tears to near-full-thickness rupture from the radial tuberosity [2].
- The mechanism of full-thickness distal biceps tendon tears is well reported with a defined episode of injury, deformity, pain, and weakness [2].
- Partial distal biceps tendon tears may have a variable presentation with either an insidious or acute traumatic history, pain, mechanical symptoms, and subtle examination findings [2].
- The condition of partial distal biceps tendon tears may remain undiagnosed or mismanaged, leading to a delay in treatment [2].
- The insertion site of the distal biceps tendon on the radial tuberosity undergoes degenerative changes that begin with partial tearing of the tendon [40].
- Degenerative changes at the distal biceps insertion can be painful but also clearly can be asymptomatic [40].
- Patients with distal biceps ruptures often show signs of significant chronic degeneration with partial tearing before the acute rupture [40].
- Many patients with distal biceps ruptures deny having any symptoms referable to their distal biceps insertion before the acute event that caused them to present for treatment [40].
- Partial biceps tendon tears may result from an acute event or tearing in conjunction with chronic degeneration [40].
Classification
- Partial distal biceps tendon tears encompass a spectrum of disease ranging from tendinopathic micro-tears to near-full-thickness rupture from the radial tuberosity [2].
- Full-thickness distal biceps tendon tear patients tend to present acutely [2].
- Recommended management algorithms for partial distal biceps tendon tears typically focus on patient factors and a tear percentage of 50% as a guide for conservative treatment versus repair [2].
- The '50%-rule' on a 2-dimensional MRI measurement is likely an over-simplified parameter for a complex three-dimensional structure with known anatomical variants [2].
- Isolated short head ruptures are a rare and distinct form of distal biceps tear that present with consistent clinical findings that can aid in diagnosis [19].
- The incidence of women sustaining a distal biceps tendon tear is 3.2% [20].
- Partial tears are statistically more common than complete ruptures in women sustaining a distal biceps tendon tear [20].
- Injury to the distal biceps typically occurs in middle aged, higher demand patients who often require surgical reconstruction to optimize outcome and performance [24].
- Distal biceps tendon ruptures occur at a rate of 1.2 ruptures per 100,000 persons per year [47].
- Distal biceps tendon ruptures account for approximately 3% of all biceps tendon injuries [47].
- Distal biceps tendon ruptures remain a predominately male injury, possibly due to the larger cross-sectional area of biceps in men [47].
- Distal biceps tendon injuries are most likely traumatic events arising when sudden extension load is applied to a flexed, supinated arm [47].
- The aetiology of biceps tendon ruptures is most likely multifactorial, involving a variety of mechanical, degenerative and hypovascular factors [47].
- Seiler et al. discovered three vascular zones in the tendon and reported an approximately 2 cm zone of hypovascularity between the proximal and distal zones [47].
- A more than 50% decrease in the cross sectional area available for the tendon from full supination to full pronation leads to an increased risk for rupture [47].
- Kannus and colleagues reported degenerative tendinopathy in ruptured tendons, based on histopathologic findings [47].
- Smokers have a 7.5 times higher risk of a total rupture compared with non smokers [47].
- Smoking along with anabolic steroids may be related to tendon degeneration and rupture [47].
- There was a 7-fold increase in the incidence of distal biceps tendon rupture surgery in Finnish men during 1997 to 2016 [25].
- There was a 28-fold increase in the incidence of distal biceps tendon rupture surgery in Swedish men during 1997 to 2016 [25].
Clinical Presentation
Epidemiology and Risk Factors
- Distal biceps tendon ruptures typically occur in the dominant arm of males during the fifth to sixth decade of life at a rate of 1.2 per 100,000 persons per year [37].
- The vast majority of complete distal biceps tendon ruptures occurs in men between 40 and 60 years of age [46].
- The dominant limb is involved in 52% of complete distal biceps tendon rupture cases [46].
- An 8% cumulative incidence of bilateral biceps tendon ruptures has been reported [46].
- The incidence of women sustaining a distal biceps tendon tear is 3.2%, with partial tears being statistically more common than complete ruptures in women [20].
- In women, distal biceps tendon ruptures are described as having a more gradual onset of symptoms and a higher incidence of partial tears [46].
- There was a 7-fold increase in the incidence of distal biceps tendon rupture surgery in Finnish men between 1997 and 2016 [25].
- There was a 28-fold increase in the incidence of distal biceps tendon rupture surgery in Swedish men between 1997 and 2016 [25].
History and Mechanism
- Patients with full-thickness distal biceps tendon tears tend to present acutely [2].
- Distal biceps tendon ruptures are associated with a traumatic event which causes a sudden, eccentric load to a flexed and supinated forearm [37].
- A patient typically relates a history of lifting an object or a forced extension of a flexed and loaded forearm [40].
- The patient may recall an audible pop over the anterior elbow [37].
- Patients with chronic and slowly degenerative partial tears often complain of nonspecific elbow pain that is worsened with daily activities [40].
Physical Examination Findings
- A patient with biceps pathologic conditions exhibits pain and weakness in flexion and supination [34].
- Ecchymoses in the antecubital fossa may be present in patients with biceps pathologic conditions [34].
- An abnormal muscle contour of the biceps may be observed in patients with biceps pathologic conditions [34].
- Inspection of the soft tissues tends to demonstrate swelling of the soft tissues in the antecubital fossa [37].
- Retraction of the muscle belly with a visible bulge, known as a reverse Popeye deformity, is a clinical finding supporting the diagnosis of distal biceps rupture [37].
- Weakness in flexion and supination is a clinical finding supporting the diagnosis of distal biceps rupture [37].
- Bruising is a clinical finding supporting the diagnosis of distal biceps rupture [37].
- If seen a few days after the injury episode, ecchymosis is commonly present over the elbow and proximal forearm [40].
- Patients often point out the asymmetry and the "Pop-eye" deformity in the biceps muscle belly [40].
- In partial tears, the biceps may still be palpable [40].
- Patients with chronic partial tears often point to the anterior middle aspect of the antecubital fossa but do not specifically point to the posterolateral aspect of the elbow or the area of the radial tuberosity [40].
- Pain elicited by deep palpation of the radial tuberosity from the posterolateral aspect while passively pronating the forearm is a good indication of tendinopathy involving the insertion of the distal biceps [40].
- Isolated short head ruptures present with consistent clinical findings that can aid in diagnosis [19].
Diagnostic Tests
- The hook test involves having the patient's elbow in 90° of flexion and full supination, then hooking a finger around the lateral edge of the distal biceps tendon as it spans the antecubital fossa [37].
- The hook test has proven 100% sensitivity and specificity for making a prompt diagnosis of distal biceps rupture [37].
- The hook test allows for the distinction between complete avulsion, which results in an abnormal hook test, and partial avulsion, which yields a painful hook test [37].
- O'Driscoll hook test sensitivity is not 100% but remains a useful clinical test to assess patients with suspected distal biceps tendon tears [81].
- A negative O'Driscoll hook test does not exclude rupture [81].
- The evidence-based diagnostic algorithm using the combination of the Flexion Initiation Test (FIT) and hook test demonstrates high accuracy for the diagnosis of both complete and high-grade partial distal biceps tendon tears [33].
- Missed injuries have been attributed to the examiner palpating an intact brachialis tendon, which is an intramuscular tendon at the level of the antecubital fossa and cannot be hooked away from an underlying muscle belly [37].
- Occasionally, some fibers or a fascial sleeve may remain intact, giving an appearance of an intact tendon [34].
- The examiner must discriminate between the normal lacertus fibrosus, which often remains intact even with biceps rupture, and the biceps tendon [34].
Imaging
- Plain film radiographs are most commonly normal and do not show pathologic changes in distal biceps ruptures [34].
- Biceps ruptures typically do not involve bony ruptures, and minimal changes are seen on standard radiographs of the elbow [34].
- MRI may show rupture but is unnecessary in most cases and occasionally may be read as falsely negative [34].
- Some authors suggest a 100% correlation between MRI findings and intraoperative findings for distal biceps ruptures [34].
- MRI did not affect the operative plan in the setting of rupture of a previously repaired ruptured distal biceps tendon [34].
- MRI is useful to exclude alternative diagnoses and to evaluate the extent of suspected partial rupture [34].
- MRI is useful in cases where the history suggests a biceps rupture but the clinical examination is unclear [34].
- MRI tells the surgeon the expected location of the distal tendon end and whether it has retracted proximally [34].
- MRI findings suggestive of complete rupture include absence of the tendon insertion or a fluid-filled sheath [34].
- Partial ruptures on MRI are typically seen as high signal intensity, fluid within the tendon sheath, or thinning or thickening of the tendon distally [34].
- The FABS view (shoulder abducted over the head, elbow in 90 degrees of flexion, forearm in supination) has been suggested to improve visualization of the distal biceps insertion into the radial tuberosity [34].
- Ultrasound is a lower-cost diagnostic tool that is usually unnecessary but has been shown to be accurate in the diagnosis of complete or partial tears [34].
- Ultrasound findings suggestive of complete rupture include tendon absence, fluid, and mass in the antecubital fossa [34].
- Incomplete rupture on ultrasound may be represented by a focal hypoechogenic area or thinning of the tendon [34].
- Advanced imaging with MRI or ultrasonography is helpful in cases of partial avulsions as it can assess the biceps insertion [37].
- The finding that distal biceps MRI signal changes consistent with tendinopathy are common even in asymptomatic elbows reduces the probability that symptoms correlate with pathology on imaging [42].
- The prevalence of distal biceps tendon signal changes on MRI in asymptomatic patients is very low [43].
Investigations
Clinical Examination
- The hook test has proven 100% sensitivity and specificity for making a prompt diagnosis of distal biceps tendon rupture [37].
- Missed injuries have been attributed to the examiner palpating an intact brachialis tendon, which is an intramuscular tendon at the level of the antecubital fossa and cannot be hooked away from an underlying muscle belly as in the case of an intact distal biceps tendon [37].
- On clinical examination, a patient with biceps pathologic conditions exhibits pain and weakness in flexion and supination and sometimes ecchymoses in the antecubital fossa or an abnormal muscle contour of the biceps [34].
- With the elbow at 90 degrees of flexion, the examiner may ask the patient to rotate the pronated forearm into supination; normally, the examiner can hook the tip of his or her thumb around the biceps tendon in the cubital fossa, but with distal avulsion of the tendon, this may be impossible [34].
- Deep palpation of the radial tuberosity from the posterolateral aspect while passively pronating the forearm sometimes elicits pain, which is a very good indication of tendinopathy involving the insertion of the distal biceps [40].
Imaging
- Plain film radiographs should be obtained but are most commonly normal and do not show pathologic changes, as biceps ruptures typically do not involve bony ruptures [34].
- MRI may show rupture, but it is unnecessary in most cases and occasionally may be read as falsely negative [34].
- Some authors suggest a 100% correlation between MRI findings and intraoperative findings for distal biceps rupture [34].
- If obtained, the surgeon should view the MRI images themselves, as the radiologic interpretation is just an interpretation [34].
- In the setting of rupture of a previously repaired ruptured distal biceps tendon, MRI did not affect the operative plan [34].
- MRI may be useful to exclude alternative diagnoses and to evaluate the extent of suspected partial rupture [34].
- MRI may be useful in cases in which the history suggests a biceps rupture but the clinical examination is unclear [34].
- Positioning the prone patient with the shoulder abducted over the head and the elbow in 90 degrees of flexion and the forearm in supination (the FABS view) has been suggested to improve visualization of the distal biceps insertion into the radial tuberosity [34].
- Obtaining an MRI view of the elbow during flexion, abduction, and supination allows for optimal evaluation of the tendon along its long axis and minimizes error by reducing volume averaging [37].
Treatment
Non-Operative Management
- Nonoperative management of complete distal biceps tendon ruptures does not restore function to the elbow [45].
- Conservative treatment is a viable option for very low-demand patients who have concerns about problems connected to surgery [86].
- For partial distal biceps tears, nonoperative treatment is recommended initially if less than 50% of the tendon is involved [86].
- Patients with partial distal biceps tears should be treated nonoperatively for the first 3 to 6 months [87].
- Patients with partial distal biceps tears are encouraged to avoid heavy lifting and use the arm primarily for activities of daily living only [87].
- Strengthening exercises and physical therapy are unnecessary for patients with partial biceps tendon ruptures [87].
- In a cohort study, 82% of participants with partial distal biceps tears had failed non-surgical treatment [86].
- In a study by Bauer et al., 55.7% of patients who tried a nonoperative course for partial distal biceps tears ultimately underwent surgery [36].
- High-need patients, as defined by occupation, were more likely to report ideal recovery if they underwent surgery compared to those who did not [36].
- An MRI-diagnosed tear of greater than 50% was a predictor of needing surgery for partial distal biceps tears [36].
- A meta-analysis showed the superiority of surgical management over the nonoperative approach for distal biceps tendon detachment, with superior flexion and supination strength and better patient-reported outcomes [73].
- In two case reports of nonoperative management for distal biceps tendon rupture, flexion and supination strength returned to normal limits when compared with the opposite upper extremity [22].
Operative Management
- Surgical reinsertion of the biceps tendon to the radial tuberosity is considered the treatment of choice for most complete ruptures [112].
- Although there may be a slightly higher immediate complication rate for chronic distal biceps repairs, functional outcomes remain comparable with those seen in the patient population with acute distal biceps [6].
- Patients undergoing distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair [18].
- Patients can be consulted that direct repair in the acute setting is preferred; however, even in the setting of a distal biceps reconstruction with graft augmentation, they can expect low complications and good functional results [10].
- Distal biceps tendon repair surgery can be safely and successfully executed with either a single- or double-incision approach [48].
- Single anterior incision with suture anchor repair may be utilized for repair of ruptures of the distal biceps tendon with good clinical and functional outcomes and minimal loss of range of motion and strength [80].
- Bioabsorbable interference screw fixation of distal biceps ruptures through a single anterior incision is a safe and successful technique [15].
- Anatomic reattachment of the distal biceps tendon is a successful operative treatment option [29].
- In chronic biceps tendon rupture, anatomical reinsertion is the desired surgical approach due to a high unsatisfactory results rate of 40% in non-anatomical insertion [86].
- Morrey et al. suggest performing primary distal biceps tendon repairs in up to 90 degrees of flexion [86].
- Operative treatment for significant partial distal biceps tears that do not improve after 6 months of nonoperative treatment involves taking down the remaining fibers of the distal biceps and repair to the insertion site [87].
- Operative management for significant partial distal biceps tears has been found to be satisfactory with restoration of function and resolution of symptoms through a single posterior incision [87].
- Patients who present with a classic history of a “pop” in the arm with resisted motion and sudden onset of pain should be treated as having complete biceps tears regardless of MRI findings suggestive of “partial tear” [87].
- The average time to surgery for the operative group in a study of distal biceps tendon ruptures was 9 days, ranging from 3 days to 4 weeks [69].
Complications and Outcomes
- Complication rates after distal biceps repair are low [5].
- Distal biceps repair is associated with a 7.5% major complication rate and 4.5% reoperation rate [7].
- Workers' compensation patients who underwent distal biceps tendon repair took longer to return to work and had worse DASH scores than non-workers' compensation patients [56].
Complications
- The short-term clinical influence of biceps complications on shoulder outcome is very limited [4].
- Although there may be a slightly higher immediate complication rate, the functional outcomes remain comparable with those seen in the patient population with acute distal biceps [6].
- The study examined clinical and surgical outcomes for distal biceps tendon repairs in a large cohort, finding that anterior single incision techniques were used in the majority of cases with varying fixation methods [13].
- This is a safe and successful technique for the management of distal biceps tendon ruptures [15].
- Patients that underwent distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair [18].
- Minor complications were common after distal biceps tendon repair; however, most were sensory nerve injuries that resolved with time [26].
- This is the largest analysis of complications after distal biceps repair, indicating a major complication rate of 4.6% [31].
- Complication rates after distal biceps tendon repair performed by newly trained surgeons were similar to those previously reported in large cohort studies, with nerve injury as the most common complication [38].
Complication Rates and Outcomes
Specific Complications and Risk Factors
- Timing significantly impacts surgical technique selection in distal biceps tendon ruptures, with direct repair favored for acute injuries and high flexion angle repair or allograft reconstruction for chronic cases [39].
Functional Recovery and Strength
- Distal biceps repair/reconstruction can restore near-normal flexion and supination strength [108].
Key Evidence
- [L1] The overall frequency of reported complications is higher for single-incision distal biceps repair than for double-incision repair. [1] (10.1177/2325967116668137)
- [L5] [2] (10.1177/17585732241245054)
- [L1] Surgical treatment of chronic distal biceps injuries yields favorable objective and subjective outcomes. [3] (10.1016/j.xrrt.2022.02.007)
- [L3] Nevertheless, the short-term clinical influence of biceps complications on shoulder outcome is very limited. [4] (10.1177/2325967121s00362)
- [L3] Complication rates after distal biceps repair are low. [5] (10.5397/cise.2021.00472)
- [L4] Although there may be a slightly higher immediate complication rate, the functional outcomes remain comparable with those seen in the patient population with acute distal biceps. [6] (10.1177/23259671211065772)
- [L3] Distal biceps repair is associated with a 7.5% major complication rate and 4.5% reoperation rate. [7] (10.1016/j.jse.2018.06.028)
- [L3] Surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications regardless of approach or technique. [8] (10.1016/j.jse.2017.06.021)
- [L3] Surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications regardless of approach or technique. [9] (10.1016/j.jse.2017.06.020)
- [L3] Patients can be consulted that direct repair in the acute setting is preferred; however, even in the setting of a distal biceps reconstruction with graft augmentation, they can expect low complications and good functional results. [10] (10.1016/j.jseint.2020.10.023)
- [L3] The surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications, regardless of approach or technique. [11] (10.1177/0363546517720200)
- [L3] The surgical repair of distal biceps tendon ruptures has an overall low rate of serious complications, regardless of approach or technique. [12] (10.1016/j.arthro.2017.08.065)
- [L3] The study examined clinical and surgical outcomes for distal biceps tendon repairs in a large cohort, finding that anterior single incision techniques were used in the majority of cases with varying fixation methods. [13] (10.1016/j.jse.2016.12.053)
- [L4] Patients should be counseled that 1 in 5 patients will have a minor complication and 1 in 20 patients will have a major complication after surgery on the distal biceps tendon. [14] (10.1016/j.jse.2016.02.032)
- [Paper] This is a safe and successful technique for the management of distal biceps tendon ruptures. [15] (10.1007/s00402-009-0974-x)
- [L2] Surgical management of distal biceps tears was a predictor of improved patient-reported outcomes only for patients with complete tears. [16] (10.1016/j.jhsa.2025.12.027)
- [Paper] Distal biceps injuries frequently occur in middle-aged males after an eccentric load to the elbow in flexion. [17] (10.1016/j.injury.2025.112556)
- [L3] Patients that underwent distal biceps reconstruction with a graft had similar failure rates, reoperation rates, and final range of motion compared to primary repair. [18] (10.1016/j.jse.2020.01.062)
- [L4] Isolated short head ruptures are a rare and distinct form of distal biceps tear that present with consistent clinical findings that can aid in diagnosis. [19] (10.1016/j.jse.2020.04.038)
- [L4] The incidence of women sustaining a distal biceps tendon tear is 3.2%, with partial tears being statistically more common than complete ruptures. [20] (10.1016/j.jse.2014.02.006)
- [L5] In both patients, flexion and supination strength returned to normal limits when compared with the opposite upper extremity. [22] (10.1016/j.jht.2020.03.013)
- [L4] The early complication rate following partial distal biceps tendon repair was 20.5%. [23] (10.1016/j.jhsa.2025.04.012)
- [Paper] Injury to the distal biceps typically occurs in middle aged, higher demand patients who often require surgical reconstruction to optimize outcome and performance. [24] (10.1016/j.csm.2020.02.004)
- [L4] There was a 7-fold and a 28-fold increase in the incidence of distal biceps tendon rupture surgery in Finnish and Swedish men during 1997 to 2016. [25] (10.1016/j.jhsa.2020.07.024)
- [L4] Minor complications were common after distal biceps tendon repair; however, most were sensory nerve injuries that resolved with time. [26] (10.1016/j.jhsa.2012.06.022)
- [Case_report] Anatomic reattachment of the distal biceps tendon is a successful operative treatment option. [29] (10.1186/s12891-020-03304-3)
- [L2] This is the largest analysis of complications after distal biceps repair, indicating a major complication rate of 4.6%. [31] (10.1177/0363546519899933)
- [L4] The evidence-based diagnostic algorithm using the combination of the FIT and hook test demonstrates high accuracy for the diagnosis of both complete and high-grade partial distal biceps tendon tears. [33] (10.1016/j.asmr.2021.01.010)
- [L4] [36] (10.1016/j.jse.2017.12.010)
- [L4] Complication rates after distal biceps tendon repair performed by newly trained surgeons were similar to those previously reported in large cohort studies, with nerve injury as the most common complication. [38] (10.1016/j.jse.2022.09.014)
- [L3] Timing significantly impacts surgical technique selection in distal biceps tendon ruptures, with direct repair favored for acute injuries and high flexion angle repair or allograft reconstruction for chronic cases. [39] (10.1016/j.jse.2025.07.027)
- [L4] The finding that distal biceps MRI signal changes consistent with tendinopathy are common even in asymptomatic elbows reduces the probability that symptoms correlate with pathology on imaging. [42] (10.5397/cise.2023.00164)
- [L3] The prevalence of distal biceps tendon signal changes on MRI in asymptomatic patients is very low. [43] (10.1016/j.jhsa.2022.01.020)
- [L5] Nonoperative management does not restore function to the elbow. [45] (10.1007/s11552-013-9551-4)
- [L4] [46] (10.1302/2058-5241.6.200145)
- [Paper] [47] (10.1016/j.injury.2013.01.003)
- [L4] Distal biceps tendon repair surgery can be safely and successfully executed with either a single- or double-incision approach. [48] (10.1016/j.jse.2010.11.009)
- [L4] Athletes sustaining distal biceps tendon rupture have a high postoperative return to sport rate, independently of selected surgical technique or rehabilitation program. [50] (10.1016/j.jse.2022.02.027)
- [L4] [52] (10.1097/00130911-199812000-00005)
- [L4] Surgical repair of the distal biceps insertion reliably regains both supination and flexion strength in appropriate patients. [55] (10.5435/00124635-201003000-00003)
- [L3] WC patients who underwent distal biceps tendon repair took longer to return to work and had worse DASH scores than non-WC patients. [56] (10.1016/j.jse.2012.11.011)
- [L4] [69] (10.1016/s1058-2746(00)90059-4)
- [L1] The results of this meta-analysis showed the superiority of surgical management over the nonoperative approach for distal biceps tendon detachment, with superior flexion and supination strength and better patient-reported outcomes. [73] (10.1177/23259671211037311)
- [L4] Single anterior incision with suture anchor repair may be utilized for repair of ruptures of the distal biceps tendon with good clinical and functional outcomes and minimal loss of range of motion and strength. [80] (10.1097/bco.0000000000000529)
- [L3] O'Driscoll hook test sensitivity is not 100% but remains a useful clinical test to assess patients with suspected distal biceps tendon tears; a negative test does not exclude rupture. [81] (10.1177/1758573219847146)
- [L5] [86] (10.1530/eor-23-0035)
- [L4] Distal biceps tendon ruptures were most commonly observed in weightlifting with a slightly flexed or isometrically extended elbow and forearm supination. [98] (10.1016/j.jse.2023.02.061)
- [L5] Distal biceps repair/reconstruction can restore near-normal flexion and supination strength. [108] (10.1016/j.jhsa.2019.09.014)
- [Paper] Surgical reinsertion of the biceps tendon to the radial tuberosity is considered the treatment of choice for most complete ruptures. [112] (10.1097/bte.0000000000000011)
- [L4] [119] (10.1177/23259671251322700)
- [L5] [120] (10.1016/s1058-2746(05)80044-8)
References
[1] Complications of Distal Biceps Tendon Repair. Orthopaedic Journal of Sports Medicine. 2016. DOI: 10.1177/2325967116668137
[2] Current concepts in the aetiology, assessment and management of partial distal biceps tendon tears. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241245054
[3] Outcomes and complications after different surgical techniques for the treatment of chronic distal biceps tendon ruptures: a systematic review and quantitative synthesis. JSES Reviews, Reports, and Techniques. 2022. DOI: 10.1016/j.xrrt.2022.02.007
[4] Biceps-related complications after tenotomy associated with arthroscopic rotator cuff repair: risk factors and clinical impact. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/2325967121s00362
[5] Determining the incidence and risk factors for short-term complications following distal biceps tendon repair. Clinics in Shoulder and Elbow. 2022. DOI: 10.5397/cise.2021.00472
[6] Surgical Results of Chronic Distal Biceps Ruptures: A Systematic Review. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671211065772
[7] Major complications after distal biceps tendon repairs: retrospective cohort analysis of 970 cases. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2018.06.028
[8] Analysis of 784 surgically treated distal biceps tendon ruptures. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.06.021
[9] The distal biceps deficient arm, “the short arc syndrome”. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.06.020
[10] Outcomes of chronic distal biceps reconstruction with tendon grafting: a matched comparison with primary repair. JSES International. 2021. DOI: 10.1016/j.jseint.2020.10.023
[11] Surgical Treatment of Distal Biceps Tendon Ruptures: An Analysis of Complications in 784 Surgical Repairs. The American Journal of Sports Medicine. 2017. DOI: 10.1177/0363546517720200
[12] Paper #76: All‐Endoscopic Distal Biceps Repair: Cadaveric Portal Safety Analysis and Technical Feasibility Using 2 Fixation Techniques. Arthroscopy. 2017. DOI: 10.1016/j.arthro.2017.08.065
[13] The distal biceps deficient arm, “the short arc syndrome”. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2016.12.053
[14] Factors associated with adverse events after distal biceps tendon repair or reconstruction. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2016.02.032
[15] Bioabsorbable interference screw fixation of distal biceps ruptures through a single anterior incision: a single-surgeon case series and review of the literature. Archives of Orthopaedic and Trauma Surgery. 2009. DOI: 10.1007/s00402-009-0974-x
[16] Thirty-Six Percent Conversion to Surgery Rate for Nonsurgical Treatment of Complete and Partial Distal Biceps Tears. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.12.027
[17] Distal biceps injuries: an overview. Injury. 2025. DOI: 10.1016/j.injury.2025.112556
[18] Chronic Distal Biceps Repair with Tendon Grafting: A Matched Comparison to Primary Repair. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.01.062
[19] Distal biceps short head tears: repair, reconstruction, and systematic review. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.04.038
[20] Re-rupture rate of primarily repaired distal biceps tendon injuries. Journal of Shoulder and Elbow Surgery. 2014. DOI: 10.1016/j.jse.2014.02.006
[22] Distal biceps tendon rupture: Is surgery the best course of treatment? Two case reports. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.03.013
[23] Early Postoperative Complications Following Partial Distal Biceps Tendon Surgical Repair. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.04.012
[24] Distal Biceps Injuries. Clinics in Sports Medicine. 2020. DOI: 10.1016/j.csm.2020.02.004
[25] Distal Biceps Tendon Rupture Surgery: Changing Incidence in Finnish and Swedish Men Between 1997 and 2016. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2020.07.024
[26] Complications Following Distal Biceps Repair. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.06.022
[29] No functional differences in anatomic reconstruction with one vs. two suture anchors after non-simultaneous bilateral distal biceps brachii tendon rupture: a case report and review of the literature. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03304-3
[31] Complications After Distal Biceps Tendon Repair: A Systematic Review. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546519899933
[33] The Flexion Initiation Test and an Evidence‐Based Diagnostic Algorithm for Distal Biceps Tendon Tears. Arthroscopy, Sports Medicine, and Rehabilitation. 2021. DOI: 10.1016/j.asmr.2021.01.010
[34] Green S Operative Hand Surgery. DISTAL BICEPS RUPTURE > Diagnosis.
[36] Is nonoperative management of partial distal biceps tears really successful?. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2017.12.010
[37] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Tendinopathy, Elbow Ligament Reconstruction, and Throwing Injuries > Tendinopathy > Distal Biceps Injury.
[38] Trends and complications of distal biceps tendon repair among American Board of Orthopaedic Surgery part II oral examination candidates. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2022.09.014
[39] Effect of time from injury to surgery on surgical technique and complication rate in distal biceps tendon repair. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.07.027
[40] Green S Operative Hand Surgery. DISTAL BICEPS RUPTURE.
[42] Prevalence of incidental distal biceps signal changes on magnetic resonance imaging. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00164
[43] Evaluation of MRI Signal Changes of the Distal Biceps Tendon in Asymptomatic Patients. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.01.020
[45] Treatment of Chronic Biceps Tendon Ruptures. HAND. 2013. DOI: 10.1007/s11552-013-9551-4
[46] Acute complete and partial distal biceps tendon ruptures: what have we learned? A review. EFORT Open Reviews. 2021. DOI: 10.1302/2058-5241.6.200145
[47] Distal biceps and triceps ruptures. Injury. 2013. DOI: 10.1016/j.injury.2013.01.003
[48] Controversies in the surgical treatment of distal biceps tendon ruptures: single versus double-incision repairs. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.11.009
[50] Systematic review of distal biceps tendon rupture in athletes: treatment and rehabilitation. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.02.027
[52] Single Incision Repair of Distal Biceps Tendon Rupture. Techniques in Hand & Upper Extremity Surgery. 1998. DOI: 10.1097/00130911-199812000-00005
[55] Surgical Treatment of Distal Biceps Rupture. American Academy of Orthopaedic Surgeon. 2010. DOI: 10.5435/00124635-201003000-00003
[56] Outcomes after distal biceps repair in patients with workers' compensation claims. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2012.11.011
[69] Repair of distal biceps brachii tendon ruptures. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1016/s1058-2746(00)90059-4
[73] Operative Versus Nonoperative Management for Distal Biceps Brachii Tendon Lesions: A Systematic Review and Meta-analysis. Orthopaedic Journal of Sports Medicine. 2021. DOI: 10.1177/23259671211037311
[80] Clinical outcomes of single-incision suture anchor repair of distal biceps tendon rupture. Current Orthopaedic Practice. 2017. DOI: 10.1097/bco.0000000000000529
[81] Distal biceps hook test – Sensitivity in acute and chronic tears and ability to predict the need for graft reconstruction. Shoulder & Elbow. 2019. DOI: 10.1177/1758573219847146
[86] Distal biceps tendon rupture: a comprehensive overview. EFORT Open Reviews. 2023. DOI: 10.1530/eor-23-0035
[87] Green S Operative Hand Surgery. AUTHORS’ PREFERRED METHOD OF TREATMENT: PARTIAL BICEPS TEARS.
[98] Distal Biceps Tendon Ruptures Occur With The Almost Extended Elbow And Supinated Forearm – An Online Video Analytic Study. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2023.02.061
[108] Distal Biceps Tendon Repair and Reconstruction. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.09.014
[112] Repair and Rehabilitation of Distal Biceps Ruptures. Techniques in Shoulder & Elbow Surgery. 2014. DOI: 10.1097/bte.0000000000000011
[119] Distal Biceps Tendon Repair in Competitive Strength Athletes: A Retrospective Series of 183 Athletes. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/23259671251322700
[120] The distal biceps tendon. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80044-8