Patients › Rehabilitation
杜普伊特伦挛缩松解术
Rehabilitation after Dupuytren's fasciectomy — the extension splint regime and exercise program, with hand-therapist follow-up.
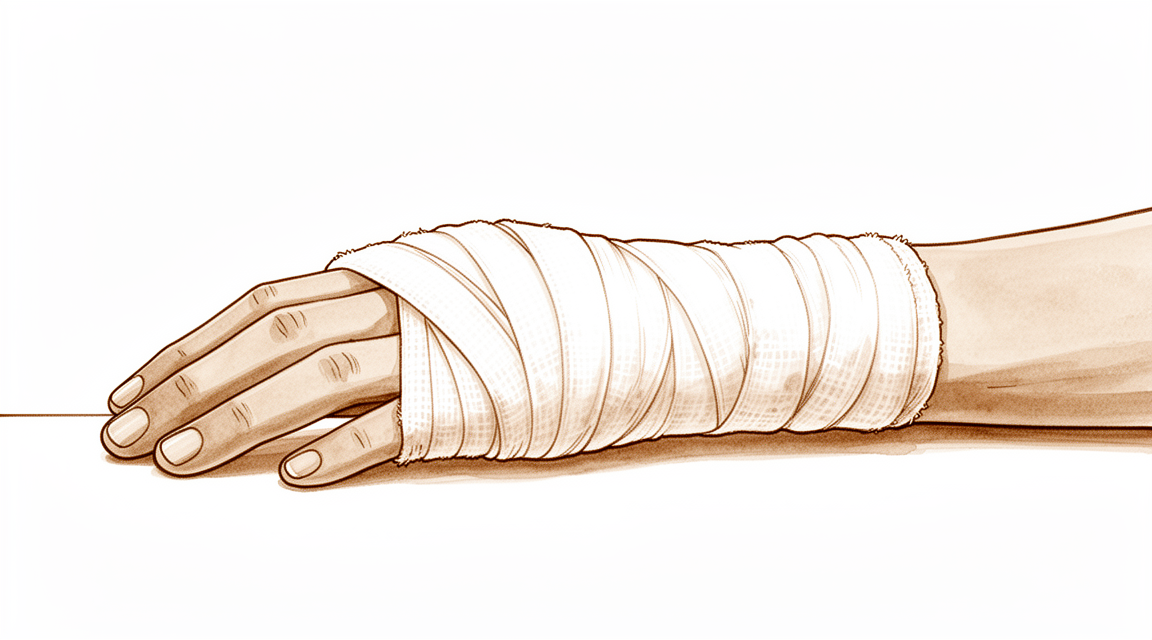
本方案指导您在 Mater Private Hospital Rockhampton 接受 Kieran Hirpara 医生进行杜普伊特伦挛缩(屈肌腱鞘纤维瘤病)手术松解(筋膜切除术)后的康复过程。获得良好疗效的两大支柱是夹板,用于在组织愈合期间保持已松解的手指伸直;以及锻炼计划,用于保持手指活动。请携带此页面或其 PDF 文件前往手部治疗师处,以确保您的康复过程协调一致。
如果您对术后伤口有任何疑虑,请联系诊所。通常,拍摄伤口照片并通过电子邮件发送以供审阅会很有帮助。
预期情况¶
针对杜普伊特伦病(Dupuytren's disease)的手术旨在切除导致手指向手掌屈曲的病变组织索带,从而恢复手指伸直的能力。该疾病本身的说明详见杜普伊特伦病页面;该病无法永久治愈,手术的目标是切除病变组织并恢复手指的伸展功能。
您通常会在术后2–3天被转诊至手部治疗师。治疗师将为您制作一个定制塑料夹板,使手术部位的手指保持在伸直(平直)位置,并指导您开始执行以下温和的锻炼计划。夹板与锻炼相辅相成:夹板保护手术所获得的伸直状态,而锻炼则保持手指的弯曲活动,防止其僵硬。
在拆线前,请保持伤口清洁干燥。拆线后,皮肤可以接触水,但在接下来的一周内,应避免将手浸泡或浸没在水中。本诊所的伤口护理页面详细涵盖了敷料、感染迹象及疤痕护理的内容。杜普伊特伦病手术后的疤痕按摩至关重要,待伤口愈合后,您的治疗师将指导您进行按摩。
疤痕护理¶
在杜普伊特伦手术后的最初几周内,手掌部位的疤痕通常质地坚硬、隆起且触痛,随后在随后的几个月内逐渐软化并淡化。疤痕按摩是澳大利亚手部治疗护理的常规组成部分:在一项针对认证手部治疗师的全国性调查中,几乎所有治疗师都在手部手术后使用该方法(通常在拆线后、伤口完全愈合时开始),以软化疤痕、改善皮肤与下方组织之间的滑动性,并缓解疤痕敏感性,通常与硅凝胶或硅片联合使用,而非单独使用 [6]。疤痕按摩的研究证据仍在发展中,但支持其用于减轻与疤痕相关的不适并改善活动度 [6]。您的治疗师将向您演示该技术,并可能添加硅产品,通常与支具一起在夜间佩戴。
恢复、工作与长期预后¶
在术后早期几周,肿胀和僵硬属于正常现象,随着手部的使用会逐渐消退;舒适度、活动度和抓握力通常会在数月内持续改善。在早期几周保持手部抬高并进行轻柔活动,有助于减轻肿胀,并防止小关节僵硬。手术所获得的伸直度通常在此阶段能得到良好维持。在一项关于杜普伊特伦挛缩松解术后康复的随机对照试验中,大多数手术手指在为期三个月的手部治疗期间,其伸直功能得以维持或改善 [2]。
停工时间取决于您的手部工作内容。在一项针对 2,500 多名杜普伊特伦病患者接受开放筋膜切开术的研究中,中位复工时间约为两周,约十分之九的患者在一年内重返工作岗位;从事体力要求较高的工作所需时间更长 [4]。Hirpara 医生将在复诊时与您讨论针对您具体工作的时间安排;较重的体力劳动通常需等到伤口牢固愈合且抓握舒适后方可进行。
由于杜普伊特伦病是一种终身性疾病,部分紧绷感可能在数年后复发,且不同研究报告的复发率差异较大,这取决于复发的定义方式。长期预后总体令人放心:在一项使用现代共识定义、对 142 例筋膜切开术进行约四年随访的研究中,真正挛缩复发发生在约 3–4% 的手部,尽管约三分之一的手部仍保留一定的残余弯曲,但通常较轻,远未达到手术时矫正的挛缩程度 [5]。夹板、疤痕护理和锻炼计划均旨在保护您的手术效果;如果任何手指在任何时候再次开始紧绷,请告知诊所。
您的夹板¶
- 大约第一周: 白天和夜间均需佩戴夹板,仅在锻炼时(以及获准清洗时)取下。
- 第一周之后: 大多数人转为仅夜间佩戴夹板,白天可开始用手进行轻度活动。
- 夜间佩戴夹板持续约 3 个月(在某些情况下长达 6 个月),以保护组织成熟期间手指不向手掌方向回缩。
- 您的手部治疗师和 Hirpara 医生将具体指导您的夹板佩戴时间表和活动安排。上述时间仅为通常模式,并非固定规则。
当您的手佩戴夹板时,严禁驾驶。 一旦转为仅夜间佩戴,只要感到舒适且能安全握住方向盘,即可恢复白天驾驶。
致您的物理治疗师 / 手部治疗师:
管理
- 术后 2–3 天转诊以制作热塑性伸指夹板
- 夹板方案:最初约一周内白天和夜间均佩戴(锻炼时取下),随后转为仅夜间佩戴,白天可进行轻度功能性使用;夜间佩戴夹板持续约 3 个月(必要时长达 6 个月),具体依外科医生/治疗师评估而定
- 家庭锻炼计划如下方卡片所示:主动伸指、阻挡性远端指间关节屈曲、笔上远端/近端指间关节屈曲、复合屈曲、腕部腱止点滑动
- 伤口护理遵循本诊所的伤口护理指南;愈合后进行瘢痕管理
- 重复次数和每日频率由主治治疗师设定
注意事项
- 拆线前保持伤口清洁干燥;拆线后一周内禁止浸泡/浸没
- 严格遵循夹板佩戴方案对于维持手术获得的伸指功能至关重要
- 手部佩戴夹板时严禁驾驶
这些是您手册中的锻炼项目,由您的手部治疗师指导开始,并在家中继续执行。
您的练习¶
Kieran Hirpara 4.0
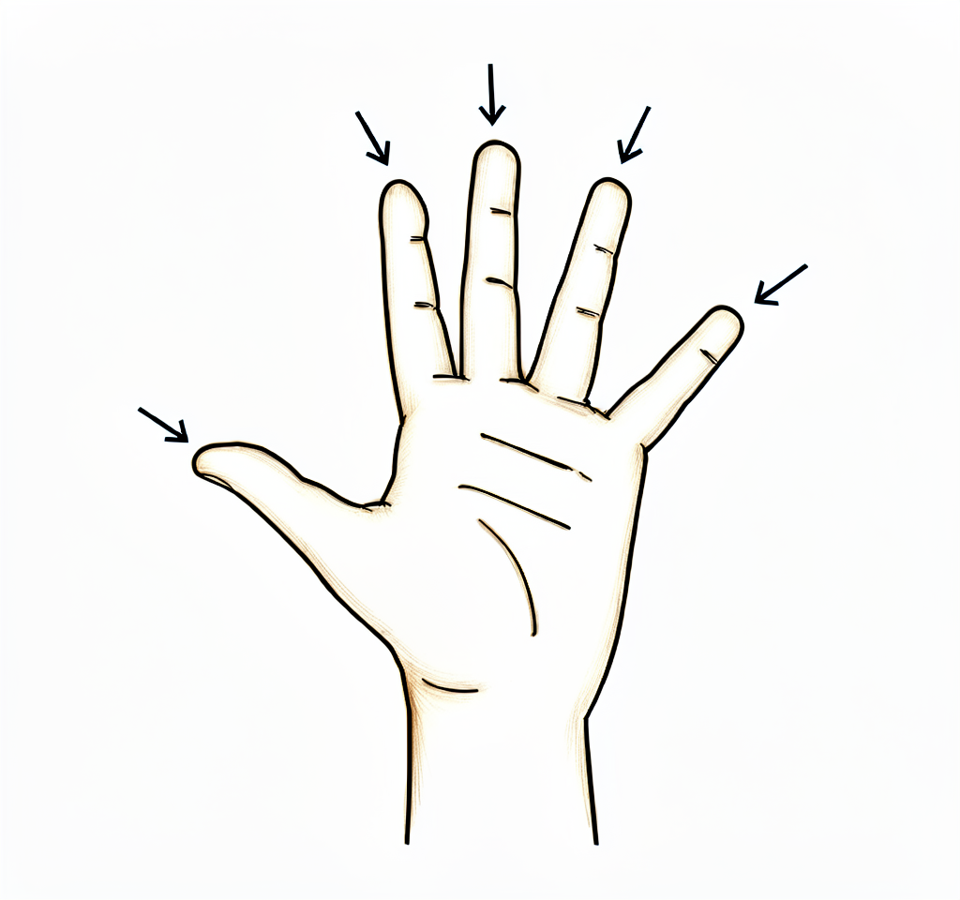
主动伸指
手腕保持伸直,将手指尽可能伸直并张开。可用另一只手轻轻辅助。放松后重复该动作。
遵从您的手部治疗师处方
Kieran Hirpara 4.0
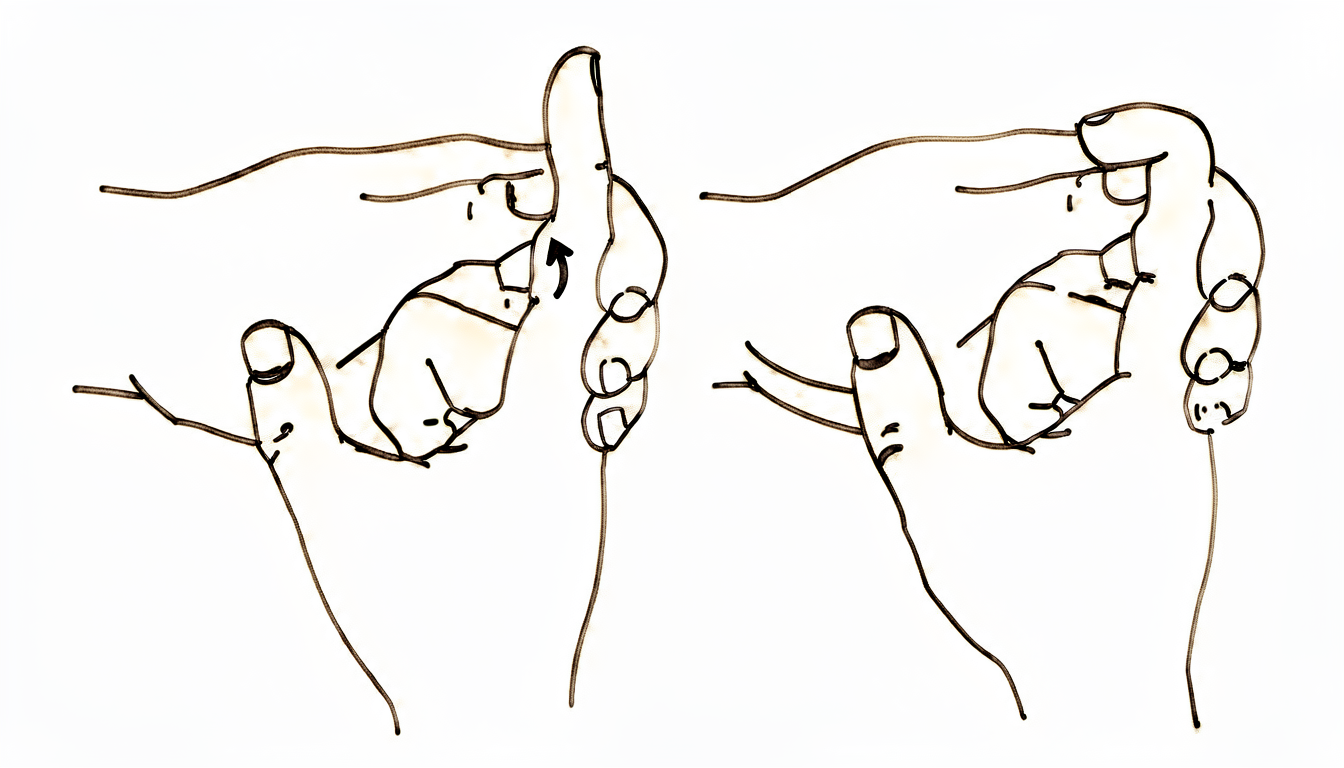
主动远端指间关节(DIP)屈曲
用另一只手在远端(DIP)关节褶皱下方支撑手指。用力弯曲远端关节,然后放松。
遵从您的手部治疗师处方
Kieran Hirpara 4.0
主动的远端指间关节/近端指间关节屈曲
将一支笔横放在手指根部。弯曲手指环绕笔身,使两个指关节(中间关节和末端关节)弯曲,然后放松。
遵从您的手部治疗师处方
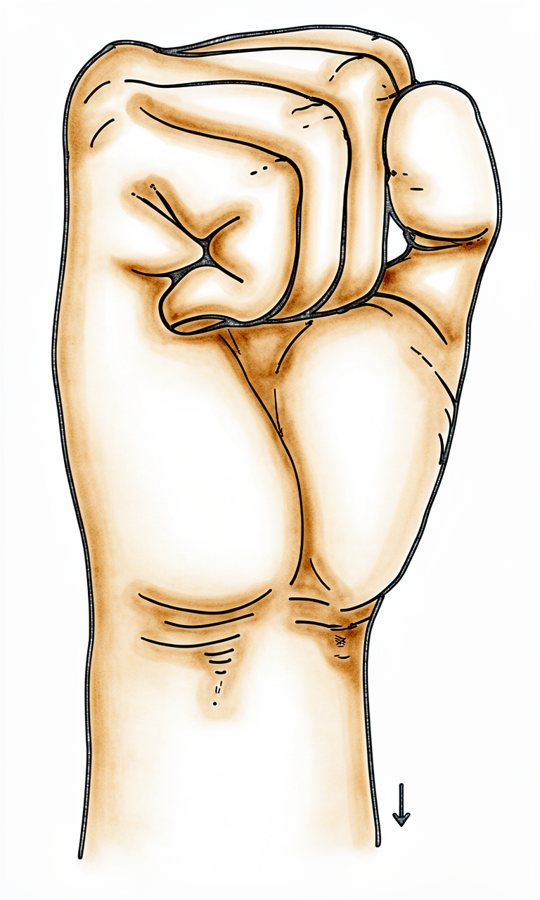
Kieran Hirpara 4.0
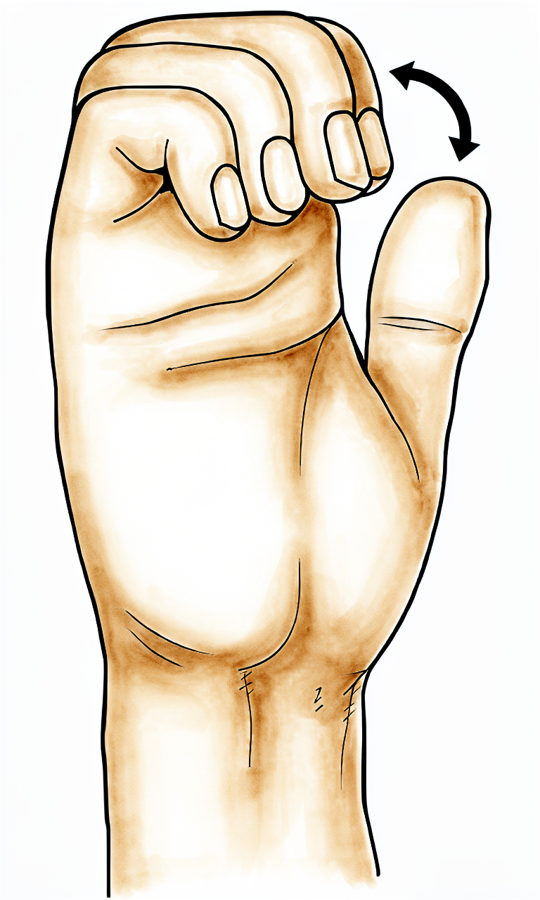
复合屈曲
轻轻握成一个松散的拳头,然后放松,让手指伸直。
遵从您的手部治疗师处方
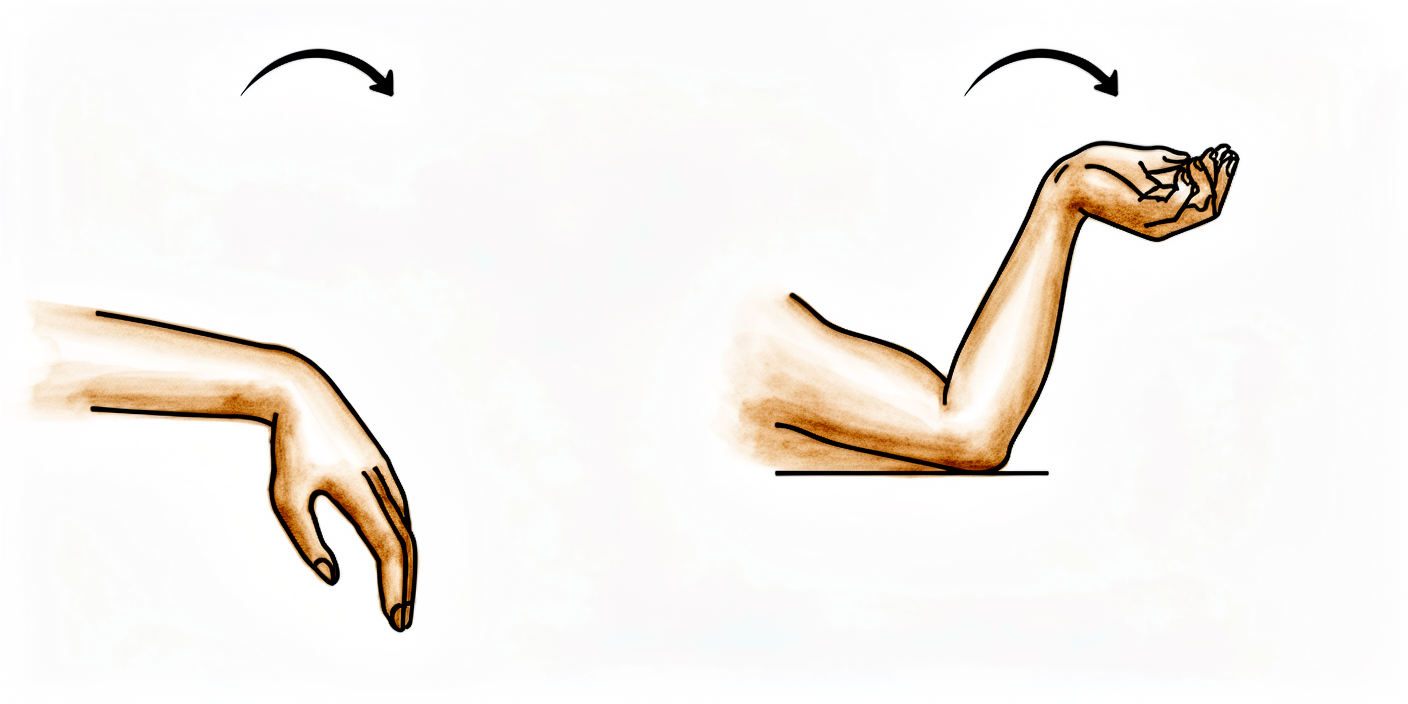
Kieran Hirpara 4.0
腕关节肌腱固定效应练习
将肘部支撑,手指放松,将手腕向前弯曲,然后向后弯曲,让手指自然跟随。
遵从您的手部治疗师处方
请仅在Hirpara医生和您的手部治疗师的指导下开始进行下面这些练习,并严格保持在您被允许的活动范围和限制内。伸直是本次手术的核心目标,因此主动伸指是优先练习——如果您放任不管,手指会回缩至弯曲位置,您保持的活动范围就是您实际能使用的范围。弯曲练习(远端指间关节、远端/近端指间关节及复合屈曲)同样重要,因为只能伸直的手指与只能弯曲的手指一样没有用处。腕部腱固定术将两者联系起来。请按指示佩戴夜间支具。停止任何引起剧烈疼痛的动作,如果某根手指开始丧失伸直能力,请告知您的治疗师。
方案之后¶
本方案由认证手治疗师 Ruby Doolan(Extend Rehabilitation)协助撰写。它与诊所的一般康复建议配合使用:请参阅术后疼痛管理、伤口护理和手部治疗基础。关于手术本身,请参阅杜普伊特伦筋膜切除术。
上述康复预期、返工数据及瘢痕护理指导均源自关于杜普伊特伦手术后康复的已发表试验、综述和调查,包括随机试验以及关于筋膜切除术后支具固定和手部治疗的系统综述 [1–3]。支具方案和锻炼计划为本诊所自有方案,由 Hirpara 医生与您的手治疗师商定,您的支具佩戴时间表将在复查时进行个体化调整。
参考文献¶
[1] Jerosch-Herold C, Shepstone L, Chojnowski AJ, Larson D, Barrett E, Vaughan SP. 针对杜普伊特伦挛缩行筋膜切除术或真皮筋膜切除术后夜间夹板固定:一项实用性、多中心、随机对照试验。BMC Musculoskeletal Disorders. 2011;12:136. https://pmc.ncbi.nlm.nih.gov/articles/PMC3146906/ [2] Collis J, Collocott S, Hing W, Kelly E. 杜普伊特伦挛缩手术松解后夜间伸展矫形器的效果:一项单中心、随机、对照试验。Journal of Hand Surgery (American). 2013;38(7):1285–1294.e2. https://doi.org/10.1016/j.jhsa.2013.04.012 [3] Karam M, Kahlar N, Abul A, Rahman S, Pinder R. 杜普伊特伦挛缩筋膜切除术后伴或不伴夹板固定的手部治疗比较:系统综述和荟萃分析。Journal of Hand and Microsurgery. 2022;14(4):308–314. https://pmc.ncbi.nlm.nih.gov/articles/PMC10042625/ [4] Blake SN, Poelstra R, Andrinopoulou ER, et al. 杜普伊特伦病治疗后的复工情况及相关成本。Plastic and Reconstructive Surgery. 2021;148(3):580–590. https://pubmed.ncbi.nlm.nih.gov/34292887/ [5] Radhamony NG, Nair RR, Sreenivasan S, et al. 杜普伊特伦掌部筋膜切除术后残留畸形与复发——142例长期随访。Annals of Medicine and Surgery. 2022;73:103224. https://pmc.ncbi.nlm.nih.gov/articles/PMC8767281/ [6] Scott HC, Robinson LS, Brown T. 疤痕按摩作为术后疤痕的干预措施:澳大利亚手部治疗师实践调查。Hand Therapy. 2024;29(1):21–29. https://pmc.ncbi.nlm.nih.gov/articles/PMC10901164/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Dupuytren Contracture — Surgical Release & Post-operative Hand-Therapy Rehabilitation (Open Fasciectomy)¶
Topic scope: post-operative rehabilitation after open excision of diseased palmar/digital fascia for Dupuytren contracture — limited/regional fasciectomy, extending to dermofasciectomy (fascia plus overlying involved skin, replaced with a graft) for aggressive or recurrent disease. The procedure-selection literature (fasciectomy vs needle aponeurotomy vs collagenase) is summarised only as far as it frames recurrence expectations and rehabilitation; the rehab focus is the post-fasciectomy pathway — early active and passive finger extension and flexion, oedema control, scar management, and night extension splinting.
Defining principle of this rehab: fasciectomy removes diseased tissue and restores extension that the disease had taken away — it does not cure the diathesis, and the corrected finger sits in a tissue bed that wants to contract back. So the rehab is a "regain-and-hold" pathway: early motion to keep the freed joints supple and prevent the new flexor-tendon and skin-glide planes from binding down, oedema and scar control so the soft tissues mature without tethering, and a night extension orthosis to defend the surgical correction during healing. The defining clinical question is not whether a construct needs protection (there is no construct), but how aggressively to splint — and here the evidence has shifted decisively toward selective, not routine, splinting.
A. PROCEDURE OUTCOMES & RECURRENCE (context for the rehab)¶
Open partial (limited) fasciectomy is the long-standing reference operation for Dupuytren contracture and gives the most durable correction of the three mainstream options:
- Correction is reliable and recurrence is the dominant long-term limitation. Across modern series the operation restores extension well, but Dupuytren is a lifelong diathesis and some tightening returns over years. Reported recurrence rates vary enormously because studies define recurrence differently (any palpable disease vs a threshold extension loss vs need for re-intervention). Using the modern consensus definition, true recurrence of contracture is low at medium-term follow-up, though a substantial minority retain mild residual curvature well short of the pre-operative deformity [corpus: jhsa.2012.06.032; literature: Radhamony 2022].
- Fasciectomy vs minimally invasive options. Compared with needle aponeurotomy/fasciotomy and collagenase Clostridium histolyticum, open fasciectomy has a longer recovery and higher minor complication rate but lower recurrence — the recurring trade-off in this disease. Needle and collagenase are quicker with faster return to function but recur sooner [corpus: jhsa.2021.05.022; jhsa.2011.08.004; 1753193418786947]. This trade-off is why fasciectomy is typically chosen for denser, multi-ray or PIP-predominant contractures — the same cases whose rehab is hardest and whose splinting is most likely to be justified.
- Repeat limited fasciectomy for recurrence is safe and effective, supporting fasciectomy as a durable, repeatable mainstay rather than a one-shot procedure [corpus: bjj-2020-1393.r2].
Why this matters for rehab: recovery counselling and splint expectations must be framed against a disease that cannot be cured, only corrected — the rehab protects a correction, it does not prevent the diathesis.
B. THE SPLINTING CONTROVERSY (the central rehab question)¶
Historically, every patient was issued a static night extension orthosis after fasciectomy on the assumption it preserved the correction. The best available evidence does not support routine splinting — it supports selective splinting for patients who lose extension.
- Jerosch-Herold 2011 (pragmatic multi-centre RCT, n = 154). Hand therapy alone vs hand therapy + night splinting after fasciectomy/dermofasciectomy. No between-group difference in self-reported function (DASH), finger range of motion, or satisfaction. Authors concluded routine night splinting for all patients is not recommended, reserving it for cases where extension deficits recur [literature: Jerosch-Herold 2011, BMC Musculoskelet Disord].
- Collis 2013 (single-centre RCT, n = 56). Night extension orthosis + hand therapy vs hand therapy alone after surgical release. No significant difference in total active extension or any secondary outcome at 3 months. Same conclusion: provide an orthosis selectively, when extension loss occurs, not universally [corpus: jhsa.2013.04.012; literature: Collis 2013].
- Karam 2022 (systematic review + meta-analysis, 4 RCTs, n = 295). Pooling the splint-vs-no-splint trials found no significant difference in total active flexion/extension, DASH, pain, grip or satisfaction. The collective signal is consistent and now moderately strong: adding a splint to good hand therapy does not improve the average outcome [corpus: 1055/s-0041-1725221; literature: Karam 2022].
- Earlier/smaller work (e.g., post-fasciectomy splinting pilot studies) pointed the same way — splinting is low-yield as a blanket policy [corpus: 1753193412437631].
Practical reading for this protocol. The practice's pattern — splint day-and-night for ~1 week, then night-only with a low threshold to continue (or reinstate) splinting if a finger starts to drift back into flexion — is a reasonable, evidence-aligned middle path: it defends the correction during the highest-risk early healing window and during sleep, while honouring the trial finding that indefinite routine splinting adds little. The trials measured average outcomes; they do not say splinting is useless for the individual who is losing extension, which is exactly the subgroup the authors carved out. This is a defensible selective-splinting stance, not a contradiction of the protocol.
C. HAND-THERAPY & EXERCISE EVIDENCE¶
- Early supervised hand therapy is the backbone of recovery and is where the demonstrable benefit lies (the splint trials all compared against a hand-therapy baseline, not against nothing). Active and passive extension and flexion, oedema control and scar management are standard from the first post-operative therapy visit, typically 2–3 days after surgery.
- Most operated fingers hold or improve their extension over the first three months of hand therapy — the window in which the protocol concentrates splinting and exercise [corpus: jhsa.2013.04.012, control arm; literature: Collis 2013].
- Scar management. Scar massage is near-universal in hand-therapy practice after Dupuytren surgery to soften the palmar scar, improve skin glide and settle sensitivity, generally combined with silicone gel/sheeting and begun around suture removal once the wound is healed. The supporting evidence is developing rather than definitive but favours reduced scar-related discomfort and improved movement [literature: Scott 2024, Australian hand-therapist survey].
- Return to work. In a large cohort, median return after open fasciectomy was ~2 weeks with ~90% back at work within the year; physically demanding jobs took longer [literature: Blake 2021].
- Pre-operative hand therapy has a thinner evidence base and is not a substitute for the post-operative programme [corpus: 17589983241227162].
Phased rehabilitation timeline (matching the synthesis phases)¶
| Phase | Window | Splint | Movement / use | Scar & oedema | Notes |
|---|---|---|---|---|---|
| I — Protect & mobilise | ~Days 2–7 | Custom thermoplastic extension orthosis day & night, off for exercises | Gentle active extension + active DIP/PIP and composite flexion from the first therapy visit; wrist tenodesis | Oedema control (elevation, gentle movement); wound kept clean & dry | Therapy referral 2–3 days post-op; splint defends the surgical correction during the highest-risk window |
| II — Restore motion | ~Week 1 → 6–8 | Transition to night-only; light functional day use of the hand | Progress active + passive extension and flexion; restore full composite fist and full extension | Scar massage + silicone once wound healed (around suture removal) | Most extension is held or regained through this window; daytime driving resumes once out of the splint and grip is safe |
| III — Strengthen & return | ~Week 6–8 → 3 months | Night-only continues ~3 months (up to ~6 months selectively if extension is being lost) | Grip and functional strengthening; return to heavier manual work as wound is soundly healed and grip comfortable | Ongoing scar maturation over months | Splinting beyond this window is selective, driven by extension loss — not routine (see §B) |
The phase structure and timings are protocol/consensus, agreed between the surgeon and hand therapist; the trials inform the splinting policy within them, not the exact week boundaries.
D. COMPLICATIONS (rehab-relevant)¶
- Flare reaction / early CRPS-spectrum. A proportion of patients develop a post-operative inflammatory "flare" — disproportionate swelling, stiffness, redness and pain — which can progress to complex regional pain syndrome (CRPS type 1). Early recognition, oedema control, gentle continued motion and analgesia matter; CRPS is one of the more feared rehab-derailing complications after hand surgery [corpus: jht.2024.09.002 (Dupuytren CRPS-1 case); hcl.2009.11.001 (CRPS after hand surgery)].
- Digital nerve / vessel injury. The neurovascular bundles are displaced by Dupuytren cords, especially in recurrent disease and at the PIP; injury is a recognised operative risk. New sensory change post-operatively warrants surgeon review [corpus: hansur.2017.07.002 — complications systematic review; 17531934231206317 — surgical complications/adverse events].
- Wound healing, haematoma, infection, stiffness. Open fasciectomy has a higher minor-complication rate than the minimally invasive options; meticulous wound care and early motion mitigate stiffness and tethering [corpus: hansur.2017.07.002].
- Incomplete correction / residual PIP deficit. PIP contractures correct less completely than MCP; residual deficit may persist and is the usual trigger for selective ongoing splinting.
E. KEY CONTROVERSIES / EVIDENCE QUALITY¶
- Routine vs selective splinting — the headline controversy, now reasonably settled toward selective: three RCTs and a meta-analysis show no average benefit from adding a static night orthosis to good hand therapy, with all authors carving out the extension-loss subgroup. The practice's "night-only, low threshold to continue if drifting" approach is consistent with this. Moderate (multiple RCTs + SR/MA).
- Recurrence is definition-dependent — headline recurrence figures are not comparable across studies; the consensus definition gives lower, more credible rates. Counsel against the cure expectation. Moderate.
- Procedure choice frames rehab — fasciectomy trades a longer recovery and more minor complications for lower recurrence than needle/collagenase. The fasciectomy cohort is, by selection, the harder-rehab cohort. Moderate.
- The phase timings are consensus — drawn from surgeon/therapist protocols, not a rehab RCT. The splinting policy within them is trial-informed; the week boundaries are typical, not trial-derived. Weak/consensus.
F. EVIDENCE STRENGTH FLAGS (summary)¶
- MODERATE (multiple RCTs + SR/MA): routine night splinting adds no average benefit over hand therapy alone after fasciectomy — splint selectively for extension loss (Jerosch-Herold 2011; Collis 2013; Karam 2022 meta-analysis of 4 RCTs / 295 patients).
- MODERATE (cohorts / comparative): fasciectomy gives durable correction with lower recurrence but longer recovery and more minor complications than needle aponeurotomy/collagenase; repeat fasciectomy is safe and effective; CRPS and digital-nerve injury are recognised rehab-relevant complications.
- WEAK / CONSENSUS: the post-operative phase structure and timings themselves (surgeon + hand-therapist protocol; no defining rehab RCT). Scar-massage benefit is supportive but the evidence base is still developing.
CITATIONS¶
RAG corpus (180,000+ Orthopaedic articles)¶
- Correction of contracture and recurrence rates of Dupuytren contracture following fasciectomy. J Hand Surg Am. 2012. DOI: 10.1016/j.jhsa.2012.06.032
- Repeat limited fasciectomy is a safe and effective treatment for recurrence of Dupuytren's contracture. Bone Joint J. 2021. DOI: 10.1302/0301-620X.103B5.BJJ-2020-1393.R2
- Limited fasciectomy versus collagenase Clostridium histolyticum for Dupuytren contracture. J Hand Surg Am. 2021. DOI: 10.1016/j.jhsa.2021.05.022
- The efficacy and safety of fasciectomy and fasciotomy for Dupuytren's contracture. J Hand Surg Eur. 2011. DOI: 10.1177/1753193410397971
- Cost-effectiveness of open partial fasciectomy, needle aponeurotomy, and collagenase injection for Dupuytren contracture. J Hand Surg Am. 2011. DOI: 10.1016/j.jhsa.2011.08.004
- Three-year recurrence of Dupuytren's contracture after needle fasciotomy and collagenase injection. J Hand Surg Eur. 2018. DOI: 10.1177/1753193418786947
- The effect of night extension orthoses following surgical release of Dupuytren contracture: a single-centre RCT. J Hand Surg Am. 2013. DOI: 10.1016/j.jhsa.2013.04.012
- Comparison of hand therapy with or without splinting postfasciectomy for Dupuytren's contracture: systematic review and meta-analysis. J Hand Microsurg. 2022. DOI: 10.1055/s-0041-1725221
- Does use of a night extension orthosis improve outcomes in patients with Dupuytren contracture? J Hand Surg Glob Online. 2021. DOI: 10.1016/j.jhsg.2021.05.001
- A pilot study assessing the effectiveness of postoperative splinting after limited fasciectomy. J Hand Surg Eur. 2012. DOI: 10.1177/1753193412437631
- Pre-operative hand therapy management of Dupuytren's disease: a systematic review. Hand Ther. 2024. DOI: 10.1177/17589983241227162
- Current concepts in the management of Dupuytren disease of the hand. J Am Acad Orthop Surg. 2020. DOI: 10.5435/JAAOS-D-20-00190
- Complications after treating Dupuytren's disease: a systematic literature review. Hand Surg Rehabil. 2017. DOI: 10.1016/j.hansur.2017.07.002
- Surgical complications: errors and adverse events (hand surgery). J Hand Surg Eur. 2023. DOI: 10.1177/17531934231206317
- The case of a woman with bilateral Dupuytren's contractures who developed CRPS-1. J Hand Ther. 2024. DOI: 10.1016/j.jht.2024.09.002
- Complex regional pain syndrome after hand surgery. Hand Clin. 2009. DOI: 10.1016/j.hcl.2009.11.001
Splinting & hand-therapy literature (URLs)¶
- Jerosch-Herold C, Shepstone L, Chojnowski AJ, et al. Night-time splinting after fasciectomy or dermo-fasciectomy for Dupuytren's contracture: a pragmatic, multi-centre, randomised controlled trial. BMC Musculoskelet Disord. 2011;12:136. https://pmc.ncbi.nlm.nih.gov/articles/PMC3146906/
- Collis J, Collocott S, Hing W, Kelly E. The effect of night extension orthoses following surgical release of Dupuytren contracture: a single-centre, randomised, controlled trial. J Hand Surg Am. 2013. https://pubmed.ncbi.nlm.nih.gov/23790420/
- Karam M, Kahlar N, Abul A, et al. Comparison of hand therapy with or without splinting postfasciectomy for Dupuytren's contracture: systematic review and meta-analysis. J Hand Microsurg. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC10042625/
- Blake SN, Poelstra R, Andrinopoulou ER, et al. Return to work and associated costs after treatment for Dupuytren's disease. Plast Reconstr Surg. 2021. https://pubmed.ncbi.nlm.nih.gov/34292887/
- Radhamony NG, Nair RR, Sreenivasan S, et al. Residual deformity versus recurrence following Dupuytren's palmar fasciectomy — long-term follow-up of 142 cases. Ann Med Surg. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC8767281/
- Scott HC, Robinson LS, Brown T. Scar massage as an intervention for post-surgical scars: a practice survey of Australian hand therapists. Hand Ther. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC10901164/
Society guidance & published rehab protocols¶
- The British Society for Surgery of the Hand (BSSH) — Dupuytren's disease patient and professional guidance. https://www.bssh.ac.uk/patients/conditions/25/dupuytrens_disease
- BSSH — Assessing the outcome of surgery for Dupuytren's disease of the hand. https://www.bssh.ac.uk/assessing_the_outcome_of_surgery_for_dupuytrens_disease_of_the_hand.aspx