Patients › Wrist
桡骨远端切开复位内固定术
Open reduction and volar plate fixation of the distal radius — operation, recovery, rehabilitation.
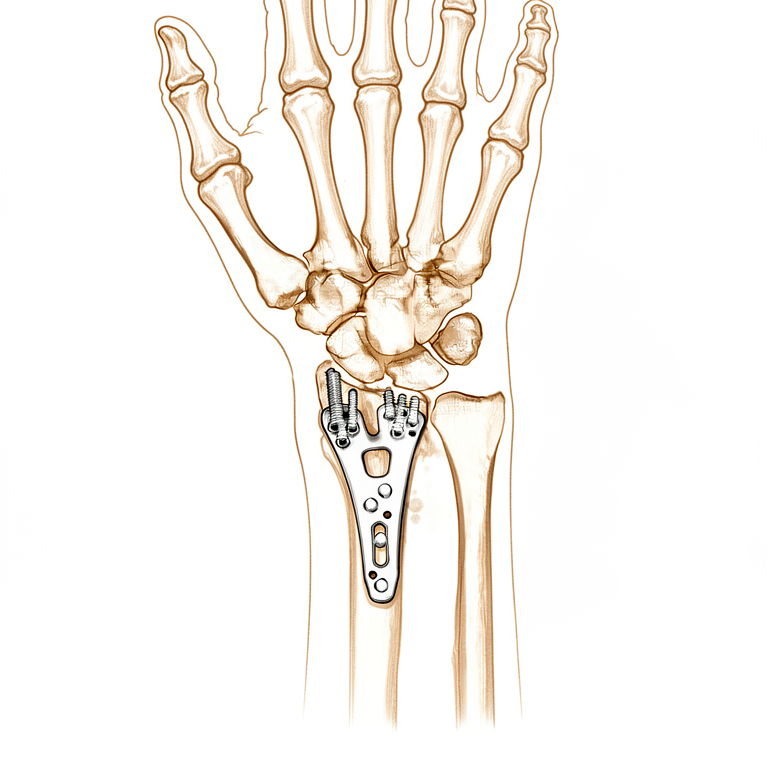
为何建议进行此手术
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会根据您的具体伤情制定治疗方案。患者通常由全科医生(GP)转诊至我们的诊所;如果物理治疗师建议您就诊,您仍需获得全科医生的转诊才能符合 Medicare 报销资格。在就诊时,我们会采集病史、检查您的手腕,并在必要时安排影像学检查。该评估结果将告诉我们骨折是否不稳定或已移位至关节内,此时通常会建议进行手术。
该手术称为切开复位内固定术。通俗地说,这意味着将断裂的骨骼恢复到正常位置,并使用小型金属板和螺钉将其固定。对于大多数此类手腕骨折,在手腕掌侧放置钢板是常规方法。对于较轻的骨折,通常会先尝试非手术治疗,如石膏或夹板固定。当骨骼不稳定或发生移位时,可能会立即建议手术,因为石膏可能无法将骨块保持在原位。
目标是让手腕在良好的位置愈合,以便您能活动手部并尽快恢复正常活动。
术前
手术当天,您需要在手术时间前七小时停止进食和饮水。我们要求七小时而非六小时,以便如果手术室手术安排提前结束,您的手术可以提前进行。您的外科医生会告诉您当天需要跳过哪些常规药物,以及哪些药物应照常服用。请携带一份您服用的所有药物的书面清单,包括药片、滴剂以及从药房购买的其他任何物品。请安排他人在术后驾车送您回家,因为您将无法自行驾驶。请穿着宽松舒适的衣物,且袖子易于脱下。
为了规划手术,我们使用从多个角度拍摄的X光片。有时还需要进行CT扫描(一种详细的X光检查)或MRI扫描(一种显示韧带等软组织的扫描)。如果您有其他健康状况,可能需要在手术当天之前进行血液检查或与麻醉师进行会诊。
手术当天
您将抵达医院的手术入院单元,在此办理入院手续并进行术前准备。您将在该处见到麻醉师。本手术在全身麻醉下进行。手术期间您将处于完全睡眠状态。部分患者可能还会接受区域神经阻滞以缓解术后疼痛;麻醉师将根据您当天的具体情况决定是否实施。
随后,您将被带入手术室进行手术。术后,您将在复苏区苏醒,护士会在此监测您的状况,直至麻醉作用消退。待您的生命体征稳定后,根据手术类型及恢复情况,您将被安排入住病房或直接回家。
手术内容
手术通过手腕掌侧的切口进行。通过这个开口,您的外科医生会将断裂的骨块复位至正常位置。随后,一块小型金属钢板被塑形以贴合骨骼,并用螺钉固定。钢板位于腕骨的前方,其与您拇指和手指的肌腱之间有一层组织。
有时,关节面本身需要更仔细的检查。在这种情况下,您的外科医生可能会使用带有微型摄像头的细长器械,在骨块对位的同时检查关节内部。这有助于在固定钢板之前确认关节面光滑且平整。
一旦骨骼被牢固固定,您的外科医生将通过术中拍摄的X光片检查其位置。随后,伤口用缝线缝合,并在表面覆盖敷料。
钢板和螺钉将永久保留在您的手腕中。它们在骨骼愈合期间起到固定作用,类似于内部夹板。在某些骨折中,需要额外的支撑。如果骨骼碎裂成多块,您的外科医生可能会在手腕背侧添加第二块钢板,或使用骨移植来填充间隙并帮助骨骼愈合。
您将带着完整的敷料回家。我们要求您保持敷料干燥,并保留约10天,届时您将再次就诊以检查伤口。
术后
苏醒后,您将被安置在恢复病房,随着麻醉药效消退,护士会密切观察您的状况。您的手腕将用软敷料包扎,我们会为您提供镇痛药物以确保舒适。通常您很快即可起身活动,首次起身时会有护理团队人员协助。由于麻醉可能导致您一段时间内站立不稳,回家后请确保有人在前24小时内陪同。大多数患者在此手术后需住院一晚,但部分患者可当日出院。敷料通常保留约10天;除非我们告知您,否则请勿提前拆除。我们将在复诊时为您更换或拆除敷料。
恢复
最初几天,您的手腕会感到疼痛和肿胀,这是正常现象。休息、将手垫高放在枕头上以及我们提供的止痛药将有助于缓解不适。肿胀通常会在接下来的几周内消退,但完全消退可能需要一段时间。
您将带着软敷料而非石膏回家,因此大多数人会发现日常生活比预期的更容易。您可以立即起身活动,并可以使用另一只手进行穿衣、进食和洗漱。请保持敷料干燥。手部治疗是您恢复过程中的重要组成部分:您将见到我们手部治疗师 Ruby Doolan(在 Extend Rehabilitation),她将指导您进行锻炼,并在需要时为您制作支具。早期活动手指有助于缓解僵硬并支持愈合。
随着时间推移,您将注意到肿胀减轻,活动能力恢复。您的治疗师将向您展示锻炼方法,以增强握力并恢复手腕的弯曲功能。一旦您感觉稳定,可以在家进行轻度活动,但在我们告知安全之前,请避免提重物或让手腕承重。在手腕愈合期间请勿驾驶;一旦拆除敷料且外科医生确认您已康复,即可恢复驾驶,关于我们上肢手术后驾驶的相关页面提供了更多说明。
每个人的愈合速度不同,因此您的时间表可能有所不同。我们将在此过程中为您提供随访,并指导您度过每个阶段。
可能出现的问题
大多数患者恢复良好,但偶尔也会出现并发症。您的外科医生和医疗团队会密切监测您的状况,以便尽早发现任何问题。
有时金属接骨板或螺钉会引起刺激。您可能会感觉到皮肤下有尖锐的骨嵴,或在活动手腕时有摩擦感。如果这让您感到不适,请在下次复诊时提出。
伸直拇指的肌腱偶尔会磨损并断裂。您会突然注意到:无法将拇指向上伸直,且拇指背侧感觉松弛。这种情况通常发生在术后3个月左右,有时没有任何预警性疼痛。如果您的拇指出现这种功能障碍,请立即联系诊所。
为拇指、食指和中指提供感觉的神经可能会受到刺激。您可能会注意到这些手指有刺痛感、针刺感或局部麻木。轻微症状很常见,通常会自行缓解。请在复诊时提及任何未改善的麻木感。
伤口感染不常见,但需要迅速处理。请注意观察:不随普通止痛药缓解的深部搏动性疼痛、从伤口向外扩散的红肿、局部发热,或液体透过敷料渗出。如果您发现这些情况中的任何一种,请立即致电诊所,或在非工作时间前往急诊科。
偶尔,骨骼在愈合前会发生移位,或愈合过程缓慢。您可能会感觉到手腕出现新的研磨感或咔哒声、疼痛加剧,或手腕失稳。请在复诊时告知我们,以便我们通过X光检查骨骼位置。
部分手腕在愈合后仍会僵硬或压痛。您可能会发现转动手部、向后弯曲手腕或握力比预期更困难。手部理疗和治疗师为您制定的练习是治疗此问题的主要手段。
吸烟以及任何形式的尼古丁(包括贴片和口香糖)会增加上述多种问题的风险,包括伤口感染、愈合缓慢以及需要再次手术。如果可能,建议在手术前戒烟。
如果您想了解具体数据,本页的并发症表格列出了典型的发病率。
何时联系我们
大多数问题都会出现预警信号。如果您出现发热,或伤口变得更红、更热或渗出液体,请联系我们。如果疼痛持续加重,且服用普通止痛药无效,请联系我们。如果您发现小腿肿胀或疼痛,或突然呼吸困难,请立即前往急诊,因为这些症状可能提示血栓形成。如果您的手指发麻且持续不缓解,或完全无法活动,请立即前往急诊。如果您的拇指无法向上伸直,请及时联系诊所。如有任何疑虑,请联系我们。
在哪里可以阅读更多关于该疾病的资料
本页介绍的是手术本身。它所治疗的疾病,包括证据显示手术在何时有效、何时无效,在远端桡骨骨折页面上有更详细的介绍。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A network meta-analysis of randomized trials found that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery and a reduction in fracture healing complications [7].
- In adults, early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization at earlier stages [1].
- The mean differences in DASH scores at 6 weeks for early mobilization compared to late mobilization surpass the minimal clinically important difference [1].
- Substantial variations in surgical direct costs for distal radius ORIF exist, with implant choice being the predominant driver [3].
- In comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance [2].
- The Lift-Off Screw (LOS) length can be calculated, and the technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft [5].
- Radial column plating of the distal radius is a safe treatment modality and a valuable adjunct in the setting of complex distal radius fractures [6].
- Patients undergoing radial column plating of the distal radius should be counseled that there is a 28% chance that hardware removal may be required [6].
- The treatment of displaced intra-articular distal radius fractures with a dorsally versus a volarly placed interlocking plate system demonstrated similar clinical results [9].
Anatomy & Pathophysiology
Bony Anatomy
- The distal radius articular surface is biconcave and consists of scaphoid and lunate facets [31].
- The distal radioulnar joint (DRUJ) articulates with the ulna at the sigmoid notch [31].
- Lister tubercle is a small dorsal prominence that serves as a landmark for the dorsal approach to the wrist [31].
- Lister tubercle is a cause of attritional rupture of the extensor pollicis longus (EPL) after a distal radius fracture [31].
- The distal radial metaphysis has thin cortex and is vulnerable to bending forces [31].
- The brachioradialis insertion on the radial styloid acts as a deforming force in distal radius fractures [31].
- In a normal wrist with neutral ulnar variance, the distal radius bears 80% of axial load [31].
- The carpus encompasses two rows of eight bones that serve as a bridge between the forearm and the hand [19].
- The proximal carpal row from radial to ulnar includes the scaphoid, lunate, and triquetrum [19].
- The distal carpal row from radial to ulnar includes the trapezium, trapezoid, capitate, and hamate [19].
- The scaphoid is a small, irregular S-shaped tubular bone located in the proximal carpal row on the radial aspect of the wrist [25].
- The scaphoid lies entirely within the wrist joint at a 45-degree plane to the longitudinal and horizontal axis of the wrist [25].
- The scaphoid articulates with the trapezium/trapezoid, radius, capitate, and lunate [25].
- The scaphoid has a surface extensively covered with articular cartilage (over 80%), resulting in reduced capacity for periosteal healing and an increased tendency for delayed union and nonunion [25].
- The scaphoid is ridged across its nonarticular dorsoradial surface, along which the critical dorsal ridge vessels traverse [25].
- The dorsal ridge of the scaphoid is the insertion point for both the dorsal component of the scapholunate and intercarpal ligaments [25].
- The radioscapocapitate ligament does not attach to the bone itself but crosses the waist, acting as a sling across it allowing it to rotate [25].
- There are no tendon attachments to the scaphoid [25].
- The scaphoid acts as a midcarpal joint “bridge” linking and synchronizing the motions of the proximal and distal carpal rows as part of the key intercalated segment [25].
- Motion of the scaphoid includes rotation proximally and gliding distally, while providing stability to the midcarpal joint [25].
Vascular Anatomy
- The blood supply of the scaphoid is largely retrograde and meagre, provided by two vascular pedicles originating from the scaphoid branches of the radial artery [25].
- The dorsal branch of the scaphoid blood supply enters via small foramina along the spiral groove and dorsal ridge, supplying 70% to 80% of the scaphoid proximally, including the proximal pole [25].
- The volar branch of the scaphoid blood supply enters via the scaphoid tubercle and supplies the remaining 20% to 30% of the distal scaphoid [25].
- The waist of the scaphoid has minimal or no perforating vasculature [25].
- No vessels perforate the proximal dorsal cartilaginous area or through the scapholunate ligament [25].
- Proximal scaphoid fractures are associated with at least temporary disruption of the interosseous blood supply to the proximal pole [25].
Ligamentous Anatomy
- The extrinsic ligaments of the carpus connect the carpal bones to the forearm bones proximally and the metacarpals distally [27].
- The extrinsic palmar radiocarpal ligaments include the transverse carpal, radioscaphocapitate (RSC), radioscapholunate (RSL), radial collateral, long radiolunate (RLT), and short radiolunate ligaments [27].
- The extrinsic ulnocarpal ligaments include the ulnotriquetral (dorsal and palmar), ulnolunate, and ulnocapitate ligaments [27].
- Strong oblique extrinsic palmar radial ligaments prevent the carpus from translating medially on the angulated slope of the distal radius through two V-shaped ligamentous bands [27].
- The proximal V-shaped ligamentous band connects the forearm to the proximal carpal row and includes the long radiolunate, radioscapholunate, ulnolunate, and ulnotriquetral ligaments [27].
- The distal V-shaped ligamentous band connects the forearm to the distal carpal row and includes the radioscaphocapitate and ulnocapitate ligaments [27].
- A V-shaped interligamentous sulcus over the capitolunate articulation, known as the space of Poirier, is an interval of capsular weakness [27].
- Maximal space of Poirier is seen when the wrist is dorsiflexed, with the space almost disappearing in palmar flexion [27].
- The lunate displaces into the carpal canal through the space of Poirier during dorsal dislocations [27].
- The arcuate ligament is found in the central third of the palmar joint capsule and is formed from the interdigitation of transverse fibers of the radioscaphocapitate, ulnocapitate, triquetrocapitate, and volar scaphotriquetral ligaments [27].
- The arcuate ligament forms a support sling for the midcarpal region, particularly the head of the capitate [27].
- The extrinsic dorsal carpal ligaments include the dorsal radiocarpal (DRC) ligament and the dorsal intercarpal ligament, which form a V-shaped configuration [27].
- The ulnodorsal capsule of the wrist is reinforced by the ulnolunate and ulnotriquetral ligaments and the floors of the fifth and sixth extensor compartments [27].
- The intrinsic ligaments connect individual carpal bones to one another and are intra-articular short fibers [27].
- The intrinsic ligaments include the palmar midcarpal ligaments (scaphotrapeziotrapezoid, scaphocapitate, triquetrocapiate, triquetrohamate), the proximal interosseous ligaments (scapholunate, lunotriquetral), and the distal interosseous ligaments (trapeziotrapezoid, trapeziocapitate, capitohamate) [27].
- The V-shaped scaphotrapezium–trapezoid ligament on the radial side of the wrist provides stability to the scaphoid–trapezium–trapezoid articulation as well as the scaphoid itself [27].
- The scaphocapitate ligament is a large robust ligament that provides midcarpal stability [27].
Pathophysiology & Biomechanics
- Distal radius fractures are the most common fractures of the upper extremity, with over 300,000 cases per year in the United States [31].
- Distal radius fractures have a bimodal distribution: young patients typically sustain high-energy trauma, while elderly patients typically sustain low-energy falls [31].
- In elderly patients, distal radius fractures are the most common upper extremity osteoporotic fracture [31].
- Normal radiographic parameters for the distal radius include an average radial height of 11 mm, radial inclination of 22 degrees, and volar tilt of 11 degrees [31].
- Acceptable radiographic deviations for distal radius fractures include less than 5 mm of shortening, less than a 5-degree change in radial inclination, and less than 10-degree dorsal angulation [31].
- Ulnar variance is assessed with the forearm in neutral rotation and compared with the contralateral side [31].
- The distal radioulnar joint (DRUJ) alignment is assessed on a true lateral radiograph [31].
- Ligamentous injuries associated with distal radius fractures include scapholunate (SL), lunotriquetral (LT), or triangular fibrocartilage complex (TFCC) injuries [31].
- Radiocarpal dislocation or “inferior arc” injury is highly unstable and difficult to reduce closed [31].
- Computed tomography (CT) is used for detail of complex intraarticular patterns, while magnetic resonance imaging (MRI) is used for occult fracture, bone contusion, and associated soft tissue injury [31].
- Placing the distal row of screws greater than 3mm from subchondral bone in comminuted intra-articular distal radius fractures is associated with increased odds of worsening ulnar variance [2].
Classification
- In adults, early mobilization for distal radius fractures treated with open reduction and internal fixation may have a beneficial functional effect compared to late mobilization at earlier stages [1].
- The mean difference in DASH scores at 6 weeks between early and late mobilization for distal radius fractures treated with ORIF surpasses the minimal clinically important difference [1].
- In comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone is associated with increased odds of worsening ulnar variance [2].
- The Lift-Off Screw (LOS) length can be calculated for accurate sagittal tilt correction in a distal radius fracture model [5].
- The Lift-Off Screw technique can potentially be used with any distal radius periarticular locking plate that has locking options in the shaft [5].
- Open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery [7].
- Open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of a reduction in fracture healing complications [7].
- The lifetime risk of distal radius fracture is 15% for women and 2% for men [13].
- Most distal radius fractures are treated nonsurgically with a plaster cast after closed reduction [13].
- The number of distal radius fractures receiving surgical intervention has increased as surgical treatment has advanced and the general population ages [13].
- Surgical methods for distal radius fractures have shifted from percutaneous pinning or external fixation to open reduction and internal fixation [13].
- The benefit of immediate structural rigidity of fractures, even in osteoporotic bone, after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- ORIF using volar plating and screws has become the preferred surgical approach among hand and orthopedic surgeons for distal radius fractures [13].
- Complication rates following ORIF of distal radius fractures vary from 0% to 60% [13].
- A systematic review of 55 studies including 3,911 fractures reported complication rates following ORIF of distal radius fractures varying from 0% to 60% [13].
Clinical Presentation
- The mean difference in DASH scores at 6 weeks for early mobilization compared to late mobilization in distal radius fractures treated with ORIF surpasses the minimal clinically important difference [1].
- A network meta-analysis of randomized trials indicates that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery [7].
- Open reduction and internal fixation with a plate is associated with a reduction in fracture healing complications for adult patients with a distal radius fracture compared to other interventions in a network meta-analysis of randomized trials [7].
- The benefit of immediate structural rigidity of distal radius fractures after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- Complication rates following ORIF of distal radius fractures have been reported to vary from 0% to 60% in a systematic review of 55 studies including 3,911 fractures [13].
Investigations
Imaging Protocols and Diagnostic Sensitivity
- Standard scaphoid radiographs are used for primary assessment to detect displacement and associated fractures in radiocarpal instability [29].
- Provocative stress tests may be required to demonstrate dynamic radiocarpal instability [29].
- CT may be required to better define associated bony injuries in radiocarpal instability [29].
- MRI can be used to determine the extent of ligamentous disruption in radiocarpal instability [29].
- A decrease in the ulnocarpal index may provide the only clue to diagnosis in cases of subtle ulnar translation [29].
- CT is more sensitive for diagnosing a scaphoid fracture and is useful for confirming alignment of bone fragments if surgery is planned [34].
- MRI is the definitive way to confirm or exclude a diagnosis of scaphoid fracture if the technique is available [34].
- 10–15% of scaphoid fractures are not visible on initial X-rays [28].
- If initial X-rays are normal but clinical suspicion remains, the wrist should be immobilized and re-imaged in 2 weeks or via MRI [28].
- Secondary imaging modalities are predominantly used in the assessment of scaphoid fractures and the diagnosis of intercarpal ligament injury and any associated instability [35].
- Ultrasound scanning (USS) is used for suspected carpal fractures and ligament injuries [35].
- CT (2D/3D) is used for suspected carpal fractures, fracture displacement, malunion, nonunion, and bone loss [35].
- Dynamic CT is used by some for ligament injuries [35].
- Bone scintigraphy is used for suspected carpal fractures and avulsion injuries [35].
- Arthrography ± videofluoroscopy is used for ligament injuries [35].
- MRI is used for suspected carpal fractures, avascular necrosis (AVN) of carpal bones, and ligament injuries [35].
- Wrist arthroscopy is used for suspected carpal fractures, fracture displacement, and ligament injuries [35].
- Live/video fluoroscopic evaluation of the wrist provides diagnostic clarity for dynamic instability with sensitivities reported between 86% and 95% and specificity between 80% and 97% for diagnosing scapholunate ligament injury [35].
- Ultrasound scanning (USS) provides an additional tool for the detection of carpal ligament injuries, though the technique is operator dependent [35].
Radiographic Measurements and Instability Patterns
- The lateral intrascaphoid angle is normally 30 degrees ±5 degrees on a sagittal view, with an angle greater than 35 degrees used as a cut-off for displacement [35].
- The AP intrascaphoid angle is normally 40 degrees ± 5 degrees on coronal views [35].
- The dorsal cortical angle is normally 140 degrees, with values greater than 160 degrees considered abnormal on a sagittal view [35].
- The scaphoid height-to-length ratio is normally 0.60, with values greater than 0.65 considered abnormal on a sagittal view [35].
- Intraobserver reliability for the lateral intrascaphoid angle is poor, while interobserver reliability is poor to moderate [35].
- Intraobserver reliability for the dorsal cortical angle is moderate to excellent, while interobserver reliability is moderate to excellent [35].
- Intraobserver reliability for the scaphoid height-to-length ratio is excellent, while interobserver reliability is moderate to excellent [35].
- Dorsal intercalated segmental instability (DISI) is characterized by the lunate tilting backwards and the scaphoid tilting somewhat volarwards [28].
- Volar intercalated segment instability (VISI) is characterized by the lunate and scaphoid tilting somewhat volarwards and the capitate and metacarpals lying anterior (volar) to the radius [28].
- In a normal lateral X-ray, the axes of the radius, lunate, capitate, and third metacarpal are co-linear, and the scaphoid projects at an angle of about 45 degrees to this line [28].
- DISI pattern is most commonly associated with displaced scaphoid fractures and scapholunate dissociation (SLD) [35].
- Assessment of Gilula's lines can aid in the diagnosis of perilunate dislocations [35].
Anatomical Context for Imaging Interpretation
- The proximal carpal row has no direct tendon attachments, and its movement results from bone shape, interaction with other bones, and ligament attachments [19].
- The pisiform bone is a sesamoid bone enclosed within the sheath of the flexor carpi ulnaris tendon and should not theoretically be considered within the proximal carpal row [19].
- The trapezium articulates with the first metacarpal, the trapezoid with the second, the capitate with the third, and the hamate with the fourth and fifth metacarpals [19].
- There is 30 to 40 degrees of flexion–extension and rotation at the metacarpotrapezial joint [19].
- Motion at the distal carpal row is controlled by the extrinsic wrist flexors and extensors [19].
- The ligaments of the wrist are predominantly contained within the joint capsule [19].
- Apart from the scaphocapitate ligament, carpal ligaments are not described consistently across anatomical studies [19].
Treatment
Surgical Approach and Technique
- Open reduction and internal fixation (ORIF) with a plate offers the best results for adult patients with distal radius fractures in terms of early and sustained functional recovery and a reduction in fracture healing complications [7].
- The immediate structural rigidity of fractures after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- The large tenaculum clamp facilitates anatomical restoration of volar tilt and volar translation while allowing intraoperative fluoroscopy [22].
- The use of a large tenaculum clamp potentially minimizes complications such as flexor tendon abrasion or rupture [22].
- The lift-off screw technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft [5].
Implant Selection and Positioning
- Substantial variations in surgical direct costs for distal radius ORIF exist, and implant choice is the predominant driver [3].
- Placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance in comminuted intra-articular distal radius fractures [2].
Postoperative Management
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial effect compared to late mobilization at earlier stages [1].
- Mean differences in DASH scores at 6 weeks for early mobilization compared to late mobilization surpass the minimal clinically important difference [1].
Complications and Hardware
- There is a 28% chance that hardware removal may be required for patients treated with radial column plating of the distal radius [6].
Complications
- Complication rates following open reduction and internal fixation (ORIF) of distal radius fractures have been reported to vary from 0% to 60% [13].
- A systematic review of 55 studies including 3,911 fractures found no standard for evaluating what should be defined as a complication after ORIF using volar plating [13].
- In a retrospective study of 822 patients, the complication rate following volar locking plate fixation of distal radius fractures was determined as the primary aim [13].
- Radial column plating of the distal radius is associated with a 28% chance that hardware removal may be required [6].
- Open reduction and internal fixation with a plate offers a reduction in fracture healing complications compared to other treatments for adult patients with distal radius fractures [7].
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization, with mean differences in DASH scores at 6 weeks surpassing the minimal clinically important difference [1].
Recovery
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization at earlier stages [1].
Key Evidence
- [L1] Functionally, at earlier stages, early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial effect compared to late mobilization, with mean differences in DASH scores at 6 weeks surpassing the minimal clinically important difference. [1] (10.1186/s13018-021-02837-0)
- [L4] In this two-center retrospective cohort of comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance. [2] (10.1016/j.jhsa.2025.03.016)
- [L3] Substantial variations in surgical direct costs for distal radius ORIF exist, and implant choice is the predominant driver. [3] (10.1016/j.jhsa.2018.04.015)
- [L5] The LOS length can be calculated, and this technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft. [5] (10.1016/j.jhsa.2018.02.011)
- [L4] Radial column plating of the distal radius is a safe treatment modality and a valuable adjunct in the setting of complex distal radius fractures, but patients should be counseled that there is a 28% chance that hardware removal may be required. [6] (10.1177/1558944718760861)
- [L1] A network meta-analysis of randomized trials revealed that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture, in terms of early and sustained functional recovery and a reduction in fracture healing complications. [7] (10.5435/jaaos-d-18-00424)
- [L3] The treatment of displaced intra-articular distal radius fractures with a dorsally versus a volarly placed interlocking plate system demonstrated similar clinical results. [9] (10.1177/1558944716675129)
- [L4] [13] (10.1016/j.jhsa.2022.11.012)
- [L4] The large tenaculum clamp facilitates anatomical restoration of volar tilt and volar translation while allowing intraoperative fluoroscopy, potentially minimizing complications such as flexor tendon abrasion or rupture. [22] (10.1016/j.jhsa.2018.11.017)
References
[1] In adults, early mobilization may be beneficial for distal radius fractures treated with open reduction and internal fixation: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02837-0
[2] The Association Between Distal Screw and Articular Subsidence in the Open Treatment of Intra-articular Distal Radius Fractures. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.03.016
[3] Evaluation of Factors Driving Cost Variation for Distal Radius Fracture Open Reduction Internal Fixation. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.04.015
[5] Lift-Off Screw Results in Accurate Sagittal Tilt Correction in a Distal Radius Fracture Model. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.011
[6] Complications of Radial Column Plating of the Distal Radius. HAND. 2018. DOI: 10.1177/1558944718760861
[7] Interventions for Distal Radius Fractures: A Network Meta-analysis of Randomized Trials. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-18-00424
[9] Management of Intra-Articular Distal Radius Fractures: Volar or Dorsal Locking Plate—Which Has Fewer Complications?. HAND. 2016. DOI: 10.1177/1558944716675129
[13] Complications After Volar Locking Plate Fixation of Distal Radius Fractures: A Retrospective Study of 822 Patients. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.11.012
[19] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Pathoanatomy and Applied Anatomy Relating to Carpal Fractures and Dislocations.
[22] Use of a Large Tenaculum Clamp as a Reduction Technique for Treatment of Distal Radius Fractures. The Journal of Hand Surgery. 2019. DOI: 10.1016/j.jhsa.2018.11.017
[25] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Pathoanatomy and Applied Anatomy Related to Scaphoid Fractures.
[27] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Extrinsic Ligaments.
[28] Apley And Solomon S Concise System Of Orthopaedics And Trauma. FRACTURES OF THE DISTAL RADIUS IN CHILDREN > Imaging.
[29] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Assessment of Radiocarpal Instability.
[31] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > DISTAL RADIUS FRACTURES.
[34] Apley And Solomon S Concise System Of Orthopaedics And Trauma. FRACTURES OF THE DISTAL RADIUS IN CHILDREN > FRACTURE OF THE SCAPHOID.
[35] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Secondary Imaging Methods.