Patients › General-Health
骨骼健康与骨质疏松症
How bone strength affects fractures, fixation and recovery — bone density, fragility fractures, and what helps keep bones strong (lifestyle, supplements and medications).
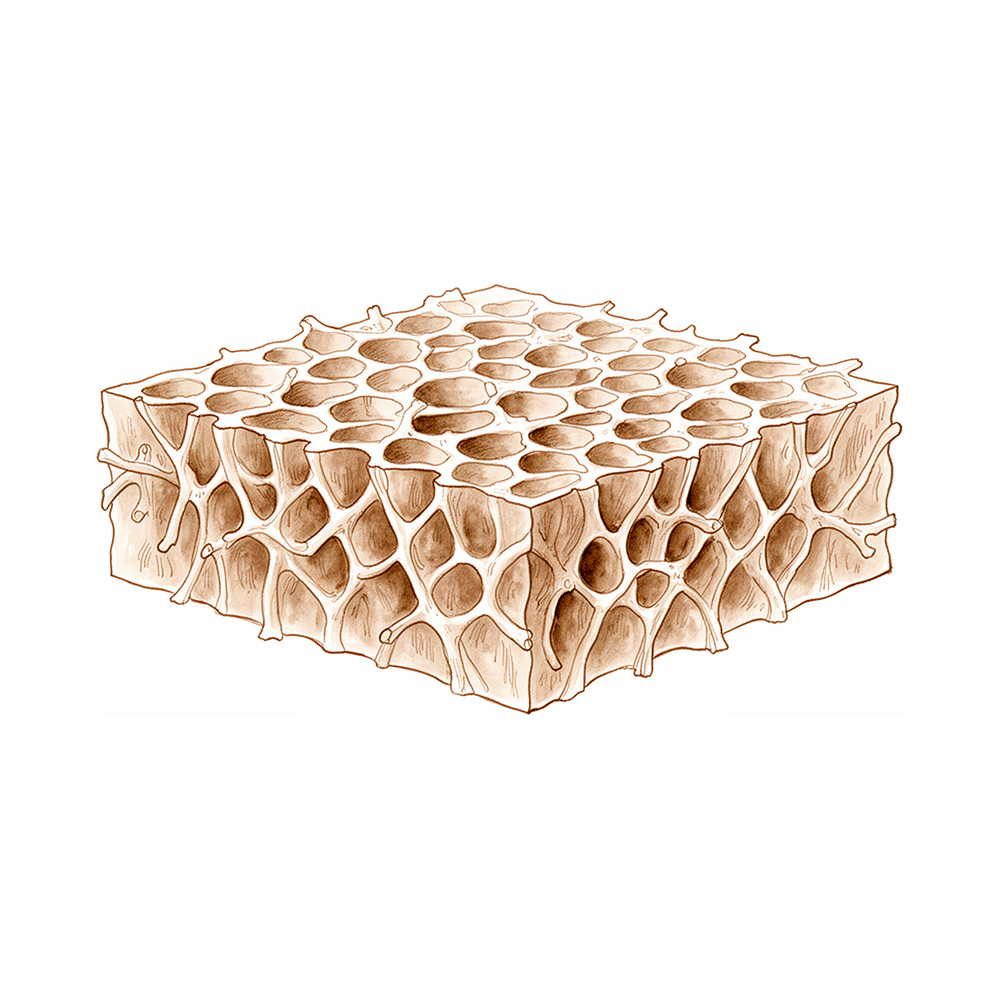
什么是
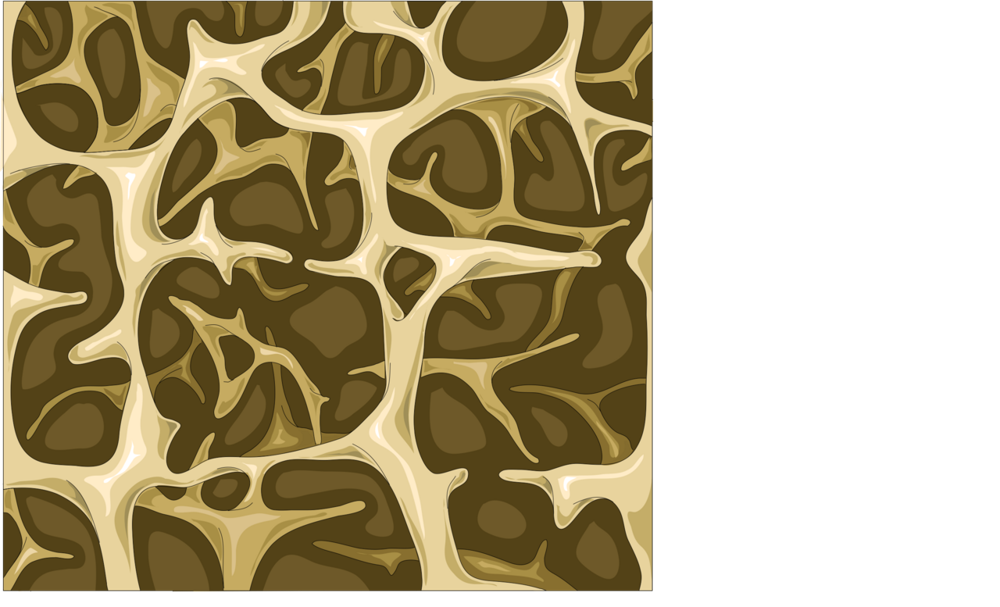
骨质疏松症是一种骨骼失去强度的疾病。随着时间推移,骨骼会变薄、变脆,因此一次轻微的跌倒甚至一次小小的碰撞都可能导致骨折。最常见的骨折部位是髋部、腕部和脊柱。
您可能会听到“脆性骨折”这个说法。它指的是骨骼比正常情况下更容易发生了骨折。如果您曾经发生过这类骨折,这可能是一个警示信号,说明您的骨骼比正常人更脆弱。
这方面存在一个公认的诊疗空白。研究发现,以这种方式发生骨折的人,往往没有接受骨质疏松症检查,也没有开始治疗 [1]。即使已有相关指南,这种情况仍然存在 [2]。这一点很重要,因为治疗潜在的骨骼脆弱可以降低再次骨折的几率。试验表明,在脆性骨折后治疗骨质疏松症,可使再次骨折的风险降低多达 50%,并使死亡率降低多达 30% [3]。
骨骼并不是一成不变的。它们是活组织,在不断地被分解和重建。当分解的速度超过重建的速度时,骨密度就会下降,从而发生骨质疏松症。预防的目标是尽可能把骨骼练得最强壮,然后保持住这份强度 [4]。治疗的目标是阻止骨量进一步流失,让第一次骨折或再次骨折永远不会发生 [4]。
有一项发现值得了解:一项汇总了九项研究的分析发现,体质指数每增加 1 个单位,骨质疏松症风险就降低 9% [5]。体重只是整体情况中的一部分,其他因素还包括年龄、激素和整体健康状况等。
如果您曾经很容易就发生了骨折,或者您担心自己的骨骼强度,请询问是否可以做骨密度检查。及早发现骨质疏松症,能让您有最好的机会在骨折发生之前采取行动。
它有效吗?
坦率地说,治疗越早开始效果越好,而在如何做到这一点上仍有改进的空间。研究发现,腕部骨折的人如果参加专门的项目,接受骨质疏松症检查的比例远高于接受常规诊疗的人:分别为 92% 和 23% [6]。其他研究发现,髋部或脊柱骨骼骨折的人往往根本没有开始强化骨骼的治疗,尽管指南建议这样做 [7] [2]。这就是为什么在任何轻易发生的骨折之后询问骨密度检查如此重要。
一旦确诊骨质疏松症,有证据表明治疗可以帮助骨骼愈合,并降低再次骨折的几率。在一项试验中,腕部骨折并接受了促进骨形成的激素注射的人,愈合时间为 7.8 周,而未接受治疗的人为 12.6 周 [8]。运动也有作用。骨质疏松症患者应进行抗阻运动和冲击性运动,以最大限度地增强骨骼强度,同时进行提高力量和平衡能力的活动以减少跌倒,并进行脊柱伸展运动以改善姿势 [9]。
一些较新的研究结论尚不明确。通过扫描或血液检查预测骨质疏松症的机器学习工具显示出一定前景,但综述发现它们存在较高的偏倚风险,而且尚未在临床中得到充分检验 [10]。另有一项分析发现,一种被认为能保护骨骼的糖尿病药物,在考虑其他健康因素后,并没有减少腕部和手臂骨折 [11]。如果您患有骨质疏松症并发生了骨折,在治疗骨骼本身的同时治疗潜在的骨骼脆弱,效果会更好 [12]。
风险有哪些?
骨质疏松症不加治疗的主要风险是骨折。如果您已经发生过一次脆性骨折,您的骨骼就更容易再次骨折,尤其是在潜在的骨骼脆弱没有得到治疗的情况下 [7] [2]。研究发现,在第一次骨折后开始治疗可以降低再次骨折的几率,这是及早采取行动最有力的理由 [3]。
骨折发生前后本身也存在风险。一项研究发现,骨质疏松症患者在手术后最初 90 天内出现的内科并发症比没有骨质疏松症的人更多 [13]。骨折的愈合情况也可能因骨骼强度不同而有所差异。在一项关于移位腕部骨折的研究中,骨质疏松症患者的畸形改善值为 12.5,不到骨质良好者的 25.6 的一半 [14]。另一项研究发现,老年人骨骼脆弱本身并不会阻止骨折愈合 [15]。
如果您患有骨质疏松症,并且需要做关节或肌腱手术,情况则更为明确。关于关节镜(锁孔)肩袖修复术的综述发现,较低的骨密度与 2 年时的效果之间没有关联,而且并发症发生率很低 [16] [17]。骨质疏松症不应被视为排除这种手术的理由 [17]。
一些治疗方法本身也存在不确定性。降钙素的鼻喷剂型在增强骨骼和降低骨折风险方面,效果不如其他骨骼药物 [18]。针灸和中药产品的证据尚处于早期阶段,还需要更多检验 [19] [20]。对于甲状旁腺激素注射,最佳的给药时间仍在试验中研究 [21]。
真正的空白在于后续跟进。研究显示,许多髋部、脊柱或腕部骨折的人根本没有开始强化骨骼的治疗 [7] [2] [22]。在任何轻易发生的骨折之后询问治疗事宜,是您可以采取的最稳妥的一步。
这适合您吗?
如果您被告知骨骼脆弱,或者您的骨折比正常情况下更容易发生,那么强化骨骼的治疗值得考虑。目标是在第一次骨折或再次骨折发生之前,阻止骨量进一步流失 [4]。脆性骨折后的治疗同样重要。它可以降低再次骨折的几率并降低死亡率 [3]。但研究显示,许多髋部、脊柱或腕部骨折的人根本没有开始治疗 [7] [2]。因此,如果您曾经轻易发生过骨折,向您的医生询问骨密度检查以及治疗是否对您有帮助,是合情合理的。
有些人不太需要治疗。如果您的骨骼仍然强壮,重点就是保持这种状态:尽可能把骨骼练得最强壮,然后保持住这份强度 [4]。运动在这方面发挥着作用。骨质疏松症患者应进行抗阻运动和冲击性运动,以最大限度地增强骨骼强度 [9]。您的医生可以帮助您确定哪些运动对您是安全的。
治疗并不是千篇一律的。骨骼药物有好几种,哪一种适合您取决于您的健康状况、骨折史以及您自己的优先考虑。这应该由您和您的医生共同决定。请询问每种选择包括哪些内容、可能有哪些副作用(见上文风险部分),以及您需要持续治疗多长时间。如果有任何不清楚的地方,请继续询问,直到您对方案有信心为止。
核心要点
如果您的骨骼脆弱,或者您曾经轻易发生过骨折,骨质疏松症治疗值得考虑。目标是在骨折或再次骨折发生之前,阻止骨量进一步流失 [4]。及早行动很重要,因为脆性骨折后的治疗可以降低再次骨折的几率并降低死亡率 [3]。最重要的一点提醒是后续跟进:许多髋部、脊柱或腕部骨折的人根本没有接受过检查或治疗 [7] [2]。因此,如果您曾经轻易发生过骨折,请要求做骨密度检查,并持续询问,直到您有了明确的方案。
参考文献
[1] The osteoporosis care gap in Canada. BMC Musculoskeletal Disorders. 2004. DOI: 10.1186/1471-2474-5-11
[2] A Missed Opportunity? Osteoporosis Treatment Following Femoral Neck Fractures: Reducing the Risk of Secondary Hip Fracture. The Journal of Arthroplasty. 2026. DOI: 10.1016/j.arth.2025.07.028
[3] Medical management of osteoporosis and the doctor's' role. Injury. 2016. DOI: 10.1016/s0020-1383(16)30014-6
[4] BONE HEALTH AND OSTEOPOROSIS. Clinics in Sports Medicine. 2000. DOI: 10.1016/s0278-5919(05)70201-5
[5] The association between body mass index and osteoporosis, with consideration of sex differences: a systematic review and dose-response meta-analysis. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09675-3
[6] Wristwatch—distal radial fracture as a marker for osteoporosis investigation:. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.001
[7] The Management of Pelvic and Vertebral Fragility Fractures: An Unmet Care Need. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.26.00966
[8] Use of teriparatide in osteoporotic fracture patients. Injury. 2016. DOI: 10.1016/s0020-1383(16)30009-2
[9] Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022. DOI: 10.1136/bjsports-2021-104634
[10] Risk prediction models for postmenopausal osteoporosis: a systematic review and meta-analysis study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-025-09385-2
[11] Glucagon-like peptide-1 receptor agonist use for type 2 diabetes and risk of upper extremity fragility fracture. Injury. 2026. DOI: 10.1016/j.injury.2026.113456
[12] Continuity and volume of bone cement and anti osteoporosis treatment were guarantee of good clinical outcomes for percutaneous vertebroplasty: a multicenter study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08153-y
[13] Impact of osteoporosis on post-operative outcomes following rotator cuff repair. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100723
[14] Osteoporosis and colles' fractures in the elderly. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90058-1
[15] A89 Osteoporosis is not a risk factor for the development of nonunion: a cohort nested case-control study. Injury. 2011. DOI: 10.1016/s0020-1383(11)70106-1
[16] No difference in 2-year outcomes of arthroscopic rotator cuff repair in patients with osteoporosis. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.011
[17] Osteoporosis is a risk factor for complications and reoperations at 1 and 3 years after arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101678
[18] Revisiting Intranasal Salmon Calcitonin: Historical Osteoporosis Evidence and a Potential Role in Acute Orthopaedic Pain Management. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00021
[19] Efficacy of acupuncture for primary osteoporosis: a systematic review and meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05513-9
[20] Natural traditional Chinese medicine products: emerging therapeutic targets for the treatment of osteoporosis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05879-w
[21] Timing optimization of teriparatide dosing for postmenopausal osteoporosis: a randomized controlled trial. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06083-6
[22] Incidence of Anti-osteoporosis Diagnosis and Treatment After Distal Radius Fractures. HAND. 2016. DOI: 10.1177/1558944716660555dj
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Fragility fractures represent a major and growing global health concern [15].
- Prevention of osteoporosis is accomplished by maximizing peak bone density and maintaining that bone density [6].
- The goal of osteoporosis treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures [6].
- There is evidence of a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada [12].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated following pelvic and vertebral fragility fractures [7].
- Treatments for pelvic and vertebral fragility fractures vary widely and are not always evidence-based [7].
- Wider recognition of common risk factors of osteoporosis and the expansion of screening protocols are necessary to ensure that osteoporosis is properly diagnosed and treated in patients receiving lumbar fusion [3].
- Findings from over one million cases support early, coordinated post-fracture osteoporosis treatment following an initial fragility fracture [4].
- The observational design of the study on recurrent hip fracture risk precludes causal inference [4].
- Each 1-unit increase in body mass index was associated with a 9% reduction in osteoporosis risk based on a dose-response analysis of nine studies [8].
- A bone density based aging model approach may facilitate and support the development of precision medicine strategies in osteoporosis prevention and management [1].
- A nomogram with an online dynamic calculator could facilitate the early prediction, diagnosis, and treatment of osteoporosis, contributing to the bone health of the elderly population and promoting the development of public health [20].
- Patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period than nonosteoporotic patients following rotator cuff repair [22].
- Overall rates of complication after arthroscopic rotator cuff repair were low, and osteoporosis should not be considered a contraindication to the procedure [33].
- Patients with distal radial fractures in elderly women should be screened for osteoporosis [23].
- The ability of monocytes to fuse declines significantly in patients with osteoporosis [55].
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing bone mineral density and reducing fracture risk [11].
- The use of intranasal salmon calcitonin is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [11].
- Sequential anabolic-to-anti-resorptive therapy may inform treatment guidelines for high-risk postmenopausal populations [9].
- Current online health information on osteoporosis often fails to meet basic standards of evidence-based health information, highlighting the urgent need to improve quality to support informed decision-making [5].
- Investigators must select an osteoporotic fracture model that best reflects the clinical problem being studied and the underlying pathophysiology of the osteoporosis in the target patient group [2].
- There is no perfect model for osteoporosis, but a variety of models are appropriate for answering specific questions [10].
How It Works
Pathophysiology and Mechanisms
- Hypothalamic-pituitary disconnection leads to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation, with reduced osteoblast and osteoclast activity [29].
- Evidence of early changes in bone geometry and increased bone turnover could be used to detect osteoporosis before estrogen deficiency has adversely affected bone strength [27].
- MiR-137 promotes TLR4/NF-κB pathway activity through targeting KDM4A, which inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis [37].
- The gut microbiota–metabolite–bone network may be involved in the skeletal effects of leptin, providing mechanistic insights for osteoporosis management [36].
- Macrophage polarization-related genes have potential causal roles in osteoporosis, though these findings are exploratory and require validation in bone marrow-specific and functional studies [35].
Risk Factors and Screening
- Each 1-unit increase in BMI was associated with a 9% reduction in osteoporosis risk based on a dose-response analysis of nine studies [8].
- Postmenopausal women with distal radius fractures have diminished bone mass, which might make a bone more likely to break [45].
- Machine learning application to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and earlier treatment of osteoporosis/osteopenia [19].
- A nomogram with an online dynamic calculator developed based on NHANES data could facilitate the early prediction, diagnosis, and treatment of osteoporosis [20].
- A bone density-based aging model may facilitate the development of precision medicine strategies in osteoporosis prevention and management [1].
- Current online health information on osteoporosis often fails to meet basic standards of evidence-based health information, highlighting the need to improve quality to support informed decision-making [5].
Treatment and Management
- Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density, although the goal of treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures [6].
- Randomized controlled trials have demonstrated that treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30% [18].
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing BMD and reducing fracture risk, and its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [11].
- The current evidence suggests that the efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention [16].
- Late osteoporosis treatment was associated with no significant further decline in periprosthetic BMD but did not reverse severe proximal bone loss [28].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated, and treatments for pelvic and vertebral fragility fractures vary widely and are not always evidence-based [7].
- These findings support early, coordinated post-fracture osteoporosis treatment, although the observational design precludes causal inference [4].
- A program for secondary osteoporotic fracture prevention is needed following distal radius fractures [30].
- Natural traditional Chinese medicine products provide a theoretical and experimental basis for the development of new drugs and the improvement of osteoporosis management [24].
- Findings from studies on long-term hospitalized patients with muscular dystrophy may help inform strategies for osteoporotic treatment and nutritional care in this patient population [17].
Fracture Healing and Repair
- The effect of ovariectomy on fracture repair was to delay healing as evidenced by histological and radiological analysis, and the deleterious effect might be more related to change of structure than to loss of BMD [41].
- In humans, de novo use of bisphosphonate therapy after fracture does not appear to have a significant effect on fracture healing [46].
- Although bone quality may be diminished in the elderly, this does not influence the occurrence of nonunion [47].
- Prior bisphosphonate treatment affects the mineralization pattern of the tissue repair consistently with a reduction in bone turnover, but does not abolish the repair process [26].
- There is some promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents [39].
- Fracture healing in SAMP6 mice is not detrimentally affected by impairment of bone marrow stem cell osteogenesis, suggesting that bone marrow-mediated repair processes are dispensable for normal bone healing in this senile osteoporotic fracture model [44].
- Cracks in bone following bisphosphonate treatment were shorter than in control or ovariectomized groups, which may explain why increased damage levels following bisphosphonate treatment have not led to increased fractures [40].
- Bone histomorphometry revealed that bone architecture in the treatment group using a calcitonin release system was improved and results were not different from those observed after calcitonin injection [31].
Clinical Outcomes and Assessment
- There was no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair in patients with osteoporosis [21].
- Multiscale biomechanical assessment approaches have potential applications in fracture risk assessment, the design of patient-specific implants, and research into the mechanisms of bone metabolic diseases [38].
- Investigators must select an animal model that best reflects the clinical problem being studied and the underlying pathophysiology of the osteoporosis in the target patient group [2].
What the Evidence Shows
Epidemiology and Risk Factors
- Fragility fractures are a major and growing global health concern [15].
- Each 1-unit increase in body mass index is associated with a 9% reduction in osteoporosis risk [8].
- Type 2 diabetes shows significant associations with femoral neck and total body bone mineral density, while HbA1c shows significant associations with heel bone mineral density [56].
- Osteoporosis is present in long-term hospitalized patients with muscular dystrophy, informing strategies for osteoporotic treatment and nutritional care in this population [17].
Diagnosis and Screening
- There is a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada [12].
- Osteoporosis screening gaps exist among patients undergoing lumbar fusion surgery, necessitating wider recognition of risk factors and expanded screening protocols [3].
- Patients with distal radial fractures should be screened for osteoporosis [23].
- Intervention programs for distal radius fractures increased the rate of osteoporosis investigation from 26.6% in controls to 87.5% in intervention participants [32].
- Intervention subjects for distal radial fractures were investigated for osteoporosis at a rate of 92%, compared to 23% in the usual-care group [43].
- Machine learning models applied to hand radiographs represent a step toward more accessible, cost-effective, and automated diagnosis of osteoporosis and osteopenia [19].
- A fracture risk prediction model based on routine blood test markers was successfully developed and validated for patients newly diagnosed with osteoporosis [52].
- Current machine learning-based prediction models for postmenopausal osteoporosis without fractures demonstrate good discriminative ability but are characterized by a high risk of bias, lack of calibration performance evaluation, and insufficient validation of clinical utility [58].
- Online health information on osteoporosis often fails to meet basic standards of evidence-based health information [5].
Treatment and Management
- Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density [6].
- Treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30% [18].
- Early, coordinated post-fracture osteoporosis treatment is supported by findings from over one million cases, though the observational design precludes causal inference [4].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated in patients with pelvic and vertebral fragility fractures [7].
- Patients receiving parathyroid hormone (1–84) injections experienced accelerated radiographic and clinical fracture healing at 7.8 weeks compared to 12.6 weeks in untreated patients [48].
- Late osteoporosis treatment was associated with no significant further decline in periprosthetic bone mineral density but did not reverse severe proximal bone loss after cementless total hip arthroplasty [28].
- Continuous bone cement and standardized treatment for osteoporosis were guarantees of good clinical outcomes for percutaneous vertebroplasty [50].
- Injected bone cement greater than 5.5 ml might be a guarantee of good clinical outcomes for percutaneous vertebroplasty [50].
- Prior bisphosphonate treatment affects the mineralization pattern of tissue repair following vertebral fragility fracture, consistent with reduced bone turnover, but does not abolish the repair process [26].
- The efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention [16].
- Key recommendations for people with osteoporosis include undertaking resistance and impact exercise to maximize bone strength [34].
- Key recommendations for people with osteoporosis include activities to improve strength and balance to reduce falls [34].
- Key recommendations for people with osteoporosis include spinal extension exercise to improve posture and potentially reduce the risk of falls and vertebral fractures [34].
Surgical Outcomes and Complications
- There is no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair [21].
- Patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period following rotator cuff repair than nonosteoporotic patients [22].
- In severely displaced distal radial fractures, the final improvement in bony deformity was significantly less in patients with osteoporosis compared to those without [53].
- The initial deformity in severely displaced distal radial fractures was not influenced by osteoporosis [53].
Research Models
- Hypothalamic-pituitary disconnection leads to low turnover osteoporosis in sheep after 12 months, characterized by a reduction in both trabecular and cortical bone with reduced osteoblast and osteoclast activity [29].
Practical Considerations
Screening and Diagnosis
- A bone density-based aging model approach may facilitate the development of precision medicine strategies in osteoporosis prevention and management [1].
- Machine learning application to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and earlier treatment of osteoporosis or osteopenia [19].
- In a study of wristwatch interventions, seven of the eight remaining intervention participants were investigated for osteoporosis (87.5%), compared to four of the remaining 15 control subjects (26.6%) [32].
- Patients with hand fragility fractures represent a high-risk cohort that is currently underserved by osteoporosis screening pathways [42].
- A cortical bone thickness average below 4.5 mm should prompt DXA referral to improve preoperative bone health assessment without added cost or radiation [49].
Treatment and Management
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing bone mineral density and reducing fracture risk, and its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [11].
- Findings from a prospective observational study highlight opportunities for systematic primary and secondary fracture prevention and structured medication review prior to femoral fracture [25].
- Findings from a retrospective cross-sectional study may help inform strategies for osteoporotic treatment and nutritional care in long-term hospitalized patients with muscular dystrophy [17].
Surgical Considerations
- Despite previous literature showing the negative effect of osteoporosis on rotator cuff healing, data showed no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair [21].
Lifestyle and Prevention
- Key recommendations for people with osteoporosis include undertaking resistance and impact exercise to maximise bone strength [34].
- Key recommendations for people with osteoporosis include spinal extension exercise to improve posture and potentially reduce risk of falls and vertebral fractures [34].
Research Models
Key Evidence
- [L3] This approach may facilitate and support the development of precision medicine strategies in osteoporosis prevention and management. [1] (10.1186/s12891-025-09298-0)
- [L5] Investigators must select a model that best reflects the clinical problem being studied, and the underlying pathophysiology of the osteoporosis in the target patient group. [2] (10.1016/s0020-1383(16)30004-3)
- [Paper] Wider recognition of common risk factors of osteoporosis and the expansion of screening protocols are necessary to ensure that osteoporosis is properly diagnosed and treated in patients receiving lumbar fusion. [3] (10.5435/jaaos-d-26-00335)
- [Paper] These findings support early, coordinated post-fracture osteoporosis treatment; the observational design precludes causal inference. [4] (10.1016/j.injury.2026.113865)
- [Paper] Current OHI on osteoporosis often fails to meet basic standards of EBHI, highlighting the urgent need to improve the quality to support informed decision-making. [5] (10.1186/s12891-026-09711-2)
- [Paper] Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density, although the goal of treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures. [6] (10.1016/s0278-5919(05)70201-5)
- [L5] The treatments vary widely and are not always evidence-based and, unfortunately, treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated. [7] (10.2106/jbjs.26.00966)
- [L1] Based on our dose-response analysis of nine studies, each 1-unit increase in BMI was associated with a 9% reduction in osteoporosis risk. [8] (10.1186/s12891-026-09675-3)
- [L1] This sequential anabolic-to-anti-resorptive therapy may inform treatment guidelines for high-risk postmenopausal populations. [9] (10.1186/s13018-025-06040-3)
- [Paper] However, there is no perfect model for osteoporosis, but a variety of models appropriate for answering specific questions. [10] (10.1016/s0020-1383(16)30002-x)
- [Paper] IN-CAL is less effective than bisphosphonates and modern anabolic agents for increasing BMD and reducing fracture risk; accordingly, its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference. [11] (10.2106/jbjs.rvw.26.00021)
- [L4] There is evidence of a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada. [12] (10.1186/1471-2474-5-11)
- [Paper] Fragility fractures are a major and growing global health concern. [15] (10.1016/j.injury.2026.113902)
- [L1] The current evidence suggests that the efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention. [16] (10.1186/s13018-025-05513-9)
- [L4] These findings may help inform strategies for osteoporotic treatment and nutritional care in this patient population. [17] (10.1186/s12891-026-10045-2)
- [Paper] Randomized controlled trials have demonstrated that treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30%. [18] (10.1016/s0020-1383(16)30014-6)
- [L2] The findings represent a possible step toward more accessible, cost-effective, automated diagnosis and therefore earlier treatment of osteoporosis/osteopenia. [19] (10.1016/j.jhsa.2024.09.008)
- [L3] Ultimately, this tool could facilitate the early prediction, diagnosis, and treatment of osteoporosis, thus contributing to the bone health of the elderly population and promoting the development of public health. [20] (10.1186/s12891-026-09920-9)
- [L3] Despite previous literature showing the negative effect of osteoporosis on rotator cuff healing, our data showed no relationship between decreased bone mineral density and 2-year clinical outcomes following RCR. [21] (10.1016/j.jse.2025.02.011)
- [L3] In addition, patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period than nonosteoporotic patient. [22] (10.1016/j.xrrt.2026.100723)
- [L4] It is the authors' opinion that such patients should be screened for osteoporosis. [23] (10.1016/j.jhsb.2004.05.002)
- [L4] This paper summarises recent research progress on natural TCM products in preventing and treating osteoporosis and provides a theoretical and experimental basis for the development of new drugs and the improvement of osteoporosis management. [24] (10.1186/s13018-025-05879-w)
- [L3] These findings highlight important opportunities for systematic primary and secondary fracture prevention and structured medication review. [25] (10.1007/s00402-026-06401-5)
- [L4] Prior bisphosphonate treatment affects the mineralization pattern of the tissue repair consistently with a reduction in bone turnover as found in post-menopausal osteoporotic women, but does not abolish the repair process. [26] (10.1002/jor.22026)
- [Paper] Therefore, evidence of early changes in bone geometry and increased bone turnover could be used to detect osteoporosis before estrogen deficiency has adversely affected bone strength. [27] (10.1002/jor.20961)
- [Paper] Late osteoporosis treatment was associated with no significant further decline in periprosthetic BMD but did not reverse severe proximal bone loss. [28] (10.1007/s00264-026-07068-8)
- [Paper] HPD leads after 12 month to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation, with reduced osteoblast and osteoclast activity, as compared to controls (OVX). [29] (10.1002/jor.22066)
- [L4] The results of our study evidenced the need of a program for secondary osteoporotic fracture prevention; this program has now been developed and is active at our institution. [30] (10.1177/1558944716660555dj)
- [Paper] Bone histomorphometry revealed that bone architecture in the treatment group was improved and results were not different from those observed after calcitonin injection. [31] (10.1016/s0736-0266(01)00074-7)
- [L1] Seven of the eight remaining intervention participants were investigated for osteoporosis (87.5%), compared to four of the remaining 15 control subjects (26.6%). [32] (10.1197/j.jht.2003.10.030)
- [L3] Overall rates of complication were low and osteoporosis should not be considered a contraindication to arthroscopic RCR. [33] (10.1016/j.jseint.2026.101678)
- [L5] Key recommendations are that people with osteoporosis should undertake (1) resistance and impact exercise to maximise bone strength; (2) activities to improve strength and balance to reduce falls; (3) spinal extension exercise to improve posture and potentially reduce risk of falls and vertebral fractures. [34] (10.1136/bjsports-2021-104634)
- [Paper] These findings are exploratory and hypothesis-generating and require validation in bone marrow-specific and functional studies. [35] (10.1186/s13018-026-06905-1)
- [Paper] These findings suggest that the gut microbiota–metabolite–bone network may be involved in the skeletal effects of leptin, providing novel mechanistic insights and potential therapeutic strategies for osteoporosis management. [36] (10.1186/s12891-026-09950-3)
- [Paper] This mechanism inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis. [37] (10.1186/s13018-023-03918-y)
- [L5] It explores the potential applications of these multiscale approaches in fracture risk assessment, the design of patient-specific implants, and research into the mechanisms of bone metabolic diseases. [38] (10.1016/j.injury.2026.113659)
- [Paper] There is some promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents. [39] (10.1016/s0020-1383(16)30003-1)
- [Paper] However, these cracks were shorter than in control or OVX groups which may provide one explanation as to why increased damage levels following bisphosphonate treatment have not lead to increased fractures. [40] (10.1002/jor.21229)
- [Paper] The effect of OVX on fracture repair was to delay healing as evidenced by histological and radiological analysis, and the evidence suggests that the deleterious effect might be more related to change of structure than to loss of BMD. [41] (10.1002/jor.20505)
- [L3] Patients with hand fragility fractures represent a high-risk cohort that is currently underserved by osteoporosis screening pathways. [42] (10.1016/j.injury.2026.113261)
- [L2] Results indicate that 92% of the intervention subjects were investigated for osteoporosis, compared with the usual-care group, in which only 23% were investigated. [43] (10.1197/j.jht.2004.04.001)
- [Paper] Fracture healing in SAMP6 mice is not detrimentally affected by impairment of BMSC osteogenesis, suggesting that bone marrow-mediated repair processes are dispensable for normal bone healing in this senile osteoporotic fracture model. [44] (10.1002/jor.21041)
- [L4] They also have diminished bone mass, which might make a bone more likely to break. [45] (10.1016/0363-5023(88)90227-4)
- [L4] In humans, de novo use of bisphosphonate therapy after fracture does not appear to have a significant effect on fracture healing. [46] (10.1016/s0020-1383(16)30015-8)
- [L3] Although bone quality may be diminished in the elderly, this does not influence the occurrence of nonunion. [47] (10.1016/s0020-1383(11)70106-1)
- [Paper] Patients who received the PTH (1–84) injections accelerated radiographic and clinical fracture healing (7.8 weeks) when compared to patients who received no treatment (12.6 weeks). [48] (10.1016/s0020-1383(16)30009-2)
- [L4] A CBTavg below 4.5 mm should prompt DXA referral, improving preoperative bone health assessment without added cost or radiation. [49] (10.1177/17585732261491314)
- [L3] Continuous bone cement and standardized treatment for osteoporosis were guarantees of good clinical outcomes for PVP, and injected bone cement >5.5 ml might be a guarantee. [50] (10.1186/s12891-024-08153-y)
- [L3] We successfully developed and validated a fracture risk prediction model for patients newly diagnosed with osteoporosis. [52] (10.1186/s12891-026-09768-z)
- [L3] In severely displaced fractures, the initial deformity was not influenced by osteoporosis, but the final improvement in bony deformity was significantly less in patients with osteoporosis. [53] (10.1016/0266-7681(87)90058-1)
- [L4] It was clearly demonstrated that the ability of monocytes to fuse declines significantly in patients with osteoporosis. [55] (10.1002/jor.1100180215)
- [Paper] The results show varying associations across different BMD sites (femoral neck, lumbar spine, heel, total body) and methods (IVW, MR-Egger, Weighted median), with some significant associations found for T2D on femoral neck and total body BMD, and HbA1c on heel BMD. [56] (10.1186/s12891-024-07430-0)
- [L1] Current machine learning-based prediction models for postmenopausal osteoporosis without fractures demonstrate good discriminative ability but are generally characterized by a high risk of bias, a notable lack of calibration performance evaluation, and insufficient validation of clinical utility. [58] (10.1186/s12891-025-09385-2)
References
[1] Unveiling risk factors and predicting osteoporosis through bone density based aging model: a community-based cohort in Guangdong, China. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09298-0
[2] Main differences in osteoporotic fracture models: which should I use?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30004-3
[3] Osteoporosis Screening Gaps Among Patients Undergoing Lumbar Fusion Surgery. Journal of the American Academy of Orthopaedic Surgeons. 2026. DOI: 10.5435/jaaos-d-26-00335
[4] Osteoporosis Treatment Gaps and Risk of Recurrent Hip Fracture Following Initial Fragility Fracture: Insights from Over One Million Cases. Injury. 2026. DOI: 10.1016/j.injury.2026.113865
[5] Mapping the quality of information on osteoporosis: a cross-sectional analysis of online health information. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09711-2
[6] BONE HEALTH AND OSTEOPOROSIS. Clinics in Sports Medicine. 2000. DOI: 10.1016/s0278-5919(05)70201-5
[7] The Management of Pelvic and Vertebral Fragility Fractures: An Unmet Care Need. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.26.00966
[8] The association between body mass index and osteoporosis, with consideration of sex differences: a systematic review and dose-response meta-analysis. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09675-3
[9] Effectiveness of anabolic and anti-resorptive agents for preventing postmenopausal osteoporosis fractures: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06040-3
[10] Can we induce osteoporosis in animals comparable to the human situation?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30002-x
[11] Revisiting Intranasal Salmon Calcitonin: Historical Osteoporosis Evidence and a Potential Role in Acute Orthopaedic Pain Management. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00021
[12] The osteoporosis care gap in Canada. BMC Musculoskeletal Disorders. 2004. DOI: 10.1186/1471-2474-5-11
[15] Fragility fractures: an increasing issue in the ageing population worldwide. Injury. 2026. DOI: 10.1016/j.injury.2026.113902
[16] Efficacy of acupuncture for primary osteoporosis: a systematic review and meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05513-9
[17] Osteoporosis in long-term hospitalized patients with muscular dystrophy: a retrospective cross-sectional study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-10045-2
[18] Medical management of osteoporosis and the surgeons' role. Injury. 2016. DOI: 10.1016/s0020-1383(16)30014-6
[19] Application of Machine Learning to Osteoporosis and Osteopenia Screening Using Hand Radiographs. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.09.008
[20] A nomogram with online dynamic calculator for predicting osteoporosis: development and validation based on NHANES. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09920-9
[21] No difference in 2-year outcomes of arthroscopic rotator cuff repair in patients with osteoporosis. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.011
[22] Impact of osteoporosis on post-operative outcomes following rotator cuff repair. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100723
[23] The Distal Radial Fracture in Elderly Women and the Bone Mineral Density of the Lumbar Spine and Hip. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2004.05.002
[24] Natural traditional Chinese medicine products: emerging therapeutic targets for the treatment of osteoporosis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05879-w
[25] Osteoporosis treatment gap prior to femoral fracture and prevalence of pharmacological risk factors: a prospective observational study. Archives of Orthopaedic and Trauma Surgery. 2026. DOI: 10.1007/s00402-026-06401-5
[26] Mineralization pattern of vertebral bone material following fragility fracture of the spine. Journal of Orthopaedic Research. 2012. DOI: 10.1002/jor.22026
[27] Structural adaptation and intracortical bone turnover in an ovine model of osteoporosis. Journal of Orthopaedic Research. 2009. DOI: 10.1002/jor.20961
[28] Long-term periprosthetic femoral bone loss after cementless total hip arthroplasty: natural history and response to late osteoporosis treatment. International Orthopaedics. 2026. DOI: 10.1007/s00264-026-07068-8
[29] Low turnover osteoporosis in sheep induced by hypothalamic‐pituitary disconnection. Journal of Orthopaedic Research. 2012. DOI: 10.1002/jor.22066
[30] Incidence of Anti-osteoporosis Diagnosis and Treatment After Distal Radius Fractures. HAND. 2016. DOI: 10.1177/1558944716660555dj
[31] Calcitonin release system in the treatment of experimental osteoporosis. Histomorphometric evaluation. Journal of Orthopaedic Research. 2001. DOI: 10.1016/s0736-0266(01)00074-7
[32] Wristwatch: distal radius fractures as a marker for osteoporosis investigation. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2003.10.030
[33] Osteoporosis is a risk factor for complications and reoperations at 1 and 3 years after arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101678
[34] Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022. DOI: 10.1136/bjsports-2021-104634
[35] Macrophage polarization-related genes with potential causal roles in osteoporosis: a multi-omics Mendelian randomization study. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06905-1
[36] Role and mechanism of leptin in improving osteoporosis via the “gut–bone axis”. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09950-3
[37] MiR-137 promotes TLR4/NF-κB pathway activity through targeting KDM4A, inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis. Journal of Orthopaedic Surgery and Research. 2023. DOI: 10.1186/s13018-023-03918-y
[38] Progress in Multiscale Biomechanical Assessment of Cancellous Bone: From Bone Density to Multiscale Mechanical Phenotypes. Injury. 2026. DOI: 10.1016/j.injury.2026.113659
[39] Fracture repair: general aspects and influence of osteoporosis and anti-osteoporosis treatment. Injury. 2016. DOI: 10.1016/s0020-1383(16)30003-1
[40] Effects of estrogen deficiency and bisphosphonate therapy on osteocyte viability and microdamage accumulation in an ovine model of osteoporosis. Journal of Orthopaedic Research. 2010. DOI: 10.1002/jor.21229
[41] Effect of osteoporosis on bone mineral density and fracture repair in a rat femoral fracture model. Journal of Orthopaedic Research. 2007. DOI: 10.1002/jor.20505
[42] Hand fragility fractures as a missed opportunity for secondary prevention: A retrospective cohort study and assessment of the Second Metacarpal Cortical Index. Injury. 2026. DOI: 10.1016/j.injury.2026.113261
[43] Wristwatch—distal radial fracture as a marker for osteoporosis investigation:. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.001
[44] Influence of defective bone marrow osteogenesis on fracture repair in an experimental model of senile osteoporosis. Journal of Orthopaedic Research. 2010. DOI: 10.1002/jor.21041
[45] Postural stability and bone density in postmenopausal women with distal radius fractures. The Journal of Hand Surgery. 1988. DOI: 10.1016/0363-5023(88)90227-4
[46] How do bisphosphonates affect fracture healing?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30015-8
[47] A89 Osteoporosis is not a risk factor for the development of nonunion: a cohort nested case-control study. Injury. 2011. DOI: 10.1016/s0020-1383(11)70106-1
[48] Use of teriparatide in osteoporotic fracture patients. Injury. 2016. DOI: 10.1016/s0020-1383(16)30009-2
[49] Magnetic resonance imaging-based cortical thickness as a predictor of osteoporosis in rotator cuff tears. Shoulder & Elbow. 2026. DOI: 10.1177/17585732261491314
[50] Continuity and volume of bone cement and anti osteoporosis treatment were guarantee of good clinical outcomes for percutaneous vertebroplasty: a multicenter study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08153-y
[52] SuperLearner approach for predicting imminent risk of fracture in older Chinese patients with newly diagnosed osteoporosis based on their routine blood test markers. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09768-z
[53] Osteoporosis and colles' fractures in the elderly. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90058-1
[55] Ability of osteoclast formation from peripheral monocytes using anti‐fusion regulatory protein‐1/cd98/4f2 monoclonal antibodies in patients with osteoporosis. Journal of Orthopaedic Research. 2000. DOI: 10.1002/jor.1100180215
[56] Diabetes and osteoporosis: a two-sample mendelian randomization study. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07430-0
[58] Risk prediction models for postmenopausal osteoporosis: a systematic review and meta-analysis study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-025-09385-2