Patients › Shoulder
全肩关节置换术
Total shoulder replacement for severe arthritis — stemless options if rotator cuff is intact.
为何建议进行此手术
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生,会从适合您病情的最微创方案开始。患者通常由其全科医生(GP)转诊至我们的诊所;如果物理治疗师建议您就诊,您仍需获得全科医生的转诊,才有资格享受 Medicare 报销。诊所评估包括您的病史、体格检查以及必要时进行的影像学检查,以确立诊断。对于磨损性问题,如关节炎(覆盖关节的光滑软骨磨损),我们通常首先尝试非手术治疗:改变活动方式、物理治疗和夹板固定。当这些方法未能带来足够改善时,我们才会考虑手术。
全肩关节置换术即肩关节置换:移除肩关节磨损的表面,并用人工部件进行替换。当肩痛和僵硬限制了您的日常生活,且其他治疗效果不佳时,我们建议进行此手术。手术旨在缓解疼痛并改善肩部的活动能力和功能。约 90% 至 95% 接受此手术的患者疼痛得到缓解。超过 80% 的肩关节置换术可维持 10 年以上,75% 可维持 20 年以上。肩关节置换术的安全性与其它主要关节置换术相当。我们将与您详细讨论您的选择,并共同决定此手术是否适合您的肩部状况及您的目标。
术前
您的外科医生将根据肩部的X光片来规划手术,有时还会使用磁共振成像(MRI,一种显示软组织的扫描)或超声(一种利用声波进行的扫描)。这些影像显示了关节的形状、磨损程度以及周围肌腱的状况。这些细节有助于您的外科医生为您的肩部选择合适的假体部件。
在手术前的几天里,您将收到需要遵循的明确指示。您需要在手术前七小时停止进食和饮水。这段较长的禁食时间允许我们在手术室手术列表提前完成时,将您的手术提前安排。某些药物可能需要暂停服用,您的外科医生会告知您具体是哪些药物以及何时暂停。请携带一份您正在服用的所有药物的书面清单,包括药片、滴剂和天然疗法产品。请安排他人驾车送您回家,因为您将无法自行驾驶。请穿着宽松、舒适且易于穿脱的衣物。如果您有其他健康状况,可能需要在手术当天之前进行血液检查或接受麻醉师(负责实施麻醉的医生)的评估。
手术当天
您将抵达医院的手术入院单元,在此办理入院手续并做术前准备。术前您将与麻醉医生见面,并与其讨论麻醉方案。本手术在全身麻醉联合区域神经阻滞下进行。麻醉医生将在术前与您见面,并详细讲解这两部分的内容。随后,您将被带入手术室进行手术。
苏醒后,您将在复苏区。在麻醉药效消退期间,护士将对您进行监护。一旦您的生命体征稳定,您将被转入病房。如果您出院,您事先安排好的司机将接您回家。
手术内容
您的外科医生会在肩部前方做一个切口以进入关节。通过这个开口,他们会移除磨损的关节面:即肱骨顶端的圆形关节头以及与之相对运动的浅窝。这些部分将被替换为金属和塑料制成的人工部件,其形状与您的自身关节相匹配。
关节前方的一条肌腱——肩胛下肌(一个帮助手臂内旋的肌肉-肌腱单元)——会被轻轻移开以提供操作空间,并在手术结束时修复回原位。在整个过程中,您的外科医生会小心保护关节周围的软组织,并准确放置新的部件。
当新部件就位且肌腱修复完成后,伤口将被缝合关闭。首先,在闭合的伤口上覆盖一层细密的自粘网状物,以固定皮肤边缘。随后,在网状物上涂抹液体皮肤粘合剂,使其凝固以密封整体。该装置会保留大约一到两周,然后自行剥离脱落,因此无需取出任何异物。
术后
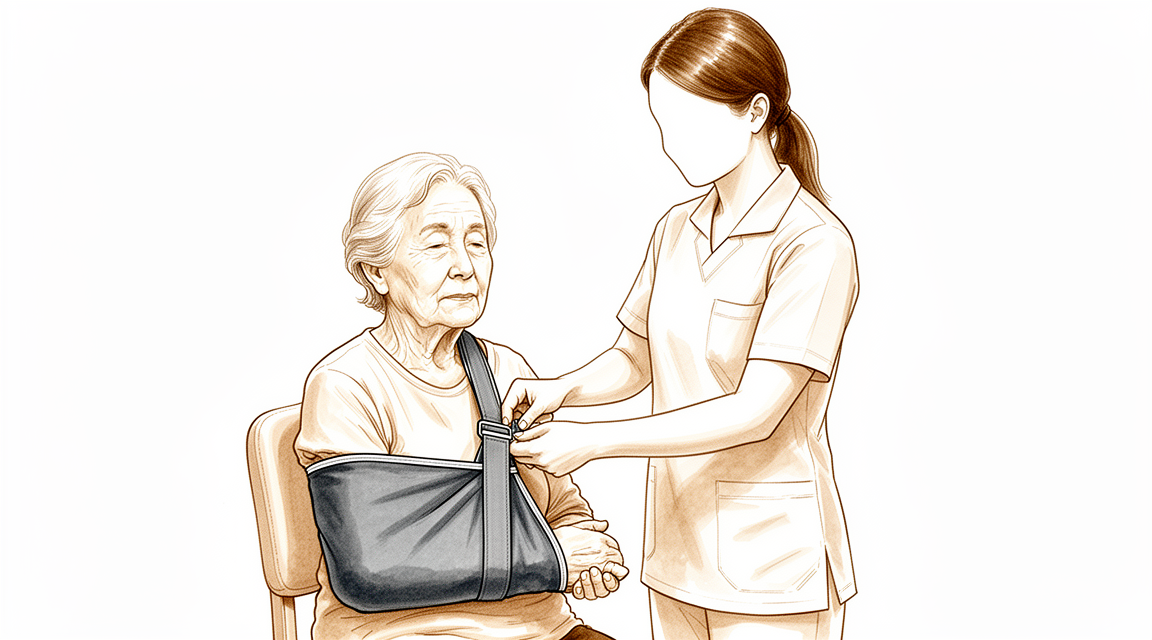
苏醒后,您将被安置在恢复区,随后转入病房。大多数患者在此手术后需在医院住一至两晚。您的手臂将佩戴简易三角巾以提供舒适支撑。进行锻炼和清洗时需取下三角巾。在离开手术室前,已为您制定疼痛控制方案,您的医疗团队将持续评估您的感受并根据需要调整方案。敷料将保留约10天;除非我们另行通知,否则请勿提前拆除。我们将在复诊时更换或拆除敷料。物理治疗师通常会在病房内为您进行初次评估,以开始轻柔的活动。请安排有人在您回家后的最初24小时内陪伴您。
恢复
每个人的恢复过程都有其独特的路径,您的时间表可能有所不同。您的外科医生和物理治疗师将在每次就诊时为您提供指导。
在最初几天和几周内,请预期肩部周围会出现一些疼痛和肿胀。对于大多数人来说,这种情况会逐渐缓解。您的医疗团队会在您出院前制定止痛方案,并根据需要进行调整。许多人通过简单的非阿片类止痛方案就能很好地控制疼痛。在练习间隙将手臂保持在吊带中有助于提高舒适度。休息、按照物理治疗师示范进行温和活动并遵循计划,将有助于减轻不适。
物理治疗师通常会在病房内为您进行初次温和活动训练。回家后,您需按指示继续进行这些练习。进行练习和洗澡时需取下吊带。起初,您在进行某些日常任务(如穿衣)时可能需要他人协助,因为手术侧手臂的活动会受到限制。早期睡眠可能会受到干扰,但随着肩部状况稳定,大多数人会发现睡眠质量有所改善。
活动能力和力量会分阶段恢复。随着肿胀消退和活动范围增大,日常任务会变得更加容易。一旦外科医生允许您驾驶(通常在术后六周复查时),您即可重新驾车。请参阅我们的指南上肢手术后驾驶。重返工作和运动取决于您的工作性质、活动类型以及肩部的愈合情况。您的外科医生和物理治疗师将向您说明在每个阶段哪些活动是安全的。
可能出现的并发症
大多数患者恢复良好,但偶尔可能出现并发症。您的外科医生和医疗团队会密切监测您的状况,以便尽早发现任何问题。
感染是需要警惕的最严重问题。其表现可能包括:不随普通止痛药缓解的深层搏动性疼痛、从伤口向外扩散的红肿,或发热。如果您注意到上述任何迹象,请立即告知诊所。有些感染可能在数月后才显现,因此在复查时,即使症状看似轻微,也请提及任何异常情况。
此手术后,静脉内可能形成血栓。这可能导致小腿突然肿胀和压痛。如果血栓碎片随血流到达肺部,您可能会感到突然的呼吸困难或胸部不适。若出现这种情况,请立即前往急诊科。
手术过程中,肩部周围的神经可能受到牵拉或挫伤。您可能会注意到手臂或手部出现麻木、刺痛或无力。其中许多症状可完全恢复,部分则仅能部分恢复。请在下次复查时告知医生,以便进行跟踪观察。
新关节附近的骨折并不常见,但可能在手术期间或术后发生。您会感到剧烈疼痛,并失去正常活动手臂的能力。若发生此情况,请致电诊所。
人工部件可能会随时间推移而松动。这通常表现为疼痛复发,有时伴有肩部的咔哒声或研磨感。请在复查时提及此情况,因为影像学检查可以显示具体发生了什么。
肩部还可能变得僵硬或不稳定,或者新部件可能脱位。您会注意到活动度突然丧失,或感觉关节位置发生偏移。请迅速联系诊所。
如果您之前接受过肩部手术,上述某些风险可能会更高。您的外科医生会在手术前与您讨论这一点。
如果您想了解具体数据,本页面中的并发症表格列出了典型的发生率。
何时联系我们
请相信您的直觉。如果感觉有任何异常,请联系我们。如果您出现发热、伤口红肿加重或渗出液增多,或疼痛持续加剧,请致电诊所。如果您出现小腿突然肿胀、呼吸困难或胸部不适,请立即前往急诊。这些可能是血栓的迹象。如果您手臂或手部失去感觉,或完全无法活动,请立即联系我们。大多数问题在早期更容易解决。
关于该疾病的更多阅读
本页介绍手术本身。该手术所治疗的疾病,包括证据显示手术在何时有效、何时无效,在肩关节炎页面上有更详细的介绍。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humerus comprises four main parts: the humeral head, greater tuberosity, lesser tuberosity, and humeral shaft [3].
- The articular head of the humerus is spherical with a diameter of 37 to 57 mm [3].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [3].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [3].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [3].
- The neck-shaft angle measures an average of 135 degrees [4].
- The humeral head is retroverted an average of 30 degrees [4].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [6].
- The anatomic neck of the proximal humerus is located at the junction of the articular surface and the tuberosities [3].
- The surgical neck represents an indistinct region below the tuberosities but above the humeral shaft [3].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [3].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [4].
- The subchondral bone of the glenoid is relatively flat, with articular concavity augmented by cartilage and a circumferential labrum [6].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [6].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [5].
- The scapula is separated from the chest wall by thin gliding fibro-fatty tissue, allowing smooth excursion over the chest wall [5].
- The basic part of the scapula is the body, which is triangular when viewed anteroposteriorly with its base situated superiorly and its apex inferiorly [5].
- The glenoid is connected with the flat body of the scapula by the scapular neck [5].
- The hook-shaped coracoid process curves forwards from the superior surface of the scapular neck [5].
- The scapular spine ends in a flattened bony process, the acromion, which curves forwards [5].
- The highest concentration of bony mass in the scapula is located in the glenoid, the scapular neck, and the lateral border of the scapular body [5].
- Two bony pillars transmit compressive forces from the glenoid fossa: the lateral pillar and the spinal pillar [5].
- The lateral pillar connects the inferior border of the glenoid with the inferior angle [5].
- The spinal pillar arises from the central part of the glenoid and continues medially to become part of the base of the scapular spine [5].
- The weakest bone in the scapula is located primarily in the central part of the biomechanical body, specifically in the infraspinous fossa [5].
- The weakest area of the circumference of the biomechanical body of the scapula is the spinomedial angle [5].
- The clavicle is the first bone to ossify, occurring in the fifth week of gestation [6].
- The clavicle is the only long bone to ossify by intramembranous ossification [6].
- The medial (sternal) epiphysis of the clavicle is the last ossification center to fuse, at age 20 to 25 years [6].
- Ossification of the scapular body begins at the eighth week of gestation [6].
- The acromion has three ossification centers: the metacromion, mesoacromion, and preacromion [6].
- Failure of fusion of the acromial ossification centers results in os acromiale [6].
- The proximal humerus has three centers of ossification: the humeral head, greater tuberosity, and lesser tuberosity [6].
- The humeral head ossification center appears at 4 to 6 months [6].
- The greater tuberosity ossification center appears at 1 to 3 years [6].
- The lesser tuberosity ossification center appears at 3 to 5 years [6].
- The proximal humeral ossification centers fuse to the shaft at age 17 to 20 years [6].
Soft Tissue Anatomy
- The greater tuberosity serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [3].
- The lesser tuberosity serves as the attachment site for the subscapularis tendon [3].
- The bicipital groove lies between the greater and lesser tuberosities and serves as a pathway for the long head of the biceps [3].
- The distal aspect of the bicipital groove is internally rotated with respect to the proximal portion [3].
- The rotator cuff consists of four muscles: the subscapularis, supraspinatus, infraspinatus, and teres minor [4].
- The teres major is not a rotator cuff muscle [4].
- The rotator cuff muscles serve as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [4].
- The infraspinatus and teres minor are external rotators of the humerus [4].
- The subscapularis is an internal rotator of the humerus [4].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch [3].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [3].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula [7].
- The subscapular bursa communicates with the joint cavity between the superior and middle glenohumeral ligaments [7].
- The subscapular bursa is linked to the coracoid process by a suspensory ligament [7].
- In 28% of dissected specimens, the subscapular bursae merged with the subcoracoid bursae, forming a unique wide bursa [7].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [6].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [6].
- The average area of the rotator interval is 20.96 mm [7].
- The superior transverse scapular ligament arises from the medial base of the coracoid overlying the suprascapular notch [6].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the nerve runs deep to it [6].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [6].
Vascular and Neural Anatomy
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [3].
- The posterior humeral circumflex artery travels with the axillary nerve and enters the quadrilateral space posteriorly [3].
- The anterior humeral circumflex artery arises from the axillary artery at the inferior border of the subscapularis [3].
- The anterior humeral circumflex artery provides vascular inflow to the humeral head via its terminal anterolateral branch, known as the artery of Laing or arcuate artery [3].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon [3].
- The ascending branch of the anterior humeral circumflex artery enters the humeral head at the interface of the bicipital groove and greater tuberosity [3].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [6].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [6].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [3].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [3].
- Fractures of the anatomic neck have a poor prognosis because of complete disruption of the blood supply to the head [4].
- Surgical neck fractures are common, and with these, the blood supply to the head is preserved [4].
- The brachial plexus and axillary artery are anterior to the coracoid process of the scapula and humeral head [4].
- Nerves innervating muscles around the shoulder include the axillary, suprascapular, subscapular, and musculocutaneous nerves [4].
- An axillary nerve injury from proximal humeral fracture or fracture-dislocation results in paralysis of the deltoid muscle and anesthesia over the “badge” region at the lateral proximal arm [4].
- Entrapment of the suprascapular nerve at the superior transverse scapular ligament causes denervation of both the supraspinatus and the infraspinatus [6].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [6].
Joint Stability and Ligaments
- Stability and function of the glenohumeral joint are provided by the interaction of structures that promote a near global range of motion and purposeful function [3].
- External loads transferred to the shoulder girdle are initially offset by joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion [3].
- Moderate and large loads are counterbalanced by the deltoid and rotator cuff and by the capsulolabral and bone structures, respectively [3].
- The glenohumeral joint is stabilized dynamically by the rotator cuff via joint compression [6].
- Static stabilizers of the glenohumeral joint include articular congruity, the glenoid labrum, concavity-compression, negative intra-articular pressure, and the glenohumeral capsule and ligaments [6].
- The glenoid labrum provides concavity and up to 50% of marginal glenoid socket depth [6].
- The coracohumeral ligament restricts external rotation in adduction [6].
- The coracohumeral ligament is a static restraint to inferior and posterior translation in adduction and external rotation [6].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [6].
- The superior glenohumeral ligament and coracohumeral ligament form a pulley that provides restraint against medial subluxation of the long head of the biceps tendon [6].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [6].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation of the glenohumeral joint in 90° of abduction and external rotation [6].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [6].
- Laxity of the rotator interval results in inferior laxity, known as the sulcus sign [6].
- Contracture of the rotator interval is seen with adhesive capsulitis [6].
- The superior shoulder suspensory complex provides a stable connection between the scapula and the axial skeleton [6].
- The superior shoulder suspensory complex is composed of the glenoid, coracoid process, coracoclavicular ligaments, distal clavicle, acromioclavicular joint, and acromion [6].
- The superior strut of the superior shoulder suspensory complex comprises the middle clavicle [6].
- The inferior strut of the superior shoulder suspensory complex comprises the lateral scapular border and spine of the scapula [6].
- The sternoclavicular joint is the only true diarthrodial articulation between the upper appendicular and axial skeletons [6].
- The posterior sternoclavicular joint capsule and ligaments are the primary stabilizers to anterior and posterior translation of the medial clavicle [6].
- The acromioclavicular joint is a small diarthrodial joint with an interposed fibrocartilaginous disk [6].
- The superior and posterior acromioclavicular ligaments are the primary stabilizers to anterior and posterior translation of the clavicle [6].
- The coracoclavicular ligaments are the primary stabilizers to superior translation of the distal clavicle [6].
Pathophysiology
- Post-traumatic shoulder fractures alter complex interactions of the shoulder girdle, resulting in pain, decreased range of motion and stiffness, and disability [3].
- Displacement of proximal humeral fracture fragments is based on deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [3].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement of the fragment [3].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement of the fragment [3].
- The pectoralis major inserts on the humeral shaft and displaces it medially [3].
- A fracture involving the anatomic neck is prognostically worse than fractures involving other regions of the proximal humerus regarding potential disruption of the vascular supply to the humeral head and subsequent development of avascular necrosis [3].
- Displaced proximal humeral fractures can impede normal movement of structures passing under the coracoacromial arch, causing impingement and disruption of normal glenohumeral motion [3].
- In proximal humeral fractures, the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that limit normal glenohumeral motion [3].
- The pathogenesis of shoulder stiffness is still elusive, though basic science research has provided insight into cellular and biochemical pathways [1].
- The diagnosis of a stiff shoulder depends on awareness of the problem, with history and physical examination being paramount [1].
- No treatment for a stiff shoulder has proved to be definitive [1].
- The literature supports many forms of treatment for a stiff shoulder, both operative and nonoperative [1].
- The treatment approach for a stiff shoulder should be tailored to each individual patient to ensure the best possible outcome [1].
- Arthritis usually involves the central aspect of the humeral head [2].
- Joint space narrowing in arthritis is most evident on the axillary view taken with the arm in elevation, as opposed to images made with the arm at the side [2].
- The axillary view taken with the arm in elevation can show posterior subluxation or “functional decentering” that is not evident in images taken with the arm at the side [2].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and “rocking horse” loosening of prosthetic glenoid components [2].
- The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the plane of the scapula [2].
- The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the glenoid face [2].
- The degree of posterior subluxation can be measured by the point of contact of the humeral articular surface on the glenoid articular surface [2].
- The point of contact of the humeral articular surface on the glenoid articular surface reflects the degree of centering of the net humeral joint reaction force on the glenoid [2].
- Normal shoulder motion is approximately two-thirds glenohumeral and one third scapulothoracic [6].
- The relationship between acromial anatomy and rotator cuff disease remains controversial [6].
- The classification of acromial morphology (flat, curved, or hooked) is challenged by poor interobserver reliability [6].
- The relationship between coracoid morphology and subscapularis tears is controversial [6].
Investigations
Radiographic Evaluation
- The purpose of shoulder imaging is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [2].
- Unless a specific research protocol is in place, the tendency to "overimage" should be resisted by obtaining only the scans or reconstructions necessary for patient care [2].
- Standardized plain films are almost always sufficient to garner the information needed for total shoulder arthroplasty [2].
- CT scans may offer increased precision in the measurement of glenoid version, but this precision does not improve the quality of the surgery or the clinical outcome [2].
- Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [2].
- The first key radiographic view is the anteroposterior (AP) view in the plane of the scapula, taken so that the x-ray beam passes through the glenohumeral joint [2].
- The AP view in the plane of the scapula shows the superoinferior position of the humeral head relative to the glenoid, presence of osteophytes, narrowing of the joint space, degree of medial displacement of the humerus, quality of bone, presence of loose bodies, and humeral head collapse or deformity [2].
- The second key radiographic view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [2].
- The axillary view is oriented so that both the spinoglenoid notch and the scapular neck are visible [2].
- The axillary view demonstrates the amount of glenoid bone, shape of the glenoid, its version in relation to the plane of the scapula, and the relationship of the humeral head to the glenoid fossa [2].
- The axillary view is referred to as the "truth view" because it demonstrates glenohumeral relationships in the functional position of elevation [2].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view [2].
- Many axillary views sent for consultation are taken without standardization, making it impossible to determine important features of the glenohumeral joint [2].
- Standardized anteroposterior and axillary views indicate the thickness of the cartilage space between the humerus and the glenoid, relative positions of the humeral head and glenoid, presence of osteophytes, degree of osteopenia, and extent of bony deformity and erosion [2].
- Joint space narrowing is most evident on the axillary truth view as opposed to images made with the arm at the side [2].
- The axillary truth view shows posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [2].
- Three-dimensional reconstructions can reveal fine details of shoulder anatomy, but this additional information rarely changes the planning or conduct of the arthroplasty [2].
- At least two X-ray views should be obtained: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [11].
- Computed tomography (CT) is helpful for planning shoulder joint replacement [11].
Magnetic Resonance Imaging
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head or a bone tumour [11].
- MRI can identify labral tears and rotator cuff tears, although the accuracy for these is enhanced by combining the scan with arthrography [11].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [11].
- Ultrasonography can be useful in guiding injections or barbotage (aspirating calcific deposits in the rotator cuff) [11].
- The most commonly performed joint examination using ultrasonography is the shoulder examination [9].
- The accuracy of rotator cuff ultrasonography depends on the skill of the scanner operator and an awareness of pitfalls encountered [9].
General Imaging Principles
- The shoulder is a three-dimensional structure that cannot be represented by a single planar view [13].
- Critical relationships, such as the degree of centering of the humeral head, change with the position of the arm [13].
- Shoulder pathology may be found in a large number of different bones and soft tissues [13].
- Overlying and superimposed structures as well as metallic implants may complicate imaging the structures of interest [13].
- Surgeons need to develop a judicious approach to imaging that yields necessary information while avoiding the tendency to "over-image" [13].
References
[1] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > SUMMARY.
[2] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[3] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[4] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[5] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[6] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[7] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[9] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[11] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[13] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.