Patients › General-Health
富血小板血浆(PRP)与注射治疗
What the evidence shows for platelet-rich plasma and related injection therapies in tendinopathy, osteoarthritis and rotator cuff disease — where they help and where the data is weak.
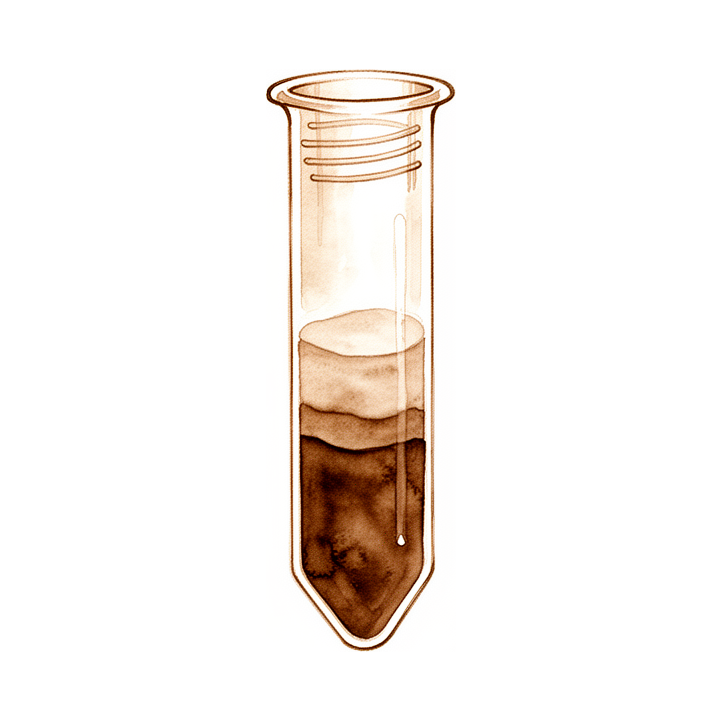
什么是 PRP
富血小板血浆(通常简称 PRP)是一种用您自己的血液制成的治疗。医生会抽取您的一小份血液样本,放入机器中离心,使血小板分离并浓缩。血小板是血液中帮助凝血的微小成分,它们还携带生长因子,这是一类可能有助于愈合的天然物质。随后,将浓缩的血小板注射到疼痛部位。
对于膝关节的磨损性关节炎、肘部、肩部或腕部的肌腱问题,以及某些运动中的肌肉损伤等问题,您的医生可能会考虑使用 PRP。它并不适用于所有疾病。对于网球肘,证据不一:一些研究发现,从较长期来看,PRP 的效果优于类固醇注射 [1],而一项对多项试验的综述并不支持 PRP 优于安慰剂 [2]。对于膝关节炎,通常建议注射两次,效果可持续至少 24 周 [3]。对于腕管综合征,在 6 个月随访时,PRP 显示出比类固醇注射更持久的获益 [4]。
PRP 背后的设想是,血小板中的生长因子可能减轻炎症并促进组织修复。相关细节仍在研究之中。研究显示,不同的制备方式效果各不相同:一种富含白细胞的类型似乎适合早期关节炎,而另一种血小板更多、白细胞更少的类型可能适合较晚期的关节炎 [5]。一些试验发现,对于肩部和肘部的肌腱问题,PRP 的效果优于麻醉剂注射,但并不优于干针或盐水注射 [6]。总体而言,证据因疾病而异,您的医生会与您讨论 PRP 对您的具体问题是否合理。
它有效吗?
坦白地说,这取决于具体疾病,而且在某些情况下,研究仍在追赶之中。一项证据综述发现,PRP 是一种可能值得关注的治疗,但目前还没有足够的高质量研究来支持广泛使用它 [7]。研究人员还指出,一些关于 PRP 治疗膝关节炎试验的摘要对结果作了偏向正面的表述,这可能让该治疗看起来比证据实际显示的更好 [8]。
对于某些疾病,结果更令人鼓舞。对于肌腱问题,试验发现 PRP 改善了疼痛以及受累部位的功能,并且在中期效果优于类固醇注射 [9]。对于膝关节炎,PRP 改善了整体功能,尤其是在较年轻的人群中 [10]。将 PRP 与透明质酸(一种天然存在于关节中的润滑物质)联合使用,比单用 PRP 带来了更好的疼痛缓解和功能 [11]。
对于另一些疾病,情况不一或尚不明确。对于网球肘,一些试验发现 PRP 在最初几个月减轻了疼痛并改善了功能 [12],而另一些研究并不支持将其作为一种治疗 [2]。对于肩袖撕裂,目前没有足够的可靠证据来判断其是否有效 [13]。对于膝关节软骨损伤,现有证据尚不支持单独进行 PRP 注射 [14]。
这对您意味着什么?PRP 可能对某些问题有帮助,但它并不是对所有问题都已证实有效的解决办法。您的医生会与您讨论针对您的具体疾病证据显示了什么,以便您和医生共同决定是否值得一试。
风险有哪些?
PRP 是用您自己的血液制成的,因此您的身体不太可能对这种材料本身产生不良反应。但这并不意味着该治疗毫无风险。注射本身可能在之后几天引起疼痛、肿胀和僵硬,治疗部位可能会先感到酸痛,然后才好转。您的医生会告诉您如何处理这些情况。
关于 PRP 治疗膝关节炎的研究尚未确定其效果究竟如何,一些已发表的摘要对结果作了偏向正面的表述 [8]。在您权衡是否接受治疗时,这一点很重要,因为一种听起来很有前景的治疗,可能无法带来您所期望的缓解。对于肩袖修复,加用 PRP 提高了愈合率,但并未改变患者在日常生活中使用肩部的能力 [15]。对于跟腱问题,试验发现 PRP 的效果并不优于安慰剂 [16]。
您的身体如何反应也可能取决于您的个人情况。既往接受过皮质类固醇注射以及使用烟草,似乎会降低 PRP 治疗慢性内上髁炎(一种肘部内侧的肌腱问题)的效果 [17]。如果您吸烟,或曾在同一部位接受过类固醇注射,请在决定治疗前告知医生。
一些问题仍未有定论。研究人员指出,还需要更多研究来证实 PRP 的长期效果 [18]。关于 PRP 治疗网球肘的研究结果不一,一些试验报告了早期疼痛缓解和功能改善 [12],而另一些则发现与安慰剂相比没有明确获益 [2]。此外,目前也还没有足够的可靠证据支持单独进行 PRP 注射来治疗膝关节软骨损伤 [14]。
如果在治疗后几天内,您注意到注射部位周围的疼痛加重、发红或发热,请联系我们的诊所,以便我们为您检查。在您决定是否接受治疗之前,您的医生会与您讨论针对您病情的具体风险。
这适合您吗?
PRP 往往更适合某些人。如果您的膝关节患有磨损性关节炎,建议至少注射两次,效果可持续至少 24 周 [3]。如果您参加竞技体育运动,研究人员建议为竞技体育运动员提供 PRP 治疗 [19]。如果您双侧手腕都患有腕管综合征,在 6 个月随访时,PRP 显示出比类固醇注射更持久的获益 [4]。
在某些情况下,PRP 不太可能是合适的选择。如果您的膝关节软骨受损,现有证据尚不支持单独进行 PRP 注射 [14]。对于网球肘,证据不一,因此它可能对您有帮助,也可能没有帮助。如果您吸烟,或之前曾在同一部位接受过类固醇注射,PRP 对您的效果可能会较差。
PRP 是多种选择之一。对于某些疾病,类固醇注射是主要的替代方案,而在某些情况下,PRP 已显示出比类固醇更持久的获益 [4]。另一种选择是透明质酸,一种天然存在于关节中的润滑物质。比较这两者的研究仍处于早期阶段,因此您的医生会向您解释目前已知的情况。
这应当是您与医生共同作出的决定。请考虑您的目标、您的病情以及针对该病情的证据。您的医生会与您讨论各种选择,包括上文所述的风险,以便您和医生共同决定 PRP 是否适合您。
核心要点
对于某些问题,PRP 值得考虑,但请抱有现实的期望。它可能缓解膝关节炎和某些肌腱疾病的疼痛并改善功能,但效果因人而异。最重要的提醒是,研究仍在追赶之中,对于若干疾病,目前还没有足够的高质量证据来支持广泛使用它 [7]。您的医生会帮助您权衡它对您的具体问题是否合理。
参考文献
[1] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[2] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[3] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[4] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[5] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[6] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[7] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[8] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[9] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[10] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[11] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[12] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[13] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[14] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[15] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[16] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[17] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[18] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[19] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- PRP remains a potentially interesting intervention for chronic tennis elbow but currently lacks sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- At least two PRP injections are recommended for treating knee osteoarthritis, with effects lasting for at least 24 weeks [2].
- The conclusions of the study on PRP for knee osteoarthritis do not provide a conclusive statement but aim to stimulate further research and shed light on factors influencing efficacy in clinical practice [3].
- There is no definitive evidence regarding the effectiveness of PRP treatment when the literature is evaluated [4].
- Further studies are needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future [5].
- Conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [6].
- Future studies should prioritize long-term outcomes to guide clinical decision-making more effectively [6].
- Both leukocyte-rich (L-PRP) and leukocyte-poor (LP-PRP) are effective treatment options with comparable efficacy based on current evidence [7].
- PRP was superior to anesthetics in 2 studies for shoulder and elbow tendinopathy [8].
- PRP showed no clinical efficacy compared with dry needling or saline injections in 3 studies for shoulder and elbow tendinopathy [8].
- Interventions employing PRP, MSCs, and exosomes are considered in the context of degenerative osteoarthritis as a reversible chronic disease [9].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [10].
- The authors recommend systematically offering PRP therapy for competition sports practitioners [11].
- PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection for gluteal tendinopathy [12].
- The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO [13].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in bilateral moderate carpal tunnel syndrome [14].
- Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease [15].
- There is insufficient evidence to recommend for or against the use of PRP for rotator cuff tears given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant [16].
- Current evidence supports the selective use of PRP in sports settings for acute muscle injuries, though standardization in protocols and outcomes is needed [18].
- Studies evaluating the outcomes and procedures of the use of PRP in the setting of lateral epicondylitis have poor adherence to MIBO guidelines [22].
- The statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
- Findings from a meta-analysis of randomized clinical trials do not support PRP as a recommended treatment for lateral epicondylitis as compared with placebo [27].
- It is recommended to wait for at least one month before considering another injection or alternative treatments for first presentation trigger digits [28].
- The authors do not support the routine use of PRP for the treatment of greater trochanteric pain syndrome [29].
How It Works
Tendinopathy and Soft Tissue
- PRP was superior to anesthetics in 2 studies but showed no clinical efficacy compared with dry needling or saline injections in 3 studies for shoulder and elbow tendinopathy [8].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis [23].
- High-dose PRP showed significant efficacy over alternative treatment strategies for lateral epicondylitis [23].
- Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months for lateral elbow tendinopathy [20].
- PRP is no more effective than placebo for treating Achilles tendinopathy [21].
- Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP for chronic medial epicondylitis [35].
- Time-dependent growth factor kinetics and platelet concentration influence clinical response following PRP versus saline in chronic tenosynovitis [10].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo for chronic tenosynovitis [10].
- PRP enhances anabolic gene expression patterns in flexor digitorum superficialis tendons [34].
- An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations [32].
Osteoarthritis
- At least two PRP injections are recommended for knee osteoarthritis, with effects lasting for at least 24 weeks [2].
- Both leukocyte-rich PRP (L-PRP) and leukocyte-poor PRP (LP-PRP) are effective treatment options with comparable efficacy for knee osteoarthritis based on current evidence [7].
- Optimizing osteoarthritis treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects [36].
- High platelet, low leukocyte PRP is preferred for advanced osteoarthritis to promote tissue repair and regeneration [36].
- The improvement from PRP injections for knee osteoarthritis is clinically significant and influenced by platelet concentration [3].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection for bilateral moderate carpal tunnel syndrome [14].
- The study compared the efficacy of intra-articular injections of platelet-rich plasma (PRP) and viscosupplementation (hyaluronic acid [HA]) for the treatment of knee degenerative cartilage lesions and osteoarthritis [19].
- The authors recommend systematically offering PRP therapy for competition sports practitioners with large joint osteoarthritis [11].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future for hypertrophic facet joints [5].
Fracture Healing and Nonunion
- The effectiveness rate for excellent and good limb function was 85.19% in the combined group (PRP plus extracorporeal shock wave) versus 60.71% in the PRP group for long diaphysis aseptic nonunion [25].
- At final follow-up, all patients in the PRP-enhanced group healed, while 80.49% of the non-PRP group healed for aseptic femoral shaft nonunion (p = 0.049) [37].
- Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of a specific study on delayed union or non-union [31].
Rotator Cuff Repair
- LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes for rotator cuff repair [40].
- The authors state that the significant difference in the retear rate, even in an underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP) for arthroscopic repair of medium to large rotator cuff tears [26].
General Mechanisms and Evidence Status
- PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use for chronic tennis elbow [1].
- The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [6].
- Future studies should prioritize long-term outcomes to guide clinical decision-making more effectively for PRP [6].
- The goal of a specific study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations [33].
- The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA [17].
- The PRP used in a specific study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP [38].
What the Evidence Shows
Tendinopathy and Soft Tissue Injuries
- A meta-analysis of randomized clinical trials found that PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [21].
- A meta-analysis of randomized clinical trials found that PRP does not improve pain or function in patients with lateral epicondylitis as compared with placebo and does not support PRP as a recommended treatment for this condition [27].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis, with high-dose PRP showing significant efficacy over alternative treatment strategies [23].
- PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis in the early follow-up period [45].
- After autologous blood injection therapy, 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity for refractory lateral epicondylitis [47].
- PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids [43].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in patients with bilateral moderate carpal tunnel syndrome [14].
Osteoarthritis
- A double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee osteoarthritis [41].
- Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary osteoarthritis, particularly in younger individuals [46].
- For patients with knee osteoarthritis, PRP combined with hyaluronic acid (HA) therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy [44].
- The combination of PRP with non-crosslinked HA in mono-injection was found to be non-inferior to crosslinked HA, with regards to the percentage of responders over 6 months (WOMAC pain) for knee osteoarthritis [49].
- Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP [48].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the treatment of hypertrophic facet joints [5].
Rotator Cuff and Shoulder
- Among level 1 RCTs reporting VAS pain scores after PRP injection for partial-thickness rotator cuff tears, platelet concentration was not significantly associated with improved pain outcomes [50].
Other Indications and Methodology
- The application of PRP following core decompression results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to core decompression alone for early osteonecrosis of the femoral head [42].
- Current evidence is insufficient to support orthobiologic injections adjunctive to cartilage-preserving surgery as standalone procedures for focal knee chondral defects [30].
Practical Considerations
General Evidence Status and Research Needs
- PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- There is no definitive evidence regarding the effectiveness of PRP treatment [4].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future [5].
- Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed [18].
Dosing, Protocol, and Preparation
- At least two PRP injections are recommended, with effects lasting for at least 24 weeks [2].
- Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence [7].
Indication-Specific Outcomes and Comparisons
- These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [10].
- PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [21].
- There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant for rotator cuff tears [16].
- The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost after arthroscopic rotator cuff repair [39].
- Current evidence is insufficient to support orthobiologic injections as standalone procedures for focal knee chondral defects [30].
Methodological and Interpretive Caveats
- The conclusions of a study on intra-articular PRP injections for knee osteoarthritis do not intend to provide a conclusive statement but rather to stimulate further research [3].
- The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
Key Evidence
- [L5] The authors conclude that PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use. [1] (10.1177/0363546513512784)
- [L3] At least two PRP injections are recommended, with effects lasting for at least 24 weeks. [2] (10.1186/s13018-025-05756-6)
- [Paper] The conclusions of this study do not intend to provide a conclusive statement but rather to stimulate further research in this complex field and contribute to shedding light on the several aspects influencing the efficacy of intra-articular platelet-rich plasma (PRP) injections for knee osteoarthritis (OA) in clinical practice. [3] (10.1177/03635465251387701)
- [L5] When the literature is evaluated, it is understood that there is no definitive evidence regarding the effectiveness of PRP treatment. [4] (10.1177/23259671241255700)
- [L4] Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future. [5] (10.5435/jaaosglobal-d-24-00140)
- [L5] The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up; future studies should prioritize long-term outcomes to guide clinical decision-making more effectively. [6] (10.1016/j.arth.2025.05.007)
- [L1] Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence. [7] (10.1186/s13018-026-06689-4)
- [L1] PRP was superior to anesthetics in 2 studies but showed no clinical efficacy compared with dry needling or saline injections in 3 studies. [8] (10.1097/bte.0000000000000118)
- [L5] Interventions employing PRP, MSCs and exosomes are considered in this article. [9] (10.1016/j.reth.2020.07.007)
- [L1] These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo. [10] (10.1186/s12891-025-09339-8)
- [L4] The authors recommend systematically offering PRP therapy for competition sports practitioners. [11] (10.1186/s12891-025-08663-3)
- [L5] The authors state that the conclusion of the referenced randomized controlled trial is that PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection. [12] (10.1177/0363546518773719)
- [Paper] The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO. [13] (10.1177/03635465231203202)
- [L1] PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up. [14] (10.1016/j.injury.2026.113018)
- [Paper] Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease. [15] (10.1177/03635465251395284)
- [L5] There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant. [16] (10.1177/0363546520918190)
- [L5] The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA. [17] (10.1177/0363546514537991)
- [L2] Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed. [18] (10.1177/23259671251399907)
- [L1] Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months. [20] (10.1177/23259671251386862)
- [L1] PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge. [21] (10.1097/corr.0000000000003478)
- [L2] This review demonstrated that studies evaluating the outcomes and procedures of the use of PRP in the setting of LE have poor adherence to MIBO guidelines. [22] (10.5397/cise.2024.01060)
- [L1] A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection, with high-dose PRP showing significant efficacy over alternative treatment strategies. [23] (10.1016/j.jisako.2025.100442)
- [L5] The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations. [24] (10.1177/0363546517703364)
- [L1] The effectiveness rate for excellent and good limb function was 85.19% in the combined group versus 60.71% in the PRP group. [25] (10.1016/j.otsr.2022.103417)
- [L5] The authors state that the significant difference in the retear rate, even in this underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP). [26] (10.1177/0363546515625958)
- [L1] These findings do not support PRP as a recommended treatment for this condition. [27] (10.1177/03635465251383039)
- [L3] It is recommended to wait for at least one month before considering another injection or alternative treatments. [28] (10.1142/s2424835520500253)
- [L1] As a result, we do not support the routine use of PRP for the treatment of this condition. [29] (10.2106/jbjs.24.00763)
- [L2] Current evidence is insufficient to support such injections as standalone procedures. [30] (10.1002/arj.70548)
- [L4] Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of the current study. [31] (10.1016/s0020-1383(13)70158-x)
- [L5] An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations. [32] (10.1016/s0020-1383(14)70004-x)
- [L5] The goal of the study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations. [33] (10.1177/03635465231206930)
- [Paper] These findings support in vivo investigation of PRP as an autogenous, patient-side treatment for tendonitis. [34] (10.1002/jor.20278)
- [L4] Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP. [35] (10.1177/1753193414567012)
- [L1] Optimizing OA treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects and high platelet, low leukocyte PRP preferred for advanced OA to promote tissue repair and regeneration. [36] (10.1186/s13018-025-06026-1)
- [L3] At final follow-up, all patients in Group 1 (PRP-enhanced) healed, while 80.49% of Group 2 (non-PRP) healed (p = 0.049). [37] (10.1016/j.injury.2025.112325)
- [L5] The authors also highlight that the PRP used in the study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP. [38] (10.1177/0363546514537996)
- [L1] The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost. [39] (10.1016/j.jse.2026.02.018)
- [L1] Consequently, LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes. [40] (10.1002/arj.70537)
- [L1] This double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee OA. [41] (10.1177/03635465241283500)
- [L3] The application of PRP following CD results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to CD alone. [42] (10.1186/s12891-024-08243-x)
- [L1] PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids. [43] (10.1186/s12891-025-08566-3)
- [L1] This meta-analysis reveals that, for patients with KOA, PRP + HA therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy. [44] (10.1186/s13018-024-05429-w)
- [L4] PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis. [45] (10.1177/2325967125s00169)
- [L1] Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary OA, particularly in younger individuals. [46] (10.1186/s12891-026-09486-6)
- [L4] After autologous blood injection therapy 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity. [47] (10.1053/jhsu.2003.50041)
- [L1] Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP. [48] (10.1002/arj.70027)
- [L1] The combination of PRP with non-crosslinked HA in mono-injection was found to be non-inferior to crosslinked HA, with regards to the percentage of responders over 6 months (WOMAC pain). [49] (10.1186/s12891-026-09625-z)
- [L1] Among level 1 RCTs reporting VAS pain scores after PRP injection for partial-thickness rotator cuff tears, platelet concentration was not significantly associated with improved pain outcomes. [50] (10.1177/23259671261480483)
References
[1] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[2] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[3] PRP Injections for the Treatment of Knee Osteoarthritis: The Improvement Is Clinically Significant and Influenced by Platelet Concentration: Response. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251387701
[4] Comparison of Conventional Dose Versus Superdose Platelet-Rich Plasma for Knee Osteoarthritis: Letter to the Editor. Orthopaedic Journal of Sports Medicine. 2024. DOI: 10.1177/23259671241255700
[5] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[6] Letter Regarding “Platelet-Rich Plasma Injections are Inferior to Corticosteroid Injections for Short-Term Pain Relief: A Prospective, Double-Blinded, Randomized Controlled Trial”. The Journal of Arthroplasty. 2025. DOI: 10.1016/j.arth.2025.05.007
[7] Leukocyte-rich versus leukocyte-poor platelet-rich plasma and hyaluronic acid for knee osteoarthritis: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06689-4
[8] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[9] Degenerative osteoarthritis a reversible chronic disease. Regenerative Therapy. 2020. DOI: 10.1016/j.reth.2020.07.007
[10] Time-dependent growth factor kinetics, platelet concentration, and clinical response following platelet-rich plasma versus saline in chronic tenosynovitis: a randomized controlled trial. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09339-8
[11] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
[12] The Effectiveness of Platelet-Rich Plasma Injections in Gluteal Tendinopathy: Response. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518773719
[13] Improving Injectable Orthobiologics Reporting Guidelines Adherence: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231203202
[14] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[15] Platelet-Rich Plasma in the Treatment of Musculoskeletal Disease in 2025 and Beyond. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251395284
[16] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[17] The Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Patel and Dhillon. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537991
[18] Platelet-Rich Plasma in Acute Muscle Injuries: An Umbrella Review and Meta-analysis of Return to Sport and Reinjury Outcomes. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251399907
[19] Platelet-Rich_Plasma_Versus_Hyaluronic_Acid_S0749806312015812. 2015.
[20] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[21] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[22] Adherence rates to the Minimum Information for Studies Evaluating Biologics in Orthopedics guidelines for clinical studies on platelet-rich plasma for the treatment of lateral epicondylitis: a systematic review. Clinics in Shoulder and Elbow. 2026. DOI: 10.5397/cise.2024.01060
[23] Platelet Concentration Factor Explains Variability in Outcomes of Platelet-rich Plasma for Lateral Epicondylitis: High Dose Critical for Positive Response. Journal of ISAKOS. 2025. DOI: 10.1016/j.jisako.2025.100442
[24] Hyaluronic Acid Versus Platelet-rich Plasma: Response. The American Journal of Sports Medicine. 2017. DOI: 10.1177/0363546517703364
[25] Synergistic effects of autologous platelet-rich plasma combined with an extracorporeal shock wave in treatment of long diaphysis aseptic nonunion. Orthopaedics & Traumatology: Surgery & Research. 2024. DOI: 10.1016/j.otsr.2022.103417
[26] PRP for Arthroscopic Repair of Medium to Large Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2016. DOI: 10.1177/0363546515625958
[27] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[28] Time to Resolution of Triggering after Steroid Injection for First Presentation Trigger Digits. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520500253
[29] Efficacy of Platelet-Rich Plasma Versus Placebo for the Treatment of Greater Trochanteric Pain Syndrome. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00763
[30] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[31] PS9 Is platelet-rich plasma injection an effective choice in cases of delayed union or non-union?. Injury. 2013. DOI: 10.1016/s0020-1383(13)70158-x
[32] Muscle repair: platelet-rich plasma derivates as a bridge from spontaneity to intervention. Injury. 2014. DOI: 10.1016/s0020-1383(14)70004-x
[33] The Accurate Characterization of Platelet-Rich Plasma Enables Its Classification and Comparison: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231206930
[34] Platelet rich plasma (PRP) enhances anabolic gene expression patterns in flexor digitorum superficialis tendons. Journal of Orthopaedic Research. 2006. DOI: 10.1002/jor.20278
[35] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[36] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[37] Based on the diamond concept, application of platelet-rich plasma in the treatment of aseptic femoral shaft nonunion: A retrospective controlled study on 66 patients. Injury. 2025. DOI: 10.1016/j.injury.2025.112325
[38] Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Andia and Maffulli. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537996
[39] Leukocyte-poor platelet-rich plasma reduces retear risk after arthroscopic rotator cuff repair: a meta-analysis with mechanistic and economic evaluation. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.018
[40] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[41] Leukocytes Do Not Influence the Safety and Efficacy of Platelet-Rich Plasma Injections for the Treatment of Knee Osteoarthritis: A Double-Blind Randomized Controlled Trial. The American Journal of Sports Medicine. 2024. DOI: 10.1177/03635465241283500
[42] Efficacy of small-diameter core decompression with platelet-rich plasma in early osteonecrosis of the femoral head: a retrospective study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08243-x
[43] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[44] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[45] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[46] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[47] Autologous blood injections for refractory lateral epicondylitis. The Journal of Hand Surgery. 2003. DOI: 10.1053/jhsu.2003.50041
[48] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[49] Efficacy and safety of a combination of platelet-rich plasma with non-crosslinked hyaluronic acid versus a crosslinked hyaluronic acid, in single-injection for knee osteoarthritis. Randomized, controlled, multicenter, non-inferiority trial. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09625-z
[50] Platelet Concentration Is Not Associated With Improved Pain for Partial-Thickness Rotator Cuff Tears Treated With Platelet-Rich Plasma: A Systematic Review and Meta-analysis With Meta-regression of Level 1 Randomized Controlled Trials. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671261480483