Patients › Hand
屈肌腱鞘囊肿
A benign, fluid-filled cyst arising from the flexor tendon sheath – often painless, but can cause clicking or limited finger movement.
您的症状
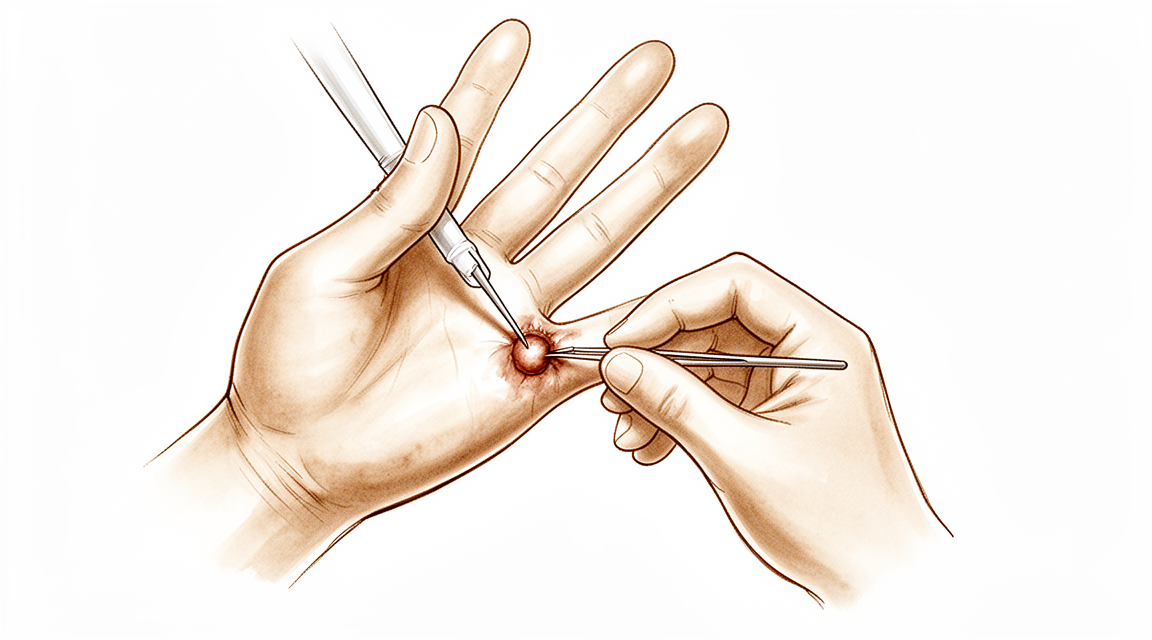
屈肌腱鞘腱鞘囊肿是位于手掌中手指根部的一个小而坚硬的肿块。它通常直径只有几毫米,但引起的疼痛可能比您想象中这么小的东西要严重。疼痛出现在您紧握坚硬且狭窄的物体时,例如方向盘、高尔夫球杆、自行车把手或购物袋提手。肿块被夹在物体与手指骨骼之间,没有柔软的组织作为缓冲。
疼痛往往在这些抓握动作期间或之后加重。提重的购物袋、握工具或拧干洗好的衣物等事情都可能变得不适。有些人注意到,松开物体后酸痛就会缓解。肿块本身质地坚硬而非柔软,正好位于手指弯向手掌的位置。
由于疼痛与抓握有关,它可能开始限制您用这只手所做的事情。您可能会发现自己在回避某些活动,或改变握持物品的方式,以免压到该处。
如果您的手指、手部或手臂变得发热、发红、肿胀并疼痛,尤其是伴有发烧,需要当天前往急诊科就诊。无需全科医生转诊。
实际发生了什么
您的手指之所以能弯曲,是因为有两条肌腱从前臂出发,沿手指的掌侧走行,并附着在指骨上。可以把它们想象成您弯曲手指时拉动的绳索。为了使这些绳索紧贴骨骼而不是向外弓起,它们在一条由称为滑车的坚韧束带构成的隧道内走行。这条隧道内衬一层薄而滑的组织,为肌腱提供营养,并使其顺畅滑动。
屈肌腱鞘腱鞘囊肿是从这条隧道中突出的一个小囊袋,里面充满浓稠、果冻状的液体。囊袋由腱鞘本身的内衬充盈,因此它就像一处承受压力的小渗漏:把液体抽掉,它又会重新充满,因为渗漏点仍然存在。囊袋正好位于手掌中手指的根部,在这里隧道紧紧附着在骨骼上,上面没有柔软的衬垫。这就是为什么一个直径只有几毫米的肿块在您抓握时会如此疼痛:肿块被夹在您所握的物体与下方的骨骼之间。
同一个部位也解释了您可能注意到的其他情况。由于肿块在狭窄的隧道内占据空间,它可能在肌腱滑过时挤压肌腱,这就是为什么此部位有肿块的一些人手指还会出现卡住或弹响。通往手指的神经就在腱鞘旁边走行,两侧各有一条,因此肿块压迫神经时可能引起刺痛或麻木,而不仅仅是疼痛。
值得了解的是,恰好位于此部位的肿块也可能由其他原因引起,例如肌腱在滑动时卡住,或手掌组织增厚将手指拉向手掌。您的外科医生通常可以通过检查您的手部来区分这些情况,而每种情况的治疗方法各不相同。
我们如何处理
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会从适合您病情的最微创方案入手。患者通常由全科医生转诊至我们的诊所;如果理疗师建议您就诊,您仍需获得全科医生的转诊才能符合 Medicare 报销资格。就诊时,我们会询问病史,检查您的手部,并在需要确认肿块性质时安排超声等影像学检查。
由于这种肿块是无害的,也不会持续增大,治疗完全取决于它对您造成多大困扰。如果您能摸到肿块,但在日常抓握时并不疼痛,可能根本不需要任何处理。如果某种特定的抓握动作反复引起疼痛,改变握持物品的方式或暂时减少该活动可能就足够了。手部治疗也可以帮助您找到对该处压力较小的用手方式。
用针头抽出肿块内的液体,称为抽吸,通常会在手术之前尝试。它可以排空囊内的液体,但由于囊袋由腱鞘供给液体,通常会再次充满。有些肿块也会随时间自行消退。我们会与您讨论在您的情况下是否值得尝试抽吸。
如果这些较简单的步骤未能让您得到足够的缓解,可以考虑手术。手术通过手指根部的一个小切口切除肿块,同时切除其起源处的一小段腱鞘,正是这样才能防止它复发。当您日常生活中某项特定的、反复进行的活动因疼痛而受到限制时,我们通常会建议手术,而且这个决定由我们与您共同做出。
如果您的手指、手部或手臂变得发热、发红、肿胀并疼痛,尤其是伴有发烧,请当天前往急诊科。
预期情况
大多数此类腱鞘囊肿是无害的,也不会持续增大。有些会随时间自行消退,有些则时有时无。如果您的肿块不痛,您可能根本不需要治疗。
如果肿块在您抓握时确实疼痛,一些简单的措施会有所帮助。用针头抽吸可以排空囊袋,但由于囊袋由腱鞘供给液体,通常会再次充满。在您等待观察它是否消退期间,改变握持物品的方式,或减少引发疼痛的活动,可能就足够了。
如果这些措施的帮助不够,手术会切除肿块以及其起源处的一小段腱鞘,正是这样才能防止它复发。大多数人发现,当该处不再被挤压后,抓握会感觉更舒适。与任何手部手术一样,手术也有需要权衡的风险,包括手指一侧出现一片麻木区域、僵硬、感染,以及疤痕增厚或有压痛。在您做决定之前,您的外科医生会与您详细讨论这些风险。
术后恢复需要数周而不是数天。起初您的手会疼痛,手指根部的小切口也需要一段时间才能愈合。术后手部治疗由 Extend Rehabilitation 的 Ruby Doolan 负责。Ruby 是一名手部治疗师:在您的手指愈合期间,她会指导您的锻炼,并为您制作所需的夹板。大多数人在数周内即可恢复日常的抓握活动,但疤痕处的压痛可能会持续稍长一些时间。
如果您的症状没有缓解、在数周内逐渐加重、使您在夜间痛醒,或使您无法工作或使用手部,请就诊于您的全科医生,或要求专科医生评估。
何时就医
手指根部的大多数肿块都是无害的腱鞘囊肿,但该部位还有其他一些情况看起来可能一样。手指弯曲时锁住或弹响,或手掌中有一条坚硬的索带将手指拉向手掌,这些情况您的外科医生可以通过检查您的手部加以区分。任何新出现的肿块都值得检查,这样您就能知道自己患的是哪一种。
如果肿块在抓握时疼痛、您注意到手指刺痛或麻木,或者手指出现卡住或弹响,请要求专科医生评估。如果您的症状没有缓解、在数周内逐渐加重、使您在夜间痛醒,或使您无法工作或使用手部,也请要求评估。
如果您的手指、手部或手臂变得发热、发红、肿胀并疼痛,尤其是伴有发烧,请当天前往急诊科。无需全科医生转诊。
深入探讨
Advanced reading: the deeper science (optional)
本节内容超出了您做出自身治疗决策所需的深度。屈肌腱鞘腱鞘囊肿值得额外阅读,因为它是手部外科中最小的肿块,却能可靠地引发不成比例的症状;并且,其附着部位决定了疼痛的原因以及简单治疗失败的原因。
豌豆大小且疼痛与体积不成比例的肿块
这些囊肿也称为腱鞘囊肿或掌侧腱鞘囊肿,起源于将屈肌腱固定在指骨上的纤维鞘[1]。它们位于手掌中手指的基部,通常直径仅几毫米,质地坚硬而非柔软。
其症状具有特征性,一旦解剖结构清晰便不言自明:在紧握坚硬且狭窄的物体(如方向盘、高尔夫球杆、自行车把手、购物袋提手)时出现疼痛。囊肿被夹在物体与下方的骨骼之间,由于鞘直接附着于指骨,缺乏软组织缓冲。
这就是为什么肿块大小与症状相关性极差的原因。手腕背侧较大的柔软肿胀可能无痛,而手指基部仅为其几分之一大小的病变却可能真正造成活动受限。
与其他所有腱鞘囊肿相同的规则
其生物学行为取决于其所连接的结构。囊肿起源于腱鞘,并由其充盈,这意味着其力学机制与腕部腱鞘囊肿及黏液囊肿相同:囊袋是问题的可见末端,而非源头。
因此,穿刺或抽吸仅针对肿胀,而非渗漏。单纯引流后复发常见,确定性治疗需切除囊肿及其起源的受累腱鞘部分。
为何该手术听起来较小但并非微不足道
切除术是通过手指基底部的小切口进行的短程手术,通常具有治愈性。该部位的两个解剖学事实使得谨慎操作至关重要。
指神经紧邻屈肌腱鞘走行,每侧各有一支,且在手指基底部,它们位置表浅,靠近正在被切除的中线结构。手指一侧边缘出现麻木斑块是此部位小型手术的一个已知风险。
其次,只能切除腱鞘的冗余部分。将肌腱固定在骨骼上的滑车是承重结构,失去关键的滑车会导致肌腱弓弦样脱离手指,从而削弱抓握力。因此,切除术被刻意限制在不执行该功能的腱鞘节段。
何时不予处理
由于该病变为良性且不会无限增大,治疗仅由症状驱动。若囊肿明显但日常抓握时不引起疼痛,则无需任何处理。若进行治疗,是因为特定且重复的活动受到损害,这比大多数情况下的指征更为明确,因为诱发症状的抓握动作通常易于患者识别。
指间关节和腕部的相关囊肿将在各自的页面中单独介绍;这三者共同的原则是,决定问题是否复发的因素是囊蒂,而非囊体。
参考文献
[1] Foret AL, Chhabra AB. 掌侧腱鞘囊肿(Volar retinacular ganglions)。J Hand Surg Am. 2012;37(3):566-7. https://doi.org/10.1016/j.jhsa.2011.05.013
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Epidemiology and Natural History
- Pediatric ganglions are more commonly found on the volar surface of the hand and wrist compared to adults [7].
- Pediatric ganglions more commonly have a tendon sheath origin compared to adults [7].
- Approximately 40% of wrist ganglion lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
Diagnosis
- Ultrasound is useful for assisting in the diagnosis of suspected flexor tendon sheath ganglions [1].
- Ultrasound is useful for determining whether patients with suspected flexor tendon sheath ganglions should undergo aspiration or surgical excision [1].
- Routine wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [21].
Non-Operative Management
- A nonsurgical approach to flexor tendon sheath ganglions is both cost-effective and successful [3].
- Most ganglions recur after aspiration [25].
- Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions given its low cost, lack of downtime, and low recurrence rate [5].
- No recurrences were observed after a second puncture in the cohort assessed for percutaneous puncture of flexor sheath ganglions [5].
Operative Management
- Surgical excision is a simple, safe, and effective method for treating a painful ganglion of the digital flexor tendon sheath [2].
- Surgical intervention for wrist ganglions has about a 10% recurrence rate [25].
- Surgical intervention for wrist ganglions leaves scars and has some risk for adverse events [25].
- Ultrasound-guided excision of flexor tendon sheath ganglion using a 2-mm portal under local anaesthesia was reliable and efficient without specific morbidity [4].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis and less soft tissue trauma [9].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy allows for the management of concomitant FCR tendon pathology [9].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy carries risks of recurrence and nerve or vessel injury [9].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the ganglion being distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [60].
Pediatric Management
- There is no consensus within the literature regarding the best management of pediatric wrist ganglia [22].
- No single treatment modality confers a particular advantage or disadvantage over another for pediatric wrist ganglia [22].
Anatomy & Pathophysiology
Flexor Tendon Sheath Anatomy
- The fibroosseous tunnel, or digital flexor sheath, extends distally from the metacarpal neck to the proximal aspect of the distal phalanx [75].
- The tendinous sheath consists of annular pulleys that provide mechanical stability and cruciate pulleys that provide flexibility [75].
- The A2 and A4 pulleys are situated over the middle portion of the proximal and middle phalanges, respectively [75].
- The A2 and A4 pulleys are the most essential in maintaining the mechanical advantage of the flexor tendons [75].
- The tenosynovium lining the fibroosseous tunnel supplies both nutrition and lubrication to the poorly vascularized flexor tendons [75].
- Within the sheath, tendon vascularity is supplied via the vincula system, specifically the vinculum longus and brevis [75].
- Anatomical studies have identified two annular and one oblique pulley in the thumb [91].
- A branch from the digital nerve enters the flexor tendon sheath at the same place as the transverse branch of the digital artery [8].
- The nerve branch entering the flexor tendon sheath supplies the nerve fibres found within the vinculum [8].
- The transverse branch of the digital artery enters the edge of the sheath to reach the area of the vinculum brevis [8].
Gliding Mechanisms and Biomechanics
- In narrow crowded areas, the gliding mechanism is assured by the synovial sheath, which allows a considerable amplitude of movement [76].
- Fibrous sheaths surrounding synovial sheaths keep the tendon close to the skeleton, particularly when the tendon crosses an articular angle [76].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [76].
- Each synovial sheath has a visceral and parietal component separated by a potential synovial cavity containing a very thin layer of synovial fluid [76].
- This synovial fluid constitutes the basic gliding and nutritional mechanism for the tendon [76].
- Diffusion is a significant nutrient pathway to the flexor tendon, supporting the importance of sheath closure at the time of tendon suture [36, 37].
- At half the total tendon excursion, the force required to flex the digit through half its range is always less than a third of the force required to flex the digit fully [46].
- The force required to fully flex the digit decreased with more extensive A1 pulley release, becoming significant when more than 50% of the pulley was released [97].
Pathophysiology of Triggering and Ganglions
- Triggering results from the loss of smooth gliding of a tendon within its tendon sheath [6].
- Inflammation of the synovium lining the tendon sheath interferes with the normal gliding mechanism [6].
- Interference with the gliding mechanism is especially troublesome at a point of change in direction of a tendon [6].
- Ganglions are defined as cystic swellings closely connected to joints or tendon sheaths which contain mucinous material [141].
- The etiology of ganglions is unknown [141].
- The articular (synovial) theory has gained worldwide acceptance as a scientifically proven explanation for the formation of intraneural ganglions [17].
- Triggering of the finger can occur secondary to a partial flexor tendon tear after closed direct injury [98].
Classification
- Volar wrist ganglions may arise from a variety of locations, unlike dorsal wrist ganglions which typically arise from a specific location at the dorsal margin of the scapholunate interosseous membrane [16].
- Approximately two thirds of anterior wrist ganglions reportedly arise from the radiocarpal joint [16].
- One third of anterior wrist ganglions reportedly arise from the scaphotrapezial joint [16].
- Ganglion cysts that arise from the flexor carpi radialis (FCR) sheath are often in a slightly more medial location, either just radial or palmar to the sheath [16].
- Ganglions arising from the FCR sheath are typically less mobile than ganglions arising from the wrist joint [16].
- Ganglions arising from the first extensor compartment tend to adhere to the sheath (extensor retinaculum) [16].
- Ganglions arising from the first extensor compartment tend to be quite firm and are less mobile [16].
- In children aged <10 years, ganglion cysts present on the volar aspect of the wrist [13].
- In patients aged >10 years, ganglions resemble those in the adult population and present on the dorsal aspect of the wrist [13].
Clinical Presentation
General Characteristics
- Ganglions are the most common cause of focal masses in the hand and foot [50].
- Ganglions commonly arise from the synovium of joints, tendon sheaths, or the epineurium of nerves [50].
- Ganglions are filled with synovial fluid that may become jelly-like over time [50].
- Most patients with intraneural ganglions present with a painless mass [17].
- Some patients with intraneural ganglions present with symptoms of nerve irritation or entrapment neuropathy [17].
- In many patients with intraneural ganglions, definitive diagnosis is made only at the time of surgery [17].
Volar Wrist and Hand
- Volar wrist ganglia tend to arise in the interval between the first extensor compartment and flexor carpi radialis (FCR) tendon sheath, just proximal to the wrist flexion crease [16].
- Volar wrist ganglia typically appear to be 1 to 2 cm in size but may be significantly larger at the time of surgical dissection [16].
- Patients with volar wrist ganglions often present with complaints of a mass that has been present for a number of months or years and is typically asymptomatic [16].
- Patients with volar wrist ganglions often note discomfort when the mass is "bumped" [16].
- Volar wrist ganglia are clinically compressible, slightly mobile, nontender, and visible when transilluminated [16].
- Volar wrist ganglia are nonpulsatile but are often intimate with the radial artery, which is palpable alongside the lesion [16].
- Approximately one third of anterior wrist ganglions reportedly arise from the scaphotrapezial joint [16].
- Ganglion cysts that arise from the FCR sheath are often in a slightly more medial location, either just radial or palmar to the sheath [16].
- Ganglion cysts arising from the FCR sheath are typically less mobile than ganglions arising from the wrist joint [16].
Pediatric Population
- In children aged <10 years, ganglion cysts are generally amenable to observation with spontaneous regression [13].
- Ganglions in pediatric populations most commonly affect the dorsal wrist [47].
- Ganglions in pediatric populations demonstrate a female predilection [47].
- Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist [52].
Diagnostic Imaging
- Ultrasound is useful for assisting in diagnosis and determining whether patients should undergo aspiration or surgical excision for suspected flexor tendon sheath ganglions [1].
- MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard [48].
- MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes [33].
- The use of the 3-dimensional FSE extended echo train MRI sequence, called cube, has revolutionized the visualization of intraneural ganglions and articular branches that connect them to the joint [17].
Investigations
Imaging Modalities
- The architecture and relationship of the FDS to FDP within the flexor sheath is accurately defined using a non-invasive imaging technique and the pulley system can be clearly imaged in cross-section [58].
- Sonography-guided wrist arthroscopy provides visualization of the ganglions and ganglion stalk, as well as of the arthroscopic shaver and adjacent structures such as nerves, vessels, and tendons to perform surgery safely [124].
- Sonography-assisted arthroscopy allows clear visualization of ganglia, vessels, nerves, and tendons, enabling safe guidance of the arthroscopic shaver to the lesion without blind resection [126].
Diagnostic Limitations and Utility
- The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [21].
- Radiologists are less likely to identify occult dorsal ganglion cysts on MRI if the cyst is smaller or if the requisition form does not mention a cyst [138].
Pathology and Histology
- In patients with the clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision of the ganglion cyst [27, 31].
Treatment
Non-Operative Management
- Ultrasound imaging assists in determining whether patients with suspected flexor tendon sheath ganglions should undergo aspiration or surgical excision [1].
- Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions due to its low cost, lack of downtime, and low recurrence rate [5].
- No recurrences were observed after a second percutaneous puncture in the cohort assessed for recurrence [5].
- Ganglion aspiration should be considered as a first-line intervention [55].
- Nonsurgical treatment is largely ineffective in treating ganglion cysts, though it may be considered for symptomatic relief in patients who do not want surgery [125].
- Aspiration, with or without cortisone injection, has an average success rate of 35% to 50% [122].
- Approximately 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
Operative Management
- Ultrasound-guided excision of flexor tendon sheath ganglions using a 2-mm portal under local anaesthesia was reliable and efficient without specific morbidity [4].
- Open surgical excision offers a significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions [135].
- Surgical intervention for ganglions has about a 10% recurrence rate [25].
- Surgical intervention for ganglions leaves scars and carries some risk for adverse events [25].
- In patients with a clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision [27, 31].
- Arthroscopic resection is an effective treatment strategy for intra-articular synovial ganglions refractory to conservative measures, providing complete resolution of symptoms and functional recovery with minimal soft tissue damage [119].
- Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia [120].
- Arthroscopic ganglionectomy is a safe and reliable alternative to open resection [140].
- At 12 months follow-up, the rates of recurrence with arthroscopic dorsal ganglion excision are comparable with and not superior to those of open excision [24].
- Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes [35].
- Recurrent ganglion cysts originating from the midcarpal joint are not contraindications for arthroscopic resection [38].
- Arthroscopy allows for the simultaneous treatment of ganglions and other pathologies [29].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis, less soft tissue trauma, and the ability to manage concomitant FCR tendon pathology [9].
- There was no impairment of wrist motion and function in all patients following arthroscopic resection of palmar ganglions [51].
- The key to successful open treatment of dorsal wrist ganglions is excision of the ganglion stalk based at the scapholunate ligament and its associated dorsal-capsular attachments [122].
- Open ganglionectomy creates a defect in the capsule of 1 to 1.5 cm, which is left open [122].
- Stiffness has been reported from prolonged immobilization following open ganglionectomy [122].
- The rate of recurrence for open ganglionectomy can be as high as 40% [122].
- Indications for surgery include pain, restricted motion, and/or aesthetic complaints as a result of the ganglion cyst [113].
- Ultrasound, magnetic resonance imaging, or X-rays are performed to confirm the presence of a ganglion cyst or to rule out other conditions when surgery is indicated [113].
- The operation for dorsal wrist ganglion excision is generally performed under regional anaesthesia and a tourniquet [113].
- A dorsal incision distal to Lister’s tubercle is used, with the extensor retinaculum between the tendons of the second and fourth extensor compartments incised [113].
- A small arthrotomy is performed over the scapholunate ligament, where the dorsal wrist ganglion usually originates [113].
- Complete excision of the ganglion along with its capsule is performed with local synovectomy [113].
- The capsule is either fenestrated or sutured, depending on the surgeon [113].
- A compressive dressing is applied after skin closure and left in place for 3 days [113].
- Active mobilization of the wrist starts after the hand therapist changes the dressing [113].
- Sutures are removed 10 to 14 days postoperatively [113].
- Splints are not used on a regular basis [113].
- Patients start with a stabilizing and strength programme under the guidance of the hand therapist after 3 weeks [113].
- In pediatric wrist ganglion excision, a transverse incision is made over the ganglion to expose the cyst's wall [123].
- Fluid is aspirated and 0.3e0.5 mL of methylene blue is injected into the cavity to facilitate dye penetration into the cyst wall [123].
- The base of the ganglion is ligated with a 4e0 absorbable suture [123].
- All blue-stained ganglion tissue is thoroughly resected [123].
- The wrist is immobilized with a plaster cast for 7 to 10 days following pediatric excision [123].
- Followup examinations occur monthly for 6 months and every 3 months thereafter [123].
- Recurrence is assessed within 48 months' follow-up by palpation alone [123].
- Patients undergoing initial pediatric excision had been treated conservatively for more than 1 year [123].
- Recurrence of the wrist ganglion cyst occurred in 9% of patients in a cohort of 53 arthroscopic resections [116].
- PRWE scores were significantly higher in patients with a recurrence (30 vs. 12, p = 0.002) [116].
- Patients initially presenting with a new ganglion cyst had fewer recurrences at final follow-up compared with patients initially presenting with recurrence (4 vs. 15%) [116].
- Asymptomatic ganglion cysts were left untreated in the arthroscopic cohort [116].
- One patient experienced neuropraxia of the radial superficial nerve, which resolved spontaneously [116].
- One patient developed extensor carpi ulnaris (ECU) tendinitis, which was successfully treated with splinting [116].
- One patient experienced painful scar tissue, which was successfully removed surgically [116].
Complications
- Surgical intervention for wrist ganglions carries a recurrence rate of approximately 10% [25].
- Surgical intervention for wrist ganglions leaves scars and carries some risk for adverse events [25].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the cyst, specifically when it is distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [60].
- Open surgical excision of pediatric wrist ganglions demonstrates minimal complications [13].
Recovery
Non-Operative Management
- No recurrences were observed after a second puncture in the cohort assessed for percutaneous puncture management [5].
- About 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
- In a child with a wrist ganglion, if the cyst ultimately resolved, it usually did so within 18 months [20].
Operative Management
- Surgical intervention has about a 10% recurrence rate [25].
- Surgical intervention leaves scars and has some risk for adverse events [25].
Key Evidence
- [L4] Ultrasound is useful for assisting in diagnosis and determining whether patients should undergo aspiration or surgical excision for suspected flexor tendon sheath ganglions. [1] (10.1016/s0363-5023(97)80043-3)
- [L4] Surgical excision is a simple, safe, and effective method for treating a painful ganglion of the digital flexor tendon sheath. [2] (10.1007/s11552-007-9028-4)
- [L4] A nonsurgical approach to flexor tendon sheath ganglions is both cost-effective and successful. [3] (10.1053/jhsu.2002.34318)
- [L4] The ultrasound-guided excision of flexor tendon sheath ganglion, using a 2-mm portal, under local anaesthesia was reliable and efficient, without specific morbidity. [4] (10.1016/j.hansur.2018.10.116)
- [L4] Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions given its low cost, lack of downtime, and low recurrence rate, with no recurrences observed after a second puncture in this cohort. [5] (10.1177/17531934221115983)
- [L5] [6] (10.1016/0266-7681(94)90139-2)
- [L4] Pediatric ganglions are more commonly found on the volar surface of the hand and wrist and more commonly have tendon sheath origin compared to adults. [7] (10.1007/s11552-008-9122-2)
- [L5] [8] (10.1016/0266-7681(91)90138-e)
- [Paper] Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis, less soft tissue trauma, and the ability to manage concomitant FCR tendon pathology, though it carries risks of recurrence and nerve or vessel injury. [9] (10.1016/j.eats.2017.06.002)
- [L4] [13] (10.1016/j.jhsa.2021.12.015)
- [L5] [16] (10.1016/j.hcl.2004.03.015)
- [L4] [17] (10.1016/j.jhsa.2015.05.025)
- [L4] In a child with a wrist ganglion, if the cyst ultimately resolved, it usually did so within 18 months. [20] (10.1016/j.jhsa.2019.10.032)
- [L4] The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings. [21] (10.1007/s11552-007-9032-8)
- [L4] There is no consensus within the literature regarding the best management of pediatric wrist ganglia, and no single treatment modality confers a particular advantage or disadvantage over another. [22] (10.1177/1558944720966716)
- [L1] At 12 months follow-up, the rates of recurrence with arthroscopic dorsal ganglion excision are comparable with and not superior to those of open excision. [24] (10.1016/j.jhsa.2008.01.009)
- [L5] Current best evidence suggests that about 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon, that most ganglions recur after aspiration, and that surgical intervention has about a 10% recurrence rate, leaves scars, and has some risk for adverse events. [25] (10.1016/j.jhsa.2010.11.048)
- [L3] This study suggests that, in patients with the clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision of the ganglion cyst. [27] (10.1016/j.jhsa.2010.03.021)
- [L4] Arthroscopy allows for the simultaneous treatment of ganglions and other pathologies. [29] (10.1016/j.jhsa.2012.04.042)
- [L4] In patients with the clinical diagnosis of wrist ganglion cyst, the quality of care would not be compromised by abandoning the practice of routine submission of surgical specimens for pathological examination after excision of the ganglion cyst. [31] (10.1016/s0363-5023(10)60107-4)
- [L4] MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes. [33] (10.1007/s11552-007-9083-x)
- [L3] Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes. [35] (10.1177/17531934251405730)
- [L5] The importance of sheath closure at the time of tendon suture is based in part on the evidence that diffusion is a significant nutrient pathway to the flexor tendon. [36] (10.1016/0266-7681(88)90077-0)
- [L5] The importance of sheath closure at the time of tendon suture is based in part on the evidence that diffusion is a significant nutrient pathway to the flexor tendon. [37] (10.1016/0266-7681_88_90077-0)
- [L4] Ganglion cysts also have a high association with certain interosseous laxities, and recurrent ganglion cysts originating from the midcarpal joint are not contraindications for arthroscopic resection. [38] (10.1016/j.jhsa.2008.11.025)
- [L5] At half the total tendon excursion, the force required to flex the digit through half its range is always less than a third of the force required to flex the digit fully. [46] (10.1016/0266-7681(90)90086-j)
- [L2] Ganglions in pediatric populations, which most commonly affect the dorsal wrist, demonstrate a female predilection. [47] (10.1016/j.jhsa.2021.02.026)
- [L3] MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard. [48] (10.1177/1753193408092041)
- [Case_report] [50] (10.1007/s12593-014-0117-7)
- [L4] There was no impairment of wrist motion and function in all patients. [51] (10.1016/j.main.2006.07.028)
- [L4] Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist. [52] (10.1016/j.jhsa.2023.07.002)
- [L4] Ganglion aspiration should be considered as a first-line intervention, with surgical excision remaining an effective option for symptomatic cases. [55] (10.1177/1753193411434376)
- [L5] The architecture and relationship of the FDS to FDP within the flexor sheath is accurately defined using a non-invasive imaging technique and the pulley system can be clearly imaged in cross-section. [58] (10.1016/j.jhsb.2005.08.001)
- [L3] The operation-related complications after arthroscopic volar wrist ganglionectomy are associated with its anatomical location: distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer. [60] (10.1186/s12891-025-08766-x)
- [L5] Anatomical studies have identified two annular and one oblique pulley in the thumb. [91] (10.1016/s0363-5023(77)80101-9)
- [L5] The force required to fully flex the digit decreased with more extensive A1 pulley release, becoming significant when more than 50% of the pulley was released. [97] (10.1016/s0266-7681(98)80217-9)
- [L5] This illustrates another post-traumatic mechanical cause for triggering of the finger. [98] (10.1016/0363-5023(93)90059-c)
- [L2] [113] (10.1177/17531934231153029)
- [L4] [116] (10.1055/s-0040-1716509)
- [L4] Arthroscopic resection is an effective treatment strategy for intra-articular synovial ganglions refractory to conservative measures, providing complete resolution of symptoms and functional recovery with minimal soft tissue damage. [119] (10.1016/j.jhsg.2024.05.007)
- [L4] Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia. [120] (10.1016/j.arthro.2009.08.021)
- [L4] [122] (10.1016/s0749-0712(21)00020-2)
- [L2] [123] (10.1016/j.jhsa.2015.01.015)
- [L4] Sonography-guided wrist arthroscopy provides several advantages for surgeons, including visualization of the ganglions and ganglion stalk, as well as of the arthroscopic shaver and adjacent structures such as nerves, vessels, and tendons to perform surgery safely. [124] (10.1016/j.jhsa.2012.04.012)
- [L4] Nonsurgical treatment is largely ineffective in treating ganglion cysts, though it may be considered for symptomatic relief in patients who do not want surgery. [125] (10.1155/2013/940615)
- [Paper] Sonography-assisted arthroscopy allows clear visualization of ganglia, vessels, nerves, and tendons, enabling safe guidance of the arthroscopic shaver to the lesion without blind resection. [126] (10.1016/j.eats.2011.12.007)
- [L1] Open surgical excision offers significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions. [135] (10.1016/j.jhsa.2014.12.014)
- [L3] Radiologists are less likely to identify occult dorsal ganglion cysts on MRI if the cyst is smaller or if the requisition form does not mention a cyst. [138] (10.1055/s-0039-1683847)
- [L4] Arthroscopic ganglionectomy is a safe and reliable alternative to open resection. [140] (10.1016/j.jhsa.2003.10.018)
- [L4] [141] (10.2106/00004623-197254070-00009)
References
[1] Treatment of flexor tendon sheath ganglions using ultrasound imaging. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80043-3
[2] Flexor Tendon Sheath Ganglions: Results of Surgical Excision. HAND. 2007. DOI: 10.1007/s11552-007-9028-4
[3] Management of flexor tendon sheath ganglions: A cost analysis. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.34318
[4] Flexor tendon sheath ganglions — A new procedure to perform excision under ultrasound-guidance. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.116
[5] Percutaneous puncture of flexor sheath ganglions: an assessment of recurrence. Journal of Hand Surgery (European Volume). 2022. DOI: 10.1177/17531934221115983
[6] Extensor Tendon Sheath Stenosis Resulting in Triggering of the Little Finger. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90139-2
[7] Pediatric Ganglion Cysts of the Hand and Wrist: An Epidemiologic Analysis. HAND. 2008. DOI: 10.1007/s11552-008-9122-2
[8] Anatomical Demonstration of the Nerve-Supply to the Flexor Tendon. Journal of Hand Surgery. 1991. DOI: 10.1016/0266-7681(91)90138-e
[9] Endoscopic Ganglionectomy of Palmar Ganglion via Flexor Carpi Radialis Tendoscopy. Arthroscopy Techniques. 2017. DOI: 10.1016/j.eats.2017.06.002
[13] Pediatric Ganglions of the Hand and Wrist: A Review of Current Literature. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.12.015
[16] Ganglion cysts and other tumor related conditions of the hand and wrist. Hand Clinics. 2004. DOI: 10.1016/j.hcl.2004.03.015
[17] Intraneural Ganglions of the Hand and Wrist. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.05.025
[20] Wrist Ganglia in Children: Nonsurgical Versus Surgical Treatment. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.10.032
[21] The Use of Routine Wrist Radiography is Not Useful in the Evaluation of Patients with a Ganglion Cyst of the Wrist. HAND. 2007. DOI: 10.1007/s11552-007-9032-8
[22] Wrist Ganglion Cysts in Children: An Update and Review of the Literature. HAND. 2022. DOI: 10.1177/1558944720966716
[24] Arthroscopic Versus Open Dorsal Ganglion Excision: A Prospective, Randomized Comparison of Rates of Recurrence and of Residual Pain. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.01.009
[25] Wrist Ganglions. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2010.11.048
[27] Necessity of Routine Pathological Examination After Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.03.021
[29] Ganglions of the Wrist and Associated Triangular Fibrocartilage Lesions: A Prospective Study in Arthroscopically-treated Patients. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.04.042
[31] Necessity of Routine Pathological Examination following Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/s0363-5023(10)60107-4
[33] Compression Neuropathy of the Radial Nerve Due to Ganglion Cysts. HAND. 2008. DOI: 10.1007/s11552-007-9083-x
[35] Arthroscopic resection of dorsal wrist ganglions with or without midcarpal exploration. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251405730
[36] Flexor tendon healing. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90077-0
[37] Flexor Tendon Healing. Journal of Hand Surgery. 1988. DOI: 10.1016/0266-7681_88_90077-0
[38] Prospective Outcomes and Associations of Wrist Ganglion Cysts Resected Arthroscopically. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.11.025
[46] The Mechanical Effect of Partial Resection of the Digital Fibrous Flexor Sheath. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681(90)90086-j
[47] Clinical Presentation and Characteristics of Hand and Wrist Ganglion Cysts in Children. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.02.026
[48] Magnetic Resonance Imaging in the Diagnosis of Occult Dorsal Wrist Ganglions. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408092041
[50] Intraneural Ganglion of Digital Nerve of Thumb: A Case Report and Review of Literature. Journal of Hand and Microsurgery. 2015. DOI: 10.1007/s12593-014-0117-7
[51] Résection des kystes synoviaux palmaires par arthroscopie. Chirurgie de la Main. 2006. DOI: 10.1016/j.main.2006.07.028
[52] Natural History of Pediatric Hand and Wrist Ganglion Cysts: Longitudinal Follow-Up of a Prospective, Dual-Center Cohort. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.002
[55] Patient outcomes following wrist ganglion excision surgery. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193411434376
[58] Mri ‘Magic Angle’ Imaging of Finger Tendons. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.08.001
[60] Anatomical location of volar wrist ganglion in preoperative MRI is a risk factor for operation-related complications after arthroscopic ganglionectomy. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08766-x
[75] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[76] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.
[91] Anatomy of the flexor tendon sheath and pulleys of the thumb. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80101-9
[97] The Effect of the Extent of A1 Pulley Release on the Force Required to Flex the Digits. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80217-9
[98] Triggering of the finger secondary to partial flexor tendon tear after closed direct injury. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90059-c
[113] Factors associated with self-reported pain and hand function following dorsal wrist ganglion excision. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231153029
[116] Patient-Related Outcomes of Arthroscopic Resection of Ganglion Cysts of the Wrist. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1716509
[119] Intra-articular Synovial Ganglion of the Wrist. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.05.007
[120] Arthroscopic Ganglionectomy Through an Intrafocal Cystic Portal for Wrist Ganglia. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.08.021
[122] ARTHROSCOPIC RESECTION OF DORSAL GANGLION OF THE WRIST. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00020-2
[123] Visualization of the Wrist Ganglion Capsule by Methylene Blue Staining as an Aid for Complete Resection in Children. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.01.015
[124] Sonography-guided Arthroscopy for Wrist Ganglion. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.04.012
[125] Treatment of Ganglion Cysts. ISRN Orthopedics. 2013. DOI: 10.1155/2013/940615
[126] Sonography‐Assisted Arthroscopic Resection of Volar Wrist Ganglia: A New Technique. Arthroscopy Techniques. 2012. DOI: 10.1016/j.eats.2011.12.007
[135] Wrist Ganglion Treatment: Systematic Review and Meta-Analysis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.014
[138] Radiologist Identification of Occult Dorsal Wrist Ganglion Cysts on MRI. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1683847
[140] Arthroscopic resection in the management of dorsal wrist ganglions: results with a minimum 2-year follow-up period. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.10.018
[141] Ganglions of the Wrist and Hand. The Journal of Bone & Joint Surgery. 1972. DOI: 10.2106/00004623-197254070-00009