Patients › Hand
手部肌腱和神经损伤
Hand tendon and nerve injuries – understanding symptoms, diagnosis, and treatment options.
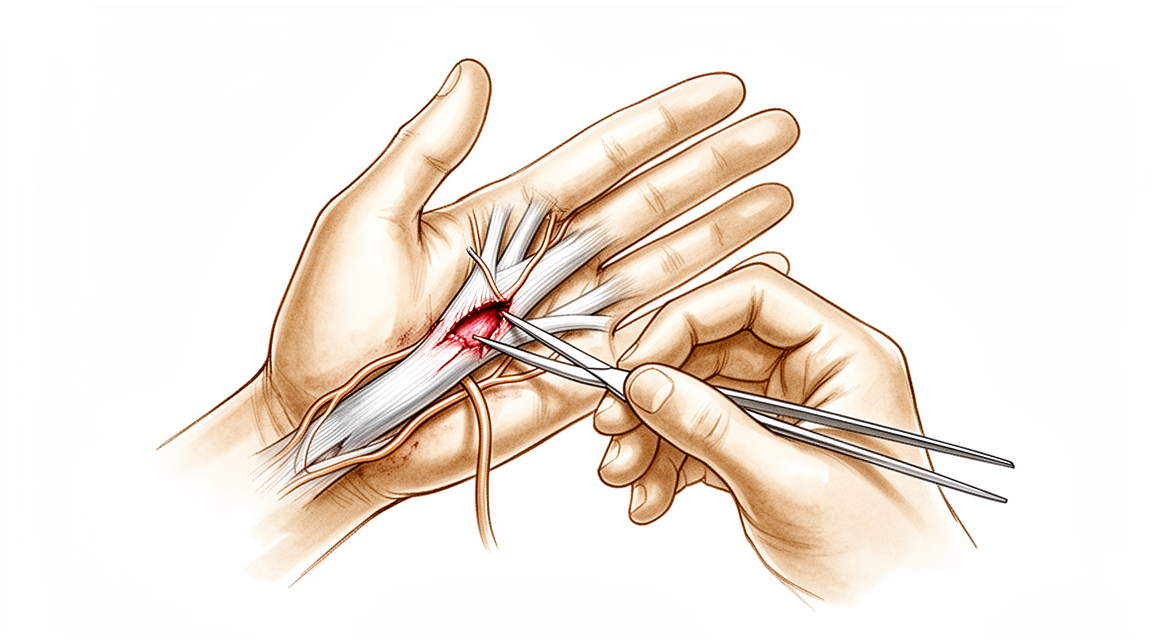
您的感受
当您手部的肌腱或神经被切断时,造成的影响取决于受伤的是哪一条以及受伤的位置。肌腱被切断通常意味着您无法像平常那样弯曲或伸直一根或多根手指。神经被切断会使其支配的区域出现麻木或针刺感,当您轻叩受伤部位时,可能会感到一阵麻刺感或类似电击的感觉。这种叩击时的感觉可能是神经开始恢复的迹象。
疼痛通常就在伤口处,当您尝试使用手部时往往会加剧:抓握、捏取、提购物袋、转动钥匙或扣纽扣。许多人发现手部在夜间或醒来时更加酸痛。让手部休息并保持静止通常能使疼痛缓解,而活动和负重会使疼痛加重。如果肌腱只是被部分切断,手指起初可能仍能活动,但之后会出现卡顿、弹响或使不上力。
需要指尖感觉的日常事务会变得困难:捡起硬币等小物件、扣纽扣或拉拉链、握笔、使用餐具,或感知水是否烫。您可能会在不知不觉中掉落东西,因为手部无法告诉您抓握的力度有多大。如果损伤除了肌腱或神经之外还伴有骨折,无力和麻木往往更为严重。
有些警示征象需要紧急处理。如果您的手指、手或手臂变得发烫、发红、肿胀且疼痛,尤其是伴有发烧时,或者您的手指或手变得苍白、冰冷、发白或发青,或者在受伤后突然失去感觉或活动能力,请当天前往急诊科。如果症状没有缓解、在数周内逐渐加重、在夜间使您痛醒,或使您无法工作或使用手部,请去看全科医生或要求专科医生评估。
实际发生了什么
您的手部由 27 块小骨头构成,排列成五条指列。每条指列都是一串一起弯曲和伸直的骨头。带动手指活动的肌肉一部分位于前臂,一部分位于手部内部,它们通过称为肌腱的索状结构牵拉手指。可以把肌腱想象成在光滑隧道内穿行的一根绳索。每根手指的掌侧有两根这样的绳索:一根弯曲中间的关节,另一根一直延伸到指尖,弯曲末端的关节。在手背,另外一些肌腱负责伸直手指。
当您割伤手部时,其中一根绳索可能被完全切断或部分切断。肌腱被完全切断,意味着牵拉它的肌肉失去了与手指的连接,因此这根手指无法自主弯曲或伸直。部分切断的肌腱起初可能仍能发挥作用,这就是为什么手指在开始出现卡顿或使不上力之前,看起来可能一切正常。肌腱在那些光滑的隧道内滑动,因此修复后的肌腱在愈合后既要足够牢固、能够承受拉力,又要能够顺畅滑动。
神经就像电线。它们将指尖的感觉传回大脑,并将指令传递到肌肉。神经被切断会使这一回路中断,这就是其支配区域出现麻木、麻刺感或类似电击感觉的原因。与肌腱不同,神经无法简单地缝合后就立即恢复功能。神经必须沿其外层神经鞘重新生长,速度大约为每天一毫米,因此感觉会在数月内缓慢恢复,而且在变得有用之前,常常先表现为令人不适的过度敏感。
如果损伤同时伴有骨折,就会同时影响不止一种结构,无力和麻木往往也会更严重。
我们如何处理
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会根据您的具体损伤情况制定治疗方案。有些手部肌腱和神经损伤无需手术即可愈合,而另一些则需要在受伤后尽快手术,因此及时评估很重要。患者通常由其全科医生(GP)转诊至我们的诊所;如果理疗师建议您就诊,您仍需获得全科医生的转诊,才有资格享受 Medicare(澳大利亚公共医疗保险)报销。在诊所,我们会仔细采集病史并检查您的手部,并在需要时安排影像学检查或神经检查。这些检查可以显示神经或肌腱受伤的严重程度,并帮助我们决定治疗方案。
并非每一种损伤都需要手术。如果神经是挫伤而非切断,我们可能只是在它自行恢复期间进行观察。如果观察 6 周后仍没有肌肉重新开始工作的迹象,或者无力持续加重,我们会建议直接探查神经。在神经或肌腱愈合期间,使手部保持静止的器具(例如支具或石膏)可以保护修复部位。术后,您的康复采用的是手部治疗,而非物理治疗:Extend Rehabilitation 的 Ruby Doolan 会指导您进行锻炼,并为您制作所需的任何支具。
当需要手术时,目标是恢复被切断结构原本的功能:将肌腱重新缝合,使手指能够再次弯曲或伸直;将切断的神经接合,使感觉能够重新生长。如果两个神经断端无法在不牵拉的情况下对合,我们可能会用移植物或一段小导管来桥接缺损,或者在某些情况下,将一条功能正常的神经改道,去承担更有用的功能。如果神经损伤使某块肌肉永久无力,可以将一条肌腱从它可以让出的功能上移开,去接替那块肌肉的工作。有时我们会在同一次手术中修复神经并转移肌腱。对于神经愈合不良处形成的疼痛肿块,手术的主要目标是缓解疼痛,其次是恢复感觉。
预期情况
恢复情况取决于受伤的是哪种结构以及损伤的严重程度。仍保持完整的挫伤神经,通常比被切断后修复的神经恢复得更好。修复后的肌腱通常能够愈合,手指也能重新活动,但修复处在术后几周、手指开始感觉好转时最为脆弱,因此在愈合期间需要保护手部。
无论修复做得多好,神经的恢复都很缓慢。感觉大约以每天一毫米的速度恢复,因此在手腕处切断的神经可能需要许多个月才能恢复,而且在变得有用之前,感觉常常先以令人不适的过度敏感的形式出现。有些因素会使恢复的可能性更大:尽早而非延迟修复神经、神经断端之间的缺损较短,以及年纪较轻。修复延迟少于 6 个月和缺损小于 5 cm 都与更好的恢复相关。即便如此,并非每一条修复的神经都能恢复正常。只有 24% 的修复后指神经能恢复到接近或等同于受伤前水平的感觉,因此部分感觉变化可能是永久性的。
肌腱修复也有其自身需要权衡的风险。约 6% 的屈肌腱修复需要再次手术,最常见的原因是瘢痕组织将肌腱粘连、使其无法滑动,或者修复处被拉开。修复处被拉开的情况约占 4%。当神经损伤使某块肌肉永久无力时,肌腱转位术可以恢复有用的活动;当单靠神经修复无法恢复功能时,这是一个成熟可靠的选择。
如果对损伤置之不理,会发生什么取决于受伤的结构。完全切断的肌腱不会自行愈合,因此那根手指会一直无法弯曲或伸直。切断的神经也无法跨越缺损重新生长,麻木会持续存在。与在受伤后不久进行修复相比,延迟治疗通常效果较差,不过即使拖延很久,仍有可能获得良好的结果。
如果症状没有缓解或在数周内逐渐加重,请去看全科医生或要求专科医生评估。
何时就医
破皮的手部损伤需要及时检查,因为切断的肌腱或神经不会自行愈合。如果您的手指、手或手臂变得发烫、发红、肿胀且疼痛,尤其是伴有发烧时;如果您的手指或手变得苍白、冰冷、发白或发青;如果您在受伤后突然失去感觉或活动能力;或者如果骨折或关节上方的皮肤破损、骨头外露,或手指明显变形,请当天前往急诊科。如果起初看似正常的手指开始出现卡顿、弹响或使不上力(肌腱只被部分切断时可能出现这种情况),请要求专科医生评估。如果疼痛严重,您无法让手部保持足够静止以接受检查,请去看全科医生,因为扫描可以确定肌腱是否完好。
深入探讨
Advanced reading: the deeper science (optional)
本节内容超出了您自身治疗决策所需的范围。手部肌腱和神经修复值得额外阅读,因为手术仅是治疗的一部分,术后数周内的恢复过程对最终结果的影响与修复手术本身同等重要,且相关证据已变得非常具体。
早期活动优于保护
屈肌腱修复术后,存在两种相互竞争的情况:活动手指可能导致修复处断裂;保持静止则会使肌腱与腱鞘发生瘢痕粘连,导致肌腱虽愈合完整但无法滑动,最终形成一根内部肌腱已愈合但手指僵硬的状态。
在 569 例患者中,早期主动活动组的总主动活动度优于早期被动活动组。限定条件与发现本身同样重要:在使用仅 2 股核心缝线 进行修复的主动屈伸亚组中,观察到 更高的断裂风险 [1]。
这正是精确陈述的权衡。早期主动活动能带来更好的最终活动度,但它要求修复强度足以承受这种活动。这就是为什么修复处跨越的缝线股数值得讨论,这并非单纯的技术细节,而是决定能否采用更安全、更优康复方案的关键因素。
相对运动法及其证据的实际适用范围
相对运动夹板将受伤手指固定在与邻近手指略有不同的对位中,从而为修复部位卸载应力,同时允许手部活动。与将手部固定六周相比,其在耐受性方面是一项显著进步。
证据基础并不均衡,准确了解这一点至关重要。目前已有充分证据表明,相对运动法在 V-VI 区伸肌腱修复中是安全的,但对于 IV 区和 VII 区伸肌腱以及屈肌腱修复的证据有限 [2]。
因此,尽管该方案在手背伸肌腱修复中得到了充分支持,但根据现有证据,其在手指屈肌腱修复中的应用尚未得到同等程度的确立。若在此处使用,属于合理的推断,而非已证实的临床实践。
对于神经而言,技术的重要性不如间隙
指神经修复采用了多种技术,包括直接缝合、取自其他部位的自体神经移植、经处理的同种异体神经移植以及人工导管。
在625例修复中,所有可用技术均具有合理的疗效,且当存在间隙时,排除直接修复,自体移植与同种异体移植的疗效相当 [3]。
因此,决定性变量是神经断端能否在无张力状态下对接。如果可以,则进行直接修复。如果不可以,则必须桥接间隙,而目前的证据并不强制要求从患者身体其他部位取神经来完成此操作,这避免了供区损伤及其伴随的麻木区域。
为何恢复期以月计
两种组织的愈合均遵循生物时间表,任何技术手段都无法缩短这一过程。修复后的肌腱在术后三周左右最为脆弱,此时初始的纤维蛋白已被吸收,而新的胶原尚未成熟,这恰恰是手指感觉好转、人们最倾向于使用手指的时期。
神经通过轴突沿残留的神经鞘生长来再生,速度大约为每天一毫米。因此,从手指基部的切断处到指尖需要数月时间,感觉的恢复是渐进且不完整的,通常先表现为令人不适的超敏状态,之后才转变为有用的感觉。这一过程属于预期的恢复过程,而非并发症。
参考文献
[1] Xu H, Huang X, Guo Z, Zhou H, Jin H, Huang X. Outcome of surgical repair and rehabilitation of flexor tendon injuries in zone II of the hand: systematic review and meta-analysis. J Hand Surg Am. 2023;48(4):407.e1-407.e11. https://doi.org/10.1016/j.jhsa.2021.11.013
[2] Shaw AV, Verma Y, Tucker S, Jain A, Furniss D. Relative motion orthoses for early active motion after finger extensor and flexor tendon repairs: a systematic review. J Hand Ther. 2023;36(2):332-46. https://doi.org/10.1016/j.jht.2023.02.011
[3] Herman ZJ, Ilyas AM. Sensory outcomes in digital nerve repair techniques: an updated meta-analysis and systematic review. Hand (N Y). 2019;15(2):157-64. https://doi.org/10.1177/1558944719844346
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Preoperative Assessment and Diagnosis
- Factors that interfere with the examination of nerves in the hand include other injuries that may be life threatening or limb threatening, patient intoxication, anxiety or lack of cooperation of the patient, and an extensive injury to the hand [9].
- If conditions are not satisfactory for a thorough examination during the initial evaluation, the hand should be reexamined within a reasonable period to determine the extent of nerve and other injuries sustained [9].
- If a flexor tendon function deficit is present after a finger laceration, at least one digital nerve probably has been injured as well [9].
- At least four areas of consideration are important when evaluating a patient with an injury to a nerve in the hand: (1) type of injury, (2) sensibility evaluation, (3) motor function, and (4) sudomotor function (sweating) [9].
- The Seddon classification of nerve injury includes Neurapraxia, Axonotmesis, and Neurotmesis [9].
- The Sunderland classification of nerve injury includes degrees I through VI, with degree VI being a combination of any of Sunderland I–V [9].
- Magnetic resonance neurography (MRA) is reported to be able to provide details regarding nerve anatomic relationships, fascicular pattern, intraneural swelling, and evaluation of downstream muscle injury [9].
- Customary methods used to evaluate damaged sensory nerves include the use of a sharp pin to assess pain, a cotton-tipped applicator or a finger eraser to assess light touch, and the tips of a paper clip or commercially prepared tool to assess two-point discrimination [9].
- Normal two-point discrimination usually is 6 mm or less [9].
- If the nerve is transected, a patient would not feel light touch, would not appreciate the pin as a sharp stimulus, and would be unable to discriminate between one and two points [9].
- Patients with closed injuries or partial injuries to nerves may show spotty appreciation of light touch and pain and have markedly widened two-point discrimination [9].
Anatomy and Surgical Considerations
- It is of paramount importance to respect and preserve the sensibility of the skin of the fingers and to avoid placing incisions in regions where pressure is commonly applied [67].
- In the palm, the nerves are protected by the overlying aponeurosis, but on the dorsum and palmar aspects of the wrist, and on the dorsum of the hand and fingers, the nerves are superficial and very much at risk if an incision is made without due care [67].
- The palmar cutaneous branch of the median nerve is the sensory nerve most susceptible to iatrogenic injury [67].
- The diameter of the palmar cutaneous branch of the median nerve is about 0.8 mm [67].
- The palmar cutaneous branch of the median nerve originates on the radial border of the median nerve 5 to 6 cm above the distal transverse flexion crease of the wrist [67].
- The palmar cutaneous branch of the median nerve courses alongside the median nerve for 2–3 cm [67].
- The palmar cutaneous branch of the median nerve follows the course of the flexor carpi radialis tendon and passes between the two layers of the forearm fascia, which provide it with its own short tunnel just ulnar to the flexor carpi radialis tendon [67].
- The palmar cutaneous branch of the median nerve passes through the superficial layer of the forearm fascia at the bifurcation of the palmaris longus into the root of the palmar aponeurosis and the tendon giving origin to the superficial portion of the abductor pollicis brevis [67].
- After only 5–10 mm, the palmar cutaneous branch of the median nerve divides into three terminal branches, which cross the mid-palmar aponeurosis to supply the deep layers of the dermis [67].
- To avoid the palmar cutaneous branch of the median nerve and its branches, which constitute the most frequent source of palmar neuromas, the forearm incision must be ulnar to the palmaris longus tendon [67].
- The main branch of the palmar cutaneous branches of the ulnar nerve arises from the cutaneous branch of the ulnar nerve, originating in the forearm a few centimeters above the origin of the dorsal branch [67].
- The cutaneous branch of the ulnar nerve runs against the palmar aspect of the nerve up to the level of the wrist, where it becomes superficial, crossing into the hypothenar eminence palmar to the palmaris brevis muscle [67].
- In 16 of 21 cases, the palmar cutaneous branch of the ulnar nerve was replaced by branches from the superficial division of the ulnar nerve or from its dorsal division [67].
- The dorsal branch of the ulnar nerve arises from the medial aspect of the ulnar nerve at an average distance of 6.4 cm from the distal aspect of the head of the ulna and 8.3 cm from the proximal border of the pisiform [67].
- The dorsal branch of the ulnar nerve passes dorsal to the flexor carpi ulnaris and pierces the deep fascia [67].
- The dorsal branch of the ulnar nerve becomes subcutaneous on the medial aspect of the forearm at a mean distance of 5 cm from the proximal edge of the pisiform [67].
- Proximal to the wrist, the dorsal branch of the ulnar nerve provides two to three branches [67].
- With the forearm supinated, the dorsal branches of the ulnar nerve pass along the medial aspect of the head of the ulna, then on the dorsal aspect of the triquetrum [67].
- With the forearm pronated, the dorsal branches of the ulnar nerve displace slightly ulnarly [67].
- The terminal sensory branch of the radial nerve passes deep to the flattened tendon of the brachioradialis and becomes superficial about 4 cm proximal to the radiocarpal joint line [67].
- The terminal sensory branch of the radial nerve crosses superficially, from radial to ulnar, the tendons of the abductor pollicis longus and extensor pollicis brevis [67].
- The terminal sensory branch of the radial nerve divides into a lateral branch, the dorsal collateral lateral of the thumb, and a medial branch that supplies the index and middle fingers [67].
- The course of the terminal sensory branch of the radial nerve is along a line drawn from the dorsolateral border of the radius toward the angle formed by the proximal junction of the first and second metacarpals [67].
- The medial branch of the terminal sensory branch of the radial nerve follows this line and divides just distal to the angle of the first and second metacarpals [67].
- The dorsal collateral nerve of the thumb follows the radial border of the extensor pollicis brevis tendon [67].
- The dorsal collateral nerve of the thumb gives the palmar cutaneous branch of the radial nerve, which follows the tendon of the abductor pollicis longus and anastomoses with or substitutes for the external branch of the palmar cutaneous branch of the median nerve [67].
- An injury to the median nerve of a hand with unusual anatomic variation of palmar sensory branches of the ulnar nerve would not experience sensory impairment of the ulnar halves of the index and middle and the radial half of the ring fingers [1].
Treatment and Outcomes
- The one-stage procedure of combined nerve repair and two-tendon transfer permits early and useful function of the hand, due to the action of the transferred tendons [2, 3].
- Tendon or tissue transfers in combined nerve palsies require longer follow-up than isolated nerve palsies to make a valid assessment of the outcome [4].
- Nerve transfers are an option for restoring hand and forearm function in patients with peripheral nerve injuries adversely affecting their ability to function [5].
- End to end nerve repair was performed in 10% of cases and 35% had excellent results in brachial plexus injury in war victims [6].
- If not corrected, secondary defects of the hand with intrinsic paralysis may compromise normal function of the hand when either nerve function recovers or tendon transfers have been performed to correct the primary functional defects [7].
- Despite the use of microsurgical techniques, outcome after median and ulnar nerve repair is suboptimal [10].
- The conservation of amputated finger-tips provides the hand surgeon with new possibilities for late reconstruction of an injured digit [13].
- The biomechanical principles, indications and limitations of tendon transfers, nerve transfers and combined approaches are compared, with particular attention to timing, patient selection, and functional goals [17].
- In lower-type injuries of the brachial plexus, transfer of median nerve branches that innervate the palm of the hand to the ulnar proper digital nerve of the little finger predictably restored protective sensation on the ulnar side of the hand [21].
- Hand therapists are going to be needed for a long time-certainly as long as tendon and nerve repairs are immobilized 3 weeks and fractures are immobilized 6 weeks [22].
- Nerve transfer is favored over nerve grafting in managing high ulnar nerve injuries because of better improvement of motor power and better restoration of grip functions of the hand [26].
- Experimental studies and positive reports from large clinical series suggest that new techniques using foreign nerves for reinnervation are worthy of integration into the management of upper brachial plexus injuries, though many questions regarding timing, donor morbidity, and comparative efficacy remain unanswered [27].
- More homogeneous follow-up protocols are needed for strength measurement and patient-reported outcome measures for both nerve and tendon transfers [30].
- The authors prefer specific nerve transfers for motor and sensory restoration, noting that median nerve repair is mandatory for patients with concomitant pain in high median nerve injury [33].
- End-to-side distal anterior interosseous nerve transfer in treatment of proximal ulnar nerve injuries provides significantly better results than a standard more proximal nerve repair [41].
- Nerve transfers provide significantly better treatment options in many cases of nerve injury where previous outcomes were expected to be poor, such as with proximal injuries, long nerve gaps, or unavailability of the proximal injured segment [43].
- Vascularized ulnar nerve graft technique should be recommended for reconstruction of the median or radial nerves in selected cases after severe trauma of the upper extremity [44].
- Nerve transfer to the median nerve using parts of the ulnar and radial nerves may offer an alternative option for proximal nerve injuries or for free functioning muscle transplantations [66].
- Tendon transfers remain the primary reconstructive procedure for paralytic injuries of the upper limb until sufficiently powered studies of nerve transfer outcomes are published [141].
Anatomy & Pathophysiology
Skeletal Architecture and Kinematics
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [48].
- The hand skeleton is divided into five rays, each forming a polyarticulated chain comprising metacarpals and phalanges [48].
- The thumb ray is the shortest, consisting of a metacarpal and two phalanges, and is more mobile than the other rays [48].
- The index metacarpal is the longest, while the thumb metacarpal is the shortest [48].
- The proximal and middle phalanges of the middle and ring fingers are longer than those of the index finger [48].
- The transverse palmar axis is oblique, forming an acute angle of approximately 75 degrees with the longitudinal axis [48].
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration for grasping [48].
- The metacarpophalangeal joints serve as the keystones of the longitudinal arches of the hand [85].
- The volar plates prevent hyperextension at the metacarpophalangeal joints [85].
- The fourth metacarpal has approximately 10 degrees of mobility in flexion and extension [85].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [85].
- The index ray possesses a degree of independence at the phalangeal level due to the arrangement of its flexor and extensor muscles [85].
- The axes of flexion are arranged such that flexion of all metacarpophalangeal and proximal interphalangeal joints causes the fingers to converge toward the scaphoid [91].
- The hand presents a longitudinal and transverse concavity, giving it the shape of a cup with a palmar concavity when the thumb is placed next to the index finger [48].
Soft Tissue and Gliding Mechanisms
- The dorsal skin is thin, possesses a normal pilosebaceous system, and has loose connections with deeper planes allowing free gliding [89].
- Flexion of the fingers produces a significant lengthening of the dorsal skin, with an average increase of 3 cm in the middle finger from extension to full flexion [89].
- The dorsal and palmar areas of skin are independent due to a system of adhesions anchoring their common boundary to the underlying plane [89].
- In unrestricted areas, tendons are surrounded by paratenon and areolar connective tissue arranged in layers [88].
- In narrow crowded areas, the gliding mechanism is assured by synovial sheaths surrounded by fibrous sheaths that act as pulleys [88].
- The synovial sheaths for flexor tendons are much more developed on the palmar aspect than on the dorsal aspect [88].
- The digital neurovascular structures are surrounded by a diffuse network of thin transverse oblique fibers, with dorsal fibers called Cleland ligament and palmar fibers called Grayson ligament [90].
- The superficial palmar fascia covers a triangular area of the central palm, with the palmaris longus tendon terminating in continuity with its proximal corner [90].
- The tenosynovium lining the fibroosseous tunnel supplies nutrition and lubrication to the poorly vascularized flexor tendons [87].
- Within the flexor tendon sheath, tendon vascularity is supplied via the vincula system, specifically the vinculum longus and brevis [87].
Nerve Anatomy and Sensory Distribution
- The palmar cutaneous branch of the median nerve has a diameter of about 0.8 mm [67].
- The dorsal branch of the ulnar nerve arises from the medial aspect of the ulnar nerve at an average distance of 6.4 cm from the distal aspect of the head of the ulna [67].
- The dorsal cutaneous branch of the radial nerve becomes superficial about 4 cm proximal to the radiocarpal joint line [67].
- The palmar cutaneous branch of the ulnar nerve originates at a variable level and was replaced in 16 of 21 cases by branches from the superficial division of the ulnar nerve or its dorsal division [67].
- The ramus communicans between the ulnar and median nerves could cross over anywhere in the middle three fifths of the palm [109].
- The hand contains "functional cutaneous units" similar to those described in the face [81].
- The dorsal covering of the interphalangeal articulations forms a unique cutaneous unit characterized by a considerable excess of skin when the digits are in extension [81].
- The palmar integument of the digits is subdivided into phalangeal units separated by digital flexion folds [81].
- When a digit is completely flexed, the integument of adjacent phalanges comes into contact in the zones of the flexion creases, establishing areas of cutaneous contact in the form of a diamond [81].
Vascular Anatomy
- The "princeps pollicis" artery is the terminal branch of the radial artery that crosses the first intermetacarpal space and runs along the ulnar side of the first metacarpal bone [86].
- In anatomical studies, only 15% of dissections of the palmar arteries of the thumb fall into the classical "typical" category [86].
- The two palmar collateral arteries of the thumb run alongside the flexor tendon and behind the collateral nerves in the second segment of the thumb [86].
- The dorsal arteries of the thumb originate from the palmar arteries at the level of the first metacarpal and head distally on the side of the two distal phalanges [86].
Muscle and Tendon Anatomy
- There are seven interosseous muscles in the hand: four dorsal and three volar [82].
- The dorsal interossei are abductors, while the volar interossei are adductors [82].
- The middle finger has two dorsal interossei and no volar interossei because the central axis of the hand lies within it [82].
- The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [47].
- The first extensor compartment contains the abductor pollicis longus and the extensor pollicis brevis [47].
- The second extensor compartment contains the extensor carpi radialis longus and the extensor carpi radialis brevis [47].
- The third extensor compartment contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [47].
- The fourth extensor compartment contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [47].
- The fifth extensor compartment contains the extensor digiti quinti [47].
- The sixth extensor compartment contains the extensor carpi ulnaris [47].
- The flexor digitorum profundus originates from the proximal ulna and the interosseous membrane [87].
- The flexor digitorum superficialis has two heads: a radial head from the proximal shaft of the radius and a humeral ulnar head from the medial humeral epicondyle and coronoid process of the ulna [87].
- The flexor pollicis longus originates from two heads: a radial head from the proximal radius and interosseous membrane, and an accessory head from the coronoid process of the ulna and medial epicondyle of the humerus [87].
- The A2 and A4 pulleys are the most essential in maintaining the mechanical advantage of the flexor tendons [87].
- The lumbricals originate from the radial side of the index, middle, ring, and little fingers in the palm [87].
Pathophysiology and Injury Classification
- The Sunderland classification of nerve injury includes degrees I through VI, with degree VI being a combination of any of degrees I–V [9].
- Normal two-point discrimination in the hand is usually 6 mm or less [9].
- If a nerve is transected, a patient would not feel light touch, would not appreciate a pin as a sharp stimulus, and would be unable to discriminate between one and two points [9].
- Patients with closed or partial nerve injuries may show spotty appreciation of light touch and pain and have markedly widened two-point discrimination [9].
- The mechanism of ulnar nerve injury, excluding compression neuropathy, in order of frequency includes laceration, stretch, and contusion [19].
- Electrodiagnostic testing is critical in determining the level of nerve injury, but nerve conduction velocity studies and electromyography can be limited in cases of severe axonal loss or early after injury [19].
- High-resolution ultrasound imaging can show individual nerve fascicules and identify peripheral nerve disruption [19].
- Tendon injuries are present in some aspect in all cases of mutilating hand trauma [35].
- An injury to one digital nerve did not affect the result of a tendon graft in a finger, but when both nerves were injured, the result was compromised [34].
- In the thumb, there was slight but definite impairment of function when either one or both digital nerves were injured [34].
- Double crush syndrome involves nerve symptomatology from two distinct nerve lesions, with no clear consensus on what qualifies the diagnosis [56].
- Double crush syndrome patients commonly present with peripheral sensorimotor neuropathy, which may include sensory loss, burning or tingling sensation, decreased limb dexterity, limb weakness, or lack of coordination [56].
- Section of the median nerve causes paralysis of the lateral thenar muscles, resulting in loss of the anteposition of the thumb [104].
- Section of the median nerve above the elbow produces paralysis of the flexor pollicis longus, flexor digitorum superficialis, and the lateral half of the flexor profundus [104].
- The second interosseous does not provide sufficient stability to prevent ulnar drift of the middle finger, whereas the first interosseous does this for the index finger [137].
Classification
- Nerve injuries are classified based on severity and extent of damage, with recovery and outcome dependent on the original classification [20].
- The Seddon classification categorizes nerve injuries into neurapraxia, axonotmesis, and neurotmesis [9].
- The Sunderland classification categorizes nerve injuries into degrees I through VI, where degree VI is a combination of any of degrees I–V [9].
- In the Seddon-Sunderland mapping, neurapraxia corresponds to Sunderland degree I [9].
- In the Seddon-Sunderland mapping, axonotmesis corresponds to Sunderland degrees II, III, and IV [9].
- In the Seddon-Sunderland mapping, neurotmesis corresponds to Sunderland degree V [9].
- Rapid intervention generally improves outcome in peripheral nerve injuries [20].
- Prolonged denervation of nerve segments can lead to low recovery rates and other disabilities [20].
Clinical Presentation
History and Initial Assessment
- A careful history is essential to differentiate between neurapraxia and axonotmesis, which can be treated without surgery, and neurotmesis, which requires surgical intervention [19].
- Factors that interfere with the examination of nerves in the hand include other life-threatening or limb-threatening injuries, patient intoxication, anxiety, lack of cooperation, and extensive hand injury [9].
- If conditions are not satisfactory for a thorough initial evaluation, the hand should be reexamined within a reasonable period to determine the extent of nerve and other injuries [9].
- A high index of suspicion is necessary in the evaluation of patients with hand injuries [9].
- The mechanism of ulnar nerve injury, excluding compression neuropathy, occurs in order of frequency as laceration, stretch, and contusion [19].
- The presence of fractures is associated with a higher incidence of nerve and tendon injuries [18].
- Involvement of nerve and tendon structures in hand injuries is linked to an increased risk of long-term disability [18].
- Persistent neurological deficits after distal radius fractures should prompt early investigation and consideration for structural nerve injury [51].
- Such injuries are likely to be missed in casualty because of extensive soft tissue swelling, the apparent normal appearance of anteroposterior X-rays, and the technical difficulty in testing the motor branch of the ulnar nerve in the presence of pain [63].
- The case illustrates the diagnostic difficulty of ulnar nerve motor branch lesions in emergency settings [60].
Sensory Evaluation
- At least four areas of consideration are important when evaluating a patient with a nerve injury in the hand: type of injury, sensibility evaluation, motor function, and sudomotor function [9].
- Customary methods to evaluate damaged sensory nerves include using a sharp pin to assess pain, a cotton-tipped applicator or finger eraser to assess light touch, and the tips of a paper clip or commercially prepared tool to assess two-point discrimination [9].
- In simple nerve injuries, a plastic pen test can detect immediate cessation of sweating in the denervated area without any discomfort to the patient [95].
- In complicated injuries where the diagnosis is in doubt, measurement of skin resistance alone will not establish the nature of the injury [95].
- The combination of sensory threshold testing with skin conductance gives rise to great accuracy in the diagnosis of difficult nerve problems [95].
- Although electrical resistance will alter immediately following injury, it is the last thing to return to normal following repair and is not of value in assessing recovery [95].
- Additional central nervous system symptoms in double crush syndrome may include radiating nerve pain, paresthesia, loss of sensation, hand and upper extremity weakness, hyperreflexia, balance impairment, Lhermitte’s sign, and loss of fine motor control [56].
Motor and Functional Evaluation
- An injury to the digital nerves frequently is overlooked; however, if a flexor tendon function deficit is present after a finger laceration, at least one digital nerve probably has been injured as well [9].
- Proximal radial nerve injuries result in lack of wrist and digit extension with diminished grip strength and hand function [59].
- A migrating Tinel's phenomenon is a good prognostic indicator for radial nerve injuries [64].
- If not corrected, secondary defects of the hand with intrinsic paralysis may compromise normal function when either nerve function recovers or tendon transfers have been performed to correct the primary functional defects [7].
- The final status of the median nerve was at least no worse on the average in cases where the carpal tunnel was used as a pathway for a graft [12].
- Rates of median nerve symptoms were high and resolved in most cases (92%) after reduction of perilunate dislocation [40].
- At a mean final follow-up of 7 months, full recovery of median nerve function was seen in all patients with the triad of multiple metacarpal fractures/dislocations, severe hand swelling, and acute median nerve dysfunction [69].
- Grip and tip-pinch strength improve over a mean period of three years following median and/or ulnar nerve lesion [29].
- For median nerve injuries, signs of reinnervation appeared between the fourth and sixth postoperative month, but the two-point discrimination test never became normal [24].
- The sequence of early sensory recovery following repair of peripheral nerve lesions has varied significantly from that reported in the literature [38].
Diagnostic Imaging and Electrodiagnostics
- Electrodiagnostic testing is critical in determining the level of injury; however, nerve conduction velocity studies and the results of electromyography (EMG) can be limited in cases of severe axonal loss or early after injury when neurapraxia cannot be discerned from neurotmesis [19].
- EMG can also be limited by pain and an inability to identify anatomical variability [19].
- High-resolution ultrasound imaging can show individual nerve fascicules [19].
- Objective measures are limited because MRI and ultrasound have been of limited use for radial nerve injuries [64].
- Electromyography and nerve conduction velocity studies are rarely helpful acutely except when continuity is unknown because slowed but intact conduction indicates some continuity [64].
- Study is recommended around 3 to 4 months after radial nerve injury [64].
- Larger polyphasic motor action potentials of longer duration may be seen before clinical recovery, although the degree of recovery is unclear [64].
- If the amplitude of motor nerve conduction velocity is low, less than 0.3 mV, exploration can be undertaken, with repair remaining a viable option even 5 to 6 months after injury [64].
- Nerve conduction studies should be performed in patients presenting with possible carpal tunnel syndrome to assist diagnosis, and may need to be repeated at intervals in those managed conservatively [52].
- While nerve conduction studies may potentially help to find multiple lesions on the same nerve, there may still be overlap in determining lesion type which makes determining whether there are 2 distinct crush injuries challenging [56].
Investigations
Diagnostic Modalities and Limitations
- Electrodiagnostic testing is critical in determining the level of ulnar nerve injury [19].
- Nerve conduction velocity studies and electromyography (EMG) results can be limited in cases of severe axonal loss or early after injury when neurapraxia cannot be discerned from neurotmesis [19].
- EMG can be limited by pain and an inability to identify anatomical variability [19].
- Ultrasound imaging can identify a change in the hypoechoic signal within the nerve to indicate injury [19].
- Ultrasound can visualize the epineurium to suggest whether the nerve is in continuity [19].
- Ultra-sonography provides a new ability to study the complex anatomical structures of the hand, with the technique being quick and simple to perform [49].
- Nerve conduction studies should be performed in patients presenting with possible carpal tunnel syndrome to assist diagnosis [52].
- Nerve conduction studies may need to be repeated at intervals in patients managed conservatively for carpal tunnel syndrome [52].
- No predictor in clinical and MR neurography variables was found that correlates with recovery of thumb opposition in severe carpal tunnel syndrome [70].
Clinical Assessment and History
- A careful history is essential, particularly in cases of blunt trauma, to differentiate between neurapraxia and axonotmesis (which can be treated without surgery) and neurotmesis (which requires surgical intervention) [19].
- Recovery of sensitivity in reinnervated cutaneous areas is evaluated using the two-point discrimination test [14].
- Signs of reinnervation for median nerve injuries appeared between the fourth and sixth postoperative month [24].
- The two-point discrimination test never became normal for median nerve injuries in the reported series [24].
- Ulnar nerve motor branch lesions present diagnostic difficulty in emergency settings [60].
- Injuries causing transient motor neurapraxia of the ulnar nerve are likely to be missed in casualty due to extensive soft tissue swelling, apparent normal anteroposterior X-rays, and technical difficulty in testing the motor branch in the presence of pain [63].
Anatomic Variations and Innervation Patterns
- Communicating branches between the median and ulnar nerves in the palm were found in 20 of 30 (67%) specimens [80].
- Ulnar-based cutaneous nerves to the palm were found within the zone of incision in 16 of 25 specimens [45].
- Ulnar-based cutaneous nerves to the palm are not necessarily preserved by longitudinal palmar incisions in the axis of the ring finger [45].
- An injury to the median nerve in a hand with unusual anatomic variation would not experience sensory impairment of the ulnar halves of the index and middle and the radial half of the ring fingers [1].
Treatment
Nerve Repair and Grafting
- End-to-end nerve repair was performed in 10% of cases in a series of brachial plexus injuries, with 35% of those cases having excellent results [6].
- Tubular repair is an attractive alternative to primary, delayed primary, or secondary repair of severed major nerve trunks in the human forearm [74].
- Tubular repair may not be superior to conventional techniques in terms of functional recovery but represents a simple biological approach to nerve repair [74].
- When direct suture is not possible because of tension, tubular repair leaving a short distance between the nerve ends may be the key to avoiding nerve grafting [74].
- Experimental work proved that tension at the suture line has a detrimental role on nerve repair outcomes [124].
- Experimental work proved that postoperative stretching has a deleterious effect on successful functional recovery after nerve repair [124].
- Regenerating axons advanced more easily through nerve grafts of 2 cm with two tension-free anastomoses compared with a single suture under tension [124].
- The epineurium was the primary source of connective tissue proliferation in experimental nerve repair studies [124].
- Motor recovery for median nerve repair was excellent in 40%, good in 40%, and fair in 20% of cases [124].
- Motor recovery for ulnar nerve repair was excellent in 38%, good in 40%, and fair in 22% of cases [124].
- Motor recovery for radial nerve repair was excellent in 42%, good in 38%, and fair in 20% of cases [124].
- Vascularized ulnar nerve grafts should be recommended for reconstruction of the median or radial nerves in selected cases [44].
- Nerve grafting of a large defect in a high median nerve injury involves a relatively long duration of recovery with unpredictable recovery [68].
- The final status of the median nerve was at least no worse on the average in cases where the carpal tunnel was used as a pathway for the graft [12].
Nerve Transfers
- Distal nerve transfers for the treatment of high ulnar nerve injuries allow for a shorter reinnervation period and improved ulnar intrinsic recovery [39].
- End-to-side distal anterior interosseous nerve transfer provides significantly better results than a standard more proximal nerve repair for proximal ulnar nerve injuries [41].
- Transfer of the superficial radial or dorsal cutaneous branch of the ulnar nerve, or both, produced successful restoration of innervation of the thumb and index and long fingers in experimental monkey models [28].
- A dual nerve transfer from the median nerve to the distal nerve branches of the radial nerve is a preferred procedure to restore radial nerve function [59].
- In a dual median-to-radial nerve transfer, coaptation of the flexor digitorum superficialis (FDS) nerve to the extensor carpi radialis brevis (ECRB) nerve is performed to restore wrist extension [59].
- In a dual median-to-radial nerve transfer, the flexor carpi radialis (FCR) nerve is transferred to the posterior interosseous nerve (PIN) to restore finger and thumb extension [59].
- Nerve transfers for restoration of radial nerve function optimize recovery by providing pure motor donors from a near-target axon source allowing for earlier reinnervation [59].
- Nerve transfers are particularly useful for patients with hand stiffness and complex regional pain syndrome who may otherwise not be ideal candidates for tendon transfers [59].
- The authors prefer specific nerve transfers for motor and sensory restoration in high median nerve injury, noting that median nerve repair is mandatory for patients with concomitant pain [33].
- Experimental studies and positive reports from large clinical series suggest that new techniques using foreign nerves for reinnervation are worthy of integration into the management of upper brachial plexus injuries [27].
- Many questions regarding timing, donor morbidity, and comparative efficacy remain unanswered for nerve transfer techniques in upper brachial plexus injuries [27].
- A supercharged end-to-side anterior interosseous nerve transfer to the deep motor branch of the ulnar nerve was performed in 40 patients [31].
- The supercharged end-to-side anterior interosseous nerve transfer procedure involves transecting the anterior interosseous nerve at the midportion of the pronator quadratus muscle and anastomosing it to the side of the motor branch of the ulnar nerve [132].
- The supercharged end-to-side anterior interosseous nerve transfer coaptation can be augmented with fibrin glue [132].
- An above-elbow slab is applied for 3 weeks following a supercharged end-to-side anterior interosseous nerve transfer [132].
- In patients with complete pan-plexal injuries, intact extraplexal nerves (spinal accessory, intercostal, C3 and C4 nerves) can be transferred and coapted to the distal peripheral nerve of the brachial plexus as a method for reinnervation of critical sensory or motor nerves [100].
- Sensation in the median nerve distribution of the hand can be provided by the transfer of sensory branches of the intercostal nerves to the lateral cord contribution of the median nerve in pan-plexus injury [100].
Tendon Transfers
- In a high median nerve injury, if the nerve has been repaired, extrinsic transfers are seldom required because sufficient extrinsic muscle function is usually regained [55].
- If a patient needs a nerve graft for high median nerve injury, especially if done late or under unfavorable conditions, useful extrinsic functional recovery is unlikely [55].
- In high median nerve palsy where nerve grafting is required, one should consider performing early extrinsic end-to-side transfers and/or a side-to-side transfer of the index and conjoined profundus tendons [55].
- All intrinsic and extrinsic transfers for high median nerve palsy can be performed at the same time [55].
- The author does not favor early extrinsic tendon transfers for high median nerve palsy and only restores opposition if, after maximal recovery has occurred, both the patient and the surgeon believe that this will improve hand function [55].
- Most patients with combined median sensory and motor deficit will adapt and increasingly use their normal arm for precision function, making restoration of opposition rarely attempted [55].
- If an opposition transfer is indicated for high median nerve palsy, the author favors EIP transfer [55].
- The BR transfer is used for restoration of thumb flexion in high median nerve palsy, especially for conditions in which there is relative sensory sparing [55].
- An end-to-side attachment is used for the BR transfer unless there is no prospect of later reinnervation [55].
- The author does not think an ECRL transfer to restore index finger flexion is needed often in high median nerve palsy and prefers to join the index and the common profundi tendons in a side-to-side fashion [55].
- A side-to-side join of the index and common profundi tendons does not restore power to the index finger but is preferred when the hand condition is too poor to benefit from an ECRL transfer, especially if there is a marked sensory deficit [55].
- Because worthwhile sensory recovery is so unlikely in high median nerve palsy for adults, opponensplasty is typically not beneficial [55].
- The goal of any repair in high median nerve palsy is to create the best possible “helper” hand, with precision function assumed by the other hand [55].
- A reliable tendon prosthesis inserted as one stage in tendon reconstruction is the additional step needed to improve the results of flexor-tendon reconstructive surgery in hands with severe damage [50].
- The anatomic, two-tendon, three-joint finger with a perfect tendon sheath cannot always be restored to normal after severe injury to the flexor tendon system [77].
- The muscle and tendon to the middle finger arise separately and are therefore more suitable for non-synergistic transfers [149].
- None of the procedures is superior to the other statistically in terms of improvement in grip strength, improvement in active ROM of MCPJs, claw correction, or improvement in overall patient hand functions, in the intermediate follow-up duration, when comparing Zancolli Lasso versus Modified Stiles-Bunnell techniques for post-leprosy ulnar claw hand correction [32].
Nonoperative Management and Rehabilitation
- Nonoperative management of the hand is important while waiting for recovery of radial nerve function from either a presumed axonotmetic nerve injury or after nerve repair [99].
- Nonoperative management is also important while waiting for the hand and arm to recover from associated soft tissue injuries after an irreparable radial nerve injury [99].
- The most important aspects of nonoperative management for radial nerve palsy are maintenance of full passive range of motion in all joints of the wrist and hand and prevention of contractures, including contracture of the thumb–index web [99].
- For most patients with radial nerve palsy, the constant supervision of a therapist is not required, but the patient must be taught very soon after the original nerve injury how to perform an appropriate exercise program to keep the joints supple [99].
- It is the patient’s responsibility to do the exercises, and the role of the therapist at this point is to teach the patient and to monitor progress to ensure that the exercise program is performed correctly [99].
- Few, if any, patients need or want elaborate splinting with dynamic outriggers that can interfere with, rather than improve, function in radial nerve palsy [99].
- Patients’ individual needs should dictate the type of splint for radial nerve palsy, but most find an “off-the-shelf” inconspicuous $10 cock-up wrist splint, which stabilizes the wrist and restores adequate, and often remarkably good, function without interfering with clothing [99].
- A cock-up wrist splint often substantially increases grip strength in patients with radial nerve palsy [99].
- If a wrist splint is worn only during the day for radial nerve palsy, a splint to hold the wrist and fingers in extension is worn at night to prevent loss of fiber length of the flexor muscles [99].
- Clinical outcomes indicate that remote and in-person hand therapy provide similar results for patients with flexor tendon repairs in zones 1 and 2 [102].
- The study confirms that the management and follow-up of closed hand traumas are primarily the responsibility of physiotherapists [150].
- Early mobilisation after flexor tendon repair does not offer an easy solution to what remains a difficult problem and a high degree of expertise will continue to be demanded of the surgeon and hand therapist if consistently good results are to be achieved [151].
Revision and Secondary Procedures
- Revision nerve reconstruction is typically only considered if a “red flag” has been identified, or if definite clinical failure has been confirmed (via EMG and sensory mapping) before the development of irreversible denervation atrophy [36].
- Revision nerve reconstruction usually involves a repair close to the end targets, such as a median or ulnar nerve repair at the wrist [36].
- Rarely is a reexploration performed before 3 to 4 months post-repair for nerve injuries [36].
- If axons are regenerating across the repair, a delay of 3 to 4 months will allow enough axonal growth to be detectable using operative nerve-to-nerve conduction studies [36].
- Nerve transfers have become the author’s preferred reconstructive strategy in many primary situations, and the inevitable time delay associated with revision nerve surgery makes this option (if available) even more appealing [36].
- A supercharging nerve transfer may be the perfect application if successful axonal regeneration is suspected or still anticipated during revision surgery [36].
- Neurolysis and wrapping of the repair can be helpful when functional recovery is hindered by neuropathic pain, though this strategy is unpredictable at best, and the potential for iatrogenic deterioration must be considered [36].
- Prolonged expectant observation and medical management is preferred in most situations for revision nerve surgery [36].
- Unrealistic expectations and secondary gain are practically predictive of failure in revision nerve surgery [36].
- The best indication of the reversed digital artery island flap is not the treatment of fingertip injuries, but rather the coverage of large defects of the dorsal aspects of the middle and third phalanx [144].
- This protective distal finger splint allowed the patient to return to work successfully, without contraindications [142].
Complications
Diagnostic and Assessment Challenges
- Nerve injuries may be overlooked during the initial or preliminary examination if conditions are not satisfactory for a thorough evaluation [9].
- An injury to the digital nerves is frequently overlooked during the evaluation of hand injuries [9].
- Electrodiagnostic testing can be limited in cases of severe axonal loss or early after injury when neurapraxia cannot be discerned from neurotmesis [19].
- Electromyography (EMG) can be limited by pain and an inability to identify anatomical variability [19].
- The outcome of digital nerve repair is difficult to assess, particularly if only one nerve to a finger has been injured [72].
- Some improvement in sensation following digital nerve repair may be a result of crossover from the adjacent nerve territory [72].
Sensory Deficits and Neuromas
- Digital nerve injury causes loss of precise sensation on the pulps of fingers, which is important for normal hand function [72].
- Injury to digital nerves may be complicated by formation of painful neuromas, which can be more disabling than the impairment of sensation [72].
- Sensation does not recover to normal at least in adult patients following digital nerve repair [72].
- Mean two-point discrimination was 10.6 mm compared with 4.4 mm on the contralateral side in a long-term outcome study of 93 digital nerves repaired by direct epineural suture [72].
- Only 2% of patients developed painful neuromas in a long-term outcome study of 93 digital nerves repaired by direct epineural suture [72].
- Useful recovery with MRC grade S3 or S4 was achieved in 79.5% of nerves in a long-term study of secondary repair of 254 completely divided digital nerves [72].
- Age is an important factor in digital nerve recovery, with 100% of patients under age 15 years regaining useful sensation compared with 26% of patients over 40 years [72].
- Results of digital nerve repair deteriorate with increasing length of nerve grafts, with useful recovery in only 15% of nerves that required a graft over 50 mm in length [72].
- An unusual anatomic variation of palmar sensory branches of the ulnar nerve means an injury to the median nerve would not cause sensory impairment of the ulnar halves of the index and middle and the radial half of the ring fingers [1].
- Ulnar-based cutaneous nerves to the palm were found within the zone of incision in 16 of 25 specimens, indicating these nerves are not necessarily preserved by longitudinal palmar incisions in the axis of the ring finger [45].
Motor Deficits and Functional Limitations
- Recovery of the thenar muscles is likely after median nerve repair, but overall control of muscle function is compromised by the sensory impairment [72].
- For the ulnar nerve, finger abduction and thumb adduction are more likely to show recovery than finger adduction [72].
- Return of two-point discrimination is rare following median and ulnar nerve repair, although correct localization of sensation to each finger may be regained [72].
- Outcomes for median and ulnar nerve repairs are better for primary compared to delayed repair [72].
- Overall 33% of median and ulnar nerve repairs gained a good result, 50% fair, 10% poor, and 7% bad according to Seddon's report of 584 repairs [72].
- Outcomes in children were notably better than adults for median and ulnar nerve repairs, with 71% good results in those below age 10 years and 58% in those aged 11 to 15 years [72].
- The presence of fractures is associated with a higher incidence of nerve and tendon injuries, and involvement of these structures is linked to an increased risk of long-term disability [18].
- Long-term follow-up in transient patient populations with pay phone receiver cord injuries was impossible, and anticipated hand function results are less than optimal [11].
Iatrogenic and Secondary Complications
- Secondary defects of the hand with intrinsic paralysis may compromise normal function when either nerve function recovers or tendon transfers have been performed to correct primary functional defects if not corrected [7].
- Nerve compression following opponensplasty can result in almost complete sensory loss of the hand and clawing of all fingers, as reported in a case where numbness and tingling progressed to anesthetic hand [25].
- Electromyogram studies in a case of nerve compression following opponensplasty showed complete conduction loss of both the ulnar and median nerves at the wrist [25].
- In a case of nerve compression following opponensplasty, the hand became much more anesthetic as the function improved in the opponensplasty [25].
- Revision nerve reconstruction is typically considered only if a "red flag" has been identified or if definite clinical failure has been confirmed via EMG and sensory mapping before the development of irreversible denervation atrophy [36].
- Neurolysis and wrapping of the repair can be helpful when functional recovery is hindered by neuropathic pain, though this strategy is unpredictable and carries a potential for iatrogenic deterioration [36].
- Even brief delays or misguided treatment initially may doom the patient to lifelong disability in hand surgery [78].
Graft and Transfer Complications
- In neurovascular island grafts, sensibility is never normal after transfer, and more than half of patients have persistently hyperesthetic skin [76].
- All patients lack precise sensory reorientation following neurovascular island graft transfer, although reorientation seems to improve with time and use [76].
- Temporary impairment of the circulation in a neurovascular island graft can cause permanent sensory deficit in the graft and a partial failure of the operation [76].
Recovery
Nerve Repair Outcomes and Sensory Recovery
- In median nerve injuries, signs of reinnervation appeared between the fourth and sixth postoperative month [24].
- Following median nerve repair, the two-point discrimination test never became normal [24].
- Mean two-point discrimination was 10.6 mm compared with 4.4 mm on the contralateral side in a series of 93 digital nerves repaired by direct epineural suture [72].
- Only 2% of patients developed painful neuromas in a series of 93 digital nerves repaired by direct epineural suture [72].
- Useful recovery, with MRC grade S3 or S4, was achieved in 79.5% of nerves in a series of 254 completely divided digital nerves [72].
- 100% of patients under age 15 years regained useful sensation following secondary repair of digital nerves [72].
- 26% of patients over 40 years regained useful sensation following secondary repair of digital nerves [72].
- Better results were found in those who had digital nerve repair within 3 months [72].
- Useful recovery was achieved in only 15% of nerves that required a graft over 50 mm in length [72].
- Overall, 33% of median and ulnar nerve repairs gained a good result, 50% fair, 10% poor, and 7% bad [72].
- Outcomes in children were notably better than adults with 71% good results in those below age 10 years and 58% in those aged 11 to 15 years following median and ulnar nerve repair [72].
- Correct localization of sensation to each finger may be regained, but return of two-point discrimination is rare following median and ulnar nerve repair [72].
- Outcomes have been shown to be better for primary compared to delayed repair of median and ulnar nerves [72].
- An injury to the median nerve of a hand with unusual anatomic variation of palmar sensory branches would not experience sensory impairment of the ulnar halves of the index and middle and the radial half of the ring fingers [1].
Motor Recovery and Functional Strength
- Transfer of the superficial radial or dorsal cutaneous branch of the ulnar nerve, or both, produced successful restoration of innervation of the thumb and index and long fingers in experimental sensory reinnervation of the median nerve [28].
- New techniques using foreign nerves for reinnervation are worthy of integration into the management of upper brachial plexus injuries, though many questions regarding timing, donor morbidity, and comparative efficacy remain unanswered [27].
- The choice between nerve transfer and tendon transfer should consider individual patient factors, balancing early functional recovery with long-term outcomes [75].
Specific Injury Mechanisms and Complications
- The final status of the median nerve was at least no worse on the average in cases where the carpal tunnel was used as a pathway for the graft during tendon transfer for ulnar paralysis [12].
- The presence of fractures is associated with a higher incidence of nerve and tendon injuries, and involvement of these structures is linked to an increased risk of long-term disability in ballistic injuries to the hand [18].
- Numbness and tingling occurred in the areas of distribution of the ulnar and median nerves following opponensplasty, leading to almost complete sensory loss of the hand and clawing of all fingers in a reported case [25].
- An electromyogram study showed complete conduction loss of both the ulnar and median nerves at the wrist following complications from an opponensplasty in a reported case [25].
Rehabilitation and Timing
- Rapid intervention generally improves outcome in peripheral nerve injury, while prolonged denervation of the nerve segments can lead to low recovery rates and to other disabilities [20].
- Hand therapists are needed for a long time, certainly as long as tendon and nerve repairs are immobilized 3 weeks and fractures are immobilized 6 weeks [22].
- Flexor tendon repair was followed by good function in a case of simultaneous dislocation of both interphalangeal joints and flexor tendon tear [140].
- At 6 months, very significant progress was observed with complete and total recovery of active flexion amplitudes of the proximal and distal interphalangeal joints of 4 long fingers following secondary flexor tendon surgery using silicone perfusion tubing [155].
Key Evidence
- [L5] An injury to the median nerve of such a hand would not experience sensory impairment of the ulnar halves of the index and middle and the radial half of the ring fingers. [1] (10.1053/jhsu.2002.30368)
- [L4] The one-stage procedure of combined nerve repair and two-tendon transfer permits early and useful function of the hand, due to the action of the transferred tendons. [2] (10.1016/0266-7681_89_90090-9)
- [L4] The one-stage procedure of combined nerve repair and two-tendon transfer permits early and useful function of the hand, due to the action of the transferred tendons. [3] (10.1016/0266-7681(89)90090-9)
- [L5] Tendon or tissue transfers in combined nerve palsies require longer follow-up than isolated nerve palsies to make a valid assessment of the outcome. [4] (10.1016/0266-7681(92)90183-3)
- [L4] Nerve transfers are an option for restoring hand and forearm function in patients with peripheral nerve injuries adversely affecting their ability to function. [5] (10.2106/jbjs.rvw.24.00150)
- [L4] End to end nerve repair was performed in 10% of cases and 35% had excellent results. [6] (10.1016/s0363-5023(03)80320-9)
- [Paper] If not corrected, these defects may compromise normal function of the hand when either nerve function recovers or tendon transfers have been performed to correct the primary functional defects. [7] (10.1016/s0894-1130(12)80364-4)
- [L1] Despite the use of microsurgical techniques, outcome after median and ulnar nerve repair is suboptimal. [10] (10.1016/s0363-5023(03)80328-3)
- [L4] Long-term follow-up in this particular transient patient population was impossible, and anticipated hand function results are less than optimal. [11] (10.1016/s0363-5023(84)80078-7)
- [L4] The final status of the median nerve was at least no worse on the average in the cases where the carpal tunnel was used as a pathway for the graft. [12] (10.1016/s0266-7681(85)80010-3)
- [L4] The conservation of these finger-tips provides the hand surgeon with new possibilities for late reconstruction of an injured digit. [13] (10.1016/s0020-1383(73)80022-1)
- [L4] [14] (10.1016/0266-7681(88)90062-9)
- [L5] The biomechanical principles, indications and limitations of tendon transfers, nerve transfers and combined approaches are compared, with particular attention to timing, patient selection, and functional goals. [17] (10.1177/17531934261416300)
- [L4] The presence of fractures is associated with a higher incidence of nerve and tendon injuries, and involvement of these structures is linked to an increased risk of long-term disability. [18] (10.1177/15589447221092111)
- [L5] [19] (10.1016/j.jhsa.2014.04.038)
- [L4] [20] (10.1177/17531934241240867)
- [L4] In lower-type injuries of the brachial plexus, transfer of median nerve branches that innervate the palm of the hand to the ulnar proper digital nerve of the little finger predictably restored protective sensation on the ulnar side of the hand. [21] (10.1016/j.jhsa.2012.02.047)
- [Paper] Hand therapists are going to be needed for a long time-certainly as long as tendon and nerve repairs are immobilized 3 weeks and fractures are immobilized 6 weeks. [22] (10.1016/s0894-1130(89)80035-3)
- [Paper] For median nerve injuries, signs of reinnervation appeared between the fourth and sixth postoperative month, but the two-point discrimination test never became normal. [24] (10.1016/s0363-5023(82)80187-1)
- [L5] [25] (10.1016/s0363-5023(80)80014-1)
- [L4] Nerve transfer is favored over nerve grafting in managing high ulnar nerve injuries because of better improvement of motor power and better restoration of grip functions of the hand. [26] (10.1016/j.jhsa.2017.01.027)
- [L5] Experimental studies and positive reports from large clinical series suggest that new techniques using foreign nerves for reinnervation are worthy of integration into the management of upper brachial plexus injuries, though many questions regarding timing, donor morbidity, and comparative efficacy remain unanswered. [27] (10.1054/jhsb.2000.0460)
- [L5] Transfer of the superficial radial or dorsal cutaneous branch of the ulnar nerve, or both, produced successful restoration of innervation of the thumb and index and long fingers. [28] (10.2106/00004623-197759030-00016)
- [L4] Grip and tip-pinch strength improve over a mean period of three years, following median and/or ulnar nerve lesion. [29] (10.1016/s0363-5023(03)80327-1)
- [L4] More homogeneous follow-up protocols are needed for strength measurement and patient-reported outcome measures for both nerve and tendon transfers. [30] (10.1016/j.jhsg.2026.101116)
- [L2] None of the procedures is superior to the other statistically in terms of improvement in grip strength, improvement in active ROM of MCPJs, claw correction, or improvement in overall patient hand functions, in the intermediate follow-up duration. [32] (10.1177/15589447251364568)
- [L4] The authors prefer specific nerve transfers for motor and sensory restoration, noting that median nerve repair is mandatory for patients with concomitant pain. [33] (10.1016/j.hcl.2015.12.008)
- [L5] [35] (10.1016/s0749-0712(02)00130-0)
- [L4] In our clinical experience, the sequence of early sensory recovery following repair of peripheral nerve lesions has varied significantly from that reported in the literature. [38] (10.1016/s0894-1130(89)80038-9)
- [L5] Distal nerve transfers for the treatment of high ulnar nerve injuries allow for a shorter reinnervation period and improved ulnar intrinsic recovery, which is critical to function of the hand. [39] (10.1016/j.hcl.2015.12.009)
- [L4] Rates of median nerve symptoms were high and resolved in most cases (92%) after reduction. [40] (10.1177/15589447251317236)
- [L4] It provides significantly better results than a standard more proximal nerve repair. [41] (10.1016/s0363-5023(11)60008-7)
- [Paper] Such nerve transfers provide significantly better treatment options in many cases of nerve injury where previous outcomes were expected to be poor, such as with proximal injuries, long nerve gaps, or unavailability of the proximal injured segment. [43] (10.1097/bth.0b013e31812714f3)
- [L4] This technique should be recommended for reconstruction of the median or radial nerves in selected cases. [44] (10.1016/j.jhsa.2005.03.017)
- [L5] Our finding that the ulnar-based cutaneous nerves to the palm were found within the zone of incision in 16 of 25 specimens indicates that these nerves are also not necessarily preserved by longitudinal palmar incisions in the axis of the ring finger. [45] (10.1016/s0363-5023(96)80017-7)
- [L4] Ultra-sonography provides a new ability to study the complex anatomical structures of the hand, with the technique being quick and simple to perform. [49] (10.1016/0266-7681(90)90133-o)
- [L4] The authors conclude that a reliable tendon prosthesis inserted as one stage in tendon reconstruction is the additional step needed to improve the results of flexor-tendon reconstructive surgery in hands with severe damage. [50] (10.2106/00004623-197153050-00001)
- [L5] Persistent neurological deficits after distal radius fractures should prompt early investigation and consideration for structural nerve injury. [51] (10.1016/j.jhsg.2026.101074)
- [L5] Nerve conduction studies should be performed in patients presenting with possible carpal tunnel syndrome to assist diagnosis, and may need to be repeated at intervals in those managed conservatively. [52] (10.1016/j.cnp.2018.02.005)
- [Paper] [56] (10.1177/15589447251352122)
- [L5] [59] (10.1016/j.jht.2013.12.007)
- [L5] The case illustrates the diagnostic difficulty of ulnar nerve motor branch lesions in emergency settings. [60] (10.1016/j.main.2015.10.040)
- [L4] Such injuries are likely to be missed in casualty because of the extensive soft tissue swelling, the apparent normal appearance of anteroposterior X-rays and the technical difficulty in testing the motor branch of the ulnar nerve in the presence of pain. [63] (10.1016/s0020-1383(96)00207-0)
- [L5] [64] (10.5435/jaaos-d-17-00325)
- [L5] Clinically, this technique may offer an alternative option for proximal nerve injuries or for free functioning muscle transplantations. [66] (10.1054/jhsb.2000.0389)
- [L5] [68] (10.1142/s2424835520720121)
- [L4] At a mean final follow-up of 7 months, full recovery of median nerve function was seen in all patients, and all patients were able to return to work. [69] (10.1177/1753193408087105)
- [L3] In practical terms, we did not find any predictor in clinical and MR neurography variables that correlate with recovery of thumb opposition. [70] (10.1177/1558944716660555fw)
- [L1] [74] (10.1097/00130911-199706000-00008)
- [L4] The anatomic, two-tendon, three-joint finger with a perfect tendon sheath cannot always be restored to normal after severe injury to the flexor tendon system. [77] (10.1016/s0894-1130(89)80048-1)
- [L5] He states that surgery of the hand is a demanding and very difficult art, and that even brief delays or misguided treatment initially may doom the patient to lifelong disability. [78] (10.1016/s0363-5023(80)80070-0)
- [L5] The communicating branches between the median and ulnar nerves in the palm were found in 20 of the 30 (67%) specimens. [80] (10.1053/jhsu.1999.1171)
- [L5] [95] (10.1016/0266-7681(86)90198-1)
- [L3] Clinical outcomes indicate that remote and in-person hand therapy provide similar results for patients with flexor tendon repairs in zones 1 and 2. [102] (10.1177/15589447251339498)
- [L5] As a cautious measure, hand surgeons should take into account that this structure could cross over anywhere in the middle three fifths of the palm. [109] (10.1053/jhsu.2000.16352)
- [L1] [124] (10.1016/s0363-5023(03)80333-7)
- [L4] [132] (10.1186/s12891-024-07650-4)
- [Paper] The second interosseous apparently does not provide sufficient stability to prevent ulnar drift of the middle finger, whereas the first interosseous does do this for the index finger. [137] (10.1016/s0363-5023(77)80081-6)
- [L5] Flexor tendon repair was followed by good function. [140] (10.1016/s0020-1383(97)00202-7)
- [L5] Tendon transfers remain the primary reconstructive procedure for paralytic injuries of the upper limb until sufficiently powered studies of nerve transfer outcomes are published. [141] (10.1177/1753193419864838)
- [L5] This protective distal finger splint allowed the patient to return to work successfully, without contraindications. [142] (10.1016/s0894-1130(99)80032-5)
- [L4] The best indication of the reversed digital artery island flap is not the treatment of fingertip injuries, but rather the coverage of large defects of the dorsal aspects of the middle and third phalanx. [144] (10.1016/0363-5023(94)90032-9)
- [L5] The muscle and tendon to the middle finger arise separately and are therefore more suitable for non-synergistic transfers. [149] (10.1016/0266-7681(91)90131-7)
- [L4] The study confirms that the management and follow-up of these closed hand traumas are primarily the responsibility of physiotherapists. [150] (10.1016/j.hansur.2017.10.231)
- [Paper] They do not offer an easy solution to what remains a difficult problem and a high degree of expertise will continue to be demanded of the surgeon and hand therapist if consistently good results are to be achieved. [151] (10.1016/0266-7681(89)90150-2)
- [L5] At 6 months, very significant progress was observed with complete and total recovery of active flexion amplitudes of the proximal and distal interphalangeal joints of 4 long fingers. [155] (10.1016/j.hansur.2018.10.074)
References
[1] Unusual anatomic variation of palmar sensory branches of the ulnar nerve: A case report. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.30368
[2] Early Restoration of Pinch Grip after Ulnar Nerve Repair and Tendon Transfer. Journal of Hand Surgery. 1989. DOI: 10.1016/0266-7681_89_90090-9
[3] Early restoration of pinch grip after ulnar nerve repair and tendon transfer. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1989. DOI: 10.1016/0266-7681(89)90090-9
[4] Tendon Transfers for Combined Traumatic Nerve Palsies of the Forearm and Hand. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90183-3
[5] Review of Outcomes After Peripheral Nerve Transfers for Motor Nerve Injury in the Upper Extremity. JBJS Reviews. 2024. DOI: 10.2106/jbjs.rvw.24.00150
[6] Brachial plexus injury in war victims. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80320-9
[7] Secondary defects of the hand with intrinsic paralysis. Journal of Hand Therapy. 1990. DOI: 10.1016/s0894-1130(12)80364-4
[9] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > EVALUATION.
[10] Meta-analysis: Repair of median and ulnar nerve transection injuries. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80328-3
[11] Pay phone receiver cord injuries to the hand. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80078-7
[12] Median Nerve Function After Tendon Transfer For Ulnar Paralysis. Journal of Hand Surgery. 1985. DOI: 10.1016/s0266-7681(85)80010-3
[13] Preservation of amputated finger-tips. Injury. 1973. DOI: 10.1016/s0020-1383(73)80022-1
[14] Transfer of sensory branches of radial nerve in hand surgery. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90062-9
[17] Tendon versus nerve transfers – balancing hand function in upper extremity high nerve injuries. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261416300
[18] Outcomes in Ballistic Injuries to the Hand: Fractures and Nerve/Tendon Damage as Predictors of Poor Outcomes. HAND. 2022. DOI: 10.1177/15589447221092111
[19] Management of Ulnar Nerve Injuries. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.04.038
[20] Timing of surgery in peripheral nerve injury of the upper extremity. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241240867
[21] Distal Sensory Nerve Transfers in Lower-Type Injuries of the Brachial Plexus. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.02.047
[22] Frontiers in wound healing research that may affect the work of hand therapists. Journal of Hand Therapy. 1989. DOI: 10.1016/s0894-1130(89)80035-3
[24] Belgian Hand Group. The Journal of Hand Surgery. 1982. DOI: 10.1016/s0363-5023(82)80187-1
[25] Nerve compression following opponensplasty as a result of wrist anomalies: Report of a case. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80014-1
[26] Nerve Transfer Versus Nerve Graft for Reconstruction of High Ulnar Nerve Injuries. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.01.027
[27] Avulsion Injuries to the Brachial Plexus and the Value of Motor Reinnervation by Ipsilateral Nerve Transfer. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.2000.0460
[28] Experimental sensory reinnervation of the median nerve by nerve transfer in monkeys. The Journal of Bone & Joint Surgery. 1977. DOI: 10.2106/00004623-197759030-00016
[29] Motor recovery following median and ulnar nerve injuries. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80327-1
[30] Nerve and Tendon Transfers After Cervical Spinal Cord Injury: A Systematic Review of Strength Outcomes in 959 Patients. Journal of Hand Surgery Global Online. 2027. DOI: 10.1016/j.jhsg.2026.101116
[31] Supercharged_End-to-Side_Nerve_Transfer_Too_Soon_for_“Prime_Time”_S036350231300138X. n.d..
[32] Functional Outcomes of Zancolli Lasso Versus Modified Stiles-Bunnell Techniques for Post-Leprosy Ulnar Claw Hand Correction: A Prospective Randomized Comparative Study. HAND. 2025. DOI: 10.1177/15589447251364568
[33] High Median Nerve Injury. Hand Clinics. 2016. DOI: 10.1016/j.hcl.2015.12.008
[34] Flexor-Tendon Grafts in the Fingers and Thumb: A STUDY OF FACTORS INFLUENCING RESULTS IN 1000 CASES.. The Journal of Bone and Joint Surgery. American Volume. 1971.
[35] Biomechanics and hand trauma: what you need. Hand Clinics. 2003. DOI: 10.1016/s0749-0712(02)00130-0
[36] Green S Operative Hand Surgery. Technique: Target Muscle Reinnervation > AUTHOR'S PREFERRED METHOD OF TREATMENT: REVISION SURGERY.
[38] Sequence of sensory recovery: A retrospective study. Journal of Hand Therapy. 1989. DOI: 10.1016/s0894-1130(89)80038-9
[39] High Ulnar Nerve Injuries. Hand Clinics. 2016. DOI: 10.1016/j.hcl.2015.12.009
[40] Perilunate Dislocation Reduction Technique and Results. HAND. 2025. DOI: 10.1177/15589447251317236
[41] End-to-side Distal Anterior Interosseous Nerve Transfer in Treatment of Proximal Ulnar Nerve Injuries. The Journal of Hand Surgery. 2011. DOI: 10.1016/s0363-5023(11)60008-7
[43] Nerve Transfers in the Hand and Upper Extremity Surgery. Techniques in Hand & Upper Extremity Surgery. 2008. DOI: 10.1097/bth.0b013e31812714f3
[44] Vascularized Ulnar Nerve Graft for Reconstruction of a Large Defect of the Median or Radial Nerves After Severe Trauma of the Upper Extremity. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.03.017
[45] The cutaneous innervation of the palm: An anatomic study of the ulnar and median nerves. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80017-7
[47] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[48] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[49] Diagnostic medical ultrasound in the management of hand injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1990. DOI: 10.1016/0266-7681(90)90133-o
[50] Flexor-Tendon Reconstruction in Severely Damaged Hands. The Journal of Bone & Joint Surgery. 1971. DOI: 10.2106/00004623-197153050-00001
[51] Ulnar Neuroma-in-Continuity Following Distal Radius Fracture: A Rare Complication Requiring Reconstruction with Nerve Allograft and Dynamic Tendon Transfer. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101074
[52] Nerve conduction studies and EMG in carpal tunnel syndrome: Do they add value?. Clinical Neurophysiology Practice. 2018. DOI: 10.1016/j.cnp.2018.02.005
[55] Green S Operative Hand Surgery. Tendon Transfers for Median, Radial, and Ulnar Nerve Palsy > ECRL-to-Index Profundus Transfer > High Median Nerve Palsy Summary.
[56] Double Crush Syndrome: A Review of the Literature. HAND. 2025. DOI: 10.1177/15589447251352122
[59] Advances in nerve transfer surgery. Journal of Hand Therapy. 2014. DOI: 10.1016/j.jht.2013.12.007
[60] Lésion de la branche motrice du nerf ulnaire après le canal de Guyon – diagnostic, options thérapeutiques et revue de la littérature. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2015.10.040
[63] Carpometacarpal dislocation producing transient motor neurapraxia of the ulnar nerve. Injury. 1997. DOI: 10.1016/s0020-1383(96)00207-0
[64] Updates on and Controversies Related to Management of Radial Nerve Injuries. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-17-00325
[66] Nerve Transfer to the Median Nerve Using Parts of the Ulnar and Radial Nerves in the Rabbit – Effects on Motor Recovery of the Median Nerve and Donor Nerve Morbidity. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.2000.0389
[67] Exam Of The Hand Wrist 2Ed. Skin incisions > Sensation.
[68] Functional Restoration Following Resection of Malignant Peripheral Nerve Sheath Tumour of the Median Nerve: A Case Report. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520720121
[69] The Triad of Multiple Metacarpal Fractures and/or Dislocations of the Fingers, Severe Hand Swelling and Clinical Evidence of Acute Median Nerve Dysfunction. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408087105
[70] Does MR Neurography Parameters Predict or Correlate With Clinical Recovery in Severe Carpal Tunnel Syndrome. HAND. 2016. DOI: 10.1177/1558944716660555fw
[72] Rockwood And Green S Fractures In Adults. 19: Principles of Nerve Injuries and Their Management > Open Injuries to the Hand and Wrist.
[74] The Tube Concept in Nerve Repair. Techniques in Hand & Upper Extremity Surgery. 1997. DOI: 10.1097/00130911-199706000-00008
[75] 10.1177-15589447251406719. n.d..
[76] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > NEUROVASCULAR ISLAND GRAFTS.
[77] Flexor tendon salvage and functional redemption using the hunter tendon implant and the superficialis finger operation. Journal of Hand Therapy. 1989. DOI: 10.1016/s0894-1130(89)80048-1
[78] The hand and the psyche. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80070-0
[80] Anatomic variations in sensory innervation of the hand and digits. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1171
[81] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[82] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[85] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[86] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[87] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[88] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.
[89] Exam Of The Hand Wrist 2Ed. The dorsal skin.
[90] Green S Operative Hand Surgery. PERTINENT ANATOMY.
[91] Exam Of The Hand Wrist 2Ed. The digital rays.
[95] A simple device for the objective evaluation of peripheral nerve injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90198-1
[99] Green S Operative Hand Surgery. Tendon Transfers for Median, Radial, and Ulnar Nerve Palsy > Nonoperative Treatment.
[100] Green S Operative Hand Surgery. Intraoperative Decisions and Priorities of Repair > Pan-Plexal Injury.
[102] Telerehabilitation After Zone 1 and 2 Flexor Tendon Repairs: Comparison With In-Person Therapy. HAND. 2025. DOI: 10.1177/15589447251339498
[104] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Radial nerve > Median nerve palsy.
[109] Anatomic study of the ramus communicans between the ulnar and median nerves. The Journal of Hand Surgery. 2000. DOI: 10.1053/jhsu.2000.16352
[124] Introduction neurolac® trial and the preliminary results. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80333-7
[132] Supercharged end-to-side anterior interosseous nerve transfer to restore intrinsic function in high ulnar nerve injury: a prospective cohort study. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07650-4
[137] Ulnar drift. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80081-6
[140] Simultaneous dislocation of both interphalangeal joints and flexor tendon tear in a finger. Injury. 1998. DOI: 10.1016/s0020-1383(97)00202-7
[141] Tendon transfers after peripheral nerve injuries: my preferred techniques. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419864838
[142] Protective distal finger splint. Journal of Hand Therapy. 1999. DOI: 10.1016/s0894-1130(99)80032-5
[144] A Reversed Digital Artery Island Flap for the Treatment of Fingertip Injuries. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90032-9
[149] The Anatomy of the Flexor Digitorum Superficialis Relevant to Tendon Transfers. Journal of Hand Surgery. 1991. DOI: 10.1016/0266-7681(91)90131-7
[150] Fast-track rehabilitation dans les SOS mains. Étude prospective sur la traumatologie fermée prise en charge par les rééducateurs. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.10.231
[151] Early mobilisation after flexor tendon repair. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1989. DOI: 10.1016/0266-7681(89)90150-2
[155] Tubulure de perfusion siliconée en lieu et place de tiges de Hunter dans la chirurgie secondaire des tendons fléchisseurs en zone 2 dans un environnement chirurgical à ressources limitées. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.074