Patients › Hand
指骨骨折
Phalangeal and metacarpal fractures of the hand — non-operative care and indications for fixation.
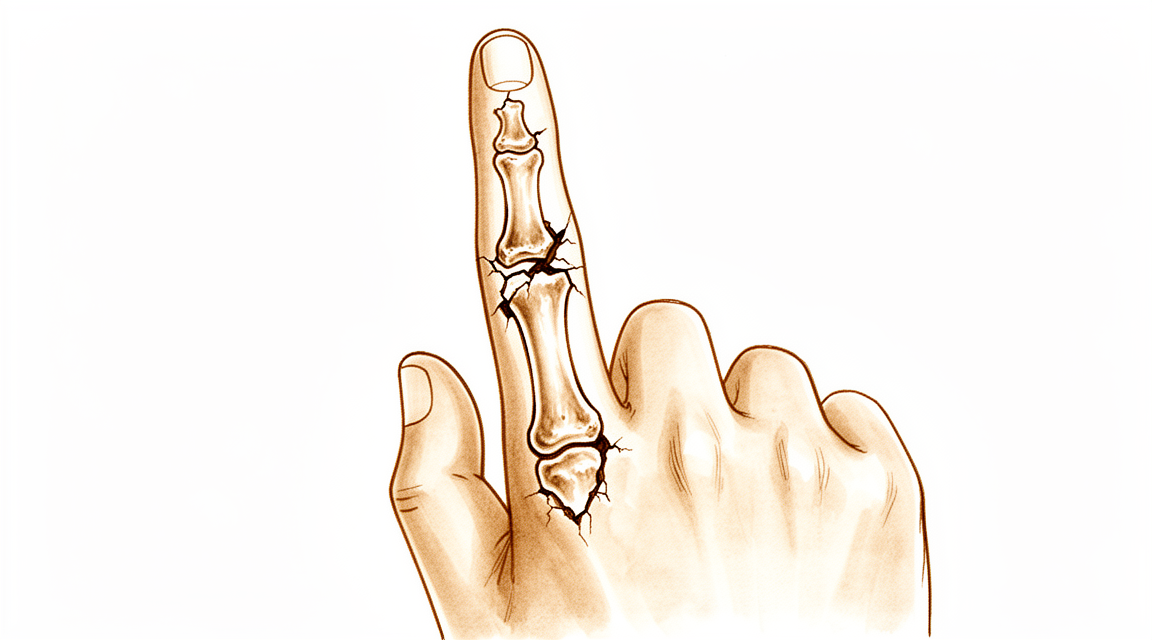
您的感受
手指骨折通常发生在明确的一瞬间。球戳到您的指尖、您跌倒时手着地,或者手指受到直接撞击。在那一刻,您可能会听到或感觉到“啪”的一声或断裂声。疼痛会立即出现,手指也会迅速肿胀。几小时内常常会出现瘀青。
受伤的手指可能看起来弯曲或扭转,也可能只是疼得无法活动。握拳时,您可能会注意到手指之间不再整齐对齐。在儿童中,同样的损伤常常发生在手指根部,而小指和拇指是最常受伤的部位。指尖被压伤可能使皮肤破损,有时指甲或指甲周围的皮肤会被撕裂。
在最初几天,当您试图弯曲手指或抓握时,疼痛最为剧烈。握笔、扣衬衫纽扣或转动门把手等简单动作都可能引起疼痛。早期疼痛常常会在夜间把您痛醒。在最初两到三周内,随着骨头开始长合,肿胀和疼痛会逐渐缓解。
有几个警示征象一旦出现就需要当天处理,而不是等到下次预约。如果受伤的手指或关节上方的皮肤破损、骨头外露,或手指明显变形,请当天前往急诊科。如果您的手指变得苍白、冰冷、发白或发青,或者受伤后手指突然失去感觉或无法活动,也同样需要当天前往急诊科。如果手指变得发热、发红、肿胀并疼痛,尤其是伴有发烧时,也需要当天接受急诊处理。以上任何一种情况都无需全科医生转诊。
如果疼痛在数周内没有缓解、逐渐加重,或使您无法用手或无法工作,请去看您的全科医生或要求专科评估。
实际发生了什么
手指骨折是指手指内部的一块小骨头发生断裂。每根手指有三块这样的骨头,拇指有两块。骨折通常发生在直接撞击、跌倒或运动损伤使骨头弯曲超过其承受极限时。有时会同时有不止一根手指骨折,而手腕或手部的骨骼也可能在同一次事故中受伤。
骨折的骨头可能保持对位,也可能移位。发生移位时,附着在这块骨头上的肌肉和肌腱会牵拉骨折块。肌腱是将肌肉连接到骨头上的索带,它们紧贴指骨走行,因此骨头一断裂,它们就会牵拉骨折碎片。正是这种牵拉使骨折的手指看起来弯曲或变短,也是在骨折块未对齐时手指无法正常抓握或伸直的原因。
您的身体会立即开始修复骨折。血液会聚集在骨折周围,骨头开始跨过断裂处重新长合,就像一根裂开的树枝长出新木质而愈合一样。问题在于,骨折附近的一切也会随之愈合。血液和肿胀会变成瘢痕组织,可能把肌腱粘连在骨头上。由于肌腱紧贴骨头,两者之间几乎没有任何间隔,即使骨折本身很轻微,也可能出现这种僵硬。这就是为什么一根骨头已经长合良好的手指,仍可能僵硬、弯曲缓慢。
如果骨折线延伸到指关节的关节面,原本光滑的滑动面就无法再对合,这会带来额外的问题。大多数手指骨折无需手术即可恢复,但有些骨折,尤其是移位或不稳定的骨折,需要借助外力在愈合期间保持固定。
我们如何处理
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会根据您的具体伤情匹配治疗方案。有些手指骨折无需手术即可愈合,另一些则需要在受伤后尽快手术,因此及时评估很重要。患者通常由全科医生(GP)转诊至我们的诊所;如果物理治疗师建议您就诊,您仍需获得全科医生的转诊,才有资格享受 Medicare 报销。在诊所,我们会询问病史,检查您的手部,并在必要时安排 X 光检查。X 光片可以显示骨头是否仍然对位、移位了多少,以及骨折线是否延伸到关节面。
大多数手指骨折无需手术即可治疗。如果骨头稳定或仅轻微移位,我们会在愈合期间用夹板或石膏将其固定。用于手指骨折的夹板通常让指根关节保持弯曲、手指关节保持伸直,并且可能让您的手腕可以自由活动。有些损伤则改用少量持续牵引来固定,这样无需手术就能让骨折碎片保持对位。用胶带把受伤的手指固定在相邻手指上是另一种支撑方法,这对许多儿童手指骨折效果很好。我们会在需要时通过复查影像来监测手指,并在骨折能够承受时分阶段让它活动起来。尽早活动很重要,因为即使骨头长合良好,固定太久的手指也会变僵。
当骨头严重移位、无法保持在原位,或骨折线延伸到指关节且关节面不再对合时,会从一开始就建议手术。有些类型的骨折始终需要手术,例如关节同时发生骨折和脱位,或儿童指甲附近的骨折且指甲下方的皮肤撕裂。您自身的需求也很重要:需要强大握力的技术工人,可能会与从事轻体力工作的人做出不同的选择。手术的目的是将骨折块固定在正确的位置,使手指在愈合期间可以活动。我们会与您讨论各种选择,包括每种方案对疼痛、僵硬以及手指最终外观和力量意味着什么,并共同做出决定。
无论您选择哪种方案,最初几周的情况都相似。止痛治疗让您在肿胀消退期间保持舒适。在骨头长合期间,您要保护手指免受碰撞和过度用力。手部治疗会在适合您伤情的阶段开始,通过练习恢复手指的弯曲和伸直,同时不干扰正在愈合的骨头。
预期情况
大多数手指骨折都能顺利愈合,但手指感觉恢复正常所需的时间,往往比骨头长合所需的时间更长。许多骨折在 4 周内长合,大多数在 5 至 9 周之间愈合。平均愈合时间约为 6 周。在这几周里,手指始终由夹板或石膏保护,疼痛和肿胀会稳步缓解。一旦骨折能够承受,活动能力会分阶段恢复。
您能恢复多少功能取决于骨折本身。手指小骨头的骨折通常恢复良好,大多数人到九周时就能恢复良好的功能。有些类型更难恢复:靠近指关节的骨折、碎成数块的骨折,以及周围皮肤严重受损的骨折,可能使手指比您期望的更僵硬或更无力。僵硬是治疗后最常见的问题,即使骨头已经完美长合也可能出现。这就是为什么只要安全,我们都会尽早活动您的手指,也是手部治疗如此重要的原因。
在恢复过程中,有几种情况可能会出问题。有时骨头长合缓慢,或者根本不长合。有时骨头在不良位置长合,这可能会限制手指弯曲和伸直的幅度。如果靠近指关节的骨折愈合时没有对齐,该关节可能会失去弯曲和伸直的活动度。正因为存在这些问题,您的外科医生会在愈合期间通过 X 光检查手指,遵守夹板或石膏的使用指示也因此很重要。
手术后,骨头会用钢针、螺钉或小钢板固定在位,使手指能够更早开始活动。大多数人能恢复良好的活动度和握力,许多人会在手指情况允许时恢复平时的工作和活动。术后的手部治疗由 Extend Rehabilitation 的 Ruby Doolan 负责。Ruby 会指导您的练习,并在康复过程中为您制作所需的任何夹板。
如果疼痛或僵硬在数周内没有缓解、逐渐加重,或使您无法工作或无法用手,请去看您的全科医生或要求专科评估。
何时就医
如果您的手指明显弯曲或扭转、受伤处上方的皮肤破损、骨头外露、手指变得苍白、冰冷、发白或发青,或者手指突然失去感觉或无法活动,请寻求紧急救治。如果手指变得发热、发红、肿胀并疼痛,尤其是伴有发烧时,也需要当天接受急诊处理。以上任何一种情况都无需全科医生转诊。如果您联系不上诊所,请前往离您最近的急诊科。
如果疼痛在数周内没有缓解、逐渐加重,或在骨头愈合期间肿胀、活动或握力没有逐周改善,请去看您的全科医生或要求专科评估。有些手指损伤起初看起来很轻微,但仍需要适当评估,因此任何疼痛、肿胀或活动不正常的手指都值得检查,而不是一味等待。
深入探讨
Advanced reading: the deeper science (optional)
本节内容超出了您自身治疗决策所需的范围。指骨骨折值得额外阅读,因为有两项发现与常规做法相悖:预防性抗生素似乎对开放性指尖骨折并无益处;而对于中间指关节处的困难关节骨折,目前尚无固定方法被证明优于其他方法。
开放性指尖骨折使用抗生素并不能降低感染率
远节指骨开放性骨折,即骨骼经伤口暴露,通常由挤压伤所致,通常基于“开放性骨折需要抗生素”的一般原则,常规给予预防性抗生素。
现有证据在此处并不支持这一做法。在 353 名患者中,研究结果未能显示预防性抗生素对开放性远节指骨骨折后浅表感染率有任何影响,作者得出结论,重点应放在及时的冲洗和清创,而非使用预防性抗生素 [1]。
其区别在于清洁伤口与药物治疗伤口。机械性去除污染物才是降低感染的关键;在此情境下,抗生素并未被证明能在此基础上进一步降低感染风险。鉴于不必要的抗生素使用所带来的成本,了解在彻底伤口护理后省略抗生素是基于证据而非疏忽,这一点值得注意。
对于中间关节的骨折脱位,没有任何一种技术占优
近端指间关节的骨折脱位是手部较难处理的损伤之一,该关节较小,骨折面既需要复位,又需要在活动过程中维持复位状态。
在735例患者中,比较结果具有启发性,恰恰因为它未能区分各选项:经皮固定获得了最高的术后活动范围,伸展位阻挡钉固定获得了最大的握力,且没有任何一种治疗方法或骨折类型能持续优于其他方法或类型 [2]。
当关节面受累超过一半时,一种重建选项是使用钩骨植骨进行重建。在235例患者中,半钩骨关节成形术被证明可靠且有效,可提供症状缓解和功能恢复 [3]。
僵硬才是真正的敌人
这些损伤之所以棘手,并非因为骨折不愈合,指骨骨折通常能顺利愈合。问题在于手指会僵硬。
屈肌腱和伸肌腱紧贴骨面走行,其间软组织极少,因此骨折周围的血液和肿胀会机化形成瘢痕,将肌腱与骨面粘连。这一过程在数周内便已显著进展,一旦形成便难以逆转。
正因如此,只要骨折足够稳定,指骨骨折应尽早开始活动;选择固定方式时,部分考量在于其是否允许活动,而非仅取决于其固定骨骼的刚性。这也解释了看似矛盾的现象:X光片显示骨折完美愈合,但手指却无法弯曲——骨骼从来不是问题所在。
参考文献
[1] Metcalfe D, Aquilina AL, Hedley HM. 开放远节指骨骨折的预防性抗生素使用:系统评价与荟萃分析. J Hand Surg Eur Vol. 2015;41(4):423-30. https://doi.org/10.1177/1753193415601055
[2] Demino C, Yates M, Fowler JR. 近端指间关节骨折脱位的手术治疗:系统评价. Hand (N Y). 2019;16(4):453-60. https://doi.org/10.1177/1558944719873152
[3] Faulkner H, Graham DJ, Hile M, Lawson RD, Sivakumar BS. 半钩骨关节成形术治疗中节指骨基底骨折:系统评价. Hand (N Y). 2021;18(2):300-6. https://doi.org/10.1177/15589447211014623
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Recent PIP joint fractures present challenges in both diagnosis and treatment, with final outcomes significantly impacting global finger and hand function [1].
- Most pediatric hand fractures are treated nonoperatively with good results [2].
- A subset of pediatric phalangeal fractures requires prompt recognition and surgical intervention to minimize complications [2].
- The majority of hand fractures can be treated without surgery [3].
- Surgery offers distinct advantages in properly selected cases of hand fractures [3].
- Good or excellent function was achieved in 94% of metacarpal fractures treated with external fixation by nine weeks [4].
- Good or excellent function was achieved in 85% of phalangeal fractures treated with external fixation by nine weeks [4].
- No differences in outcome were observed between dorsal and lateral plate fixation for finger proximal phalangeal fractures [5].
- Approximately one quarter of open finger fractures will likely need more than one surgical procedure [6].
- The need for multiple surgical procedures in open finger fractures is especially common in more severely injured fingers, due to crush or with vascular impairment [6].
- Results from external fixation of closed metacarpal and phalangeal fractures were similar to those obtained in the management of stable and undisplaced fractures [7].
- Indications for surgical treatment of finger fractures are more clearly defined than previously [8].
- Operative techniques and implants for osteosynthesis of finger fractures are continuing to evolve and improve [8].
- Results for finger fracture treatment vary according to fracture type, surgeon experience, and patient compliance [8].
- It is recommended that all finger fractures should be assessed and treated by surgeons with training in the management of hand injuries [9].
- Conservative functional techniques are the optimum treatment for the majority of patients with single metacarpal fractures [10].
- All six fingers in a study of intramedullary fixation through a volar extra-tendon sheath approach obtained satisfactory union of proximal phalangeal fractures [11].
- No patient complained of pain at the final follow-up in a study of intramedullary fixation through a volar extra-tendon sheath approach [11].
- Open finger fractures formed the majority of the workload of open fractures at a specific trauma centre [12].
- Open finger fractures usually required simple treatments only [12].
- Traction splinting has been shown to be successful in the treatment of closed proximal phalangeal fractures [13].
- Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation after vascular reconstruction [14].
- The likelihood of unplanned reoperation for thumb and index finger injuries may guide initial treatment decision-making and postoperative follow-up [14].
- Miniature plates and screws are applicable for selected unstable metacarpal and phalangeal fractures of certain configurations [17].
- Miniature plate fixation showed to be safe and effective when used for treatment of extra-articular metacarpal and proximal phalangeal fractures [19].
- Most pediatric phalangeal fractures can be treated nonsurgically [22].
- A small subset of pediatric phalangeal fractures benefits from surgical intervention [22].
- Screw fixation is suggested to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalanx fractures of the long fingers [23].
- The Ichi-Fixator system is a definitive treatment option for managing various phalangeal fractures [28].
- Taping finger fractures can be recommended irrespective of the degree of displacement or the need for reduction in children [44].
- Intramedullary fixation approaches have been reviewed for metacarpal fractures, phalangeal fractures, and interphalangeal joint arthrodesis [55].
- Percutaneous compressive bone tie was used to treat two intraarticular proximal phalangeal fractures of the thumb with satisfactory outcomes [68].
- Full range of movements was achieved within 3 weeks in a study using percutaneous compressive bone tie for thumb phalangeal fractures [68].
- No complications were reported in a study using percutaneous compressive bone tie for thumb phalangeal fractures [68].
- No need for implant removal was reported in a study using percutaneous compressive bone tie for thumb phalangeal fractures [68].
Anatomy & Pathophysiology
Bony Anatomy
- All phalanges consist of a proximal base, a central diaphysis, and a distal head [52].
- In contrast with the metacarpals, the bases of all the phalanges and not the heads develop as metaphyses [52].
- The distal portion of the distal phalanx is referred to as the tuft [52].
- Fingers usually follow a typical pattern of relative lengths where the tip of the index finger extends to the base of the nail of the middle finger, the tip of the ring finger to the mid-aspect of the middle finger nail, and the tip of the small finger to a corresponding point [52].
- The length of the metacarpal and the phalanges of the same finger resembles the series of Fibonacci [79].
- In complex flexion, a finger describes an equiangular spiral [79].
- The articulations of the fingers form a triarticular chain that flexes toward the thumb and the palm to allow grasp [79].
- The interphalangeal articulations of the digits function uniquely in flexion–extension and their trochlear-shaped articulations are closely congruent throughout excursion of motion [79].
- The normal finger phalangeal joint surfaces are congruent throughout the arc of motion of the interphalangeal joints [52].
- The third and fourth metacarpal heads help stabilize the metacarpal arch by providing attachments for the transverse metacarpal ligament [18].
- The proximal phalanx of either the middle or the ring finger is important functionally because its absence creates a hole through which small objects can pass and impairs scooping maneuvers [18].
- The small finger plays an important role in palmar grip because of the mobility of its CMC joint and the action of the hypothenar muscles [33].
- The small finger increases the span of the hand for grasp owing to its abduction moment [33].
- The ring finger forms the keystone of the palmar arch and participates in power grip [48].
- The ring finger plays a minimal role in precision pinch [48].
Joint Anatomy & Ligaments
- The articulations of the digits have two firm collateral ligaments and a thick reinforced anterior capsule, the anterior fibrocartilage, also known as the volar plate [79].
- The fibrous dorsal capsule of the digit articulations is thin and lax [79].
- The interphalangeal joint is a stable uniaxial hinge joint [79].
- Flexion of the metacarpophalangeal joint is about 85 degrees [79].
- Flexion of the proximal interphalangeal joint is about 115 degrees [79].
- Flexion of the distal interphalangeal joint is 80 degrees [79].
- The index finger is capable of less flexion than the other fingers because it opposes the thumb [79].
- The normal ulnar inclination of the fingers occurs at the metacarpophalangeal joints [84].
- Ulnar inclination is most marked in the index finger, less in the middle and little fingers, and almost non-existent in the ring finger [84].
- The ulnar inclination is due to anatomical factors including asymmetry of the metacarpal heads and collateral ligaments, tendon crossing on the ulnar side, intrinsic muscle predominance, and forward displacement of the ulnar metacarpals [84].
- The ulnar inclination is normally limited by capsuloligamentous resistance at the MP joints and by the action of the interosseous muscles [84].
- The dislocation of the carpometacarpal joint of the little finger causes rupture of the hamatometacarpal and intermetacarpal ligaments [65].
- The dislocation of the carpometacarpal joint of the little finger leaves intact the deep transverse metacarpal ligament and the extensor and flexor carpi ulnaris tendons [65].
Soft Tissue & Tendon Anatomy
- The extensor tendons pass from the forearm onto the dorsum of the hand through six compartments beneath the extensor retinaculum [83].
- The first compartment contains the extensor pollicis brevis and the abductor pollicis longus [83].
- The second compartment contains the extensors carpi radialis longus and brevis [83].
- The third compartment contains the extensor pollicis longus [83].
- The fourth compartment contains the four tendons of the extensor digitorum communis plus the extensor indicis proprius [83].
- The fifth compartment contains the extensor digiti quinti [83].
- The sixth compartment contains the extensor carpi ulnaris [83].
- The interosseous muscles produce lateral movements of fingers through their insertions on the lateral aspect of the base of the proximal phalanges [89].
- When the metacarpophalangeal joint is in extension, the interosseous muscles extend the distal phalanges [89].
- When the metacarpophalangeal joint is in flexion, the interosseous muscles reinforce flexion of the proximal phalanx and lose their extensor action on the distal phalanges [89].
- The lumbrical muscles are able to extend the two distal phalanges whether the metacarpophalangeal joint is in extension or flexion [89].
- The lumbricals participate in extension of the distal phalanges by pulling distally on the flexor profundus tendon when this muscle is at rest [89].
- The palmar skin is anchored to the underlying fascial planes by a system of fibrous tracts [80].
- The palmar skin adheres closely to the aponeurosis in the mid-palmar area [80].
- In all other areas, the deep aspect of the skin is separated from the superficial palmar fascia by a layer of fatty tissue divided into compartments by fibrous septa [80].
- The metacarpophalangeal pad sits transversely over the base of the fingers from the ulnar to the radial border of the hand [80].
- The pulp has a lobulated palmar pad where fibrous septa join the periosteum of the distal phalanx to the deep aspect of the dermis [80].
- The cutaneous striations that make up fingerprints reflect the arrangement of the papillary ridges of the underlying dermis [80].
- The concentric arrangement of striae at the pulp ensures the presence of a group of striae perpendicular to the force exerted, whatever its direction [80].
- The soft tissue of the fingertips is tightly anchored [81].
- The soft tissue of the fingers between the fingertips and the area of the aponeurosis is mobile and flexible [81].
- The mobile soft tissue of the fingers overlies the fibrous tendon sheaths and extends from the distal phalanges to the metacarpophalangeal joints [81].
- The midlateral finger incision allows the neurovascular bundle to be carried volarward with the volar flap of the incision [47].
- On the radial sides of the index and middle fingers and on the ulnar side of the little finger, the dorsal branch of the digital nerve should be preserved if possible [47].
Pathophysiology & Mechanism of Injury
- Intrinsic and extrinsic tendon insertions act as deforming forces to create typical angulation patterns in phalangeal fractures [52].
- Proximal and middle phalangeal shaft fractures typically collapse into apex volar angulation because of the proximal flexion moment of the intrinsics and distal extensor moment of the extensor mechanism [52].
- Intraarticular fractures that disrupt joint congruency can occur at either the distal (condylar fracture) or proximal (pilon or proximal condylar fracture) articular surface [52].
- Most commonly, intraarticular phalangeal fractures are produced by an axial loading injury [52].
- Fractures of the proximal phalangeal shaft typically exhibit an apex palmar angulation with the fracture gap wider volarly and compressed dorsally [36].
- The intrinsic muscles flex the proximal fragment of a proximal phalangeal shaft fracture, whereas the distal fragment is extended by the attachment of the central slip to the dorsal lip of the middle phalanx [36].
- The axis of rotation of proximal phalangeal fractures lies on the fibro-osseous border of the flexor tendon sheath [36].
- The moment arm from the rotational axis of the fracture site to the extensor tendon is greater than that to the flexor tendon [36].
- Fracture hematoma permeates the zone of injury and incites a proliferative fibroblastic response of the multiple surrounding collagenous structures [36].
- Scar tissue tends to involve all of the structures within the zone of injury, producing adherence between the bone and the adjacent tendons, joint capsule, and ligaments [36].
- Adhesions formed between the extensor mechanism and the fracture may result in loss of extensor glide [36].
- The mallet finger deformity is characterized by a loss of active distal interphalangeal joint extension with full passive ROM evident [61].
- The mallet finger reflects the loss of normal extensor force transmission via the terminal tendon insertion onto the distal phalanx [61].
- The unopposed flexor digitorum profundus pulls the distal joint into flexion in mallet finger [61].
- The usual mechanism of injury for mallet finger involves sudden passive flexion of the actively extended distal interphalangeal joint [61].
- Disruption of the terminal tendon in mallet finger may be entirely confined to the tendon or may involve an avulsed fracture fragment from the dorsal lip of the distal phalanx proximal articular surface [61].
- The forces of the extensor digitorum communis and of the flexor superficialis on the middle phalanx have a component that produces extension of the proximal phalanx [89].
- The intrinsic muscles (lumbrical and interossei) normally oppose the extension force on the proximal phalanx produced by extrinsic tendons [89].
- When intrinsic muscles are paralyzed, no force exists to prevent the proximal phalanx from swinging into hyperextension if the extensor digitorum communis and flexor superficialis are active [89].
- Shortening and closing an injury that leads to proximal migration of the FDP from its insertion at the base of the distal phalanx may result in a lumbrical-plus finger [31].
- In a lumbrical-plus finger, the FDP tendon retracts and creates tension on the extensor mechanism through the lumbrical that originates off the FDP tendon, causing paradoxical IP joint extension with active digit flexion [31].
- The "jammed" finger with a swollen, painful PIP joint usually involves a volar plate injury or small nondisplaced avulsion fracture off the volar base of the middle finger epiphysis [29].
- Salter-Harris II fractures of the digits are an extremely common hand fracture with the little finger proximal phalanx being the most commonly injured [29].
- Salter-Harris II fractures of the digits usually occur because of a jamming or hyperextension injury to the finger resulting in an abduction deformity [29].
- Malrotation in Salter-Harris II fractures does not remodel and can result in problems with grip formation [29].
- Seymour fractures are a Salter-Harris I/II or juxtaphyseal fracture of the distal phalanx with interposed nail bed at the fracture site [29].
- Seymour fractures are open fractures but are often missed [29].
- Missed Seymour fractures have a high rate of complication including infection and nail or physeal growth disturbance [29].
- The key to diagnosis of Seymour fractures is disruption of the nail plate/cuticle as well as a displaced fracture of the distal phalanx on radiographs [29].
- Displaced phalangeal neck fractures require reduction and pin fixation which can usually be achieved through a closed fashion [29].
- Condyle fractures can often also be treated with closed reduction and pinning [29].
- Open procedures for condyle fractures increase a risk for osteonecrosis [29].
- The dislocation of the carpometacarpal joint of the little finger results in fixed supination of the finger, disturbing the normal axis of movement and weakening power grip if treatment is delayed [65].
- This deformity may be obscured by swelling and bruising on the ulnar border of the hand [65].
- Palmar dislocation of the metacarpophalangeal joint is a rare injury where the mechanism is likely hyperextension force applied during strong active flexion [127].
Classification
- Type I phalangeal neck fractures are defined as undisplaced fractures [148].
- Type II phalangeal neck fractures are defined as displaced fractures where the distal fragment maintains some bone-to-bone contact with the proximal fragment [35, 148].
- Type III phalangeal neck fractures are defined as displaced fractures with loss of bone-to-bone contact between the proximal and distal fragments at the fracture site [35].
- A minimally displaced phalangeal neck fracture should be classified as Type II rather than Type I [148].
- Salter-Harris type II fractures of the proximal phalanx are the most frequent phalangeal fractures in children [74].
- Type II D phalangeal neck fractures tend to occur in young children and the majority involve the middle phalanx [146].
Clinical Presentation
Epidemiology and Demographics
- Fractures of the finger phalanges account for about 10% of all fractures seen [42].
- Finger phalangeal fractures are the second most common fracture in males [42].
- The little and ring fingers are the most affected by finger phalangeal fractures [42].
- The prevalence of little finger phalangeal fractures is 32.5% [42].
- The prevalence of ring finger phalangeal fractures is 25.8% [42].
- The prevalence of thumb phalangeal fractures is 18.4% [42].
- The prevalence of middle finger phalangeal fractures is 14.3% [42].
- The prevalence of index finger phalangeal fractures is 9.0% [42].
- Direct blow or assault is the most common mode of injury for finger phalangeal fractures, accounting for 39.1% of cases [42].
- Falls from standing height account for 29.5% of finger phalangeal fractures [42].
- Sports injuries account for 23.8% of finger phalangeal fractures [42].
- Approximately 70% of all phalangeal and metacarpal fractures occur in patients between the ages of 11 and 45 years [52].
- Phalangeal fractures are more common in men than women [52].
- Hand and finger fractures are the second most common fracture presenting to emergency departments in the pediatric population [29].
- Pediatric hand and finger fractures have a bimodal age distribution with peaks at 0 to 2 years of age and 12 to 16 years of age [29].
- The most commonly injured location in pediatric hand fractures is the base of the proximal phalanx, accounting for 67% of cases [29].
- In pediatric hand fractures, the little finger is the most commonly injured border ray at 52.2% [29].
- In pediatric hand fractures, the thumb is the second most commonly injured border ray at 23.5% [29].
- Open fractures of the phalanges are relatively common, with the highest prevalence seen in 36- to 64-year-old males [42].
- The distal phalanges are the most common site for open phalangeal fractures, with 25.3% of fractures at this site being open [42].
- About 55% of patients with multiple phalangeal fractures have other phalangeal fractures as the associated injury [42].
- The average age of patients presenting with multiple phalangeal fractures is 55.4 years [42].
Mechanism and Injury Patterns
- Proximal and middle phalangeal shaft fractures typically collapse into apex volar angulation due to the proximal flexion moment of the intrinsics and distal extensor moment of the extensor mechanism [52].
- Intraarticular phalangeal fractures that disrupt joint congruency are most commonly produced by an axial loading injury [52].
- The classic "jammed" finger with a swollen, painful PIP joint usually involves a volar plate injury or small nondisplaced avulsion fracture off the volar base of the middle finger epiphysis [29].
- Phalangeal neck and condyle fractures have a similar presentation to a simple "jammed" finger and are often missed [29].
- Toddlers and preschool age children usually sustain hand injuries while at home, usually as a crush injury [29].
- Adolescents most often get injured outside the home with sporting activities [29].
- A spiral fracture of the proximal phalanx of the index finger can result from finger wrestling [25].
- Severe mincer injuries carry a potential risk of damaging vital structures if the caught hand is freed by rotating the handle in the reverse direction [27].
- Punch injuries commonly occur in road traffic accidents and are usually associated with other serious injuries of the hand, wrist, and distal forearm [58].
Clinical Examination and Diagnosis
- Appropriate evaluation of hand and finger fractures includes clinical examination and radiographs [29].
- Clinical examination must assess for open injuries and angular and rotational malalignment of the injured ray [29].
- Rotational alignment can be confirmed by ensuring that all fingers point to the scaphoid tubercle when the fingers are flexed [29].
- Radiographs should include PA, lateral, and oblique views of the injured location [29].
- The coronal plane deformity in Salter-Harris II fractures is easy to assess, but extra care must be taken to assess for rotational deformity, which is not as obvious on radiographs [29].
- Prolonged immobilization of simple "jammed" finger injuries can result in significant joint stiffness [29].
- Seymour fractures are open fractures that are often missed [29].
- The key to diagnosing Seymour fractures is disruption of the nail plate/cuticle, which indicates disruption of the nail bed and the likelihood of an open fracture with interposed tissue [29].
- Radiographs for Seymour fractures reveal a displaced fracture of the distal phalanx [29].
- A meticulous examination of the patient’s hand is required for injury diagnosis [52].
- Open finger fractures formed the majority of the workload of open fractures at a trauma centre but usually required simple treatments only [12].
- Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation, which may guide initial treatment decision-making and postoperative follow-up [14].
Pediatric Specifics
- Most pediatric phalangeal fractures can be treated nonsurgically, but a small subset benefits from surgical intervention [22].
- Most phalangeal neck fractures in children less than 3 years old obtained satisfactory results [16].
- Articular fractures of the fingers in children often result in sequelae, with a rate as high as 50% when the fracture was displaced initially [21].
- Complications of distal phalanx fractures in children are frequent [100].
- Avascular necrosis following phalangeal neck fractures usually affects the little finger and presents with stiffness [57].
- Further surgery is not often required short term for avascular necrosis following phalangeal neck fractures in children [57].
- Salter-Harris II fractures of the digits are an extremely common hand fracture in children, with the little finger proximal phalanx being the most commonly injured [29].
- Treatment for Seymour fractures involves removal of the nail plate with débridement of the fracture site, extrication of the interposed nail bed, and reduction of the fracture [29].
- If a Seymour fracture is unstable, it may require Kirschner wire placement in addition to immobilization in splint/cast [29].
- Antibiotics are a necessity to prevent infection in Seymour fractures as these are open fractures [29].
- Recommended antibiotic treatment for Seymour fractures includes a dose of IV antibiotic in the emergency department followed by a 7- to 10-day course of oral antibiotic [29].
- A first-generation cephalosporin is the preferred antibiotic for Seymour fractures [29].
- Displaced phalangeal neck fractures in children require reduction and pin fixation which can usually be achieved through a closed fashion [29].
- Condyle fractures in children can often be treated with closed reduction and pinning [29].
- Open procedures for condyle fractures increase a risk for osteonecrosis, so all attempts should be made for early diagnosis and treatment [29].
- In a retrospective review of 105 pediatric patients treated with closed reduction pin fixation of a displaced proximal phalanx fracture, the average age was 11 years [29].
- The complication rate for closed reduction pin fixation of displaced proximal phalanx fractures in children was 4.8%, including infection, pin site complication, and malunion [29].
- Thirty-six of 105 pediatric patients had postoperative stiffness, with 31 requiring therapy [29].
- Phalangeal neck fractures had the highest rate of postoperative stiffness in pediatric patients treated with closed reduction pin fixation [29].
- Thirty-one pediatric patients available for follow-up at 1 year or greater reported return of full motion, no pain, and happiness with function and appearance [29].
- Despite 22% (7 of 31) of pediatric patients having a measurable coronal plane deformity on radiograph, they reported full motion and satisfaction at follow-up [29].
Adult Specifics
- The majority of hand fractures can be treated without surgery, though surgery offers distinct advantages in properly selected cases [3].
- Most hand fractures can be managed successfully without operation, and conservative functional techniques are the optimum treatment for the majority of patients with single metacarpal fractures [10].
- Recent PIP fractures are challenging trauma in terms of diagnosis as well as treatment, with the final outcome having a considerable impact on global finger and hand function [1].
- A quarter of open finger fractures will likely need more than one surgical procedure, especially in more severely injured fingers, due to crush or with vascular impairment [6].
- Phalangeal neck fractures of the proximal phalanx in adults are rare with limited options for unstable fractures [62].
- Fractures of the fingers are better understood, indications for surgical treatment are more clearly defined, and operative techniques and implants for osteosynthesis are continuing to evolve and improve [8].
- Results for finger fractures vary according to fracture type, surgeon experience, and patient compliance [8].
- The primary goals of phalangeal fracture treatment are to restore anatomy and preserve function [54].
- Lost productivity attributed to phalangeal fractures exceeds 2 billion every year, making early return to activities a key goal [54].
- The preferred method of treatment for phalangeal fractures is one that offers limited soft tissue damage and enables mobilization of the injured digit(s) as soon as fracture stability permits [54].
- Operative treatment for phalangeal fractures is reserved for unstable fractures or those creating unacceptable articular incongruity [54].
- Complications such as nonunion, malunion, infection, and stiffness can occur even in the setting of appropriate surgical treatment for phalangeal fractures [54].
- There are two major causes of PIP joint extensor lag following proximal phalangeal fractures: soft tissue adhesions and persistent skeletal deformity [36].
- Fracture hematoma permeates the zone of injury and incites a proliferative fibroblastic response of the multiple surrounding collagenous structures that is proportionate to injury severity [36].
- Simple fractures caused by low-energy injuries occasionally may be complicated by some measure of permanent stiffness as a result of soft tissue adhesion [36].
- When adjacent flexor or extensor tendon injury accompanies a proximal phalangeal fracture, the difficulty of treatment and achieving a favorable outcome may be compounded substantially [36].
- Surgical treatment for proximal phalangeal fractures requires a second "planned injury," superimposing further soft tissue injury and increasing the risk of soft tissue adhesions [36].
- The intrinsic muscles flex the proximal fragment, whereas the distal fragment is extended by the attachment of the central slip to the dorsal lip of the middle phalanx [36].
- Phalangeal fractures tend to deteriorate total active motion (TAM) more than metacarpal fractures [39].
- Pain in the post-operative week predicts pain and hand use twelve weeks after proximal phalangeal fracture fixation [34].
- In a study of proximal phalangeal fractures, 52% of fractures were little fingers, 40% were intra-articular, and 46% were in the dominant hand [34].
- The mean age of patients in a study on post-operative pain after proximal phalangeal fracture fixation was 35 years, with 75% being male [34].
- Extension lags of the PIP joints were found in 67% of all fractured fingers treated with plate fixation for extra-articular proximal phalanx fractures [60].
- At 6 weeks postoperatively, an average TAM of 183° was found in patients treated with plate fixation for extra-articular proximal phalanx fractures [60].
- At final follow-up, an improved average TAM of 213° was found in patients treated with plate fixation for extra-articular proximal phalanx fractures [60].
- In a study of conservative management of proximal phalangeal fractures in an A&E department, 147 of 242 phalangeal fractures (61%) involved the proximal phalanx [49].
- Proximal phalangeal fractures formed 7% of all hand fractures and 0.3% of all attendances in a study of A&E patients [49].
- The results achieved with external fixation for closed metacarpal and phalangeal fractures were similar to those obtained in the management of stable and undisplaced metacarpal and phalangeal fractures [7].
- No differences in the outcome of finger proximal phalangeal fractures treated by dorsal and lateral plate fixation were observed [5].
- All six fingers obtained satisfactory union of the fractures, and no patient complained of pain at the final follow-up in a study of intramedullary fixation of proximal phalangeal fractures through a volar extra-tendon sheath approach [11].
- A mini external fixator constructed from readily available materials is another tool available to the hand surgeon treating fractures of the hand and phalanges [38].
- The Joshi's External Stabilization System (JESS) has had extensive use in the management of hand injuries [63].
- Hand fractures require excellent communication between the surgeon and therapist to progress the patient through the course of therapy [41].
- These findings underscore the importance of careful assessment and management of nail bed injuries and fracture healing when treating distal phalanx fractures [96].
- The patient returned to his previous activity level but demonstrated a residual deficit in thumb IP joint flexion with follow-up radiographic evidence of a healed fracture and a physis that remains open in a case of Salter-Harris Type III fracture of the distal phalanx [24].
Investigations
Imaging and Diagnostic Modalities
- A true lateral radiograph is required for the accurate diagnosis of carpometacarpal fracture-dislocations because swelling can obscure the deformity [108].
- Loss of parallel joint surfaces at the carpometacarpal articulations on a posteroanterior radiograph is indicative of carpometacarpal fracture-dislocation [108].
- Computed tomography scans are beneficial for determining the extent of joint surface involvement in carpometacarpal injuries and guiding appropriate intervention [108].
- Ultrasonography may provide greater accuracy in fracture diagnostics by revealing small avulsed bony fragments missed on radiographs [155].
- Ultrasonography can be beneficial in diagnosing occult fractures, especially in children [155].
- Quantitative 3DCT analysis of fracture fragments provides useful information that could facilitate surgery and analysis of complex fractures of the base of the middle phalanx [156].
Clinical Examination
- The coronal plane deformity of Salter-Harris II fractures is easy to assess, but extra care must be taken to assess for rotational deformity, which is not as obvious on radiographs [29].
- Malrotation does not remodel and can result in problems with grip formation [29].
- The key to diagnosing Seymour fractures is disruption of the nail plate/cuticle as well as a displaced fracture of the distal phalanx on radiographs [29].
- Disruption of the nail bed indicates the likelihood of an open fracture with interposed tissue in Seymour fractures [29].
Treatment
General Principles
- Recent PIP fractures present diagnostic and treatment challenges where final outcome significantly impacts global finger and hand function [1].
- Fractures of the fingers are better understood, indications for surgical treatment are more clearly defined, and operative techniques and implants for osteosynthesis are continuing to evolve and improve, though results vary according to fracture type, surgeon experience, and patient compliance [8].
- The preferred method of treatment is one that offers limited soft tissue damage and enables mobilization of the injured digit(s) as soon as fracture stability permits [54].
- In general, operative treatment is reserved for unstable fractures or those creating unacceptable articular incongruity [54].
- Optimal outcome from surgical treatment demands appropriate surgical plan, atraumatic soft tissue handling, and stable fixation to facilitate early motion; however, complications such as nonunion, malunion, infection, and stiffness can occur even in the setting of appropriate treatment [54].
- A management algorithm proposes that if a fracture is deemed stable, nonoperative management is recommended [116].
- A finger undergoing any type of surgery is likely to be stiffer than one that was treated nonoperatively [116].
- If a fracture is deemed stable yet not quite enough to begin early active range of motion, it is reasonable to delay motion for an additional week or two [116].
- A fracture that did not undergo surgery and progressed more slowly to allow for adequate fracture healing is still better than one that underwent surgery followed by an early range of motion protocol [116].
Non-Operative Management
- The majority of pediatric hand and finger fractures can be treated with closed reduction, appropriate immobilization, and early motion [29].
- Well-reduced, minimally angulated, or nonangulated fractures of the proximal phalanges of the fingers can be effectively treated using functional casts without immobilizing the wrist [122].
- A non-invasive technique using a thermoplastic traction platform is safe and effective in the management of proximal phalangeal fractures [140].
- Traction splinting presents a method for noninvasive management of angulated and rotated phalanx fractures [138].
- Buddy taping is a non-inferior treatment modality for most paediatric finger fractures compared to splint immobilization [105].
- Taping paediatric finger fractures can be recommended irrespective of the degree of displacement or the need for reduction [44].
- Nonsurgical treatment is supported for closed and displaced mallet finger fractures with greater than one-third articular surface involvement [69].
- For a closed extensor tendon rupture from its insertion into the distal phalanx, the treatment usually is nonsurgical [73].
- The distal interphalangeal joint is constantly held in hyperextension on a splint for 6 to 8 weeks and at night only for 2 to 4 additional weeks to allow tendon healing and prevent stretching [73].
- Splint treatment within 2 weeks of injury has been found to be as effective as splinting more than 4 weeks after injury for mallet finger [73].
- This treatment can be successful in some patients 3 months after injury for mallet finger [73].
- High patient satisfaction was reported at an average of 5 years after splint treatment of mallet deformities, with and without fracture [73].
- Osteoarthritic changes were seen in 48% of mallet finger cases treated with splinting, usually associated with fractures [73].
- Mallet finger deformities in children caused by traumatic separation of the epiphysis can be treated with early detection, straightforward reduction with hyperextension of the distal interphalangeal joint, and splinting for 3 to 4 weeks [73].
- Antibiotics are a necessity to prevent infection for Seymour fractures, with recommended treatment including a dose of IV antibiotic in the emergency department followed by a 7- to 10-day course of oral antibiotic [29].
- The classic “jammed” finger involving a volar plate injury or small nondisplaced avulsion fracture off the volar base of the middle finger epiphysis does not require surgical intervention [29].
- Jammed fingers should be splinted in approximately 30° of flexion for a week followed by 3 weeks of buddy tape to allow for healing [29].
- For transverse metacarpal fractures of the shaft and neck, historically patients were left to mobilize freely and healed with some deformity but good function [103].
- Barton (1984) showed the efficacy of plaster or splint support to reduce the angulation of transverse metacarpal shaft fractures [103].
- For metacarpal neck (boxer’s) fractures, acceptable flexion malunion has been variously suggested as 50° to 60°, 30°, and 20° [103].
- For little finger metacarpal shaft fractures, acceptable angulation has been suggested as 30° [103].
- A Cochrane review has shown there is no good evidence that more marked malunion causes reduced hand function or unacceptable deformity for metacarpal fractures [103].
- The outcome of non-operative treatment for metacarpal fractures is typically an excellent functional outcome apart from a mild cosmetic abnormality [103].
- No one technique of non-operative management has been shown to be superior in the published studies for metacarpal fractures [103].
- Treatment for phalangeal fractures in baseball should be immediate, with nonoperative splinting for at least 3 weeks for nondisplaced fractures [129].
- Fingertip injuries without exposed bone are allowed to heal by second intention if less than 1 cm² of the tip or pulp is involved [31].
- Full-thickness skin grafts (FTSGs) are preferred for the fingertip because they provide better durability, less contraction, and superior sensibility than composite or split-thickness skin grafts (STSGs) [31].
- Composite flaps for distal fingertip amputations may be attempted in patients younger than 6 years, but patients’ parents must acknowledge possibility of failure [31].
Operative Management
- Surgery for displaced proximal phalangeal fractures in baseball is indicated [129].
- External fixation of unstable metacarpal and phalangeal fractures achieved good or excellent function in 94% of metacarpal and 85% of phalangeal fractures by nine weeks [4].
- The results achieved with external fixation of closed metacarpal and phalangeal fractures were similar to those obtained in the management of stable and undisplaced metacarpal and phalangeal fractures [7].
- Non-locking plates are appropriate for most metacarpal and phalangeal fractures necessitating plate fixation [132].
- Intramedullary screw fixation for proximal phalangeal fractures finds good functional outcomes and a low complication rate [45].
- Intramedullary fixation of proximal phalangeal fractures through a volar extra-tendon sheath approach resulted in satisfactory union of the fractures in all six fingers, with no patient complaining of pain at the final follow-up [11].
- Screw fixation is suggested to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalangeal fractures of the long fingers [23].
- The Ichi-Fixator system (IFS) is a definitive treatment option for managing various phalangeal fractures [28].
- Open reduction and internal fixation (ORIF) of proximal phalangeal fractures achieved excellent outcomes, providing a benchmark for recovery [37].
- Open reduction and interfragmentary screw fixation is an effective treatment modality for symptomatic non-union of distal phalangeal fractures with minimal morbidity, resulting in union and normal function in all patients [104].
- In a retrospective review of 105 patients treated with closed reduction pin fixation of a displaced proximal phalanx fracture, the complication rate was 4.8% including infection, pin site complication, and malunion [29].
- Thirty-six of 105 patients had postoperative stiffness with 31 requiring therapy after closed reduction pin fixation of displaced proximal phalanx fractures [29].
- Phalangeal neck fractures had the highest rate of postoperative stiffness after closed reduction pin fixation [29].
- Thirty-one patients available for follow-up at 1 year or greater all reported return of full motion, no pain, and happiness with function and appearance despite 22% (7 of 31) having a measurable coronal plane deformity on radiograph [29].
- Unstable PIP fracture-dislocations must be managed surgically using ORIF or hemihamate arthroplasty [142].
- Chronic PIP fracture-dislocations are managed using volar plate arthroplasty or hemihamate arthroplasty [142].
- Pilon fractures of the base of the middle phalanx are managed using longitudinal traction (pin and rubber band traction) and immediate motion [142].
- Rotatory subluxation-dislocations of the PIP often require surgical intervention for reduction because of interposed soft tissues [142].
- If a voral PIP dislocation is still unstable after reduction, pinning for 3 weeks is required [142].
- Excising the third metacarpal shaft removes the origin of the adductor pollicis and weakens pinch [18].
- The index ray should not be transposed unless the adductor pollicis can be reattached elsewhere [18].
- Transposition of the index metacarpal after partial middle finger metacarpal amputation is technically challenging and has significant complications [18].
- Union of midshaft metacarpal osteotomies is more difficult, and metaphyseal fixation is recommended in such instances [18].
- Amputation of the index, long, and small fingers requires preservation of the metacarpal base to protect the insertion of the flexor and extensor tendons [33].
- Ray resections without transposition avoid complications such as nonunion and minimize postoperative immobilization [33].
- Ray resections with transposition narrow the resultant open space and avoid complications such as malrotation leading to scissoring [33].
- An acute ray amputation following trauma should be performed sparingly as delayed ray resection can be performed to address functional or esthetic concerns [33].
- Cross-finger flap is indicated for volar oblique fingertip injuries with exposed bone [31].
- The donor site for a cross-finger flap is covered with an STSG and the flap is split during a separate procedure 2 to 3 weeks later [31].
- Thenar flap is indicated for volar oblique injuries to the index or long digits [31].
- Complications of the thenar flap include donor site tenderness and PIP contracture, especially in older patients [31].
- Homodigital island flap is raised on the digital artery of the involved finger and may maintain sensory innervation to the fingertip [31].
- Heterodigital island flap is raised on the ulnar aspect of the long or ring finger and typically tunneled in the palm to provide coverage to the thumb [31].
- V-Y advancement is indicated to preserve length and cover transverse or dorsal oblique fingertip injuries [31].
- Reverse cross-finger flap is indicated for loss of tenosynovium and dorsal exposure of bone [31].
- A lumbrical-plus finger is treated with release of the radial lateral band [31].
- Moberg advancement flap is most useful for amputations distal to the thumb interphalangeal (IP) joint [31].
- Complications of the Moberg advancement flap include flap necrosis and thumb IP joint flexion contracture [31].
- First dorsal metacarpal artery “kite” flap or heterodigital island flap is indicated for thumb tip injury of any size [31].
- The best indication of the reversed digital artery island flap is the coverage of large defects of the dorsal aspects of the middle and third phalanx, not the treatment of fingertip injuries [115].
Complications
General and Pediatric Outcomes
- Recent PIP fractures present challenges in diagnosis and treatment, with final outcomes having a considerable impact on global finger and hand function [1].
- In younger children, residual angulation of 30 degrees or less should remodel without significant disability [139].
- Uncorrected angulation of 25 degrees or more in the adult or older child usually results in loss of both flexion and extension of the proximal interphalangeal joint, aside from any adherence of tendon apparatus adjacent to the fracture site [139].
- Two of six children over age ten with impacted fractures in the proximal third of the proximal phalax had malunion with loss of significant flexion and extension of the proximal interphalangeal joint [139].
- Of seventeen adults with impacted fractures in the proximal third of the proximal phalax, nine had malunion [139].
- Seven adults first seen more than five weeks after injury had angulation of 25 to 70 degrees with significant loss of both flexion and extension at the proximal interphalangeal joint [139].
- The commonest causes of malunion in impacted proximal phalangeal fractures were immobilization of the digit in insufficient flexion at the metacarpophalangeal and proximal interphalangeal joints, permitting loss of reduction [139].
- Acceptance of oblique rather than true lateral roentgenograms for evaluation of angulation in fractures of the proximal phalanx, both before and after reduction, was a common cause of malunion [139].
Operative Complications and Reoperation
- Postoperative finger stiffness occurred in 43% of fractures treated with titanium plates and/or screws for unstable proximal phalangeal fractures [26].
- Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation after phalangeal fractures requiring vascular reconstruction [14].
- The risk for postoperative complications and reoperations after closed reduction and percutaneous pinning (CRPP) of closed proximal phalanx fractures is considerable [125].
- Union of midshaft metacarpal osteotomies is more difficult in the context of index ray transposition [18].
- The operation of index ray transposition is contraindicated if the hand is needed for heavy manual labor [18].
- The authors do not agree with the system of freeing the caught hand by rotating the handle in the reverse direction due to the potential risk of damaging vital structures in severe mincer injuries [27].
- Long-term follow-up in patients with pay phone receiver cord injuries to the hand was impossible, and anticipated hand function results are less than optimal [43].
- The patient with a Salter-Harris Type III fracture of the distal phalanx demonstrated a residual deficit in thumb IP joint flexion [24].
- Follow-up radiographic evidence in the patient with a Salter-Harris Type III fracture of the distal phalanx showed a healed fracture and a physis that remains open [24].
Specific Technique Outcomes
- Good or excellent function was achieved in 94% of metacarpal and 85% of phalangeal fractures treated with external fixation by nine weeks [4].
- All six fingers treated with intramedullary fixation through a volar extra-tendon sheath approach obtained satisfactory union of the fractures [11].
- No patient complained of pain at the final follow-up after intramedullary fixation through a volar extra-tendon sheath approach [11].
- Dual antegrade intramedullary headless screw fixation of proximal phalangeal fractures resulted in no complications with follow-up of at least 1 year [67].
- An updated systematic review finds a low complication rate following the use of intramedullary screw (IMS) fixation for proximal phalangeal fractures [45].
- The remaining patients in a series of phalangeal fractures had either suffered an unusual type of injury, or had developed an arthrosis associated with a long delay between injury and operation [76].
Recovery
General Outcomes and Prognosis
- Recent PIP fractures have a final outcome that considerably impacts global finger and hand function [1].
- Fractures of the fingers are better understood, with indications for surgical treatment more clearly defined, though results vary according to fracture type, surgeon experience, and patient compliance [8].
- In a retrospective series of nearly 7,000 hospital admissions for phalangeal fractures, no significant change in incidence was found in any specific age group during the study period [75].
- Patients who suffered an unusual type of injury or developed arthrosis associated with a long delay between injury and operation had less favorable outcomes [76].
Non-Operative Recovery
Operative Recovery and Complications
- Good or excellent function was achieved in 94% of metacarpal and 85% of phalangeal fractures by nine weeks following external fixation [4].
- No differences in the outcome of finger proximal phalangeal fractures were observed between dorsal and lateral plate fixation [5].
- A quarter of open finger fractures will likely need more than one surgical procedure, especially in more severely injured fingers due to crush or vascular impairment [6].
- Open fractures with both palmar and dorsal wounds should be treated with delayed fixation of K-wires otherwise stabilized immediately after injury [163].
- Most fractures healed within 4 weeks following closed reduction and periarticular pinning of base and shaft fractures of the proximal phalanx, with the majority of patients having excellent or good results [157].
- Excellent outcomes were achieved in a prospective longitudinal study of open reduction and internal fixation of proximal phalangeal fractures, providing a benchmark for recovery [37].
- Dual antegrade intramedullary headless screw fixation of proximal phalangeal fractures resulted in excellent postoperative motion, near-normal grip strength, positive self-reported patient outcomes, and no complications with follow-up of at least 1 year [67].
- An updated systematic review found good functional outcomes and a low complication rate following the use of intramedullary screw fixation for proximal phalangeal fractures [45].
- All six fingers obtained satisfactory union of the fractures, and no patient complained of pain at the final follow-up after intramedullary fixation through a volar extra-tendon sheath approach [11].
- The authors suggest using screw fixation to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalanx fractures of the long fingers [23].
- Dynamic external fixation is considered an effective tool in the management of a range of complex intraarticular phalangeal fractures [72].
Pediatric and Articular Specifics
- A patient with a Salter-Harris Type III fracture of the distal phalanx returned to his previous activity level but demonstrated a residual deficit in thumb IP joint flexion with follow-up radiographic evidence of a healed fracture and a physis that remains open [24].
Rehabilitation and Long-Term Follow-Up
- Long-term follow-up in a specific transient patient population with pay phone receiver cord injuries was impossible, and anticipated hand function results are less than optimal [43].
- Bone resorption occurred in a digit reconstructed using the circumferential method seven months after surgery, though the true incidence remains unclear as radiographs are not commonly performed after such procedures [78].
- At 6 months, very significant progress was observed with complete and total recovery of active flexion amplitudes of the proximal and distal interphalangeal joints of 4 long fingers following secondary tendon surgery [153].
Key Evidence
- [L5] Recent PIP fractures are challenging trauma in terms of diagnosis as well as treatment, with the final outcome having a considerable impact on global finger and hand function. [1] (10.1016/j.main.2004.08.010)
- [L5] Most pediatric hand fractures are treated nonoperatively with good results, but a subset of phalangeal fractures requires prompt recognition and surgical intervention to minimize complications. [2] (10.1097/01.blo.0000205890.88952.97)
- [L5] The majority of hand fractures can be treated without surgery, though surgery offers distinct advantages in properly selected cases. [3] (10.1016/j.jhsa.2013.02.017)
- [L3] Good or excellent function was achieved in 94% of metacarpal and 85% of phalangeal fractures by nine weeks. [4] (10.1016/0266-7681(92)90077-f)
- [L3] No differences in the outcome of finger proximal phalangeal fractures treated by dorsal and lateral plate fixation were observed. [5] (10.1007/s00402-017-2650-x)
- [L3] A quarter of open finger fractures will likely need more than one surgical procedure, especially in more severely injured fingers, due to crush or with vascular impairment. [6] (10.1177/15589447211043191)
- [L2] The results achieved were similar to those obtained in the management of stable and undisplaced metacarpal and phalangeal fractures. [7] (10.1016/j.jhsb.2005.09.013)
- [L5] Fractures of the fingers are better understood, indications for surgical treatment are more clearly defined, and operative techniques and implants for osteosynthesis are continuing to evolve and improve, though results vary according to fracture type, surgeon experience, and patient compliance. [8] (10.1054/jhsb.2002.0889)
- [L3] It is recommended that all finger fractures should be assessed and treated by surgeons with training in the management of hand injuries. [9] (10.1016/0266-7681(90)90008-r)
- [L5] Most hand fractures can be managed successfully without operation, and conservative functional techniques are the optimum treatment for the majority of patients with single metacarpal fractures. [10] (10.1177/1753193420928820)
- [L4] All six fingers obtained satisfactory union of the fractures, and no patient complained of pain at the final follow-up. [11] (10.1142/s0218810411005230)
- [L3] Open finger fractures formed the majority of the workload of open fractures at our trauma centre but usually required simple treatments only. [12] (10.1142/s2424835516500338)
- [L4] We believe we have shown its success in the treatment of closed proximal phalangeal fractures. [13] (10.1016/s0020-1383(01)00138-3)
- [L3] Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation, which may guide initial treatment decision-making and postoperative follow-up. [14] (10.1177/15589447221109635)
- [L4] Most phalangeal neck fractures in children less than 3 years old obtained satisfactory results. [16] (10.1186/s13018-025-05849-2)
- [L4] We conclude that this technique is applicable for selected unstable metacarpal and phalangeal fractures of certain configurations. [17] (10.1016/s0363-5023(86)80072-7)
- [L4] It showed to be safe and effective when used for treatment of extra-articular metacarpal and proximal phalangeal fractures. [19] (10.1177/1558944716660555dq)
- [L4] Articular fractures of the fingers in children often result in sequelae, with a rate as high as 50% when the fracture was displaced initially. [21] (10.1016/s0749-0712(21)00213-4)
- [Paper] Most pediatric phalangeal fractures can be treated nonsurgically, but a small subset benefits from surgical intervention. [22] (10.1016/j.jhsa.2025.08.015)
- [L4] The authors suggest using screw fixation to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalanx fractures of the long fingers. [23] (10.1016/j.hansur.2016.08.009)
- [L4] The patient returned to his previous activity level but demonstrated a residual deficit in thumb IP joint flexion with follow-up radiographic evidence of a healed fracture and a physis that remains open. [24] (10.1177/15589447221082165)
- [L4] These two cases present an uncommon mechanism resulting in a spiral fracture of the proximal phalanx of the index finger, which to our knowledge has not been reported previously in the English literature. [25] (10.1016/0020-1383(92)90162-l)
- [L2] Postoperative finger stiffness occurred in 43% of fractures. [26] (10.1016/j.jhsa.2014.06.107)
- [L4] The authors do not agree with the system of freeing the caught hand by rotating the handle in the reverse direction due to the potential risk of damaging vital structures. [27] (10.1016/0266-7681(85)90045-2)
- [L4] The IFS is a definitive treatment option for managing various phalangeal fractures. [28] (10.1016/j.hansur.2019.07.011)
- [L3] [34] (10.1142/s2424835519500607)
- [L4] [35] (10.1177/1753193408091430)
- [Paper] [36] (10.1016/s0894-1130(03)80008-x)
- [L3] Excellent outcomes were achieved, providing a benchmark for recovery after ORIF of proximal phalangeal fractures. [37] (10.1177/1753193416670591)
- [L5] This is another tool available to the hand surgeon treating fractures of the hand and phalanges. [38] (10.1097/bth.0b013e318217615f)
- [L2] The phalangeal fractures tend to deteriorate %TAM than metacarpal fractures. [39] (10.1016/s0363-5023(11)60047-6)
- [L5] Hand fractures, in particular, require excellent communication between the surgeon and therapist to progress the patient through the course of therapy. [41] (10.1016/s0894-1130(03)80006-6)
- [L4] Long-term follow-up in this particular transient patient population was impossible, and anticipated hand function results are less than optimal. [43] (10.1016/s0363-5023(84)80078-7)
- [L1] With the current data, we can conclude that taping these finger fractures can be recommended irrespective of the degree of displacement or the need for reduction. [44] (10.1177/17531934241293338)
- [L4] This updated systematic review finds good functional outcomes and a low complication rate following the use of IMS fixation for proximal phalangeal fractures. [45] (10.1177/15589447251329597)
- [L4] [49] (10.1016/0266-7681(92)90123-j)
- [L5] [52] (10.1016/j.hcl.2012.05.032)
- [L5] [54] (10.1016/j.hcl.2013.08.006)
- [L5] The article reviews the background, biomechanics, applications, techniques, outcomes, and costs of this approach for metacarpal fractures, phalangeal fractures, and interphalangeal joint arthrodesis. [55] (10.1016/j.jhsa.2023.08.011)
- [L4] In contrast, avascular necrosis following phalangeal neck fractures usually affects the little finger and presents with stiffness, and hence, further surgery is not often required short term. [57] (10.1016/j.jhsa.2010.03.038)
- [L5] It commonly occurs in RTAs and is usually associated with other serious injuries of the hand, wrist and distal forearm so adequate imaging should be sought early in all instances. [58] (10.1016/j.jhsb.2007.01.009)
- [L4] [60] (10.1007/s00402-015-2155-4)
- [L4] Phalangeal neck fractures of the proximal phalanx in adults are rare with limited options for unstable fractures. [62] (10.1016/j.injury.2010.06.017)
- [Paper] The system has had extensive use in the management of hand injuries. [63] (10.1016/s0020-1383(97)88363-5)
- [L5] [65] (10.1016/0266-7681(87)90028-3)
- [L4] Dual antegrade IMHS fixation of proximal phalanx fractures resulted in excellent postoperative motion, near-normal grip strength, positive self-reported patient outcomes, and no complications with follow-up of at least 1 year. [67] (10.1177/1558944717750919)
- [L4] The technique was used to treat two intraarticular proximal phalangeal fractures of the thumb with satisfactory outcomes, including full range of movements within 3 weeks, no complications, and no need for implant removal. [68] (10.1177/1753193415615032)
- [L4] This study supports the rationale for nonsurgical treatment of closed and displaced mallet finger fractures with greater than one-third articular surface involvement. [69] (10.1016/j.jhsa.2005.02.010)
- [L4] We consider that this device is an effective tool in the management of a range on complex intraarticular phalangeal fractures. [72] (10.1016/j.jhsb.2003.08.009)
- [L5] Phalangeal fractures are the most common hand fractures in children, with Salter-Harris type II fractures of the proximal phalanx being the most frequent. [74] (10.5435/jaaos-d-16-00199)
- [L4] In this retrospective series of nearly 7,000 hospital admissions for phalangeal fractures we found no significant change in incidence in any specific age group during the study period. [75] (10.1016/0266-7681(94)90157-0)
- [L4] The remaining patients had either suffered an unusual type of injury, or had developed an arthrosis, associated with a long delay between injury and operation. [76] (10.1016/0020-1383(81)90217-5)
- [L4] Bone resorption occurred in the digit reconstructed using the circumferential method seven months after surgery, though the true incidence remains unclear as radiographs are not commonly performed after such procedures. [78] (10.1177/1753193412453413)
- [L3] These findings underscore the importance of careful assessment and management of nail bed injuries and fracture healing when treating distal phalanx fractures. [96] (10.1177/17531934261456220)
- [L4] Complications of distal phalanx fractures in children are frequent. [100] (10.1016/j.jhsa.2017.03.042)
- [L4] [103] (10.1177/1753193414548170)
- [L4] Open reduction and interfragmentary screw fixation is an effective treatment modality for symptomatic non-union of distal phalangeal fractures with minimal morbidity, resulting in union and normal function in all patients. [104] (10.1177/1753193407087866)
- [L1] Buddy taping is a non-inferior treatment modality for most paediatric finger fractures compared to splint immobilization. [105] (10.1177/1753193418822692)
- [L4] The best indication of the reversed digital artery island flap is not the treatment of fingertip injuries, but rather the coverage of large defects of the dorsal aspects of the middle and third phalanx. [115] (10.1016/0363-5023(94)90032-9)
- [L4] [116] (10.1177/1558944717735947)
- [L2] Well-reduced, minimally angulated, or nonangulated fractures of the proximal phalanges of the fingers can be effectively treated using functional casts without immobilizing the wrist. [122] (10.1016/j.jhsa.2012.02.017)
- [L3] The risk for postoperative complications and reoperations after CRPP of closed proximal phalanx fractures is considerable, and surgeons should counsel patients before surgery about these risks. [125] (10.1016/j.jhsg.2023.11.004)
- [L5] Palmar dislocation of the metacarpophalangeal joint is a rare injury where the mechanism is likely hyperextension force applied during strong active flexion. [127] (10.1016/j.jhsb.2003.09.009)
- [L5] Treatment should be immediate, with nonoperative splinting for at least 3 weeks for nondisplaced fractures and surgery for displaced fractures. [129] (10.1016/j.hcl.2012.05.033)
- [L5] Non-locking plates are appropriate for most metacarpal and phalangeal fractures necessitating plate fixation. [132] (10.1016/j.jhsa.2011.09.023)
- [L5] The case study presents a method for noninvasive management of angulated and rotated phalanx fractures. [138] (10.1016/s0894-1130(04)00198-x)
- [L4] [139] (10.2106/00004623-196951070-00006)
- [L4] This non-invasive technique using a thermoplastic traction platform is safe & effective in the management of proximal phalangeal fractures. [140] (10.1016/j.jht.2021.02.001)
- [Paper] Type II D phalangeal neck fractures tend to occur in young children and the majority involve the middle phalanx. [146] (10.1055/s-0040-1703097)
- [L4] [148] (10.1054/jhsb.2000.0506)
- [L5] At 6 months, very significant progress was observed with complete and total recovery of active flexion amplitudes of the proximal and distal interphalangeal joints of 4 long fingers. [153] (10.1016/j.hansur.2018.10.074)
- [L4] Ultrasonography may provide greater accuracy in fracture diagnostics by revealing small avulsed bony fragments missed on radiographs and can be beneficial in diagnosing occult fractures, especially in children. [155] (10.1016/j.jhsa.2015.02.022)
- [L4] Quantitative 3DCT analysis of fracture fragments provides useful information that could facilitate surgery and analysis of complex fractures of the base of the middle phalanx. [156] (10.1007/s11552-014-9665-3)
- [L4] Most fractures healed within 4 weeks, and the majority of patients had excellent or good results. [157] (10.1016/j.jhsa.2014.05.008)
- [L3] Open fractures with both palmar and dorsal wounds should be treated with delayed fixation of K-wires otherwise stabilized immediately after injury. [163] (10.1038/s41598-017-11918-2)
References
[1] Fractures récentes des articulations IPP. Chirurgie de la Main. 2005. DOI: 10.1016/j.main.2004.08.010
[2] Pediatric Phalanx Fractures. Clinical Orthopaedics and Related Research. 2006. DOI: 10.1097/01.blo.0000205890.88952.97
[3] Hand Fractures: A Review of Current Treatment Strategies. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.02.017
[4] External Fixation of Unstable Metacarpal and Phalangeal Fractures. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90077-f
[5] Dorsal versus lateral plate fixation of finger proximal phalangeal fractures: a retrospective study. Archives of Orthopaedic and Trauma Surgery. 2017. DOI: 10.1007/s00402-017-2650-x
[6] Reoperation After Operative Treatment of Open Finger Fractures. HAND. 2022. DOI: 10.1177/15589447211043191
[7] External Fixation of Closed Metacarpal and Phalangeal Fractures of Digits. A Prospective Study of One Hundred Consecutive Patients. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.09.013
[8] Treatment of Fractures of the Fingers. What’s New?. Journal of Hand Surgery. 2003. DOI: 10.1054/jhsb.2002.0889
[9] Why all finger fractures should be referred to a hand surgery service: A prospective study of primary management. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1990. DOI: 10.1016/0266-7681(90)90008-r
[10] Current methods, outcomes and challenges for the treatment of hand fractures. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420928820
[11] INTRAMEDULLARY FIXATION OF PROXIMAL PHALANGEAL FRACTURES THROUGH A VOLAR EXTRA-TENDON SHEATH APPROACH. Hand Surgery. 2011. DOI: 10.1142/s0218810411005230
[12] Open Finger Fractures: Incidence, Patterns of Injury and the Influence of Social Deprivation. The Journal of Hand Surgery (Asian-Pacific Volume). 2016. DOI: 10.1142/s2424835516500338
[13] Old principles revisited—traction splinting for closed proximal phalangeal fractures. Injury. 2002. DOI: 10.1016/s0020-1383(01)00138-3
[14] Phalangeal Fractures Requiring Vascular Reconstruction: Epidemiology and Factors Predictive of Reoperation. HAND. 2022. DOI: 10.1177/15589447221109635
[16] Clinical results of phalangeal neck fractures in children aged 3 years or younger: a case series of 37 patients. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05849-2
[17] Fixation of metacarpal and phalangeal fractures with miniature plates and screws. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80072-7
[18] Campbell S Operative Orthopaedics 4 Volume Set. AMPUTATION THROUGH THE SURGICAL NECK OF THE HUMERUS > MIDDLE OR RING FINGER RAY AMPUTATIONS.
[19] Metacarpal and Proximal Phalangeal Fracture. HAND. 2016. DOI: 10.1177/1558944716660555dq
[21] ARTICULAR FRACTURES OF THE FINGERS IN CHILDREN. Hand Clinics. 2000. DOI: 10.1016/s0749-0712(21)00213-4
[22] Pediatric Finger Fractures: Preventing Big Problems After Small Fractures. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.08.015
[23] Surgical management of closed, isolated proximal phalanx fractures in the long fingers: Functional outcomes and complications of 87 fractures. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2016.08.009
[24] Salter-Harris Type III Fracture of the Distal Phalanx: A Rare Juxtaphyseal Variant. HAND. 2022. DOI: 10.1177/15589447221082165
[25] Spiral fracture of the proximal phalanx of the index finger by finger wrestling. Injury. 1992. DOI: 10.1016/0020-1383(92)90162-l
[26] Predictors of Postoperative Finger Stiffness After Treatment of Unstable Proximal Phalangeal Fractures With Titanium Plates And/Or Screws. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.107
[27] Severe mincer injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1985. DOI: 10.1016/0266-7681(85)90045-2
[28] Treatment of finger phalangeal fractures using the Ichi-Fixator system: A prospective study of 12 cases. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.07.011
[29] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Pediatric Forearm, Wrist, and Hand Trauma > Hand and Finger Fractures.
[31] Miller S Review Of Orthopaedics. 4. Fingertip injuries with tissue loss.
[33] Green S Operative Hand Surgery. SMALL FINGER RAY AMPUTATION.
[34] Pain in the Post-Operative Week Predicts Pain and Hand Use Twelve Weeks after Proximal Phalangeal Fracture Fixation. The Journal of Hand Surgery (Asian-Pacific Volume). 2019. DOI: 10.1142/s2424835519500607
[35] Phalangeal Neck Fractures with Concurrent Vascular Injury. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408091430
[36] Rehabilitation for proximal phalangeal fractures. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)80008-x
[37] Pattern of recovery after open reduction and internal fixation of proximal phalangeal fractures in the finger: a prospective longitudinal study. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193416670591
[38] A Mini External Fixator for Hand and Finger Fractures Constructed From Readily Available Materials. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e318217615f
[39] Predictors of the Postoperative Range of Finger Motion for Comminuted Hand and Finger Fractures Treated with a Titanium Plate. The Journal of Hand Surgery. 2011. DOI: 10.1016/s0363-5023(11)60047-6
[41] Rehabilitation approaches for distal and middle phalanx fractures of the hand. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)80006-6
[42] Rockwood And Green S Fractures In Adults. 3: Biologic and Biophysical Technologies for the Enhancement of Fracture Repair > Finger Phalanges.
[43] Pay phone receiver cord injuries to the hand. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80078-7
[44] Buddy taping after reduction of displaced extra-articular phalangeal finger fractures in children: a randomized controlled trial. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241293338
[45] Intramedullary Compression Screw Fixation of Proximal Phalanx Fractures: An Updated Systematic Review. HAND. 2025. DOI: 10.1177/15589447251329597
[47] Campbell S Operative Orthopaedics 4 Volume Set. RESULTS OF SUTURE OF THE SCIATIC NERVE > FINGER INCISIONS.
[48] Green S Operative Hand Surgery. RING FINGER RAY AMPUTATION.
[49] The Conservative Management of Proximal Phalangeal Fractures of the Hand in an Accident and Emergency Department. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90123-j
[52] Phalangeal Fractures. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.032
[54] Treatment of Phalangeal Fractures. Hand Clinics. 2013. DOI: 10.1016/j.hcl.2013.08.006
[55] Intramedullary Fixation of Hand Fractures and Arthrodeses. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.08.011
[57] Nonunion and Avascular Necrosis Following Phalangeal Neck Fractures in Children. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.03.038
[58] An Unusual Punch Injury. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhsb.2007.01.009
[60] Plate fixation of extra-articular fractures of the proximal phalanx: do new implants cause less problems?. Archives of Orthopaedic and Trauma Surgery. 2015. DOI: 10.1007/s00402-015-2155-4
[61] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > 3. Mallet Finger.
[62] Phalangeal neck fractures of the proximal phalanx of the fingers in adults. Injury. 2010. DOI: 10.1016/j.injury.2010.06.017
[63] Joshi's External Stabilization System (JESS): a simple mini external fixator for the management of hand trauma and its sequels. Injury. 1997. DOI: 10.1016/s0020-1383(97)88363-5
[65] Dislocation of carpometacarpal joint of the little finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90028-3
[67] Dual Antegrade Intramedullary Headless Screw Fixation for Treatment of Unstable Proximal Phalanx Fractures. HAND. 2018. DOI: 10.1177/1558944717750919
[68] Percutaneous compressive bone tie for reduction of condylar phalangeal fractures. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193415615032
[69] Nonsurgical Treatment of Closed Mallet Finger Fractures. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.02.010
[72] Dynamic External Fixation for Complex Intraarticular Phalangeal Fractures. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.08.009
[73] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTION OF FINGER FLEXORS: SINGLE-STAGE TENDON GRAFT > EXTENSOR TENDON REPAIR.
[74] Pediatric Phalanx Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2016. DOI: 10.5435/jaaos-d-16-00199
[75] Phalangeal Fractures of the Hand. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90157-0
[76] Fractures of phalanges. Injury. 1981. DOI: 10.1016/0020-1383(81)90217-5
[78] Bone resorption of the proximal phalanx secondary to pulley reconstruction. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412453413
[79] Exam Of The Hand Wrist 2Ed. Movements of the fingers > Articulations of the fingers.
[80] Exam Of The Hand Wrist 2Ed. Macroscopic appearance of palmar skin > Fingerprints.
[81] Dupuytren S Disease And Related Hyperproliferative Disorders. 2. Palmar Fibromatosis or the Loss of Flexibility of the Palmar Finger Tissue: A New Insight into the Disease Process of Dupuytren Contracture > 2.2 The Skin Anchoring Fibers in the Normal and Diseased Hand > 2.2.1 The External View of the Soft Tissue of the Fingers.
[83] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTION OF FINGER FLEXORS: SINGLE-STAGE TENDON GRAFT > EXTENSOR TENDONS.
[84] Exam Of The Hand Wrist 2Ed. Movements of the fingers > Normal ulnar inclination of the fingers.
[89] Exam Of The Hand Wrist 2Ed. Mechanisms of finger flexion and extension > Actions of the intrinsic muscles.
[96] Risk factors for nail dystrophy following distal phalangeal fractures of the hand. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261456220
[100] Complications of Distal Phalanx Fractures in Children. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.03.042
[103] The non-operative management of hand fractures. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414548170
[104] OPEN REDUCTION AND INTERFRAGMENTARY SCREW FIXATION FOR SYMPTOMATIC NONUNION OF DISTAL PHALANGEAL FRACTURES. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193407087866
[105] Buddy taping versus splint immobilization for paediatric finger fractures: a randomized controlled trial. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193418822692
[108] Campbell S Operative Orthopaedics 4 Volume Set. FRACTURES, DISLOCATIONS, AND LIGAMENTOUS INJURIES OF THE HAND AND WRIST > FINGER METACARPALS.
[115] A Reversed Digital Artery Island Flap for the Treatment of Fingertip Injuries. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90032-9
[116] Proximal Phalanx Fracture Management. HAND. 2017. DOI: 10.1177/1558944717735947
[122] Extra-Articular Fractures of the Proximal Phalanges of the Fingers: A Comparison of 2 Methods of Functional, Conservative Treatment. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.02.017
[125] Risks of Reoperation in Surgically Treated Fractures of the Proximal Phalanx. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2023.11.004
[127] Palmar Dislocation of the Metacarpophalangeal Joint of the Finger. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.09.009
[129] Phalangeal Fractures in Baseball: Commentary. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.033
[132] Non-Locked and Locked Plating Technology for Hand Fractures. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.09.023
[138] Traction splinting phalanx fractures: A case study. Journal of Hand Therapy. 2004. DOI: 10.1016/s0894-1130(04)00198-x
[139] Impacted Fractures in the Proximal Portion of the Proximal Phalanx of the Finger. The Journal of Bone & Joint Surgery. 1969. DOI: 10.2106/00004623-196951070-00006
[140] A traction orthosis for the treatment of proximal phalangeal fractures. Journal of Hand Therapy. 2022. DOI: 10.1016/j.jht.2021.02.001
[142] Orthopaedic Knowledge Update Sports Medicine 6. Hand and Wrist Injuries > Hand Injuries > Finger Dislocations.
[146] Type II D Phalangeal Neck Fractures in Children: A Series of 20 Cases Treated According to a Preset Stepwise Algorithm. Journal of Hand and Microsurgery. 2021. DOI: 10.1055/s-0040-1703097
[148] PHALANGEAL NECK FRACTURES IN CHILDREN: CLASSIFICATION AND OUTCOME IN 66 CASES. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0506
[153] Tubulure de perfusion siliconée en lieu et place de tiges de Hunter dans la chirurgie secondaire des tendons fléchisseurs en zone 2 dans un environnement chirurgical à ressources limitées. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.074
[155] Ultrasonography Can Be Used to Assess Phalanx Fractures. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.02.022
[156] Quantitative 3-Dimensional CT Analyses of Fractures of the Middle Phalanx Base. HAND. 2014. DOI: 10.1007/s11552-014-9665-3
[157] Outcomes of Closed Reduction and Periarticular Pinning of Base and Shaft Fractures of the Proximal Phalanx. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.05.008
[163] Timing for Surgical Stabilization with K-wires after Open Fractures of Proximal and Middle Phalangeal Shaft. Scientific Reports. 2017. DOI: 10.1038/s41598-017-11918-2