为何建议进行此手术
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会从适合您病情的最微创方案开始。患者通常由全科医生转诊至我们的诊所;如果物理治疗师建议您就诊,您仍需获得全科医生的转诊才能符合 Medicare 报销资格。在您的预约就诊中,我们会采集病史、检查您的手部,并在需要时安排影像学检查以确认诊断。
这项手术称为大多角骨切除术(trapeziectomy)。它是指切除拇指基底的一块小骨,即大多角骨,磨损性关节炎已在此处磨坏了关节面。我们通常首先尝试非手术治疗,例如改变用手方式、手部治疗和佩戴支具。当这些措施未能为您带来足够的改善时,才会考虑手术。
我们建议这项手术,可能是因为拇指疼痛限制了您能做的事情,或是因为影像检查中看到的关节变化与您的症状相符。切除这块磨损的骨头可以去除相互摩擦、引起疼痛的表面。手术的目的是持久缓解疼痛,让您在日常活动中更有信心地使用拇指。
术前
在手术之前,我们会给您明确的须知以供遵循。您需要在手术前七小时停止进食和饮水。我们要求七小时而不是六小时,是为了在手术排期提前时可以将您的手术提前进行。您的外科医生会告诉您哪些常用药物需要停用以及何时停用。请携带一份书面清单,列出您正在服用的所有药物。请安排他人在术后驾车送您回家,因为您将无法自行驾驶。手术当天请穿着宽松、舒适的衣物。我们会事先获得X光片等影像检查结果,有时还有核磁共振(MRI)或超声检查结果,以规划手术。如果您有其他基础疾病,可能需要进行血液检查或由麻醉医生进行评估。
手术当天
手术当天,您需前往医院的手术入院单元报到。工作人员会在那里为您办理入院手续并做术前准备。随后您将见到麻醉医生,即在手术期间负责您的麻醉和止痛的医生。之后,您将被带入手术室进行手术。
本手术在全身麻醉下进行。手术期间您将处于完全睡眠状态。部分患者可能还会接受区域神经阻滞以缓解术后疼痛;麻醉医生将根据您当天的具体情况决定是否实施。
手术结束后,您将在复苏区醒来。在麻醉消退期间,护士会陪伴在您身边并密切观察您的状况。待您的状况稳定后,根据手术类型及恢复情况,您将被转入病房或直接回家。
手术内容
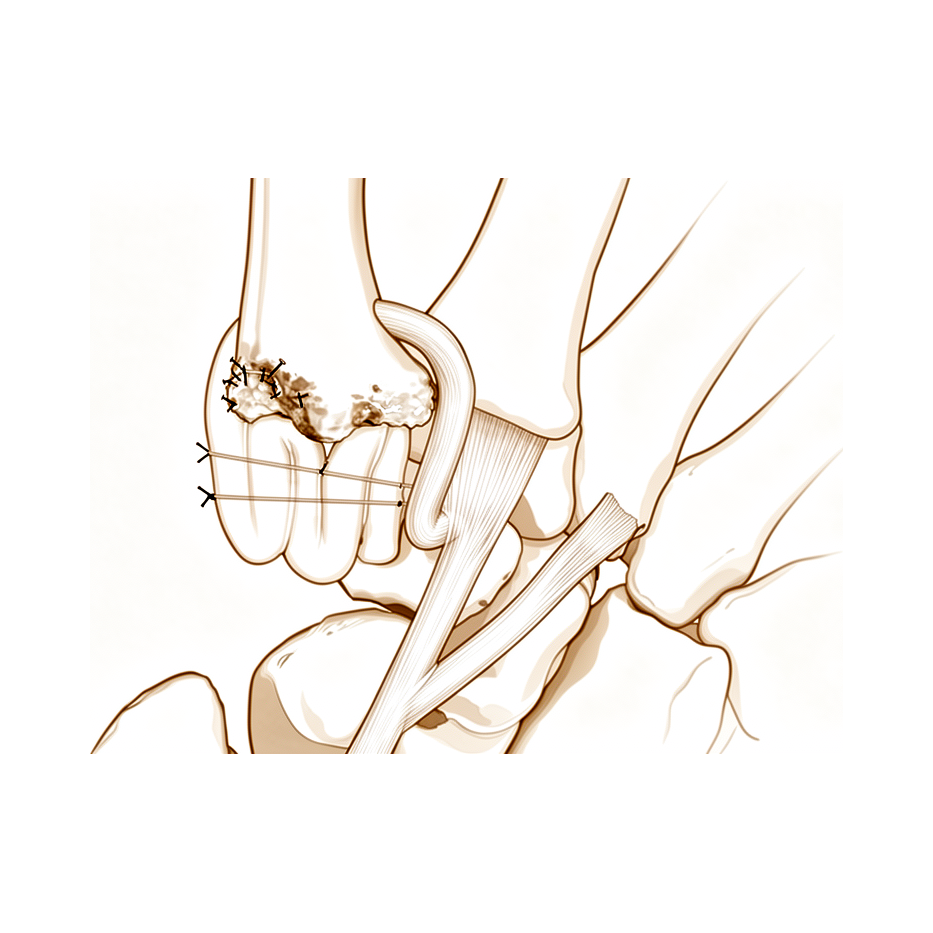
大多角骨切除术是一种开放手术,通过手术区域上方、位于拇指基底处的一个切口进行。外科医生通过这个切口切除大多角骨,即位于拇指与手腕之间那块已磨损的小骨。取出这块骨头即可去除一直相互摩擦、粗糙且引起疼痛的表面。
骨头切除后,留下的空隙会随时间逐渐被您自身的瘢痕组织填充,您的拇指将依靠这一软垫而不是磨损的关节来支撑。外科医生不会放入任何人工关节或植入物。伤口用缝线缝合,上面覆盖敷料。
手术本身并不复杂,以日间手术方式进行,因此您可以当天回家。
术后
此手术后,您可能当天回家,也可能在医院住一晚。这两种情况都很常见,您的医疗团队会与您讨论哪种适合您。您的手部会用支具固定,伤口上覆盖敷料;在最初一两天,吊带可以帮助您舒适地让手臂休息。护士会教您如何处理敷料,以及如何抬高手部以帮助减轻肿胀。我们通常会保留敷料约10天;除非我们告知您,否则请勿在此之前拆除。我们将在复诊时为您更换或拆除敷料。出院前会为您安排好止痛药,护士会向您解释如何服用。回家后,请让他人在最初的24小时内陪伴您。
恢复
在最初几天,您的手会疼痛和肿胀,伤口部位可能会有搏动感。将手抬高放在枕头上,即使在休息或睡觉时也是如此,有助于肿胀消退。请按医嘱服用止痛药,不要等到疼痛加剧时才服用。
在伤口愈合期间,您的拇指将用支具固定。手部治疗师会教您一些轻柔的锻炼,让手指保持活动,防止出现僵硬。您可以用另一只手完成家中的轻松日常事务,但在拇指受保护期间,不能用做过手术的拇指进行抓握、捏合或提举。在佩戴支具期间,您不能开车,因为它会妨碍您安全地握住方向盘。一旦拆除支具且您的外科医生允许,就可以恢复驾驶;请参阅我们关于 上肢手术后驾驶 的页面。
随着时间一周周过去,肿胀会消退,活动能力会逐步恢复。手部治疗会继续进行,治疗师会逐渐增加您使用拇指的程度。握力和捏力恢复得很慢,许多人发现即使日常活动已感觉正常,拇指仍感觉不如以前有力。手术的全部效果会随时间逐渐显现,疼痛和力量持续改善长达一年是很常见的。
您的恢复时间表可能与他人不同。您的外科医生和手部治疗师会在每一步为您提供指导。
可能出现的并发症
大多数患者恢复良好,但偶尔也可能出现问题。您的外科医生和医疗团队会密切监测您的状况,以便尽早发现任何问题。
手术后,拇指附近的神经有时会受到刺激。这可能表现为手背或拇指背面出现刺痛、灼热感或麻木。如果发生这种情况,通常在一年内会完全缓解。请在下次复诊时告知我们,以便我们进行观察。
有时用于固定骨骼位置的钢针可能会引起问题。钢针周围的皮肤可能会变得疼痛或受到刺激,钢针也可能松动或移位。移位的钢针通常需要尽早取出,目前尚未发现这会影响最终效果。如果钢针部位变得疼痛,或其周围的皮肤看起来发炎,请在复诊时告知我们。
感染并不常见,但任何伤口都有可能发生。请注意观察是否出现从伤口向外扩散的红肿、伤口有液体或脓液渗出,或发热。如果您注意到其中任何一种情况,请当天致电诊所。如果尽管服用了止痛药,疼痛仍持续加重,也需要当天致电诊所。
拇指的血液供应受到影响的情况非常罕见。如果您的拇指、手指或手部变得苍白、冰冷、发白、发青或发黑,请前往急诊科。
如果使用肌腱垫填充骨头切除后留下的空隙,它偶尔可能会在皮下凸起。您可能会注意到拇指附近有一个柔软的肿块,或有一处压痛、发炎的区域。这通常可以通过一个小手术将其取出来治疗,从而缓解疼痛。
一些较罕见的问题与这项手术的更复杂的术式有关,例如人工关节植入物。与单纯的大多角骨切除术相比,这些术式风险更大,这也是我们倾向于选择较简单方案的原因之一。如果首次手术日后需要矫正,其效果往往不如第一次那样可靠。在您做出决定之前,我们会与您讨论这些问题。
如果您想了解具体数据,本页的并发症表格列出了典型的发病率。
何时联系我们
大多数问题会在最初几周内出现,因此了解需要留意什么会有帮助。如果您出现小腿肿胀或疼痛、呼吸急促或胸痛,请前往急诊科,因为这些可能是血栓的征象。如果您的拇指、手指或手部变得苍白、冰冷、发白、发青或发黑,请前往急诊科。如果您出现发热、伤口周围红肿扩散,或伤口有液体或脓液渗出,请当天致电诊所。如果尽管服用了止痛药,疼痛仍持续加重,请当天致电诊所。神经阻滞后最初24小时内出现麻木或无力是预料之中的。阻滞作用消退后,如果您的手臂、手部或手指没有感觉或无法活动,请致电诊所。如果您无法联系到诊所,请前往最近的急诊科。
在哪里阅读更多关于该疾病的资料
本页介绍的是手术本身。它所治疗的疾病,包括证据显示手术在何时有效、何时无效,在拇指基底关节炎页面上有更详细的介绍。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Outcomes of trapeziectomy with or without ligament reconstruction or tendon interposition were very similar at 1-year follow-up [1].
- The value of adding ligament reconstruction and temporary stabilization with a Kirschner wire to trapeziectomy remains unproven until further larger studies are performed [2].
- Secondary trapeziectomy after revision of trapeziometacarpal implants provides results comparable with primary trapeziectomy [3].
- Partial trapeziectomy does not provide an advantage over total trapeziectomy at 1 year after surgery [4].
- Outcomes of secondary trapeziectomy after failed trapeziometacarpal joint replacement arthroplasty generally do not differ from primary trapeziectomy results [5].
- Simple trapeziectomy may have an advantage over trapeziectomy with ligament reconstruction and tendon interposition, though further study is warranted [6].
- A large improvement in pain and function can be expected after trapeziectomy, although it remains unclear how much of this change is attributable to the surgery itself [7].
- Thumb metacarpal immobilization after trapeziectomy is now routinely employed to address concerns with instability [8].
- Complications can occur after trapeziectomy and suspension arthroplasty despite proper preoperative evaluation, meticulous surgical technique, and vigilant postoperative rehabilitation [9].
- Trapeziectomy with an alternative suspension technique shows good patient-reported outcome measures for primary surgery and poor patient-reported outcome measures after secondary surgery [10].
- Total trapeziectomy is currently the only surgical technique for thumb basal joint arthritis that can lay claim to being a potential life-long procedure due to its long-lasting benefits and lack of need for an implant [11].
- Trapeziectomy combined with a Swanson implant gives better results in the short term if there are no complications of the operation [13].
- Outcomes of trapeziectomy variations including excision, tendon interposition, and ligament reconstruction with tendon interposition were similar after a minimum follow-up of 5 years [14].
- Standard radiographs are appropriate to use at the 1-year follow-up examination to assess and compare the trapezial space after different techniques of trapeziectomy [15].
- Improved clinical outcomes can be achieved by maintaining at least 50% of the preoperative trapezial space after trapeziectomy with ligament reconstruction tendon interposition [16].
- Complete trapezoid excision is not recommended in the context of abductor pollicis longus suspensionplasty [17].
- Simple excision of the trapezium remains an acceptable treatment for osteoarthritis of the trapeziometacarpal joint [18].
- Partial trapezoid excision is preferred over complete excision due to no significant differences in outcomes between the two [20].
- Surgeons should use caution when considering suture button fixation after complete trapeziectomy until more data are available [22].
- Functional outcomes of partial trapeziectomy and pyrocarbon interpositional arthroplasty were not superior to simpler techniques like trapeziectomy with or without ligamentoplasty [37].
- At 1 year, total joint arthroplasty showed no superiority over trapeziectomy regarding the total score of the Michigan Hand Outcomes Questionnaire [39].
- At 1 year, total joint arthroplasty demonstrated a significant advantage over trapeziectomy in strength and range of motion [39].
- Trapeziectomy produces better functional results and overall satisfaction than pyrocarbon arthroplasty [44].
Anatomy & Pathophysiology
Bony Anatomy
- The skeleton of the hand consists of 27 bones, of which 19 are long bones [48].
- The radial ray or first ray is the shortest and is made up of only three bones: a metacarpal and two phalanges [48].
- The trapezium is clearly angled out in front of the carpal plane so that the first metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [48].
- The thumb metacarpal is the shortest metacarpal [48].
- The thumb ray continues the external column of the carpus formed by the scaphoid and trapezium [48].
- The thumb metacarpal is independent and articulates with the trapezium [68].
- The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal [48].
Joint Mechanics & Biomechanics
- The trapeziometacarpal joint has a saddle shape in opposing planes of the articular surfaces [48].
- The thumb ray is more mobile, shorter, and more proximal than the other rays, allowing it to project in front of the plane of the palm to oppose itself to the other four rays [48].
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration [48].
- The thumb metacarpal base articulates with the distal row of the carpus [48].
- The first ray is endowed with a relative autonomy owing to scapholunate mobility [48].
- The thumb metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane, explaining the gap between the first ray and the palm [48].
- The thumb metacarpal is the shortest and the index metacarpal is by far the longest [48].
- The thumb ray is clearly separated from the fingers and is implanted proximally [63].
- The thumb has a more proximal and lateral position, allowing movement inward and outward from the palm [63].
- The web space of the thumb is the largest and deepest [63].
- The index metacarpal is the most firmly fixed [68].
- The ring metacarpal has about 10 degrees of mobility in flexion and extension [68].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [68].
- The thumb ray is the most divergent of the longitudinal arches [68].
- The thumb is the master digit of the hand and represents the dominant element which gives value to all the others [68].
- The thumb metacarpal base is fixed to the carpus by the intrinsic interlocking encasement of the bones themselves [68].
Soft Tissue Anatomy
- The abductor pollicis longus has multiple slips that insert at the base of the thumb metacarpal and radially abducts the thumb [47].
- The extensor pollicis brevis inserts on the dorsum of the proximal aspect of the proximal phalanx of the thumb and actively extends the metacarpophalangeal joint of the thumb [47].
- The extensor pollicis longus provides forceful extension of the thumb interphalangeal joint [47].
- The oblique course of the extensor pollicis longus tendon provides a substantial adduction component to its pull [47].
- The flexor pollicis longus inserts into the proximal base of the thumb distal phalanx and is innervated by the anterior interosseous branch of the median nerve [72].
- The flexor pollicis longus flexes both the interphalangeal and metacarpophalangeal joints of the thumb [72].
- The tenosynovial sheath of the flexor pollicis longus is continuous with the radial bursa [72].
- The "princeps pollicis" artery, the terminal branch of the radial artery, crosses the first intermetacarpal space and runs along the ulnar side of the first metacarpal bone [69].
- The princeps pollicis artery emerges onto the subcutaneous palmar tissue at the level of the cutaneous flexion crease of the metacarpophalangeal joint [69].
- The princeps pollicis artery divides into two terminal rami, namely the collateral palmar arteries of the thumb [69].
- The collateral palmar arteries of the thumb run along the digital tunnel symmetrically and are of equal caliber [69].
- An arcade located deep in the flexor tendon joins together the two arteries at the level of the distal metaphysis of the first phalanx [69].
- The dorsal arteries of the thumb stem from the terminal branches of the radial artery at the level of the anatomical snuff-box [69].
- The posterior area of the thumb is vascularized by two arteries which originate from the palmar arteries at the level of the first metacarpal [69].
- The ulnar dorso-collateral artery generally stems from the "princeps pollicis" onto the medial border of the neck of the first metacarpal [69].
- The skin of the radial portion of the palm covers the thenar eminence and is the mobile portion [64].
- The skin of the ulnar and distal portion covers the hypothenar eminence where the skin has poor mobility [64].
- The central triangular part of the palm has fixed and poorly vascularized skin covering almost directly the superficial palmar aponeurosis [64].
- The web spaces are formed from the union of two nonsymmetrical cutaneous surfaces [64].
- The dorsal slope of the web space has a gradual incline and its supple skin is not adherent to the subjacent region [64].
- The palmar surface of the web space is flat and precipitously interrupted, and the skin is densely adherent to the commissural skeleton [64].
- The commissural skeleton is formed by the interdigital palmar (natatory) ligament between the fingers and by the distal transverse ligament at the level of the thumb web [64].
- The distal transverse ligament at the level of the thumb web is by far the deepest and the most mobile [64].
- The superficial palmar fascia lies in a coronal plane beneath the palmar subcutaneous tissue [75].
- There is no central band of fascia for the thumb [75].
- A subdermal fascial layer borders the periphery of the web spaces from roughly the radial thumb sesamoid to the ulnar side of the small finger’s proximal flexion crease [75].
- The distal first web space ligament between thumb and index is in continuity with the natatory ligament that spans the remaining web spaces [75].
- The dorsal skin is thin and lined by a horny layer that is only 0.02 mm thick [74].
- The dorsal skin possesses a normal pilosebaceous system [74].
- The dorsal skin has loose connections with the deeper planes, allowing free gliding and full flexion at the digital joints [74].
- Flexion of the fingers produces a significant lengthening of the dorsal skin [74].
- In the middle finger, the distance between the wrist and the ungual fold shows an average increase of 3 cm as the finger goes from extension to full flexion [74].
- Flexion at the metacarpophalangeal joint alone requires an average skin lengthening of 1.25 cm [74].
- The dorsal and palmar areas of skin are independent because of a system of adhesions that anchors their common boundary to the underlying plane [74].
- In the proximal part of the first phalanx, fixation occurs almost in a straight line in the plane of the commissural crest [74].
- The fixation in the proximal part of the first phalanx takes the form of small fibrils arranged in the shape of a fan that unite the deep aspect of the skin and the digital fascia [74].
- More distally, and especially opposite the middle and distal phalanges, the adhesion band is more tightly packed and lies just posterior to the palmar collateral neurovascular bundle on the lateral side [74].
- These deep attachments stabilize the skin in relation to the skeleton and prevent the integument from sliding freely over the motor system like the finger of a glove [74].
- The necessary skin to cover the thumb distal to the metacarpophalangeal joint is about 9 cm wide and 8 cm long [67].
- Skin loss of thumb and first metacarpal is 13 cm wide and 12 cm long [67].
- The skin cover of both the palmar and dorsal surfaces of the hand is 12 cm by 10 cm [67].
- The skin covering each finger is 7 cm by 10 cm on both the palmar and dorsal aspects [67].
- Skin grafting or flaps for both sides of the hand and digits requires a skin of 20 cm by 20 cm [67].
- Skin grafting or flaps for one aspect of the forearm from wrist to elbow requires skin of 30 cm by 15 cm [67].
- Both aspects of the forearm require skin of 30 cm by 30 cm [67].
- The thumb skin distal to the metacarpophalangeal joint is 9 cm wide and 8 cm long [67].
- The thumb skin distal to thenar crease and dorsal line of index metacarpal is 13 cm wide and 12 cm long [67].
- The skin for palmar side of hand from thenar crease and midradial border to midulnar border, and from volar crease of wrist to proximal digital crease is 12 cm wide and 10 cm long [67].
- The skin for dorsal side of hand, midradial to midulnar border, and volar crease of wrist to dorsal web space is 12 cm wide and 10 cm long [67].
- The skin for entire surface of a single digit is 7 cm wide and 10 cm long [67].
- The skin for both sides of hands and digits is 20 cm wide and 20 cm long [67].
- The skin for volar surface of forearm is 28 cm wide and 15 cm long [67].
- The skin for dorsal surface of forearm is 28 cm wide and 15 cm long [67].
- The skin for entire volar and dorsal surface of forearm is 30 cm wide and 30 cm long [67].
Pathophysiology & Biomechanical Consequences
- The trapezial space ratio decreased significantly from a preoperative mean of 0.40 (range, 0.20–0.56) to a mean of 0.18 (range, 0.08–0.30) after trapeziectomy [34].
- The trapezial space ratio after trapeziectomy with tendon interposition was a mean of 0.16 (range, 0.07–0.30) [34].
- The trapezial space ratio after trapeziectomy with ligament reconstruction was a mean of 0.20 (range, 0.00–0.33) [34].
- There was no significant difference between the 1-year follow-up trapezial space ratios of trapeziectomy alone, with tendon interposition, or with ligament reconstruction [34].
- The placement of a K-wire across the trapezial void is as effective as tendon interposition or ligament reconstruction in creating a trapezial space in the short term [34].
- The trapezial space height did not correlate with thumb strength at 1-year follow-up examination [34].
- Performing a trapeziectomy followed by up to 4 mm of proximal trapezoid resection has a negligible effect upon carpal, specifically lunocapitate and scapholunate, stability [51].
- Trapeziectomy results in proximal migration of the first metacarpal [85].
- Proximal migration of the first metacarpal is mitigated by suture suspensionplasty while maintaining normal motion [85].
- Proximal migration of the thumb metacarpal does not appear to influence the functional outcome [86].
- With axial compressive loading of the arthroplasty, such as in lateral pinch, there is some further proximal migration of the first metacarpal [105].
- The proximal migration of the first metacarpal during axial compressive loading is minimal and does not correlate with functional outcome [105].
- Combining the trapeziectomy with surgeries addressing the MCP-1-joint hyperextension induced a shift of the thumb in pronation-abduction that could impair the key-pinch stability [102].
- The decrease in key pinch force was larger than the relatively small increase in thumb CMC force [87].
- The impact on wrist mobility is moderate [81].
- No intracarpal deformities were seen and there was no sign of graft wear; the length of the thumb ray is preserved [43].
- Important improvements in web space with increased palmar and radial abduction and grip and pinch strength measurements were observed [30].
- The procedure provides excellent pain relief and significant improvement in strength of thumb grip in severe carpometacarpal osteoarthritis [36].
- Excellent results were achieved in 23 thumbs or 92% of cases, with no deterioration of function or stability noted over time and no revisional procedures necessary [54].
- Although there is some reduction in thumb abduction from 3.5 to 13 years after surgery, other gains after surgery are retained and in some instances slightly improved [55].
- The modified procedure improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength [92].
- This technique also provided an increase in grip strength and key pinch with return of range of motion early in the postoperative period [93].
- LRTI and SSA exhibit equivalent thumb metacarpal subsidence over a greater than 6-month postoperative time frame [94].
- According to our series, this surgical technique relieves pain and provides stability and mobility of the thumb [96].
- Our results compare well with those of most studies in the literature in terms of pain relief, thumb motion, pinch strength, and function [99].
- The use of a tenodesis screw and half of the flexor carpi radialis had minor advantages, such as increasing the grip and key pinch strength without differences relative to the non-operated thumb, and minimal migration of the first metacarpal bone compared with the other technique [101].
- Both TightRope constructs provided improved axial stability after trapeziectomy while not excessively limiting any one motion of the thumb [104].
- This simple surgical reconstruction abducts the first metacarpal bone and improves metacarpophalangeal joint hyperextension [107].
- The position of the bone anchor in the thumb metacarpal base did not affect the range of motion [90].
- The SB's trajectory when passed from the thumb metacarpal to the second metacarpal minimally affects range of motion and resistance to subsidence following trapeziectomy [80].
- The SB's mechanism of action depends more on the proper tensioning of the device than on the trajectory angle or on any special features of the attachment site along the second metacarpal [80].
- The risk of injuring the nerve to the first DI during SB placement is also minimal [80].
- The proximal trajectory was significantly further away from the nerve compared to the distal trajectory, but the distal trajectory was still safely away from the nerve in all specimens (greater than 1 cm) [80].
- The SB suspension technique may serve as an alternative to the traditional K-wire fixation method [80].
- Suture button suspensionplasty may lead to earlier mobilization of the thumb because of the implanted nature of the device [80].
- No soft tissue healing is necessary prior to the onset of range of motion of the thumb, thereby accelerating recovery [80].
- K-wire related complications such as pin track infections may be eliminated [80].
- A potential complication from drilling the second metacarpal is metacarpal fracture if the drill is placed too far dorsally [80].
- With more recent refinement of the technique, a smaller (1.1-mm) guidewire is used to introduce the suture button device and the larger drill is no longer necessary, thereby theoretically decreasing the risk of iatrogenic fracture [80].
- These findings provide biomechanical context for reported index metacarpal fractures following SBS and may inform surgical technique and patient counseling [89].
Classification
- Osteoarthritis of the trapeziometacarpal joint is the fourth commonest condition referred to a hand unit, with an incidence of 34 per 100,000 of population per year [23].
- Approximately one-third of postmenopausal women have arthritis of the thumb carpometacarpal joint, and one-third of these patients experience pain at the base of their thumb [122].
- The treatment for trapeziometacarpal joint osteoarthritis is based on the patient’s symptomatology and expectations in combination with the radiological classification [60].
- Trapezium resection remains the reference standard for surgical treatment in Eaton-Littler stage III or IV thumb trapeziometacarpal osteoarthritis [60].
- The most common cause of pain originating at the base of the thumb in patients older than 50 years is osteoarthritis of the trapeziometacarpal joint [29].
- Isolated osteoarthritis of the scaphotrapeziotrapezoid joint occurs in 2% to 24% of patients with pain at the base of the thumb [29].
- Isolated scaphotrapeziotrapezoid osteoarthritis occurs more frequently combined with trapeziometacarpal joint osteoarthritis [29].
- Stage IV osteoarthritis is treated by trapeziectomy due to the potential occurrence of intra- or postoperative complications such as trapezial fracture and trapezial loosening associated with total joint replacement [26].
Clinical Presentation
- In some patients with pain at the base of the thumb, radiographs reveal isolated osteoarthritis of the scaphotrapeziotrapezoid joint, with an incidence varying between 2% and 24% [29].
- Surgery for trapeziometacarpal joint osteoarthritis is indicated due to the presence of pain, incapacitating working activities or daily life, after failure of conventional conservative methods for at least six months [23].
- Conventional conservative methods include NSAIDs, local infiltrations with corticoids, and temporary immobilisation devices [23].
- Patients with psychological risk factors experience improved pain and function outcomes following trapeziectomy, however their outcomes are significantly worse than patients who do not have psychological risk factors [84].
Investigations
- Standard radiographs are appropriate for assessing and comparing the trapezial space at the 1-year follow-up examination after trapeziectomy [15].
- Maintaining at least 50% of the preoperative trapezial space is associated with improved clinical outcomes after trapeziectomy with ligament reconstruction tendon interposition [16].
- The trapezial gap decreases by a mean of 61% two weeks after surgery [21].
- The trapezium space loses 14% of its height compared with preoperative values following trapeziectomy and intermetacarpal ligament reconstruction with the extensor carpi radialis longus [125].
- The radiographic presence of scaphotrapezoidal arthritis does not correlate with the patient's main symptoms after partial trapeziectomy [117].
- At an average 9-year follow-up, patients who underwent partial trapeziectomy demonstrated stage 1 disease (minimal narrowing) at the scaphotrapezoidal joint on radiographs [35].
- No symptomatic progression of arthritis at the scaphotrapezoidal joint was observed after partial trapeziectomy in patients with no preoperative symptoms of scaphotrapezoidal arthritis [35].
- Degenerative change at the pseudarthrosis site can occur at 6-year follow-up after trapeziectomy [18].
- Impingement between the base of the thumb metacarpal and the remaining trapezoid is a potential source of pain after trapeziectomy and basal joint soft tissue arthroplasty [40].
Treatment
Surgical Techniques and Variations
- Outcomes of trapeziectomy with ligament reconstruction or tendon interposition were very similar to other variations at 1-year follow-up [1].
- The value of ligament reconstruction and temporary stabilization of the pseudarthrosis with a Kirschner wire remains unproven until further larger studies are performed [2].
- Partial trapeziectomy does not provide a proven advantage over total trapeziectomy at 1 year after surgery for Eaton-Littler Grade II to III osteoarthritis [4].
- Simple trapeziectomy is an effective operation for osteoarthrosis at the base of the thumb, and the addition of ligament reconstruction was not shown to confer any additional benefit [82].
- Outcomes of three variations of trapeziectomy (excision, tendon interposition, and ligament reconstruction with tendon interposition) were similar after a minimum follow-up of 5 years [14].
- Trapeziectomy via the anterior approach yields functional results equally good as those via standard approaches [12].
- Outcomes for the anterior approach are equally good or better than with the posterior approach [79].
- Total video-assisted trapeziectomy is described as fulfilling the premises of a simple technique and patient comfort [33].
- Trapeziectomy and ligament reconstruction tendon interposition (LRTI) are effective procedures for patients aged less than 56 years [50].
- Trapeziectomy and LRTI is an effective treatment in significantly reducing pain in 80% of patients over a 12-month follow-up period [42].
- Total trapeziectomy is currently the only surgical technique for thumb basal joint arthritis that can lay claim to being a potential life-long procedure due to the lack of implants and long-lasting benefits [11].
- Abductor pollicis longus tendon interposition arthroplasty provides excellent pain relief and significant improvement in strength of thumb grip in severe carpometacarpal osteoarthritis [36].
- Partial trapeziectomy with capsular interposition arthroplasty results in a stable thumb with pain relief [56].
- Trapeziectomy with an alternative suspension technique shows good patient-reported outcome measures for primary surgery but poor outcomes after secondary surgery [10].
- In view of comparable results between fusion, trapeziectomy, and silastic replacement, excision of the trapezium with or without soft-tissue reconstruction is recommended as the operation of choice in middle-aged to elderly patients [27].
- Arthroscopic hemitrapsiectomy and thermal capsular modification without interposition for Stage III arthritis yields results that last for a minimum of 4 years and are comparable to open techniques involving complete trapeziectomy [19].
- Partial trapeziectomy with costal cartilage autograft preserves the length of the thumb ray with no intracarpal deformities or sign of graft wear [43].
- Partial trapeziectomy and pyrocarbon interpositional arthroplasty functional outcomes were not superior to simpler techniques like trapeziectomy with or without ligamentoplasty [37].
- At 1 year, total joint arthroplasty showed no superiority over trapeziectomy regarding the total score of the Michigan Hand Outcomes Questionnaire, but demonstrated a significant advantage in strength and range of motion [39].
Complications and Revision
- Increased complications have been observed in trapeziectomy with ligament reconstruction and tendon interposition compared with trapeziectomy alone, suggesting an advantage of simple trapeziectomy [6].
- Complications after trapeziectomy and suspension arthroplasty can occur despite proper preoperative evaluation, meticulous surgical technique, and vigilant postoperative rehabilitation [9].
- Management of complications of trapeziectomy is difficult, and results from retrospective series of failed cases are disappointing and disparate [25].
- The removal of a pyrocarbon carpometacarpal implant using subsequent trapeziectomy successfully relieves pain in patients in whom pyrocarbon arthroplasty has failed [28].
- Trapeziectomy with LRTI after TMC joint replacement appears to be an attractive salvage procedure [109].
- Scaphometacarpal arthroplasty is a reliable medium-term solution for revision of the loosening of a trapeziometacarpal prosthesis with trapezial damage and for failed trapeziectomy [31].
- Surgeons should use caution when considering suture button fixation after complete trapeziectomy until more data are available, due to reported index metacarpal fractures [22].
Biomechanics and Radiographic Outcomes
- Maintaining at least 50% of the preoperative trapezial space can achieve improved clinical outcomes after trapeziectomy with LRTI [16].
- Complete trapezoid excision is not recommended when performing abductor pollicis longus suspensionplasty [17].
- There was a significant mean decrease of 61% in the trapezial gap 2 weeks after surgery [21].
- Standard radiographs are appropriate for assessing and comparing the trapezial space at the 1-year follow-up examination [15].
- Biomechanical analysis found several advantages to tie-in trapezium implant arthroplasty compared with LRTI, including reduction in axial and radial displacement and maintenance of the trapezial space [53].
- Total trapeziectomy with external minifixation provides acceptable clinical results, stabilizes the base of the thumb, and prevents scapho-metacarpal impingement [103].
Perioperative Care and Rehabilitation
- A large improvement can be expected after trapeziectomy following orthosis, although it remains unclear how much of this change is attributable to the surgery itself [7].
- Continuous local anaesthetic infusion following trapeziectomy was used as a routine for 3 years on 40 patients for pain relief [83].
- Wide-awake basal joint trapeziectomy can be performed using only locally injected lidocaine and epinephrine without a tourniquet or sedation [61].
- A trapeziectomy rehabilitation protocol involves immobilizing the operated hand for 1 week in a back-slab and instructing patients to keep the hand elevated and regularly move fingers, thumb IPJ, elbow, and shoulder [116].
Complications
General Complications and Outcomes
- Management of complications of trapeziectomy is difficult, and the results of a retrospective series of 10 cases were disappointing and disparate [25].
- The postoperative intervals before pronouncing failure and the frequent need for iterative surgery can leave the patient in a position of perpetual convalescence, the functional benefit of which is not guaranteed [25].
- Clumsiness is a symptom that should be asked about in longer term follow-ups to determine if it is a common complaint specific to simple trapeziectomy [32].
- Women who are forty years or older with trapeziometacarpal osteoarthritis have fewer moderate and severe complications after trapeziectomy with ligament reconstruction and tendon interposition than those who undergo arthrodesis [52].
- Patients who undergo arthrodesis have higher reoperation rates and incidence of postoperative complications than those who undergo ligament reconstruction and tendon interposition [135].
- Although complications were more frequent following arthrodesis, most did not affect the overall outcome [134].
- The risk of complications and requirement for further surgery is greater for total joint arthroplasty compared to trapeziectomy and must be carefully considered during patient selection and preoperative counselling [128].
- The event-free survival rate for trapeziectomy with Gore-Tex ligament reconstruction was 92.5% at 5 years, 91.3% at 10 years, and 74.7% at 15 years [49].
- In a series of 117 trapeziectomy procedures with Gore-Tex ligament reconstruction, 16 events were recorded during follow-up [49].
- Complications that did not require revision in a series of trapeziectomy with Gore-Tex ligament reconstruction included chondrocalcinosis, trapezial dysplasia, and transient dysesthesia [49].
- In a series of partial trapeziectomy and interpositional arthroplasty, there were no post-operative infections, but one patient developed a sensitive scar requiring neurolysis of the sensory branch of the radial nerve [110].
- In a series of arthroscopic partial trapeziectomy with soft tissue interposition, there were no infections [114].
- In a series of arthroscopic partial trapeziectomy with soft tissue interposition, five patients developed transient superficial radial nerve neuritis that resolved over 3 months [114].
- In a series of arthroscopic partial trapeziectomy with soft tissue interposition, one patient developed a 30-degree hyperextension deformity at the MCP joint requiring MCP joint arthrodesis [114].
- In a series of arthroscopic partial trapeziectomy with soft tissue interposition, one patient developed painful instability of the thumb metacarpal base with radial and proximal migration of the thumb metacarpal [114].
- In a series of trapeziectomy with a Weilby sling, Grade 2 and 3 complications are associated with clinically relevant poorer patient-reported outcomes 12 months after surgery [132].
Nerve and Vascular Injuries
- Possible complications of trapeziectomy include injury to the superficial radial nerve or 1 of its branches [59].
- Possible complications of trapeziectomy include injury to the radial artery, which is minimized by a volar approach [59].
- Possible complications of trapeziectomy include injury to the flexor carpi radialis (FCR) tendon during bone removal [59].
- These nerve and vascular complications can be avoided with careful, meticulous dissection [59].
- Potential complications of suture button suspensionplasty include radial artery injury and injury to the FCR tendon during bone removal [106].
- A case report highlights radial artery thrombosis secondary to unrecognized iatrogenic injury during trapeziectomy with ligament reconstruction and tendon interposition [127].
- Thumb and fingertip ischaemia can occur after trapeziectomy [127].
Bony and Structural Complications
- Index metacarpal fracture after suture button suspensionplasty has been reported [106].
- Impingement between the base of the thumb metacarpal and remaining trapezoid should be considered a potential source of pain after trapeziectomy and soft tissue arthroplasty [40].
- Concurrent trapeziectomy with proximal row carpectomy resulted in a significant increase in thumb metacarpal subsidence compared to trapeziectomy alone [62].
- There is a substantial risk of first ray subsidence when performing trapeziectomy and proximal row carpectomy together [62].
- Postoperative subsidence with weakness and recurrence of pain is a potential complication of suture button suspensionplasty [106].
- Due to the potential occurrence of intra- or postoperative complications such as trapezial fracture and trapezial loosening, stage IV osteoarthritis is treated by trapeziectomy [26].
Tendon and Soft Tissue Complications
- High incidence of flexor carpi radialis tendinitis has been reported after trapeziectomy and abductor pollicis longus suspensionplasty for basal joint arthritis [131].
- Patients should be warned about the potential complication of flexor carpi radialis tendinitis after trapeziectomy and abductor pollicis longus suspensionplasty [131].
- Infection is a potential complication of suture button suspensionplasty [106].
- Sensory nerve irritation is a potential complication of suture button suspensionplasty [106].
Recovery
- A postoperative regimen with early mobilization after trapeziectomy is as safe and effective as a postoperative regimen with longer immobilization in patients with first carpometacarpal osteoarthritis [95].
- There was a significant mean decrease (P < 0.001) in the trapezial gap of 61% 2 weeks after surgery [21].
- Improved clinical outcomes can be achieved by maintaining at least 50% of the preoperative trapezial space [16].
- Over a follow-up period of 12 months, trapeziectomy and LRTI is an effective treatment in significantly reducing pain in 80% of patients [42].
- The authors draw attention to clumsiness as a symptom to encourage others to ask patients about it in longer term follow-ups to see whether it is a common complaint and specific to simple trapeziectomy [32].
- In contrast, a large improvement can be expected after trapeziectomy, although it remains unclear how much of this change is attributable to the surgery itself [7].
- The event-free survival rate was 92.5% (95% CI, 86.6–98.4) at 5 years, 91.3% (95% CI, 85–97.6) at 10 years, and 74.7% (95% CI, 62.3–87.1) at 15 years for trapeziectomy with Gore-Tex ligament reconstruction [49].
Key Evidence
- [L1] The outcomes of these 3 variations of trapeziectomy were very similar at 1-year follow-up evaluation. [1] (10.1016/j.jhsa.2004.06.017)
- [L1] Until further larger studies are performed, the value of such additions to trapeziectomy remains unproven. [2] (10.1177/1753193408098483)
- [L3] Secondary trapeziectomy after revision of trapeziometacarpal implants provides results comparable with primary trapeziectomy. [3] (10.1177/17531934211039184)
- [L2] We cannot conclude that partial trapeziectomy provides an advantage over total trapeziectomy at 1 year after surgery. [4] (10.1016/j.jhsg.2020.03.004)
- [L3] The outcomes of secondary trapeziectomy after failed trapeziometacarpal joint replacement arthroplasty generally do not differ from the primary trapeziectomy results. [5] (10.1016/j.jhsa.2013.01.030)
- [L3] These results suggest an advantage of simple trapeziectomy; however, further study is warranted. [6] (10.1177/1558944715617215)
- [L2] In contrast, a large improvement can be expected after trapeziectomy, although it remains unclear how much of this change is attributable to the surgery itself. [7] (10.1016/j.jhsg.2025.100741)
- [L5] They conclude that thumb metacarpal immobilization after trapeziectomy is now routinely employed to address concerns with instability. [8] (10.1177/17531934231217371)
- [L4] Complications after trapeziectomy and suspension arthroplasty can occur despite proper preoperative evaluation, meticulous surgical technique, and vigilant postoperative rehabilitation. [9] (10.1016/j.jhsa.2013.07.018)
- [L4] Trapeziectomy with this alternative suspension technique for treatment of carpometacarpal thumb joint osteoarthritis shows good patient-reported outcome measures for primary surgery and poor patient-reported outcome measures after the secondary surgery. [10] (10.1016/j.jhsg.2022.02.006)
- [Paper] Without the need for an implant and because of its long-lasting benefits, total trapeziectomy is currently the only surgical technique for thumb basal joint arthritis that can lay claim to being a potential life-long procedure. [11] (10.1016/j.hansur.2020.05.015)
- [L4] The functional results of trapeziectomy through the anterior approach are equally good with the results of trapeziectomy through the standard approaches. [12] (10.1097/00130911-200206000-00005)
- [L3] Trapeziectomy combined with Swanson implant gives better results in the short term if there are no complications of the operation. [13] (10.1054/jhsb.1999.0156)
- [L1] The outcomes of these 3 variations of trapeziectomy were similar after a minimum follow-up of 5 years. [14] (10.1016/j.jhsa.2011.11.027)
- [L3] It is thus appropriate to use standard radiographs at the 1-year follow-up examination to assess and compare the trapezial space after these different techniques of trapeziectomy. [15] (10.1053/jhsu.2003.50065)
- [L4] Improved clinical outcomes can be achieved by maintaining at least 50% of the preoperative trapezial space. [16] (10.1016/j.hansur.2021.01.002)
- [L4] Complete trapezoid excision is not recommended. [17] (10.1016/j.jhsa.2019.10.006)
- [L2] Simple excision of the trapezium remains an acceptable treatment for osteoarthritis of the trapeziometacarpal joint. [18] (10.1007/s11999-013-2956-0)
- [L4] These results appear to last for a minimum of 4 years and are comparable to those reported for open techniques involving complete trapeziectomy. [19] (10.1016/j.jhsa.2009.12.022)
- [L4] Due to no significant differences in outcomes between partial and complete excision, the authors now prefer partial trapezoid excision. [20] (10.1016/j.jhsa.2017.06.062)
- [L4] There was a significant mean decrease (P < 0.001) in the trapezial gap of 61% 2 weeks after surgery. [21] (10.1016/j.jhsb.2006.06.004)
- [Case_report] Surgeons should use caution when considering suture button fixation after complete trapeziectomy until more data are available. [22] (10.1016/j.jhsa.2011.12.017)
- [L3] [23] (10.1016/j.main.2009.02.001)
- [L4] [25] (10.1016/j.hansur.2021.03.014)
- [L4] Due to the potential occurrence of intra- or postoperative complications such as trapezial fracture and trapezial loosening, stage IV OA is treated by trapeziectomy. [26] (10.1016/j.hansur.2019.11.012)
- [L3] In view of the comparable results of the three treatments investigated in this study, we recommend excision of the trapezium with or without soft-tissue reconstruction as the operation of choice in middle aged to elderly patients. [27] (10.1016/j.jhsb.2004.08.006)
- [L3] The removal of a pyrocarbon carpometacarpal implant using subsequent trapeziectomy successfully relieves pain in patients in whom pyrocarbon arthroplasty has failed. [28] (10.1016/j.jhsa.2022.01.004)
- [L4] [29] (10.1177/1753193413514500)
- [L4] Important improvements in web space with increased palmar and radial abduction and grip and pinch strength measurements were observed. [30] (10.1053/jhsu.2000.jhsu025a0061)
- [L4] Scaphometacarpal arthroplasty is a reliable medium-term solution for revision of the loosening of a trapeziometacarpal prosthesis with trapezial damage and for failed trapeziectomy. [31] (10.1177/1753193419900470)
- [L4] The authors draw attention to this symptom to encourage others to ask patients about it in longer term follow-ups to see whether it is a common complaint and specific to simple trapeziectomy. [32] (10.1177/1753193414567828)
- [L4] The total video-assisted trapeziectomy fulfills 2 premises: a simple technique and comfort for the patient. [33] (10.1097/bth.0b013e3181f42899)
- [L1] [34] (10.1053/jhsu.2001.27761)
- [L4] [35] (10.1016/j.jhsa.2012.02.007)
- [L4] The procedure provides excellent pain relief and significant improvement in strength of thumb grip in severe carpometacarpal osteoarthritis. [36] (10.1053/jhsu.1999.0469)
- [L4] However, functional outcomes were not superior to simpler techniques like trapeziectomy with or without ligamentoplasty, suggesting a potential role only in select young patients as a time-procuring procedure. [37] (10.1177/1753193420906805)
- [L1] At 1 year, total joint arthroplasty showed no superiority over trapeziectomy regarding the total score of the Michigan Hand Outcomes Questionnaire, but demonstrated a significant advantage in strength and range of motion. [39] (10.1177/17531934231185245)
- [L4] Impingement between the base of the thumb metacarpal and remaining trapezoid should be considered a potential source of pain after trapeziectomy and soft tissue arthroplasty. [40] (10.1016/j.jhsa.2021.02.017)
- [L2] Over a follow-up period of 12 months, trapeziectomy and LRTI is an effective treatment in significantly reducing pain in 80% of patients. [42] (10.1016/j.jhsa.2021.04.036)
- [L4] No intracarpal deformities were seen and there was no sign of graft wear; the length of the thumb ray is preserved. [43] (10.1016/j.main.2012.03.002)
- [L3] Trapeziectomy produces better functional results and overall satisfaction than pyrocarbon arthroplasty. [44] (10.1177/1753193411433176)
- [L4] [49] (10.1016/j.otsr.2022.103366)
- [L4] Trapeziectomy and LRTI are effective procedures for patients aged less than 56 years. [50] (10.1016/j.jhsa.2024.07.024)
- [L5] This biomechanical cadaveric study shows that performing a trapeziectomy followed by up to 4 mm of proximal trapezoid resection has a negligible effect upon carpal, specifically lunocapitate and scapholunate, stability. [51] (10.1016/j.jhsa.2019.06.015)
- [L1] Women who are forty years or older with trapeziometacarpal osteoarthritis have fewer moderate and severe complications after trapeziectomy with ligament reconstruction and tendon interposition and are more likely to consider the surgery again under the same circumstances than are those who undergo arthrodesis. [52] (10.2106/jbjs.l.01344)
- [L5] The study found several biomechanic advantages to the implant compared with LRTI, including reduction in axial and radial displacement and maintenance of the trapezial space. [53] (10.1016/j.jhsa.2007.02.025)
- [L4] Excellent results were achieved in 23 thumbs or 92% of cases, with no deterioration of function or stability noted over time and no revisional procedures necessary. [54] (10.1016/s0363-5023(86)80137-x)
- [L3] Although there is some reduction in thumb abduction from 3.5 to 13 years after surgery, other gains after surgery are retained and in some instances slightly improved. [55] (10.1186/s12891-016-0910-5)
- [L5] The procedure results in a stable thumb with pain relief. [56] (10.1097/bth.0000000000000048)
- [L4] [59] (10.1097/bth.0b013e3181e71728)
- [L4] [60] (10.1177/1753193419843850)
- [L4] The paper presents a video detailing the technique for wide-awake basal joint trapeziectomy using only locally injected lidocaine and epinephrine without a tourniquet or sedation. [61] (10.1007/s11552-011-9367-z)
- [L5] Concurrent trapeziectomy with PRC resulted in a significant increase in thumb metacarpal subsidence compared to trapeziectomy alone, suggesting a substantial risk of first ray subsidence when performing both operations together. [62] (10.1016/j.jhsa.2023.06.013)
- [L1] Trapeziectomy is a good method of treating osteoarthritis of the thumb base, but outcomes for the anterior approach are equally good or better than with the posterior approach. [79] (10.1177/1753193407087571)
- [L5] [80] (10.1007/s11552-012-9473-6)
- [L5] The impact on wrist mobility is moderate. [81] (10.1016/j.main.2015.05.002)
- [L1] Simple trapeziectomy is an effective operation for osteoarthrosis at the base of the thumb and the addition of a ligament reconstruction was not shown to confer any additional benefit. [82] (10.1054/jhsb.2000.0431)
- [L4] The authors used continuous local anaesthetic infusion following trapeziectomy as a routine for 3 years on 40 patients. [83] (10.1016/j.jhsb.2006.04.022)
- [L2] Brief psychological screening shows that patients with psychological risk factors experience improved pain and function outcomes following trapeziectomy, however their outcomes are significantly worse than patients who do not have psychological risk factors. [84] (10.1177/17589983221120839)
- [L5] This biomechanical cadaver study supports the hypothesis that trapeziectomy results in proximal migration of the first metacarpal, which is mitigated by suture suspensionplasty while maintaining normal motion. [85] (10.1016/j.jhsa.2022.05.001)
- [L1] Furthermore, proximal migration of the thumb metacarpal does not appear to influence the functional outcome. [86] (10.2106/jbjs.d.02630)
- [L5] The decrease in key pinch force was larger than the relatively small increase in thumb CMC force. [87] (10.1016/j.jhsa.2022.11.018)
- [L5] These findings provide biomechanical context for reported index metacarpal fractures following SBS and may inform surgical technique and patient counseling. [89] (10.1016/j.jhsa.2026.07.009)
- [L5] The position of the bone anchor in the thumb metacarpal base did not affect the range of motion. [90] (10.1016/j.jhsa.2022.08.001)
- [L4] The modified procedure improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength. [92] (10.1177/1753193414553368)
- [L4] This technique also provided an increase in grip strength and key pinch with return of range of motion early in the postoperative period. [93] (10.1016/j.jhsa.2015.10.010)
- [L3] LRTI and SSA exhibit equivalent thumb metacarpal subsidence over a greater than 6-month postoperative time frame. [94] (10.1177/15589447221084014)
- [L2] A postoperative regimen with early mobilization after trapeziectomy is as safe and effective as a postoperative regimen with longer immobilization in patients with first carpometacarpal osteoarthritis. [95] (10.1016/j.jhsa.2021.08.015)
- [L4] According to our series, this surgical technique relieves pain and provides stability and mobility of the thumb. [96] (10.1016/j.main.2012.10.170)
- [L4] Our results compare well with those of most studies in the literature in terms of pain relief, thumb motion, pinch strength, and function. [99] (10.1016/j.hansur.2020.11.010)
- [L4] The use of a tenodesis screw and half of the flexor carpi radialis had minor advantages, such as increasing the grip and key pinch strength without differences relative to the non-operated thumb, and minimal migration of the first metacarpal bone compared with the other technique. [101] (10.1016/j.hansur.2021.03.009)
- [L5] Combining the trapeziectomy with surgeries addressing the MCP-1-joint hyperextension induced a shift of the thumb in pronation-abduction that could impair the key-pinch stability. [102] (10.1142/s2424835519500206)
- [L4] Total trapeziectomy with external minifixation provides acceptable clinical results, stabilizes the base of the thumb and prevents scapho-metacarpal impingement. [103] (10.1016/j.main.2013.10.180)
- [L5] Both TightRope constructs provided improved axial stability after trapeziectomy while not excessively limiting any one motion of the thumb. [104] (10.1177/1558944720906551)
- [L4] With axial compressive loading of the arthroplasty, such as in lateral pinch, there is some further proximal migration of the first metacarpal, but this is minimal and does not correlate with functional outcome. [105] (10.1016/s0363-5023(98)80167-6)
- [L4] [106] (10.1016/j.jhsa.2014.09.012)
- [L5] This simple surgical reconstruction abducts the first metacarpal bone and improves metacarpophalangeal joint hyperextension. [107] (10.1097/bth.0000000000000265)
- [L4] Trapeziectomy with LRTI after TMC joint replacement appears to be an attractive salvage procedure. [109] (10.1016/j.hansur.2015.09.002)
- [L4] [110] (10.1016/s0266-7681(05)80140-8)
- [L4] [114] (10.1016/j.jhsa.2017.10.016)
- [L3] [116] (10.1177/1758998317691792)
- [L4] The study cannot demonstrate that the radiographic presence of scaphotrapezoidal arthritis correlates with the patient's main symptoms after partial trapeziectomy. [117] (10.1016/j.jhsg.2020.06.005)
- [L1] [122] (10.1177/1753193420952966)
- [L4] The trapezium space lost 14% of its height compared with preoperative values, and there were no cases of instability. [125] (10.1016/j.jhsa.2006.07.002)
- [L5] This case highlights radial artery thrombosis secondary to unrecognized iatrogenic injury during trapeziectomy with LRTI. [127] (10.1177/17531934231151215)
- [L3] However the risk of complications and requirement for further surgery is greater and must be carefully considered during patient selection and preoperative counselling. [128] (10.1142/s0218810417500526)
- [L4] Patients should be warned about this potential complication. [131] (10.1177/1753193413506150)
- [L4] We recommend describing Grade 1 as 'adverse protocol deviations' and grade 2 and 3 as complications, because of clinically relevant poorer patient-reported outcomes 12 months after surgery. [132] (10.1016/j.jhsa.2023.01.022)
- [L3] Although complications were more frequent following arthrodesis, most did not affect the overall outcome. [134] (10.2106/00004623-200110000-00002)
- [L1] Patients who undergo arthrodesis have higher reoperation rates and incidence of postoperative complications than those who undergo LRTI. [135] (10.1016/j.jhsa.2024.10.018)
References
[1] Excision of the trapezium for osteoarthritis of the trapeziometacarpal joint: A study of the benefit of ligament reconstruction or tendon interposition. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.06.017
[2] Trapeziectomy for Trapeziometacarpal Joint Osteoarthritis: Is Ligament Reconstruction and Temporary Stabilisation of the Pseudarthrosis with a Kirschner Wire Important?. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193408098483
[3] Outcomes of secondary trapeziectomy after revision of trapeziometacarpal implants: a retrospective comparative matched study. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/17531934211039184
[4] Partial Versus Total Trapeziectomy With Interposition Arthroplasty for Trapeziometacarpal Osteoarthritis Grade II to III Eaton-Littler: A Clinical Trial. Journal of Hand Surgery Global Online. 2020. DOI: 10.1016/j.jhsg.2020.03.004
[5] Outcome Comparison of Primary Trapeziectomy Versus Secondary Trapeziectomy Following Failed Total Trapeziometacarpal Joint Replacement. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.01.030
[6] Increased Complications in Trapeziectomy With Ligament Reconstruction and Tendon Interposition Compared With Trapeziectomy Alone. HAND. 2016. DOI: 10.1177/1558944715617215
[7] Orthosis Followed by Trapeziectomy for Thumb Base Osteoarthritis: A Cohort Pilot Study on Pain and Function. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2025.100741
[8] Re: Lui H, Galbraith JG, Meyers K, Bindra R, Lee SK. Biomechanical analysis of three techniques of suspensionplasty after trapeziectomy: a cadaveric study. J Hand Surg Eur. 2023, doi:10.1177/17531934231186495. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231217371
[9] Complications of Trapeziectomy With or Without Suspension Arthroplasty. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.07.018
[10] Trapeziectomy and Alternative Suspension Technique in Thumb Carpometacarpal Arthritis: Patient-Reported Outcome Measures. Journal of Hand Surgery Global Online. 2022. DOI: 10.1016/j.jhsg.2022.02.006
[11] Total trapeziectomy. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.05.015
[12] Anterior Approach for Trapeziectomy. Techniques in Hand and Upper Extremity Surgery. 2002. DOI: 10.1097/00130911-200206000-00005
[13] A Patient-Reported Comparison of Trapeziectomy with Swanson Silastic Implant or Sling Ligament Reconstruction. Journal of Hand Surgery. 1999. DOI: 10.1054/jhsb.1999.0156
[14] Five- to 18-Year Follow-Up for Treatment of Trapeziometacarpal Osteoarthritis: A Prospective Comparison of Excision, Tendon Interposition, and Ligament Reconstruction and Tendon Interposition. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.11.027
[15] Trapezial space height measurement after trapeziectomy: A comparison of the use of standard and stress radiographs. The Journal of Hand Surgery. 2003. DOI: 10.1053/jhsu.2003.50065
[16] The effect of remaining trapezial space on outcomes after trapeziectomy with ligament reconstruction tendon interposition for trapeziometacarpal osteoarthritis. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.01.002
[17] Effect of Partial and Complete Trapezoid Excision on Radiographic and Functional Results After Abductor Pollicis Longus Suspensionplasty. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.10.006
[18] Degenerative Change at the Pseudarthrosis After Trapeziectomy at 6-year Followup. Clinical Orthopaedics & Related Research. 2014. DOI: 10.1007/s11999-013-2956-0
[19] Prospective Outcomes of Stage III Thumb Carpometacarpal Arthritis Treated With Arthroscopic Hemitrapeziectomy and Thermal Capsular Modification Without Interposition. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2009.12.022
[20] Long-term Outcomes of APL Suspensionplasty with No, Partial, or Complete Trapezoid Excision. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.062
[21] The Gap after Trapeziectomy: A Prospective Study. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2006.06.004
[22] Index Metacarpal Fracture After Tightrope Suspension Following Trapeziectomy: Case Report. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.12.017
[23] Partial trapeziectomy with ligament reconstruction – tendon interposition in thumb carpo-metacarpal osteoarthritis. A study of 112 cases. Chirurgie de la Main. 2009. DOI: 10.1016/j.main.2009.02.001
[25] Revision of trapeziectomy failures in thumb base osteoarthritis: retrospective analysis of ten cases and review of the literature. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.03.014
[26] Trapeziometacarpal total joint replacement as an alternative to trapeziectomy depends on trapezium height: Retrospective study of 67 patients. Hand Surgery and Rehabilitation. 2020. DOI: 10.1016/j.hansur.2019.11.012
[27] A Comparison of Fusion, Trapeziectomy and Silastic Replacement for the Treatment of Osteoarthritis of the Trapeziometacarpal Joint. Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsb.2004.08.006
[28] Outcomes of Secondary Trapeziectomy Following Carpometacarpal Pyrocarbon Prosthetic Arthroplasty. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.01.004
[29] Trapeziectomy and ligament reconstruction tendon interposition for isolated scaphotrapeziotrapezoid osteoarthritis of the wrist. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413514500
[30] Thumb trapeziometacarpal joint arthritis: Partial trapeziectomy with ligament reconstruction and interposition costochondral allograft. The Journal of Hand Surgery. 2000. DOI: 10.1053/jhsu.2000.jhsu025a0061
[31] Scaphometacarpal arthroplasty: a report of ten cases of trapeziometacarpal prosthesis and trapeziectomy revision. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193419900470
[32] Clumsiness: a complication of trapeziectomy for thumb carpometacarpal joint arthritis?. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567828
[33] Arthroscopic Total Trapeziectomy. Techniques in Hand & Upper Extremity Surgery. 2010. DOI: 10.1097/bth.0b013e3181f42899
[34] Trapezial space height after trapeziectomy: Mechanism of formation and benefits. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.27761
[35] The Scaphotrapezial Joint After Partial Trapeziectomy for Trapeziometacarpal Joint Arthritis: Long-term Follow-up. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.02.007
[36] Abductor pollicis longus tendon interposition arthroplasty for carpometacarpal osteoarthritis of the thumb. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0469
[37] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420906805
[39] Total joint arthroplasty versus trapeziectomy in the treatment of trapeziometacarpal joint arthritis: a randomized controlled trial. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231185245
[40] Thumb Metacarpal-Trapezoid Impingement as an Etiology of Pain After Trapeziectomy and Basal Joint Soft Tissue Arthroplasty: A Case Series. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.02.017
[42] Functional Recovery Following Trapeziectomy and Ligament Reconstruction and Tendon Interposition: A Prospective Longitudinal Study. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.04.036
[43] Treatment of trapeziometacarpal osteoarthritis by partial trapeziectomy and costal cartilage autograft. A review of 100 cases. Chirurgie de la Main. 2012. DOI: 10.1016/j.main.2012.03.002
[44] Thumb carpometacarpal osteoarthritis: trapeziectomy versus pyrocarbon interposition implant (Pi2) arthroplasty. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193411433176
[47] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[48] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[49] Long-term outcomes of trapeziectomy with Gore-Tex® ligament reconstruction for trapezio-metacarpal osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2024. DOI: 10.1016/j.otsr.2022.103366
[50] Outcome of Trapeziectomy and Ligament Reconstruction and Tendon Interposition for Patients Aged Less Than 56 Years: A Retrospective Study With a Minimum 5-Year Follow-Up. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.07.024
[51] The Biomechanical Consequences of Trapeziectomy and Partial Trapezoidectomy in the Treatment of Thumb Carpometacarpal and Scaphotrapeziotrapezoid Arthritis. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.06.015
[52] Trapeziometacarpal Arthrodesis or Trapeziectomy with Ligament Reconstruction in Primary Trapeziometacarpal Osteoarthritis. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.l.01344
[53] Biomechanic Analysis of Trapeziectomy, Ligament Reconstruction With Tendon Interposition, and Tie-In Trapezium Implant Arthroplasty for Thumb Carpometacarpal Arthritis: A Cadaver Study. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.02.025
[54] Surgical management of basal Joint arthritis of the thumb. Part II. Ligament reconstruction with tendon interposition arthroplast. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80137-x
[55] Abductor pollicis longus tendon interposition for arthrosis of the first carpo-metacarpal joint. Long-term results. BMC Musculoskeletal Disorders. 2016. DOI: 10.1186/s12891-016-0910-5
[56] Partial Trapeziectomy With Capsular Interposition Arthroplasty (PTCI). Techniques in Hand & Upper Extremity Surgery. 2014. DOI: 10.1097/bth.0000000000000048
[59] Ligament Reconstruction Tendon Interposition With Mersilene Augmentation. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e3181e71728
[60] A health utility assessment of trapeziectomy with ligament reconstruction and tendon interposition for thumb trapeziometacarpal osteoarthritis. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419843850
[61] Wide-Awake Trapeziectomy: Video Detailing Local Anesthetic Injection and Surgery. HAND. 2011. DOI: 10.1007/s11552-011-9367-z
[62] The Effect of Proximal Row Carpectomy and Trapeziectomy on First Ray Stability: A Cadaveric Study. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.06.013
[63] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[64] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[67] Exam Of The Hand Wrist 2Ed. Planning skin cover of the hand and forearm.
[68] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[69] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[72] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[74] Exam Of The Hand Wrist 2Ed. The dorsal skin.
[75] Green S Operative Hand Surgery. PERTINENT ANATOMY.
[79] A Comparison of Trapeziectomy Via Anterior and Posterior Approaches. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193407087571
[80] Suture Button Suspension following Trapeziectomy in a Cadaver Model. HAND. 2012. DOI: 10.1007/s11552-012-9473-6
[81] Surgical treatment after a failed trapeziectomy: A case report. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2015.05.002
[82] A Comparison of Trapeziectomy with and without Ligament Reconstruction and Tendon Interposition. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.2000.0431
[83] Continuous Local Anaesthetic Infusion after Trapeziectomy for Pain Relief. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2006.04.022
[84] Brief psychological screening for trapeziectomy: Identifying patients at high risk of a poor functional outcome. Hand Therapy. 2022. DOI: 10.1177/17589983221120839
[85] First Carpometacarpal Joint Motion and Proximal Migration of the First Metacarpal After Tensioning of a Suture Device Suspensionplasty Compared With Trapeziectomy: A Biomechanical Cadaver Study. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.05.001
[86] Ligament Reconstruction with or without Tendon Interposition to Treat Primary Thumb Carpometacarpal Osteoarthritis. Journal of Bone and Joint Surgery. 2005. DOI: 10.2106/jbjs.d.02630
[87] The Effect of Thumb Metacarpophalangeal Hyperextension on Thumb Axial Load and Lateral Pinch Force in a Cadaver Model of Thumb Trapeziectomy and Flexor Carpi Radialis Suspensionplasty. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.11.018
[89] Index Metacarpal Fracture Risk in Suture Button Suspensionplasty and the Effects of Drill Hole Position: A Cadaveric Study. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2026.07.009
[90] Optimal Position of the Bone Anchor for the Internal Brace Suspensionplasty Technique for Thumb Basal Joint Arthroplasty. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.08.001
[92] Re: Mariconda et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. J Hand Surg Eur. 2014, 39: 604–610. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414553368
[93] Trapeziectomy Arthroplasty With Suture Suspension: Short- to Medium-Term Outcomes From a Single-Surgeon Experience. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2015.10.010
[94] Radiographic Thumb Metacarpal Subsidence Following Ligament Reconstruction With Tendon Interposition and Suture-Only Suspension Arthroplasty in the Treatment of Basal Joint Arthritis. HAND. 2022. DOI: 10.1177/15589447221084014
[95] Comparison of 2 Postoperative Therapy Regimens After Trapeziectomy Due to Osteoarthritis: A Randomized, Controlled Trial. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.08.015
[96] Ligament reconstruction and tendon interposition arthroplasty of the trapeziometacarpal joint with the use of the full thickness of the flexor carpi radialis tendon. Chirurgie de la Main. 2012. DOI: 10.1016/j.main.2012.10.170
[99] Trapeziectomy and suspension arthroplasty with the flexor carpi radialis tendon for treatment of trapeziometacarpal osteoarthritis. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.11.010
[101] Thumb carpometacarpal arthroplasty and trapeziectomy using a tenodesis screw compared to ligament reconstruction. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.03.009
[102] Benefits of Additional Procedures for Metacarpophalangeal Hyperextension on Simple Trapeziectomy in Thumb Basal Osteoarthritis: A Biomechanical Cadaver Study. The Journal of Hand Surgery (Asian-Pacific Volume). 2019. DOI: 10.1142/s2424835519500206
[103] Trapeziometacarpal osteoarthrosis: Clinical results and sonographic evaluation of the interposed tissue after trapeziectomy and first metacarpal suspension by external minifixation at a minimal two-year follow-up. Chirurgie de la Main. 2014. DOI: 10.1016/j.main.2013.10.180
[104] Optimal Position of the Suture Button Suspensionplasty (TightRope) for Thumb Basal Joint Arthritis. HAND. 2020. DOI: 10.1177/1558944720906551
[105] First metacarpal subsidence during pinch after ligament reconstruction and tendon interposition basal joint arthroplasty of the thumb. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80167-6
[106] Double Tightrope for Basilar Thumb Arthritis. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.09.012
[107] Suture Suspension Arthroplasty With Trapeziectomy for Thumb Carpometacarpal Arthritis Using a Wide-awake Approach. Techniques in Hand & Upper Extremity Surgery. 2019. DOI: 10.1097/bth.0000000000000265
[109] Trapeziectomy and ligament reconstruction tendon interposition after failed trapeziometacarpal joint replacement. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2015.09.002
[110] Partial Trapeziectomy and Interpositional Arthroplasty for Trapeziometacarpal Osteoarthritis of the Thumb. Journal of Hand Surgery. 1995. DOI: 10.1016/s0266-7681(05)80140-8
[114] Arthroscopic Partial Trapeziectomy With Soft Tissue Interposition for Symptomatic Trapeziometacarpal Arthritis: 6-Month and 5-Year Minimum Follow-Up. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.10.016
[116] Development and implementation of a trapeziectomy rehabilitation protocol. Hand Therapy. 2017. DOI: 10.1177/1758998317691792
[117] Long-Term Evaluation Following Partial Trapeziectomy and Suspension Arthroplasty for Trapeziometacarpal Osteoarthritis: An Observational Study. Journal of Hand Surgery Global Online. 2020. DOI: 10.1016/j.jhsg.2020.06.005
[122] Simple trapeziectomy versus trapeziectomy with flexor carpi radialis suspension: a 17-year follow-up of a randomized blind trial. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420952966
[125] Trapeziectomy and Intermetacarpal Ligament Reconstruction With the Extensor Carpi Radialis Longus for Osteoarthritis of the Trapeziometacarpal Joint: Surgical Technique and Long-Term Results. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.07.002
[127] Thumb and fingertip ischaemia after trapeziectomy. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231151215
[128] Early Results of the ARPE Arthroplasty Versus Trapeziectomy for the Treatment of Thumb Carpometacarpal Joint Osteoarthritis. The Journal of Hand Surgery (Asian-Pacific Volume). 2017. DOI: 10.1142/s0218810417500526
[131] High incidence and treatment of flexor carpi radialis tendinitis after trapeziectomy and abductor pollicis longus suspensionplasty for basal joint arthritis. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413506150
[132] Prevalence of Complications and Association With Patient-Reported Outcomes After Trapeziectomy With a Weilby Sling: A Cohort Study. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.01.022
[134] Thumb Carpometacarpal Osteoarthritis: Arthrodesis Compared with Ligament Reconstruction and Tendon Interposition. The Journal of Bone and Joint Surgery-American Volume. 2001. DOI: 10.2106/00004623-200110000-00002
[135] Arthrodesis Versus Ligament Reconstruction and Tendon Interposition for Thumb Carpometacarpal Joint Arthritis: A Systematic Review and Meta-Analysis. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.10.018