Patients › Wrist
Lesão do CFTC
TFCC injuries — pain on the ulnar side of the wrist, often with clicking, and treatment options.
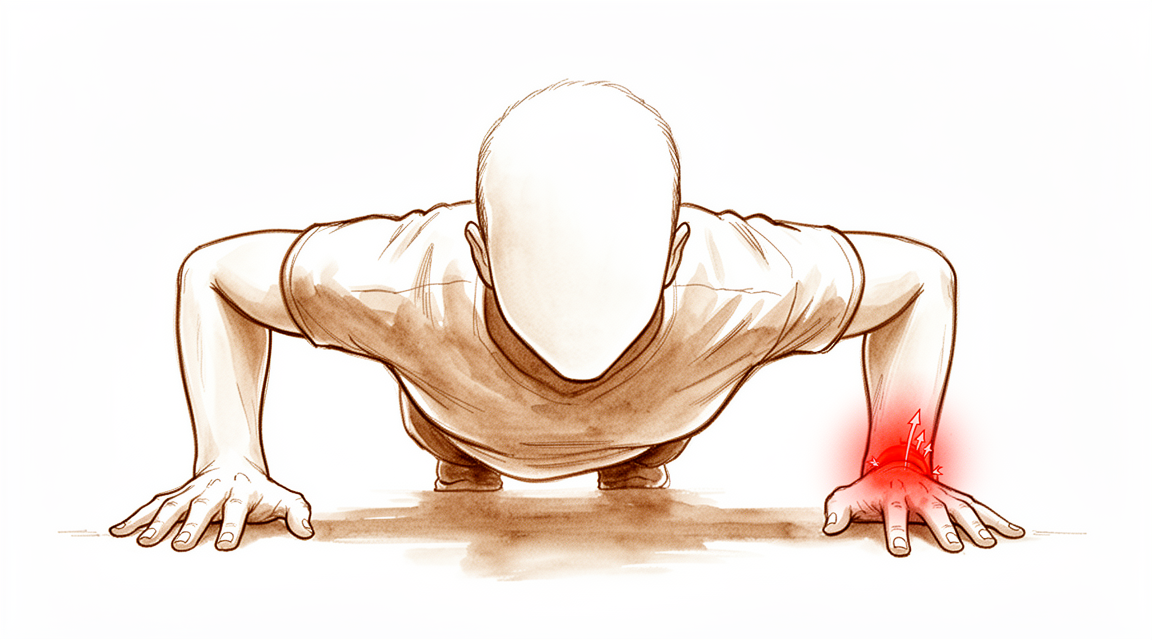
O que você está sentindo
A dor fica no lado do dedo mínimo do seu punho, o lado ulnar. Ela costuma piorar quando você coloca carga nesse lado: ao se apoiar para levantar de uma cadeira, ao segurar um pote com força ou ao girar uma maçaneta enquanto segura algo pesado. Movimentos de torção, como torcer um pano ou usar uma chave de fenda, também podem desencadeá-la.
Algumas pessoas percebem que o punho parece instável, como se fosse ceder, ou que dá um estalo quando o antebraço gira. Outras têm uma dor que persiste sem nenhuma causa clara nos exames de imagem, o que é comum nessa parte do punho. A dor pode ser pior depois da atividade e pode incomodar à noite ou logo ao acordar.
No dia a dia, as tarefas que exigem segurar com firmeza e girar ficam difíceis: abrir uma tampa emperrada, carregar uma sacola de compras pesada desse lado ou se apoiar na mão para levantar de um assento baixo. Trabalhos que envolvem ferramentas ou esforço repetido do punho podem manter a dor.
Se os seus sintomas não estiverem melhorando, estiverem piorando ao longo de semanas, acordarem você à noite ou impedirem você de trabalhar ou de usar a mão, consulte o seu médico de família ou peça uma avaliação com especialista.
O que está realmente acontecendo
Dentro do seu punho, no lado do dedo mínimo, há uma estrutura chamada complexo fibrocartilaginoso triangular, ou TFCC. Imagine-a como um amortecedor com cordas presas a ele. O amortecedor é um disco de cartilagem resistente e lisa que fica entre a extremidade da ulna, o osso do antebraço desse lado, e os pequenos ossos do punho. As cordas são ligamentos que prendem esse disco à ulna e estabilizam a articulação onde os dois ossos do antebraço se encontram no punho.
O TFCC faz duas funções ao mesmo tempo. Ele amortece a carga que passa pelo lado ulnar do punho e mantém essa articulação do antebraço unida enquanto você vira a palma da mão para cima e para baixo. Essa dupla função explica os dois padrões descritos acima. Quando a parte do amortecedor se rompe, colocar carga nesse lado dói: ao se apoiar para levantar de uma cadeira, ao segurar com força, ao torcer. Quando as cordas se soltam do seu ponto de fixação na ulna, a própria articulação perde a sua sustentação, por isso o punho parece que vai ceder ou dá um estalo quando o antebraço gira. O segundo padrão é mais importante, porque é a parte ligamentar que mantém a articulação unida.
Há mais uma coisa que vale a pena saber sobre esse local. Apenas a borda externa do TFCC tem suprimento sanguíneo, aproximadamente os 10% a 40% mais externos dele. A parte interna quase não recebe sangue. É o sangue que traz a cicatrização, por isso as rupturas perto da borda têm uma chance real de se reparar, enquanto as rupturas no meio tendem a não cicatrizar sozinhas. É também por isso que uma ruptura nesse local pode continuar doendo: o tecido lesionado fica em um lugar onde o corpo tem dificuldade para repará-lo, e cada vez que você segura ou torce algo, ele continua recebendo carga.
Portanto, a dor, os estalos e a sensação de que o punho vai ceder não são problemas separados. Eles são o que acontece quando uma estrutura de amortecimento e sustentação, que recebe carga a cada movimento da mão, deixa de cumprir as suas duas funções.
O que podemos fazer a respeito
O Dr. Kieran Hirpara, cirurgião de membro superior no Mater Private Hospital Rockhampton, começa com as opções menos invasivas adequadas ao seu caso. Em geral, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que você nos procurasse, ainda assim será necessário um encaminhamento do seu médico de família para ter direito ao reembolso do Medicare. Nessa primeira consulta, colhemos a sua história clínica, examinamos o seu punho e solicitamos exames de imagem, quando necessário, para descobrir o que está rompido.
Algumas rupturas do TFCC melhoram sem cirurgia. Uma tala pode manter o punho imóvel e tirar a carga do ponto dolorido, enquanto a borda externa, a parte que tem suprimento sanguíneo, tem a chance de se reparar. A terapia da mão busca aliviar a dor e recuperar a força e a preensão, para que o punho volte a suportar as cargas do dia a dia. Geralmente damos a essas medidas um bom período de semanas antes de avaliar se estão funcionando.
Analgésicos e anti-inflamatórios podem ajudar você a continuar se movimentando enquanto a ruptura melhora. Eles não reparam o tecido; eles tornam os dias mais confortáveis.
Se, depois disso, a dor ou os estalos ainda limitarem você, conversamos sobre cirurgia. O primeiro passo padrão é uma cirurgia minimamente invasiva, chamada artroscopia de punho. O cirurgião examina o interior da articulação por pequenos cortes usando uma câmera minúscula, que é a forma mais precisa de confirmar uma ruptura do TFCC e, ao mesmo tempo, avaliar os ligamentos e as superfícies articulares. Algumas rupturas podem ser regularizadas ou reparadas por esses mesmos pequenos cortes. Quando o amortecedor está desgastado e o lado do dedo mínimo do punho está sobrecarregado, um procedimento pode desgastar uma pequena quantidade da extremidade da ulna para aliviar a pressão desse lado. A escolha entre regularizar a ruptura, repará-la ou reconstruí-la com um enxerto de tendão depende de onde a ruptura está e de há quanto tempo ela existe.
Esta é uma decisão compartilhada. Explicamos o que cada opção envolve e o que ela pode e não pode mudar, e você decide o que se adequa ao seu punho e à sua vida.
O que esperar
Para muitas pessoas, uma ruptura do TFCC melhora com o tempo e com o cuidado adequado. As rupturas perto da borda externa, onde está o suprimento sanguíneo, têm uma chance real de se reparar sozinhas ou com uma tala. As rupturas mais profundas no amortecedor tendem a não cicatrizar sozinhas, mas a dor ainda pode diminuir quando o punho é poupado e recebe menos carga.
A recuperação é gradual, e não repentina. A maioria das pessoas percebe a dor diminuindo ao longo de semanas, e não de dias, e a força para segurar e girar volta à medida que o punho melhora. Se você fizer uma cirurgia minimamente invasiva para uma ruptura isolada nesse lado do dedo mínimo, o tempo médio de volta ao trabalho é de 5,5 semanas. Atletas podem levar mais tempo para voltar ao seu esporte, principalmente se houver outras lesões no mesmo lado do punho. Um padrão que vale a pena conhecer: se a extremidade da ulna estava pressionando o punho e causando dor, essa dor tende a voltar quando você retoma o esporte.
Se a ruptura não for tratada, o prognóstico depende de qual parte está lesionada. Uma ruptura na borda pode se acalmar. Uma ruptura no meio, ou uma em que as cordas ligamentares se soltaram, muitas vezes continua doendo a cada vez que você segura ou torce algo, porque esse tecido fica onde o corpo tem dificuldade para repará-lo. A sensação de que o punho vai ceder também pode permanecer.
A cirurgia não garante um punho sem dor. Pessoas que fizeram cirurgia minimamente invasiva para dor no punho de longa data melhoraram, em média, cerca de 50% em um ano, e a maioria ainda tinha alguma dor e rigidez nesse momento. O que a cirurgia faz bem é confirmar exatamente o que está rompido e reparar o que pode ser reparado, o que geralmente significa menos dor e um punho que volta a suportar as cargas do dia a dia.
Se os seus sintomas não estiverem melhorando, estiverem piorando ao longo de semanas, acordarem você à noite ou impedirem você de trabalhar ou de usar a mão, consulte o seu médico de família ou peça uma avaliação com especialista.
Quando procurar ajuda médica
A maioria das rupturas do TFCC não é uma emergência. Algumas situações são. Vá ao pronto-socorro no mesmo dia se o seu punho ficar quente, vermelho, inchado e dolorido, especialmente com febre, porque isso indica uma infecção que precisa de atendimento no mesmo dia. O mesmo vale se os seus dedos ou a sua mão ficarem pálidos, frios, brancos ou azulados, ou se você perder subitamente a sensibilidade ou o movimento da mão após uma lesão. Para todo o resto, o momento certo depende da persistência dos sintomas, e não da urgência. Consulte o seu médico de família se a dor no lado do dedo mínimo do punho já durar mais de 3 meses e não tiver melhorado com repouso, tala ou terapia da mão. Peça uma avaliação com especialista mais cedo se o punho parecer instável, ceder ou der um estalo quando você vira a palma da mão para cima e para baixo, pois isso sugere que a parte ligamentar do TFCC se soltou. Uma dor que impede você de trabalhar, acorda você à noite ou continua apesar de exames de imagem normais também merece a opinião de um especialista, porque esse local muitas vezes precisa de uma avaliação mais detalhada do que os exames de imagem sozinhos conseguem oferecer.
Em maior profundidade
Advanced reading: the deeper science (optional)
Esta seção vai além do que você precisa saber para tomar decisões sobre o próprio tratamento. As lesões do complexo fibrocartilaginoso triangular merecem uma leitura mais aprofundada, pois os debates técnicos que dominam a discussão ainda não foram resolvidos; além disso, um detalhe do regime pós-operatório — que recebe bem menos atenção — parece ser importante.
Qual é a função real dessa estrutura
O TFCC é um disco de cartilagem cercado por um feixe de ligamentos, localizado entre a extremidade da ulna e os ossos do carpo. Ele desempenha duas funções simultaneamente: amortece a carga transmitida para o lado ulnar do punho e estabiliza a articulação entre os dois ossos do antebraço no nível do punho — a articulação radioulnar distal.
Essa dupla função explica por que as lesões nessa região se manifestam de duas maneiras distintas. Uma ruptura que afeta principalmente o disco provoca dor sob carga, como ao levantar-se de uma cadeira, ao segurar objetos ou ao torcer o punho. Já uma ruptura que separa as fibras profundas de sua inserção na ulna, a inserção foveolar, gera instabilidade, fazendo com que o paciente sinta que o punho “cede” ou “estala” durante a rotação do antebraço. Esta segunda situação é mais grave, pois é justamente essa inserção ligamentar que mantém a articulação unida.
A RM é precisa, com uma ressalva importante a ser conhecida
O diagnóstico depende em grande medida da imagiologia. Em 1.298 pacientes, a precisão geral da RM foi aceitável; no caso das lesões periféricas, a precisão agregada foi relativamente alta. A RM, quando utilizada com os parâmetros adequados, é considerada o método ideal para diagnosticar os diferentes tipos de lesões [1].
A ressalva refere-se à palavra “periféricas”. A RM apresenta melhor desempenho na região externa do complexo, que é mais vascularizada e onde se encontram as lesões passíveis de reparo. Já as lesões centrais e degenerativas, bem como o estado exato da inserção foveal, são mais difíceis de caracterizar; por isso, os achados do exame clínico e, às vezes, a artroscopia também têm importância no diagnóstico, ao lado da ressonância magnética.
As comparações entre técnicas não são feitas de forma separada
Existem dois debates cirúrgicos recorrentes, e nenhum deles foi resolvido.
No caso da ruptura periférica comum na região ulnar, uma revisão sistemática envolvendo 240 pacientes constatou ausência de evidências de alta qualidade para se chegar a conclusões definitivas sobre a reparação artroscópica versus a reparação aberta; além disso, não há evidências científicas que indiquem superioridade de uma técnica em relação à outra [2].
Quanto à reparação da fóvea, ao comparar o uso de âncoras de sutura com a sutura transóssea em 904 pacientes, ambos os métodos resultaram em melhora dos desfechos funcionais, da dor e da força de preensão, além de baixa taxa de reoperação — porém a comparação quanto à amplitude de movimento permaneceu inconclusiva [3].
A mensagem constante é que a reparação deve restaurar a fixação do tecido; não há comprovação de que o material utilizado para isso influencie o resultado final.
O detalhe pós-operatório que, ao que parece, realmente importa
Neste caso, as evidências são mais discriminatórias e praticamente úteis. Ao comparar os regimes de imobilização após o reparo do complexo fibrocartilaginoso do punho em 288 pacientes, verificou-se que a imobilização pós-operatória pode trazer mais benefícios ao restringir a rotação do antebraço do que ao limitar o movimento do cotovelo; além disso, a restrição adicional da flexão e extensão do cotovelo não demonstrou vantagem consistente [4].
Isso decorre diretamente da anatomia: a estrutura reparada é submetida a carga pela rotação do antebraço, não pela flexão do cotovelo; portanto, a tala deve controlar o movimento de rotação da palma da mão para cima e para baixo. Geralmente, utiliza-se um gesso acima do cotovelo para conseguir esse efeito indiretamente, impedindo a rotação no nível do cotovelo; contudo, essas evidências indicam que o componente do cotovelo não é a parte que faz o trabalho. Para o paciente, passar seis semanas com uma órtese que deixa o cotovelo livre é uma experiência bastante diferente daquela vivida ao usar um gesso acima do cotovelo durante o mesmo período.
Referências
[1] Wang ZX, Chen SL, Wang QQ, Liu B, Zhu J, Shen J. O desempenho da ressonância magnética na detecção de lesões do complexo fibrocartilaginoso triangular: uma meta-análise. J Hand Surg Eur Vol. 2015;40(5):477-84. https://doi.org/10.1177/1753193414567425
[2] Robba V, Fowler A, Karantana A, Grindlay D, Lindau T. Reparo aberto versus artroscópico de rupturas do complexo fibrocartilaginoso triangular do lado ulnar do tipo 1B: uma revisão sistemática. Hand (N Y). 2019;15(4):456-64. https://doi.org/10.1177/1558944718815244
[3] Ma H, Wang J, Yang C. Eficácia da técnica de âncora de sutura e sutura transóssea no reparo artroscópico da fóvea do complexo fibrocartilaginoso triangular: uma revisão sistemática e meta-análise. J Orthop Surg Res. 2024;19(1). https://doi.org/10.1186/s13018-024-04530-4
[4] Lee J, Lee T, Lee S, Lim H, Chang E, Park MO, et al. Imobilização pós-operatória após reparo da fóvea do complexo fibrocartilaginoso triangular: uma revisão sistemática e meta-análise. J Hand Surg Am. 2026;51(5):512.e1-512.e11. https://doi.org/10.1016/j.jhsa.2026.01.029
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Diagnosis and Assessment
- Careful history and physical examination are required to determine whether a TFCC tear is symptomatic [6].
- It is important to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary [6].
- Acute TFCC injuries require differentiation between those causing distal radioulnar joint instability and those that do not [7].
- TFCC injury should be considered with all distal radial fractures [16].
- 1B TFCC injury is most common in patients with distal radius fractures and concomitant TFCC injury [5].
Natural History and Prognosis
- About 40% of patients sustaining a TFCC tear without distal radioulnar joint instability still had pain and disability at 1 year [8].
Surgical Outcomes
- Surgical treatment of TFCC tears and concomitant pathology in the pediatric and adolescent population results in decreased pain, improved motion and stability, and excellent functional outcomes in the majority of patients [3].
- In a series of pediatric and adolescent patients, there was marked improvement in pain, function, and range of motion in patients with TFCC tears and coexisting pathology [1].
- Arthroscopic treatment of TFCC lesions leads to satisfactory functional outcomes [4].
- Current evidence demonstrates that TFCC repair achieves good clinical outcomes, with low complication rates [23].
- There was no statistical difference in clinical outcomes after open versus arthroscopic TFCC repair [27].
- Arthroscopic debridement alone appears to be an effective and safe initial treatment for patients with traumatic central TFCC tears [32].
- With appropriate indications and patient selection, arthroscopic foveal repair of the TFCC may restore distal radioulnar joint stability and provide satisfactory results without significant complications [68].
- In high-demand athletes, arthroscopic repair of TFCC tears is becoming the treatment of choice to obtain optimum physiologic strength, complete range of motion, stability, and the shortest possible postoperative period [44].
- Open surgical TFCC repair is a safe and reliable therapeutic procedure in children and adolescent populations [56].
- TFCC capsular reattachment could be performed with an arthroscopically assisted technique, providing good long-term results [19].
Surgical Techniques and Variability
- Arthroscopic-assisted repair techniques have revolutionized surgical management, providing detailed visualization and facilitating the repair of TFCC injuries and associated pathologies with minimally invasive techniques [9].
- TFCC repair varies substantially from surgeon-to-surgeon, suggesting repairs are discretionary and preference sensitive [15].
- A systematic review demonstrates a current lack of high-quality evidence required to draw firm conclusions on the merits of arthroscopic versus open repair of 1B TFCC tears [17].
- A systematic review did not demonstrate strong evidence regarding the association between ulnar variance and outcomes after TFCC repair [31].
Anatomy & Pathophysiology
Anatomical Structures and Blood Supply
- The TFCC is a group of interrelated anatomic structures that are integral to stability of the distal radioulnar joint (DRUJ) [35].
- The TFCC acts in forearm rotation as the primary stabilizer of the DRUJ while also providing a smooth articular surface and partially absorbing the axial load from the radiocarpal joint [63].
- The central 80–85% of the articular disk is avascular, resulting in minimal healing potential for tears in this area [55].
- The outer 10% to 40% of the articular disk is well perfused, suggesting a healing potential for injured areas upon repair [49].
- The ulnar attachment of the TFCC is a three-dimensional complex consisting of proximal radioulnar ligaments, a distal hammock structure (fibrocartilage disk, meniscus homologue, and ulnocarpal ligaments), and a functional ulnar collateral ligament (UCL) [49].
- The distal hammock structure and the UCL constitute the distal component of the TFCC (dc-TFCC), while the radioulnar ligament represents the proximal component (pc-TFCC) [49].
- The palmar and dorsal radioulnar ligaments span from the dorsal and volar corners of the distal radius to a broad area of the fovea at the base of the ulnar styloid [49].
- The deep foveal components of the radioulnar ligaments are considered the true stabilizers of the DRUJ [49].
- The triangular fibrocartilage is less stiff in neutral forearm rotation, and its palmar and dorsal parts have material properties similar to those of the radiocarpal ligaments [88].
Classification and Pathology
- Palmer classification categorizes TFCC tears into traumatic (Class 1) or degenerative (Class 2) based on mechanism and location [20, 21, 49, 55].
- Class 1A injuries are central perforations or tears of the articular disk [20, 21, 55].
- Class 1B injuries are ulnar avulsions of the TFCC with or without an ulnar styloid fracture [20, 21, 55].
- Class 1C injuries are distal avulsions involving the origins of the ulnolunate and ulnotriquetral ligaments [20, 21].
- Class 1D injuries are radial avulsions involving the dorsal and/or volar radioulnar ligaments [20, 21].
- Class 2 injuries represent degeneration of the central portion of the TFCC and are associated with ulnocarpal impaction syndrome [55].
- Class 2A involves TFCC wear or thinning, progressing through Class 2E which includes ulnocarpal and DRUJ arthritis [20, 21].
- A foveal tear is a partial tear of the ulnar insertion where the foveal insertion is disrupted but some styloid insertion remains intact [132].
- The foveal insertion has a greater effect on DRUJ stability than the styloid insertion due to its closer relationship to the rotational axis of the forearm [132].
- Degenerative TFCC tears occur as a result of chronic excessive loading through the ulnocarpal joint along with natural tissue degeneration [126].
- Cadaveric examinations found TFCC perforations and chondromalacia of the ulnar head, lunate, and triquetrum in 30% to 70% of specimens [126].
Injury Mechanisms and Clinical Presentation
- Traumatic TFCC injuries may occur from falls on an outstretched hand or hyper-rotational injuries to the forearm [35].
- Repetitive forceful movement of the wrist from supination to pronation can cause overload stress affecting components of the TFCC [35].
- Injuries to the TFCC typically occur with extension and pronation of the axially loaded wrist [49].
- The most common mechanism of injury is a fall on an outstretched hand [49].
- Traumatic radial-sided tears of the TFCC typically occur during acute rotational injuries involving combined axial load with a distraction injury to the ulnar border of the forearm [126].
- Patients with peripheral TFCC tears complain of deep diffuse pain across the ulnar side of the wrist, weakness when gripping, and a clicking sensation with forearm rotation [49].
- Pain in peripheral TFCC tears is accentuated by passive pronation and supination of the wrist [49].
- A dorsally prominent ulnar head in relation to the radius can be seen in foveal detachments [49].
- Ballottement of the DRUJ reveals increased translation of the joint associated with pain in peripheral tears [49].
- A class 1A tear typically manifests as ulnar-sided wrist pain aggravated by power grip, especially with ulnar deviation or forearm rotation [43].
- Class 1A tears are confined to the disc, located 2 to 3 mm ulnar to its radial attachment, and oriented volar to dorsal [43].
- Class 1B injuries may present with point tenderness volar to the ulnar styloid, coinciding anatomically with the fovea (fovea sign) [60].
- A fracture through the base of the ulnar styloid that disrupts both deep and superficial limbs of the TFCC is more predictive of DRUJ instability than fractures through the shaft or tip [60].
- Deep TFCC fiber tears may contribute to decreased wrist rotational positioning sense and have biomechanical importance in DRUJ stability [50].
Biomechanical Effects of Deformity
- Radial shortening causes the greatest disturbance in DRUJ kinematics and the most distortion of the triangular fibrocartilage [74].
- Decreased radial inclination and dorsal angulation cause intermediate changes in DRUJ kinematics, while dorsal displacement produces minimal changes [74].
- Radial deformity does not produce DRUJ dislocation but provides biomechanical evidence of a relationship between radial malunion and persistent symptoms [74].
- Changes in ulnar variance due to ulnar lengthening or radial shortening dramatically alter force transmission through the distal ulna [90].
Classification
Palmer Classification System
- The Palmer classification divides TFCC injuries into traumatic (Class 1) and degenerative (Class 2) categories [20].
- Subtypes within the Palmer classification are based on the specific location of the tear within the TFCC [20].
- The class and location of a TFCC tear have important implications for treatment [20].
- Palmer created a classification system that divides TFCC injuries into Type I (traumatic) or Type II (degenerative) lesions [53].
- Traumatic injuries are categorized based on the location of the pathology [55].
- Degenerative tears represent the spectrum of lesions found with ulnocarpal impaction syndrome [55].
Class 1 (Traumatic) Subtypes
- Class 1A injuries are characterized by central perforation or tear of the TFCC [20].
- Class 1A injuries are characterized by central articular disc perforation [53].
- Class 1B injuries are characterized by ulnar avulsion with or without ulnar styloid fracture [20].
- Class 1B injuries are characterized by ulnar-sided avulsion with or without ulnar styloid fracture [53].
- Class 1C injuries are characterized by distal avulsion involving the origins of the ulnolunate and ulnotriquetral ligaments [20].
- Class 1C injuries are characterized by distal avulsion with disruption from distal ulnocarpal ligaments [53].
- Class 1D injuries are characterized by radial avulsion involving the dorsal and/or volar radioulnar ligaments [20].
- Class 1D injuries are characterized by radial-sided avulsion with or without sigmoid notch fracture [53].
- Class 1D injuries involve avulsion of the articular disk and the dorsal and palmar radioulnar ligaments [55].
- Class 1D injuries render the distal radioulnar joint (DRUJ) unstable [55].
- Type IA lesions are perforations of the thin, avascular articular disc and represent the most common type of traumatic tear [53].
- Traumatic tears of the articular disk commonly occur along the origin of the articular disk from the radius, which are class 1A injuries [55].
- Class 1B lesions describe traumatic avulsion of the TFCC insertion onto the ulna [55].
- Class 1B injuries are seen with or without fractures of the ulnar styloid [55].
- Avulsions of the TFCC ulnar attachment often create DRUJ instability [55].
- Class 1C lesions involve disruption of the TFCC distally through the ulnolunate and ulnotriquetral ligaments [55].
- The area of the TFCC involved in Class 1C lesions is well vascularized, giving these lesions greater potential to heal [55].
- Class 1D injuries are less common and involve radial avulsion of the entire TFCC from its attachment to the radius at the sigmoid notch [55].
Class 2 (Degenerative) Subtypes
- Class 2A is characterized by TFCC wear or thinning [20].
- Class 2B is characterized by TFCC wear plus lunate and/or ulnar chondromalacia [20].
- Class 2C is characterized by TFCC perforation plus lunate and/or ulnar chondromalacia [20].
- Class 2D is characterized by TFCC perforation, lunate and/or ulnar chondromalacia, and lunotriquetral ligament disruption [20].
- Class 2E is characterized by TFCC perforation, lunate and/or ulnar chondromalacia, lunotriquetral ligament disruption, and ulnocarpal and DRUJ arthritis [20].
- Type IIA is characterized by TFCC wear [53].
- Type IIB is characterized by TFCC wear with lunate and/or ulnar chondromalacia [53].
- Type IIC is characterized by TFCC perforation with lunate and/or ulnar chondromalacia [53].
- Type IID is characterized by TFCC perforation with lunate and/or ulnar chondromalacia and lunotriquetral ligament perforation [53].
- Type IIE is characterized by TFCC perforation with lunate and/or ulnar chondromalacia, lunotriquetral ligament perforation, and ulnocarpal arthritis [53].
Alternative Classifications
- Atzei proposed a treatment-oriented classification for Palmer 1B type peripheral tears [109].
- The Atzei classification distinguishes repairable lesions of the single distal component of the TFCC (Class 1) from those of the proximal component, which includes foveal insertions of DRUJ ligaments [121].
- Atzei Class 2 represents a complete tear pattern involving both the distal and proximal components of the TFCC [121].
- Atzei Class 3 represents an isolated tear of the proximal component of the TFCC [121].
- Atzei Class 4 represents nonrepairable lesions [121].
- Atzei Class 5 represents tears associated with DRUJ arthritis [121].
- The Atzei classification highlights clinical and arthroscopic criteria to categorize five classes of TFCC peripheral tears on a treatment-oriented system [47].
- In the pediatric population, traumatic (Class 1) injuries represent the vast majority of TFCC tears, while degenerative (Class 2) tears are far less common [24].
- There is an apparent increased prevalence of Palmer 1B tears in pediatric patients compared with adults [24].
- Palmer 1B tears represent the most common variety of TFCC injuries in children and adolescents [24].
- Tears of the radial attachment (Palmer 1D) represent the second most common type of TFCC injuries in children and adolescents [24].
- The Melone classification system does not predict the presence of TFCC lesions [102].
- Frykman Type VI and VIII fractures show a significantly higher incidence of TFCC tears [102].
Diagnostic Correlates for Classification
- Arthroscopy is the gold standard for detection of TFCC tears [20].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting the central portion with a small probe [20].
- The arthroscopic hook test can be used to demonstrate peripheral detachment of the TFCC [20].
- The arthroscopic suction test can show laxity of the TFCC when peripherally scarred in or foveal detachment when the DRUJ is clinically unstable [20].
- Classification of central triangular fibrocartilage complex lesions as traumatic or degenerative depends on the information provided upon viewing the lesion at arthroscopy [28].
- In more detailed classification of TFCC injuries, such as pc-TFCC tears classified by Atzei's classification, the diagnostic accuracy of MRI remains lower compared to wrist arthroscopy [36].
- Diagnostic accuracy for TFCC injuries was highest for central TFCC injuries [39].
- The presence of ulnar styloid fracture associated with distal radius fracture predicted the presence of frequently occurring traumatic triangular fibrocartilage complex injury and TFCC 1B injury [14].
Clinical Presentation
General Presentation and Diagnosis
- TFCC tears are a common cause of ulnar-sided wrist pain in athletes [10].
- Ulnar-sided wrist pain in athletes can be caused by injury to the TFCC [35].
- Wrist arthroscopy is considered the benchmark for the diagnosis and management of TFCC injuries [110].
- Wrist arthroscopy allows the direct evaluation of the TFCC and surrounding ligaments [110].
- Arthroscopy is effective in obtaining both correct diagnosis and treatment of peripheral TFCC tear [33].
- The more experienced observer had more sensitive, specific, and accurate interpretations than the less experienced observer in predicting the presence and location of a TFCC tear [13].
- There is a high rate of abnormal TFCC identified on MRI in patients without corresponding ulnar-sided wrist symptoms [34].
- The presence of an abnormal TFCC on MRI may be of questionable clinical meaning, because there is a high incidence of TFCC abnormalities in asymptomatic subjects, particularly those over the age of 50 [62].
- MR arthrography is more sensitive and specific method in terms of the diagnosis of TFCC tears compared to conventional wrist MRI [54].
- Diagnostic accuracy was highest for central TFCC injuries [39].
- The technique is best used in young patients with indeterminate physical examinations and normal radiography in whom intrinsic ligament or TFCC tears are suspected to assist decision making regarding the performance of arthroscopy [64].
Pediatric and Adolescent Presentation
- In the pediatric population, traumatic (class 1) injuries represent the vast majority of TFCC tears [24].
- Degenerative (class 2) tears of the TFCC are far less common in the pediatric population [24].
- Palmer 1B tears from the ulnar attachment with or without associated ulnar styloid fractures represent the most common variety of TFCC injuries in children and adolescents [24].
- Tears of the radial attachment (Palmer 1D tears) represent the second most common type of TFCC injuries in children and adolescents [24].
- If radial-sided tears (Palmer 1D) are mistaken for a central traumatic tear (Palmer 1A), simple debridement alone may result in persistent pain, instability, and functional limitations [24].
Association with Distal Radius Fractures
- 1B TFCC injury is most common in patients with distal radius fracture and concomitant TFCC injury [5].
- Disability outcomes were worse in patients with distal radial fracture where TFCC was injured [41].
Natural History and Chronic Findings
- About 40% of patients sustaining TFCC tear without DRUJ instability still had pain and disability at 1 year [8].
- Nonsurgical treatment is moderately successful for treating patients with TFCC tears without DRUJ instability [22].
- A higher frequency of accompanying ECU tendon and/or DRUJ disorders was found in patients with chronic TFCC tears as compared to the control group [40].
- Deep TFCC fiber tear may contribute to decreased wrist rotational positioning sense and may have biomechanical importance in distal radioulnar joint stability [50].
Investigations
Clinical Examination and Provocative Tests
- Careful history and physical examination are required to determine whether a TFCC tear is symptomatic and to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary [6].
- A positive ulnar fovea sign was reported to be 90% sensitive and 88% specific in detecting a split tear of the ulnotriquetral ligament [70].
- Load-bearing RaUl measurement is a simple method to diagnose an unstable distal radioulnar joint in patients with TFCC injury [59].
Magnetic Resonance Imaging (MRI)
- MRI interpretation of TFCC lesions is more sensitive, specific, and accurate when performed by a more experienced observer compared to a less experienced observer [13].
- The sensitivity, specificity, and accuracy of 3.0T wrist MRI for the TFCC is consistently higher compared with those of 1.5T wrist MRI [119].
- High-resolution magnetic resonance imaging permits accurate depiction and localization of tears of the triangular fibrocartilage complex [133].
- High-resolution MRI using a microscopy surface coil allowed assessment of each TFCC component and showed a higher accuracy for diagnosing injuries to the radial attachment and the disc of the TFC compared with previous studies [113].
- MRI is controversial, but newer innovations suggest value in detection and localization of TFCC pathology [20].
MR Arthrography
- MR arthrography is a more sensitive and specific method in terms of the diagnosis of TFCC tears compared to conventional wrist MRI [54].
Computed Tomography (CT) and Arthrography
- CT scan is effective for evaluating DRUJ instability [135].
- Since ulnar-sided contrast leakage is more common in patients with peripheral TFCC injuries, distinction between an atypical configuration of the prestyloid recess and actual leakage is important in CT arthrography of the wrist [42].
- Radial multiplanar reconstructions are important for the assessment of triangular fibrocartilage complex injury in CT arthrography of the wrist [61].
- Single-injection wrist arthrography is superior to routine MRI for the detection of full-thickness triangular fibrocartilage tears [136].
Arthroscopy
Association with Distal Radius Fractures
Treatment
Non-Operative Management
- All Class 1 (acute traumatic) TFCC injuries are initially managed with immobilization and NSAIDs [20].
- Initial treatment for Class 1B injuries involves protective above-elbow immobilization for 4 to 6 weeks toward the forearm in neutral rotation [60].
- Nonoperative management of traumatic TFCC injuries with above-elbow immobilization is a viable treatment method, particularly in patients without DRUJ subluxation [123].
- Moritomo and colleagues reported that 46% of patients with avulsion of the TFCC from the fovea were pain-free after conservative treatment [49].
- Non-operative treatment is the first line of treatment for most DRUJ problems, with exceptions including some unstable distal ulnar fractures and early marked painful block to forearm rotation [125].
- In the year of natural recovery following a distal radius fracture, management options for ongoing ulnar-sided wrist pain include activity modification, splints or straps, and oral analgesics, typically NSAIDs [125].
- Steroid injections are given to treat ongoing wrist pain after distal radius fractures, with 90% of patients reporting some improvement in symptoms when reviewed at 6–8 weeks after injection [125].
- Patients with persistent pain after distal radius fractures should be supported and encouraged to wait for spontaneous improvement in symptoms over at least 1 year from injury, assuming there is no gross bone malalignment [125].
- There is no good evidence that early treatment improves the outcome of DRUJ instability, so it is worth waiting for a prolonged period, typically at least 12 months, before addressing it [125].
- The mean DASH scores showed no difference across all groups, calling into question the clinical need to pursue operative treatment via K-wire stabilization or TFCC repair over conservative treatment via cast immobilization for acute DRUJ instability following distal radius fracture [129].
Surgical Indications and Decision Making
- Careful history and physical examination are required to determine whether a TFCC tear is symptomatic, and it is important to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary [6].
- Acute TFCC injuries require differentiation between those causing distal radioulnar joint instability and those that do not, with management ranging from nonsurgical immobilization to arthroscopic or open surgical repair depending on the specific injury pattern and stability [7].
- Surgical treatment is indicated for Class 1 TFCC injuries with failure of nonoperative treatment [20].
- Indications for surgical intervention include specific ulnar-sided wrist pain not relieved by conservative management for 3 months, especially in the presence of symptomatic instability of the DRUJ [49].
- Surgery is indicated for Class 1B injuries with persistent symptoms or evidence of DRUJ instability [60].
- Arthroscopy remains the gold standard in diagnosing and assessing the type and extent of the TFCC tear [49].
- A recent study in magnetic resonance arthrography performed with wrist traction applied demonstrated high accuracy of TFCC tear detection of 98% [49].
- Some studies have demonstrated that MRI missed over half of TFCC tears, as later confirmed on wrist arthroscopy [122].
- An MRI finding showing greater than 10% subluxation of the DRUJ on axial MRI has been shown to have increased sensitivity and specificity for TFCC tear and DRUJ instability [122].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting central portion with a small probe [20].
Arthroscopic Debridement (Class 1A and Degenerative)
- Class 1A (central) TFCC tears are inherently stable and treated with débridement if persistently symptomatic because this area of the TFCC is devoid of vascularity and unable to heal [20].
- A 2-mm peripheral rim should be maintained during debridement of Class 1A tears [20].
- Indications for arthroscopic TFCC debridement include acute traumatic Palmer type 1A TFCC, degenerative central tear of TFCC with ulnar neutral or negative variance, and failure to respond to conservative treatment with splint and medication for more than 3 months [26].
- Resection of unstable flaps is sufficient when the remaining margins are smooth and stable, and the peripheral 2 to 3 mm must be preserved to protect the radioulnar ligaments [26].
- A thorough synovectomy of the ulnocarpal joint and DRUJ is essential for early pain control as the pain mainly originates from the inflamed synovium over the capsule which is richly innervated [26].
- Excessive use of RF energy can lead to thermal chondral damage [26].
- Overaggressive debridement can cause DRUJ instability [26].
- Failure to diagnose ulnar impaction syndrome may lead to continued pain [26].
- No restriction of wrist and forearm motion is required postoperatively after arthroscopic TFCC debridement [26].
- Although clinical outcome scores showed significant improvement after arthroscopic debridement for central TFCC tears, wearing type tears and greater ulnar plus variance were associated with dissatisfaction and poorer postoperative outcomes after the procedure [117].
- Removal of a perforated TFC is contraindicated in the presence of radiocarpal or distal radioulnar arthritis [58].
- Patients who underwent debridement for any Type 1 Palmer class returned to work at a rate of 92%, but only 44% were free of pain [63].
Arthroscopic and Open Repair (Class 1B, 1C, 1D)
- Class 1B (peripheral) TFCC tears are amenable to arthroscopic or open repair because the rim is well vascularized [20].
- Concurrent fractures of ulnar styloid with persistent instability are either excised or fixed during repair of Class 1B tears [20].
- Class 1C (rare) TFCC tears are amenable to arthroscopic or open repair [20].
- Class 1D TFCC tears are frequently associated with distal radius fractures and often respond to reduction of the radius [20].
- Repair of a traumatic TFCC tear within 3 months of injury allows a patient to regain 80% of wrist ROM and grip strength [20].
- Arthroscopic-assisted repair techniques provide detailed visualization and facilitate the repair of TFCC injuries and associated pathologies with minimally invasive techniques [9].
- Arthroscopic transosseous foveal repair of the TFCC resulted in improvements in grip strength and functional outcomes with low complication and reoperation rates [45].
- The refixation of the TFCC after shortening of the ulnar head for traumatic avulsion class 1B of the TFCC is effective in restoring its function [29].
- Arthroscopic exploration and surgical treatment of peripheral ulnar TFCC lesions allow for satisfactory results regarding mobility and patient satisfaction [116].
- For 1B lesions that underwent repair, 68.3% were able to return to work and 41% had persistent pain [63].
- Coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in patients with peripheral ulnar-side TFCC tears [30].
- The technique of arthroscopic transosseous repair using a modified outside-in technique allows for low-profile fixation for distal radioulnar joint instability and provides excellent biomechanical fixation [48].
- The combined HS and suture repair effectively restores stability to both the DRUJ and UCJ in patients with TFCC-related ulnocarpal instability, considerably reducing pain and preserving range of motion [111].
- This technique provides a minimally invasive and anatomically guided solution for restoring DRUJ stability in chronic TFCC injuries [71].
Pediatric and Adolescent Considerations
- If Palmer 1D tears are mistaken for a central traumatic tear (Palmer 1A), simple debridement alone may result in persistent pain, instability, and functional limitations [24].
- In this series, there was marked improvement in pain, function, and range of motion in patients with TFCC tears and coexisting pathology [1].
- Unlike in adults, in whom Palmer 1A (central) tears are most common, pediatric patients commonly have Palmer 1B (ulnar peripheral) tears, in some studies up to 79% of the patients [122].
- Given the improved vascularity at the periphery of the TFCC, many of these tears are amenable to repair, rather than solely débridement [122].
- 1B TFCC injury is most common in patients with DRF and concomitant TFCC injury [5].
- The most frequent ligament tear in distal fractures of the radius in young adults was the triangular fibrocartilage complex in 39 cases (78%), with a statistical correlation to ulnar styloid fractures [72].
Reconstruction and Salvage Procedures
- TFCC reconstruction with tendon graft is indicated in irreparable TFCC injuries with symptomatic DRUJ instability, neglected chronic injuries, or after suboptimal healing following nonoperative or surgical repair [38].
- Skeletal malalignment that may be responsible for the DRUJ instability should be addressed concomitantly, including ulnar incongruity, malunion of the sigmoid notch, and dorsal tilt or coronal shift of the radius [38].
- Osteoarthritis of the DRUJ and an axial instability of the forearm due to interosseous membrane injury are contraindications to TFCC reconstruction [38].
- The results of a study suggest that arthroscopic TFCC reconstruction using the free PL tendon is an effective method for treating chronic and irreparable TFCC tears with DRUJ instability [66].
- Hemiresection or interposition arthroplasty maintains the ulnar insertion of the TFCC and prevents radioulnar impingement by soft tissue (ECU tendon or capsular flap) interposition [20].
- The Sauvé-Kapandji procedure involves DRUJ arthrodesis with creation of a proximal pseudarthrosis at the ulnar neck [20].
- Ulnar head or total joint implant arthroplasty maintains the relationship between the radius and the ulnar [20].
- Results of ulnar head or total joint implant arthroplasty show good pain relief at the risk of ulnar head instability, aseptic loosening, and no appreciable change in pronosupination in comparison with preoperative values [20].
- One-bone forearm through elimination of forearm rotation represents the ultimate salvage operation for persistent pain/complications by fusing the proximal ulnar to the distal radius shaft [20].
- A complication of TFCC treatment is painful proximal ulna stump instability and convergence of the radius upon the ulna [20].
Postoperative Rehabilitation
- Traumatic tears of the peripheral portions of the TFCC may be surgically repaired and are immobilized immediately postoperatively in a long arm cast to prevent forearm rotation and wrist motion that would stress the repair [127].
- After the first 10 days to 2 weeks following surgery, the cast may be changed to a thermoplastic splint that continues the immobilization of the forearm and wrist [127].
- Splinting generally continues for 4 to 6 weeks following surgery [127].
- Elbow range of motion may be permitted at 4 weeks, generally under the supervision of the therapist [127].
- At 6 weeks, immobilization is discontinued and the patient may use a wrist and forearm splint for intermittent support and protection [127].
- The focus of therapy at 6 weeks is on the gradual mobilization of the forearm and wrist [127].
- A reverse sugar tong cast with forearm in neutral rotation is preferred to long-arm cast to allow early elbow motion after TFCC reconstruction with tendon graft [37].
- Change to reverse sugar tong splint after 3 weeks and allow early midrange forearm rotation after TFCC reconstruction with tendon graft [37].
- Allow full range active forearm rotation after full 6 weeks, start passive motion after full 8 weeks after TFCC reconstruction with tendon graft [37].
- Specific neuromuscular potential training exercises and proprioceptive hand and wrist exercises are included in the rehabilitation program to recuperate functional wrist range of motion in association with fine and gross motor prehensile strength without provoking wrist instability due to overstretching of the newly reconstructed ligament [118].
Complications
Post-traumatic and Associated Pathology
- TFCC tears are associated with positive ulnar variance in up to 81% of cases [69].
- TFCC tears are associated with lunotriquetral ligament perforation in 70% to 76% of cases [69].
- TFCC tears are associated with chondromalacia of the distal ulna or of the ulnar carpal bones in up to 100% of cases [69].
- In patients with distal radius fractures, the most frequent ligament tear was the triangular fibrocartilage complex, occurring in 39 of 50 cases (78%) [72].
- In patients with distal radius fractures, there was a statistical correlation between TFCC tears and ulnar styloid fractures [72].
- In patients with distal radius fractures, chondral lesions were found in 16 of 50 patients (32%) [72].
- In patients with distal radius fractures, the scapholunate ligament was partially or totally torn in 27 of 50 cases (54%) [72].
- In patients with chronic TFCC tears, there is a higher frequency of accompanying extensor carpi ulnaris tendon and/or distal radioulnar joint disorders compared to a control group [40].
- Disability outcomes were worse in patients with distal radial fracture where the TFCC was injured [41].
- Coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in patients undergoing arthroscopic repair of peripheral ulnar-side TFCC tears [30].
Natural History and Untreated Outcomes
- Nonsurgical treatment is moderately successful for treating patients with TFCC tears without distal radioulnar joint instability [22].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, instability of the distal radioulnar joint was found in 19 patients at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, distal radioulnar joint instability was painful in 13 patients at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, 10 of 11 patients with complete peripheral TFCC tears had distal radioulnar joint instability at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, 7 of 32 patients with partial or no peripheral tears had distal radioulnar joint instability at 1-year follow-up [130].
- In a prospective study of 43 patients with arthroscopically proven TFCC tears after distal radius fractures who were not initially treated, patients with distal radioulnar joint instability had a worse Gartland and Werley wrist score [130].
- Traumatic linear TFCC tears do not necessarily lead to significant degenerative arthritis of the ulnar head or lunate [73].
Surgical Complications and Contraindications
- Removal of a perforated triangular fibrocartilage is contraindicated in the presence of radiocarpal or distal radioulnar arthritis [58].
- Arthroscopic transosseous foveal repair of the TFCC resulted in low complication and reoperation rates [45].
Recovery
Natural History and Non-Operative Outcomes
- About 40% of patients sustaining a TFCC tear without distal radioulnar joint (DRUJ) instability still had pain and disability at 1 year [8].
Surgical Outcomes and Functional Recovery
- Arthroscopic TFCC reconstruction using the free PL tendon is an effective method for treating chronic and irreparable TFCC tears with DRUJ instability [66].
Return to Work and Activity
- In the first year after open TFCC reinsertion, 91% of the patients returned to work, including 50% within 12 weeks [137].
- Eighty-four per cent of patients had a good or excellent range of motion of the injured wrist and this resulted in an early return to former activity [140].
Complications and Associated Pathology
- Coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in patients with ulnar-plus variance [30].
- Ulnar variance may be changed after a TFCC tear; it decreased after TFCC foveal repair but increased again over time, which could be one of the causes of ulnar impaction syndrome and ulnar-sided wrist pain [139].
Key Evidence
- [L4] In this series, there was marked improvement in pain, function, and range of motion in patients with TFCC tears and coexisting pathology. [1] (10.1016/s0363-5023(98)80048-8)
- [L4] Surgical treatment of TFCC tears and concomitant pathology in the pediatric and adolescent population results in decreased pain, improved motion and stability, and excellent functional outcomes in the majority of patients. [3] (10.1016/j.jhsa.2019.06.019)
- [L4] Arthroscopic treatment of TFCC lesions leads to satisfactory functional outcomes. [4] (10.1055/s-0039-3400454)
- [L3] 1B TFCC injury is most common in patients with DRF and concomitant TFCC injury. [5] (10.1186/s13018-023-04438-5)
- [L4] Careful history and physical examination are required to determine whether a TFCC tear is symptomatic, and it is important to quantify the severity of symptoms related to TFCC pathology to determine whether surgical treatment is necessary. [6] (10.5435/jaaos-d-20-00998)
- [L5] Acute TFCC injuries require differentiation between those causing distal radioulnar joint instability and those that do not, with management ranging from nonsurgical immobilization to arthroscopic or open surgical repair depending on the specific injury pattern and stability. [7] (10.5435/00124635-200806000-00004)
- [L4] About 40% of patients sustaining TFCC tear without DRUJ instability still had pain and disability at 1 year. [8] (10.1016/j.jhsa.2018.06.064)
- [L5] Arthroscopic-assisted repair techniques have revolutionized surgical management, providing detailed visualization and facilitating the repair of TFCC injuries and associated pathologies with minimally invasive techniques. [9] (10.1016/j.jhsg.2024.03.011)
- [L5] Tears of the triangular fibrocartilage complex (TFCC) are a common cause of ulnar-sided wrist pain in athletes. [10] (10.1016/s0894-1130(12)80104-9)
- [L3] The more experienced observer had more sensitive, specific, and accurate interpretations than the less experienced observer in predicting the presence and location of a TFCC tear. [13] (10.1053/jhsu.2001.24966)
- [L4] The presence of ulnar styloid fracture associated with distal radius fracture predicted the presence of frequently occurring traumatic triangular fibrocartilage complex injury and TFCC 1B injury. [14] (10.1016/j.arthro.2020.05.025)
- [L4] TFCC repair varies substantially from surgeon-to-surgeon, suggesting repairs are discretionary and preference sensitive. [15] (10.1055/s-0038-1625953)
- [L4] TFCC injury should be considered with all distal radial fractures. [16] (10.1177/1558944716660555bh)
- [L4] This SR demonstrates a current lack of high-quality evidence required to draw firm conclusions on the merits of arthroscopic versus open repair of 1B TFCC tears. [17] (10.1177/1558944718815244)
- [L5] TFCC capsular reattachment could be performed with an arthroscopically assisted technique, providing good long-term results. [19] (10.1016/j.hcl.2017.06.005)
- [L3] Nonsurgical treatment is moderately successful for treating patients with TFCC tears without DRUJ instability. [22] (10.1097/corr.0000000000000533)
- [L4] Current evidence demonstrates that TFCC repair achieves good clinical outcomes, with low complication rates. [23] (10.1055/s-0040-1718913)
- [L5] [24] (10.1016/j.hcl.2005.09.002)
- [L3] There was no statistical difference in clinical outcomes after open versus arthroscopic TFCC repair. [27] (10.1016/j.jhsa.2008.01.020)
- [L2] Classification of central triangular fibrocartilage complex lesions as traumatic or degenerative depends on the information provided upon viewing the lesion at arthroscopy. [28] (10.1177/1753193416684658)
- [L4] The refixation of the TFCC after shortening of the ulnar head for traumatic avulsion class 1B of the TFCC is effective in restoring its function. [29] (10.1016/s0266-7681(05)80046-4)
- [L4] However, coexisting type 2 TFCC tears significantly increased the risk of index surgery failure in these patients. [30] (10.1016/j.arthro.2020.05.012)
- [L4] This systematic review did not demonstrate strong evidence regarding the association between ulnar variance and outcomes after TFCC repair. [31] (10.1142/s2424835518300025)
- [L3] Arthroscopic debridement alone appears to be an effective and safe initial treatment for patients with traumatic central TFCC tears. [32] (10.1302/0301-620x.106b4.bjj-2023-0642.r3)
- [L4] Arthroscopy is effective in obtaining both correct diagnosis and treatment of peripheral TFCC tear. [33] (10.2174/1874325001711010525)
- [L4] There is a high rate of abnormal TFCC identified on MRI in patients without corresponding ulnar-sided wrist symptoms. [34] (10.1177/15589447241277846)
- [L5] [35] (10.1016/j.csm.2019.12.008)
- [L4] In more detailed classification of TFCC injuries, such as pc-TFCC tears classified by Atzei's classification, the diagnostic accuracy of MRI remains lower compared to wrist arthroscopy. [36] (10.1186/s12891-023-07140-z)
- [L1] Diagnostic accuracy was highest for central TFCC injuries. [39] (10.1055/s-0038-1629911)
- [L3] We found a higher frequency of accompanying ECU tendon and/or DRUJ disorders in patients with chronic TFCC tears as compared to the control group. [40] (10.1016/j.jhsa.2016.07.040)
- [L2] Disability outcomes were worse in patients with distal radial fracture where TFCC was injured. [41] (10.1016/j.jht.2017.09.002)
- [L4] Since ulnar-sided contrast leakage is more common in patients with peripheral TFCC injuries, distinction between an atypical configuration of the prestyloid recess and actual leakage is important in CT arthrography of the wrist. [42] (10.1186/s12891-022-05241-9)
- [L4] In high-demand athletes, arthroscopic repair of TFCC tears is becoming the treatment of choice to obtain optimum physiologic strength, complete range of motion, stability, and the shortest possible postoperative period. [44] (10.1016/j.hcl.2009.05.011)
- [L1] Arthroscopic transosseous foveal repair of the TFCC resulted in improvements in grip strength and functional outcomes with low complication and reoperation rates. [45] (10.1016/j.arthro.2020.12.209)
- [L2] The classification highlights clinical and arthroscopic criteria to categorize five classes of TFCC peripheral tears on a treatment-oriented system. [47] (10.1177/1753193416687479)
- [L5] The technique allows for low-profile fixation for distal radioulnar joint instability and provides excellent biomechanical fixation. [48] (10.1016/j.eats.2024.103349)
- [L3] Deep TFCC fiber tear may contribute to decreased wrist rotational positioning sense and may have biomechanical importance in distal radioulnar joint stability. [50] (10.1016/j.jhsa.2018.01.022)
- [L5] [53] (10.1016/j.hcl.2012.05.014)
- [L3] MR arthrography is more sensitive and specific method in terms of the diagnosis of TFCC tears compared to conventional wrist MRI. [54] (10.1016/j.injury.2019.07.032)
- [L5] [55] (10.1016/s0894-1130(96)80071-8)
- [L4] This study emphasizes that open surgical TFCC repair is a safe and reliable therapeutic procedure in children and adolescent populations. [56] (10.1142/s2424835518500509)
- [L4] Removal of a perforated TFC is contraindicated in the presence of radiocarpal or distal radioulnar arthritis. [58] (10.1016/s0363-5023(84)80104-5)
- [L2] Load-bearing RaUl measurement is a simple method to diagnose an unstable distal radioulnar joint in patients with TFCC injury. [59] (10.1016/j.jhsa.2022.01.008)
- [L3] [61] (10.1186/s12891-020-03321-2)
- [L3] The presence of an abnormal TFCC on MRI may be of questionable clinical meaning, because there is a high incidence of TFCC abnormalities in asymptomatic subjects, particularly those over the age of 50. [62] (10.1016/j.jhsa.2011.10.006)
- [Paper] [63] (10.1055/s-0040-1713580)
- [L5] The technique is best used in young patients with indeterminate physical examinations and normal radiography in whom intrinsic ligament or TFCC tears are suspected to assist decision making regarding the performance of arthroscopy. [64] (10.1016/j.jhsa.2006.03.015)
- [L4] The results of this study suggest that arthroscopic TFCC reconstruction using the free PL tendon is an effective method for treating chronic and irreparable TFCC tears with DRUJ instability. [66] (10.1186/s13018-021-02827-2)
- [L4] With appropriate indications and patient selection, arthroscopic foveal repair of the TFCC may restore DRUJ stability and provide satisfactory results without significant complications. [68] (10.1055/s-0035-1544226)
- [L4] [69] (10.1016/0363-5023(92)90325-j)
- [L5] This technique provides a minimally invasive and anatomically guided solution for restoring DRUJ stability in chronic TFCC injuries. [71] (10.1002/atn2.70005)
- [L4] [72] (10.1016/s0266-7681(97)80364-6)
- [L5] Traumatic linear TFCC tears do not necessarily lead to significant degenerative arthritis of the ulnar head or lunate. [73] (10.1016/0266-7681(94)90078-7)
- [L5] [74] (10.1016/0363-5023(93)90098-n)
- [Paper] The study showed that the triangular fibrocartilage is less stiff in neutral forearm rotation and that the palmar and dorsal parts have material properties similar to those of the radiocarpal ligaments. [88] (10.1016/s0363-5023(10)80075-9)
- [L5] Changes in ulnar variance of a forearm due to ulnar lengthening or radial shortening do, however, dramatically alter the force transmission. [90] (10.1016/0363-5023(92)90342-m)
- [L3] The Melone classification system does not predict the presence of TFCC lesions, while Frykman Type VI and VIII fractures show a significantly higher incidence of TFCC tears. [102] (10.1177/1753193408090106)
- [L5] [109] (10.1177/1753193409100120)
- [L5] [110] (10.5435/jaaos-d-16-00407)
- [L4] The combined HS and suture repair effectively restores stability to both the DRUJ and UCJ in patients with TFCC-related ulnocarpal instability, considerably reducing pain and preserving range of motion. [111] (10.1016/j.jhsg.2025.100806)
- [L3] High-resolution MRI using a microscopy surface coil allowed assessment of each TFCC component and showed a higher accuracy for diagnosing injuries to the radial attachment and the disc of the TFC compared with previous studies. [113] (10.1016/j.jhsa.2006.05.001)
- [L4] Arthroscopic exploration and surgical treatment of peripheral ulnar TFCC lesions allow for satisfactory results regarding mobility and patient satisfaction. [116] (10.1016/j.hansur.2016.10.110)
- [L4] Although clinical outcome scores showed significant improvement after arthroscopic debridement for central TFCC tears, wearing type tears and greater ulnar plus variance were associated with dissatisfaction and poorer postoperative outcomes after the procedure. [117] (10.1016/j.arthro.2018.05.044)
- [L4] [118] (10.1016/j.jhse.2007.02.170)
- [L3] The sensitivity, specificity, and accuracy of 3.0T wrist MRI for the TFCC is consistently higher compared with those of 1.5T wrist MRI, suggesting improved capability for detection of TFCC injuries. [119] (10.1016/j.jhsa.2008.02.028)
- [L2] [121] (10.1016/j.arthro.2021.03.005)
- [L5] [122] (10.5435/jaaos-d-21-01029)
- [L3] Nonoperative management of traumatic TFCC injuries with above-elbow immobilization is a viable treatment method, particularly in patients without DRUJ subluxation. [123] (10.1302/0301-620x.103b8.bjj-2020-2310.r2)
- [L5] [125] (10.1177/17531934221140238)
- [L4] [126] (10.1177/15589447221084125)
- [L5] [127] (10.1097/00130911-199709000-00009)
- [L2] However, the mean DASH scores showed no difference across all groups, calling into question the clinical need to pursue operative treatment via K-wire stabilization or TFCC repair over conservative treatment via cast immobilization. [129] (10.1016/j.jhsg.2021.02.005)
- [Paper] [130] (10.1016/j.jhsa.2006.08.015)
- [L5] [132] (10.1097/bth.0b013e3181bd8319)
- [L2] High-resolution magnetic resonance imaging permits accurate depiction and localization of tears of the triangular fibrocartilage complex. [133] (10.2106/00004623-199711000-00009)
- [L2] This finding confirms the efficacy of CT scan for evaluating DRUJ instability. [135] (10.1016/j.ijsu.2011.08.005)
- [L3] Although future advances in MRI technology will probably improve its usefulness, single-injection wrist arthrography currently is superior to routine MRI for the detection of fullthickness triangular fibrocartilage tears. [136] (10.1016/s0266-7681(98)80068-5)
- [L3] In the first year after open TFCC reinsertion, 91% of the patients returned to work, including 50% within 12 weeks. [137] (10.1016/j.hansur.2021.03.012)
- [L4] Ulnar variance may be changed after a TFCC tear; it decreased after TFCC foveal repair but increased again over time, which could be one of the causes of ulnar impaction syndrome and ulnar-sided wrist pain. [139] (10.1055/s-0038-1668153)
- [L4] Eighty-four per cent of patients had a good or excellent range of motion of the injured wrist and this resulted in an early return to former activity. [140] (10.1016/j.jhsb.2006.03.101)
References
[1] Triangular fibrocartilage injuries in pediatric and adolescent patients. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80048-8
[3] Early Results of Surgical Treatment of Triangular Fibrocartilage Complex Tears in Children and Adolescents. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.06.019
[4] Patient-Reported Outcomes following Arthroscopic Triangular Fibrocartilage Complex Repair. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-3400454
[5] Association between imaging parameter changes and triangular fibrocartilage complex injury after distal radius fractures. Journal of Orthopaedic Surgery and Research. 2023. DOI: 10.1186/s13018-023-04438-5
[6] Open and Arthroscopic Triangular Fibrocartilage Complex (TFCC) Repair. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-20-00998
[7] Management of Acute Triangular Fibrocartilage Complex Injury of the Wrist. Journal of the American Academy of Orthopaedic Surgeons. 2008. DOI: 10.5435/00124635-200806000-00004
[8] The Natural Course of Triangular Fibrocartilage Complex Tear without Distal Radioulnar Joint Instability. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.064
[9] Arthroscopic-Assisted Repair of the Triangular Fibrocartilage Complex. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.03.011
[10] Arthroscopic management of the athlete. Journal of Hand Therapy. 1991. DOI: 10.1016/s0894-1130(12)80104-9
[13] The effect of observer experience on magnetic resonance imaging interpretation and localization of triangular fibrocartilage complex lesions. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.24966
[14] The Presence and the Location of an Ulnar Styloid Fracture Associated With Distal Radius Fracture Predict the Presence of Triangular Fibrocartilage Complex 1B Injury. Arthroscopy: The Journal of Arthroscopic & Related Surgery. 2020. DOI: 10.1016/j.arthro.2020.05.025
[15] Variation in Repair of the Triangular Fibrocartilage Complex. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1625953
[16] The Correlation of Fracture Patterns of Distal Radius Fractures and Triangular Fibrocartilage Complex Injures. HAND. 2016. DOI: 10.1177/1558944716660555bh
[17] Open Versus Arthroscopic Repair of 1B Ulnar-Sided Triangular Fibrocartilage Complex Tears: A Systematic Review. HAND. 2019. DOI: 10.1177/1558944718815244
[19] Arthroscopic Management of Triangular Fibrocartilage Complex Peripheral Injury. Hand Clinics. 2017. DOI: 10.1016/j.hcl.2017.06.005
[20] Miller S Review Of Orthopaedics. DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[21] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[22] What is the Natural History of the Triangular Fibrocartilage Complex Tear Without Distal Radioulnar Joint Instability?. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000533
[23] Surgical Repair of Triangular Fibrocartilage Complex Tears: A Systematic Review. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1718913
[24] Pediatric Distal Radius Fractures and Triangular Fibrocartilage Complex Injuries. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2005.09.002
[26] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic TFCC Debridement.
[27] Clinical Comparison of Arthroscopic Versus Open Repair of Triangular Fibrocartilage Complex Tears. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.01.020
[28] Diagnosing central lesions of the triangular fibrocartilage as traumatic or degenerative: a review of clinical accuracy. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416684658
[29] A New Technique of Reattachment after Traumatic Avulsion of the TFCC at Its Ulnar Insertion. Journal of Hand Surgery. 1995. DOI: 10.1016/s0266-7681(05)80046-4
[30] What Is the Effect of the Ulnar‐Plus Variance on the Outcomes of Arthroscopic Repair of the Peripheral Ulnar‐Side Triangular Fibrocartilage Complex Tear?. Arthroscopy. 2020. DOI: 10.1016/j.arthro.2020.05.012
[31] Triangular Fibrocartilage Complex Repair and Ulna Variance: A Systematic Review. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518300025
[32] Prognostic factors for clinical outcomes after arthroscopic treatment of traumatic central tears of the triangular fibrocartilage complex. The Bone & Joint Journal. 2024. DOI: 10.1302/0301-620x.106b4.bjj-2023-0642.r3
[33] Results of Arthroscopic Repair of Peripheral Triangular Fibrocartilage Complex Tear With Exploration of Dorsal Sensory Branch of Ulnar Nerve. The Open Orthopaedics Journal. 2017. DOI: 10.2174/1874325001711010525
[34] Incidental Triangular Fibrocartilage Complex Changes on Wrist MRI. HAND. 2024. DOI: 10.1177/15589447241277846
[35] Ulnar-Sided Wrist Pain in the Athlete. Clinics in Sports Medicine. 2020. DOI: 10.1016/j.csm.2019.12.008
[36] Diagnostic value of MRI in traumatic triangular fibrocartilage complex injuries: a retrospective study. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-023-07140-z
[37] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic TFCC Reconstruction With Tendon Graft.
[38] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > TFCC Reconstruction with Tendon Graft.
[39] TFCC Injuries: Meta-Analysis and Comparison of Diagnostic Imaging Modalities. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1629911
[40] The Factors Correlated with the Extensor Carpi Ulnaris Tendon and Distal Radioulnar Joint Disorder in Patients with Chronic Triangular Fibrocartilage Tears. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2016.07.040
[41] Outcomes of surgically treated distal radial fractures with associated triangular fibrocartilage complex injury. Journal of Hand Therapy. 2019. DOI: 10.1016/j.jht.2017.09.002
[42] Evaluation of prestyloid recess morphology and ulnar-sided contrast leakage in CT arthrography of the wrist. BMC Musculoskeletal Disorders. 2022. DOI: 10.1186/s12891-022-05241-9
[43] Green S Operative Hand Surgery. Chronic Perilunate Instability (SL Plus LT Instability) > Palmer’s Classification of TFCC Lesions > Class 1A Tear.
[44] Repair of Arthroscopic Triangular Fibrocartilage Complex Tears in Athletes. Hand Clinics. 2009. DOI: 10.1016/j.hcl.2009.05.011
[45] Arthroscopic Transosseous Repair of Foveal Tears of the Triangular Fibrocartilage Complex: A Systematic Review of Clinical Outcomes. Arthroscopy. 2020. DOI: 10.1016/j.arthro.2020.12.209
[47] Classification of ulnar triangular fibrocartilage complex tears. A treatment algorithm for Palmer type IB tears. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416687479
[48] Arthroscopic Triangular Fibrocartilage Complex Repair Using Modified Outside‐In Technique. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2024.103349
[49] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > TFCC Repair > Classification, Functional Anatomy, Clinical Features, and Indication for Repair.
[50] The Effect of Triangular Fibrocartilage Complex Tear on Wrist Proprioception. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.01.022
[53] Triangular Fibrocartilage Complex Injuries in the Elite Athlete. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.014
[54] Comparison between conventional MRI and MR arthrography in the diagnosis of triangular fibrocartilage tears and correlation with arthroscopic findings. Injury. 2019. DOI: 10.1016/j.injury.2019.07.032
[55] The Distal Radiou1nar joint. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80071-8
[56] TFCC Lesions in Children and Adolescents: Open Treatment. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518500509
[58] Isolated tears of the triangular fibrocartilage of the wrist: Results of partial excision. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80104-5
[59] Load-Bearing Radioulnar Distances to Evaluate an Unstable Distal Radioulnar Joint in Patients With Triangular Fibrocartilage Complex Tears. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.01.008
[60] Green S Operative Hand Surgery. Chronic Perilunate Instability (SL Plus LT Instability) > Palmer’s Classification of TFCC Lesions > Class 1B Tear.
[61] The importance of radial multiplanar reconstructions for assessment of triangular fibrocartilage complex injury in CT arthrography of the wrist. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03321-2
[62] Prevalence of Triangular Fibrocartilage Complex Abnormalities on MRI Scans of Asymptomatic Wrists. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.10.006
[63] A Systematic Review and Analysis of Palmer Type I Triangular Fibrocartilage Complex Injuries: Outcomes of Treatment. Journal of Hand and Microsurgery. 2020. DOI: 10.1055/s-0040-1713580
[64] Magnetic Resonance Arthrography of the Wrist: Case Presentation and Discussion. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.03.015
[66] Arthroscopic triangular fibrocartilage complex reconstruction with free tendon graft for chronic distal radioulnar joint instability. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02827-2
[68] Arthroscopic Foveal Repair of the Triangular Fibrocartilage Complex. Journal of Wrist Surgery. 2015. DOI: 10.1055/s-0035-1544226
[69] Wafer distal ulna resection for triangular fibrocartilage tears and/or ulna impaction syndrome. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90325-j
[70] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Arthroscopic Repair of Class 1B TFCC Tears.
[71] Arthroscopic‐Assisted Suture Tape–Reinforced Triangular Fibrocartilage Complex Repair and Distal Radioulnar Ligament Augmentation Using a Modified Adams‐Berger Technique. Arthroscopy Techniques. 2026. DOI: 10.1002/atn2.70005
[72] Intraarticular Lesions in Distal Fractures of the Radius in Young Adults. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80364-6
[73] Wear Patterns of the Articular Cartilage and Triangular Fibrocartilaginous Complex of the Wrist: A Cadaveric Study. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90078-7
[74] Effects of radial deformity on distal radioulnar joint mechanics. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90098-n
[88] The distal radioulnar ligaments: A biomechanical study. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80075-9
[90] Force transmission through the distal ulna: Effect of ulnar variance, lunate fossa angulation, and radial and palmar tilt of the distal radius. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90342-m
[102] The Value of Plain X-Rays in Predicting TFCC Injury after Distal Radial Fractures. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408090106
[109] New trends in arthroscopic management of type 1-B TFCC injuries with DRUJ instability. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193409100120
[110] Evaluation of Ulnar-sided Wrist Pain. Journal of the American Academy of Orthopaedic Surgeons. 2017. DOI: 10.5435/jaaos-d-16-00407
[111] Extensor Retinaculum Capsulorrhaphy and Suture Repair for Ulnocarpal and Distal Radioulnar Joint Instability: One-Year Results. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2025.100806
[113] Comparison Between High-Resolution MRI With a Microscopy Coil and Arthroscopy in Triangular Fibrocartilage Complex Injury. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.05.001
[116] Résultats des réinsertions du TFCC sous arthroscopie. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.110
[117] RETRACTED: Prognostic Factors of Arthroscopic Debridement for Central Triangular Fibrocartilage Complex Tears in Adults Younger Than 45 Years: A Retrospective Case Series Analysis. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.05.044
[118] A-0263Session 16:Ulnar sided wrist pain. Journal of Hand Surgery: European Volume. 2007. DOI: 10.1016/j.jhse.2007.02.170
[119] Diagnostic Comparison of 1.5 Tesla and 3.0 Tesla Preoperative MRI of the Wrist in Patients With Ulnar-Sided Wrist Pain. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.02.028
[121] The Hook Test Is More Accurate Than the Trampoline Test to Detect Foveal Tears of the Triangular Fibrocartilage Complex of the Wrist. Arthroscopy: The Journal of Arthroscopic & Related Surgery. 2021. DOI: 10.1016/j.arthro.2021.03.005
[122] Pediatric Ulnar-sided Wrist Pain: A Review of the Current Literature. Journal of the American Academy of Orthopaedic Surgeons. 2022. DOI: 10.5435/jaaos-d-21-01029
[123] Predictors for poor outcome for conservatively treated traumatic triangular fibrocartilage complex tears. The Bone & Joint Journal. 2021. DOI: 10.1302/0301-620x.103b8.bjj-2020-2310.r2
[125] The distal radioulnar joint after distal radial fractures: when and how do we need to treat pain, stiffness or instability?. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934221140238
[126] Radial Sided Triangular Fibrocartilage Complex Tears: A Comprehensive Review. HAND. 2022. DOI: 10.1177/15589447221084125
[127] Rehabilitation Following Surgery for the Distal Radioulnar Joint. Techniques in Hand & Upper Extremity Surgery. 1997. DOI: 10.1097/00130911-199709000-00009
[129] Management of Acute Distal Radioulnar Joint Instability Following a Distal Radius Fracture: A Systematic Review and Meta-Analysis. Journal of Hand Surgery Global Online. 2021. DOI: 10.1016/j.jhsg.2021.02.005
[130] Arthroscopic Management of Distal Radius Fractures. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.08.015
[132] Advantages of Open Repair of a Foveal Tear of the Triangular Fibrocartilage Complex Via a Palmar Surgical Approach. Techniques in Hand & Upper Extremity Surgery. 2009. DOI: 10.1097/bth.0b013e3181bd8319
[133] The Utility of High-Resolution Magnetic Resonance Imaging in the Evaluation of the Triangular Fibrocartilage Complex of the Wrist. The Journal of Bone and Joint Surgery (American Volume)*. 1997. DOI: 10.2106/00004623-199711000-00009
[135] DRUJ instability after distal radius fracture: A comparison between cases with and without ulnar styloid fracture. International Journal of Surgery. 2011. DOI: 10.1016/j.ijsu.2011.08.005
[136] Arthrography is Superior to Magnetic Resonance Imaging for Diagnosing Injuries of the Triangular Fibrocartilage. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80068-5
[137] Factors associated with return to work after open reinsertion of the triangular fibrocartilage. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.03.012
[139] Changes in Ulnar Variance after a Triangular Fibrocartilage Complex Tear. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1668153
[140] 5.3 Volar locking compression plate technique for dorsally displaced fractures of the distal radius – our first clinical results. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2006. DOI: 10.1016/j.jhsb.2006.03.101