Por que esta cirurgia foi recomendada
O Dr. Kieran Hirpara, cirurgião de membros superiores no Mater Private Hospital Rockhampton, começa com as opções menos invasivas adequadas ao seu quadro clínico. Geralmente, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que você nos procure, ainda assim será necessário um encaminhamento do seu médico de família para que você tenha direito ao reembolso do Medicare. Na sua consulta, colhemos o histórico clínico, examinamos a sua mão e solicitamos exames de imagem, se forem necessários, para confirmar o diagnóstico.
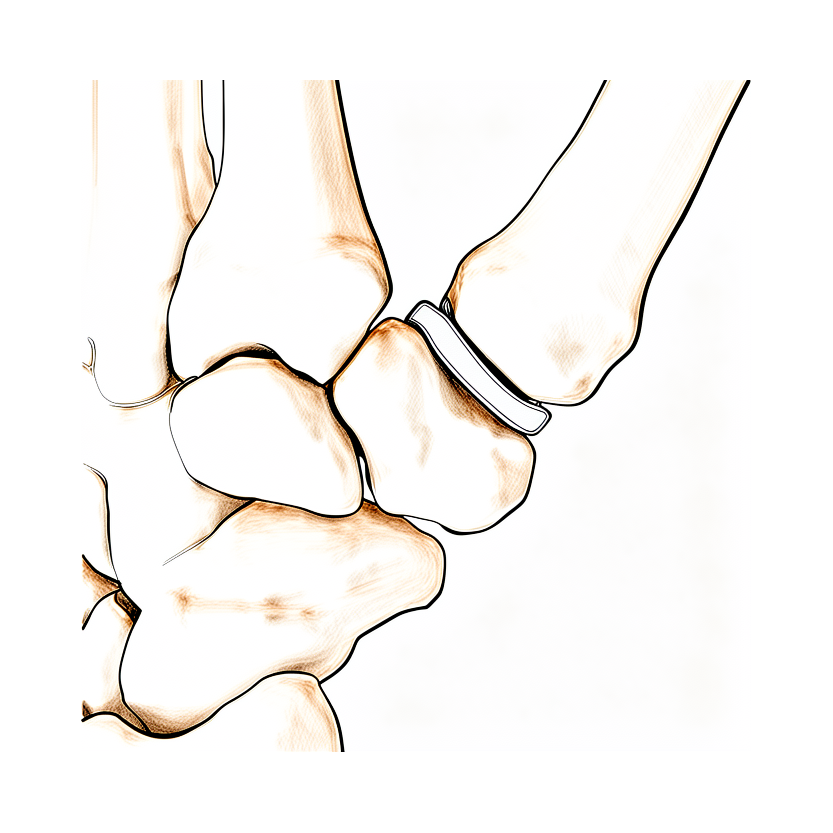
Esta operação substitui a superfície desgastada de uma pequena articulação por uma peça de carbono lisa e moldada. Ela geralmente é indicada para artrite de longa data que não melhorou com mudanças nas atividades, terapia de mão ou uso de talas. Normalmente, tentamos primeiro o tratamento não cirúrgico e consideramos a cirurgia quando ele não trouxe melhora suficiente. Em alguns problemas estruturais, a cirurgia pode ser recomendada desde o início.
A operação tem como objetivo aliviar a dor mantendo a articulação em movimento. Ela também busca manter a altura natural do polegar e preservar a força de pinça e de preensão. Na articulação da base do polegar, 91% dos implantes continuam funcionando bem no acompanhamento de médio prazo. Vamos conversar com você sobre esta opção e decidir juntos se ela é adequada para a sua mão e os seus objetivos.
Antes da operação
Nas sete horas antes da sua operação, não coma nem beba nada. Pedimos sete horas em vez de seis para que a sua cirurgia possa ser antecipada caso a agenda cirúrgica ande mais rápido. O seu cirurgião vai dizer quais dos seus medicamentos habituais você deve suspender e quando, e ajuda trazer uma lista escrita de tudo o que você toma. Providencie alguém para levar você para casa depois e use roupas largas e confortáveis. Em geral, radiografias são tudo de que precisamos para planejar a operação, embora às vezes também se use uma ressonância magnética ou uma ultrassonografia. Se você tiver outras condições médicas, poderá precisar de exames de sangue ou de uma avaliação com o anestesista, o médico que aplica a anestesia. A maioria dos pacientes não precisa de nenhum dos dois.
No dia da cirurgia
Você chega à unidade de admissão cirúrgica do hospital, onde é registrado e preparado para o centro cirúrgico. Você vai conhecer o anestesista, o médico que cuida da sua anestesia. Esta operação é realizada sob anestesia geral. Você ficará completamente adormecido durante a operação. Alguns pacientes também podem receber um bloqueio nervoso regional para alívio da dor pós-operatória; o anestesista decide isso no dia, conforme as suas condições individuais.
Em seguida, você é levado à sala de operações, onde a operação é realizada. Depois, você acorda na sala de recuperação, onde as enfermeiras cuidam de você enquanto o efeito da anestesia passa. Quando você estiver estável, vai para o quarto do hospital ou para casa, dependendo do procedimento e de como está a sua recuperação.
Como é realizada a operação
O seu cirurgião faz um único corte sobre a área da mão que está sendo operada. Por essa abertura, ele remove as superfícies desgastadas e danificadas da articulação. No lugar das superfícies desgastadas, ele coloca uma peça de carbono lisa e moldada, que fica entre os ossos. Esse espaçador assume a função da superfície articular desgastada, para que os ossos deslizem suavemente em vez de se esfregarem um contra o outro.
Na articulação da base do polegar, o seu cirurgião mantém a altura natural do polegar colocando o espaçador entre os ossos. Em seguida, a articulação é reparada e sustentada para que cicatrize em uma boa posição. O seu polegar pode ser mantido imóvel em uma posição reta enquanto cicatriza.
O corte é fechado com pontos. Um curativo é colocado sobre a ferida, e a nossa equipe vai explicar como cuidar dele nos primeiros dias.
Após a operação
A maioria dos pacientes permanece uma noite no hospital após esta operação, embora alguns possam ir para casa no mesmo dia. Você acorda na sala de recuperação e depois vai para o quarto. As enfermeiras vão manter você confortável e dar medicamentos para a dor, se precisar. A sua mão ficará com um curativo e uma tala, que protegem a operação enquanto ela cicatriza. Você pode sair da cama e se movimentar assim que se sentir firme. Providencie para que alguém fique com você nas primeiras 24 horas em casa. Deixamos o curativo por cerca de 10 dias; por favor, não o retire antes disso, a menos que lhe seja indicado. Trocamos ou removemos o curativo quando o examinarmos.
Recuperação
Espere um pouco de dor e inchaço na mão nos primeiros dias e semanas. Isso faz parte normal da cicatrização e melhora aos poucos. Manter a mão elevada quando estiver descansando ajuda, e os medicamentos para a dor que damos vão aliviar o desconforto. A maioria das pessoas percebe que a pior parte da dor passa cedo, e o conforto melhora de forma contínua a partir daí.
A sua mão ficará com um curativo e uma tala, que protegem a articulação enquanto ela cicatriza. Deixamos o curativo por cerca de 10 dias e o trocamos ou removemos quando o examinarmos. A reabilitação após uma cirurgia da mão é feita com terapia de mão, não com fisioterapia. A sua terapia de mão após a cirurgia é com Ruby Doolan, da Extend Rehabilitation. Ruby é terapeuta de mão: ela vai orientar os seus exercícios e confeccionar qualquer tala de que você precise enquanto a mão se recupera. No início, os exercícios são leves e têm como foco controlar o inchaço. À medida que o movimento volta, eles avançam para recuperar a capacidade de dobrar, esticar e segurar objetos.
Você conseguirá fazer tarefas leves do dia a dia em casa, dentro dos limites da sua tala. Você não poderá apertar, fazer pinça nem levantar peso com a mão operada enquanto ela estiver imobilizada. Depois que a tala for retirada e o seu cirurgião liberar, você pode começar a usar a mão de forma mais normal, e depois pode voltar a dirigir. Consulte nossa página sobre Dirigir após cirurgia no membro superior para mais detalhes.
A recuperação varia de pessoa para pessoa. O seu cronograma pode ser diferente, e o seu cirurgião e a sua terapeuta vão orientar você ao longo do caminho.
O que pode dar errado
A maioria dos pacientes tem bons resultados, mas, ocasionalmente, podem surgir problemas. Seu cirurgião e a equipe monitoram você de perto para detectar qualquer problema precocemente.
Às vezes, o implante muda de posição ou afunda no osso. Você pode notar uma dor nova na articulação, a sensação de que o dedo ou o polegar não está reto, ou uma mudança na forma como ele se move. Se notar qualquer uma dessas coisas, mencione na sua próxima consulta de acompanhamento.
O implante também pode afrouxar. Isso geralmente se manifesta como uma dor que volta depois de um bom período de melhora, muitas vezes pior quando você aperta ou faz pinça. Avise o seu cirurgião se isso acontecer.
A articulação pode ficar rígida. O dedo ou o polegar pode não dobrar ou esticar tanto quanto antes, e o tendão do dorso da articulação pode ficar preso por tecido cicatricial. Mencione isso na sua consulta de acompanhamento para que a sua terapeuta possa ajustar os seus exercícios.
A articulação pode ficar instável ou a deformidade original pode voltar. Você pode ver o dedo se desviando do alinhamento novamente. Fale sobre isso na sua próxima consulta.
A infecção é incomum, mas precisa de atenção rápida. Ligue para a clínica no mesmo dia se tiver febre, vermelhidão que se espalha ao redor da ferida, ou saída de líquido ou pus por ela. Uma dor que continua piorando apesar dos analgésicos também significa que você deve ligar para a clínica no mesmo dia.
Estruturas próximas podem ser irritadas ou lesionadas durante este tipo de cirurgia. Um nervo perto do polegar pode ficar sensível, causando formigamento ou alteração da sensibilidade na pele. A artéria do lado do polegar do punho, ou um tendão na parte da frente do punho, pode ser afetada. Se notar dormência ou não conseguir mexer os dedos depois que o efeito do bloqueio nervoso passar, por volta de 24 horas, ligue para a clínica. Dormência e fraqueza nas primeiras 24 horas após um bloqueio nervoso são esperadas.
Um osso da mão pode, ocasionalmente, quebrar durante ou após a cirurgia. Isso causa dor e inchaço repentinos. Ligue para a clínica se isso acontecer.
Se um implante falhar e não puder ser salvo, outras operações podem ajudar. O implante pode ser removido e a articulação tratada de outra forma, o que alivia a dor de maneira confiável. Em casos raros, a articulação pode ser fundida, ou seja, ficar permanentemente rígida, ou pode ser necessário remover o dedo.
A tabela de complicações nesta página lista as taxas típicas, caso queira informações mais detalhadas.
Quando nos contactar
A maioria dos problemas aparece cedo, e agir rapidamente facilita resolvê-los. Ligue para a clínica no mesmo dia se tiver febre, vermelhidão que se espalha ao redor da ferida, ou saída de líquido ou pus por ela. Ligue para a clínica no mesmo dia também se a dor continuar piorando apesar dos analgésicos. Ligue para a clínica se notar dormência ou não conseguir mexer os dedos depois que o efeito do bloqueio nervoso passar, por volta de 24 horas. Dormência e fraqueza nas primeiras 24 horas após um bloqueio nervoso são esperadas.
Vá ao pronto-socorro se tiver inchaço ou dor na panturrilha, ou falta de ar ou dor no peito. Esses podem ser sinais de um coágulo sanguíneo. Vá ao pronto-socorro se os seus dedos, a mão ou o polegar ficarem pálidos, frios, brancos, azulados ou escuros. Isso pode ser um problema de circulação.
Se não conseguir falar com a clínica, fora do horário de atendimento ou no fim de semana, vá ao pronto-socorro mais próximo.
Onde ler mais sobre a condição
Esta página trata da própria operação. A condição que ela trata, incluindo o que as evidências indicam sobre quando a cirurgia é benéfica e quando não é, é abordada com mais detalhes na página Artrite Basal do Polegar.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a study with minimum 8-year follow-up [1].
- Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate [4].
- The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition [6].
- The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis [7].
- Arthroplasty is recommended for patients with post-trauma painful PIP joints [8].
- Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years [9].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity [10].
- The results of pyrolytic carbon PIPJ arthroplasty in review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
- A study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs was conducted [11].
- The PyroDisk interposition arthroplasty confirmed good 5-year clinical results [12, 13].
- PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis [15].
- All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty [16].
- The encouraging mid-term clinical results of the interposition implant (APSI) in the context of proximal pole scaphoid pseudarthrosis make this technique a proven alternative, without precluding a definitive therapeutic option in case of failure [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Anatomy & Pathophysiology
Bony Anatomy
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [28].
- The radial ray or first ray is the shortest, made up of only three bones: a metacarpal and two phalanges [28].
- The trapezium is clearly angled out in front of the carpal plane so that the first metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [28].
- The thumb metacarpal is the shortest, while the index metacarpal is by far the longest [28].
- The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal, whereas they are located at the distal ends of the other metacarpals [28].
- The thumb metacarpal is independent and articulates with the trapezium [35].
- The index metacarpal is the most firmly fixed [35].
- The ring metacarpal has about 10 degrees of mobility in flexion and extension [35].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [35].
Soft Tissue & Vascular Anatomy
- The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [27].
- The first (most radial) compartment contains the abductor pollicis longus and the extensor pollicis brevis [27].
- The second extensor compartment contains the extensor carpi radialis longus and the extensor carpi radialis brevis [27].
- The third compartment contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [27].
- The fourth extensor compartment contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [27].
- The fifth compartment contains the extensor digiti quinti [27].
- The sixth compartment contains the extensor carpi ulnaris tendon, which inserts at the base of the little finger metacarpal [27].
- The extrinsic finger flexors are the flexor digitorum profundus and the flexor digitorum superficialis [27].
- The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx [27].
- The flexor digitorum superficialis acts as a flexor of the proximal interphalangeal and metacarpophalangeal joints [27].
- There are seven interosseous muscles, four dorsal and three volar [32].
- The dorsal interossei are abductors [32].
- The volar interossei are adductors [32].
- The middle finger has two dorsal interossei (abductors) and no volar interossei (adductors) because the central axis of the hand lies within it [32].
- The "princeps pollicis" artery is the terminal branch of the radial artery and crosses the first intermetacarpal space [36].
- The princeps pollicis runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [36].
- The princeps pollicis divides into two terminal rami, namely the collateral palmar arteries of the thumb, at the level of the cutaneous flexion crease of the metacarpophalangeal joint [36].
- An arcade located deep in the flexor tendon joins together the two arteries at the level of the distal metaphysis of the first phalanx [36].
- The dorsal arteries of the thumb originate from the palmar arteries (princeps, commissural or anastomoses of the superficial arcade) at the level of the first metacarpal [36].
Functional Mechanics
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration [28].
- The thumb ray is more mobile, shorter, and more proximal than the other rays, allowing it to project in front of the plane of the palm to oppose itself to the other four rays [28].
- The skeleton of the hand presents a longitudinal and transverse concavity, giving it the shape of a cup with a palmar concavity when the thumb is placed next to the index finger [28].
- The transverse axis of the palm forms an acute angle of approximately 75 degrees with the longitudinal axis [28].
- The metacarpal arch is endowed with a great deal of adaptability because of the mobility of the peripheral metacarpals [35].
- The heads of the second and third metacarpals are fixed [35].
- The mobility of the ulnar metacarpals allows "flexion" of 10 degrees for the fourth metacarpal, and "flexion" of 20 degrees for the fifth metacarpal [35].
- The keystones of the longitudinal arches are the metacarpophalangeal articulations, whose thick anterior glenoid capsules, the volar plates, prevent hyperextension [35].
- The dorsal skin slides distally to allow metacarpophalangeal joint flexion [40].
- Interphalangeal flexion is accomplished by means of a special arrangement of skin folds on the dorsum of each articulation [40].
- The gliding mechanism for tendons in narrow crowded areas is assured by the synovial sheath, which allows a considerable amplitude of movement [40].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [40].
- The position of each articulation depends on the equilibrium of forces acting at that level, and this equilibrium is subject to the position of the immediately proximal articulation [40].
- Single articular movements around a fixed perpendicular axis simply do not exist in the hand [40].
- Almost all movements in the hand are around oblique and variable axes, resulting in combined movements permitting optimal orientation of the phalanges at the time of prehension [40].
Indications and Disease Staging
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan resurfacing implant is a valid option for treating scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- The pyrocarbon implant is indicated for the treatment of STT arthrosis [15].
- The pyrocarbon interposition implant (APSI) is an alternative for the treatment of proximal pole scaphoid pseudarthrosis [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT osteoarthritis who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Patient Selection and Demographics
- Active patients under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint are candidates for anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation [9].
- Pyrocarbon disc interposition is used for the treatment of CMC1 osteoarthritis grade 2 to 3 [11].
- Total trapezectomy associated with the placement of a NuGrip pyrocarbon implant is a procedure for the replacement of the TMC joint [22].
Comparative Classification and Efficacy
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
Clinical Presentation
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal osteoarthritis [1].
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan implant is used for trapeziometacarpal osteoarthritis [4].
- The Pyrocardan implant is used for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant is used for advanced trapeziometacarpal arthritis [6].
- The Pyrocardan resurfacing implant is used for scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- Pyrocarbon PIP arthroplasty is used for post-trauma painful joints [8].
- Anatomic pyrolytic carbon resurfacing hemiarthroplasty is used for Eaton-Littler stage III osteoarthritis of the thumb CMC joint in patients under 65 years of age [9].
- Pyrolytic carbon implants are used for proximal interphalangeal joint (PIPJ) arthroplasty [10].
- Pyrocarbon disc interposition is used for CMC1 osteoarthritis grade 2 to 3 [11].
- PyroDisk interposition arthroplasty is used for trapeziometacarpal osteoarthritis [12].
- PyroDisk interposition is indicated for patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The pyrocarbon implant is used for STT arthrosis [15].
- Pyrolytic interpositional arthroplasty is used for TMC arthritis [16].
- Pi2 pyrocarbon spacer arthroplasty is used for carpometacarpal joint osteoarthritis [17].
- The interposition implant (APSI) is used for pseudarthrosis of the proximal pole of the scaphoid [18].
- A pyrocarbon implant is used for Kienböck disease [19].
- Total trapeziectomy associated with the placement of a pyrocarbon type Nugrip implant is used after replacement of the TMC joint [22].
- The Pyrocardan implant is used for stage 2 trapeziometacarpal osteoarthritis [23].
- The Pi2 pyrocarbon implant is used in total trapeziectomy and suspension ligamentoplasty [24].
- The Pi2 pyrocarbon implant is used in destructions of the capitolunate joint space [25].
Investigations
- Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [26].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining hand pathology but can be expensive, time-consuming, and often nonspecific [26].
- A systematic method to approaching the physical examination of the hand is essential due to the number of structures in a small space [26].
Treatment
Trapeziometacarpal Joint Osteoarthritis
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a minimum 8-year follow-up study [1].
- Partial trapeziectomy with pyrocarbon arthroplasty provides excellent pain relief and high patient satisfaction for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis that can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate for trapeziometacarpal osteoarthritis [4].
- Long-term follow-up data for pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 is available in a study involving more than 150 thumbs [11].
- Interposition arthroplasty with PyroDisk confirmed good 5-year clinical results [12, 13].
- The modified procedure of partial trapeziectomy and pyrocarbon interpositional arthroplasty improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength [29].
- Pyrocarbon interposition arthroplasty for trapeziometacarpal osteoarthritis does not preclude subsequent conventional arthroplasty techniques in the event of failure [23].
Scaphotrapeziotrapezoid Joint Osteoarthritis
- The Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis, evidenced by good functional and radiographic outcomes and the absence of surgical complications [7].
- The good results, simple surgical procedure, absence of complications, and lack of need for fixation or ligamentoplasty confirm the advantages of the pyrocarbon implant in the treatment of STT arthrosis [15].
Other Indications
- Pyrocarbon PIP arthroplasty is recommended for post-trauma painful joints [8].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure with the potential to achieve pain relief, stability, satisfactory ROM, and correction of deformity, though results were unpredictable and may not be superior to other methods of arthroplasty [10].
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis, especially in opposition with a mean Kapandji score of 9.60, with no major aggravation of metacarpophalangeal extension [17].
- The interposition implant (APSI) for proximal scaphoid pseudarthrosis provides encouraging mid-term clinical results and serves as a proven alternative without precluding a definitive therapeutic option in case of failure [18].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant, and the average grip strength was 76.5% of the contralateral side [19].
Complications
- The Pyrocardan implant has a high complication rate [4].
- The Pyrocardan resurfacing implant for STT osteoarthritis was associated with the absence of surgical complications [7].
- The pyrocarbon implant for STT arthrosis was associated with the absence of complications [15].
Recovery
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty, especially in opposition, with a mean Kapandji score of 9.60 [17].
- There was no major aggravation of metacarpophalangeal extension following Pi2 pyrocarbon spacer arthroplasty [17].
- The average grip strength was 76.5% of the contralateral side after pyrocarbon implant treatment for Kienböck disease [19].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant [19].
Key Evidence
- [L4] Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity. [1] (10.1177/1753193420906805)
- [L3] Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction. [2] (10.1177/1753193413519384)
- [L4] PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint. [3] (10.1097/bth.0b013e318271aab7)
- [L4] The study concludes that the Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate. [4] (10.1016/j.hansur.2016.09.004)
- [L4] The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray. [5] (10.1016/j.hansur.2018.10.044)
- [L4] The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition. [6] (10.1016/j.jhsa.2014.07.011)
- [L3] The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan1 resurfacing implant is a valid option for treating STT osteoarthritis. [7] (10.1016/j.hansur.2017.01.003)
- [L4] We recommend arthroplasty for this group of patients. [8] (10.1016/s0363-5023(03)80384-2)
- [L3] Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years. [9] (10.1142/s2424835518500443)
- [L4] The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty. [10] (10.1016/j.jhsa.2006.02.018)
- [L4] This is the first study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs. [11] (10.1016/j.jhsa.2018.06.086)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [12] (10.1177/1558944716660555n)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [13] (10.1177/1558944716660555m)
- [L4] PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous. [14] (10.1177/1753193420981552)
- [L4] The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis. [15] (10.1016/j.main.2005.04.010)
- [L3] All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty. [16] (10.1155/2019/7961507)
- [L3] Range of motion improved, especially in opposition (mean Kapandji score, 9.60), with no major aggravation of metacarpophalangeal extension. [17] (10.1016/j.hansur.2016.05.002)
- [L4] Les résultats cliniques encourageants à moyen terme de l’implant d’interposition (APSI), dans le cadre d’une pseudarthrose du pôle proximal du scaphoïde, font de cette technique une alternative probante, sans interdire une option thérapeutique définitive en cas d’échec. [18] (10.1016/j.main.2011.10.031)
- [L5] There were no changes in range of motion after surgery and the average grip strength was 76.5% of the contralateral side. [19] (10.1016/j.main.2014.09.002)
- [Case_report] The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis. [20] (10.1016/j.jhsg.2026.100964)
- [L4] La trapézectomie totale associée à la mise en place d'un implant en pyrocarbone type Nugrip après le remplacement de l'articulation TMC semble être une procédure attrayante. [22] (10.1016/j.hansur.2018.10.166)
- [L3] Il ne coupe pas les ponts en cas d'éventuel échec à des techniques d'arthroplastie plus conventionnelles. [23] (10.1016/j.main.2011.10.132)
- [L3] The implant Pi2 seems to contribute keeping trapezial height, without functional advantages and with a risk of dislocation. [24] (10.1016/j.main.2013.04.003)
- [L4] Cette technique a l'avantage de préserver les mobilités médio-carpiennes et les ligaments extrinsèques du poignet. [25] (10.1016/j.hansur.2016.10.125)
- [L4] The modified procedure improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength. [29] (10.1177/1753193414553368)
References
[1] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420906805
[2] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413519384
[3] PyroCarbon Implant Hemiarthroplasty for Trapeziometacarpal Arthritis. Techniques in Hand & Upper Extremity Surgery. 2013. DOI: 10.1097/bth.0b013e318271aab7
[4] Early outcomes of Pyrocardan® implants for trapeziometacarpal osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.09.004
[5] L’implant en Pyrocarbone (Pyrocardan®) dans le traitement de l’arthrose carpo-métacarpienne ulnaire post-traumatique. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.044
[6] Pyrocarbon Interposition (PyroDisk) Implant for Trapeziometacarpal Osteoarthritis: Minimum 5-Year Follow-Up. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.07.011
[7] Treatment of scaphotrapeziotrapezoid osteoarthritis with the Pyrocardan® implant: Results with a minimum follow-up of 2 years. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.01.003
[8] Pyrocarbon PIP arthroplasty for post trauma painful joints. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80384-2
[9] Anatomic Pyrocarbon Hemiarthroplasty for Thumb Carpometacarpal Osteoarthritis in Patients under 65 Years: Mid Term Results. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518500443
[10] Pyrolytic Carbon Proximal Interphalangeal Joint Resurfacing Arthroplasty. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.02.018
[11] Long-Term Follow-Up After Pyrocarbon Disc Interposition for Thumb CMC Osteoarthritis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.086
[12] Pyrocarbon Interposition Arthroplasty of the Trapeziometacarpal Joint With the PyroDisk. HAND. 2016. DOI: 10.1177/1558944716660555n
[13] PyroDisk Interposition Implant for Trapeziometacarpal Osteoarthritis. HAND. 2016. DOI: 10.1177/1558944716660555m
[14] Re: Smeraglia F, et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. J Hand Surg Eur. 2020, 45: 472–6. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/1753193420981552
[15] Traitement de l'arthrose S.T.T. par un Implant en pyrocarbone. Premiers résultats. Chirurgie de la Main. 2005. DOI: 10.1016/j.main.2005.04.010
[16] Tendon versus Pyrocarbon Interpositional Arthroplasty in the Treatment of Trapeziometacarpal Osteoarthritis. BioMed Research International. 2019. DOI: 10.1155/2019/7961507
[17] A ten-year prospective outcome study of Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.05.002
[18] Pseudarthrose du scaphoïde : résection proximale et interposition d’un implant en pyrocarbone, à propos de 20 cas. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.031
[19] Le traitement de la maladie de Kienböck par un implant en pyrocarbone : fait clinique. Chirurgie de la Main. 2014. DOI: 10.1016/j.main.2014.09.002
[20] Game, Set… Revision! A Case Report of a Tennis Player Who Smashed His Scaphotrapeziotrapezoid-Joint Pyrocardan Implant Twice. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.100964
[22] Reprise de prothèses totales trapézo-métacarpiennes par un implant en Pyrocarbone type NuGrip. À propos de 6 cas. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.166
[23] L’implant pyrocardan : interposition libre en pyrocarbone trapezometacarpienne pour l’arthrose de stade 2. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.132
[24] Trapézectomie totale et ligamentoplastie de suspension : une interposition par un implant Pi2® en pyrocarbone a-t-elle un intérêt ?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.04.003
[25] Utilisation de l’implant en pyrocarbone de type Pi2 dans les destructions de l’interligne articulaire capito-lunaire. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.125
[26] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[27] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[28] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[29] Re: Mariconda et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. J Hand Surg Eur. 2014, 39: 604–610. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414553368
[32] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[35] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[36] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[40] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.