Patients › Wrist
Doença de Kienböck
Kienböck’s disease — progressive wrist pain from lunate avascular necrosis; diagnosis and treatment options.
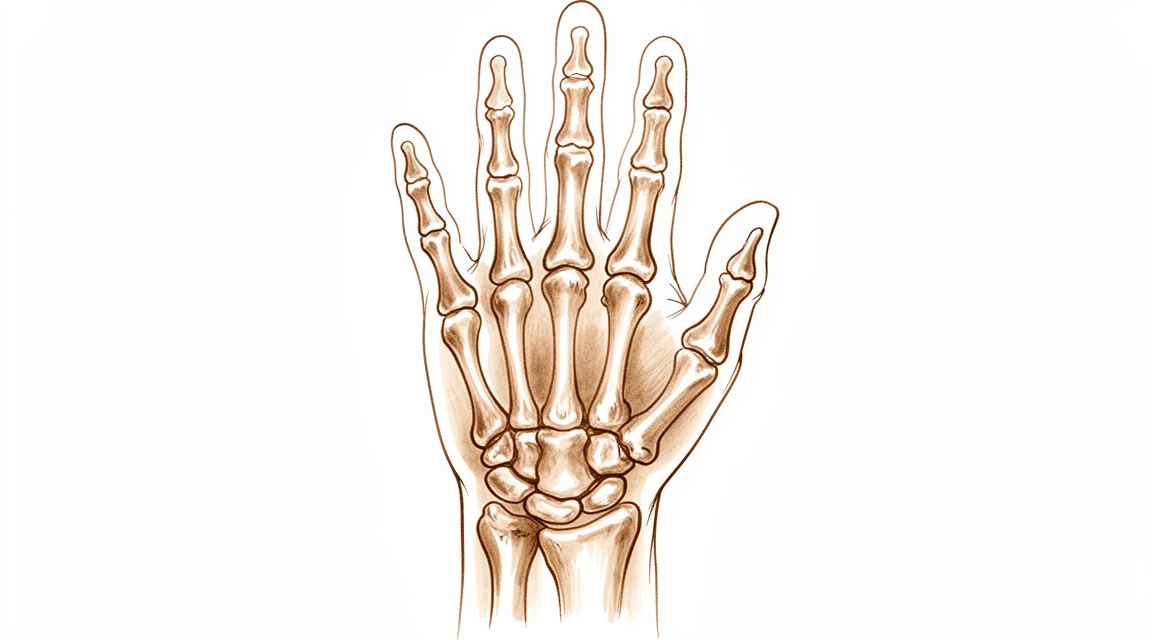
O que você está sentindo
A dor da doença de Kienböck localiza-se no meio da parte posterior do seu punho, sobre um pequeno osso chamado semilunar. Muitas vezes, ela surge sem nenhuma lesão, embora algumas pessoas se lembrem de uma pancada ou de um esforço repetitivo anteriormente. A parte de trás do punho também pode parecer inchada. O punho pode ficar rígido, e a sua força de preensão pode ser menor do que o normal.
A dor tende a piorar ao segurar, torcer e colocar carga sobre o punho, como ao carregar as compras, girar a tampa de um pote ou empurrar o corpo para se levantar de uma cadeira. Descansar a mão geralmente alivia a dor. Tarefas do dia a dia que exigem uma preensão firme ou o punho dobrado para trás, como usar um martelo, torcer um pano ou segurar o volante por longos períodos, podem se tornar difíceis ou desconfortáveis.
A doença de Kienböck costuma surgir entre os 30 e os 40 anos de idade. É pouco comum em pessoas mais velhas, embora, quando aparece mais tarde na vida, seja mais frequente em mulheres e na mão que elas mais usam para trabalhos pesados. Em pessoas mais velhas, a dor pode ser discreta ou passar facilmente despercebida, o que às vezes atrasa o diagnóstico.
Se não for tratada, a condição geralmente piora lentamente com o tempo, e pode evoluir mais rápido do que os médicos acreditavam. Ao longo dos anos, pode levar à artrose (artrite do desgaste) no punho. Por esse motivo, o seu outro punho também deve ser examinado e radiografado, porque a doença pode afetar os dois lados.
Consulte o seu médico de família ou solicite uma avaliação por um especialista se a dor não estiver melhorando, estiver piorando ao longo de semanas, acordar você à noite ou impedir você de trabalhar ou de usar a mão. Se não conseguir entrar em contato com a clínica fora do horário de atendimento ou no fim de semana, vá ao pronto-socorro mais próximo.
O que está realmente acontecendo
O seu punho é formado por oito pequenos ossos dispostos em duas fileiras. O semilunar fica no meio da fileira de trás, encaixado entre os ossos vizinhos e a extremidade do osso do antebraço. Nenhum músculo se prende a ele, por isso ele simplesmente se move conforme os ossos ao redor se movem.
O semilunar também tem um suprimento sanguíneo frágil. Pequenos vasos entram no osso por cada extremidade e, em alguns punhos, apenas um caminho leva sangue até ele. Quando esse suprimento é interrompido, o tecido ósseo morre. Os médicos chamam isso de osteonecrose, que significa morte do osso por falta de sangue. Esse é o problema central da doença de Kienböck.
Ainda não está totalmente esclarecido por que o suprimento falha. Uma única lesão geralmente não é a culpada. A doença muitas vezes começa aos poucos, sem nenhuma queda ou acidente, e problemas no fluxo de sangue para dentro e para fora do osso parecem ter mais importância do que o desgaste. Alguns punhos também têm um formato que coloca mais carga sobre o semilunar do que outros, o que pode preparar o terreno para a doença.
Depois que o osso enfraquece, as consequências vêm em seguida. Normalmente, o semilunar funciona como um pequeno amortecedor, dividindo a carga que passa pelo punho toda vez que você segura ou empurra algo. Um osso morto não consegue suportar bem essa carga. Ele endurece, depois racha e colapsa sob pressão. À medida que perde altura, os ossos acima dele afundam, as pequenas articulações do punho saem do alinhamento e os ligamentos que mantêm tudo no lugar ficam frouxos. É esse colapso que produz a dor, a rigidez e a preensão fraca descritas anteriormente.
Os médicos descrevem a condição em estágios, desde o osso endurecido, mas intacto, passando pelo colapso do semilunar, até a artrose em todo o punho. Os estágios iniciais podem melhorar apenas com repouso e uso de tala. Os estágios mais avançados, em que o osso já colapsou ou as superfícies da articulação estão desgastadas, são os que têm maior probabilidade de precisar de cirurgia.
O que podemos fazer a respeito
O Dr. Kieran Hirpara, cirurgião de membros superiores no Mater Private Hospital Rockhampton, começa com as opções menos invasivas adequadas ao seu quadro clínico. Em geral, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que você nos procure, ainda assim será necessário um encaminhamento do seu médico de família para que você tenha direito ao reembolso do Medicare. Uma avaliação na clínica, que inclui o seu histórico, um exame físico e exames de imagem quando necessários, estabelece o diagnóstico.
Nos estágios iniciais, geralmente começamos pelo tratamento não cirúrgico. Isso significa modificar a forma como você usa o punho, usar uma tala ou gesso para mantê-lo imóvel e fazer terapia da mão. Para crianças e adolescentes com menos de 15 anos, recomendamos manter o punho imóvel por pelo menos 6 semanas e depois acompanhá-lo de perto com novas radiografias, tomografia computadorizada e ressonância magnética. Alguns punhos melhoram apenas com isso, e em algumas pessoas a condição pode ter uma evolução leve.
Quando o tratamento não cirúrgico não traz melhora suficiente, consideramos a cirurgia. O objetivo da maioria das operações é tirar carga do semilunar para que ele fique protegido enquanto cicatriza, ou reconstruir o punho para que as superfícies desgastadas sejam contornadas. Nos estágios mais iniciais, um procedimento minimamente invasivo chamado descompressão do núcleo ósseo alivia a pressão dentro do osso. Outra opção é encurtar o osso do antebraço, a chamada osteotomia de encurtamento radial, que desvia a carga do semilunar. Um enxerto ósseo vascularizado leva um pequeno pedaço de osso vivo, com o seu suprimento sanguíneo preservado, até o semilunar para ajudá-lo a cicatrizar. Nos punhos em que o semilunar sofreu colapso significativo ou em que surgiu artrose (artrite do desgaste), as opções de “salvamento” incluem remover a fileira de ossos danificados, a chamada carpectomia da fileira proximal, unir alguns dos ossos do punho ou fazer a artrodese completa do punho. Vamos conversar sobre qual opção é adequada para o seu punho e para o seu estágio, e decidir juntos.
A terapia da mão depois da cirurgia é feita com Ruby Doolan, da Extend Rehabilitation. Ruby é terapeuta da mão: ela conduz a sua reabilitação e confecciona qualquer tala de que você precise.
Consulte o seu médico de família ou solicite uma avaliação por um especialista se a dor não estiver melhorando, estiver piorando ao longo de semanas, acordar você à noite ou impedir você de trabalhar ou de usar a mão. Se não conseguir entrar em contato com a clínica fora do horário de atendimento ou no fim de semana, vá ao pronto-socorro mais próximo.
O que esperar
A doença de Kienböck geralmente evolui devagar, mas tende a evoluir. Se não for tratada, o semilunar pode continuar se desfazendo, e a condição pode terminar em artrose em todo o punho. Ela também pode evoluir mais rápido do que os médicos acreditavam, e a superfície lisa do semilunar pode se desgastar logo no início. Dito isso, nem todo punho segue o mesmo caminho. Algumas pessoas têm a doença sem sentir nenhuma dor, e as alterações na radiografia nem sempre correspondem ao que o punho sente. Um punho pode parecer pior no exame de imagem enquanto se sente melhor, e é por isso que os seus sintomas e o que a sua mão consegue fazer importam mais do que as imagens.
Com tratamento, o prognóstico é mais estável. Os estágios iniciais muitas vezes melhoram com repouso, uma tala ou gesso e mudanças na forma como você usa o punho. Crianças e adolescentes respondem bem ao tratamento não cirúrgico. Quando a cirurgia é necessária, o objetivo é honesto: as operações são oferecidas para reduzir a dor e manter o punho em movimento, e não para prometer que o semilunar será salvo. A osteotomia de encurtamento radial traz melhora ao longo de uma década em 75% dos pacientes, e o seu efeito se mantém por mais de 10 anos. O enxerto ósseo vascularizado e a descompressão do núcleo ósseo também mostram resultados que duram muito tempo. Nos punhos em que o semilunar já colapsou ou em que a artrose se instalou, remover a fileira de ossos danificados ou fazer a artrodese do punho ainda pode resultar em um punho funcional, embora a força de preensão e o conforto variem de pessoa para pessoa.
Se não for tratada, a evolução provável é uma piora gradual: mais rigidez, uma preensão mais fraca e dor que piora quando se coloca carga sobre o punho. Alguns punhos permanecem com sintomas leves por anos. Outros, não. Como a evolução é difícil de prever, vale a pena acompanhar esta condição em vez de ignorá-la, mesmo quando a dor é tolerável.
Não há sinais de emergência específicos da doença de Kienböck em si, mas se a sua mão ficar quente, vermelha, inchada e dolorida, especialmente com febre, vá ao pronto-socorro mais próximo no mesmo dia. Consulte o seu médico de família ou solicite uma avaliação por um especialista se a dor não estiver melhorando, estiver piorando ao longo de semanas, acordar você à noite ou impedir você de trabalhar ou de usar a mão.
Quando procurar ajuda médica
Consulte o seu médico de família ou solicite uma avaliação por um especialista se você tiver dor no meio da parte de trás do punho que não esteja melhorando, esteja piorando ao longo de semanas, acorde você à noite ou impeça você de trabalhar ou de usar a mão. O mesmo vale se a parte de trás do punho estiver inchada, se a sua força de preensão parecer menor do que o normal ou se o punho estiver rígido e difícil de mover. Esses sinais são importantes porque a condição tende a progredir, e uma avaliação mais cedo mantém mais opções em aberto. Solicite também uma avaliação por um especialista se você tiver mais de 60 anos e sentir uma dor no punho vaga ou fácil de passar despercebida, já que o diagnóstico muitas vezes não é feito em mulheres mais velhas. Não há sinais de emergência específicos da doença de Kienböck em si, mas se a sua mão ficar quente, vermelha, inchada e dolorida, especialmente com febre, vá ao pronto-socorro mais próximo no mesmo dia. Se não conseguir entrar em contato com a clínica fora do horário de atendimento ou no fim de semana, vá ao pronto-socorro mais próximo.
Em maior profundidade
Advanced reading: the deeper science (optional)
Esta seção vai além do que você precisa saber para tomar decisões sobre o próprio tratamento. A doença de Kienböck merece essa leitura adicional devido a uma constatação desconfortável presente na literatura sobre o tema: as cirurgias realizadas para tratá-la aliviam os sintomas, mas não alteram claramente o impacto da doença no osso.
A cirurgia alivia a dor; porém, não foi comprovado que altera a evolução da doença
A comparação mais direta disponível analisou pacientes a longo prazo após osteotomia radial, em comparação com aqueles tratados de forma não cirúrgica. A osteotomia radial não se mostrou superior ao tratamento não cirúrgico no que diz respeito à progressão da doença, conforme avaliado pelo estágio de Lichtman; contudo, gerou melhores resultados no que tange à dor e à amplitude de movimento do punho [1].
Essas são duas afirmações distintas, e devem ser interpretadas como tais. A cirurgia melhora a sensação de conforto no punho e a sua mobilidade. Porém, não foi demonstrado que ela impeça o colapso do semilunar. Uma comparação de longo prazo posterior, entre tratamento não cirúrgico e enxerto ósseo vascularizado, chegou a uma conclusão semelhante [2].
Esse é o ponto mais importante a ser compreendido antes de concordar com a cirurgia. Se a operação for oferecida como forma de salvar o semilunar, essa abordagem vai além das evidências científicas. Se, por outro lado, for oferecida para reduzir a dor e preservar a mobilidade de um punho que já está dolorido, então há respaldo científico para tal.
Por que as radiografias e os sintomas não coincidem
A doença de Kienböck é definida radiologicamente; os estágios de Lichtman descrevem a esclerose, seguida do colapso e da desintegração do carpo. É natural supor que as imagens radiográficas reflitam a intensidade da dor. Contudo, isso muitas vezes não acontece. Em alguns casos, o carpo apresenta piora nos exames radiográficos enquanto o paciente sente melhora; em outros, a dor persiste mesmo nos estágios iniciais da doença.
Essa discrepância explica por que o fato de “a radiografia parecer pior” não constitui, por si só, motivo para cirurgia, e por que o acompanhamento radiográfico contínuo é um critério pouco confiável para a tomada de decisão. A decisão deve basear-se nos sintomas e na função do membro superior.
Existem inúmeras operações, o que em si já é informativo
Encurtamento do rádio, encurtamento do capitato, enxerto ósseo vascularizado, descompressão do núcleo ósseo, fusões parciais, carpectomia da fileira proximal – o número de procedimentos descritos é grande. Uma revisão sistemática sobre a osteotomia de encurtamento do capitato é uma das adições mais recentes [3].
Em cirurgia, uma longa lista de procedimentos concorrentes para uma mesma condição geralmente indica que nenhum deles é decisivamente superior. Essa é a interpretação correta aqui, e explica por que dois cirurgiões qualificados podem propor procedimentos diferentes para o mesmo punho, sem que nenhum esteja errado.
A lógica unificadora por trás da maioria desses procedimentos é mecânica: reduzir a carga que incide sobre o semilunar, seja encurtando o rádio para que a ulna suporte mais carga, seja encurtando o capitato para que menos força seja transmitida ao semilunar. São tentativas de aliviar a carga sobre um osso cujo suprimento sanguíneo está falhando; não visam restaurar esse suprimento sanguíneo, com exceção parcial do enxerto vascularizado, que procura atingir ambos os objetivos.
O que isso significa para você
Três consequências práticas. A conduta de observação vigilante é uma opção válida, e não um fracasso em agir, especialmente quando a dor é tolerável. O objetivo de qualquer cirurgia deve ser definido em termos de sintomas, e não de estágio da doença. E, como nenhum procedimento se destacou dos demais, saber por que esta cirurgia é adequada para seu punho, para sua variação ulnar, para o seu estágio clínico e para suas necessidades — isso é ainda mais importante aqui do que na maioria das cirurgias da mão.
Referências
[1] Shin YH, Kim JK, Han M, Lee TK, Yoon JO. Comparação dos resultados a longo prazo da osteotomia radial e do tratamento não cirúrgico na doença de Kienböck: uma revisão sistemática. J Bone Joint Surg Am. 2018;100(14):1231-40. https://doi.org/10.2106/JBJS.17.00764
[2] Park JY, Kim JK, Shin YH. Comparação dos resultados a longo prazo entre o tratamento não cirúrgico e o enxerto ósseo vascularizado na doença de Kienböck. Clin Orthop Surg. 2023;15(4):643. https://doi.org/10.4055/cios22307
[3] Simske N, Pourghaed M, Johnson C, Clark DM. Osteotomia de encurtamento do capitato para a doença de Kienböck: uma revisão sistemática. Hand (N Y). 2026. https://doi.org/10.1177/15589447261441826
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
General Management Principles
- Surgical indications for Kienböck's disease should be carefully considered, keeping in mind their side-effects and the relative benignity in some cases of the natural course of the disease [47].
- Children, adolescents, and elderly patients with Kienböck disease respond well to nonoperative treatments, and this should be considered before any surgical intervention [20].
- A prospective investigation is needed to delineate the appropriate management and expected outcomes of pediatric and adolescent Kienbock disease [3].
Skeletally Immature Patients
- Good and excellent clinical and radiological outcomes can be achieved with both nonsurgical and surgical treatments in skeletally immature patients with Kienböck disease [10].
- Radial osteotomies are effective in improving not only short-term clinical outcomes, but also radiographic findings in teenage patients with Kienböck disease [4].
- Temporary scaphotrapezoidal joint fixation is recommended for the surgical treatment of adolescent Kienböck's disease [14].
Radial Osteotomy
- Radial osteotomy for Kienböck’s disease is a reasonable treatment option and clinical improvement lasts for a long period of time [49].
- Radial osteotomies are reliable surgical methods for Kienböck disease in that the effect is maintained for more than 10 years [54].
- A long-term follow-up period is essential in evaluating radial osteotomy in the treatment of Kienböck's disease [9].
- Radial shortening osteotomy provides decade-long improvement in 75% of patients and seems to be a reasonable treatment for symptomatic Kienböck’s disease [23].
- Radial shortening osteotomy for symptomatic Kienböck's disease yields reasonable long-term function, though approximately one in eight patients underwent salvage surgery [15].
- Radial shortening osteotomy should not be contraindicated in advanced Kienbock's disease (without radiocarpal osteoarthritis) as it achieves long-lasting good clinical results with very few complications [28].
- Radial shortening osteotomy offers at least comparable outcomes with proximal row carpectomy in treating Kienböck's disease, particularly in preserving joint function and patient satisfaction [44].
Scaphocapitate Arthrodesis
- Scaphocapitate arthrodesis is an effective procedure for treatment of Kienböck disease associated with satisfactory functional outcomes and significant improvement in pain scores and grip strength [19].
- The long-term clinical benefits of scaphocapitate arthrodesis for treatment of collapsed Kienböck disease are demonstrated [12].
- Functional outcomes in medium-term follow-up are discouraging after scaphocapitate arthrodesis for advanced stages of Kienböck disease [2].
Vascularized Bone Grafting
- Vascularized bone grafting for stage III Kienböck disease demonstrated favorable long-term results and is recommended as a surgical treatment [22].
- The treatment of Kienböck disease with vascularized bone graft from the dorsum of the radius has encouraging results and needs no other additional procedures [58].
Other Surgical Interventions
- Tendon ball arthroplasty in advanced Kienböck's disease results in long-term satisfactory clinical outcomes, despite widespread changes in the bones and joints within the wrist [16].
- Patients with Kienböck's disease treated with lunate excision and followed up for more than 5 years have generally shown satisfactory results that are considered definitive [17].
- Distal radius metaphyseal core decompression demonstrated favorable long-term results and is recommended as a surgical alternative for stage IIIa of the Kienböck disease [24].
- Capitate shortening is a safe and effective approach for treatment of the early stages of Kienböck's disease and can be associated with a satisfying outcome [40].
Publication Bias
- The acceptance rate for negative outcomes studies regarding Kienböck's disease is higher than for other surgical disorders, indicating a relative decrease in positive outcome bias among published Kienböck's disease studies compared with other surgical disorders [34].
Anatomy & Pathophysiology
Bony Anatomy
- The wrist includes the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones and their proximal and distal articulations and attached ligaments [83].
- The eight carpal bones include the scaphoid, lunate, triquetrum, and pisiform in the proximal row and the trapezium, trapezoid, capitate, and hamate in the distal row [83].
- The radiocarpal joints are formed by the articulation of the distal radius with the scaphoid and lunate through their respective concave facets on the distal radius and the triquetrum on the triangular fibrocartilage [83].
- The distal concave articular surfaces of the proximal carpal row form the midcarpal articulations with the distal row [83].
- The distal radius articular surface has two concave facets, the scaphoid and lunate facets, separated by the scapholunate, or anterior-posterior, ridge [96].
- The sigmoid notch, along the ulnar border of the distal radius, is a shallow concavity for the articulating ulnar head at the distal radioulnar joint [96].
- The lunate is broader palmarly than dorsally [96].
- The capitate head (the proximal portion) often relies on a retrograde vascular supply [96].
- The distal radius has three articular components: distally the scaphoid and lunate fossae, and the sigmoid notch which allows articulation with the ulna medially [88].
- The concave elliptical distal radius is oriented in the sagittal plane with an average of 11 degrees of volar tilt [88].
- In the frontal plane, the average radial inclination of the distal radius is 23 degrees [88].
- Radial length is measured from the tip of the radial styloid to the ulnar articular surface and averages 13 mm [88].
Ligaments
- Extrinsic carpal ligaments connect the radius or the ulna to the carpus [89].
- In general, the volar ligaments are stronger than the dorsal ligaments [89].
- The radioscaphocapitate (RSC) ligament connects to the waist of the scaphoid, around which the scaphoid rotates, and limits ulnar translation of the carpus [89].
- The long radiolunate ligament helps to limit ulnar translocation of the carpus [89].
- The short radiolunate ligament helps control lunate position [89].
- The radioscapholunate ligament is a vascular conduit, not a true ligament, and is also known as the ligament of Testut [89].
- The ulnolunate ligament attaches to the palmar radioulnar ligament and lunate [89].
- The ulnocapitate ligament attaches to the ulnar head and is the most superficial or palmar of the palmar ulnocarpal ligaments [89].
- The ulnotriquetral ligament attaches to the palmar radioulnar ligament and triquetrum [89].
- The dorsal radiocarpal ligament has a trapezoidal shape and passes from the dorsal rim of the distal radius to the lunate and the triquetrum [89].
- The scapholunate interosseous ligament (SLIL) is the major stabilizer of the wrist and the most commonly injured wrist ligament [89].
- The SLIL is C-shaped, consisting of dorsal, palmar, and interosseous portions, with the dorsal portion being the strongest and thickest [89].
- The SLIL provides a flexion force on the lunate given its attachment to the scaphoid [89].
- The lunotriquetral interosseous ligament (LTIL) is C-shaped, where the volar portion is the thickest and strongest [89].
- The LTIL provides an extension moment on the lunate given its attachment to the triquetrum [89].
- The capitohamate ligament is a thick ligament, 5 × 5 mm in cross section, with extensions to the third or fourth metacarpals [89].
- The dorsal intercarpal ligament (DIC) passes from the dorsal tubercle of the triquetrum to the distal pole of the scaphoid [89].
- The DIC ligament reinforces the elastic dorsal wrist capsule and helps stabilize the scapholunate articulation with a contribution to the dorsal SLIL from its deep fibers [89].
- The space of Poirier is an area adjacent to the proximal capitate without ligamentous attachment, situated ulnar to the RSC ligament and radial to the long radiolunate in the floor of the carpal tunnel [89].
- The space of Poirier is a weak area that is vulnerable to instability; the distal carpal row separates from the lunate through this space during a perilunate dislocation [89].
- The triangular fibrocartilage complex (TFCC) is formed by the central meniscus homolog, the dorsal and volar radioulnar ligaments, the floor of the extensor carpi ulnaris (ECU) tendon sheath, and the volar ulnocarpal ligaments [96].
- The TFCC arises from the radial border of the distal radius and inserts into the base of the ulnar styloid and distal ulna through the ligamentum subcruentum [96].
- The dorsal and volar radioulnar ligaments are the primary stabilizers of the distal radioulnar joint [96].
- Only the peripheral 10% to 40% of the volar, ulnar, and dorsal TFCC has a vascular supply [96].
Vascular Anatomy
- The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches with longitudinal connections [102].
- The dorsal radiocarpal arch is located at the radiocarpal joint and supplies the lunate and triquetrum [102].
- The dorsal intercarpal arch is the largest of the dorsal arches, located between the proximal and distal carpal rows, supplying the distal carpal row and, through anastomoses with the radiocarpal arch, the lunate and triquetrum [102].
- The basal metacarpal arch is located at the base of the metacarpals, is the most variable of the dorsal arches, and supplies the distal carpal row [102].
- The palmar radiocarpal arch is located at the level of the radiocarpal joint on the palmar surfaces of the lunate and triquetrum [102].
- The palmar intercarpal arch is located between the proximal and distal carpal rows, is the most variable of the palmar arches, and does not contribute to nutrient vessels in the carpus [102].
- The deep palmar arch is located at the level of the metacarpal bases, is consistent, and communicates with the dorsal basal metacarpal arch and the palmar metacarpal arteries [102].
- A dorsal and a palmar vascular supply are found in 80% of wrists; in 20% of wrists, only a palmar supply is found for the lunate [96].
- The extraosseous vascularity of the lunate is profuse through two to three dorsal and three to four volar vessels feeding dorsal and volar capsular plexuses [159].
- One to two nutrient vessels enter the dorsal and volar poles of the lunate from both plexuses [159].
- The intraosseous vascularity of the lunate forms one of three consistent patterns with anastomoses of dorsal and volar vessels in each specimen [159].
Biomechanics & Kinematics
- The wrist joint’s motion planes include flexion, extension, radial deviation, ulnar deviation, and circumduction; there is minimal carpal motion with pronosupination [89].
- Approximately 62° of wrist extension occurs through the radiocarpal joint and 62% of wrist flexion occurs through the midcarpal joint [89].
- The midcarpal joint is mostly responsible for 20° and 40° of radial and ulnar deviation, respectively [89].
- The midcarpal joint is responsible for the “dart thrower’s motion” which involves moving from radial extension into ulnar flexion positioning of the wrist [89].
- The radius bears 80% of the axial load transmitted through the radiocarpal joint, while the ulna bears 20% in neutral ulnar variance [89].
- The proximal row of carpal bones form an intercalated segment between the distal carpal row and the distal radius and are bound into a functional unit by the SLIL and LTIL [89].
- The distal row is rigid, with little motion between its bones due to stout intercarpal ligaments, and thus they act as a functional unit with the scaphoid bridging both rows [89].
- During wrist flexion from neutral, the distal row flexes and ulnarly deviates slightly while the scaphoid also pronates [89].
- During wrist flexion from neutral, the proximal row flexes differentially, with more rotation through the scaphoid, followed by the triquetrum and the lunate [89].
- During wrist flexion from neutral, the proximal row translates dorsally [89].
- During wrist extension from neutral, the distal row extends and radially deviates slightly while the scaphoid also supinates [89].
- During wrist extension from neutral, the proximal row extends differentially, with more motion in the scaphoid, followed by the triquetrum and then the lunate [89].
- During wrist extension from neutral, the proximal row translates palmarly [89].
- The proximal carpal row has no muscular or tendinous attachments and is an intercalary segment [96].
- With ulnar deviation, the proximal row extends relative to the forearm/distal row [96].
- With radial deviation, the proximal row flexes relative to the forearm/distal row [96].
- With axial loading through the neutral wrist, approximately 80% of forces are transmitted through the distal radius (60% scaphoid facet, 40% lunate facet) and 20% through the distal ulna [96].
- With wrist flexion, 60% of the motion is midcarpal and 40% is radiocarpal [96].
- With wrist extension, 33% of the motion is midcarpal and 66% is radiocarpal [96].
- The lunate, capitate, hamate, trapezium, and trapezoid function collectively as the “stable central column,” controlled by the scaphoid in a two-gear, four-bar linkage system and stabilized by the triquetrum, which buffers lunate rotation and prevents ulnar translation [97].
- The dart-thrower’s path of radial extension to ulnar flexion defines the transition between flexion and extension of the scaphoid and lunate, and a path of motion during which the proximal row motion approaches zero [97].
- The dart-thrower’s motion occurs almost exclusively through the midcarpal joint, and rotation occurs along the mechanical axis of the wrist [97].
- A wrist joint should be considered biomechanically unstable when it is not able to bear loads and does not exhibit normal kinematics throughout its arc of motion [78].
Pathophysiology
- Kienböck disease is an isolated disorder of the carpal lunate associated with characteristic, and often progressive, clinical and radiographic changes [7].
- Biologic, not just traumatic, processes may explain the onset and progression through the disease continuum [7].
- There has been renewed interest in understanding the vascular and cartilaginous manifestations of the disorder [7].
- Infantile, juvenile, and geriatric forms of Kienböck disease have been described [7].
- It has been suggested that the disease pathway in infantile, juvenile, and geriatric individuals may differ from the typical adult patient population [7].
- Kienböck's disease may not always develop acutely after a single injury but may have a more gradual onset [11].
- Mechanical factors, acute trauma and repeated microtrauma no longer seem to be primary factors that cause the disease, but instead are factors that make symptoms of pre-existing Kienböck’s disease worse [21].
- The disease seems to correspond more to a biological phenomenon, probably vascular and non-traumatic, with a proximal subchondral infarction [21].
- Following proximal subchondral infarction, there is attempted repair through creeping substitution, where there is more osteoclastic resorption activity than osteoblastic repair activity [21].
- Genetic, viral and metabolic theories must still be developed, as they could provide avenues for genetic or molecular treatment in the initial stages of the disease [21].
- Some patients are predisposed to Kienböck disease, and the evolution of the disease may be influenced by the patient’s demographic [36].
- Both biomechanical and biological factors play a significant role in Kienböck disease [36].
- The morphology of the wrist and lunate influence loading mechanics through the central column [36].
- Both arterial and venous factors are important in the development of ischemia and the onset of a compartment syndrome of bone [36].
- Stability of the wrist plays a role in Kienböck disease [36].
- The disease affects the ligaments within and between the carpus and radius through synovitis or avulsion [36].
- Disruption of ligaments can lead to collapse of the lunate and carpus [36].
- Kienböck disease usually affects men aged 18 to 40 years old in their dominant hand [45].
- Documented cases of Kienböck’s disease presenting in the elderly are rare in the medical literature [45].
- Kienböck’s disease may have a silent presentation in the population older than 60 years, such that the wrist pain of Kienböck’s disease is masked [45].
- The etiology and pathophysiology of Kienböck’s disease may differ between men and women [45].
- Kienböck’s disease in the elderly predominantly affects women [45].
- Three of the 4 reported cases in patients over the age of 65 are women, with the oldest being 75 years old [45].
- Osteoporosis, seen commonly in elderly women, may be a contributing factor to the development of Kienböck’s disease whereas repetitive microtrauma may account for the majority of cases in the younger male population [45].
- Kienböck disease, or osteonecrosis of the lunate, is a progressive disease process that can lead to wrist pain and dysfunction [75].
- Anatomic, mechanical, vascular, and traumatic factors have been suggested to contribute to Kienböck disease [75].
- The natural history of Kienböck disease is unknown, and radiographic and clinical findings do not always correlate [75].
- Kienböck disease typically presents in male patients in the age group of 20 to 40 years [125].
- There is thought to be an “at-risk” patient who is predisposed due to anatomic factors [125].
- Kienböck's disease is an eponym for idiopathic avascular osteonecrosis of the lunate [114].
- It usually has an insidious onset without a history of injury; however, diagnosis is sometimes made after a simple fall that fractures the necrotic bone [114].
- Osteonecrosis may be the result of interruption of the vascular supply to the lunate, which shows no radiographic evidence of injury until sclerosis and osteochondral collapse [114].
- The condition is more common in patients with an ulnar minus variant [114].
- Some believe that unrecognized and untreated fractures of the lunate lead to Kienböck's disease, predominantly due to the cadaveric work of Verdan who applied strong forces to cadaver bones and observed that the resulting fractures were not visible on standard radiographs but only on histology [114].
- Others have questioned these findings, with one study suggesting that early venous congestion, not fracture, of the lunate was responsible for the pathogenesis of Kienböck's disease [114].
- The lunate necrosis after perilunate dislocation is probably due to impairment of the arterial vasculature [114].
- Fragmentation of the lunate results not only in loss of the mechanical strength of the central column but also in proximal migration of the capitate, which slackens the RSC and SC ligaments and leads to kinematic disruption of the carpus [101].
- In such circumstances, the loaded scaphoid is apt to follow its natural tendency and progressively collapse into flexion, another example of adaptive carpal instability [101].
- Rarely does Kienböck disease demonstrate SL gap, DISI, or dorsal translation of the scaphoid, the pathognomonic findings of dissociative instability [101].
- One of the prognostic factors of Kienböck disease is the absence (stage 3A) or presence (stage 3B) of abnormal flexion and pronation deformity of the scaphoid [101].
- In stage 3A, the carpus remains relatively stable, whereas in stage 3B, it has collapsed [101].
- Kienböck disease (idiopathic osteone
Classification
Osseous Staging (Lichtman)
- The Lichtman classification system for Kienböck’s disease has substantial agreement in terms of interobserver reliability and intraobserver reproducibility [81].
- The Lichtman et al. classification for Kienböck's disease has good reliability and reproducibility [79].
- The interobserver reliability of the traditional Lichtman classification was substantial with a coefficient of 0.63 [129].
- Stage 3A of the traditional Lichtman classification was less reliably identified with a coefficient of 0.38 [129].
- A modification of the Lichtman classification using a radioscaphoid angle of 60° to subdivide stage 3 increased overall interobserver reliability to a coefficient of 0.81 [129].
- The same modification increased the interobserver reliability for stage 3A to a coefficient of 0.75 [129].
- Stage IIIA is defined by lunate fragmentation without changes in carpal alignment [66].
- Stage IIIB is defined by lunate fragmentation associated with fixed anterior flexion of the scaphoid, proximal migration of the capitate, and loss of carpal height [66].
- Lunate collapse and the appearance of radiocarpal or midcarpal degenerative arthritis occur in Stage IV [66].
- The surgical treatment decision from stage III and IV is determined by the bony morphology of the lunate [71].
- Assessment of the internal osseous structure and integrity of the lunate is often not possible by conventional radiography owing to superimposition of other information in the image [71].
- High-resolution computed tomography has been shown to be more accurate in the assessment of the osseous microstructure of the lunate in Kienböck disease than conventional radiography [71].
- The diagnosis of Kienböck disease in the precollapse stages is not well defined, as evidenced by substantial interobserver variability [53].
- Traditional radiographic indices measured on plain radiographs have poor diagnostic performance in the detection of carpal collapse in Kienböck's disease [29].
- The classification of Kienböck’s disease in stages IIIA (without carpal collapse) or IIIB (with carpal collapse) is done by comparing to the contralateral wrist [80].
Vascular Staging
- A separate vascular classification for Kienböck disease was developed by Schmitt et al. [71].
Articular Cartilage Staging
- A separate cartilage classification for Kienböck disease was developed by Bain and Begg [71].
- Arthroscopy provides a valuable assessment and subsequent classification of Kienböck’s disease based on the number of non-functional articular surfaces [86].
- Arthroscopy in Kienböck disease allows precise evaluation of pathology severity and associated chondral lesions, refining classification to provide the most appropriate treatment [42].
- The Bain and Begg arthroscopic classification and an articular-based approach to Kienböck disease provide a high probability of good long-term relief of pain and a minimal chance of requiring a salvage procedure [126].
- Contrary to current classifications, the articular cartilage of the lunate degenerates in early stages [8].
Unified Classifications
- A unified classification and treatment algorithm has been proposed that coordinates osseous, vascular, and articular data alongside patient age to allow for more precise and individualized treatment plans [26].
- Lichtman et al. recently developed a unified classification and treatment algorithm combining the three existing classifications (osseous, vascular, and cartilage) [71].
- A new treatment algorithm has been presented that integrates traditional osseous classification with perfusion/viability and articular cartilage-based classifications [41].
Clinical Presentation
- Kienböck disease is suspected clinically in the presence of central dorsal pain at the wrist over the lunate [113].
- The condition often appears spontaneously, although more or less intense or repeated injury events may be present [113].
- Patients frequently exhibit limited mobility and grip strength [113].
- Clinical examination can suggest the presence of Kienböck disease but cannot confirm it [113].
- Dorsal wrist swelling is a common manifestation and constitutes part of the pathology of Kienböck disease [94].
- Kienböck disease is uncommon in the elderly and usually appears in patients between the age of 30 and 40 [92].
- In elderly patients, Kienböck disease commonly occurred in the dominant hand of manual workers [93].
- Kienböck disease in the elderly predominantly affects women [45].
- The disease may have a silent presentation in the population older than 60 years, such that wrist pain is masked [45].
- A delay in diagnosis may be common in older female populations because the diagnosis is not typically considered [45].
- The natural history of Kienböck disease is generally considered a progressive condition that can end in Stage IV changes [5].
- Kienböck disease progresses substantially faster than previously described [8].
- Kienböck disease has a naturally benign course, and remaining symptoms at follow-up might be caused by osteoarthrosis [6].
- Lunate morphology may affect the severity of Kienböck disease at the time of initial presentation [27].
- Patients with Kienböck disease should have their other wrist examined and radiographed for early diagnosis and treatment of the disease [18].
- Patients with symptoms suggestive of advanced Kienböck disease should undergo imaging of the wrist joints to ascertain concomitant Kienböck’s disease [25].
Investigations
Imaging Modalities and Diagnostic Performance
- MRI is useful in detecting additional marrow abnormalities in osteonecrosis, as seen in the lunate in Kienböck disease [118].
- A properly performed, high-resolution MRI aids in the evaluation of ligament injuries of the wrist [110].
- A static magnetic field strength of at least 1.5 T using a dedicated wrist coil is recommended for analyzing the interosseous, intrinsic, and extrinsic ligament insertions [110].
- Higher magnetic field strengths result in a higher signal-to-noise ratio with shorter scan times [110].
- The volar extrinsic, SL interosseous, dorsal intercarpal, and LT ligaments are best visualized using 1 mm slices (with no interslice gap) in the coronal plane [110].
- The DRC and intercarpal ligaments are best viewed on both the coronal and sagittal images [110].
- Oblique axial views along the longitudinal axes of these ligaments allow further analysis, especially when an injury is suspected [110].
- Concomitant cartilage-sensitive imaging is integrative to influence the assessment/surgical management, as the cartilage integrity will influence the clinical/surgical management [110].
- Real-time MRI has been used to investigate dynamic instabilities, although its routine use in clinical practice is yet to be further determined [110].
- CT scanning enables the 3D analysis of carpal dysfunction [110].
- By adding motion in real time (4D CT), this may hold promise in the future to potentially quantify the location and degree of injury noninvasively and help surgeons plan their surgical treatment [110].
- Dynamic fluoroscopy not only shows abnormal motion between the scaphoid and lunate but also changes in the kinematics of the midcarpal joint [110].
- Live imaging shows whether the DISI is reducible, giving the physician valuable information as the treatment is planned [110].
- Arthroscopy is considered by many to be the diagnostic intervention of choice for determining the degree of injury to the wrist and can assess the condition of the cartilage (normal or degenerative), ability to reduce the carpus and any other associated injuries [110].
- The degree of intrinsic and extrinsic ligament injury can be identified from the arthroscopic evaluation [110].
- MRI has an expanding role in the evaluation of pathologic conditions of the elbow and wrist [118].
- Successful study of both articulations requires high-resolution images that are best obtained with surface coil technique and high field system [118].
- Often these joints are examined in the extremity coil, requiring extension of the arm overhead within the center of the magnet field [118].
- This position is difficult to maintain in elderly patients [118].
- The larger-diameter bore current generation of high-field scanners can allow for off-axis imaging with the arm at the side [118].
- Dedicated wrist coils, when available, or coupled surface coils also are designed for imaging of this articulation at the patient’s side [118].
- The MRI examination should be directed at solving a specific clinical problem or question [118].
- In the wrist, a common indication for MRI is evaluation of the intrinsic carpal ligaments [118].
- With proper technique, injuries to the triangular fibrocartilage complex (TFCC) can be demonstrated with MRI [118].
- The TFCC is composed of signal-poor fibrocartilage, and perforations in the TFCC appear as linear defects or gaps filled with hyperintense fluid on coronal gradient-echo or T2-weighted pulse sequences [118].
- Although evaluation of the scapholunate and lunotriquetral ligaments is more challenging, with optimal technique and equipment the integrity of these structures can be consistently assessed [118].
- The addition of arthrographic contrast improves the visualization of these ligaments on MR images [118].
- The extrinsic carpal ligaments can be identified with three-dimensional volumetric scanning and subsequent reconstruction [118].
- At present, the MRI assessment of these ligaments has less impact on treatment [118].
- MRI has gained a greater role in the evaluation of acute wrist trauma [118].
- Not infrequently, bone marrow edema may reveal fractures of the carpal bones or distal radius that are radiographically occult [118].
- Asymmetry of marrow signal in proximal and distal fragments of a fractured scaphoid is suggestive of proximal pole ischemia [118].
- MRI currently has a limited role in the evaluation of carpal tunnel syndrome [118].
- Although this remains a clinical diagnosis, axial imaging with T2 weighting can clearly display masses within the confines of the carpal tunnel, as well as edema and swelling of the median nerve [118].
- As in the ankle, tenosynovitis and tendon injuries in the wrist and hand can be assessed [118].
- Additionally, MRI has an expanding role in the evaluation of inflammatory arthritis [118].
- Numerous studies have shown that MRI provides earlier detection of synovitis and erosive bone changes associated with rheumatoid arthritis than do radiographs [118].
- The use of MRI for hand and wrist imaging was first reported in 1986 and since that time has been an important diagnostic tool with significant impact on patient care [91].
- The primary advantages of MRI compared with CT and radiography are the improved tissue characterization, especially of soft tissues such as the ligamentous structures in the wrist and synovium in the hand, and the lack of ionizing radiation due to its use of radiofrequency waves to generate images [91].
- It is the modality of choice for imaging radiographically occult fractures of the hand and wrist [91].
- Early MRI was limited by its low magnetic field strength (0.15 T) and limited image options and image processing [91].
- Field strength is critical, as this is directly related to signal to noise ratio (SNR); high SNR allows better visualization of small structures at higher resolution, but processing capacity and speed is increasingly important [91].
- Modern MRI is generally at 1.5T or 3T with a wide variety of imaging options and powerful image processing and postprocessing available [91].
- 3T is much preferred for hand and wrist imaging, especially for imaging small fields of view [91].
- Dedicated extremity magnets have been marketed, but image quality is poor compared with conventional MR imaging [91].
- 7T MRI has recently become approved for clinical use [91].
- At more than double the magnetic field strength of 3T MRI, 7T has the potential to become a powerful tool for hand and wrist imaging as applications are developed [91].
- While more imaging of the wrist is performed without contrast, MRI with contrast enhancement is most commonly used to determine whether soft-tissue lesions are solid or cystic or, in the case of rheumatologic imaging, to better visualize erosions and synovial burden [91].
- Dynamic contrast enhancement has been used with inconsistent results to assess for the presence of avascular necrosis in the lunate or scaphoid after injury [91].
- MR angiography of the hand and wrist can be helpful in situations such as diagnosis of the hypothenar hammer syndrome [91].
- MR arthrography can be performed for evaluation of the triangular fibrocartilage and intercarpal ligament tears, but this is generally unnecessary with the increasing availability of high field MRI [91].
- Assessment of the internal osseous structure and integrity of the lunate is often not possible by conventional radiography (CR) owing to superimposition of other information in the image [71].
- High-resolution computed tomography (CT) has been shown to be more accurate in the assessment of the osseous microstructure of the lunate in KD [71].
- Computed tomography of the lunate in Kienböck disease is an important investigative tool [123].
- In this study, the six patients with the diagnosis of Kienböck's disease demonstrated a correlation between the loss of signal intensity on T1 and T2-weighted MRI images and evidence of osteonecrosis by histology [105].
- Proton density–weighted MRIs but not fast-field echo images using a 47-mm microscopy coil reflected the extent and localization of the necrotic area in Kienböck-diseased lunates, as evidenced by comparison with histological analyses of the lunate specimens [133].
- MRI showed complete loss of signal intensity in T1 images of the lesion of the lunate in advanced Stage 3 Kienböck's disease, but is at present unable to distinguish bone necrosis, the histological reactive interface or surrounding hyperaemia in detail [149].
- The author expresses concerns regarding the methodology and MRI findings used to define lunate revascularization in Kienböck's disease [145].
Clinical and Diagnostic Considerations
- Kienböck disease, osteonecrosis of the lunate, is a well-known but poorly understood complication seen by hand surgeons [1].
- This review presents the background and important patient-specific parameters of the disease and reviews the numerous treatment options that exist for the disease [1].
- The exact mechanism(s) of Kienböck disease has not been [1].
- Kienböck's disease is generally considered to be a posttraumatic condition of multifactorial origin [11].
- Among the factors to be considered in its etiology are ulnar variance, initial lunate vascularity, mechanism of injury, patient age, and lunate geometry [11].
- There is a known association of lunate fracture with Kienböck's disease [11].
- The question frequently arises as to whether the fracture is secondary to a preexisting osteonecrosis or whether the fracture is itself a cause of osteonecrosis [11].
- Peste, who originally described the condition in 1843, believed that the initial event was a fracture [11].
- Kienböck, in 1912, favored an initial vascular insult, with subsequent osteonecrosis and secondary fracture propagation [11].
- There has also been some question as to whether the osteonecrosis that develops is the immediate result of a single discrete episode or whether it develops gradually as the result of the accumulated effects of several traumatic episodes, posttraumatic synovitis, or other factors [11].
- Despite numerous proponents of the various theories, adequate documentation of the pathogenesis is lacking [11].
- This is due, in part, to delay in definitive diagnosis, often months or years after the onset of symptoms [11].
- We describe a patient in whom, despite normal initial radiographs, tomograms, bone scan, and magnetic resonance imaging, Kienböck's disease developed without the patient suffering an intercurrent injury [11].
- This case suggests that Kienböck's disease may not always develop acutely after a single injury but may have a more gradual onset [11].
- The natural history of Kienbock's disease is not fully known, though it is generally considered a progressive condition that can end in Stage IV changes [5].
- Treatment strategies focus on biomechanical unloading, vascularized bone grafts, or salvage procedures depending on the stage [5].
- Kienböck's disease has a naturally benign course, and the remaining symptoms at follow-up might be caused by osteoarthrosis [6].
- Kienböck's disease progresses substantially faster than previously described and, contrary to current classifications, the articular cartilage of the lunate degenerates in early stages [8].
- The current results indicate that radial osteotomies are effective in improving not only short-term clinical outcomes, but also radiographic findings in teenage patients with Kienböck disease [4].
- This case supports recommendations that patients younger than 15 years with Kienböck’s disease initially should be treated nonsurgically with immobilization for 6 weeks at least, followed by careful follow-up with repeated standard radiographs, CTs, and MRI [68].
- It is suggested that any patient diagnosed as suffering from Kienböck's disease should also have his other wrist examined and radiographed for early diagnosis and treatment of the disease [18].
- Patients with these symptoms should undergo imaging of the wrist joints to ascertain concomitant Kienböck’s disease [25].
- The authors believe the most likely diagnosis is primary Kienböck’s disease leading to secondary synovitis and tertiary autofusion, though an unusual presentation of a monoarticular nonrheumatoid inflammatory arthropathy remains in the differential [43].
- The etiology of Kienbo¨ck disease is still unknown and, consequently, the ideal treatment is in doubt [13].
- Our understanding of Kienbock disease has evolved significantly over the last decade with advances in the study of basic science and advanced imaging [36].
- Some patients are predisposed to the disease, and the evolution of the disease may be influenced by the patient’s demographic [36].
- Both biomechanical and biological factors play a significant role [36].
- Stability of the wrist plays a role [36].
- The disease affects the ligaments within and between the carpus and radius through synovitis or avulsion, and disruption of these can leading to collapse of the lunate and carpus [36].
- Better understanding of the disease pathogenesis will improve our ability to strategize surgical management [36].
- There have been many recent advances in the understanding of etiology of Kienbock disease (KD) [36].
- A basic science model of the disease has been studied over the last decade to further our understanding and improve our management rationale [36].
- In this current concepts review, we present concepts on the etiology and pathogenesis of the disease through basic science models and clinical research, including the osseous, vascular, ch [36].
- Kienbo¨ck disease is an isolated disorder of the carpal lunate associated with characteristic, and often progressive, clinical and radiographic changes [7].
- Appropriate intervention at specific disease stages represents the best opportunity to achieve good outcomes [7].
- As understanding of the disease improves, new therapeutic and diagnostic innovations have surfaced that further augment existing treatment options [7].
- In addition to observing the obvious osseous changes, there has been renewed interest in understanding the vascular and cartilaginous manifestations of the disorder [7].
- Recognition of these factors can permit focused areas of intervention, including gene and cell-based therapies in the earliest stages [7].
- New diagnostic techniques are also being investigated [7].
- Advanced imaging modalities can facilitate the earlier recognition of Kienbo¨ck disease and enhance the assessment of lunate vascularity [7].
- Moreover, diagnostic arthroscopy permits us to directly visualize and characterize affected structures, including cartilage [7].
- Finally, there has been much recent interest in the natural history of Kienbo¨ck disease [7].
- Infantile, juvenile, and geriatric forms have been described [7].
- It has been suggested that the disease pathway in these individuals may differ from the typical adult patient population [7].
- Integrating these contemporary findings with the classic information on Kienbock disease can permit a more sophisticated approach to stage-specific treatment [7].
- This article reexamines the current classification systems to accou [7].
- The authors propose a unified classification and treatment algorithm that coordinates osseous, vascular, and articular data alongside patient age to allow for more precise and individualized treatment plans for Kienböck disease [26].
- Kienbo€ck’s disease (KD) is characterized by osteonecrosis, fragmentation and collapse of the lunate, followed by carpal instability and osteoarthritis [71].
- The lunate consists of osseous, vascular and cartilaginous components, for each of which a separate classification has been developed: osseous, Lichtman (Lichtman and Degnan, 1993; Lichtman et al., 2010), vascular, Schmitt (Schmitt et al., 1997) and cartilage, Bain (Bain and Begg, 2006) [71].
- Lichtman et al. (2022) recently developed a unified classification and treatment algorithm combining the three existing classifications [71].
- Besides age, cartilage condition and vascularity, bone morphology is particularly important for choosing the most appropriate treatment in KD [71].
- In particular, the surgical treatment decision from stage III and IV is determined by the bony morphology of the lunate: apart from unloading procedures, revascularizing, local or carpal reconstructive methods or salvage procedures are used [71].
- The aim of the study was to compare the Lichtman osseous staging (Lichtman and Degnan, 1993; Lichtman et al., 2010) of KD by CR and
Treatment
Non-Operative Management
- Kienböck's disease has a naturally benign course, and remaining symptoms at follow-up might be caused by osteoarthrosis [6].
- Patients younger than 15 years with Kienböck’s disease initially should be treated nonsurgically with immobilization for 6 weeks at least, followed by careful follow-up with repeated standard radiographs, CTs, and MRI [68].
Core Decompression
- Arthroscopic lunate core decompression appears to be an effective and safe surgery for treating Kienböck disease on the basis of mid-term follow-up [31].
- In this limited series, distal radius metaphyseal core decompression demonstrated favorable long-term results and is recommended as a surgical alternative for stage IIIa of the Kienböck disease [24].
- Findings suggest that stage I and II lunate necrosis can be effectively treated without alterations of individual wrist mechanics [69].
- Core decompression resulted in pain relief, radiological stability, and MRI normalization at 7-year follow-up in a case of early-stage Kienböck's disease [32].
Radial Osteotomy
- Excluding the rare extended stage IV disease in which midcarpal arthritis with or without intercarpal instability is present, radial shortening osteotomy has been successfully applied to all stages of Kienböck's disease [60].
- Radial closing wedge osteotomy is an effective procedure for patients with Kienböck's disease, providing effective pain relief in all cases with few complications [90].
- Based on observations regarding ulnar variance, it seems unlikely that the 'ulnar minus variant' has any bearing on the cause of Kienböck's disease and consequently the indications for ulnar lengthening and radial shortening osteotomies needs to be re-evaluated [132].
Vascularized Bone Grafting
- Vascularized grafts in general have demonstrated satisfactory clinical results in Kienböck disease, with excellent pain relief and improvement in range of motion and strength [121].
- Improved results were found in postoperative grip strength, pain relief, and function when a vascularized graft was combined with 4 months’ temporary scaphocapitate pinning [121].
- Not all patients had evidence of revascularization on radiography after vascularized bone graft combined with unloading procedures for Kienböck disease [72].
- The combination of cancellous bone grafting and external fixation is an alternative treatment for Kienböck's disease [74].
Arthrodesis and Salvage Procedures
- The efficacy of triscaphe arthrodesis in maintaining carpal height is the main reason to use it in Kienböck's disease at stage 3 [48].
- Scaphotrapeziotrapezoid arthrodesis with lunate excision for advanced Kienböck disease provided favorable clinical results in terms of pain relief and functional improvement [106].
- Given the significant postoperative reduction in associated pain symptoms at the time of follow-up, scaphocapitate arthrodesis should be considered as a treatment option for wrist salvage in the patient with advanced Kienbock's disease [176].
- The continued use of silicone replacement arthroplasty (without intercarpal fusion) in the treatment of Kienböck's disease should be discouraged [120].
- Partial capitate shortening osteotomies are used in Lichtman stages II and III-A, before significant fixed deformity has occurred [77].
- Surgical management of Kienböck's disease in adolescent patients can yield satisfactory outcomes in those that fail conservative management [52].
General Treatment Considerations
- The natural history of Kienbock's disease is not fully known, though it is generally considered a progressive condition that can end in Stage IV changes; treatment strategies focus on biomechanical unloading, vascularized bone grafts, or salvage procedures depending on the stage [5].
- The etiology of Kienbock disease is still unknown and, consequently, the ideal treatment is in doubt [13].
- Based on retrospective data from uncontrolled studies, no active treatment is superior in the treatment of Kienböck's disease and there are insufficient data to determine whether the outcomes of any intervention are superior to placebo or the natural history of the disease [35].
- There is limited, low-quality evidence that surgical treatment slows progression of Kienböck's disease, and many uncontrolled case series document slight improvement in motion and grip after surgical treatment without clear evidence that this is better than placebo or no intervention [99].
- First-line surgical treatment for Kienböck disease is a joint-leveling procedure or core decompression of the radius [63].
- For ulnar-negative variance, radial shortening osteotomy is the first-line surgical treatment [63].
- Supplemental vascularized bone grafting is described for Kienböck disease [63].
- For Stage IIIB Kienböck disease, a salvage procedure for associated carpal instability and/or degenerative osteoarthritis such as proximal row carpectomy is indicated [63].
Complications
- Kienböck disease is a progressive condition that can end in Stage IV changes [5].
- The articular cartilage of the lunate degenerates in early stages of Kienböck disease [8].
- Approximately one in eight patients undergoing radial shortening osteotomy for symptomatic Kienböck disease underwent salvage surgery [15].
- Tendon ball arthroplasty in advanced Kienböck disease results in widespread changes in the bones and joints within the wrist [16].
- The natural history of Kienböck disease is not fully known [5].
- Radiographic and clinical findings do not always correlate in Kienböck disease [75].
- The etiology of Kienböck disease is still unknown [13].
- The aetiology of Kienböck's disease remains controversial, with theories including traumatic compression fracture, repeated minor trauma, and vascular insufficiency [156].
- The disease affects the ligaments within and between the carpus and radius through synovitis or avulsion, and disruption of these can lead to collapse of the lunate and carpus [36].
- AVN of the carpal bones other than Kienböck disease is a rare cause of chronic wrist pain with a poorly understood natural history [50].
- At least 1.9% of persons in the African population examined had asymptomatic stage II, III, and IV Kienböck’s disease [167].
- Not all cases of Kienböck’s disease are painful or symptomatic [167].
Recovery
Natural History and Progression
- The natural history of Kienböck's disease is not fully known, though it is generally considered a progressive condition that can end in Stage IV changes [5].
- Kienböck's disease progresses substantially faster than previously described, and the articular cartilage of the lunate degenerates in early stages [8].
- Radiographic progression of Kienböck disease over 1 year or more seems slight on average regardless of treatment [37].
Non-Operative and Early Stage Outcomes
- Kienböck’s disease in a 15-year-old girl was treated successfully by temporary scaphotrapezoidal joint fixation using longitudinal K-wires [73].
Radial Osteotomy Outcomes
- The medium- and long-term results of radial shortening osteotomy for Kienböck's disease in patients with negative ulnar variance are comparable to short-term results, providing long-lasting pain relief [65].
- Clinical outcomes of radius shortening failed to demonstrate predicted clinically relevant differences between stage II/IIIA and IIIB Kienböck's disease [51].
Core Decompression Outcomes
Vascularized Bone Graft Outcomes
- Free vascularized iliac bone grafting for Kienböck's disease is a reasonable treatment option, and clinical and radiological improvements last for a long period of time [38].
Salvage and Arthrodesis Outcomes
- Nonetheless, functional outcomes in medium-term follow-up are discouraging after scaphocapitate arthrodesis for advanced stages of Kienböck disease [2].
- SCA resulted in improved grip strength with correction of carpal alignment in patients with advanced stages of Kienböck disease in medium-term follow-up [139].
- At an average follow-up of 10 years, proximal row carpectomy is a reliable and durable procedure for patients with Lichtman stage IIIA or IIIB Kienböck's disease [140].
- The longer-term results of TLA for stage III Kienböck disease are promising [61].
Key Evidence
- [L5] [1] (10.5435/jaaos-d-20-00020)
- [L4] Nonetheless, functional outcomes in medium-term follow-up are discouraging after scaphocapitate arthrodesis for advanced stages of Kienböck disease. [2] (10.1016/j.jhsa.2013.08.063)
- [L3] A prospective investigation is needed to delineate the appropriate management and expected outcomes of pediatric and adolescent Kienbock disease. [3] (10.1016/j.jhsg.2026.101068)
- [L4] The current results indicate that radial osteotomies are effective in improving not only short-term clinical outcomes, but also radiographic findings in teenage patients with Kienböck disease. [4] (10.1097/01.blo.0000173254.46899.72)
- [L5] The natural history of Kienbock's disease is not fully known, though it is generally considered a progressive condition that can end in Stage IV changes; treatment strategies focus on biomechanical unloading, vascularized bone grafts, or salvage procedures depending on the stage. [5] (10.1016/j.hcl.2006.07.003)
- [L4] Kienböck's disease has a naturally benign course, and the remaining symptoms at follow-up might be caused by osteoarthrosis. [6] (10.1016/0266-7681(86)90171-3)
- [L5] [7] (10.1097/bth.0b013e31820e82d2)
- [L4] Kienböck's disease progresses substantially faster than previously described and, contrary to current classifications, the articular cartilage of the lunate degenerates in early stages. [8] (10.1016/j.jhsa.2014.06.032)
- [L4] A long-term follow-up period is essential in evaluating radial osteotomy in the treatment of Kienböck's disease. [9] (10.1016/s0363-5023(98)80170-6)
- [L4] Good and excellent clinical and radiological outcomes can be achieved with both nonsurgical and surgical treatments in skeletally immature patients with Kienböck disease. [10] (10.1016/j.jhsa.2018.02.029)
- [L5] [11] (10.1016/s0363-5023(87)80109-0)
- [L4] The long-term clinical benefits of scaphocapitate arthrodesis for treatment of collapsed Kienböck disease are demonstrated. [12] (10.1177/1753193413496177)
- [L5] The etiology of Kienbo¨ck disease is still unknown and, consequently, the ideal treatment is in doubt. [13] (10.1097/bth.0b013e3182107329)
- [L4] We therefore recommend this procedure for the surgical treatment of adolescent Kienböck's disease. [14] (10.1016/j.jhsa.2008.09.019)
- [L4] Radial shortening osteotomy for symptomatic Kienböck's disease yields reasonable long-term function, though approximately one in eight patients underwent salvage surgery. [15] (10.1055/s-0040-1714750)
- [L4] Tendon ball arthroplasty in advanced Kienböck's disease results in long-term satisfactory clinical outcomes, despite widespread changes in the bones and joints within the wrist. [16] (10.1177/1753193412471183)
- [L4] Patients with Kienböck's disease treated with lunate excision and followed up for more than 5 years have generally shown satisfactory results that are considered definitive. [17] (10.1016/s0363-5023(85)80027-7)
- [L5] It is suggested that any patient diagnosed as suffering from Kienböck's disease should also have his other wrist examined and radiographed for early diagnosis and treatment of the disease. [18] (10.1016/s0363-5023(85)80142-8)
- [L4] Scaphocapitate arthrodesis is an effective procedure for treatment of Kienböck disease associated with satisfactory functional outcomes and significant improvement in pain scores and grip strength. [19] (10.1016/j.jhsg.2023.03.014)
- [L4] Children, adolescents, and elderly patients with Kienböck disease respond well to nonoperative treatments, and this should be considered before any surgical intervention. [20] (10.2106/jbjs.24.01090)
- [L5] [21] (10.1016/j.main.2014.10.149)
- [L3] Vascularized bone grafting for stage III Kienböck disease demonstrated favorable long-term results and is recommended as a surgical treatment. [22] (10.1016/j.jhsa.2013.02.010)
- [L4] Radial shortening osteotomy provides decade-long improvement in 75% of patients and seems to be a reasonable treatment for symptomatic Kienböck’s disease. [23] (10.1177/1753193413512222)
- [L4] In this limited series, distal radius metaphyseal core decompression demonstrated favorable long-term results and is recommended as a surgical alternative for stage IIIa of the Kienböck disease. [24] (10.1177/1558944716660555ih)
- [L5] Patients with these symptoms should undergo imaging of the wrist joints to ascertain concomitant Kienböck’s disease. [25] (10.1142/s2424835520720042)
- [L5] The authors propose a unified classification and treatment algorithm that coordinates osseous, vascular, and articular data alongside patient age to allow for more precise and individualized treatment plans for Kienböck disease. [26] (10.1016/j.jhsa.2022.03.014)
- [L3] Lunate morphology may affect the severity of Kienböck disease at the time of initial presentation. [27] (10.1016/j.jhsa.2014.12.024)
- [L4] Radial shortening osteotomy should not be contraindicated in advanced Kienbock's disease (without radiocarpal osteoarthritis) as it achieves long-lasting good clinical results with very few complications. [28] (10.1055/s-0039-1688947)
- [L3] Traditional radiographic indices measured on plain radiographs have poor diagnostic performance in the detection of carpal collapse in Kienböck's disease. [29] (10.1177/17531934231153966)
- [L4] Arthroscopic lunate core decompression appears to be an effective and safe surgery for treating Kienböck disease on the basis of mid-term follow-up. [31] (10.1016/j.jhsa.2023.02.011)
- [L5] The article presents a case of early-stage Kienböck's disease where core decompression resulted in pain relief, radiological stability, and MRI normalization at 7-year follow-up, supporting the potential of disease-modifying treatments in early stages. [32] (10.1177/17531934221146851)
- [L2] The acceptance rate for negative outcomes studies regarding Kienböck's disease is higher than for other surgical disorders, indicating a relative decrease in positive outcome bias among published Kienböck's disease studies compared with other surgical disorders. [34] (10.1016/j.jhsa.2009.12.003)
- [L4] Based on retrospective data from uncontrolled studies, no active treatment is superior in the treatment of Kienböck's disease and there are insufficient data to determine whether the outcomes of any intervention are superior to placebo or the natural history of the disease. [35] (10.1016/j.jhsa.2010.02.002)
- [Paper] [36] (10.1016/j.jhsa.2026.07.013)
- [L4] [37] (10.1016/j.jhsa.2016.02.016)
- [L4] Free vascularized iliac bone grafting for Kienböck's disease is a reasonable treatment option, and clinical and radiological improvements last for a long period of time. [38] (10.1016/j.jhsa.2007.11.005)
- [L2] Capitate shortening is a safe and effective approach for treatment of the early stages of Kienböck's disease and can be associated with a satisfying outcome. [40] (10.1177/15589447221081564)
- [L5] The manuscript reviews recent advances in diagnostics, classification, and treatment options for Kienböck disease to present a new treatment algorithm that integrates traditional osseous classification with perfusion/viability and articular cartilage-based classifications. [41] (10.1016/j.jhsa.2016.02.013)
- [L4] Arthroscopy in Kienböck disease allows precise evaluation of pathology severity and associated chondral lesions, refining classification to provide the most appropriate treatment. [42] (10.1016/j.main.2015.10.097)
- [L5] The authors believe the most likely diagnosis is primary Kienböck’s disease leading to secondary synovitis and tertiary autofusion, though an unusual presentation of a monoarticular nonrheumatoid inflammatory arthropathy remains in the differential. [43] (10.1016/j.jhsa.2004.09.003)
- [L4] Radial shortening osteotomy offers at least comparable outcomes with PRC in treating Kienböck's disease, particularly in preserving joint function and patient satisfaction. [44] (10.1016/j.jhsa.2026.02.031)
- [L5] [45] (10.1016/j.jhsa.2004.02.013)
- [L4] Surgical indications for Kienböck's disease should be carefully considered, keeping in mind their side-effects and the relative benignity in some cases of the natural course of the disease. [47] (10.1016/s0266-7681(98)80214-3)
- [L4] The efficacy of triscaphe arthrodesis in maintaining carpal height is the main reason to use it in Kienböck's disease at stage 3. [48] (10.1016/0266-7681(92)90005-m)
- [L4] Radial osteotomy for Kienböck’s disease is a reasonable treatment option and clinical improvement lasts for a long period of time. [49] (10.1016/s0363-5023(03)00490-8)
- [L5] AVN of the carpal bones other than Kienböck disease is a rare cause of chronic wrist pain with a poorly understood natural history. [50] (10.1016/j.jhsa.2019.05.022)
- [L4] Clinical outcomes of radius shortening failed to demonstrate predicted clinically relevant differences between stage II/IIIA and IIIB Kienböck's disease. [51] (10.1016/j.jhsa.2010.08.017)
- [L4] Surgical management of Kienböck ' s disease in adolescent patients can yield satisfactory outcomes in those that fail conservative management. [52] (10.1055/s-0040-1701511)
- [L4] Surgeons should be aware that the diagnosis of Kienböck disease in the precollapse stages is not well defined, as evidenced by the substantial interobserver variability. [53] (10.1177/1558944716677538)
- [L5] Radial osteotomies are reliable surgical methods for Kienböck disease in that the effect is maintained for more than 10 years. [54] (10.1097/bth.0b013e31820baa36)
- [L4] The treatment of Kienböck disease with vascularized bone graft from the dorsum of the radius has encouraging results and needs no other additional procedures. [58] (10.1007/s00402-008-0586-x)
- [L4] Excluding the rare extended stage IV disease in which midcarpal arthritis with or without intercarpal instability is present, we have successfully applied this technique to all stages of Kienböck's disease. [60] (10.1016/0363-5023(91)90013-2)
- [L4] The longer-term results of TLA for stage III Kienböck disease are promising. [61] (10.1016/j.jhsa.2018.02.009)
- [L3] The medium- and long-term results of radial shortening osteotomy for Kienböck's disease in patients with negative ulnar variance are comparable to short-term results, providing long-lasting pain relief. [65] (10.1097/blo.0b013e318041d309)
- [L4] [66] (10.1177/1753193416676723)
- [L5] This case supports recommendations that patients younger than 15 years with Kienböck’s disease initially should be treated nonsurgically with immobilization for 6 weeks at least, followed by careful follow-up with repeated standard radiographs, CTs, and MRI. [68] (10.1016/j.jhsa.2005.09.016)
- [L4] Findings suggest that stage I and II lunate necrosis can be effectively treated without alterations of individual wrist mechanics. [69] (10.1142/s2424835519500346)
- [L3] [71] (10.1177/17531934241286115)
- [L4] Not all patients had evidence of revascularization on radiography after VBG combined with unloading procedures for Kienböck disease. [72] (10.1142/s2424835519500541)
- [L4] Kienböck’s disease in a 15-year-old girl was treated successfully by temporary scaphotrapezoidal joint fixation using longitudinal K-wires. [73] (10.1016/j.jhsa.2005.08.015)
- [L4] The combination of cancellous bone grafting and external fixation is an alternative treatment for Kienböck's disease. [74] (10.1016/s0363-5023(96)80186-9)
- [L5] [75] (10.1016/j.jhsa.2012.06.029)
- [L4] [77] (10.1177/1753193414562355)
- [L5] A wrist joint should be considered biomechanically unstable when it is not able to bear loads and does not exhibit normal kinematics throughout its arc of motion. [78] (10.1053/jhsu.1999.0866)
- [L4] The Lichtman et al. classification for Kienböck's disease has good reliability and reproducibility. [79] (10.1177/1753193410373862)
- [L5] The author states that their classification of Kienbock’s disease in stages IIIA (without carpal collapse) or IIIB (with carpal collapse) is done comparing to the contralateral wrist. [80] (10.1177/17531934231205707)
- [L4] The results of our study show that the Lichtman classification system for Kienbo¨ck’s disease has substantial agreement both in terms of interobserver reliability and intraobserver reproducibility. [81] (10.1053/jhsu.2000.7377)
- [L4] Arthroscopy provides a valuable assessment and subsequent classification of Kienbock’s disease based on the number of non-functional articular surfaces. [86] (10.1097/00130911-200603000-00003)
- [L4] Radial closing wedge osteotomy is an effective procedure for patients with Kienböck's disease, providing effective pain relief in all cases with few complications. [90] (10.1016/s0363-5023(96)80311-x)
- [L5] Kienböcks disease is uncommon in the elderly and usually appears in patients between the age of 30 and 40. [92] (10.1016/s0363-5023(05)80056-5)
- [L4] In elderly patients Kienbo¨ck’s disease commonly occurred in the dominant hand of manual workers, similar to the conventional characterization of Kienbo¨ck’s disease. [93] (10.1016/s0363-5023(03)00299-5)
- [L3] Dorsal wrist swelling in Kienböck ' s disease is a common manifestation and constitutes a part of pathology of Kienböck ' s disease, although further study is required to clarify the relation between wrist swelling and etiology of Kienböck ' s disease. [94] (10.1055/s-0038-1661420)
- [L5] There is limited, low-quality evidence that surgical treatment slows progression of Kienböck's disease, and many uncontrolled case series document slight improvement in motion and grip after surgical treatment without clear evidence that this is better than placebo or no intervention. [99] (10.1016/j.jhsa.2009.10.013)
- [L4] In this study, the six patients with the diagnosis of Kienböck's disease demonstrated a correlation between the loss of signal intensity on T1 and T2-weighted MRI images and evidence of osteonecrosis by histology. [105] (10.1016/0363-5023(90)90007-e)
- [L4] Scaphotrapeziotrapezoid arthrodesis with lunate excision for advanced Kienböck disease provided favorable clinical results in terms of pain relief and functional improvement. [106] (10.1016/j.jhsa.2012.08.031)
- [L4] [113] (10.1016/j.otsr.2021.103161)
- [L4] The continued use of SRA (without intercarpal fusion) in the treatment of Kienböck's disease should be discouraged. [120] (10.1016/0363-5023(90)90050-2)
- [L4] Computed tomography of the lunate in Kienböck disease is an important investigative tool. [123] (10.1016/j.jhsa.2018.05.008)
- [L4] This study confirms that the Bain and Begg arthroscopic classification and an articular-based approach to Kienböck disease provide a high probability of good longterm relief of pain and a minimal chance of requiring a salvage procedure. [126] (10.1016/j.jhsa.2020.11.004)
- [L4] [129] (10.1053/jhsu.2003.50035)
- [L4] Based on these observations it seems unlikely that the 'ulnar minus variant' has any bearing on the cause of Kienböck's disease and consequently the indications for ulnar lengthening and radial shortening osteotomies needs to be re-evaluated. [132] (10.1016/0266-7681(86)90275-5)
- [L4] Proton density–weighted MRIs but not fast-field echo images using a 47-mm microscopy coil reflected the extent and localization of the necrotic area in Kienböck-diseased lunates, as evidenced by comparison with histological analyses of the lunate specimens. [133] (10.1016/j.jhsa.2011.09.027)
- [L4] SCA resulted in improved grip strength with correction of carpal alignment in patients with advanced stages of Kienböck disease in medium-term follow-up. [139] (10.1016/j.jhsa.2014.12.013)
- [L4] At an average follow-up of 10 years, proximal row carpectomy is a reliable and durable procedure for patients with Lichtman stage IIIA or IIIB Kienböck's disease. [140] (10.1016/j.jhsa.2008.02.031)
- [L4] MRI showed complete loss of signal intensity in T1 images of the lesion of the lunate in advanced Stage 3 Kienböck's disease, but is at present unable to distinguish bone necrosis, the histological reactive interface or surrounding hyperaemia in detail. [149] (10.1016/s0266-7681(96)80019-2)
- [L5] The aetiology of Kienbock's disease remains controversial, with theories including traumatic compression fracture, repeated minor trauma, and vascular insufficiency. [156] (10.1016/j.jhsb.2004.01.006)
- [L5] [159] (10.1016/s0363-5023(80)80013-x)
- [L4] [167] (10.1177/1753193408098481)
- [L4] Given the significant postoperative reduction in associated pain symptoms at the time of follow-up, scaphocapitate arthrodesis should be considered as a treatment option for wrist salvage in the patient with advanced Kienbock's disease. [176] (10.1007/s11552-014-9705-z)
References
[1] Osteonecrosis of the Lunate: Kienböck Disease. Journal of the American Academy of Orthopaedic Surgeons. 2020. DOI: 10.5435/jaaos-d-20-00020
[2] Scaphocapitate Arthrodesis in the Treatment of Kienböck Disease. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.08.063
[3] A Scoping Review of Pediatric Kienböck Disease: What Do We Know?. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101068
[4] Radial Osteotomies for Teenage Patients with Kienböck Disease. Clinical Orthopaedics and Related Research. 2005. DOI: 10.1097/01.blo.0000173254.46899.72
[5] Kienböck's Disease: An Approach to Treatment. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2006.07.003
[6] Kienböck's disease — late results by non-surgical treatment A follow-up study. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90171-3
[7] A Classification-based Treatment Algorithm for Kienböck Disease. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e31820e82d2
[8] Characteristic Features and Natural Evolution of Kienböck Disease: Five Years Results of a Prospective Case Series and Retrospective Case Series of 106 Patients. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.032
[9] Arthroscopic evaluation of radial osteotomy for Kienböck's disease. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80170-6
[10] Kienböck Disease in the Skeletally Immature Patient. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.029
[11] The genesis of Kienböck's disease: Evaluation of a case by magnetic resonance imaging. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80109-0
[12] Scaphocapitate arthrodesis for treatment of late stage Kienböck disease. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413496177
[13] Etiology of Kienböck Disease. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e3182107329
[14] Temporary Scaphotrapezoidal Joint Fixation for Adolescent Kienböck's Disease. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.09.019
[15] Radial Shortening Osteotomy for Symptomatic Kienböck's Disease: Complications and Long-Term Patient-Reported Outcome. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1714750
[16] Long-term clinical results and MRI changes after tendon ball arthroplasty for advanced Kienböck’s disease. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193412471183
[17] Excision of the lunate in Kienböck's disease: Long-term results. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80027-7
[18] Bilateral Kienböck's disease. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80142-8
[19] Clinical and Radiological Outcomes of Scaphocapitate Fusion in Kienböck Disease: A Systematic Review and Meta-Analysis. Journal of Hand Surgery Global Online. 2023. DOI: 10.1016/j.jhsg.2023.03.014
[20] Kienböck Disease: Recent Advances in Understanding and Management. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.01090
[21] Kienböck's disease. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2014.10.149
[22] Long-Term Results of Vascularized Bone Graft for Stage III Kienböck Disease. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.02.010
[23] Long-term outcome (20 to 33 years) of radial shortening osteotomy for Kienböck’s lunatomalacia. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413512222
[24] Long-Term Outcomes of Distal Radius Metaphyseal Core Decompression for Kienböck Disease Stage IIIa. HAND. 2016. DOI: 10.1177/1558944716660555ih
[25] Extensor Tendon Rupture Due to Advanced Kienböck’s Disease: Two Case Reports and a Review of Literature. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520720042
[26] Precision Medicine for Kienböck Disease in the 21st Century. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.03.014
[27] The Effect of Lunate Morphology in Kienböck Disease. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.024
[28] Treatment of Advanced Kienbock's Disease (Lichtman Stage IIIB with Carpal Collapse) by a Shortening Osteotomy of the Radius: 21 Cases. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1688947
[29] Diagnostic performance of traditional radiographic indices in detection of carpal collapse in Kienböck’s disease. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231153966
[31] Arthroscopic Treatment of Kienböck Disease: Mid-Term Outcome of Arthroscopic Lunate Core Decompression. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.02.011
[32] Kienböck’s disease: preventing disease progression in early-stage disease. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934221146851
[34] Publication Bias in Kienböck's Disease: Systematic Review. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2009.12.003
[35] Systematic Review of the Treatment of Kienböck's Disease in Its Early and Late Stages. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.02.002
[36] Modern Concepts in the Etiology and Pathogenesis of Kienbock Disease. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2026.07.013
[37] Radiographic Progression of Kienböck Disease: Radial Shortening Versus No Surgery. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2016.02.016
[38] Long-Term Subjective and Radiological Outcome After Reconstruction of Kienböck’s Disease Stage 3 Treated by a Free Vascularized Iliac Bone Graft. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2007.11.005
[40] Comparing the Radiologic and Functional Outcome of Radial Shortening Versus Capitate Shortening in Management of Kienböck’s Disease. HAND. 2022. DOI: 10.1177/15589447221081564
[41] Kienböck Disease: Moving Forward. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2016.02.013
[42] Apport de l’arthroscopie dans le bilan et le traitement de la maladie de Kienböck. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2015.10.097
[43] Spontaneous wrist fusion: An unusual complication of Kienböck’s disease. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2004.09.003
[44] Save or Salvage: Radial Shortening Osteotomy and Proximal Row Carpectomy in Kienböck’s Disease—A Descriptive Study. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2026.02.031
[45] Kienböck’s disease in an elderly patient treated with proximal row carpectomy. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.02.013
[47] Conservative Versus Operative Treatment for Kienböck’s Disease. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80214-3
[48] Scapho-Trapezio-Trapezoid Arthrodesis in the Treatment of Kienböck’s Disease. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90005-m
[49] Surgical outcome of radial osteotomy for Kienböck’s disease—minimum 10 years of follow-up. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)00490-8
[50] Avascular Necrosis of the Carpal Bones Other Than Kienböck Disease. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.05.022
[51] Joint Leveling for Advanced Kienböck's Disease. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.08.017
[52] Adolescent Kienböck's Disease: A Comparison between Lunate Offloading and Revascularization Procedures. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1701511
[53] Interobserver Agreement in Diagnosing Early-Stage Kienböck Disease on Radiographs and Magnetic Resonance Imaging. HAND. 2016. DOI: 10.1177/1558944716677538
[54] Radial Osteotomy for Kienböck Disease. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e31820baa36
[58] The treatment of Kienböck disease with vascularized bone graft from dorsal radius. Archives of Orthopaedic and Trauma Surgery. 2008. DOI: 10.1007/s00402-008-0586-x
[60] Radial shortening osteotomy for treatment of Kienböck's disease. The Journal of Hand Surgery. 1991. DOI: 10.1016/0363-5023(91)90013-2
[61] Long-Term Clinical Outcome After Titanium Lunate Arthroplasty for Kienböck Disease. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.009
[63] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > TESTABLE CONCEPTS > IDIOPATHIC OSTEONECROSIS OF THE CARPUS.
[65] Outcome of Kienböck's Disease 22 Years after Distal Radius Shortening Osteotomy. Clinical Orthopaedics & Related Research. 2007. DOI: 10.1097/blo.0b013e318041d309
[66] Radial shortening osteotomy for treatment of Lichtman Stage IIIA Kienböck disease. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193416676723
[68] Kienböck’s Disease in a 14-Year-Old Gymnast: A Case Report. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2005.09.016
[69] Metaphyseal Core Decompression of the Distal Radius for Early Lunate Necrosis. The Journal of Hand Surgery (Asian-Pacific Volume). 2019. DOI: 10.1142/s2424835519500346
[71] Radiography versus computed tomography for osseous staging of Kienböck’s disease. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241286115
[72] Is Joint Levelling Procedure Better than Temporary Scaphocapitate Pinning in Patients Undergoing Vascularized Bone Graft for Kienböck Disease?. The Journal of Hand Surgery (Asian-Pacific Volume). 2019. DOI: 10.1142/s2424835519500541
[73] Time Course of Magnetic Resonance Images in an Adolescent Patient With Kienböck’s Disease Treated by Temporary Scaphotrapezoidal Joint Fixation: A Case Report. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2005.08.015
[74] External fixation and cancellous bone grafting for Kienböck's disease: A preliminary report. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80186-9
[75] Kienböck Disease. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.06.029
[77] Partial capitate shortening for Kienböck’s disease. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414562355
[78] Position Statement: Definition of Carpal Instability. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0866
[79] Reliability and reproducibility of Kienböck’s disease staging. Journal of Hand Surgery (European Volume). 2010. DOI: 10.1177/1753193410373862
[80] Re: Luitjens J, Goller SS, Schmitt R, Erber B, Van Scoonhoven J, Hess N. Diagnostic performance of traditional radiographic indices in detection of carpal collapse in Kienbock’s disease. J Hand Surg Eur. 2023, 48: 619–24.. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231205707
[81] Reliability of the Lichtman classification of Kienböck's disease. The Journal of Hand Surgery. 2000. DOI: 10.1053/jhsu.2000.7377
[83] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[86] Arthroscopic Assessment and Classification of Kienbock's Disease. Techniques in Hand & Upper Extremity Surgery. 2006. DOI: 10.1097/00130911-200603000-00003
[88] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS OF THE DISTAL AND MID-FOREARM.
[89] Aaos Comprehensive Orthopaedic Review 3. Carpal Instability* > II. Anatomy and Biomechanics (See Chapter 92).
[90] Radial closing wedge osteotomy for Kienböck's disease. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80311-x
[91] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Imaging: Advances in Imaging of the Hand and Upper Extremity > Magnetic Resonance Imaging.
[92] Kienböck's disease in an elderly patient. The Journal of Hand Surgery. 1995. DOI: 10.1016/s0363-5023(05)80056-5
[93] Kienböck’s disease in elderly patients. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)00299-5
[94] Wrist Swelling in Kienböck's Disease. Journal of Wrist Surgery. 2018. DOI: 10.1055/s-0038-1661420
[96] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[97] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[99] Kienböck's Disease. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2009.10.013
[101] Green S Operative Hand Surgery. AUTHORS' PREFERRED METHOD OF TREATMENT: SL DISSOCIATION > Carpal Malalignment Secondary to Deformity of the Lunate.
[102] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[105] Histologic and magnetic resonance imaging correlations in Kienböck's disease. The Journal of Hand Surgery. 1990. DOI: 10.1016/0363-5023(90)90007-e
[106] Scaphotrapeziotrapezoid Arthrodesis and Lunate Excision for Advanced Kienböck Disease. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.08.031
[110] Green S Operative Hand Surgery. Advanced Imaging.
[113] Kienböck's disease in 2021. Orthopaedics & Traumatology: Surgery & Research. 2022. DOI: 10.1016/j.otsr.2021.103161
[114] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Kienböck's Disease.
[118] Campbell S Operative Orthopaedics 4 Volume Set. WRIST AND ELBOW.
[120] Lunate silicone replacement arthroplasty in Kienböck's disease: A long-term follow-up. The Journal of Hand Surgery. 1990. DOI: 10.1016/0363-5023(90)90050-2
[121] Green S Operative Hand Surgery. VASCULARIZED GRAFTS: SMALL BONE AND PERIOSTEAL FLAPS > Lunate Graft in Kienböck Disease.
[123] Fixation of the Fractured Lunate in Kienböck Disease. The Journal of Hand Surgery. 2019. DOI: 10.1016/j.jhsa.2018.05.008
[125] Green S Operative Hand Surgery. Osteonecrosis.
[126] Long-Term Outcome of Surgical Treatment for Kienböck Disease Using an Articular-Based Classification. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2020.11.004
[129] The Lichtman classification for Kienböck's disease: An assessment of reliability. The Journal of Hand Surgery. 2003. DOI: 10.1053/jhsu.2003.50035
[132] Ulnar variance in Kienböck's disease. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90275-5
[133] Correlation of Histopathology With Magnetic Resonance Imaging in Kienböck Disease. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.09.027
[139] Scaphocapitate Arthrodesis for Kienböck Disease. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.013
[140] Proximal Row Carpectomy for Advanced Kienböck's Disease: Average 10-Year Follow-Up. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.02.031
[145] Lunate_Revascularization_in_Kienböck's_Disease_S0363502311002838. n.d..
[149] Histopathology of Kienböck’s Disease. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(96)80019-2
[156] Aetiology of Kienbőck’s Disease. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2004.01.006
[159] The vascularity of the lunate bone and Kienböck's disease. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80013-x
[167] The Incidence of Asymptomatic Kienböck’s Disease. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193408098481
[176] Limited Intercarpal Fusion as a Salvage Procedure for Advanced Kienbock Disease. HAND. 2014. DOI: 10.1007/s11552-014-9705-z