Patients › Hand
Gânglio na bainha do tendão flexor
A benign, fluid-filled cyst arising from the flexor tendon sheath – often painless, but can cause clicking or limited finger movement.
O que você está sentindo
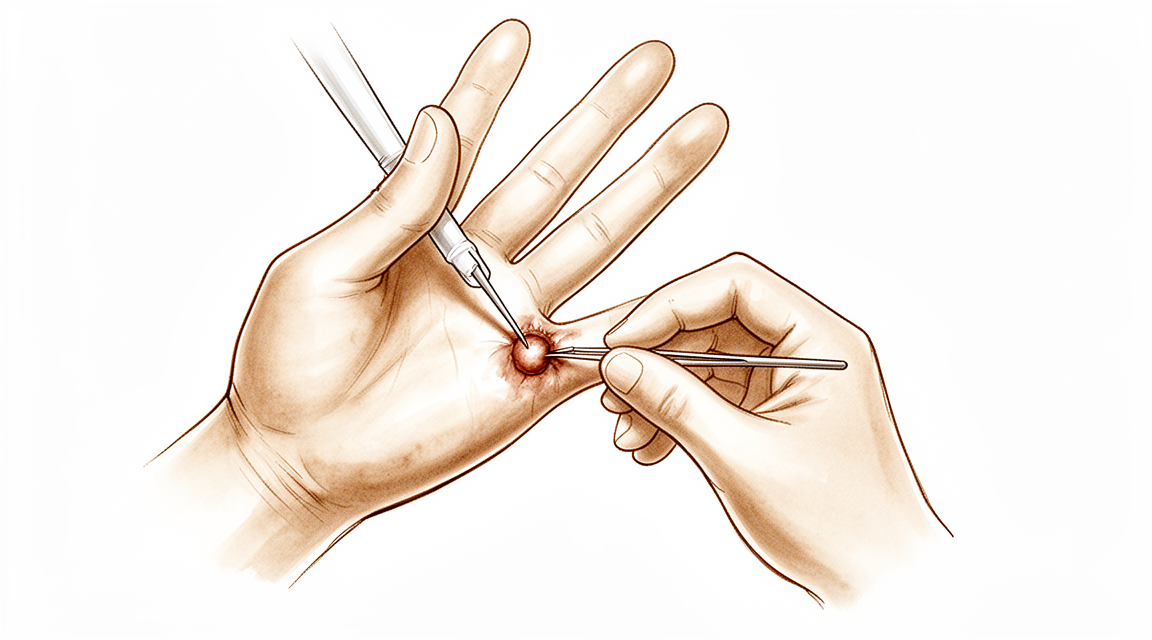
O cisto sinovial da bainha do tendão flexor é um nódulo pequeno e firme na base de um dedo, na palma da mão. Geralmente tem apenas alguns milímetros de diâmetro, mas pode doer mais do que se esperaria de algo tão pequeno. A dor surge quando você segura algo duro e estreito, como um volante, um taco de golfe, o guidão de uma bicicleta ou a alça de uma sacola de compras. O nódulo fica comprimido entre o objeto e o osso do dedo, sem nada macio para amortecê-lo.
A dor tende a piorar durante ou depois dessas tarefas de segurar objetos. Atividades como carregar compras pesadas, segurar ferramentas ou torcer roupa lavada podem se tornar desconfortáveis. Algumas pessoas percebem que a dor diminui quando soltam o objeto. O nódulo em si é firme, e não macio, e fica exatamente onde os dedos se dobram em direção à palma.
Como a dor está ligada ao ato de segurar, ela pode começar a limitar o que você faz com essa mão. Você pode perceber que está evitando certas tarefas ou mudando a forma de segurar as coisas para não pressionar o local.
Se em algum momento o dedo, a mão ou o braço ficar quente, vermelho, inchado e dolorido, especialmente com febre, isso exige atendimento no mesmo dia em um pronto-socorro. Você não precisa de encaminhamento do seu médico de família para ir.
O que está realmente acontecendo
O dedo se dobra graças a dois tendões que saem do antebraço, correm pelo lado da palma do dedo e se prendem ao osso do dedo. Pense neles como cordas que puxam quando você dobra o dedo. Para que essas cordas fiquem junto ao osso, em vez de se afastarem dele formando um arco, elas correm dentro de um túnel feito de faixas resistentes chamadas polias. Esse túnel é revestido por uma camada fina e escorregadia que mantém os tendões nutridos e deslizando suavemente.
O cisto sinovial da bainha do tendão flexor é um pequeno saco de líquido espesso, com consistência de gelatina, que se projeta para fora desse túnel. O saco é preenchido a partir do próprio revestimento da bainha, por isso se comporta como um pequeno vazamento sob pressão: se for drenado, ele volta a encher, porque o vazamento continua lá. O saco fica bem na base do dedo, na palma da mão, onde o túnel está firmemente preso ao osso, sem nenhum acolchoamento macio por cima. É por isso que um nódulo de apenas alguns milímetros de diâmetro pode doer tanto quando você segura algo: o nódulo fica comprimido entre o que você está segurando e o osso logo abaixo.
Esse mesmo local explica as outras coisas que você talvez tenha notado. Como o nódulo ocupa espaço dentro de um túnel estreito, ele pode apertar o tendão enquanto este desliza, e é por isso que algumas pessoas com um nódulo nesse local também têm o dedo enganchando ou “clicando”. Os nervos do dedo correm bem ao lado da bainha, um de cada lado, por isso um nódulo que pressione um nervo pode causar formigamento ou dormência, e não apenas dor.
Vale saber que um nódulo exatamente nesse local também pode ter outras causas, como um tendão que engancha ao deslizar ou um espessamento do tecido da palma que puxa o dedo em direção à palma. O seu cirurgião geralmente consegue diferenciá-los examinando a sua mão, e o tratamento é diferente para cada um.
O que podemos fazer a respeito
O Dr. Kieran Hirpara, cirurgião de membros superiores no Mater Private Hospital Rockhampton, começa com as opções menos invasivas que se adequam ao seu caso. Em geral, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que você nos procure, ainda assim será necessário um encaminhamento do seu médico de família para que você tenha direito ao reembolso do Medicare. Na sua consulta, colhemos o seu histórico, examinamos a sua mão e solicitamos exames de imagem, como uma ultrassonografia, se for necessário para confirmar o que é o nódulo.
Como esse nódulo é inofensivo e não continua crescendo, o tratamento depende inteiramente de quanto ele incomoda você. Um nódulo que você consegue sentir, mas que não dói quando você segura objetos normalmente, pode não precisar de nenhum tratamento. Se uma forma específica de segurar continuar causando dor, mudar a maneira de segurar as coisas ou reduzir essa tarefa por um tempo pode ser suficiente. A terapia da mão também pode ajudar você a encontrar formas de usar a mão que coloquem menos pressão sobre o local.
A drenagem do nódulo com uma agulha, chamada aspiração, costuma ser tentada antes da cirurgia. Ela esvazia o líquido do saco, mas, como o saco é alimentado pela bainha do tendão, geralmente ele volta a encher. Alguns nódulos também melhoram sozinhos com o tempo. Conversaremos sobre se vale a pena tentar a drenagem no seu caso.
Se essas medidas mais simples não trouxerem alívio suficiente, a cirurgia pode ser considerada. A operação remove o nódulo por meio de um pequeno corte na base do dedo, junto com o pequeno pedaço da bainha do tendão de onde ele cresce, e é isso que impede que ele volte. Geralmente sugerimos a cirurgia quando uma atividade específica e repetida do seu dia a dia está sendo limitada pela dor, e tomamos essa decisão junto com você.
Se em algum momento o dedo, a mão ou o braço ficar quente, vermelho, inchado e dolorido, especialmente com febre, vá a um pronto-socorro no mesmo dia.
O que esperar
A maioria dos cistos sinoviais como este é inofensiva e não continua crescendo. Alguns melhoram sozinhos com o tempo, e outros aparecem e desaparecem. Se o seu não dói, talvez você nunca precise de tratamento.
Se o nódulo doer quando você segura objetos, medidas simples podem ajudar. A drenagem com uma agulha esvazia o saco, mas, como o saco é alimentado pela bainha do tendão, geralmente ele volta a encher. Mudar a forma de segurar as coisas, ou reduzir a tarefa que desencadeia a dor, pode ser suficiente enquanto você espera para ver se o nódulo melhora.
Se essas medidas não ajudarem o suficiente, a cirurgia remove o nódulo junto com o pequeno pedaço da bainha de onde ele cresce, e é isso que impede que ele volte. A maioria das pessoas percebe que segurar objetos fica mais confortável quando o local deixa de ser comprimido. Como em qualquer operação da mão, há riscos a considerar, incluindo uma área dormente ao longo de um dos lados do dedo, rigidez, infecção e uma cicatriz espessa ou sensível. O seu cirurgião conversará sobre eles com você antes de você decidir.
A recuperação após a cirurgia leva semanas, e não dias. A mão ficará dolorida no início, e o pequeno corte na base do dedo levará algum tempo para se acomodar. A terapia da mão após a cirurgia é feita com Ruby Doolan, da Extend Rehabilitation. Ruby é terapeuta da mão: ela orientará os seus exercícios e confeccionará as talas necessárias enquanto o dedo cicatriza. A maioria das pessoas volta às suas tarefas normais de segurar objetos dentro de algumas semanas, embora alguma sensibilidade na cicatriz possa durar um pouco mais.
Se os seus sintomas não estiverem melhorando, estiverem piorando ao longo de semanas, acordarem você à noite ou impedirem você de trabalhar ou de usar a mão, procure o seu médico de família ou peça uma avaliação com um especialista.
Quando procurar ajuda médica
A maioria dos nódulos na base de um dedo são cistos sinoviais inofensivos, mas algumas outras condições podem ter a mesma aparência nesse local. Um dedo que trava ou “clica” ao dobrar, ou um cordão firme na palma que puxa o dedo em direção à palma, são condições que o seu cirurgião consegue diferenciar examinando a sua mão. Vale a pena examinar qualquer nódulo novo para saber qual deles você tem.
Peça uma avaliação com um especialista se o nódulo doer quando você segura objetos, se notar formigamento ou dormência no dedo, ou se o dedo estiver enganchando ou “clicando”. Peça também se os seus sintomas não estiverem melhorando, estiverem piorando ao longo de semanas, acordarem você à noite ou impedirem você de trabalhar ou de usar a mão.
Se em algum momento o dedo, a mão ou o braço ficar quente, vermelho, inchado e dolorido, especialmente com febre, vá a um pronto-socorro no mesmo dia. Você não precisa de encaminhamento do seu médico de família para ir.
Em maior profundidade
Advanced reading: the deeper science (optional)
Esta seção vai além do que você precisa saber para tomar decisões sobre o próprio tratamento. O ganglion na bainha do tendão flexor merece uma leitura mais detalhada, pois é o menor nódulo na cirurgia da mão capaz de provocar sintomas desproporcionalmente intensos; além disso, o tecido ao qual está ligado determina tanto o motivo da dor quanto o porquê de os tratamentos simples não surtirem efeito.
Um nódulo do tamanho de uma ervilha que causa dor desproporcional
Esses cistos, também chamados de cistos retinaculares ou gânglios retinaculares volares, surgem a partir da bainha fibrosa que mantém os tendões flexores presos aos ossos dos dedos [1]. Eles ficam na base do dedo, na palma da mão; geralmente têm apenas alguns milímetros de diâmetro e são firmes, não macios.
O sintoma é característico e se explica facilmente quando se compreende a anatomia: dor ao segurar algo duro e estreito — um volante, um taco de golfe, o guidão de uma bicicleta ou a alça de uma sacola de compras. O cisto fica preso entre o objeto e o osso subjacente; não há tecido mole para amortecer a pressão, pois a bainha está diretamente ligada à falange.
É por isso que o tamanho do cisto tem pouca correlação com os sintomas. Um inchaço grande e macio na parte de trás do pulso pode ser indolor, enquanto uma lesão muito menor na base de um dedo pode realmente limitar os movimentos.
A mesma regra aplicável a qualquer outro cisto sinovial
O seu comportamento depende do que está conectado a ele. O cisto se origina da bainha do tendão e é preenchido por ela; portanto, a mecânica é a mesma dos cistos sinoviais do punho e dos cistos mucosos: a bolsa cística é apenas a manifestação visível do problema, não a sua origem.
Assim, a punção ou aspiração do cisto alivia o inchaço, mas não corrige a causa do vazamento. A recorrência após uma drenagem simples é comum; o tratamento definitivo consiste na excisão do cisto juntamente com a porção afetada da bainha tendinosa de onde ele se origina.
Por que a cirurgia é menos extensa do que parece, mas não é trivial
A excisão é um procedimento breve, realizado por meio de uma pequena incisão na base do dedo, sendo geralmente curativa. Dois aspectos anatômicos justificam a necessidade de cuidado nessa região.
Os nervos digitais percorrem imediatamente ao lado da bainha flexora, um de cada lado; na base do dedo, eles são superficiais e ficam próximos às estruturas da linha média que são removidas. O surgimento de uma área adormecida ao longo de uma das bordas do dedo é um risco conhecido de cirurgias pequenas nessa localização.
Em segundo lugar, apenas a porção redundante da bainha pode ser removida. As estruturas que fixam os tendões ao osso são responsáveis por suportar cargas; a perda de uma dessas estruturas críticas faz com que o tendão se afaste do dedo, enfraquecendo a força de preensão. Por isso, a excisão é deliberadamente limitada ao trecho da bainha que não exerce essa função.
Quando não é necessário intervir
Como essa lesão é benigna e não cresce indefinidamente, o tratamento é indicado apenas com base nos sintomas. Um cisto que é visível, mas não causa dor durante o aperto diário, não requer nenhum tipo de intervenção. O tratamento só é indicado quando uma atividade específica e repetida fica comprometida; esse é um indicador mais claro do que a maioria dos outros, pois a pessoa geralmente consegue identificar facilmente o tipo de movimento que desencadeia os sintomas.
Os cistos relacionados na articulação da ponta do dedo e no pulso são abordados em páginas separadas; o princípio comum a todos os três casos é que o “pedúnculo” do cisto, e não o próprio saco cístico, determina se o problema voltará a ocorrer.
Referências
[1] Foret AL, Chhabra AB. Ganglios na retinácula volar. J Hand Surg Am. 2012;37(3):566-7. https://doi.org/10.1016/j.jhsa.2011.05.013
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Epidemiology and Natural History
- Pediatric ganglions are more commonly found on the volar surface of the hand and wrist compared to adults [7].
- Pediatric ganglions more commonly have a tendon sheath origin compared to adults [7].
- Approximately 40% of wrist ganglion lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
Diagnosis
- Ultrasound is useful for assisting in the diagnosis of suspected flexor tendon sheath ganglions [1].
- Ultrasound is useful for determining whether patients with suspected flexor tendon sheath ganglions should undergo aspiration or surgical excision [1].
- Routine wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [21].
Non-Operative Management
- A nonsurgical approach to flexor tendon sheath ganglions is both cost-effective and successful [3].
- Most ganglions recur after aspiration [25].
- Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions given its low cost, lack of downtime, and low recurrence rate [5].
- No recurrences were observed after a second puncture in the cohort assessed for percutaneous puncture of flexor sheath ganglions [5].
Operative Management
- Surgical excision is a simple, safe, and effective method for treating a painful ganglion of the digital flexor tendon sheath [2].
- Surgical intervention for wrist ganglions has about a 10% recurrence rate [25].
- Surgical intervention for wrist ganglions leaves scars and has some risk for adverse events [25].
- Ultrasound-guided excision of flexor tendon sheath ganglion using a 2-mm portal under local anaesthesia was reliable and efficient without specific morbidity [4].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis and less soft tissue trauma [9].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy allows for the management of concomitant FCR tendon pathology [9].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy carries risks of recurrence and nerve or vessel injury [9].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the ganglion being distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [60].
Pediatric Management
- There is no consensus within the literature regarding the best management of pediatric wrist ganglia [22].
- No single treatment modality confers a particular advantage or disadvantage over another for pediatric wrist ganglia [22].
Anatomy & Pathophysiology
Flexor Tendon Sheath Anatomy
- The fibroosseous tunnel, or digital flexor sheath, extends distally from the metacarpal neck to the proximal aspect of the distal phalanx [75].
- The tendinous sheath consists of annular pulleys that provide mechanical stability and cruciate pulleys that provide flexibility [75].
- The A2 and A4 pulleys are situated over the middle portion of the proximal and middle phalanges, respectively [75].
- The A2 and A4 pulleys are the most essential in maintaining the mechanical advantage of the flexor tendons [75].
- The tenosynovium lining the fibroosseous tunnel supplies both nutrition and lubrication to the poorly vascularized flexor tendons [75].
- Within the sheath, tendon vascularity is supplied via the vincula system, specifically the vinculum longus and brevis [75].
- Anatomical studies have identified two annular and one oblique pulley in the thumb [91].
- A branch from the digital nerve enters the flexor tendon sheath at the same place as the transverse branch of the digital artery [8].
- The nerve branch entering the flexor tendon sheath supplies the nerve fibres found within the vinculum [8].
- The transverse branch of the digital artery enters the edge of the sheath to reach the area of the vinculum brevis [8].
Gliding Mechanisms and Biomechanics
- In narrow crowded areas, the gliding mechanism is assured by the synovial sheath, which allows a considerable amplitude of movement [76].
- Fibrous sheaths surrounding synovial sheaths keep the tendon close to the skeleton, particularly when the tendon crosses an articular angle [76].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [76].
- Each synovial sheath has a visceral and parietal component separated by a potential synovial cavity containing a very thin layer of synovial fluid [76].
- This synovial fluid constitutes the basic gliding and nutritional mechanism for the tendon [76].
- Diffusion is a significant nutrient pathway to the flexor tendon, supporting the importance of sheath closure at the time of tendon suture [36, 37].
- At half the total tendon excursion, the force required to flex the digit through half its range is always less than a third of the force required to flex the digit fully [46].
- The force required to fully flex the digit decreased with more extensive A1 pulley release, becoming significant when more than 50% of the pulley was released [97].
Pathophysiology of Triggering and Ganglions
- Triggering results from the loss of smooth gliding of a tendon within its tendon sheath [6].
- Inflammation of the synovium lining the tendon sheath interferes with the normal gliding mechanism [6].
- Interference with the gliding mechanism is especially troublesome at a point of change in direction of a tendon [6].
- Ganglions are defined as cystic swellings closely connected to joints or tendon sheaths which contain mucinous material [141].
- The etiology of ganglions is unknown [141].
- The articular (synovial) theory has gained worldwide acceptance as a scientifically proven explanation for the formation of intraneural ganglions [17].
- Triggering of the finger can occur secondary to a partial flexor tendon tear after closed direct injury [98].
Classification
- Volar wrist ganglions may arise from a variety of locations, unlike dorsal wrist ganglions which typically arise from a specific location at the dorsal margin of the scapholunate interosseous membrane [16].
- Approximately two thirds of anterior wrist ganglions reportedly arise from the radiocarpal joint [16].
- One third of anterior wrist ganglions reportedly arise from the scaphotrapezial joint [16].
- Ganglion cysts that arise from the flexor carpi radialis (FCR) sheath are often in a slightly more medial location, either just radial or palmar to the sheath [16].
- Ganglions arising from the FCR sheath are typically less mobile than ganglions arising from the wrist joint [16].
- Ganglions arising from the first extensor compartment tend to adhere to the sheath (extensor retinaculum) [16].
- Ganglions arising from the first extensor compartment tend to be quite firm and are less mobile [16].
- In children aged <10 years, ganglion cysts present on the volar aspect of the wrist [13].
- In patients aged >10 years, ganglions resemble those in the adult population and present on the dorsal aspect of the wrist [13].
Clinical Presentation
General Characteristics
- Ganglions are the most common cause of focal masses in the hand and foot [50].
- Ganglions commonly arise from the synovium of joints, tendon sheaths, or the epineurium of nerves [50].
- Ganglions are filled with synovial fluid that may become jelly-like over time [50].
- Most patients with intraneural ganglions present with a painless mass [17].
- Some patients with intraneural ganglions present with symptoms of nerve irritation or entrapment neuropathy [17].
- In many patients with intraneural ganglions, definitive diagnosis is made only at the time of surgery [17].
Volar Wrist and Hand
- Volar wrist ganglia tend to arise in the interval between the first extensor compartment and flexor carpi radialis (FCR) tendon sheath, just proximal to the wrist flexion crease [16].
- Volar wrist ganglia typically appear to be 1 to 2 cm in size but may be significantly larger at the time of surgical dissection [16].
- Patients with volar wrist ganglions often present with complaints of a mass that has been present for a number of months or years and is typically asymptomatic [16].
- Patients with volar wrist ganglions often note discomfort when the mass is "bumped" [16].
- Volar wrist ganglia are clinically compressible, slightly mobile, nontender, and visible when transilluminated [16].
- Volar wrist ganglia are nonpulsatile but are often intimate with the radial artery, which is palpable alongside the lesion [16].
- Approximately one third of anterior wrist ganglions reportedly arise from the scaphotrapezial joint [16].
- Ganglion cysts that arise from the FCR sheath are often in a slightly more medial location, either just radial or palmar to the sheath [16].
- Ganglion cysts arising from the FCR sheath are typically less mobile than ganglions arising from the wrist joint [16].
Pediatric Population
- In children aged <10 years, ganglion cysts are generally amenable to observation with spontaneous regression [13].
- Ganglions in pediatric populations most commonly affect the dorsal wrist [47].
- Ganglions in pediatric populations demonstrate a female predilection [47].
- Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist [52].
Diagnostic Imaging
- Ultrasound is useful for assisting in diagnosis and determining whether patients should undergo aspiration or surgical excision for suspected flexor tendon sheath ganglions [1].
- MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard [48].
- MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes [33].
- The use of the 3-dimensional FSE extended echo train MRI sequence, called cube, has revolutionized the visualization of intraneural ganglions and articular branches that connect them to the joint [17].
Investigations
Imaging Modalities
- The architecture and relationship of the FDS to FDP within the flexor sheath is accurately defined using a non-invasive imaging technique and the pulley system can be clearly imaged in cross-section [58].
- Sonography-guided wrist arthroscopy provides visualization of the ganglions and ganglion stalk, as well as of the arthroscopic shaver and adjacent structures such as nerves, vessels, and tendons to perform surgery safely [124].
- Sonography-assisted arthroscopy allows clear visualization of ganglia, vessels, nerves, and tendons, enabling safe guidance of the arthroscopic shaver to the lesion without blind resection [126].
Diagnostic Limitations and Utility
- The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [21].
- Radiologists are less likely to identify occult dorsal ganglion cysts on MRI if the cyst is smaller or if the requisition form does not mention a cyst [138].
Pathology and Histology
- In patients with the clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision of the ganglion cyst [27, 31].
Treatment
Non-Operative Management
- Ultrasound imaging assists in determining whether patients with suspected flexor tendon sheath ganglions should undergo aspiration or surgical excision [1].
- Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions due to its low cost, lack of downtime, and low recurrence rate [5].
- No recurrences were observed after a second percutaneous puncture in the cohort assessed for recurrence [5].
- Ganglion aspiration should be considered as a first-line intervention [55].
- Nonsurgical treatment is largely ineffective in treating ganglion cysts, though it may be considered for symptomatic relief in patients who do not want surgery [125].
- Aspiration, with or without cortisone injection, has an average success rate of 35% to 50% [122].
- Approximately 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
Operative Management
- Ultrasound-guided excision of flexor tendon sheath ganglions using a 2-mm portal under local anaesthesia was reliable and efficient without specific morbidity [4].
- Open surgical excision offers a significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions [135].
- Surgical intervention for ganglions has about a 10% recurrence rate [25].
- Surgical intervention for ganglions leaves scars and carries some risk for adverse events [25].
- In patients with a clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision [27, 31].
- Arthroscopic resection is an effective treatment strategy for intra-articular synovial ganglions refractory to conservative measures, providing complete resolution of symptoms and functional recovery with minimal soft tissue damage [119].
- Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia [120].
- Arthroscopic ganglionectomy is a safe and reliable alternative to open resection [140].
- At 12 months follow-up, the rates of recurrence with arthroscopic dorsal ganglion excision are comparable with and not superior to those of open excision [24].
- Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes [35].
- Recurrent ganglion cysts originating from the midcarpal joint are not contraindications for arthroscopic resection [38].
- Arthroscopy allows for the simultaneous treatment of ganglions and other pathologies [29].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis, less soft tissue trauma, and the ability to manage concomitant FCR tendon pathology [9].
- There was no impairment of wrist motion and function in all patients following arthroscopic resection of palmar ganglions [51].
- The key to successful open treatment of dorsal wrist ganglions is excision of the ganglion stalk based at the scapholunate ligament and its associated dorsal-capsular attachments [122].
- Open ganglionectomy creates a defect in the capsule of 1 to 1.5 cm, which is left open [122].
- Stiffness has been reported from prolonged immobilization following open ganglionectomy [122].
- The rate of recurrence for open ganglionectomy can be as high as 40% [122].
- Indications for surgery include pain, restricted motion, and/or aesthetic complaints as a result of the ganglion cyst [113].
- Ultrasound, magnetic resonance imaging, or X-rays are performed to confirm the presence of a ganglion cyst or to rule out other conditions when surgery is indicated [113].
- The operation for dorsal wrist ganglion excision is generally performed under regional anaesthesia and a tourniquet [113].
- A dorsal incision distal to Lister’s tubercle is used, with the extensor retinaculum between the tendons of the second and fourth extensor compartments incised [113].
- A small arthrotomy is performed over the scapholunate ligament, where the dorsal wrist ganglion usually originates [113].
- Complete excision of the ganglion along with its capsule is performed with local synovectomy [113].
- The capsule is either fenestrated or sutured, depending on the surgeon [113].
- A compressive dressing is applied after skin closure and left in place for 3 days [113].
- Active mobilization of the wrist starts after the hand therapist changes the dressing [113].
- Sutures are removed 10 to 14 days postoperatively [113].
- Splints are not used on a regular basis [113].
- Patients start with a stabilizing and strength programme under the guidance of the hand therapist after 3 weeks [113].
- In pediatric wrist ganglion excision, a transverse incision is made over the ganglion to expose the cyst's wall [123].
- Fluid is aspirated and 0.3e0.5 mL of methylene blue is injected into the cavity to facilitate dye penetration into the cyst wall [123].
- The base of the ganglion is ligated with a 4e0 absorbable suture [123].
- All blue-stained ganglion tissue is thoroughly resected [123].
- The wrist is immobilized with a plaster cast for 7 to 10 days following pediatric excision [123].
- Followup examinations occur monthly for 6 months and every 3 months thereafter [123].
- Recurrence is assessed within 48 months' follow-up by palpation alone [123].
- Patients undergoing initial pediatric excision had been treated conservatively for more than 1 year [123].
- Recurrence of the wrist ganglion cyst occurred in 9% of patients in a cohort of 53 arthroscopic resections [116].
- PRWE scores were significantly higher in patients with a recurrence (30 vs. 12, p = 0.002) [116].
- Patients initially presenting with a new ganglion cyst had fewer recurrences at final follow-up compared with patients initially presenting with recurrence (4 vs. 15%) [116].
- Asymptomatic ganglion cysts were left untreated in the arthroscopic cohort [116].
- One patient experienced neuropraxia of the radial superficial nerve, which resolved spontaneously [116].
- One patient developed extensor carpi ulnaris (ECU) tendinitis, which was successfully treated with splinting [116].
- One patient experienced painful scar tissue, which was successfully removed surgically [116].
Complications
- Surgical intervention for wrist ganglions carries a recurrence rate of approximately 10% [25].
- Surgical intervention for wrist ganglions leaves scars and carries some risk for adverse events [25].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the cyst, specifically when it is distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [60].
- Open surgical excision of pediatric wrist ganglions demonstrates minimal complications [13].
Recovery
Non-Operative Management
- No recurrences were observed after a second puncture in the cohort assessed for percutaneous puncture management [5].
- About 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
- In a child with a wrist ganglion, if the cyst ultimately resolved, it usually did so within 18 months [20].
Operative Management
- Surgical intervention has about a 10% recurrence rate [25].
- Surgical intervention leaves scars and has some risk for adverse events [25].
Key Evidence
- [L4] Ultrasound is useful for assisting in diagnosis and determining whether patients should undergo aspiration or surgical excision for suspected flexor tendon sheath ganglions. [1] (10.1016/s0363-5023(97)80043-3)
- [L4] Surgical excision is a simple, safe, and effective method for treating a painful ganglion of the digital flexor tendon sheath. [2] (10.1007/s11552-007-9028-4)
- [L4] A nonsurgical approach to flexor tendon sheath ganglions is both cost-effective and successful. [3] (10.1053/jhsu.2002.34318)
- [L4] The ultrasound-guided excision of flexor tendon sheath ganglion, using a 2-mm portal, under local anaesthesia was reliable and efficient, without specific morbidity. [4] (10.1016/j.hansur.2018.10.116)
- [L4] Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions given its low cost, lack of downtime, and low recurrence rate, with no recurrences observed after a second puncture in this cohort. [5] (10.1177/17531934221115983)
- [L5] [6] (10.1016/0266-7681(94)90139-2)
- [L4] Pediatric ganglions are more commonly found on the volar surface of the hand and wrist and more commonly have tendon sheath origin compared to adults. [7] (10.1007/s11552-008-9122-2)
- [L5] [8] (10.1016/0266-7681(91)90138-e)
- [Paper] Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis, less soft tissue trauma, and the ability to manage concomitant FCR tendon pathology, though it carries risks of recurrence and nerve or vessel injury. [9] (10.1016/j.eats.2017.06.002)
- [L4] [13] (10.1016/j.jhsa.2021.12.015)
- [L5] [16] (10.1016/j.hcl.2004.03.015)
- [L4] [17] (10.1016/j.jhsa.2015.05.025)
- [L4] In a child with a wrist ganglion, if the cyst ultimately resolved, it usually did so within 18 months. [20] (10.1016/j.jhsa.2019.10.032)
- [L4] The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings. [21] (10.1007/s11552-007-9032-8)
- [L4] There is no consensus within the literature regarding the best management of pediatric wrist ganglia, and no single treatment modality confers a particular advantage or disadvantage over another. [22] (10.1177/1558944720966716)
- [L1] At 12 months follow-up, the rates of recurrence with arthroscopic dorsal ganglion excision are comparable with and not superior to those of open excision. [24] (10.1016/j.jhsa.2008.01.009)
- [L5] Current best evidence suggests that about 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon, that most ganglions recur after aspiration, and that surgical intervention has about a 10% recurrence rate, leaves scars, and has some risk for adverse events. [25] (10.1016/j.jhsa.2010.11.048)
- [L3] This study suggests that, in patients with the clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision of the ganglion cyst. [27] (10.1016/j.jhsa.2010.03.021)
- [L4] Arthroscopy allows for the simultaneous treatment of ganglions and other pathologies. [29] (10.1016/j.jhsa.2012.04.042)
- [L4] In patients with the clinical diagnosis of wrist ganglion cyst, the quality of care would not be compromised by abandoning the practice of routine submission of surgical specimens for pathological examination after excision of the ganglion cyst. [31] (10.1016/s0363-5023(10)60107-4)
- [L4] MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes. [33] (10.1007/s11552-007-9083-x)
- [L3] Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes. [35] (10.1177/17531934251405730)
- [L5] The importance of sheath closure at the time of tendon suture is based in part on the evidence that diffusion is a significant nutrient pathway to the flexor tendon. [36] (10.1016/0266-7681(88)90077-0)
- [L5] The importance of sheath closure at the time of tendon suture is based in part on the evidence that diffusion is a significant nutrient pathway to the flexor tendon. [37] (10.1016/0266-7681_88_90077-0)
- [L4] Ganglion cysts also have a high association with certain interosseous laxities, and recurrent ganglion cysts originating from the midcarpal joint are not contraindications for arthroscopic resection. [38] (10.1016/j.jhsa.2008.11.025)
- [L5] At half the total tendon excursion, the force required to flex the digit through half its range is always less than a third of the force required to flex the digit fully. [46] (10.1016/0266-7681(90)90086-j)
- [L2] Ganglions in pediatric populations, which most commonly affect the dorsal wrist, demonstrate a female predilection. [47] (10.1016/j.jhsa.2021.02.026)
- [L3] MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard. [48] (10.1177/1753193408092041)
- [Case_report] [50] (10.1007/s12593-014-0117-7)
- [L4] There was no impairment of wrist motion and function in all patients. [51] (10.1016/j.main.2006.07.028)
- [L4] Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist. [52] (10.1016/j.jhsa.2023.07.002)
- [L4] Ganglion aspiration should be considered as a first-line intervention, with surgical excision remaining an effective option for symptomatic cases. [55] (10.1177/1753193411434376)
- [L5] The architecture and relationship of the FDS to FDP within the flexor sheath is accurately defined using a non-invasive imaging technique and the pulley system can be clearly imaged in cross-section. [58] (10.1016/j.jhsb.2005.08.001)
- [L3] The operation-related complications after arthroscopic volar wrist ganglionectomy are associated with its anatomical location: distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer. [60] (10.1186/s12891-025-08766-x)
- [L5] Anatomical studies have identified two annular and one oblique pulley in the thumb. [91] (10.1016/s0363-5023(77)80101-9)
- [L5] The force required to fully flex the digit decreased with more extensive A1 pulley release, becoming significant when more than 50% of the pulley was released. [97] (10.1016/s0266-7681(98)80217-9)
- [L5] This illustrates another post-traumatic mechanical cause for triggering of the finger. [98] (10.1016/0363-5023(93)90059-c)
- [L2] [113] (10.1177/17531934231153029)
- [L4] [116] (10.1055/s-0040-1716509)
- [L4] Arthroscopic resection is an effective treatment strategy for intra-articular synovial ganglions refractory to conservative measures, providing complete resolution of symptoms and functional recovery with minimal soft tissue damage. [119] (10.1016/j.jhsg.2024.05.007)
- [L4] Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia. [120] (10.1016/j.arthro.2009.08.021)
- [L4] [122] (10.1016/s0749-0712(21)00020-2)
- [L2] [123] (10.1016/j.jhsa.2015.01.015)
- [L4] Sonography-guided wrist arthroscopy provides several advantages for surgeons, including visualization of the ganglions and ganglion stalk, as well as of the arthroscopic shaver and adjacent structures such as nerves, vessels, and tendons to perform surgery safely. [124] (10.1016/j.jhsa.2012.04.012)
- [L4] Nonsurgical treatment is largely ineffective in treating ganglion cysts, though it may be considered for symptomatic relief in patients who do not want surgery. [125] (10.1155/2013/940615)
- [Paper] Sonography-assisted arthroscopy allows clear visualization of ganglia, vessels, nerves, and tendons, enabling safe guidance of the arthroscopic shaver to the lesion without blind resection. [126] (10.1016/j.eats.2011.12.007)
- [L1] Open surgical excision offers significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions. [135] (10.1016/j.jhsa.2014.12.014)
- [L3] Radiologists are less likely to identify occult dorsal ganglion cysts on MRI if the cyst is smaller or if the requisition form does not mention a cyst. [138] (10.1055/s-0039-1683847)
- [L4] Arthroscopic ganglionectomy is a safe and reliable alternative to open resection. [140] (10.1016/j.jhsa.2003.10.018)
- [L4] [141] (10.2106/00004623-197254070-00009)
References
[1] Treatment of flexor tendon sheath ganglions using ultrasound imaging. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80043-3
[2] Flexor Tendon Sheath Ganglions: Results of Surgical Excision. HAND. 2007. DOI: 10.1007/s11552-007-9028-4
[3] Management of flexor tendon sheath ganglions: A cost analysis. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.34318
[4] Flexor tendon sheath ganglions — A new procedure to perform excision under ultrasound-guidance. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.116
[5] Percutaneous puncture of flexor sheath ganglions: an assessment of recurrence. Journal of Hand Surgery (European Volume). 2022. DOI: 10.1177/17531934221115983
[6] Extensor Tendon Sheath Stenosis Resulting in Triggering of the Little Finger. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90139-2
[7] Pediatric Ganglion Cysts of the Hand and Wrist: An Epidemiologic Analysis. HAND. 2008. DOI: 10.1007/s11552-008-9122-2
[8] Anatomical Demonstration of the Nerve-Supply to the Flexor Tendon. Journal of Hand Surgery. 1991. DOI: 10.1016/0266-7681(91)90138-e
[9] Endoscopic Ganglionectomy of Palmar Ganglion via Flexor Carpi Radialis Tendoscopy. Arthroscopy Techniques. 2017. DOI: 10.1016/j.eats.2017.06.002
[13] Pediatric Ganglions of the Hand and Wrist: A Review of Current Literature. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.12.015
[16] Ganglion cysts and other tumor related conditions of the hand and wrist. Hand Clinics. 2004. DOI: 10.1016/j.hcl.2004.03.015
[17] Intraneural Ganglions of the Hand and Wrist. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.05.025
[20] Wrist Ganglia in Children: Nonsurgical Versus Surgical Treatment. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.10.032
[21] The Use of Routine Wrist Radiography is Not Useful in the Evaluation of Patients with a Ganglion Cyst of the Wrist. HAND. 2007. DOI: 10.1007/s11552-007-9032-8
[22] Wrist Ganglion Cysts in Children: An Update and Review of the Literature. HAND. 2022. DOI: 10.1177/1558944720966716
[24] Arthroscopic Versus Open Dorsal Ganglion Excision: A Prospective, Randomized Comparison of Rates of Recurrence and of Residual Pain. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.01.009
[25] Wrist Ganglions. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2010.11.048
[27] Necessity of Routine Pathological Examination After Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.03.021
[29] Ganglions of the Wrist and Associated Triangular Fibrocartilage Lesions: A Prospective Study in Arthroscopically-treated Patients. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.04.042
[31] Necessity of Routine Pathological Examination following Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/s0363-5023(10)60107-4
[33] Compression Neuropathy of the Radial Nerve Due to Ganglion Cysts. HAND. 2008. DOI: 10.1007/s11552-007-9083-x
[35] Arthroscopic resection of dorsal wrist ganglions with or without midcarpal exploration. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251405730
[36] Flexor tendon healing. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90077-0
[37] Flexor Tendon Healing. Journal of Hand Surgery. 1988. DOI: 10.1016/0266-7681_88_90077-0
[38] Prospective Outcomes and Associations of Wrist Ganglion Cysts Resected Arthroscopically. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.11.025
[46] The Mechanical Effect of Partial Resection of the Digital Fibrous Flexor Sheath. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681(90)90086-j
[47] Clinical Presentation and Characteristics of Hand and Wrist Ganglion Cysts in Children. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.02.026
[48] Magnetic Resonance Imaging in the Diagnosis of Occult Dorsal Wrist Ganglions. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408092041
[50] Intraneural Ganglion of Digital Nerve of Thumb: A Case Report and Review of Literature. Journal of Hand and Microsurgery. 2015. DOI: 10.1007/s12593-014-0117-7
[51] Résection des kystes synoviaux palmaires par arthroscopie. Chirurgie de la Main. 2006. DOI: 10.1016/j.main.2006.07.028
[52] Natural History of Pediatric Hand and Wrist Ganglion Cysts: Longitudinal Follow-Up of a Prospective, Dual-Center Cohort. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.002
[55] Patient outcomes following wrist ganglion excision surgery. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193411434376
[58] Mri ‘Magic Angle’ Imaging of Finger Tendons. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.08.001
[60] Anatomical location of volar wrist ganglion in preoperative MRI is a risk factor for operation-related complications after arthroscopic ganglionectomy. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08766-x
[75] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[76] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.
[91] Anatomy of the flexor tendon sheath and pulleys of the thumb. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80101-9
[97] The Effect of the Extent of A1 Pulley Release on the Force Required to Flex the Digits. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80217-9
[98] Triggering of the finger secondary to partial flexor tendon tear after closed direct injury. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90059-c
[113] Factors associated with self-reported pain and hand function following dorsal wrist ganglion excision. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231153029
[116] Patient-Related Outcomes of Arthroscopic Resection of Ganglion Cysts of the Wrist. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1716509
[119] Intra-articular Synovial Ganglion of the Wrist. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.05.007
[120] Arthroscopic Ganglionectomy Through an Intrafocal Cystic Portal for Wrist Ganglia. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.08.021
[122] ARTHROSCOPIC RESECTION OF DORSAL GANGLION OF THE WRIST. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00020-2
[123] Visualization of the Wrist Ganglion Capsule by Methylene Blue Staining as an Aid for Complete Resection in Children. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.01.015
[124] Sonography-guided Arthroscopy for Wrist Ganglion. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.04.012
[125] Treatment of Ganglion Cysts. ISRN Orthopedics. 2013. DOI: 10.1155/2013/940615
[126] Sonography‐Assisted Arthroscopic Resection of Volar Wrist Ganglia: A New Technique. Arthroscopy Techniques. 2012. DOI: 10.1016/j.eats.2011.12.007
[135] Wrist Ganglion Treatment: Systematic Review and Meta-Analysis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.014
[138] Radiologist Identification of Occult Dorsal Wrist Ganglion Cysts on MRI. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1683847
[140] Arthroscopic resection in the management of dorsal wrist ganglions: results with a minimum 2-year follow-up period. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.10.018
[141] Ganglions of the Wrist and Hand. The Journal of Bone & Joint Surgery. 1972. DOI: 10.2106/00004623-197254070-00009