Patients › General-Health
Plasma rico em plaquetas (PRP) e terapias injetáveis
What the evidence shows for platelet-rich plasma and related injection therapies in tendinopathy, osteoarthritis and rotator cuff disease — where they help and where the data is weak.
O que é
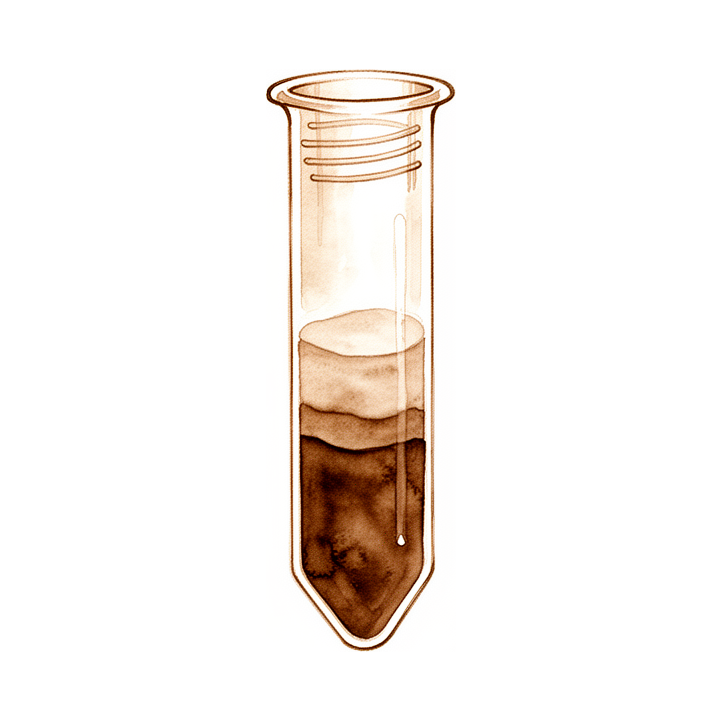
O plasma rico em plaquetas, muitas vezes abreviado como PRP, é um tratamento feito a partir do seu próprio sangue. Uma pequena amostra do seu sangue é girada em uma máquina para que as plaquetas sejam separadas e concentradas. As plaquetas são as pequenas partes do sangue que ajudam na coagulação, e elas também carregam fatores de crescimento, que são substâncias naturais que podem favorecer a cicatrização. As plaquetas concentradas são então injetadas na área dolorida.
O seu médico pode considerar o PRP para problemas como a artrose do joelho (artrite do desgaste), problemas de tendões no cotovelo, no ombro ou no punho e algumas lesões musculares no esporte. Ele não é usado para todas as condições. No cotovelo de tenista, as evidências são mistas: alguns estudos verificaram que o PRP funcionou melhor do que as injeções de corticoide a longo prazo [1], enquanto uma revisão de ensaios clínicos não confirmou que ele seja melhor do que o placebo [2]. Na artrose do joelho, muitas vezes são recomendadas duas injeções, com efeitos que duram pelo menos 24 semanas [3]. Na síndrome do túnel do carpo, o PRP mostrou benefícios mais duradouros do que uma injeção de corticoide no acompanhamento de 6 meses [4].
A ideia por trás do PRP é que os fatores de crescimento das plaquetas podem reduzir a inflamação e estimular o reparo dos tecidos. As pesquisas ainda estão esclarecendo os detalhes. Os estudos mostram que preparações diferentes se comportam de formas diferentes: um tipo rico em glóbulos brancos parece adequado para a artrose em fase inicial, enquanto outro, com mais plaquetas e menos glóbulos brancos, pode ser adequado para fases mais avançadas [5]. Alguns ensaios clínicos verificaram que o PRP funcionou melhor do que as injeções de anestésico em problemas dos tendões do ombro e do cotovelo, mas não melhor do que o agulhamento seco ou as injeções de água com sal [6]. De modo geral, as evidências variam de uma condição para outra, e o seu médico vai conversar com você sobre se o PRP faz sentido para o seu problema específico.
Funciona mesmo?
A resposta honesta é que depende da condição e, em alguns casos, as pesquisas ainda estão se atualizando. Uma revisão das evidências concluiu que o PRP é um tratamento potencialmente interessante, mas que ainda não há pesquisas de boa qualidade suficientes para apoiar o seu uso amplo [7]. Os pesquisadores também observaram que alguns resumos de ensaios clínicos sobre o PRP na artrose do joelho apresentam os seus resultados de forma excessivamente positiva, o que pode fazer o tratamento parecer melhor do que as evidências realmente mostram [8].
Para algumas condições, os resultados são mais animadores. Nos problemas de tendões, ensaios clínicos verificaram que o PRP melhorou a dor e o funcionamento da parte afetada, e funcionou melhor do que as injeções de corticoide a médio prazo [9]. Na artrose do joelho, o PRP melhorou a função geral, principalmente em pessoas mais jovens [10]. A combinação do PRP com o ácido hialurônico, uma substância lubrificante encontrada naturalmente nas articulações, proporcionou mais alívio da dor e melhor função do que o PRP sozinho [11].
Para outras condições, o quadro é misto ou incerto. No cotovelo de tenista, alguns ensaios clínicos verificaram que o PRP reduziu a dor e melhorou a função nos primeiros meses [12], enquanto outras pesquisas não o apoiaram como tratamento [2]. Nas rupturas do manguito rotador, não há evidências de boa qualidade suficientes para dizer se ele ajuda ou não [13]. Na cartilagem do joelho danificada, as evidências ainda não apoiam as injeções de PRP isoladamente [14].
O que isso significa para você? O PRP pode ajudar em alguns problemas, mas não é uma solução comprovada para tudo. O seu médico vai explicar o que as evidências mostram para a sua condição específica, para que vocês possam decidir juntos se vale a pena tentar.
Quais são os riscos?
O PRP é feito a partir do seu próprio sangue, por isso é pouco provável que o seu corpo reaja mal ao material em si. Isso não significa que o tratamento seja isento de riscos. A própria injeção pode causar dor, inchaço e rigidez nos dias seguintes, e a área tratada pode ficar dolorida antes de melhorar. O seu médico vai orientar você sobre como lidar com isso.
As pesquisas sobre o PRP na artrose do joelho ainda não resolveram a questão de quão bem ele funciona, e alguns resumos publicados apresentaram os seus resultados de forma excessivamente positiva [8]. Isso importa quando você está avaliando se deve seguir em frente, porque um tratamento que parece promissor pode não trazer o alívio que você espera. No reparo do manguito rotador, acrescentar PRP aumentou as taxas de cicatrização, mas não mudou o quanto os pacientes conseguiam usar o ombro no dia a dia [15]. Nos problemas do tendão de Aquiles, ensaios clínicos verificaram que o PRP não funcionou melhor do que o placebo [16].
A forma como o seu corpo responde também pode depender das suas circunstâncias. Injeções anteriores de corticoide e o uso de tabaco parecem reduzir a eficácia do PRP na epicondilite medial crônica, um problema de tendão na parte de dentro do cotovelo [17]. Se você fuma ou já recebeu injeções de corticoide na mesma área, mencione isso antes de decidir sobre o tratamento.
Algumas questões continuam em aberto. Os pesquisadores observaram que são necessários mais estudos para confirmar os efeitos do PRP a longo prazo [18]. Os estudos sobre o PRP no cotovelo de tenista mostraram resultados mistos: alguns ensaios clínicos relataram alívio precoce da dor e melhora da função [12], e outros não encontraram benefício claro em relação ao placebo [2]. Também ainda não há evidências de boa qualidade suficientes para apoiar as injeções de PRP isoladamente na cartilagem do joelho danificada [14].
Se você notar aumento da dor, da vermelhidão ou do calor ao redor do local da injeção nos dias após o tratamento, entre em contato com o consultório para que possamos examinar. O seu médico vai conversar com você sobre os riscos específicos da sua condição antes de você decidir se vai seguir em frente.
É a opção certa para você?
O PRP costuma ser mais adequado para algumas pessoas do que para outras. Se você tem artrose do joelho (artrite do desgaste), recomendam-se pelo menos duas injeções, com efeitos que duram pelo menos 24 semanas [3]. Se você pratica esporte competitivo, os pesquisadores recomendaram oferecer a terapia com PRP a praticantes de esportes de competição [19]. Se você tem síndrome do túnel do carpo nos dois punhos, o PRP mostrou benefícios mais duradouros do que uma injeção de corticoide no acompanhamento de 6 meses [4].
Há situações em que o PRP tem menos probabilidade de ser a escolha certa. Se você tem cartilagem danificada no joelho, as evidências ainda não apoiam as injeções de PRP isoladamente [14]. No cotovelo de tenista, as evidências são mistas, então ele pode ou não ajudar você. Se você fuma ou já recebeu injeções de corticoide na mesma área, o PRP pode funcionar menos bem para você.
O PRP é uma opção entre várias. As injeções de corticoide são a principal alternativa para algumas condições, e o PRP mostrou benefícios mais duradouros do que os corticoides em alguns casos [4]. Outra opção é o ácido hialurônico, uma substância lubrificante encontrada naturalmente nas articulações. As pesquisas que comparam os dois ainda estão em fase inicial, então o seu médico vai explicar o que se sabe até agora.
Esta deve ser uma decisão compartilhada entre você e o seu médico. Pense nos seus objetivos, na sua condição e no que as evidências mostram sobre ela. O seu médico vai conversar com você sobre as opções, incluindo os riscos descritos na seção acima, para que vocês possam decidir juntos se o PRP faz sentido para você.
Conclusão
Vale a pena considerar o PRP para alguns problemas, mas com expectativas realistas. Ele pode aliviar a dor e melhorar a função na artrose do joelho e em algumas condições dos tendões, embora os resultados variem de pessoa para pessoa. A ressalva mais importante é que as pesquisas ainda estão se atualizando e, para várias condições, ainda não há evidências de boa qualidade suficientes para apoiar o seu uso amplo [7]. O seu médico vai ajudar você a avaliar se ele faz sentido para o seu problema específico.
Referências
[1] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[2] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[3] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[4] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[5] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[6] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[7] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[8] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[9] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[10] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[11] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[12] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[13] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[14] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[15] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[16] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[17] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[18] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[19] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- PRP remains a potentially interesting intervention for chronic tennis elbow but currently lacks sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- At least two PRP injections are recommended for treating knee osteoarthritis, with effects lasting for at least 24 weeks [2].
- The conclusions of the study on PRP for knee osteoarthritis do not provide a conclusive statement but aim to stimulate further research and shed light on factors influencing efficacy in clinical practice [3].
- There is no definitive evidence regarding the effectiveness of PRP treatment when the literature is evaluated [4].
- Further studies are needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future [5].
- Conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [6].
- Future studies should prioritize long-term outcomes to guide clinical decision-making more effectively [6].
- Both leukocyte-rich (L-PRP) and leukocyte-poor (LP-PRP) are effective treatment options with comparable efficacy based on current evidence [7].
- PRP was superior to anesthetics in 2 studies for shoulder and elbow tendinopathy [8].
- PRP showed no clinical efficacy compared with dry needling or saline injections in 3 studies for shoulder and elbow tendinopathy [8].
- Interventions employing PRP, MSCs, and exosomes are considered in the context of degenerative osteoarthritis as a reversible chronic disease [9].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [10].
- The authors recommend systematically offering PRP therapy for competition sports practitioners [11].
- PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection for gluteal tendinopathy [12].
- The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO [13].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in bilateral moderate carpal tunnel syndrome [14].
- Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease [15].
- There is insufficient evidence to recommend for or against the use of PRP for rotator cuff tears given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant [16].
- Current evidence supports the selective use of PRP in sports settings for acute muscle injuries, though standardization in protocols and outcomes is needed [18].
- Studies evaluating the outcomes and procedures of the use of PRP in the setting of lateral epicondylitis have poor adherence to MIBO guidelines [22].
- The statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
- Findings from a meta-analysis of randomized clinical trials do not support PRP as a recommended treatment for lateral epicondylitis as compared with placebo [27].
- It is recommended to wait for at least one month before considering another injection or alternative treatments for first presentation trigger digits [28].
- The authors do not support the routine use of PRP for the treatment of greater trochanteric pain syndrome [29].
How It Works
Tendinopathy and Soft Tissue
- PRP was superior to anesthetics in 2 studies but showed no clinical efficacy compared with dry needling or saline injections in 3 studies for shoulder and elbow tendinopathy [8].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis [23].
- High-dose PRP showed significant efficacy over alternative treatment strategies for lateral epicondylitis [23].
- Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months for lateral elbow tendinopathy [20].
- PRP is no more effective than placebo for treating Achilles tendinopathy [21].
- Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP for chronic medial epicondylitis [35].
- Time-dependent growth factor kinetics and platelet concentration influence clinical response following PRP versus saline in chronic tenosynovitis [10].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo for chronic tenosynovitis [10].
- PRP enhances anabolic gene expression patterns in flexor digitorum superficialis tendons [34].
- An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations [32].
Osteoarthritis
- At least two PRP injections are recommended for knee osteoarthritis, with effects lasting for at least 24 weeks [2].
- Both leukocyte-rich PRP (L-PRP) and leukocyte-poor PRP (LP-PRP) are effective treatment options with comparable efficacy for knee osteoarthritis based on current evidence [7].
- Optimizing osteoarthritis treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects [36].
- High platelet, low leukocyte PRP is preferred for advanced osteoarthritis to promote tissue repair and regeneration [36].
- The improvement from PRP injections for knee osteoarthritis is clinically significant and influenced by platelet concentration [3].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection for bilateral moderate carpal tunnel syndrome [14].
- The study compared the efficacy of intra-articular injections of platelet-rich plasma (PRP) and viscosupplementation (hyaluronic acid [HA]) for the treatment of knee degenerative cartilage lesions and osteoarthritis [19].
- The authors recommend systematically offering PRP therapy for competition sports practitioners with large joint osteoarthritis [11].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future for hypertrophic facet joints [5].
Fracture Healing and Nonunion
- The effectiveness rate for excellent and good limb function was 85.19% in the combined group (PRP plus extracorporeal shock wave) versus 60.71% in the PRP group for long diaphysis aseptic nonunion [25].
- At final follow-up, all patients in the PRP-enhanced group healed, while 80.49% of the non-PRP group healed for aseptic femoral shaft nonunion (p = 0.049) [37].
- Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of a specific study on delayed union or non-union [31].
Rotator Cuff Repair
- LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes for rotator cuff repair [40].
- The authors state that the significant difference in the retear rate, even in an underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP) for arthroscopic repair of medium to large rotator cuff tears [26].
General Mechanisms and Evidence Status
- PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use for chronic tennis elbow [1].
- The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [6].
- Future studies should prioritize long-term outcomes to guide clinical decision-making more effectively for PRP [6].
- The goal of a specific study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations [33].
- The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA [17].
- The PRP used in a specific study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP [38].
What the Evidence Shows
Tendinopathy and Soft Tissue Injuries
- A meta-analysis of randomized clinical trials found that PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [21].
- A meta-analysis of randomized clinical trials found that PRP does not improve pain or function in patients with lateral epicondylitis as compared with placebo and does not support PRP as a recommended treatment for this condition [27].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis, with high-dose PRP showing significant efficacy over alternative treatment strategies [23].
- PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis in the early follow-up period [45].
- After autologous blood injection therapy, 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity for refractory lateral epicondylitis [47].
- PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids [43].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in patients with bilateral moderate carpal tunnel syndrome [14].
Osteoarthritis
- A double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee osteoarthritis [41].
- Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary osteoarthritis, particularly in younger individuals [46].
- For patients with knee osteoarthritis, PRP combined with hyaluronic acid (HA) therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy [44].
- The combination of PRP with non-crosslinked HA in mono-injection was found to be non-inferior to crosslinked HA, with regards to the percentage of responders over 6 months (WOMAC pain) for knee osteoarthritis [49].
- Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP [48].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the treatment of hypertrophic facet joints [5].
Rotator Cuff and Shoulder
- Among level 1 RCTs reporting VAS pain scores after PRP injection for partial-thickness rotator cuff tears, platelet concentration was not significantly associated with improved pain outcomes [50].
Other Indications and Methodology
- The application of PRP following core decompression results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to core decompression alone for early osteonecrosis of the femoral head [42].
- Current evidence is insufficient to support orthobiologic injections adjunctive to cartilage-preserving surgery as standalone procedures for focal knee chondral defects [30].
Practical Considerations
General Evidence Status and Research Needs
- PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- There is no definitive evidence regarding the effectiveness of PRP treatment [4].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future [5].
- Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed [18].
Dosing, Protocol, and Preparation
- At least two PRP injections are recommended, with effects lasting for at least 24 weeks [2].
- Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence [7].
Indication-Specific Outcomes and Comparisons
- These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [10].
- PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [21].
- There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant for rotator cuff tears [16].
- The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost after arthroscopic rotator cuff repair [39].
- Current evidence is insufficient to support orthobiologic injections as standalone procedures for focal knee chondral defects [30].
Methodological and Interpretive Caveats
- The conclusions of a study on intra-articular PRP injections for knee osteoarthritis do not intend to provide a conclusive statement but rather to stimulate further research [3].
- The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
Key Evidence
- [L5] The authors conclude that PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use. [1] (10.1177/0363546513512784)
- [L3] At least two PRP injections are recommended, with effects lasting for at least 24 weeks. [2] (10.1186/s13018-025-05756-6)
- [Paper] The conclusions of this study do not intend to provide a conclusive statement but rather to stimulate further research in this complex field and contribute to shedding light on the several aspects influencing the efficacy of intra-articular platelet-rich plasma (PRP) injections for knee osteoarthritis (OA) in clinical practice. [3] (10.1177/03635465251387701)
- [L5] When the literature is evaluated, it is understood that there is no definitive evidence regarding the effectiveness of PRP treatment. [4] (10.1177/23259671241255700)
- [L4] Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future. [5] (10.5435/jaaosglobal-d-24-00140)
- [L5] The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up; future studies should prioritize long-term outcomes to guide clinical decision-making more effectively. [6] (10.1016/j.arth.2025.05.007)
- [L1] Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence. [7] (10.1186/s13018-026-06689-4)
- [L1] PRP was superior to anesthetics in 2 studies but showed no clinical efficacy compared with dry needling or saline injections in 3 studies. [8] (10.1097/bte.0000000000000118)
- [L5] Interventions employing PRP, MSCs and exosomes are considered in this article. [9] (10.1016/j.reth.2020.07.007)
- [L1] These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo. [10] (10.1186/s12891-025-09339-8)
- [L4] The authors recommend systematically offering PRP therapy for competition sports practitioners. [11] (10.1186/s12891-025-08663-3)
- [L5] The authors state that the conclusion of the referenced randomized controlled trial is that PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection. [12] (10.1177/0363546518773719)
- [Paper] The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO. [13] (10.1177/03635465231203202)
- [L1] PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up. [14] (10.1016/j.injury.2026.113018)
- [Paper] Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease. [15] (10.1177/03635465251395284)
- [L5] There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant. [16] (10.1177/0363546520918190)
- [L5] The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA. [17] (10.1177/0363546514537991)
- [L2] Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed. [18] (10.1177/23259671251399907)
- [L1] Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months. [20] (10.1177/23259671251386862)
- [L1] PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge. [21] (10.1097/corr.0000000000003478)
- [L2] This review demonstrated that studies evaluating the outcomes and procedures of the use of PRP in the setting of LE have poor adherence to MIBO guidelines. [22] (10.5397/cise.2024.01060)
- [L1] A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection, with high-dose PRP showing significant efficacy over alternative treatment strategies. [23] (10.1016/j.jisako.2025.100442)
- [L5] The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations. [24] (10.1177/0363546517703364)
- [L1] The effectiveness rate for excellent and good limb function was 85.19% in the combined group versus 60.71% in the PRP group. [25] (10.1016/j.otsr.2022.103417)
- [L5] The authors state that the significant difference in the retear rate, even in this underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP). [26] (10.1177/0363546515625958)
- [L1] These findings do not support PRP as a recommended treatment for this condition. [27] (10.1177/03635465251383039)
- [L3] It is recommended to wait for at least one month before considering another injection or alternative treatments. [28] (10.1142/s2424835520500253)
- [L1] As a result, we do not support the routine use of PRP for the treatment of this condition. [29] (10.2106/jbjs.24.00763)
- [L2] Current evidence is insufficient to support such injections as standalone procedures. [30] (10.1002/arj.70548)
- [L4] Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of the current study. [31] (10.1016/s0020-1383(13)70158-x)
- [L5] An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations. [32] (10.1016/s0020-1383(14)70004-x)
- [L5] The goal of the study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations. [33] (10.1177/03635465231206930)
- [Paper] These findings support in vivo investigation of PRP as an autogenous, patient-side treatment for tendonitis. [34] (10.1002/jor.20278)
- [L4] Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP. [35] (10.1177/1753193414567012)
- [L1] Optimizing OA treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects and high platelet, low leukocyte PRP preferred for advanced OA to promote tissue repair and regeneration. [36] (10.1186/s13018-025-06026-1)
- [L3] At final follow-up, all patients in Group 1 (PRP-enhanced) healed, while 80.49% of Group 2 (non-PRP) healed (p = 0.049). [37] (10.1016/j.injury.2025.112325)
- [L5] The authors also highlight that the PRP used in the study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP. [38] (10.1177/0363546514537996)
- [L1] The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost. [39] (10.1016/j.jse.2026.02.018)
- [L1] Consequently, LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes. [40] (10.1002/arj.70537)
- [L1] This double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee OA. [41] (10.1177/03635465241283500)
- [L3] The application of PRP following CD results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to CD alone. [42] (10.1186/s12891-024-08243-x)
- [L1] PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids. [43] (10.1186/s12891-025-08566-3)
- [L1] This meta-analysis reveals that, for patients with KOA, PRP + HA therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy. [44] (10.1186/s13018-024-05429-w)
- [L4] PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis. [45] (10.1177/2325967125s00169)
- [L1] Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary OA, particularly in younger individuals. [46] (10.1186/s12891-026-09486-6)
- [L4] After autologous blood injection therapy 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity. [47] (10.1053/jhsu.2003.50041)
- [L1] Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP. [48] (10.1002/arj.70027)
- [L1] The combination of PRP with non-crosslinked HA in mono-injection was found to be non-inferior to crosslinked HA, with regards to the percentage of responders over 6 months (WOMAC pain). [49] (10.1186/s12891-026-09625-z)
- [L1] Among level 1 RCTs reporting VAS pain scores after PRP injection for partial-thickness rotator cuff tears, platelet concentration was not significantly associated with improved pain outcomes. [50] (10.1177/23259671261480483)
References
[1] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[2] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[3] PRP Injections for the Treatment of Knee Osteoarthritis: The Improvement Is Clinically Significant and Influenced by Platelet Concentration: Response. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251387701
[4] Comparison of Conventional Dose Versus Superdose Platelet-Rich Plasma for Knee Osteoarthritis: Letter to the Editor. Orthopaedic Journal of Sports Medicine. 2024. DOI: 10.1177/23259671241255700
[5] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[6] Letter Regarding “Platelet-Rich Plasma Injections are Inferior to Corticosteroid Injections for Short-Term Pain Relief: A Prospective, Double-Blinded, Randomized Controlled Trial”. The Journal of Arthroplasty. 2025. DOI: 10.1016/j.arth.2025.05.007
[7] Leukocyte-rich versus leukocyte-poor platelet-rich plasma and hyaluronic acid for knee osteoarthritis: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06689-4
[8] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[9] Degenerative osteoarthritis a reversible chronic disease. Regenerative Therapy. 2020. DOI: 10.1016/j.reth.2020.07.007
[10] Time-dependent growth factor kinetics, platelet concentration, and clinical response following platelet-rich plasma versus saline in chronic tenosynovitis: a randomized controlled trial. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09339-8
[11] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
[12] The Effectiveness of Platelet-Rich Plasma Injections in Gluteal Tendinopathy: Response. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518773719
[13] Improving Injectable Orthobiologics Reporting Guidelines Adherence: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231203202
[14] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[15] Platelet-Rich Plasma in the Treatment of Musculoskeletal Disease in 2025 and Beyond. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251395284
[16] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[17] The Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Patel and Dhillon. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537991
[18] Platelet-Rich Plasma in Acute Muscle Injuries: An Umbrella Review and Meta-analysis of Return to Sport and Reinjury Outcomes. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251399907
[19] Platelet-Rich_Plasma_Versus_Hyaluronic_Acid_S0749806312015812. 2015.
[20] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[21] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[22] Adherence rates to the Minimum Information for Studies Evaluating Biologics in Orthopedics guidelines for clinical studies on platelet-rich plasma for the treatment of lateral epicondylitis: a systematic review. Clinics in Shoulder and Elbow. 2026. DOI: 10.5397/cise.2024.01060
[23] Platelet Concentration Factor Explains Variability in Outcomes of Platelet-rich Plasma for Lateral Epicondylitis: High Dose Critical for Positive Response. Journal of ISAKOS. 2025. DOI: 10.1016/j.jisako.2025.100442
[24] Hyaluronic Acid Versus Platelet-rich Plasma: Response. The American Journal of Sports Medicine. 2017. DOI: 10.1177/0363546517703364
[25] Synergistic effects of autologous platelet-rich plasma combined with an extracorporeal shock wave in treatment of long diaphysis aseptic nonunion. Orthopaedics & Traumatology: Surgery & Research. 2024. DOI: 10.1016/j.otsr.2022.103417
[26] PRP for Arthroscopic Repair of Medium to Large Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2016. DOI: 10.1177/0363546515625958
[27] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[28] Time to Resolution of Triggering after Steroid Injection for First Presentation Trigger Digits. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520500253
[29] Efficacy of Platelet-Rich Plasma Versus Placebo for the Treatment of Greater Trochanteric Pain Syndrome. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00763
[30] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[31] PS9 Is platelet-rich plasma injection an effective choice in cases of delayed union or non-union?. Injury. 2013. DOI: 10.1016/s0020-1383(13)70158-x
[32] Muscle repair: platelet-rich plasma derivates as a bridge from spontaneity to intervention. Injury. 2014. DOI: 10.1016/s0020-1383(14)70004-x
[33] The Accurate Characterization of Platelet-Rich Plasma Enables Its Classification and Comparison: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231206930
[34] Platelet rich plasma (PRP) enhances anabolic gene expression patterns in flexor digitorum superficialis tendons. Journal of Orthopaedic Research. 2006. DOI: 10.1002/jor.20278
[35] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[36] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[37] Based on the diamond concept, application of platelet-rich plasma in the treatment of aseptic femoral shaft nonunion: A retrospective controlled study on 66 patients. Injury. 2025. DOI: 10.1016/j.injury.2025.112325
[38] Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Andia and Maffulli. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537996
[39] Leukocyte-poor platelet-rich plasma reduces retear risk after arthroscopic rotator cuff repair: a meta-analysis with mechanistic and economic evaluation. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.018
[40] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[41] Leukocytes Do Not Influence the Safety and Efficacy of Platelet-Rich Plasma Injections for the Treatment of Knee Osteoarthritis: A Double-Blind Randomized Controlled Trial. The American Journal of Sports Medicine. 2024. DOI: 10.1177/03635465241283500
[42] Efficacy of small-diameter core decompression with platelet-rich plasma in early osteonecrosis of the femoral head: a retrospective study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08243-x
[43] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[44] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[45] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[46] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[47] Autologous blood injections for refractory lateral epicondylitis. The Journal of Hand Surgery. 2003. DOI: 10.1053/jhsu.2003.50041
[48] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[49] Efficacy and safety of a combination of platelet-rich plasma with non-crosslinked hyaluronic acid versus a crosslinked hyaluronic acid, in single-injection for knee osteoarthritis. Randomized, controlled, multicenter, non-inferiority trial. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09625-z
[50] Platelet Concentration Is Not Associated With Improved Pain for Partial-Thickness Rotator Cuff Tears Treated With Platelet-Rich Plasma: A Systematic Review and Meta-analysis With Meta-regression of Level 1 Randomized Controlled Trials. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671261480483