Patients › Wrist
Redução e fixação interna da extremidade distal do rádio
Open reduction and volar plate fixation of the distal radius — operation, recovery, rehabilitation.
Por que esta operação foi sugerida
O Dr. Kieran Hirpara, cirurgião de membros superiores no Mater Private Hospital Rockhampton, adapta o tratamento à sua lesão específica. Geralmente, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que você nos procure, ainda assim será necessário um encaminhamento do seu médico de família para que você tenha direito ao reembolso do Medicare. Na sua consulta, colhemos o histórico clínico, examinamos o seu pulso e solicitamos exames de imagem, se necessário. Essa avaliação nos informa se a fratura é instável ou se os fragmentos ósseos se deslocaram para dentro da articulação; nesses casos, a cirurgia costuma ser indicada.
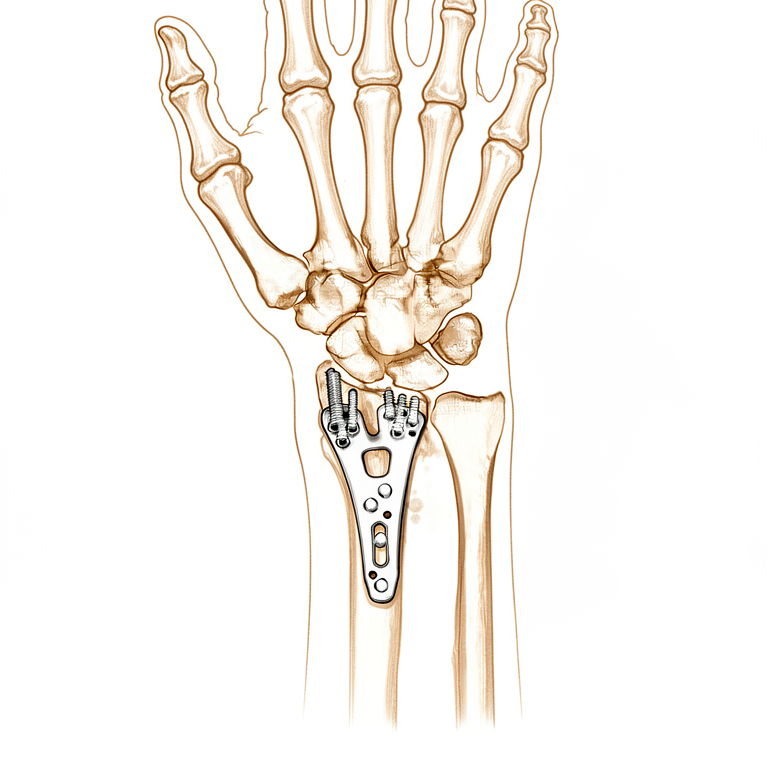
A operação é chamada de redução aberta e fixação interna. Em termos simples, isso significa que o osso fraturado é recolocado na posição normal e fixado ali com uma pequena placa metálica e parafusos. Para a maioria das fraturas de pulso desse tipo, a utilização de uma placa no lado palmar do pulso é o método padrão. Para fraturas menos graves, geralmente se tenta primeiro o tratamento não cirúrgico, como o uso de gesso ou talas. Quando o osso é instável ou já se deslocou, a cirurgia pode ser recomendada imediatamente, pois o gesso pode não ser suficiente para manter os fragmentos no lugar.
O objetivo é que o pulso cicatrize na posição correta, permitindo que você movimente a mão e volte às suas atividades normais o quanto antes.
Antes da operação
No dia da operação, você deverá suspender a ingestão de alimentos e líquidos sete horas antes do horário marcado para a operação. Pedimos sete horas em vez de seis para que a cirurgia possa ser antecipada caso a agenda cirúrgica avance. O seu cirurgião informará quais dos seus medicamentos habituais devem ser omitidos no dia da operação e quais devem ser tomados normalmente. Leve uma lista por escrito de todos os medicamentos que utiliza, incluindo comprimidos, gotas e qualquer produto adquirido na farmácia. Providencie alguém para levá-lo para casa após a cirurgia, pois você não poderá dirigir. Use roupas largas e confortáveis, cuja manga seja fácil de retirar.
Para planejar a operação, utilizamos radiografias tiradas de diversos ângulos. Às vezes, também é necessário realizar uma tomografia computadorizada (um tipo de radiografia detalhada) ou uma ressonância magnética (exame que mostra os tecidos moles, como os ligamentos). Caso tenha outras condições médicas, pode ser preciso fazer exames de sangue ou uma avaliação com o anestesista antes do dia da cirurgia.
No dia da cirurgia
Você chegará à unidade de admissão cirúrgica do hospital, onde será registrado e preparado para a sala de operações. Lá, conhecerá o anestesista. Esta cirurgia é realizada sob anestesia geral; você ficará completamente inconsciente durante o procedimento. Alguns pacientes também recebem um bloqueio nervoso regional para alívio da dor pós-operatória; o anestesista decide isso no dia da cirurgia, conforme as suas condições individuais.
Em seguida, você será levado à sala de operações, onde a cirurgia será realizada. Depois, acordará na sala de recuperação, onde as enfermeiras monitorarão seu estado enquanto a anestesia passa. Uma vez estabilizado, será encaminhado para um quarto ou liberado para ir para casa, dependendo do tipo de procedimento e da sua recuperação.
O que envolve a operação
A operação é realizada através de um corte no lado palmar do seu pulso. Por essa abertura, o cirurgião recoloca os fragmentos ósseos quebrados em sua posição normal. Em seguida, uma pequena placa metálica é moldada para se adaptar ao osso e fixada com parafusos. A placa fica na parte frontal do osso do pulso, onde existe uma camada de tecido entre ela e os tendões responsáveis pelo movimento do polegar e dos dedos.
Às vezes, é necessário examinar mais de perto a própria superfície da articulação. Nesses casos, o cirurgião pode utilizar um instrumento fino equipado com uma câmera minúscula para inspecionar o interior da articulação enquanto os fragmentos ósseos são alinhados. Isso ajuda a confirmar que a superfície articular está lisa e uniforme antes da fixação da placa.
Após o osso ficar bem fixado, o cirurgião verifica sua posição por meio de radiografias tiradas durante a operação. Em seguida, a incisão é fechada com pontos de sutura, e um curativo é aplicado sobre ela.
A placa e os parafusos permanecem no seu pulso permanentemente. Eles mantêm o osso estável durante a cicatrização, funcionando como uma tala interna. Em algumas fraturas, é necessário suporte adicional. Se o osso estiver quebrado em vários pedaços, o cirurgião pode colocar uma segunda placa na parte dorsal do pulso ou utilizar um enxerto ósseo para preencher os espaços e auxiliar na união dos fragmentos.
Você irá para casa com o curativo intacto. Pedimos que o mantenha seco e em seu lugar por cerca de 10 dias, quando retornará para uma avaliação da ferida.
Após a operação
Ao acordar, você estará na sala de recuperação, onde as enfermeiras monitoram de perto o seu estado à medida que o efeito da anestesia passa. O seu pulso será envolto em uma compressa macia, e forneceremos analgésicos para mantê-lo confortável. Geralmente, você poderá levantar-se e caminhar pouco depois; um membro da equipe de enfermagem o ajudará na primeira vez. Como a anestesia pode deixá-lo um pouco instável por algum tempo, peça a alguém para ficar com você nas primeiras 24 horas após voltar para casa. A maioria dos pacientes permanece uma noite no hospital após esta operação, embora alguns possam ir para casa no mesmo dia. Deixamos a compressa no lugar por cerca de 10 dias; por favor, não a retire antes disso, a menos que lhe seja indicado. Trocamos ou retiramos a compressa quando o atendemos.
Recuperação
Nos primeiros dias, o seu pulso ficará dolorido e inchado, o que é normal. O repouso, manter a mão elevada sobre travesseiros e os analgésicos que lhe fornecemos ajudarão a aliviar o desconforto. O inchaço geralmente diminui nas semanas seguintes, embora possa levar algum tempo para desaparecer por completo.
Você irá para casa com uma compressa macia em vez de uma tala, por isso a maioria das pessoas percebe que a rotina diária fica mais fácil do que esperavam. Você poderá levantar-se e movimentar-se imediatamente, além de usar a outra mão para se vestir, comer e tomar banho. Mantenha a compressa seca. A terapia ocupacional é parte essencial da sua recuperação: você será atendida por Ruby Doolan, da Extend Rehabilitation, nossa terapeuta especializada em mãos, que orientará os exercícios e confeccionará uma tala, se necessário. Movimentar os dedos desde cedo ajuda a prevenir rigidez e favorece a cicatrização.
Com o passar das semanas, notará que o inchaço diminui e a mobilidade volta. Sua terapeuta lhe ensinará exercícios para fortalecer a força de preensão e recuperar a flexão do pulso. Você poderá realizar atividades leves em casa assim que se sentir estável, mas evite levantar objetos pesados ou colocar carga sobre o pulso até que seu cirurgião autorize. Você não poderá dirigir enquanto o pulso estiver em processo de cicatrização; após a retirada da compressa e com autorização do cirurgião, poderá voltar a dirigir. Nossa página sobre direção após cirurgia de membro superior traz mais detalhes.
Cada pessoa tem seu próprio ritmo de recuperação, portanto seu cronograma pode ser diferente. Nós a acompanharemos ao longo do processo e orientaremos em cada etapa.
O que pode dar errado
A maioria dos pacientes se recupera bem, mas, ocasionalmente, podem surgir problemas. O seu cirurgião e a equipe monitoram você de perto para detectar qualquer problema precocemente.
Às vezes, a placa metálica ou os parafusos causam irritação. Você pode sentir uma protuberância sob a pele ou uma sensação de atrito ao mover o punho. Se isso o incomodar, mencione-o na próxima consulta de acompanhamento.
O tendão responsável por esticar o polegar pode, ocasionalmente, se romper. Você perceberá isso de repente: não conseguirá levantar o polegar, e a parte de trás do polegar parecerá flácida. Isso geralmente ocorre cerca de 3 meses após a cirurgia, às vezes sem qualquer dor prévia. Se o seu polegar parar de funcionar dessa forma, entre em contato com a clínica imediatamente.
O nervo responsável pela sensibilidade do polegar, dedo indicador e dedo médio pode ficar irritado. Você pode notar formigamento, sensação de “alfinetadas” ou áreas de dormência nesses dedos. Sintomas leves são comuns e geralmente desaparecem. Informe qualquer dormência que não melhore na próxima consulta.
Infecção na ferida é rara, mas requer atenção imediata. Fique atento a dor profunda e pulsante que não melhora com analgésicos comuns, vermelhidão que se espalha a partir da ferida, calor na área ou vazamento de líquido através do curativo. Se notar algum desses sinais, ligue para a clínica imediatamente ou vá ao pronto-socorro, caso seja fora do horário de atendimento.
Ocasionalmente, o osso se desloca antes de cicatrizar ou a cicatrização é lenta. Você pode sentir um novo ruído de atrito ou estalo no punho, aumento da dor ou sensação de instabilidade no punho. Informe-nos na próxima consulta para que possamos verificar a posição por meio de um raio-X.
Alguns punhos permanecem rígidos ou sensíveis após a cicatrização. Você pode ter dificuldade para girar a mão, dobrar o punho para trás ou fazer um aperto mais forte do que o esperado. A terapia ocupacional e os exercícios indicados pelo terapeuta são os principais tratamentos para isso.
O tabagismo e a nicotina, em qualquer forma — inclusive adesivos e gomas — aumentam o risco de vários desses problemas, como infecção da ferida, cicatrização lenta e necessidade de novas cirurgias. Vale a pena parar de fumar antes da operação, se possível.
A tabela de complicações nesta página lista as taxas típicas, caso você queira informações mais detalhadas.
Quando nos contatar
A maioria dos problemas apresenta sinais de alerta. Contate-nos se tiver febre, ou se o ferimento ficar mais vermelho, quente ou começar a vazar líquido. Contate-nos se a dor continuar piorando, mesmo após o uso de analgésicos comuns. Procure atendimento de emergência se notar inchaço ou dor na panturrilha, ou dificuldade súbita para respirar, pois isso pode indicar a presença de um coágulo sanguíneo. Procure atendimento de emergência se os dedos ficarem dormentes e permanecerem assim, ou se você não conseguir movê-los de forma alguma. Se o polegar deixar de se levantar normalmente, entre em contato com a clínica imediatamente. Quando tiver dúvidas, contate-nos.
Onde ler mais sobre a condição
Esta página trata especificamente da operação. A condição que ela trata, incluindo as evidências sobre quando a cirurgia é benéfica e quando não é, são abordadas com mais detalhes na página Fratura da Extremidade Distal do Rádio.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A network meta-analysis of randomized trials found that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery and a reduction in fracture healing complications [7].
- In adults, early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization at earlier stages [1].
- The mean differences in DASH scores at 6 weeks for early mobilization compared to late mobilization surpass the minimal clinically important difference [1].
- Substantial variations in surgical direct costs for distal radius ORIF exist, with implant choice being the predominant driver [3].
- In comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance [2].
- The Lift-Off Screw (LOS) length can be calculated, and the technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft [5].
- Radial column plating of the distal radius is a safe treatment modality and a valuable adjunct in the setting of complex distal radius fractures [6].
- Patients undergoing radial column plating of the distal radius should be counseled that there is a 28% chance that hardware removal may be required [6].
- The treatment of displaced intra-articular distal radius fractures with a dorsally versus a volarly placed interlocking plate system demonstrated similar clinical results [9].
Anatomy & Pathophysiology
Bony Anatomy
- The distal radius articular surface is biconcave and consists of scaphoid and lunate facets [31].
- The distal radioulnar joint (DRUJ) articulates with the ulna at the sigmoid notch [31].
- Lister tubercle is a small dorsal prominence that serves as a landmark for the dorsal approach to the wrist [31].
- Lister tubercle is a cause of attritional rupture of the extensor pollicis longus (EPL) after a distal radius fracture [31].
- The distal radial metaphysis has thin cortex and is vulnerable to bending forces [31].
- The brachioradialis insertion on the radial styloid acts as a deforming force in distal radius fractures [31].
- In a normal wrist with neutral ulnar variance, the distal radius bears 80% of axial load [31].
- The carpus encompasses two rows of eight bones that serve as a bridge between the forearm and the hand [19].
- The proximal carpal row from radial to ulnar includes the scaphoid, lunate, and triquetrum [19].
- The distal carpal row from radial to ulnar includes the trapezium, trapezoid, capitate, and hamate [19].
- The scaphoid is a small, irregular S-shaped tubular bone located in the proximal carpal row on the radial aspect of the wrist [25].
- The scaphoid lies entirely within the wrist joint at a 45-degree plane to the longitudinal and horizontal axis of the wrist [25].
- The scaphoid articulates with the trapezium/trapezoid, radius, capitate, and lunate [25].
- The scaphoid has a surface extensively covered with articular cartilage (over 80%), resulting in reduced capacity for periosteal healing and an increased tendency for delayed union and nonunion [25].
- The scaphoid is ridged across its nonarticular dorsoradial surface, along which the critical dorsal ridge vessels traverse [25].
- The dorsal ridge of the scaphoid is the insertion point for both the dorsal component of the scapholunate and intercarpal ligaments [25].
- The radioscapocapitate ligament does not attach to the bone itself but crosses the waist, acting as a sling across it allowing it to rotate [25].
- There are no tendon attachments to the scaphoid [25].
- The scaphoid acts as a midcarpal joint “bridge” linking and synchronizing the motions of the proximal and distal carpal rows as part of the key intercalated segment [25].
- Motion of the scaphoid includes rotation proximally and gliding distally, while providing stability to the midcarpal joint [25].
Vascular Anatomy
- The blood supply of the scaphoid is largely retrograde and meagre, provided by two vascular pedicles originating from the scaphoid branches of the radial artery [25].
- The dorsal branch of the scaphoid blood supply enters via small foramina along the spiral groove and dorsal ridge, supplying 70% to 80% of the scaphoid proximally, including the proximal pole [25].
- The volar branch of the scaphoid blood supply enters via the scaphoid tubercle and supplies the remaining 20% to 30% of the distal scaphoid [25].
- The waist of the scaphoid has minimal or no perforating vasculature [25].
- No vessels perforate the proximal dorsal cartilaginous area or through the scapholunate ligament [25].
- Proximal scaphoid fractures are associated with at least temporary disruption of the interosseous blood supply to the proximal pole [25].
Ligamentous Anatomy
- The extrinsic ligaments of the carpus connect the carpal bones to the forearm bones proximally and the metacarpals distally [27].
- The extrinsic palmar radiocarpal ligaments include the transverse carpal, radioscaphocapitate (RSC), radioscapholunate (RSL), radial collateral, long radiolunate (RLT), and short radiolunate ligaments [27].
- The extrinsic ulnocarpal ligaments include the ulnotriquetral (dorsal and palmar), ulnolunate, and ulnocapitate ligaments [27].
- Strong oblique extrinsic palmar radial ligaments prevent the carpus from translating medially on the angulated slope of the distal radius through two V-shaped ligamentous bands [27].
- The proximal V-shaped ligamentous band connects the forearm to the proximal carpal row and includes the long radiolunate, radioscapholunate, ulnolunate, and ulnotriquetral ligaments [27].
- The distal V-shaped ligamentous band connects the forearm to the distal carpal row and includes the radioscaphocapitate and ulnocapitate ligaments [27].
- A V-shaped interligamentous sulcus over the capitolunate articulation, known as the space of Poirier, is an interval of capsular weakness [27].
- Maximal space of Poirier is seen when the wrist is dorsiflexed, with the space almost disappearing in palmar flexion [27].
- The lunate displaces into the carpal canal through the space of Poirier during dorsal dislocations [27].
- The arcuate ligament is found in the central third of the palmar joint capsule and is formed from the interdigitation of transverse fibers of the radioscaphocapitate, ulnocapitate, triquetrocapitate, and volar scaphotriquetral ligaments [27].
- The arcuate ligament forms a support sling for the midcarpal region, particularly the head of the capitate [27].
- The extrinsic dorsal carpal ligaments include the dorsal radiocarpal (DRC) ligament and the dorsal intercarpal ligament, which form a V-shaped configuration [27].
- The ulnodorsal capsule of the wrist is reinforced by the ulnolunate and ulnotriquetral ligaments and the floors of the fifth and sixth extensor compartments [27].
- The intrinsic ligaments connect individual carpal bones to one another and are intra-articular short fibers [27].
- The intrinsic ligaments include the palmar midcarpal ligaments (scaphotrapeziotrapezoid, scaphocapitate, triquetrocapiate, triquetrohamate), the proximal interosseous ligaments (scapholunate, lunotriquetral), and the distal interosseous ligaments (trapeziotrapezoid, trapeziocapitate, capitohamate) [27].
- The V-shaped scaphotrapezium–trapezoid ligament on the radial side of the wrist provides stability to the scaphoid–trapezium–trapezoid articulation as well as the scaphoid itself [27].
- The scaphocapitate ligament is a large robust ligament that provides midcarpal stability [27].
Pathophysiology & Biomechanics
- Distal radius fractures are the most common fractures of the upper extremity, with over 300,000 cases per year in the United States [31].
- Distal radius fractures have a bimodal distribution: young patients typically sustain high-energy trauma, while elderly patients typically sustain low-energy falls [31].
- In elderly patients, distal radius fractures are the most common upper extremity osteoporotic fracture [31].
- Normal radiographic parameters for the distal radius include an average radial height of 11 mm, radial inclination of 22 degrees, and volar tilt of 11 degrees [31].
- Acceptable radiographic deviations for distal radius fractures include less than 5 mm of shortening, less than a 5-degree change in radial inclination, and less than 10-degree dorsal angulation [31].
- Ulnar variance is assessed with the forearm in neutral rotation and compared with the contralateral side [31].
- The distal radioulnar joint (DRUJ) alignment is assessed on a true lateral radiograph [31].
- Ligamentous injuries associated with distal radius fractures include scapholunate (SL), lunotriquetral (LT), or triangular fibrocartilage complex (TFCC) injuries [31].
- Radiocarpal dislocation or “inferior arc” injury is highly unstable and difficult to reduce closed [31].
- Computed tomography (CT) is used for detail of complex intraarticular patterns, while magnetic resonance imaging (MRI) is used for occult fracture, bone contusion, and associated soft tissue injury [31].
- Placing the distal row of screws greater than 3mm from subchondral bone in comminuted intra-articular distal radius fractures is associated with increased odds of worsening ulnar variance [2].
Classification
- In adults, early mobilization for distal radius fractures treated with open reduction and internal fixation may have a beneficial functional effect compared to late mobilization at earlier stages [1].
- The mean difference in DASH scores at 6 weeks between early and late mobilization for distal radius fractures treated with ORIF surpasses the minimal clinically important difference [1].
- In comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone is associated with increased odds of worsening ulnar variance [2].
- The Lift-Off Screw (LOS) length can be calculated for accurate sagittal tilt correction in a distal radius fracture model [5].
- The Lift-Off Screw technique can potentially be used with any distal radius periarticular locking plate that has locking options in the shaft [5].
- Open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery [7].
- Open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of a reduction in fracture healing complications [7].
- The lifetime risk of distal radius fracture is 15% for women and 2% for men [13].
- Most distal radius fractures are treated nonsurgically with a plaster cast after closed reduction [13].
- The number of distal radius fractures receiving surgical intervention has increased as surgical treatment has advanced and the general population ages [13].
- Surgical methods for distal radius fractures have shifted from percutaneous pinning or external fixation to open reduction and internal fixation [13].
- The benefit of immediate structural rigidity of fractures, even in osteoporotic bone, after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- ORIF using volar plating and screws has become the preferred surgical approach among hand and orthopedic surgeons for distal radius fractures [13].
- Complication rates following ORIF of distal radius fractures vary from 0% to 60% [13].
- A systematic review of 55 studies including 3,911 fractures reported complication rates following ORIF of distal radius fractures varying from 0% to 60% [13].
Clinical Presentation
- The mean difference in DASH scores at 6 weeks for early mobilization compared to late mobilization in distal radius fractures treated with ORIF surpasses the minimal clinically important difference [1].
- A network meta-analysis of randomized trials indicates that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery [7].
- Open reduction and internal fixation with a plate is associated with a reduction in fracture healing complications for adult patients with a distal radius fracture compared to other interventions in a network meta-analysis of randomized trials [7].
- The benefit of immediate structural rigidity of distal radius fractures after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- Complication rates following ORIF of distal radius fractures have been reported to vary from 0% to 60% in a systematic review of 55 studies including 3,911 fractures [13].
Investigations
Imaging Protocols and Diagnostic Sensitivity
- Standard scaphoid radiographs are used for primary assessment to detect displacement and associated fractures in radiocarpal instability [29].
- Provocative stress tests may be required to demonstrate dynamic radiocarpal instability [29].
- CT may be required to better define associated bony injuries in radiocarpal instability [29].
- MRI can be used to determine the extent of ligamentous disruption in radiocarpal instability [29].
- A decrease in the ulnocarpal index may provide the only clue to diagnosis in cases of subtle ulnar translation [29].
- CT is more sensitive for diagnosing a scaphoid fracture and is useful for confirming alignment of bone fragments if surgery is planned [34].
- MRI is the definitive way to confirm or exclude a diagnosis of scaphoid fracture if the technique is available [34].
- 10–15% of scaphoid fractures are not visible on initial X-rays [28].
- If initial X-rays are normal but clinical suspicion remains, the wrist should be immobilized and re-imaged in 2 weeks or via MRI [28].
- Secondary imaging modalities are predominantly used in the assessment of scaphoid fractures and the diagnosis of intercarpal ligament injury and any associated instability [35].
- Ultrasound scanning (USS) is used for suspected carpal fractures and ligament injuries [35].
- CT (2D/3D) is used for suspected carpal fractures, fracture displacement, malunion, nonunion, and bone loss [35].
- Dynamic CT is used by some for ligament injuries [35].
- Bone scintigraphy is used for suspected carpal fractures and avulsion injuries [35].
- Arthrography ± videofluoroscopy is used for ligament injuries [35].
- MRI is used for suspected carpal fractures, avascular necrosis (AVN) of carpal bones, and ligament injuries [35].
- Wrist arthroscopy is used for suspected carpal fractures, fracture displacement, and ligament injuries [35].
- Live/video fluoroscopic evaluation of the wrist provides diagnostic clarity for dynamic instability with sensitivities reported between 86% and 95% and specificity between 80% and 97% for diagnosing scapholunate ligament injury [35].
- Ultrasound scanning (USS) provides an additional tool for the detection of carpal ligament injuries, though the technique is operator dependent [35].
Radiographic Measurements and Instability Patterns
- The lateral intrascaphoid angle is normally 30 degrees ±5 degrees on a sagittal view, with an angle greater than 35 degrees used as a cut-off for displacement [35].
- The AP intrascaphoid angle is normally 40 degrees ± 5 degrees on coronal views [35].
- The dorsal cortical angle is normally 140 degrees, with values greater than 160 degrees considered abnormal on a sagittal view [35].
- The scaphoid height-to-length ratio is normally 0.60, with values greater than 0.65 considered abnormal on a sagittal view [35].
- Intraobserver reliability for the lateral intrascaphoid angle is poor, while interobserver reliability is poor to moderate [35].
- Intraobserver reliability for the dorsal cortical angle is moderate to excellent, while interobserver reliability is moderate to excellent [35].
- Intraobserver reliability for the scaphoid height-to-length ratio is excellent, while interobserver reliability is moderate to excellent [35].
- Dorsal intercalated segmental instability (DISI) is characterized by the lunate tilting backwards and the scaphoid tilting somewhat volarwards [28].
- Volar intercalated segment instability (VISI) is characterized by the lunate and scaphoid tilting somewhat volarwards and the capitate and metacarpals lying anterior (volar) to the radius [28].
- In a normal lateral X-ray, the axes of the radius, lunate, capitate, and third metacarpal are co-linear, and the scaphoid projects at an angle of about 45 degrees to this line [28].
- DISI pattern is most commonly associated with displaced scaphoid fractures and scapholunate dissociation (SLD) [35].
- Assessment of Gilula's lines can aid in the diagnosis of perilunate dislocations [35].
Anatomical Context for Imaging Interpretation
- The proximal carpal row has no direct tendon attachments, and its movement results from bone shape, interaction with other bones, and ligament attachments [19].
- The pisiform bone is a sesamoid bone enclosed within the sheath of the flexor carpi ulnaris tendon and should not theoretically be considered within the proximal carpal row [19].
- The trapezium articulates with the first metacarpal, the trapezoid with the second, the capitate with the third, and the hamate with the fourth and fifth metacarpals [19].
- There is 30 to 40 degrees of flexion–extension and rotation at the metacarpotrapezial joint [19].
- Motion at the distal carpal row is controlled by the extrinsic wrist flexors and extensors [19].
- The ligaments of the wrist are predominantly contained within the joint capsule [19].
- Apart from the scaphocapitate ligament, carpal ligaments are not described consistently across anatomical studies [19].
Treatment
Surgical Approach and Technique
- Open reduction and internal fixation (ORIF) with a plate offers the best results for adult patients with distal radius fractures in terms of early and sustained functional recovery and a reduction in fracture healing complications [7].
- The immediate structural rigidity of fractures after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- The large tenaculum clamp facilitates anatomical restoration of volar tilt and volar translation while allowing intraoperative fluoroscopy [22].
- The use of a large tenaculum clamp potentially minimizes complications such as flexor tendon abrasion or rupture [22].
- The lift-off screw technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft [5].
Implant Selection and Positioning
- Substantial variations in surgical direct costs for distal radius ORIF exist, and implant choice is the predominant driver [3].
- Placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance in comminuted intra-articular distal radius fractures [2].
Postoperative Management
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial effect compared to late mobilization at earlier stages [1].
- Mean differences in DASH scores at 6 weeks for early mobilization compared to late mobilization surpass the minimal clinically important difference [1].
Complications and Hardware
- There is a 28% chance that hardware removal may be required for patients treated with radial column plating of the distal radius [6].
Complications
- Complication rates following open reduction and internal fixation (ORIF) of distal radius fractures have been reported to vary from 0% to 60% [13].
- A systematic review of 55 studies including 3,911 fractures found no standard for evaluating what should be defined as a complication after ORIF using volar plating [13].
- In a retrospective study of 822 patients, the complication rate following volar locking plate fixation of distal radius fractures was determined as the primary aim [13].
- Radial column plating of the distal radius is associated with a 28% chance that hardware removal may be required [6].
- Open reduction and internal fixation with a plate offers a reduction in fracture healing complications compared to other treatments for adult patients with distal radius fractures [7].
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization, with mean differences in DASH scores at 6 weeks surpassing the minimal clinically important difference [1].
Recovery
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization at earlier stages [1].
Key Evidence
- [L1] Functionally, at earlier stages, early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial effect compared to late mobilization, with mean differences in DASH scores at 6 weeks surpassing the minimal clinically important difference. [1] (10.1186/s13018-021-02837-0)
- [L4] In this two-center retrospective cohort of comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance. [2] (10.1016/j.jhsa.2025.03.016)
- [L3] Substantial variations in surgical direct costs for distal radius ORIF exist, and implant choice is the predominant driver. [3] (10.1016/j.jhsa.2018.04.015)
- [L5] The LOS length can be calculated, and this technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft. [5] (10.1016/j.jhsa.2018.02.011)
- [L4] Radial column plating of the distal radius is a safe treatment modality and a valuable adjunct in the setting of complex distal radius fractures, but patients should be counseled that there is a 28% chance that hardware removal may be required. [6] (10.1177/1558944718760861)
- [L1] A network meta-analysis of randomized trials revealed that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture, in terms of early and sustained functional recovery and a reduction in fracture healing complications. [7] (10.5435/jaaos-d-18-00424)
- [L3] The treatment of displaced intra-articular distal radius fractures with a dorsally versus a volarly placed interlocking plate system demonstrated similar clinical results. [9] (10.1177/1558944716675129)
- [L4] [13] (10.1016/j.jhsa.2022.11.012)
- [L4] The large tenaculum clamp facilitates anatomical restoration of volar tilt and volar translation while allowing intraoperative fluoroscopy, potentially minimizing complications such as flexor tendon abrasion or rupture. [22] (10.1016/j.jhsa.2018.11.017)
References
[1] In adults, early mobilization may be beneficial for distal radius fractures treated with open reduction and internal fixation: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02837-0
[2] The Association Between Distal Screw and Articular Subsidence in the Open Treatment of Intra-articular Distal Radius Fractures. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.03.016
[3] Evaluation of Factors Driving Cost Variation for Distal Radius Fracture Open Reduction Internal Fixation. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.04.015
[5] Lift-Off Screw Results in Accurate Sagittal Tilt Correction in a Distal Radius Fracture Model. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.011
[6] Complications of Radial Column Plating of the Distal Radius. HAND. 2018. DOI: 10.1177/1558944718760861
[7] Interventions for Distal Radius Fractures: A Network Meta-analysis of Randomized Trials. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-18-00424
[9] Management of Intra-Articular Distal Radius Fractures: Volar or Dorsal Locking Plate—Which Has Fewer Complications?. HAND. 2016. DOI: 10.1177/1558944716675129
[13] Complications After Volar Locking Plate Fixation of Distal Radius Fractures: A Retrospective Study of 822 Patients. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.11.012
[19] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Pathoanatomy and Applied Anatomy Relating to Carpal Fractures and Dislocations.
[22] Use of a Large Tenaculum Clamp as a Reduction Technique for Treatment of Distal Radius Fractures. The Journal of Hand Surgery. 2019. DOI: 10.1016/j.jhsa.2018.11.017
[25] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Pathoanatomy and Applied Anatomy Related to Scaphoid Fractures.
[27] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Extrinsic Ligaments.
[28] Apley And Solomon S Concise System Of Orthopaedics And Trauma. FRACTURES OF THE DISTAL RADIUS IN CHILDREN > Imaging.
[29] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Assessment of Radiocarpal Instability.
[31] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > DISTAL RADIUS FRACTURES.
[34] Apley And Solomon S Concise System Of Orthopaedics And Trauma. FRACTURES OF THE DISTAL RADIUS IN CHILDREN > FRACTURE OF THE SCAPHOID.
[35] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Secondary Imaging Methods.