Patients › Elbow
Fratura do olécrano
Olecranon fractures — patterns, non-operative care, and tension-band or plate fixation.
O que você está sentindo
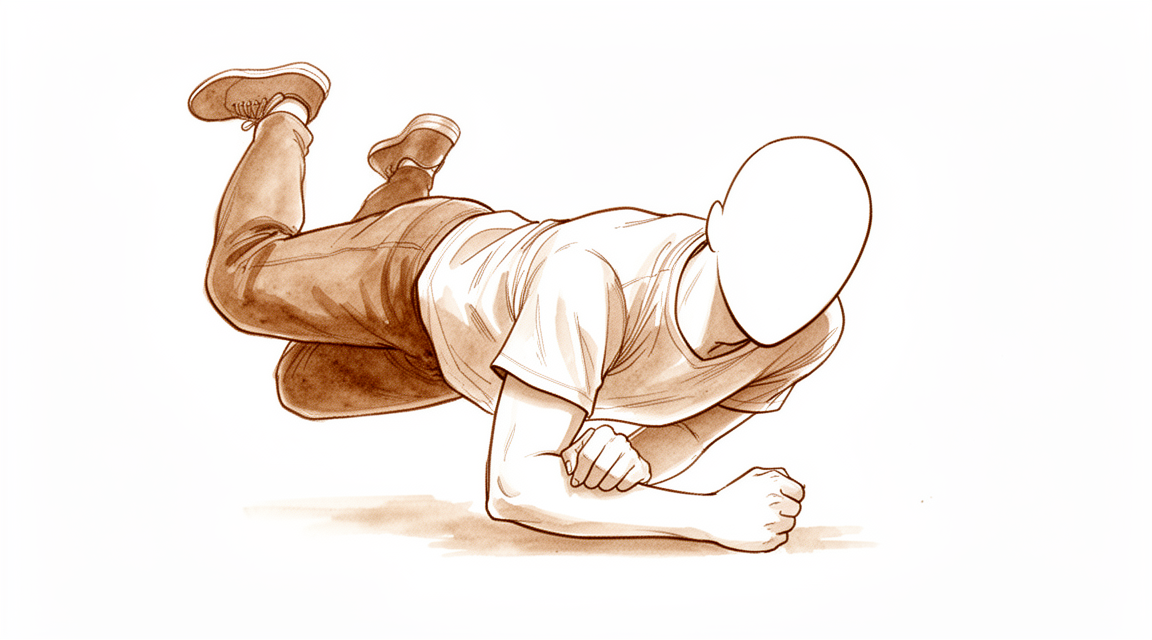
A fratura do olécrano é uma quebra na ponta óssea da parte de trás do cotovelo. Ela costuma acontecer de uma de duas formas. Em pessoas mais jovens, tende a ocorrer após uma queda forte ou uma pancada direta no cotovelo. Em pessoas mais velhas, muitas vezes resulta de uma simples queda da própria altura. Um movimento repentino e forte de esticar o braço também pode arrancar um fragmento de osso da ponta do cotovelo.
Em geral, você sentirá dor bem na parte de trás do cotovelo, e ela tende a ficar concentrada em um ponto, e não espalhada. O inchaço na parte de trás do cotovelo é típico e pode ser bastante acentuado. Como essa ponta óssea fica logo abaixo da pele, às vezes é possível sentir a borda da fratura através da pele. Se a pele se rompeu na queda, a ferida costuma ficar na parte de trás do cotovelo, onde ele bateu no chão. Pode ser difícil usar o braço, e esticá-lo contra alguma resistência, como ao se levantar de uma cadeira empurrando com os braços, pode parecer fraco ou impossível.
Nos primeiros dias, a dor costuma piorar quando você tenta mexer o cotovelo e pode atrapalhar o sono. Tarefas do dia a dia que dobram o cotovelo ou colocam carga sobre ele, como levantar uma chaleira, se vestir ou se apoiar no antebraço, geralmente doem. O inchaço e os hematomas diminuem ao longo das primeiras duas semanas, e a dor vai melhorando aos poucos à medida que o osso começa a cicatrizar.
Algumas situações exigem atendimento urgente. Vá ao pronto-socorro no mesmo dia se a pele sobre o cotovelo estiver aberta, se o osso estiver aparecendo ou se o braço estiver visivelmente deformado. O mesmo vale se a mão ou os dedos ficarem pálidos, frios, brancos ou azulados, ou se você perder subitamente a sensibilidade ou o movimento do braço após a lesão. Se os sintomas não estiverem melhorando, estiverem piorando ao longo de semanas ou acordarem você à noite, consulte o seu médico de família ou peça uma avaliação com especialista. Se não conseguir falar com a clínica, vá ao pronto-socorro mais próximo.
O que realmente acontece
A ponta óssea na parte de trás do cotovelo se chama olécrano. Ela é a extremidade superior de um dos ossos do antebraço e funciona como a tampa de uma dobradiça. Quando você estica o braço, essa tampa desliza num sulco na extremidade do osso do braço. A fratura é importante por causa do que está preso a ela: o tendão do tríceps, o músculo da parte de trás do braço, está ancorado exatamente nesse ponto. É esse tendão que permite esticar o cotovelo contra uma carga.
Pense numa porta com uma mola forte que a puxa para fechar. O olécrano é o suporte que segura essa mola. Quando o osso se quebra, a mola continua puxando e arrasta o fragmento quebrado para cima e para longe, deixando um espaço na superfície da articulação. É por isso que o seu braço não está funcionando normalmente agora: o músculo continua forte, mas está puxando um fragmento solto de osso em vez de mover o antebraço. Esticar o braço contra resistência fica fraco ou impossível.
O osso cicatriza se unindo novamente, e um fragmento solto com o tendão preso a ele pode voltar a se fixar à medida que o osso se consolida. Mas, para isso dar certo, os fragmentos precisam estar na posição correta. Quando a fratura não se deslocou, os fragmentos podem simplesmente ser mantidos imóveis enquanto se consolidam. Quando os fragmentos se afastaram, ou quando a superfície da articulação se quebrou em vários pedaços, o cotovelo pode ficar instável, e essas fraturas geralmente precisam de cirurgia para mantê-los no lugar enquanto cicatrizam.
Os cirurgiões classificam essas fraturas conforme o quanto os fragmentos se deslocaram e se a articulação do cotovelo permanece estável. Uma fratura de grau um não se deslocou. Uma de grau dois se deslocou, mas a articulação ainda funciona. Uma de grau três significa que a própria articulação do cotovelo está instável. Os graus com deslocamento e instabilidade são os que mais frequentemente precisam de cirurgia.
A maioria dessas fraturas cicatriza bem, e uma pequena perda da capacidade de esticar o braço completamente é comum.
O que podemos fazer a respeito
O Dr. Kieran Hirpara, cirurgião de membros superiores no Mater Private Hospital Rockhampton, adapta o tratamento à sua lesão específica. Algumas dessas fraturas cicatrizam sem cirurgia, e outras precisam de cirurgia logo após a lesão; por isso, uma avaliação rápida é importante. Em geral, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que nos procurasse, ainda assim será necessário um encaminhamento do seu médico de família para que você tenha direito ao reembolso do Medicare. Na clínica, colhemos o histórico clínico, examinamos o seu braço e solicitamos exames de imagem quando necessário.
Se a fratura não se deslocou, ou se deslocou só um pouco, e o seu cotovelo está estável, podemos recomendar mantê-lo imóvel enquanto cicatriza. Isso significa usar uma tala ou gesso por um período, com controles por novas radiografias para garantir que os fragmentos permaneçam no lugar. Esse caminho é comum em pacientes idosos e em pessoas que usam o braço para tarefas do dia a dia, e não para trabalho pesado. Ele evita uma operação e os riscos que a acompanham. A desvantagem é que, no fim, o cotovelo pode não esticar completamente, e algumas pessoas têm dificuldade em aceitar isso. Os movimentos são recuperados por etapas com o seu terapeuta da mão, que também confeccionará qualquer tala de que você precise.
Se os fragmentos se afastaram, ou se a articulação do cotovelo está instável, geralmente recomendaremos cirurgia desde o início. O objetivo é manter os fragmentos na posição correta para que o osso se consolide e você possa começar a se movimentar cedo. A forma de fixar o osso depende do padrão da fratura, e nenhum método serve para todas as fraturas. Às vezes, os dois caminhos são realmente possíveis, por exemplo, num paciente idoso com uma fratura deslocada. Conversaremos sobre o que é importante para você: quanta dor você está disposto a tolerar e se perder os últimos graus da capacidade de esticar o braço incomodaria você.
Seja qual for o caminho escolhido, as primeiras semanas são parecidas. O alívio da dor mantém você confortável enquanto o inchaço diminui. A lesão precisa ser protegida enquanto o osso se consolida, e diremos o que você pode e o que não pode fazer com o braço. O seu terapeuta da mão orientará os seus movimentos no momento certo, com cuidado no início e aumentando aos poucos à medida que o osso cicatriza. A maioria dessas fraturas cicatriza bem, e uma pequena perda da capacidade de esticar o braço completamente é comum. Os implantes metálicos que ficam logo abaixo da pele na parte de trás do cotovelo podem incomodar, e algumas pessoas precisam de uma pequena operação mais tarde para retirá-los.
O que esperar
A maioria dessas fraturas cicatriza bem. Uma pequena perda da capacidade de esticar o braço completamente é comum, e a maioria das pessoas mantém um bom uso do braço. Os resultados a longo prazo após cirurgia de fraturas complexas são bons, mesmo quando alguma artrose por desgaste aparece na articulação em radiografias posteriores.
Se a sua fratura for mantida imóvel numa tala ou gesso, o osso se consolida ao longo de semanas, e não de dias. Você fará novas radiografias para garantir que os fragmentos permaneçam onde devem estar. Esse caminho é adequado para pacientes idosos e para pessoas que usam o braço em tarefas do dia a dia, e não em trabalho pesado. Os resultados, tanto a curto quanto a longo prazo, são satisfatórios nesse grupo. A desvantagem é que, no fim, o cotovelo pode não esticar completamente.
Se você fizer cirurgia, o osso é mantido no lugar com implantes metálicos enquanto se consolida. Os movimentos começam cedo e avançam por etapas com o seu terapeuta da mão. Alguma perda da capacidade de esticar o braço completamente é esperada após essa lesão, seja qual for o caminho escolhido. Num acompanhamento de longo prazo de pessoas tratadas com cirurgia para uma fratura deslocada, 96% tiveram resultados bons ou excelentes até 25 anos após a lesão.
A recuperação é um retorno gradual às suas atividades normais. As tarefas leves do dia a dia voltam primeiro; depois, levantar peso e usar o braço com mais força, à medida que o osso se fortalece. Quando você poderá dirigir, trabalhar ou praticar esportes depende do seu trabalho, do seu braço e de como o osso cicatriza, e orientaremos você em cada etapa.
Vale a pena conhecer as possíveis complicações. Os implantes metálicos ficam logo abaixo da pele na parte de trás do cotovelo e podem incomodar a ponto de algumas pessoas optarem por retirá-los mais tarde. Esse é um problema recorrente após essa cirurgia. Outros problemas, como o osso cicatrizar numa posição ruim ou o cotovelo continuar rígido, são menos comuns. Se os seus sintomas não estiverem melhorando, estiverem piorando ao longo de semanas ou acordarem você à noite, consulte o seu médico de família ou peça uma avaliação com especialista. Se não conseguir falar com a clínica, vá ao pronto-socorro mais próximo.
Quando procurar ajuda médica
Procure atendimento urgente se o cotovelo estiver visivelmente deformado, se a pele sobre a lesão estiver aberta, ou se a mão ou os dedos ficarem pálidos, frios, brancos ou azulados. A perda súbita de sensibilidade ou de movimento no braço após a lesão também exige ida ao pronto-socorro no mesmo dia. Esses sinais indicam que a lesão precisa ser avaliada imediatamente.
Para todo o resto, comece pelo seu médico de família. Ele pode examinar o seu braço e solicitar radiografias, que geralmente são tudo o que é necessário para mostrar esse tipo de fratura. Se o seu médico de família achar que um especialista deve assumir o caso, ele encaminhará você para uma avaliação.
Volte, ou peça uma avaliação com especialista, se a dor não estiver melhorando, ou se o inchaço, os movimentos ou o uso do braço não estiverem melhorando semana a semana à medida que o osso cicatriza. Sintomas que estão piorando ao longo de semanas, que acordam você à noite ou que impedem você de trabalhar ou de usar o braço também merecem uma nova avaliação. Se não conseguir falar com a clínica, vá ao pronto-socorro mais próximo.
Em maior profundidade
Advanced reading: the deeper science (optional)
Esta seção vai além do que você precisa saber para tomar decisões sobre o próprio tratamento. A fratura do olécrano merece uma leitura mais aprofundada devido a uma constatação que inverte a lógica habitual da cirurgia de fraturas: em pacientes idosos, uma fratura deslocada do olécrano pode ser deixada sem fixação, e o cotovelo continua funcionando normalmente.
A fratura deslocada que não precisa de correção
Uma fratura no olécrano separa o tríceps do antebraço; por isso, a lógica convencional é de que ela deve ser reimplantada, caso contrário o cotovelo não conseguirá ser estendido contra resistência. Em pacientes com mais de 70 anos, essa lógica não se aplica. Uma revisão sistemática constatou que fraturas deslocadas do olécrano nesse grupo podem ser tratadas de forma não cirúrgica, com alto grau de satisfação do paciente e manutenção de uma amplitude de movimento funcional [1].
O que se perde nesse tratamento é mensurável: déficit na extensão do cotovelo, incapacidade de estender completamente o membro e redução da força de extensão. O que se evita, por outro lado, é a formação de ferida sobre um osso subcutâneo em pele fina e frequentemente frágil, além da necessidade de implantar materiais metálicos sob essa pele. Como o uso de implantes é a causa mais comum de uma segunda cirurgia após a fixação do olécrano, evitá-los elimina por completo essa complicação frequente.
Para um idoso cujo braço é utilizado para tarefas cotidianas, e não para esforços de empuxo intensos, um cotovelo que não consegue atingir os últimos graus de extensão representa um incômodo menor do que as complicações decorrentes de feridas. Para um paciente mais jovem ou com demandas físicas maiores, isso não se aplica; por isso, essa abordagem é indicada especificamente para idosos, e não de forma geral.
Naqueles casos em que a fixação é necessária, a escolha do implante faz diferença
Para o padrão comum de fraturas deslocadas, porém simples, dois tipos de implantes competem: a estrutura de fios de tensão e a placa óssea. Em 827 pacientes com fraturas do tipo II segundo a classificação de Mayo, a fixação com placa demonstrou maior eficácia e segurança em comparação com o uso de fios de tensão; os autores ressaltam, porém, que poucos estudos foram incluídos e que ainda são necessários ensaios randomizados de maior qualidade [2]. Uma revisão de 2025 envolvendo 472 pacientes, que comparou técnicas modernas de fixação com os métodos tradicionais de fios de tensão, chegou à mesma conclusão [3].
Este é um dos poucos casos neste site em que a comparação entre técnicas aponta para uma direção clara, em vez de deixar a questão em aberto. Contudo, vale considerar essa conclusão com cautela, dado o próprio nível de evidência apontado pelos autores.
A artrite se desenvolve, mas, na maioria dos casos, não é um problema
Os achados de exames de imagem a longo prazo podem ser alarmantes quando apresentados sem contexto. Após fraturas isoladas do olécrano, a incidência média de osteoartrite pós-traumática foi de 19%, em um seguimento médio de 41 meses; além disso, os resultados relatados pelos pacientes variaram de bons a excelentes, independentemente do tipo de fratura ou da presença de artrite [4].
Ambas as partes dessa frase são essenciais para a compreensão do tema. A artrite observada em radiografias de acompanhamento após essa lesão é comum. Contudo, nesse período de tempo, ela praticamente não influencia a forma como os pacientes avaliam a função do cotovelo. Um achado radiológico não equivale automaticamente a um problema clínico, e por si só não deve ser motivo para intervenções adicionais.
Referências
[1] Alvara CA, Biedron G, Dunn JC. Tratamento não cirúrgico de fraturas do olécrano em pacientes idosos: uma revisão sistemática. Hand (N Y). 2020;17(4):734-9. https://doi.org/10.1177/1558944720944261
[2] Jia Y, Liu A, Guo T, Chen J, Yu W, Zhai J. Eficácia e segurança do fio de tensão em comparação com placa para fraturas do olécrano tipo Mayo II: uma revisão sistemática e meta-análise. J Orthop Surg Res. 2022;17(1). https://doi.org/10.1186/s13018-022-03262-7
[3] Wang C, Li C. Técnicas modernas de fixação versus o método tradicional de fio de tensão para fraturas do olécrano: uma revisão sistemática e meta-análise. J Orthop Surg Res. 2025;20(1). https://doi.org/10.1186/s13018-025-06061-y
[4] Wiersma JP, de Klerk HH, Priester-Vink S, Doornberg JN, Bhasyam AR, van den Bekerom MP. Incidência de osteoartrite pós-traumática em fraturas do olécrano e o papel do tipo de fratura: uma revisão sistemática. J Shoulder Elbow Surg. 2026. https://doi.org/10.1016/j.jse.2026.02.024
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
General Outcomes and Complications
- A majority of olecranon fractures heal uneventfully with good or excellent results, with a small loss of motion expected [11].
- 96% of individuals with a closed displaced fracture of the olecranon treated by open reduction and internal fixation had excellent or good outcomes up to 25 years after the fracture [4].
- Surgical treatment of olecranon fractures is associated with a high rate of complications [18].
- Patients undergoing revisions beyond implant removal after olecranon fracture fixation had poorer functional outcomes [18].
- No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method for olecranon fractures [18].
- The incidence of post-traumatic osteoarthritis following isolated olecranon fractures is 19% at a median follow-up of 41 months [22].
Operative Management
- No single technique is suitable for the management of all olecranon fractures [21].
- Low-profile double-plate osteosynthesis is a safe and effective alternative treatment for olecranon fractures with excellent subjective and objective clinical outcome measures [1].
- Plating of the olecranon leads to predictable union, though the most common complication was lack of full extension in 39% of patients [16].
- Both Kirschner wire tension band and anatomical locking plate procedures effectively treat Mayo type II olecranon fractures [9].
- Current randomized evidence suggests that tension band wiring and plate fixation may yield similar functional outcomes for displaced olecranon fractures, based on a limited number of randomized controlled trials [24].
- Tension band wiring remains an effective treatment for appropriately selected olecranon fractures and outperformed plate osteosynthesis in one cohort [40].
- The timing of fixation of displaced olecranon fractures does not significantly increase the rate of early complications or reoperation [15].
- Excision of the olecranon fragment with repair of the triceps mechanism is supported as a preferred method of treatment due to significantly less morbidity compared with internal fixation [65].
Non-Operative Management
- Close radiographic follow-up is recommended for nonsurgically treated olecranon fractures in children [2].
- Some isolated displaced (>2 mm) olecranon fractures in elderly patients can be successfully treated nonoperatively [6].
- Satisfactory short-term and long-term outcomes were found following the nonoperative management of isolated displaced olecranon fractures in older, lower-demand patients [13].
- Displaced olecranon fractures in patients older than 70 years may be effectively managed with nonoperative measures to produce high satisfaction and functional range of motion [23].
- Nonoperative management of olecranon fractures in elderly patients offers comparable functional outcomes to surgical intervention while significantly reducing exposure to potential complications and healthcare costs [41].
- Nonoperative treatment is a reasonable option for displaced stable olecranon fractures in elderly patients [29].
Elderly Population Specifics
- Olecranon fractures in the elderly have higher than expected 1-year mortality rates [5].
- Patients with olecranon fractures have essentially similar demographic characteristics compared to patients with distal radius fractures [10].
- The literature on the treatment of olecranon fractures in elderly patients is limited [7].
Anatomy & Pathophysiology
Bony Anatomy
- The olecranon and the coronoid process form the greater sigmoid notch, which articulates with the trochlea of the distal humerus [37].
- The intrinsic anatomy of the ulnohumeral articulation allows flexion/extension movement of the elbow joint and provides stability for the elbow [37].
- The olecranon serves as the insertion for the triceps tendon, which blends with the periosteum of the proximal ulna [37].
- The exposed, subcutaneous position of the olecranon renders it vulnerable to direct trauma and violent muscular contractions from the triceps [37].
- In children, the olecranon is predominantly cartilage, particularly in younger children, which reduces the chance of fracture occurring with a direct blow [48].
- In children, the thick periosteum and relatively thin metaphyseal cortex of the olecranon predispose it to minimally displaced greenstick fractures [48].
- Radiographic measurements of normal elbows guide the surgeon to obtain a more reliable length of the olecranon and maintain articular geometry during fixation [69].
Mechanisms of Injury
- Olecranon fractures can result from a direct blow, a fall on an outstretched hand with the elbow in flexion, or high-energy trauma associated with radial head fractures or elbow dislocation [37].
- Sudden and violent triceps muscle contraction can produce an avulsion fracture of varying size of the olecranon tip [37].
- A bimodal distribution of olecranon fractures is seen in young patients with high-energy trauma and elderly patients with low-energy trauma such as a fall from standing [37].
- Olecranon fractures typically occur as low-energy falls from standing in older patients or high-energy injury mechanisms in younger patients [38].
- The bone typically fails from a direct blow to the elbow or as a tensile force from the pull of the triceps tendon [38].
- Regardless of the mechanism of injury, the triceps acts as the main deforming mechanism pulling the fractured fragment proximally, creating a gap at the articular surface, and an incompetent extensor mechanism [38].
- In children, olecranon fractures are usually the result of a hyperextension injury [48].
- In children, flexion injuries are usually caused by a fall on an outstretched hand with the elbow flexed, resulting from a strong eccentric contraction of the triceps pulling the olecranon over the fulcrum of the distal humerus [48].
- In children, shear injuries result from a force to the proximal ulna just anterior to the humeral condyles, causing the olecranon to fracture through metaphyseal bone with anterior displacement of the distal fragment [48].
- Olecranon fractures commonly occur with a direct blow, generally resulting in comminuted fractures, or as an avulsion injury with triceps contracture [54].
- Contraction of the triceps often results in transverse or short oblique types of olecranon fractures [54].
- In children, hyperextension injuries are frequently associated with other elbow injuries, where the direction of the associated coronal plane force determines the corresponding injuries [48].
- In children, a valgus hyperextension force may produce an associated radial neck or medial epicondyle fracture [48].
- In children, a varus hyperextension injury may be associated with lateral dislocation of the radial head or a Bado type III Monteggia lesion [48].
- In children, flexion injuries are generally transverse (perpendicular to the axis of the ulna), displaced posteriorly rather than anteriorly, and rarely associated with other injuries [48].
Associated Injuries
- Olecranon fractures typically occur in isolation; however, given the subcutaneous location of the injury, there is a risk to soft tissues as well as risk of the fracture being open [38].
- In an epidemiologic study of olecranon fractures, 22% of patients had injuries to the ipsilateral limb and 6.4% of fractures were open [38].
- In children, olecranon fractures are associated with other elbow injuries (usually the medial epicondyle) in 20% to 50% of cases [48].
Classification
- The Mayo classification is the most common classification used for olecranon fractures, based on the amount of fracture displacement, the presence of comminution, and stability of the ulnohumeral joint [38].
- In the Mayo classification, Type I fractures are nondisplaced, Type II fractures are displaced, and Type III fractures have an unstable ulnohumeral joint [38].
- In the Mayo classification, modifier A indicates simple (noncomminuted) fractures and modifier B indicates comminuted fractures [38].
- The Mayo classification is simple to use, can help guide fracture management, and has good interobserver reliability [38].
- Displaced olecranon fracture lines entered along the medial side of the trochlear notch and exited at the base of the coronoid, while minimally displaced fractures entered and exited the trochlear notch at the base of the coronoid [38].
- The Schatzker and Colton classification attempted to classify olecranon fractures based on different fracture pattern morphology; however, its application was limited [38].
- A proposed fragment-specific classification system for complex olecranon fractures is anatomically based and considers the deforming forces from ligaments and tendons [64].
- In a study of 2462 fractures, the distribution included a larger share of comminuted central fractures (29%) compared to a single-center report from Scotland [8].
- In a study of 2462 fractures, an almost threefold larger share of distal olecranon fractures was observed compared to the 6.2% reported in a Scottish study of 64 olecranon fractures [8].
- In a study of 2462 fractures, the distribution differed from a single-center report from Scotland where 74% of the fractures were simple central fractures and 81% were central fractures [8].
Classification
Classification Systems and Reproducibility
- The Mayo classification is the most commonly used classification system in clinical practice for olecranon fractures [43].
- The Mayo classification consists of 3 types with a modifier to indicate comminution [43].
- Type I fractures in the Mayo classification are nondisplaced [43].
- Type II fractures in the Mayo classification are displaced [43].
- Type III fractures in the Mayo classification have accompanying injuries [43].
- The Mayo classification was designed to simplify categorization of olecranon fractures but does not achieve this goal due to poor reproducibility [27].
- Multiple classification systems for olecranon fractures exist, including AO, Mayo, Schatzker and Colton, but none are widely accepted or provide direct and reliable advice on operative strategies [88].
- The low reproducibility rates of existing olecranon fracture classification systems raise questions about their use in clinical and research contexts [88].
- The Colton classification had the best intra- and inter-observer agreement among the Mayo, AO/OTA, and Colton & Schatzker classifications [111].
- The AO classification subsumes olecranon fractures to proximal forearm injuries [88].
- Schatzker and Colton divide olecranon fractures into groups by quantity of fragments and fracture lines [88].
Fracture Morphology and Distribution
- Quantitative 3-dimensional computed tomography analysis further clarified the fracture morphology of Mayo type I, II, and III fractures [62].
- In a study of 2462 fractures from the Swedish Fracture Register, 29% of olecranon fractures were comminuted central fractures [8].
- The share of distal olecranon fractures in the Swedish Fracture Register was almost threefold larger than the 6.2% reported in a Scottish study of 64 olecranon fractures [8].
- In a study of 64 olecranon fractures, the most frequent injury according to the AO fracture classification was the 21-B1.1 type [94].
- In a study of 64 olecranon fractures, a simple isolated displaced olecranon fracture (Mayo type 2A) was the most common according to the Mayo classification [94].
- In a study of 44 patients treated with tension band wiring, Type IIA fractures were the most common pattern, accounting for 91% of cases [107].
- In a study of 57 patients treated with a shape-memory alloy concentrator, the Mayo classification system was used to distinguish fracture displacement, presence of comminution, and ulnohumeral stability [60].
- Mayo type III fractures are categorized into anterior and posterior olecranon fracture-dislocations based on the radio-ulnar relationship [106].
- Articular impaction is a common feature of geriatric olecranon fractures [32].
Pediatric and Adolescent Considerations
- Fracture of the olecranon in a child is often only part of a complex injury to the bone and soft tissues around the elbow [30].
- The olecranon apophyseal ossification system, when combined with age and sex, successfully predicts peak height velocity within a year in 90% of cases [93].
Clinical Presentation
Mechanisms and Epidemiology
- The triceps acts as the main deforming mechanism pulling the fractured fragment proximally, creating a gap at the articular surface, and an incompetent extensor mechanism [38].
- The incidence of olecranon fractures increased by 29% over a 20-year study period in Denmark [12].
- In a Swedish study of 2462 fractures, 29% were comminuted central fractures and the share of distal olecranon fractures was almost threefold larger than in a Scottish study [8].
- In a Swedish study, high-energy injury mechanisms accounted for 5.7% of female and 11.6% of male patients overall, while low-energy mechanisms accounted for 87.4% of female and 77.8% of male patients overall [8].
- Fractures of the ipsilateral olecranon associated with the radial neck are not as rare as previously reported [42].
Physical Examination
- Pain is usually localized to the posterior part of the elbow [37].
- Given the subcutaneous location of the olecranon, the fracture itself may be palpable [37].
- Extensive posterior swelling is typical [37].
- A careful examination of the integrity of the extensor mechanism with gravity eliminated can aid surgical decision making [37].
- If present, open wounds are typically posterior and result from the direct impact of the posterior surface of the elbow against an unyielding structure [37].
- The affected extremity from shoulder to hand should be thoroughly examined for any soft tissue compromise [38].
- There is a low suspicion for open fractures given the subcutaneous nature of the olecranon [38].
- The elbow will often present with a large fluid collection subcutaneously over the olecranon [38].
- Examination of the extensor mechanism both with and without gravity eliminated should be performed to assess competency [38].
Imaging
- Plain radiographs are usually sufficient for isolated fractures of the olecranon [37].
- A true lateral radiograph is necessary to accurately identify the plane of the fracture and the number of fracture fragments [37].
- The examiner should assess for fracture comminution and impaction on radiographs [37].
- In more complex cases, CT may help delineate the comminution or impaction better, but this is not routinely required [37].
- Anteroposterior and lateral radiographs of the elbow are required for olecranon fractures [38].
- If there is concern for a radial head fracture, a radiocapitellar view of the elbow can be obtained [38].
- In the setting of an elbow dislocation, post-reduction radiographs should be obtained [38].
- Computed tomography (CT) can be used for preoperative planning for comminuted fractures of the olecranon if there is an associated radial head or coronoid fracture, but this is not routinely utilized [38].
Classification
- The Mayo classification is based on the amount of fracture displacement, the presence of comminution, and stability of the ulnohumeral joint [38].
- The modifier A (simple) and B (comminuted) in the Mayo classification indicate the presence of comminution [38].
- The Schatzker and Colton classification attempted to classify olecranon fractures based on different fracture pattern morphology, but its application was limited [38].
Prognosis and Outcomes
- A majority of olecranon fractures heal uneventfully with good or excellent results with a small loss of motion to be expected [11].
- Primary elbow instability and fracture morphology are prognostic factors for elbow function and development of arthrosis after operative treatment of olecranon fractures [45].
- The median incidence of post-traumatic osteoarthritis following isolated olecranon fractures is 19% at a median follow-up of 41 months [22].
- Patients aged 50 years or more with olecranon fracture should be evaluated for osteoporosis and fracture risks for secondary prevention of subsequent fractures [36].
Investigations
Clinical Examination
- The history may help distinguish a triceps avulsion from an actual direct blow to the elbow [37].
- Extensive posterior swelling is typical of olecranon fractures [37].
- Open wounds, if present, are typically posterior and result from the direct impact of the posterior surface of the elbow against an unyielding structure [37].
- The affected extremity from shoulder to hand should be thoroughly examined to identify associated ipsilateral injuries [38].
- The arm should be examined for soft tissue compromise, with a low suspicion for open fractures maintained given the subcutaneous nature of the olecranon [38].
Imaging
- In more complex cases, CT may help delineate comminution or impaction better, though this is not routinely required [37].
- Quantitative analysis of olecranon fractures via CT further clarified fracture morphology of Mayo type I, II, and III fractures [62].
Classification
- The distribution of olecranon fractures in a Swedish register study showed a larger share of comminuted central fractures (29%) compared to a single-center report from Scotland [8].
- The Swedish register study observed an almost threefold larger share of distal olecranon fractures than the 6.2% reported in a Scottish study of 64 olecranon fractures [8].
Pediatric Specifics
- Olecranon fractures are associated with other elbow injuries (usually the medial epicondyle) in 20% to 50% of pediatric cases [48].
- In younger children, the olecranon is predominantly cartilage, which reduces the chance of a fracture occurring with a direct blow [48].
- The thick periosteum and relatively thin metaphyseal cortex of the pediatric olecranon predispose it to minimally displaced greenstick fractures [48].
Treatment
General Principles and Indications
- Conventional indications for surgical treatment of olecranon fractures include open fractures, displaced fractures, and fractures causing disruption to the extensor mechanism affecting the insertion of the triceps muscle into the olecranon [28].
- The aims of treatment for all olecranon fractures are restoration of function and stability to the elbow joint to allow early mobilization, while minimizing associated complications [113].
- Fixation must be secure enough to permit early motion to avoid significant stiffness of the elbow joint [20].
- Good results overall are to be expected after surgical management of olecranon fractures [43].
Non-Operative Management
- Mayo type I stable undisplaced fractures can be managed effectively with nonoperative management [113].
- Some authors suggest splinting the elbow in 45° to 90° of flexion for three to four weeks followed by supervised mobilization for stable undisplaced fractures [113].
- Early active mobilization is recommended where pain allows, and time in a cast should be minimized to reduce stiffness [113].
- The acceptable degree of fracture displacement for nonoperative management is commonly quoted as < 2 mm of articular displacement on the lateral radiograph [113].
- Aggregate data support the non-operative treatment of isolated undisplaced olecranon fractures in children with good results [33].
- Nonoperative management of isolated displaced olecranon fractures in older, lower-demand patients yields satisfactory short-term and long-term outcomes [13].
Operative Management: Techniques and Outcomes
- There are four common methods in the surgical management of olecranon fractures: tension band wiring, plate fixation, intramedullary fixation, and excision of the proximal fractured fragment with re-attachment of triceps tendon [28].
- Both operative procedures (Kirschner wire tension band and anatomical locking plate) effectively treat Mayo type II olecranon fractures [9].
- Current randomized evidence suggests that tension band wiring (TBW) and plate fixation (PF) may yield similar functional outcomes for displaced olecranon fractures, based on a limited number of RCTs [24].
- Among active patients with a simple isolated, displaced fracture of the olecranon, no difference was found between TBW and plate fixation in patient-reported outcome at 1 year following surgery [35].
- Plate fixation has better efficacy and safety for Mayo II olecranon fractures compared to tension band wiring [51].
- TBW remains an effective treatment for appropriately selected olecranon fractures and outperformed plate osteosynthesis in one cohort [40].
- Internal fixation by cable pin system (CPS) is associated with a shorter healing time, fewer complications, and better function than TBW [34].
- Low-profile double-plate osteosynthesis is a safe and effective alternative treatment of olecranon fractures with excellent subjective and objective clinical outcome measures [1].
- Low-profile double-plate osteosynthesis for treating olecranon fractures resulted in good clinical outcomes [85].
- Suture tension band fixation reduces hardware complications in olecranon fractures [3].
- In all patients treated with percutaneously placed K-wires and absorbable tension-band sutures for displaced olecranon fractures, fracture united within 6 weeks and full painless range of movement was regained within 6 months [47].
- Fractures through an ununited olecranon apophysis are successfully treated with plate and screw fixation with bone grafting [71].
- The Nickel-Titanium olecranon memory connector (OMC) can be an effective alternative to treat olecranon fractures [77].
- The study supports the rationale for excision of the fragment of the olecranon with repair of the triceps mechanism as the preferred method of treatment due to significantly less morbidity compared with internal fixation [65].
- Functional results after at least 2 years were equally good with tension band and screwing techniques, but there was a considerably higher rate of separation at the fracture after screwing than after inserting a tension band [46].
Complications and Risk Factors
- Patients undergoing revisions beyond implant removal had poorer functional outcomes after olecranon fracture fixation [18].
- No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method for olecranon fracture fixation [18].
- Patients who have operative fixation of a fracture of the olecranon can be counseled that most patients keep their implants, that only 3% experience implant migration, and that technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [25].
- Risk factors associated with a poorer outcome following operative treatment of displaced olecranon fractures are patient factors, fracture morphology, and associated elbow instability or fractures [113].
Complications
General Outcomes and Mortality
- ORIF for olecranon fractures demonstrates low short-term complication rates [101].
- Specific comorbidities such as smoking and ascites were associated with increased risk of short-term complications following ORIF for olecranon fractures [101].
Hardware and Fixation Complications
- Symptomatic hardware requiring removal is a recurring and frequent problem in olecranon fracture management [43].
- The most common complication following plating of the olecranon was lack of full extension in 39% of patients [16].
- Only 3% of patients who undergo operative fixation of an olecranon fracture experience implant migration [25].
- Technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [25].
- Internal fixation by cable pin system (CPS) is associated with fewer complications than tension band wiring (TBW) for olecranon fractures [34].
- Suture tension band fixation reduces hardware complications in olecranon fractures compared to traditional techniques [3].
Long-Term and Specific Complications
- Articular impaction in olecranon fractures is associated with worse postoperative outcomes [67].
- Inadequate reduction of articular impaction contributes to increased step-off and poorer function in olecranon fractures [67].
Recovery
General Outcomes
- Articular impaction in olecranon fractures is associated with worse postoperative outcomes, with inadequate impaction reduction contributing to increased step-off and poorer function [67].
Operative Recovery
- Surgical treatment of olecranon fractures is associated with a high rate of complications, and patients undergoing revisions beyond implant removal had poorer functional outcomes [18].
- No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method following open reduction and fixation of olecranon fractures [18].
- Both tension band wiring and plate fixation yield excellent or good clinical outcomes with minimal loss of physical capacity, little pain, and disability in the majority of patients with simple and comminuted displaced olecranon fractures [68].
- Among active patients with a simple isolated, displaced fracture of the olecranon, no difference was found between tension band wiring and plate fixation in the patient-reported outcome at 1 year following surgery [35].
- Internal fixation by cable pin system is an effective method for olecranon fracture and is associated with a shorter healing time, fewer complications, and better function than tension band wiring [34].
- Tension band wiring remains an effective treatment for appropriately selected olecranon fractures and in one cohort outperformed plate osteosynthesis [40].
- Both Kirschner wire tension band combined with anatomical locking plate and standard operative procedures effectively treat Mayo type II olecranon fractures [9].
Non-Operative Recovery
- Close radiographic follow-up for nonsurgically treated olecranon fractures is recommended due to the risk of further displacement after initial nonsurgical treatment in children [2].
- All 10 cases of olecranon fractures in children treated with a sling were free of symptoms and had a full range of elbow movement at 3 weeks [17].
Elderly-Specific Outcomes
Key Evidence
- [L3] Low-profile double-plate osteosynthesis is a safe and effective alternative treatment of olecranon fractures with excellent subjective and objective clinical outcome measures. [1] (10.1016/j.otsr.2019.08.019)
- [L4] Close radiographic follow-up for nonsurgically treated olecranon fractures is recommended. [2] (10.5435/jaaos-d-25-00821)
- [L3] Future studies should focus on the long-term outcomes of this technique, as compared to traditional and more established techniques to treat olecranon fractures. [3] (10.1016/j.jseint.2026.101734)
- [L3] 96% of individuals with a closed displaced fracture of the olecranon treated by open reduction and internal fixation had excellent or good outcomes up to 25 years after the fracture. [4] (10.1067/mse.2002.124548)
- [L3] Olecranon fractures in the elderly have higher than expected 1 year mortality rates. [5] (10.1177/1758573221994860)
- [L4] Some isolated displaced (>2 mm) olecranon fractures in elderly patients can be successfully treated nonoperatively. [6] (10.1016/j.ocl.2016.08.011)
- [L4] The literature on the treatment of olecranon fractures in elderly patients is limited. [7] (10.1007/s11678-018-0488-7)
- [L4] [8] (10.1007/s00068-021-01765-2)
- [L3] Both operative procedures effectively treat Mayo type II olecranon fractures. [9] (10.1186/s12891-025-08843-1)
- [L3] Patients with olecranon fractures have essentially similar demographic characteristics compared to patients with distal radius fractures. [10] (10.1177/17585732221124301)
- [L4] A majority of olecranon fractures heal uneventfully with good/excellent results with a small loss of motion to be expected. [11] (10.1016/j.hcl.2015.07.003)
- [L3] The incidence of olecranon fractures increased by 29% over the 20-year study period. [12] (10.1186/s13018-025-05970-2)
- [L4] We found satisfactory short-term and long-term outcomes following the nonoperative management of isolated displaced olecranon fractures in older, lower-demand patients. [13] (10.2106/jbjs.l.01137)
- [L3] The timing of fixation of displaced olecranon fractures does not significantly increase the rate of early complications or reoperation. [15] (10.1016/j.jhsg.2023.09.002)
- [L3] Plating of the olecranon leads to predictable union, though the most common complication was lack of full extension in 39% of patients. [16] (10.1016/j.injury.2016.04.015)
- [L4] All 10 cases treated with a sling were free of symptoms and had a full range of elbow movement at 3 weeks. [17] (10.1016/0020-1383(75)90056-x)
- [L4] Surgical treatment of olecranon fractures is associated with a high rate of complications, and patients undergoing revisions beyond implant removal had poorer functional outcomes; however, no significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method. [18] (10.1016/j.xrrt.2025.08.004)
- [L5] Fixation must be secure enough to permit early motion to avoid significant stiffness of the elbow joint. [20] (10.5435/00124635-200007000-00007)
- [Paper] No one technique is suitable for the management of all olecranon fractures. [21] (10.1016/j.injury.2008.12.013)
- [L4] This review identified a median OA incidence of 19% at a median follow-up of 41 months following isolated olecranon fractures. [22] (10.1016/j.jse.2026.02.024)
- [L4] Displaced olecranon fractures in patients older than 70 years may be effectively managed with nonoperative measures to produce high satisfaction and functional range of motion. [23] (10.1177/1558944720944261)
- [L1] Current randomized evidence suggests that TBW and PF may yield similar functional outcomes for displaced olecranon fractures; however, these findings are based on a limited number of RCTs, with several secondary outcomes derived from only 2 studies. [24] (10.1016/j.xrrt.2026.100817)
- [L3] Patients who have operative fixation of a fracture of the olecranon can be counseled that most patients keep their implants, that only 3% experience implant migration, and that technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal. [25] (10.1007/s11999-015-4488-2)
- [L5] The Mayo classification was designed to simplify categorization of olecranon fractures but does not achieve this goal due to poor reproducibility. [27] (10.1097/corr.0000000000000614)
- [L1] [28] (10.1002/14651858.cd010144.pub2)
- [L1] This supports nonoperative treatment as a reasonable option for displaced stable olecranon fractures in elderly patients. [29] (10.2106/jbjs.24.00655)
- [L4] Fracture of the olecranon in a child is often only part of a complex injury to the bone and soft tissues around the elbow. [30] (10.1016/0020-1383(80)90009-1)
- [L4] Articular impaction is a common feature of geriatric olecranon fractures. [32] (10.5435/jaaos-d-20-01293)
- [L4] Aggregate data support the non-operative treatment of isolated undisplaced olecranon fractures with good results, and support the operative treatment of fractures displaced ≥4 mm. [33] (10.1302/2058-5241.5.190082)
- [L1] Internal fixation by CPS is an effective method for olecranon fracture and is associated with a shorter healing time, fewer complications and better function than TBW. [34] (10.1177/147323001204000324)
- [L1] Among active patients with a simple isolated, displaced fracture of the olecranon, no difference was found between TBW and plate fixation in the patient-reported outcome at 1 year following surgery. [35] (10.2106/jbjs.16.00773)
- [L4] Our results suggest that patients aged 50 years or more with olecranon fracture should be evaluated for osteoporosis and fracture risks for secondary prevention of subsequent fractures. [36] (10.11005/jbm.2017.24.3.175)
- [L4] TBW remains an effective treatment for appropriately selected olecranon fractures and in this cohort outperformed plate osteosynthesis. [40] (10.1007/s00590-015-1724-0)
- [L5] Nonoperative management of olecranon fractures in elderly patients offers comparable functional outcomes to surgical intervention while significantly reducing exposure to potential complications and healthcare costs. [41] (10.1016/j.injury.2025.112579)
- [L3] Fractures of the ipsilateral olecranon associated with the radial neck are not so rare as previously reported. [42] (10.1186/s13018-021-02373-x)
- [L4] [43] (10.1016/j.jhsa.2012.12.036)
- [L3] Primary elbow instability and fracture morphology are prognostic factors for elbow function and development of arthrosis after operative treatment of olecranon fractures. [45] (10.1016/j.injury.2003.12.002)
- [L4] [46] (10.1016/0020-1383(87)90386-x)
- [L4] In all patients, fracture was united within 6 weeks and all patients regained full painless range of movement of elbow within 6 months. [47] (10.1097/bte.0b013e318254642f)
- [L1] Plate has better efficacy and safety for Mayo II olecranon fractures. [51] (10.1186/s13018-022-03262-7)
- [L4] [60] (10.1186/s13018-020-01982-2)
- [L4] Quantitative analysis of olecranon fractures further clarified fracture morphology of Mayo type I, II, and III fractures. [62] (10.1016/j.jse.2015.10.002)
- [L4] This proposed classification system is anatomically based and considers the deforming forces from ligaments and tendons. [64] (10.1016/j.jse.2023.12.021)
- [L3] The study supports the rationale for excision of the fragment of the olecranon with repair of the triceps mechanism as the preferred method of treatment of fractures of the olecranon due to significantly less morbidity compared with internal fixation. [65] (10.2106/00004623-198163050-00005)
- [L3] Articular impaction in olecranon fractures is associated with worse postoperative outcomes, with inadequate impaction reduction contributing to increased step-off and poorer function. [67] (10.1302/0301-620x.108b1.bjj-2025-0444.r1)
- [L3] Both TBW and plate fixation yield excellent/good clinical outcomes with minimal loss of physical capacity, little pain and disability in the majority of patients with simple and comminuted displaced olecranon fractures. [68] (10.1007/s00402-014-2021-9)
- [L4] The authors conclude that these measurements guide the surgeon to obtain a more reliable length of the olecranon and maintain articular geometry during fixation. [69] (10.1002/ca.20431)
- [L5] Fractures through an ununited olecranon apophysis are successfully treated with plate and screw fixation with bone grafting. [71] (10.1142/s2424835520720017)
- [L2] The study showed that OMC could be an effective alternative to treat olecranon fractures. [77] (10.1007/s00264-013-1878-5)
- [L3] Low-profile double-plate osteosynthesis for treating olecranon fractures resulted in good clinical outcomes. [85] (10.1016/j.jse.2020.01.091)
- [L4] [88] (10.1016/j.jor.2019.09.017)
- [L3] When combined with age and sex, the olecranon system successfully predicts PHV within a year in 90% of cases, establishing a single lateral view of the olecranon as a simple alternative to more complex grading systems. [93] (10.2106/jbjs.20.01856)
- [L3] [94] (10.1016/j.injury.2011.10.017)
- [L4] ORIF for olecranon fractures demonstrates low short-term complication rates; however, specific comorbidities such as smoking and ascites were associated with increased risk. [101] (10.1016/j.jseint.2025.06.017)
- [Paper] [106] (10.1007/s00402-016-2593-7)
- [L4] [107] (10.1016/j.jhsa.2013.05.012)
- [L4] [111] (10.1016/j.injury.2024.111496)
- [L4] [113] (10.1302/0301-620x.105b2.bjj-2022-0703.r1)
References
[1] Clinical evaluation of double-plate osteosynthesis for olecranon fractures: A retrospective case-control study. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2019.08.019
[2] Further Displacement After Initial Nonsurgical Treatment of Minimally Displaced Olecranon Fractures in Children. Journal of the American Academy of Orthopaedic Surgeons. 2026. DOI: 10.5435/jaaos-d-25-00821
[3] Suture tension band fixation reduces hardware complications in olecranon fractures: a comparative study. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101734
[4] Comparison of tension-band and figure-of-eight wiring techniques for treatment of olecranon fractures. Journal of Shoulder and Elbow Surgery. 2002. DOI: 10.1067/mse.2002.124548
[5] Complications and mortality associated with olecranon fractures in the elderly: a retrospective cohort comparison from a large level one trauma centre. Shoulder & Elbow. 2021. DOI: 10.1177/1758573221994860
[6] Controversies in Fractures of the Proximal Ulna. Orthopedic Clinics of North America. 2017. DOI: 10.1016/j.ocl.2016.08.011
[7] Nonoperative treatment of olecranon fractures in the elderly—a systematic review. Obere Extremität. 2018. DOI: 10.1007/s11678-018-0488-7
[8] Epidemiology, classification and treatment of olecranon fractures in adults: an observational study on 2462 fractures from the Swedish Fracture Register. European Journal of Trauma and Emergency Surgery. 2021. DOI: 10.1007/s00068-021-01765-2
[9] Efficacy evaluation of Kirschner wire tension band combined with anatomical locking plate in the treatment of Mayo type II olecranon fractures. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08843-1
[10] Mortality and subsequent fractures of patients with olecranon fractures compared to other upper extremity osteoporotic fractures. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221124301
[11] Olecranon Fractures. Hand Clinics. 2015. DOI: 10.1016/j.hcl.2015.07.003
[12] Epidemiology and Treatment of Olecranon Fractures: a nationwide register-based analysis of 27,880 cases in Denmark from 1999 to 2018. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05970-2
[13] Nonoperative Management of Displaced Olecranon Fractures in Low-Demand Elderly Patients. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.l.01137
[15] Timing of Olecranon Fracture Fixation Does Not Affect Early Complication or Reoperation Rates. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2023.09.002
[16] Outcomes after plating of olecranon fractures: A multicenter evaluation. Injury. 2016. DOI: 10.1016/j.injury.2016.04.015
[17] Olecranon fractures in children. Injury. 1975. DOI: 10.1016/0020-1383(75)90056-x
[18] Risk factors for complications and poor function after open reduction and fixation of olecranon fractures. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.08.004
[20] Olecranon Fractures: Treatment Options. Journal of the American Academy of Orthopaedic Surgeons. 2000. DOI: 10.5435/00124635-200007000-00007
[21] Olecranon fractures. Injury. 2009. DOI: 10.1016/j.injury.2008.12.013
[22] Incidence of Post-traumatic Osteoarthritis in Olecranon Fractures and the Role of Instability and Comminution in its Development: A Systematic Review. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.024
[23] Nonoperative Management of Olecranon Fractures in Elderly Patients: A Systematic Review. HAND. 2020. DOI: 10.1177/1558944720944261
[24] Comparative efficacy and safety of tension band wiring versus plate fixation for olecranon fractures: a meta-analysis and trial sequential analysis of randomized clinical trials. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100817
[25] Factors Associated With Reoperation After Fixation of Displaced Olecranon Fractures. Clinical Orthopaedics & Related Research. 2016. DOI: 10.1007/s11999-015-4488-2
[27] Classifications in Brief: Mayo Classification of Olecranon Fractures. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000614
[28] Surgical interventions for treating fractures of the olecranon in adults. Cochrane Database of Systematic Reviews. 2014. DOI: 10.1002/14651858.cd010144.pub2
[29] Surgery for Olecranon Fractures in the Elderly (SOFIE). Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00655
[30] Fractures of the olecranon in children. Injury. 1980. DOI: 10.1016/0020-1383(80)90009-1
[32] Incidence and Management of Articular Impaction in Geriatric Olecranon Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-20-01293
[33] Paediatric olecranon fractures: a systematic review. EFORT Open Reviews. 2020. DOI: 10.1302/2058-5241.5.190082
[34] Randomized Prospective Study of Olecranon Fracture Fixation: Cable Pin System versus Tension Band Wiring. Journal of International Medical Research. 2040. DOI: 10.1177/147323001204000324
[35] Plate Versus Tension-Band Wire Fixation for Olecranon Fractures. Journal of Bone and Joint Surgery. 2017. DOI: 10.2106/jbjs.16.00773
[36] Olecranon Fractures Have Features of Osteoporotic Fracture. Journal of Bone Metabolism. 2017. DOI: 10.11005/jbm.2017.24.3.175
[37] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Elbow > II. Olecranon Fractures.
[38] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Assessment of Olecranon Fractures.
[40] Outcome after olecranon fracture repair: Does construct type matter?. European Journal of Orthopaedic Surgery & Traumatology. 2015. DOI: 10.1007/s00590-015-1724-0
[41] How should displaced olecranon fractures in the elderly be treated - nonoperatively or operatively?. Injury. 2025. DOI: 10.1016/j.injury.2025.112579
[42] Management strategies of pediatric ipsilateral olecranon with associated radial neck fractures based on multicenter experience. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02373-x
[43] Olecranon Fractures. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.12.036
[45] Olecranon fractures in adults: factors influencing outcome. Injury. 2004. DOI: 10.1016/j.injury.2003.12.002
[46] The complications of surgical treatment of displaced fractures of the olecranon. Injury. 1987. DOI: 10.1016/0020-1383(87)90386-x
[47] Outcome of Open Reduction and Internal Fixation With Percutaneously Placed K-wires and Absorbable Tension-band Sutures for Displaced Olecranon Fractures in Children. Techniques in Shoulder & Elbow Surgery. 2012. DOI: 10.1097/bte.0b013e318254642f
[48] Tachdjian S Pediatric Orthopaedics From The Texas Scottish Rite Hospital For Children E Book. Pigmented Villonodular Synovitis and Giant Cell Tumor of the Tendon Sheath > Olecranon Fractures.
[51] Efficacy and safety of tension band wire versus plate for Mayo II olecranon fractures: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2022. DOI: 10.1186/s13018-022-03262-7
[54] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > OLECRANON FRACTURES (ICD-9:813.01).
[60] Application of a novel shape-memory alloy concentrator in displaced olecranon fractures: a report of the technique and mid-term clinical results. Journal of Orthopaedic Surgery and Research. 2020. DOI: 10.1186/s13018-020-01982-2
[62] Quantitative 3-dimensional computed tomography analysis of olecranon fractures. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.10.002
[64] A novel fragment specific classification of complex olecranon fractures: 3-dimensional model design, radiological validation, and proposed surgical algorithm. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2023.12.021
[65] Operative treatment of olecranon fractures. Excision or open reduction with internal fixation.. The Journal of Bone & Joint Surgery. 1981. DOI: 10.2106/00004623-198163050-00005
[67] Articular impaction of olecranon fracture is associated with poor postoperative clinical outcome. The Bone & Joint Journal. 2026. DOI: 10.1302/0301-620x.108b1.bjj-2025-0444.r1
[68] Simple and comminuted displaced olecranon fractures: a clinical comparison between tension band wiring and plate fixation techniques. Archives of Orthopaedic and Trauma Surgery. 2014. DOI: 10.1007/s00402-014-2021-9
[69] Radiographic measurements of normal elbows: Clinical relevance to olecranon fractures. Clinical Anatomy. 2006. DOI: 10.1002/ca.20431
[71] Olecranon Fracture through Persistent Olecranon Apophysis in a 21-Year-Old Male: A Case Report and Systematic Review of the Literature. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520720017
[77] Design and application of Nickel-Titanium olecranon memory connector in treatment of olecranon fractures: a prospective randomized controlled trial. International Orthopaedics. 2013. DOI: 10.1007/s00264-013-1878-5
[85] Can low-profile double-plate osteosynthesis for olecranon fractures reduce implant removal? A retrospective multicenter study. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.01.091
[88] Plate fixation and tension band wiring after isolated olecranon fracture comparison of outcome and complications. Journal of Orthopaedics. 2020. DOI: 10.1016/j.jor.2019.09.017
[93] The Relationship of Olecranon Apophyseal Ossification and Sanders Hand Scores with the Timing of Peak Height Velocity in Adolescents. Journal of Bone and Joint Surgery. 2021. DOI: 10.2106/jbjs.20.01856
[94] The epidemiology of fractures of the proximal ulna. Injury. 2012. DOI: 10.1016/j.injury.2011.10.017
[101] Short-term complications of open reduction and internal fixation of olecranon fractures: a national database study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.06.017
[106] Fracture line distribution of olecranon fractures. Archives of Orthopaedic and Trauma Surgery. 2016. DOI: 10.1007/s00402-016-2593-7
[107] Use of Kirschner Wires With Eyelets for Tension Band Wiring of Olecranon Fractures. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.05.012
[111] Olecranon fractures: An old fixation device for a new surgical technique. Injury. 2024. DOI: 10.1016/j.injury.2024.111496
[113] Olecranon fractures. The Bone & Joint Journal. 2023. DOI: 10.1302/0301-620x.105b2.bjj-2022-0703.r1