Patients › Shoulder
Revisão de artroplastia de ombro
Revision shoulder replacement — addressing failure of prior shoulder replacements with a reverse design.
Por que esta cirurgia foi sugerida
O Dr. Kieran Hirpara, cirurgião de membro superior no Mater Private Hospital Rockhampton, começa com as opções menos invasivas adequadas ao seu caso. Em geral, os pacientes são encaminhados à nossa clínica pelo médico de família; caso um fisioterapeuta tenha sugerido que você nos procure, ainda assim será necessário um encaminhamento do seu médico de família para que você tenha direito ao reembolso do Medicare. Na primeira consulta, colhemos o histórico clínico, examinamos seu ombro e solicitamos exames de imagem quando necessário. Para problemas de longa data, geralmente tentamos primeiro tratamentos não cirúrgicos, como mudança de atividades, fisioterapia ou uso de talas, e só consideramos a cirurgia quando esses métodos não trazem melhoria suficiente.
A revisão da artroplastia de ombro é uma segunda cirurgia que substitui algumas ou todas as peças da artroplastia anterior. Sugerimos esse procedimento quando a primeira artroplastia já não funciona bem, geralmente porque as peças se soltaram, a articulação ficou instável ou a cavidade acetabular se desgastou. A dor intensa e a rigidez são os principais motivos pelos quais os pacientes procuram nós para esta cirurgia. O objetivo é reduzir a dor, melhorar a mobilidade e tornar o ombro mais estável. A taxa de sobrevivência do implante na revisão da artroplastia reversa de ombro é de 85% aos dez anos. Conversaremos sobre o que esta cirurgia pode ou não fazer por você, e decidiremos juntos se ela é adequada ao seu caso.
Antes da operação
Será necessário realizar exames de imagem no seu ombro para que possamos planejar a cirurgia. Geralmente, radiografias simples de vários ângulos são suficientes. Por vezes, também é indicada uma ressonância magnética (exame que mostra os tecidos moles) ou uma ultrassonografia. Antes do dia da cirurgia, receberá instruções claras da nossa equipe. Você deverá suspender a ingestão de alimentos e líquidos por sete horas antes do procedimento. Pedimos sete horas em vez das seis habituais para que seja possível antecipar sua cirurgia caso a lista de cirurgias do dia se esgote mais cedo. Traga uma lista por escrito de todos os medicamentos que está tomando, pois alguns talvez precisem ser interrompidos. Providencie alguém para levá-lo para casa. Use roupas largas e confortáveis. Caso tenha outras condições médicas, poderá ser necessário fazer exames de sangue ou uma avaliação com o anestesista (o especialista responsável pela aplicação da anestesia).
No dia da cirurgia
Você chegará à unidade de admissão cirúrgica do hospital, onde será registrado e preparado para a sala de operações. Em seguida, encontrará o anestesista. Esta cirurgia é realizada sob anestesia geral combinada com bloqueio nervoso regional. O anestesista se encontrará com você antes da operação e explicará ambos os procedimentos.
Depois, você será levado para a sala de operações, onde a cirurgia será realizada. Ao final, acordará na área de recuperação. As enfermeiras monitorarão você ali, enquanto a anestesia vai passando. Assim que seu estado se estabilizar, você será transferido para o quarto.
O que envolve a operação
A revisão da prótese de ombro é uma cirurgia aberta realizada por meio de uma única incisão na área a ser operada. O cirurgião trabalha através dessa única incisão para alcançar a articulação.
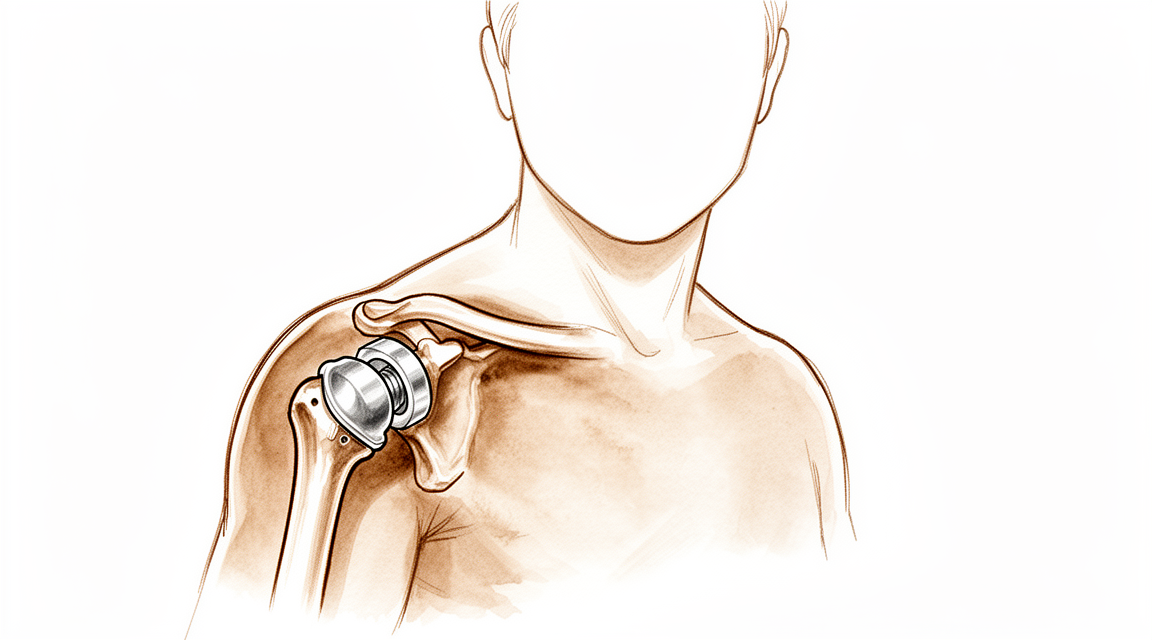
Os passos exatos dependem do motivo pelo qual a primeira prótese falhou. O cirurgião pode remover parte ou todas as peças desgastadas ou soltas, substituindo-as por novas superfícies metálicas e plásticas. Caso o osso da cavidade articular esteja desgastado, pode-se inserir um pequeno enxerto ósseo (um pedaço de osso usado para reconstruir a área ausente), de modo que uma nova peça para a cavidade possa ser instalada. Sempre que possível, o cirurgião tentará colocar um novo componente na cavidade em vez de deixá-la vazia. Se a articulação estiver instável, o cirurgião pode optar por uma prótese reversa, na qual as posições da esfera e da cavidade são trocadas para tornar a articulação mais estável. Às vezes, o cimento antigo ao redor da parte da prótese situada no braço é mantido, e um novo cimento é aplicado por cima, em vez de remover todo o cimento anterior.
Após a colocação e verificação das novas peças, a incisão é fechada. Primeiro, uma malha autoadesiva fina é colocada sobre a incisão fechada, mantendo as bordas da pele unidas. Em seguida, um adesivo cutâneo líquido é aplicado sobre essa malha; ele endurece e sela toda a área. Esse adesivo permanece no local por cerca de uma a duas semanas, quando se solta e se desprende sozinho, não sendo necessário removê-lo.
Após a operação
Você acordará na sala de recuperação, sob a vigilância das enfermeiras. Assim que estiver estável, será transferido para o quarto. A maioria dos pacientes permanece uma ou duas noites no hospital após esta operação. O controle da dor é personalizado para você; além disso, o bloqueio nervoso aplicado durante a cirurgia costuma manter o ombro confortável nos primeiros momentos. Seu braço ficará apoiado em uma tipoia simples para maior conforto; ela é retirada durante os exercícios e para a higiene. Deixamos o curativo no lugar por cerca de 10 dias; por favor, não o retire antes disso, a menos que receba instrução em contrário. Trocamos ou retiramos o curativo quando o examinamos. Um fisioterapeuta poderá visitá-lo para iniciar movimentos suaves. Por favor, providencie alguém para ficar com você nas primeiras 24 horas após voltar para casa.
Recuperação
Nos primeiros dias, o foco é o repouso e o conforto. O seu ombro ficará dolorido e inchado; o bloqueio nervoso aplicado durante a cirurgia costuma mantê-lo adormecido inicialmente. À medida que esse efeito passa, a dor se torna mais perceptível. O alívio da dor adequado ao seu caso, o repouso e movimentos suaves são fundamentais. O inchaço diminui gradualmente ao longo das primeiras semanas.
Para maior conforto, o seu braço fica apoiado em uma tipoia simples. Ela é retirada para a realização de exercícios e para a higiene. Um fisioterapeuta orientará os movimentos suaves no início, aumentando depois a força e a amplitude de movimento conforme o ombro permitir. No dia a dia, inicialmente você precisará de ajuda para tarefas mais pesadas, mas o uso leve do braço voltará de forma progressiva. Nos primeiros dias, dormir sentado ou com travesseiros de apoio costuma ser mais confortável.
A recuperação ocorre em etapas, não de uma só vez. Quando o cirurgião autorizar, geralmente na consulta de seis semanas, você poderá voltar a dirigir; consulte nosso guia sobre dirigir após cirurgia no membro superior. À medida que os movimentos retornam, tarefas cotidianas como se vestir e cozinhar ficam mais fáceis. Quando o ombro estiver suficientemente forte, a maioria das pessoas retorna ao trabalho e muitas voltam a praticar esportes ou atividades que gostam. Muitos percebem que a melhora do ombro continua ao longo do primeiro ano.
O seu cronograma pode ser diferente do de outras pessoas. O cirurgião e o fisioterapeuta orientarão você em cada consulta, ajustando o plano conforme a evolução da recuperação do seu ombro.
O que pode dar errado
A maioria dos pacientes se recupera bem, mas, ocasionalmente, podem surgir problemas. O seu cirurgião e a equipe o monitoram de perto para detectar qualquer problema precocemente.
Às vezes, as próteses se soltam ou a articulação torna-se instável. Você pode sentir o retorno da dor que tinha antes ou uma nova dor que não existia após a cirurgia. Algumas pessoas percebem um som de clique, rangido ou estalo, ou a sensação de que o ombro está se deslocando. Se isso acontecer, mencione o fato na próxima consulta ou ligue para a clínica mais cedo caso a dor piore.
A infecção é um risco em qualquer cirurgia de substituição articular. Fique atento a uma dor profunda e latejante que não melhora com analgésicos comuns, vermelhidão que se espalha a partir da incisão, calor no ombro ou febre. Caso note algum desses sinais, ligue imediatamente para a clínica. Se sentir-se mal, com febre ou se a vermelhidão se espalhar rapidamente, vá ao pronto-socorro.
Às vezes, pode ocorrer uma fratura no osso ao redor das próteses; isso geralmente é detectado em radiografias feitas logo após a cirurgia. Você sentiria uma dor aguda e súbita, pior do que a dor pós-operatória habitual, às vezes acompanhada de um estalo ou sensação de “cedimento” ósseo. Se isso acontecer, informe o seu cirurgião ou a clínica.
Algumas condições de saúde e circunstâncias aumentam o risco de complicações. Entre elas estão a doença de Parkinson, má nutrição antes da cirurgia, fratura por fragilidade óssea (quebra causada por uma queda leve) prévia à operação, cirurgias anteriores no ombro, artrite inflamatória (artrite decorrente de um sistema imunológico hiperativo), necessidade de uso de medicamentos anticoagulantes após a cirurgia e a realização de cirurgias nos dois ombros em intervalo curto. Se alguma dessas situações se aplicar a você, levaremos isso em conta no planejamento e o monitoraremos mais de perto.
A tabela de complicações nesta página apresenta as taxas típicas, caso deseje conhecer os detalhes.
Quando nos contatar
Ligue para a clínica se tiver febre, vermelhidão crescente ou secreção na ferida, ou dor que continua piorando. Dirija-se ao pronto-socorro se sentir falta de ar repentina, tiver inchaço ou dor na panturrilha, ou se a dor no ombro se tornar súbita e intensa. Ligue imediatamente se perder a sensibilidade no braço ou na mão, ou se não conseguir movê-los. Em caso de dúvida, ligue para nós. Preferimos ser contatados com antecedência.
Onde ler mais sobre a condição
Esta página trata especificamente da operação. A condição que ela visa tratar, incluindo as evidências sobre quando a cirurgia é benéfica e quando não é, é abordada com mais detalhes na página Artrite do Ombro.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humerus comprises four main parts: the humeral head, greater tuberosity, lesser tuberosity, and humeral shaft [3].
- The articular head of the proximal humerus is spherical with a diameter of 37 to 57 mm [3].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [3].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [3].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [3].
- The anatomic neck of the proximal humerus is located at the junction of the articular surface and the tuberosities [3].
- The surgical neck represents an indistinct region below the tuberosities but above the humeral shaft [3].
- The greater tuberosity serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [3].
- The lesser tuberosity serves as the attachment site for the subscapularis tendon [3].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [3].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [4].
- The neck-shaft angle measures an average of 135 degrees [4].
- The humeral head is retroverted an average of 30 degrees [4].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [5].
- The glenoid is connected with the flat body of the scapula by the scapular neck [5].
- The coracoid process curves forwards from the superior surface of the scapular neck [5].
- The scapular spine ends in a flattened bony process, the acromion, which curves forwards [5].
- The highest concentration of bony mass in the scapula is located in the glenoid, the scapular neck, and the lateral border of the scapular body [5].
- Two bony pillars transmit compressive forces from the glenoid fossa: the lateral pillar and the spinal pillar [5].
- The lateral pillar connects the inferior border of the glenoid with the inferior angle [5].
- The spinal pillar arises from the central part of the glenoid and continues medially to become part of the base of the scapular spine [5].
- The weakest bone in the scapula is located primarily in the central part of the infraspinous fossa [5].
- The weakest area of the circumference of the biomechanical body of the scapula is the spinomedial angle [5].
- The subchondral bone of the glenoid is relatively flat, with articular concavity augmented by cartilage and a circumferential labrum [6].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [6].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [6].
- The acromion has three ossification centers: the metacromion, mesoacromion, and preacromion [6].
- Failure of fusion of the acromial ossification centers results in os acromiale [6].
Vascular Anatomy
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [3].
- The posterior humeral circumflex artery travels with the axillary nerve and enters the quadrilateral space posteriorly [3].
- The anterior humeral circumflex artery arises from the axillary artery at the inferior border of the subscapularis [3].
- The anterior humeral circumflex artery provides vascular inflow to the humeral head via its terminal anterolateral branch, known as the artery of Laing or arcuate artery [3].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon [3].
- The ascending branch of the anterior humeral circumflex artery enters the humeral head at the interface of the bicipital groove and greater tuberosity [3].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [3].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [3].
- The major blood supply to the humeral head is through the ascending branch of the anterior humeral circumflex artery, which penetrates the head at the bicipital groove and becomes the arcuate artery [4].
- Fractures of the anatomic neck have a poor prognosis because of complete disruption of the blood supply to the head [4].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [6].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [6].
Soft Tissue & Ligamentous Anatomy
- The rotator cuff consists of four muscles: the subscapularis, supraspinatus, infraspinatus, and teres minor [4].
- The teres major is not a rotator cuff muscle [4].
- The rotator cuff muscles serve as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [4].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [4].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch [3].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [3].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula [7].
- The subscapular bursa communicates with the joint cavity between the superior and middle glenohumeral ligaments [7].
- The subscapular bursa protects the tendon of the subscapularis at the point where it passes under the base of the coracoid process and over the neck of the scapula [7].
- The subscapular bursa often houses loose bodies in the shoulder [7].
- The subscapular bursa is a region in which synovitis of the shoulder may be most intense [7].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [6].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [6].
- Laxity of the rotator interval results in inferior laxity (the sulcus sign) [6].
- Contracture of the rotator interval is seen with adhesive capsulitis [6].
- The coracohumeral ligament restricts external rotation in adduction [6].
- The coracohumeral ligament is a static restraint to inferior and posterior translation in adduction and external rotation [6].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [6].
- With the coracohumeral ligament, the superior glenohumeral ligament forms a pulley that provides restraint against medial subluxation of the long head of the biceps tendon [6].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [6].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation of the glenohumeral joint in 90° of abduction and external rotation [6].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [6].
- The glenoid labrum provides concavity and up to 50% of marginal glenoid socket depth [6].
- The superior transverse scapular ligament arises from the medial base of the coracoid overlying the suprascapular notch [6].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the nerve runs deep to it [6].
- Entrapment of the suprascapular nerve at the superior transverse scapular ligament causes denervation of both the supraspinatus and the infraspinatus [6].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [6].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [6].
Pathophysiology & Biomechanics
- Stability and function of the glenohumeral joint are provided by the interaction of structures that promote a near global range of motion and purposeful function [3].
- External loads transferred to the shoulder girdle are initially offset by joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion [3].
- Moderate and large loads are counterbalanced by the deltoid and rotator cuff and by the capsulolabral and bone structures, respectively [3].
- Proximal humeral fractures alter complex interactions, resulting in pain, decreased range of motion and stiffness, and disability [3].
- Displacement of proximal humeral fracture fragments is based on the deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [3].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement [3].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement [3].
- The pectoralis major inserts on the humeral shaft and displaces it medially [3].
- A fracture involving the anatomic neck is prognostically worse than fractures involving other regions of the proximal humerus with respect to the potential disruption of the vascular supply to the humeral head and subsequent development of avascular necrosis [3].
- Displaced proximal humeral fractures can impede normal movement of structures passing under the coracoacromial arch, causing impingement and disruption of normal glenohumeral motion [3].
- In proximal humeral fractures, the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that limit normal glenohumeral motion [3].
- The malcentering of the joint reaction force on the glenoid leads to posterior instability, posterior glenoid wear, and "rocking horse" loosening of prosthetic glenoid components [2].
- The point of contact of the humeral articular surface on the glenoid articular surface reflects the degree of centering of the net humeral joint reaction force on the glenoid [2].
- Arthritis usually involves the central aspect of the humeral head [2].
- Joint space narrowing is most evident on the axillary view taken with the arm in elevation compared to images made with the arm at the side [2].
- The axillary view taken with the arm in elevation demonstrates posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [2].
- Dense scarring from previous operations commonly complicates the surgical approach in revision shoulder arthroplasty [15].
- Exposure in revision shoulder arthroplasty is typically quite difficult, making component implantation less predictable [15].
- Preexisting instability or subscapularis deficiency often is not correctable with an anatomic revision arthroplasty [15].
- The rotator cuff is often deficient in patients with massive (>4 cm) proximal humeral bone loss [15].
Investigations
Plain Radiography
- The purpose of shoulder imaging is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [2].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder care [2].
- The first key radiographic view is the anteroposterior (AP) view taken in the plane of the scapula such that the x-ray beam passes through the glenohumeral joint [2].
- The AP view in the plane of the scapula shows the superoinferior position of the humeral head relative to the glenoid, the presence of osteophytes on the humeral head and glenoid, narrowing of the joint space, and the degree of medial displacement of the humerus in relation to the lateral acromial line [2].
- The AP view in the plane of the scapula also shows the quality of the humeral and glenoid bone, the presence of loose bodies, and whether there is humeral head collapse or deformity [2].
- The second key radiographic view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [2].
- The axillary view is oriented so that both the spinoglenoid notch and the scapular neck are visible [2].
- The axillary view demonstrates a different perspective of humeral anatomy, the amount of glenoid bone, the shape of the glenoid, its version in relation to the plane of the scapula, and the relationship of the humeral head to the glenoid fossa [2].
- The axillary view is referred to as the “truth view” because it demonstrates glenohumeral relationships in the functional position of elevation [2].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view which is taken in elevation [2].
- Many axillary views sent for consultation are taken without standardization, making it impossible to determine important features of the glenohumeral joint [2].
- When taken properly, standardized anteroposterior and axillary views indicate the thickness of the cartilage space between the humerus and the glenoid, relative positions of the humeral head and glenoid, presence of osteophytes, degree of osteopenia, and extent of bony deformity and erosion [2].
- Joint space narrowing is most evident on the axillary truth view as opposed to images made with the arm at the side [2].
- The axillary truth view can show posterior subluxation or “functional decentering” that is not evident in images taken with the arm at the side [2].
- The degree of posterior subluxation can be measured as the position of the center of the humeral head in relation to the plane of the scapula [2].
- The degree of posterior subluxation can be measured as the position of the center of the humeral head in relation to the glenoid face [2].
- The degree of posterior subluxation can be measured as the point of contact of the humeral articular surface on the glenoid articular surface [2].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and “rocking horse” loosening of prosthetic glenoid components [2].
- At least two X-ray views should be obtained: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [11].
Computed Tomography
- CT scans may offer a few degrees of increased precision in the measurement of glenoid version [2].
- The authors are not convinced that the increased precision of CT scans in measuring glenoid version improves the quality of the surgery or the clinical outcome [2].
- There is information that can be gathered from properly taken plain films that cannot be obtained from CT scans [2].
- Three-dimensional reconstructions can reveal fine details of the shoulder anatomy, but this additional information rarely changes the planning or conduct of the arthroplasty [2].
- Computed tomography (CT) is helpful for planning fracture surgery and shoulder joint replacement [11].
Magnetic Resonance Imaging
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head, or a bone tumour [11].
- MRI can identify labral tears and rotator cuff tears [11].
- The accuracy of MRI for identifying labral tears and rotator cuff tears is enhanced by combining the scan with arthrography [11].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [11].
- Ultrasonography can be useful in guiding injections or barbotage (aspirating calcific deposits in the rotator cuff) [11].
- The most commonly performed joint examination using ultrasonography is the shoulder examination [9].
- The accuracy of rotator cuff ultrasonography depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [9].
General Imaging Principles
- The diagnosis of a stiff shoulder depends on awareness of the problem, with history and physical examination being paramount and ancillary studies helpful in certain circumstances [1].
- Unless a specific research protocol is in place, the temptation to “overimage” should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [2].
- Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [2].
- The shoulder is a three-dimensional structure that cannot be represented by a single planar view [13].
- Critical relationships, such as the degree of centering of the humeral head, change with the position of the arm [13].
- Shoulder pathology may be found in a large number of different bones and soft tissues [13].
- Overlying and superimposed structures as well as metallic implants may complicate imaging the structures of interest [13].
- Surgeons need to develop a judicious approach to imaging that yields the information necessary to treat the patient while avoiding the tendency to "over-image" [13].
References
[1] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > SUMMARY.
[2] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[3] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[4] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[5] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[6] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[7] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[9] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[11] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[13] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.
[15] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > REVISION SHOULDER ARTHROPLASTY > INDICATIONS.