为何建议进行此手术
Mater Private Hospital Rockhampton 的上肢外科医生 Kieran Hirpara 医生会根据您的具体伤情制定治疗方案。患者通常由全科医生转诊至我们的诊所;如果理疗师建议您就诊,您仍需获得全科医生的转诊,才有资格享受 Medicare 报销。在就诊时,我们会采集病史,检查您的手部,并在必要时安排影像学检查,以明确损伤情况。
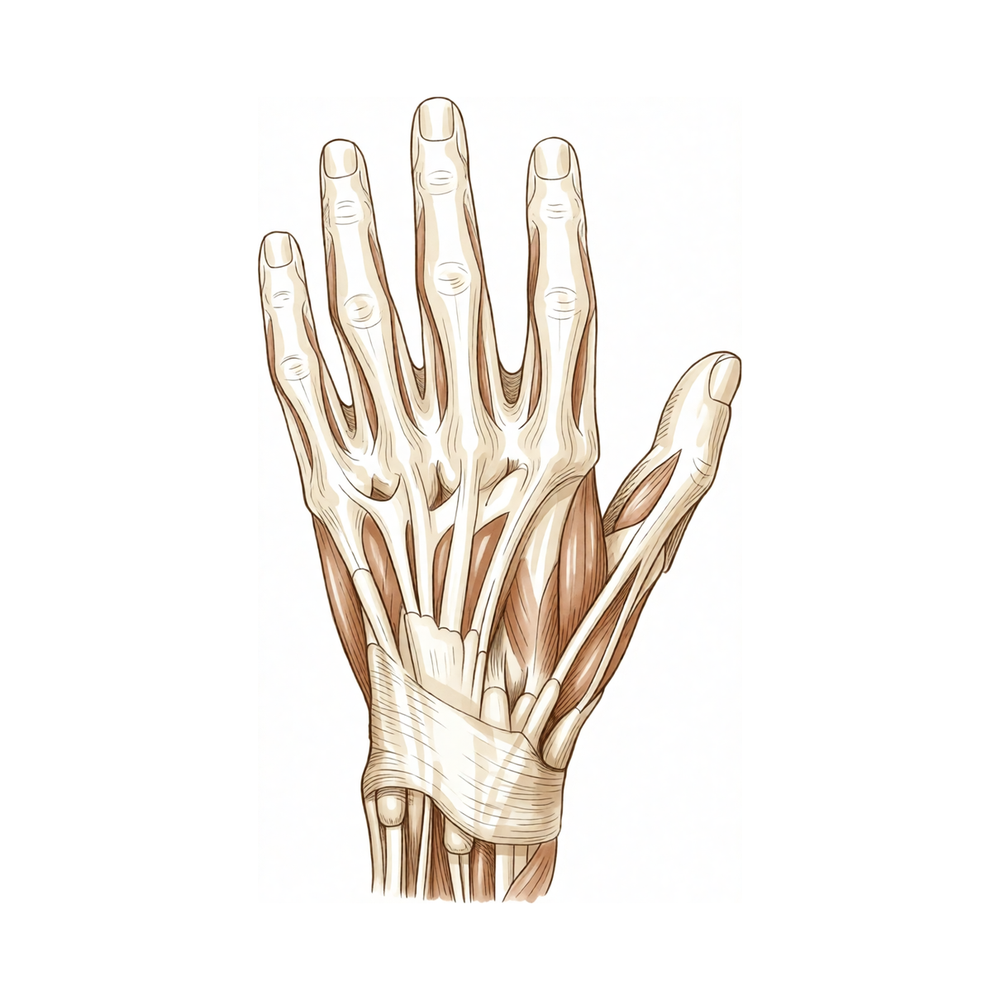
伸肌腱是位于手背和手指背侧、用于伸直手指的肌腱。它们可能因切割伤而断裂,因挤压伤或运动损伤而撕裂,或在骨折后发生断裂。许多此类损伤(如锤状指)无需手术,可通过支具固定治疗。其他情况则需要修复,尤其是开放性切割伤、陈旧性撕裂或肌腱严重受损的损伤。当支具固定未能提供足够改善,或损伤为急性且肌腱无法自行愈合时,我们会考虑进行手术。手术旨在恢复肌腱的长度和强度,使您的手指或拇指能够再次伸直,从而恢复手部功能并消除疼痛。
手术前
一旦您的手术预约确认,我们将在您就诊前的几天内提供明确的指导说明。您需要在手术前七小时停止进食和饮水。我们要求提前七小时禁食,以便如果手术室手术日程提前,可以提前安排您的手术。您的外科医生会告知您哪些常用药物需要停用,哪些需要继续服用,因此请携带一份书面清单,列出您正在服用的所有药物,包括任何抗凝药物。请安排他人在术后驾车送您回家,因为您将无法自行驾驶。请穿着宽松、舒适的衣物,且袖子易于脱下。大多数人无需其他准备工作。如果您有其他健康状况,可能需要进行血液检查或接受麻醉医生的评估,麻醉医生是负责实施麻醉的医生。
手术当日
您将前往医院的手术入院单元,在那里办理入院手续并进行术前准备。您将在该处见到麻醉师。本手术在全身麻醉下进行。有时会追加区域神经阻滞以缓解术后疼痛;麻醉师将在手术当日就此与您沟通。随后,您将被带入手术室进行手术。术后,您将在复苏区苏醒,护士会监测您的状况直至麻醉消退。待您的生命体征平稳后,根据手术类型及您的恢复情况,您将被转入病房或直接回家。
手术内容
具体步骤取决于肌腱撕裂的位置和严重程度。伸肌腱位于手背和手指背侧皮肤下方,因此外科医生通常可以通过在受影响手指或手背的切口到达损伤部位。如果皮肤本身也受损,会先清除受损组织,并可能将健康的皮肤覆盖物转移到该区域。
找到肌腱断端后,外科医生会将它们缝合在一起。修复的强度足以应对术后手部早期的活动。如果一段肌腱缺失或损伤过重无法缝合,则可以通过桥接来填补间隙。这可以通过使用无法保留的手指上的肌腱片段、移植物,或将邻近的肌腱转移过来承担撕裂肌腱的功能来实现。外科医生旨在恢复肌腱的自然长度,因为如果肌腱过松或过紧,手指将无法正确伸直。
切口用缝线关闭并覆盖敷料。您将收到关于手部护理的书面说明。
后续处理与修复本身同样重要。有些修复需要夹板固定手指,而另一些则在最初几周内开始早期、受保护的活动。一种方法允许在前两周进行30度的主动活动,第三周增加到40度,第四周增加到50度。您的外科医生将根据您的损伤情况制定计划,并确切告知您可以和不可以做什么。
术后
您将在复苏区苏醒,期间护士会密切观察您,直至麻醉作用消退。根据您的伤情,您的手部将被包扎,并可能置于夹板中固定。在离开手术室前,我们会为您安排镇痛措施;若您在任何时刻感到疼痛,请随时告知护士。术后最初24小时内,应有人陪同您。大多数人苏醒后即可正常活动;手术部位在您的手部,而非腿部。您的医疗团队会告知您是当天出院,还是在医院留观一晚。我们通常会保留敷料约10天;除非我们另有指示,否则请勿在此之前拆除敷料。我们将在复诊时为您更换或拆除敷料。
恢复
您的手部在最初几天和几周内会出现疼痛和肿胀。这是正常现象。将手部垫高在枕头上,即使在睡眠时也是如此,有助于减轻肿胀。按照医疗团队的指导使用简单的止痛药通常可以缓解不适。
您的敷料将保留约 10 天。根据您的伤情,您可能需要佩戴固定手指的夹板,或者开始早期保护性活动。如果早期活动是您康复计划的一部分,我们将向您展示手指弯曲和伸直的确切幅度以及频率。起初动作幅度较小,随着修复强度的增加而逐渐增大。康复训练由 Extend Rehabilitation 的手部治疗师 Ruby Doolan 负责。她将指导您的锻炼并制作您所需的任何夹板。
在家中,您可以进行大多数不会给手部带来压力的日常活动。在治疗师允许之前,您需要避免提重物、抓握以及任何可能撞击修复部位的动作。在复查伤口之前,请保持手部清洁干燥。随着肿胀消退和活动恢复,锻炼会变得更容易,手指也会开始更顺畅地伸直。
每个人的恢复情况各不相同。您的时间表可能有所不同,您的外科医生和手部治疗师将在每次复查时为您提供指导。
可能出现的并发症
大多数患者恢复良好,但偶尔可能出现一些问题。您的外科医生和医疗团队会密切监测您的状况,以便尽早发现任何问题。
此次手术后最常见的问题是僵硬。手指可能无法完全伸直或完全握拳,抓握力量可能持续弱于术前。这种情况发生在手部保持静止时,肌腱与周围组织发生瘢痕粘连。您的治疗师将在每次就诊时观察此情况并调整您的锻炼方案。如果活动度停滞或手指感觉越来越紧,请在下次复诊时提出,不要等待。
即使其他方面恢复良好,有时伸直力量也会略有损失。您可能会注意到,当您尝试伸直手指时,该手指的位置略低于相邻手指,或者手指无法完全弯曲至掌心。这被称为伸肌滞后。了解这种情况可能发生是值得的,尤其是如果损伤在治疗前已经存在较长时间。请在复诊时提及此事,以便您的治疗师进行针对性训练。
修复本身可能会失败。如果您感觉到突然的“啪”的一声,或者原本伸直良好的手指突然再次下垂,请立即联系诊所。不要等到下次预约。
感染并不常见,但需要迅速处理。请注意观察疼痛是否持续加重而非缓解,伤口周围红斑是否扩散,肿胀是否持续增加而非消退,或缝合处是否有液体渗出。伴有手部疼痛的发热也是警示信号。如果您发现上述任何症状,请在当天致电诊所,或在非工作时间前往急诊科。
如果后续需要手术以松解瘢痕化的肌腱,这被称为肌腱松解术。它不属于初始计划的一部分,但如果僵硬对治疗无反应,则是一个可选方案。只有当您的活动度达到平台期时,您的外科医生才会与您讨论此选项。
如果您想了解具体细节,本页的并发症表格列出了典型的发病率。
何时联系我们
问题在早期发现时更容易解决。如果您的疼痛持续加重而非缓解,或伤口周围皮肤变得更红、更热或开始渗出液体,请致电我们。如果您感到发烧、手指或手部麻木,或完全无法活动手指,请致电我们。如果您发现小腿突然肿胀和疼痛,或出现呼吸急促,请立即前往急诊。如果原本伸直良好的手指突然下垂,或您感到有“啪”的一声,请立即联系我们。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
General Hand Architecture
- The hand is composed of 19 bones, 17 articulations, and 19 muscles situated entirely within the hand [2].
- Approximately the same number of tendons activated by forearm muscles are present in the hand [2].
- The hand functions efficiently only if the proximal joints of the limb are stable and yet mobile [2].
- The dorsal aspect of the hand is convex, while the anterior, palmar, or volar aspect is concave [2].
- The palmar surface is the functional surface of the hand, while the dorsal surface is usually visible and aesthetically important [2].
- The thumb has a more proximal and lateral position than the four fingers, allowing movement inward and outward from the palm [2].
- When fingers are extended and separated, their tips lie on the circumference of a circle whose center is the head of the third metacarpal [2].
Metacarpal and Longitudinal Arch Anatomy
- The metacarpal arch possesses adaptability due to the mobility of the peripheral metacarpals [7].
- The index metacarpal is the most firmly fixed of the metacarpals [7].
- The ring metacarpal has approximately 10 degrees of mobility in flexion and extension [7].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [7].
- The second to fifth metacarpals are bound together by the deep transverse intermetacarpal ligament, also known as the interglenoid ligament [7].
- The interglenoid ligament ties together the anterior glenoid ligaments of the metacarpophalangeal articulations, known as volar plates [7].
- The metacarpophalangeal joints serve as the keystones of the longitudinal arches of the hand [7].
- The volar plates prevent hyperextension at the metacarpophalangeal joints [7].
- The sagittal bands of the extensor apparatus insert onto the volar plate [7].
- The first annular segment of the pulley of the flexor tendons inserts onto the volar plate [7].
Extensor Tendon and Intrinsic Muscle Anatomy
- There are seven interosseous muscles in the hand, consisting of four dorsal and three volar muscles [4].
- The dorsal interossei are abductors, while the volar interossei are adductors [4].
- The middle finger has two dorsal interossei and no volar interossei because the central axis of the hand lies within it [4].
- Each dorsal interosseous muscle, with the exception of the third, has two muscle heads: a superficial head and a deep head [4].
- The superficial head of the dorsal interosseous muscles abducts and weakly flexes the proximal phalanx [4].
- The deep head of the dorsal interosseous muscles forms the lateral band at the level of the metacarpophalangeal joint [4].
- The deep head of the dorsal interosseous muscles flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [4].
- Transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [4].
- Oblique or spiral fibers from the lateral bands insert onto the lateral tubercles at the base of the middle phalanx to extend the middle phalanx [4].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [4].
- The two conjoined lateral bands unite at the distal third of the middle phalanx to form the terminal tendon [4].
- The terminal tendon inserts at the base of the distal phalanx to extend it [4].
- The volar interossei have only one muscle head and do not insert onto the proximal phalanx [4].
- The flexor digiti quinti brevis forms the ulnar lateral band of the little finger [4].
Cutaneous and Vascular Anatomy
- The dorsal cutaneous unit extends from the wrist to the proximal interphalangeal joints of the fingers and the interphalangeal joint of the thumb [3].
- The dorsal covering of the interphalangeal articulations forms a unique cutaneous unit characterized by considerable excess of skin when digits are in extension [3].
- The palmar integument is subdivided into two zones by the oppositional crease of the thumb [3].
- The skin of the radial portion of the palm covers the thenar eminence and is relatively well vascularized and mobile [3].
- The skin of the ulnar and distal portion of the palm covers the hypothenar eminence and has poor mobility [3].
- The central triangular part of the palm has fixed, poorly vascularized skin that covers the superficial palmar aponeurosis [3].
- Incisions made along the sides of the diamond-shaped cutaneous contact zones in flexed digits present a minimal chance of retraction [3].
- The princeps pollicis artery is the terminal branch of the radial artery that crosses the first intermetacarpal space [8].
- The princeps pollicis artery runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [8].
- The princeps pollicis artery divides into two terminal rami, the collateral palmar arteries of the thumb, at the level of the metacarpophalangeal joint flexion crease [8].
- Only 15% of anatomical dissections of the palmar arteries of the thumb fall into the classical "typical" category [8].
- In the second segment of the thumb, the ulnar collateral artery is often easier to dissect than the radial collateral artery [8].
- A subtendinous anastomosis at the level of the neck of the first phalanx acts as a moderator between the two collateral arteries [8].
- The dorsal arteries of the thumb originate from palmar arteries at the level of the first metacarpal and head distally on the side of the two distal phalanges [8].
Investigations
- Clinical evaluation of the injured or dysfunctional hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [1].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining pathology but can be expensive, time consuming, and often nonspecific [1].
- A careful physical examination is essential to direct care and future testing if indicated [1].
- A systematic method to approaching the physical examination of the hand and wrist is essential due to the number of structures in a small space [1].
- An 8-MHz Doppler tone assessment may be used to identify superficially displaced neurovascular bundles when Dupuytren cords lie beneath soft fleshy prominences [11].
- False-negatives are possible with 8-MHz Doppler tone assessment for identifying neurovascular bundles [11].
- Doppler imaging is a promising improvement for identifying structures, but higher resolution imaging technology is needed [11].
- MR assessment of Dupuytren’s disease is hindered by the resolution of current equipment, orientation issues due to multiplanar deformities of the fingers, and lack of intraoperative availability [11].
- MRI is probably most useful in identifying additional pathology such as flexor tendon bowstringing [11].
- MRI may be helpful in providing a quantitative noninvasive measure of cellularity of affected areas, which is an index of biologic activity [11].
- The potential staging tool of MRI for measuring cellularity has not been investigated yet on a large scale [11].
References
[1] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[2] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[3] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[4] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[7] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[8] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[11] Dupuytren S Disease And Related Hyperproliferative Disorders. 54. The Future of Dupuytren’s Research and Treatment > 54.4 Mechanical Measurements and Procedures > 54.4.4 Imaging.