Patients › Shoulder
Revision Shoulder Replacement
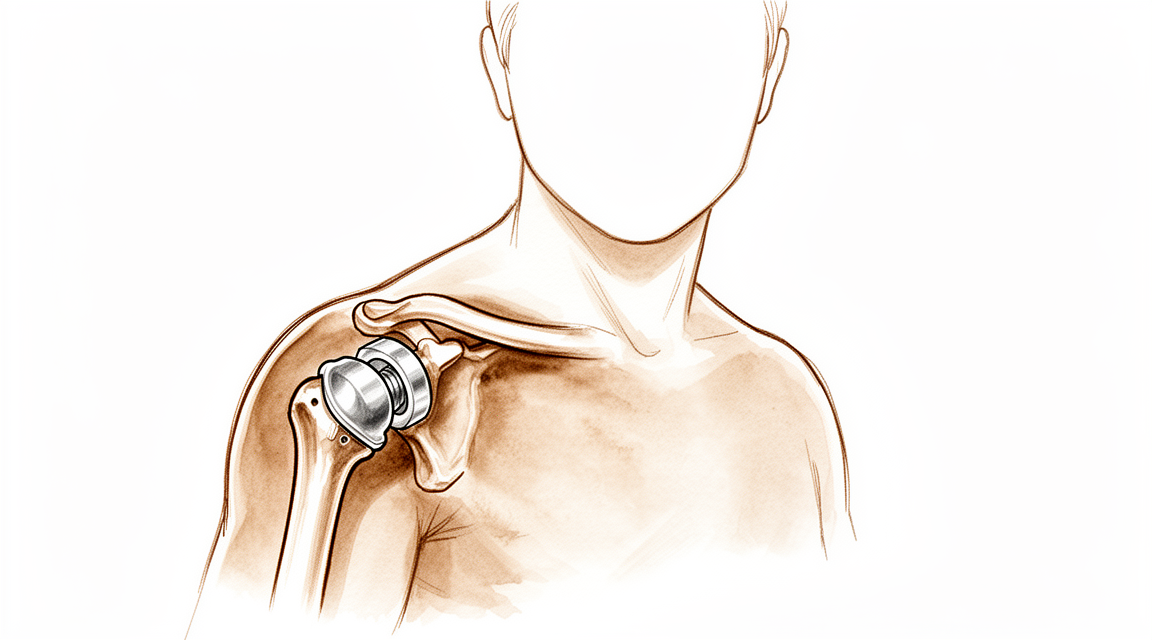
Revision shoulder replacement — addressing failure of prior shoulder replacements with a reverse design.
Why this operation has been suggested
Dr Kieran Hirpara, an upper-limb surgeon at Mater Private Hospital Rockhampton, starts with the least invasive options that suit your condition. Patients are generally referred to our clinic by their GP; if a physiotherapist has suggested you see us, you will still need a referral from your GP in order to be eligible for the Medicare rebate. At your first visit we take a history, examine your shoulder, and arrange imaging where it is needed. For long-standing problems we usually try non-operative care first, such as activity change, physiotherapy, or splinting, and we consider surgery when that has not given enough improvement.
A revision shoulder replacement is a second operation that replaces some or all of the parts of an earlier shoulder replacement. We suggest it when the first replacement is no longer working well, most often because the parts have worked loose, the joint has become unstable, or the socket has worn. Severe pain and stiffness are the main reasons people come to us for this operation. The aim is less pain, better movement, and a steadier shoulder. Revision reverse shoulder replacement has an implant survival rate of 85% at ten years. We will talk through what this operation can and cannot do for you, and decide together whether it is right for you.
Before the operation
Your shoulder will need imaging so we can plan the operation. Plain X-rays from a few angles are usually enough. Sometimes an MRI (a scan that shows soft tissues) or an ultrasound is added. Before the day of surgery, you will get clear instructions from our team. You will need to stop eating and drinking for seven hours beforehand. We ask for seven hours rather than the usual six so you can be brought forward if the theatre list runs early. Bring a written list of all your current medicines, as some may need to be paused. Arrange for someone to drive you home. Wear loose, comfortable clothing. If you have other medical conditions, you may need blood tests or a review with the anaesthetist (the specialist who gives the anaesthetic).
On the day
You will arrive at the hospital's surgical admissions unit, where you are checked in and prepared for theatre. You will then meet the anaesthetist. This operation is done under general anaesthetic combined with a regional nerve block. The anaesthetist will meet you before the operation and talk you through both parts.
You are then taken into the operating theatre, where the operation is performed. When it is finished, you will wake up in the recovery area. Nurses will monitor you there while the anaesthetic wears off. Once you are stable, you will move to the ward.
What the operation involves
A revision shoulder replacement is an open operation done through a single cut over the area being operated on. Your surgeon works through this one incision to reach the joint.
The exact steps depend on why the first replacement failed. Your surgeon may remove some or all of the worn or loose parts and replace them with new metal and plastic surfaces. If the socket bone has worn away, a small bone graft (a piece of bone used to rebuild a missing area) can be packed in so a new socket part can be fitted. Whenever possible, your surgeon will try to fit a new socket component rather than leave it out. If the joint has been unstable, your surgeon may change the design of the replacement to a reverse one, where the ball and socket positions are swapped to make the joint steadier. Sometimes the old cement around the arm-side part is kept and new cement is placed inside it, rather than removing every trace.
Once the new parts are in place and checked, the wound is closed. A fine self-adhesive mesh is laid over the closed wound first, holding the skin edges together. A liquid skin adhesive is then painted over the mesh, where it sets to seal the whole thing. This stays on for roughly one to two weeks and then lifts and peels away by itself, so there is nothing to be taken out.
After the operation
You will wake up in the recovery area with nurses watching over you. Once you are steady, you will move to the ward. Most patients stay one or two nights in hospital after this operation. Pain relief is tailored to you, and the nerve block from theatre often keeps the shoulder comfortable at first. Your arm will rest in a simple sling for comfort; it comes off for exercises and washing. We leave the dressing on for about 10 days; please do not take it off before then unless we tell you to. We change or remove it when we see you. A physiotherapist may visit to start gentle movements. Please arrange for someone to stay with you for the first 24 hours after you go home.
Recovery
The first days are about rest and comfort. Your shoulder will be sore and swollen, and the nerve block from theatre often keeps it quiet at first. As that wears off, you will feel more of the ache. Pain relief tailored to you, rest, and gentle movement all help. The swelling settles gradually over the early weeks.
Your arm rests in a simple sling for comfort. It comes off for exercises and washing. A physiotherapist will guide you through gentle movements early on, then build up your strength and range of motion as your shoulder allows. Around the house, you will need help with heavier tasks at first, but light use of your arm returns steadily. Sleeping upright or propped on pillows is often more comfortable in the early days.
Recovery happens in stages rather than all at once. Once your surgeon clears you to drive, typically at the six-week review, you can get back on the road; see our guide on driving after upper-limb surgery. As movement returns, everyday tasks like dressing and cooking become easier. When your shoulder is strong enough, most people get back to work and many return to a sport or activity they enjoy. Many people notice their shoulder keeps improving over the first year.
Your timeline may differ from someone else's. Your surgeon and physiotherapist will guide you at each review and adjust the plan to suit how your shoulder is healing.
What can go wrong
Most patients do well, but problems can occasionally happen. Your surgeon and the team monitor you closely to spot any issue early.
Sometimes the new parts work loose or the joint becomes unstable. You might feel a return of the pain you had before, or a new ache that was not there after the operation. Some people notice a clicking, grinding, or clunking feeling, or a sense that the shoulder is shifting out of place. If this happens, bring it up at your next review, or call the clinic sooner if the pain is getting worse.
Infection is a risk with any replacement surgery. Watch for a deep, throbbing pain that does not ease with simple painkillers, redness that spreads out from the wound, warmth over the shoulder, or a fever. If you notice any of these, call the clinic straight away. If you feel unwell with a fever or the redness is spreading quickly, go to the emergency department.
Sometimes a break can happen in the bone around the new parts, most often picked up on early X-rays after the operation. You would feel sudden sharp pain, worse than the usual postoperative ache, sometimes with a crack or give. Tell your surgeon or the clinic if this happens.
Some health conditions and circumstances raise the chance of problems. These include Parkinson disease, poor nutrition before surgery, a fragility fracture (a break from a minor fall) before the operation, previous shoulder surgery, inflammatory arthritis (arthritis caused by an overactive immune system), needing blood-thinning medicine after surgery, and having both shoulders operated on close together. If any of these apply to you, we will factor them into the plan and watch you more closely.
The complications table on this page lists typical rates if you want the specifics.
When to call us
Call the clinic if you have a fever, increasing redness or discharge from the wound, or pain that keeps getting worse. Go to the emergency department if you feel suddenly short of breath, have swelling or pain in your calf, or your shoulder pain becomes sudden and severe. Call us straight away if you lose feeling in your arm or hand, or you cannot move it. If in doubt, call us. We would rather hear from you early.
Where to read more about the condition
This page is about the operation itself. The condition it treats, including what the evidence shows about when surgery helps and when it does not, is covered in more detail on the Shoulder Arthritis page.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humerus comprises four main parts: the humeral head, greater tuberosity, lesser tuberosity, and humeral shaft [3].
- The articular head of the proximal humerus is spherical with a diameter of 37 to 57 mm [3].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [3].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [3].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [3].
- The anatomic neck of the proximal humerus is located at the junction of the articular surface and the tuberosities [3].
- The surgical neck represents an indistinct region below the tuberosities but above the humeral shaft [3].
- The greater tuberosity serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [3].
- The lesser tuberosity serves as the attachment site for the subscapularis tendon [3].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [3].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [4].
- The neck-shaft angle measures an average of 135 degrees [4].
- The humeral head is retroverted an average of 30 degrees [4].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [5].
- The glenoid is connected with the flat body of the scapula by the scapular neck [5].
- The coracoid process curves forwards from the superior surface of the scapular neck [5].
- The scapular spine ends in a flattened bony process, the acromion, which curves forwards [5].
- The highest concentration of bony mass in the scapula is located in the glenoid, the scapular neck, and the lateral border of the scapular body [5].
- Two bony pillars transmit compressive forces from the glenoid fossa: the lateral pillar and the spinal pillar [5].
- The lateral pillar connects the inferior border of the glenoid with the inferior angle [5].
- The spinal pillar arises from the central part of the glenoid and continues medially to become part of the base of the scapular spine [5].
- The weakest bone in the scapula is located primarily in the central part of the infraspinous fossa [5].
- The weakest area of the circumference of the biomechanical body of the scapula is the spinomedial angle [5].
- The subchondral bone of the glenoid is relatively flat, with articular concavity augmented by cartilage and a circumferential labrum [6].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [6].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [6].
- The acromion has three ossification centers: the metacromion, mesoacromion, and preacromion [6].
- Failure of fusion of the acromial ossification centers results in os acromiale [6].
Vascular Anatomy
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [3].
- The posterior humeral circumflex artery travels with the axillary nerve and enters the quadrilateral space posteriorly [3].
- The anterior humeral circumflex artery arises from the axillary artery at the inferior border of the subscapularis [3].
- The anterior humeral circumflex artery provides vascular inflow to the humeral head via its terminal anterolateral branch, known as the artery of Laing or arcuate artery [3].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon [3].
- The ascending branch of the anterior humeral circumflex artery enters the humeral head at the interface of the bicipital groove and greater tuberosity [3].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [3].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [3].
- The major blood supply to the humeral head is through the ascending branch of the anterior humeral circumflex artery, which penetrates the head at the bicipital groove and becomes the arcuate artery [4].
- Fractures of the anatomic neck have a poor prognosis because of complete disruption of the blood supply to the head [4].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [6].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [6].
Soft Tissue & Ligamentous Anatomy
- The rotator cuff consists of four muscles: the subscapularis, supraspinatus, infraspinatus, and teres minor [4].
- The teres major is not a rotator cuff muscle [4].
- The rotator cuff muscles serve as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [4].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [4].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch [3].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [3].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula [7].
- The subscapular bursa communicates with the joint cavity between the superior and middle glenohumeral ligaments [7].
- The subscapular bursa protects the tendon of the subscapularis at the point where it passes under the base of the coracoid process and over the neck of the scapula [7].
- The subscapular bursa often houses loose bodies in the shoulder [7].
- The subscapular bursa is a region in which synovitis of the shoulder may be most intense [7].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [6].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [6].
- Laxity of the rotator interval results in inferior laxity (the sulcus sign) [6].
- Contracture of the rotator interval is seen with adhesive capsulitis [6].
- The coracohumeral ligament restricts external rotation in adduction [6].
- The coracohumeral ligament is a static restraint to inferior and posterior translation in adduction and external rotation [6].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [6].
- With the coracohumeral ligament, the superior glenohumeral ligament forms a pulley that provides restraint against medial subluxation of the long head of the biceps tendon [6].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [6].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation of the glenohumeral joint in 90° of abduction and external rotation [6].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [6].
- The glenoid labrum provides concavity and up to 50% of marginal glenoid socket depth [6].
- The superior transverse scapular ligament arises from the medial base of the coracoid overlying the suprascapular notch [6].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the nerve runs deep to it [6].
- Entrapment of the suprascapular nerve at the superior transverse scapular ligament causes denervation of both the supraspinatus and the infraspinatus [6].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [6].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [6].
Pathophysiology & Biomechanics
- Stability and function of the glenohumeral joint are provided by the interaction of structures that promote a near global range of motion and purposeful function [3].
- External loads transferred to the shoulder girdle are initially offset by joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion [3].
- Moderate and large loads are counterbalanced by the deltoid and rotator cuff and by the capsulolabral and bone structures, respectively [3].
- Proximal humeral fractures alter complex interactions, resulting in pain, decreased range of motion and stiffness, and disability [3].
- Displacement of proximal humeral fracture fragments is based on the deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [3].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement [3].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement [3].
- The pectoralis major inserts on the humeral shaft and displaces it medially [3].
- A fracture involving the anatomic neck is prognostically worse than fractures involving other regions of the proximal humerus with respect to the potential disruption of the vascular supply to the humeral head and subsequent development of avascular necrosis [3].
- Displaced proximal humeral fractures can impede normal movement of structures passing under the coracoacromial arch, causing impingement and disruption of normal glenohumeral motion [3].
- In proximal humeral fractures, the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that limit normal glenohumeral motion [3].
- The malcentering of the joint reaction force on the glenoid leads to posterior instability, posterior glenoid wear, and "rocking horse" loosening of prosthetic glenoid components [2].
- The point of contact of the humeral articular surface on the glenoid articular surface reflects the degree of centering of the net humeral joint reaction force on the glenoid [2].
- Arthritis usually involves the central aspect of the humeral head [2].
- Joint space narrowing is most evident on the axillary view taken with the arm in elevation compared to images made with the arm at the side [2].
- The axillary view taken with the arm in elevation demonstrates posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [2].
- Dense scarring from previous operations commonly complicates the surgical approach in revision shoulder arthroplasty [15].
- Exposure in revision shoulder arthroplasty is typically quite difficult, making component implantation less predictable [15].
- Preexisting instability or subscapularis deficiency often is not correctable with an anatomic revision arthroplasty [15].
- The rotator cuff is often deficient in patients with massive (>4 cm) proximal humeral bone loss [15].
Investigations
Plain Radiography
- The purpose of shoulder imaging is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [2].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder care [2].
- The first key radiographic view is the anteroposterior (AP) view taken in the plane of the scapula such that the x-ray beam passes through the glenohumeral joint [2].
- The AP view in the plane of the scapula shows the superoinferior position of the humeral head relative to the glenoid, the presence of osteophytes on the humeral head and glenoid, narrowing of the joint space, and the degree of medial displacement of the humerus in relation to the lateral acromial line [2].
- The AP view in the plane of the scapula also shows the quality of the humeral and glenoid bone, the presence of loose bodies, and whether there is humeral head collapse or deformity [2].
- The second key radiographic view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [2].
- The axillary view is oriented so that both the spinoglenoid notch and the scapular neck are visible [2].
- The axillary view demonstrates a different perspective of humeral anatomy, the amount of glenoid bone, the shape of the glenoid, its version in relation to the plane of the scapula, and the relationship of the humeral head to the glenoid fossa [2].
- The axillary view is referred to as the “truth view” because it demonstrates glenohumeral relationships in the functional position of elevation [2].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view which is taken in elevation [2].
- Many axillary views sent for consultation are taken without standardization, making it impossible to determine important features of the glenohumeral joint [2].
- When taken properly, standardized anteroposterior and axillary views indicate the thickness of the cartilage space between the humerus and the glenoid, relative positions of the humeral head and glenoid, presence of osteophytes, degree of osteopenia, and extent of bony deformity and erosion [2].
- Joint space narrowing is most evident on the axillary truth view as opposed to images made with the arm at the side [2].
- The axillary truth view can show posterior subluxation or “functional decentering” that is not evident in images taken with the arm at the side [2].
- The degree of posterior subluxation can be measured as the position of the center of the humeral head in relation to the plane of the scapula [2].
- The degree of posterior subluxation can be measured as the position of the center of the humeral head in relation to the glenoid face [2].
- The degree of posterior subluxation can be measured as the point of contact of the humeral articular surface on the glenoid articular surface [2].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and “rocking horse” loosening of prosthetic glenoid components [2].
- At least two X-ray views should be obtained: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [11].
Computed Tomography
- CT scans may offer a few degrees of increased precision in the measurement of glenoid version [2].
- The authors are not convinced that the increased precision of CT scans in measuring glenoid version improves the quality of the surgery or the clinical outcome [2].
- There is information that can be gathered from properly taken plain films that cannot be obtained from CT scans [2].
- Three-dimensional reconstructions can reveal fine details of the shoulder anatomy, but this additional information rarely changes the planning or conduct of the arthroplasty [2].
- Computed tomography (CT) is helpful for planning fracture surgery and shoulder joint replacement [11].
Magnetic Resonance Imaging
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head, or a bone tumour [11].
- MRI can identify labral tears and rotator cuff tears [11].
- The accuracy of MRI for identifying labral tears and rotator cuff tears is enhanced by combining the scan with arthrography [11].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [11].
- Ultrasonography can be useful in guiding injections or barbotage (aspirating calcific deposits in the rotator cuff) [11].
- The most commonly performed joint examination using ultrasonography is the shoulder examination [9].
- The accuracy of rotator cuff ultrasonography depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [9].
General Imaging Principles
- The diagnosis of a stiff shoulder depends on awareness of the problem, with history and physical examination being paramount and ancillary studies helpful in certain circumstances [1].
- Unless a specific research protocol is in place, the temptation to “overimage” should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [2].
- Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [2].
- The shoulder is a three-dimensional structure that cannot be represented by a single planar view [13].
- Critical relationships, such as the degree of centering of the humeral head, change with the position of the arm [13].
- Shoulder pathology may be found in a large number of different bones and soft tissues [13].
- Overlying and superimposed structures as well as metallic implants may complicate imaging the structures of interest [13].
- Surgeons need to develop a judicious approach to imaging that yields the information necessary to treat the patient while avoiding the tendency to "over-image" [13].
References
[1] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > SUMMARY.
[2] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[3] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[4] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[5] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[6] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[7] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[9] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[11] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[13] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.
[15] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > REVISION SHOULDER ARTHROPLASTY > INDICATIONS.