Patients › General-Health
Platelet-Rich Plasma (PRP) at mga Injection Therapy
What the evidence shows for platelet-rich plasma and related injection therapies in tendinopathy, osteoarthritis and rotator cuff disease — where they help and where the data is weak.
Ano ito
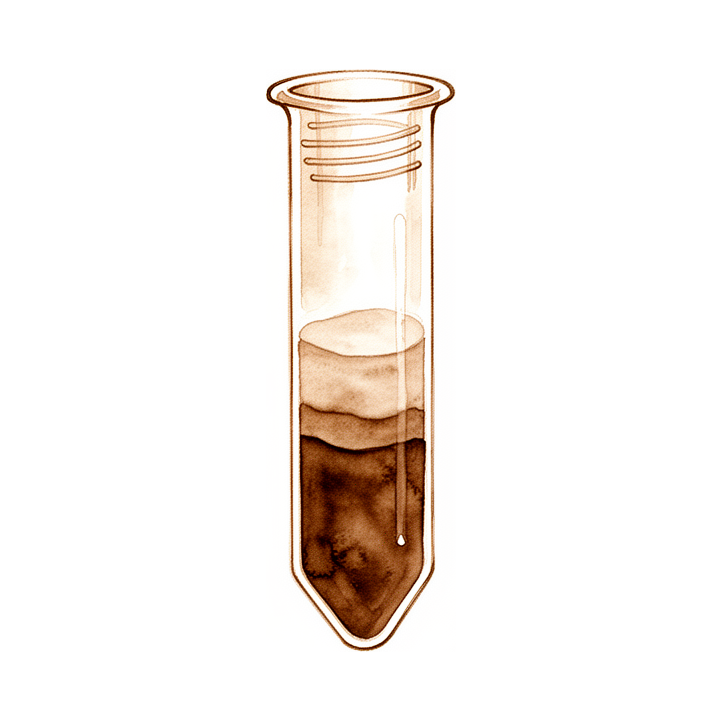
Ang platelet-rich plasma, na madalas pinaiikli bilang PRP, ay isang paggamot na ginagawa mula sa sarili mong dugo. Pinapaikot ang isang maliit na sample ng iyong dugo sa isang makina upang mahiwalay at mapakonsentra ang mga platelet. Ang mga platelet ay ang napakaliliit na bahagi ng dugo na tumutulong sa pamumuo nito, at nagdadala rin ang mga ito ng mga growth factor, na mga natural na sangkap na maaaring sumuporta sa paggaling. Pagkatapos, ini-inject ang mga nakonsentrang platelet sa masakit na bahagi.
Maaaring isaalang-alang ng iyong doktor ang PRP para sa mga problema gaya ng wear-and-tear arthritis sa tuhod, mga problema sa tendon sa siko, balikat o pulso, at ilang pinsala sa kalamnan sa sports. Hindi ito ginagamit para sa bawat kondisyon. Para sa tennis elbow, halo-halo ang ebidensya: natuklasan ng ilang pag-aaral na mas gumana ang PRP kaysa sa mga steroid injection sa mas mahabang panahon [1], habang hindi ito sinuportahan ng isang review ng mga trial kumpara sa placebo [2]. Para sa arthritis ng tuhod, madalas na inirerekomenda ang dalawang injection, na may epektong tumatagal nang hindi bababa sa 24 na linggo [3]. Para sa carpal tunnel syndrome, nagpakita ang PRP ng mga benepisyong mas tumatagal kaysa sa isang steroid injection sa follow-up sa ika-6 na buwan [4].
Ang ideya sa likod ng PRP ay maaaring bawasan ng mga growth factor sa mga platelet ang pamamaga at hikayatin ang pag-aayos ng tissue. Inaalam pa ng pananaliksik ang mga detalye. Ipinapakita ng mga pag-aaral na magkakaiba ang kilos ng iba't ibang paghahanda: ang isang uri na mayaman sa white blood cell ay tila angkop sa maagang arthritis, habang ang isa pang may mas maraming platelet at mas kaunting white blood cell ay maaaring angkop sa mas huling yugto [5]. Natuklasan ng ilang trial na mas gumana ang PRP kaysa sa mga anaesthetic injection para sa mga problema sa tendon ng balikat at siko, ngunit hindi ito mas mahusay kaysa sa dry needling o sa mga injection ng tubig na may asin [6]. Sa kabuuan, nag-iiba-iba ang ebidensya sa bawat kondisyon, at pag-uusapan ng iyong doktor kung makatwiran ang PRP para sa iyong partikular na problema.
Gumagana ba ito?
Ang tapat na sagot ay nakadepende ito sa kondisyon, at sa ilang kaso ay humahabol pa ang pananaliksik. Natuklasan ng isang review ng ebidensya na ang PRP ay isang paggamot na posibleng kawili-wili, ngunit wala pang sapat na de-kalidad na pananaliksik upang suportahan ang malawak na paggamit nito [7]. Napansin din ng mga mananaliksik na ang ilang buod ng mga trial ng PRP para sa arthritis ng tuhod ay pinalabas na mas positibo ang kanilang mga resulta, na maaaring magpamukhang mas mahusay ang paggamot kaysa sa talagang ipinapakita ng ebidensya [8].
Para sa ilang kondisyon, mas nakapagpapalakas ng loob ang mga resulta. Para sa mga problema sa tendon, natuklasan ng mga trial na pinabuti ng PRP ang sakit at kung gaano kahusay gumagana ang apektadong bahagi, at mas gumana ito kaysa sa mga steroid injection sa katamtamang tagal ng panahon [9]. Para sa arthritis ng tuhod, pinabuti ng PRP ang pangkalahatang paggana, lalo na sa mga mas batang tao [10]. Ang pagsasama ng PRP at hyaluronic acid, isang pampadulas na sangkap na natural na matatagpuan sa mga joint, ay nagbigay ng mas mahusay na ginhawa sa sakit at paggana kaysa sa PRP lamang [11].
Para sa ibang mga kondisyon, halo-halo o hindi malinaw ang larawan. Para sa tennis elbow, natuklasan ng ilang trial na binawasan ng PRP ang sakit at pinabuti ang paggana sa mga unang buwan [12], habang hindi ito sinuportahan bilang paggamot ng ibang pananaliksik [2]. Para sa mga punit sa rotator cuff, walang sapat na mahusay na ebidensya upang masabi kung nakakatulong ito o hindi [13]. Para sa napinsalang cartilage ng tuhod, hindi pa sinusuportahan ng ebidensya ang mga PRP injection nang mag-isa [14].
Ano ang ibig sabihin nito para sa iyo? Maaaring makatulong ang PRP sa ilang problema, ngunit hindi ito napatunayang lunas para sa lahat. Ipapaliwanag sa iyo ng iyong doktor kung ano ang ipinapakita ng ebidensya para sa iyong partikular na kondisyon, upang makapagpasya kayo nang magkasama kung sulit itong subukan.
Ano ang mga panganib?
Ang PRP ay ginagawa mula sa sarili mong dugo, kaya hindi malamang na magkaroon ng masamang reaksyon ang iyong katawan sa materyal mismo. Hindi ibig sabihin nito na walang panganib ang paggamot. Ang injection mismo ay maaaring magdulot ng sakit, pamamaga at paninigas sa mga araw pagkatapos nito, at maaaring sumakit muna ang ginamot na bahagi bago ito bumuti. Ipapaliwanag sa iyo ng iyong doktor kung paano ito pamahalaan.
Hindi pa nasasagot ng pananaliksik sa PRP para sa arthritis ng tuhod ang tanong kung gaano ito kahusay gumagana, at ang ilang nailathalang buod ay pinalabas na mas positibo ang kanilang mga resulta [8]. Mahalaga iyon kapag tinitimbang mo kung itutuloy ito, dahil ang isang paggamot na mukhang promising ay maaaring hindi magbigay ng ginhawang inaasahan mo. Para sa rotator cuff repair, pinataas ng pagdaragdag ng PRP ang antas ng paggaling ngunit hindi nito binago kung gaano kahusay magamit ng mga pasyente ang kanilang balikat sa pang-araw-araw na buhay [15]. Para sa mga problema sa Achilles tendon, natuklasan ng mga trial na hindi mas mahusay ang PRP kaysa sa placebo [16].
Ang tugon ng iyong katawan ay maaari ring nakadepende sa iyong sitwasyon. Ang mga naunang corticosteroid injection at ang paggamit ng tabako ay tila nagpapababa sa bisa ng PRP para sa chronic medial epicondylitis, isang problema sa tendon sa loob na bahagi ng siko [17]. Kung naninigarilyo ka o nagkaroon ka na ng steroid injection sa parehong bahagi, banggitin ito bago magpasya sa paggamot.
May ilang tanong na hindi pa nasasagot. Napansin ng mga mananaliksik na kailangan pa ng mas maraming pag-aaral upang makumpirma ang pangmatagalang epekto ng PRP [18]. Halo-halo ang mga resulta ng mga pag-aaral ng PRP para sa tennis elbow: ang ilang trial ay nag-ulat ng maagang ginhawa sa sakit at mas mahusay na paggana [12], at ang iba ay walang natuklasang malinaw na benepisyo kumpara sa placebo [2]. Wala pa ring sapat na mahusay na ebidensya upang suportahan ang mga PRP injection nang mag-isa para sa napinsalang cartilage ng tuhod [14].
Kung mapansin mo ang lumalalang sakit, pamumula o pag-init sa paligid ng lugar ng injection sa mga araw pagkatapos ng paggamot, makipag-ugnayan sa aming klinika upang masuri namin ito. Pag-uusapan ng iyong doktor ang mga partikular na panganib para sa iyong kondisyon bago ka magpasya kung itutuloy ito.
Tama ba ito para sa iyo?
Mas angkop ang PRP sa ilang tao kaysa sa iba. Kung mayroon kang wear-and-tear arthritis sa iyong tuhod, inirerekomenda ang hindi bababa sa dalawang injection, na may epektong tumatagal nang hindi bababa sa 24 na linggo [3]. Kung naglalaro ka ng competitive na sports, inirekomenda ng mga mananaliksik na ialok ang PRP therapy sa mga naglalaro ng competitive na sports [19]. Kung mayroon kang carpal tunnel syndrome sa parehong pulso, nagpakita ang PRP ng mga benepisyong mas tumatagal kaysa sa isang steroid injection sa follow-up sa ika-6 na buwan [4].
May mga sitwasyon kung saan mas maliit ang posibilidad na ang PRP ang tamang pagpili. Kung may napinsalang cartilage ka sa iyong tuhod, hindi pa sinusuportahan ng ebidensya ang mga PRP injection nang mag-isa [14]. Para sa tennis elbow, halo-halo ang ebidensya, kaya maaari itong makatulong sa iyo o hindi. Kung naninigarilyo ka o nagkaroon ka na dati ng steroid injection sa parehong bahagi, maaaring hindi gaanong gumana ang PRP para sa iyo.
Ang PRP ay isa sa ilang opsyon. Ang mga steroid injection ang pangunahing alternatibo para sa ilang kondisyon, at sa ilang kaso ay nagpakita ang PRP ng mga benepisyong mas tumatagal kaysa sa steroid [4]. Ang isa pang opsyon ay ang hyaluronic acid, isang pampadulas na sangkap na natural na matatagpuan sa mga joint. Nasa maagang yugto pa ang pananaliksik na naghahambing sa dalawa, kaya ipapaliwanag ng iyong doktor kung ano ang alam na sa ngayon.
Dapat itong maging magkasamang desisyon ninyo ng iyong doktor. Pag-isipan ang iyong mga layunin, ang iyong kondisyon at kung ano ang ipinapakita ng ebidensya para dito. Ipapaliwanag sa iyo ng iyong doktor ang mga opsyon, kasama ang mga panganib na tinalakay sa seksyon sa itaas, upang makapagpasya kayo nang magkasama kung makatwiran ang PRP para sa iyo.
Ang pinaka-importanteng punto
Sulit isaalang-alang ang PRP para sa ilang problema, ngunit magsimula nang may makatotohanang inaasahan. Maaari nitong pagaanin ang sakit at pabutihin ang paggana para sa arthritis ng tuhod at ilang kondisyon sa tendon, bagaman nag-iiba-iba ang mga resulta sa bawat tao. Ang pinakamahalagang paalala ay humahabol pa ang pananaliksik, at para sa ilang kondisyon ay wala pang sapat na de-kalidad na ebidensya upang suportahan ang malawak na paggamit nito [7]. Tutulungan ka ng iyong doktor na timbangin kung makatwiran ito para sa iyong partikular na problema.
Mga Sanggunian
[1] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[2] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[3] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[4] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[5] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[6] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[7] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[8] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[9] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[10] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[11] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[12] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[13] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[14] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[15] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[16] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[17] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[18] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[19] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- PRP remains a potentially interesting intervention for chronic tennis elbow but currently lacks sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- PRP therapies for shoulder and elbow tendinopathy have only partially fulfilled therapeutic expectations, necessitating new approaches [2].
- For knee osteoarthritis, at least two PRP injections are recommended, with effects lasting for at least 24 weeks [3].
- The conclusions of recent studies on intra-articular PRP for knee osteoarthritis are intended to stimulate further research rather than provide a conclusive statement on efficacy [4].
- There is no definitive evidence regarding the effectiveness of PRP treatment when the literature is evaluated [5].
- Further studies are needed to evaluate the long-term efficacy and cost-effectiveness of PRP for practical patient use in hypertrophic facet joints [6].
- Conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [7].
- Leukocyte-rich (L-PRP) and leukocyte-poor (LP-PRP) are effective treatment options for knee osteoarthritis with comparable efficacy based on current evidence [8].
- PRP may have a potential role as a biological adjunct in fracture nonunion management, but further well-designed randomized controlled trials are required before definitive clinical recommendations can be made [9].
- PRP injections must be integrated into a comprehensive treatment plan with non-pharmacological measures and post-procedural care that needs to be better defined [10].
- Interventions employing PRP, MSCs, and exosomes are considered in the context of degenerative osteoarthritis as a reversible chronic disease [11].
- PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection for gluteal tendinopathy [12].
- PRP demonstrated indications of more sustained benefits, particularly at the 6-month follow-up, in patients with bilateral moderate carpal tunnel syndrome [13].
- There is insufficient evidence to recommend for or against the use of PRP for rotator cuff tears due to literature heterogeneity and effect sizes failing to reach MCID values even when significant [14].
- The authors recommend systematically offering PRP therapy for competition sports practitioners with large joint osteoarthritis [16].
- The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO [18].
- The statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
- It is recommended to wait for at least one month before considering another injection or alternative treatments for first presentation trigger digits [27].
- Findings from a meta-analysis of randomized clinical trials do not support PRP as a recommended treatment for lateral epicondylitis [28].
- The efficacy of autologous platelets is well established, and the study reinforced the previously published report by the author regarding diabetic tibial non-union [51].
How It Works
Mechanisms and Biological Effects
- PRP enhances anabolic gene expression patterns in flexor digitorum superficialis tendons [34].
- The effect of PRP on chondrocytes and macrophages is mainly influenced by the age and disease status of the PRP donor rather than inflammatory mediator or growth factor groupings [33].
- PRP from older males with knee osteoarthritis depresses chondrocyte metabolism and upregulates inflammation [33].
- Leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations have discernible key molecular mediators [32].
- Low platelet, high leukocyte PRP is recommended for early osteoarthritis due to its anti-inflammatory effects [36].
- High platelet, low leukocyte PRP is preferred for advanced osteoarthritis to promote tissue repair and regeneration [36].
- The application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations is an innovative biological approach to the treatment of muscle injuries [31].
Efficacy and Clinical Outcomes
- PRP demonstrated indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in bilateral moderate carpal tunnel syndrome [13].
- Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months for lateral elbow tendinopathy [20].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [15].
- Both leukocyte-rich PRP (L-PRP) and leukocyte-poor PRP (LP-PRP) are effective treatment options with comparable efficacy for knee osteoarthritis based on current evidence [8].
- LP-PRP augmentation during rotator cuff repair increases healing rates but does not affect clinically meaningful functional outcomes [39].
- PRP may serve as an adjunct to structured rehabilitation rather than a determinant of long-term strength recovery for lateral epicondylitis [40].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis [22].
- High-dose PRP showed significant efficacy over alternative treatment strategies for lateral epicondylitis [22].
- Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of a study on delayed union or non-union [30].
- PRP remains a potentially interesting intervention for chronic tennis elbow but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- PRP therapies have only partially fulfilled therapeutic expectations for shoulder and elbow tendinopathy, and new approaches are necessary [2].
- The conclusions of a study on intra-articular PRP injections for knee osteoarthritis do not intend to provide a conclusive statement but rather to stimulate further research [4].
- A prospective, multicenter, double-blind randomized controlled trial for Kellgren-Lawrence Grade I and II knee osteoarthritis does not establish PRP efficacy or component-specific effects because components were bundled and no placebo group was included [19].
- The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [7].
Protocols and Influencing Factors
- At least two PRP injections are recommended for treating knee osteoarthritis, with effects lasting for at least 24 weeks [3].
- Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP for chronic medial epicondylitis [35].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future for hypertrophic facet joints [6].
- Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease [21].
- The PRP used in a study on anti-inflammatory and matrix restorative mechanisms came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP [37].
- A study compared the efficacy of intra-articular injections of platelet-rich plasma (PRP) and viscosupplementation (hyaluronic acid [HA]) for the treatment of knee degenerative cartilage lesions and osteoarthritis [17].
What the Evidence Shows
General Applicability and Methodology
- PRP remains a potentially interesting intervention but currently lacks sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- PRP therapies have only partially fulfilled therapeutic expectations, necessitating new approaches [2].
- Studies evaluating the outcomes and procedures of PRP use in lateral epicondylitis demonstrate poor adherence to MIBO guidelines [26].
- Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP for knee osteoarthritis, with identified spin tending to favor the use of PRP [52].
Knee Osteoarthritis
- At least two PRP injections are recommended for knee osteoarthritis, with effects lasting for at least 24 weeks [3].
- The conclusions of studies on intra-articular PRP for knee osteoarthritis intend to stimulate further research rather than provide a conclusive statement [4].
- Both leukocyte-rich (L-PRP) and leukocyte-poor (LP-PRP) are effective treatment options with comparable efficacy based on current evidence [8].
- Leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee osteoarthritis [43].
- PRP + HA therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy for patients with knee osteoarthritis [47].
- Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary osteoarthritis, particularly in younger individuals [49].
- PRP demonstrated limited and inconsistent effects on imaging-based structural outcomes in knee osteoarthritis, and did not confer significant and consistent benefits in medial tibial cartilage measurements, cartilage defect progression, synovitis, or most WORMS domains [53].
- A prospective, multicenter, double-blind randomized controlled trial for Kellgren-Lawrence Grade I and II knee osteoarthritis did not establish PRP efficacy or component-specific effects because components were bundled and no placebo group was included [19].
- The authors recommend systematically offering PRP therapy for competition sports practitioners in the context of large joint osteoarthritis treatment protocols [16].
Lateral Epicondylitis (Tennis Elbow)
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection, with high-dose PRP showing significant efficacy over alternative treatment strategies [22].
- PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis in the early follow-up period [48].
- After autologous blood injection therapy, 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity [50].
Rotator Cuff and Shoulder
- There is insufficient evidence to recommend for or against the use of PRP for rotator cuff tears given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant [14].
- A significant difference in the retear rate, even in an underpowered study, has further confirmed the positive effect of platelet-rich plasma for arthroscopic repair of medium to large rotator cuff tears [42].
- Substantial heterogeneity and inconsistent reporting of PRP composition limit the certainty of findings regarding platelet concentration and improved pain for partial-thickness rotator cuff tears treated with PRP [55].
Other Tendinopathies and Musculoskeletal Conditions
- PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [41].
- PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids [46].
- A randomized trial found no significant difference in outcomes between LR-PRP and placebo for the treatment of greater trochanteric pain up to 6 months following the intervention [44].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo for chronic tenosynovitis [15].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in patients with bilateral moderate carpal tunnel syndrome [13].
Fractures, Nonunion, and Bone Pathology
- The application of PRP following core decompression results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to core decompression alone for early osteonecrosis of the femoral head [45].
Sports Injuries and Adjunctive Procedures
- Current evidence supports the selective use of PRP in sports settings for acute muscle injuries, though standardization in protocols and outcomes is needed [25].
- PRP, used as an adjuvant in meniscal repair, may be associated with improved clinical and radiographic outcomes, particularly by reducing failure rates and enhancing PROs [54].
- Current evidence is insufficient to support orthobiologic injections adjunctive to cartilage-preserving surgery as standalone procedures for focal knee chondral defects [29].
Spine and Facet Joints
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the treatment of hypertrophic facet joints [6].
Practical Considerations
- Further studies are needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in hypertrophic facet joints [6].
- Both leukocyte-rich (L-PRP) and leukocyte-poor (LP-PRP) are effective treatment options with comparable efficacy for knee osteoarthritis based on current evidence [8].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in bilateral moderate carpal tunnel syndrome [13].
- The authors recommend systematically offering PRP therapy for competition sports practitioners for large joint osteoarthritis [16].
- A trial evaluating PRP therapy in Kellgren-Lawrence Grade I and II knee osteoarthritis does not establish PRP efficacy or component-specific effects because components were bundled and no placebo group was included [19].
- Results from an in vitro study regarding the anti-inflammatory and matrix restorative mechanisms of PRP in osteoarthritis should be interpreted with caution [23].
- Studies evaluating the outcomes and procedures of the use of PRP in the setting of lateral epicondylitis have poor adherence to MIBO guidelines [26].
- Current evidence is insufficient to support orthobiologic injections as standalone procedures for focal knee chondral defects [29].
- The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost [38].
Key Evidence
- [L5] The authors conclude that PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use. [1] (10.1177/0363546513512784)
- [L1] PRP therapies have only partially fulfilled therapeutic expectative, and new approaches are necessary. [2] (10.1097/bte.0000000000000118)
- [L3] At least two PRP injections are recommended, with effects lasting for at least 24 weeks. [3] (10.1186/s13018-025-05756-6)
- [Paper] The conclusions of this study do not intend to provide a conclusive statement but rather to stimulate further research in this complex field and contribute to shedding light on the several aspects influencing the efficacy of intra-articular platelet-rich plasma (PRP) injections for knee osteoarthritis (OA) in clinical practice. [4] (10.1177/03635465251387701)
- [L5] When the literature is evaluated, it is understood that there is no definitive evidence regarding the effectiveness of PRP treatment. [5] (10.1177/23259671241255700)
- [L4] Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future. [6] (10.5435/jaaosglobal-d-24-00140)
- [L5] The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up; future studies should prioritize long-term outcomes to guide clinical decision-making more effectively. [7] (10.1016/j.arth.2025.05.007)
- [L1] Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence. [8] (10.1186/s13018-026-06689-4)
- [Paper] PRP may have a potential role as a biological adjunct in a fracture nonunion management, but further well-designed randomized controlled trials are required before definitive clinical recommendations can be made. [9] (10.1016/j.injury.2026.113826)
- [Paper] PRP injections must be integrated into a comprehensive treatment plan with non-pharmacological measures and post-procedural care that needs to be better defined. [10] (10.1016/j.otsr.2026.104972)
- [L5] Interventions employing PRP, MSCs and exosomes are considered in this article. [11] (10.1016/j.reth.2020.07.007)
- [L5] The authors state that the conclusion of the referenced randomized controlled trial is that PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection. [12] (10.1177/0363546518773719)
- [L1] PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up. [13] (10.1016/j.injury.2026.113018)
- [L5] There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant. [14] (10.1177/0363546520918190)
- [L1] These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo. [15] (10.1186/s12891-025-09339-8)
- [L4] The authors recommend systematically offering PRP therapy for competition sports practitioners. [16] (10.1186/s12891-025-08663-3)
- [Paper] The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO. [18] (10.1177/03635465231203202)
- [L1] Because components were bundled and no placebo group was included, the trial does not establish PRP efficacy or component-specific effects. [19] (10.1177/03635465261486945)
- [L1] Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months. [20] (10.1177/23259671251386862)
- [Paper] Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease. [21] (10.1177/03635465251395284)
- [L1] A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection, with high-dose PRP showing significant efficacy over alternative treatment strategies. [22] (10.1016/j.jisako.2025.100442)
- [L5] The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA. [23] (10.1177/0363546514537991)
- [L5] The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations. [24] (10.1177/0363546517703364)
- [L2] Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed. [25] (10.1177/23259671251399907)
- [L2] This review demonstrated that studies evaluating the outcomes and procedures of the use of PRP in the setting of LE have poor adherence to MIBO guidelines. [26] (10.5397/cise.2024.01060)
- [L3] It is recommended to wait for at least one month before considering another injection or alternative treatments. [27] (10.1142/s2424835520500253)
- [L1] These findings do not support PRP as a recommended treatment for this condition. [28] (10.1177/03635465251383039)
- [L2] Current evidence is insufficient to support such injections as standalone procedures. [29] (10.1002/arj.70548)
- [L4] Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of the current study. [30] (10.1016/s0020-1383(13)70158-x)
- [L5] An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations. [31] (10.1016/s0020-1383(14)70004-x)
- [L5] The goal of the study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations. [32] (10.1177/03635465231206930)
- [Paper] The effect of PRP on chondrocytes and macrophages was mainly influenced by the age and disease status of the PRP donor as opposed to the inflammatory mediator or growth factor groupings. [33] (10.1002/jor.24322)
- [Paper] These findings support in vivo investigation of PRP as an autogenous, patient-side treatment for tendonitis. [34] (10.1002/jor.20278)
- [L4] Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP. [35] (10.1177/1753193414567012)
- [L1] Optimizing OA treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects and high platelet, low leukocyte PRP preferred for advanced OA to promote tissue repair and regeneration. [36] (10.1186/s13018-025-06026-1)
- [L5] The authors also highlight that the PRP used in the study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP. [37] (10.1177/0363546514537996)
- [L1] The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost. [38] (10.1016/j.jse.2026.02.018)
- [L1] Consequently, LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes. [39] (10.1002/arj.70537)
- [L1] PRP may serve as an adjunct to structured rehabilitation rather than a determinant of long-term strength recovery. [40] (10.1016/j.jse.2026.09.009)
- [L1] PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge. [41] (10.1097/corr.0000000000003478)
- [L5] The authors state that the significant difference in the retear rate, even in this underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP). [42] (10.1177/0363546515625958)
- [L1] This double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee OA. [43] (10.1177/03635465241283500)
- [L1] This randomized trial found no significant difference in outcomes between LR-PRP and placebo for the treatment of greater trochanteric pain up to 6 months following the intervention. [44] (10.2106/jbjs.24.00763)
- [L3] The application of PRP following CD results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to CD alone. [45] (10.1186/s12891-024-08243-x)
- [L1] PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids. [46] (10.1186/s12891-025-08566-3)
- [L1] This meta-analysis reveals that, for patients with KOA, PRP + HA therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy. [47] (10.1186/s13018-024-05429-w)
- [L4] PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis. [48] (10.1177/2325967125s00169)
- [L1] Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary OA, particularly in younger individuals. [49] (10.1186/s12891-026-09486-6)
- [L4] After autologous blood injection therapy 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity. [50] (10.1053/jhsu.2003.50041)
- [L3] The efficacy of this autologous platelets is once again well established and this study reinforced categorically the previously published report by the author. [51] (10.1016/j.injury.2024.111469)
- [L1] Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP. [52] (10.1002/arj.70027)
- [Paper] In this systematic review and meta-analysis, PRP demonstrated limited and inconsistent effects on imaging-based structural outcomes in knee OA, and did not confer significant and consistent benefits in medial tibial cartilage measurements, cartilage defect progression, synovitis, or most WORMS domains. [53] (10.1007/s00402-026-06543-6)
- [L3] This systematic review indicates that PRP, used as an adjuvant in meniscal repair, may be associated with improved clinical and radiographic outcomes, particularly by reducing failure rates and enhancing PROs. [54] (10.1177/23259671261467213)
- [L1] However, substantial heterogeneity and inconsistent reporting of PRP composition limit the certainty of this finding. [55] (10.1177/23259671261480483)
References
[1] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[2] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[3] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[4] PRP Injections for the Treatment of Knee Osteoarthritis: The Improvement Is Clinically Significant and Influenced by Platelet Concentration: Response. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251387701
[5] Comparison of Conventional Dose Versus Superdose Platelet-Rich Plasma for Knee Osteoarthritis: Letter to the Editor. Orthopaedic Journal of Sports Medicine. 2024. DOI: 10.1177/23259671241255700
[6] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[7] Letter Regarding “Platelet-Rich Plasma Injections are Inferior to Corticosteroid Injections for Short-Term Pain Relief: A Prospective, Double-Blinded, Randomized Controlled Trial”. The Journal of Arthroplasty. 2025. DOI: 10.1016/j.arth.2025.05.007
[8] Leukocyte-rich versus leukocyte-poor platelet-rich plasma and hyaluronic acid for knee osteoarthritis: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06689-4
[9] Union Rate and Time to Union Following Platelet-Rich Plasma Therapy in Fracture Nonunion: A Systematic Review and Meta-Analysis. Injury. 2026. DOI: 10.1016/j.injury.2026.113826
[10] PRP injection in musculoskeletal pathology: what level of evidence, and what recommendations?. Orthopaedics & Traumatology: Surgery & Research. 2026. DOI: 10.1016/j.otsr.2026.104972
[11] Degenerative osteoarthritis a reversible chronic disease. Regenerative Therapy. 2020. DOI: 10.1016/j.reth.2020.07.007
[12] The Effectiveness of Platelet-Rich Plasma Injections in Gluteal Tendinopathy: Response. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518773719
[13] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[14] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[15] Time-dependent growth factor kinetics, platelet concentration, and clinical response following platelet-rich plasma versus saline in chronic tenosynovitis: a randomized controlled trial. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09339-8
[16] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
[17] Platelet-Rich_Plasma_Versus_Hyaluronic_Acid_S0749806312015812. 2015.
[18] Improving Injectable Orthobiologics Reporting Guidelines Adherence: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231203202
[19] Clinical Pathway Management for Platelet-Rich Plasma Therapy in Kellgren-Lawrence Grade I and II Knee Osteoarthritis: A Prospective, Multicenter, Double-Blind Randomized Controlled Trial. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465261486945
[20] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[21] Platelet-Rich Plasma in the Treatment of Musculoskeletal Disease in 2025 and Beyond. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251395284
[22] Platelet Concentration Factor Explains Variability in Outcomes of Platelet-rich Plasma for Lateral Epicondylitis: High Dose Critical for Positive Response. Journal of ISAKOS. 2025. DOI: 10.1016/j.jisako.2025.100442
[23] The Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Patel and Dhillon. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537991
[24] Hyaluronic Acid Versus Platelet-rich Plasma: Response. The American Journal of Sports Medicine. 2017. DOI: 10.1177/0363546517703364
[25] Platelet-Rich Plasma in Acute Muscle Injuries: An Umbrella Review and Meta-analysis of Return to Sport and Reinjury Outcomes. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251399907
[26] Adherence rates to the Minimum Information for Studies Evaluating Biologics in Orthopedics guidelines for clinical studies on platelet-rich plasma for the treatment of lateral epicondylitis: a systematic review. Clinics in Shoulder and Elbow. 2026. DOI: 10.5397/cise.2024.01060
[27] Time to Resolution of Triggering after Steroid Injection for First Presentation Trigger Digits. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520500253
[28] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[29] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[30] PS9 Is platelet-rich plasma injection an effective choice in cases of delayed union or non-union?. Injury. 2013. DOI: 10.1016/s0020-1383(13)70158-x
[31] Muscle repair: platelet-rich plasma derivates as a bridge from spontaneity to intervention. Injury. 2014. DOI: 10.1016/s0020-1383(14)70004-x
[32] The Accurate Characterization of Platelet-Rich Plasma Enables Its Classification and Comparison: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231206930
[33] Platelet‐Rich Plasma (PRP) From Older Males With Knee Osteoarthritis Depresses Chondrocyte Metabolism and Upregulates Inflammation. Journal of Orthopaedic Research. 2019. DOI: 10.1002/jor.24322
[34] Platelet rich plasma (PRP) enhances anabolic gene expression patterns in flexor digitorum superficialis tendons. Journal of Orthopaedic Research. 2006. DOI: 10.1002/jor.20278
[35] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[36] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[37] Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Andia and Maffulli. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537996
[38] Leukocyte-poor platelet-rich plasma reduces retear risk after arthroscopic rotator cuff repair: a meta-analysis with mechanistic and economic evaluation. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.018
[39] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[40] Comparative Efficacy of Leukocyte-Rich and Leukocyte-Poor PRP for Lateral Epicondylitis on Isokinetic and Isometric Upper Limb Strength under an Identical Rehabilitation Protocol: A Randomized Controlled Trial. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.09.009
[41] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[42] PRP for Arthroscopic Repair of Medium to Large Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2016. DOI: 10.1177/0363546515625958
[43] Leukocytes Do Not Influence the Safety and Efficacy of Platelet-Rich Plasma Injections for the Treatment of Knee Osteoarthritis: A Double-Blind Randomized Controlled Trial. The American Journal of Sports Medicine. 2024. DOI: 10.1177/03635465241283500
[44] Efficacy of Platelet-Rich Plasma Versus Placebo for the Treatment of Greater Trochanteric Pain Syndrome. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00763
[45] Efficacy of small-diameter core decompression with platelet-rich plasma in early osteonecrosis of the femoral head: a retrospective study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08243-x
[46] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[47] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[48] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[49] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[50] Autologous blood injections for refractory lateral epicondylitis. The Journal of Hand Surgery. 2003. DOI: 10.1053/jhsu.2003.50041
[51] Percutaneous injection of autologous platelet gel accelerate healing in diabetic tibial non union: On going longitudinal study. Injury. 2024. DOI: 10.1016/j.injury.2024.111469
[52] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[53] Platelet-rich plasma for knee osteoarthritis: a systematic review and meta-analysis of structural outcomes. Archives of Orthopaedic and Trauma Surgery. 2026. DOI: 10.1007/s00402-026-06543-6
[54] A Systematic Review of PRP Augmentation for Nondegenerative Meniscal Repair: Is There a Benefit?. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671261467213
[55] Platelet Concentration Is Not Associated With Improved Pain for Partial-Thickness Rotator Cuff Tears Treated With Platelet-Rich Plasma: A Systematic Review and Meta-analysis With Meta-regression of Level 1 Randomized Controlled Trials. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671261480483