Patients › Rehabilitation
Reverse Shoulder Arthroplasty
Phase-by-phase rehabilitation protocol after reverse shoulder replacement, including dislocation precautions and the early exercise program.

Ang protocol na ito ay nagsisilbing gabay sa iyong paggaling pagkatapos ng reverse shoulder arthroplasty (reverse shoulder replacement) kasama si Dr Kieran Hirpara sa Mater Private Hospital Rockhampton. Ang bawat phase sa ibaba ay nagsisimula sa isang paliwanag sa simpleng Ingles tungkol sa kung ano ang nangyayari at kung ano ang pinakamahalaga, na sinusundan ng structured protocol na isinulat para sa iyong physiotherapist: dalhin ang pahinang ito o ang PDF nito sa iyong unang pagbisita sa physiotherapy upang manatiling coordinated ang iyong rehabilitasyon. Maaaring i-adjust ng iyong physiotherapist ang plano depende sa pag-unlad ng iyong paggaling.
Kung mayroon kang anumang alalahanin tungkol sa iyong sugat pagkatapos ng operasyon, makipag-ugnayan sa mga rooms. Madalas na nakatutulong ang pagkuha ng larawan ng sugat at pag-email nito para sa pagsusuri.
Ano ang dapat asahan
Manhid ang iyong braso paggising mo, at karaniwang bumabalik ang pakiramdam sa loob ng 6 hanggang 12 oras. Bihira, ang ilang pamamanhid o panghihina ay maaaring magpatuloy sa loob ng 2 hanggang 3 araw.
Pagkagising mo mula sa iyong operasyon, ikaw ay nasa isang sling, na may malaking pad sa ibabaw ng iyong balikat. Ang pad na ito ay aalisin bago ang discharge. Sa ilalim nito ay may waterproof dressing na tumatakip sa isang surgical glue strip, na maaaring hayaan lamang sa loob ng 2 linggo. Ang iyong mga tahi ay dissolvable at hindi kailangang tanggalin, ngunit maaaring may ilang dulo ng tahi sa bawat dulo ng sugat na maaaring gupitin nang pantay sa balat pagkatapos ng 2 linggo. Ikaw ay itatakda para makita ang aming nurse para sa wound check 1–2 linggo pagkatapos ng iyong operasyon. Kung hindi ka makakadalo sa dressing check, maaari mong tanggalin ang iyong dressing nang mag-isa pagkatapos ng 2 linggo.
Tinatayang timeframe para sa pagbabalik sa mga aktibidad:
- Pagmamaneho: 6 na linggo
- Paglangoy: breaststroke: 8 linggo; freestyle: 12 linggo
- Golf: 4–6 buwan
- Pagbubuhat: ang magaan na pagbubuhat ay maaaring magsimula sa ika-6 na linggo; iwasan ang pagbubuhat ng mabibigat na gamit sa loob ng 6 na buwan
- Trabaho: sedentary job: 6 na linggo; manual job: gabay ng iyong surgeon
Pagsusuot ng iyong sling
Sinuportahan ng iyong sling ang iyong balikat para sa ginhawa habang humuhupa ang unang pananakit. Narito ito upang suportahan ang bigat ng braso. Hindi nito pinapanatili sa pwesto ang isang repair. Simple lang ang mga panuntunan:
- Isuot ito sa loob ng humigit-kumulang 2 linggo para sa ginhawa at suporta, pagkatapos ay simulan ang unti-unting pag-alis nito sa oras ng araw. Ang maikling paggamit ng sling sa gabi ay ayos lang kung nakakatulong ito sa iyong pagpahinga, ngunit ito ay optional.
- Hubarin ito para sa pagligo at para sa iyong mga ehersisyo, kapag naipakita na sa iyo kung paano.
- Habang nagpapahinga sa bahay, maaari itong alisin anumang oras na komportable ka: suportado ang braso sa isang unan habang nakaupo.
- Gumamit ng ice kung ang balikat ay namamagâ o masakit, lalo na pagkatapos ng ehersisyo.
Tutulungan ka ng iyong physiotherapist sa unang pagsusuot ng sling, at tuturuan ka na pamahalaan ito nang mag-isa bago ka umuwi. Mahalaga ang tamang pagkakasuot, dahil ang maluwag na sling ay hindi nagbibigay ng wastong suporta:
- Laging tiyakin na kapag isinusuot ang sling, ang iyong siko ay nakapwesto sa kanto ng sling at suportadong mabuti.
- Ang dulo ng isang tamang sukat na sling ay dapat nakapatong nang komportable sa knuckle ng iyong kalingkingan. Kung ang iyong kamay ay masyadong nakalawit sa labas ng sling, hindi ito magbibigay sa iyo ng sapat na suporta.
- Ang iyong sling ay may dalawang Velcro strap: isa ay ikinakabit sa paligid ng iyong leeg at isa sa paligid ng iyong baywang.
- Kapag nailagay mo na nang tama ang iyong siko at forearm, gamitin ang iyong braso na hindi na-operahan upang iikot ang upper strap sa iyong leeg patungo sa harap at ikabit ito sa upper loop ng sling.
- Gamitin ang parehong pamamaraan upang ikabit ang lower strap sa paligid ng iyong baywang, at i-secure ito sa lower loop ng sling.
Habang gumagamit ng sling, maging malay sa iyong postura sa lahat ng oras at iwasang hayaang ang iyong mga balikat ay mapunta sa isang nakayukod na posisyon. Upang makamit ang isang mabuting postural position, subukang panatilihing magkahanay ang iyong mga tainga, balikat, at balakang; mahalaga ito para sa iyong likod at makakatulong upang maiwasan ang paninigas sa iyong shoulder joint. Ang isang nakarolyong tuwalya na nakalagay sa ibabang bahagi ng iyong likod (small of your back) kapag nakaupo ay maaaring magsilbing paalala.
Ang iyong mga unang araw sa ospital
Bago ka umuwi, sisimulan ka ng mga physiotherapist ng ospital sa isang simpleng set ng mga ehersisyo, na ipinapakita sa ibaba. Makakatulong ang pag-unawa sa tatlong terminong gagamitin nila. Ang Active range of motion ay nangangahulugang paggalaw na ginagawa mo nang mag-isa, nang walang tulong. Ang Active-assisted range of motion ay nangangahulugang paggamit ng iyong kabilang braso (o isang bagay, gaya ng tungkod) upang tulungang igalaw ang braso. Ang Passive range of motion ay nangangahulugang ang braso ay nananatiling lubos na relax habang ang iyong kabilang braso (o ibang tao) ang gumagawa ng paggalaw. Sa simula, maaari mo nang simulan ang paggalaw ng balikat nang may tulong mula sa iyong kabilang braso at, hangga't komportable, dahan-dahang igalaw gamit ang sariling lakas, na kadalasang pinakamadali kung nakahiga nang patihaya upang makatulong ang gravity. Hayaan ang iyong komportable na maging gabay at magpatuloy ayon sa kakayahan.
Ilang praktikal na punto para sa mga unang araw na ito:
- Gamitin ang sling para sa komportable. Ang maikling paggamit nito sa gabi ay ayos lang kung nakakatulong ito sa iyong pagpahinga, ngunit ito ay optional.
- Gumamit ng ice para sa pagbawas ng sakit kung kinakailangan.
- Kapag suot ang iyong sling, i-relax ang iyong balikat at hayaang dalhin ng sling ang bigat ng iyong braso.
- Inumin ang iyong mga painkiller bago gawin ang iyong mga ehersisyo, at bago ang iyong mga appointment sa physiotherapy.
- Pinapayagan kang ilabas ang iyong braso mula sa sling para sa iyong mga ehersisyo at pagliligo.
- Isuot ang sling para sa komportable at suporta sa loob ng mga 2 linggo, pagkatapos ay unti-unting bawasan ang paggamit nito sa oras ng araw.
- Maliban kung pinili mong ayusin ang iyong sariling physiotherapy, may nakatakda nang appointment para sa iyo at nakadetalye ito sa iyong discharge pack.
- Kung mayroon kang anumang problema, makipag-ugnayan sa opisina o ipaalam sa iyong physiotherapist.
Ito ang mga ehersisyo na sisimulan sa iyo ng mga physiotherapist ng ospital, na ipagpapatuloy sa bahay ayon sa gabay ng iyong physiotherapist.
Ang iyong mga ehersisyo sa ospital

Kieran Hirpara 4.0
Buksan at isara ang kamay
Panatilihing gumagalaw ang iyong kamay at mga daliri sa pamamagitan ng pagbubukas at pagsasara ng mga ito, o sa pamamagitan ng pagpisil sa isang malambot na bola.
10 beses, 3 beses bawat araw

Kieran Hirpara 4.0
Paggalaw ng pulso
Panatilihing gumagalaw ang iyong pulso sa pamamagitan ng pagbaluktot nito pasulong, pabalik, at sa magkabilang gilid.
10 beses, 3 beses bawat araw

Kieran Hirpara 4.0
Siko
Ibaluktot at ituwid ang iyong siko.
10 beses, 3 beses bawat araw

Kieran Hirpara 4.0
Mga Pendulum
Ito ay isang passive exercise. Yumuko nang bahagya pasulong at hayaang lumaylay ang iyong braso. Gamitin ang iyong katawan upang dahan-dahang igalaw ang braso pakanan (clockwise) o pakaliwa (anti-clockwise), gayundin pasulong, pabalik, at pagilid-gilid.
Mga 30 segundo bawat direksyon, 3 beses kada araw

Kieran Hirpara 4.0
Forward flexion
Habang nakaupo sa isang upuan at nakayuko pasulong, alalayan ang iyong inoperahang braso gamit ang kabilang braso at dahan-dahang igalaw ang iyong braso pataas sa iyong harapan. Ibaba itong muli sa tulong ng iyong braso na hindi inoperahan. Maaari mo ring subukang humiga nang patihaya sa kama at tulungan ang braso pataas kung mas gusto mo ito.
10 beses, 3 beses bawat araw
Kieran Hirpara 4.0
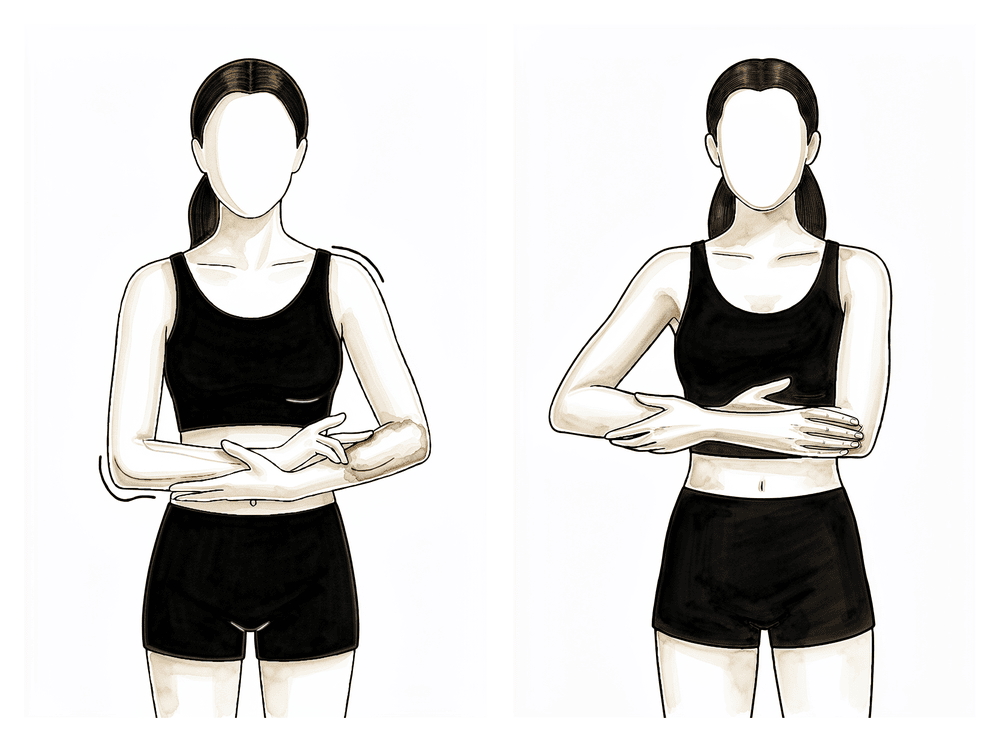
Abduction
Nakaupo sa isang upuan at nakayuko pasulong, alalayan muli ang braso at tulungan itong igalaw palabas sa gilid (hal. gaya ng pagduyan ng isang sanggol).
10 beses, 3 beses bawat araw
Kieran Hirpara 4.0
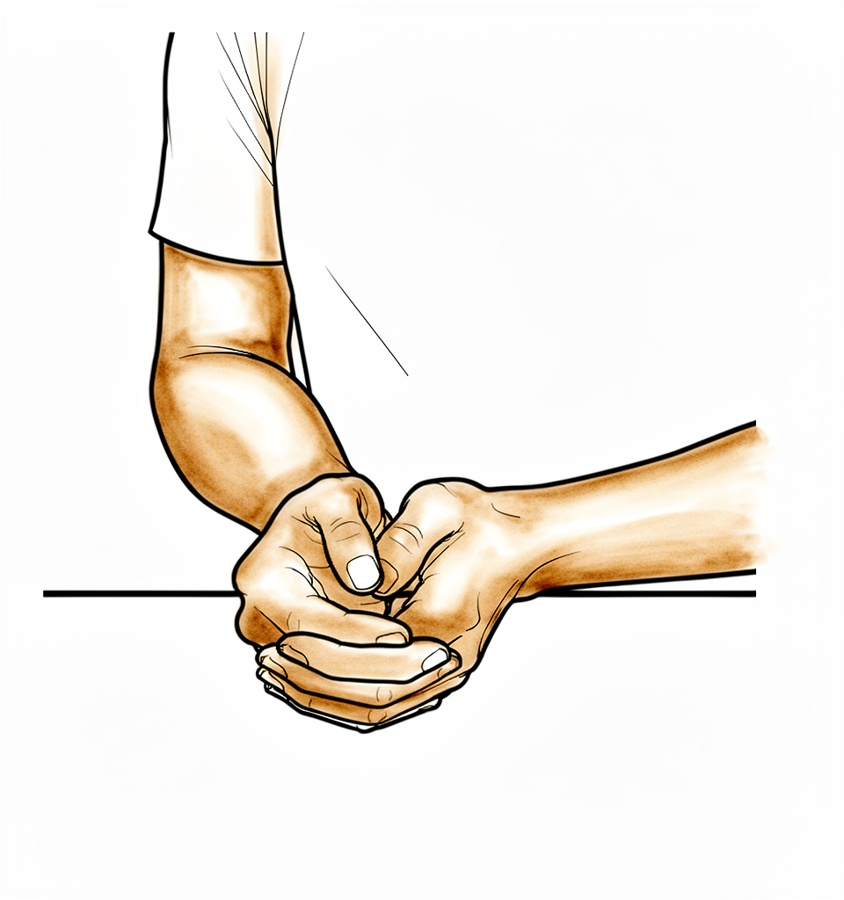
External rotation
Habang nakaupo sa isang upuan, igalaw lamang ang iyong braso mula sa posisyon nito sa sling hanggang sa ituro ito nang diretso sa iyong harapan. Huwag itong igalaw nang mas palabas pa.
Dahan-dahan, 10 beses, 3 beses bawat araw
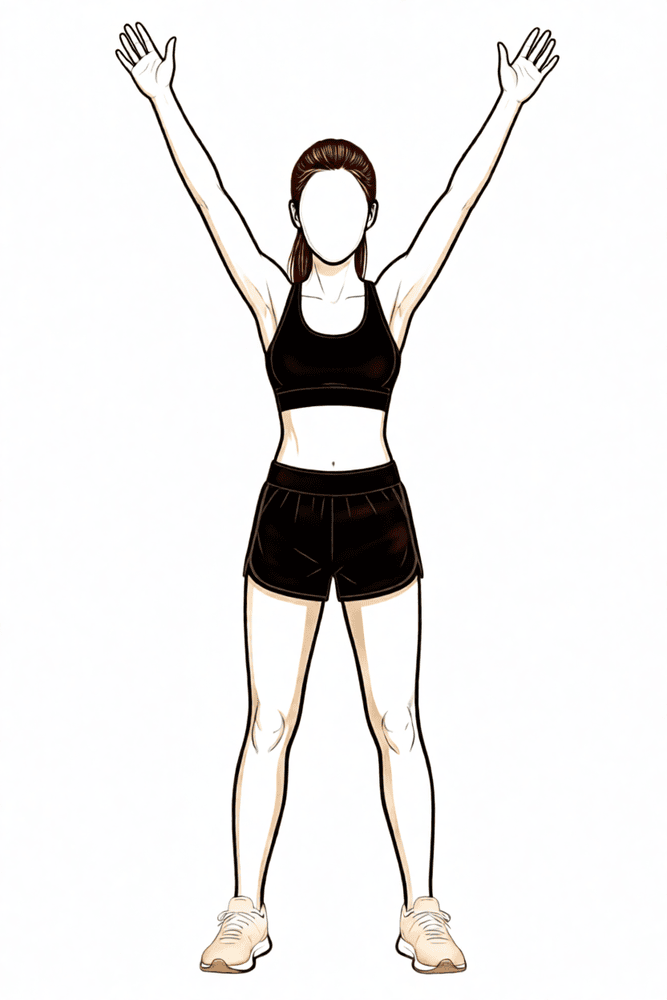
Kieran Hirpara 4.0
Pag-set ng lower trapezius
I-squeeze ang iyong mga shoulder blade pababa at magkasama.
Hawakan nang 5 segundo, 5 beses; ulitin nang 3 beses araw-araw
Kieran Hirpara 4.0
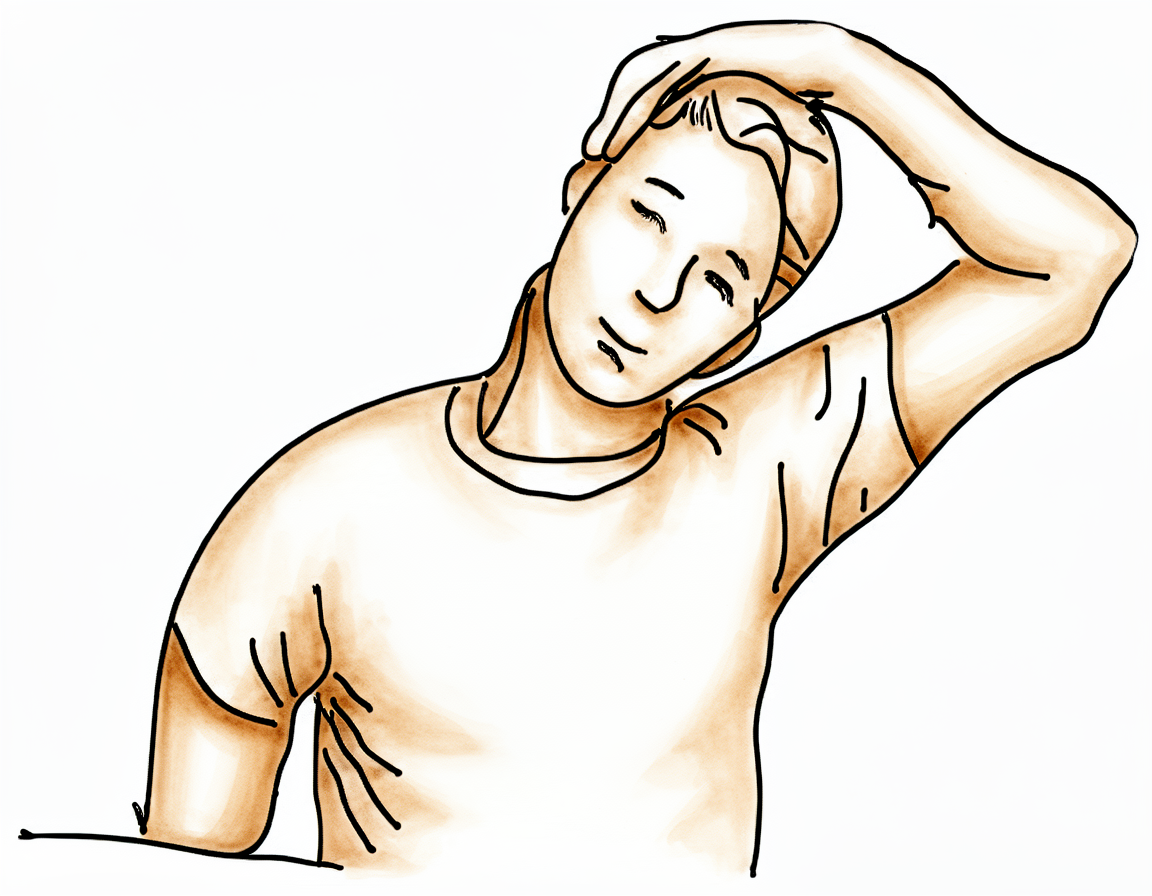
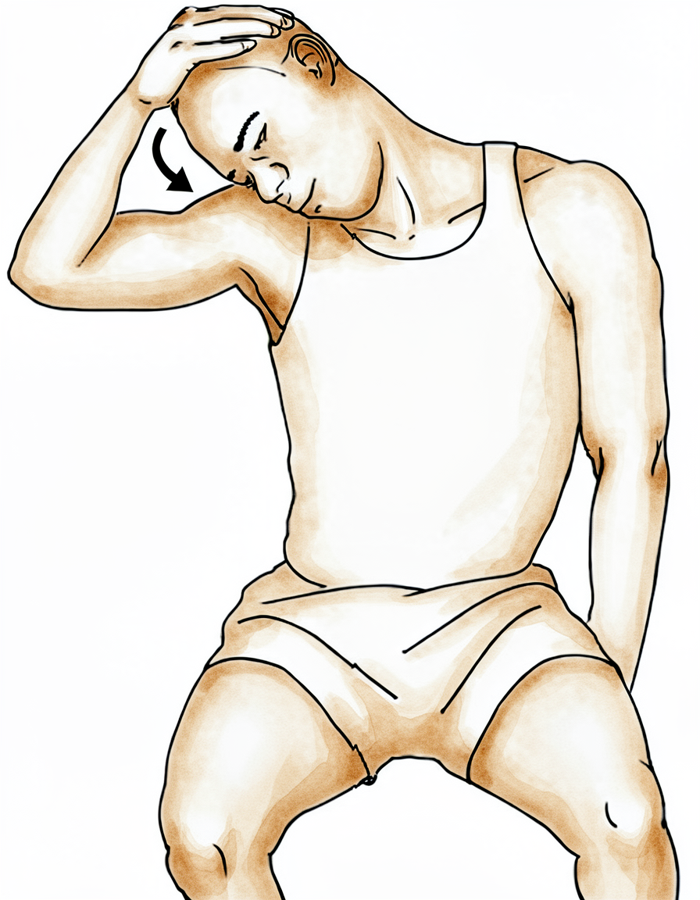
Stretch ng upper trapezius
Gamitin ang iyong braso na hindi naoperahan upang ilapit ang iyong tainga sa iyong balikat, palayo sa panig na naoperahan.
Hawakan nang 10 segundo, 3 beses; ulitin nang 3 beses bawat araw
Kieran Hirpara 4.0
Stretch ng levator scapulae
Gamitin ang iyong braso na hindi naoperahan upang ilapit ang iyong ilong sa iyong utong o sa bahagi ng iyong kili-kili.
Hawakan nang 10 segundo, 3 beses; ulitin nang 3 beses bawat araw
Phase I — Proteksyon (Weeks 0–3)
Kieran Hirpara 4.0
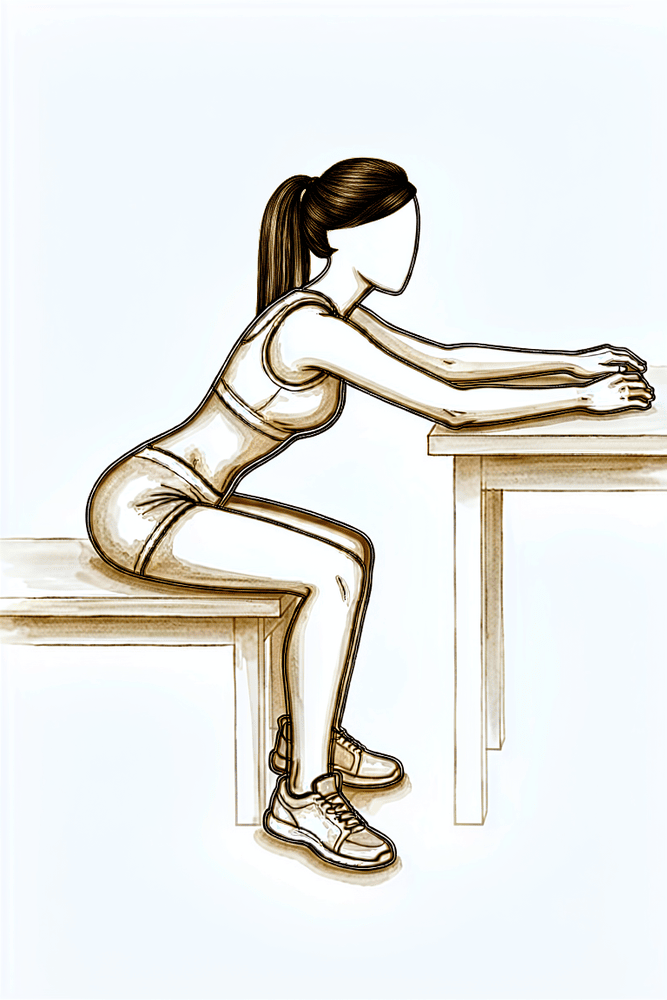
Seated table slide
Umupo sa isang mesa na ang iyong forearm ay nakapatong sa ibabaw nito. Hayaan ang iyong kamay na dumulas pasulong sa mesa habang dahan-dahang yumuyuko, hayaang tumiklop ang balikat pasulong nang hindi gumagamit ng mga kalamnan sa balikat, pagkatapos ay idulas ito pabalik. Panatilihing relaks at komportable ang paggalaw — ang balikat mismo ay nananatiling passive.
Ayon sa gabay ng iyong physiotherapist
Ang unang tatlong linggo ay para sa pagpapatatag ng iyong bagong shoulder joint at dahan-dahang pagbabalik nito sa paggalaw. Gamitin ang sling para sa ginhawa, kontrolin ang pamamaga gamit ang ice at compression, at panatilihing gumagalaw ang iyong siko, pulso, at kamay. Mula sa simula, magsisimula ka rin ng banayad na paggalaw ng balikat, na tinutulungan ng iyong kabilang braso at, hangga't komportable, dahan-dahang gamit ang sariling lakas, na kadalasang pinakamadali kapag nakahiga nang patihaya upang makatulong ang gravity. Hayaan ang iyong ginhawa na maging gabay at huwag pilitin ang anuman. Ang mga panuntunang pinakamahalaga ay tungkol sa pagprotekta sa joint upang hindi ito mawala sa puwesto: huwag abutin ang likod, huwag i-rotate ang braso papasok (inwards), huwag magbuhat ng anuman, at huwag itulak ang sarili pataas gamit ang mga kamay. Kapag nakahiga nang patihaya, maglagay ng maliit na unan o ni-roll na tuwalya sa ilalim ng iyong siko upang hindi mabatak ang balikat pabalik.
Para sa iyong physiotherapist:
Mga Layunin
- Protektahan ang stability ng component (iwasan ang dislocation position)
- Bawasan ang pamamaga, minimisahin ang sakit
- Panatilihin ang upper extremity (UE) range of motion (ROM) sa siko, kamay, at pulso
- Simulan ang maagang shoulder active-assisted at active motion hangga't komportable
- Minimisahin ang muscle inhibition
- Edukasyon ng pasyente
Sling
- Neutral rotation
- Para sa ginhawa at suporta; opsyon ang maikling paggamit sa gabi; unti-unting alisin sa araw mula ~2 weeks
Pamamahala
- Pamamahala sa pamamaga: ice, compression
- Range of motion / mobility:
- PROM: external rotation (ER) sa scapular plane hanggang sa tolerance; flexion/scaption ≤ 120 degrees; abduction (ABD) ≤ 90 degrees; seated glenohumeral (GH) flexion table slide; pendulums; seated horizontal table slides
- Active-assisted range of motion (AAROM): mula sa simula: active-assisted shoulder flexion (magsimula nang supine/gravity-assisted), sa loob ng mga limitasyon ng PROM sa itaas
- Active range of motion (AROM): mula sa simula: banayad na active shoulder motion ayon sa tolerance hangga't komportable; kasama ang siko, kamay, at pulso
Mga Pag-iingat
- Bawal ang shoulder PROM/AROM patungong internal rotation (IR)
- Bawal ang pag-abot sa likod, lalo na patungong internal rotation
- Iwasan ang pinagsamang extension + adduction + internal-rotation (dislocation) position
- Bawal ang pagbuhat ng mga bagay
- Bawal ang pagsuporta ng bigat ng katawan gamit ang mga kamay
- Maglagay ng maliit na unan/towel roll sa ilalim ng siko habang nakahiga nang patihaya upang maiwasan ang shoulder hyperextension
Mga Kraytirya para sa pag-usad
- Unti-unting pagtaas ng shoulder PROM, AAROM, at AROM hangga't komportable
- 0 degrees shoulder PROM patungong IR
- Sakit < 4/10
- Walang mga komplikasyon sa Phase I
Phase II — Intermediate (Weeks 4–6)

Kieran Hirpara 4.0
Stretch ng external rotation gamit ang baston
Humiga nang patihaya na ang iyong siko ay nasa iyong tabi at nakabaluktot nang 90 degrees. Humawak ng baston o tungkod sa magkabilang kamay at gamitin ang braso na hindi naoperahan upang dahan-dahang itulak palabas ang kamay ng braso na naoperahan, hanggang sa kung ano lamang ang komportable. Huwag kailanman pilitin ang paggalaw.
Ayon sa gabay ng iyong physiotherapist
Kieran Hirpara 4.0
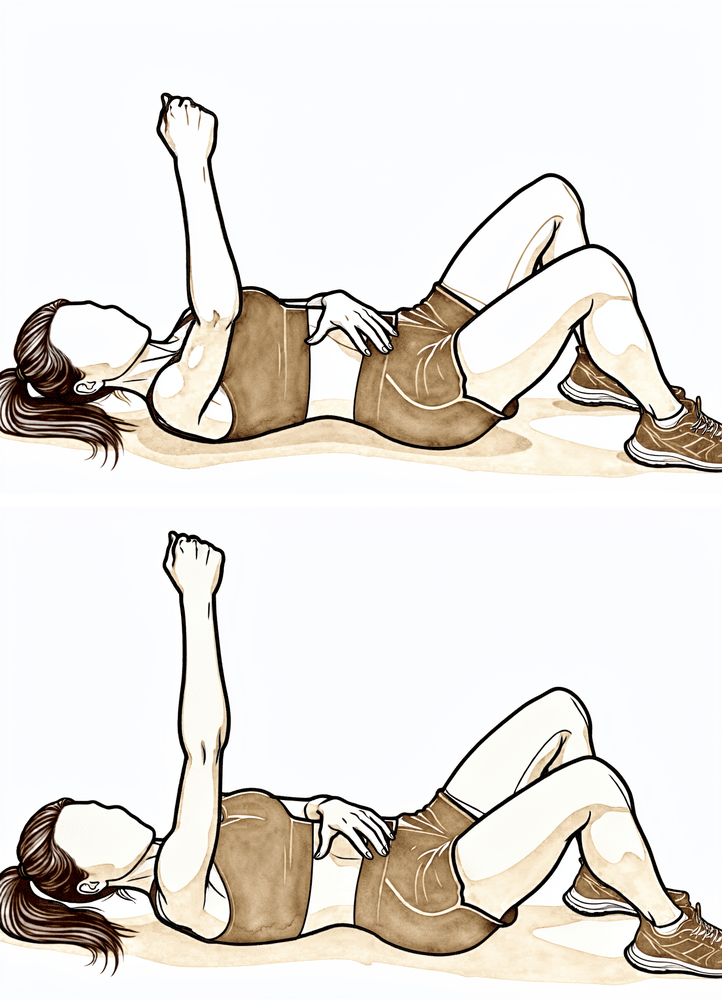
Supine punch
Humiga nang patihaya at itaas nang diretso ang operadong braso patungo sa kisame. Habang pinapanatiling diretso ang siko, itulak nang bahagya ang kamay paitaas patungo sa kisame upang umangat ang shoulder blade mula sa kama, pagkatapos ay ibaba ito nang may kontrol.
Ayon sa gabay ng iyong physiotherapist
Ang balikat ngayon ay magpapatuloy sa paggalaw na sinimulan mo agad pagkatapos ng operasyon. Patuloy na tataas ang range of motion, at ang unang activation at strengthening work para sa mga kalamnan ng shoulder-blade (periscapular) at deltoid ay magsisimula sa paligid ng ika-4 na linggo. Sa yugtong ito, dapat ay hindi mo na ginagamit ang sling sa araw; maaari mo pa rin itong gamitin nang panandalian sa gabi kung ito ay nagbibigay ng ginhawa. Ang mga protective rules ay umiiral pa rin: huwag magbuhat ng anumang mas mabigat kaysa sa isang tasa ng kape, huwag abutin ang likod, huwag tumulak gamit ang iyong mga kamay, at panatilihin ang unan sa ilalim ng iyong siko kapag nakahiga nang patihaya.
Para sa iyong physiotherapist:
Mga Layunin
- Patuloy na protektahan ang stability ng component (iwasan ang dislocation position)
- Bawasan ang pamamaga, bawasan ang sakit
- Unti-unting dagdagan ang shoulder PROM
- Isulong ang shoulder AAROM/AROM
- Simulan ang periscapular muscle activation at strengthening (~ika-4 na linggo)
- Simulan ang deltoid activation at strengthening (~ika-4 na linggo; iwasan ang shoulder extension kapag ina-activate ang posterior deltoid)
- Edukasyon ng pasyente
Sling
- Itigil ang paggamit sa araw (weaned off mula ~2 linggo)
- Opsyonal na panandaliang paggamit sa gabi kung ito ay nagbibigay ng ginhawa
Pamamahala
- Ipagpatuloy ang mga interbensyon ng Phase I
- Range of motion / mobility:
- AAROM: active-assistive shoulder flexion, shoulder flexion gamit ang cane, cane external rotation stretch, washcloth press, seated shoulder elevation gamit ang cane
- AROM: supine flexion, salutes, supine punch
- Strengthening:
- Periscapular: scapular retraction, standing scapular setting, supported scapular setting, low row, inferior glide
- Deltoid: isometrics sa scapular plane
Mga Pag-iingat
- Bawal abutin ang likod, lalo na sa internal rotation
- Iwasan ang pinagsamang extension + adduction + internal-rotation (dislocation) position hanggang ~ika-6 na linggo
- Bawal magbuhat ng mga bagay na mas mabigat kaysa sa isang tasa ng kape
- Bawal suportahan ang bigat ng katawan gamit ang mga kamay
- Maglagay ng maliit na unan/towel roll sa ilalim ng siko habang nakahiga nang patihaya upang maiwasan ang shoulder hyperextension
Mga Pamantayan para sa pag-usad
- Unti-unting pagtaas ng shoulder PROM, AAROM, AROM
- 0 degrees shoulder PROM patungong IR
- Nararamdamang muscle contraction sa scapular musculature
- Sakit < 4/10
- Walang mga komplikasyon sa Phase II
Phase III — Intermediate, pagpapatuloy (Weeks 7–8)
Kieran Hirpara 4.0
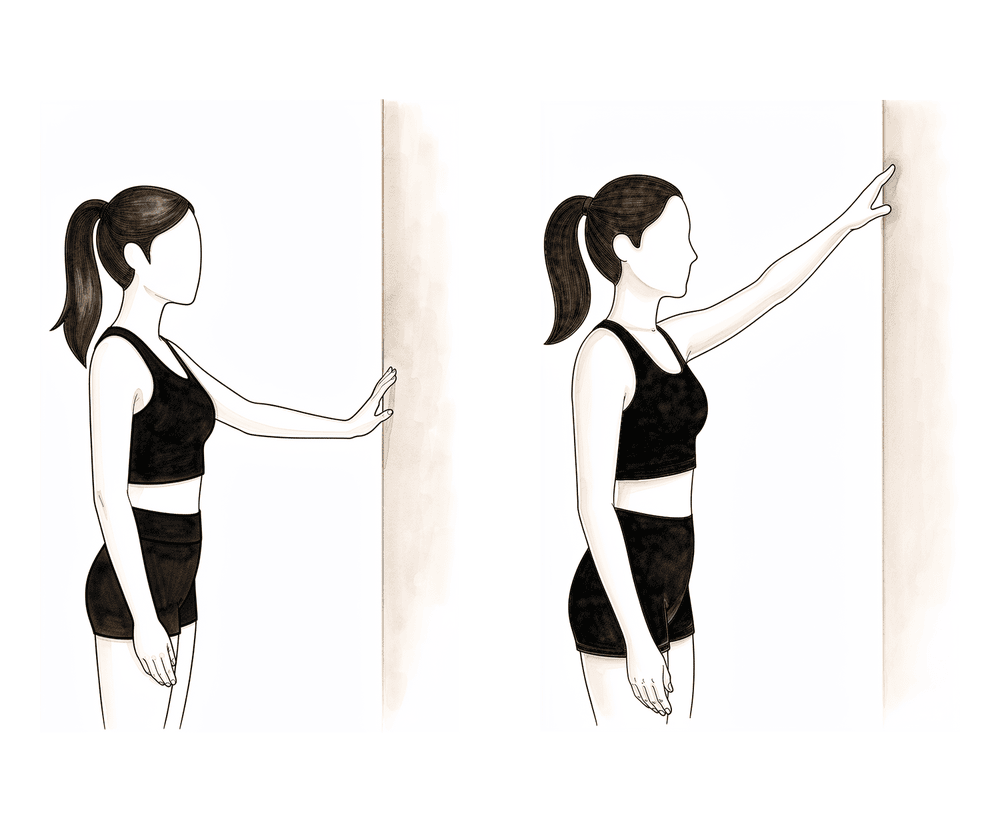
Wall climbs
Tumayo nang nakaharap sa pader at i-lakad ang mga daliri ng operadong braso pataas sa pader hanggang sa komportable pa, hayaang tulungan ng pader ang braso na pumunta pataas. I-lakad ang mga daliri pabalik pababa nang may kontrol — huwag hayaang biglang bumagsak ang braso.
Ayon sa gabay ng iyong physiotherapist
Kieran Hirpara 4.0
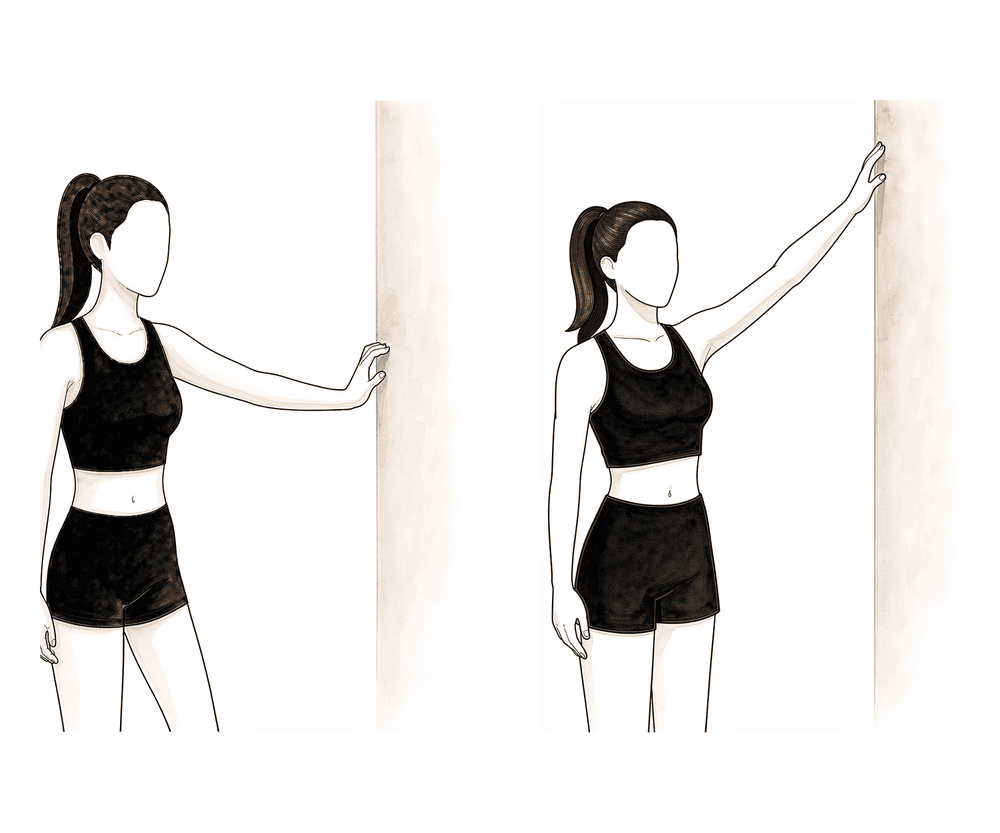
Wall walk palabas sa gilid
Tumayo nang patagilid sa isang pader na ang iyong mga dulo ng daliri ay nakapatong dito. I-lakad ang iyong mga daliri pataas sa pader palabas sa gilid, itaas ang braso hanggang sa komportable, pagkatapos ay dahan-dahang i-lakad ang mga ito pabalik pababa nang may kontrol. Sinusuportahan ng pader ang braso habang binabawi mo ang paggalaw palabas sa gilid.
Ayon sa gabay ng iyong physiotherapist
Tapos na ang paggamit mo ng sling sa puntong ito. Ang paggalaw ay umuusad sa lahat ng direksyon, kabilang ang unang banayad na passive internal rotation (pag-ikot ng braso papasok), at ang pagpapalakas ng mga kalamnan ng deltoid at shoulder-blade ay itinataas, kasabay ng mga unang motor-control (coordination) exercises. Ang mga limitasyong nananatili: walang mas mabigat kaysa sa tasa ng kape, bawal ang pag-abot sa likod na lampas sa bulsa ng pantalon, bawal ang paglalagay ng bigat ng katawan sa mga kamay, at iwasan ang pag-unat ng braso pabalik sa likod ng iyong katawan.
Para sa iyong physiotherapist:
Mga Layunin
- Bawasan ang sakit
- Unti-unting isulong ang shoulder PROM; simulan ang shoulder PROM IR sa scapular plane
- Unti-unting isulong ang shoulder AAROM
- Unti-unting isulong ang shoulder AROM
- Isulong ang pagpapalakas ng deltoid
- Isulong ang pagpapalakas ng periscapular
- Simulan ang motor control exercise
- Edukasyon ng pasyente
Sling
- Itigil na
Pamamahala
- Ipagpatuloy ang mga interbensyon ng Phase I & II
- Range of motion / mobility:
- PROM: puno sa lahat ng plane; unti-unting PROM IR sa scapular plane ≤ 50 degrees
- AAROM: incline table slides, wall climbs, pulleys, seated shoulder elevation gamit ang cane na may active lowering
- AROM: seated scaption, seated flexion, supine forward elevation na may elastic resistance hanggang 90 degrees
- Pagpapalakas:
- Periscapular: row sa isang physioball, serratus punches
- Deltoid: seated shoulder elevation gamit ang cane, seated shoulder elevation gamit ang cane na may active lowering, ball roll sa dingding
- Motor control:
- IR/ER sa scaption plane at flexion 90–125 degrees (rhythmic stabilisation) sa supine
- Pag-unat (Stretching):
- Sidelying horizontal adduction (ADD), triceps at lats
Mga Pag-iingat
- Bawal ang pag-abot sa likod na lampas sa bulsa ng pantalon
- Bawal ang pagbuhat ng mga bagay na mas mabigat kaysa sa tasa ng kape
- Bawal ang pagsuporta ng bigat ng katawan gamit ang mga kamay
- Iwasan ang shoulder hyperextension
Mga Kraytirya para sa pag-usad
- Mga layunin sa ROM (ang mga inaasahan sa PROM at AROM ay indibidwal at nakadepende sa mga ROM measurement na nakuha sa operating room pagkatapos ng operasyon):
- Elevation ≤ 140 degrees
- ER ≤ 30 degrees sa neutral
- IR ≤ 50 degrees sa scapular plane, o back pocket
- Minimal hanggang sa walang substitution patterns sa shoulder AROM
- Sakit < 4/10
Phase IV — Transitional (Weeks 9–11)
Ang phase na ito ang tulay pabalik sa normal na paggamit ng braso. Ang passive movement ay dapat na full na sa lahat ng planes, at ang pokus ay lilipat sa pagpapalakas ng mga kalamnan ng deltoid at shoulder-blade, pagbuo ng dynamic stability at coordination, at unti-unting pagbabalik ng lakas at endurance, kasama ang pagbabalik sa full functional activities. Ang isang mahigpit na limitasyon: bawal magbuhat ng mabibigat na bagay (higit sa 5 kg).
Para sa iyong physiotherapist:
Mga Layunin
- Panatilihin ang pain-free ROM
- Isulong ang periscapular strengthening
- Isulong ang deltoid strengthening
- Isulong ang motor control exercise
- Pagbutihin ang dynamic shoulder stability
- Unti-unting ibalik ang shoulder strength at endurance
- Bumalik sa full functional activities
Pamamahala
- Ipagpatuloy ang mga interbensyon ng Phase II–III
- Range of motion / mobility:
- PROM: full ROM sa lahat ng planes
- Strengthening:
- Periscapular: resistance band shoulder extension, resistance band seated rows, rowing, robbery, lawnmowers, tripod, pointer
- Deltoid: unti-unting magdagdag ng resistance sa deltoid exercise
- Motor control:
- IR/ER at flexion 90–125 degrees (rhythmic stabilisation)
- Quadruped alternating isometrics at ball stabilisation sa wall
- Field goals
- Proprioceptive neuromuscular facilitation (PNF): D1 diagonal lifts, D2 diagonal lifts
Mga Pag-iingat
- Bawal magbuhat ng mabibigat na bagay (> 5 kg)
Mga Kraytirya para sa pag-usad
- Naisasagawa ang lahat ng ehersisyo na nagpapakita ng symmetric scapular mechanics
- Pain < 2/10
Phase V — Advanced strengthening (Weeks 12–16)
Kieran Hirpara 4.0
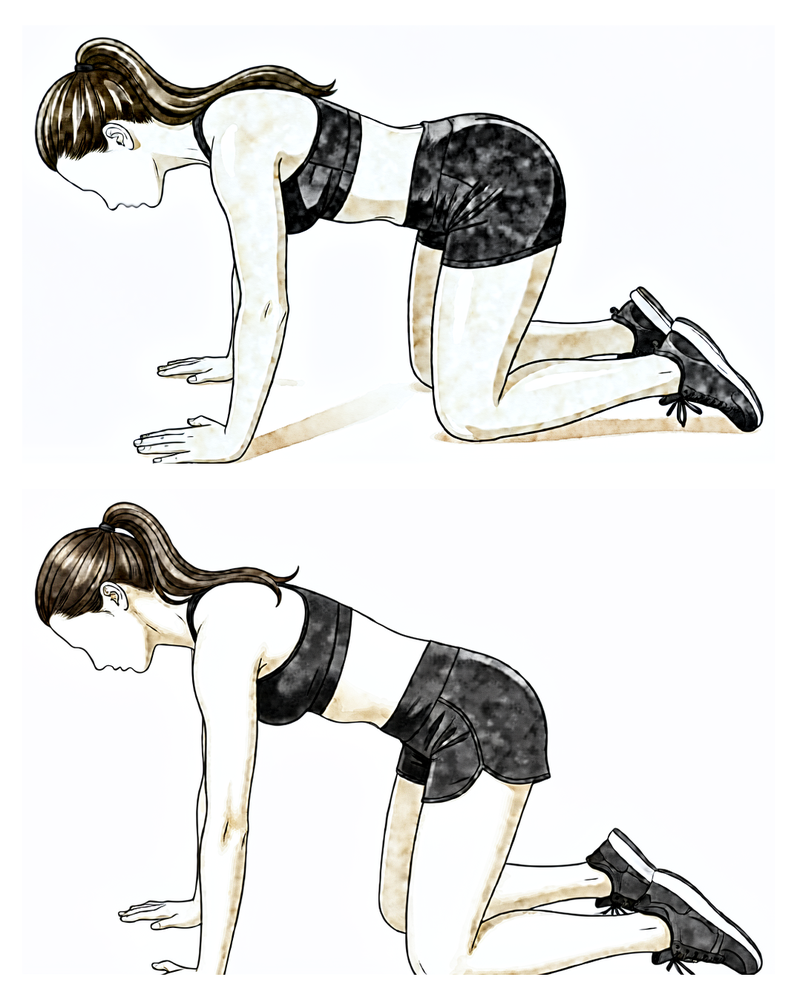
Push-up plus nang nakaluhod
Mula sa posisyon ng push-up gamit ang iyong mga tuhod at ang mga kamay ay nasa ilalim ng mga balikat, panatilihing diretso ang mga siko at itulak ang itaas na bahagi ng likod patungo sa kisame, hayaang maghiwalay ang mga shoulder blade, pagkatapos ay ibaba ito nang may kontrol.
Ayon sa gabay ng iyong physiotherapist
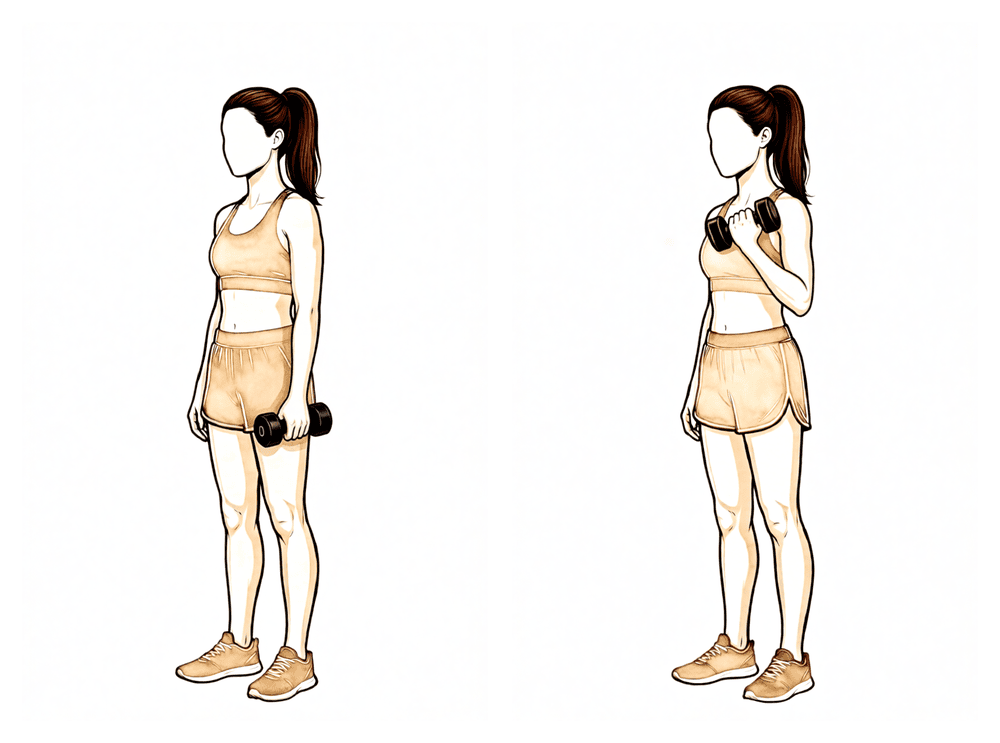
Kieran Hirpara 4.0
Biceps curl
Humawak ng magaan na pabigat nang nakaharap pataas ang iyong palad at ang iyong braso ay nasa iyong gilid, itiklop ang siko upang ilapit ang kamay sa balikat, pagkatapos ay ibaba ito nang may kontrol. Panatilihing magaan ang pabigat — ang mabibigat na pagbuhat (higit sa 7 kg) ay bawal pa rin sa yugtong ito.
Ayon sa gabay ng iyong physiotherapist
Ang huling phase ay inihahanda ang balikat para sa pang-araw-araw na buhay: pinapanatiling walang sakit ang iyong paggalaw habang binubuo ang lakas at endurance upang magamit ang braso nang may kumpiyansa. Kung ang rotator cuff repair ay isinagawa kasabay ng iyong replacement, ang pagpapalakas ng rotator cuff (RTC) ay magsisimula na ngayon. Ang limitasyon sa pagbuhat ay tataas, ngunit ang mabibigat na bagay (higit sa 7 kg) ay bawal pa rin. Ang phase na ito, at ang protocol, ay matatapos kapag may clearance na mula sa iyong surgeon kapag ang lahat ng milestones ay nakamit na.
Para sa iyong physiotherapist:
Mga Layunin
- Panatilihin ang pain-free ROM
- Simulan ang pagpapalakas ng rotator cuff (RTC) kung may kasabay na repair
- Pagbutihin ang lakas at endurance ng balikat
- Paghusayin ang functional use ng upper extremity
Pamamahala
- Ipagpatuloy ang mga interbensyon mula Phase II–IV
- Pagpapalakas (Strengthening):
- Periscapular: push-up plus on knees, "W" exercise, resistance band Ws, prone shoulder extension Is, dynamic hug, resistance band dynamic hug, resistance band forward punch, forward punch, T and Y, "T" exercise
- Deltoid: ipagpatuloy ang unti-unting pagpapataas ng resisted flexion at scaption sa mga functional position
- Elbow: bicep curl, resistance band bicep curls, at triceps
- Rotator cuff: internal/external rotation isometrics, side-lying external rotation, standing external rotation na may resistance band, standing internal rotation na may resistance band, internal rotation, external rotation, sidelying ABD na mag-pro-progress sa standing ABD
- Motor control:
- Resistance band PNF pattern, PNF D1 diagonal lifts na may resistance, diagonal-up, diagonal-down, wall slides na may resistance band
Mga Pag-iingat
- Bawal magbuhat ng mabibigat na bagay (> 7 kg)
Mga Kraytirya para mag-progress
- Clearance mula sa surgeon, at LAHAT ng milestone criteria ay nakamit na
- Pinapanatili ang pain-free PROM at AROM
- Isinasagawa ang lahat ng ehersisyo na nagpapakita ng symmetric scapular mechanics
- QuickDASH at ASES patient-reported outcome measures
Pagkatapos ng iyong protocol
Ang protocol na ito ay kasabay ng pangkalahatang payo sa paggaling ng klinika: tingnan ang pamamahala ng sakit pagkatapos ng operasyon at pag-aalaga ng sugat. Para sa mismong operasyon, tingnan ang reverse shoulder replacement.
Ang klinikal na ebidensya sa likod ng protocol na ito (ang mga nailathalang rehabilitation trial, ang pangangatwiran para sa sling at mga panuntunan sa paggalaw, at ang mga sanggunian sa pananaliksik) ay nakasaad sa kalakip na buod ng ebidensya (available bilang isang downloadable PDF).
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Reverse Shoulder Arthroplasty (Cuff-Tear Arthropathy / Arthritis) — Post-operative Rehabilitation Evidence
Topic scope: Post-operative rehabilitation after elective reverse total shoulder arthroplasty (RSA / rTSA) for rotator-cuff-tear arthropathy, glenohumeral arthritis with an irreparable cuff, or a massive irreparable cuff tear — not the acute proximal-humerus-fracture indication, where tuberosity healing imposes its own restrictions. The evidence base for the operation (when RSA is indicated, implant survivorship, complication profile) is extensive; the evidence base for the rehabilitation protocol is smaller but, unusually for shoulder surgery, now includes several randomised trials directly comparing immobilisation strategies.
Defining principle of this rehab: RSA rehabilitation is comparatively permissive and is increasingly run on an accelerated footing. Two features of the reconstructed joint explain why. First, the deltoid — not the rotator cuff — drives elevation after RSA; the design medialises and lowers the centre of rotation so the deltoid can elevate an arm that has no functioning cuff. Second, there is usually no subscapularis repair to protect (and many surgeons deliberately leave it unrepaired with a lateralised implant), so the external-rotation restriction that dominates anatomic-TSA rehab is far less central here. The principal early caution is therefore not tissue healing but component stability: a reverse prosthesis can dislocate, and the at-risk position is the combination of extension + adduction + internal rotation (the hand-behind-the-back / tucking-in-a-shirt movement). Early rehab accordingly protects against that position while otherwise encouraging motion. The sling is largely for comfort, support and dislocation-avoidance, and the published trial evidence shows that shortening or even omitting it does not increase the dislocation or complication rate.
Surgeon's protocol note: Dr Hirpara's protocol on this page is run on an accelerated footing, directly aligned with the randomised and cohort evidence below: a short ~2-week comfort sling (weaned off during the day; optional brief night use), active-assisted and active shoulder motion from the start (within defined limits, beginning supine/gravity-assisted), and deltoid + periscapular strengthening from ~week 4. The main early constraint is component stability, so the extension + adduction + internal-rotation (hand-behind-back) dislocation position is avoided for the first ~6 weeks while motion is otherwise encouraged. Elevation after RSA is deltoid-driven, which is why strengthening is deltoid- and periscapular-focused. Follow the protocol your surgeon has set.
The operation, in brief
In a reverse replacement the normal anatomy is inverted: a ball (glenosphere) is fixed to the shoulder blade and a cup is fixed to the top of the arm bone. This moves the joint's pivot point down and in, which lengthens and tensions the deltoid and lets that muscle lift the arm even when the rotator cuff is gone — the situation in cuff-tear arthropathy. Because the implant, not the patient's own cuff, provides stability and power, the rehabilitation logic differs fundamentally from a cuff repair (where a healing tendon must be protected) and from an anatomic replacement (where a repaired subscapularis must be protected).
Evidence by theme
1. Early / accelerated motion is safe — multiple randomised trials
This is the best-supported part of RSA rehabilitation, and it is unusually strong for a shoulder rehab question because it rests on randomised controlled trials, not just consensus:
- Hagen et al. (2020), single-blind RCT, 107 shoulders — randomised to immediate physical therapy (passive + active ROM from the start) versus 6-week delayed therapy. No difference in final ROM, patient-reported outcomes, or dislocation/complication rate (early 7.1% vs delayed 9.1%). [RAG corpus — 10.1016/j.jse.2020.11.017]
- Edwards / "two rehabilitation approaches" RCT, 61 patients (63 shoulders) — early active (submaximal isometric deltoid work from week 2) versus delayed active rehab, both with a 6-week sling. Pain and overall function were equivalent at 3, 6 and 12 months, but the early-active group had significantly better active forward flexion at 3 months (p = 0.019) — i.e. earlier functional gain without added risk. [Literature — PMC8512973]
- Lee et al. (2021), 357 shoulders — randomised to no immobilisation / early motion, 3-week sling, or 6-week sling. No difference in patient-reported outcomes, satisfaction, pain or ROM; the immediate-motion group had the lowest overall complication rate (reported as ~4% vs ~24.6% in the 6-week cohort in the pooled systematic-review re-analysis). [via Sachinis 2024 SR]
A systematic review (Sachinis et al., 2024; 3 controlled trials, ~527 shoulders) concluded that accelerated rehabilitation is safe and yields equivalent 12-month outcomes, while cautioning that protocols should still be individualised by bone quality, age, diagnosis and surgical complexity rather than applied uniformly. [Literature — PMC11034463]
Evidence: MODERATE–STRONG (several RCTs + SR), though individual trials are modest in size.
2. Sling duration can be shortened without added risk
- A large retrospective cohort (960 patients) compared 2-week vs 6-week sling immobilisation after RSA and found no difference in complication rate (12.0% vs 15.0%, p = 0.21), dislocation rate (p = 0.79), acromial stress fracture, loosening or infection; final flexion and ER were equivalent. The authors concluded shorter immobilisation does not incur additional risk. [Literature — PMC10638591]
- Published institutional protocols (e.g. Massachusetts General Brigham) have themselves moved from a 6-week to a 4-week sling standard, attributing the change to improved implant design. [Published protocol — MGH Sports Medicine]
Evidence: MODERATE (one large cohort + protocol trend; the question is now whether 6 weeks is necessary, not whether it is safe).
3. The deltoid drives recovery — and formal active PT may add little
Because elevation depends on deltoid recruitment (with documented compensatory recruitment of upper trapezius, latissimus and posterior deltoid), strengthening is deltoid- and periscapular-focused rather than cuff-focused. Notably, a multicentre RCT found that a formal active physical-therapy programme did not improve outcomes over a home/self-directed programme after RSA — many patients recover well with a structured home programme and physiotherapist supervision rather than intensive hands-on active therapy. [RAG corpus — 10.1016/j.jse.2022.12.011] This supports a pragmatic, education-and-home-exercise model.
Evidence: MODERATE (RCT).
4. Dislocation: low but real, and the early protective position is specific
Dislocation is the relevant early stability complication (as opposed to the tissue-healing concern of a cuff repair). Corpus series on dislocation following RSA identify the at-risk position as adduction + internal rotation + extension, and identify subscapularis insufficiency and implant/soft-tissue tensioning as contributors to instability. [RAG corpus — 10.1016/j.jse.2016.12.073; 10.1016/j.jse.2008.12.013] This is precisely why early protocols — accelerated or conservative — restrict reaching behind the back and forced internal rotation while otherwise allowing supported elevation. The role of routine subscapularis repair in preventing dislocation is debated and interacts with glenosphere lateralisation (a lateralised design appears less reliant on subscapularis repair for stability). [RAG corpus — 10.5435/jaaos-d-16-00781]
Evidence: MODERATE (cohort/registry); the precaution itself is universal consensus.
5. Contrast with anatomic TSA rehabilitation
The American Society of Shoulder and Elbow Therapists (ASSET) consensus on anatomic TSA rehab centres on protecting the subscapularis repair — limiting passive external rotation and active internal rotation for ~6 weeks. [RAG corpus — 10.1016/j.jse.2020.05.019] After RSA that specific constraint is usually absent or much reduced (no cuff repair to protect; subscapularis often not repaired), which is the structural reason RSA rehab is more permissive in external rotation while being more attentive to the dislocation-position combination.
Phased post-operative timeline
This table reflects Dr Hirpara's protocol on this page (the accelerated, ~2-week-sling approach). The right-hand column notes the published evidence that the protocol is grounded in.
| Phase | Window | Sling | Shoulder motion | Strengthening | Accelerated-evidence basis |
|---|---|---|---|---|---|
| I — Protection | Week 0–3 | Comfort/support; wean off during the day from ~2 weeks; optional brief night use | Active-assisted and active as tolerated from the start (begin supine/gravity-assisted; ER in scapular plane to tolerance; flexion/scaption ≤120°; abduction ≤90°); no IR, no reaching behind back, avoid the dislocation position; elbow/wrist/hand active | — | RCTs show early active/AAROM from the start carries no added dislocation/complication risk (Hagen 2020; Edwards) |
| II — Intermediate | Week 4–6 | Off during the day; optional brief night use | Progress AAROM and AROM | Periscapular + deltoid activation and strengthening initiated (~week 4) | Early active deltoid work gives earlier functional gain without added risk (Edwards) |
| III — Intermediate cont. | Week 7–8 | Discontinued | Progress AROM all planes; first gentle passive IR in scapular plane (≤50°) | Deltoid + periscapular progressed; motor control | Cohort data: 2-week sling non-inferior to 6 weeks (no extra dislocations) |
| IV — Transitional | Week 9–11 | — | Full passive ROM all planes | Resisted deltoid/periscapular; dynamic stability; PNF; no lifting >5 kg | — |
| V — Advanced strengthening | Week 12–16 | — | Maintain pain-free full ROM | Add rotator-cuff strengthening if a cuff repair was done; functional loading; no lifting >7 kg | Resisted IR / eccentric / closed-chain typically from ~12 weeks |
Return-to-activity anchors (from this protocol): driving ~6 weeks; light lifting from 6 weeks but no heavy lifting for ~6 months; swimming (breaststroke) 8 weeks / freestyle 12 weeks; golf ~3 months; sedentary work 6 weeks, manual work surgeon-guided. Published sport-return data after RSA are encouraging for low-impact activity (≈60–86% return; swimming ~84%, golf/fitness ~77%) but caution against high-impact and contact sport given prosthesis-loading and revision concerns. [Literature — PMC10043097]
Key controversies / evidence quality
-
Accelerated vs conservative rehab — and where this protocol sits. The randomised evidence shows early motion and shorter (or no) immobilisation are safe and may give earlier functional gain, with equivalent 12-month outcomes. Dr Hirpara's ~2-week comfort sling, active-assisted/active motion from the start, strengthening from ~week 4 protocol aligns with this accelerated evidence. The systematic review still endorses individualisation (bone quality, fixation, intra-operative stability, soft-tissue tensioning, any concomitant cuff repair), so the surgeon may dial the plan back for a borderline-stable construct, softer bone, or a concomitant repair. The prescribed plan is the one to follow.
-
Immobilisation duration. Trial and large-cohort data show 2–4 weeks is non-inferior to 6 weeks for dislocation and complications, which is why this protocol uses a short ~2-week comfort sling. Longer 6-week protocols persist elsewhere out of surgeon preference and construct-specific factors, with the low absolute dislocation rate making the question hard to power definitively.
-
Precautions. The extension + adduction + internal rotation (hand-behind-back) restriction is near-universal consensus early on; the disagreement is about how long, and how much external-rotation freedom to allow (more than anatomic TSA, but bounded by soft-tissue tension).
-
Subscapularis repair. Whether to repair it — and whether repair reduces dislocation — interacts with glenosphere lateralisation and remains debated; this in turn influences how restrictive early rehab needs to be.
-
Active physiotherapy intensity. At least one RCT found formal active PT did not beat a structured home programme, supporting an education-led, home-exercise model with physiotherapist oversight rather than intensive hands-on therapy.
Evidence-strength flags (summary)
- MODERATE–STRONG (RCT / SR): accelerated/early-motion rehab is safe with equivalent 12-month outcomes (Hagen 2020 RCT; Edwards RCT; Lee 2021; Sachinis 2024 SR); formal active PT not superior to home programme (multicentre RCT).
- MODERATE (large cohort): 2-week sling non-inferior to 6-week sling for dislocation/complications (960-patient cohort); deltoid-driven recovery biomechanics.
- CONSENSUS / WEAK: the dislocation-position precaution (universal but not trial-quantified for duration); the specific phase timings of this protocol (drawn from published institutional protocols + surgeon preference, not a head-to-head rehab RCT); subscapularis-repair effect on instability (conflicting cohort data).
Citations
RAG corpus (180,000+ Orthopaedic articles) — real DOIs returned by search
- Hagen MS, et al. Accelerated rehabilitation following reverse total shoulder arthroplasty. J Shoulder Elbow Surg / Semin Arthroplasty. 2021. DOI: 10.1016/j.jse.2020.11.017
- Active physical therapy does not improve outcomes after reverse total shoulder arthroplasty: a multi-center, randomized clinical trial. J Shoulder Elbow Surg. 2023. DOI: 10.1016/j.jse.2022.12.011
- Kennedy J, et al. The American Society of Shoulder and Elbow Therapists' consensus statement on rehabilitation for anatomic total shoulder arthroplasty. J Shoulder Elbow Surg. 2020. DOI: 10.1016/j.jse.2020.05.019
- Dislocation following reverse total shoulder arthroplasty. J Shoulder Elbow Surg. 2017. DOI: 10.1016/j.jse.2016.12.073
- Edwards TB, et al. Subscapularis insufficiency and the risk of shoulder dislocation after reverse shoulder arthroplasty. J Shoulder Elbow Surg. 2009. DOI: 10.1016/j.jse.2008.12.013
- Clinical Outcomes After Reverse Shoulder Arthroplasty With and Without Subscapularis Repair: The Importance of Considering Glenosphere Lateralization. J Am Acad Orthop Surg. 2018. DOI: 10.5435/jaaos-d-16-00781
Literature (URLs)
- Sachinis NP, et al. Can we accelerate rehabilitation following reverse shoulder arthroplasty? A systematic review. Shoulder Elbow. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC11034463/
- A randomised trial comparing two rehabilitation approaches following reverse total shoulder arthroplasty (early active vs delayed active). 2021. https://pmc.ncbi.nlm.nih.gov/articles/PMC8512973/
- No difference in complications between two-week vs. six-week duration of sling immobilization after reverse total shoulder arthroplasty (960-patient cohort). 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10638591/
- Optimizing Outcomes After Reverse Total Shoulder Arthroplasty: Rehabilitation, Expected Outcomes, and Maximizing Return to Activities. 2023. https://pmc.ncbi.nlm.nih.gov/articles/PMC10043097/
- Kim Y-T, et al. Four weeks of immobilisation after reverse shoulder arthroplasty yields outcomes comparable to six weeks. Clin Shoulder Elb. 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC11546419/
Published rehabilitation protocols (basis for the phase structure)
- Massachusetts General Brigham Sports Medicine. Rehabilitation Protocol for Reverse Shoulder Arthroplasty. Revised December 2018. https://www.massgeneral.org/assets/mgh/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-reverse-shoulder-arthroplasty.pdf
- Brigham and Women's Hospital. Reverse Total Shoulder Arthroplasty Protocol. https://www.brighamandwomens.org/assets/BWH/patients-and-families/pdfs/shoulder--reverse-total-shoulder-arthroplasty-protocol.pdf