Patients › Shoulder
Os Acromiale
Patient-facing topic on os acromiale — failed fusion of an acromial ossification centre that may cause shoulder pain and contribute to subacromial impingement.
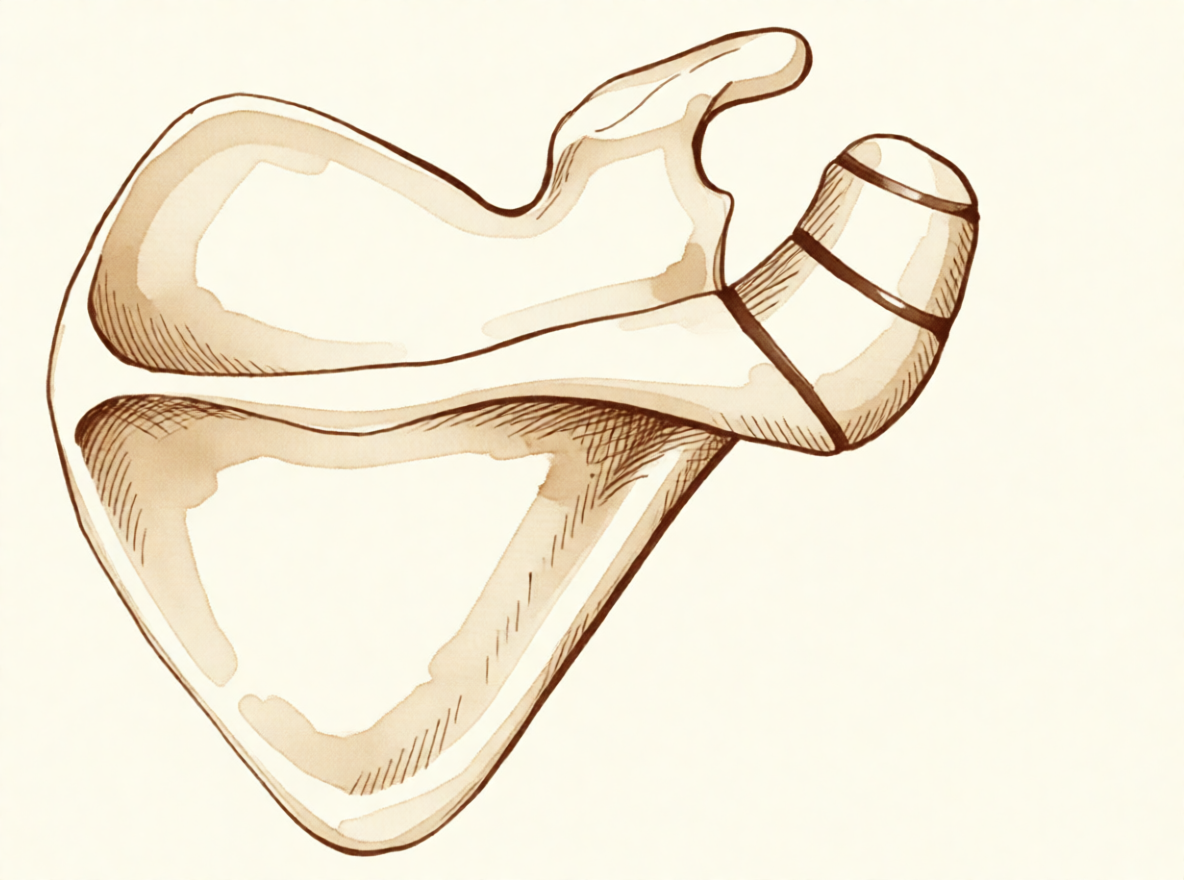
Ang iyong nararamdaman
Sa os acromiale, ang sakit ay karaniwang nasa harap at gilid ng iyong balikat, sa ibabaw ng butong bubong ng joint. Lumalala ito sa mga aktibidad na nakataas ang braso sa itaas ng ulo. Ang pag-abot sa mataas na istante, pagsasampay ng labada, o pagbubuhat ng isang bagay nang mas mataas sa taas ng balikat ay maaaring lahat magpasimula nito. Marami rin ang nakakapansin ng sakit sa gabi, at maaari ka nitong gisingin kapag nakahiga ka sa panig na iyon.
Ang sakit ay nagmumula sa isang maliit na piraso ng buto sa itaas ng balikat na hindi kailanman dumugtong sa natitirang bahagi habang lumalaki. Kapag itinataas mo ang iyong braso, hinihila ng isang kalamnan ang maluwag na pirasong ito at bahagya itong gumagalaw, na dumidiin sa tendon sa ilalim nito. Ang bahagi kung saan nagtatagpo ang dalawang piraso ng buto ay maaari ring maging masakit kapag hinawakan, at ang direktang pagpindot dito ay maaaring magpasimula ng sakit.
Sa pang-araw-araw, maaari mong mapansin na mahina ang iyong braso kapag itinataas mo ito palabas sa gilid o pinipihit ito palabas. Karaniwan ang painful arc: sumasakit ang balikat sa kalagitnaan habang itinataas mo ito, pagkatapos ay humuhupa habang itinataas pa nang mas mataas. Dahil ang mga sintomas ay halos kamukha ng pagkaluma (wear-and-tear) ng tendon sa ilalim ng bubong ng balikat, madaling mapagkamalan ang kondisyong ito bilang problema sa rotator cuff, at maaari itong patuloy na magdulot ng sakit kahit pagkatapos ng gamutan para doon.
Karamihan sa mga taong may ganitong anyo ng buto ay hindi kailanman nakakaramdam ng anuman. Madalas itong natutuklasan nang hindi sinasadya sa isang scan na ginawa para sa ibang bagay. Kapag nagdulot ito ng sakit, may tendensiya itong lumitaw sa mga mas batang adulto, kadalasan nang walang anumang pinsala, at dapat itong paghinalaan kung ang sakit sa iyong balikat ay hindi humupa sa physiotherapy, pahinga mula sa sport, o injection.
Kung hindi humuhupa ang iyong mga sintomas, lumalala sa loob ng ilang linggo, ginigising ka sa gabi, o pinipigilan kang magtrabaho o gamitin ang iyong braso, magpatingin sa iyong GP o humingi ng pagsusuri ng isang espesyalista.
Ano ang aktwal na nangyayari
Ang butong bubong ng iyong balikat ay hindi nabubuo bilang iisang piraso ng buto. Nagsisimula ito bilang tatlong magkakahiwalay na sentro na dahan-dahang nagsasama, simula sa mga edad 15 at karaniwang tapos na pagsapit ng edad 25. Sa humigit-kumulang 8% ng mga tao, ang isa sa mga pagdudugtong na ito ay hindi kailanman nagsasara. Ang puwang ay napupuno ng matigas na tissue na parang gristle sa halip na buto, na nag-iiwan ng isang maliit na piraso ng bubong na nakakabit sa pamamagitan ng isang flexible na dugtungan sa halip na solidong buto.
Isipin ito na parang tablang nakakabit sa pader na may isang maluwag na turnilyo. Nakakapit ito, ngunit bahagya itong gumagalaw kapag sumasandal ka rito. Ang kalamnan na nagtataas ng iyong braso palabas sa gilid ay nakakabit sa bubong na ito, kaya sa tuwing itinataas mo ang iyong braso, hinihila ng kalamnang iyon ang maluwag na piraso at bahagya itong bumabaluktot. Ang paggalaw na iyon ay dumidiin pababa sa tendon na dumadaan sa ilalim ng bubong, at ang pagkiskis ay nakakairita rito. Iyan ang dahilan kung bakit masakit ang mga aktibidad na nakataas ang braso sa itaas ng ulo at kung bakit ang sakit ay nasa harap at gilid ng iyong balikat.
Ang flexible na dugtungan mismo ay maaari ring maging problema. Maaari itong maging masakit nang sarili nito, katulad ng isang lumang joint, at ang pagpindot dito ay nagpapasimula ng sakit. Karamihan sa mga taong may ganitong anyo ng buto ay hindi kailanman nakakaramdam ng anuman, at mukhang hindi ito nagdudulot ng sakit sa balikat nang mag-isa o nagpapataas ng posibilidad ng punit sa tendon. Ngunit kapag ang maluwag na piraso ay nagsimulang gumalaw nang higit sa karaniwan, dahil man sa paraan ng pagkakabuo nito o pagkatapos ng pagkakauntog sa bahaging iyon, maaari itong dumiin sa tendon sa tuwing nagbubuhat ka. Iyan ang nagdudulot ng painful arc at sakit sa gabi na inilarawan sa itaas.
Dahil ang maluwag na piraso ay nasa mismong lugar kung saan naroon ang tendon, madalas na sabay na lumilitaw ang dalawang problema. Kung nagamot na ang iyong balikat para sa isang problema sa tendon at hindi pa rin humuhupa ang sakit, dapat ipasuri ang hindi nagsamang pirasong ito, dahil ang pag-opera sa tendon lamang ay hindi magpapatahimik sa isang gumagalaw na piraso ng buto sa itaas nito.
Ano ang maaari naming gawin tungkol dito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyon na hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Sa iyong unang pagbisita, kumukuha kami ng history, sinusuri ang iyong balikat at nag-aayos ng imaging kung saan ito kinakailangan.
Ang unang hakbang ay karaniwang ang pagbabago kung paano mo ginagamit ang iyong balikat at ang pagbibigay ng tunay na pagkakataon sa physiotherapy. Layunin ng physio na pahupain ang iritasyon sa ilalim ng butong bubong at palakasin ang mga kalamnan sa paligid ng iyong balikat upang mas makayanan nila ang mga gawaing nakataas ang braso sa itaas ng ulo. Bigyan ito ng sapat na pagsubok bago mag-isip ng anumang susunod na hakbang.
Makatutulong ang gamot sa sakit upang patuloy kang makagalaw habang nangyayari iyon. Ang mga simpleng anti-inflammatory, na iniinom ayon sa payo ng iyong GP, ay nagpapahupa ng pananakit upang komportable mong magawa ang iyong mga ehersisyo. Kung hindi humuhupa ang sakit, lumalala sa loob ng ilang linggo, ginigising ka sa gabi, o pinipigilan kang magtrabaho o gamitin ang iyong braso, magpatingin sa iyong GP o humingi ng pagsusuri ng isang espesyalista.
Kapag ang non-operative care ay hindi nagbigay ng sapat na pagbuti, isinasaalang-alang namin ang operasyon. Bago iyon, kinukumpirma namin ang diagnosis sa pamamagitan ng karaniwang X-ray, na halos palaging sapat upang ipakita ang hindi nagsamang piraso. Ang isang view na kinuha mula sa ilalim ng kilikili ay malinaw na nagpapakita ng hugis ng joint at ng harapang bahagi ng bubong, at mahalaga ito dahil ang isang pinsala ay maaaring makasira sa dugtungan sa pagitan ng dalawang piraso ng buto. Ang ultrasound ay isang simple at tumpak na paraan upang suriin ang tendon na dumadaan sa ilalim ng bubong, at ang MRI scan ay nagbibigay ng mas kumpletong larawan ng tendon na iyon at ng nakapaligid na soft tissue.
Ang operasyong pinakamadalas naming iniaalok ay isang keyhole (arthroscopic) na pagsusuri sa joint kasama ang bursectomy, na nangangahulugang paglilinis ng inflamed na tissue mula sa espasyo sa ilalim ng bubong, at pagkatapos ay isang maliit na open na hiwa para sa bone grafting at fixation, na nangangahulugang pagpapanatiling hindi gumagalaw ng maluwag na piraso upang ito ay dumugtong sa natitirang bahagi ng buto. Ang pagpapanatili rito na hindi gumagalaw ay nagpapahintulot sa dalawang piraso na magsama. Kung maliit ang maluwag na piraso, maaari namin itong alisin sa halip na i-fix. Kailangan ng ingat sa pag-fix ng mas malaking piraso, dahil patuloy itong hinihila ng kalamnan na nagtataas ng iyong braso at manipis ang piraso. Kung minsan, ang fragment ay hindi dumudugtong pagkatapos ng fixation, na tinatawag na non-union. Pag-uusapan natin kung aling opsyon ang angkop sa iyong balikat at magpapasya tayo nang magkasama.
Ano ang dapat asahan
Karamihan sa mga taong may ganitong anyo ng buto ay hindi kailanman nagkakaroon ng anumang problema, at hindi ito nangangailangan ng gamutan. Kapag nagdulot ito ng sakit, ang inaasahang kalalabasan ay nakadepende kung stable ang maluwag na piraso at kung ito nga ba talaga ang pinagmumulan ng iyong sakit.
Para sa isang masakit na piraso, ang pangangalaga ay karaniwang nagsisimula nang walang operasyon. Ang pagbabago kung paano mo ginagamit ang iyong balikat, physiotherapy at simpleng gamot sa sakit ay nakapagpapahupa ng mga bagay para sa maraming tao. Kung hindi ito umubra pagkatapos ng sapat na pagsubok, ang operasyon ay maaaring humantong sa tunay na pagbaba ng sakit at mas mahusay na paggana ng balikat. Kapag ang maluwag na piraso ay napanatiling hindi gumagalaw at dumugtong sa natitirang bahagi ng buto, mas mahusay ang mga resulta ng mga tao sa mga sukatan ng paggana ng balikat kaysa kapag nananatiling hiwalay ang dalawang piraso. Gayunpaman, ang operasyon ay hindi palaging ang sagot. Sa ilang taong may ganitong kondisyon at may punit din sa tendon, halo-halo ang mga resulta pagkatapos ng operasyon, kung saan 53% ang nakakamit ng kasiya-siyang resulta sa kabuuan.
Kung hahayaan lang ito at patuloy kang ginagambala nito, ang sakit ay karaniwang hindi nawawala nang kusa. Madali rin itong makaligtaan: dapat paghinalaan ang kondisyong ito kapag ang sakit sa balikat ay hindi humupa pagkatapos ng gamutan, kabilang ang pagkatapos ng operasyon para sa isang problema sa tendon, dahil ang pag-opera sa tendon lamang ay hindi magpapatahimik sa isang gumagalaw na piraso ng buto sa itaas nito.
Unti-unti ang paggaling pagkatapos ng operasyon. Makikipagtulungan ka sa iyong physiotherapist, uunahin ang pagbabalik ng galaw at pagkatapos ay ang lakas, at ang pagbubuhat sa itaas ng ulo ay dahan-dahang babalik sa loob ng ilang linggo hanggang ilang buwan. Ang layunin ay isang balikat na kaya ang pang-araw-araw na buhay nang walang matinding sakit sa pagbubuhat na dinala mo noong pumunta ka sa amin.
Kung mapansin mo na ang isang daliri, kamay o braso ay naging mainit, namumula, namamaga at masakit, lalo na kung may kasamang lagnat, pumunta sa emergency department sa parehong araw. Hindi kailangan ng referral mula sa GP.
Kailan dapat magpatingin
Karamihan sa mga taong may ganitong anyo ng buto ay hindi kailanman nangangailangan ng pangangalaga, ngunit magpatingin sa iyong GP o humingi ng pagsusuri ng isang espesyalista kung ang sakit sa iyong balikat ay hindi humuhupa, lumalala sa loob ng ilang linggo, ginigising ka sa gabi, o pinipigilan kang magtrabaho o gamitin ang iyong braso. Humingi ng pagsusuri nang mas maaga kung ang sakit ay nasa harap at gilid ng balikat, lumalala sa mga aktibidad na nakataas ang braso sa itaas ng ulo, o paulit-ulit kang ginigising kapag nakahiga ka sa panig na iyon. Sulit din ang magpasuri kung masakit kapag pinipindot ang masakit na bahagi sa itaas ng balikat, kung pakiramdam mo ay mahina ang iyong braso kapag itinataas ito palabas sa gilid o pinipihit ito palabas, o kung sumasakit ang balikat sa kalagitnaan habang itinataas mo ito. Ang mga mas batang adulto na may ganitong mga sintomas at walang pinsala ay dapat suriin para sa kondisyong ito, lalo na kung hindi nakatulong ang physiotherapy, pahinga mula sa sport, o injection. Kung ang isang daliri, kamay o braso ay naging mainit, namumula, namamaga at masakit, lalo na kung may kasamang lagnat, pumunta sa emergency department sa parehong araw; hindi kailangan ng referral mula sa GP.
Higit pang detalye
Advanced reading: the deeper science (optional)
Ang seksyong ito ay higit pa sa kailangan mo para sa iyong sariling mga desisyon sa paggamot. Ang Os acromiale ay karapat-dapat sa karagdagang pagbabasa dahil ito ay isang normal na anatomical variant sa isang makabuluhang minorya ng mga tao, karaniwang walang idinudulot, at madalas na sinisisi sa pananakit ng balikat na hindi naman nito pananagutan.
Ano ito, at gaano ito karaniwan
Ang acromion, ang butong bubong sa ibabaw ng balikat, ay nabubuo mula sa ilang magkakahiwalay na sentro ng buto na karaniwang nagsasama (fuse) sa huling bahagi ng teenage years o unang bahagi ng twenties. Sa ilang tao, may isang hindi nagsasama, na nag-iiwan ng isang permanenteng fibrous junction. Iyon ay isang os acromiale, at ito ay naroon na mula pa sa adolescence sa halip na nakuha (acquired).
Ang prevalence ay nag-iiba depende sa populasyon. Isang multicentre study sa 6,842 na pasyente ang nakatuklas na ang os acromiale ay nauugnay sa mga rotator cuff injury, na ang prevalence sa pinag-aralang populasyong Hapones ay mas mababa kaysa sa mga non-Asian population, at ang laki ng fragment ay may tendensiyang maging mas maliit [1].
Ang asosasyong iyon sa cuff injury ay dapat basahin nang maigi. Itinatatag nito na ang dalawa ay nangyayari nang magkasama nang mas madalas kaysa sa tsamba, hindi na ang os ang sanhi ng punit (tear). Ang plausible mechanism ay gumagana sa dalawang direksyon: ang isang hindi nagsamang fragment ay bahagyang gumagalaw sa ilalim ng hila ng deltoid, na maaaring makairita sa tendon sa ilalim — o ang parehong shoulder mechanics na nagiging sanhi ng cuff disease ang nagiging dahilan upang maging symptomatic ang isang unstable fragment.
Kung ito ba ang pinagmumulan ng sakit ang pangunahing katanungan
Dahil ito ay nakikita, permanente, at mukhang abnormal sa imaging, ang os acromiale ay madaling nagiging iniuulat na paliwanag para sa sakit sa balikat. Karamihan ay walang sintomas, at karamihan sa mga taong mayroon nito ay hindi kailanman nakakaalam.
Ang nagtatangi sa isang symptomatic na os acromiale ay ang localised tenderness direkta sa ibabaw ng fragment, sakit na nararamdaman kapag pinipindot ito, at, kung gumagamit ng diagnostic injection, ginhawa partikular mula sa pag-inject sa junction na iyon sa halip na sa subacromial space sa ilalim. Sa kawalan ng mga ito, ang natuklasan ay pinakamainam na ituring bilang incidental.
Ang mga subtype ay kumbensyonal na kinaklasipika ayon sa kung aling fusion site ang kasangkot [2], na mahalaga sa operasyon dahil ang laki ng mobile fragment ang nagtatakda kung maaari itong excise o kailangang i-fix.
Bakit nito pinapakomplikado ang ibang operasyon sa balikat
Ang praktikal na kahalagahan ng isang os acromiale ay madalas na hindi tungkol sa sarili nitong mga sintomas kundi tungkol sa epekto nito sa mga operasyong nakaplano para sa ibang bagay.
Ang deltoid ay nakakabit sa acromion, kaya ang isang hindi nag-fuse na fragment ay dinadala ang hila na iyon sa isang mobile junction. Ang pagtatanggal ng buto mula sa undersurface, gaya ng sa acromioplasty, ay nagpapanipis sa isang fragment na unstable na, at maaaring gawing masakit ang isang symptomless variant o magdulot ng nonunion. Ito ang pinakamalakas na dahilan upang makilala ito sa pre-operative imaging: hindi upang gamutin ito, kundi upang maiwasang maging destabilized ito.
Kung kinakailangan nito ng gamutan, ang pagpipilian ay sa pagitan ng pag-excise ng isang maliit na fragment at pag-fix ng isang mas malaking fragment, at ang fixation sa junction na ito ay kilalang mahirap, dahil manipis ang fragment, patuloy itong hinahila ng deltoid, at kapansin-pansin ang mga nonunion rate. Ang kahirapang iyon mismo ay isang dahilan upang maging sigurado na ang os ay tunay na pinagmumulan ng sakit bago ito operahan.
Mga Sanggunian
[1] Kozono N, Nishii A, Ishitani E, Mizuki Y, Kimura T, Yamamoto S, et al. Prevalence and factors associated with os acromiale: a multicenter study. JSES Int. 2025;9(5):1541-5. https://doi.org/10.1016/j.jseint.2025.05.015
[2] Boehm TD, Matzer M, Brazda D, Gohlke FE. Os acromiale associated with tear of the rotator cuff treated operatively. Review of 33 patients. J Bone Joint Surg Br. 2003;85(4):545-9. https://doi.org/10.1302/0301-620X.85B4.13634
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A symptomatic, unstable os acromiale is relatively rare despite the radiographic appearance of an os acromiale being not uncommon in patients presenting with shoulder pain [1].
- An os acromiale should always be suspected in cases of failed rotator cuff surgery or ongoing shoulder pain after failed treatment [2].
- The prevalence of os acromiale was 2.13% in Thai patients with shoulder problems who required MRI evaluation [3].
- Os acromiale is associated with rotator cuff injuries [7].
- The greater the distance of the acromioclavicular joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale [15].
- The authors recommend that the acromion be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear [10].
- Surgical treatment is usually not indicated for os acromiale in the professional tennis player [9].
- Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes [4].
- Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments [13].
- Patients with a united os acromiale had a significantly better functional outcome as measured by the Constant score (P = .0169) [12].
- The advantages of arthroscopic internal fixation include improved visualization of the undersurface of the acromion, allowing excellent reduction, the possibility of treating concomitant shoulder pathologies, and to avoid increased morbidity of the open approach [14].
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients [5].
- The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option [6].
- The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale [11].
- Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate [16].
Anatomy & Pathophysiology
Bony Anatomy
- The acromion has three ossification centers: the metacromion (base), the mesoacromion (middle), and the preacromion (tip) [38].
- Failure of fusion of the acromial ossification centers results in os acromiale [38].
- Os acromiale is defined as incomplete fusion of secondary ossification centers, most commonly between the mesoacromion and meta-acromion [49].
- The unfused segment in os acromiale is most commonly the meso-acromion, a configuration often termed a meso-type os acromiale [22].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [35].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [35].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [37].
- The acromion is a flattened bony process that curves forwards from the scapular spine [37].
Prevalence and Associations
- In Thai patients with shoulder problems who required MRI evaluation, the prevalence of os acromiale was 2.13% [3].
- The radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain [1].
- A symptomatic, unstable os acromiale is relatively rare [1].
Pathophysiology
- Most diagnoses of os acromiale are made incidentally on axillary view radiographs of the shoulder [22].
- Primary shoulder pain is usually unrelated to the unfused os acromiale [22].
- When an os acromiale drives symptoms, the two principal causes are motion at the non-union site or an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [22].
- Pain from an os acromiale due to these mechanisms has been reported in a variety of sports, particularly among throwing athletes and swimmers [22].
- Previously stable non-unions can become unstable following an episode of blunt trauma to the region [22].
- The synchondrosis of an os acromiale can be injured following trauma [24].
- Extrinsic impingement occurs when the space available for the rotator cuff is diminished, with examples including acromial fracture or pathologic os acromiale [62].
Epidemiology and Prevalence
- Liberson reviewed 1800 shoulder girdles and identified an incidence of os acromiale of 1.4% [21].
- The lesion was bilateral in 62% of patients in Liberson's review of 1800 shoulder girdles [21].
Associated Pathology and Risk Factors
- The greater the distance of the AC joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale [15].
Diagnostic Considerations
- Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis [19].
- Appropriate radiographic investigation including axillary views is emphasized for the diagnosis of os acromiale injuries [24].
Clinical Presentation
- An os acromiale should always be suspected in cases of failed rotator cuff surgery [2].
- An os acromiale should always be suspected in cases of ongoing shoulder pain after failed treatment [2].
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients [5].
- Postoperative local tenderness at the os acromiale resolves spontaneously over time in the majority of patients [5].
- The lesion was bilateral in 62% of patients in Liberson's review [21].
- The unfused segment is most commonly the meso-acromion [22].
- Any primary shoulder pain is usually unrelated to the unfused os [22].
- If the os acromiale is driving symptoms, one principle cause is motion at the non-union site [22].
- If the os acromiale is driving symptoms, another principle cause is an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [22].
- Pain from an os acromiale by the mechanism of impingement has been reported in a variety of sports [22].
- Pain from an os acromiale by the mechanism of impingement has been reported in particular among throwing athletes and swimmers [22].
- Meta–os acromiale is the rarest subtype of os acromiale [23].
Investigations
Prevalence and Demographics
- Liberson reviewed 1800 shoulder girdles and identified an incidence of os acromiale of 1.4%, with the lesion being bilateral in 62% of patients [21].
- A multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population [8].
- The radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain, but a symptomatic, unstable os acromiale is relatively rare [1].
Radiographic Evaluation
- The acromion should be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear [10].
- Appropriate radiographic investigation for os acromiale includes axillary views [24].
- Awareness of the os acromiale in the young athlete requires appropriate clinical examination and image studies to confirm diagnosis [19].
- The standard shoulder series should include orthogonal views of the shoulder, including a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [60].
- The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs, which have been closely associated with the presence of rotator cuff pathology [60].
- The scapular Y view can also show acromial shape [60].
- At least two X-ray views should be obtained for shoulder imaging: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [52].
- The purpose of imaging of the shoulder is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [30].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder evaluation [30].
- The first key view for shoulder imaging is the anteroposterior (AP) in the plane of the scapula taken so that the x-ray beam passes through the glenohumeral joint [30].
- The second key view for shoulder imaging is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula and oriented so that both the spinoglenoid notch and the scapular neck are visible [30].
- The axillary view is referred to as the "truth view" because it demonstrates the glenohumeral relationships in the functional position of elevation [30].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view [30].
- The temptation to "overimage" should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [30].
Magnetic Resonance Imaging
- In Thai patients with shoulder problems, os acromiale was identified via Magnetic Resonance Imaging evaluation [3].
- MRI is useful to identify labral tears and rotator cuff tears, although the accuracy for these is enhanced by combining the scan with arthrography [52].
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [59].
- T2-weighted MRI provides better visualization of full thickness rotator cuff tears [59].
- MR arthrography is considered the benchmark for evaluation for labral tears and rarely is indicated for evaluation of rotator cuff pathology [59].
- When MRI or MR arthrography is contraindicated, CT arthrography is indicated [59].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [52].
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [59].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [59].
- Ultrasonography can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [59].
- Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [59].
- The most commonly performed joint examination using ultrasonography is the shoulder examination, and accuracy depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [50].
Clinical Associations and Diagnostic Implications
- The synchondrosis of an os acromiale can be injured following trauma, though rarely [24].
Treatment
Non-Operative
- A symptomatic os acromiale in a competitive female fastball pitcher was treated successfully with open reduction and internal fixation [27].
Operative
- Symptomatic unstable os acromiale can be effectively treated with autogenous bone-grafting and internal fixation using a rigid tension-band construct and cannulated screws, which results in a high rate of union [65].
- This new arthroscopic technique of fixation of os acromiale with absorbable screws provides promising clinical, cosmetic, and radiologic results with high patient satisfaction [28].
- After 3 to 6 years of follow-up, all 6 shoulders were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons [18].
- Modified arthroscopic subacromial decompression can provide results similar to standard arthroscopic subacromial decompression for routine impingement [25].
- Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation [23].
Complications
Post-operative and Surgical Complications
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients following reverse total shoulder arthroplasty [5].
Diagnostic and Clinical Implications
Pathophysiology and Mechanisms of Symptom
- Pain from an os acromiale by the mechanism of impingement has been reported in a variety of sports, in particular among throwing athletes and swimmers [22].
Recovery
- After 3 to 6 years of follow-up, all 6 shoulders treated with osteosynthesis of an unstable mesoacromion were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons [18].
- At a two to five year follow-up, all patients treated for fusion of the unstable mesoacromion had fused [69].
Key Evidence
- [L4] While the radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain, a symptomatic, unstable os acromiale is relatively rare. [1] (10.1097/00132589-200412000-00006)
- [L4] An os acromiale should always be suspected in cases of failed rotator cuff surgery or ongoing shoulder pain after failed treatment. [2] (10.1097/00132589-200609000-00006)
- [L3] In Thai patients with shoulder problems who required MRI evaluation, the prevalence of os acromiale was 2.13%. [3] (10.1177/23259671221078806)
- [L4] Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes. [4] (10.1016/j.jse.2019.05.047)
- [L3] Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients. [5] (10.1177/2325967120965131)
- [L4] The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option. [6] (10.1016/j.xrrt.2025.01.002)
- [L3] The study supports previous findings that os acromiale is associated with rotator cuff injuries. [7] (10.1016/j.jseint.2025.05.015)
- [L3] This multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population. [8] (10.1016/j.jse.2025.01.008)
- [L4] Surgical treatment is usually not indicated for os acromiale in the professional tennis player. [9] (10.1177/2325967118773723)
- [L4] The authors recommend that the acromion be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear. [10] (10.2106/00004623-198466080-00029)
- [L4] The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale. [11] (10.1016/j.jse.2017.02.012)
- [L4] Patients with a united os acromiale had a significantly better functional outcome as measured by the Constant score (P = .0169). [12] (10.1016/s1058-2746(98)90008-8)
- [L5] Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments. [13] (10.5435/jaaos-d-17-00011)
- [L5] The advantages of this technique are improved visualization of the undersurface of the acromion, allowing excellent reduction, the possibility of treating concomitant shoulder pathologies, and to avoid increased morbidity of the open approach. [14] (10.1097/bte.0000000000000191)
- [L4] Our data suggest that the greater the distance of the AC joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale. [15] (10.1067/mse.2003.128136)
- [L4] Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate. [16] (10.1186/s12891-021-04841-1)
- [L4] After 3 to 6 years of follow-up, all 6 shoulders were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons. [18] (10.1016/s1058-2746(99)90004-6)
- [L4] Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis. [19] (10.1016/j.jseint.2020.02.008)
- [L4] [22] (10.1302/2058-5241.4.180100)
- [L4] Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation. [23] (10.1177/03635465211028238)
- [L4] This case highlights that the synchondrosis of an os acromiale can be injured following trauma, though rarely, and emphasizes the need for appropriate radiographic investigation including axillary views and a flexible surgical approach. [24] (10.1016/j.jse.2008.02.012)
- [L5] Increased awareness of the diagnosis and improved techniques have shown that modified arthroscopic subacromial decompression can provide results similar to standard arthroscopic subacromial decompression for routine impingement. [25] (10.1097/00132589-200206000-00003)
- [L4] A symptomatic os acromiale in a competitive female fastball pitcher was treated successfully with open reduction and internal fixation. [27] (10.1177/0363546506288305)
- [L4] This new arthroscopic technique of fixation of os acromiale with absorbable screws provides promising clinical, cosmetic, and radiologic results with high patient satisfaction. [28] (10.1016/j.jse.2011.12.011)
- [L4] Symptomatic unstable os acromiale can be effectively treated with autogenous bone-grafting and internal fixation using a rigid tension-band construct and cannulated screws, which results in a high rate of union. [65] (10.2106/00004623-199809000-00011)
- [L4] At a two to five year followup all had fused. [69] (10.1016/s1058-2746(95)80192-8)
References
[1] Treatment of the Symptomatic Os Acromiale. Techniques in Shoulder and Elbow Surgery. 2004. DOI: 10.1097/00132589-200412000-00006
[2] Management of Os Acromiale. Techniques in Shoulder and Elbow Surgery. 2006. DOI: 10.1097/00132589-200609000-00006
[3] Prevalence of Os Acromiale in Thai Patients With Shoulder Problems: A Magnetic Resonance Imaging Study. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671221078806
[4] Os acromiale: systematic review of surgical outcomes. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.05.047
[5] Os Acromiale in Reverse Total Shoulder Arthroplasty: A Cohort Study. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120965131
[6] Clinical implications of reverse total shoulder arthroplasty with an os acromiale: a systematic review. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.01.002
[7] Prevalence and factors associated with os acromiale: a multicenter study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.05.015
[8] The prevalence and associated factors of os acromiale: a multicenter study. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.01.008
[9] Os Acromiale in Professional Tennis Players. Orthopaedic Journal of Sports Medicine. 2018. DOI: 10.1177/2325967118773723
[10] Rotator cuff tears associated with os acromiale.. The Journal of Bone & Joint Surgery. 1984. DOI: 10.2106/00004623-198466080-00029
[11] Reverse shoulder arthroplasty in patients with os acromiale. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.02.012
[12] Transacromial approach to obtain fusion of unstable os acromiale. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90008-8
[13] Symptomatic, Unstable Os Acromiale. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-17-00011
[14] Arthroscopic Internal Fixation of Symptomatic Os Acromiale. Techniques in Shoulder & Elbow Surgery. 2020. DOI: 10.1097/bte.0000000000000191
[15] Relationship between os acromiale and acromioclavicular joint anatomic position. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1067/mse.2003.128136
[16] Os acromiale may be a contraindication of the clavicle hook plate: case reports and literature review. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04841-1
[18] Successful osteosynthesis of an unstable mesoacromion in 6 shoulders: A new technique. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90004-6
[19] The unstable os acromiale: a cause of pain in the young athlete. JSES International. 2020. DOI: 10.1016/j.jseint.2020.02.008
[21] Types of os acromiale according to Liberson. 2006.
[22] Os acromiale: a review of its incidence, pathophysiology, and clinical management. EFORT Open Reviews. 2019. DOI: 10.1302/2058-5241.4.180100
[23] Rare Symptomatic Meta–Os Acromiale in an Athlete. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211028238
[24] Fracture of an os acromiale with associated rupture of the coracoclavicular ligaments. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2008.02.012
[25] Arthroscopic Management of the Mesoacromion. Techniques in Shoulder and Elbow Surgery. 2002. DOI: 10.1097/00132589-200206000-00003
[27] Surgical Stabilization of Os Acromiale in a Fast-Pitch Softball Pitcher. The American Journal of Sports Medicine. 2006. DOI: 10.1177/0363546506288305
[28] Arthroscopically assisted internal fixation of the symptomatic unstable os acromiale with absorbable screws. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2011.12.011
[30] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[35] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[37] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[38] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[49] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[50] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[52] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[59] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[60] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[62] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > Developmental Stages of Impingement Syndrome.
[65] The Treatment of Symptomatic Os Acromiale. The Journal of Bone & Joint Surgery*. 1998. DOI: 10.2106/00004623-199809000-00011
[69] Successful fusion of the unstable mesoacromion: Technique and report of five cases. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80192-8