Patients › Rehabilitation
Trigger Finger Release
Post-operative exercises and precautions after trigger finger release, including tendon glides and joint blocking exercises.
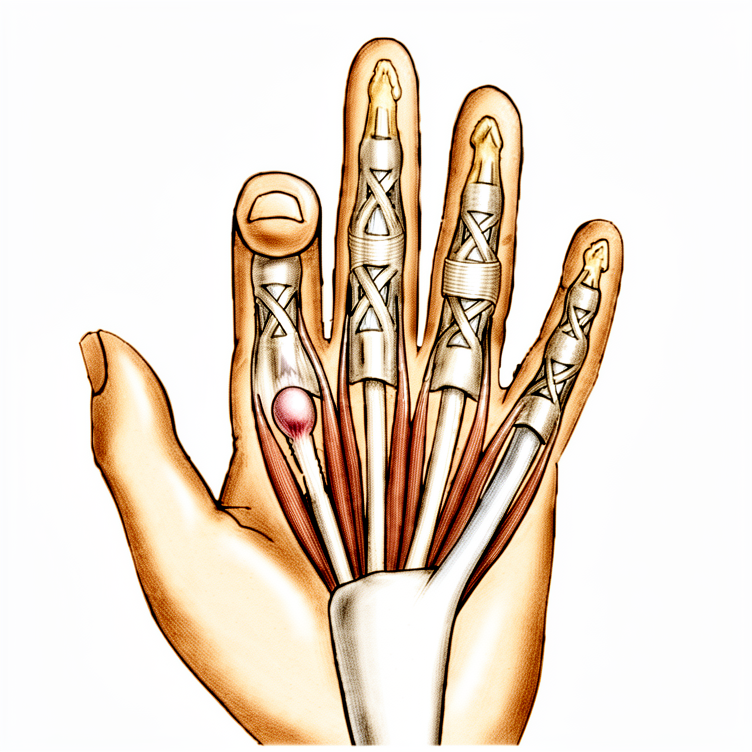
Ang protocol na ito ay nagsisilbing gabay sa iyong paggaling pagkatapos ng trigger finger release kasama si Dr Kieran Hirpara sa Mater Private Hospital Rockhampton. Ipinapaliwanag nito ang mga dapat asahan, ang mga pag-iingat na dapat sundin, at ang post-operative exercise program: dalhin ang pahinang ito o ang PDF nito sa iyong physiotherapist o hand therapist upang manatiling coordinated ang iyong rehabilitasyon.
Kung mayroon kang anumang alalahanin tungkol sa iyong sugat pagkatapos ng operasyon, makipag-ugnayan sa mga rooms. Madalas na nakatutulong ang pagkuha ng larawan ng sugat at pag-email nito para masuri.
Ano ang dapat asahan
Ang pag-aalaga sa iyong sugat ay ipinaliwanag nang hiwalay: tingnan ang pahina ng pag-aalaga sa sugat na naka-link sa dulo ng protocol na ito.
Ang mga ehersisyo sa ibaba ay napakahalaga upang maiwasan ang pagdidikit ng iyong mga tendon habang gumagaling ang iyong sugat. Kung minsan, ang mga joint sa iyong mga daliri ay maaaring tumigas pagkatapos ng procedure na ito. Mahalaga ang maagang pag-iwas sa paninigas na ito, kaya hinihikayat kang maglapat ng matatag at matagal na stretching sa iyong daliri (gamit ang iyong kabilang kamay), lalo na sa pagtutuwid. Ang anyong ito ng passive stretching ay ligtas at hindi makakaapekto sa operasyon: ang pulley ay nailabas na, kaya wala nang anumang bagay sa loob na maaaring maabala ng stretching.
Kapag magaling na ang iyong sugat, maglagay ng init sa iyong kamay sa loob ng 20 minuto bago gawin ang mga ehersisyong ito. Pagkatapos kumpletuhin ang mga ehersisyo, ang paglalagay ng yelo ay maaaring makatulong upang maiwasan ang pamamaga.
Minsan, ang kamay o sugat ay maaaring maging sensitibo. Normal ito, at maaaring maiwasan o mabawasan sa pamamagitan ng pagsisimula ng araw-araw na desensitisation: dahan-dahang pagtapik o paghaplos sa ibabaw ng sugat (habang may dressing), simula agad pagkatapos ng iyong operasyon. Ang uri ng "sensory feedback" na ito ay nagpapahintulot sa balat na maibalik sa normal ang pakiramdam sa paghipo at texture.
Sa unang 48 oras, sikaping mapababa ang pamamaga: panatilihing nakataas ang kamay, gumamit ng yelo, maglagay ng compression kung ibinigay ito ng iyong therapist, at dahan-dahang i-"pump" ang mga daliri (ibukas at isara) upang maigalaw ang pamamaga.
Simulang gamitin ang kamay para sa mga magagaan na gawain (pagbibihis, pagkain at mga katulad nito) sa oras na payagan na ng sakit, at unti-unting dagdagan. Huwag sobrahan: kung ang iyong sakit o pamamaga ay malinaw na tumitindi pagkatapos ng isang aktibidad, bawasan muna hanggang sa kumalma ang kamay, pagkatapos ay unti-unting dagdagan muli.
Kapag ganap nang magaling ang sugat, simulan ang scar massage: matatag na pabilog na masahe sa ibabaw ng incision. Ang pahina ng pag-aalaga sa sugat ay may higit pang impormasyon tungkol sa pamamahala ng peklat.
Ano ang sinasabi ng ebidensya tungkol sa recovery
Ang open release ng A1 pulley ay isang well-established na operasyon na may matibay na track record sa mga nailathalang literatura. Ang catching at locking ay naitatama ng mismong surgery: kapag nahati na ang pulley, muling malayang nakaka-glide ang tendon, at ang triggering ay karaniwang hindi na bumabalik. Sa isang serye ng halos 1,600 open releases, mas mababa sa 1% ng mga pasyente ang nangailangan ng pangalawang operasyon para sa persistent o recurrent triggering, at walang mga nerve injury o deep infection [4]. Isang comparative study na may higit sa tatlong taon ng follow-up ay gayundin na nakakita ng walang recurrences pagkatapos ng open release [5].
Ang pananakit sa palad ay nababawasan nang malaki sa loob ng unang isa hanggang dalawang linggo. Sa isang comparative study, ang median time para sa makabuluhang pagbaba ng sakit pagkatapos ng open release ay humigit-kumulang isang linggo [5]. Ang ilang tenderness sa palad kapag mahigpit ang pagkakahawak, mild swelling o paninigas ng daliri ay maaaring manatili ng ilang linggo pagkatapos nito. Ito ay normal at repleksyon ng pag-mature ng scar, na tumatagal ng humigit-kumulang tatlong buwan [3]; ang desensitisation, scar massage at exercise program sa protocol na ito ay idinisenyo upang pamahalaan mismo ito. Sa malaking serye sa itaas, humigit-kumulang isa sa bawat dalawampung daliri ang may dokumentadong problema pagkatapos ng surgery, na pinakakaraniwan ay temporary stiffness o scar tenderness na nawala sa pamamagitan ng treatment; ang recovery ng motion ay may tendensiyang maging mas mabagal sa mga taong may diabetes, kaya ang exercise program ay mas mahalaga pa sa grupong iyon [4].
Ang mga nailathalang hand-therapy protocol ay nagsisimula ng active at passive finger motion at tendon-glide exercises sa loob ng mga unang araw pagkatapos ng surgery, nagdaragdag ng scar management at desensitisation kapag gumaling na ang sugat, at muling nagpapakilala ng graded grip strengthening kalaunan [2][3], ang parehong staged approach gaya ng program sa pahinang ito. Ang maagang pagsisimula ng mga ehersisyo ang nagpapanatili sa pag-glide ng tendon at pagiging supple ng mga joint habang gumagaling ang sugat.
Ang pagbabalik sa trabaho ay depende sa kung ano ang hinihingi ng iyong trabaho sa kamay. Sa isang comparative study, kalahati ng mga pasyente ay nakabalik na sa trabaho sa loob ng humigit-kumulang dalawang linggo pagkatapos ng open release [5]; ang mga tao sa mas magaan o desk-based na mga role ay madalas na nakakabalik nang mas maaga, habang ang mas mabigat na manual work ay naghihintay hanggang sa maalis ang lifting at gripping restriction sa ibaba.
Isang randomised controlled trial ang naghambing ng tatlong buwan ng supervised therapy pagkatapos ng open release sa isang self-directed home exercise program: ang overall function, motion at pain ay magkakatulad sa pagitan ng mga grupo sa loob ng anim na buwan, ang grip strength ay mas nakarekober pa sa supervised therapy, at ang mga pasyenteng malinaw na nakinabang mula sa formal therapy ay yaong mga ang triggering ay naroon na nang higit sa labindalawang buwan bago ang surgery at yaong mga gumagawa ng housework o mas magaan na trabaho [1]. Sa praktikal na mga termino, ang isang maayos na naisagawang home program (ang mga ehersisyo sa pahinang ito) ay sapat na para sa karamihan ng mga pasyente, kung saan ang formal hand therapy ay nagdaragdag ng halaga kung ang daliri ay matagal nang matigas bago ang surgery o mabagal ang progreso.
Mga pag-iingat at limitasyon
Hinihikayat ang magaan na functional na paggamit ng iyong kamay para sa mga gawaing pang-araw-araw tulad ng pag-aalaga sa sarili, pagkain, pagbibihis, pagsusulat at pag-type. Ang mga limitasyong mahalaga:
- Iwasan ang pagbuhat, paghawak nang mahigpit (gripping) at pagdadala ng bigat (weight bearing) hanggang 4 na linggo pagkatapos ng operasyon.
- Limitado ang pagmamaneho sa unang linggo; ituloy kapag pinahintulutan na ng sakit, kapag kaya nang itikom nang buo ang kamao, at kapag ligtas mo nang makokontrol ang sasakyan.
Para sa iyong physiotherapist:
Pamamahala
- Home exercise program ayon sa mga card sa ibaba: wrist flexion/extension stretch; DIP (distal interphalangeal) at PIP (proximal interphalangeal) joint blocking; tendon glides (Series A at Series B)
- Matitigas at matagal na passive stretches sa daliri, lalo na sa extension, para sa maagang pag-iwas sa paninigas ng joint
- Heat sa kamay sa loob ng 20 minuto bago ang mga ehersisyo kapag magaling na ang sugat; ice pagkatapos ng mga ehersisyo upang maiwasan ang pamamaga (inflammation)
- Araw-araw na desensitisation (magaang pagtapik / paghaplos sa ibabaw ng sugat, habang may dressing) na magsisimula agad pagkatapos ng operasyon
- Pamamahala ng pamamaga sa unang 48 oras: elevation, ice, compression kung kinakailangan, magaan na finger pumps
- Gradual na pagbabalik sa magaan na functional na paggamit habang pinahihintulutan ng sakit, pagsubaybay sa mga flare-up ng sakit/pamamaga pagkatapos ng aktibidad
- Scar massage (matitigas na pabilog na masahe sa ibabaw ng incision) kapag ganap nang magaling ang sugat
Mga Pag-iingat
- Magaan na functional na paggamit lamang para sa mga gawaing pang-araw-araw (pag-aalaga sa sarili, pagkain, pagbibihis, pagsusulat, pag-type)
- Walang pagbuhat, paghawak nang mahigpit o pagdadala ng bigat hanggang 4 na linggo pagkatapos ng operasyon
- Limitado ang pagmamaneho sa unang linggo; ituloy kapag pinahintulutan ng sakit, nakakamit na ang buong kamao at ligtas nang makokontrol ng pasyente ang sasakyan
Inaasahang milestones (batay sa criteria, ginagabayan ng mga nailathalang protocol [1][2][3])
- Ang sakit ay bumaba sa komportableng antas gamit ang simpleng analgesia sa loob ng 1–2 linggo [5]
- Sugat ay magaling na, kasama ang scar massage at patuloy na desensitisation, sa loob ng 2–3 linggo [2][3]
- Buong active finger flexion at extension (buong kamao at buong composite extension) sa loob ng humigit-kumulang 3 linggo, na naibalik at napanatili sa pamamagitan ng blocking at tendon-glide program [2]
- Gradual na pagpapalakas ng grip at pinch (hal. putty) na ipapakilala kapag natapos na ang 4-na linggong pag-iingat sa pagbuhat/paghawak, patungo sa buong functional na paggamit
- Isaalang-alang ang paglipat sa supervised hand therapy kung ang triggering ay naroon na nang higit sa 12 buwan bago ang operasyon, kung ang mga tungkulin ng pasyente ay kinapapalooban ng patuloy na magaan/pino na paggamit ng kamay, o kung mabagal ang pagbawi ng range of motion o grip [1]
Ito ang mga ehersisyo mula sa iyong handout, na sinimulan pagkatapos ng operasyon at ipinagpapatuloy sa bahay ayon sa gabay ng iyong physiotherapist o hand therapist.
Iyong mga ehersisyo

Kieran Hirpara 4.0
Stretch ng flexion / extension ng pulso
Ipatong ang iyong siko sa mesa (o ang iyong forearm sa gilid ng mesa o arm chair) at dahan-dahang igalaw ang iyong pulso nang pabalik-balik. Kapag mas komportable na, hawakan ang iyong palad gamit ang kabilang kamay at itulak ang pulso pabalik (nakalaylay ang mga daliri, nakaturo sa kisame) — manatili sa posisyong ito nang 15 segundo; pagkatapos ay sa kabilang direksyon (nakalaylay ang mga daliri, nakaturo sa sahig) — manatili sa posisyong ito nang 15 segundo. Ulitin nang 5 beses sa bawat direksyon.
10 reps, 4–5 beses araw-araw
Kieran Hirpara 4.0
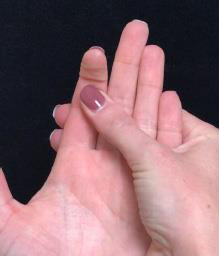
DIP joint blocking
Ang DIP (distal interphalangeal) joint ay ang dulo na kasukasuan ng iyong daliri. Magsimula nang nakaharap sa itaas ang palad, habang sinusuportahan ang apektadong kamay gamit ang iyong kabilang kamay sa bahagi na nasa ibaba lamang ng dulo na kasukasuan. Itiklop at ituwid ang dulo na kasukasuan, panatilihin ang bawat posisyon sa loob ng 3–5 segundo. Suportahan ang gitnang kasukasuan nang sapat lamang upang hindi ito matiklop. Ayos lang kung gumagalaw ang ibang mga daliri habang ginagawa ang ehersisyong ito.
10 reps, 4 beses sa isang araw, araw-araw
Kieran Hirpara 4.0
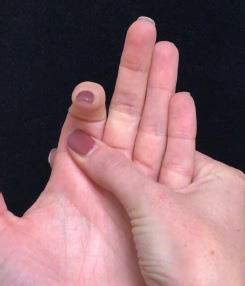
pag-block sa PIP joint
Ang PIP (proximal interphalangeal) joint ay ang gitnang kasukasuan ng iyong daliri. Magsimula nang nakaharap sa itaas ang palad, habang sinusuportahan ang apektadong kamay gamit ang iyong kabilang kamay sa bahagi na nasa ibaba lamang ng ikalawang kasukasuan. Itiklop at ituwid ang iyong daliri sa gitnang kasukasuan, panatilihin ang bawat posisyon sa loob ng 3–5 segundo. Ayos lang kung gumagalaw din ang ibang mga daliri.
10 reps, 4 beses sa isang araw, araw-araw
Kieran Hirpara 4.0
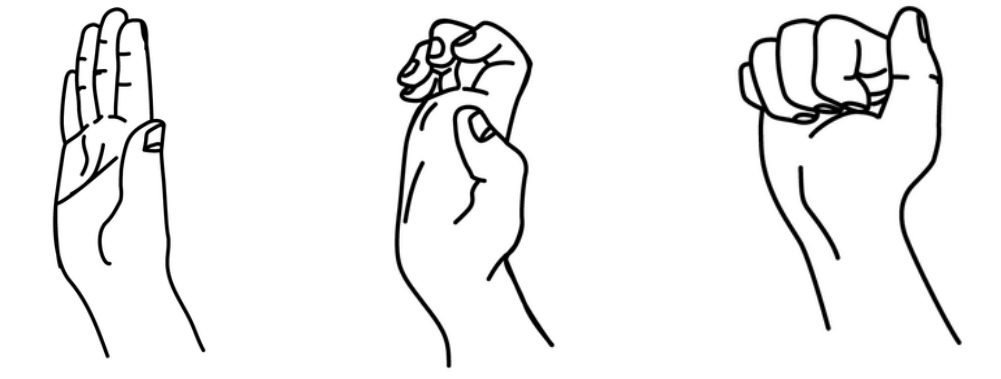
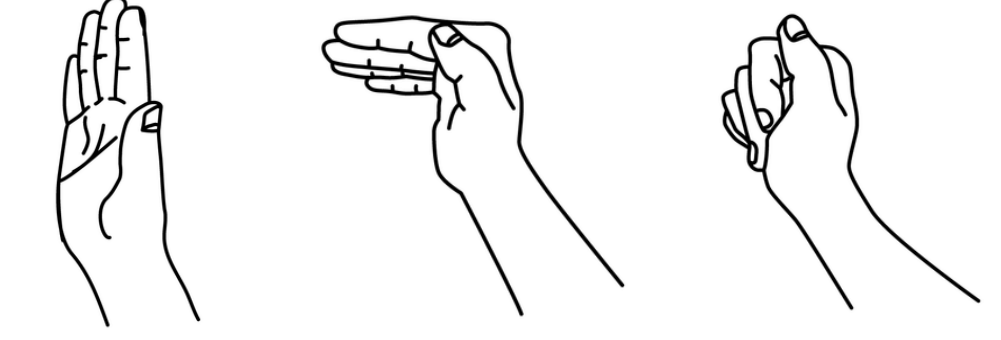
Tendon glides — Series A
Habang ang iyong kamay ay nasa harap mo at ang iyong pulso ay diretso, i-unat nang husto ang lahat ng iyong mga daliri — maaari mong gamitin ang iyong kabilang kamay upang matiyak na ang mga daliri ay nakamit ang full extension (posisyon 1). I-bend ang mga dulo ng iyong mga daliri sa "hook" na posisyon habang ang iyong mga knuckles ay nakaturo pataas (posisyon 2). Pagkatapos ay gumawa ng mahigpit na kamao na ang iyong hinlalaki ay nasa ibabaw ng iyong mga daliri (posisyon 3).
5–10 reps, 2–3 beses sa isang araw, araw-araw
Kieran Hirpara 4.0
Tendon glides — Series B
Habang ang iyong kamay ay nasa harap mo at ang iyong pulso ay diretso, ituwid nang husto ang lahat ng iyong mga daliri — maaari mong gamitin ang iyong kabilang kamay upang matiyak na ang mga daliri ay nakakamit ang full extension (posisyon 1). Gumawa ng "tabletop" gamit ang iyong mga daliri sa pamamagitan ng pagbaluktot sa iyong bottom knuckle at panatilihing diretso ang mga daliri — tiyaking hindi bumabagsak ang iyong pulso paharap (posisyon 2). Pagkatapos ay ibaluktot ang iyong mga daliri sa middle joint, at idikit ang iyong mga daliri sa iyong palad (posisyon 3).
5–10 reps, 2–3 beses sa isang araw, araw-araw
Kieran Hirpara 4.0
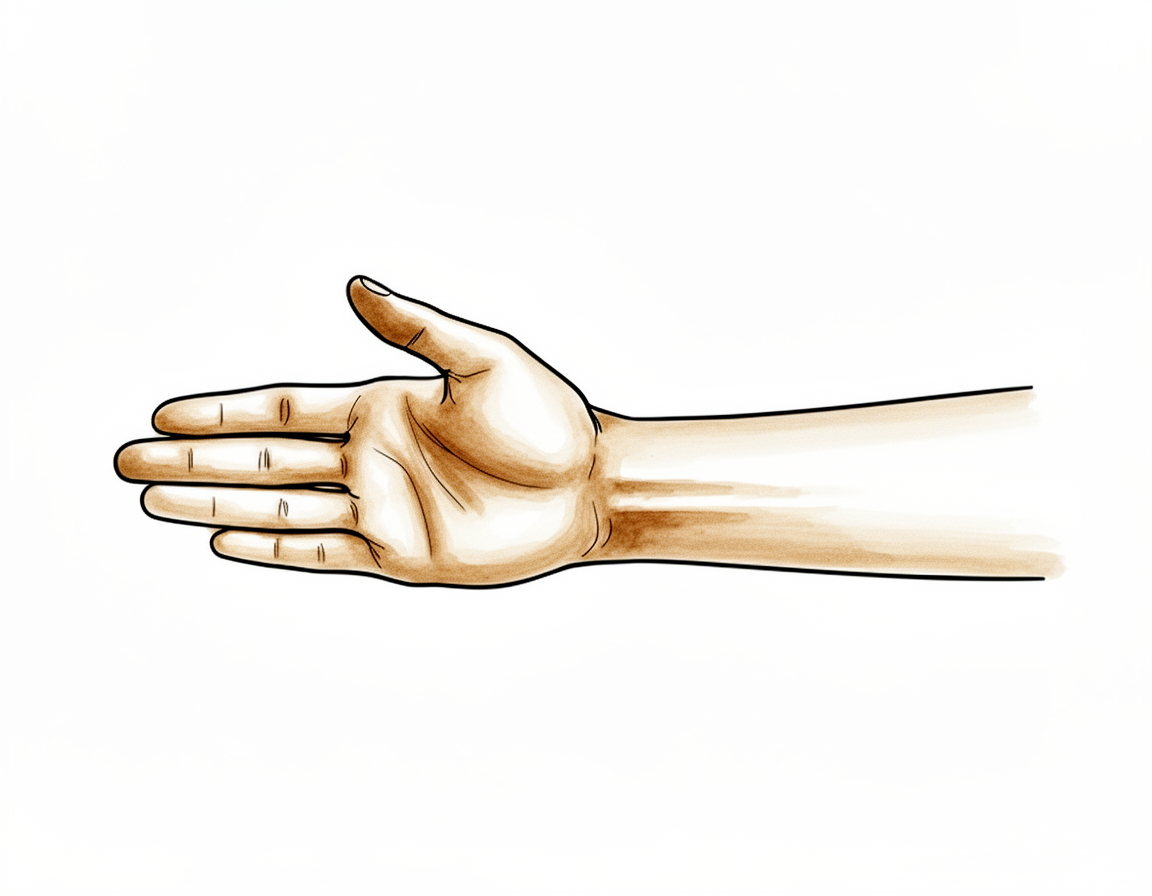
Aktibong composite extension
Ipatong ang iyong siko sa mesa, ituwid ang iyong mga daliri hangga't maaari, pagkatapos ay itulak pa nang kaunti gamit ang iyong kabilang kamay. Magbilang hanggang 5, at i-relax.
10 reps, 3–4 beses araw-araw
Kieran Hirpara 4.0
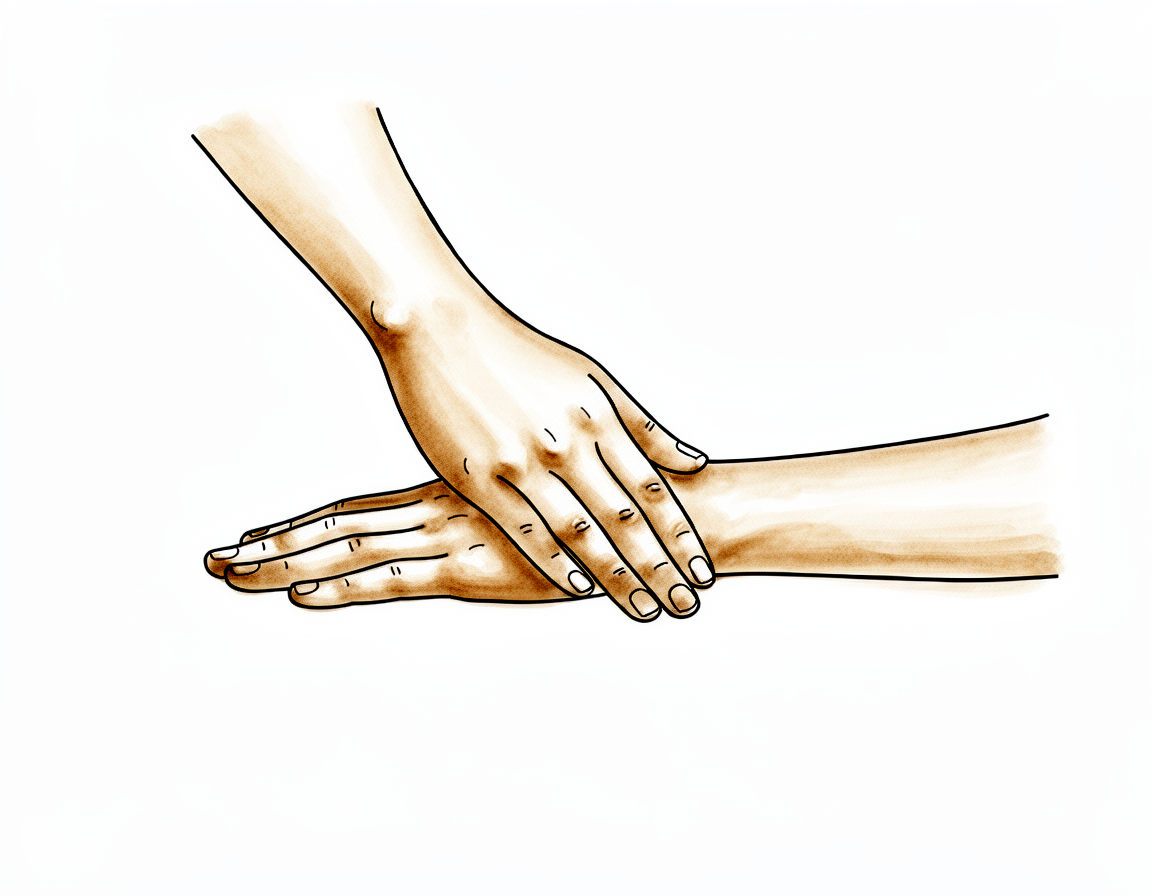
Pasibong composite extension
Ipatong nang patag ang iyong kamay sa mesa, nakasubsob ang palad. Gamit ang iyong kabilang kamay, maglagay ng presyon sa likod ng kamay at 'i-massage' ito patungo sa iyong katawan. Magbilang hanggang 5, at mag-relax.
10 reps, 3–4 beses araw-araw
Kieran Hirpara 4.0
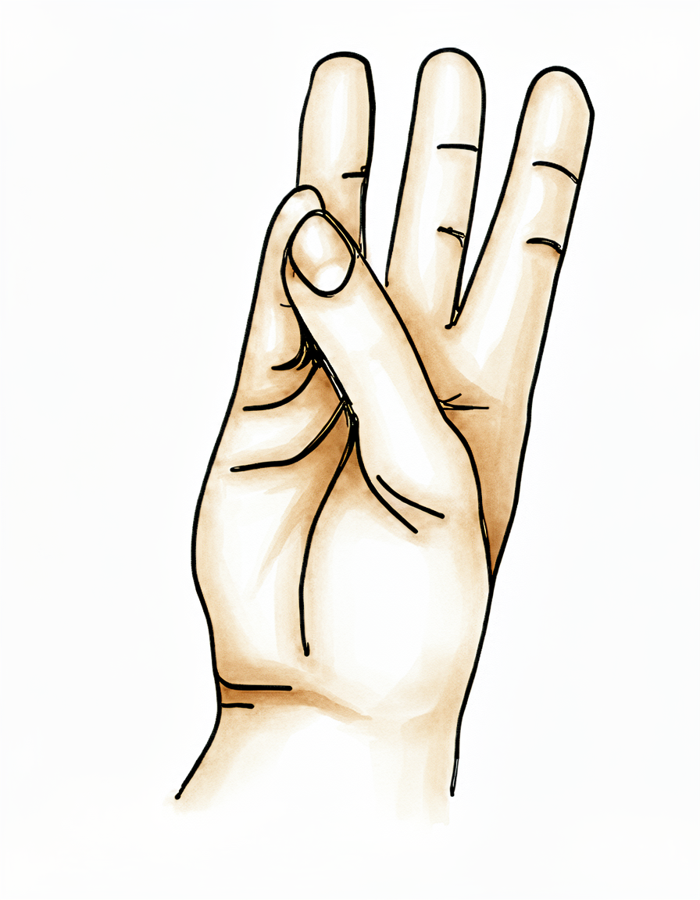
Opposisyon ng hinlalaki
Magsimula nang diretso at relax ang mga daliri. Idikit ang dulo ng iyong hinlalaki sa dulo ng iyong hintuturo. Panatilihin ito sa loob ng 5 segundo, pagkatapos ay bumalik sa simula.
10 reps, 3–4 beses araw-araw
Simulan lamang ang mga ehersisyo sa ibaba ayon sa gabay ni Dr Hirpara at ng iyong hand therapist, at manatili sa anumang range at limitasyong ibinigay sa iyo. Ang tendon-glide series at ang mga blocking exercise ay pinapanatiling malayang gumagalaw ang inoperahang tendon sa loob ng sheath upang hindi ito dumikit sa naghihilom na peklat — ito ang pumipigil upang hindi bumalik ang triggering bilang paninigas. Ang active at passive composite extension ay pinapanatiling tuwid nang lubos ang daliri, ang thumb opposition ay muling bumubuo sa pinch, at ang wrist stretch ay pumipigil sa paninigas ng pulso habang nakatuon ang pansin sa daliri. Inaasahan ang pananakit nang direkta sa ibabaw ng peklat sa palad sa loob ng ilang linggo. Itigil ang anumang nagdudulot ng matalas na sakit.
Pagkatapos ng iyong protocol
Ang protocol na ito ay isinulat sa pakikipagtulungan kay Sarah Farrell, BOccThy (Bachelor of Occupational Therapy), Accredited Hand Therapist, at nagsasama ng updated na gabay sa post-surgical management (Abril 2025) mula kay Ruby Doolan, Accredited Hand Therapist, Extend Rehabilitation. Gumagana ito kasabay ng pangkalahatang payo sa paggaling ng klinika: tingnan ang pamamahala ng post-operative pain, pag-aalaga ng sugat at mga pangunahing kaalaman sa hand therapy. Para sa operasyon mismo, tingnan ang trigger finger release.
Ang pag-frame ng paggaling at mga milestone ay karagdagan ding ibinatay sa mga nailathalang trigger finger release rehabilitation protocol, kabilang ang sa University of Virginia Hand Center at Twin Cities Orthopedics, at sa mga nailathalang outcome study ng open trigger finger release, kabilang ang isang randomised controlled trial ng post-operative rehabilitation (Saito et al., Journal of Clinical Medicine, 2023) at isang malaking adverse-event series (Bruijnzeel et al., Journal of Hand Surgery, 2012).
Mga Sanggunian
[1] Saito T, Nakamichi R, Nakahara R, Nishida K, Ozaki T. The effectiveness of rehabilitation after open surgical release for trigger finger: a prospective, randomized, controlled study. J Clin Med. 2023;12(22):7187. https://pmc.ncbi.nlm.nih.gov/articles/PMC10671987/ [2] University of Virginia Hand Center. Trigger Finger Release Guidelines (post-operative therapy protocol). https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2015/11/Triggerfingerreleaseprotocol.pdf [3] Meletiou SD, Twin Cities Orthopedics. Post-operative Management of Trigger Release (A1 pulley release). https://tcomn.com/wp-content/uploads/2017/10/Trigger-Release-A1.pdf [4] Bruijnzeel H, Neuhaus V, Fostvedt S, Jupiter JB, Mudgal CS, Ring DC. Adverse events of open A1 pulley release for idiopathic trigger finger. J Hand Surg Am. 2012;37(8):1650–1656. https://pubmed.ncbi.nlm.nih.gov/22763058/ [5] Chanthanapodi P, Aodsup S. Comparative results of percutaneous and open surgery for trigger fingers: a propensity score analysis. Front Surg. 2025;12:1509292. https://pmc.ncbi.nlm.nih.gov/articles/PMC11922895/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Trigger Finger Release (A1 Pulley Release) — Surgical Outcomes & Post-operative Rehabilitation
Topic scope: (A) the place of surgery in stenosing tenosynovitis (trigger finger/thumb) after failed conservative care (splinting, corticosteroid injection), and (B) post-operative rehabilitation after surgical division of the A1 pulley — open or percutaneous. This is an early-motion pathway: nothing is reconstructed, the catching is mechanically abolished the moment the pulley is divided, and the rehab exists to keep the now-free tendon gliding and the finger joints supple while the wound heals.
Defining principle of the rehab here: A1 pulley release removes the obstruction; it does not create a construct that needs protecting. Once the pulley is divided the flexor tendon glides freely and triggering does not usually recur. So — unlike a tendon repair, and like a carpal-tunnel decompression — the pathway is immediate active motion: full active finger flexion/extension and tendon glides from the first days, oedema and scar care, early light functional use, and a quick return. Most patients need no formal hand therapy at all; supervised therapy is reserved for the minority with pre-existing joint stiffness, long-standing triggering, or slow recovery. The single branch point is whether the finger was already stiff before surgery (long-standing fixed flexion / PIP contracture) — those patients need active therapy to recover motion the release alone cannot restore.
A. WHERE SURGERY SITS IN THE PATHWAY
Trigger finger is usually managed non-operatively first: activity modification, splinting, and corticosteroid injection, which resolves a substantial proportion of digits without surgery. Surgery (A1 pulley release) is reserved for digits that fail injection, recur, or present with a fixed deformity. The corpus contains the comparative evidence underpinning this stepped approach (percutaneous release vs steroid injection; one- vs two-injection regimens; corticosteroid solution choice) — Moderate (RCT). The rehab protocol on the patient page begins after that decision has been made, so this brief concentrates on the surgical and post-surgical evidence.
B. SURGICAL OUTCOMES & RESOLUTION RATES
Open release of the A1 pulley is one of the most reliable operations in hand surgery. The mechanical problem — a thickened tendon catching under a tight pulley — is solved by dividing the pulley, and the result is durable:
- In a series of 1,598 open releases, fewer than 1% required a second operation for persistent or recurrent triggering, with no nerve injuries and no deep infections [Bruijnzeel 2012]. About one digit in twenty had a documented post-operative problem, almost all minor and self-limiting (transient stiffness, scar tenderness). Strong (large cohort).
- Recovery of motion is slower in patients with diabetes, reinforcing the value of the exercise program in that group [Bruijnzeel 2012]. Moderate.
- A propensity-matched comparison with >3 years follow-up found no recurrences after open release, with median time to significant pain reduction of about one week and roughly half of patients back at work within ~2 weeks [Chanthanapodi 2025]. Moderate.
Take-home for rehab: because the operation itself abolishes the triggering, the rehabilitation is not "earning back" a surgical result — it is preventing the two things that can go wrong during healing: tendon adhesion and joint stiffness. Early glide and early extension are the levers.
C. OPEN vs PERCUTANEOUS RELEASE
Both techniques divide the same structure and converge to the same place.
- A Level I meta-analysis of 8 RCTs (548 patients) found no significant difference between open and percutaneous release in revision, complication, or pain rates — both are appropriate options [Casey 2024, J Hand Surg Am]. Strong (meta-analysis of RCTs).
- Larger RCT syntheses show percutaneous release confers faster early functional recovery — better short/mid-term Q-DASH, ~12 days earlier return to work, and shorter analgesic use — while long-term function, grip, motion and complication/revision rates are equivalent. Strong.
- Percutaneous (including ultrasound-guided/sonographically-controlled) technique is supported by multiple corpus series for efficacy and safety, with the main theoretical risks being incomplete release and digital nerve proximity, mitigated by surface landmarks and imaging [corpus percutaneous series]. Moderate.
Rehab implication: the post-operative program is essentially the same for both approaches — early active motion, glides, oedema and scar care. The patient page applies regardless of whether the release was open or percutaneous; percutaneous patients simply tend to be comfortable and back to activity a little sooner.
D. THE ROLE — AND LIMITS — OF POST-OPERATIVE HAND THERAPY
This is the central evidence point for the protocol, and it is one where "more therapy" is not automatically better.
- A prospective RCT compared 3 months of supervised rehabilitation after open
release against a self-directed home exercise program: at six months,
overall function, motion and pain were similar between groups. Supervised
therapy added further grip-strength recovery, and the patients who clearly
benefited from formal therapy were those whose **triggering had been present
12 months pre-operatively and those in housework/lighter-work roles [Saito 2023, J Clin Med]. Moderate (single RCT).
- Published surgeon and hand-therapy protocols (e.g. University of Virginia Hand Center; Twin Cities Orthopedics) start active and passive finger motion and tendon glides within the first days, add scar massage and desensitisation once the wound is healed, and reintroduce graded grip strengthening later — precisely the staged structure of the patient page. Consensus.
Bottom line: a well-performed home program carries most patients through. Formal hand therapy is reserved, not routine — escalate it for long-standing pre-operative triggering, pre-existing joint stiffness/contracture, manual or fine-use occupational demands, or slow motion/grip recovery.
E. COMPLICATIONS
Serious complications are uncommon (roughly <1–4% across series) and most "complications" are minor, self-limiting healing phenomena:
- Digital nerve injury — the most feared complication, particularly relevant to percutaneous technique (blind division near the radial digital nerve of the thumb and index) and to scar/retraction in open release. Rare in experienced hands; transient paraesthesia is more common than true division [corpus complication series]. Moderate.
- Incomplete release / persistent triggering — failure to fully divide the A1 pulley (or an A2/FDS slip contribution); a recognised cause of revision, more often discussed with percutaneous technique. Moderate.
- Recurrent triggering — uncommon after adequate open release (<1% reoperation in the 1,598-digit series) [Bruijnzeel 2012]. Strong.
- Infection — usually superficial; deep infection rare (none in the large open series) [Bruijnzeel 2012]. Strong.
- Bowstringing — a rare complication from excessive proximal pulley loss (A1 plus encroachment on A2); largely avoided by limiting division to A1 [bowstringing case literature]. Weak (case-level).
- Stiffness / flexion contracture / "flare" — the commonest self-limiting problem; transient PIP stiffness, scar tenderness and a post-operative inflammatory flare that settle with the motion, desensitisation and scar program. Recovery is slower in diabetes. Moderate. This is the category the rehabilitation program actively targets.
F. PHASED POST-OP TIMELINE (matches the patient protocol)
| Phase | Window | Protection | Motion / use | Therapy add-ons | Notes |
|---|---|---|---|---|---|
| I — Immediate active motion & oedema control | Day 0–2 | None beyond dressing | Active finger flexion/extension and finger "pumps" from day 1; tendon glides commenced | Elevation, ice, compression if provided; desensitisation (tap/rub over dressed wound) from day 1 | Nothing reconstructed -> motion is the priority; manage swelling actively |
| II — Glide & joint motion | Week 0–2 | None | Tendon glides (Series A/B), DIP & PIP blocking, composite extension; firm passive stretch into extension | Continue desensitisation | Goal: keep tendon gliding, prevent adhesion & stiffness; pain settles substantially (~1 wk) [Chanthanapodi 2025] |
| III — Scar maturation & function | Week 2–4 | Light functional use only | Full active fist + full composite extension by ~3 wk; build light daily-living use | Scar massage (firm circles) once wound healed; heat before / ice after exercises | No lifting/gripping/weight-bearing to ~4 wk; driving limited ~first week (full fist + safe control) |
| IV — Strengthening & return | Week 4+ | None | Graded grip/pinch (e.g. putty) once 4-wk precaution lifts -> full function | Supervised therapy if indicated (long-standing trigger, stiffness, slow recovery, occupational demand) [Saito 2023] | Manual workers return later than desk/light roles |
Timings are criteria-based and drawn from published surgeon/hand-therapy protocols; they are typical, not trial-mandated.
G. KEY CONTROVERSIES / EVIDENCE QUALITY
- Is routine post-op hand therapy necessary? The best available evidence (Saito 2023 RCT) says no for most — home exercise matches supervised therapy on function/pain/motion at six months, with supervised therapy adding grip strength and benefiting a defined subgroup (long-standing trigger, lighter-work roles). The protocol's "therapy reserved, not routine" stance is evidence-aligned. Moderate.
- Open vs percutaneous. Equivalent long-term outcomes and safety (Casey 2024 meta-analysis); percutaneous offers faster early recovery. The rehab is the same either way. The live debate is technique-side (nerve safety, completeness of release), not rehab-side. Strong on equivalence.
- The rehab protocol structure itself is consensus/expert, built from surgeon patient-guidance documents plus one rehabilitation RCT — there is no large trial dictating exact phase timings.
- Diabetes modifies recovery — slower motion recovery and a lower threshold to involve a hand therapist; not a different protocol, a different pace. Moderate.
H. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (meta-analysis / RCTs / large cohort): open vs percutaneous equivalence in revision/complication/pain (Casey 2024, 8 RCTs); percutaneous faster early functional recovery (RCT syntheses); durability of open release (<1% reoperation, no nerve injury/deep infection in 1,598 digits, Bruijnzeel 2012).
- MODERATE (single RCT / cohorts): home exercise ~ supervised therapy at 6 months with grip-strength edge for supervised therapy (Saito 2023); percutaneous efficacy/safety series; slower recovery in diabetes; injection-vs- surgery comparative data.
- WEAK / CONSENSUS: the post-operative rehabilitation protocol structure and exact phase timings (surgeon/hand-therapy patient-guidance documents); bowstringing risk (case-level).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Open Versus Percutaneous Fixation of Trigger Finger: Meta-Analysis of Clinical Outcomes. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.03.010
- Complications of Open Trigger Finger Release. J Hand Surg Am. 2010. DOI: 10.1016/j.jhsa.2009.12.040
- Differential Pulley Release in Trigger Finger: A Prospective, Randomized Clinical Trial. Hand (N Y). 2021. DOI: 10.1177/1558944721994231
- Percutaneous A1 pulley release vs steroid injection for trigger digit. J Hand Surg Eur. 2010. DOI: 10.1177/1753193410381824
- Comparative Study of A1 Pulley Release and Ulnar Superficialis Slip Resection in Trigger Finger. J Hand Surg Am. 2022. DOI: 10.1016/j.jhsa.2022.04.021
- Risk Factors for Requiring Ulnar Superficialis Slip Resection During Trigger Finger Release. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.08.013
- Impact of Flexor Tendon Traction Tenolysis on Clinical Outcomes in Open A1 Pulley Release. J Hand Surg Glob Online. 2024. DOI: 10.1016/j.jhsg.2024.09.010
- Ultrasound-Assisted Percutaneous Trigger Finger Release: Is It Safe? Hand (N Y). 2008. DOI: 10.1007/s11552-008-9137-8
- Evaluation of Percutaneous First Annular Pulley Release: Efficacy and Complications. J Hand Surg Am. 2016. DOI: 10.1016/j.jhsa.2016.04.009
- Sonographically controlled minimally-invasive A1 pulley release using a new guide. BMC Musculoskelet Disord. 2023. DOI: 10.1186/s12891-023-06982-x
- Percutaneous A1 pulley with corticosteroid injection for trigger finger release. J Orthop Surg Res. 2025. DOI: 10.1186/s13018-025-05776-2
- A Cost and Efficiency Analysis of the WALANT Technique for the Management of Trigger Finger. Plast Reconstr Surg Glob Open. 2019. DOI: 10.1097/gox.0000000000002509
- Management of Pediatric Trigger Thumb and Trigger Finger. J Am Acad Orthop Surg. 2012. DOI: 10.5435/jaaos-20-04-206
- What's New in Hand Surgery. J Bone Joint Surg Am. 2024. DOI: 10.2106/jbjs.23.01343
Trigger finger surgical & rehabilitation literature (URLs)
- Saito T, et al. The Effectiveness of Rehabilitation after Open Surgical Release for Trigger Finger: A Prospective, Randomized, Controlled Study. J Clin Med. 2023;12(22):7187. https://pmc.ncbi.nlm.nih.gov/articles/PMC10671987/
- Bruijnzeel H, et al. Adverse Events of Open A1 Pulley Release for Idiopathic Trigger Finger. J Hand Surg Am. 2012;37(8):1650-1656. https://pubmed.ncbi.nlm.nih.gov/22763058/
- Casey JC, et al. Open Versus Percutaneous Fixation of Trigger Finger: Meta-Analysis of Clinical Outcomes. J Hand Surg Am. 2024;49(6):570-575. https://pubmed.ncbi.nlm.nih.gov/38727666/
- Chanthanapodi P, Aodsup S. Comparative results of percutaneous and open surgery for trigger fingers: a propensity score analysis. Front Surg. 2025;12:1509292. https://pmc.ncbi.nlm.nih.gov/articles/PMC11922895/
- Complications of Percutaneous Release of the Trigger Finger. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC6485534/
- Trigger Finger. StatPearls, NCBI Bookshelf. https://www.ncbi.nlm.nih.gov/books/NBK459310/
- Bowstringing as a complication of trigger finger release. J Hand Surg Am. 1988. https://www.jhandsurg.org/article/S0363-5023(88)80097-2/abstract
- Trigger Finger (patient information). British Society for Surgery of the Hand (BSSH). https://www.bssh.ac.uk/patients/conditions/15/trigger_finger
Published rehab protocols (patient-guidance — basis for the phase structure)
- University of Virginia Hand Center. Trigger Finger Release Guidelines (post-operative therapy protocol). https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2015/11/Triggerfingerreleaseprotocol.pdf
- Meletiou SD, Twin Cities Orthopedics. Post-operative Management of Trigger Release (A1 pulley release). https://tcomn.com/wp-content/uploads/2017/10/Trigger-Release-A1.pdf
- EmergeOrtho. Trigger Finger Release - Post-operative Instructions. https://emergeortho.com/wp-content/uploads/2022/06/Trigger-Finger-Release.pdf