Patients › Shoulder
Osteoarthritis sa AC Joint
AC joint osteoarthritis causes localized shoulder pain with cross-body movements; treatment ranges from activity modification to surgery.
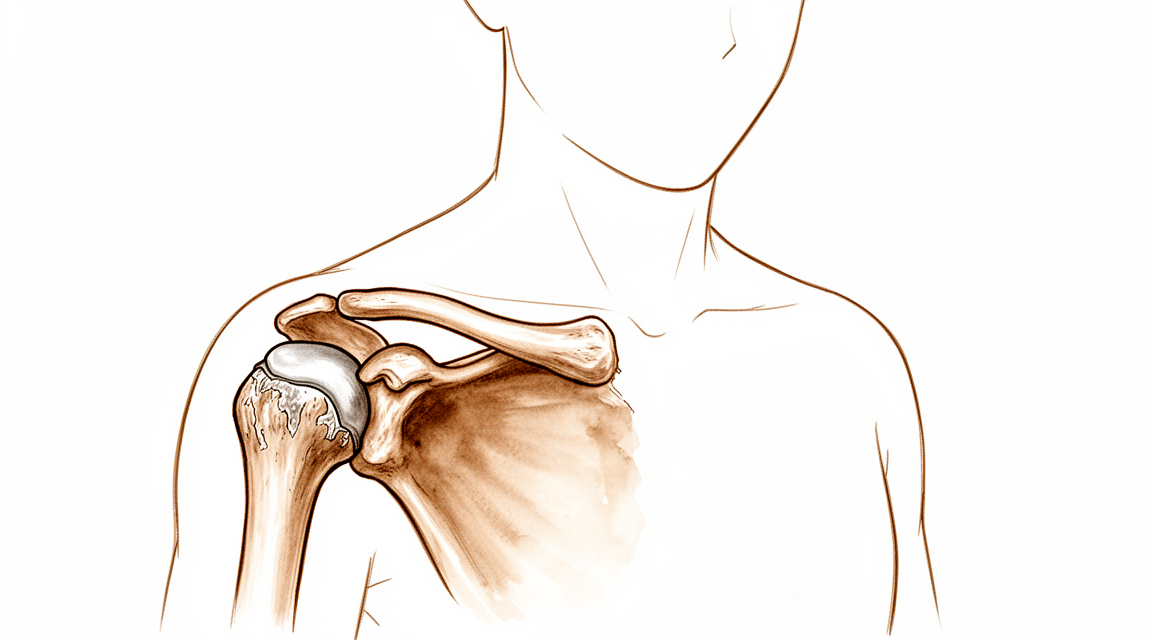
Ang iyong nararamdaman
Ang sakit ay nasa mismong itaas ng iyong balikat, sa maliit na joint kung saan nagtatagpo ang iyong collarbone at ang pinakamataas na bahagi ng iyong shoulder blade. Madalas itong kumakalat patungo sa harap ng iyong balikat o pataas sa kalamnan na tumatakbo mula sa iyong leeg hanggang sa iyong balikat. Ang pagbubuhat ng anumang mabigat ay nagpapasimula nito, at ang paghiga sa panig na iyon sa gabi ay maaaring gumising sa iyo o magpahirap sa iyong makahanap ng komportableng posisyon.
Ang direktang pagdiin sa bahaging iyon ay karaniwang nakakatagpo ng pananakit kapag diniinan (tenderness). Ang pag-abot ng iyong braso sa tapat ng iyong dibdib, o ang pagtataas nito nang diretso pataas at palabas sa gilid, ay may tendensiyang sumakit sa joint. Nagiging mahirap ang mga pang-araw-araw na gawain na naglalagay ng load sa itaas ng balikat: ang pagdadala ng mga shopping bag sa iyong tagiliran, ang pagbubuhat ng mabigat na kawali papunta sa kalan, ang pag-abot sa mataas na istante, o ang paghila ng seatbelt sa tapat ng iyong katawan.
Ang kirot ay madalas na sumisidhi pagkatapos ng aktibidad sa halip na habang ginagawa ito, kaya ang isang araw ng pagbubuhat o overhead work ay maaaring mag-iwan sa iyong masakit sa gabing iyon at kinaumagahan. Karaniwan ang pananakit sa gabi sa apektadong panig, at may ilang tao na kailangang matulog nang nakatihaya o sa kabilang panig.
Isang bagay na mahalagang malaman: ang arthritis sa joint na ito ay lumalabas sa mga scan ng maraming tao na walang nararamdamang anuman. Karamihan sa mga joint na tulad nito na mukhang pudpod sa X-ray ay nananatiling tahimik, at ang masakit na balikat na may joint na mukhang pudpod ay hindi laging nangangahulugang ang joint ang sanhi. Iyan ang dahilan kung bakit maaaring imungkahi ng iyong surgeon ang isang injection ng pampamanhid na gamot sa mismong joint. Kung humupa ang sakit nang ilang sandali pagkatapos nito, malamang na ang joint ang pinagmumulan ng iyong problema. Kung hindi, ang pagkapudpod na nakikita sa scan ay malamang na hindi ang nagdudulot ng iyong sakit, at malamang na hindi makakatulong ang paggamot dito.
Kung hindi humuhupa ang pananakit ng iyong balikat sa loob ng ilang linggo, lumalala, ginigising ka sa gabi, o pinipigilan kang gamitin ang iyong braso o magtrabaho, magpatingin sa iyong GP o humingi ng pagsusuri ng isang espesyalista.
Ano ang aktwal na nangyayari
Ang iyong balikat ay may maliit na joint kung saan nagtatagpo ang panlabas na dulo ng iyong collarbone at ang dulo ng iyong shoulder blade. Ito ang AC joint, maikli para sa acromioclavicular joint. Ito ay isang joint na gumagalaw, hindi isang matigas na hinang. Gumagalaw ito nang ilang milimetro habang umiikot at dumudulas ang iyong shoulder blade sa normal na paggamit ng braso, at pinahihintulutan nito ang iyong shoulder blade at collarbone na gumana bilang iisang magkakabit na piraso. Pinagdudugtong ito ng matitibay na ligament, sa tulong ng mga kalamnan na tumatakip sa itaas ng iyong balikat.
Sa loob ng joint ay may isang manipis na disc na nagsisilbing cushion, medyo katulad ng gasket sa pagitan ng dalawang piraso ng buto. Mula sa maagang katanghaliang-gulang pataas, nagsisimulang mapudpod ang disc na ito, at kasabay nitong napupudpod ang mga surface ng joint sa likod nito. Iyan ang wear-and-tear arthritis, at sa joint na ito ay napakakaraniwan nito. Ang pagkapudpod ay karaniwang tahimik na nagsisimula sa iyong edad na beinte at treinta at dahan-dahang umuusad sa paglipas ng mga taon. Pinabibilis ito ng mabigat o paulit-ulit na pagbubuhat, lalo na ng overhead work. Ganoon din ang isang lumang sprain o separation ng joint mula sa isang pagkahulog, kahit isang mild lang na tila gumaling na.
Ang problema ay ang joint na mukhang pudpod ay hindi laging masakit. Maraming tao ang may pagkapudpod sa kanilang mga scan at walang anumang sintomas, at karamihan sa mga joint na mukhang pudpod ay nananatiling tahimik. Kaya ang sakit na nararamdaman mo ay nagmumula sa mismong joint lamang kapag talagang iniirita ng pagkapudpod, ng mga hilaw na surface, o ng pamamaga sa paligid nito ang mga tissue doon. Iyan ang dahilan kung bakit ang iyong mga sintomas ay nasa mismong itaas ng balikat at sumisidhi pagkatapos itong lagyan ng load.
Ang isang hindi gaanong karaniwang bersyon ng problemang ito ay tinatawag na distal clavicle osteolysis. Dito, ang panlabas na dulo mismo ng collarbone ang nasisira, na may pamamaga, maliliit na fracture sa buto, at pagkawala ng buto. Ito ay nakikita kadalasan sa mga mas nakababatang lalaki na gumagawa ng mabigat o paulit-ulit na pagbubuhat, at humahantong ito sa parehong uri ng arthritis sa joint.
Kung lumubha ang pagkapudpod, maaaring tumubo ang mga bone spur malapit sa joint at dumiin sa tendon na tumatakbo sa ilalim ng bubong ng iyong balikat, na nagdaragdag sa problema.
Ano ang maaari naming gawin tungkol dito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyon na hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Kinukumpirma namin kung ano ang nangyayari sa pamamagitan ng maingat na history, isang pagsusuri, at imaging kung saan ito kinakailangan. Para sa isang matagal nang problema tulad nito, karaniwan naming sinusubukan muna ang non-operative care at isinasaalang-alang lamang ang operasyon kapag hindi ito nagbigay ng sapat na pagbuti.
Ang mga unang hakbang ay mga bagay na kaya mong gawin nang mag-isa. Ang pagpapahinga sa joint ay nangangahulugan ng pagbabawas sa mabibigat na pagbubuhat at overhead work na naglalagay ng load sa itaas ng iyong balikat. Ang ice ay makakapagpakalma sa pagsidhi ng sakit pagkatapos ng isang abalang araw. Layunin ng physiotherapy na pakalmahin ang iritadong joint at palakasin ang paligid ng iyong balikat upang mas kaunti ang bigat na ipinapataw dito ng mga pang-araw-araw na gawain. Bigyan ang mga pagbabagong ito ng sapat na pagsubok bago husgahan ang mga ito, dahil ang kirot ay madalas na sumisidhi pagkatapos ng aktibidad sa halip na habang ginagawa ito.
Kung hindi sapat ang pangangalaga sa sarili, makakatulong ang mga pampawala ng sakit at mga anti-inflammatory. Ang mga anti-inflammatory ay mga tablet na nagpapakalma sa pamamaga sa joint at nagpapagaan din ng sakit. Gumagamit din kami ng mga injection ng cortisone, isang malakas na anti-inflammatory medicine, na inilalagay sa mismong joint. Ang isang injection ay may dalawang layunin: tumutulong itong kumpirmahin na ang joint na ito ang pinagmumulan ng iyong sakit, at maaari nitong pagaanin ang sakit bilang gamutan. Humigit-kumulang 47 sa bawat 100 taong nagpa-injection ay may magandang resulta pa rin pagkalipas ng isang taon.
Pumapasok ang operasyon kapag nananatili ang sakit sa kabila ng mga gamutang ito. Tinatanggal ng operasyon ang ilang milimetro ng buto mula sa panlabas na dulo ng iyong collarbone, ang kalahati ng pudpod na joint na nasa panig ng collarbone. Kapag natanggal na ang pudpod na surface na iyon, hindi na nagkikiskisan ang dalawang hilaw na dulo ng buto. Maaari itong gawin sa pamamagitan ng maliliit na hiwa gamit ang camera, o sa pamamagitan ng isang maliit na open incision. Kung nagkaroon ka na dati ng separation ng joint na ito na may tumatagal na instability, maingat namin itong pag-uusapan kasama ka, dahil binabago nito kung gaano kahusay karaniwang gumagana ang operasyong ito. Kung ang operasyon ay tama para sa iyo ay isang desisyong gagawin natin nang magkasama, tinitimbang kung ano ang gusto mong magawa ng iyong balikat laban sa kung ano ang kinapapalooban ng operasyon.
Ano ang dapat asahan
Para sa karamihan ng mga tao, ang pagkapudpod sa joint na ito na lumalabas sa scan ngunit hindi nagdudulot ng sakit ay nananatili lamang na tahimik. Sa loob ng pitong taon, 90% ng mga joint na tulad nito na walang sakit sa simula ay hindi kailanman nagkaroon ng mga sintomas. Kaya kung mukhang pudpod ang iyong joint ngunit hindi ito masakit, malaki ang posibilidad na mananatili itong maayos.
Kapag ang joint ay talagang masakit, nag-iiba-iba ang takbo nito. May ilang tao na nakikitang humuhupa ang kirot sa pamamagitan ng pahinga, pagbabawas ng mabibigat na pagbubuhat, at physiotherapy. Ang iba naman ay nakikitang ito ay pabalik-balik, sumisidhi pagkatapos ng isang abalang araw at humuhupa kapag nagpahinga ka na muli. Nang walang gamutan, ang sakit ay may tendensiyang manatili o patuloy na bumalik tuwing lalagyan mo ng load ang itaas ng iyong balikat, dahil ang pagkapudpod sa joint ay hindi kusang bumabalik sa dati.
Kung hindi nagbigay ng sapat na ginhawa ang non-operative care, nakakatulong sa ilang tao ang isang injection ng cortisone sa joint. Humigit-kumulang 47 sa bawat 100 taong nagpa-injection ay may magandang resulta pa rin pagkalipas ng isang taon. Ibig sabihin nito, para sa humigit-kumulang kalahati ng mga tao, nawawala ang ginhawa sa loob ng taon, at maaaring kailanganing ulitin ang injection o isaalang-alang ang ibang mga hakbang.
Kung nananatili ang sakit sa kabila ng mga gamutang ito, ang pagtanggal ng ilang milimetro ng buto mula sa panlabas na dulo ng iyong collarbone ay isang opsyon na maaaring talakayin sa iyo ng iyong surgeon. Ang layunin ay pigilan ang pagkikiskisan ng dalawang hilaw at pudpod na surface. Ang paggaling mula sa operasyong iyon ay tumatagal nang ilang linggo hanggang buwan, sa gabay ng iyong physiotherapist, at nakikita ng karamihan na humuhupa ang kirot sa itaas ng balikat habang kumakalma ang joint.
Ang makatotohanan mong maaasahan sa mga darating na buwan ay nakadepende sa landas na pipiliin mo. Sa makatwirang pangangalaga sa sarili at physiotherapy, maraming tao ang nakababalik sa kanilang mga normal na aktibidad nang humupa na ang kirot sa antas na kaya nilang pakisamahan. Kung patuloy na sumisidhi ang joint sa kabila ng sapat na pagsubok sa mga hakbang na ito, mabuting bumalik sa iyong GP o humingi ng pagsusuri ng isang espesyalista sa halip na tiisin ang sakit.
Kailan dapat magpatingin
Ito ay isang wear-and-tear na problema, hindi isang emergency, kaya walang mga mapanganib na palatandaan na kailangang bantayan sa parehong araw para sa kondisyong ito. Ang mahalaga ay kung humuhupa ang sakit. Magpatingin sa iyong GP kung ang sakit sa itaas ng iyong balikat ay hindi bumubuti pagkatapos ng ilang linggong pahinga mula sa mabibigat na pagbubuhat, o kung patuloy ka nitong ginigising kapag nakahiga ka sa panig na iyon. Humingi ng pagsusuri ng isang espesyalista kung lumalala ang kirot sa loob ng ilang linggo, pinipigilan kang magtrabaho o gamitin nang normal ang iyong braso, o kung nananatiling masakit ang pagbubuhat at ang pag-abot sa tapat ng iyong katawan sa kabila ng pagbabawas ng aktibidad. Kung ang iyong balikat ay naging mainit, mapula, namamaga at masakit, lalo na kung may lagnat, hindi iyon arthritis at kailangan itong magamot sa mismong araw na iyon sa isang emergency department.
Higit pang detalye
Advanced reading: the deeper science (optional)
Ang seksyong ito ay higit pa sa kailangan mo para sa iyong sariling mga desisyon sa paggamot. Ang arthritis ng AC joint ay karapat-dapat sa karagdagang pagbabasa sa isang hindi komportableng dahilan: ito ay lubhang karaniwan sa imaging, madalas itong isinisisi sa pananakit ng balikat, at ang ebidensya na ang paggamot dito ay nakatutulong ay mas mahina kaysa sa halos anumang bagay sa site na ito.
Hindi pinapatunayan ng ebidensya na may gumagana
Ang isang systematic review ng paggamot sa primary AC joint osteoarthritis ay pinagsama-sama ang 1,902 na pasyente at nakarating sa isang konklusyon na bihirang sabihin nang ganito kaplinaw: ang mga pag-aaral ay nag-iba-iba sa indikasyon, interbensyon at kalidad, at hindi nagbigay ng ebidensya na ang alinman sa non-operative o operative na mga interbensyon ay epektibo [1].
Hindi ito katulad ng pagsasabing walang nakakatulong. Nangangahulugan ito na ang mga trial na magpapatunay nito ay hindi ginawa sa isang pamantayan na nagpapahintulot sa claim. Ang distal clavicle excision ay isang matagal nang itinatag na operasyon na isinasagawa batay sa makatwirang mechanical logic na ang pagtanggal sa gasgas na joint surface ay nag-aalis ng sakit, ngunit ang "matagal nang itinatag at mechanically sensible" ay hindi ebidensya, at mahalagang malaman ang pagkakaiba kapag gumagawa ng desisyon.
Ang pagdaragdag nito sa ibang operasyon ay hindi nagpapabuti sa operasyong iyon
Ang pinaka-direktang pagsusuri ay nagmula sa mga pasyenteng may ibang ginagawang pamamaraan sa parehong oras. Sa mga 208 na pasyenteng may rotator cuff tears, ang pagdaragdag ng distal clavicle resection ay hindi nagresulta sa mas mabuting clinical outcome scores o mas mabuting range of motion [2].
Mahalaga ito dahil ito mismo ang sitwasyon kung saan ang joint ay madalas na resected, ang surgeon ay nasa loob na ng balikat, ang AC joint ay mukhang degenerate sa imaging, at ang pagtanggal ng ilang millimetres ng buto ay mabilis. Sinasabi ng ebidensya na ang pasyente ay walang nasusukat na benepisyo. Kung ito ay iminumungkahi bilang add-on sa iyong cuff repair, ito ay isang makatwirang bagay na itanong.
Ang teknika ay hindi ang kawili-wiling katanungan
Ang open versus arthroscopic resection ay paulit-ulit nang pinaghambing at ang sagot ay pare-pareho: magkatulad na functional at clinical outcomes sa alinmang approach sa 319 na pasyente [3], kung saan ang isang naunang paghahambing sa 429 na pasyente ay hindi rin pumanig nang mapagpasyahan sa alinman [4].
Kapag ang dalawang magkaibang technical approach ay nagbubunga ng parehong resulta, ang tapat na konklusyon ay na ang teknika ay hindi ang nagtatakda ng outcome, kundi ang pagpili ng pasyente.
Bakit napakahirap ng pagpili rito
Ang AC joint ay nag-dedegenerate sa halos lahat ng tao habang tumatanda. Ito ay isang maliit at may mataas na load na joint na may manipis na disc na madaling mapudpod, kaya ang isang report na naglalarawan ng AC joint degeneration sa iyong scan ay malapit nang ituring na isang inaasahang finding pagkatapos ng middle age kaysa sa isang diagnosis.
Mayroong nasusukat na structural correlate: sa mga symptomatic degenerative AC joints, kapwa lumalaki ang distal clavicle at ang acromion, samantalang sa mga asymptomatic na tao, ang relasyon sa pagitan ng dalawa ay hindi nagbabago [5]. Iyon ay isang kapaki-pakinabang na pahiwatig na ang symptomatic at incidental degeneration ay magkaiba structurally, ngunit ito ay isang group-level observation, hindi isang test na maaaring ilapat sa iyong balikat.
Sa praktikal na aspeto, ito ang dahilan kung bakit ang isang diagnostic injection sa joint ay may malaking timbang rito. Kung ang local anaesthetic na inilagay nang tumpak sa AC joint ay nag-aalis ng sakit, malamang na ang joint ang pinagmumulan nito. Kung hindi, ang degeneration sa scan ay malamang na isang bystander lamang, at ang pag-resect nito ay malamang na hindi makakatulong, na siyang sitwasyong binabalaan ng ebidensya sa itaas.
Mga Sanggunian
[1] Welch M, Rankin S, How Saw Keng M, Woods D. A systematic review of the treatment of primary acromioclavicular joint osteoarthritis. Shoulder Elbow. 2023;16(2):129-44. https://doi.org/10.1177/17585732231157090
[2] Wang J, Ma J, Zhu S, Jia H, Ma X. Does distal clavicle resection decrease pain or improve shoulder function in patients with rotator cuff tears? A meta-analysis. Clin Orthop Relat Res. 2018;476(12):2402-14. https://doi.org/10.1097/CORR.0000000000000424
[3] Hohmann E, Tetsworth K, Glatt V. Open versus arthroscopic acromioclavicular joint resection: a systematic review and meta-analysis. Arch Orthop Trauma Surg. 2019;139(5):685-94. https://doi.org/10.1007/s00402-019-03114-w
[4] Pensak M, Grumet RC, Slabaugh MA, Bach BR. Open versus arthroscopic distal clavicle resection. Arthroscopy. 2010;26(5):697-704. https://doi.org/10.1016/j.arthro.2009.12.007
[5] Bulkmans K, Peeters I, De Wilde L, Van Tongel A. The relationship of the acromion to the distal clavicle in normal and symptomatic degenerative acromioclavicular joints. Arch Orthop Trauma Surg. 2019;140(4):465-72. https://doi.org/10.1007/s00402-019-03258-9
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Asymptomatic acromioclavicular osteoarthritis remained asymptomatic in 90% of cases over a seven-year course [1].
- Treatment choice for acromioclavicular dislocation should not be influenced by the potential development of acromioclavicular osteoarthritis [2].
- Further characterisation is needed to identify patients in whom mild arthroscopic findings of acromioclavicular joint osteoarthritis are clinically significant and warrant resection [3].
- Persistent pain and osteoarthritis progression remain concerns following revision of failed open anterior stabilization of the shoulder [4].
- Both open and arthroscopic resection arthroplasty techniques provide predictable pain relief for symptomatic acromioclavicular osteoarthritis [5].
- Symptomatic acromioclavicular joint osteoarthritis occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years [6].
- Untreated acromioclavicular joint osteoarthritis, symptomatic or not, encountered during arthroscopic rotator cuff repair is associated with a low percentage of failure [8].
- Biplanar reconstruction with pectoralis minor tendon and coracoacromial ligament transfer aims to preserve the lateral portion of the clavicle whenever possible, limiting resection exclusively to cases of acromioclavicular joint osteoarthritis or irreducible joints [9].
- Radiographic acromioclavicular joint osteoarthritis is common in patients undergoing reverse shoulder arthroplasty [10].
- Clinicians should consider overreduction of the acromioclavicular joint because it may lead to favorable radiological results [11].
- A distinction between symptomatic and asymptomatic radiographic acromioclavicular osteoarthritis is unnecessary, as all patients were equally satisfied with the outcome following preoperative acromioclavicular injection [12].
- Open and arthroscopic acromioclavicular joint reconstruction techniques have no differences in loss of reduction, the complication rate, and the revision rate [13].
- Arthroscopic debridement of the acromioclavicular joint can produce a favorable result in young patients presenting with isolated acromioclavicular joint-related pain but with normal imaging [15].
- Limited distal clavicle excision of patients with acromioclavicular joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [17].
- All patients undergoing free tissue graft reconstruction of the acromioclavicular joint are satisfied with their surgery and demonstrate good reduction of the acromioclavicular joint on radiographs, although follow-up periods are less than 1 year [21].
- Additional research is needed to determine the main cause of pain and compare clinical outcomes of intra-articular versus extra-articular injections for isolated acromioclavicular osteoarthritis [23].
- Nanoscopic distal clavicle resection offers advantages including decreased morbidity, less risk to the acromioclavicular joint ligaments, and decreased loss and need for fluid [44].
Anatomy & Pathophysiology
Bony Anatomy and Joint Structure
- The acromioclavicular (AC) joint is a diarthrodial joint that supports the shoulder girdle through the clavicular “strut” [36].
- The AC joint serves as a primary link between the axial skeleton and the upper extremity [122].
- The AC joint is movable in all planes and is not a rigid structure [122].
- The normal AC joint is capable of translating 4 to 6 mm in the anterior, posterior, and superior planes under 70-N loads [122].
- The AC joint accommodates rotary motion of 5° to 8° during scapulothoracic motion and 40° to 45° with shoulder abduction and elevation [122].
- The scapula and clavicle are linked into a single segment referred to as the “claviscapula” [112].
Ligamentous Anatomy and Stability
- The AC and coracoclavicular (CC) ligaments are the static stabilizers of the AC joint, whereas the deltoid and trapezius muscles are the dynamic stabilizers [122].
- The horizontal plane stability of the clavicle is provided by the AC ligaments, specifically the posterior and superior portions [25].
- The AC and CC ligaments play a role in torque transduction and horizontal and vertical stability [112].
- Injury to the AC joint results in progressive disruption of the ligamentous support, beginning with the capsular ligaments and progressing to the CC ligaments [30].
Pathophysiology of Degeneration
- AC joint osteoarthritis is more common with advanced age following degeneration of the intra-articular disk [25].
- Arthritic deterioration of the AC joint starts in early middle age [25].
- AC joint osteoarthritis is more common in patients engaged in repetitive overhead or lifting activities [25].
- Previous low-grade AC joint separations can result in painful arthritis [25].
- The radiographic severity of AC joint arthritis does not always correlate with patient symptoms [25].
- Asymptomatic AC joint degeneration is frequent and does not always correlate with the presence of symptoms [36].
- Degeneration of the AC joint is classified as primary osteoarthritis, posttraumatic osteoarthritis, or distal clavicle osteolysis [123].
- The process of AC joint degeneration begins in the second decade of life and can progress to complete obliteration of the joint [123].
- Complete obliteration of the AC joint can lead to subclavicular spurring, which contributes to subacromial impingement of the supraspinatus [123].
- Asymptomatic AC osteoarthritis remained asymptomatic in 90% of cases over a seven-year course [1].
- Patients with loss of immediate postoperative reduction after AC joint dislocation more often developed radiologic and symptomatic AC osteoarthritis than those in whom the AC joint was anatomically restored [7].
- Kinematic changes associated with AC joint dislocation could be a potential source of pain and dysfunction in the shoulder [59].
- Scapular and clavicular kinematics are affected in AC separation models [60].
- Decoupling the claviscapular segment has deleterious effects on the functional integrity of the AC joint complex within scapulohumeral rhythm [112].
Distal Clavicle Osteolysis
- Distal clavicle osteolysis is characterized by localized hyperemia of the distal clavicle, resulting in inflammation, bone resorption, microfractures, and secondary arthritis of the AC joint [25].
- Distal clavicle osteolysis is more common in males and seen in younger patients [25].
- Distal clavicle osteolysis is associated with heavy lifting or repetitive motions [25].
- Osteolysis of the distal clavicle was first reported in conjunction with acute trauma [121].
- Intraarticular distal clavicle fractures and AC separations can lead to osteolysis [121].
- Other causes of distal clavicle osteolysis include rheumatoid arthritis, hyperparathyroidism, and repetitive microtrauma [121].
- The most common cause of distal clavicle osteolysis is repetitive microtrauma [121].
- Radiographic findings indicative of distal clavicle osteolysis include loss of subchondral bone detail, cystic reabsorption of the distal clavicle, and generalized osteopenia of the distal clavicle [121].
Classification
- Asymptomatic acromioclavicular osteoarthritis diagnosed by MRI remained asymptomatic in 90% of cases over a seven-year course [1].
- Treatment choice for acromioclavicular dislocation should not be influenced by the potential development of acromioclavicular osteoarthritis based on available evidence [2].
- Patients with loss of immediate postoperative reduction following arthroscopically assisted reduction of acute acromioclavicular joint dislocation more often developed radiologic and symptomatic acromioclavicular osteoarthritis than those in whom the joint was anatomically restored [7].
- Untreated acromioclavicular joint osteoarthritis, whether symptomatic or not, encountered during arthroscopic rotator cuff repair is associated with a low percentage of failure [8].
- Biplanar reconstruction with pectoralis minor tendon and coracoacromial ligament transfer aims to preserve the lateral portion of the clavicle, limiting resection exclusively to cases of acromioclavicular joint osteoarthritis or irreducible joints [9].
- Open and arthroscopic acromioclavicular joint reconstruction techniques have no differences in loss of reduction, complication rate, and revision rate based on available literature [13].
- A study evaluated three groups of patients: 84 acromioclavicular joints without clinical or radiological pathology, 39 patients with signs of osteoarthritis on CT without symptoms, and 30 patients with acromioclavicular joint pain [14].
- In the study of acromion-clavicle relationships, Group 2 included patients with signs of osteoarthritis on CT (joint space narrowing, osteophytes, and/or bone cyst) who were asymptomatic based on physical examination and negative cross-body adduction test [14].
- In the study of acromion-clavicle relationships, Group 3 included patients with acromioclavicular joint pain confirmed by tenderness and temporary pain relief with intra-articular injection, who were treated with open distal clavicle resection after failure of non-operative treatment [14].
- The occurrence of acromioclavicular joint osteoarthrosis was surprisingly frequent in a study of shoulder pain [18].
- Anatomic techniques that address both coracoclavicular ligaments and the acromioclavicular capsule are recommended to restore horizontal and vertical stability while allowing physiological rotation [19].
- The acromial center line to dorsal clavicle radiographic measurement and use of the Alexander view provides a more realistic appreciation of true acromioclavicular joint displacement, especially in defining watershed cases (IIIA/IIB/IV) [22].
- Osteolytic changes seemed to be associated with incongruity of the acromioclavicular joint but did not correlate with clinical results in a review of surgical treatment for acromioclavicular dislocation [24].
- A procedure for exact anatomical acromioclavicular joint reconstruction using acromioclavicular and coracoclavicular FiberWire cerclage shows good objective results with high Constant and Rowe scores for shoulder function [27].
- Preoperative radiographs were evaluated to determine whether there was any osteolysis of the distal clavicle in a study of preoperative factors associated with subsequent distal clavicle resection after rotator cuff repair [31].
- Preoperative radiographs were graded for severity of arthritis per the Petersson classification by two attending orthopaedic surgeons blinded to each other's grade in a study of preoperative factors associated with subsequent distal clavicle resection after rotator cuff repair [31].
- Type V acromioclavicular dislocations may be given a trial of conservative therapy [35].
- Non-operative reduction and stabilization of high-grade acromioclavicular joint separations seems to be a valuable treatment option [45].
- Evaluating the integrity of the capsuloligamentous structures stabilizing the acromioclavicular joint is reproducible and gives additional information on the severity of the injury, which might also influence the treatment decision [49].
- Severe chronic symptomatic acromioclavicular joint separations (Rockwood types III through V) can be repaired entirely by arthroscopy safely and effectively by transferring the coracoacromial ligament with a bone block in the distal clavicle [50].
- The treatment of Type III acromioclavicular joint separation has remained controversial, with many studies demonstrating good results with nonoperative management and most series failing to document the superiority of either operative or nonoperative management [51].
- Surgical management of acromioclavicular joint injuries is associated with a relatively high complication profile and common loss of reduction, though the revision surgery rate is low [53].
- Arthroscopically assisted treatment of acute acromioclavicular joint dislocation provides good clinical results and few complications, though the rate of recurrence and postoperative loss of reduction requires better definition of indications and improvement of surgical implants and technique [55].
- In every coracoclavicular loop repair, regardless of hole placement, complete acromioclavicular joint congruity is not restored [86].
- Given that more than 100 surgical stabilization techniques have been proposed for acromioclavicular joint injuries, a deeper understanding of the underlying anatomy integrated with biomechanical evidence may help guide the development of a standardized, evidence-based approach to treatment [88].
- Early and delayed surgical interventions of high-grade acromioclavicular joint dislocation provide equivalent clinical scores when combined coracoclavicular and acromioclavicular joint fixation is used for stabilization [95].
- Acromioclavicular joint osteoarthritis was graded using the Kellgren-Lawrence classification system in a retrospective cohort study of concomitant open distal clavicle excision after reverse total shoulder arthroplasty [101].
Clinical Presentation
History and Symptoms
- Patients report activity-related pain localized to the AC joint [25].
- Pain may radiate anteriorly or along the trapezius [25].
- Pain is reported with heavy lifting or when sleeping on the affected side [25].
- AC joint osteoarthrosis is a frequent cause of shoulder pain [18].
- In patients with rheumatoid arthritis, clinical symptoms and radiologic appearances are often poor indicators of the source of pain in the shoulder joint complex [64].
Physical Examination
- Point tenderness is seen at the AC joint [25].
- Horizontal stability of the AC joint should be assessed [25].
- Pain at the AC joint with terminal elevation and cross-body motion is often seen [25].
- The adduction sign, where pain is produced in the AC joint during maximal adduction of the internally rotated arm, was positive in all 20 patients with AC joint arthritis in one study [63].
- An average decrease of 5 cm in the distance from the ipsilateral antecubital fossa to the contralateral anterior shoulder was noted during cross-body adduction in patients with AC joint arthritis [63].
- Selective injection of anesthetic into the AC joint can confirm the diagnosis [25].
- Patients with ACJ pain showed clinical signs including AC joint tenderness to palpation and temporary pain relief with intra-articular injection [14].
Imaging
- An AP view and/or a Zanca view of the shoulder provides good visualization of the AC joint [25].
- Osteophyte formation, sclerotic reaction, and bone cysts are commonly seen on radiographs of the AC joint [25].
- Bone and joint edema on MRI correlate with AC joint pain [25].
- The radiographic severity of arthritis does not always correlate with patient symptoms [25].
- Radiographic ACJ osteoarthritis is common in patients undergoing reverse shoulder arthroplasty [10].
- Asymptomatic AC-OA remained asymptomatic in 90% of patients over a seven-year course [1].
- A distinction between symptomatic and asymptomatic radiographic AC OA may be unnecessary, as all patients were equally satisfied with the outcome in one study [12].
- Osteolytic changes seemed to be associated with incongruity of the AC joint but did not correlate with clinical results [24].
Investigations
Clinical Evaluation
- Patients with AC joint osteoarthritis report activity-related pain localized to the AC joint, with occasional radiation anteriorly or along the trapezius [25].
- Pain with heavy lifting or when sleeping on the affected side is reported in patients with AC joint osteoarthritis [25].
- Physical examination of the AC joint reveals point tenderness at the joint [25].
- Horizontal stability of the AC joint should be assessed during physical examination [25].
- Pain at the AC joint with terminal elevation and cross-body motion is often seen in patients with AC joint osteoarthritis [25].
- Selective injection of anesthetic into the AC joint can confirm the diagnosis of symptomatic AC osteoarthritis [25].
- A distinction between symptomatic and asymptomatic radiographic AC OA is unnecessary, as all patients were equally satisfied with the outcome following preoperative injection [12].
Imaging
- Patients with edema on MRI were more likely to present pain than patients without edema [92].
- Subchondral bone edema on histologic examination was more frequent in patients with pain [92].
- The AC-DC measurement and use of the Alexander view provides a more realistic appreciation of true AC joint displacement, especially in defining watershed cases (ie, IIIA/IIB/IV) [22].
- Preoperative radiographs are evaluated to determine whether there is any osteolysis of the distal clavicle [31].
- The Petersson classification is used to grade the severity of arthritis on preoperative radiographs [31].
- In a study of AC joint osteoarthrosis, the occurrence was surprisingly frequent [18].
Treatment
Non-Operative Management
- Rest, ice, and NSAIDs are used initially for AC joint osteoarthritis [25].
- Corticosteroid injections can be used for diagnostic or therapeutic purposes in AC joint osteoarthritis [25].
- AC injections offer a 1-year success rate of 47% [33].
- Conservative and surgical treatments are both effective in acromioclavicular joint osteoarthritis management [38].
- A distinction between symptomatic and asymptomatic radiographic AC OA is unnecessary, as all patients were equally satisfied with the outcome following injection [12].
- Additional research is needed to determine the main cause of pain and compare clinical outcomes of intra-articular versus extra-articular injections [23].
Operative Management: Distal Clavicle Resection
- Surgical indications for AC joint osteoarthritis include persistent pain and failure of nonsurgical treatment [25].
- Both open and arthroscopic resection arthroplasty techniques provide predictable pain relief for symptomatic AC osteoarthritis [5].
- Arthroscopic distal clavicle excision provides reliable pain relief in >90% of patients in the absence of instability [25].
- Previous traumatic instability is associated with persistent pain in 30% to 40% of cases following distal clavicle excision [25].
- One systematic review showed slightly better results with arthroscopic excision than with open distal clavicle excision [25].
- Direct comparison studies have shown similar or better results with arthroscopic excision than with open techniques [25].
- Biomechanical evidence suggests a resection of 5 mm is needed to prevent contact between the clavicle and the acromion in the absence of instability [25].
- Care should be taken to preserve the posterior and superior AC ligaments during arthroscopic distal clavicle excision [25].
- Between 5 and 10 mm of the distal clavicle should be resected during an open Mumford procedure [25].
- Meticulous repair of the deltotrapezial fascia is important during open distal clavicle resection [25].
- Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [17].
- Arthroscopic debridement of the AC joint can produce a favorable result in young patients presenting with isolated AC joint-related pain but with normal imaging [15].
- The nanoscopic distal clavicle resection technique offers advantages including decreased morbidity, less risk to the AC joint ligaments, and decreased loss and need for fluid [44].
- Patients with AC joint instability have poor results after distal clavicle resection [36].
- The optimal amount of distal clavicle resection remains elusive [36].
Operative Management: Concomitant Procedures and Specific Populations
- Preventive arthroscopic distal clavicle resection is not recommended in patients with radiological but asymptomatic ACJ arthritis and rotator cuff tears [34].
- Untreated ACJ osteoarthritis, symptomatic or not, encountered during arthroscopic rotator cuff repair is associated with a low percentage of failure [8].
- Further characterisation of patients in whom mild arthroscopic findings of OA of AC joint are clinically significant and warrant resection is needed [3].
- Symptomatic ACJ OA occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years [6].
- Osteoarthritis is associated with poorer final clinical outcomes after rotator cuff repair, and an unhealed or re-torn cuff increases the risk of osteoarthritis [26].
Operative Management: Reconstruction and Stabilization
- Open and arthroscopic AC joint reconstruction techniques have no differences in loss of reduction, the complication rate, and the revision rate based on the available literature [13].
- Treatment choice for AC dislocation should not be influenced by the potential development of AC OA [2].
- Achieving and maintaining satisfactory joint reduction is a factor of good prognosis, both radiologically and functionally, in AC dislocation treatment [7].
- Patients with loss of immediate postoperative reduction more often developed radiologic and symptomatic AC osteoarthritis than those in whom the AC joint was anatomically restored [7].
- Clinicians should consider overreduction of the AC joint because it may lead to favorable radiological results [11].
- Ensuring good initial recovery of the coracoclavicular distance and precise placement of the AC joints was important in maintaining the proper AC position at the final follow-up [46].
- Combined stabilization of the AC capsule and CC ligaments demonstrated the greatest capacity to restore native stability against translational and rotational loads [81].
- The biplanar reconstruction procedure aims to preserve the lateral portion of the clavicle whenever possible, limiting resection exclusively to cases of AC joint osteoarthritis or irreducible joints [9].
- Some persistent pain and osteoarthritis progression remain concerns following revision of failed open anterior stabilization of the shoulder [4].
Complications
Natural History and Progression
- Patients who experienced loss of immediate postoperative reduction after acute acromioclavicular dislocation more often developed radiologic and symptomatic acromioclavicular osteoarthritis than those in whom the joint was anatomically restored [7].
- Osteoarthritis is associated with poorer final clinical outcomes following rotator cuff repair [26].
- An unhealed or re-torn rotator cuff increases the risk of developing osteoarthritis [26].
- Severe acromioclavicular joint osteoarthritis is associated with acromial stress fractures after reverse shoulder arthroplasty [10].
Surgical Complications and Outcomes
- Treatment of acromioclavicular dislocation by synthetic ligament reconstruction carries a risk of significant early osteolysis [56].
- Complications such as anterior shoulder pain, acromioclavicular joint asymmetry, and activity-related weakness are common sequelae of coracoclavicular ligament reconstruction [43].
- Three patients with old acromioclavicular separations had prominence of the distal clavicle or symptoms due to residual hypermobility of the clavicle despite concurrent coracoclavicular stabilization [114, 115, 116, 117].
- A patient who did not undergo anterior acromioplasty despite subacromial impingement had unchanged impingement symptoms after distal clavicle resection [114, 115, 116, 117].
- Open and arthroscopic resection arthroplasty techniques for symptomatic acromioclavicular osteoarthritis each have a unique set of potential complications that may be minimized with improved understanding of anatomy, biomechanics, and meticulous surgical technique [5].
Recovery
Natural History and Prognosis
- Asymptomatic acromioclavicular osteoarthritis diagnosed by MRI remained asymptomatic in 90% of patients over a seven-year course [1].
- Osteolytic changes associated with incongruity of the acromioclavicular joint did not correlate with clinical results in a review of 39 patients [24].
- An unhealed or re-torn rotator cuff increases the risk of osteoarthritis following rotator cuff repair [26].
Impact of Joint Reduction and Stability
- Patients with loss of immediate postoperative reduction after arthroscopically assisted reduction of acute acromioclavicular joint dislocation more often developed radiologic and symptomatic acromioclavicular osteoarthritis than those in whom the joint was anatomically restored [7].
- Achieving and maintaining satisfactory joint reduction is a factor of good prognosis, both radiologically and functionally [7].
- Ensuring good initial recovery of the coracoclavicular distance and precise placement of the acromioclavicular joints was important in maintaining the proper acromioclavicular position at final follow-up [46].
Surgical Considerations Regarding Osteoarthritis
- Further characterisation of patients in whom mild arthroscopic findings of acromioclavicular joint osteoarthritis are clinically significant and warrant resection is needed [3].
- Biplanar reconstruction for chronic acromioclavicular joint dislocations aims to preserve the lateral portion of the clavicle, limiting resection exclusively to cases of acromioclavicular joint osteoarthritis or irreducible joints [9].
- The average angle from the central portion of the acromioclavicular joint anteriorly for a novel anterior portal for arthroscopic distal clavicle excision was 6 degrees, with a range of 0 to 15 degrees [29].
Non-Operative Management and Diagnostic Implications
- Acromioclavicular injections offer a 1-year success rate of 47% in patients with acromioclavicular osteoarthritis [33].
Key Evidence
- [L2] Asymptomatic AC-OA remained asymptomatic in 90% over 7 years. [1] (10.1016/j.jse.2019.04.004)
- [L4] Based on the available evidence, treatment choice for AC dislocation should not be influenced by the potential development of AC OA. [2] (10.2106/jbjs.rvw.24.00085)
- [L2] Further characterisation of patients in whom mild arthroscopic findings of OA of AC joint are clinically significant and warrant resection is needed. [3] (10.1007/s00167-014-3114-2)
- [L4] Some persistent pain and osteoarthritis progression remain concerns. [4] (10.1016/j.arthro.2009.04.073)
- [L5] Both open and arthroscopic resection arthroplasty techniques provide predictable pain relief for symptomatic AC osteoarthritis, though each has a unique set of potential complications that may be minimized with improved understanding of anatomy, biomechanics, and meticulous surgical technique. [5] (10.1177/0363546513485359)
- [L4] Symptomatic ACJ OA occurred in 15.9% of patients after total anatomic shoulder replacement with follow-up of up to 12 years. [6] (10.1177/17585732221114796)
- [L4] [7] (10.1016/j.otsr.2017.11.001)
- [L2] Untreated ACJ osteoarthritis, symptomatic or not, encountered during arthroscopic RCR is associated with a low percentage of failure. [8] (10.1007/s00167-020-06098-y)
- [L5] The procedure aims to preserve the lateral portion of the clavicle whenever possible, limiting resection exclusively to cases of AC joint osteoarthritis or irreducible joints. [9] (10.1016/j.eats.2024.103104)
- [L3] Radiographic ACJ osteoarthritis is common in patients undergoing RSA. [10] (10.1016/j.jseint.2021.11.008)
- [L3] Clinicians should consider overreduction of the AC joint because it may lead to favorable radiological results. [11] (10.1177/0363546519862850)
- [L4] The outcomes of this study seem to suggest that a distinction between symptomatic and asymptomatic radiographic AC OA is unnecessary, as all patients were equally satisfied with the outcome. [12] (10.5397/cise.2023.00073)
- [L1] Open and arthroscopic AC joint reconstruction techniques have no differences in loss of reduction, the complication rate, and the revision rate based on the available literature. [13] (10.1177/0363546518795147)
- [L3] [14] (10.1007/s00402-019-03258-9)
- [L4] Arthroscopic debridement of the AC joint can produce a favorable result in this difficult group of young patients presenting with isolated AC joint-related pain but with normal imaging. [15] (10.1097/bte.0b013e31816276cb)
- [L4] Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up. [17] (10.1016/j.otsr.2016.01.008)
- [L3] In this study the occurrence of AC joint osteoarthrosis was surprisingly frequent. [18] (10.1016/s1058-2746(96)80122-4)
- [L5] Anatomic techniques that address both coracoclavicular ligaments and the AC capsule are recommended to restore horizontal and vertical stability while allowing physiological rotation. [19] (10.1016/j.arthro.2019.01.038)
- [L4] Although the follow-up periods are less than 1 year, all patients are satisfied with their surgery and demonstrate good reduction of the AC joint on radiographs. [21] (10.1097/bte.0b013e31818a5dd9)
- [L4] The AC-DC measurement and use of the Alexander view provides the clinician with a more realistic appreciation of true AC joint displacement, especially in defining watershed cases (ie, IIIA/IIB/IV) and may better inform the decision-making process regarding management options and recommendations. [22] (10.1016/j.jse.2019.12.014)
- [L4] Additional research is needed to determine the main cause of pain and compare clinical outcomes of intra-articular versus extra-articular injections. [23] (10.5397/cise.2023.00311)
- [L4] Osteolytic changes seemed to be associated with incongruity of the AC joint, but did not correlate with clinical results. [24] (10.1016/0020-1383(83)90092-x)
- [L4] Osteoarthritis is associated with poorer final clinical outcomes, and an unhealed or re-torn cuff increases the risk of osteoarthritis. [26] (10.1016/j.otsr.2017.03.007)
- [L4] This procedure for an exact anatomical AC joint reconstruction shows good objective results with a high Constant and Rowe scores for shoulder function. [27] (10.1055/s-2008-1038577)
- [L4] The average angle from the central portion of the AC joint anteriorly was 6 degrees (range, 0 to 15 degrees). [29] (10.1097/bte.0000000000000033)
- [L3] [31] (10.1177/2325967119844295)
- [L4] AC injections offer a 1-year success rate of 47%. [33] (10.5397/cise.2023.00031)
- [L1] Preventive arthroscopic DCR is not recommended in patients with radiological but asymptomatic ACJ arthritis. [34] (10.1177/0363546514547254)
- [L4] This suggests that Type V AC dislocations may be given a trial of conservative therapy. [35] (10.1177/2325967115s00017)
- [L5] [36] (10.5435/00124635-199905000-00004)
- [L4] Conservative and surgical treatments are both effective in acromioclavicular joint osteoarthritis management. [38] (10.1007/s00167-020-06377-8)
- [L4] Most patients were ultimately treated surgically, although complications such as anterior shoulder pain, AC joint asymmetry, and activity-related weakness were common sequelae resulting in physical limitations and separation from military service. [43] (10.1177/03635465211036713)
- [L5] The technique offers advantages including decreased morbidity, less risk to the AC joint ligaments, and decreased loss and need for fluid. [44] (10.1016/j.eats.2021.12.006)
- [L4] Non-operative reduction and stabilization of high-grade AC joint separations seems to be a valuable treatment option. [45] (10.1007/s00402-020-03630-0)
- [L4] Ensuring good initial recovery of the CCD and precise placement of the AC joints was important in maintaining the proper AC position at the final follow-up. [46] (10.1016/j.arthro.2018.07.007)
- [L1] Evaluating the integrity of the capsuloligamentous structures stabilizing the AC joint is reproducible and gives additional information on the severity of the injury, which might also influence the treatment decision. [49] (10.1016/j.jse.2020.10.026)
- [L4] Severe chronic symptomatic AC joint separations (Rockwood types III through V) can be repaired entirely by arthroscopy safely and effectively by transferring the coracoacromial ligament with a bone block in the distal clavicle. [50] (10.1016/j.arthro.2009.08.008)
- [L5] [51] (10.1097/00132589-200603000-00004)
- [L4] Surgical management of AC joint injuries is associated with a relatively high complication profile and common loss of reduction, though the revision surgery rate is low. [53] (10.1016/j.jse.2023.03.019)
- [L4] [55] (10.1016/j.otsr.2010.10.004)
- [L4] Treatment of ACD by synthetic ligament reconstruction gave satisfactory results, notably in terms of recovery of strength, but evolution is not risk-free with onset of significant early osteolysis. [56] (10.1016/j.otsr.2010.06.004)
- [L5] The kinematic changes could be a potential source of pain and dysfunction in the shoulder with AC joint dislocation. [59] (10.1177/0363546512458571)
- [L5] Scapular and clavicular kinematics were affected in AC separation models. [60] (10.1016/j.jse.2013.01.004)
- [L4] [63] (10.1177/036354659302100113)
- [L4] Clinical symptoms and radiologic appearances are often poor indicators of the source of pain in the shoulder joint complex in patients with rheumatoid arthritis. [64] (10.1016/s1058-2746(09)80111-0)
- [L5] Combined stabilization of the AC capsule and CC ligaments demonstrated the greatest capacity to restore native stability against translational and rotational loads. [81] (10.1177/0363546518807908)
- [L5] In every CC loop repair, regardless of hole placement, complete AC joint congruity is not restored. [86] (10.1016/s1058-2746(03)00050-8)
- [L5] Given that more than 100 surgical stabilization techniques have been proposed for AC-joint injuries, a deeper understanding of the underlying anatomy, integrated with biomechanical evidence, may help to guide the development of a standardized, evidence-based approach to the treatment of AC-joint instability. [88] (10.2106/jbjs.25.01392)
- [L4] Patients with edema on MRI were more likely to present pain than patients without edema, and subchondral bone edema on histologic examination was more frequent in patients with pain. [92] (10.1016/j.jseint.2020.03.007)
- [L3] Early and delayed surgical interventions of high-grade AC joint dislocation provide equivalent clinical scores when combined CC and AC joint fixation is used for stabilization. [95] (10.1016/j.jse.2020.06.026)
- [L3] [101] (10.5397/cise.2023.00465)
- [L5] [112] (10.5435/jaaos-d-24-00360)
- [L4] [114] (10.1016/s1058-2746(96)80521-0)
- [L4] [115] (10.1016/s1058-2746(96)80520-9)
- [L4] [116] (10.1016/s1058-2746(96)80523-4)
- [L3] [117] (10.1016/s1058-2746(96)80522-2)
- [L4] [121] (10.1016/s1058-2746(10)80007-2)
- [L4] [122] (10.1302/2058-5241.3.170027)
- [L5] [123] (10.1016/s0278-5919(02)00102-3)
References
[1] Seven-year course of asymptomatic acromioclavicular osteoarthritis diagnosed by MRI. Journal of Shoulder and Elbow Surgery. 2019. DOI: 10.1016/j.jse.2019.04.004
[2] Choice of Acromioclavicular Dislocation Treatment Should Not Be Influenced by Risk of Development of Acromioclavicular Osteoarthritis. JBJS Reviews. 2024. DOI: 10.2106/jbjs.rvw.24.00085
[3] Outcome of distal clavicle resection in patients with acromioclavicular joint osteoarthritis and full‐thickness rotator cuff tear. Knee Surgery, Sports Traumatology, Arthroscopy. 2014. DOI: 10.1007/s00167-014-3114-2
[4] The Role of Arthroscopy in Revision of Failed Open Anterior Stabilization of the Shoulder. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.04.073
[5] Degenerative Joint Disease of the Acromioclavicular Joint. The American Journal of Sports Medicine. 2013. DOI: 10.1177/0363546513485359
[6] The incidence and treatment of symptomatic acromioclavicular joint osteoarthritis following total shoulder arthroplasty. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221114796
[7] Arthroscopically assisted reduction of acute acromioclavicular joint dislocation using a single double-button device: Medium-term clinical and radiological outcomes. Orthopaedics & Traumatology: Surgery & Research. 2018. DOI: 10.1016/j.otsr.2017.11.001
[8] Acromioclavicular joint arthritis is not an indication for routine distal clavicle excision in arthroscopic rotator cuff repair. Knee Surgery, Sports Traumatology, Arthroscopy. 2020. DOI: 10.1007/s00167-020-06098-y
[9] Biplanar Reconstruction With Pectoralis Minor Tendon and Coracoacromial Ligament Transfer for Chronic Acromioclavicular Joint Dislocations. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103104
[10] Severe acromioclavicular joint osteoarthritis is associated with acromial stress fractures after reverse shoulder arthroplasty. JSES International. 2022. DOI: 10.1016/j.jseint.2021.11.008
[11] Factors Predicting the Outcome After Arthroscopically Assisted Stabilization of Acute High-Grade Acromioclavicular Joint Dislocations. The American Journal of Sports Medicine. 2019. DOI: 10.1177/0363546519862850
[12] Diagnostic value of a preoperative acromioclavicular injection for symptomatic acromioclavicular osteoarthritis: a retrospective study of cross-sectional midterm outcomes. Clinics in Shoulder and Elbow. 2024. DOI: 10.5397/cise.2023.00073
[13] Current Concepts in the Operative Management of Acromioclavicular Dislocations: A Systematic Review and Meta-analysis of Operative Techniques. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518795147
[14] The relationship of the acromion to the distal clavicle in normal and symptomatic degenerated acromioclavicular joints. Archives of Orthopaedic and Trauma Surgery. 2019. DOI: 10.1007/s00402-019-03258-9
[15] Acromioclavicular Joint Arthroscopy and Debridement. Techniques in Shoulder & Elbow Surgery. 2008. DOI: 10.1097/bte.0b013e31816276cb
[17] Limited distal clavicle excision of acromioclavicular joint osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2016.01.008
[18] Osteoarthrosis of the acromioclavicular joint, an underestimated cause of shoulder pain. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80122-4
[19] Editorial Commentary: Why We Have To Respect The Anatomy In Acromioclavicular Joint Surgery And Why Clinical Shoulder Scores Might Not Give Us The Information We Need!. Arthroscopy. 2019. DOI: 10.1016/j.arthro.2019.01.038
[21] Free Tissue Graft Reconstruction of the Acromioclavicular Joint. Techniques in Shoulder & Elbow Surgery. 2008. DOI: 10.1097/bte.0b013e31818a5dd9
[22] Improved identification of unstable acromioclavicular joint injuries in a clinical population using the acromial center line to dorsal clavicle radiographic measurement. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.12.014
[23] Isolated acromioclavicular osteoarthritis and steroid injection. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00311
[24] Surgical treatment of acromioclavicular dislocation: A review of 39 patients. Injury. 1983. DOI: 10.1016/0020-1383(83)90092-x
[25] Aaos Comprehensive Orthopaedic Review 3. Disorders of the Acromioclavicular Joint > III. Atraumatic and Degenerative Conditions of the AC Joint.
[26] Osteoarthritis after rotator cuff repair: A 10-year follow-up study. Orthopaedics & Traumatology: Surgery & Research. 2017. DOI: 10.1016/j.otsr.2017.03.007
[27] Versorgung der Schultereckgelenksprengung mittels akromioklavikulärer und korakoklavikulärer FiberWire®-Cerclage. Zeitschrift für Orthopädie und Unfallchirurgie. 2008. DOI: 10.1055/s-2008-1038577
[29] A Novel and Reproducible Anterior Portal for Arthroscopic Distal Clavicle Excision. Techniques in Shoulder & Elbow Surgery. 2014. DOI: 10.1097/bte.0000000000000033
[30] Aaos Comprehensive Orthopaedic Review 3. Disorders of the Acromioclavicular Joint > II. Traumatic Conditions of the AC Joint.
[31] Preoperative Factors Associated With Subsequent Distal Clavicle Resection After Rotator Cuff Repair. Orthopaedic Journal of Sports Medicine. 2019. DOI: 10.1177/2325967119844295
[33] Mid- to long-term success rate and functional outcomes of acromioclavicular injections in patients with acromioclavicular osteoarthritis. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00031
[34] Is Arthroscopic Distal Clavicle Resection Necessary for Patients With Radiological Acromioclavicular Joint Arthritis and Rotator Cuff Tears?. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514547254
[35] Successful Conservative Therapy in Rockwood Type V Acromioclavicular Dislocations. Orthopaedic Journal of Sports Medicine. 2015. DOI: 10.1177/2325967115s00017
[36] Painful Conditions of the Acromioclavicular Joint. Journal of the American Academy of Orthopaedic Surgeons. 1999. DOI: 10.5435/00124635-199905000-00004
[38] No differences between conservative and surgical management of acromioclavicular joint osteoarthritis: a scoping review. Knee Surgery, Sports Traumatology, Arthroscopy. 2021. DOI: 10.1007/s00167-020-06377-8
[43] Coracoid or Clavicle Fractures Associated With Coracoclavicular Ligament Reconstruction. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211036713
[44] Nanoscopic Distal Clavicle Resection. Arthroscopy Techniques. 2022. DOI: 10.1016/j.eats.2021.12.006
[45] Can an acute high-grade acromioclavicular joint separation be reduced and stabilized without surgery? A surgeon’s experience. Archives of Orthopaedic and Trauma Surgery. 2020. DOI: 10.1007/s00402-020-03630-0
[46] Arthroscopic Coracoclavicular Fixation Using Multiple Low‐Profile Devices in Acute Acromioclavicular Joint Dislocation. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.07.007
[49] The ligamentous injury pattern in acute acromioclavicular dislocations and its impact on clinical and radiographic parameters. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.10.026
[50] All‐Arthroscopic Weaver‐Dunn‐Chuinard Procedure With Double‐Button Fixation for Chronic Acromioclavicular Joint Dislocation. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.08.008
[51] Primary and Revision Acromioclavicular Joint Reconstruction. Techniques in Shoulder and Elbow Surgery. 2006. DOI: 10.1097/00132589-200603000-00004
[53] Complications after operative treatment of high-grade acromioclavicular injuries. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2023.03.019
[55] Endoscopically assisted reconstruction of acute acromioclavicular joint dislocation using a synthetic ligament. Outcomes at 12 months. Orthopaedics & Traumatology: Surgery & Research. 2011. DOI: 10.1016/j.otsr.2010.10.004
[56] Acute grade III and IV acromioclavicular dislocations: Outcomes and pitfalls of reconstruction procedures using a synthetic ligament. Orthopaedics & Traumatology: Surgery & Research. 2010. DOI: 10.1016/j.otsr.2010.06.004
[59] The Function of the Acromioclavicular and Coracoclavicular Ligaments in Shoulder Motion. The American Journal of Sports Medicine. 2012. DOI: 10.1177/0363546512458571
[60] Acromioclavicular joint ligamentous system contributing to clavicular strut function: a cadaveric study. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2013.01.004
[63] Arthroscopic resection of the acromioclavicular joint. The American Journal of Sports Medicine. 1993. DOI: 10.1177/036354659302100113
[64] The source of shoulder pain in rheumatoid arthritis: Usefulness of local anesthetic injections. Journal of Shoulder and Elbow Surgery. 1994. DOI: 10.1016/s1058-2746(09)80111-0
[81] Primary Stability of an Acromioclavicular Joint Repair Is Affected by the Type of Additional Reconstruction of the Acromioclavicular Capsule. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518807908
[86] A cadaveric study examining acromioclavicular joint congruity after different methods of coracoclavicular loop repair. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1016/s1058-2746(03)00050-8
[88] Anatomical Nuance and Relevance: Reflections on the Trapezius and Acromioclavicular Joint Stability. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.25.01392
[92] Histologic and magnetic resonance image evaluation in acromioclavicular joint osteoarthritis. JSES International. 2020. DOI: 10.1016/j.jseint.2020.03.007
[95] Early and delayed acromioclavicular joint reconstruction provide equivalent outcomes. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.06.026
[101] Concomitant open distal clavicle excision is associated with greater improvement in range of motion without increased risk of acromial stress fracture after reverse total shoulder arthroplasty: a retrospective cohort study. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2023.00465
[112] Effect of Acromioclavicular Joint Injuries on the Acromioclavicular Joint Complex and Scapulohumeral Rhythm: A Functional and Mechanical Perspective. Journal of the American Academy of Orthopaedic Surgeons. 2025. DOI: 10.5435/jaaos-d-24-00360
[114] Arthroscopic surgery for the throwing injury of the shoulder department of orthopaedic surgery school of medicine, fukuoka university. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80521-0
[115] The usefulness of distal clavicle resection for acromioclavicular joint disease. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80520-9
[116] Open reduction and internal fixation for fractures of the proximal humerus by rush pin and wire. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80523-4
[117] Natural history of rotator cuff tear using the evaluation of MR imaging. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80522-2
[121] Arthroscopic resection of the distal clavicle with a superior approach. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(10)80007-2
[122] Acromioclavicular joint injuries: diagnosis, classification and ligamentoplasty procedures. EFORT Open Reviews. 2018. DOI: 10.1302/2058-5241.3.170027
[123] Complications of the treatment of the acromioclavicular and sternoclavicular joint injuries, including instability. Clinics in Sports Medicine. 2003. DOI: 10.1016/s0278-5919(02)00102-3