Bakit iminungkahi ang operasyong ito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyon na hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Sa iyong appointment, kumukuha kami ng history, sinusuri ang iyong kamay, at nagsasaayos ng imaging kung kinakailangan upang kumpirmahin ang diagnosis.
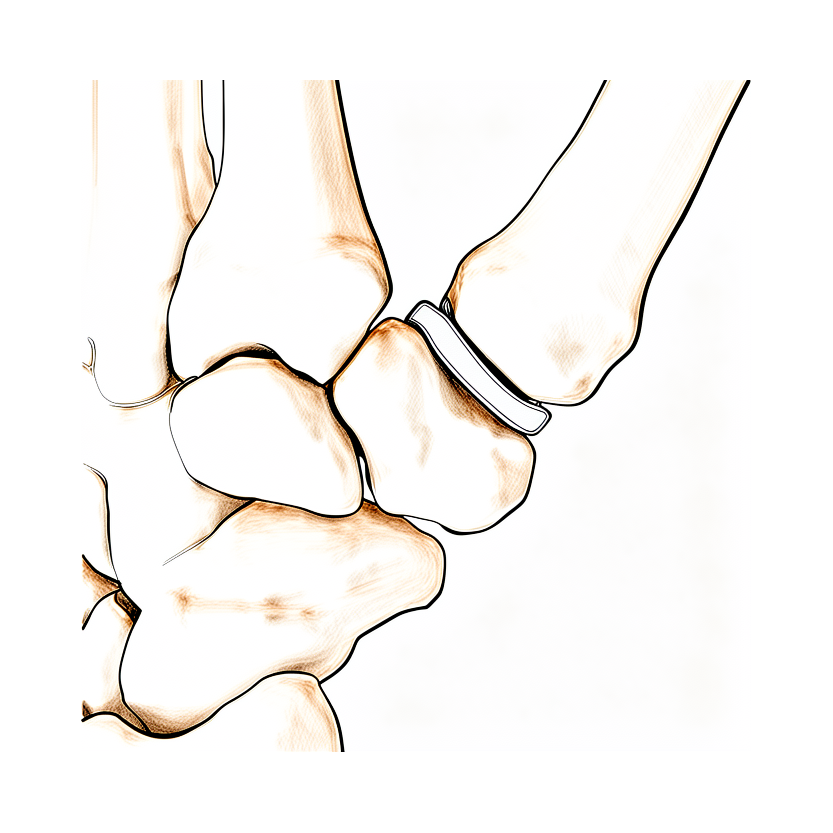
Pinapalitan ng operasyong ito ang gasgas na ibabaw ng isang maliit na joint ng isang makinis at hinubog na piraso ng carbon. Karaniwan itong inaalok para sa matagal nang arthritis na hindi humupa sa pagbabago sa aktibidad, hand therapy, o splinting. Karaniwan naming sinusubukan muna ang non-operative care at isinasaalang-alang ang operasyon kapag hindi ito nagbigay ng sapat na pagbuti. Para sa ilang problemang istruktural, maaaring irekomenda kaagad ang operasyon.
Layunin ng operasyon na maibsan ang sakit habang pinapanatiling gumagalaw ang joint. Layunin din nitong mapanatili ang natural na taas ng thumb at ang lakas ng pinch at grip. Para sa joint ng thumb sa base, 91% ng mga implant ay maayos pa ring gumagana sa medium-term follow-up. Pag-uusapan namin ang opsyong ito kasama ka at sabay naming pagpapasyahan kung angkop ito sa iyong kamay at sa iyong mga layunin.
Bago ang operasyon
Sa loob ng pitong oras bago ang iyong operasyon, huwag kumain o uminom ng anuman. Humihingi kami ng pitong oras sa halip na anim upang maaaring mapaaga ang iyong operasyon kung maagang umusad ang listahan sa theatre. Sasabihin sa iyo ng iyong surgeon kung alin sa iyong mga karaniwang gamot ang ihihinto at kailan, at makatutulong na magdala ng nakasulat na listahan ng lahat ng iyong iniinom. Mag-ayos ng maghahatid sa iyo pauwi pagkatapos, at magsuot ng maluwag at komportableng damit. Karaniwang X-ray lamang ang kailangan namin upang maplano ang operasyon, bagaman minsan ay ginagamit din ang MRI o ultrasound scan. Kung mayroon kang iba pang kondisyong medikal, maaaring kailanganin mo ng blood test o pagsusuri kasama ang anaesthetist, ang doktor na nagbibigay ng anaesthetic. Karamihan sa mga pasyente ay hindi nangangailangan ng alinman sa dalawa.
Sa araw ng operasyon
Pupunta ka sa surgical admissions unit ng ospital, kung saan ikaw ay i-che-check in at ihahanda para sa theatre. Makikipagkita ka sa anaesthetist, ang doktor na nangangalaga sa iyong anaesthetic. Ang operasyong ito ay ginagawa sa ilalim ng general anaesthetic. Ikaw ay tulog na tulog sa panahon ng operasyon. Ang ilang mga pasyente ay maaaring sumailalim din sa regional nerve block para sa pagpapaginhawa ng sakit pagkatapos ng operasyon; ang anaesthetist ang magpapasya sa araw na iyon base sa iyong indibidwal na kalagayan.
Pagkatapos ay dadalhin ka sa operating theatre, kung saan isasagawa ang operasyon. Pagkatapos nito ay magigising ka sa recovery area, kung saan babantayan ka ng mga nurse habang nawawala ang bisa ng anaesthetic. Kapag ikaw ay stable na, dadalhin ka sa ward o uuwi ka na, depende sa procedure at kung paano ang iyong paggaling.
Ano ang kinapapalooban ng operasyon
Gagawa ang iyong surgeon ng isang hiwa sa ibabaw ng bahagi ng iyong kamay na inooperahan. Sa pamamagitan ng bukasang ito, tinatanggal nila ang mga gasgas at napinsalang ibabaw ng joint. Kapalit ng mga gasgas na ibabaw, naglalagay sila ng makinis at hinubog na piraso ng carbon na nakaupo sa pagitan ng mga buto. Ang spacer na ito ang pumapalit sa trabaho ng gasgas na ibabaw ng joint, upang dumulas nang makinis ang mga buto sa halip na magkiskisan.
Para sa joint ng thumb sa base ng iyong kamay, pinapanatili ng iyong surgeon ang natural na taas ng thumb sa pamamagitan ng paglalagay ng spacer sa pagitan ng mga buto. Pagkatapos ay kinukumpuni at sinusuportahan ang joint upang gumaling ito sa magandang posisyon. Maaaring panatilihing hindi gumagalaw ang iyong thumb sa tuwid na posisyon habang gumagaling ito.
Ang hiwa ay isinasara gamit ang mga tahi. Nilalagyan ng dressing ang sugat, at sasabihin sa iyo ng aming team kung paano ito alagaan sa mga unang araw.
Pagkatapos ng operasyon
Karamihan sa mga pasyente ay nananatili ng isang gabi sa ospital pagkatapos ng operasyong ito, bagaman ang ilan ay nakakauwi sa mismong araw. Magigising ka sa recovery area, pagkatapos ay ililipat sa ward. Pananatilihin kang komportable ng mga nars at bibigyan ka ng gamot sa sakit kung kailangan mo. Ang iyong kamay ay nasa dressing at splint, na nagpoprotekta sa operasyon habang ito ay gumagaling. Maaari kang bumangon sa kama at gumalaw-galaw sa sandaling pakiramdam mo ay matatag ka na. Mangyaring mag-ayos ng sasama sa iyo sa unang 24 oras sa bahay. Iniiwan namin ang dressing sa loob ng humigit-kumulang 10 araw; mangyaring huwag itong tanggalin bago ang panahong iyon maliban kung sinabi namin sa iyo. Papalitan o tatanggalin namin ito kapag nakita ka namin.
Paggaling
Asahan ang kaunting sakit at pamamaga sa iyong kamay sa mga unang araw at linggo. Normal itong bahagi ng paggaling at unti-unting humuhupa. Nakatutulong ang pagpapanatiling nakataas ng iyong kamay kapag nagpapahinga, at ang gamot sa sakit na ibinibigay namin ay magpapagaan sa hindi komportableng pakiramdam. Napapansin ng karamihan na maagang lumilipas ang pinakamatinding sakit, at patuloy na bumubuti ang ginhawa mula roon.
Ang iyong kamay ay nasa dressing at splint, na nagpoprotekta sa joint habang ito ay gumagaling. Iniiwan namin ang dressing sa loob ng humigit-kumulang 10 araw at papalitan o tatanggalin namin ito kapag nakita ka namin. Ang rehabilitasyon pagkatapos ng operasyon sa kamay ay hand therapy, hindi physiotherapy. Ang hand therapy pagkatapos ng operasyon ay kasama si Ruby Doolan sa Extend Rehabilitation. Si Ruby ay isang hand therapist: gagabayan niya ang iyong mga ehersisyo at gagawin ang anumang splint na kailangan mo habang gumagaling ang iyong kamay. Sa simula, banayad ang mga ehersisyo at nakatuon sa pagpapanatiling mababa ang pamamaga. Habang bumabalik ang paggalaw, unti-unting dinadagdagan ang mga ito upang maibalik ang pagbaluktot, pagtuwid at grip.
Magagawa mo ang magagaang pang-araw-araw na gawain sa bahay sa loob ng mga limitasyon ng iyong splint. Hindi ka makakahawak nang mahigpit, makakaipit (pinch) o makakapagbuhat gamit ang inoperahang kamay habang ito ay pinapanatiling hindi gumagalaw. Kapag natanggal na ang splint at binigyan ka na ng clearance ng iyong surgeon, maaari mo nang simulang gamitin ang kamay nang mas normal, at maaaring sumunod ang pagmamaneho. Tingnan ang aming pahina sa Pagmamaneho pagkatapos ng operasyon sa upper limb para sa mga detalye.
Iba-iba ang paggaling ng bawat indibidwal. Maaaring iba ang iyong timeline, at gagabayan ka ng iyong surgeon at therapist sa bawat hakbang.
Ano ang maaaring maging problema
Karamihan sa mga pasyente ay gumagaling nang maayos, ngunit paminsan-minsan ay maaaring magkaroon ng mga problema. Binabantayan kayo nang maigi ng inyong surgeon at ng team upang maagang matukoy ang anumang isyu.
Minsan ay lumilipat ng posisyon ang implant o lumulubog ito sa buto. Maaari mong mapansin ang bagong sakit sa joint, pakiramdam na hindi tuwid ang pagkakaupo ng daliri o thumb, o pagbabago sa kung paano ito gumagalaw. Kung mapansin mo ang alinman sa mga ito, banggitin ito sa iyong susunod na review.
Maaari ring lumuwag ang implant. Karaniwan itong nararamdaman bilang sakit na bumabalik pagkatapos ng mahabang panahon ng pagbuti, kadalasang mas malala kapag humahawak ka nang mahigpit o nag-iipit (pinch). Sabihin sa iyong surgeon kung mangyari ito.
Maaaring manigas ang joint. Maaaring hindi na bumaluktot o tumuwid ang daliri o thumb nang kasinlayo ng dati, at maaaring dumikit dahil sa peklat na tissue ang tendon sa likod ng joint. Banggitin ito sa iyong review upang maiayos ng iyong therapist ang iyong mga ehersisyo.
Maaaring maging hindi matatag (unstable) ang joint o maaaring bumalik ang orihinal na deformity. Maaari mong makitang muling lumilihis sa linya ang daliri. Banggitin ito sa iyong susunod na appointment.
Hindi karaniwan ang impeksyon ngunit nangangailangan ito ng mabilis na atensyon. Tumawag sa klinika sa mismong araw kung ikaw ay may lagnat, kumakalat na pamumula sa paligid ng sugat, o likido o nana na tumatagas mula rito. Ang sakit na patuloy na lumalala sa kabila ng iyong mga gamot sa sakit ay nangangahulugan din na dapat kang tumawag sa klinika sa mismong araw.
Maaaring mairita o mapinsala ang mga kalapit na istruktura sa ganitong uri ng operasyon. Maaaring maging sensitibo ang isang nerve malapit sa thumb, na nagdudulot ng pangingilig o pagbabago sa pakiramdam ng balat. Maaaring maapektuhan ang artery sa gilid ng pulso na nasa panig ng thumb, o ang isang tendon sa harap ng pulso. Kung mapansin mo ang pamamanhid o hindi mo maigalaw ang iyong mga daliri kapag nawala na ang bisa ng nerve block, sa humigit-kumulang 24 oras, tumawag sa klinika. Inaasahan ang pamamanhid at panghihina sa unang 24 oras pagkatapos ng nerve block.
Paminsan-minsan ay maaaring mabali ang isang buto sa kamay habang o pagkatapos ng operasyon. Nagdudulot ito ng biglaang sakit at pamamaga. Tumawag sa klinika kung mangyari ito.
Kung pumalya ang isang implant at hindi na ito maisasalba, may iba pang operasyon na makatutulong. Maaaring tanggalin ang implant at gamutin ang joint sa ibang paraan, na maaasahang nagpapaginhawa sa sakit. Sa mga bihirang kaso, maaaring i-fuse ang joint, ibig sabihin ay permanente itong paninigasin, o maaaring kailanganing tanggalin ang daliri.
Ang complications table sa pahinang ito ay naglilista ng mga tipikal na rate kung nais mo ang mga detalye.
Kailan dapat tumawag sa amin
Karamihan sa mga problema ay lumilitaw nang maaga, at mas madaling maayos ang mga ito kung kikilos agad. Tumawag sa klinika sa mismong araw kung ikaw ay may lagnat, kumakalat na pamumula sa paligid ng sugat, o likido o nana na tumatagas mula rito. Tumawag din sa klinika sa mismong araw kung patuloy na lumalala ang sakit sa kabila ng iyong mga gamot sa sakit. Tumawag sa klinika kung mapansin mo ang pamamanhid o hindi mo maigalaw ang iyong mga daliri kapag nawala na ang bisa ng nerve block, sa humigit-kumulang 24 oras. Inaasahan ang pamamanhid at panghihina sa unang 24 oras pagkatapos ng nerve block.
Pumunta sa emergency department kung may pamamaga o sakit sa iyong binti (calf), o kung ikaw ay hinihingal o may pananakit ng dibdib. Maaaring ito ay mga senyales ng namuong dugo (blood clot). Pumunta sa emergency department kung ang iyong mga daliri, kamay o thumb ay naging maputla, malamig, puti, asul o madilim ang kulay. Maaaring ito ay problema sa sirkulasyon.
Kung hindi mo makontak ang klinika, sa labas ng oras ng klinika o sa weekend, pumunta sa pinakamalapit na emergency department.
Saan maaaring magbasa nang higit pa tungkol sa kondisyon
Ang pahinang ito ay tungkol sa operasyon mismo. Ang kondisyong ginagamot nito, kabilang ang kung ano ang ipinapakita ng ebidensya tungkol sa kung kailan nakatutulong ang operasyon at kung kailan hindi, ay tinalakay nang mas detalyado sa pahinang Basal Thumb Arthritis.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a study with minimum 8-year follow-up [1].
- Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate [4].
- The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition [6].
- The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis [7].
- Arthroplasty is recommended for patients with post-trauma painful PIP joints [8].
- Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years [9].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity [10].
- The results of pyrolytic carbon PIPJ arthroplasty in review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
- A study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs was conducted [11].
- The PyroDisk interposition arthroplasty confirmed good 5-year clinical results [12, 13].
- PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis [15].
- All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty [16].
- The encouraging mid-term clinical results of the interposition implant (APSI) in the context of proximal pole scaphoid pseudarthrosis make this technique a proven alternative, without precluding a definitive therapeutic option in case of failure [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Anatomy & Pathophysiology
Bony Anatomy
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [28].
- The radial ray or first ray is the shortest, made up of only three bones: a metacarpal and two phalanges [28].
- The trapezium is clearly angled out in front of the carpal plane so that the first metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [28].
- The thumb metacarpal is the shortest, while the index metacarpal is by far the longest [28].
- The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal, whereas they are located at the distal ends of the other metacarpals [28].
- The thumb metacarpal is independent and articulates with the trapezium [35].
- The index metacarpal is the most firmly fixed [35].
- The ring metacarpal has about 10 degrees of mobility in flexion and extension [35].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [35].
Soft Tissue & Vascular Anatomy
- The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [27].
- The first (most radial) compartment contains the abductor pollicis longus and the extensor pollicis brevis [27].
- The second extensor compartment contains the extensor carpi radialis longus and the extensor carpi radialis brevis [27].
- The third compartment contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [27].
- The fourth extensor compartment contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [27].
- The fifth compartment contains the extensor digiti quinti [27].
- The sixth compartment contains the extensor carpi ulnaris tendon, which inserts at the base of the little finger metacarpal [27].
- The extrinsic finger flexors are the flexor digitorum profundus and the flexor digitorum superficialis [27].
- The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx [27].
- The flexor digitorum superficialis acts as a flexor of the proximal interphalangeal and metacarpophalangeal joints [27].
- There are seven interosseous muscles, four dorsal and three volar [32].
- The dorsal interossei are abductors [32].
- The volar interossei are adductors [32].
- The middle finger has two dorsal interossei (abductors) and no volar interossei (adductors) because the central axis of the hand lies within it [32].
- The "princeps pollicis" artery is the terminal branch of the radial artery and crosses the first intermetacarpal space [36].
- The princeps pollicis runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [36].
- The princeps pollicis divides into two terminal rami, namely the collateral palmar arteries of the thumb, at the level of the cutaneous flexion crease of the metacarpophalangeal joint [36].
- An arcade located deep in the flexor tendon joins together the two arteries at the level of the distal metaphysis of the first phalanx [36].
- The dorsal arteries of the thumb originate from the palmar arteries (princeps, commissural or anastomoses of the superficial arcade) at the level of the first metacarpal [36].
Functional Mechanics
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration [28].
- The thumb ray is more mobile, shorter, and more proximal than the other rays, allowing it to project in front of the plane of the palm to oppose itself to the other four rays [28].
- The skeleton of the hand presents a longitudinal and transverse concavity, giving it the shape of a cup with a palmar concavity when the thumb is placed next to the index finger [28].
- The transverse axis of the palm forms an acute angle of approximately 75 degrees with the longitudinal axis [28].
- The metacarpal arch is endowed with a great deal of adaptability because of the mobility of the peripheral metacarpals [35].
- The heads of the second and third metacarpals are fixed [35].
- The mobility of the ulnar metacarpals allows "flexion" of 10 degrees for the fourth metacarpal, and "flexion" of 20 degrees for the fifth metacarpal [35].
- The keystones of the longitudinal arches are the metacarpophalangeal articulations, whose thick anterior glenoid capsules, the volar plates, prevent hyperextension [35].
- The dorsal skin slides distally to allow metacarpophalangeal joint flexion [40].
- Interphalangeal flexion is accomplished by means of a special arrangement of skin folds on the dorsum of each articulation [40].
- The gliding mechanism for tendons in narrow crowded areas is assured by the synovial sheath, which allows a considerable amplitude of movement [40].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [40].
- The position of each articulation depends on the equilibrium of forces acting at that level, and this equilibrium is subject to the position of the immediately proximal articulation [40].
- Single articular movements around a fixed perpendicular axis simply do not exist in the hand [40].
- Almost all movements in the hand are around oblique and variable axes, resulting in combined movements permitting optimal orientation of the phalanges at the time of prehension [40].
Indications and Disease Staging
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan resurfacing implant is a valid option for treating scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- The pyrocarbon implant is indicated for the treatment of STT arthrosis [15].
- The pyrocarbon interposition implant (APSI) is an alternative for the treatment of proximal pole scaphoid pseudarthrosis [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT osteoarthritis who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Patient Selection and Demographics
- Active patients under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint are candidates for anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation [9].
- Pyrocarbon disc interposition is used for the treatment of CMC1 osteoarthritis grade 2 to 3 [11].
- Total trapezectomy associated with the placement of a NuGrip pyrocarbon implant is a procedure for the replacement of the TMC joint [22].
Comparative Classification and Efficacy
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
Clinical Presentation
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal osteoarthritis [1].
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan implant is used for trapeziometacarpal osteoarthritis [4].
- The Pyrocardan implant is used for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant is used for advanced trapeziometacarpal arthritis [6].
- The Pyrocardan resurfacing implant is used for scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- Pyrocarbon PIP arthroplasty is used for post-trauma painful joints [8].
- Anatomic pyrolytic carbon resurfacing hemiarthroplasty is used for Eaton-Littler stage III osteoarthritis of the thumb CMC joint in patients under 65 years of age [9].
- Pyrolytic carbon implants are used for proximal interphalangeal joint (PIPJ) arthroplasty [10].
- Pyrocarbon disc interposition is used for CMC1 osteoarthritis grade 2 to 3 [11].
- PyroDisk interposition arthroplasty is used for trapeziometacarpal osteoarthritis [12].
- PyroDisk interposition is indicated for patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The pyrocarbon implant is used for STT arthrosis [15].
- Pyrolytic interpositional arthroplasty is used for TMC arthritis [16].
- Pi2 pyrocarbon spacer arthroplasty is used for carpometacarpal joint osteoarthritis [17].
- The interposition implant (APSI) is used for pseudarthrosis of the proximal pole of the scaphoid [18].
- A pyrocarbon implant is used for Kienböck disease [19].
- Total trapeziectomy associated with the placement of a pyrocarbon type Nugrip implant is used after replacement of the TMC joint [22].
- The Pyrocardan implant is used for stage 2 trapeziometacarpal osteoarthritis [23].
- The Pi2 pyrocarbon implant is used in total trapeziectomy and suspension ligamentoplasty [24].
- The Pi2 pyrocarbon implant is used in destructions of the capitolunate joint space [25].
Investigations
- Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [26].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining hand pathology but can be expensive, time-consuming, and often nonspecific [26].
- A systematic method to approaching the physical examination of the hand is essential due to the number of structures in a small space [26].
Treatment
Trapeziometacarpal Joint Osteoarthritis
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a minimum 8-year follow-up study [1].
- Partial trapeziectomy with pyrocarbon arthroplasty provides excellent pain relief and high patient satisfaction for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis that can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate for trapeziometacarpal osteoarthritis [4].
- Long-term follow-up data for pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 is available in a study involving more than 150 thumbs [11].
- Interposition arthroplasty with PyroDisk confirmed good 5-year clinical results [12, 13].
- The modified procedure of partial trapeziectomy and pyrocarbon interpositional arthroplasty improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength [29].
- Pyrocarbon interposition arthroplasty for trapeziometacarpal osteoarthritis does not preclude subsequent conventional arthroplasty techniques in the event of failure [23].
Scaphotrapeziotrapezoid Joint Osteoarthritis
- The Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis, evidenced by good functional and radiographic outcomes and the absence of surgical complications [7].
- The good results, simple surgical procedure, absence of complications, and lack of need for fixation or ligamentoplasty confirm the advantages of the pyrocarbon implant in the treatment of STT arthrosis [15].
Other Indications
- Pyrocarbon PIP arthroplasty is recommended for post-trauma painful joints [8].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure with the potential to achieve pain relief, stability, satisfactory ROM, and correction of deformity, though results were unpredictable and may not be superior to other methods of arthroplasty [10].
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis, especially in opposition with a mean Kapandji score of 9.60, with no major aggravation of metacarpophalangeal extension [17].
- The interposition implant (APSI) for proximal scaphoid pseudarthrosis provides encouraging mid-term clinical results and serves as a proven alternative without precluding a definitive therapeutic option in case of failure [18].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant, and the average grip strength was 76.5% of the contralateral side [19].
Complications
- The Pyrocardan implant has a high complication rate [4].
- The Pyrocardan resurfacing implant for STT osteoarthritis was associated with the absence of surgical complications [7].
- The pyrocarbon implant for STT arthrosis was associated with the absence of complications [15].
Recovery
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty, especially in opposition, with a mean Kapandji score of 9.60 [17].
- There was no major aggravation of metacarpophalangeal extension following Pi2 pyrocarbon spacer arthroplasty [17].
- The average grip strength was 76.5% of the contralateral side after pyrocarbon implant treatment for Kienböck disease [19].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant [19].
Key Evidence
- [L4] Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity. [1] (10.1177/1753193420906805)
- [L3] Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction. [2] (10.1177/1753193413519384)
- [L4] PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint. [3] (10.1097/bth.0b013e318271aab7)
- [L4] The study concludes that the Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate. [4] (10.1016/j.hansur.2016.09.004)
- [L4] The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray. [5] (10.1016/j.hansur.2018.10.044)
- [L4] The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition. [6] (10.1016/j.jhsa.2014.07.011)
- [L3] The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan1 resurfacing implant is a valid option for treating STT osteoarthritis. [7] (10.1016/j.hansur.2017.01.003)
- [L4] We recommend arthroplasty for this group of patients. [8] (10.1016/s0363-5023(03)80384-2)
- [L3] Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years. [9] (10.1142/s2424835518500443)
- [L4] The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty. [10] (10.1016/j.jhsa.2006.02.018)
- [L4] This is the first study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs. [11] (10.1016/j.jhsa.2018.06.086)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [12] (10.1177/1558944716660555n)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [13] (10.1177/1558944716660555m)
- [L4] PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous. [14] (10.1177/1753193420981552)
- [L4] The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis. [15] (10.1016/j.main.2005.04.010)
- [L3] All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty. [16] (10.1155/2019/7961507)
- [L3] Range of motion improved, especially in opposition (mean Kapandji score, 9.60), with no major aggravation of metacarpophalangeal extension. [17] (10.1016/j.hansur.2016.05.002)
- [L4] Les résultats cliniques encourageants à moyen terme de l’implant d’interposition (APSI), dans le cadre d’une pseudarthrose du pôle proximal du scaphoïde, font de cette technique une alternative probante, sans interdire une option thérapeutique définitive en cas d’échec. [18] (10.1016/j.main.2011.10.031)
- [L5] There were no changes in range of motion after surgery and the average grip strength was 76.5% of the contralateral side. [19] (10.1016/j.main.2014.09.002)
- [Case_report] The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis. [20] (10.1016/j.jhsg.2026.100964)
- [L4] La trapézectomie totale associée à la mise en place d'un implant en pyrocarbone type Nugrip après le remplacement de l'articulation TMC semble être une procédure attrayante. [22] (10.1016/j.hansur.2018.10.166)
- [L3] Il ne coupe pas les ponts en cas d'éventuel échec à des techniques d'arthroplastie plus conventionnelles. [23] (10.1016/j.main.2011.10.132)
- [L3] The implant Pi2 seems to contribute keeping trapezial height, without functional advantages and with a risk of dislocation. [24] (10.1016/j.main.2013.04.003)
- [L4] Cette technique a l'avantage de préserver les mobilités médio-carpiennes et les ligaments extrinsèques du poignet. [25] (10.1016/j.hansur.2016.10.125)
- [L4] The modified procedure improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength. [29] (10.1177/1753193414553368)
References
[1] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420906805
[2] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413519384
[3] PyroCarbon Implant Hemiarthroplasty for Trapeziometacarpal Arthritis. Techniques in Hand & Upper Extremity Surgery. 2013. DOI: 10.1097/bth.0b013e318271aab7
[4] Early outcomes of Pyrocardan® implants for trapeziometacarpal osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.09.004
[5] L’implant en Pyrocarbone (Pyrocardan®) dans le traitement de l’arthrose carpo-métacarpienne ulnaire post-traumatique. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.044
[6] Pyrocarbon Interposition (PyroDisk) Implant for Trapeziometacarpal Osteoarthritis: Minimum 5-Year Follow-Up. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.07.011
[7] Treatment of scaphotrapeziotrapezoid osteoarthritis with the Pyrocardan® implant: Results with a minimum follow-up of 2 years. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.01.003
[8] Pyrocarbon PIP arthroplasty for post trauma painful joints. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80384-2
[9] Anatomic Pyrocarbon Hemiarthroplasty for Thumb Carpometacarpal Osteoarthritis in Patients under 65 Years: Mid Term Results. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518500443
[10] Pyrolytic Carbon Proximal Interphalangeal Joint Resurfacing Arthroplasty. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.02.018
[11] Long-Term Follow-Up After Pyrocarbon Disc Interposition for Thumb CMC Osteoarthritis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.086
[12] Pyrocarbon Interposition Arthroplasty of the Trapeziometacarpal Joint With the PyroDisk. HAND. 2016. DOI: 10.1177/1558944716660555n
[13] PyroDisk Interposition Implant for Trapeziometacarpal Osteoarthritis. HAND. 2016. DOI: 10.1177/1558944716660555m
[14] Re: Smeraglia F, et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. J Hand Surg Eur. 2020, 45: 472–6. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/1753193420981552
[15] Traitement de l'arthrose S.T.T. par un Implant en pyrocarbone. Premiers résultats. Chirurgie de la Main. 2005. DOI: 10.1016/j.main.2005.04.010
[16] Tendon versus Pyrocarbon Interpositional Arthroplasty in the Treatment of Trapeziometacarpal Osteoarthritis. BioMed Research International. 2019. DOI: 10.1155/2019/7961507
[17] A ten-year prospective outcome study of Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.05.002
[18] Pseudarthrose du scaphoïde : résection proximale et interposition d’un implant en pyrocarbone, à propos de 20 cas. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.031
[19] Le traitement de la maladie de Kienböck par un implant en pyrocarbone : fait clinique. Chirurgie de la Main. 2014. DOI: 10.1016/j.main.2014.09.002
[20] Game, Set… Revision! A Case Report of a Tennis Player Who Smashed His Scaphotrapeziotrapezoid-Joint Pyrocardan Implant Twice. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.100964
[22] Reprise de prothèses totales trapézo-métacarpiennes par un implant en Pyrocarbone type NuGrip. À propos de 6 cas. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.166
[23] L’implant pyrocardan : interposition libre en pyrocarbone trapezometacarpienne pour l’arthrose de stade 2. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.132
[24] Trapézectomie totale et ligamentoplastie de suspension : une interposition par un implant Pi2® en pyrocarbone a-t-elle un intérêt ?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.04.003
[25] Utilisation de l’implant en pyrocarbone de type Pi2 dans les destructions de l’interligne articulaire capito-lunaire. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.125
[26] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[27] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[28] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[29] Re: Mariconda et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. J Hand Surg Eur. 2014, 39: 604–610. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414553368
[32] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[35] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[36] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[40] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.