Patients › Wrist
Wrist Arthroscopy
Diagnostic and therapeutic wrist arthroscopy — what it is, when it's used, and recovery.
Bakit iminungkahi ang operasyong ito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyong hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Sa iyong appointment, kumukuha kami ng maingat na history, sinusuri ang iyong pulso, at nag-aayos ng imaging kung kinakailangan upang malaman kung ano ang sanhi ng iyong pananakit.
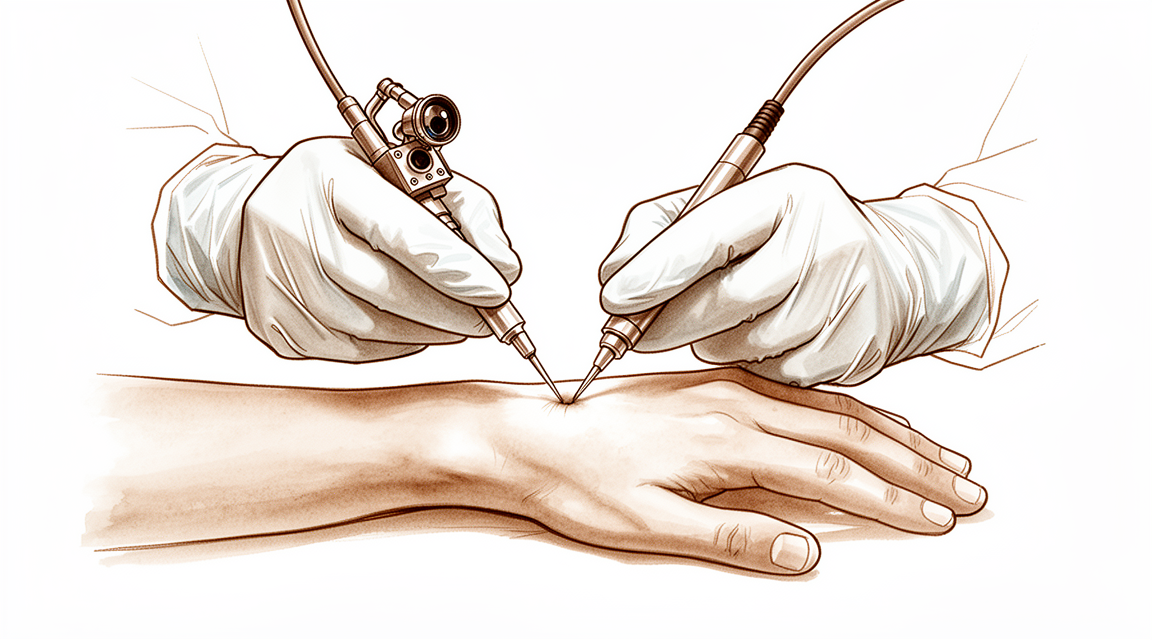
Ang wrist arthroscopy ay isang operasyon na gumagamit ng isang maliit na camera sa loob ng wrist joint upang masusing tingnan ang mga joint surface at mga soft tissue. Karaniwan namin itong iminumungkahi kapag ang pananakit ng pulso ay tumagal na ng higit sa 3 buwan, hindi gumaling sa non-operative care gaya ng pagbabago sa aktibidad, hand therapy, splinting o mga injection, at kapag ang mga scan at pagsusuri ay hindi nakapagbigay ng sapat na malinaw na sagot. Maaari rin itong irekomenda pagkatapos ng isang bali (fracture) o pinsala sa ligament, upang suriin ang mga joint surface at mga soft tissue at upang gamutin ang ilang problema nang sabay. Makatutulong din ang operasyon sa paninigas, sa ilang uri ng arthritis, at sa matagal nang problema sa ligament. Ang mga taong sumailalim sa operasyon dahil sa patuloy na pananakit ng pulso ay bumuti sa average na humigit-kumulang 50% pagkaraan ng isang taon, bagaman karamihan ay patuloy na nagkaroon ng kaunting pananakit at kapansanan. Ang pangunahing layunin ay mas kaunting pananakit, mas maayos na paggalaw at mas matatag na pulso, na pagpapasyahan natin nang magkasama.
Bago ang operasyon
Bibigyan ka ng iyong surgeon ng malinaw na mga tagubilin bago ang araw ng operasyon, at tinatalakay namin dito ang mga praktikal na detalye. Kakailanganin mong itigil ang pagkain at pag-inom simula pitong oras bago ang iyong operasyon. Humihingi kami ng pitong oras sa halip na ang karaniwang anim upang ang iyong operasyon ay maaaring mauna kung maagang matapos ang listahan sa theatre. Magdala ng listahan ng iyong kasalukuyang mga gamot, at sasabihin sa iyo ng iyong surgeon kung may anumang kailangang itigil pansamantala bago ang operasyon. Mag-ayos ng taong maghahatid sa iyo pauwi pagkatapos, at magsuot ng maluwag at komportableng damit. Ang imaging gaya ng X-ray, MRI o ultrasound ay nakatutulong sa pagpaplano ng operasyon, at karaniwan itong inaayos sa iyong appointment. Kung mayroon kang iba pang kondisyong medikal, maaaring kailanganin mo ng mga blood test o pagsusuri kasama ang anaesthetist.
Sa araw ng operasyon
Sa araw ng iyong operasyon, pupunta ka sa surgical admissions unit ng ospital. Doon ka iche-check in at ihahanda para sa theatre. Pagkatapos ay makikilala mo ang anaesthetist, ang doktor na nangangasiwa sa iyong anaesthetic at pain relief. Ang operasyong ito ay ginagawa sa ilalim ng general anaesthetic. Ikaw ay magiging tulog nang husto para sa operasyon. Ang ilang mga pasyente ay maaari ring sumailalim sa regional nerve block para sa pagpapaginhawa ng sakit pagkatapos ng operasyon; ang anaesthetist ang magpapasya sa araw na iyon base sa iyong indibidwal na kalagayan.
Pagkatapos ay dadalhin ka sa operating theatre, kung saan isasagawa ang operasyon. Kapag tapos na ito, magigising ka sa recovery area. Babantayan ka roon ng mga nurse habang nawawala ang bisa ng anaesthetic. Kapag stable ka na, pupunta ka sa ward o uuwi na, depende sa procedure at sa iyong paggaling.
Ano ang kinapapalooban ng operasyon
Ang wrist arthroscopy ay isang keyhole na operasyon. Gumagawa ang iyong surgeon ng ilang maliliit na hiwa sa paligid ng pulso, at isang maliit na camera ang ipinapasok sa isa sa mga ito upang makita sa isang screen ang loob ng joint. Habang isinasagawa ang operasyon, ang iyong braso ay pinananatiling matatag at ang iyong mga daliri ay marahang nakabitin sa mga soft finger trap, na may tuloy-tuloy na hila sa pulso na nagbubukas sa joint at lumilikha ng espasyo para makapagtrabaho. Salt water ang dumadaloy sa joint upang mapanatiling malinaw ang paningin.
Kapag nasa loob na ang camera, masusing matitingnan ng iyong surgeon ang mga joint surface at ang mga soft tissue, kabilang ang cartilage na bumabalot sa mga buto at ang mga ligament na humahawak sa maliliit na buto ng pulso upang manatiling magkakadikit. Ang susunod na mangyayari ay depende sa kung ano ang makikita. Maaaring tanggalin ang mga maluwag na piraso ng cartilage o buto. Ang inflamed na tissue na bumabalot sa loob ng joint ay maaaring tabasin. Ang isang cyst o makapal na banda ng tissue ay maaaring gamutin. Ang mga punit na ligament, kabilang ang triangular na cartilage sa panig ng hinliliit ng pulso, ay maaaring tabasin o kumpunihin. Kung may nabaling buto, ang mga piraso ay maaaring ihanay nang tumpak habang nakikita sa camera at i-secure gamit ang mga screw o pin habang gumagaling ang mga ito. Kung naninigas ang pulso pagkatapos ng isang pinsala o naunang operasyon, maaaring luwagan ang masikip na tissue upang muli itong makagalaw.
Sa pagtatapos, ang maliliit na hiwa ay isinasara gamit ang mga tahi. Nilalagyan ng dressing ang pulso, at ang iyong kamay ay karaniwang sinusuportahan ng isang benda o splint. Mananatili ang dressing nang mga 10 araw, at sasabihin namin sa iyo kung paano alagaan ang mga sugat habang naghihintay.
Pagkatapos ng operasyon
Magigising ka sa recovery area, kung saan babantayan ka ng mga nurse habang nawawala ang bisa ng anaesthetic. Karaniwan itong day case, kaya maaari kang makauwi sa mismong araw, bagaman paminsan-minsan ay nananatili ang mga pasyente nang magdamag. Ang iyong pulso ay may dressing, at ang iyong kamay ay maaaring sinusuportahan ng isang benda o splint. Hinahayaan naming nakakabit ang dressing sa loob ng humigit-kumulang 10 araw; mangyaring huwag itong tatanggalin bago ang panahong iyon maliban kung sinabi namin sa iyo. Papalitan o tatanggalin namin ito kapag nakita ka na namin. Ang iyong pain relief ay pinaplano para sa iyo bago ka umuwi; inumin ito ayon sa itinagubilin. Kung ikaw ay nagkaroon ng nerve block, inaasahan ang pamamanhid at panghihina sa unang 24 oras. Kapag nawala na ang bisa nito, sa humigit-kumulang 24 oras, tumawag sa klinika kung nananatiling manhid ang iyong mga daliri o hindi mo maigalaw ang mga ito. Mag-ayos ng taong makakasama mo sa unang 24 oras. Tumawag sa klinika sa mismong araw kung ikaw ay may lagnat, kumakalat na pamumula sa paligid ng sugat, likido o nana na tumatagas mula rito, o sakit na patuloy na lumalala sa kabila ng iyong mga gamot sa sakit. Pumunta sa emergency department kung ang iyong mga daliri o kamay ay naging maputla, malamig, puti, asul o madilim ang kulay, dahil maaaring ito ay problema sa sirkulasyon. Panatilihing nakataas ang iyong kamay kapag nagpapahinga upang makatulong na humupa ang pamamaga. Karamihan sa mga tao ay normal na nakakagalaw sa loob ng bahay mula sa araw ng operasyon; hindi mo kailangan ng bed rest.
Paggaling
Sa unang ilang araw, ang iyong pulso ay masakit at namamaga, at ang iyong mga daliri ay maaaring makaramdam ng paninigas. Ang pagpapanatiling nakataas ng iyong kamay kapag nagpapahinga ay nakatutulong upang humupa ang pamamaga. Inumin ang iyong pain relief ayon sa itinagubilin, at asahan na unti-unting mababawasan ang hindi komportableng pakiramdam habang lumilipas ang mga araw.
Karamihan sa mga tao ay normal na nakakagalaw sa loob ng bahay mula sa araw ng operasyon. Kakailanganin mo ng ibang tao na hahawak sa mabibigat na pagbubuhat at pagmamaneho sa simula. Kapag natanggal na ang anumang splint at kaya mo nang humawak ng manibela nang komportable, maaari ka nang magmaneho muli; ipinapaliwanag ito nang mas detalyado ng aming pahina tungkol sa pagmamaneho pagkatapos ng upper-limb surgery. Mananatili ang dressing nang mga 10 araw, at susuriin namin ang mga sugat kapag nakita ka na namin.
Malaking bahagi ng muling pagpapagalaw sa iyong pulso ang hand therapy. Ang iyong rehabilitasyon ay kasama si Ruby Doolan sa Extend Rehabilitation. Si Ruby ay isang hand therapist: gagabayan niya ang iyong mga ehersisyo at gagawa siya ng anumang splint na iyong kakailanganin sa proseso. Sa simula, nakatuon ito sa marahang paggalaw at pagkontrol sa pamamaga. Habang humuhupa ang pulso, unti-unting dinadagdagan ang mga ehersisyo hanggang sa paghawak nang mahigpit, pagbubuhat at paggamit ng iyong kamay sa mga pang-araw-araw na gawain. Sumusunod ang paggaling sa isang hakbang-hakbang na pattern, at patuloy na bumubuti ang magkakaugnay na paggalaw ng pulso at mga daliri habang lumilipas ang mga linggo.
Kung gaano kabilis ka makakabalik sa trabaho, sports o gym ay depende sa kung ano ang nakita at kinumpuni sa loob ng iyong pulso, at sa iyong trabaho at mga libangan. Ang iyong timeline ay maaaring iba sa iba; gagabayan ka namin at ng iyong therapist sa bawat yugto.
Ano ang maaaring maging problema
Karamihan sa mga pasyente ay gumagaling nang maayos, ngunit paminsan-minsan ay maaaring magkaroon ng mga problema. Binabantayan kayo nang maigi ng inyong surgeon at ng team upang maagapan ang anumang isyu.
Hindi karaniwan ang impeksyon pagkatapos ng operasyong ito, ngunit mahalaga ito kapag nangyari. Tumawag sa klinika sa mismong araw kung kayo ay may lagnat, kumakalat na pamumula sa paligid ng sugat, o likido o nana na tumatagas mula rito. Tumawag din sa klinika sa mismong araw kung patuloy na lumalala ang sakit sa kabila ng inyong mga gamot sa sakit. Sa isang malubhang impeksyon sa kalaliman ng pulso, kung minsan ay kinakailangan ang karagdagang operasyon, at ito ay napakabihira.
Ang mga finger trap na humahawak sa inyong mga daliri habang isinasagawa ang operasyon ay maaaring mag-iwan ng pananakit sa mga kasukasuan ng inyong mga daliri pagkatapos, o makabugbog sa soft tissue o sa maliliit na nerve sa isang daliri. Sa karamihan ng kaso, kusa itong nawawala. Banggitin ito sa inyong susunod na review kung masakit pa rin o kakaiba ang pakiramdam ng isang daliri.
Ang fluid na ginagamit upang punuin ang joint habang isinasagawa ang operasyon ay paminsan-minsang maaaring tumagas sa mga tissue ng forearm. Bantayan ang pamamaga sa forearm na mabilis na tumataas, kasabay ng paninikip at sakit na patuloy na lumalala. Tumawag agad sa klinika kung mapansin ninyo ito.
Ang mga nerve na malapit sa pulso ay maaaring mairita o mapinsala habang isinasagawa ang operasyon. Maaari ninyong mapansin ang pamamanhid, pangingilig o isang bahagi ng balat na iba ang pakiramdam kapag nawala na ang bisa ng nerve block, sa humigit-kumulang 24 oras. Inaasahan ang pamamanhid at panghihina sa unang 24 oras pagkatapos ng nerve block. Tumawag sa klinika kung ang pamamanhid ay tumagal nang lampas doon, o kung hindi ninyo maigalaw ang inyong mga daliri o kamay kapag nawala na ang bisa ng block. Kung hindi ninyo maabot ang klinika, pumunta sa pinakamalapit na emergency department.
Ang complications table sa pahinang ito ay naglilista ng mga tipikal na rate kung nais ninyo ang mga detalye.
Kailan dapat tumawag sa amin
Karamihan sa mga tao ay gumagaling nang walang problema, ngunit makatutulong na malaman kung ano ang dapat bantayan. Tumawag sa klinika sa mismong araw kung ikaw ay may lagnat, kumakalat na pamumula sa paligid ng sugat, likido o nana na tumatagas mula rito, o sakit na patuloy na lumalala sa kabila ng iyong mga gamot sa sakit. Tumawag sa klinika kung nananatiling manhid ang iyong mga daliri o hindi mo maigalaw ang mga ito kapag nawala na ang bisa ng nerve block, sa humigit-kumulang 24 oras. Pumunta sa emergency department kung namamaga o masakit ang iyong binti (calf), kung ikaw ay hinihingal o may pananakit ng dibdib, o kung ang iyong mga daliri o kamay ay naging maputla, malamig, puti, asul o madilim ang kulay. Ang mga ito ay maaaring mga palatandaan ng blood clot o problema sa sirkulasyon. Kung hindi mo maabot ang klinika, pumunta sa pinakamalapit na emergency department.
Saan maaaring magbasa nang higit pa tungkol sa kondisyon
Ang pahinang ito ay tungkol sa operasyon mismo. Ang kondisyong ginagamot nito, kabilang ang kung ano ang ipinapakita ng ebidensya tungkol sa kung kailan nakatutulong ang operasyon at kung kailan hindi, ay tinalakay nang mas detalyado sa pahinang Wrist Ligament Injuries.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Wrist arthroscopy is a valuable means of diagnosis and treatment of wrist disorders [2].
- Wrist arthroscopy is a safe procedure with a low rate of major and minor complications [3].
- Wrist arthroscopy provides views of and access to the intraarticular spaces of the wrist that are otherwise difficult to achieve without widely open approaches [4].
- The indications for wrist arthroscopy are growing with the description of volar portals for the radiocarpal and scaphotrapezial trapezoid joint [1].
- Volar portals for wrist arthroscopy have certain advantages over the standard dorsal portals for visualizing dorsal capsular structures as well as the palmar aspects of the carpal ligaments [15].
- The routine use of wrist arthroscopy as a replacement or supplement to arthrography cannot be justified [5].
- Wrist arthroscopy may be recommended in cases of chronic wrist pain where the clinical suspicion is strong and the operating team is well-versed with the technique [6].
- Postoperative infection after wrist arthroscopy is uncommon but clinically relevant, particularly in elderly, male patients with systemic comorbidities or undergoing synovectomy [7].
- Arthroscopic arthrolysis is a suitable and promising surgical option for the treatment of wrist stiffness after trauma or surgery [8].
- In a prospective comparative study, the arthroscopically guided procedure for intra-articular distal radius fracture was superior to the conventional open procedure [12].
- Arthroscopic exploration of the extensor carpi ulnaris and its subsheath using standard wrist arthroscopy is relatively simple to perform without the need of a further portal [11].
- Complete avulsion of the distal posterior interosseous nerve during wrist arthroscopy is a possible cause of persistent pain after arthroscopy [10].
- It is questioned whether distal posterior interosseous nerve avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation [10].
- A simple, effective, and cost-efficient solution exists to overcome oversized finger traps for wrist arthroscopy distraction [9].
- The concept to use a physical model for wrist arthroscopy training is well perceived and indicates the potential for continued development [14].
Anatomy & Pathophysiology
Bony Anatomy
- The wrist includes the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones and their proximal and distal articulations and attached ligaments [38].
- The carpus comprises eight ossicles traditionally separated into two rows: the proximal row (scaphoid, lunate, triquetrum, pisiform) and the distal row (trapezium, trapezoid, capitate, hamate) [39].
- The distal radius articular surface has two concave facets for the scaphoid and lunate, separated by the scapholunate ridge [39].
- The sigmoid notch along the ulnar border of the distal radius is a shallow concavity for the articulating ulnar head at the distal radioulnar joint [39].
- The distal ulna is covered with hyaline cartilage on its dorsal, lateral, palmar, and distal surfaces [39].
- The ulnar styloid projects distally, and at its base, the fovea is the insertion for the triangular fibrocartilaginous complex (TFCC) [39].
- The scaphoid's primary vascular supply is a branch of the radial artery at the dorsal ridge, with smaller vessels entering the palmar tubercle to supply the distal 30% [39].
- The lunate has a dorsal and palmar vascular supply in 80% of wrists, while 20% have only a palmar supply [39].
- The capitate head often relies on a retrograde vascular supply [39].
- The pisiform is a sesamoid bone within the flexor carpi ulnaris tendon and serves as the origin for the abductor digiti minimi [39].
- The distal radial articular surface has a double obliquity of 12–15 degrees in the lateral view and 15–20 degrees in the anteroposterior view [43].
- The carpal articular surface has a smaller diameter of curvature than the radius, with stability in the medial and palmar aspects dependent on ligamentous and capsular resistance [43].
- The scaphoid presents a long axis inclined by 45 degrees to the long axis of the radius [43].
- The triquetrum is not in contact with the ulnar head; a fibro-cartilage disc, the triangular ligament, separates the two bones [43].
Ligaments and Soft Tissue Anatomy
- The triangular fibrocartilage complex (TFCC) consists of the central meniscus homolog, dorsal and volar radioulnar ligaments, the floor of the extensor carpi ulnaris tendon sheath, and volar ulnocarpal ligaments [39].
- The TFCC arises from the radial border of the distal radius and inserts into the base of the ulnar styloid and distal ulna through the ligamentum subcruentum [39].
- The dorsal and volar radioulnar ligaments are the primary stabilizers of the distal radioulnar joint [39].
- Only the peripheral 10% to 40% of the volar, ulnar, and dorsal TFCC has a vascular supply [39].
- The scapholunate interosseous ligament is C-shaped in the sagittal plane, with the dorsal third being the thickest and strongest portion [39].
- The volar portion of the lunotriquetral ligament is the thickest [39].
- The extrinsic wrist ligaments include the dorsal intercarpal ligament and the dorsal radiocarpal ligament [39].
- The dorsal radiocarpal ligament originates at the dorsal lip of the distal radius adjacent to Lister's tubercle and inserts into the lunate and triquetrum [39].
- The dorsal intercarpal ligament arises from the triquetrum and attaches to the scaphoid, trapezoid, and capitate [39].
- The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches [41].
- The dorsal intercarpal arch is the largest of the dorsal arches and supplies the distal carpal row and, through anastomoses, the lunate and triquetrum [41].
- The deep palmar arch at the level of the metacarpal bases is consistent and communicates with the dorsal basal metacarpal arch and palmar metacarpal arteries [41].
- The extensor carpi ulnaris tendon rotates around the ulnar head, situated on the ulnar side of the styloid in pronation and on the radial side in supination [44].
- The extensor carpi radialis brevis is the primary wrist extensor with a moment arm of 16.30 mm, compared to 12.50 mm for the extensor carpi radialis longus [44].
Kinematics and Biomechanics
- The wrist functions as a two-joint system linking the hand to the forearm around the highly mobile bones of the proximal carpal row [40].
- With axial loading through the neutral wrist, approximately 80% of forces are transmitted through the distal radius (60% scaphoid facet, 40% lunate facet) and 20% through the distal ulna [39].
- With wrist flexion, 60% of the motion is midcarpal and 40% is radiocarpal [39].
- With wrist extension, 33% of the motion is midcarpal and 66% is radiocarpal [39].
- The proximal carpal row has no muscular or tendinous attachments and is an intercalary segment [39].
- With ulnar deviation, the proximal row extends relative to the forearm/distal row, while with radial deviation, the proximal row flexes [39].
- The dart-thrower's path of radial extension to ulnar flexion defines the transition between flexion and extension of the scaphoid and lunate [40].
- Dart-thrower's motion occurs almost exclusively through the midcarpal joint [40].
Pathophysiology of Wrist Disorders
- Scapholunate advanced collapse (SLAC) wrist pathophysiology involves scapholunate interosseous ligament injury leading to palmar flexion of the scaphoid and extension of the lunate (DISI) [36].
- In SLAC wrist, the radioscaphoid joint becomes incongruous, leading to altered contact forces and arthrosis at the radioscaphoid and capitolunate joints [36].
- The radiolunate joint is typically spared in SLAC wrist due to its spheroid shape [36].
- Ulnocarpal impingement is a degenerative condition resulting from a discrepancy in the relative length of the distal articular surfaces of the radius and ulna (positive ulnar variance) [36].
- Posttraumatic causes of ulnocarpal impingement include distal radius fracture with shortening, Galeazzi or Essex-Lopresti fracture, and childhood epiphyseal plate injuries [36].
- Congenital causes of ulnocarpal impingement include dyschondroplasia (Madelung deformity) and naturally occurring positive ulnar variance [36].
- In rheumatoid arthritis, the classic pattern of wrist deformity involves destabilization of the carpus caused by attenuation of extrinsic wrist ligaments, resulting in ulnar-palmar translocation and wrist supination [49].
- Three main pathophysiological factors drive rheumatoid wrist deformation: cartilage destruction, synovial expansion, and ligamentous laxity [49].
- In juvenile arthritis, uncontrolled joint synovitis stretches essential ligaments and erodes cartilage and bone, resulting in a progressive shift of the carpus ulnarward and volarward [50].
- The dorsal wrist ganglion is the prototype of hand and wrist ganglions, accounting for 60% to 70% of all hand and wrist ganglions [23].
- The main cyst of a dorsal wrist ganglion is usually located directly over the scapholunate ligament [23].
- A small, mucin-filled duct invariably pierces the transverse fibers of the scapholunate ligament, connecting the underlying scapholunate joint with the main ganglion cyst [23].
TFCC Tear Classification
- The Palmer classification categorizes triangular fibrocartilage complex (TFCC) tears into traumatic (class 1) or degenerative (class 2) [24].
- Subtypes within the Palmer classification are based on the specific location within the TFCC [24].
- The class and location of a TFCC tear have important implications for treatment [24].
- Class 1A traumatic TFCC injuries are characterized by central perforation or tear [24].
- Class 1B traumatic TFCC injuries are characterized by ulnar avulsion with or without ulnar styloid fracture [24].
- Class 1C traumatic TFCC injuries are characterized by distal avulsion involving the origins of the ulnolunate and ulnotriquetral ligaments [24].
- Class 1D traumatic TFCC injuries are characterized by radial avulsion involving the dorsal and/or volar radioulnar ligaments [24].
- Class 2A degenerative TFCC tears are characterized by TFCC wear or thinning [24].
- Class 2B degenerative TFCC tears are characterized by Class 2A findings plus lunate and/or ulnar chondromalacia [24].
- Class 2C degenerative TFCC tears are characterized by TFCC perforation plus lunate and/or ulnar chondromalacia [24].
- Class 2D degenerative TFCC tears are characterized by Class 2C findings plus lunotriquetral ligament disruption [24].
- Class 2E degenerative TFCC tears are characterized by Class 2D findings plus ulnocarpal and distal radioulnar joint arthritis [24].
- Arthroscopy is the gold standard for the detection of TFCC tears [24].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting the central portion with a small probe [24].
- The arthroscopic hook test can be used to demonstrate peripheral detachment of the TFCC [24].
- The arthroscopic suction test can show laxity of the TFCC when peripherally scarred in or foveal detachment when the distal radioulnar joint is clinically unstable [24].
Clinical Presentation
Diagnostic Indications
- Indications for diagnostic wrist arthroscopy include chronic wrist pain of uncertain etiology with more than 3 months interval, unresponsive to conservative treatment [21, 37].
- Indications for diagnostic wrist arthroscopy include assessment of acute ligamentous injuries, including scapholunate, lunotriquetral, and triangular fibrocartilage complex (TFCC) injuries [21].
- Indications for diagnostic wrist arthroscopy include evaluation of carpal instability [21].
- Indications for diagnostic wrist arthroscopy include assessment of chondral lesions [21].
- Indications for diagnostic wrist arthroscopy include evaluation of associated soft tissue injury in fracture conditions, including distal radius, scaphoid, ulnar styloid, and other carpal bone fractures [21].
- Indications for diagnostic wrist arthroscopy include assessment of scaphoid healing in delayed union and nonunion [21].
- Indications for diagnostic wrist arthroscopy include staging of posttraumatic arthritis, including scapholunate advanced collapse (SLAC), scaphoid nonunion advanced collapse (SNAC), and distal radius fractures [21].
- Indications for diagnostic wrist arthroscopy include evaluation of monoarticular arthritis and synovial biopsy [21].
- Indications for diagnostic wrist arthroscopy include evaluation of Kienböck disease [21, 37].
- Patients without positive provocative sign on examination seldom yield positive findings at wrist arthroscopy [37].
- Arthroscopic findings need to correlate with clinical examination [37].
Clinical Examination Principles
- The natural inclination to study radiographs or special imaging studies and reports prior to a thorough history and physical examination should be avoided, as this introduces cognitive bias which can affect thinking and decision making [34].
- Physical examination always needs to be preceded by a thorough investigation of the patient’s medical history, with special emphasis on the mechanism of injury and acuity [34].
- The patient should be asked details about the location, duration, and characteristics of any pain, including aggravating and relieving factors and previous treatments [34].
- With chronic problems, it is important to inquire about the patient’s jobs and hobbies, and whether there has been exposure to repetitive stress, vibrating tools, or potentially dangerous instruments [34].
- Elucidating a history of ligamentous laxity or multiple joint instabilities, especially in younger patients presenting with chronic wrist pain, is important [34].
- Such an evaluation should also include an assessment of the patient's stress coping skills [34].
- Swelling is generally moderate in wrist dislocations, and bone displacements may be evident only if the patient is seen immediately after experiencing trauma [34].
- If there has been a delay since the accident, swelling may have increased substantially, making visualization of the displaced bones more difficult [34].
- Skin abrasions, contusions, or ecchymosed areas may be helpful in determining the mechanism of injury and the potential areas of damage [34].
- Range of motion is usually limited by pain in acute injuries, whereas it may be reduced or normal in more chronic cases [34].
- In chronic cases, passive assessment of mobility is valuable not only in determining the presence of abnormal motion or crepitus but also in reproducing the patient’s pain [34].
- The physician should record the motion in the contralateral, uninjured wrist for comparative purposes [34].
- Palpation for areas of maximal tenderness is one of the most useful tools in the diagnosis of wrist pathology, especially in patients with chronic dysfunctions [34].
- In acute dislocations, tenderness is seldom elicited at specific points but rather in a diffuse manner due to extensive soft tissue damage [34].
- Palpation should always be performed in a methodical way, starting from the basal joint of the thumb and proceeding across the proximal carpal row from the scaphoid to the triquetrum and continuing from the hamate back across the distal row and CMC joints [34].
- A careful assessment of neural and vascular status is imperative, with particular attention being paid to the median and ulnar nerves [34].
- The median and ulnar nerves may be injured by direct contusion at the moment of impact, by compression from displaced bones or by swelling within the carpal canal [34].
- A thorough set of provocative maneuvers should be performed to rule out alternative or even concurrent diagnoses [34].
- The examination should begin in a nontender area and proceed rotationally around the carpus, ending at the most symptomatic area [34].
- Bilateral grip and pinch strength are useful to uncover underlying pathology in chronic cases [34].
- Strength may be diminished due to muscle atrophy, pain inhibition, or learned behaviors [34].
- Rapid alternating grip assessment may be helpful in determining voluntary effort [34].
- A local injection of anesthetic to a painful joint or selected tendon sheath may help normalize the dynamometer readings and narrow the diagnostic spectrum [34].
- Sensory testing should always accompany an examination of suspected nerve compression, using threshold or density testing [34].
Specific Provocative Maneuvers
- The ligamentous habitus of a given individual must be assessed using information from the normal wrist because of the wide variation in mobility and laxity [54].
- The Watson test, or scaphoid shift test, is designed to show scaphoid instability [54].
- In the Watson test, the examiner puts one hand on the radial border of the distal forearm with the thumb on the palmar aspect of the scaphoid while moving the patient’s hand to bring about ulnar then radial deviation of the wrist [54].
- The Watson test causes a dorsal subluxation of the scaphoid, accompanied by a painful click [54].
- A positive Watson shift test results when the scaphoid subluxates dorsally out of the scaphoid fossa and relocates when pressure is released [36].
- The ballotment tests, or shear tests, consist of demonstrating abnormal movements between adjacent bones by exerting pressure in opposite directions [54].
- The scapholunate ballotment test involves stressing of the scapholunate joint by volar pressure on the tubercle of the scaphoid and dorsal pressure on the lunate [54].
- If there is any ligament damage, pressure on these two bones causes a painful shearing of the scapholunate joint [54].
- Instability of the lunotriquetral joint can be demonstrated by Reagan’s test, which involves dorsal pressure on the lunate and volar pressure on the triquetrum [54].
- The midcarpal joint "pivot shift" test consists of supinating and volar subluxing the distal row of the carpus [54].
- The pivot shift test is performed by placing the patient elbow upon a firm surface, holding the elbow at 90 degrees, putting the hand into a fully supine position and holding the distal forearm firmly [54].
- The hand is moved into full radial deviation and then the ulnar side of the carpus is forced into further supination and a volar subluxed position [54].
- The wrist must not be flexed during the pivot shift test [54].
- The hand, still with the displacing force applied, is gently moved from radial to full ulnar deviation [54].
- The normal wrist will notch into a less supinated position as the head of the capitate engages the lunate, because of the restraint of the anterior capsule and triquetrolunate interosseous ligaments [54].
- Rupture, attenuation or excess laxity allow the capitate to drift out of the lunate [54].
- Triquetral hamate instability is demonstrated with the wrist straight with ulnar deviation [54].
- After a range of about 20 degrees, triquetral hamate instability produces a firm block [54].
- If one forces a sharp click accompanied by discrete posterior movement of the wrist, the proximal row of the carpus has moved from the VISI position to that of DISI, thus allowing a complete ulnar deviation of the wrist joint [54].
- The radio-carpal and midcarpal joint anteroposterior drawer test involves one hand holding the patient’s hand by the metacarpals to apply axial traction while the other hand stabilizes the patient’s forearm [54].
- While holding this traction, anteroposterior force is applied and a drawer is elicited at the radio-carpal, then the midcarpal joint [54].
- The ability to push the midcarpal joint volarward is present to a varying degree in most normal asymptomatic patients [54].
- A marked drawer test is a sign of congenital laxity [54].
- An exaggeration of the normal ulna head prominence is seen in dorsal subluxation or articular effusion [54].
- The prominence of the ulna head may be temporarily reduced by direct pressure over the ulna head [54].
- In the rheumatoid wrist, the ulna head prominence is further exaggerated by a supination deformity of the carpus [54].
- If the hand is held in full ulnar deviation and the ulna head is held forward by the examiner’s thumb, significant pain may be precipitated by this movement alone, suggesting DRUJ pathology [54].
- Pain precipitated by pronosupination while the ulna head is pressed volarward and the pisiform pressed dorsally is usually indicative of some form of ulnar impingement or abutment syndrome [54].
- The diagnosis of DRUJ arthrosis is confirmed by improvement in rotation and grip strength with injection of a local anesthetic into the DRUJ [36].
- Clinical findings for DRUJ arthrosis include pain that increases with proximal rotation of the forearm and compression of the ulna against the radius [36].
- Symptoms of ulnocarpal impingement include pain on the dorsal side of the DRUJ and an intermittent clicking sensation [36].
- Pain in ulnocarpal impingement is exacerbated by forearm rotation and ulnar deviation [36].
- Pain in ulnocarpal impingement occurs with axial loading of the ulnar side of the wrist [36].
- Pain in ulnocarpal impingement occurs with dorsal and palmar displacement of the distal ulna, with the wrist in ulnar deviation (positive ballottement test) [36].
- Symptoms of SLAC wrist include reduced grip and pinch strength [36].
- Symptoms of SLAC wrist include stiffness with extension and radial deviation [36].
- Symptoms of SLAC wrist include localized tenderness at the radioscaphoid articulation [36].
- Symptoms of SLAC wrist include decreased wrist motion on extension and radial deviation [36].
Imaging and Preoperative Evaluation
- After the history and physical examination, radiographic evaluation is helpful in determining the diagnosis, prognosis, and management of wrist problems [32].
- MRI should be added for evaluation of the triangular fibrocartilage; the distal radioulnar joint (DRUJ); and vascularity of the various carpal bones, extrinsic ligaments, joint surfaces, and surrounding soft tissues to confirm clinical suspicion and correlate with physical examination findings [32].
- A high rate of false-positive findings on MR images of normal subjects has been reported [32].
- A dedicated wrist coil provides enhanced resolution of wrist structures [32].
- Routine radiographic series for the wrist consist of four views: posteroanterior, lateral, oblique, and ulnar-deviated posteroanterior scaphoid view [32].
- Spot views of the carpal bones for detail (carpal tunnel view) are a useful radiographic technique [32].
- Fluoroscopic spot views of the wrist are a useful radiographic technique [32].
- A series of views for instability includes anteroposterior clenched fist, posteroanterior in neutral, radial, and ulnar deviation, lateral in neutral and full flexion and extension, semipronated oblique 30 degrees from the posteroanterior, and semisupinated oblique 30 degrees from the lateral [32].
- Diagnostic ultrasound is a useful radiographic technique for evaluating a painful wrist [32].
- Cine or video fluoroscopy is a useful radiographic technique for evaluating a painful wrist [32].
- Bone scanning is a useful radiographic technique for evaluating a painful wrist [32].
- Arthrography of the wrist (triple injection when indicated) is a useful radiographic technique [32].
- CT is a useful radiographic technique for evaluating a painful wrist [32].
- MRI is a useful radiographic technique for evaluating a painful wrist [32].
- The authors do not feel that the routine use of wrist arthroscopy as a replacement or supplement to arthrography can be justified [5].
- Perform repeated clinical examinations for chronic wrist pain as part of preoperative evaluation [37].
Investigations
Diagnostic Role and Indications
- Arthroscopic assessment of intercarpal ligament injuries and instability is considered by many the “gold standard” for evaluation of these conditions [31].
- Arthroscopy is the gold standard for detection of triangular fibrocartilage complex (TFCC) tears [24].
- Arthroscopy has been found to be more accurate than arthrography in identifying the location and size of triangular fibrocartilage and interosseous ligament injuries [31].
- Arthroscopy is more accurate than triple-injection cinearthrography in detecting tears of the dorsal sensory branch of the ulnar nerve during arthroscopic repair of the triangular fibrocartilage [31].
- Indications for wrist arthroscopy include the evaluation of ligamentous injuries, examination of joint articular surfaces, removal of loose bodies, biopsy of synovium, irrigation and debridement of joints, and confirmation and supplementation of wrist arthrography [31].
Arthroscopic Tests
Imaging Modalities
- MRI should be added for evaluation of the triangular fibrocartilage, the distal radioulnar joint, and vascularity of the various carpal bones, extrinsic ligaments, joint surfaces, and surrounding soft tissues to confirm clinical suspicion and correlate with physical examination findings [32].
- With proper technique, injuries to the triangular fibrocartilage complex can be demonstrated with MRI [46].
- Perforations in the triangular fibrocartilage complex appear as linear defects or gaps filled with hyperintense fluid on coronal gradient-echo or T2-weighted pulse sequences [46].
- The addition of arthrographic contrast improves the visualization of carpal ligaments on MR images [46].
- MRI is useful in detecting additional marrow abnormalities in osteonecrosis, as seen in the lunate in Kienböck disease or in the scaphoid after fracture [46].
- Asymmetry of marrow signal in proximal and distal fragments of a fractured scaphoid is suggestive of proximal pole ischemia [46].
- MRI has a limited role in the evaluation of carpal tunnel syndrome, which remains a clinical diagnosis [46].
- Axial imaging with T2 weighting can clearly display masses within the confines of the carpal tunnel, as well as edema and swelling of the median nerve [46].
- MRI provides earlier detection of synovitis and erosive bone changes associated with rheumatoid arthritis than do radiographs [46].
- MRI has an expanding role in the evaluation of inflammatory arthritis [46].
- MRI has gained a greater role in the evaluation of acute wrist trauma, where bone marrow edema may reveal fractures of the carpal bones or distal radius that are radiographically occult [46].
- MRI is controversial for TFCC pathology, but newer innovations suggest value in detection and localization of TFCC pathology [24].
Radiographic Techniques
- Spot views of the carpal bones are used for detail, including the carpal tunnel view [32].
- Arthrography of the wrist, including triple injection when indicated, is a useful radiographic technique [32].
Preoperative Assessment
- The natural inclination to study radiographs or special imaging studies and reports prior to a thorough history and physical examination should be avoided, as this introduces cognitive bias [34].
Treatment
Indications and Diagnostic Role
Operative Technique and Setup
- The patient is positioned supine on the operating table with a traction device applied to distract the wrist joint [21].
- Traction force of 10 to 12 lb is applied through plastic finger traps over the index and middle fingers, or more preferably, the middle three fingers [21].
- Overdistraction or use of wire finger traps may cause postoperative finger joint pain or localized contusion to soft tissue or digital nerves [21].
- Nylon finger traps are more comfortable and atraumatic to the patient, especially in awake cases [21].
- For arthroscopy over the scaphotrapeziotrapezoid joint, an additional trap and traction can be put on the thumb [21].
- When an overhead traction boom is employed, countertraction is provided by securing the arm to the hand table, and the operated limb is draped free up to the elbow level [21].
- When a dedicated wrist traction device is being used, the limb is draped up to the axilla level and the lower arm is wrapped to the basal plate of the device close to the elbow level [21].
- A traction device should be sterilizable and allow flexible positioning of the wrist intraoperatively in varying degrees of extension, flexion, and radial and ulnar deviation [21].
- Tourniquet use is optional and is often unnecessary, especially for diagnostic and uncomplicated therapeutic procedures performed under local anesthesia without sedation [21].
- Joint visibility is maintained by saline inflow, as the small volume of the wrist makes fluid distention rather impractical compared to the knee or shoulder joint [21].
- The main maneuver in creating the working space is controlled traction, while saline maintains a clear view by removing intraarticular debris through the outflow portal [21].
- The hydrostatic pressure generated by saline irrigation serves a hemostatic role when arthroscopy is performed without a tourniquet [21].
- Continuous irrigation is achieved with a 3 L bag of normal saline suspended 1.5 m above the patient and instilled under gravity [21].
- Caution should be used to avoid extravasation of fluid that may lead to compartment syndrome [21].
Therapeutic Procedures
- In the treatment of central triangular fibrocartilage complex tears, partial excision using the holmium:Yttrium-aluminum-garnet laser has been performed over a five-year experience [13].
- Arthroscopically guided procedure for intra-articular distal radius fracture was found to be superior to the conventional open procedure based on a prospective comparative study [12].
- Ablative procedures in wrist arthroscopy include TFCC debridement, debridement of ligament tears, synovectomy, wrist ganglionectomy, removal of loose body, capsulotomy/capsulectomy, lavage, and arthrolysis [21].
- Ablative bony procedures in wrist arthroscopy include scaphoidectomy, radial styloidectomy, wafer procedure, proximal row carpectomy, and proximal hamate excision [21].
- Ablative cartilage procedures in wrist arthroscopy include debridement of chondral and osteochondral lesions [21].
- Reparative soft tissue procedures in wrist arthroscopy include peripheral TFCC tear repair, TFCC foveal avulsion repair, scapholunate ligament injury repair, and lunotriquetral ligament injury repair [21].
- Reparative bony tissue procedures in wrist arthroscopy include arthroscopic-assisted reduction and internal fixation (ARIF) for distal radius fracture and scaphoid fracture [21].
- Reparative cartilage procedures in wrist arthroscopy include drill/abrasion chondroplasty [21].
- Reconstructive soft tissue procedures in wrist arthroscopy include arthroscopic TFCC reconstruction with tendon graft and arthroscopic-assisted scapholunate ligament reconstruction with tendon graft [21].
- Reconstructive bony procedures in wrist arthroscopy include arthroscopic bone grafting for scaphoid nonunion, limited carpal fusion, intraosseous bone cyst, and intraosseous ganglion [21].
- Reconstructive cartilage tissue procedures in wrist arthroscopy include osteochondral grafting [21].
Complications and Safety
- DPIN avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation [10].
Complications
- Overdistraction during wrist arthroscopy distraction can cause postoperative finger joint pain [21].
- Use of wire finger traps for wrist arthroscopy distraction may cause localized contusion to soft tissue or digital nerves [21].
- Nylon finger traps are more comfortable and atraumatic to the patient than other traction methods, especially in awake cases [21].
- Extravasation of fluid during wrist arthroscopy may lead to compartment syndrome [21].
- Postoperative infection after wrist arthroscopy is uncommon but clinically relevant [7].
- Postoperative infection risk after wrist arthroscopy is particularly elevated in elderly, male patients with systemic comorbidities or those undergoing synovectomy [7].
- Complete avulsion of the distal posterior interosseous nerve can occur during wrist arthroscopy [10].
- Distal posterior interosseous nerve avulsion is a possible cause of persistent pain after wrist arthroscopy [10].
- Inadvertent damage to the dorsal branch of the ulnar nerve can be avoided by placing the 6R portal in the proximal fifth (19%) of a line drawn from the ulnar styloid to the fourth dorsal web space [22].
Recovery
- Postoperative infection risk is particularly relevant in elderly, male patients with systemic comorbidities or undergoing synovectomy [7].
Key Evidence
- [Paper] The indications for wrist arthroscopy are growing with the description of volar portals for the radiocarpal and scaphotrapezial trapezoid joint. [1] (10.1097/00130911-200603000-00007)
- [L4] From these data it appears that wrist arthroscopy is a valuable means of diagnosis and treatment of wrist disorders. [2] (10.1016/s0266-7681(96)80100-8)
- [L4] Wrist arthroscopy is a safe procedure with a low rate of major and minor complications. [3] (10.1016/j.jhsa.2003.12.020)
- [L5] Wrist arthroscopy can be a useful tool in one’s armamentarium in the diagnosis and treatment of wrist pathology, providing views of and access to the intraarticular spaces of the wrist that are otherwise difficult to achieve without widely open approaches. [4] (10.1016/j.eats.2024.103223)
- [L4] The authors do not feel that the routine use of wrist arthroscopy as a replacement or supplement to arthrography can be justified. [5] (10.1016/0266-7681(94)90256-9)
- [L4] It may be recommended in cases of chronic wrist pain where the clinical suspicion is strong and the operating team is well-versed with the technique. [6] (10.1177/1558944716660555ig)
- [L3] Postoperative infection after wrist arthroscopy is uncommon but clinically relevant, particularly in elderly, male patients with systemic comorbidities or undergoing synovectomy. [7] (10.1016/j.otsr.2026.104771)
- [L4] Arthroscopic arthrolysis is a suitable and promising surgical option for the treatment of wrist stiffness after trauma or surgery. [8] (10.1016/s0363-5023(03)80309-x)
- [L5] We present a simple, effective, and cost-efficient solution to overcome oversized finger traps for wrist arthroscopy distraction. [9] (10.1016/j.eats.2025.103662)
- [L5] An alternate question is whether DPIN avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation. [10] (10.1053/jhsu.1999.0240)
- [L5] They found this arthroscopic exploration relatively simple to perform without the need of a further portal. [11] (10.1177/1753193420948404)
- [L3] On the basis of our prospective comparative study, we found that the arthroscopically guided procedure was superior to the conventional open procedure. [12] (10.1016/j.jhsb.2006.03.177)
- [L4] [13] (10.1053/jhsu.2001.20157)
- [Paper] The concept to use a physical model for wrist arthroscopy training is well perceived, and indicates the potential for continued development. [14] (10.1016/j.main.2015.10.087)
- [L5] Volar portals for wrist arthroscopy have certain advantages over the standard dorsal portals for visualizing dorsal capsular structures as well as the palmar aspects of the carpal ligaments. [15] (10.1097/00130911-200412000-00006)
- [L5] Inadvertent damage to the dorsal branch of the ulnar nerve can be avoided if care is taken to place the 6R portal in the ‘‘safe area’’ found within the proximal fifth (19%) of a line drawn from the ulnar styloid to the fourth dorsal web space. [22] (10.1016/j.jhsb.2005.10.005)
References
[1] Uses and Abuses of Wrist Arthroscopy. Techniques in Hand & Upper Extremity Surgery. 2006. DOI: 10.1097/00130911-200603000-00007
[2] The Value of Wrist Arthroscopy. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(96)80100-8
[3] Complications of wrist arthroscopy. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.12.020
[4] Wrist Arthroscopy: Positioning, Portal Placement, and Diagnostic Evaluation. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103223
[5] Wrist Arthroscopy. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90256-9
[6] Wrist Arthroscopy as a Diagnostic Tool in Chronic Wrist Pain. HAND. 2016. DOI: 10.1177/1558944716660555ig
[7] Incidence and risk factors of postoperative infection after wrist arthroscopy: an 11-year nationwide population-based cohort study in South Korea. Orthopaedics & Traumatology: Surgery & Research. 2026. DOI: 10.1016/j.otsr.2026.104771
[8] Arthroscopic wrist arthrolysis. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80309-x
[9] Tip to Overcome Oversized Finger Traps in Wrist Arthroscopy Distraction. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2025.103662
[10] Complete avulsion of the distal posterior interosseous nerve during wrist arthroscopy: A possible cause of persistent pain after arthroscopy. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0240
[11] Visualization of the extensor carpi ulnaris and its subsheath using standard wrist arthroscopy. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420948404
[12] 2.3 Wrist arthroscopy in intra-articular distal radius fracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2006. DOI: 10.1016/j.jhsb.2006.03.177
[13] The holmium:Yttrium-aluminum-garnet laser in wrist arthroscopy: A five-year experience in the treatment of central triangular fibrocartilage complex tears by partial excision. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.20157
[14] Development of a wrist arthroscopy simulator. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2015.10.087
[15] Clinical Applications of Volar Portals in Wrist Arthroscopy. Techniques in Hand & Upper Extremity Surgery. 2004. DOI: 10.1097/00130911-200412000-00006
[21] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > SURGICAL TECHNIQUE FOR DIAGNOSTIC ARTHROSCOPY > Setup.
[22] The Anatomy of the Dorsal Cutaneous Branch of the Ulnar Nerve – a Safe Zone for Positioning of the 6r Portal in Wrist Arthroscopy. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.10.005
[23] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Dorsal Wrist Ganglion.
[24] Miller S Review Of Orthopaedics. DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[31] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ARTHROSCOPY OF THE WRIST.
[32] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > RADIOGRAPHIC TECHNIQUES.
[34] Green S Operative Hand Surgery. Diagnosis and Treatment > Assessment of the Symptomatic Wrist.
[36] Aaos Comprehensive Orthopaedic Review 3. Arthritides of the Hand and Wrist* > IV. Posttraumatic Arthritis.
[37] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Diagnostic Wrist Arthroscopy.
[38] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[39] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[40] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[41] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[43] Exam Of The Hand Wrist 2Ed. 1.2 SKELETON OF THE WRIST.
[44] Exam Of The Hand Wrist 2Ed. Extension of the wrist > Muscles of wrist extension.
[46] Campbell S Operative Orthopaedics 4 Volume Set. WRIST AND ELBOW.
[49] Green S Operative Hand Surgery. WRIST INVOLVEMENT IN RA.
[50] Tachdjian S Pediatric Orthopaedics From The Texas Scottish Rite Hospital For Children E Book. Wrist Involvement.
[54] Exam Of The Hand Wrist 2Ed. Examination.