Patients › General-Health
Kalusugan ng Buto at Osteoporosis
How bone strength affects fractures, fixation and recovery — bone density, fragility fractures, and what helps keep bones strong (lifestyle, supplements and medications).
Ano ito
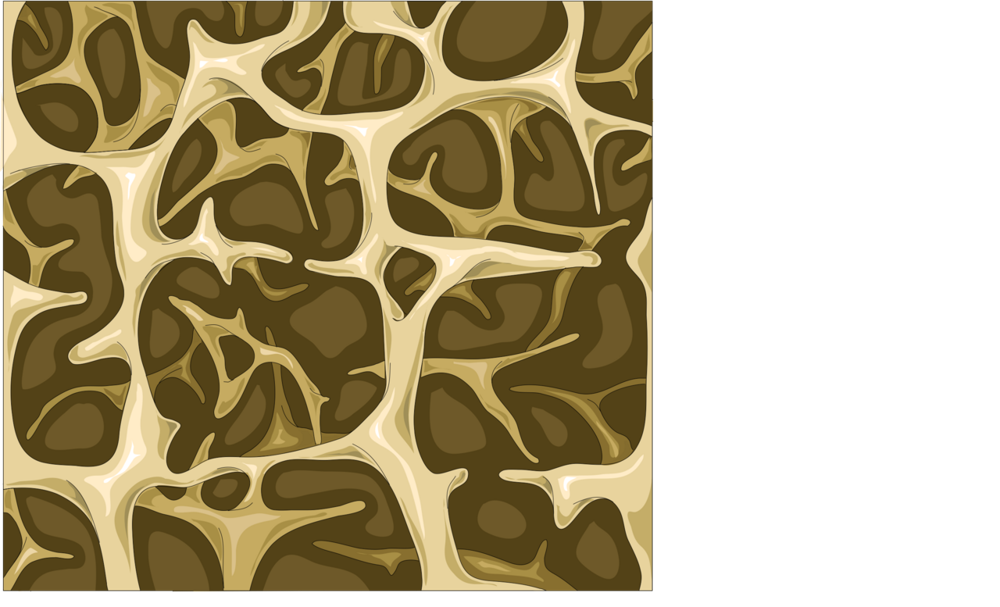
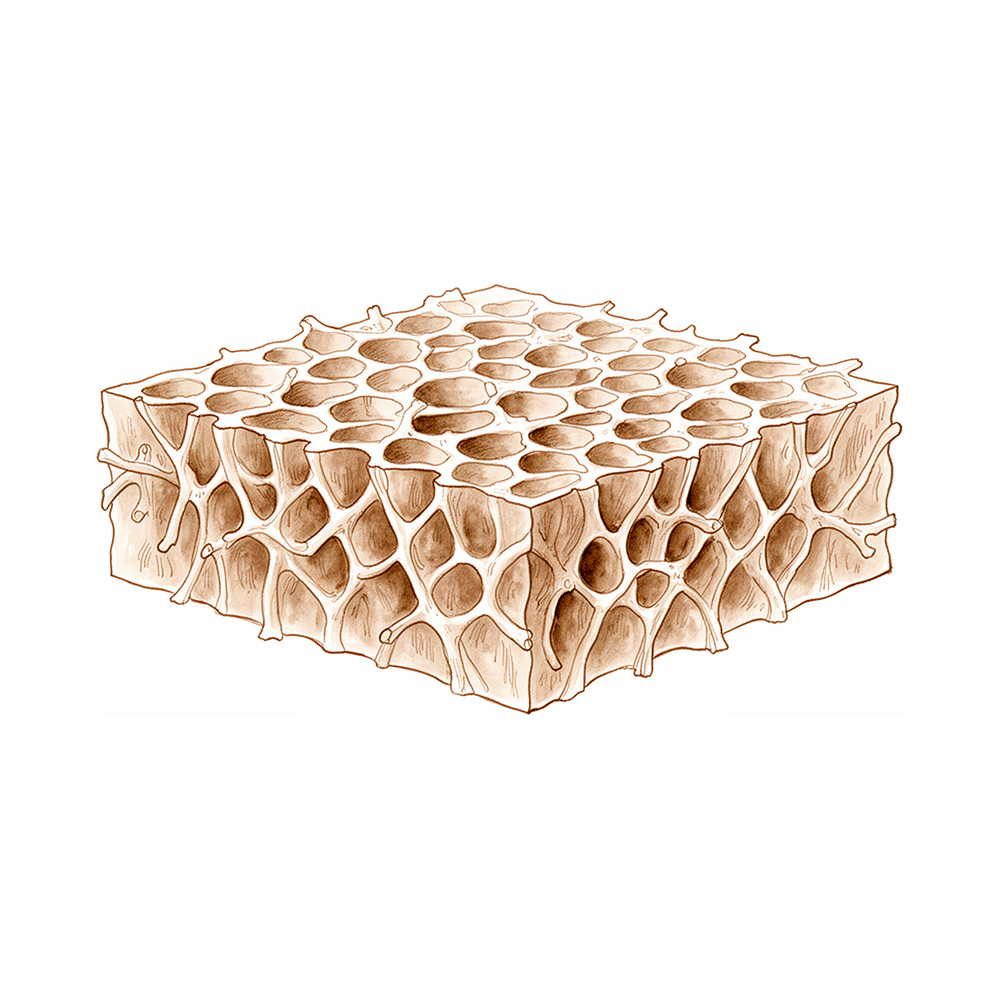
Ang osteoporosis ay isang kondisyon kung saan nawawalan ng lakas ang iyong mga buto. Sa paglipas ng panahon, nagiging manipis at marupok ang mga ito, kaya maaari silang mabali dahil sa isang bahagyang pagkahulog o kahit isang maliit na pagkabunggo. Ang pinakakaraniwang mga bali ay nangyayari sa balakang, sa pulso at sa gulugod (spine).
Maaari mong marinig ang terminong "fragility fracture". Nangangahulugan ito ng isang buto na mas madaling nabali kaysa sa nararapat. Kung nagkaroon ka ng isa sa mga baling ito, maaari itong maging babala na mas mahina ang iyong mga buto kaysa sa normal.
May kilalang agwat sa pangangalaga dito. Natuklasan ng pananaliksik na ang mga taong nabalian ng buto sa ganitong paraan ay madalas na hindi nasusuri para sa osteoporosis o hindi sinisimulan sa paggamot [1]. Nangyayari ito kahit na may umiiral na mga alituntunin (guidelines) [2]. Mahalaga ito dahil ang paggamot sa pinagbabatayang kahinaan ng buto ay maaaring magpababa ng posibilidad ng isa pang bali. Ipinakita ng mga trial na ang paggamot sa osteoporosis pagkatapos ng isang fragility fracture ay maaaring magbawas ng panganib ng karagdagang mga bali nang hanggang 50% at magpababa ng bilang ng namamatay nang hanggang 30% [3].
Ang mga buto ay hindi nananatiling pareho. Ang mga ito ay buhay na tisyu na palaging sinisira at muling binubuo. Nagkakaroon ng osteoporosis kapag mas mabilis ang pagkasira kaysa sa muling pagbuo, kaya bumababa ang bone density. Ang layunin ng pag-iwas ay makabuo ng pinakamatibay na mga buto na kaya mo, at pagkatapos ay panatilihin ang lakas na iyon [4]. Ang layunin ng paggamot ay pigilan ang karagdagang pagkawala ng buto upang hindi kailanman mangyari ang unang bali, o ang isa pa [4].
Isang natuklasang dapat mong malaman: natuklasan ng isang pagsusuri ng siyam na pag-aaral na ang bawat pagtaas ng 1 unit sa body mass index ay nauugnay sa 9% na pagbaba ng panganib ng osteoporosis [5]. Ang timbang ng katawan ay isang bahagi lamang ng larawan, kasama ng mga bagay tulad ng edad, mga hormone at pangkalahatang kalusugan.
Kung madali kang nabalian ng buto, o nag-aalala ka tungkol sa lakas ng iyong mga buto, magtanong tungkol sa pagsusuri ng bone density. Ang maagang pagtuklas ng osteoporosis ay nagbibigay sa iyo ng pinakamagandang pagkakataon na kumilos bago mangyari ang isang bali.
Gumagana ba ito?
Ang tapat na sagot ay pinakamabisa ang paggamot kapag maaga itong sinimulan, at may puwang pa rin para sa pagpapabuti sa kung paano ito nangyayari. Natuklasan ng pananaliksik na ang mga taong nabalian ng pulso ay mas madalas na nasusuri para sa osteoporosis kapag bahagi sila ng isang nakalaang programa kaysa kapag tumatanggap sila ng karaniwang pangangalaga: 92% kumpara sa 23% [6]. Natuklasan ng ibang mga pag-aaral na ang mga taong nabalian ng balakang o ng isang buto sa gulugod ay madalas na hindi man lang sinisimulan sa paggamot na nagpapatibay ng buto, kahit na inirerekomenda ito ng mga alituntunin [7] [2]. Ito ang dahilan kung bakit napakahalaga na magtanong tungkol sa pagsusuri ng bone density pagkatapos ng anumang madaling pagkabali.
Kapag na-diagnose na ang osteoporosis, may ebidensya na makatutulong ang paggamot sa paggaling ng mga buto at sa pagbabawas ng posibilidad ng isa pang bali. Sa isang trial, ang mga taong may baling pulso na tumanggap ng injection ng hormone na bumubuo ng buto ay gumaling sa loob ng 7.8 linggo, kumpara sa 12.6 linggo para sa mga hindi tumanggap ng paggamot [8]. May papel din ang ehersisyo. Ang mga taong may osteoporosis ay dapat gumawa ng resistance at impact exercise upang mapalaki hangga't maaari ang lakas ng buto, kasama ang mga aktibidad na nagpapabuti ng lakas at balanse upang mabawasan ang pagkahulog, at spinal extension exercise upang mapabuti ang tindig (posture) [9].
Ang ilan sa mas bagong pananaliksik ay hindi pa tiyak. Ang mga machine learning tool na humuhula ng osteoporosis mula sa mga scan o blood test ay mukhang may pangako, ngunit natuklasan ng mga review na mataas ang panganib ng bias ng mga ito at hindi pa maayos na nasusubok sa mga klinika [10]. At natuklasan ng isang pagsusuri na ang isang gamot sa diabetes na inakalang nagpoprotekta sa mga buto ay hindi nagpababa ng mga bali sa pulso at braso kapag isinaalang-alang na ang ibang mga salik sa kalusugan [11]. Kung mayroon kang osteoporosis at nabalian ka ng buto, mas mabisa ang paggamot sa mismong buto kapag ginagamot din nang sabay ang pinagbabatayang kahinaan ng buto [12].
Ano ang mga panganib?
Ang pangunahing panganib ng hindi paggamot sa osteoporosis ay ang pagkabali ng buto. Kung nagkaroon ka na ng isang fragility fracture, mas malamang na mabali muli ang iyong mga buto, lalo na kung hindi ginagamot ang pinagbabatayang kahinaan ng buto [7] [2]. Natuklasan ng pananaliksik na ang paggamot na sinimulan pagkatapos ng unang bali ay nagpapababa ng posibilidad ng isa pa, at ito ang pinakamatibay na dahilan upang kumilos nang maaga [3].
Mayroon ding mga panganib sa panahon mismo ng bali. Natuklasan ng isang pag-aaral na ang mga taong may osteoporosis ay nagkaroon ng mas maraming medikal na komplikasyon sa unang 90 araw pagkatapos ng operasyon kaysa sa mga taong wala nito [13]. Ang mga baling buto ay maaari ding gumaling nang magkakaiba depende sa lakas ng buto. Sa isang pag-aaral ng mga displaced na bali sa pulso, ang pagbuti sa deformity ay 12.5 sa mga taong may osteoporosis, wala pang kalahati ng 25.6 na nakita sa mga taong may magandang kalidad ng buto [14]. Natuklasan ng isa pang pag-aaral na ang mahinang buto sa mga nakatatanda ay hindi, sa sarili nito, pumipigil sa pagdugtong ng isang bali [15].
Kung mayroon kang osteoporosis at kailangan mo ng operasyon sa isang kasukasuan o tendon, mas tiyak ang larawan. Natuklasan ng mga review ng keyhole rotator cuff repair na walang kaugnayan ang mas mababang bone density sa mga resulta sa 2 taon, at mababa ang bilang ng mga komplikasyon [16] [17]. Hindi dapat ituring ang osteoporosis na dahilan upang alisin ang operasyong ito sa mga pagpipilian [17].
May sariling mga kawalang-katiyakan ang ilang paggamot. Ang anyong nasal spray ng calcitonin ay hindi kasing-bisa ng ibang mga gamot sa buto sa pagpapatibay ng buto at pagpapababa ng panganib ng bali [18]. Maaga pa ang ebidensya para sa acupuncture at sa mga produkto ng tradisyonal na Chinese medicine, at kailangan pa ng mas maraming pagsusuri [19] [20]. Para sa mga injection ng parathyroid hormone, pinag-aaralan pa sa mga trial ang pinakamainam na timing ng mga dosis [21].
Ang tapat na agwat ay nasa pagtupad at pagsubaybay (follow-through). Ipinapakita ng mga pag-aaral na maraming tao na nabalian ng balakang, gulugod o pulso ang hindi man lang sinisimulan sa paggamot na nagpapatibay ng buto [7] [2] [22]. Ang pagtatanong tungkol sa paggamot pagkatapos ng anumang madaling pagkabali ang pinakaligtas na hakbang na magagawa mo.
Tama ba ito para sa iyo?
Sulit na isaalang-alang ang paggamot na nagpapatibay ng buto kung sinabihan ka na mahina ang iyong mga buto, o kung nabalian ka ng buto nang mas madali kaysa sa nararapat. Ang layunin ay pigilan ang karagdagang pagkawala ng buto bago mangyari ang unang bali, o ang isa pa [4]. Mahalaga rin ang paggamot pagkatapos ng isang fragility fracture. Maaari nitong pababain ang posibilidad ng isa pang bali at bawasan ang bilang ng namamatay [3]. Ngunit ipinapakita ng pananaliksik na maraming tao na nabalian ng balakang, gulugod o pulso ang hindi man lang sinisimulan sa paggamot [7] [2]. Kaya kung nagkaroon ka ng madaling pagkabali, makatwirang itanong sa iyong doktor ang tungkol sa pagsusuri ng bone density at kung makatutulong sa iyo ang paggamot.
Ang ilang tao ay mas malamang na hindi mangailangan ng paggamot. Kung matibay pa ang iyong mga buto, ang pokus ay panatilihin ang mga ito sa ganoong kalagayan: buuin ang pinakamatibay na mga buto na kaya mo, at pagkatapos ay panatilihin ang lakas na iyon [4]. May bahagi rito ang ehersisyo. Ang mga taong may osteoporosis ay dapat gumawa ng resistance at impact exercise upang mapalaki hangga't maaari ang lakas ng buto [9]. Matutulungan ka ng iyong doktor na alamin kung ano ang ligtas para sa iyo.
Ang paggamot ay hindi iisang sukat para sa lahat. May ilang uri ng gamot sa buto, at ang tamang gamot ay nakadepende sa iyong kalusugan, sa kasaysayan ng iyong mga bali at sa sarili mong mga priyoridad. Dapat itong maging magkasamang desisyon mo at ng iyong doktor. Itanong kung ano ang kinapapalooban ng bawat opsyon, ano ang mga posibleng side effect (tinalakay sa seksyon tungkol sa mga panganib sa itaas), at gaano katagal mo kailangang manatili sa paggamot. Kung may hindi malinaw, patuloy na magtanong hanggang sa makaramdam ka ng kumpiyansa sa plano.
Ang pinaka-punto
Sulit na isaalang-alang ang paggamot sa osteoporosis kung mahina ang iyong mga buto o kung madali kang nabalian ng buto. Ang layunin ay pigilan ang karagdagang pagkawala ng buto bago mangyari ang isang bali, o ang isa pa [4]. Mahalaga ang maagang pagkilos, dahil ang paggamot pagkatapos ng isang fragility fracture ay maaaring magpababa ng posibilidad ng isa pang bali at bawasan ang bilang ng namamatay [3]. Ang nag-iisang pinakamahalagang paalala ay ang pagtupad at pagsubaybay (follow-through): maraming tao na nabalian ng balakang, gulugod o pulso ang hindi kailanman nasusuri o nagagamot [7] [2]. Kaya kung nagkaroon ka ng madaling pagkabali, humingi ng pagsusuri ng bone density at patuloy na magtanong hanggang sa magkaroon ka ng plano.
Mga Sanggunian
[1] The osteoporosis care gap in Canada. BMC Musculoskeletal Disorders. 2004. DOI: 10.1186/1471-2474-5-11
[2] A Missed Opportunity? Osteoporosis Treatment Following Femoral Neck Fractures: Reducing the Risk of Secondary Hip Fracture. The Journal of Arthroplasty. 2026. DOI: 10.1016/j.arth.2025.07.028
[3] Medical management of osteoporosis and the doctor's' role. Injury. 2016. DOI: 10.1016/s0020-1383(16)30014-6
[4] BONE HEALTH AND OSTEOPOROSIS. Clinics in Sports Medicine. 2000. DOI: 10.1016/s0278-5919(05)70201-5
[5] The association between body mass index and osteoporosis, with consideration of sex differences: a systematic review and dose-response meta-analysis. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09675-3
[6] Wristwatch—distal radial fracture as a marker for osteoporosis investigation:. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.001
[7] The Management of Pelvic and Vertebral Fragility Fractures: An Unmet Care Need. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.26.00966
[8] Use of teriparatide in osteoporotic fracture patients. Injury. 2016. DOI: 10.1016/s0020-1383(16)30009-2
[9] Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022. DOI: 10.1136/bjsports-2021-104634
[10] Risk prediction models for postmenopausal osteoporosis: a systematic review and meta-analysis study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-025-09385-2
[11] Glucagon-like peptide-1 receptor agonist use for type 2 diabetes and risk of upper extremity fragility fracture. Injury. 2026. DOI: 10.1016/j.injury.2026.113456
[12] Continuity and volume of bone cement and anti osteoporosis treatment were guarantee of good clinical outcomes for percutaneous vertebroplasty: a multicenter study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08153-y
[13] Impact of osteoporosis on post-operative outcomes following rotator cuff repair. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100723
[14] Osteoporosis and colles' fractures in the elderly. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90058-1
[15] A89 Osteoporosis is not a risk factor for the development of nonunion: a cohort nested case-control study. Injury. 2011. DOI: 10.1016/s0020-1383(11)70106-1
[16] No difference in 2-year outcomes of arthroscopic rotator cuff repair in patients with osteoporosis. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.011
[17] Osteoporosis is a risk factor for complications and reoperations at 1 and 3 years after arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101678
[18] Revisiting Intranasal Salmon Calcitonin: Historical Osteoporosis Evidence and a Potential Role in Acute Orthopaedic Pain Management. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00021
[19] Efficacy of acupuncture for primary osteoporosis: a systematic review and meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05513-9
[20] Natural traditional Chinese medicine products: emerging therapeutic targets for the treatment of osteoporosis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05879-w
[21] Timing optimization of teriparatide dosing for postmenopausal osteoporosis: a randomized controlled trial. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06083-6
[22] Incidence of Anti-osteoporosis Diagnosis and Treatment After Distal Radius Fractures. HAND. 2016. DOI: 10.1177/1558944716660555dj
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Prevention of osteoporosis is accomplished by maximizing peak bone density and maintaining that bone density [4].
- The goal of osteoporosis treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures [4].
- Each 1-unit increase in body mass index is associated with a 9% reduction in osteoporosis risk [6].
- Current online health information on osteoporosis often fails to meet basic standards of evidence-based health information [3].
- There is evidence of a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada [14].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated following pelvic and vertebral fragility fractures [5].
- Low rates of osteoporotic pharmacotherapy are observed in patients who have sustained femoral neck fractures despite established guidelines [33].
- Patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period following rotator cuff repair than nonosteoporotic patients [21].
- Osteoporosis should not be considered a contraindication to arthroscopic rotator cuff repair [31].
- Patients with distal radial fractures in elderly women should be screened for osteoporosis [11].
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing bone mineral density and reducing fracture risk [12].
- The use of intranasal salmon calcitonin is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [12].
- Sequential anabolic-to-anti-resorptive therapy may inform treatment guidelines for high-risk postmenopausal populations [7].
- The ability of monocytes to fuse declines significantly in patients with osteoporosis [52].
How It Works
Pathophysiology and Mechanisms
- Hypothalamic-pituitary disconnection leads to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation, with reduced osteoblast and osteoclast activity [26].
- MiR-137 promotes TLR4/NF-κB pathway activity through targeting KDM4A, which inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis [36].
- The gut microbiota–metabolite–bone network may be involved in the skeletal effects of leptin, providing mechanistic insights for osteoporosis management [35].
- Macrophage polarization-related genes have potential causal roles in osteoporosis, though these findings are exploratory and require validation in bone marrow-specific and functional studies [34].
- Evidence of early changes in bone geometry and increased bone turnover could be used to detect osteoporosis before estrogen deficiency has adversely affected bone strength [24].
Fracture Healing and Bone Repair
- In humans, de novo use of bisphosphonate therapy after fracture does not appear to have a significant effect on fracture healing [30].
- Prior bisphosphonate treatment affects the mineralization pattern of tissue repair consistently with a reduction in bone turnover, but does not abolish the repair process [23].
- The effect of ovariectomy on fracture repair is to delay healing, with the deleterious effect potentially related more to change of structure than to loss of bone mineral density [39].
- Fracture healing in SAMP6 mice is not detrimentally affected by impairment of bone marrow stem cell osteogenesis, suggesting that bone marrow-mediated repair processes are dispensable for normal bone healing in this senile osteoporotic fracture model [42].
- There is some promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents [25].
- Bisphosphonate treatment results in cracks that are shorter than in control or ovariectomized groups, which may explain why increased damage levels following bisphosphonate treatment have not led to increased fractures [38].
- Osteoporosis is not a risk factor for the development of nonunion, although bone quality may be diminished in the elderly [44].
Risk Factors and Screening
- Each 1-unit increase in body mass index was associated with a 9% reduction in osteoporosis risk based on a dose-response analysis of nine studies [6].
- Postmenopausal women with distal radius fractures have diminished bone mass, which might make a bone more likely to break [43].
- Patients with distal radial fractures should be screened for osteoporosis [11].
- A simple inexpensive tool has potential to increase the rate of osteoporosis investigation in an at-risk population [19].
- Machine learning application to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and therefore earlier treatment of osteoporosis or osteopenia [10].
- A nomogram with an online dynamic calculator could facilitate the early prediction, diagnosis, and treatment of osteoporosis, contributing to the bone health of the elderly population [13].
- A bone density based aging model may facilitate and support the development of precision medicine strategies in osteoporosis prevention and management [1].
Treatment and Management
- Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density, although the goal of treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures [4].
- Randomized controlled trials have demonstrated that treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30% [18].
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing bone mineral density and reducing fracture risk, and its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [12].
- The current evidence suggests that the efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention [17].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated, and treatments vary widely and are not always evidence-based [5].
- A program for secondary osteoporotic fracture prevention is needed following distal radius fractures [27].
- Natural traditional Chinese medicine products provide a theoretical and experimental basis for the development of new drugs and the improvement of osteoporosis management [22].
- A calcitonin release system confirms good in vivo behavior and a therapeutic effect of the released calcitonin in the osteopenic condition [28].
- Timing optimization of teriparatide dosing may guide personalized dosing strategies to enhance bone formation and reduce fracture risk in osteoporosis [15].
Clinical Outcomes and Surgical Considerations
- There is no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair in patients with osteoporosis [20].
- Findings from studies on long-term hospitalized patients with muscular dystrophy may help inform strategies for osteoporotic treatment and nutritional care in this patient population [8].
Research Models and Assessment
- Investigators must select an osteoporotic fracture model that best reflects the clinical problem being studied and the underlying pathophysiology of the osteoporosis in the target patient group [2].
- There is no perfect model for osteoporosis, but a variety of models are appropriate for answering specific questions [9].
- Multiscale biomechanical assessment approaches have potential applications in fracture risk assessment, the design of patient-specific implants, and research into the mechanisms of bone metabolic diseases [37].
- Current online health information on osteoporosis often fails to meet basic standards of evidence-based health information, highlighting the urgent need to improve quality to support informed decision-making [3].
What the Evidence Shows
Prevention and Risk Factors
- Prevention of osteoporosis involves maximizing peak bone density and maintaining that bone density [4].
- A bone density-based aging model may facilitate the development of precision medicine strategies in osteoporosis prevention and management [1].
- A nomogram with an online dynamic calculator could facilitate the early prediction, diagnosis, and treatment of osteoporosis [13].
- Machine learning-based prediction models for postmenopausal osteoporosis without fractures demonstrate good discriminative ability but are characterized by a high risk of bias, a lack of calibration performance evaluation, and insufficient validation of clinical utility [56].
- A fracture risk prediction model based on routine blood test markers was successfully developed and validated for patients newly diagnosed with osteoporosis [49].
- Diabetes shows varying associations with bone mineral density at different sites, with significant associations found for type 2 diabetes on femoral neck and total body BMD, and HbA1c on heel BMD [54].
- After adjusting for metabolic confounds, the skeletal benefit of glucagon-like peptide-1 receptor agonists did not translate to meaningful risk reductions in upper extremity fragility fracture [48].
Diagnosis and Screening
- Application of machine learning to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and earlier treatment of osteoporosis or osteopenia [10].
- A simple inexpensive tool has the potential to increase the rate of osteoporosis investigation in an at-risk population [19].
- In a study of distal radial fractures, 92% of intervention subjects were investigated for osteoporosis compared with 23% in the usual-care group [29].
- The treatment of underlying osteoporosis to prevent secondary fractures is rarely initiated after pelvic and vertebral fragility fractures [5].
Pharmacological Treatment
- A randomized controlled trial is expected to provide insights into optimizing teriparatide administration timing to enhance bone formation and reduce fracture risk [15].
- Acupuncture has encouraging efficacy in improving the symptoms of primary osteoporosis for use in clinical practice as a physical intervention [17].
- Jintiange capsules are a good choice for patients with osteoporosis in terms of relieving pain, improving bone mineral density, improving activity function, improving gait, and preventing fracture [51].
Surgical and Orthopaedic Considerations
- There is no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair [20].
- Patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period than nonosteoporotic patients following rotator cuff repair [21].
- Continuous bone cement and standardized treatment for osteoporosis were guarantees of good clinical outcomes for percutaneous vertebroplasty [46].
- Injected bone cement greater than 5.5 ml might be a guarantee of good clinical outcomes for percutaneous vertebroplasty [46].
- Key challenges in enrollment in geriatric fracture trials comparing non-surgical management to surgical management were identified for pelvic fragility fractures [47].
- A phosphocalcic cement technique could be employed in the future to prevent the occurrence of fractures in osteoporotic patients [50].
Fracture Healing and Bone Repair
- There is promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents [25].
- Patients who received parathyroid hormone (1–84) injections accelerated radiographic and clinical fracture healing to 7.8 weeks compared to 12.6 weeks in patients who received no treatment [45].
Physical Activity and Lifestyle
- People with osteoporosis should undertake resistance and impact exercise to maximize bone strength [32].
- People with osteoporosis should undertake activities to improve strength and balance to reduce falls [32].
- People with osteoporosis should undertake spinal extension exercise to improve posture and potentially reduce risk of falls and vertebral fractures [32].
Research Models
- Hypothalamic-pituitary disconnection leads to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation with reduced osteoblast and osteoclast activity after 12 months [26].
Practical Considerations
Prevention and Risk Assessment
- A bone density based aging model approach may facilitate the development of precision medicine strategies in osteoporosis prevention and management [1].
- Machine learning application to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and earlier treatment of osteoporosis or osteopenia [10].
Screening and Diagnosis
- A simple inexpensive tool for distal radius fractures has potential to increase the rate of osteoporosis investigation in an at-risk population [19].
- Intervention subjects with distal radial fractures were investigated for osteoporosis at a rate of 92%, compared with 23% in the usual-care group [29].
- Patients with hand fragility fractures represent a high-risk cohort that is currently underserved by osteoporosis screening pathways [40].
Pharmacological Management
- Treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30% [18].
- Randomized controlled trials are expected to provide insights into optimizing teriparatide administration timing to enhance bone formation and reduce fracture risk [15].
- The efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention [17].
Non-Pharmacological Management
Clinical Gaps and Care Delivery
- Despite established guidelines, low rates of osteoporotic pharmacotherapy were seen in patients who had femoral neck fractures [33].
- Osteoporosis continues to be grossly underdiagnosed in the context of sacral fragility fractures [41].
- Surgical treatment remains underutilized for sacral fragility fractures [41].
Surgical Considerations
Key Evidence
- [L3] This approach may facilitate and support the development of precision medicine strategies in osteoporosis prevention and management. [1] (10.1186/s12891-025-09298-0)
- [L5] Investigators must select a model that best reflects the clinical problem being studied, and the underlying pathophysiology of the osteoporosis in the target patient group. [2] (10.1016/s0020-1383(16)30004-3)
- [Paper] Current OHI on osteoporosis often fails to meet basic standards of EBHI, highlighting the urgent need to improve the quality to support informed decision-making. [3] (10.1186/s12891-026-09711-2)
- [Paper] Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density, although the goal of treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures. [4] (10.1016/s0278-5919(05)70201-5)
- [L5] The treatments vary widely and are not always evidence-based and, unfortunately, treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated. [5] (10.2106/jbjs.26.00966)
- [L1] Based on our dose–response analysis of nine studies, each 1-unit increase in BMI was associated with a 9% reduction in osteoporosis risk. [6] (10.1186/s12891-026-09675-3)
- [L1] This sequential anabolic-to-anti-resorptive therapy may inform treatment guidelines for high-risk postmenopausal populations. [7] (10.1186/s13018-025-06040-3)
- [L4] These findings may help inform strategies for osteoporotic treatment and nutritional care in this patient population. [8] (10.1186/s12891-026-10045-2)
- [Paper] However, there is no perfect model for osteoporosis, but a variety of models appropriate for answering specific questions. [9] (10.1016/s0020-1383(16)30002-x)
- [L2] The findings represent a possible step toward more accessible, cost-effective, automated diagnosis and therefore earlier treatment of osteoporosis/osteopenia. [10] (10.1016/j.jhsa.2024.09.008)
- [L4] It is the authors' opinion that such patients should be screened for osteoporosis. [11] (10.1016/j.jhsb.2004.05.002)
- [Paper] IN-CAL is less effective than bisphosphonates and modern anabolic agents for increasing BMD and reducing fracture risk; accordingly, its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference. [12] (10.2106/jbjs.rvw.26.00021)
- [L3] Ultimately, this tool could facilitate the early prediction, diagnosis, and treatment of osteoporosis, thus contributing to the bone health of the elderly population and promoting the development of public health. [13] (10.1186/s12891-026-09920-9)
- [L4] There is evidence of a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada. [14] (10.1186/1471-2474-5-11)
- [L2] This trial is expected to provide crucial insights into optimizing teriparatide administration timing, potentially guiding personalized dosing strategies to enhance bone formation and reduce fracture risk in osteoporosis. [15] (10.1186/s13018-025-06083-6)
- [L1] The current evidence suggests that the efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention. [17] (10.1186/s13018-025-05513-9)
- [Paper] Randomized controlled trials have demonstrated that treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30%. [18] (10.1016/s0020-1383(16)30014-6)
- [L1] This simple inexpensive tool has potential to increase the rate of osteoporosis investigation in an at-risk population. [19] (10.1197/j.jht.2003.10.030)
- [L3] Despite previous literature showing the negative effect of osteoporosis on rotator cuff healing, our data showed no relationship between decreased bone mineral density and 2-year clinical outcomes following RCR. [20] (10.1016/j.jse.2025.02.011)
- [L3] In addition, patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period than nonosteoporotic patient. [21] (10.1016/j.xrrt.2026.100723)
- [L4] This paper summarises recent research progress on natural TCM products in preventing and treating osteoporosis and provides a theoretical and experimental basis for the development of new drugs and the improvement of osteoporosis management. [22] (10.1186/s13018-025-05879-w)
- [L4] Prior bisphosphonate treatment affects the mineralization pattern of the tissue repair consistently with a reduction in bone turnover as found in post-menopausal osteoporotic women, but does not abolish the repair process. [23] (10.1002/jor.22026)
- [Paper] Therefore, evidence of early changes in bone geometry and increased bone turnover could be used to detect osteoporosis before estrogen deficiency has adversely affected bone strength. [24] (10.1002/jor.20961)
- [Paper] There is some promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents. [25] (10.1016/s0020-1383(16)30003-1)
- [Paper] HPD leads after 12 month to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation, with reduced osteoblast and osteoclast activity, as compared to controls (OVX). [26] (10.1002/jor.22066)
- [L4] The results of our study evidenced the need of a program for secondary osteoporotic fracture prevention; this program has now been developed and is active at our institution. [27] (10.1177/1558944716660555dj)
- [Paper] These data confirm a good in vivo behavior of the system, as well as a therapeutic effect of the released calcitonin in the osteopenic condition. [28] (10.1016/s0736-0266(01)00074-7)
- [L2] Results indicate that 92% of the intervention subjects were investigated for osteoporosis, compared with the usual-care group, in which only 23% were investigated. [29] (10.1197/j.jht.2004.04.001)
- [L4] In humans, de novo use of bisphosphonate therapy after fracture does not appear to have a significant effect on fracture healing. [30] (10.1016/s0020-1383(16)30015-8)
- [L3] Overall rates of complication were low and osteoporosis should not be considered a contraindication to arthroscopic RCR. [31] (10.1016/j.jseint.2026.101678)
- [L5] Key recommendations are that people with osteoporosis should undertake (1) resistance and impact exercise to maximise bone strength; (2) activities to improve strength and balance to reduce falls; (3) spinal extension exercise to improve posture and potentially reduce risk of falls and vertebral fractures. [32] (10.1136/bjsports-2021-104634)
- [L3] Despite established guidelines, low rates of osteoporotic pharmacotherapy were seen in patients who had femoral neck fractures. [33] (10.1016/j.arth.2025.07.028)
- [Paper] These findings are exploratory and hypothesis-generating and require validation in bone marrow-specific and functional studies. [34] (10.1186/s13018-026-06905-1)
- [Paper] These findings suggest that the gut microbiota–metabolite–bone network may be involved in the skeletal effects of leptin, providing novel mechanistic insights and potential therapeutic strategies for osteoporosis management. [35] (10.1186/s12891-026-09950-3)
- [Paper] This mechanism inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis. [36] (10.1186/s13018-023-03918-y)
- [L5] It explores the potential applications of these multiscale approaches in fracture risk assessment, the design of patient-specific implants, and research into the mechanisms of bone metabolic diseases. [37] (10.1016/j.injury.2026.113659)
- [Paper] However, these cracks were shorter than in control or OVX groups which may provide one explanation as to why increased damage levels following bisphosphonate treatment have not lead to increased fractures. [38] (10.1002/jor.21229)
- [Paper] The effect of OVX on fracture repair was to delay healing as evidenced by histological and radiological analysis, and the evidence suggests that the deleterious effect might be more related to change of structure than to loss of BMD. [39] (10.1002/jor.20505)
- [L3] Patients with hand fragility fractures represent a high-risk cohort that is currently underserved by osteoporosis screening pathways. [40] (10.1016/j.injury.2026.113261)
- [L4] While cross-sectional imaging use has expanded, surgical treatment remains underutilized, and osteoporosis continues to be grossly underdiagnosed. [41] (10.1016/j.injury.2025.112850)
- [Paper] Fracture healing in SAMP6 mice is not detrimentally affected by impairment of BMSC osteogenesis, suggesting that bone marrow-mediated repair processes are dispensable for normal bone healing in this senile osteoporotic fracture model. [42] (10.1002/jor.21041)
- [L4] They also have diminished bone mass, which might make a bone more likely to break. [43] (10.1016/0363-5023(88)90227-4)
- [L3] Although bone quality may be diminished in the elderly, this does not influence the occurrence of nonunion. [44] (10.1016/s0020-1383(11)70106-1)
- [Paper] Patients who received the PTH (1–84) injections accelerated radiographic and clinical fracture healing (7.8 weeks) when compared to patients who received no treatment (12.6 weeks). [45] (10.1016/s0020-1383(16)30009-2)
- [L3] Continuous bone cement and standardized treatment for osteoporosis were guarantees of good clinical outcomes for PVP, and injected bone cement >5.5 ml might be a guarantee. [46] (10.1186/s12891-024-08153-y)
- [L2] Key challenges in enrollment in geriatric fracture trials comparing NSM to SM were identified. [47] (10.1016/j.injury.2025.112462)
- [L3] After adjusting for metabolic confounds, we found that the postulated skeletal benefit of GLP 1RAs did not translate to meaningful risk reductions in this population. [48] (10.1016/j.injury.2026.113456)
- [L3] We successfully developed and validated a fracture risk prediction model for patients newly diagnosed with osteoporosis. [49] (10.1186/s12891-026-09768-z)
- [L5] This technique could be employed in the future to prevent the occurrence of fractures in osteoporotic patients. [50] (10.1016/j.main.2003.12.003)
- [L1] In terms of relieving pain, improving BMD, improving activity function, and improving gait and preventing fracture, JTG is a good choice for patients with osteoporosis (OP). [51] (10.1186/s12891-025-08694-w)
- [L4] It was clearly demonstrated that the ability of monocytes to fuse declines significantly in patients with osteoporosis. [52] (10.1002/jor.1100180215)
- [Paper] The results show varying associations across different BMD sites (femoral neck, lumbar spine, heel, total body) and methods (IVW, MR-Egger, Weighted median), with some significant associations found for T2D on femoral neck and total body BMD, and HbA1c on heel BMD. [54] (10.1186/s12891-024-07430-0)
- [L1] Current machine learning-based prediction models for postmenopausal osteoporosis without fractures demonstrate good discriminative ability but are generally characterized by a high risk of bias, a notable lack of calibration performance evaluation, and insufficient validation of clinical utility. [56] (10.1186/s12891-025-09385-2)
References
[1] Unveiling risk factors and predicting osteoporosis through bone density based aging model: a community-based cohort in Guangdong, China. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09298-0
[2] Main differences in osteoporotic fracture models: which should I use?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30004-3
[3] Mapping the quality of information on osteoporosis: a cross-sectional analysis of online health information. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09711-2
[4] BONE HEALTH AND OSTEOPOROSIS. Clinics in Sports Medicine. 2000. DOI: 10.1016/s0278-5919(05)70201-5
[5] The Management of Pelvic and Vertebral Fragility Fractures: An Unmet Care Need. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.26.00966
[6] The association between body mass index and osteoporosis, with consideration of sex differences: a systematic review and dose-response meta-analysis. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09675-3
[7] Effectiveness of anabolic and anti-resorptive agents for preventing postmenopausal osteoporosis fractures: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06040-3
[8] Osteoporosis in long-term hospitalized patients with muscular dystrophy: a retrospective cross-sectional study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-10045-2
[9] Can we induce osteoporosis in animals comparable to the human situation?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30002-x
[10] Application of Machine Learning to Osteoporosis and Osteopenia Screening Using Hand Radiographs. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.09.008
[11] The Distal Radial Fracture in Elderly Women and the Bone Mineral Density of the Lumbar Spine and Hip. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2004.05.002
[12] Revisiting Intranasal Salmon Calcitonin: Historical Osteoporosis Evidence and a Potential Role in Acute Orthopaedic Pain Management. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00021
[13] A nomogram with online dynamic calculator for predicting osteoporosis: development and validation based on NHANES. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09920-9
[14] The osteoporosis care gap in Canada. BMC Musculoskeletal Disorders. 2004. DOI: 10.1186/1471-2474-5-11
[15] Timing optimization of teriparatide dosing for postmenopausal osteoporosis: a randomized controlled trial. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06083-6
[17] Efficacy of acupuncture for primary osteoporosis: a systematic review and meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05513-9
[18] Medical management of osteoporosis and the surgeons' role. Injury. 2016. DOI: 10.1016/s0020-1383(16)30014-6
[19] Wristwatch: distal radius fractures as a marker for osteoporosis investigation. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2003.10.030
[20] No difference in 2-year outcomes of arthroscopic rotator cuff repair in patients with osteoporosis. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.011
[21] Impact of osteoporosis on post-operative outcomes following rotator cuff repair. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100723
[22] Natural traditional Chinese medicine products: emerging therapeutic targets for the treatment of osteoporosis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05879-w
[23] Mineralization pattern of vertebral bone material following fragility fracture of the spine. Journal of Orthopaedic Research. 2012. DOI: 10.1002/jor.22026
[24] Structural adaptation and intracortical bone turnover in an ovine model of osteoporosis. Journal of Orthopaedic Research. 2009. DOI: 10.1002/jor.20961
[25] Fracture repair: general aspects and influence of osteoporosis and anti-osteoporosis treatment. Injury. 2016. DOI: 10.1016/s0020-1383(16)30003-1
[26] Low turnover osteoporosis in sheep induced by hypothalamic‐pituitary disconnection. Journal of Orthopaedic Research. 2012. DOI: 10.1002/jor.22066
[27] Incidence of Anti-osteoporosis Diagnosis and Treatment After Distal Radius Fractures. HAND. 2016. DOI: 10.1177/1558944716660555dj
[28] Calcitonin release system in the treatment of experimental osteoporosis. Histomorphometric evaluation. Journal of Orthopaedic Research. 2001. DOI: 10.1016/s0736-0266(01)00074-7
[29] Wristwatch—distal radial fracture as a marker for osteoporosis investigation:. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.001
[30] How do bisphosphonates affect fracture healing?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30015-8
[31] Osteoporosis is a risk factor for complications and reoperations at 1 and 3 years after arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101678
[32] Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022. DOI: 10.1136/bjsports-2021-104634
[33] A Missed Opportunity? Osteoporosis Treatment Following Femoral Neck Fractures: Reducing the Risk of Secondary Hip Fracture. The Journal of Arthroplasty. 2026. DOI: 10.1016/j.arth.2025.07.028
[34] Macrophage polarization-related genes with potential causal roles in osteoporosis: a multi-omics Mendelian randomization study. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06905-1
[35] Role and mechanism of leptin in improving osteoporosis via the “gut–bone axis”. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09950-3
[36] MiR-137 promotes TLR4/NF-κB pathway activity through targeting KDM4A, inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis. Journal of Orthopaedic Surgery and Research. 2023. DOI: 10.1186/s13018-023-03918-y
[37] Progress in Multiscale Biomechanical Assessment of Cancellous Bone: From Bone Density to Multiscale Mechanical Phenotypes. Injury. 2026. DOI: 10.1016/j.injury.2026.113659
[38] Effects of estrogen deficiency and bisphosphonate therapy on osteocyte viability and microdamage accumulation in an ovine model of osteoporosis. Journal of Orthopaedic Research. 2010. DOI: 10.1002/jor.21229
[39] Effect of osteoporosis on bone mineral density and fracture repair in a rat femoral fracture model. Journal of Orthopaedic Research. 2007. DOI: 10.1002/jor.20505
[40] Hand fragility fractures as a missed opportunity for secondary prevention: A retrospective cohort study and assessment of the Second Metacarpal Cortical Index. Injury. 2026. DOI: 10.1016/j.injury.2026.113261
[41] Epidemiology, imaging, and management trends in sacral fragility fractures: A 19-year nationwide analysis in Germany. Injury. 2025. DOI: 10.1016/j.injury.2025.112850
[42] Influence of defective bone marrow osteogenesis on fracture repair in an experimental model of senile osteoporosis. Journal of Orthopaedic Research. 2010. DOI: 10.1002/jor.21041
[43] Postural stability and bone density in postmenopausal women with distal radius fractures. The Journal of Hand Surgery. 1988. DOI: 10.1016/0363-5023(88)90227-4
[44] A89 Osteoporosis is not a risk factor for the development of nonunion: a cohort nested case-control study. Injury. 2011. DOI: 10.1016/s0020-1383(11)70106-1
[45] Use of teriparatide in osteoporotic fracture patients. Injury. 2016. DOI: 10.1016/s0020-1383(16)30009-2
[46] Continuity and volume of bone cement and anti osteoporosis treatment were guarantee of good clinical outcomes for percutaneous vertebroplasty: a multicenter study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08153-y
[47] Randomized trial of surgery vs. non-surgical management for pelvic fragility fractures. Injury. 2025. DOI: 10.1016/j.injury.2025.112462
[48] Glucagon-like peptide-1 receptor agonist use for type 2 diabetes and risk of upper extremity fragility fracture. Injury. 2026. DOI: 10.1016/j.injury.2026.113456
[49] SuperLearner approach for predicting imminent risk of fracture in older Chinese patients with newly diagnosed osteoporosis based on their routine blood test markers. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09768-z
[50] Augmentation expérimentale de la résistance du radius distal ostéoporotique par un ciment phosphocalcique. Chirurgie de la Main. 2004. DOI: 10.1016/j.main.2003.12.003
[51] The effect of Jintiange capsules on pain in patients with primary osteoporosis: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08694-w
[52] Ability of osteoclast formation from peripheral monocytes using anti‐fusion regulatory protein‐1/cd98/4f2 monoclonal antibodies in patients with osteoporosis. Journal of Orthopaedic Research. 2000. DOI: 10.1002/jor.1100180215
[54] Diabetes and osteoporosis: a two-sample mendelian randomization study. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07430-0
[56] Risk prediction models for postmenopausal osteoporosis: a systematic review and meta-analysis study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-025-09385-2