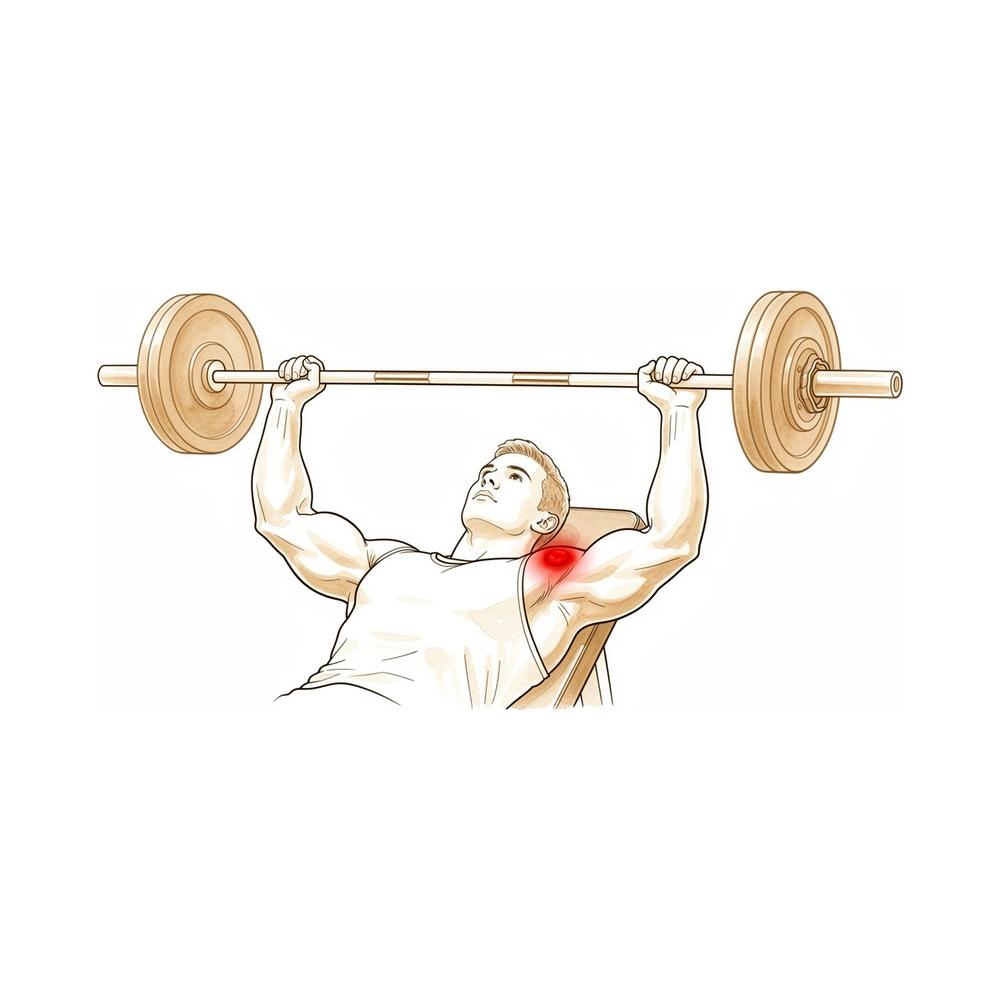
Ang iyong nararamdaman
Ang sakit ay nasa panlabas na dulo ng iyong collarbone, mismo kung saan ito nakikipagdugtong sa ibabaw ng iyong balikat. Ang bahaging ito ay tinatawag na acromioclavicular joint. May tendensiyang pinakamasakit ito kapag ginagamit mo ang braso, lalo na sa mga galaw na pagtulak, pagbubuhat o pagdiin, at karaniwan itong humuhupa kapag nagpapahinga ka.
Ang weight training ay isang karaniwang nag-uudyok nito. Ang bench pressing at iba pang mabigat na pagbubuhat ay direktang nagpapabigat sa joint na ito, at madalas na unti-unting tumitindi ang sakit sa loob ng ilang linggo ng training sa halip na lumitaw mula sa iisang malinaw na pinsala. Napapansin din ito ng ilang tao pagkatapos ng pinsala sa balikat, kapag nagtatagal ang sakit matagal pa matapos kumalma ang natitirang bahagi ng balikat.
Maaaring sumiklab ang kirot sa gabi o pagkatapos ng isang session sa gym. Ang pag-abot sa kabila ng iyong katawan, pagtulak pataas mula sa upuan, pagdadala ng pinamili sa panig na iyon o pagtulak ng lawnmower ay maaaring magpalala nito. Dahil ang pananakit ay nasa pinakaibabaw ng balikat, madali itong mapagkamalang muscle strain sa simula.
Ang kondisyong ito ay maaaring magmukhang kahawig na kahawig ng ibang mga problema sa balikat, kaya ginagamit ang mga scan upang kumpirmahin kung ano ang nangyayari. Ang isang espesyal na X-ray view ng joint, na kinukuha sa magkabilang panig para maihambing, at isang MRI scan ay maaaring magpakita ng mga pagbabago sa dulo ng collarbone.
Bantayan ang mga palatandaang ito at kumilos ayon dito:
Pumunta sa emergency department sa mismong araw na iyon kung ang iyong braso ay naging mainit, mapula, namamaga at masakit, lalo na kung may lagnat. Pumunta rin sa emergency department sa mismong araw na iyon kung bigla kang nawalan ng pakiramdam o galaw sa braso pagkatapos ng isang pinsala.
Magpatingin sa iyong GP o humingi ng specialist review kung hindi humuhupa ang sakit, lumalala ito sa loob ng mga linggo, ginigising ka nito sa gabi, o pumipigil ito sa iyong pagtatrabaho o paggamit ng iyong braso. Kung hindi mo makontak ang klinika, sa labas ng oras ng opisina o sa weekend, pumunta sa pinakamalapit na emergency department.
Ano ang aktwal na nangyayari
Ang acromioclavicular joint ay isang maliit na joint sa ibabaw ng iyong balikat, kung saan ang panlabas na dulo ng iyong collarbone ay nakikipagtagpo sa isang pasamano ng buto na tinatawag na acromion. Ang collarbone ay nagsisilbing suhay na humahawak sa iyong braso palayo sa iyong dibdib, at ang maliit na joint na ito ay isa sa mga lugar kung saan ito kumokonekta sa shoulder blade. Isang matibay na tali ng mga ligament sa ilalim ang nagpapanatiling nakahanay ang dalawang buto habang ikaw ay nagbubuhat at nagdidiin.
Sa kondisyong ito, ang panlabas na dulo ng collarbone ay nagsisimulang masira. Ang medikal na salita para sa ganitong pagkasira ng buto ay osteolysis. Karaniwang pinapalitan ng katawan ng bagong buto ang pudpod na buto, ngunit dito ay mas mabilis ang pagkasira kaysa sa pagkumpuni, kaya lumalambot at nauubos ang buto sa dulo ng collarbone. Nananatiling maayos ang joint sa itaas nito; ang problema ay limitado sa panig ng collarbone.
Ang pinakakaraniwang nag-uudyok nito ay paulit-ulit na mabigat na pagbibigat sa joint, lalo na ang bench pressing at weight training. Bawat press ay nagtutulak sa dalawang buto ng joint laban sa isa't isa, parang paulit-ulit na pagtapak sa iisang maliit na bahagi ng lupa hanggang sa ito ay maubos. Ang parehong proseso ay maaaring sumunod sa isang pinsala sa balikat, kung saan nagtatagal ang sakit nang ilang linggo hanggang ilang buwan pagkatapos ng orihinal na pagkabangga. Hindi gaanong madalas, maaari itong pasimulan ng isang banayad (low-grade) na impeksyon o ng isang metal plate na ginamit upang hawakan pababa ang collarbone pagkatapos ng dislocation.
Habang nauubos ang buto, nagiging inflamed at namamaga ang joint, kaya unti-unting tumitindi ang kirot sa loob ng mga linggo ng training at sumisiklab ito sa gabi. Nawawala rin ang makinis na pagkakalapat ng nauubos na dulo laban sa acromion, kaya ang pagdiin, pagbubuhat at pag-abot sa kabila ng iyong katawan ay nagkikiskis sa hilaw na buto. Iyan ang sakit na nararamdaman mo sa pinakaibabaw ng iyong balikat.
Ano ang maaari naming gawin tungkol dito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyon na hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Kapag nakumpirma na namin ang diagnosis sa pamamagitan ng iyong history, isang pagsusuri at mga scan, dadaanan namin ang mga paggamot nang sunud-sunod, simula sa pinakasimple.
Ang unang hakbang ay ang pagbabago sa paraan ng pagbibigat mo sa joint. Dahil ang paulit-ulit na mabigat na pagdiin ang nagpapaubos sa buto, ang pagbabawas o pagpapalit sa mga ehersisyong nagpapasiklab nito ay nagbibigay ng pagkakataon sa buto na kumalma. Layunin ng physiotherapy na pakalmahin ang inflammation at panatilihing malakas at gumagalaw ang iyong balikat habang ginagawa mo ito. Para sa mga atletang nasa gitna ng season, pinapayagan ka ng pamamaraang ito na patuloy na maglaro habang gumagana ang paggamot. Kung gaano ito katagal ay nakadepende kung talagang mababago mo ang paraan ng iyong pag-training, at pag-uusapan natin kung ano ang ibig sabihin nito para sa iyong sport o trabaho.
Ang gamot ang susunod na hakbang. Ang mga anti-inflammatory tablet, na minsang tinatawag na NSAIDs, ay nagbabawas ng pamamaga at kirot sa joint. Maaari rin kaming mag-inject ng kombinasyon ng pampamanhid na gamot at cortisone, isang malakas na anti-inflammatory, nang direkta sa joint. Dalawang bagay ang nagagawa ng injection na ito: kinukumpirma nito na ang joint ang pinagmumulan ng iyong sakit, at maaari nitong pakalmahin ang sakit na iyon nang ilang panahon pagkatapos.
Kung ang mga hakbang na ito ay hindi nagbigay sa iyo ng sapat na ginhawa, maaari nating pag-usapan ang operasyon. Tinatanggal ng operasyon ang isang manipis na hiwa ng buto mula sa panlabas na dulo ng iyong collarbone, upang ang hilaw at nauubos na mga ibabaw ay hindi na magkiskisan. Ilang milimetro lamang ng buto ang tinatanggal, at kung may bone spur na dumidiin sa isang kalapit na tendon, inaayos din namin iyon nang sabay. Dadaanan namin kung ano ang kasama sa operasyon, kung ano ang hitsura ng paggaling at kung ano ang kaya at hindi nito kayang baguhin, upang makapagpasya ka kasama namin kung ito ay tama para sa iyo.
Ano ang dapat asahan
Para sa karamihan ng tao, humuhupa ang kondisyong ito kapag huminto na ang pagbibigat na nagdulot nito. Kayang buuing muli ng buto sa dulo ng iyong collarbone ang sarili nito kapag nabawasan ang paulit-ulit na pagdiin at pagbubuhat. Iyan ang tapat na kondisyon: gumagana ang paggamot kapag talagang mababago mo ang paraan ng iyong pag-training o pagtatrabaho. Kung patuloy mong bibigatan ang joint sa parehong paraan, may tendensiyang magpatuloy ang sakit o paulit-ulit itong bumalik.
Ang paggaling nang walang operasyon ay hindi mabilisang solusyon. Unti-unting tumitindi ang kirot sa loob ng mga linggo, at karaniwang inaabot ng ilang linggo hanggang ilang buwan ng pagbabawas bago ito humupa. Sa halip, napapansin naman ng ilang tao ang sakit pagkatapos ng pinsala sa balikat, at sa ganoong kaso maaari itong magtagal matagal pa matapos gumaling ang natitirang bahagi ng balikat. Kung naroon pa rin ang sakit pagkatapos ng makatuwirang panahon ng pahinga at binagong training, mainam na ipasuri ito sa halip na pilitin itong tiisin.
Kung hindi nagbibigay ng sapat na ginhawa ang non-operative care, ang operasyon ay isang opsyon. Tinatanggal ng operasyon ang isang manipis na hiwa ng buto mula sa panlabas na dulo ng iyong collarbone upang tumigil ang pagkikiskisan ng mga hilaw na ibabaw. Ang mga taong sumailalim dito ay nag-uulat ng mas kaunting sakit at mas mabuting galaw ng balikat, at sa pangkalahatan ay nasisiyahan sila sa resulta. May tendensiyang mas kaunti ang natitirang sakit sa keyhole na bersyon kaysa sa open na bersyon, at mas maagang nakababalik ang mga tao sa kanilang mga aktibidad dito.
Ang operasyon ay hindi pangako ng balikat na walang sakit. Kaunting bilang ng mga tao ang nangangailangan ng isa pang operasyon sa kalaunan, sa pagitan ng 4% at 10%. Maaari itong mangyari kung masyadong kaunti o masyadong marami ang butong natanggal, kung may isa pang problema sa balikat na hindi napansin, o kung may bagong butong nabubuo sa joint habang ito ay gumagaling. Pag-uusapan ng iyong surgeon ang mga panganib na ito kasama mo bago ka magpasya ng anuman.
Anumang landas ang piliin mo, iisa ang layunin: pakalmahin ang inflammation, ibalik ang makinis na galaw, at makabalik ka sa paggamit ng iyong braso nang walang matalas na kirot na iyon sa ibabaw ng iyong balikat. Kung ang iyong mga sintomas ay hindi humuhupa, lumalala sa loob ng mga linggo, ginigising ka sa gabi, o pumipigil sa iyong pagtatrabaho o paggamit ng iyong braso, magpatingin sa iyong GP o humingi ng specialist review.
Kailan dapat magpatingin
Madaling mapagkamalang muscle strain ang kondisyong ito, kaya madalas itong hindi napapansin sa simula. Magpatingin sa iyong GP kung nagtatagal ang sakit sa panlabas na dulo ng iyong collarbone pagkatapos ng pinsala sa balikat, kapag na-rule out na ang bali o isang unstable na joint. Humingi ng specialist review kung patuloy na tumitindi ang kirot kasabay ng training, o kung hindi ito humuhupa sa kabila ng pahinga at binagong pagbibigat. Makukumpirma ng mga scan ang diagnosis: isang espesyal na X-ray view na kinukuha sa magkabilang balikat para maihambing, at isang MRI na nagpapakita ng pamamaga sa loob ng dulo ng collarbone. Mahalaga na tama ito, dahil ang parehong sakit ay maaaring magmula sa ibang mga problema sa balikat, at hindi makakatulong ang paggamot na nakatuon sa maling sanhi. Kung ang iyong mga sintomas ay hindi humuhupa, lumalala sa loob ng mga linggo, ginigising ka sa gabi, o pumipigil sa iyong pagtatrabaho o paggamit ng iyong braso, magpatingin sa iyong GP o humingi ng specialist review. Kung hindi mo makontak ang klinika, sa labas ng oras ng opisina o sa weekend, pumunta sa pinakamalapit na emergency department.
Higit pang detalye
Advanced reading: the deeper science (optional)
Ang seksyong ito ay mas malalim kaysa sa kailangan mo para sa iyong sariling mga desisyon sa paggamot. Ang distal clavicle osteolysis ay karapat-dapat sa karagdagang pagbabasa dahil halos laging natutukoy ang sanhi, karamihan sa mga tao ay gumagaling nang walang operasyon, at ang mahirap na bahagi ay kung talagang mababago ang loading na nagdulot nito.
Karaniwang natutukoy ang load, at karaniwan itong ang bench press
Pinagsama ng isang scoping review noong 2026 ang 8 pag-aaral na sumasaklaw sa 483 pasyente at nakitang ang bench pressing ang nag-iisang pinakakaraniwang aktibidad na nag-uudyok nito sa 49.1%, at ang pangkalahatang weight training ay karagdagang 24.4% [1]. Ang sakit sa panlabas na dulo ng collarbone o sa acromioclavicular joint ang pangunahing sintomas sa 69.9% ng mga pasyente [1]. Ang serye na unang naglarawan sa kondisyon ay nakakita ng parehong pattern: sa 46 na lalaki na na-diagnose na may osteolysis at walang history ng acute injury, 45 ang nagbubuhat ng weights bilang bahagi ng kanilang training [2].
Karamihan ay kumakalma nang walang operasyon, ngunit kung talagang nagbabago lamang ang loading
Sa pinagsamang review, karamihan sa mga pasyente ay gumaling sa conservative care, at 16% ang humantong sa operasyon matapos mabigo ang conservative treatment [1]. Isang mas maliit na grupo, 4.4% (3 pasyente), ang humantong sa operasyon dahil lumala ang sakit sa istruktura o dahil ayaw nilang baguhin ang kanilang load dahil sa sport o trabaho [1]. Ang huling grupong iyon ang tapat na bersyon ng problema: gumagana ang non-operative treatment kapag talagang humihinto ang aktibidad na nag-uudyok nito, at bihirang nasa paggawa ng diagnosis ang kahirapan.
Kapag ginawa ang resection, kaunting buto lamang ang tinatanggal at mabilis ang paggaling
Sa isang serye ng mga weight lifter, ang isang limitadong arthroscopic resection na may average na 4.5 mm ay nagpahintulot ng pagbabalik sa sport sa average na 3.2 araw at sa preoperative na weight-training programme sa 9.1 araw, kung saan lahat ng pasyente ay nagpatuloy sa training at nagdagdag ng kanilang load pagkatapos [3]. Isang modernong prospective series ng 59 na pasyente na sinubaybayan nang hindi bababa sa dalawang taon ang nag-ulat na bumaba ang sakit mula 8.20 hanggang 1.36 sa 10 at ang SPADI disability mula 62.65 hanggang 6.13 pagsapit ng 24 na buwan, na may pagbabalik sa sport sa 1.72 buwan at sa trabaho sa 3.02 buwan [4]. Sa orihinal na serye, isinagawa ang resection sa 21 pasyente at naibsan nito ang mga sintomas sa lahat ng 19 na sinubaybayan [2].
Kinukumpirma ito ng imaging; hindi sapat ang clinical picture lamang
Ang sariling konklusyon ng review ay ang mga clinical sign at sintomas ng kondisyong ito ay hindi maihiwalay sa ibang mga problema sa balikat [1]. Ang MRI ang pinakamadalas gamiting pagsusuri, na nagpapakita ng marrow oedema at subchondral fracture sa dulo ng collarbone, at malinaw na sinasabi ng mga may-akda na dapat itong bigyang-kahulugan kasabay ng pagsusuri sa pasyente sa halip na kapalit nito [1]. Sa praktika, iyan ang dahilan kung bakit ang history — kung ano ang binubuhat mo, gaano kadalas, at gaano kabigat — ay kasinghalaga ng scan.
Mga Sanggunian
[1] Wilkinson M, Groch N, Freestone C, et al. Risk factors and management of atraumatic distal clavicular osteolysis: a scoping review. Shoulder Elbow. 2026. https://doi.org/10.1177/17585732261479715 [2] Cahill BR. Osteolysis of the distal part of the clavicle in male athletes. J Bone Joint Surg Am. 1982;64(7):1053-58. https://doi.org/10.2106/00004623-198264070-00015 [3] Auge WK, Fischer RA. Arthroscopic distal clavicle resection for isolated atraumatic osteolysis in weight lifters. Am J Sports Med. 1998;26(2):189-92. https://doi.org/10.1177/03635465980260020701 [4] Leon JV, Hermans D, Venkatesha V, et al. Patient outcomes following arthroscopic distal clavicle excision: a prospective case series. JSES Int. 2023;7(6):2400-05. https://doi.org/10.1016/j.jseint.2023.07.014
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Clinical Presentation and Diagnosis
- Clinical signs and symptoms for atraumatic distal clavicular osteolysis are not distinguishable from other shoulder pathologies [1].
- Post-traumatic osteolysis of the distal clavicle should be considered if there is persistent pain after a shoulder injury and bony lesions or instabilities have been excluded [3].
- Osteolysis of the distal end of the clavicle is a rare condition that can occur during judo [5].
- Special care must be taken to properly identify the acromioclavicular joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure [22].
Etiology and Pathogenesis
- Propionibacterium acnes–mediated distal clavicular osteolysis is a documented etiology [2].
- Heterotopic bone formation is a more common cause of failure of acromioplasty or distal claviculectomy than is acknowledged by the literature [13].
- Subacromial osteolysis can occur following hook plate fixation for acromioclavicular dislocation [4].
- The risk of subacromial osteolysis following hook plate fixation is minimized by removing the implant within 5.5 months and preventing severe osteolysis by removal no more than 11.9 months after surgery [15].
- Maintaining the acromion-hook angle at 10 degrees or less is recommended to minimize the risk of subacromial osteolysis following hook plate fixation [15].
Surgical Management
- The combination of distal clavicle resection and antibiotics halted osteolysis in a patient with Propionibacterium acnes–mediated disease, who remained symptom-free at 10 months after surgery [2].
- Arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures in carefully selected patients with isolated acromioclavicular joint pathology [7].
- Arthroscopic and open distal clavicle excisions both provide significant pain reduction at 1 year with no significant difference in outcome measures between groups, except for VAS pain score improvement [9].
- Patients undergoing arthroscopic distal clavicle excision for acromioclavicular joint pathology can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [11].
- Limited distal clavicle excision of patients with acromioclavicular joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up [14].
- Open and arthroscopic distal clavicle excision are both effective surgeries to treat recalcitrant acromioclavicular joint pain, providing similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up [32].
- Less residual pain was found using the arthroscopic technique compared to the open technique for distal clavicle excision [32].
- Both the direct superior approach and the indirect subacromial approach to arthroscopic distal clavicle resection result in successful clinical outcome with clinically insignificant difference at final follow-up [24].
- A well-performed distal clavicle excision will likely perform better than a poorly performed one, regardless of whether an open or arthroscopic approach is chosen [21].
- Portal placement remains paramount in both facilitating surgery and avoiding injury to adjacent extra-articular structures regardless of the technique chosen for distal clavicle resection [19].
- Intraoperative use of ultrasound and cannulated dilators allows surgeons to perform distal clavicle excisions in a more efficient, reproducible, and safer manner [33].
- The supraspinatus fossa portal technique provides a technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement [38].
- Coracoclavicular ligament reconstruction is an effective surgical approach for decreasing the incidence of subacromial osteolysis following hook plate fixation [4].
Surgical Technique and Biomechanics
- A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model, whereas excision with 2.5 mm of bone was successful in many specimens [16].
- Surgery for osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint may involve resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon [10].
Indications and Contraindications
- Routine distal clavicle resection in the setting of rotator cuff repair does not result in improved outcomes for patients with no difference being observed at 24 months post surgery [23].
- Distal clavicle resection in patients with rotator cuff tears did not result in better clinical outcome scores or shoulder range of motion and was not associated with a lower risk of reoperation [26].
- Routine distal clavicle excision is not absolutely necessary, even in patients with symptomatic acromioclavicular joint osteoarthritis [29].
Anatomy & Pathophysiology
Bony Anatomy
- The clavicle is the only long bone to ossify by intramembranous ossification [39].
- The clavicle serves as the primary stabilizer between the axial skeleton via the sternoclavicular joint and the appendicular skeleton via the acromioclavicular joint [39].
- The clavicle forms a unique S-shaped curve on the axial view [39].
- The distal clavicle is flat in the AP plane [39].
- The primary blood supply to the clavicle is periosteal, with no nutrient blood supply [39].
- The clavicle is subcutaneous, and its muscular envelope includes the platysma, pectoralis major, deltoid, and some of the strap muscles of the neck [39].
- In the transverse plane, the clavicle resembles an italic S [52].
- The greater radius of curvature of the clavicle occurs at its medial curve, which is anteriorly convex [52].
- The smaller lateral curve of the clavicle is posteriorly convex [52].
- The bone is somewhat rounded in its midsection and medially and relatively flat laterally [52].
- The medial end of the clavicle has a 30% incidence of a rhomboid fossa on its inferior surface where the costoclavicular ligaments insert [52].
- The medial end of the clavicle has a 2.5% incidence of actual articular surface facing inferiorly toward the first rib [52].
- The middle portion of the clavicle contains the subclavian groove where the subclavius muscle has a fleshy insertion [52].
- The lateral portion of the clavicle has the coracoclavicular process when present [52].
- The conoid ligament attaches to the clavicle at the conoid tubercle [52].
- The trapezoid ligament attaches at the trapezoid line, which lies in an anteroposterior direction just lateral to the conoid tubercle [52].
- The distance from the lateral edge of the clavicle to the medial edge of the conoid tubercle is approximately 45 mm in male and female specimens [52].
- The distance from the lateral edge of the clavicle to the center of the trapezoid tuberosity is approximately 25 mm in male and female specimens [52].
- The trapezius inserts on the posterosuperior surface of the distal end of the clavicle [52].
- The subclavius muscle has a fleshy insertion on the inferior surface of the middle third of the clavicle [52].
- The deltoid originates on the anterior portion of the inner surface of the lateral curve of the clavicle [52].
- The pectoralis major originates from the anterior portion of the medial two-thirds of the clavicle [52].
- The sternocleidomastoid largely originates on the posterior portion of the middle third of the clavicle [52].
- The sternohyoid originates on the clavicle just medial to the origin of the sternocleidomastoid [52].
- The subclavian vein and artery and brachial plexus lie posterior to the clavicle [52].
- The medial anterior curve of the clavicle is often described as an accommodation for the subclavian vein and artery and brachial plexus [52].
- The clavicle is one of the first bones to ossify, beginning from two primary ossification centers (medial and lateral) by 5 to 6 weeks of gestation [51].
- By 7 to 8 weeks of gestation, the clavicle has already assumed its overall contour and “S” shape [51].
- Most growth (80%) of the clavicle occurs from the medial physis [51].
- The lateral epiphysis of the clavicle forms and fuses at around 18 to 19 years of age [51].
- The medial epiphysis of the clavicle is the last in the body to ossify, at the age of 18 to 20 years [51].
- The medial epiphysis of the clavicle is the last to complete ossification, at the age of 23 to 25 years [51].
Ligaments and Soft Tissue Stabilizers
- The coracoclavicular ligaments consist of the conoid (medial) and trapezoid (lateral) components [39].
- The coracoclavicular ligaments are the primary stabilizers to superior (vertical) translation of the distal clavicle [39].
- The superior shoulder suspensory complex is a bone–soft-tissue ring that provides a stable connection of the glenoid and scapula to the clavicle [39].
- The superior shoulder suspensory complex is composed of four bony landmarks: distal clavicle, acromion, coracoid process, and glenoid neck [39].
- The superior shoulder suspensory complex includes the supporting ligamentous complexes of the AC joint and the CC ligaments [39].
- The acromion has three ossification centers: the meta-acromion (base), the mesoacromion (mid), and the preacromion (tip) [50].
- The coracoid process is the site of ligament attachments for the CC ligaments [50].
- The superior shoulder suspensory complex plays an important role in shoulder stability and biomechanics [50].
- The pectoralis major muscle originates from the clavicular shaft anteroinferiorly [56].
- The sternocleidomastoid originates superiorly on the clavicle [56].
- The pectoralis origin merges with the origin of the anterior deltoid laterally [56].
- The trapezius insertion blends superiorly with the deltoid origin at the lateral margin of the clavicle [56].
- The subclavius muscle inserts on the undersurface of the clavicle [56].
- The platysma usually envelopes the anterior and superior aspects of the clavicle and runs in the subcutaneous tissues [56].
- The supraclavicular nerves originate from cervical roots C3 and C4 [58].
- The supraclavicular nerves exit from a common trunk behind the posterior border of the sternocleidomastoid muscle [58].
- There are typically three major branches of the supraclavicular nerves (anterior, middle, and posterior) that cross the clavicle superficially from medial to lateral [58].
- The subclavian vein runs directly below the subclavius muscle and above the first rib [58].
- The subclavian artery and the brachial plexus lie more posteriorly than the subclavian vein, separated from the vein and clavicle by the scalenus anterior muscle medially [58].
- The brachial plexus is closest to the clavicle in its midportion [58].
- In the middle third of the clavicle, the subclavian artery is a mean of 17 mm from the clavicle [58].
- In the middle third of the clavicle, the subclavian vein is a mean of 13 mm from the clavicle [58].
- In the middle third of the clavicle, the subclavian vessels are located at an approximate angle of 60 degrees to the horizontal [58].
- Laterally, the subclavian artery is a mean of 63 mm from the clavicle [58].
- Laterally, the subclavian vein is a mean of 76 mm from the clavicle [58].
Pathophysiology
- Clinical signs and symptoms for atraumatic distal clavicular osteolysis were not distinguishable from other shoulder pathologies [1].
- Post-traumatic osteolysis of the distal clavicle occurs from several weeks to several months after injury to the acromioclavicular joint [17].
- In post-traumatic osteolysis, radiographs show no luxation or fracture initially [17].
- Shoulder pain in post-traumatic osteolysis develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [17].
- The process of osteolysis in post-traumatic distal clavicle osteolysis occurs only in the distal clavicle, and there is no osteolytic lesion in the acromion [17].
- Post-traumatic osteolysis of the distal clavicle was first described by Werder in 1950 [17].
- More than 100 cases of post-traumatic osteolysis have been reported [17].
- The pathogenesis of post-traumatic osteolysis remains unclear [17].
- Osteoclastic resorption has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Nervous system dysfunction has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Avascular necrosis has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Microfracture has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Synovial invasion has been hypothesized as a pathogenesis for post-traumatic osteolysis [17].
- Non-traumatic osteolysis of the acromial end of the clavicle should be considered in cases of pain in the shoulder in athletes [6].
- It is important to consider the possibility of post-traumatic osteolysis of the distal clavicle if there is persistent pain after a shoulder injury, and bony lesions or instabilities have been excluded [3].
- The combination of distal clavicle resection and antibiotics halted the osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis [2].
- The patient with Propionibacterium acnes–mediated distal clavicular osteolysis remained symptom free at 10 months after surgery [2].
- For all patients with atraumatic osteolysis of the distal clavicle, return to sports activities was dependent on changes in the way of training [8].
- Distal clavicle excision is a widely accepted surgical treatment for symptomatic acromioclavicular joint pathology, including osteoarthritis, post-traumatic degeneration, and osteolysis [47].
- Mechanisms of failure following distal clavicle excision include inadequate resection [47].
- Mechanisms of failure following distal clavicle excision include excessive bone removal resulting in instability [47].
- Mechanisms of failure following distal clavicle excision include unrecognized concomitant pathology [47].
- Mechanisms of failure following distal clavicle excision include iatrogenic disruption of the coracoclavicular ligaments [47].
- The reported incidence of reoperation following distal clavicle excision ranges from 4% to 10% [47].
- A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness [35].
- If the resection was 2.5 mm or less, abutment was likely to occur between the acromion and the clavicle, particularly inferiorly and posteriorly [53].
- Joint stiffness diminished with the amount of bone resected [53].
- Resection of more than 7.6 mm of the distal clavicle in men can violate the superior AC ligament [53].
- Resection of more than 5.2 mm of the distal clavicle in women can violate the superior AC ligament [53].
- Resection of less than 11.0 mm should never violate any portion of the trapezoid ligament in 98% of men or women [53].
- Resection of less than 24.0 mm should never violate any of the conoid ligament [53].
- Patients with a resection of more than 1.0 cm have more pain than patients with less than 1 cm of resection [53].
- The anterior-posterior load to clinical failure of the AC joint after 5 mm of resection from the distal clavicle and medial acromion is significantly greater than 1 cm of the resected distal clavicle alone [77].
- Intact acromioclavicular ligaments protect the coracoclavicular reconstruction by decreasing the in situ graft force [75].
- Inaccurate resection from lack of depth perception and inadequate visualization has been reported to lead to failure and revision surgery [28].
Classification
- Distal clavicular osteolysis presents as isolated pain at the distal clavicle and acromioclavicular joint that tends to worsen with activity [27].
- There are two forms of distal clavicular osteolysis: posttraumatic distal clavicular osteolysis caused by a direct traumatic injury, and atraumatic distal clavicular osteolysis attributable to repetitive stress [27].
- In adults, the most common risk factor for stress-induced distal clavicular osteolysis is weightlifting [27].
- Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than is generally recognized, with many cases potentially overlooked or misinterpreted [17].
- In post-traumatic osteolysis, radiographs initially show no luxation or fracture, followed by gradual development of shoulder pain, swelling of the acromioclavicular joint, and limitation of shoulder motion [17].
- The process of post-traumatic osteolysis occurs only in the distal clavicle, with no osteolytic lesion in the acromion [17].
- Hypothesized pathogenesis for post-traumatic osteolysis includes osteoclastic resorption, nervous system dysfunction, avascular necrosis, microfracture, and synovial invasion [17].
- Propionibacterium acnes–mediated distal clavicular osteolysis is a recognized etiology for the condition [2].
- Aseptic foreign-body reaction to Gore-Tex grafts used for clavicle-to-coracoid stabilization can result in clavicle osteolysis [20].
- Prolonged implant retention and higher-grade fracture types significantly increase the risk of subacromial osteolysis following hook plate fixation [78].
Clinical Presentation
Symptoms and Signs
- Patients with distal clavicular osteolysis present with isolated pain at the distal clavicle and acromioclavicular joint that tends to worsen with activity [27, 65].
- Post-traumatic osteolysis of the distal clavicle is characterized by shoulder pain that develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [17].
- In post-traumatic osteolysis, radiographs initially show no luxation or fracture [17].
- Persistent pain after a shoulder injury, after bony lesions or instabilities have been excluded, should prompt consideration of post-traumatic osteolysis of the distal clavicle [3].
- Non-traumatic osteolysis of the acromial end of the clavicle should be considered in cases of shoulder pain in athletes [6].
- Osteolysis of the distal end of the clavicle can occur during judo [5].
- A 58-year-old male carpenter presented with osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint [10].
Imaging Findings
- Radiographic findings for distal clavicular osteolysis may range from mild osteopenia to overt osteolysis [27, 65].
- The bilateral Zanca view is helpful for diagnosing distal clavicular osteolysis as it profiles the acromioclavicular joint and allows for comparison with the contralateral side [27, 65].
- MRI characteristics of distal clavicular osteolysis include distal clavicular bone marrow edema that is out of proportion to the edema at the acromion [27, 65].
- MRI characteristics of distal clavicular osteolysis include subchondral cystic change [27, 65].
- In advanced cases of distal clavicular osteolysis, periostitis may be observed at the distal clavicle on MRI [27, 65].
- The process of osteolysis in post-traumatic cases occurs only in the distal clavicle, with no osteolytic lesion in the acromion [17].
Risk Factors and Etiology
- Posttraumatic distal clavicular osteolysis is caused by a direct traumatic injury [27, 65].
- Atraumatic distal clavicular osteolysis is attributable to repetitive stress [27, 65].
- Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than generally recognized, with many cases potentially overlooked or misinterpreted [17].
- More than 100 cases of post-traumatic osteolysis have been reported since Werder first described the condition in 1950 [17].
- Propionibacterium acnes infection has been identified as a cause of distal clavicular osteolysis [2].
- Aseptic foreign-body reaction to Gore-Tex grafts can cause clavicle osteolysis [20].
- Bone osteolysis can occur following acromioclavicular joint reconstruction using synthetic ligament (Surgilig™) [31].
Investigations
Clinical Presentation and Diagnosis
- In post-traumatic osteolysis, radiographs typically show no luxation or fracture initially [17].
- The process of osteolysis in post-traumatic distal clavicle injury occurs only in the distal clavicle, with no osteolytic lesion in the acromion [17].
- A high index of suspicion is needed to diagnose complications such as osteolysis early before irretrievable bone loss [31].
Imaging and Anatomical Landmarks
- Special care must be taken to properly identify the AC joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure [22].
- The cross-sectional A-frame morphology of the superior cortex of the distal clavicle provides a reproducible landmark that is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle [49].
- The A-frame morphology of the distal clavicle can be used intraoperatively to determine when adequate resection has been completed [49].
Treatment
Non-Operative
- Activity modification, NSAIDs, and physical therapy are first-line treatments for distal clavicular osteolysis [27].
- Intra-articular injection of lidocaine and corticosteroids into the acromioclavicular joint is both diagnostic and therapeutic for distal clavicular osteolysis [27].
- Nonoperative treatment with injections, medication, and physical therapy is a good option for in-season athletes with distal clavicular osteolysis [27].
- The combination of distal clavicle resection and antibiotics halted osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis [2].
Operative
- Distal clavicle resection is the definitive operative treatment for distal clavicular osteolysis failing nonoperative management [27].
- Patients undergoing arthroscopic distal clavicle excision through the direct approach can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [11].
- Open and arthroscopic distal clavicle excision provide similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up, though less residual pain was found using the arthroscopic technique [32].
- A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model [16].
- A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness in a cadaveric model [35].
- Anterior acromioplasty is needed in cases with subacromial impingement during distal clavicle resection [18].
- SLAP lesion repair after initial distal clavicle resection successfully treated 15 patients, indicating that associated or underlying superior labral detachment may cause similar symptoms leading to misdiagnosis [25].
- The use of intraoperative ultrasound and cannulated dilators allows surgeons to perform distal clavicle excisions in a more efficient, reproducible, and safer manner [33].
- The introduction of the supraspinatus fossa portal technique provides a special technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement [38].
- Coracoclavicular ligament reconstruction is an effective surgical approach for decreasing the incidence of subacromial osteolysis following hook plate fixation for acromioclavicular dislocation [4].
- Removing the implant within 5.5 months minimizes osteolysis risk and no more than 11.9 months prevents severe osteolysis, while maintaining the acromion-hook angle at 10 degrees or less [15].
- Foreign-body reaction and osteolysis have been reported with the use of Gore-Tex graft to stabilize the clavicle to the coracoid [20].
Complications
Diagnostic and Pathologic Complications
- Post-traumatic osteolysis of the distal clavicle is an uncommon condition that occurs more often than generally recognized, with many cases overlooked or misinterpreted [17].
- In post-traumatic osteolysis, radiographs initially show no luxation or fracture, and shoulder pain develops gradually with swelling of the acromioclavicular joint and limitation of shoulder motion [17].
- Heterotopic bone formation may be a more common cause of failure of acromioplasty or distal clavicectomy than acknowledged in the literature [30].
- Aseptic foreign-body reaction and clavicle osteolysis can occur following acromioclavicular reconstruction using Gore-Tex graft [20].
- A high index of suspicion is needed to diagnose complications such as osteolysis early before irretrievable bone loss occurs [31].
- Distal clavicle fracture is a complication of arthroscopic distal clavicle resection [22].
- Pre-existing distal clavicle stress fracture or osteolysis must be ruled out before performing the arthroscopic Mumford procedure [22].
Operative Complications and Failure Mechanisms
- Multiple mechanisms of failure following distal clavicle excision include inadequate resection, excessive bone removal resulting in instability, unrecognized concomitant pathology, and iatrogenic disruption of the coracoclavicular ligaments [47].
- A 5 mm resection of the distal clavicle guaranteed no bone-to-bone abutment in a cadaver model, whereas 2.5 mm resection was successful in many specimens [16].
- SLAP lesions can cause continued symptoms and failure of distal clavicle resection due to misdiagnosis of associated or underlying superior labral detachment [25].
- Resection of the lateral end of the clavicle following osteolysis is a described surgical management [6].
- Surgery for osteolysis of the distal clavicle progressing to osteoarthritic change can involve resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon [10].
Outcomes and Prognosis
- A subset of patients experience persistent pain, residual instability, or functional limitation following primary distal clavicle excision that ultimately requires additional surgical intervention [47].
- Outcomes following revision surgery for persistent pain and/or instability after distal clavicle excision remain poorly characterized and are primarily composed of small cohort studies [47].
- Return to sports activities for patients with atraumatic osteolysis of the distal clavicle was dependent on changes in the way of training [8].
- In carefully selected patients with isolated acromioclavicular joint pathology, arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures [7].
Recovery
Post-operative Outcomes and Return to Activity
- Patients undergoing arthroscopic distal clavicle excision, specifically through the direct approach, can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure [11].
Surgical Technique and Biomechanics
Complications and Failure Modes
- The successful treatment of 15 patients by SLAP lesion repair after initial distal clavicle resection indicates that there may be misdiagnosis due to associated or underlying superior labral detachment causing similar symptoms [25].
- A high index of suspicion is needed to diagnose complications such as bone osteolysis following acromioclavicular joint reconstruction using synthetic ligament early before irretrievable bone loss [31].
- The combination of distal clavicle resection and antibiotics halted osteolysis in a case of Propionibacterium acnes–mediated distal clavicular osteolysis, with the patient remaining symptom free at 10 months after surgery [2].
Key Evidence
- [L4] Clinical signs and symptoms for atraumatic distal clavicular osteolysis (ADCO) were not distinguishable from other shoulder pathologies. [1] (10.1177/17585732261479715)
- [Case_report] The combination of distal clavicle resection and antibiotics halted the osteolysis, and the patient has remained symptom free at 10 months after surgery. [2] (10.1016/j.jse.2015.03.004)
- [L4] It is important to consider the possibility of post-traumatic osteolysis of the distal clavicle if there is persistent pain after a shoulder injury, and bony lesions or instabilities have been excluded. [3] (10.1007/bf00573456)
- [L1] The current analysis suggests coracoclavicular ligament reconstruction as an effective surgical approach for decreasing the incidence of subacromial osteolysis. [4] (10.1016/j.jse.2024.03.018)
- [L5] Osteolysis of the distal end of the clavicle is a rare condition and it can occur during judo. [5] (10.1016/s1058-2746(96)80543-x)
- [L4] Non-traumatic osteolysis of the acromial end of the clavicle should be borne in mind in cases of pain in the shoulder in athletes. [6] (10.1016/0020-1383(87)90010-6)
- [L4] In carefully selected patients with isolated ACJ pathology, arthroscopic distal clavicle excision results in statistically and clinically significant improvements in range of motion and patient-reported outcome measures. [7] (10.1016/j.jseint.2023.07.014)
- [L4] For all patients, return to sports activities was dependent on changes in the way of training. [8] (10.1016/s1058-2746(96)80377-6)
- [L1] Arthroscopic and open distal clavicle excisions both provide significant pain reduction at 1 year with no significant difference in outcome measures between groups, except for VAS pain score improvement. [9] (10.1016/j.jse.2006.10.006)
- [L5] A 58-year-old male carpenter with osteolysis of the distal clavicle progressing to osteoarthritic change in the acromioclavicular joint underwent surgery involving resection of the distal clavicle and capsule, transfer of the acromial attachment, and repair of the supraspinatus tendon. [10] (10.1016/s1058-2746(95)80313-0)
- [L3] Among patients undergoing distal clavicle excision for acromioclavicular joint pathology, those having an arthroscopic procedure, specifically through the direct approach, can expect a faster return to activities while obtaining similar long-term outcomes compared with the open procedure. [11] (10.1016/j.arthro.2009.12.007)
- [L4] This retrospective series suggests that heterotopic bone formation is a more common cause of failure of acromioplasty or distal claviculectomy than is acknowledged by the literature. [13] (10.1016/s1058-2746(05)80050-3)
- [L4] Limited distal clavicle excision of patients with AC joint osteoarthritis resistant to conservative treatment reduced pain and improved shoulder function at midterm follow-up. [14] (10.1016/j.otsr.2016.01.008)
- [L3] The authors recommend removing the implant within 5.5 months to minimize osteolysis risk and no more than 11.9 months to prevent severe osteolysis, while maintaining the acromion-hook angle at 10 degrees or less. [15] (10.1016/j.jse.2024.09.027)
- [Abstract] Although distal clavicle excision with 2.5 mm of bone was successful in many specimens, a 5 mm resection guaranteed no bone-to-bone abutment. [16] (10.1016/j.jse.2007.02.105)
- [L5] [17] (10.1067/mse.2002.122229)
- [L4] Additionally, the anterior acromioplasty is needed in the cases with subacromial impingement. [18] (10.1016/s1058-2746(96)80520-9)
- [Case_report] Regardless of the technique chosen for distal clavicle resection, portal placement remains paramount in both facilitating surgery and avoiding injury to adjacent extra-articular structures. [19] (10.1016/j.jse.2010.08.032)
- [L5] The case presented reports foreign-body reaction and osteolysis with the use of Gore-Tex graft to stabilize the clavicle to the coracoid. [20] (10.1016/j.jse.2004.01.027)
- [L5] A well-performed distal clavicle excision will likely perform better than a poorly performed one, regardless of whether an open or arthroscopic approach is chosen. [21] (10.1016/j.arthro.2018.03.004)
- [L4] Special care must be taken to properly identify the AC joint and rule out pre-existing distal clavicle stress fracture or osteolysis before performing the arthroscopic Mumford procedure. [22] (10.1016/j.arthro.2009.02.008)
- [L2] Routine distal clavicle resection in the setting of rotator cuff repair does not result in improved outcomes for patients with no difference being observed at 24 months post surgery. [23] (10.1177/1758573217741124)
- [L2] Both the direct superior approach and the indirect subacromial approach to the arthroscopic distal clavicle resection result in successful clinical outcome with clinically insignificant difference at final follow-up. [24] (10.1177/0363546506294855)
- [L4] The successful treatment of 15 patients by SLAP lesion repair after initial distal clavicle resection indicates that there may be misdiagnosis due to associated or underlying superior labral detachment causing similar symptoms. [25] (10.1016/s1058-2746(96)80319-3)
- [L1] Distal clavicle resection in patients with rotator cuff tears did not result in better clinical outcome scores or shoulder ROM and was not associated with a lower risk of reoperation. [26] (10.1097/corr.0000000000000424)
- [Paper] [28] (10.1016/j.eats.2020.10.010)
- [L2] Routine distal clavicle excision is not absolutely necessary, even in patients with symptomatic ACJ osteoarthritis. [29] (10.1007/s00167-020-06098-y)
- [L4] Heterotopic bone formation may be a more common cause of failure of acromioplasty or distal clavicectomy than acknowledged in the literature. [30] (10.1016/s1058-2746(96)80126-1)
- [L4] A high index of suspicion is needed to diagnose such complications early before irretrievable bone loss to osteolysis. [31] (10.1111/sae.12035)
- [L3] Open and arthroscopic distal clavicle excision are both effective surgeries to treat recalcitrant acromioclavicular joint pain, providing similarly good to excellent results regarding patient satisfaction and shoulder function at intermediate-term follow-up, though less residual pain was found using the arthroscopic technique. [32] (10.1177/0363546511419633)
- [L5] The technique will allow surgeons to perform distal clavicle excisions in a more efficient, reproducible and safer manner. [33] (10.1016/j.eats.2024.103331)
- [L5] A 5-mm distal clavicle resection guaranteed no abutment but decreased joint stiffness. [35] (10.1016/j.arthro.2007.07.004)
- [Paper] The introduction of this technique provides a special technical option for distal clavicle resection when the patient is in the lateral decubitus position, allowing convenient removal of the posterior edge of the distal clavicle to prevent impingement. [38] (10.1016/j.eats.2020.08.040)
- [L4] [47] (10.1016/j.jse.2026.08.016)
- [L5] The cross-sectional A-frame morphology of the superior cortex of the distal clavicle provides a reproducible landmark that is eliminated approximately 1.0 cm medial to the distal, lateral end of the clavicle, which can be used intraoperatively to determine when adequate resection has been completed. [49] (10.1016/j.jse.2021.10.013)
- [L5] Intact acromioclavicular ligaments protect the coracoclavicular reconstruction by decreasing the in situ graft force. [75] (10.1177/0363546510374447)
- [L5] This cadaveric study demonstrates that the anterior-posterior load to clinical failure of the AC joint after 5 mm of resection from the distal clavicle and medial acromion is significantly greater than 1 cm of the resected distal clavicle alone. [77] (10.1177/0363546512469873)
- [L3] Prolonged implant retention and higher-grade fracture types significantly increase the risk of subacromial osteolysis (SAO). [78] (10.1186/s12891-026-09516-3)
References
[1] Risk factors and management of atraumatic distal clavicular osteolysis: A scoping review. Shoulder & Elbow. 2026. DOI: 10.1177/17585732261479715
[2] Propionibacterium acnes–mediated distal clavicular osteolysis: a case report. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.03.004
[3] Post-traumatic osteolysis of the distal clavicle. Archives of Orthopaedic and Trauma Surgery. 1996. DOI: 10.1007/bf00573456
[4] Subacromial osteolysis following hook plate fixation for acromioclavicular dislocation: a systematic review and meta-analysis. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2024.03.018
[5] Post-traumatic osteolysis of the distal end of the clavicle in judo athlete: Case report. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80543-x
[6] Resection of the lateral end of the clavicle following osteolysis, with emphasis on non-traumatic osteolysis of the acromial end of the clavicle in athletes. Injury. 1987. DOI: 10.1016/0020-1383(87)90010-6
[7] Patient outcomes following arthroscopic distal clavicle excision: a prospective case series. JSES International. 2023. DOI: 10.1016/j.jseint.2023.07.014
[8] Atraumatic osteolysis of the distal clavicle. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80377-6
[9] Arthroscopic versus open distal clavicle excision: Comparative results at six months and one year from a randomized, prospective clinical trial. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2006.10.006
[10] Osteolysis of the distal end of the clavicle: A case report. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80313-0
[11] Open Versus Arthroscopic Distal Clavicle Resection. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.12.007
[13] Heterotopic ossification after acromioplasty and distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(05)80050-3
[14] Limited distal clavicle excision of acromioclavicular joint osteoarthritis. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2016.01.008
[15] Predictive value of implant removal time and acromion-hook angle on subacromial osteolysis following hook plate fixation for acromioclavicular dislocation. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.09.027
[16] Arthroscopic Distal Clavicle Resection: A Biomechanical Analysis In A Cadaver Model. Journal of Shoulder and Elbow Surgery. 2007. DOI: 10.1016/j.jse.2007.02.105
[17] A case of post-traumatic osteolysis of the distal clavicle: Histologic lesion of the acromion. Journal of Shoulder and Elbow Surgery. 2002. DOI: 10.1067/mse.2002.122229
[18] The usefulness of distal clavicle resection for acromioclavicular joint disease. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80520-9
[19] Acromioclavicular dislocation after arthroscopic distal clavicle resection: a case report. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.08.032
[20] Failure of acromioclavicular reconstruction using Gore-Tex graft due to aseptic foreign-body reaction and clavicle osteolysis: A case report. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/j.jse.2004.01.027
[21] Editorial Commentary: The “Mumford” & Sons: For Distal Clavicle Excisions, What Are Our Young Surgeons Doing, and How Well Are They Doing It?. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.03.004
[22] Distal Clavicle Fracture as a Complication of Arthroscopic Distal Clavicle Resection. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.02.008
[23] Is routine distal clavicle resection necessary in rotator cuff repair surgery? A systematic review and meta-analysis. Shoulder & Elbow. 2017. DOI: 10.1177/1758573217741124
[24] Arthroscopic Distal Clavicle Resection in Athletes. The American Journal of Sports Medicine. 2007. DOI: 10.1177/0363546506294855
[25] The slap lesion as a cause of continued symptoms and failure of distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80319-3
[26] Does Distal Clavicle Resection Decrease Pain or Improve Shoulder Function in Patients With Acromioclavicular Joint Arthritis and Rotator Cuff Tears? A Meta-analysis. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000424
[27] Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability. 2016.
[28] Distal Clavicle Excision for Acromioclavicular Joint Osteoarthritis Using a Fluoroscopic Kirschner Wire Guide. Arthroscopy Techniques. 2021. DOI: 10.1016/j.eats.2020.10.010
[29] Acromioclavicular joint arthritis is not an indication for routine distal clavicle excision in arthroscopic rotator cuff repair. Knee Surgery, Sports Traumatology, Arthroscopy. 2020. DOI: 10.1007/s00167-020-06098-y
[30] Heterotopic ossification after acromioplasty and distal clavicle resection. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80126-1
[31] Bone Osteolysis Following Acromioclavicular Joint Reconstruction Using Synthetic Ligament (Surgilig™). Shoulder & Elbow. 2014. DOI: 10.1111/sae.12035
[32] Arthroscopic Versus Open Distal Clavicle Excision. The American Journal of Sports Medicine. 2011. DOI: 10.1177/0363546511419633
[33] Intraoperative Use of Ultrasound and Cannulated Dilators to Safely Identify and Access the Acromioclavicular Joint for Distal Clavicle Excision: A Technique Guide. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103331
[35] Arthroscopic Distal Clavicle Resection: A Biomechanical Analysis of Resection Length and Joint Compliance in a Cadaveric Model. Arthroscopy. 2007. DOI: 10.1016/j.arthro.2007.07.004
[38] Arthroscopic Distal Clavicle Resection Through the Supraspinatus Fossa Portal. Arthroscopy Techniques. 2020. DOI: 10.1016/j.eats.2020.08.040
[39] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Clavicle, Scapula, and Glenoid > I. Clavicular Fractures.
[47] Clinical Outcomes and Predictors of Dissatisfaction Following Revision Surgery After Distal Clavicle Excision. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.08.016
[49] Distal clavicle “A-frame” morphology: a reliable intraoperative guide for arthroscopic distal clavicle excision. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.10.013
[50] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Clavicle, Scapula, and Glenoid > II. Scapular and Glenoid Fractures.
[51] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > FRACTURES OF THE CLAVICLE.
[52] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Clavicle.
[53] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > Neurovascular Structures > EXCISION OF THE DISTAL CLAVICLE.
[56] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Muscular Anatomy of the Clavicle.
[58] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Neurovascular Anatomy of the Clavicle.
[65] Rockwood And Matsen S The Shoulder. Arthroscopic Treatment of Acromioclavicular Joint Osteolysis, Arthritis, and Instability > Distal Clavicle Osteolysis > Indications.
[75] The Effect of Distal Clavicle Excision on in Situ Graft Forces in Coracoclavicular Ligament Reconstruction. The American Journal of Sports Medicine. 2010. DOI: 10.1177/0363546510374447
[77] The Biomechanical Stability of Distal Clavicle Excision Versus Symmetric Acromioclavicular Joint Resection. The American Journal of Sports Medicine. 2012. DOI: 10.1177/0363546512469873
[78] What is the optimal implant removal timing following hook plate fixation in distal clavicle fractures: a retrospective analysis from subacromial osteolysis cases. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09516-3