Bakit iminungkahi ang operasyong ito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyon na hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Sa iyong appointment, kumukuha kami ng history, sinusuri ang iyong balikat, at nagsasaayos ng imaging kung kinakailangan. Para sa mga problemang matagal na, karaniwan naming sinusubukan muna ang non-operative care, gaya ng pagbabago sa aktibidad, physiotherapy o mga injection. Ang operasyon ay isinasaalang-alang kapag ang mga hakbang na iyon ay hindi nagbigay sa iyo ng sapat na pagbuti.
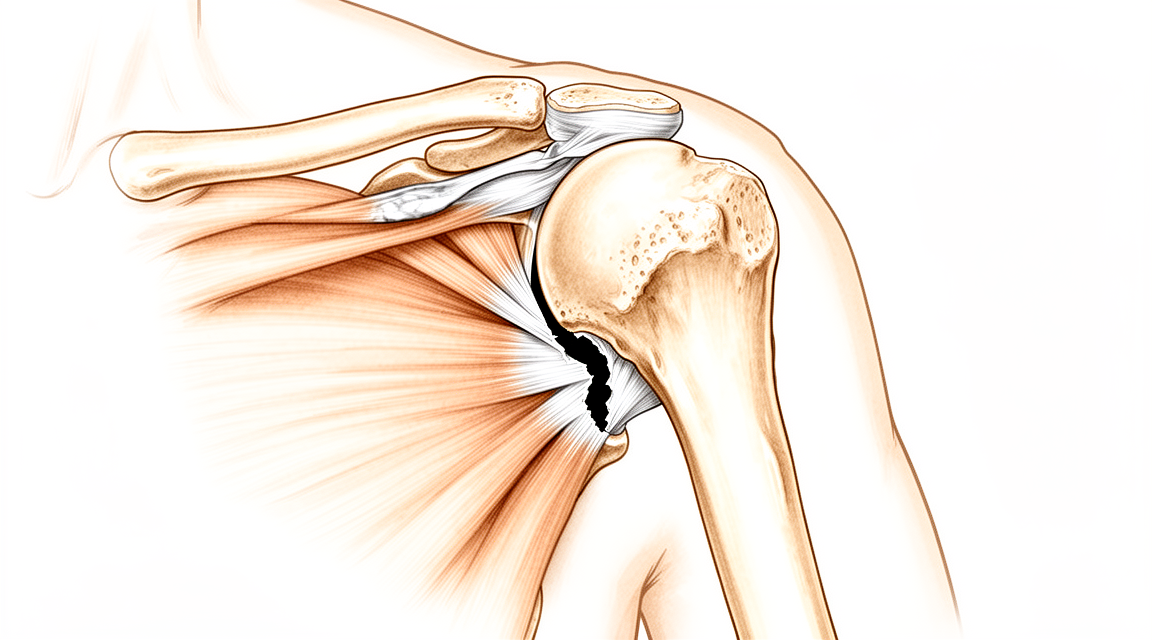
Ang revision rotator cuff repair ay isang pangalawang operasyon upang muling kumpunihin ang isang tendon sa balikat na napunit muli o hindi kailanman gumaling pagkatapos ng naunang repair. Iminumungkahi namin ito kapag ang sakit, sakit sa gabi, panghihina, o paninigas ay nagpapatuloy sa kabila ng naunang gamutan. Ang mga scan gaya ng ultrasound o MRI ay tumutulong sa amin na suriin ang tendon at ang kalamnan sa paligid nito bago magdesisyon. Layunin ng operasyon na bawasan ang iyong sakit at pagbutihin ang paggalaw at paggana ng iyong balikat. Maraming tao ang napananatili ang pagbuting iyon sa loob ng 5 taon pagkatapos ng operasyon. Pag-uusapan namin ang mga benepisyo at mga panganib kasama ka, at ang desisyon ay gagawin mo kasama namin.
Bago ang operasyon
Bago ang operasyon, nagsasaayos kami ng mga scan upang planuhin ang operasyon. Maaaring kabilang dito ang mga X-ray, ultrasound, o MRI (isang scan na nagpapakita ng mga soft tissue sa paligid ng iyong balikat nang detalyado). Sa araw ng iyong operasyon, kakailanganin mong itigil ang pagkain at pag-inom pitong oras bago ito. Humihingi kami ng pitong oras upang maaga naming maisagawa ang iyong operasyon kung maagang matatapos ang listahan sa theatre; kumpirmasyon ng iyong surgeon ang eksaktong oras. Kung ikaw ay may regular na mga gamot, magdala ng listahan ng mga ito at sasabihin namin sa iyo kung alin ang mga dapat itigil muna. Mag-ayos ng taong maghahatid sa iyo pauwi pagkatapos, dahil hindi mo kayang magmaneho nang mag-isa. Magsuot ng maluwag at komportableng damit na madaling isuot at hubarin. Kung mayroon kang iba pang kondisyong medikal, maaaring kailanganin mo ng mga blood test o pagsusuri kasama ang anaesthetist (ang espesyalista na nagbibigay ng iyong anaesthetic).
Sa araw ng operasyon
Darating ka sa surgical admissions unit ng ospital, kung saan ka ire-rehistro at ihahanda para sa theatre. Pagkatapos nito ay makikipagkita ka sa anaesthetist. Ang operasyong ito ay ginagawa sa ilalim ng general anaesthetic na pinagsama sa isang regional nerve block. Ikaw ay tulog nang tuluyan para sa operasyon, at ang block (isang injection na nagpamanhid sa mga nerve na nagsusuplay sa braso bago ka magising) ay nagbibigay ng pain relief para sa unang 12 hanggang 24 oras pagkatapos ng surgery. Makikipagkita sa iyo ang anaesthetist bago ang operasyon at ipapaliwanag sa iyo ang dalawang bahaging ito. Pagkatapos ay dadalhin ka sa operating theatre, kung saan isasagawa ang operasyon. Kapag natapos na ito, magigising ka sa recovery area, kung saan babantayan ka ng mga nurse habang nawawala ang bisa ng anaesthetic. Kapag stable ka na, maaaring pumunta ka sa ward o uuwi na, depende sa procedure at sa iyong recovery.
Ano ang kinapapalooban ng operasyon
Ang revision rotator cuff repair ay ginagawa sa pamamagitan ng keyhole surgery. Ang iyong surgeon ay gagawa ng ilang maliliit na hiwa sa paligid ng iyong balikat, kabilang ang isa sa likod, at gagamit ng isang maliit na camera sa loob ng joint. Ipinapakita ng camera ang napunit na tendon at ang buto kung saan ito napunit.
Ang karaniwang plano ay muling ikabit ang tendon gamit ang maliliit na anchor na inilalagay sa buto. Ang mga anchor na ito ang humahawak sa mga tahi na dumadaan sa tendon. Ang mga anchor ay inilalagay sa dalawang row: isang row na mas malapit sa joint, at isang pangalawang row na mas malayo na humihila sa tendon nang mahigpit laban sa buto kung saan ito kailangang gumaling. Depende sa makikita ng iyong surgeon habang nag-o-operasyon, maaari silang gumamit ng isang row lamang ng mga anchor, o ibang uri ng anchor na mas malapit sa joint.
Isang soft patch na gawa sa biological tissue ang madalas na inilalagay sa ilalim ng tendon sa repair site upang hikayatin itong gumaling pabalik sa buto. Maaari kang magbasa nang higit pa tungkol dito sa aming pahina sa EnFix biological scaffold.
Kung ang buto kung saan nakakabit ang tendon ay nakupos na, ang iyong surgeon ay maaaring magdagdag ng kaunting bone graft upang muling mabuo ito, nang sa gayon ay mayroong matigas na kapitan ang mga anchor. Kung ang tendon ay masyadong damaged para muling ikabit, ang ibang mga opsyon gaya ng paggamit ng donor tendon upang punan ang puwang ay maaaring talakayin sa iyo bago o habang isinasagawa ang iyong pangangalaga.
Ang mga hiwa ay sinasara gamit ang mga tahi, at isang dressing ang inilalagay sa ibabaw ng mga sugat. Pananatilihin mo ang dressing na iyon sa loob ng humigit-kumulang 10 araw.
Pagkatapos ng operasyon
Karamihan sa mga pasyente ay nananatili ng isang gabi sa ospital pagkatapos ng operasyong ito, bagaman ang ilan ay nakakauwi sa mismong araw. Magigising ka sa recovery area, pagkatapos ay ililipat sa ward. Susuriin ka ng mga nars at bibigyan ng pain relief ayon sa iyong pangangailangan. Ang nerve block mula sa theatre ay madalas na nagpapanatiling komportable sa balikat sa unang 12 hanggang 24 oras, kaya maaaring kakaunti lamang ang maramdaman mong sakit sa simula. Ang iyong braso ay ilalagay sa isang simpleng sling para sa iyong komportable. Maaari mo itong tanggalin para sa paghuhugas at para sa mga ehersisyong ituturo namin sa iyo. Pananatilihin namin ang dressing sa loob ng humigit-kumulang 10 araw; pakiusap na huwag itong tanggalin bago ang panahong iyon maliban kung sinabi namin sa iyo. Papalitan o tatanggalin namin ito kapag nakita ka namin. Tutulungan ka ng isang nars na maupo, tumayo, at lumakad ng maikling distansya, karaniwan ay sa loob ng ilang oras pagkagising. Mangyaring mag-ayos ng isang tao na sasama sa iyo sa unang 24 oras pagkauwi mo sa bahay.
Paggaling
Ang mga unang araw pagkatapos ng operasyon ay nakatuon sa pahinga at ginhawa. Mawawala ang bisa ng nerve block sa loob ng isang araw o higit pa, at maaaring mas sumakit ang balikat kaysa dati. Ang pamamaga at pasa sa paligid ng balikat at itaas na bahagi ng braso ay normal at mawawala sa mga sumunod na linggo. Ang mga ice pack, pahinga, at ang pain relief na aming irereseta ay nakatutulong upang maibsan ito. Maraming tao ang nakakaramdam na mas komportable ang pagtulog nang nakaupo sa isang upuan o nakasandal sa mga unan sa simula, dahil ang paghiga nang patag ay maaaring magbigay ng pressure sa balikat.
Ang iyong braso ay nakalagay sa isang simpleng sling para sa ginhawa. Tatanggalin mo ito para sa paghuhugas at para sa mga ehersisyo na ituturo sa iyo ng iyong physiotherapist. Ang mga ehersisyong ito ay magsisimula nang dahan-dahan, na may maliliit na paggalaw upang maiwasan ang paninigas ng balikat habang gumagaling ang tendon. Sa paglipas ng panahon, ang mga paggalaw ay magiging mas malaki at mas malakas, na laging ginagabayan ng iyong physiotherapist at ng iyong sariling ginhawa. Sa araw-araw, maaari kang maglakad, gumalaw sa loob ng bahay, at gamitin nang malaya ang iyong kabilang braso. Kakailanganin mo ng tulong sa mga mas mabibigat na gawain tulad ng pagbuhat, pagdadala, at pag-abot sa itaas hanggang sa maging handa na ang iyong balikat.
Kapag humupa na ang pamamaga at bumalik na ang paggalaw, magiging mas madali ang mga pang-araw-araw na aktibidad. Ang pagbibihis, paghuhugas, at magagaan na gawaing bahay ang unang babalik. Ang pagmamaneho ay maghihintay hanggang sa payagan ka ng iyong surgeon sa iyong review, karaniwan ay sa ika-anim na linggo; tingnan ang aming gabay sa Driving after upper-limb surgery para sa mga detalye. Ang trabaho at sports ay babalik sa mga yugto (in stages), kapag sumang-ayon na ang iyong surgeon at physiotherapist na ang tendon ay gumaling na nang sapat.
Ang paggaling ay nag-iiba sa bawat tao. Maaaring magkaiba ang iyong timeline, at gagabayan ka ng iyong surgeon at physiotherapist sa buong proseso.
Ano ang maaaring maging problema
Karamihan sa mga pasyente ay gumagaling nang maayos, ngunit paminsan-minsan ay may mga problemang maaaring mangyari. Binabantayan kayo nang maigi ng inyong surgeon at ng team upang maagapan ang anumang isyu.
Ang pangunahing binabantayan namin ay ang muling pagkapunit ng tendon. Maaari itong maramdaman bilang pananakit na bumabalik matapos itong magsimulang humupa, kasama ang panghihina kapag nagbubuhat o may inaabot. Karamihan sa mga punit na nauulit ay nangyayari sa loob ng unang anim na buwan, kaya binabantayan naming maigi ang inyong balikat sa panahong iyon. Kung bumalik ang inyong pananakit o panghihina, ipaalam agad sa amin sa halip na maghintay para sa inyong susunod na review.
Ang impeksyon ay hindi karaniwan ngunit nangangailangan ng mabilis na atensyon. Magpatingin sa inyong GP o pumunta sa emergency department kung mapansin ang malalim at tumitibok na pananakit (throbbing pain) na hindi nawawala sa simpleng painkiller, pamumula na kumakalat mula sa sugat, lagnat, o balikat na mainit hipuin. Minsan, ang repair na nabigo ay maaaring may kaugnayan sa isang low-grade infection na mahirap makita. Ang malalang pananakit ng balikat o paninigas na hindi humuhupa ay dapat laging suriin para sa impeksyon, kaya banggitin ito sa amin.
Hindi lahat ng revision ay naaabot ang layunin na isang balikat na walang sakit at malakas. May ilang tao na nakikita na ang kanilang paggalaw ay hindi bumuti gaya ng kanilang inaasahan, o nananatili ang paninigas at panghihina. Kung ang tissue ng tendon ay manipis, malaki ang punit, o may arthritis na, ang resulta ay maaaring mas mababa kaysa sa inaasahan nating dalawa. Mag-uusap tayo nang tapat tungkol sa ipinapakita ng inyong mga scan bago kayo magdesisyon.
Mayroon ding mga bagay na nagpapataas ng panganib na mabigo ang repair. Ang ilang partikular na antibiotic na iniinom nang maaga pagkatapos ng operasyon ay naiugnay sa pagkabigo ng mga repair at pangangailangan ng pangalawang operasyon. Kung may nireseta sa inyong anumang bagong gamot sa mga linggo pagkatapos ng inyong repair, makabubuting itanong muna ito sa amin o sa inyong GP. Ang mga problema sa cholesterol sa inyong dugo ay maaari ring makaapekto sa kung gaano kabilis gumaling ang tendon, kaya isinasama namin ang inyong pangkalahatang kalusugan kapag pinag-uusapan natin ang mga dapat asahan.
Ang table ng mga komplikasyon sa pahinang ito ay naglilista ng mga tipikal na rate kung nais ninyo ang mga detalye.
Kailan dapat tumawag sa amin
Tumawag sa amin kung mapansin ang lagnat, pamumula na kumakalat mula sa sugat, may lumalabas na likido (discharge) mula sa sugat, o pananakit na patuloy na lumalala. Ipaalam agad sa amin kung bumalik ang sakit o panghihina matapos itong magsimulang humupa, o kung bumalik sa dati ang mga milestone ng iyong paggaling. Pumunta sa emergency kung may biglaang matinding sakit, pamamaga ng binti (calf swelling), kahirapan sa paghinga, kawalan ng pakiramdam sa iyong braso, o hindi mo maigalaw ang iyong braso. Karamihan sa mga punit (tears) na nauulit ay nangyayari sa loob ng unang anim na buwan, kaya binabantayan naming mabuti ang iyong balikat sa panahong iyon.
Saan maaaring magbasa nang higit pa tungkol sa kondisyon
Ang pahinang ito ay tungkol sa operasyon mismo. Ang kondisyong ginagamot nito, kabilang ang kung ano ang ipinapakita ng ebidensya tungkol sa kung kailan nakatutulong ang operasyon at kung kailan hindi, ay tinalakay nang mas detalyado sa pahinang Rotator Cuff Disorders.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Interposition grafting using fascia lata autograft can repair multiple rotator cuff injuries to the greatest extent [1].
- Interposition grafting using fascia lata autograft can restore the function of the shoulder joint [1].
- Interposition grafting using fascia lata autograft can effectively relieve pain [1].
- Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair reduces the retear rate at 12-month follow-up by 25% [2].
- Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair yields similar improvements in clinical outcomes [2].
- Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair is associated with no increased risk of complication [2].
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humerus comprises four main parts: the humeral head, greater tuberosity (GT), lesser tuberosity (LT), and humeral shaft [5].
- The articular head of the proximal humerus is spherical with a diameter of 37 to 57 mm [5].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [5].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [5].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [5].
- The anatomic neck of the proximal humerus is located at the junction of the articular surface and the tuberosities [5].
- The surgical neck represents an indistinct region, or metadiaphyseal junction, below the tuberosities but above the humeral shaft [5].
- The greater tuberosity is located in a posterior-superior location with respect to the humeral shaft and serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [5].
- The lesser tuberosity is located on the anterior aspect of the proximal humerus and serves as the attachment site for the subscapularis tendon [5].
- The bicipital groove lies between the greater and lesser tuberosities and serves as a pathway for the long head of the biceps [5].
- The distal aspect of the bicipital groove is internally rotated with respect to the proximal portion [5].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [5].
- The glenoid articulates with the humeral head and serves as the attachment for the labrum and joint capsule [5].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [5].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [5].
- The scapula is attached to the axial skeleton by the clavicle, specifically via the acromioclavicular and sternoclavicular joints [7].
- The scapular body is triangular when viewed anteroposteriorly, with its base situated superiorly and its apex inferiorly [7].
- The glenoid is connected with the flat body of the scapula by the scapular neck [7].
- The hook-shaped coracoid process curves forwards from the superior surface of the scapular neck [7].
- The scapular spine arises from the posterior surface of the scapular body and ends in a flattened bony process, the acromion, which curves forwards [7].
- The distribution of bony mass in the scapula is highly uneven, with the highest concentration in the glenoid, scapular neck, and lateral border of the scapular body [7].
- Two bony pillars extend between the glenoid and the scapular body to transmit compressive forces from the glenoid fossa [7].
- The lateral pillar connects the inferior border of the glenoid with the inferior angle of the scapula [7].
- The spinal pillar arises from the central part of the glenoid and continues medially to become part of the base of the scapular spine [7].
- The weakest bone in the scapula is located primarily in the central part of the biomechanical body, specifically in the infraspinous fossa [7].
- The weakest area of the circumference of the biomechanical body of the scapula is the spinomedial angle, where the scapular spine connects to the medial border [7].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [8].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [8].
- The subchondral bone of the glenoid is relatively flat, with the articular concavity augmented by cartilage and a circumferential labrum [8].
- The neck-shaft angle measures an average of 135 degrees, and the humeral head is retroverted an average of 30 degrees [6].
Vascular Anatomy
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [5].
- The posterior humeral circumflex artery travels with the axillary nerve, enters the quadrilateral space posteriorly, and anastomoses with a branch of the anterior circumflex to supply the posterior cuff [5].
- The anterior humeral circumflex artery arises from the axillary artery at the inferior border of the subscapularis and provides vascular inflow to the humeral head via its terminal anterolateral branch, known as the artery of Laing or arcuate artery [5].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon and enters the humeral head at the interface of the bicipital groove and greater tuberosity [5].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [5].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [5].
- The major blood supply to the humeral head is through the ascending branch of the anterior humeral circumflex artery, which penetrates the head at the bicipital groove and becomes the arcuate artery [6].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [8].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [8].
Soft Tissue & Ligamentous Anatomy
- The rotator cuff consists of four muscles: the subscapularis, supraspinatus, infraspinatus, and teres minor [6].
- The teres major is not a rotator cuff muscle [6].
- The rotator cuff muscles serve as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [6].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [6].
- The glenohumeral joint is stabilized dynamically by the rotator cuff via joint compression and by the positioning of the scapulothoracic joint [8].
- Static stabilizers of the glenohumeral joint include articular congruity, the glenoid labrum, concavity-compression, negative intra-articular pressure, and the glenohumeral capsule and ligaments [8].
- The glenoid labrum provides concavity and up to 50% of marginal glenoid socket depth [8].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [8].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [8].
- Laxity of the rotator interval results in inferior laxity, known as the sulcus sign [8].
- Contracture of the rotator interval is seen with adhesive capsulitis [8].
- The coracohumeral ligament restricts external rotation in adduction and is a static restraint to inferior and posterior translation in adduction and external rotation [8].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [8].
- The superior glenohumeral ligament, along with the coracohumeral ligament, forms a pulley that provides restraint against medial subluxation of the long head of the biceps tendon [8].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [8].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation of the glenohumeral joint in 90° of abduction and external rotation [8].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [8].
- The superior transverse scapular ligament arises from the medial base of the coracoid overlying the suprascapular notch [8].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the nerve runs deep to it [8].
- Entrapment of the suprascapular nerve at the superior transverse scapular ligament causes denervation of both the supraspinatus and the infraspinatus [8].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [8].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [8].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula and communicates with the joint cavity between the superior and middle glenohumeral ligaments [9].
- The subscapular bursa protects the tendon of the subscapularis at the point where it passes under the base of the coracoid process and over the neck of the scapula [9].
- The subscapular bursa is linked to the coracoid process by a suspensory ligament [9].
- In 28% of dissected specimens, the subscapular bursae merged with the subcoracoid bursae, forming a unique wide bursa [9].
- The subscapular bursa often houses loose bodies in the shoulder and is a region where synovitis may be most intense [9].
- A soft tissue sheath consistently covers the long head of the biceps tendon to the level of the proximal margin of the pectoralis major tendon and contributes to the roof of the bicipital tunnel [9].
- The fibro-osseous bicipital tunnel consists of three distinct anatomic zones: Zone 1 (bony groove), Zone 2 ("no man's land" between subscapularis and pectoralis major), and Zone 3 (subpectoral region) [9].
Pathophysiology & Biomechanics
- Stability and function of the glenohumeral joint are provided by the interaction of structures that promote a near global range of motion and purposeful function [5].
- External loads transferred to the shoulder girdle are initially offset by joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion [5].
- Moderate and large loads are counterbalanced by the deltoid and rotator cuff, and by the capsulolabral and bone structures, respectively [5].
- Pathologic conditions alter complex shoulder interactions, resulting in pain, decreased range of motion and stiffness, and disability [5].
- Displacement of proximal humeral fracture fragments occurs in a predictable manner based on deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [5].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement of the fragment [5].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement of the fragment [5].
- The pectoralis major inserts on the humeral shaft and displaces it medially [5].
- Fractures involving the anatomic neck are prognostically worse than fractures involving other regions of the proximal humerus due to potential disruption of the vascular supply to the humeral head and subsequent development of avascular necrosis [5].
- Displaced proximal humeral fractures can impede normal movement of the rotator cuff, subacromial bursa, and subdeltoid bursa, causing impingement and disruption of normal glenohumeral motion [5].
- In proximal humeral fractures, the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that limit normal glenohumeral motion [5].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [6].
- Stability of the glenohumeral joint depends on the capsule, ligament, and muscle [6].
- A redundant capsule allows for motion in the glenohumeral joint [6].
- The scapula is separated from the chest wall by thin gliding fibro-fatty tissue, allowing its smooth excursion over the chest wall [7].
- The scapula provides efficient support to the humeral head, allowing compressive forces to be optimally transmitted from the upper limb to the shoulder girdle without compromising stability or mobility of the glenohumeral joint [7].
- The superior shoulder suspensory complex provides a stable connection between the scapula and the axial skeleton [8].
- The superior shoulder suspensory complex is composed of the glenoid, coracoid process, coracoclavicular ligaments, distal clavicle, acromioclavicular joint, and acromion [8].
- The superior strut of the superior shoulder suspensory complex comprises the middle clavicle [8].
- The inferior strut of the superior shoulder suspensory complex comprises the lateral scapular border and spine of the scapula [8].
- Normal shoulder motion is approximately two-thirds glenohumeral and one-third scapulothoracic [8].
- The sternoclavicular joint is the only true diarthrodial articulation between the upper appendicular and axial skeletons [8].
- The posterior sternoclavicular joint capsule and ligaments are the primary stabilizers to anterior and posterior translation of the medial clavicle [8].
- The acromioclavicular joint is a small diarthrodial joint with an interposed fibrocartilaginous disk [8].
- The superior and posterior acromioclavicular ligaments are the primary stabilizers to anterior and posterior horizontal translation of the clavicle [8].
- The coracoclavicular ligaments, consisting of the conoid (medial) and trapezoid (lateral) ligaments, are the primary stabilizers to superior vertical translation of the distal clavicle [8].
- The acromion has three ossification centers: the metacromion (base), mesoacromion (middle), and preacromion (tip) [8].
- Failure of fusion of the acromial ossification centers results in os acromiale [8].
- The relationship between acromial anatomy and rotator cuff disease remains controversial, with classification of acromial morphology challenged by poor interobserver reliability [8].
- The relationship between coracoid morphology and subscapularis tears is controversial [8].
- The coracobrachialis muscle and the short head of the biceps tendon originate from the coracoid process [8].
- The pectoralis minor muscle inserts onto the medial coracoid process [8].
- The proximal humerus has three centers of ossification: the humeral head (4 to 6 months), greater tuberosity (1 to 3 years), and lesser tuberosity (3 to 5 years) [8].
- The ossification centers of the proximal humerus fuse to the shaft at age 17 to 20 years [8].
- The clavicle is the first bone to ossify, occurring in the fifth week of gestation, and is the only long bone to ossify by intramembranous ossification [8].
- The medial (sternal) epiphysis of the clavicle is the last ossification center to fuse, occurring at age 20 to 25 years [8].
- The primary blood supply to the clavicle is periosteal, with no nutrient artery present [8].
- Ossification of the scapular body begins at the eighth week of gestation [8].
- The scapular spine is an osseous ridge that separates the supraspinatus and infraspinatus fossae [8].
- The scapula has only one true diarthrodial articulation, the acromioclavicular joint [8].
Classification
- Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair yields similar improvements in clinical outcomes compared to controls [2].
- Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair does not increase the risk of complication [2].
Clinical Presentation
- Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair reduces the retear rate by 25% at 12-month follow-up [2].
Investigations
Plain Radiography
- The purpose of shoulder imaging is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [4].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder care [4].
- The first key radiographic view is the anteroposterior (AP) view taken in the plane of the scapula such that the x-ray beam passes through the glenohumeral joint [4].
- The AP view in the plane of the scapula shows the superoinferior position of the humeral head relative to the glenoid, the presence of osteophytes on the humeral head and glenoid, narrowing of the joint space, and the degree of medial displacement of the humerus in relation to the lateral acromial line [4].
- The AP view in the plane of the scapula also shows the quality of the humeral and glenoid bone, the presence of loose bodies, and whether there is humeral head collapse or deformity [4].
- The second key radiographic view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [4].
- The axillary view is oriented so that both the spinoglenoid notch and the scapular neck are visible [4].
- The axillary view shows a different perspective of the humeral anatomy, the amount of glenoid bone, the shape of the glenoid, its version in relation to the plane of the scapula, and the relationship of the humeral head to the glenoid fossa [4].
- The standardized axillary view is referred to as the "truth view" because it demonstrates the glenohumeral relationships in the functional position of elevation [4].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view which is taken in elevation [4].
- When taken properly, standardized anteroposterior and axillary views indicate the thickness of the cartilage space between the humerus and the glenoid, relative positions of the humeral head and the glenoid, presence of osteophytes, degree of osteopenia, and extent of bony deformity and erosion [4].
- Joint space narrowing is most evident on the axillary truth view as opposed to images made with the arm at the side [4].
- The axillary truth view can show posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [4].
- The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the plane of the scapula, the position of the center of the humeral head in relation to the glenoid face, or the point of contact of the humeral articular surface on the glenoid articular surface [4].
- The point of contact of the humeral articular surface on the glenoid articular surface reflects the degree of centering of the net humeral joint reaction force on the glenoid [4].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and "rocking horse" loosening of prosthetic glenoid components [4].
- At least two X-ray views should be obtained: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [13].
Magnetic Resonance Imaging
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head, or a bone tumour [13].
- MRI can identify labral tears and rotator cuff tears, although the accuracy for these is enhanced by combining the scan with arthrography [13].
Computed Tomography
- Computed tomography (CT) is helpful for planning fracture surgery and shoulder joint replacement [13].
- CT scans may offer a few degrees of increased precision in the measurement of glenoid version, but this precision does not necessarily improve the quality of the surgery or the clinical outcome [4].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [13].
- Ultrasonography can be useful in guiding injections or barbotage (aspirating calcific deposits in the rotator cuff) [13].
- The most commonly performed joint examination using ultrasonography is the shoulder examination [11].
- The accuracy of rotator cuff ultrasonography depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [11].
General Imaging Principles
- The shoulder is a three-dimensional structure that cannot be represented by a single planar view [15].
- Critical relationships, such as the degree of centering of the humeral head, change with the position of the arm [15].
- Shoulder pathology may be found in a large number of different bones and soft tissues [15].
- Overlying and superimposed structures as well as metallic implants may complicate imaging the structures of interest [15].
- Surgeons need to develop a judicious approach to imaging that yields the information necessary to treat the patient while avoiding the tendency to "over-image" [15].
- The temptation to "overimage" should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [4].
- Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [4].
Key Evidence
- [L5] This technique can repair multiple rotator cuff injuries to the greatest extent, restore the function of the shoulder joint, and effectively relieve pain. [1] (10.1016/j.eats.2023.08.027)
- [L1] Biologic augmentation with a bioinductive collagen patch in revision rotator cuff tear repair reduces the rate at 12-month follow-up by 25%, yielding similar improvements in clinical outcomes and without any increased risk of complication. [2] (10.1016/j.jseint.2025.101507)
References
[1] Interposition Grafting Using Fascia Lata Autograft for Failed Rotator Cuff Repairs. Arthroscopy Techniques. 2023. DOI: 10.1016/j.eats.2023.08.027
[2] Biological augmentation in revision surgery: a matched-pair study of the effect of a nuns bioinductive collagen patch in patients with rotator cuff retear and a previous arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2025.101507
[4] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[5] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[6] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[7] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[8] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[9] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[11] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[13] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[15] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.